1. Introduction
Lipedema is a chronic, progressive disorder of subcutaneous adipose tissue affecting almost exclusively women, characterized by symmetrical and disproportionate fat accumulation in the extremities, pain on palpation, easy bruising, and orthostatic edema sparing the hands and feet. First described in the 1940s as a clinical syndrome of abnormal and symmetrical fat accumulation in the lower extremities accompanied by feet-sparing orthostatic edema and psychological distress, for decades the condition was not widely recognized and was often confused with obesity or lymphedema, leading to misdiagnosis and inadequate treatment [
1]. International awareness has grown substantially in recent years, culminating in the development of clinical guidelines and, most recently, in a multi-phase Delphi consensus position paper [
1,
2,
3].
Alongside improved disease recognition, the need for objective, reproducible tools to assess lipedema both at diagnosis and over time has emerged as a critical unmet need. Both the German S2k guideline and the Lipedema World Alliance (LWA) consensus formally state that no imaging modality, serological test, or genetic marker has been officially approved to verify the clinical diagnosis, which continues to rest exclusively on medical history, physical examination, and exclusion of differential diagnoses [
1,
2].
Over the years, cutaneous ultrasound has attracted growing interest in this context. Its appeal lies in its accessibility, non-invasiveness, absence of ionizing radiation, and ability to characterize the structural properties of skin and subcutaneous tissue at a resolution relevant to lipedema pathology. The histological substrate of lipedema, characterized by adipocyte hypertrophy, interstitial fibrosis, chronic low-grade inflammation, and microvascular dysfunction [
4], is in principle detectable by high-frequency ultrasound through changes in layer thickness, echogenicity, and tissue architecture. However, existing ultrasound studies in lipedema have been cross-sectional in design, have addressed differential diagnosis rather than disease monitoring, and have yielded discordant results regarding the reliability and specificity of ultrasound features [
5,
6,
7]. The S2k guideline accordingly cautions that etiological conclusions regarding subcutaneous edema shall not be drawn from B-mode sonography alone [
2]. The question of whether ultrasound can function as a longitudinal monitoring tool in lipedema able to capture tissue-level modifications over time within the same patients has not been addressed.
In light of emerging disease-modifying therapeutic candidates, this gap is particularly consequential. Lipedema is now understood as a complex immunometabolic disorder driven by adipocyte hypertrophy, chronic inflammation, extracellular matrix fibrosis, and hormonal dysregulation, mechanisms that are in principle amenable to pharmacological modulation [
4].
The present real-world observational longitudinal study aimed to systematically characterize ultrasound features in a cohort of patients with lipedema monitored for six months. The purpose was to determine whether cutaneous ultrasound parameters are sensitive to change over a clinically relevant follow-up period and to assess their association with the clinical parameters conventionally used to evaluate lipedema characteristics and disease course.
2. Materials and Methods
2.1. Study Design and Setting
This was a retrospective, single-center, real-world longitudinal observational cohort study conducted at a specialized private lipedema outpatient clinic (Siracusa, Italy). Data were collected from the medical records of consecutive female patients diagnosed with lipedema who attended scheduled follow-up visits at three pre-defined timepoints: baseline (T0), three months (T3), and six months (T6). The study was designed and reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines for observational real-world evidence. No experimental interventions were introduced for the purposes of this study; all dietary, physical activity, and physical therapy prescriptions reflected routine clinical practice. Patients were managed within a structured specialized outpatient setting with relatively standardized nutritional counselling and longitudinal follow-up protocols. All consecutive patients with a confirmed lipedema diagnosis and complete records across all three timepoints were included; no patients were prospectively screened and subsequently excluded, as the retrospective design identified the eligible cohort directly from existing medical records.
2.2. Ethical Statement
This study was conducted exclusively on anonymized clinical data and ultrasound records retrieved from existing medical files at the Poliambulatorio ID Future (Siracusa, Italy). In accordance with Italian regulations, the study was classified as a methodological and quality improvement evaluation; a formal waiver from Ethics Committee review was granted by the Clinical Medical Directorate of the Poliambulatorio ID Future. The study was conducted in accordance with the Declaration of Helsinki. All patients had previously provided written informed consent for the anonymous use of their clinical data for research purposes. As no direct patient contact or new intervention was introduced for the purposes of this study, no additional consent procedure was required.
2.3. Participants
Patients were eligible for inclusion if they had a confirmed clinical diagnosis of lipedema, were female, aged 18 years or older, and had completed all three follow-up assessments (T0, T3, T6). Diagnosis was established by a single clinician specialized in aesthetic medicine, experienced in lympho-lipid disorders, based on accepted clinical criteria including bilateral, symmetrical subcutaneous adipose tissue accumulation in the lower limbs, pain on pressure, spontaneous bruising tendency, and absence of pitting edema in the foot. Patients were excluded if they had a confirmed diagnosis of concurrent lymphedema or lipolymphedema. Furthermore, patients with a baseline BMI of 30 kg/m2 or above were excluded in order to minimize the confounding effect of concurrent obesity on ultrasound measurements and treatment response. Patients with a positive Stemmer sign in the context of advanced lipedema staging, but without clinical evidence of frank lymphedema, were included. Furthermore, patients were excluded if they were pregnant or postpartum or had incomplete baseline or follow-up records.
All patients were managed according to a structured conservative multicomponent protocol reflecting routine clinical practice at the study center. Nutritional management consisted of an individualized dietary prescription assigned by the treating clinician at baseline and maintained throughout the six-month follow-up. The dietary pattern was classified into three categories based on the regimen prescribed and confirmed by dietary recall at each visit: Mediterranean diet, low-carbohydrate diet, or ketogenic diet. Mean daily energy intake (kcal/day) and protein intake (g/kg/day) were estimated from three-day dietary records collected at baseline. Physical activity was prescribed at baseline, self-reported at each follow-up visit, and categorized as sedentary, light, or moderate. Adjunctive physical therapies—use of compression garments and receipt of manual lymphatic drainage—were recorded at baseline. No pharmacological agents were prescribed.
2.4. Clinical Assessment and Outcome Measures
At baseline, the anatomical type of lipedema was classified into five phenotypic categories: Type I (gluteal and hip distribution), Type II (extension to the knee), Type III (extension to the ankle), Type IV (upper limb involvement), and Type V (distal leg distribution). Skin surface texture was graded on a three-point scale: grade 1 (smooth), grade 2 (irregular/undulating), and grade 3 (lobular with overhanging folds). Tissue consistency was classified as grade 1 (homogeneous), grade 2 (fine nodular), or grade 3 (coarse nodular), assessed by bimanual palpation. Clinical signs routinely documented included the cuff sign, the ankle collar sign, the Stemmer sign, and the presence of spontaneous ecchymosis. Subjective heaviness of the lower limbs was rated by the patient on a four-level ordinal scale: 0 (absent), 1 (mild), 2 (moderate), or 3 (severe).
High-resolution ultrasound examinations were performed using a Clarius L20 HD3 wireless broadband linear transducer (18–20 MHz; Clarius Mobile Health Corp., Vancouver, BC, Canada), with a maximum imaging depth of 4 cm and validated imaging up to 6 cm for selected applications. Subcutaneous tissue thickness was measured from the dermal–subcutaneous junction to the superficial muscular fascia, corresponding to the full subcutaneous compartment visible within the imaging field. In a limited number of patients with marked adiposity in whom subcutaneous thickness exceeded 4 cm, the superficial muscular fascia remained identifiable within the available imaging field, allowing complete measurement of the subcutaneous compartment. Images were acquired in a standardized transverse orientation with the patient in the prone position. The subgluteal aspect and the medial and lateral aspects of the proximal thigh were measured at the same transverse level. The posterior calf was measured in the transverse plane at the level of maximum calf circumference, with the patient prone and the foot in neutral dorsiflexion. The medial aspect of the proximal thigh was selected as the primary measurement site based on cross-sectional evidence identifying thigh subcutaneous thickness as a highly discriminating ultrasound parameter for lipedema diagnosis [
5] and the compartment showing the greatest subcutaneous thickness increase in lipedema compared with healthy controls [
6]. Secondary sites—lateral proximal thigh and posterior calf—were included to characterize the spatial distribution of the ultrasound response across the lower limb. Upper limb ultrasound assessment was not included in the protocol, as the study was designed to evaluate the lower limb compartments most characteristic of lipedema-specific tissue involvement.
Subcutaneous tissue thickness was measured bilaterally at the medial and lateral aspects of the proximal thigh and at the posterior calf; dermal thickness was measured bilaterally at the medial aspect of the proximal thigh. All measurements are expressed in millimeters and reported as the mean of right and left values. All examinations were conducted by the same trained operator throughout the study period. The ultrasound pattern of subcutaneous tissue was classified on an ordinal scale into three categories: homogeneous (grade 1), hyperechoic with fibrous septa (grade 2), and nodular/disorganized (grade 3). The presence of subcutaneous edema was recorded as a binary variable (present/absent); its extent was additionally classified as absent (0), focal (1), or diffuse (2).
Body weight and height were recorded using a calibrated medical scale and stadiometer, respectively. BMI was calculated as weight divided by height squared (kg/m2). Waist circumference was measured at the midpoint between the lower costal margin and the iliac crest; the waist-to-height ratio (WHtR) was derived as waist circumference divided by height, both expressed in centimeters. Lower limb circumferences (thigh, calf, and ankle) were measured bilaterally using a non-elastic flexible tape at standardized anatomical landmarks, with the patient standing and weight evenly distributed; all values are expressed in centimeters and reported as the mean of right and left measurements.
Spontaneous pain and pressure-evoked pain were each rated by the patient on an 11-point Numeric Rating Scale (NRS; 0 = no pain, 10 = worst imaginable pain) at each timepoint. Both dimensions were recorded independently.
2.5. Sample Size Justification
Given the retrospective real-world design, no formal a priori power calculation was performed. The sample of
N = 60 is consistent with cohort sizes reported in single-center observational studies on lipedema [
8], a condition with an estimated prevalence of 1–11% in adult women [
2,
9]. The 180 total observations (60 patients × 3 timepoints) were evaluated against the effective number of estimable parameters in the linear mixed-effects models: accounting for categorical covariates entered as dummy variables, the total number of estimable parameters per model was approximately 14, yielding a ratio of approximately 12.9 observations per parameter, above the commonly cited minimum of 10, though at the lower boundary of stable estimation [
10].
2.6. Statistical Analysis
Continuous variables are reported as mean ± standard deviation (SD) and median with interquartile range (25th–75th percentile). Categorical variables are reported as frequencies and percentages. All analyses were conducted on the complete dataset of 60 patients with no missing observations. Longitudinal changes in continuous outcomes were analyzed using linear mixed-effects (LME) models estimated by restricted maximum likelihood (REML), with a random intercept per patient and timepoint entered as a continuous covariate (0, 3, 6 months). The need for a random slope on timepoint was evaluated via likelihood ratio test (LRT) with models refitted by full maximum likelihood; a random slope was retained where LRT p < 0.05. All LME models were adjusted for the following baseline covariates: age, anatomical type, dietary pattern, self-reported physical activity level, Stemmer sign, use of compression garments, and receipt of lymphatic drainage. A sensitivity analysis treating timepoint as a categorical factor (T0, T3, T6) was performed for all primary ultrasound outcomes. Normality of residuals from each model was assessed using the Shapiro–Wilk test applied post-estimation. The presence of ultrasound edema was analyzed using the Cochran Q test; post-hoc pairwise comparisons across the three timepoint pairs were performed with McNemar’s test with Bonferroni correction (adjusted α = 0.017). The ultrasound echogenicity grade was analyzed using the Friedman test; post-hoc pairwise Wilcoxon signed-rank comparisons across the three timepoint pairs were performed with Bonferroni correction (adjusted α = 0.017). Mixed-effects ordinal regression was not estimable due to structural data constraints: with three repeated observations per patient, the random-effects variance diverged, and fixed-effects ordinal regression yielded complete separation. The Friedman test was therefore adopted as the primary inferential approach for this outcome. Spearman rank correlation coefficients were computed to assess associations between changes from T0 to T6 across ultrasound, anthropometric, and pain variables. Change scores (Δ) for all variables were computed as T6 − T0; negative values therefore indicate a reduction from baseline. Normality of change scores for primary ultrasound outcomes was additionally verified prior to correlation analyses. No correction for multiple comparisons was applied to the correlation analyses; all findings are considered exploratory. As a sensitivity analysis, Monte Carlo permutation tests (1000 permutations, seed 12345) were performed for significant correlations. All statistical tests were two-tailed; the significance threshold was set at α = 0.05. Analyses were performed using STATA19 (StataCorp., College Station, TX, USA).
3. Results
A total of 60 women with lipedema were consecutively enrolled in this study (
Table 1). The mean age was 44.7 ± 10.3 years and mean BMI 28.1 ± 1.1 kg/m
2. Type II lipedema (knee-level) was the most prevalent anatomical pattern (51.7%).
All primary ultrasound outcomes decreased significantly and progressively over six months (
Table 2). Subcutaneous thickness at the medial aspect of the proximal thigh declined from 48.2 ± 8.4 mm at T0 to 39.2 ± 8.4 mm at T6 (
p < 0.001), representing a reduction of 18.7%. Lateral proximal thigh and posterior calf showed significant but smaller reductions; dermal thickness decreased modestly throughout the follow-up period. Ultrasound edema was present in all patients at baseline and decreased to 55.0% at T6 (
p < 0.001); its extent shifted progressively from predominantly diffuse at T0 to predominantly absent or focal at T6 (
Table 2). The ultrasound echogenicity grade showed no significant change between T0 and T3, but a significant shift toward less disorganized patterns emerged between T3 and T6 (
p < 0.001; T3–T6:
p < 0.001), with grade 1 appearing in 13.3% of patients only at T6. Proportional reductions over six months were comparable across anatomical sites: waist circumference declined by 9.5%, thigh circumference by 9.0%, and calf circumference by 9.5%, while ankle circumference showed a more modest reduction of 7.2%, consistent with its lower baseline absolute values.
All anthropometric secondary outcomes improved significantly over six months. Body weight decreased by a mean of 4.0 kg (−5.1%) and BMI from 28.1 to 26.7 kg/m2; the waist-to-height ratio declined from 0.641 to 0.595. Thigh circumference showed the greatest proportional reduction (−9.0%). Both spontaneous and pressure pain scores improved significantly, although the absolute reductions were modest and likely below the minimum clinically important difference of 2 points.
Shapiro–Wilk tests applied post-estimation to LME model residuals did not reveal gross violations of normality for any continuous outcome; all W statistics exceeded 0.975 for ultrasound and anthropometric models. Minor departures observed in pain score models are consistent with the discrete ordinal nature of NRS data and are not considered to compromise model validity at the sample size employed.
Reductions in proximal thigh subcutaneous thickness showed a modest inverse correlation with weight loss (ρ = −0.343,
p = 0.008) and BMI reduction (ρ = −0.321,
p = 0.013). A positive correlation was observed between reduction in thigh circumference and reduction in spontaneous pain (ρ = 0.312,
p = 0.016). No significant correlations were detected between changes in ultrasound thickness and changes in either pain dimension (
Table 3).
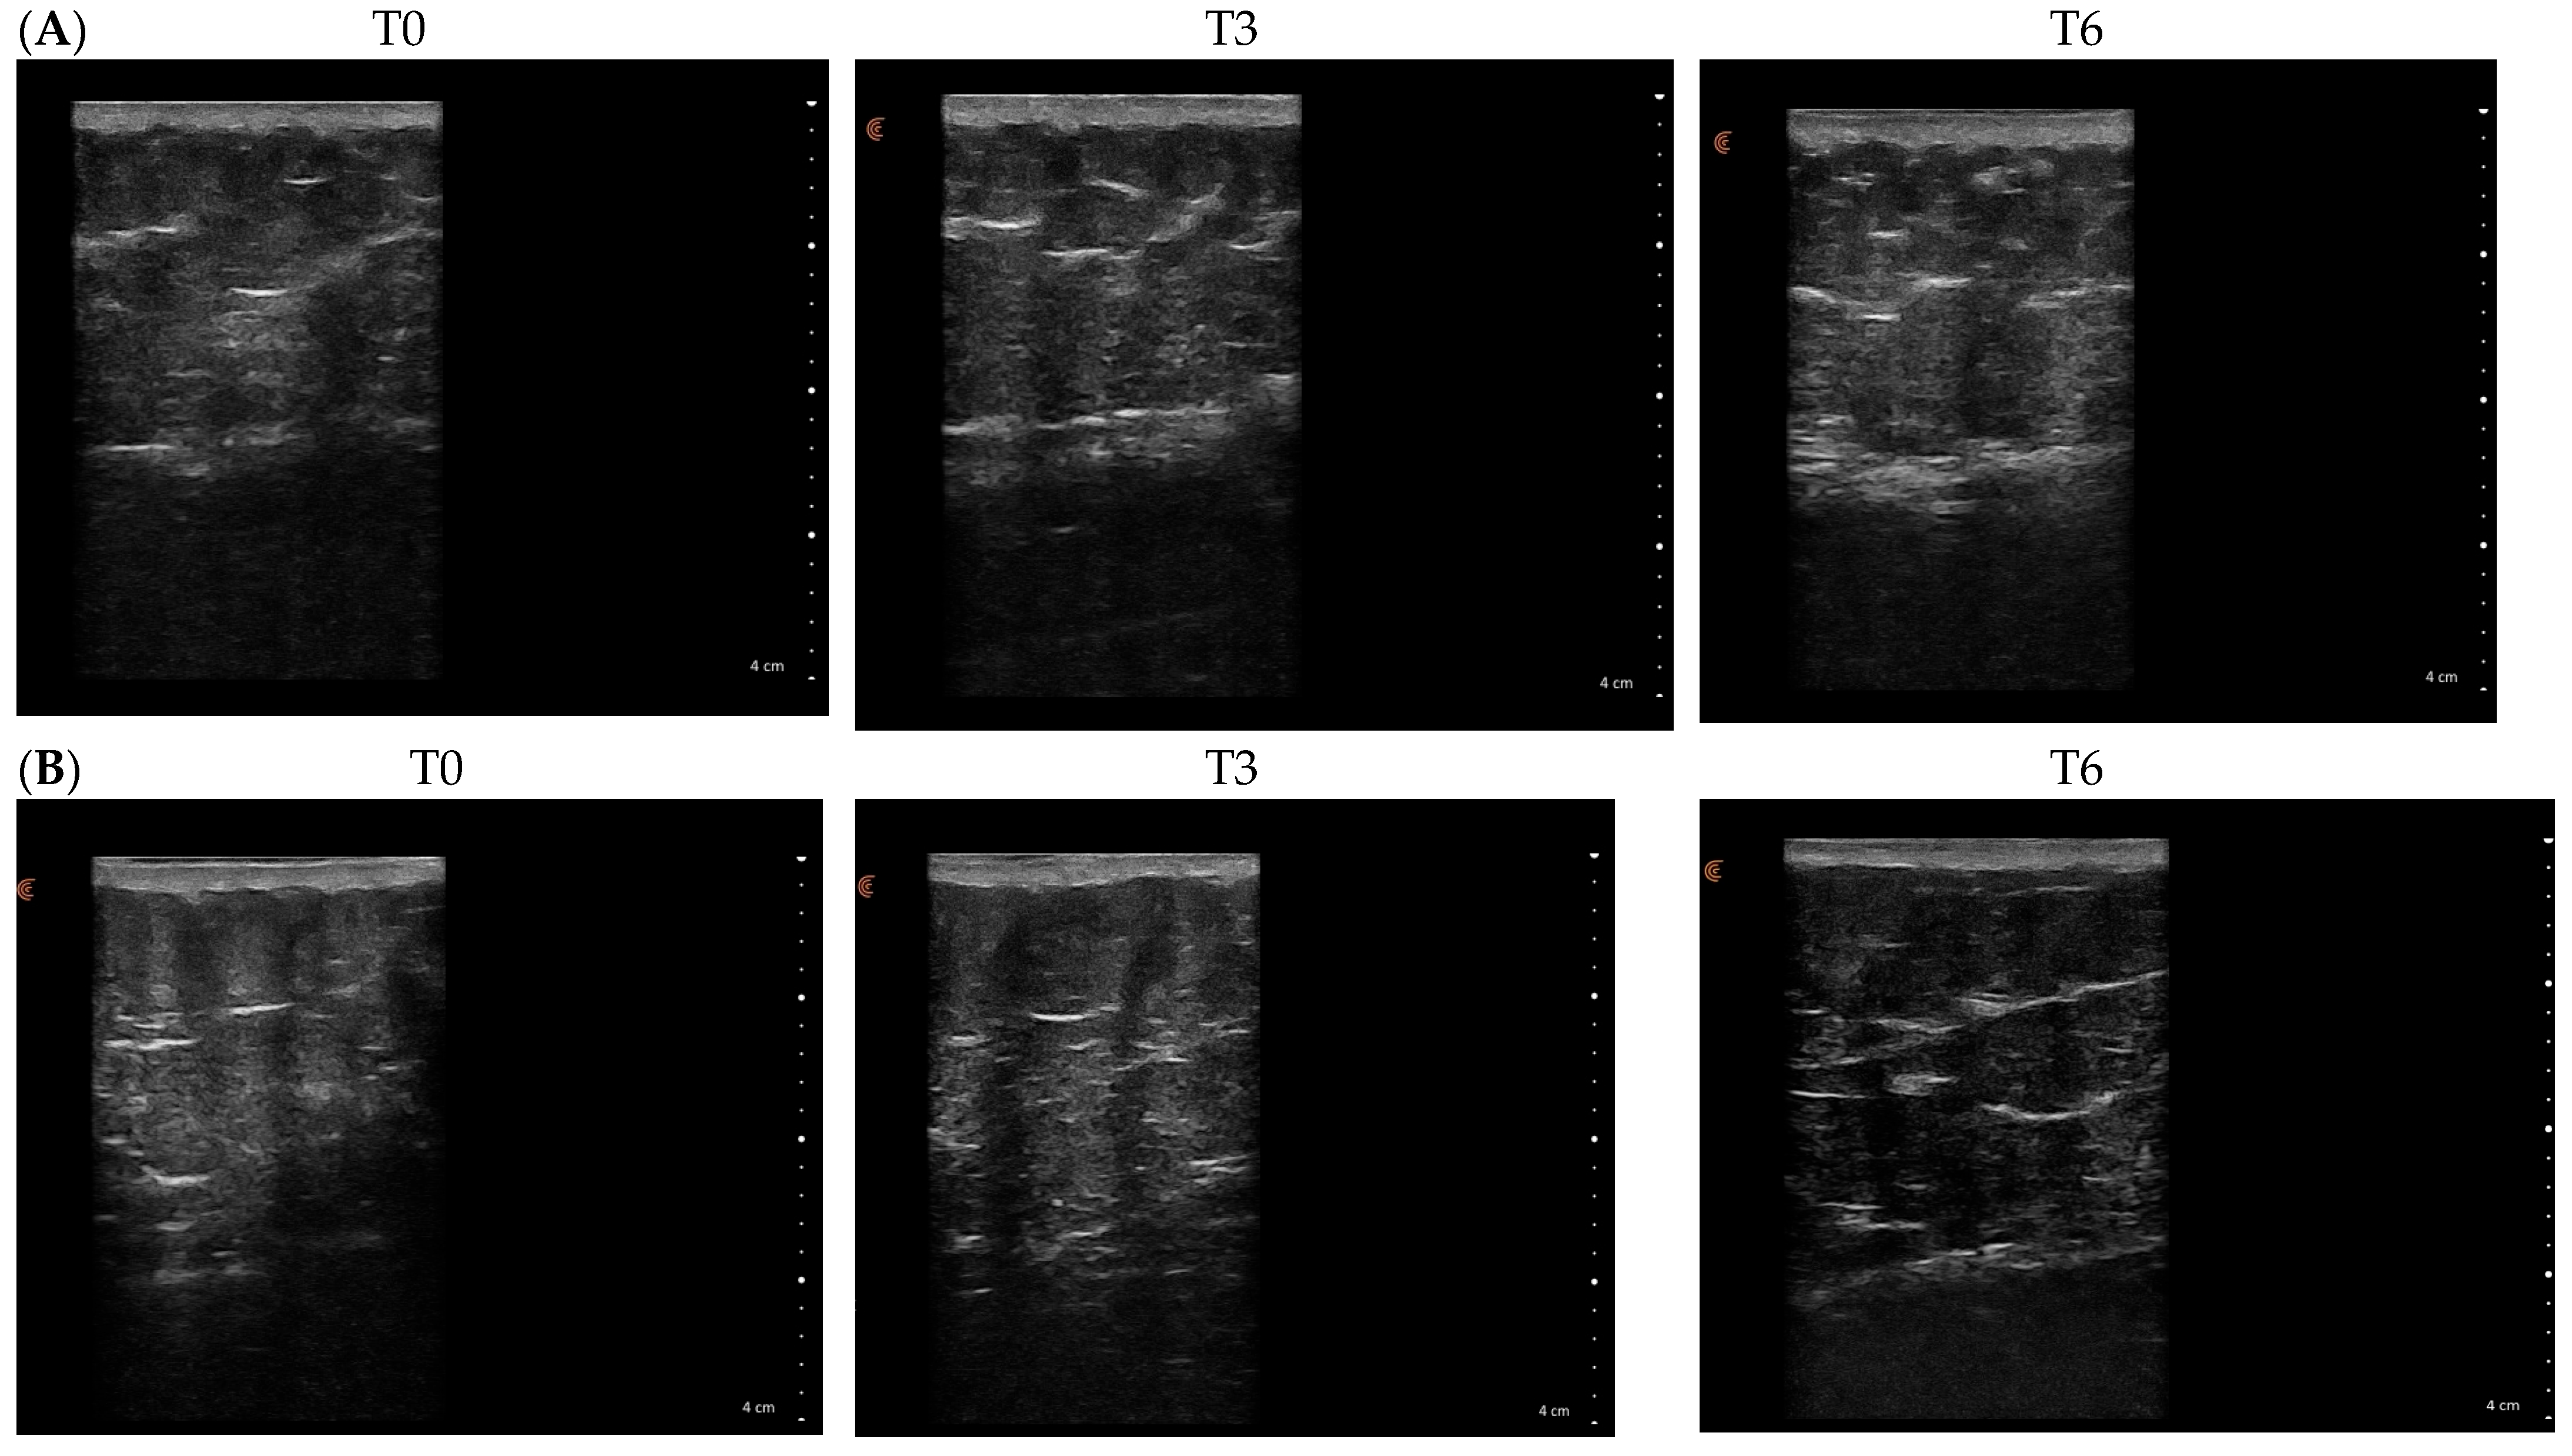
Representative longitudinal ultrasound series from two patients are illustrated in
Figure 1, demonstrating the early reduction in subcutaneous thickness observed between T0 and T3, and the subsequent structural remodeling of the fibrous septa and attenuation of hypoechoic components between T3 and T6.
4. Discussion
This study provides longitudinal real-world evidence that high-resolution ultrasound may detect measurable tissue-level changes in subcutaneous tissue thickness over six months in women with lipedema undergoing multicomponent nutritional and physical management. The medial aspect of the proximal thigh emerged as the most responsive measurement site; a finding aligned with the diagnostic framework established by previous cross-sectional studies. Amato et al. identified thigh subcutaneous thickness as the most discriminating single ultrasound measure for lipedema diagnosis, and Iker et al. demonstrated that the thigh subcutaneous compartment is the most volumetrically characteristic of lipedema compared with healthy controls, while skin thickness at the ankle and calf was the parameter most discriminating between lipedema and lymphedema [
5,
6]. Our findings indicate that the thigh subcutaneous compartment is also the most sensitive to change during conservative management follow-up, providing construct continuity between the diagnostic and monitoring roles of ultrasound in lipedema.
To our knowledge, no prior study has reported longitudinal quantitative ultrasound thickness measurements at multiple standardized anatomical sites in a consecutive cohort of lipedema patients undergoing conservative multicomponent management. The methodological approach of this study was designed to address the reproducibility limitations highlighted by the cross-sectional literature: Hirsch et al. showed that qualitative ultrasound morphological features cannot reliably differentiate lipedema from lipohypertrophy across centers, and van la Parra et al. confirmed that qualitative pattern-based approaches are insufficient for reproducible distinctions [
7,
11]. By relying on quantitative thickness measurements by a single trained operator at fixed anatomical landmarks, consistent with the single-operator acquisition protocol adopted by Pirri et al. in lymphedema to minimize observer bias [
12], the longitudinal changes detected here are attributable to true biological variation in the tissue.
One relevant finding of this study is the weak inverse correlation between proximal thigh ultrasound reduction and weight loss. Change scores were computed as T6 − T0, so that more negative values reflect greater reduction; the observed negative coefficient therefore indicates that patients with smaller weight loss showed larger ultrasound thickness reductions, a pattern not contradicted by the parallel group-level declines, which reflect the average cohort trajectory rather than individual covariation. This finding suggests that factors beyond total body weight may contribute to local tissue remodeling, potentially consistent with emerging molecular evidence that the pathological characteristics of lipedema adipose tissue may not respond proportionately to volumetric fat loss. Cifarelli et al., challenging the assumption of complete resistance to weight loss, demonstrated that in women with lipedema undergoing moderate diet-induced weight loss, lower-body fat mass measured by dual-energy X-ray absorptiometry (DXA) did reduce proportionately, but the inflammatory and fibrotic molecular characteristics of thigh subcutaneous adipose tissue persisted unchanged after weight loss: macrophage infiltration, upregulation of extracellular matrix remodeling genes, and markers of chronic low-grade inflammation remained elevated despite significant fat mass reduction and improved insulin sensitivity [
13]. Our ultrasound data appear consistent with this molecular evidence at the functional level, although direct histological confirmation was not available in this cohort. While DXA measures total lower-body fat mass, a composite that includes both lipedematous and non-lipedematous adipose depots, ultrasound at the subgluteal proximal thigh samples the site of greatest pathological involvement: the most inflamed, most fibrotic compartment, characterized by adipocyte hypertrophy, increased collagen deposition in the adipose interstitium, and a macrophage-dominated immune infiltrate with selective expansion of CD68+ macrophages without concurrent T-cell increase [
14]. Within this depot, Cifarelli et al. further documented a shift toward proinflammatory M1-like macrophage predominance in thigh subcutaneous adipose tissue specifically [
13]. One possible interpretation of the inverse correlation is that patients who lost more weight reduced primarily their non-lipedematous depots, reflected in BMI, while the pathologically remodeled tissue at the proximal thigh may have responded preferentially to components of the intervention with anti-inflammatory or decongestive properties, though this hypothesis warrants confirmation with tissue-level data. Ultrasound at this site may capture tissue-level information not fully resolved by body weight and BMI alone. Therefore, this finding should be interpreted as exploratory and hypothesis-generating, as the modest magnitude of the correlation along with a particular distribution of our sample—patients with the largest weight losses are few in number and may exert disproportionate leverage on the observed correlation—does not establish independence of ultrasound changes from weight loss but suggests that the relationship between the two is not simply linear. Confirmation in studies with concurrent histological sampling is warranted.
The absence of significant correlations between ultrasound changes and pain changes indicates that volumetric and nociceptive processes improve through distinct mechanisms. Lipedema pain is not primarily driven by mechanical compression of nerve fibers by fatty tissue: cutaneous allodynia is mediated by inflammatory sensitization of C-fiber and Aβ-fiber afferents, and comparable tissue bulk in lymphedema does not produce the same nociceptive phenotype [
15], consistent with the clinical observation that lipohypertrophy, morphologically similar to lipedema but defined by the absence of pain, represents a distinct non-nociceptive entity. This mechanistic distinction is also reflected in the observation by Jeziorek et al. that pain reduction following a Low-Carbohydrate, High-Fat (LCHF) diet in lipedema patients persisted independently of the magnitude of weight loss, suggesting that anti-inflammatory dietary effects, rather than volume reduction per se, are the primary driver of pain relief [
16]. These observations are consistent with the S2k guideline statement that pain does not correlate with the degree of disproportion or tissue volume [
2]. The positive correlation between thigh circumference reduction and spontaneous pain relief is not contradictory: it suggests that reduction in edematous tissue tension and local inflammatory burden, rather than mechanical decompression, may mediate pain improvement alongside volume change, in line with the anti-inflammatory mechanism proposed by Jeziorek et al. It should be noted, however, that the absolute reductions in both spontaneous and pressure pain were exactly 1 point on the NRS, falling below the minimum clinically important difference of 2 points generally accepted for chronic pain conditions. Statistical significance in this context should not be interpreted as clinically meaningful pain relief; the pain findings are best understood as signals of a biological trend requiring confirmation in adequately powered studies with longer follow-up.
A consistent pattern across primary outcomes is the biphasic temporal profile: volumetric indices changed significantly between T0 and T3, while the ultrasound echogenicity grade did not shift until T3–T6. The early phase may reflect reduction of interstitial edema and inflammatory exudate, processes potentially responsive to dietary modification and decongestive therapy, although attribution to specific intervention components is not possible in this uncontrolled design. The later shift in echogenicity grade, with grade 1 appearing only at T6, appears to represent structural remodeling of the fibrotic extracellular matrix architecture. This interpretation is supported by two converging lines of evidence: Herbst et al. describe fibrotic nodules within the loose connective tissue of lipedema as palpable structural elements composed of thickened fibrotic fibers connecting skin to superficial fascia, distinct from surrounding adipose tissue [
17]; and Barros et al. confirmed by biopsy that hypoechoic non-encapsulated nodules visible on B-mode correspond to foci of inflammatory microangiopathy with increased capillary density and mast cell infiltration, with the superficial fascia involvement further contextualizing these nodules within a broader adipo-fascial disease process [
18]. The slower kinetics of structural remodeling relative to volumetric improvement are biologically expected given this substrate. The clinical implication is direct: a persistent nodular pattern at three months should not be interpreted as treatment failure, since structural remodeling requires the full six-month observation window to become detectable at ultrasound. It should be noted that the echogenicity outcome was analyzed using the Friedman test without covariate adjustment, as mixed-effects ordinal regression was structurally non-estimable in this dataset. The biphasic pattern should therefore be interpreted with caution, as the possibility that baseline clinical characteristics contributed to the observed temporal shift cannot be statistically excluded.
Anthropometric outcomes improved consistently with a significant decline in WHtR, a more accurate descriptor of body composition in lipedema than BMI [
2,
19]. The proportionally greater reduction in thigh circumference relative to body weight is consistent with preferential loss from the lipedematous lower-body compartment, a pattern analogous to the preferential ankle circumference reduction observed by Jeziorek et al. in the lipedema group following an LCHF diet [
16].
Whether the observed statistically significant changes translate into clinical benefit for patients remains to be established; notably, pain reductions fell below the minimum clinically important difference, and the absence of a control group precludes attribution of tissue-level changes to the intervention. Nonetheless, the observed modifications across multiple ultrasound parameters are consistent in direction and magnitude. A reduction in subcutaneous thickness concurrent with BMI reduction is an expected finding under conservative management; what ultrasound may add is the ability to characterize the nature, timing, and tissue-level specificity of that change. The biphasic temporal profile and the dissociation between ultrasound and anthropometric trajectories at the individual level reveal processes that anthropometry cannot resolve. This additional information is precisely what may support the integration of ultrasound into routine lipedema monitoring, pending confirmation in controlled study designs.
This study has several limitations that should be considered when interpreting its findings. First, the retrospective single-center design without a control group precludes causal attribution of the observed changes to specific intervention components; the possibility that improvements reflect spontaneous disease fluctuation, regression to the mean, or unmeasured confounders cannot be excluded. Second, the multicomponent nature of the intervention precludes attribution of effects to any single component; in particular, the differential anti-inflammatory properties of low-carbohydrate and ketogenic diets relative to the Mediterranean diet may have contributed differentially to the ultrasound and pain outcomes across dietary subgroups, an analysis that was underpowered in the present cohort. Third, pain improvements, while statistically significant, were modest in absolute terms and likely below the minimum clinically important difference. Fourth, correlation analyses were exploratory and uncorrected for multiple comparisons and should be interpreted accordingly. Fifth, the six-month observation period does not permit conclusions regarding the durability of the observed improvements. Sixth, echogenicity was analyzed using non-parametric methods, as mixed-effects ordinal regression was structurally non-estimable in this dataset. Seventh, intra- and interobserver reproducibility was not formally assessed; all examinations were conducted by the same unblinded operator and, although predefined anatomical sites and standardized acquisition parameters constrained operator discretion, systematic bias related to knowledge of the patient’s timepoint cannot be entirely excluded. Finally, the restriction to patients with a baseline BMI below 30 kg/m2 limits generalizability to the broader lipedema population, which in clinical practice includes a substantial proportion of patients with obesity comorbidity.