


Abstract
Background/Objectives: Dementia represents a complex syndrome in which biological, psychological, social, and cultural dimensions intersect. While its clinical features are well documented, less is known about how lived experiences, caregiving contexts, and cultural beliefs shape the trajectory of illness. This study explored clinical, behavioral, and socio-cultural dimensions related to the quality of life of people living with dementia from an anthropological perspective, focusing on the interaction between comorbidities, cognition, lifestyle, and caregiving environments as reported by their informal caregivers. Methods: We conducted a single-center, observational cross-sectional study including 73 family caregivers of patients with clinically diagnosed dementia who accessed care at the Neurology–Psychiatry Department of the C.F.2 Clinical Hospital (Bucharest, Romania) between November 2023 and April 2024. Caregivers provided socio-demographic, behavioral, lifestyle, and cultural information using a newly developed anthropological questionnaire. Descriptive and exploratory inferential analyses were performed to examine relationships between cognitive performance, comorbidities, lifestyle factors, and socio-cultural variables. Results: People with dementia had a mean age of 79.2 ± 7.5 years (range 66–95) and were predominantly female (71.2%). Multimorbidity was common, averaging 2.22 ± 1.03 chronic conditions, mainly neurological (84.9%) and cardiovascular (68.5%). The mean BMI was 26.1 ± 3.8 kg/m2. Cognitive impairment was substantial (MMSE mean 11.47 ± 7), with descriptively lower scores among older individuals and those with lower education or income, although inferential tests were underpowered. Appetite and sleep disturbances were frequent and tended to co-occur with lower activity levels. Disclosure of diagnosis occurred in 74% of cases; reactions varied widely, ranging from acceptance to denial, confusion, anxiety, and sadness. Family responses likewise reflected a heterogeneous and often ambivalent adjustment process. Cultural beliefs and spirituality played a salient role in shaping explanatory models and coping strategies, with many caregivers attributing importance to religious practices and, to a lesser extent, alternative treatments. Conclusions: In this Romanian cohort, dementia was shaped not only by age-related multimorbidity and cognitive decline but also by caregiving practices, socioeconomic constraints and culturally grounded interpretations of illness. These findings highlight the relevance of integrative approaches to dementia care that consider medical, behavioral, and socio-cultural dimensions and that incorporate caregiver perspectives to improve the quality of life of both patients and families.
1. Introduction
Dementia represents one of the most pressing global health challenges of the 21st century, affecting over 55 million people worldwide, with nearly 10 million new cases each year. As populations age, the prevalence of dementia is projected to triple by 2050, placing increasing pressure on healthcare systems, caregivers, and society [1,2]. Despite advances in understanding its pathophysiology, dementia remains a complex syndrome influenced by biological, psychological, and social factors, requiring multidimensional approaches to research and care.
Traditional biomedical models have emphasized the role of neuropathology, particularly amyloid and tau accumulation, as central contributors to Alzheimer’s disease and related dementias. More recently, neuroimaging evidence has highlighted additional mechanisms such as demyelination, which appears to play a role in both mild cognitive impairment (MCI) and dementia [3]. At the same time, protective factors across the life course, including education, occupation, lifestyle, and social engagement, are recognized as contributors to the concept of cognitive reserve [4,5,6]. Individuals with higher education and richer cultural experiences tend to show delayed clinical manifestations of neuropathological burden, underscoring the relevance of sociodemographic context in dementia outcomes.
Multimorbidity and frailty are also highly prevalent in dementia populations, with cardiovascular, metabolic, and nutritional issues frequently coexisting. Among them, appetite disturbances are particularly relevant, being linked to malnutrition, frailty, and accelerated disease progression [7,8,9]. Similarly, sleep disruptions are increasingly recognized not only as consequences of dementia but also as potential precursors of neurodegeneration, with recent evidence showing that sleep disturbances may precede diagnosis by more than a decade [10].
Beyond biomedical frameworks, the social and cultural context profoundly shapes the lived experience of dementia. Family networks often provide the primary source of support, especially in countries with limited formal services, but this reliance places a disproportionate burden on caregivers [1]. Spirituality, religious practices and alternative explanatory models may also influence coping strategies and health-seeking behavior. Recent studies indicate that higher levels of spirituality in persons with mild to moderate dementia are associated with slower cognitive decline and fewer neuropsychiatric symptoms [11,12], while qualitative evidence shows that caregivers often turn to prayer, faith, and religious reading as mechanisms of resilience and meaning-making in the face of dementia [13]. Such findings highlight the importance of perspectives that integrate cultural and anthropological perspectives into dementia research. Here, an anthropological perspective refers to the integration of socio-cultural beliefs, lived experiences, caregiving practices, and meaning-making processes into the understanding of dementia.
Taken together, these dimensions highlight the need for integrated, caregiver-informed research that captures not only biomedical and cognitive aspects but also lifestyle, cultural, and social determinants of health. This study therefore adopts an anthropological perspective to examine caregiver-reported information on behavioral manifestations, comorbidities, and quality of life in persons living with dementia. Given the cross-sectional nature of the data, these relationships were examined descriptively and should be interpreted as exploratory rather than causal.
Despite an expanding body of research on dementia, much of the existing literature remains dominated by biomedical models that focus primarily on neuropathology. While such approaches are fundamental to understanding disease mechanisms, they often overlook the lived experiences of patients and caregivers, as well as the broader socio-cultural and lifestyle contexts in which dementia unfolds. Recent findings highlight the influence of multimorbidity, nutritional factors, sleep disturbances, and social networks on the trajectory of dementia, yet these dimensions are still underrepresented in clinical and epidemiological research [7,8,10].
In Romania and similar settings with limited formal dementia care infrastructure, caregiving is predominantly provided by family members. This reality not only places a considerable burden on caregivers but also makes their perceptions and reports a crucial source of knowledge regarding the manifestations and management of day-to-day functioning. Caregivers are uniquely positioned to observe changes in appetite, sleep, activity, cognition, and behavior over time in persons living with dementia, providing valuable insights that complement clinical assessments.
Cultural and anthropological dimensions—including spirituality, religious practices and alternative explanatory models—shape coping strategies and health-seeking behaviors in ways that biomedical frameworks cannot fully capture [11,13]. Integrating these perspectives allows for a more holistic understanding of dementia, particularly in contexts where formal healthcare services are fragmented and families rely on traditional, spiritual or community-based support systems.
In Romania and other Central and Eastern European (CEE) countries, dementia and dementia care remain areas where formal support systems are underdeveloped, making family caregivers the primary providers of care. Recent initiatives, such as Strengthening Research Capacity and Policy Responses—Dementia Romania, have highlighted the urgent need for a coherent national dementia plan to ensure equitable access to diagnosis, outpatient services, long-term care, and psychosocial support for families. Studies show that Romanian general practitioners perceive their role in dementia detection and monitoring as limited due to insufficient training, scarce resources, and the lack of specialized services, particularly in rural communities [14]. Comparative European analyses further underline major regional disparities in dementia care provision: in Romania, services are fragmented and concentrated mainly in urban centers, with restricted access in rural areas [15]. Under these conditions, caregivers’ perceptions—shaped by cultural beliefs, experiences of stigma, expectations regarding state support, and the role of religion—become central to the way dementia is experienced, understood, and managed.
The present study addresses these gaps by adopting an anthropological perspective on dementia, using caregiver-reported data to explore contextual factors, comorbidities, behavioral manifestations, and quality of life of people living with dementia. The aim was to describe the behavioral, socio-anthropological and lifestyle characteristics of community-dwelling persons with dementia as reported by their informal caregivers and to descriptively examine how caregiver-reported behavioral, lifestyle, cultural, and health-related factors vary across levels of cognitive severity of the care recipients. By integrating biomedical, behavioral, and cultural dimensions within a single analytical framework, this study seeks to contribute contextually grounded evidence and to emphasize the importance of caregivers’ perspectives in dementia research and care. In this sense, the anthropological perspective informs interpretation and contextualization of findings rather than serving as a standalone analytical framework. To this end, the study sought to answer the following exploratory question: How do caregiver-reported behavioral, lifestyle, cultural and health-related factors relate to the severity of cognitive impairment in community-dwelling persons with dementia?
2. Materials and Methods
This study was designed as a single-center, observational, analytical cross-sectional investigation examining how biomedical, behavioral and socio-cultural dimensions of dementia are perceived and reported by informal family caregivers. Given its design, all analyses were descriptive and exploratory in nature, with no causal inferences intended. Data were collected between November 2023 and April 2024 at the Neurology–Psychiatry Department of the C.F.2 Clinical Hospital in Bucharest, Romania. During this interval, a total of 120 informal caregivers sought dementia-related services at the clinic; all were screened for eligibility and 73 met inclusion criteria and agreed to participate. Because the sample reflects all eligible caregivers during a defined six-month period rather than a probabilistic selection process, the study does not aim for population representativeness and its findings should be interpreted as context-specific and exploratory. Eligibility criteria required participants to be at least 30 years old, to be a family member of the person with dementia, to have provided care for at least six months and to be actively involved in caregiving at the time of recruitment. Exclusion criteria eliminated non-family caregivers and respondents with incomplete questionnaire data. No financial or material incentives were offered for participation.
All data were collected in person at the physician’s office within the Neurology–Psychiatry Department. Caregivers completed the study questionnaires in a self-administered format while on-site, with a member of the research team available to clarify instructions if needed. Completion time averaged approximately 45 min per participant. Caregivers were informed that participation was voluntary and that their decision would not affect ongoing or future access to medical care.
The Mini-Mental State Examination (MMSE) scores for the persons with dementia were extracted from medical records at the time of diagnosis. The MMSE is a widely used cognitive screening tool scored from 0 to 30, with commonly applied orientation thresholds in clinical practice: ≤10 (severe impairment), 11–20 (moderate), 21–24 (mild) and ≥25 (mild or minimal impairment). MMSE values were used to characterize the level of cognitive functioning of the patients and to explore potential relationships with caregiver-reported data. Because MMSE scores were recorded at the time of diagnosis rather than contemporaneously with caregiver data collection, temporal mismatch represents a potential source of bias and is acknowledged as a study limitation.
To capture socio-cultural, lifestyle, and belief-related dimensions of dementia—domains often insufficiently addressed in biomedical assessments—a dedicated Anthropological Questionnaire (AQ) was developed specifically for this study. The AQ included items on sociodemographic characteristics, daily routines, lifestyle habits, perceived behavioral and functional changes, spiritual and religious practices, and cultural explanatory models related to illness and caregiving. The initial version of the AQ was piloted with 15 formal caregivers to evaluate item clarity, linguistic accessibility and content relevance. Feedback from the pilot informed the refinement of item wording, response categories and thematic grouping, resulting in the final version administered in this study. The development process was informed by anthropological frameworks on illness narratives, caregiving practices and cultural explanatory models.
Because the AQ was designed as a multidomain, context-specific tool rather than a standardized psychometric instrument, internal consistency was examined only for conceptually coherent subsets of items. Three behavioral domains were evaluated as follows: eating, activity, and sleep.
The Appetite/Eating domain included items assessing appetite disturbance, eating independence, appetite level, remembering hunger and thirst, and eating regularity. Internal consistency was acceptable for exploratory purposes (Cronbach’s α = 0.69). The Current Activity domain included physical activity, intellectual activity, walking/outdoor activity, and travel. Internal consistency was good (Cronbach’s α = 0.73).
The Sleep domain included sleep disturbance, sleeping separately, night awakenings, and daytime napping. Items did not form a coherent unidimensional structure (Cronbach’s α < 0), indicating that sleep-related behaviors captured distinct phenomena. These variables were therefore analyzed individually rather than combined.
Additional AQ subdomains capturing beliefs, perceived support, and explanatory models were also evaluated. These domains—grounded in anthropological theory rather than psychometric scale construction—were assessed within coherent thematic clusters: perceived support (family, friends, and hope), religiosity/spirituality (belief in God, and role of the priest), alternative beliefs (natural remedies, curses, and bioenergy), and lifestyle and medical trust (diet, discipline, and perceived quality of care).
Cronbach’s α indicated acceptable consistency for support (α = 0.60) and religiosity (α = 0.65), good consistency for alternative beliefs (α = 0.75), and moderate-to-good consistency for lifestyle and medical trust (α = 0.69). These values support the internal coherence of AQ subdomains while affirming the multidimensional nature of socio-cultural and belief-related constructs. All AQ-derived indices were used as descriptive, exploratory measures rather than formal scales, consistent with the study’s aims and the qualitative-anthropological origins of the instrument.
Given the modest sample size, statistical power was limited and multivariable modeling was not considered as a primary analytic strategy; analyses were restricted to descriptive and bivariate comparisons. Findings should therefore be interpreted as hypothesis-generating.
All caregiver participants provided written informed consent. They were explicitly informed that patient cognitive data were retrieved solely from medical records and were fully de-identified, thereby maintaining confidentiality and removing the need for direct patient consent. The study protocol received full approval from the Ethics Committee of the C.F.2 Clinical Hospital (Reference No. 1781/06.02.2023). Participants were informed about the objectives, procedures, potential risks, and benefits of the study and were assured of their right to withdraw at any stage without any consequences for their own or their relatives’ access to medical care. All data were stored and analyzed in aggregate form to ensure complete anonymity.
3. Results
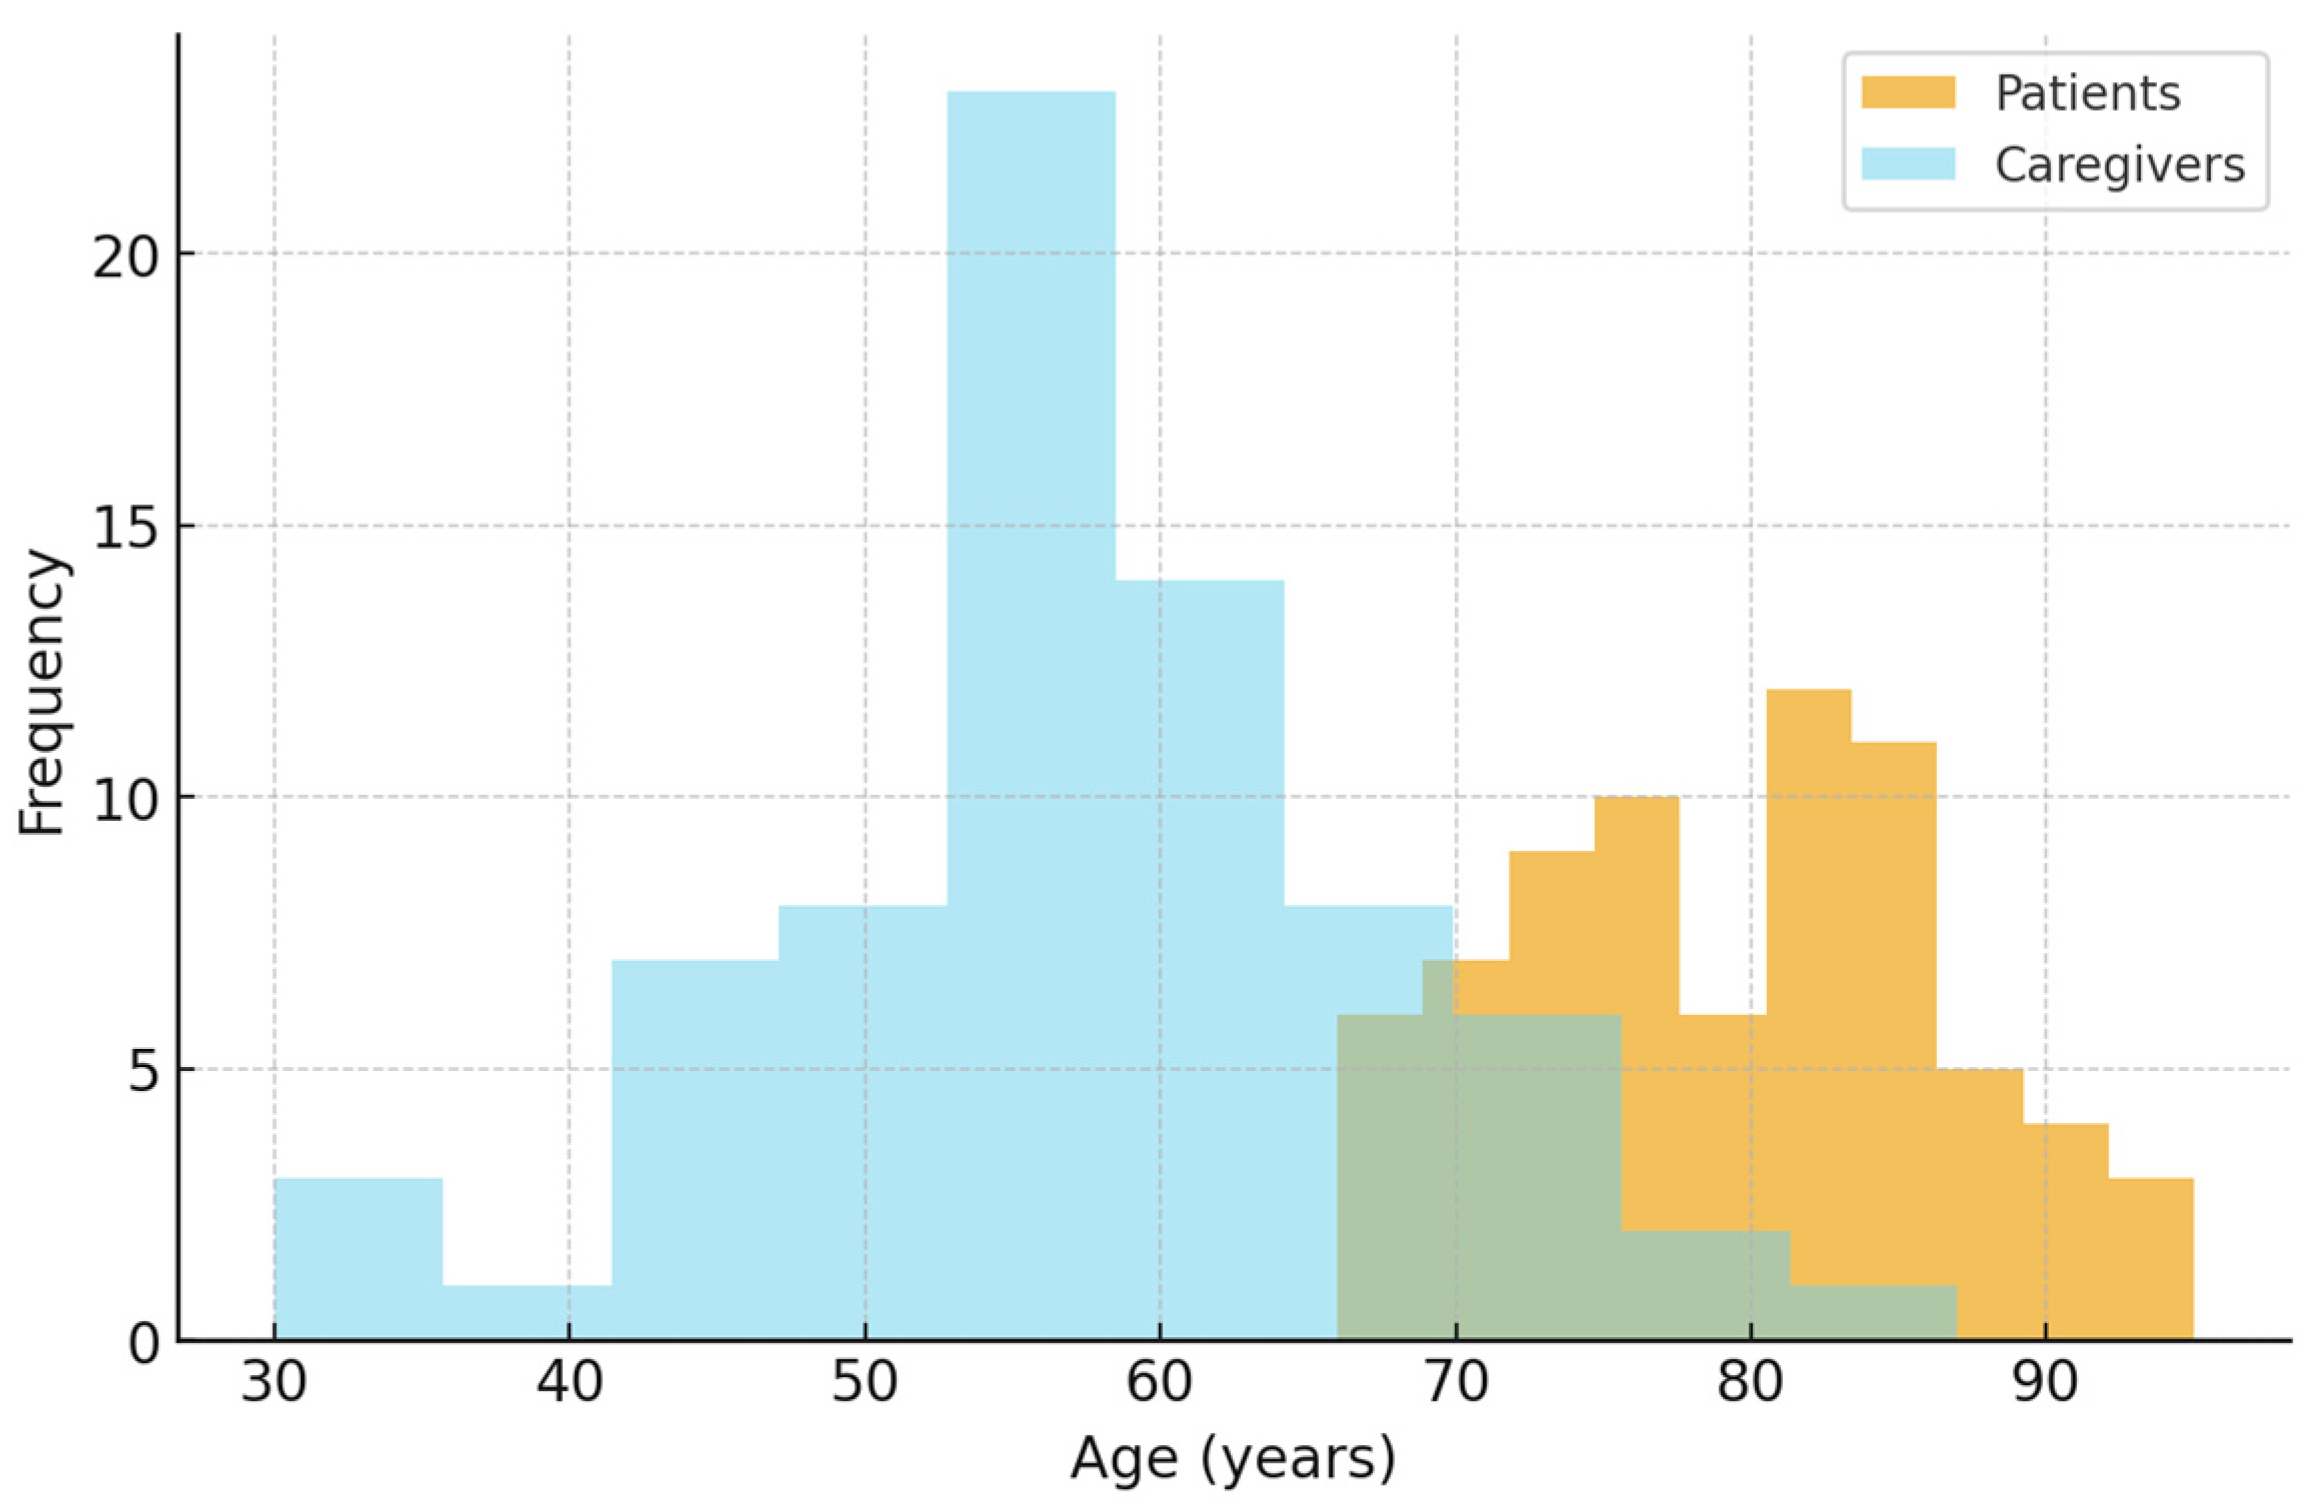
Seventy-three adults with a documented clinical diagnosis of dementia were included in the study. All study data—including behavioral, lifestyle, and socio-cultural information—were reported by family caregivers. The mean age was 79 years (SD = 8.0; range 66–95) with a median of 80 years (Table 1, Figure 1). The mean body weight was 72.6 kg (SD = 15.3) and the mean body mass index (BMI) was 26.9 kg/m2 (SD = 4.8), placing the average patient in the overweight category. Only 11 (15.1%) of the patients were living alone, with the others residing in households with a mean size of 3 members.
Table 1.
Demographic characteristics of the sample.
Figure 1.
Age distribution of patients and caregivers (Green= yellow overlapping blue).
In exploratory bivariate analyses, higher age was modestly related to lower MMSE scores (Spearman ρ = −0.259, p = 0.027), indicating that older patients tended to exhibit more pronounced cognitive impairment, although the strength of this relationship was limited. Educational attainment was generally low, with only three individuals (4.11%) having completed higher education.
When MMSE scores were examined across educational strata, descriptive differences emerged. Patients with only primary or lower secondary education (n = 46) had the lowest average MMSE scores (mean = 9.96, SD = 6.23). Those who had completed high school (n = 24) had higher average scores (mean = 14.71, SD = 7.77). The small subgroup with higher education (n = 3) showed a mean MMSE of 8.67 (SD = 2.08), but the extremely small group size and substantial within-group variability preclude meaningful statistical interpretation. A nonparametric test indicated overall differences across education categories (Kruskal–Wallis χ2 = 6.44, df = 2, p = 0.040), yet these results require cautious interpretation due to the imbalance between groups and the exploratory nature of the analyses. Taken together, the data suggest that patients with lower educational attainment tended to show poorer cognitive performance, whereas those with high school education appeared to perform somewhat better. However, the very limited number of patients with higher education and the considerable variability within groups prevent firm conclusions. Thus, while the pattern is compatible with the notion that educational attainment may relate to cognitive functioning, the present findings remain descriptive and insufficient to substantiate the cognitive reserve hypothesis.
Household income clustered mainly below 1000 EUR/month, with a substantial group (n = 43, 58.9%) in the 400–1000 EUR bracket and a smaller fraction above 1000 EUR (12.3%).
Chronic conditions were highly prevalent among the participants, reflecting the complex health profiles that often accompany dementia. Neurological disorders were reported in 84.9% of cases, cardiovascular diseases in 68.5%, and metabolic or endocrine conditions in smaller proportions. Pulmonary and digestive conditions were less common. Overall multimorbidity averaged 2.22 ± 1.03 conditions (SD = 1.03; median 2, IQR 2–3; range 0–6) (Table 2), a burden that is consistent with the advanced age of the sample and reflects the cumulative health challenges typically observed in older (Table 2). In bivariate analyses, multimorbidity showed no meaningful relationship with age (Spearman ρ = −0.026; p = 0.824) and did not differ across age strata (65–74, 75–84, ≥85 years: mean counts = 2.18, 2.27 and 2.17, respectively; χ2 = 0.48; p = 0.788). Likewise, comorbidity counts did not differ by appetite category (p > 0.99) or sleep status (p = 0.167). These findings indicate that, within this sample, multimorbidity was widespread but not a discriminating factor across demographic or behavioral subgroups. (Table 2).
Table 2.
Comorbidities and multimorbidity.
Despite its high prevalence, multimorbidity did not differentiate patients in terms of behavioral or lifestyle characteristics, prompting further examination of domains such as appetite, sleep, and daily activity.
Multimorbidity showed no significant differences by appetite status (p > 0.99) or sleep disturbance (p = 0.167). Appetite changes were frequently reported, with 58.9% of caregivers indicating reduced or affected appetite (Table 3). Body mass index did not differ across appetite categories (Kruskal–Wallis χ2 = 6.68; p = 0.352).
Table 3.
Appetite and sleep changes.
Appetite responses also displayed significant bivariate relationships with sleep disturbance (χ2 = 159.44; df = 36; p < 0.0001) and with physical activity (χ2 = 394.40; df = 282; p < 0.001), although several contingency table cells were sparse. Descriptively, reduced appetite tended to co-occur with disturbed sleep and lower activity levels, suggesting a recurrent behavioral pattern in a substantial subset of patients.
Smoking status alcohol consumption was also assessed. 18 participants (24.7%) were identified as current smokers, while 55 (75.3%) were non-smokers. Alcohol consumption varied by beverage type yet overall consumption was low, with most caregivers reporting reduced or infrequent intake (Table 4). These patterns reflect predominantly occasional rather than regular drinking behaviors within the sample.
Table 4.
Alcohol consumption.
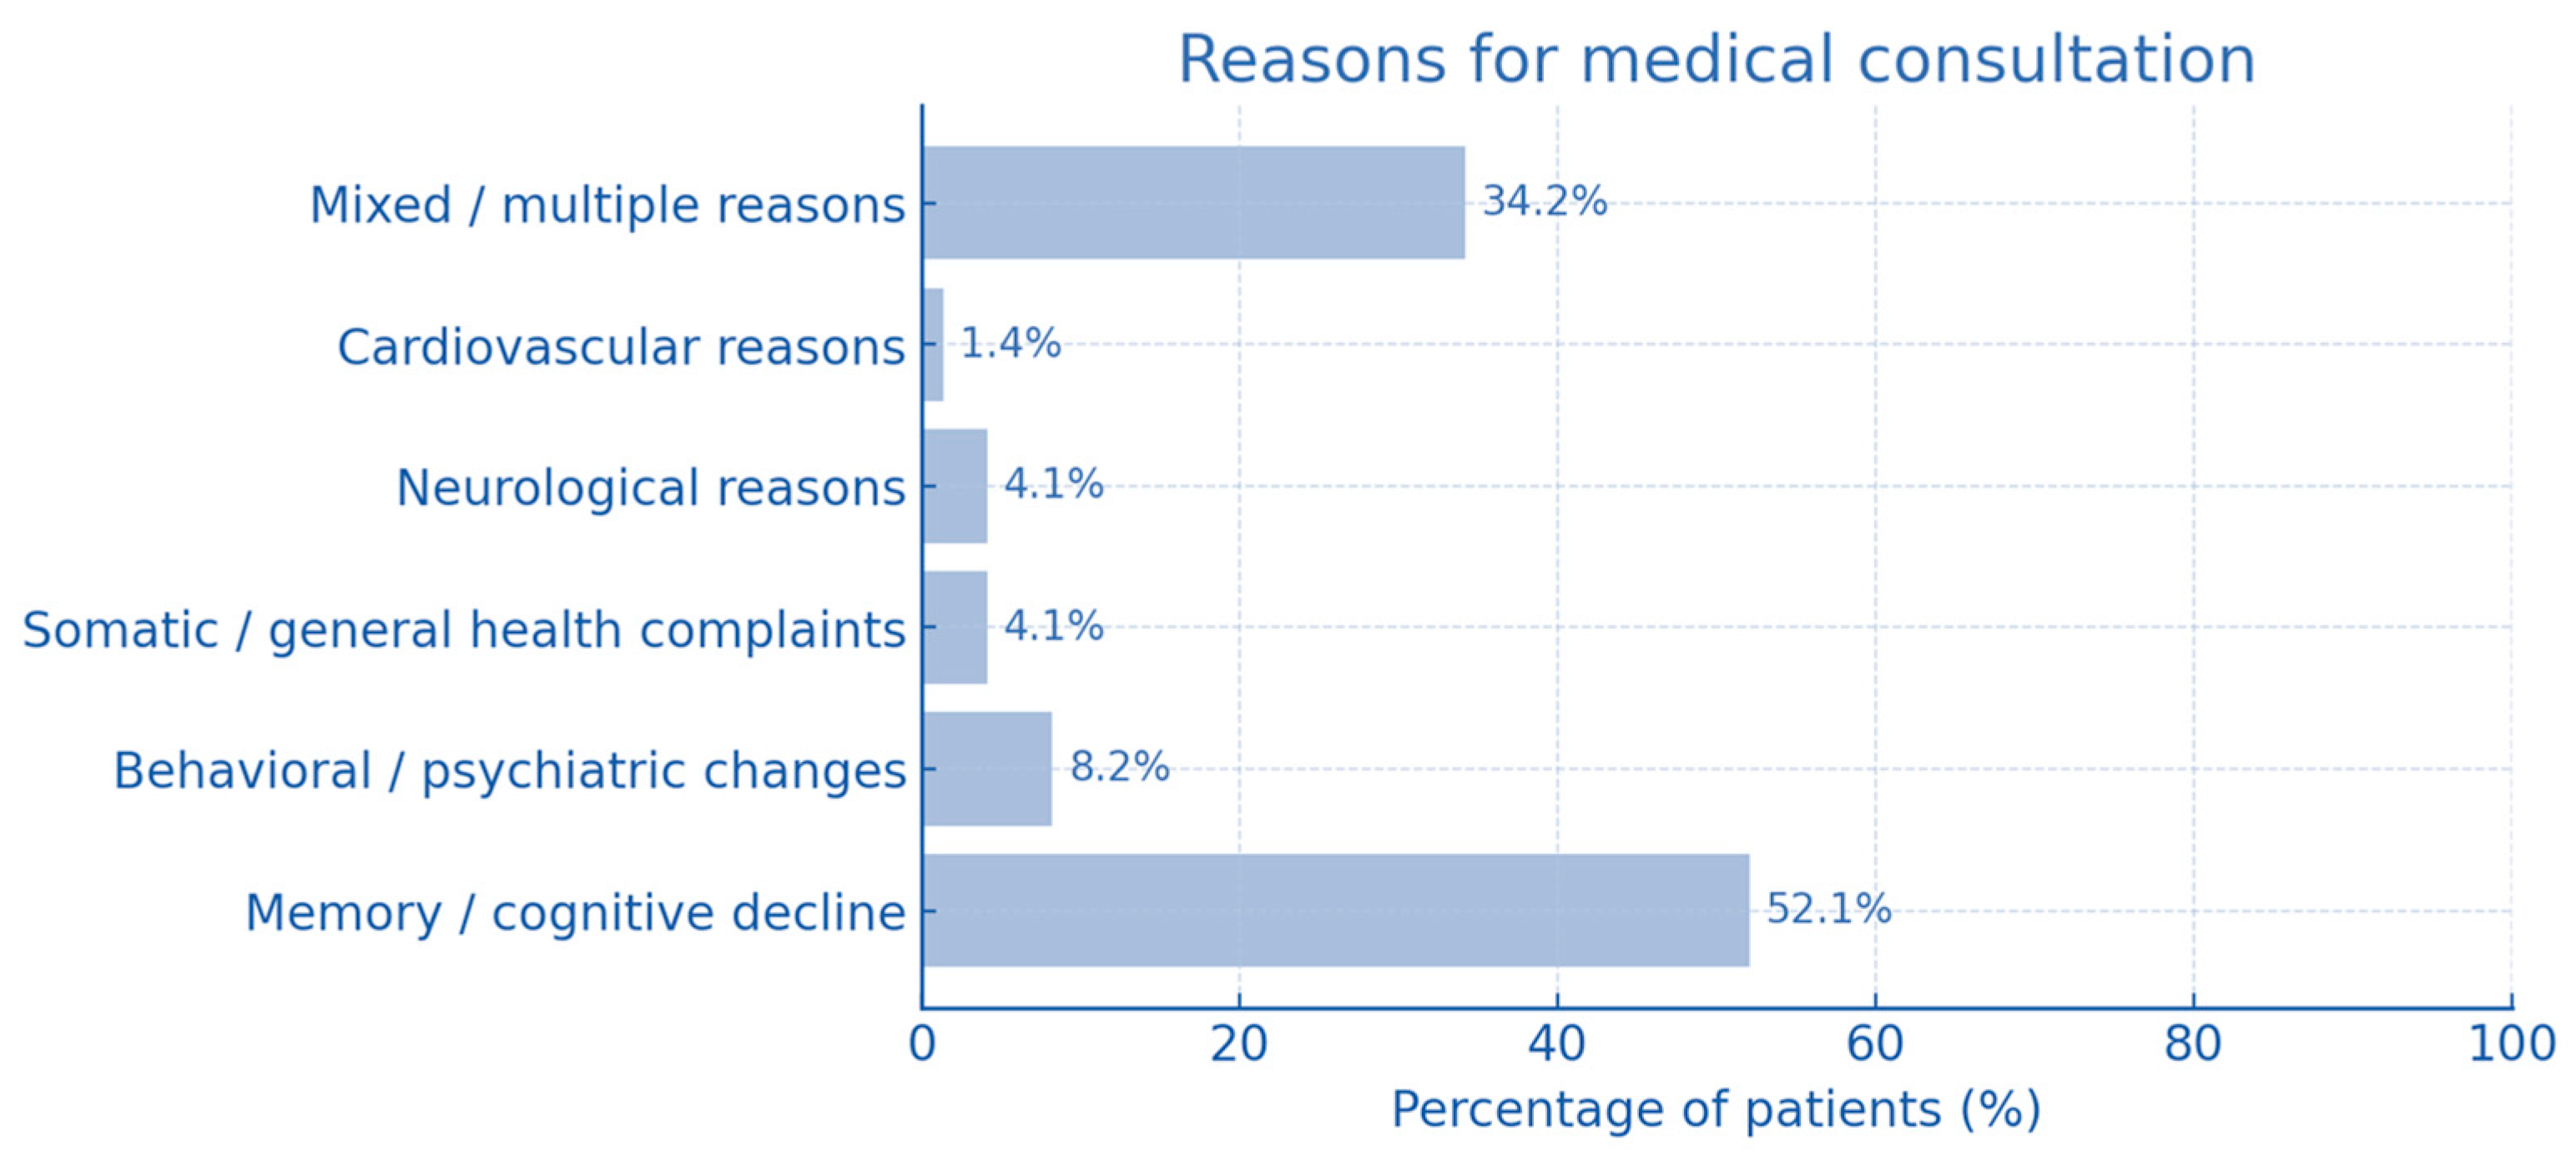
Caregivers most often reported memory impairment and cognitive decline as the presenting complaints, followed by confusion, disorientation, and progressive deterioration (Figure 2). These frequently co-occurring symptoms illustrate the overlapping cognitive and behavioral changes that prompted families to seek clinical evaluation. In many cases, multiple symptoms coexisted, reflecting the heterogeneous and multidimensional nature of early dementia presentations as perceived by caregivers, rather than discrete or isolated complaints.
Figure 2.
Reasons for seeking professional help.
Mealtime behaviors (eating independently, meal regularity, meals/day, skipped meals, and reasons) are illustrated in Table 5, outlining fragile routines with missed meals due to poor appetite, forgetfulness, or distraction. These descriptively observed patterns underscore the functional and behavioral vulnerabilities commonly encountered in day-to-day care.
Table 5.
Eating habits, meal patterns, and appetite.
Food-group consumption (fruits, vegetables, animal-source foods, cereals, and milk/dairy) is summarized in Table 6. Milk/dairy differed by appetite category (χ2 = 14.71; p = 0.023), while the other food groups did not show statistically significant variation across appetite levels. Given the exploratory nature of these analyses and uneven cell distributions, these findings should be interpreted cautiously.
Table 6.
Food group intake.
Supplement use and stimulants intake (coffee/tea/cola/energy drinks) were modest overall (Table 7). According to caregiver reports, most patients did not regularly use dietary supplements or stimulants and patterns of intake appeared largely occasional rather than habitual. Calcium, magnesium, and iron supplements were used by a small minority, while multivitamin use was somewhat more frequently noted (28.8%). Coffee was the most commonly reported stimulant (34.2%), whereas cola drinks, energy drinks, and tea were rarely mentioned.
Table 7.
Supplement use and stimulants intake.
Some of the care recipients slept separately from spouse/family (61.6%), reflecting household adaptations to nocturnal symptoms.
Physical activity was generally low, ranging from minimal in-home movement to homebound or bedbound status; according to caregiver reports, only a small proportion of patients engaged in regular chores or structured exercise (Table 8). Activity levels showed no meaningful differences across appetite categories, but were significantly related to sleep disturbance (χ2 = 49.30; p = 0.003), with lower activity tending to co-occur with poorer sleep patterns. No other consistent patterns emerged across behavioral subgroups and given the sparsity of several contingency cells, these findings should be interpreted cautiously as exploratory.
Table 8.
Reported physical activity.
As reported by caregivers, persons living with dementia’s family relationships were mostly positive, though a non-negligible minority reported limited, strained, or absent ties. Friendships were commonly reduced or absent, consistent with social network narrowing as disease advanced (Table 9).
Table 9.
Family and friends ties.
Regarding sources of support, caregivers overwhelmingly emphasized the centrality of family, with almost all respondents indicating that family support was “much” or “very much” available. Confidence in medical assistance was likewise high, as nearly 90% rated the quality of care as very good. Hope, lifestyle, or discipline and attention to diet were also frequently described as meaningful resources in coping with dementia. Religious faith played an important role for many people living with dementia, as reported by caregivers, although the perceived importance of the priest varied considerably across respondents. In contrast, alternative explanatory frameworks such as natural remedies, bioenergy therapies, or practices aimed at breaking spells or curses were endorsed infrequently, appearing to occupy only a marginal place in caregivers’ interpretations and coping strategies (Table 10).
Table 10.
Caregivers’ reported support and beliefs.
At the institutional level, most caregivers acknowledged some form of state support, although this typically referred only to the disability allowance received by patients. Beyond this financial assistance, few caregivers reported accessing additional public services and involvement from NGOs or patient associations was virtually absent. (Table 11).
Table 11.
Perceived institutional support.
According to caregiver reports, 12 patients (16.4%) had a positive family history of dementia, while 53 (72.6%) did not and in 8 (11.0%) cases, the information was missing or unclear. In those with a positive history, the most frequently affected relatives were parents (7 patients, 58.3%), followed by siblings (4, 33.3%). In one case, the affected relative was unspecified.
Disclosure of the dementia diagnosis to patients was reported by most caregivers, although not uniformly. In nearly three-quarters of cases (74%), the diagnosis was explicitly communicated, while about one-quarter (26%) of patients were not informed. Patients’ initial reactions to disclosure varied widely. Some caregivers described emotional shock, sadness, or crying (15.1%), while others reported denial or outright refusal of the diagnosis (16.4%). A substantial proportion reacted with confusion or lack of understanding (13.7%), a response that was perceived as consistent with cognitive decline at the time of disclosure. Acceptance—whether immediate or gradual—was described in 12.3% of cases, while smaller groups displayed indifference or minimization (6.8%) or marked anxiety and worry (8.2%). Almost one-third of accounts (27.4%) fell into mixed or less clearly defined categories, highlighting the heterogeneity and complexity of disclosure responses in this population.
From caregivers’ reports, we found that family members also displayed a spectrum of reactions on disclosure of the diagnosis. The most frequent were worry and concern (27.4%) and anxiety, panic, or sadness (20.5%). Some caregivers reported acceptance and a supportive stance (12.3%), while others described denial or refusal (5.5%) or indifference (2.7%). Notably, nearly one-third (31.5%) of family reactions were mixed, suggesting that adaptation within families was often uneven or fragmented rather than uniform.
When describing patients’ current positioning toward their illness, caregivers reported a similarly diverse landscape. While confusion and lack of understanding were still frequent (19.2%), other patients exhibited persistent sadness and crying (12.3%), indifference (8.2%), or denial/refusal (9.6%). A minority demonstrated partial or gradual acceptance (11.0%) and some combined refusal with partial adherence to treatment (4.1%). A large proportion (35.6%) fell into heterogeneous or mixed categories, reflecting the fluid, fluctuating, and non-linear nature of adjustment as perceived by caregivers.
Taken together, these findings indicate that disclosure and adjustment to dementia diagnosis are highly variable processes that do not follow a linear trajectory, oscillating between acceptance, confusion, denial, and distress, as shaped by the patient’s cognitive state and the family’s interpretive frameworks rather than by a single dominant pattern.
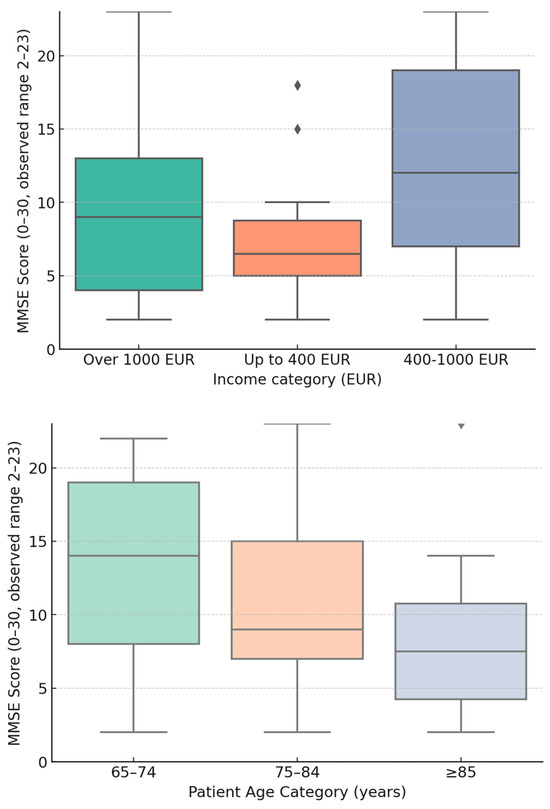
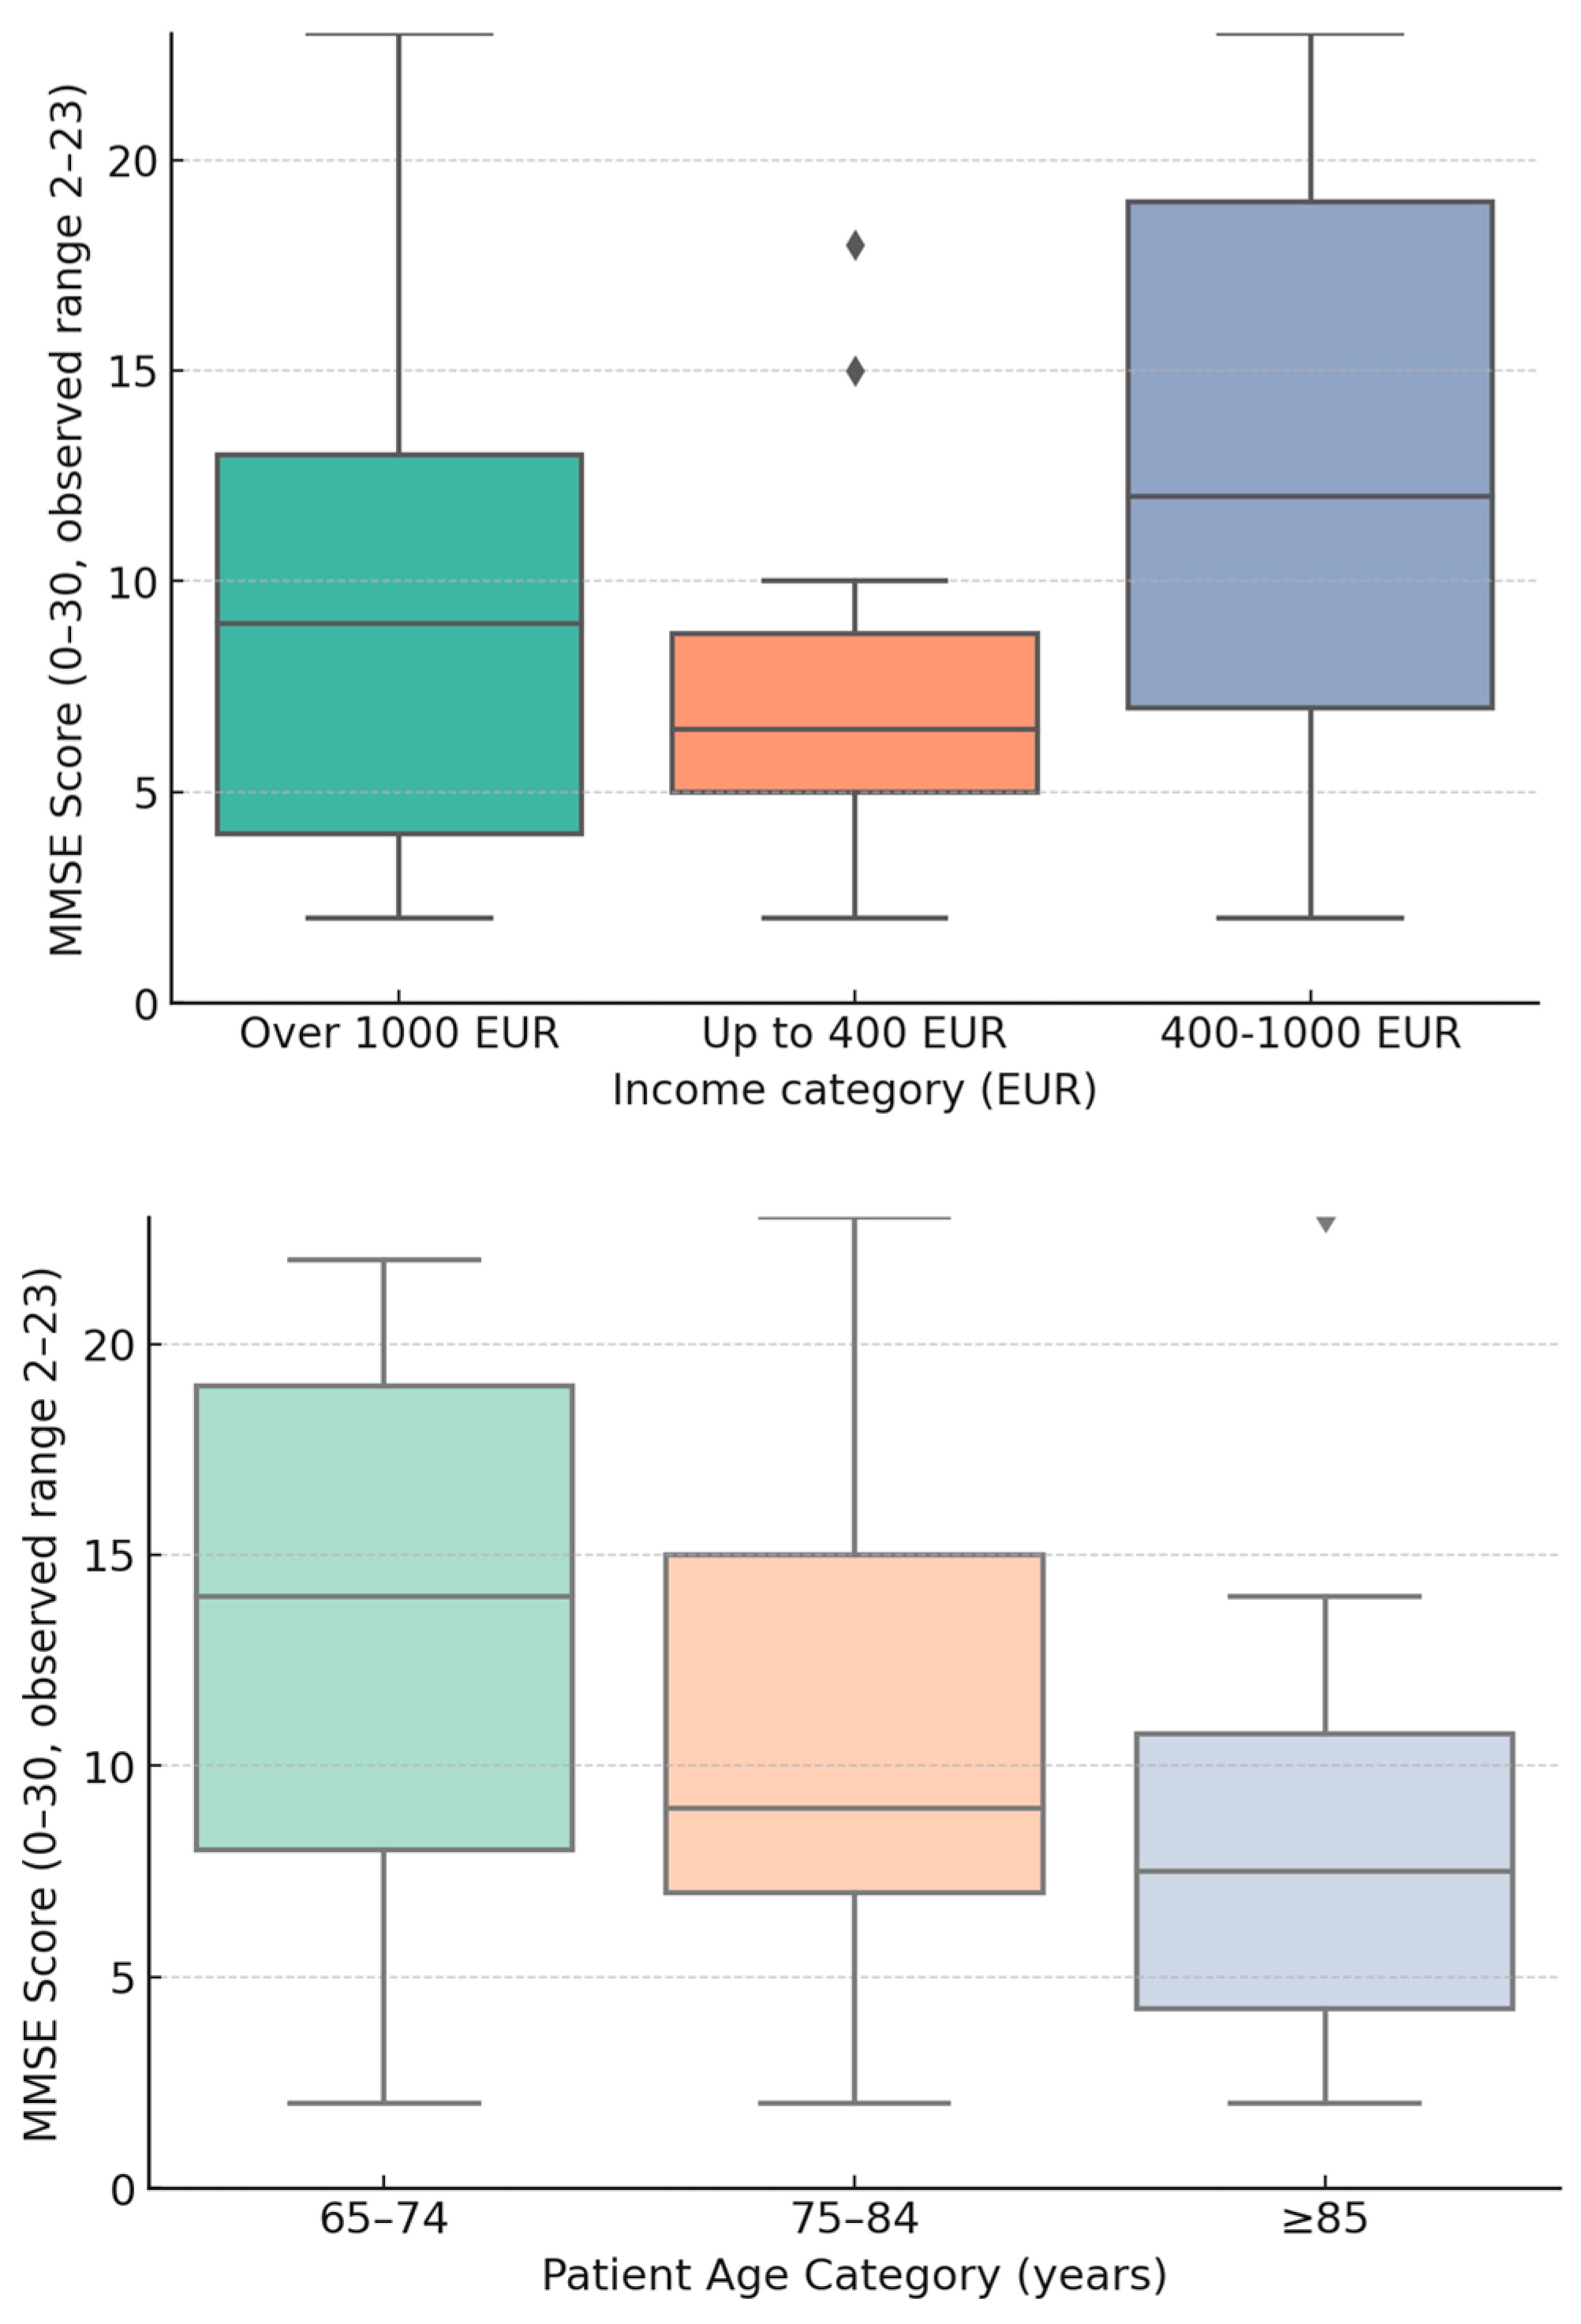
Most people living with dementia fell within the severe impairment category, with only a small minority classified as mildly impaired. Exploratory bivariate analyses showed that MMSE scores tended to decrease with advancing age and appeared descriptively higher among individuals with greater educational attainment and among those from higher income categories (Figure 3), However, these contrasts did not reach statistical significance and were limited by small subgroup sizes.
Figure 3.
MMSE scores and income and age category.
Appetite, sleep, BMI, physical activity and comorbidity count showed no meaningful differences across MMSE categories.
To further evaluate these patterns, a multivariable logistic regression model (mild vs. severe impairment) was examined, including age, education, income, BMI, and multimorbidity. No predictor reached statistical significance and confidence intervals were wide, reflecting the small number of participants in the mild-impairment group. Nonetheless, the largest nonsignificant coefficients indicated directional trends: younger age, higher income, and higher BMI were more frequently observed among individuals in the mild impairment group, whereas greater multimorbidity was more common among those in the severe category. Education did not contribute meaningfully once other variables were included in the model. This multivariable analysis is presented for completeness only and is not intended to support inferential conclusions, given the small sample size and the instability of model estimates.
Taken together, these findings suggest that certain sociodemographic and health-related characteristics display descriptive gradients across levels of cognitive impairment. However, given the small sample size and wide confidence intervals, the dataset does not provide inferential evidence for independent associations. These patterns should therefore be interpreted as exploratory signals rather than confirmatory relationships.
4. Discussion
This caregiver-based study provides an integrated perspective on the clinical, lifestyle and social dimensions of dementia in persons living with dementia, as reported by their informal caregivers. All interpretations should be read as descriptive and hypothesis-generating, given the exploratory design and limited sample size. Given the modest sample and unbalanced categories, multivariable models were underpowered. The nonsignificant and unstable estimates are in line with expectations for exploratory studies of this size. Rather than supporting statistical inference, the findings offer descriptive patterns that help situate dementia within its broader socio-cultural context. Several findings deserve emphasis. The persons living with dementia sample was characterized by advanced age, relatively low educational attainment, and limited financial resources as reported by caregivers. These sociodemographic features are relevant because education and income showed only descriptive—not statistically supported—gradients in MMSE scores. This observation aligns with the concept of cognitive reserve, according to which higher education and better socioeconomic conditions may mitigate the clinical expression of neuropathology [6,16,17]. However, the small number of participants in higher education categories prevents firm conclusions.
Importantly, Romania lacks empirical studies examining cognitive reserve or socioeconomic gradients in dementia, making these exploratory observations particularly valuable for understanding how structural disadvantages may shape dementia trajectories in this context.
The burden of multimorbidity was high, with an average of more than two chronic conditions per patient, dominated by neurologic and cardiovascular diseases. Yet comorbidity count was not significantly related to cognitive status but rather in line with persons living with dementia’s mean age, suggesting that although prevalent, multimorbidity may exert indirect rather than direct effects on cognition, possibly through functional decline and reduced resilience. Similar findings have been reported in population-based cohorts, where somatic burden predicted frailty but not always cognitive performance [5,6]. In Romania, data on multimorbidity patterns in dementia are scarce and most available reports focus narrowly on cardiovascular or metabolic disease rather than on the cumulative burden of chronic conditions. The present study therefore contributes preliminary evidence regarding multimorbidity profiles in community-dwelling persons with dementia.
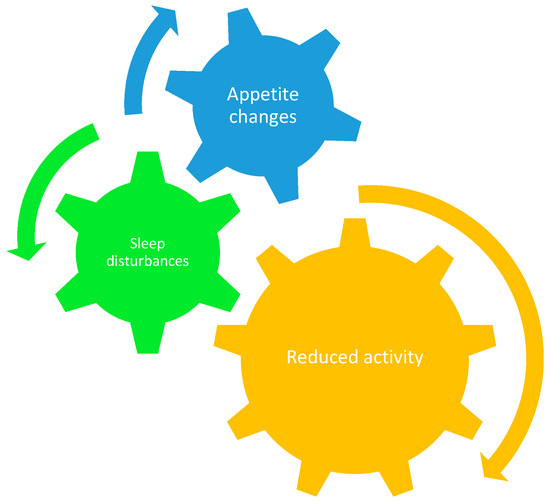
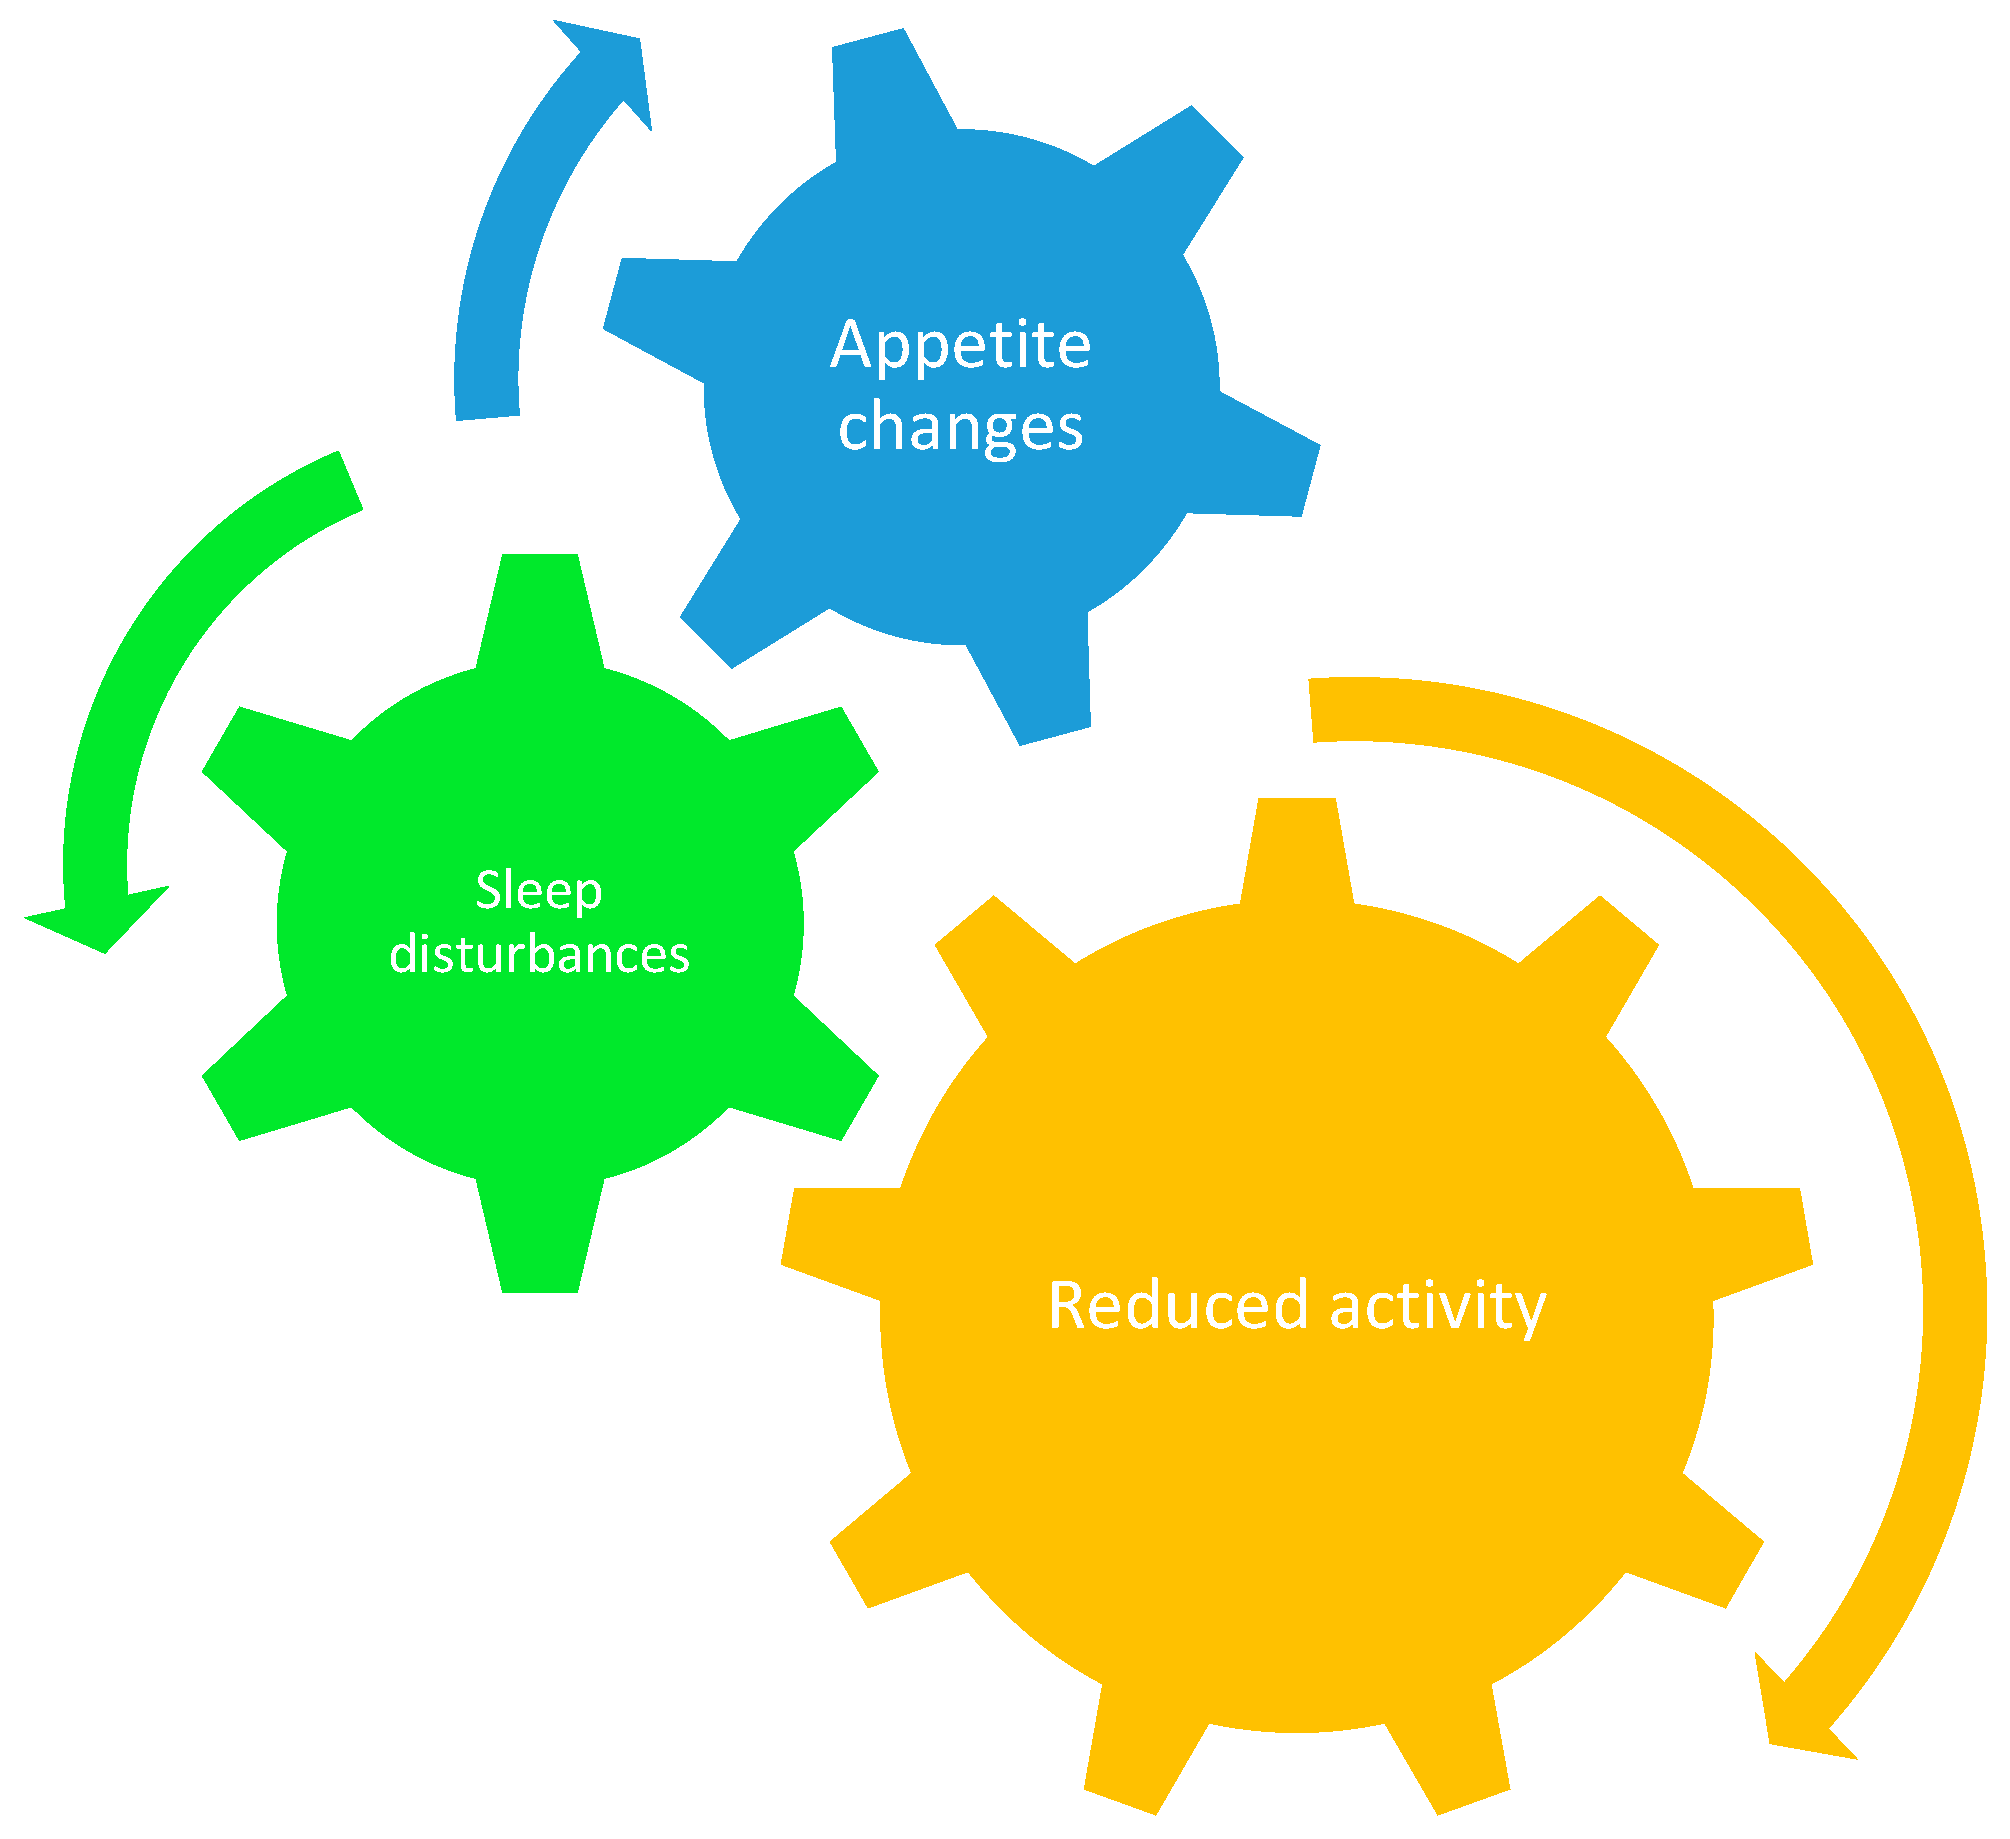
Appetite and sleep disturbances in people living with dementia were commonly reported and strongly interrelated as illustrated in Figure 4. This figure is intended as a conceptual illustration to support interpretation of the descriptive findings. It does not represent additional statistical analysis or imply causal relationships.
Figure 4.
Conceptual illustration of the co-occurrence of appetite changes, sleep disturbance, and reduced activity in people living with dementia, as reported by caregivers.
In this sample, reduced appetite tended to co-occur with poor sleep and low physical activity, suggesting a frailty-like syndrome that extends beyond cognition. Although these behaviors were not related to MMSE categories in this sample, the pattern resonates with previous work emphasizing the clustering of behavioral and nutritional symptoms in dementia [7]. Importantly, large-scale cohort studies demonstrate that sleep disturbances can precede dementia by many years and act as risk factors for neurodegeneration, even independent of genetic predisposition [10,18,19].
Lifestyle behaviors such as smoking and alcohol use were infrequent, reflecting either underreporting or genuine abstinence in a frail elderly sample. Nutritional patterns were dominated by staple foods, with only dairy intake differing significantly by appetite status. These results echo evidence linking dietary variety, appetite, and sleep quality with cognitive decline risk in older adults [16,20]. However, given the cross-sectional design and small cell counts in contingency tables, these findings should be interpreted as descriptive rather than explanatory. Moreover, sleep or frailty-related behavioral constellations in dementia, as well as nutritional research in Romanian dementia populations remains extremely limited, underscoring the need for systematic assessment of diet and eating behaviors in clinical practice.
The social environment emerged as a crucial domain. Family relationships were described as strongly supportive, whereas friendships and broader community ties appeared markedly reduced. Caregivers reported minimal support from governmental or institutional structures and almost no involvement of NGOs, underscoring the limited availability of formal dementia services. This pattern aligns with regional analyses indicating fragmented care pathways and a persistent reliance on informal, family-based care across Central and Eastern Europe. In the Romanian context, where coordinated dementia services, community programs, and long-term support infrastructures are largely absent, informal caregiving becomes the de facto system, amplifying the importance of caregivers’ perceptions and experiences. Religious beliefs and, at times, alternative practices were integrated into coping narratives, reflecting the cultural frameworks through which dementia is interpreted and managed. These meaning-making dimensions, though central to caregiving processes, remain insufficiently examined in Romanian empirical studies.
Finally, diagnostic disclosure generated heterogeneous reactions—ranging from acceptance to denial, sadness, confusion, or indifference—highlighting the diversity of coping mechanisms among patients and families. These findings highlight the relevance of communication strategies that are sensitive to both cultural context and individual cognitive capacity, as well as to caregivers’ expectations and interpretive frameworks.
Overall, this exploratory study suggests that, within this sample of persons living with dementia, differences in cognitive status varied across age and educational backgrounds rather than across somatic comorbidities or lifestyle habits. Rather than pointing to a single explanatory pathway, the findings depict dementia as a condition shaped by intersecting biological, psychosocial, and cultural dimensions. This multidimensional profile reflects not only the clinical manifestations of dementia but also the caregiving environment and the socio-cultural narratives through which illness is understood and managed.
The findings of this study have several practical implications for dementia care. The descriptive gradients observed across age and educational background suggest that interventions aimed at supporting cognitive reserve may remain relevant even in later life. Strategies that promote cognitive stimulation, meaningful engagement and tailored communication—adjusted to individuals’ educational levels—may help maintain residual functioning and enhance day-to-day quality of life.
The high prevalence of appetite and sleep disturbances of persons living with dementia in this sample, as reported by the caregivers, highlights the importance of routinely screening for and managing these symptoms in clinical practice. Addressing sleep hygiene, providing individualized nutritional guidance, and encouraging light but regular physical activity may help mitigate frailty-like features that frequently accompany dementia. These domains represent modifiable aspects of care in which caregiver education and clinical monitoring could play a meaningful role.
From caregivers’ reports, family support emerged as central to care-recipient’s well-being, reflecting both a strength and a structural vulnerability. In the absence of robust formal services, family caregivers shoulder the majority of responsibilities, often without adequate institutional backing. Strengthening community-based resources, expanding the role of NGOs, and ensuring consistent governmental involvement remain critical steps toward a more balanced and sustainable care system. Integrating caregiver perspectives into individualized care planning is equally important, as caregivers possess detailed knowledge of daily routines, behavioral changes, and context-specific needs.
Finally, the heterogeneity of reactions to diagnostic disclosure underscores the necessity of flexible, culturally informed communication strategies. Clinicians should adapt discussions to patients’ cognitive capacities, family dynamics and cultural values, recognizing that acceptance, denial and ambivalence may coexist and evolve over time. Moving beyond a strictly biomedical model toward more holistic, culturally sensitive approaches may improve patient well-being while also alleviating some of the substantial burden carried by caregivers.
5. Conclusions
This exploratory study highlights the multidimensional nature of dementia as perceived and reported by family caregivers, integrating clinical, behavioral, social and cultural components. Cognitive differences appeared primarily along age and educational gradients, whereas behavioral and frailty-related symptoms were widespread across the sample. The findings underscore the central role of family care in a setting with limited formal support and point to the value of addressing nutrition, sleep, activity, and social needs alongside medical management. Strengthening community and institutional resources, together with incorporating caregiver perspectives into individualized care, represents an important direction for improving dementia care in Romania.
6. Limitations and Future Directions
The study offers a valuable caregiver-based dataset that spans clinical, lifestyle, and social dimensions, but several limitations must be considered. The sample size was modest, with underrepresentation of individuals from higher education and higher-income groups, which limits the precision of estimates. Behavioral and socio-cultural information was derived exclusively from caregiver reports and may reflect subjective perceptions. MMSE scores were extracted from medical records rather than collected concurrently, introducing possible temporal mismatch. Finally, the cross-sectional design precludes any inference regarding directionality or causality.
Despite these constraints, the findings point to the importance of multimodal approaches that integrate medical, nutritional, sleep-related, activity-based, and social components into dementia care. Strengthening formal support systems—with greater involvement from state structures and NGOs—remains relevant in settings where caregiving relies heavily on families. In clinical practice, incorporating caregiver perspectives into individualized care planning may improve the alignment between patient needs and available resources.
Author Contributions
Conceptualization: C.S.G., L.F.T. and S.T.; formal analysis, C.S.G., L.F.T. and S.T.; investigation, L.F.T.; methodology, C.S.G., L.F.T. and S.T.; software, C.S.G., L.F.T. and S.T.; supervision, C.S.G., L.F.T. and S.T.; validation C.S.G., L.F.T. and S.T.; writing—original draft, C.S.G., L.F.T. and S.T.; writing—review and editing, C.S.G., L.F.T. and S.T. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was conducted in accordance with the Declaration of Helsinki and approved by the Ethics Committee of C.F.2 Clinical Hospital (Ref. Number: 1781; and the approval date is 6 February 2023).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Data are available upon reasonable request due to privacy and ethics regulations.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Brodaty, H.; Donkin, M. Family Caregivers of People with Dementia. Dialogues Clin. Neurosci. 2009, 11, 217–228. [Google Scholar] [CrossRef] [Scilit]
- Livingston, G.; Huntley, J.; Sommerlad, A.; Ames, D.; Ballard, C.; Banerjee, S.; Brayne, C.; Burns, A.; Cohen-Mansfield, J.; Cooper, C.; et al. Dementia Prevention, Intervention, and Care: 2020 Report of the Lancet Commission. Lancet 2020, 396, 413–446. [Google Scholar] [CrossRef] [Scilit]
- Bouhrara, M.; Reiter, D.A.; Bergeron, C.M.; Zukley, L.M.; Ferrucci, L.; Resnick, S.M.; Spencer, R.G. Evidence of Demyelination in Mild Cognitive Impairment and Dementia Using a Direct and Specific Magnetic Resonance Imaging Measure of Myelin Content. Alzheimer’s Dement. 2018, 14, 998–1004. [Google Scholar] [CrossRef] [Scilit]
- Kim, H. Effects of Self-Efficacy, Self-Esteem, and Disability Acceptance on the Social Participation of People with Physical Disabilities: Focusing on COVID-19 Pandemic. Brain Behav. 2023, 13, e2824. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; Lu, G.; Liu, L.; He, Y.; Gong, W. Cognitive Reserve over the Life Course and Risk of Dementia: A Systematic Review and Meta-Analysis. Front. Aging Neurosci. 2024, 16, 1358992. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roe, C.M.; Mintun, M.A.; D’Angelo, G.; Xiong, C.; Grant, E.A.; Morris, J.C. Alzheimer Disease and Cognitive Reserve: Variation of Education Effect With Carbon 11–Labeled Pittsburgh Compound B Uptake. Arch. Neurol. 2008, 65, 1467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fostinelli, S.; De Amicis, R.; Leone, A.; Giustizieri, V.; Binetti, G.; Bertoli, S.; Battezzati, A.; Cappa, S.F. Eating Behavior in Aging and Dementia: The Need for a Comprehensive Assessment. Front. Nutr. 2020, 7, 604488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scheufele, P.; Rappl, A.; Visser, M.; Kiesswetter, E.; Volkert, D. Characterisation of Community-Dwelling Older Adults with Poor Appetite. Eur. J. Nutr. 2023, 62, 1991–2000. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schreiner, A.S.; Yamamoto, E.; Shiotani, H. Positive Affect among Nursing Home Residents with Alzheimer’s Dementia: The Effect of Recreational Activity. Aging Ment. Health 2005, 9, 129–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simmonds, E.; Levine, K.S.; Han, J.; Iwaki, H.; Koretsky, M.J.; Kuznetsov, N.; Faghri, F.; Solsberg, C.W.; Schuh, A.; Jones, L.; et al. Sleep Disturbances as Risk Factors for Neurodegeneration Later in Life. npj Dement. 2025, 1, 6. [Google Scholar] [CrossRef] [Scilit]
- Britt, K.C.; Richards, K.C.; Hamilton, J.; Radhakrishnan, K. Symptoms of Dementia Progression in Cognitive Impairment: The Role of Religious and Spiritual Activity. J. Spiritual. Ment. Health 2025, 27, 309–328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Britt, K.C.; Kwak, J.; Acton, G.; Richards, K.C.; Hamilton, J.; Radhakrishnan, K. Measures of Religion and Spirituality in Dementia: An Integrative Review. AD Transl. Res. Clin. Interv. 2022, 8, e12352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGee, J.S.; Davie, M.; Meraz, R.; Myers, D.; Boddie, S.C. Does the Tough Stuff Make Us Stronger? Spiritual Coping in Family Caregivers of Persons with Early-Stage Dementia. Religions 2022, 13, 756. [Google Scholar] [CrossRef] [Scilit]
- Sfetcu, R.; Toma, D.; Tudose, C.; Vladescu, C. Romanian GPs Involvement in Caring for the Mental Health Problems of the Elderly Population: A Cross-Sectional Study. Front. Neurol. 2021, 12, 641217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmachtenberg, T.; Monsees, J.; Thyrian, J.R. Structures for the Care of People with Dementia: A European Comparison. BMC Health Serv. Res. 2022, 22, 1372. [Google Scholar] [CrossRef] [Scilit]
- Wilson, R.S.; Yu, L.; Lamar, M.; Schneider, J.A.; Boyle, P.A.; Bennett, D.A. Education and Cognitive Reserve in Old Age. Neurology 2019, 92, e1041–e1050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, Y.; Stern, Y.; Seo, S.W.; Na, D.L.; Jang, J.; Jang, H. Cognitive Reserve Research Group of Korea Dementia Association Factors Associated with Cognitive Reserve According to Education Level. Alzheimer’s Dement. 2024, 20, 7686–7697. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levy, B.; Priest, A.; Delaney, T.; Hogan, J.; Herrawi, F. Toward Pre-Diagnostic Detection of Dementia in Primary Care. JAD 2022, 86, 479–490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, H.; Wang, X.; Shi, Y. The Effect of Hearing Impairment and Social Participation on Depressive Symptoms in Older Adults: A Cross-Lagged Analysis. Front. Comput. Neurosci. 2023, 17, 1240587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamamoto, K.; Motokawa, K.; Yoshizaki, T.; Yano, T.; Hirano, H.; Ohara, Y.; Shirobe, M.; Inagaki, H.; Awata, S.; Shinkai, S.; et al. Association of Dietary Variety and Appetite with Sleep Quality in Urban-Dwelling Older Japanese Adults. J. Nutr. Health Aging 2020, 24, 152–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.