


Abstract
Background: Variability in procedural exposure among internal medicine junior doctors may result in inconsistent preparedness for essential bedside procedures. Simulation-based education grounded in mastery learning has been proposed to standardise skill acquisition, but less is known about how such training is integrated into clinical practice. Methods: We conducted a theory-informed mixed-methods evaluation of a mastery-oriented procedural simulation workshop. The quantitative component used pre–post assessments, including a multiple-choice knowledge test and self-reported measures of perceived knowledge, skill, and confidence using a 5-point Likert scale. Participants were required to achieve predefined competency benchmarks based on ACGME-aligned procedural checklists. The qualitative component, conducted two years later, involved semi-structured interviews exploring how participants integrated workshop learning into clinical practice. Results: Thirty-eight participants completed paired pre–post assessments. Knowledge scores and self-reported perceived knowledge, skill, and confidence improved significantly across all procedures (p < 0.01), with large effect sizes. Ten participants participated in follow-up interviews. Thematic analysis identified four themes: (1) standardization of procedural practice, (2) activation of prior knowledge, (3) hands-on experience and skill development, and (4) relevance to clinical practice. Conclusions: A mastery-oriented simulation workshop was associated with improvements in knowledge and perceived procedural readiness. Structured simulation may influence how junior doctors approach procedural learning in clinical practice.
1. Introduction
Bedside procedural skills, such as lumbar puncture and knee aspiration, are a core component of internal medicine training and are essential for ensuring quality patient care and clinical competence among junior doctors [1]. However, opportunities for hands-on procedural experience during clinical rotations are often variable and influenced by service demands. As a result, junior doctors may complete training with inconsistent exposure to, and confidence in, performing essential bedside procedures. To address these gaps, simulation-based education has been widely adopted to supplement clinical learning [2], offering a safe and structured environment in which junior doctors can acquire procedural skills and technical proficiency without risk to patients [3,4]. Importantly, the effectiveness of simulation-based education depends not only on the use of simulation itself, but also on how training is structured and implemented.
In the United Kingdom, junior doctors are defined as qualified medical graduates in clinical training with up to nine years of hospital experience [5]. In our context, junior doctors include medical officers, resident physicians, and registrars who have completed internship but are not yet enrolled in specialty or residency training, typically from postgraduate year (PGY) two onwards.
Formal procedural training has been associated with improvements in procedural performance, confidence, and patient safety [6,7]. Conversely, limited procedural exposure and lack of refresher training may erode competence and confidence, potentially affecting clinical performance and patient safety [8,9]. Procedural confidence is therefore a key determinant of a junior doctor’s willingness to perform procedures, seek supervision, and maintain ongoing competence [10].
Traditional apprenticeship models often emphasise exposure over structured, reflective learning, highlighting the need for more intentional educational approaches. Simulation-based education addresses these limitations by providing standardised exposure, protected practice environments, and structured feedback [11,12,13]. Within this framework, mastery learning has gained increasing attention, emphasising clearly defined performance standards, deliberate practice with feedback, and progression toward predefined competency benchmarks [14]. Such approaches have been shown to reduce variability in skill acquisition and improve short-term performance outcomes [15].
In Singapore, postgraduate internal medicine training occurs in a high-acuity setting with variable procedural exposure, highlighting the role of simulation-based mastery learning in standardising training and supporting safe skill development. Despite the widespread use of simulation-based procedural training, less is known about how mastery-oriented approaches influence perceived procedural readiness and longer-term integration into clinical practice [16].
This study therefore evaluated a mastery-oriented procedural simulation workshop for internal medicine junior doctors using a mixed-methods approach, examining (1) immediate changes in procedural knowledge and self-reported readiness, and (2) how participants subsequently integrated these learning experiences into clinical practice two years after the training.
2. Materials and Methods
2.1. Educational Programme Design and Implementation
The procedural skills programme was designed using Kolb’s Experiential Learning Cycle [17] integrated with a flipped classroom model to strengthen engagement and deepen learning. The design followed four iterative stages: abstract conceptualization, concrete experience, reflective observation, and active experimentation, which guided the sequence of pre-course preparation, a two-day face-to-face simulation workshop, and post-course follow-up [18,19,20]. Table 1 summarises how each phase of the course aligned with the stages of the experiential learning cycle.
Table 1.
Alignment of Course Phases with Kolb’s Experiential Learning Cycle.
The course covered seven essential internal medicine procedures considered critical for safe and competent clinical practice: lumbar puncture, thoracocentesis, abdominal paracentesis, central venous catheter insertion, femoral line insertion, chest drain insertion, and knee aspiration. These were selected based on institutional needs and national postgraduate training needs to ensure alignment with core competency frameworks [21,22].
Training incorporated principles consistent with simulation-based deliberate practice and mastery learning [14,23]. Participants practiced each procedure repeatedly under supervision until predefined competency benchmarks were achieved. Competency benchmarks were defined using standardized procedural checklists aligned with Accreditation Council for Graduate Medical Education (ACGME) guidelines, with a minimum passing standard required for each procedure. Participants who did not initially meet the expected level were provided with additional supervised practice and feedback until satisfactory performance was achieved within the workshop [24]. Feedback was delivered in a structured manner by trained faculty using checklist-based assessment and guided debriefing to support skill refinement and progression.
2.2. Study Design
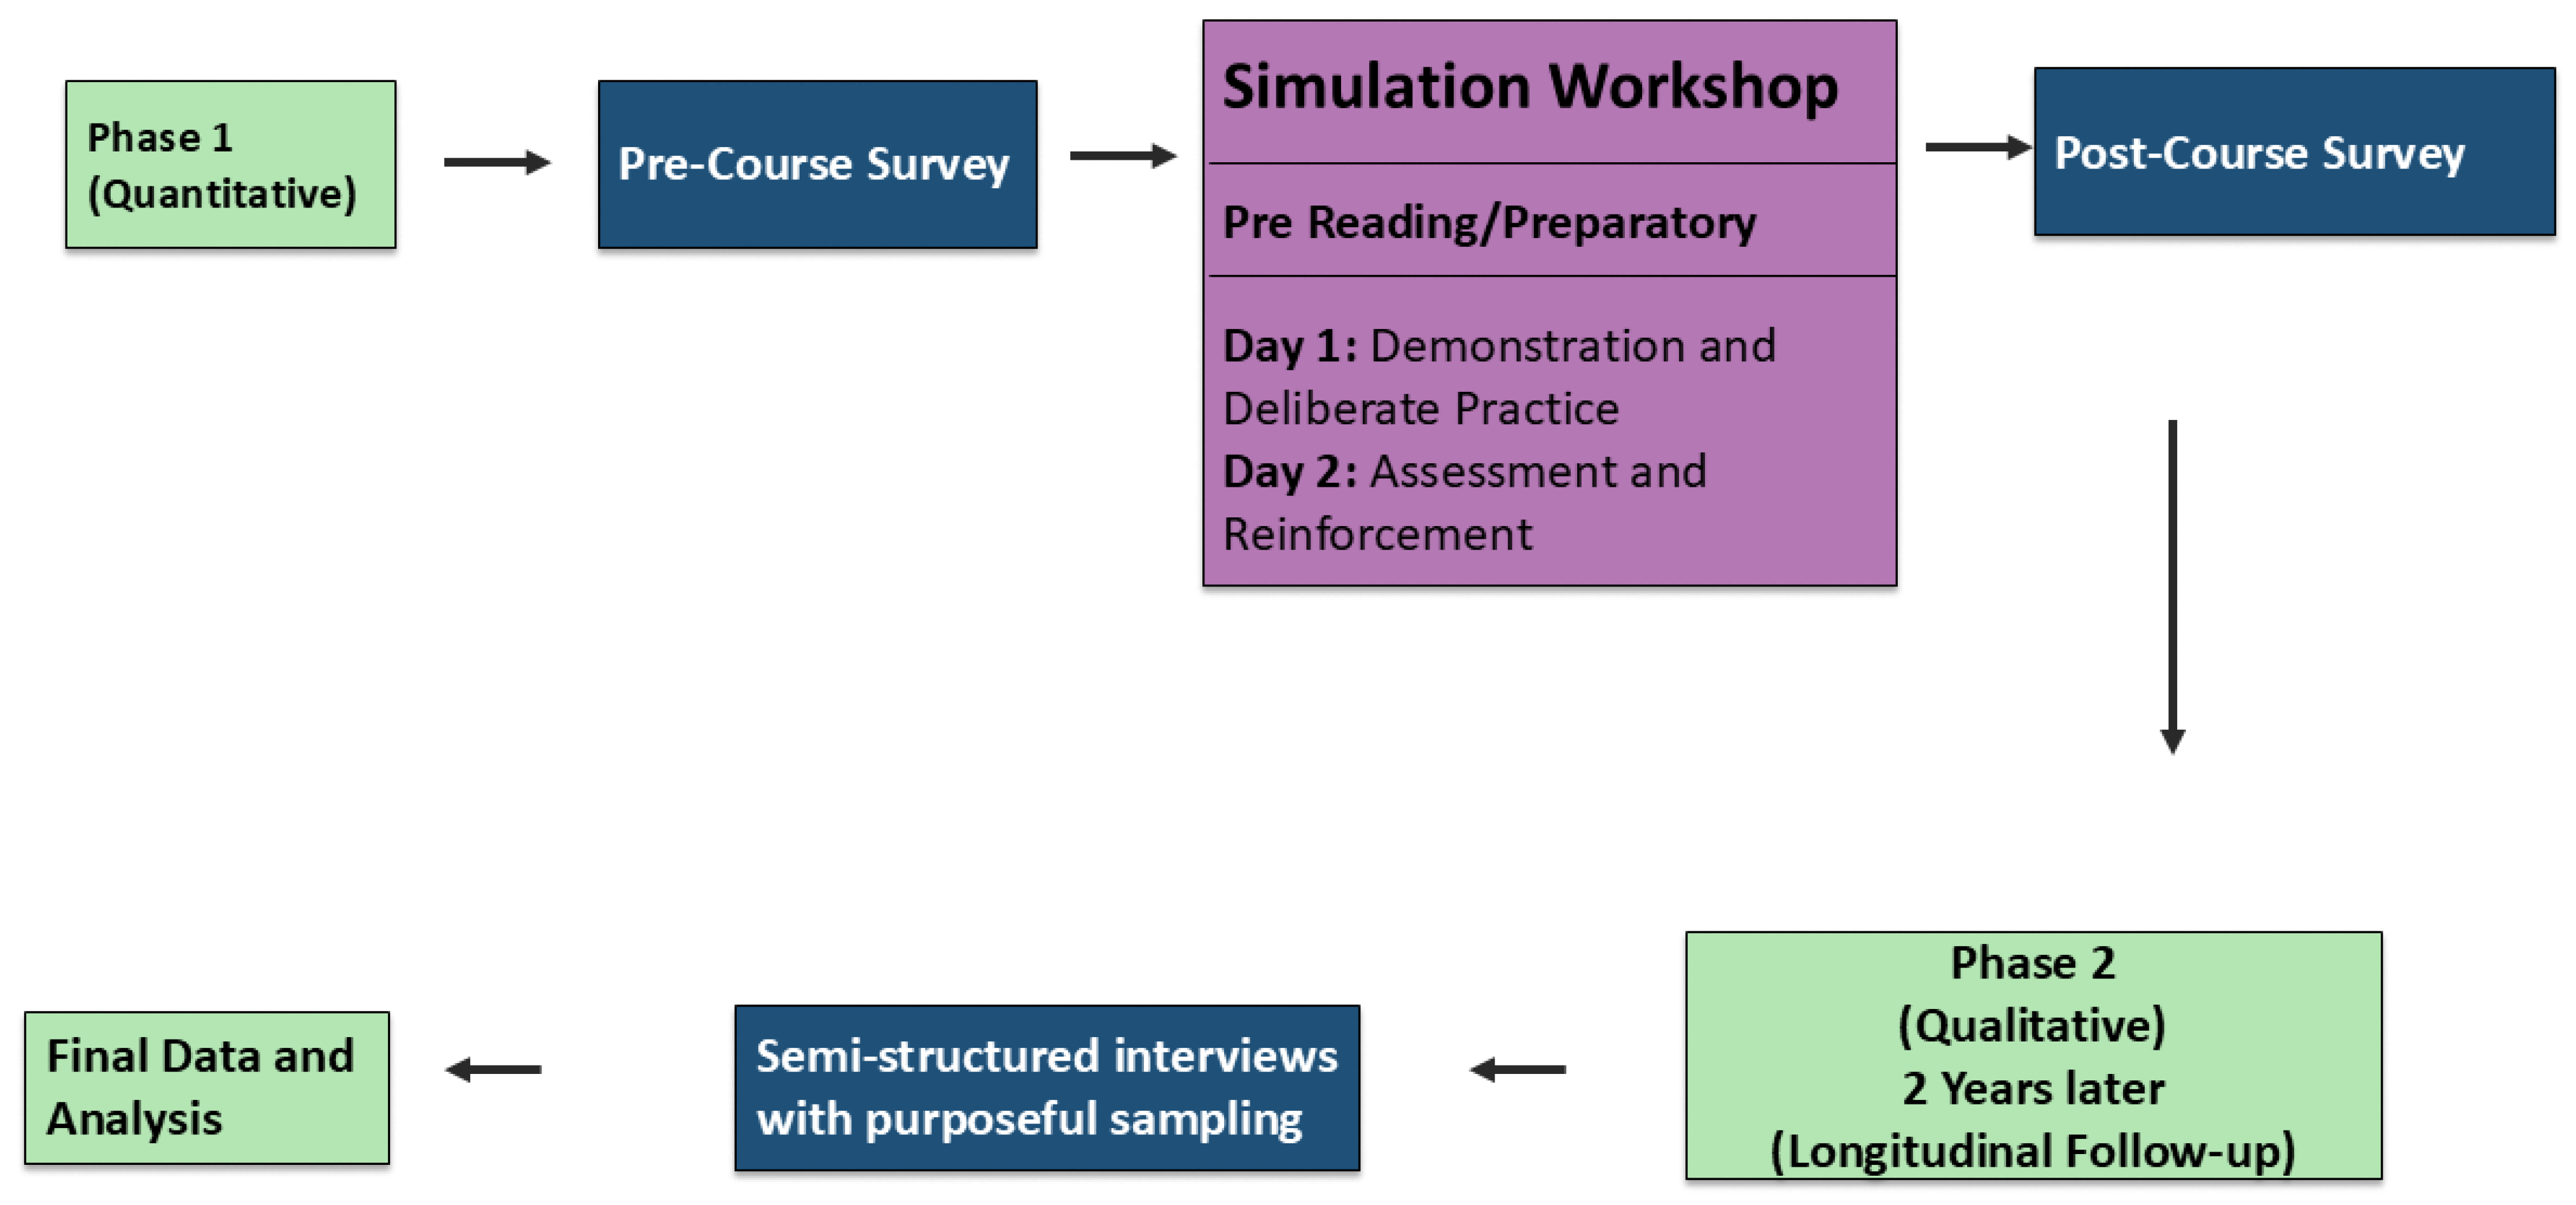
We conducted a theory-informed mixed-methods evaluation of a mastery-oriented procedural simulation workshop. The quantitative component employed a pre–post design to assess immediate changes in knowledge and self-reported procedural readiness following the workshop. The qualitative component, conducted two years later, explored how participants reflected on the training and its influence on subsequent clinical practice. Figure 1 illustrates the study process and integration points.
Figure 1.
The mixed-methods evaluation design.
2.3. Setting, Participants and Faculty
Participants were junior doctors (postgraduate year 2 or above) rotating through the Department of General Medicine at a tertiary teaching hospital in Singapore. Attendance formed part of structured postgraduate training within the department.
Ten faculty members consisted of credentialed consultant physicians with formal training in simulation-based education. Instruction and assessment were standardized using a faculty handbook, ensuring consistency of teaching approach, feedback processes, and procedural assessment. Participation was voluntary, data were anonymized, and study participation did not influence training evaluations or professional standing.
2.4. Quantitative Measures
Participants completed pre- and post-course assessments evaluating knowledge and perceived procedural readiness.
Knowledge was assessed using a 20-item multiple-choice questionnaire covering procedural indications, contraindications, anatomical landmarks, procedural steps, and complication management [Supplementary File S1]. Scores were recorded as the total number of correct responses. Perceived procedural knowledge, skill, and confidence were assessed using a 5-point Likert scale (1 = very low, 5 = very high) for each of the seven procedures. [Supplementary File S2].
The knowledge test and self-assessment questionnaires were developed by the study team based on existing procedural curricula and published simulation evaluation tools and were reviewed by content experts for face validity prior to implementation. Additional programme evaluation instruments included a programme feedback form [Supplementary File S3], and standardized procedural checklists adapted from the ACGME guidelines [Supplementary File S4] used during training to assess skill performance.
2.5. Qualitative Data Collection
Two years after the workshop, semi-structured interviews were conducted to explore participants’ reflections on how the training influenced their subsequent clinical practice and professional development. Participants were invited via email to participate in follow-up semi-structured interviews, and volunteers were purposively sampled to capture variation in clinical exposure.
The interview guide [Supplementary File S5] explored participants’ early procedural experiences following the workshop, perceived preparedness in supervised clinical settings, the role of feedback and repetitive practice during training, and how simulation learning was integrated into real patient care.
Interviews were conducted online, audio-recorded, and transcribed using Otter.ai. Transcripts were verified by investigators (DLWC and MCAZ) and reviewed by participants to ensure accuracy.
2.6. Data Analysis
2.6.1. Quantitative Analysis
No prior sample size or power calculation was performed as the study evaluated an existing educational programme and included all eligible participants during the study period; the sample size was therefore pragmatic.
Pre- and post-training scores were compared using a paired-samples t-test, reflecting the primary aim of assessing within-participant change following the intervention. The paired t-test was selected because the scores approximated a continuous distribution and the data were paired.
Missing data were handled using complete-case analysis, with only participants who completed both pre- and post-course assessments included in the final analysis. No imputation was performed.
Statistical significance was set at p < 0.05. In addition to statistical significance, effect sizes were calculated using Cohen’s d for paired comparisons, based on pooled pre- and post-intervention standard deviations. Conventional thresholds were applied (0.2 = small, 0.5 = moderate, 0.8 = large, 1.2 = very large). Analyses were conducted using Microsoft Excel 2020.
2.6.2. Qualitative Analysis
Interview transcripts were analyzed using thematic analysis supported by Atlas.ti 24. Three investigators (DLWC, OCY, MCAZ) independently coded transcripts before collaboratively refining the codebook through iterative discussion. Codes were grouped into themes representing shared experiences and reflections on procedural learning and clinical integration. Thematic saturation was achieved, indicating that no new themes emerged from additional interviews.
3. Results
Between January 2018 and June 2019, 86 doctors attended the procedural skills course. Thirty-eight participants (44.2%) completed both the pre- and post-course surveys and were included in the quantitative analysis, and 10 subsequently participated in the qualitative interviews conducted two years later. Participants were predominantly medical officers with early postgraduate clinical experience, and most had prior exposure to medical postings requiring procedural skills. Detailed participant characteristics are shown in Table 2. The interview sample included junior doctors across postgraduate years 2–5, varied range of internal medicine rotations with varying levels of procedural exposure.
Table 2.
Demographics of participants who completed the pre- and post-course survey (N = 38).
3.1. Quantitative Outcomes
Significant increases were observed in participants’ knowledge, perceived procedural skill, and confidence across all seven procedural skills taught in the course (p < 0.01 for all comparisons) (Table 3a–c).
Table 3.
(a) Changes in knowledge scores before and after the workshop. (b) Perceived skills domain changes before and after the course. (c) Confidence domain changes before and after the course.
Large effect sizes were observed across all procedures, particularly for central venous and femoral catheterisation suggesting meaningful changes between pre- and post-course assessments.
3.2. Qualitative Findings
Four interrelated themes were identified that described participants’ experiences of the procedural skills workshop and their perceptions of how the training related to subsequent clinical practice. These themes were: (1) standardization of procedural practice, (2) activation of prior knowledge, (3) hands-on experience and skill development, and (4) relevance to clinical practice.
While the quantitative findings demonstrated significant improvements in knowledge, perceived procedural skill, and confidence immediately following the workshop, the qualitative findings provided complementary insight into how participants experienced the training and perceived its influence on their procedural readiness in clinical practice. Collectively, the themes reflect principles of experiential learning and deliberate practice as operationalised within a mastery-oriented simulation framework. Participants described how structured preparation, supervised hands-on practice, and repeated performance with feedback supported progression from conceptual understanding to supervised performance and application in clinical settings. A summary of themes, analytic descriptions, and illustrative quotations is presented in Table 4.
Table 4.
Summary of Qualitative Themes, Descriptions, and Illustrative Quotations.
4. Discussion
This study evaluated a simulation-based procedural skills workshop grounded in mastery learning and experiential learning principles. Quantitative findings demonstrated significant improvements in knowledge, perceived procedural skill, and confidence across all seven procedures following the workshop, while qualitative findings provided insight into how participants experienced the training and perceived its relevance to clinical practice. Taken together, these findings suggest that a structured simulation curriculum may support procedural capability among junior doctors by providing standardised opportunities for deliberate practice, feedback, and supervised performance.
Mastery learning emphasises progression toward predefined competency standards through repeated practice and structured feedback until a minimum level of proficiency is achieved [14]. In this study, participants practised each procedure using standardised checklists aligned with competency benchmarks, and the observed improvements in perceived skill and confidence are consistent with prior literature demonstrating that mastery-oriented simulation training can support procedural skill development beyond opportunistic bedside learning [14,15]. By shifting procedural training from variable clinical exposure to a structured practice environment, mastery learning approaches may help ensure a baseline level of procedural readiness before trainees perform procedures on patients. However, the time-limited nature of the workshop constrained full implementation of iterative remediation and individualised progression characteristic of comprehensive mastery learning models. Procedural competence therefore remains an ongoing developmental process shaped by workplace experience.
The quantitative findings further suggest that structured simulation may be particularly valuable for procedures with lower baseline confidence or familiarity. Larger gains in perceived skill and confidence were observed for femoral and central venous catheterisation, likely reflecting the benefits of repeated practice and feedback in a controlled environment. In contrast, smaller gains in knowledge may reflect higher baseline familiarity with theoretical concepts acquired through prior clinical exposure or didactic learning. These patterns support existing evidence that simulation may complement clinical experience by strengthening procedural understanding and perceived readiness for performance [3,4].
The qualitative findings illuminate how participants experienced the workshop as supporting their learning. Participants described the programme as providing a structured and standardised approach to procedural training that helped align procedural techniques and expectations across trainees from diverse educational backgrounds. This perceived standardisation may be particularly valuable in clinical environments where procedural exposure varies across rotations or institutions, and simulation-based mastery learning may therefore promote more equitable access to procedural skill development [12,13].
Participants also described the workshop as activating and reinforcing prior knowledge. Less experienced trainees viewed the training as a structured introduction to procedures previously encountered primarily through observation, while more experienced participants perceived it as an opportunity to refresh procedural steps and refine technique. These experiences are consistent with experiential learning theory, which conceptualises learning as an iterative cycle involving experience, reflection, conceptualisation, and application [17]. The integration of preparatory materials, supervised hands-on practice, and structured feedback reflects this learning cycle and incorporates deliberate practice principles supporting targeted skill refinement [23].
Hands-on simulation practice emerged as a central component of the learning experience. Participants valued opportunities for repeated practice with supervision and feedback, consistent with deliberate practice approaches aimed at improving performance and reducing error [23]. At the same time, some participants described challenges in transferring simulated experience to real patients due to differences in anatomy and clinical context. This reinforces the role of simulation as a preparatory learning environment rather than a replacement for supervised clinical experience. Continued workplace practice and supervision remain essential for consolidating procedural skills in real patient-care settings [25,26].
Another key finding was the perceived relevance of the workshop to everyday clinical work. Participants described approaching procedures more systematically, with greater awareness of procedural steps and potential complications. However, opportunities to perform procedures following the workshop varied across clinical postings, reflecting a persistent challenge in procedural education whereby access to practice is dependent on clinical context and service demands. Simulation-based mastery learning may therefore help ensure baseline exposure to core procedural skills even when clinical opportunities are uneven [27,28].
Although simulation-based procedural training is widely used in medical education, prior studies suggest that its effectiveness depends on instructional design features such as structured feedback, deliberate practice, and competency benchmarks [2,14]. While simulation-based mastery learning has been associated with improved procedural performance, evidence linking simulation training to long-term clinical outcomes remains limited, and improvements in simulated performance do not always translate directly into measurable patient outcomes [29]. This study contributes to the literature by providing insight into how trainees experience mastery-oriented procedural training and how they perceive its influence on subsequent clinical practice.
Several limitations should be considered. The modest survey completion rate raises the possibility of non-response bias, as respondents may have differed systematically from non-respondents in motivation or engagement; baseline demographic data for non-respondents were not available to assess this formally. Procedural skills were assessed using self-reported measures rather than objective assessments, which may introduce response bias, although perceived confidence and skill are meaningful indicators of readiness and were contextualised through qualitative findings. The pre–post design without a control group reflects the pragmatic implementation of a mandatory departmental programme, where randomisation was not feasible. Qualitative interviews were retrospective and involved self-selected participants, introducing potential recall and positivity bias. Future studies could incorporate objective assessments, larger and more representative samples, and longitudinal designs to better examine skill retention and clinical transfer.
These findings have implications for postgraduate procedural training. Structured simulation programmes grounded in mastery learning may help address variability in procedural exposure by providing standardised opportunities for deliberate practice and feedback. Integrating experiential learning elements such as preparation, supervised hands-on practice, and reflection may further support deeper learning and reinforce prior knowledge. While simulation cannot replace clinical experience, it may complement workplace learning by preparing trainees for supervised procedural performance. Procedural curricula may therefore benefit from combining mastery-oriented simulation training with structured opportunities for supervised workplace practice.
5. Conclusions
This study suggests that mastery-oriented simulation training may support the development of procedural knowledge, perceived skill, and confidence among junior doctors through structured opportunities for deliberate practice and feedback. Such programmes may help standardise procedural readiness training while complementing, rather than replacing, supervised clinical experience.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ime5020041/s1, Supplementary Files S1–S5.
Author Contributions
Conceptualization, D.W.C.L.; methodology, D.W.C.L., C.D. and C.Y.O.; software, D.W.C.L.; validation, D.W.C.L. and M.C.A.Z.; formal analysis, D.W.C.L., M.C.A.Z. and C.Y.O.; investigation, D.W.C.L., M.C.A.Z. and C.Y.O.; resources, D.W.C.L., C.D. and M.C.A.Z.; data curation, D.W.C.L. and C.Y.O.; writing—original draft preparation, D.W.C.L.; writing—review and editing, D.W.C.L., C.D., M.C.A.Z. and C.Y.O.; supervision, D.W.C.L. and C.D.; project administration, D.W.C.L. and C.D.; funding acquisition, D.W.C.L. and C.D. All authors have read and agreed to the published version of the manuscript.
Funding
The study was funded by the SingHealth Foundation (Grant number SHF(F)/17/GMC-4C/042E).
Institutional Review Board Statement
Ethical approval was granted by the SingHealth Centralised Institutional Review Board (CRIB) (IRB No. 2020/2382).
Informed Consent Statement
Survey participants received an electronic study information page, and completion of the questionnaire constituted implied informed consent. Written informed consent was obtained for qualitative interviews, including permission for audio recording and use of anonymized quotations. Participation in the study did not affect training evaluation or professional standing.
Data Availability Statement
Anonymized research data will be made available upon request.
Acknowledgments
The authors thank Sengkang General Hospital and the workshop participants for their participation in this study. We also acknowledge the leadership and instructors of the Department of General Medicine and the simulation laboratory personnel for their support in delivering the program. We acknowledge the use of OpenAI’s ChatGPT Version 4 for language refinement. The tools were employed to improve clarity and coherence, but they did not generate original research content, analysis, or conclusions. The authors have reviewed and edited the output and take full responsibility and accuracy for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| PGY | Postgraduate Year |
| CI | Confidence Interval |
References
- Shafei, R. Better Training, Better Care: Medical Procedures Training Initiative. BMJ Qual. Improv. Rep. 2014, 2, 2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Issenberg, S.B.; McGaghie, W.C.; Hart, I.R.; Mayer, J.W.; Felner, J.M.; Petrusa, E.R.; Waugh, R.A.; Brown, D.D.; Safford, R.R.; Gessner, I.H.; et al. Simulation technology for health care professional skills training and assessment. JAMA 1999, 282, 861–866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brydges, R.; Hatala, R.; Zendejas, B.; Erwin, P.J.; Cook, D.A. Linking simulation-based educational assessments and patient-related outcomes: A systematic review and meta-analysis. Acad. Med. 2015, 90, 246–256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zendejas, B.; Brydges, R.; Wang, A.T.; Cook, D.A. Patient outcomes in simulation-based medical education: A systematic review. J. Gen. Intern. Med. 2013, 28, 1078–1089. [Google Scholar] [CrossRef] [Scilit]
- Looi, M. What do different countries call junior doctors? BMJ 2023, 382, 2130. [Google Scholar] [CrossRef] [Scilit]
- Ayub, S.M. “See one, do one, teach one”: Balancing patient care and surgical training in an emergency trauma department. J. Glob. Health 2022, 12, 03051. [Google Scholar] [CrossRef] [Scilit]
- Wayne, D.B.; Didwania, A.; Feinglass, J.; Fudala, M.J.; Barsuk, J.H.; McGaghie, W.C. Simulation-based education improves quality of care during cardiac arrest team responses at an academic teaching hospital. Chest 2008, 133, 56–61. [Google Scholar] [CrossRef] [Scilit]
- Clyne, B.; Barber Doucet, H.; Brown, L.; Musits, A.; Jacobs, E.; Merritt, C.; Lee, A.; Wilson, M.; Taylor, S.; Garcia, R.; et al. Maintaining procedural skills for academic emergency medicine faculty: A needs assessment. AEM Educ. Train. 2021, 5, e10648. [Google Scholar] [CrossRef] [Scilit]
- Yu, J.H.; Park, S.Y.; Kim, M.J.; Lee, S.H.; Choi, J.H.; Park, J.H.; Jung, S.Y.; Lee, J.Y.; Kim, S.H.; Nam, S.W.; et al. Effects of high-fidelity simulation education on medical students’ anxiety and confidence. PLoS ONE 2021, 16, e0251078. [Google Scholar] [CrossRef] [Scilit]
- Tan, I.J.L.; Ganapathy, S. Procedural skill maintenance: What it means to physicians. Asia Pac. Sch. 2024, 9, 22–31. [Google Scholar] [CrossRef] [Scilit]
- Elendu, C.; Amaechi, D.C.; Okatta, A.U.; Nwosu, C.I.; Okafor, U.M.; Nwankwo, C.E.; Uche, C.O.; Eze, C.N.; Okonkwo, I.C.; Nwobi, C.O.; et al. The impact of simulation-based training in medical education: A review. Medicine 2024, 103, e38813. [Google Scholar] [CrossRef] [Scilit]
- Kodikara, K.; Perera, S.; Jayasuriya, M.; Fernando, L.; Ratnayake, N.; Bandara, T.; Wickramasinghe, K.; Seneviratne, D.; Rajapakse, S.; De Silva, A.; et al. Challenges in learning procedural skills. Teach. Learn. Med. 2024, 36, 435–453. [Google Scholar] [CrossRef] [Scilit]
- Huo, B.; MacNevin, W.; Smyth, M.; Miller, S.G. Medical student comfort with procedural skills. Cureus 2020, 12, e12374. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGaghie, W.C.; Issenberg, S.B.; Barsuk, J.H.; Wayne, D.B. A critical review of simulation-based mastery learning with translational outcomes. Med. Educ. 2014, 48, 375–385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barsuk, J.H.; Cohen, E.R.; Feinglass, J.; McGaghie, W.C.; Wayne, D.B. Simulation-based mastery learning reduces complications during central venous catheter insertion. Arch. Intern. Med. 2009, 169, 1420–1423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cleland, J. Exploring versus measuring: Considering the fundamental differences between qualitative and quantitative research. Res. Med. Educ. 2015, 1–14. [Google Scholar] [CrossRef] [Scilit]
- Kolb, D.A. Experiential Learning: Experience as the Source of Learning and Development; Prentice Hall: Englewood Cliffs, NJ, USA, 1984. [Google Scholar]
- Green, P.; Edwards, E.J.; Tower, M. Core procedural skills competencies. BMC Med. Educ. 2022, 22, 259. [Google Scholar]
- Kneebone, R.L.; Nestel, D.; Vincent, C.; Darzi, A. Complexity, risk and simulation. Med. Educ. 2007, 41, 808–814. [Google Scholar] [CrossRef] [Scilit]
- Burgess, A.; van Diggele, C.; Roberts, C.; Mellis, C. Tips for teaching procedural skills. BMC Med. Educ. 2020, 20, 458. [Google Scholar] [CrossRef] [Scilit]
- Accreditation Council for Graduate Medical Education. The ACGME Common Programme Requirements for Residency. Available online: https://www.acgme.org (accessed on 9 April 2025).
- Singapore Accreditation Board. Specialist Training Guidelines for Internal Medicine. Available online: https://www.healthprofessionals.gov.sg (accessed on 9 April 2025).
- Ericsson, K.A.; Krampe, R.T.; Tesch-Römer, C. The role of deliberate practice in expert performance. Psychol. Rev. 1993, 100, 363–406. [Google Scholar] [CrossRef]
- Swartz, S.; Umpierrez De Reguero, A.; Puetz, J.R.; Carter, L.M.; Foster, T.R.; Bennett, K.R.; Nelson, A.C.; Reed, M.J.; Sullivan, D.P.; Morris, E.L.; et al. Advancing internal medicine training. Hosp. Top. 2023, 101, 127–134. [Google Scholar] [CrossRef] [Scilit]
- Garrood, T.; Iyer, A.; Gray, K.; Patel, R.; Patel, S.; Khan, M.; Ali, S.; Jones, P.; Smith, J.; Williams, D.; et al. A structured course teaching junior doctors invasive procedures. Clin. Med. 2010, 10, 464–467. [Google Scholar] [CrossRef] [Scilit]
- Morris, A.M.S.; Morris, A.A. Dealing with your first complications. Semin. Colon Rectal Surg. 2020, 31, 6–9. [Google Scholar] [CrossRef] [Scilit]
- Louis, A.S.; Lee, C.; Page, A.V.; Ginsburg, S. Internal medicine resident experiences performing invasive procedures. Can. Med. Educ. J. 2023, 14, 5–13. [Google Scholar]
- Barr, J.; Graffeo, C.S. Procedural experience and confidence. J. Surg. Educ. 2016, 73, 466–473. [Google Scholar] [CrossRef] [Scilit]
- Meling, T.R. The impact of surgical simulation on patient outcomes. Neurosurg. Rev. 2021, 44, 843–854. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Academic Society for International Medical Education. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.