


Abstract
Cardiac autonomic recovery after exercise is conventionally summarized as a single nocturnal heart rate variability (HRV) average, treating sleep as a passive backdrop rather than an active determinant of recovery. Three distinct levels of inference are involved and are kept separate throughout: an observed association between sleep stage and autonomic indices; causal evidence that specific experimental manipulations of slow-wave sleep alter autonomic or cardiovascular parameters; and the substantially more tentative, not-yet-demonstrated claim that slow-wave sleep plays a causal role in recovery, specifically after exercise. A fragmented but convergent literature indicates that autonomic state tracks sleep stage in real time, with HRV indices of cardiac-vagal modulation concentrated in slow-wave sleep (SWS) and attenuated during REM sleep, and that the SWS–autonomic link itself has been demonstrated experimentally, not only observed: enhancing slow-wave activity increases HRV-derived cardiac-vagal modulation, and sleep restriction directly disrupts the nocturnal autonomic state. Whether this causal pathway produces post-exercise autonomic recovery remains to be demonstrated. Exercise has been shown to modulate SWS-phase HRV, and post-exercise vagal reactivation has been reported to be depressed on nights following intense exercise in a manner localized to the SWS stage, though this rests on cardiac-derived rather than EEG-confirmed sleep staging. However, no study has manipulated SWS after exercise and tracked the resulting recovery trajectory, a gap that this review names explicitly (as Prediction 1, P1) as the framework’s most direct causal test. This review synthesizes the literature into a systems physiology framework in which SWS is hypothesized to function as a plausible moderator of post-exercise cardiac autonomic recovery, not yet as a demonstrated determinant of it, integrating brainstem circuitry and neurotransmitter systems, causal SWS manipulations (acoustic, pharmacological, deprivation-based), exercise dose-response, and boundary conditions (age, sex, training status, sleep and cardiovascular disorders) under which the coupling is preserved, attenuated, or absent. The effect is graded and window-specific rather than uniform—comparatively strongest in the early post-exercise reactivation phase and during nocturnal SWS, not established across the full multi-hour recovery curve—and is translated into falsifiable predictions and candidate study designs, including a critical appraisal of wearable sleep-tracking validity. Two evidentiary gaps are addressed transparently: the human circuit-level mechanism remains largely inferred from rodent studies, and independent citation-network verification is not feasible for all sources. These findings support slow-wave sleep as a plausible, mechanistically motivated candidate moderator of post-exercise systemic autonomic and cardiovascular physiology, rather than an established determinant of it or a variable external to it.
1. Introduction
1.1. Background and Rationale
Cardiac parasympathetic tone, most commonly indexed by heart rate variability (HRV), is widely used as a marker of post-exercise recovery, typically summarized as a single nocturnal average that treats sleep as a passive backdrop. The autonomic state in fact tracks sleep architecture in real time: parasympathetic activity peaks during slow-wave sleep (SWS) and is attenuated during REM sleep, extending to functional connectivity within central autonomic brain regions specifically during SWS [1,2]. Throughout this review, ‘parasympathetic tone’ and related terms denote an HRV-derived inference rather than a direct measure of autonomic outflow unless a direct sympathetic or vagal measure is explicitly cited (Section A Note on the HRV Indices Used in This Review).
This relationship is causal rather than correlational: enhancing slow-wave activity with closed-loop acoustic stimulation increases HRV-derived cardiac-vagal modulation and reduces HRV-derived markers of sympathetic activity, establishing that causation runs from sleep architecture to autonomic state [3]. This plausibly underlies post-exercise recovery specifically—SWS-phase HRV is depressed after intense exercise and recovers over subsequent nights [4], discriminates training load more sensitively than whole-night measures [5], and is selectively reduced in overreached athletes without a whole-night change [6]—and sleep restriction directly disrupts the same mechanism, raising sympathetic and lowering vagal tone during sleep itself, not only on waking [7].
Despite this evidence, the sleep-stage-specific basis of post-exercise autonomic recovery has not, to our knowledge, been synthesized into a dedicated framework. Existing reviews frame recovery as a function of elapsed time alone—with full recovery placed at up to 24 h after low-intensity exercise, 24–48 h after threshold-intensity, and at least 48 h after high-intensity exercise [8]—without separating the contribution of sleep architecture, particularly SWS, from time itself. The distinction matters: if SWS is the substrate of nocturnal recovery, conditions that alter SWS quantity or quality (age, sex, training status, sleep or cardiovascular disorders) should alter recovery independently of elapsed time, a prediction a purely time-based account does not make.
This review proposes slow-wave sleep as a candidate physiological gate for post-exercise cardiac autonomic recovery: a hypothesized framework in which the strength and detectability of autonomic recovery depend on how the intervening sleep period engages the SWS–autonomic coupling, not on elapsed time alone. This gating effect is graded and window-specific rather than uniform, with the strongest support in the early post-exercise reactivation phase and the SWS period itself, and considerably weaker support across the intermediate, multi-hour window [9]. The framework currently rests on combining two separately demonstrated links—that manipulating SWS causally alters autonomic tone (Section 3) and that exercise alters SWS-phase autonomic activity (Section 4)—rather than on a single design that manipulates SWS after exercise and measures the resulting recovery trajectory. No such combined study has been identified in this review, and none of the six predictions in Section 8 close this specific gap (Section 8.4).
1.2. Objectives
The objectives of this review are: (1) to synthesize the brainstem circuitry and neurotransmitter systems implicated in SWS–autonomic coupling, distinguishing human correlational evidence from causal circuit-level evidence derived predominantly from animal models (Section 2); (2) to evaluate the causal evidence linking experimental SWS manipulation—acoustic, pharmacological, deprivation-based—to autonomic outcomes (Section 3); (3) to characterize the exercise dose-response relationship for SWS-phase autonomic disruption, including trained-versus-sedentary differences (Section 4); (4) to identify the boundary conditions—age, sex, clinical disorders, sleep-monitoring technology—under which the gating effect is preserved, attenuated, or untested (Section 5, Section 6 and Section 7); and (5) to translate the framework into falsifiable predictions and candidate study designs (Section 8).
1.3. Guiding Research Questions
Q1. Which brainstem nuclei and neurotransmitter systems mediate the coupling between slow-wave sleep and autonomic tone, and to what extent is this circuitry established in humans versus that inferred from animal models?
Q2. Beyond closed-loop acoustic enhancement, which experimental manipulations of slow-wave sleep have been shown to causally alter autonomic or cardiovascular parameters, and in which direction?
Q3. How does the magnitude of slow-wave sleep phase autonomic disruption following exercise scale with exercise intensity and duration, and does this relationship differ between trained and sedentary individuals?
Q4. Do age-related declines in slow-wave sleep and documented sex differences in sleep architecture alter the strength of the slow-wave-sleep-autonomic coupling, and through which mechanisms?
Q5. In clinical populations with disrupted slow-wave sleep, is autonomic recovery measurably impaired relative to healthy sleepers, and does treating the underlying sleep disorder restore autonomic recovery capacity?
Q6. Are consumer wearable and nearable sleep-tracking devices sufficiently valid for either heart-rate-variability output or slow-wave-sleep staging to support research or the applied monitoring of this coupling in a post-exercise context?
1.4. Scope and Manuscript Structure
This review is conceptual and hypothesis-generating. Slow-wave sleep is proposed as a physiological gate for post-exercise autonomic recovery. The term is used here as an explicitly hypothetical metaphor for a proposed mechanism—not as a claim that a validated causal gating mechanism has been demonstrated for post-exercise recovery specifically—and, throughout, in the gain-modulation sense—a continuously variable multiplier on the magnitude and detectability of autonomic recovery—rather than the binary, all-or-none sense the word can also carry. Operationally, the gate acts on the amplitude of the parasympathetic (HF-HRV) response measurable during and after a given sleep period for a given exercise dose: more or better-consolidated SWS is predicted to raise this amplitude (a more ‘open’ gate), less or more fragmented SWS to lower it (a more ‘closed’ gate), with the fully closed state expected only outside the early-reactivation and nocturnal-SWS windows identified below—the gate is a dial, not a switch, and only its extremes should be read as open/closed. This is not a validated diagnostic or monitoring index.
The term ‘recovery’ is also used precisely here rather than as a single undifferentiated construct. This review’s claims concern cardiac autonomic recovery specifically—the return of HRV-indexed and, where measured, more direct autonomic readouts (Section A Note on the HRV Indices Used in This Review) toward a pre-exercise or resting reference—considered at two timescales: immediate post-exercise autonomic recovery in the minutes to first hour after exercise cessation, and the nocturnal autonomic state during the subsequent sleep period. It does not, without separate evidence, extend to next-day functional or performance recovery or to the broader systemic recovery process (thermal, endocrine, metabolic, and neuromuscular restoration), which are conceptually distinct constructs that may or may not track cardiac autonomic recovery in parallel; where a cited study measured one of these other constructs directly, this is stated explicitly rather than assimilated to cardiac autonomic recovery.
The ‘early post-exercise reactivation phase’ referenced throughout (e.g., Abstract, Section 8 and Section 9) is operationalized as the interval from exercise cessation to habitual sleep onset, together with the first sleep cycle (approximately the first 90 min of sleep, encompassing the first SWS/N3 period); this is distinguished throughout from ‘nocturnal SWS’, referring to SWS periods later in the sleep episode, and from the intermediate, multi-hour recovery window spanning the remainder of the night. Vagal reactivation measured immediately after exercise cessation and autonomic variation measured during subsequent sleep are treated as related but empirically distinct phenomena and are not assimilated without a direct within-study temporal linkage; where a cited study measured only one of the two, this is stated explicitly.
The literature was identified using a targeted, question-driven strategy detailed in Section 1.5, which also reports an independent citation-network verification step applied to several foundational sources discussed in Section 2 and Section 3.
The manuscript proceeds as follows: Section 2, brainstem circuitry and neurotransmitter systems; Section 3, causal manipulations of SWS; Section 4, exercise dose-response; Section 5, age and sex; Section 6, clinical populations; Section 7, wearable and nearable technology; Section 8, falsifiable predictions and study designs; and Section 9, discussion and conclusions.
An Alternative, Common-Cause Account
A structurally different explanation deserves statement before the framework is developed further. Intense or late exercise raises core temperature, circulating catecholamines and cortisol, and shifts substrate and fluid status—perturbations that can independently depress nocturnal HRV and alter SWS quantity and continuity, and that can also elevate heart rate and ventilation directly, independent of any change in autonomic tone narrowly defined. Under this account, a single upstream perturbation drives both the SWS reduction and the vagal-tone reduction in parallel, without SWS itself gating anything. This common-cause model fits the correlational evidence in Section 2, Section 3, Section 4, Section 5 and Section 6 essentially as well as the proposed SWS-gate model does, because most of that evidence—exercise-dose studies (Section 4), age/sex comparisons (Section 5), and much of the clinical literature (Section 6)—is observational with respect to the SWS–autonomic relationship itself, even where the exercise or clinical manipulation is controlled.
The gate model is distinguished from the common-cause model only where SWS is manipulated directly, independent of exercise or of temperature/catecholamine/cortisol change, and the autonomic effect still occurs (Section 3); this is why Section 3’s causal evidence, not the correlational evidence in Section 4, Section 5 and Section 6, carries the framework’s central claim and why Section 8’s designs measure or control candidate common-cause variables wherever possible.
1.5. Literature Review Strategy and Scope
The evidence for this review was identified using a two-stage, targeted, question-driven strategy rather than a fixed-database systematic search protocol. In the first stage, six specific, mechanistically framed questions—corresponding to Section 2, Section 3, Section 4, Section 5, Section 6 and Section 7—were submitted individually to Elicit, an AI-assisted literature discovery tool whose semantic-similarity-based ranking and corpus coverage differ structurally from Boolean, field-tagged bibliographic databases (PubMed, Scopus, Web of Science); this review therefore does not claim a systematic-review protocol (see below), and the resulting search is best read as a broad but non-exhaustive, discovery-oriented sampling of the literature rather than a benchmarked high-recall retrieval, since no comparison against a reference set or a second database was performed. Within each question’s result set, the priority for inclusion was given, in order, to human over animal studies (except where a claim is explicitly flagged as rodent-derived), experimental or interventional over purely observational designs, serial or within-night data over single-timepoint measurements, and peer-reviewed publications over conference abstracts. No formal, pre-specified inclusion/exclusion checklist was applied (Section 9.3). The full literal query text, per-question search dates, and record counts are given in File S1.
In the second stage, a citation-network cross-check (Scite) was applied to four foundational sources—a single-platform check rather than an independent, multi-source verification load-bearing for the causal claims developed in Section 2 and Section 3; the outcomes ranged from genuine cross-confirmation to an unresolved indexing failure and are summarized in Table 1, with the full per-source verification narrative provided in File S1.
Table 1.
Independent citation-network verification (Scite) outcomes for the four foundational sources.
Table 1 below summarizes the outcome of this citation-network verification step for the four foundational sources, for scannability alongside the narrative account above.
To complement the AI-assisted discovery process, a confirmatory PubMed search was run on 19 August 2026 (records from 1 January 2010 onward), combining terms central to the manuscript’s causal claims; full query strings and yields are reported in File S1. No result altered a substantive claim in this review. Two records identified through this search—Choi et al. [14] and Kwon et al. [15]—describe closed-loop vibrotactile stimulation reporting comparable HRV increases and are discussed, together with their methodological limitations, in Section 3.1.
This review reports its methodology against the SANRA (Scale for the Assessment of Narrative Review Articles) criteria: importance and aims (Section 1.1 and Section 1.2), guiding questions (Section 1.3), search strategy and limitations (this section and Section 9.3), evidence weighted by study type and species throughout (most explicitly Section 2.6, Section 3.5, Section 4.4 and Section 5.6), and data presented comparatively in tables and a figure throughout rather than only narratively; a completed SANRA checklist is provided as File S2. It does not follow a PRISMA-based systematic-review protocol: no fixed-database set, Boolean query strings, pre-registered inclusion/exclusion criteria, dual-reviewer screening, or formal risk-of-bias assessment. The evidence base is therefore heterogeneous in study type and species—human experimental/interventional studies prioritized, rodent-derived claims flagged explicitly (Section 2)—and includes a few conference abstracts, flagged as such at first mention. It should accordingly be read as a structured, mechanistically prioritized narrative synthesis with partial citation-network verification, not an exhaustive or fully reproducible systematic review. Beyond the query strings, search dates, and record counts already reported in Table 2 and File S1, a per-study evidence table (citation, species/population, design type, key finding as stated in the manuscript, and evidentiary tier for every cited study, compiled directly from content already stated in the main text) and a simplified, explicitly non-formal evidentiary-strength rating are now provided as File S3. One reproducibility element remains a stated limitation rather than a resolved item: a documented, source-by-source reason for exclusion where a candidate source identified by the search was not carried forward. This was not systematically logged during the original discovery process, since no pre-registered inclusion/exclusion checklist was applied (a limitation already stated above and in Section 9.3), and it cannot be reconstructed retrospectively without risk of post hoc rationalization. The closest available substitute, reported here in its place, is the explicit inclusion-priority ordering already stated earlier in this section (human over animal, experimental over observational, serial over single-timepoint, peer-reviewed over conference abstract), which describes the selection logic actually applied even though it does not reconstruct a per-record log.
Table 2.
The six literal queries submitted to Elicit, search date, and records returned/retained per query. “Records returned” reflects Elicit’s interface display limit for a single query rather than the tool’s total indexed corpus match count for that query; it should not be read as an exhaustive yield figure.
Table 2 reports the six literal queries submitted to Elicit, the search date, and the number of records returned and retained for each, so that the search underlying this review can be independently reproduced or audited.
2. Brainstem Circuitry and Neurotransmitter Systems Mediating the Slow-Wave-Sleep–Autonomic Coupling
One framing point governs how this section should be read: in humans, the slow-wave sleep (SWS)–autonomic link is established almost entirely through correlational evidence—coordinated cortical and cardiac oscillations whose direction of causation is difficult to establish from observational recordings alone [16]. The circuit-level, causal dissection of this coupling comes almost entirely from rodent (and some cat) studies, and much of that work characterizes NREM sleep broadly or REM sleep specifically rather than SWS in isolation. Where a finding concerns REM rather than SWS, or derives from a non-human species, this is stated explicitly below rather than being left to be inferred. For clarity, the evidence in this section falls into three tiers: (A) human evidence—the EEG-confirmed sleep-stage associations and HRV/baroreflex findings in Section 2.1; (B) translational animal evidence—the circuit-level NTS, RVLM/C1, NA, and LPGi findings in Section 2.2, Section 2.3 and Section 2.4, derived from rodent (and some cat) studies; and (C) proposed synthesis—the explicitly labeled, speculative circuit model integrating (A) and (B) for a human post-exercise context, presented in Section 2.6 and never itself demonstrated.
2.1. The Autonomic Signature of SWS in Humans
The consistent human finding is that deepening non-REM sleep is a state of parasympathetic dominance and sympathetic withdrawal. Progression into SWS is marked by increased high-frequency (parasympathetic) HRV [3], and across sleep stages, parasympathetic tone tracks the depth of sleep, whereas an index of sympathetic activity has been reported to track time asleep more than sleep depth specifically [17]—an indirect autonomic index, per the caveats in Section A Note on the HRV Indices Used in This Review, rather than a direct measure of sympathetic outflow. A more specific dissociation refines this: electroencephalographic delta power correlates negatively with the sympathetic HRV index (LF/HF) but not the vagal index, indicating deeper SWS chiefly reflects graded sympathetic withdrawal rather than further vagal gain [18]—a single-study, single-index inference that should be read as weak rather than established (Section A Note on the HRV Indices Used in This Review). Nocturnal blood-pressure “dipping” in non-REM sleep is understood to arise from generalized cardiovascular deactivation and baroreflex resetting, driven by central autonomic commands rather than passive mechanical factors [19].
A Note on the HRV Indices Used in This Review
Nearly every claim in this review rests on heart-rate-variability indices, so their limitations are appraised once here rather than re-qualified at each mention. High-frequency (HF) power and its normalized form (nHF) are reasonably well-validated correlates of cardiac-vagal (parasympathetic) outflow at rest, but HF power is strongly dependent on respiratory frequency and tidal volume, both of which change across sleep stages and after exercise; a rise or fall in HF-HRV during or after exercise-disrupted sleep cannot be unambiguously attributed to vagal tone without accounting for this, and the studies cited here vary in whether they control for it. Time-domain indices (RMSSD, pNN50) are also vagally weighted and share the same respiratory dependence. The low-frequency-to-high-frequency ratio (LF/HF), used chiefly in Section 2.1 and Section 4.2 as an index of sympathetic or sympathovagal balance, no longer has this standing in the methodological literature: LF power reflects a mixture of sympathetic and parasympathetic influences rather than sympathetic tone specifically, and LF/HF has been shown not to track directly measured sympathetic outflow (e.g., muscle sympathetic nerve activity or cardiac norepinephrine spillover) reliably [20,21,22]. Findings that depend on LF/HF as a marker of sympathetic withdrawal or activation—most notably the Section 2.1 conclusion that deepening SWS chiefly reflects graded sympathetic withdrawal rather than further vagal gain, which rests on a single LF/HF–HF-HRV dissociation [18]—are therefore presented as suggestive rather than established and should not be read as demonstrating a specifically sympathetic mechanism. This is not merely theoretical: the two foundational acoustic-enhancement studies in Section 3.1 disagree on the direction of LF itself—Grimaldi et al. [3] report a decrease, Diep et al. [10] an increase—with Diep et al. explicitly attributing this to LF being”moderated by both the parasympathetic and sympathetic nervous systems, and not informative on cardiac health as a standalone measure,” which this review adopts as its own operating assumption throughout. Finally, normalized- and absolute-unit HRV values are not interchangeable, and the studies cited here are inconsistent in what they report; where this plausibly matters, it is noted at the relevant point. More broadly, measures differ systematically in how directly they index autonomic outflow: electrocardiography interpreted alongside measured respiration, beat-to-beat blood pressure, baroreflex sensitivity, and microneurography constitute more direct and robust autonomic readouts than HRV-derived indices alone, and HRV- or heart-rate-derived sleep-stage classifications from wearable devices (Section 7.2) should be read as indirect measures on both the autonomic and the sleep-staging side. Conclusions in this review that rest chiefly on LF/HF—most notably the Section 2.1 inference that deepening SWS chiefly reflects graded sympathetic withdrawal—are accordingly presented as exploratory rather than established. As a matter of consistent usage, this review therefore prefers ‘HF-HRV’ or ‘HRV-derived cardiac-vagal modulation’ to ‘vagal activity’ or ‘parasympathetic tone,’ uses ‘HRV-derived sympathetic inference’ only where the specific index plausibly supports it, and reserves ‘sympathetic withdrawal,’ ‘sympathetic dominance,’ and ‘sympathetic activation’ for instances backed by a direct sympathetic measure (MSNA, catecholamines, pre-ejection period, or baroreflex-calibrated blood pressure); departures from this convention elsewhere in the text should be read as shorthand for the HRV-derived inference defined here, not as a claim of direct autonomic measurement.
Where a study cited in this review used a direct measure of sympathetic activity—microneurographic muscle sympathetic nerve activity (MSNA), plasma or urinary catecholamines, or beat-to-beat blood pressure as a baroreflex readout—this is noted explicitly (see, in particular, Section 3.2 and Section 6.1); in all other cases, statements about ‘sympathetic’ change in this review refer to an HRV-derived inference and should be read with the caveats above.
2.2. Brainstem and Autonomic Nuclei
Nucleus tractus solitarius (NTS). The medullary NTS is the first central relay for baroreceptors and other vagal afferents, converging cardiovascular and sleep-state control. In rats, chemogenetic/optogenetic stimulation of NTS neurons and the NTS → parabrachial pathway increased delta EEG power during NREM sleep [23]. More directly, a 2022 mouse study showed the baroreflex circuit itself ‘moonlights’ in sleep control: activated barosensitive NTS neurons promote non-REM sleep while lowering blood pressure and heart rate [13]—the most direct mechanistic bridge identified here between the baroreflex circuit and the sleep state carrying parasympathetic dominance, though still a mouse finding without a demonstrated human counterpart (Section 1.5).
Rostral ventrolateral medulla (RVLM) and C1 neurons. The RVLM is the principal sympathoexcitatory premotor source for the cardiovascular system; its activity reflects both early baroreflex response and later compensatory activity during sleep, with longer response latencies in REM than quiet sleep [24]. Adrenergic C1 neurons within the RVLM are linked to the sympathetic baroreflex limb, with C1 activation during REM specifically baroreflex-dependent in rats [25]; they are also hypoxia-responsive and can promote arousal from non-REM sleep [26], and they are activated during REM even as pontine noradrenergic cells are suppressed [27]. Yao et al. linked these observations: GABAergic caudal ventrolateral medulla neurons promote non-REM sleep partly by inhibiting these sympathoexcitatory RVLM neurons [13]. Because C1/RVLM mechanisms are characterized predominantly for REM and arousal rather than SWS specifically, they are presented here as contextual circuitry rather than an established SWS-specific mechanism.
Nucleus ambiguus (NA) and cardiac-vagal neurons. The NA houses most parasympathetic cardiac-vagal preganglionic neurons, though additional cardiac-projecting vagal preganglionic neurons also exist in the dorsal motor nucleus of the vagus (DMV); unless a source specifies otherwise, ‘cardiac-vagal neurons’ in this review refers to the NA population, which is the focus of the circuits discussed here. In mice, genetically defined (Tbx3-positive) NA cardiovagal neurons project directly onto the heart and, when activated, dramatically slow the heart rate via an atropine-sensitive (muscarinic) mechanism [13]. These neurons are intrinsically silent, so the resting vagal tone is set entirely by the synaptic drive from glutamatergic, GABAergic, glycinergic, and serotonergic inputs [28]. Cholinergic NA neurons also independently promoted non-REM sleep in the same mouse study [13], coupling the cardiac–vagal limb to the sleep state itself, not only its downstream cardiac effectors.
The lateral paragigantocellular nucleus (LPGi)—an REM-specific gate. The clearest characterized circuit for state-dependent vagal withdrawal concerns REM, not SWS. In rats, LPGi stimulation evokes the GABAergic inhibition of NA cardiac-vagal neurons, a candidate mechanism for REM’s reduced parasympathetic activity and heart-rate elevation; this pathway is itself modulated by α7-nicotinic transmission [29]. It is included here for contrast, not as SWS-gating evidence, since it describes REM-phase vagal withdrawal—the opposite stage and the opposite autonomic direction.
2.3. Higher-Order Central Autonomic Network
Above the brainstem, a forebrain “central autonomic network”—insula, anterior/midcingulate cortex, amygdala, hypothalamus, periaqueductal gray, parabrachial nucleus, together with the medullary NTS, NA, ventrolateral medulla, and raphe—overlaps anatomically with arousal circuitry [26]. Human evidence linking this network specifically to SWS comes from older adults at dementia risk: parasympathetic (HF) HRV during SWS specifically was associated with functional connectivity in core central autonomic regions (right anterior insula, posterior midcingulate cortex) and amygdala–thalamus connectivity, with no equivalent association during REM or wakefulness [2]—suggesting that SWS is a privileged window for brain–heart coupling rather than a general sleep phenomenon. Consistent with this, chronic fatigue syndrome shows a loss of the SWS-specific parasympathetic signal as a form of autonomic “hypervigilance,” with vagal HRV reduced specifically during deeper sleep but not resting wakefulness [30].
2.4. Neurotransmitter Systems
Cholinergic signaling plays two roles. In state control, wake-active cholinergic neurons of the basal forebrain and pedunculopontine tegmentum, with monoaminergic neurons, provide state-dependent input onto the glutamatergic/GABAergic command neurons setting sympathetic versus cardiovagal output, and locus coeruleus activation drives sympathetic activation with concurrent cardiovagal inhibition [26,31]. In direct modulation, nicotinic (α7) transmission gates the LPGi → cardiac–vagal inhibitory pathway [29], and the NA cardiovagal end-organ effect is muscarinic and atropine-sensitive [13].
Adenosinergic signaling is best characterized as indirect: adenosine functions as the homeostatic sleep-pressure signal building the SWS state that carries the parasympathetic shift, not as a demonstrated direct autonomic transmitter. It accumulates in the cholinergic basal forebrain during wakefulness and acts via A1 receptors to inhibit wake-active neurons, inducing NREM sleep and delta activity [32]; lesioning these neurons abolishes both the adenosine rise and the homeostatic sleep response to deprivation [33], and a glial–neuronal circuit (glial adenosine kinase acting via neuronal A1 receptors) controls slow-wave-activity magnitude [34]. Adenosine’s link to autonomic tone is thus an inferred chain—promoting deeper SWS, which carries parasympathetic dominance—not a directly mapped pathway.
Glutamate and GABA are the effector systems: the actual command neurons for sympathetic and cardiovagal output are glutamatergic/GABAergic, with cholinergic, monoaminergic, and orexinergic systems acting as state-dependent modulators superimposed on this architecture [31]. Hypothalamic orexin is a key permissive signal for sleep-related blood-pressure changes [19].
2.5. Phasic Events as a Causal-Sequence Probe: K-Complexes
Because the tonic SWS–autonomic association is fundamentally correlational in humans, the clearest evidence for the temporal directionality of central-to-autonomic coupling comes from phasic rather than tonic non-REM events. Spontaneous K-complexes are followed by transient rises in muscle sympathetic nerve activity and blood pressure—cortical activation transiently facilitating sympathetic outflow [35]—with a pressor response larger in men than women [36]. Such evoked-event paradigms are currently the primary way to probe this directionality in humans, absent the causal circuit manipulations available in animal models [16].
2.6. Synthesis: A Circuit-Level Account with an Explicit Species and Evidence-Type Gap
Taken together, this section’s evidence indicates that a plausible multi-nodal brainstem circuit spanning the NTS, RVLM/C1, and NA cardiac–vagal neurons, modulated by cholinergic and adenosinergic systems on an underlying glutamate/GABA architecture, could in principle mediate a causal SWS–autonomic link. However, a dedicated, causal, SWS-specific circuit tracing from a defined brainstem nucleus to a measured autonomic output has not, to our knowledge, been established in humans: human data are HRV correlations, while the available optogenetic/chemogenetic circuit dissections (NTS, C1/RVLM, LPGi → cardiac–vagal–neuron, cholinergic NA) are rodent-derived and frequently characterize NREM broadly or REM specifically rather than SWS—the LPGi and C1 mechanisms in particular are REM-phase phenomena, included for contrast rather than direct SWS evidence. This circuit-level account should therefore be read as a plausible mechanistic scaffold consistent with the evidence in Section 3, not a demonstrated human mechanism. Box 1 summarizes these circuit-level findings by species, sleep state studied, and level of human transposition.
Box 1. Circuit-Level Findings in Section 2, by Species, Sleep State Studied, and Level of Human Transposition.
NTS, chemogenetic/optogenetic stimulation—studied in rat, this circuit was probed during NREM sleep (delta power) and produced increased delta EEG power; the human transposition is inferred only, with no human circuit-level test identified.
NTS, barosensitive neurons—studied in mice during non-REM sleep, stimulation promoted non-REM sleep with reduced blood pressure and heart rate; this is inferred, representing the closest mechanistic bridge identified here, though still mouse-only.
RVLM/C1—studied in rat comparing REM versus quiet sleep, this circuit produced baroreflex-dependent sympathoexcitation that was more pronounced in REM; it has been characterized predominantly for REM and arousal, and is presented here as contextual circuitry rather than SWS-specific evidence.
NA cardiovagal (Tbx3-positive) neurons—studied in mice in an NREM context, activation produced marked, atropine-sensitive heart-rate slowing; the human transposition is inferred, with no human analog directly tested.
LPGi—studied in rat during REM sleep, this circuit mediates GABAergic inhibition of NA cardiac-vagal neurons underlying REM vagal withdrawal; it is REM-specific, included here for contrast rather than as SWS-gating evidence.
Cholinergic and adenosinergic modulators—studied in rodents in the context of NREM/SWS sleep-pressure regulation, these modulators set NREM/SWS depth and delta activity, with the autonomic link inferred rather than direct; this represents an inferred chain, not a demonstrated direct autonomic-transmitter role.
This compact comparison is offered alongside, not in place of, the narrative synthesis above, and is intended to make explicit how much of Section 2’s circuit-level precision is rodent-derived and REM-adjacent rather than a demonstrated human SWS-specific pathway.
3. Causal Manipulations of Slow-Wave Sleep and Their Autonomic and Cardiovascular Consequences
This section addresses which experimental manipulations of SWS, beyond closed-loop acoustic enhancement, have been shown to causally alter autonomic or cardiovascular parameters and in which direction. The evidence is markedly uneven across manipulation types: strongest and most consistent for deprivation and suppression paradigms, informative but confounded for pharmacological approaches, and largely untested for transcranial neuromodulation (Figure 1).
Figure 1.
The slow-wave sleep (SWS)–autonomic gate proposed in this review, depicted as a continuous gain control rather than a binary switch. Exercise generates a transient, dose-dependent post-exercise autonomic perturbation (Section 4). Following sleep onset, autonomic gain varies continuously with sleep stage: SWS sits at the high-gain end, supported by both correlational human evidence and causal manipulation (Section 2 and Section 3), while REM sits at the low-gain end via a distinct, contrasting rodent circuit that is not itself part of the proposed SWS gate. Age, sex/fitness, exercise timing and dose, and hypoxic sleep disorders shift position along this axis (Section 4, Section 5 and Section 6) rather than toggling it between two discrete states. The resulting autonomic recovery is strongest and most directly supported in the early post-exercise reactivation window and during nocturnal SWS itself; it is not established across the intermediate, multi-hour recovery window, where a common-cause alternative (Section An Alternative, Common-Cause Account) has not yet been excluded.
3.1. Closed-Loop Acoustic Enhancement: The Reference Causal Tool
Closed-loop acoustic stimulation remains the cleanest available causal tool for experimentally enhancing SWS while reading autonomic consequences. Automated stimulation in middle-aged men increased high-frequency HRV and SDNN specifically during N3 sleep [3], independently reproduced and extended in a separate randomized crossover sample—genuine cross-study confirmation rather than single-study reliance [10] (see also the companion executive-function report [37]; Section 1.5). The foundational design randomized 24 healthy middle-aged men (39.9 ± 4.1 years) in a double-blind crossover with one-week washout (n = 23 analyzed): stimulation produced a 14.5% SDNN increase and 31.8% HF-power increase during N3 versus sham (d = 0.4–0.8), with no whole-night difference on any HRV measure (p > 0.16), confirming an N3-specific rather than whole-night effect [10]. A related study found that auditory slow-wave enhancement improved next-day left-ventricular systolic and diastolic function [38]. One qualification: each evoked slow wave carries a transient cardiovascular activation—a brief blood-pressure rise and biphasic heart-rate response during stimulation itself [38]—and an earlier rat study found acoustic stimuli during non-REM sleep increased blood-pressure and heart-period variability enough to plausibly favor arrhythmia in a susceptible substrate [39]. Acoustic SWS enhancement should therefore be understood as a net parasympathetic gain over the study period, superimposed on transient stimulus-locked activation, not a uniformly calming intervention at every timescale.
Because every auditory stimulus activates the ascending auditory pathway, regardless of whether it evokes arousal or measurably increases slow-wave activity, a nonspecific auditory contribution to the measured autonomic changes cannot be fully excluded from the acoustic literature alone. The arousal safeguard in the foundational protocol [3] is limited: volume is calibrated once before sleep onset, and stimulation halted only reactively, once EEG shows a stage change to REM or wake—no tone-by-tone, real-time arousal detection. The SmartSleep device used for the companion cohort [10,37] is materially more conservative: stimulation for a given SWS bout continues “until the end of the N3 period or if an arousal was detected,” with volume calibrated to augment slow-wave activity “while not inducing an arousal,” and the two protocols should not be treated as equivalent. Even so, arousal-avoidance calibration prevents overt cortical arousal, not auditory-pathway activation itself, so the underlying confound is not eliminated: the transient stimulus-locked pressor and heart-period responses noted above [38,39] remain at least as consistent with a fast-timescale auditory-activation component as with a purely SWS-mediated mechanism, and this cannot be ruled out by the current protocol.
The two mechanisms are therefore best treated as coexisting rather than competing: nonspecific auditory activation as a plausible contributor to the acute, stimulus-locked signal, and SWS enhancement as the more parsimonious account of the slower, sustained, across-night parasympathetic shift, given that the sustained effect tracks the dose of slow-wave activity achieved rather than the number of tones delivered per se. A structurally different, non-auditory modality bears on this question and is reported here with its limitations made explicit: closed-loop vibrotactile stimulation, cued to the cardiac rhythm rather than phase-locked to the slow wave itself, has been reported to increase parasympathetic HRV indices (normalized high-frequency power) relative to sham [14,15]. These two studies are not independent replications in the usual sense—they share overlapping authorship and the same commercial closed-loop vibration technology—and because the stimulus is cardiac-rhythm-locked rather than slow-wave-phase-locked, an HRV increase under this modality does not by itself evidence an SWS-mediated pathway any more cleanly than the acoustic literature does; the two source studies themselves frame the intervention as autonomic modulation to improve sleep rather than as a slow-wave-specific probe. This evidence is therefore best read as a partially informative, non-auditory data point rather than as independent confirmation that removes the auditory confound.
3.2. Selective SWS Deprivation and Suppression
Selective SWS deprivation → higher nocturnal blood pressure, blunted dipping. In the landmark manipulation, Sayk et al. selectively stripped healthy participants of SWS using EEG-triggered acoustic arousals, without shortening total sleep time, in a crossover design against undisturbed sleep, with microneurographic MSNA and HRV as readouts [12]. Depriving SWS significantly attenuated blood-pressure dipping during the first, SWS-dominated half of the night (some dipping still occurred), while the second, REM-dominated half was unaffected [12]. The effect was circumscribed rather than global: nighttime catecholamine excretion, morning MSNA, morning HRV, and daytime ambulatory blood pressure were all unchanged, indicating that a single night of SWS loss did not durably reset baroreflex-mediated sympathetic regulation [12]. Independent citation-network verification of this source found only tangentially relevant citing papers (Section 1.5), so this finding rests on the original study alone and its replication status remains unresolved. Because the deprivation protocol itself used EEG-triggered acoustic arousals to strip SWS, the observed autonomic effects cannot fully exclude a contribution from the induced micro-arousals and altered sleep continuity themselves, independent of SWS loss per se.
Selective SWS suppression → metabolic shift (with an inferred, not measured, sympathetic component). Tasali and colleagues suppressed SWS throughout the night using acoustic tones while holding total sleep time constant, finding marked reductions in insulin sensitivity without compensatory insulin release, proportional to the amount of SWS removed [11]—widely interpreted as increased sympathetic and reduced parasympathetic drive during shallow sleep. An important attribution caveat: Ukraintseva et al. reproduced glucose-tolerance and melatonin changes after one night of SWS suppression but found these tracked total sleep time, REM duration, and awakenings more closely than SWS loss per se [40]. Independent citation-network verification for Tasali et al.—after confirming the correct paper by title and DOI—returned no citing paper meeting a strict quotable-evidence criterion for replication, extension, or contradiction, a confirmed citation-tracking gap rather than a replication or refutation (Section 1.5); the Ukraintseva contrast was identified through the original literature search, not citation-network tracing.
3.3. Pharmacological Enhancement: The Sodium-Oxybate Cautionary Tale
Pharmacological SWS enhancement offers a mechanistically instructive case where the autonomic direction is reversed relative to acoustic enhancement. Sodium oxybate robustly deepens SWS but is associated with increased blood pressure and sympathetic activity: microneurography in narcolepsy patients showed both MSNA and blood pressure rose after six months of treatment [41], and a large real-world cohort found initiating oxybate associated with increased new-onset hypertension risk (OR ≈ 1.6) [42]. The corrective finding is important: switching patients from high- to low-sodium oxybate at an equivalent dose lowered 24-h ambulatory systolic blood pressure by ~4 mmHg [43], indicating the hemodynamic signal is driven substantially by sodium load rather than SWS enhancement itself. This shows sodium load is an important alternative explanation, not that pharmacological SWS enhancement itself confers a parasympathetic benefit—no autonomic endpoint was measured in the low-sodium comparison, and whether SWS enhancement without the sodium confound reproduces acoustic enhancement’s parasympathetic-gain direction (P2, Section 8) remains untested. GABAergic enhancers such as tiagabine reliably increase slow-wave activity [44], but essentially no autonomic or cardiovascular endpoints have been tested with this drug class—a genuine evidence gap, not a null finding—and, like any pharmacological sleep-modifying agent, tiagabine cannot be assumed free of its own central, respiratory, or hemodynamic effects independent of its SWS-enhancing action simply because it lacks oxybate’s sodium load.
3.4. Transcranial and Emerging Neuromodulation Approaches
Slow-oscillatory transcranial direct-current stimulation delivered during NREM sleep at approximately 0.75 Hz stabilizes sleep and increases N3 duration in patients with chronic insomnia, mimicking the effect of slow-wave-enhancing pharmacology [45]; however, this pilot study did not report any autonomic outcome. Closed-loop transcranial magnetic stimulation and closed-loop transcutaneous vagus nerve stimulation phase-locked to slow oscillations are emerging tools for modulating SWS, but no autonomic or cardiovascular readouts for these specific approaches were identified in this review. Transcranial neuromodulation methods are therefore established as capable of shifting SWS, while their downstream autonomic consequences remain largely uncharacterized, an explicit evidence gap rather than a documented null effect.
3.5. Synthesis: A Directional Map Across Manipulation Types
A consistent directional pattern emerged across this section’s manipulations, alongside clearly demarcated gaps. Removing SWS, by deprivation or suppression, pushes toward higher nocturnal blood pressure and blunted dipping [12] and reduced insulin sensitivity (a labeled inference, not a separately measured autonomic outcome; Section 3.2) [11]. Acoustically adding SWS pushes toward greater overnight parasympathetic tone and improved next-day cardiac function, with transient stimulus-locked activation superimposed [3,10,38]. Pharmacological “enhancement” via sodium oxybate paradoxically raises blood pressure, attributable to sodium load rather than SWS enhancement [41,42,43]. Transcranial neuromodulation remains largely unmeasured for autonomic endpoints [45]. These paradigms should not be read as mirror tests of a single underlying mechanism: acoustic enhancement carries a distinct auditory-activation confound (Section 3.1), while deprivation and suppression protocols carry their own confound of induced micro-arousals and altered sleep continuity (Section 3.2). The pattern across this section is accordingly best summarized cautiously—interventions that modify the depth or continuity of sleep can also modify certain nocturnal autonomic and cardiovascular parameters—rather than as convergent, mechanism-specific confirmation that SWS itself gates autonomic tone, and is bounded further by the pharmacological confound, the untested transcranial route, and the unresolved citation-network status of the Sayk and Tasali findings.
4. Exercise Dose-Response and the Magnitude of Nocturnal Autonomic Disruption (Predominantly Whole-Night HRV, with SWS-Specific Evidence Distinguished in Section 4.2)
A measurement caveat governs this section: most studies reviewed here quantify whole-night or multi-hour nocturnal HRV as a proxy for deep-sleep autonomic tone rather than segmenting SWS itself; only a small subset isolates SWS specifically (identified explicitly in Section 4.2). This proxy relationship is assumed, not independently validated, in every other study cited here, so the exercise dose-response curve below should be read as a whole-night phenomenon that plausibly, but not yet demonstrably, tracks the SWS-specific mechanism proposed in Section 2 and Section 3. The exercise ‘dose’ evaluated in this section is itself necessarily incomplete: intensity and duration are the two parameters most consistently reported and are therefore this section’s organizing axes, but exercise mode, muscle mass involved, ambient temperature, hydration status, carbohydrate intake, energy availability, wake duration before sleep, core temperature, training status, and exercise performed to exhaustion are all plausible independent determinants of nocturnal HRV and sleep architecture that the literature synthesized here does not consistently measure or control for; several of these variables are also candidate common-cause factors under the alternative account in the section ‘An Alternative, Common-Cause Account’.
4.1. Dose-Response: Scaling with Session Magnitude, with Intensity and Duration Dissociating
The core finding is that post-exercise suppression of nocturnal parasympathetic activity scales with overall exercise magnitude, though intensity and duration do not contribute equally. Average nocturnal heart rate rose to ~109% of rest-day values after moderate endurance exercise but ~130% after a marathon, while vagal HF-HRV fell to ~77% and ~34%, respectively—an explicitly dose-dependent pattern [46]. Intensity and duration dissociate at sub-maximal loads: a matrix-varying intensity (45/60/75% VO2max, 30 min) and duration (30/60/90 min) found a higher-intensity elevated nocturnal heart rate without changing HRV, while HRV declined only after the 90 min session, with neither manipulation degrading sleep quality [47]. At the extreme-intensity end, supramaximal intermittent exercise suppressed vagal HRV in the first estimated SWS period, with depression persisting into the second night and recovering only by the third—intensity can extend the recovery tail even at comparatively modest total work [4].
The largest-scale confirmation comes from a wearable-based analysis of ~4 million person-nights: higher exercise strain and later timing were both associated with a higher nocturnal resting heart rate (~6.8%/3.9 bpm for maximal- vs. light-strain exercise ending 2 h before sleep, rising to ~15.0%/9.4 bpm if ending 2 h after sleep onset) and lower nocturnal HRV (~14.1%/8.3 units and ~32.6%/14.6 units respectively); bouts ending four or more hours before sleep showed no association with either measure [48], though no effect size or CI is reported for this specific null comparison. Sleep staging in this dataset was validated against polysomnography only for coarse sleep/wake classification (86–89% agreement); SWS-specific staging accuracy was not independently assessed, sharpening the circularity caveat in Section 7.2. This timing-by-intensity interaction is echoed mechanistically: morning exercise enhanced parasympathetic activity during subsequent sleep, while evening exercise shifted the nocturnal pattern toward higher heart rate, a pattern consistent with relatively greater sympathetic activity though not a direct sympathetic measure [49].
4.2. SWS-Stage-Specific Evidence: A Small but Informative Subset
The most stage-specific finding indicates that even mild physical activity within an hour of bedtime leaves overall sleep architecture intact but raises heart-rate variance and the low-frequency-to-high-frequency ratio specifically during SWS [50]—a pattern consistent with, but not direct evidence for, reduced parasympathetic dominance during the deep-sleep stage itself, since LF/HF is not a validated direct index of either autonomic limb (Section A Note on the HRV Indices Used in This Review). Evening endurance exercise similarly partially suppressed parasympathetic activity (pNN50) across the sleep period, regardless of normoxic or hypoxic conditions [51]. A recurring dissociation is worth noting: this autonomic disruption does not translate into disrupted sleep as conventionally measured—vigorous late-night exercise to exhaustion raised heart rate through the first sleeping hours yet increased the NREM proportion and left subjective/actigraphic sleep quality unchanged [52], and in ultra-endurance runners, intensity mattered more than timing for subjective sleep quality even though nocturnal HRV did not differ across conditions [53].
4.3. Trained Versus Sedentary Individuals: Characterized Separately, Not in a Matched Comparison
The baseline differences between trained and untrained individuals are large: endurance-trained men show a ~4-fold higher nocturnal HF (vagal) HRV power than untrained men, a substantially higher parasympathetic set-point at sleep onset [54], and meta-analytic evidence confirms that training raises resting parasympathetic HRV in previously sedentary individuals [55]. Trained athletes appear relatively resilient to acute evening loads: late-night training did not alter SWS-episode or hourly nocturnal HRV in highly trained female soccer players relative to rest days [56], and an evening high-intensity interval session in endurance runners raised nocturnal heart rate but left HRV unchanged and modestly improved sleep continuity [57]. On the sedentary side, morning walking/running produced no consistent nocturnal HRV change in a small pilot—though morning timing is predicted to be comparatively benign [58]. Notably, even severely overtrained athletes showed no sleep-period HRV difference from controls; the parasympathetic deficit emerged only after awakening, suggesting that the sleeping brain may protect vagal tone even under accumulated training stress [59].
4.4. Synthesis: An Inferred Rather than Directly Demonstrated Dose-Response Curve for SWS Specifically
No study identified in this review segmented the SWS stage specifically, parametrically varied exercise intensity and duration, and did so in matched trained-versus-sedentary groups within a single design: the dose-response matrix work is almost entirely in trained/active men, the trained-versus-untrained comparisons largely address baseline tone rather than post-exercise dose-response, and few studies isolate SWS rather than whole-night HRV. SWS-phase scaling with exercise dose, contrasted by training status, is therefore inferred by combining these strands rather than directly demonstrated—a gap that motivates the study designs in Section 8. Because most of the dose-response evidence reviewed above is correlational with respect to the SWS–autonomic relationship itself, it is compatible with, and does not adjudicate between, the SWS-gate account and the common-cause alternative in which exercise-induced changes in core temperature, catecholamines, cortisol, and hydration status independently drive both the SWS change and the autonomic change (Section An Alternative, Common-Cause Account).
5. Age and Sex as Sources of Variation in the Slow-Wave-Sleep–Autonomic Coupling
No study identified in this review tested the full three-way interaction of age-related SWS decline, sex differences in sleep architecture, and SWS-coupled post-exercise autonomic recovery. The following synthesizes four evidence streams bearing on this question, with the seams between them left explicit; cardiorespiratory fitness recurs as a confounder throughout, especially in the sex comparisons. Beyond fitness, future designs in this area should treat menstrual-cycle phase, hormonal contraceptive use, menopausal status, training history, body composition, and habitual sleep duration as key design considerations from the outset rather than only as a closing caveat (Section 5.6), since the sex- and hormone-related literature synthesized below (Section 5.3, Section 5.4 and Section 5.5) varies considerably in whether and how these variables were controlled.
5.1. Aging Degrades the SWS–Autonomic Coupling Itself
This is the best-supported component in this section. Slow-wave sleep and cardiac autonomic control during sleep both decline with age: in older adults, normalized HF (parasympathetic) HRV during sleep is broadly reduced, linked to decreased SWS duration, with the normal stage-dependent modulation of HRV flattening out [60]. More specifically, young adults show a discrete coupling event—a slow-wave-activity burst preceding a heart-rate burst followed by a vagal surge—that is essentially abolished in older adults, with neither component observed during SWS [61]. Aging thus appears to uncouple SWS from its autonomic correlate, not merely reduce SWS quantity.
5.2. Aging and Post-Exercise Recovery: Real, but Fitness-Dependent
Aging slows post-exercise heart-rate recovery—in women, tracking slower sympathetic withdrawal rather than impaired vagal reactivation, with the recovery time constant correlating strongly with age [62]—but this penalty largely disappears with continued physical activity: in both active young and active older men, high-intensity interval exercise depressed vagal HRV and baroreflex sensitivity comparably, recovering by 60 min in both groups with no age-associated difference [63]. “Aging blunts post-exercise recovery” is thus more precisely “aging combined with deconditioning blunts recovery.”
5.3. Sex Differences in Sleep Architecture and Sleep Autonomics
Women objectively show more SWS and greater slow-wave EEG power than men across a wide age range, which is thought to arise partly from organizational/activational effects of sex steroids [64]. Aging trajectories diverge by sex too: SWS begins declining in men during their thirties but is comparatively preserved in women over the same window, so the age-related decline in Section 5.1 is itself sex-dependent [65]. Autonomically, men show lower vagal tone and higher sympathovagal balance than women during sleep, especially REM [66], and these differences emerge as early as adolescence, with within-night autonomic recovery being blunted in girls relative to boys [67].
5.4. Sex Differences in Post-Exercise Recovery: Contested and Fitness-Confounded
The literature on sex differences in post-exercise autonomic recovery genuinely disagrees, informatively: some studies report that men show faster heart-rate recovery and greater vagal reactivation after exercise [68], while others frame premenopausal women as cardioprotective—with lower resting sympathetic tone, faster vagal reactivation, higher post-exercise HF power [69]. The reconciling finding is that the apparent male advantage disappears once aerobic capacity is controlled: matching men and women for peak oxygen uptake eliminates the sex difference, so much of the apparent sex effect is more accurately a fitness effect [69].
5.5. Attribution: Hormones, Autonomic Baseline, or Sleep Architecture
The evidence permits a reasonably clear, provisional attribution. Hormonal factors matter for baseline reflex physiology but appear weak and secondary here: exogenous estradiol increases cardiovagal baroreflex sensitivity to a hypertensive stimulus in young women [70], and menopausal status is associated with reduced HRV [71], yet estradiol did not explain autonomic modulation during exercise recovery (age did) [62], no HRV–estradiol association emerged separately [71], and the sleep-related sympathovagal sex difference persisted after adjusting for reproductive hormones [66]. The autonomic baseline is a coherent explanatory hypothesis, though not yet tested by mediation analysis or by a design that isolates it from fitness and hormonal covariates: women’s higher resting vagal tone and lower sympathetic tone propagate into both sleep and post-exercise states, and HRV sex differences are better predicted by this baseline (and by fitness) than by hormone levels [69]. Sleep architecture is plausible but essentially untested as a mediator: women have more SWS, and SWS–vagal coupling is exactly what aging degrades (Section 5.1), yet no study identified in this review used SWS as the explicit mediating variable between sex and post-exercise recovery—though adequate sleep duration improved HRV in middle-aged women but not men, a suggestive indirect hint [72].
Table 3 consolidates the six determinants addressed in this section so that the direction of effect and the proposed primary explanation for each can be compared at a glance before the integrative synthesis below.
Table 3.
Age and sex as sources of variation in the SWS–autonomic coupling and post-exercise recovery. SWS, slow-wave sleep; VO2peak, peak oxygen uptake. The directions of effect reflect the studies cited and should not be read as a claim that any single determinant has been tested in a design that isolates it from the others (Section 5.6).
5.6. Synthesis: An Integrative Study Design Is the Explicit Gap
Taken together, age-related differences in post-exercise autonomic recovery are likely influenced substantially by aerobic fitness, but the independent contributions of age, sleep architecture, and sleep-stage-specific autonomic coupling remain unresolved rather than fully attributable to deconditioning; women show more SWS, higher vagal tone, and a slower age-related decline than men; and sex differences in post-exercise recovery are real but are confounded with fitness and baseline autonomic tone in a way that the existing literature does not yet fully disentangle from hormonal contributions. To our knowledge, no integrative study has tracked SWS-stage-specific recovery after a standardized exercise dose in age- and fitness-matched men and women across the lifespan; until one does, this question is answered by inference across separate literature streams rather than direct data (Section 8). Future designs in this area should also more fully capture menstrual-cycle phase, hormonal contraceptive use, menopausal status, training level, habitual sleep duration, and body composition, rather than classifying participants by sex alone, given the sex- and hormone-related variability documented in Section 5.3, Section 5.4 and Section 5.5.
6. Clinical Populations with Disrupted Slow-Wave Sleep
This section addresses whether autonomic recovery is impaired in clinical populations with disrupted SWS, and whether treating the sleep disorder restores it. One point applies throughout: in obstructive sleep apnea (OSA), the dominant model addressed here, autonomic disruption is driven principally by intermittent hypoxia and repetitive arousals rather than SWS loss itself. “Disrupted SWS → impaired autonomic recovery” in this population is therefore best read as a correlate of broader physiological disruption, not a clean SWS-specific causal chain—a qualification to keep in mind when relating this section to the gating framework proposed elsewhere.
6.1. Obstructive Sleep Apnea: Robust Impairment, Driven Predominantly by Hypoxia Rather than SWS Loss
Foundational microneurographic work showed that OSA patients have elevated sympathetic nerve activity even while awake, and, critically, that blood pressure and sympathetic activity fail to fall during sleep, instead surging with each apneic event [73]. A meta-analysis of 850 patients across 26 microneurographic studies found muscle sympathetic activity increased monotonically with OSA severity (~42 to ~71 bursts/100 heartbeats from healthy controls to severe OSA), correlating with apnea-hypopnea index and oxygen desaturation rather than body weight [74]—in untreated OSA, the normal restorative, parasympathetic-dominant, dipping state of deep sleep is substantially disrupted by recurrent hypoxia-driven sympathetic surges and blood-pressure destabilization, rather than abolished outright.
6.2. Continuous Positive Airway Pressure: Autonomic Recovery Restored at Multiple Levels
CPAP treatment reverses the OSA autonomic signature across every readout examined here. It acutely lowers sympathetic activity and blood pressure during sleep [73], and long-term therapy reduces daytime muscle sympathetic traffic, though only after six to 12 months of treatment [75]. Mechanistically, six months of CPAP reduced muscle sympathetic nerve activity by roughly half (~54 to 23 bursts/min) and normalized abnormal RVLM, medullary raphe, and dorsolateral pons activity, indicating the brainstem sympathoexcitatory circuitry itself normalizes with treatment [76]. CPAP also improved baroreflex control of heart rate during stage-2 NREM sleep by nearly 70% [77], converted most non-dipping patients back to normal nocturnal dipping [78], and improved HRV during non-REM sleep after even a single night [79]. The most direct causal evidence runs in reverse: in a randomized withdrawal trial, discontinuing CPAP for two weeks caused OSA to recur and produced a significant rise in morning systolic blood pressure (~+8.5 mmHg), heart rate, and urinary catecholamines versus patients who continued therapy [80]—the strongest evidence that CPAP’s autonomic benefit is genuinely treatment-dependent rather than a stable trait change.
6.3. Insomnia: A Real but Weaker, Phenotype-Dependent Signal
Insomnia is associated with a hyperarousal pattern, but the supporting evidence is considerably weaker than for OSA. Young adults with primary insomnia display sustained nighttime cardiac sympathetic hyperactivation (shortened pre-ejection period) across the whole night [81], and adults with chronic insomnia show blunted sympathetic baroreflex sensitivity and exaggerated cardiovascular stress reactivity despite normal resting blood pressure, heart rate, and sympathetic activity [82]. The deficit appears concentrated in a specific phenotype: only insomnia with objective short sleep duration was associated with dampened parasympathetic activity and sympathovagal imbalance, unlike a near-normal-duration phenotype [83]. Two caveats temper this: a systematic review/meta-analysis of 17 studies found the evidence does not reliably confirm impaired HRV in insomnia disorder [84], and a focused review noted supporting studies mostly relied on sympathetic measures of limited specificity and reproducibility [85]. Whether treating insomnia (e.g., CBT-I) restores autonomic function has no adequate evidence, a genuine gap unlike the well-characterized CPAP literature.
6.4. Sleep Fragmentation: Inconsistent in Humans, with the Clearest SWS-Specific Data Coming from Animal Models
Evidence on pure sleep fragmentation, distinct from sleep restriction or OSA-related hypoxia, is mixed. In a controlled crossover, partial sleep restriction increased sympathetic and decreased vagal tone overnight, but experimental fragmentation via hourly awakenings did not significantly change any cardiac autonomic parameter [7]—fragmentation per se may be less disruptive than curtailed duration. The most SWS-specific evidence comes from a chronic rat model, where fragmentation raised mean arterial pressure specifically during SWS, with a compensatory HF-power rise normalizing during recovery sleep [86].
Table 4 arranges the three clinical conditions addressed in this section along a gradient of evidentiary strength, from the robust and multiply reversible OSA literature to the largely untested question of pure sleep fragmentation in humans.
Table 4.
Evidence gradient for autonomic impairment and its reversibility across three clinical populations with disrupted sleep. CPAP, continuous positive airway pressure; CBT-I, cognitive behavioral therapy for insomnia; RCT, randomized controlled trial; BP, blood pressure; HRV, heart rate variability. In OSA, impairment is understood to be driven predominantly by intermittent hypoxia rather than SWS loss per se (Section 6, introductory paragraph), a qualification that applies to the entire row.
6.5. Synthesis
For OSA, the evidence supports confident conclusions on both halves of this section’s question: autonomic recovery is clearly impaired, and CPAP restores sympathetic tone, baroreflex sensitivity, dipping, and brainstem function, with withdrawal reversing these gains. For insomnia, impairment is real but modest, phenotype-dependent, and inconsistently demonstrated, and whether treatment restores function is largely unstudied. For pure fragmentation, the human signal is inconsistent, and the cleanest SWS-specific evidence is from animal models. Because OSA disruption is driven substantially by intermittent hypoxia rather than SWS loss, this literature is an informative context for, not a direct confirmation of, the gating framework.
7. Wearable and Nearable Technology for Monitoring the Slow-Wave-Sleep–Autonomic Coupling
Consumer wearable (body-worn, e.g., wrist- or finger-based) and nearable (proximity-based, contactless, e.g., under-mattress or bedside) sleep-tracking devices perform two distinct measurement tasks with markedly different validity: measuring HRV, which selected devices do well under stable resting conditions (Section 7.1), and classifying the SWS stage, which they do only moderately well (Section 7.2). The post-exercise-recovery context specifically stresses the conditions under which the staging performance is weakest.
7.1. Heart-Rate-Variability Measurement: Strong at Rest, Context-Dependent Post-Exercise
On the cardiac side, validity evidence is strong under the stable, largely resting conditions in which it was generated; whether this validity extends to the post-exercise state addressed by this review is a separate, currently unresolved question (Section 7.3). Nocturnal heart rate and HRV from a wrist-worn ring agreed almost perfectly with simultaneous ECG (r2 ≈ 0.996 for heart rate, 0.980 for HRV, sub-beat/~1 ms bias) across a wide age range [87]. Among nearables, an under-mattress ballistocardiographic sensor showed only trivial mean bias in heart rate and RMSSD relative to ECG (r ≈ 0.90 and 0.89) when averaged over the full sleep period, though ~28% of epochs were erroneous or missing versus ~1% for the reference system—reliable at the night-level mean but noisier epoch-to-epoch [88]. Wrist/ring photoplethysmography and under-mattress ballistocardiography are therefore valid for nocturnal HRV at the night-average level, where most recovery-monitoring applications operate [87,88]. High correlation and low mean bias at the night-average level, however, do not by themselves establish interchangeability with ECG for individual measurements: limits of agreement, artifact and missing-data rates, proprietary and largely undisclosed derivation algorithms, the duration of the analysis window, and the physiological condition under which validation was performed (typically rest, not post-exercise) all bear on whether a given device is fit for a specific research or clinical use and should be checked against the source validation study rather than assumed from the summary correlation alone.
7.2. Slow-Wave-Sleep Staging: Only Fair-to-Moderate
Sleep-stage classification is the weaker link; deep sleep, though detected somewhat better than light sleep, remains imperfectly classified. Across validation studies against polysomnography, multi-state agreement for consumer wrist devices ranges from kappa 0.20 to 0.53, with deep and REM generally being better identified than wake or light sleep [89,90]; epoch-level sensitivity for detecting sleep can exceed 0.93 while specificity is as low as 0.18–0.54, an overall inconsistent picture [91]. The best-performing device here, a ring sensor with an updated staging algorithm, showed no significant difference from polysomnography for deep-sleep time (per-stage accuracy 75.5–90.6%) [92], but a broader eleven-tracker study reported macro-F1 scores of only 0.26–0.69 for deep sleep [93], PPG-plus-accelerometer algorithms reach a four-class kappa of only ~0.42 even in healthy adults [94], and an under-mattress nearable achieved 83% sleep-wake accuracy (95% sensitivity, only 37% specificity), overestimating total sleep time and performing worse with sleep disorders [95]. A structural reason underlies this: photoplethysmography and ballistocardiography lack EEG input and infer SWS from heart rate, HRV, and movement—the very autonomic signals under study—capping how independently these devices can validate the coupling itself, as opposed to assuming it.
Table 5 restores the device-level detail underlying Section 7.1 and Section 7.2 in comparative form, since the pattern across studies—strong HRV validity, fair-to-moderate staging validity—is easier to assess when the individual validation studies are placed side by side rather than embedded in narrative.
Table 5.
Validation of wearable and nearable devices for heart rate/HRV measurement (top two rows) and slow-wave sleep staging (remaining rows) against reference standards. HR, heart rate; HRV, heart rate variability; ECG, electrocardiography; RMSSD, root mean square of successive differences; PSG, polysomnography; PPG, photoplethysmography. None of the studies listed here incorporated a post-exercise stressor (Section 7.3 and Section 7.4).
7.3. The Post-Exercise-Recovery Context: Two Compounding Problems
Two considerations make the post-exercise context harder to monitor than a generic validation night. First, device staging accuracy degrades on more fragmented, disrupted-sleep nights [91], and intense or late exercise tends to elevate nocturnal heart rate and fragment sleep (Section 4)—precisely the regime where staging is weakest, and because staging relies on heart rate and HRV features, post-exercise elevation can bias the classification itself. Second, more encouragingly, the recovery-monitoring literature has largely sidestepped this by using nocturnal HRV directly rather than depending on precise staging. In world-class alpine skiers, HRV during deep sleep was a valid, time-efficient alternative to morning supine HRV, with deep-sleep segments from RR intervals corresponding well to EEG delta power [96]—a cardiac-derived staging method to which the Section 7.2 circularity still applies, though the reported EEG correspondence is a partial, study-specific validation unlike Leota et al. [48]. Nocturnal HRV shows high night-to-night reliability (ICC 0.91–0.98), and a maximal running test depressed HRV most systematically in four-hour and full-night segments rather than a single morning spot measurement [97]; home wrist photoplethysmography has also detected post-concussion changes in nocturnal parasympathetic activity during athletes’ return to sport [98].
7.4. Synthesis and Practical Guidance
For post-exercise applications, the two measurement functions of consumer sleep technology should be treated separately. For HRV/recovery monitoring, wrist photoplethysmography, ring sensors, and under-mattress ballistocardiography are genuinely valid at the night-average level, and nocturnal (particularly four-hour) HRV appears to capture post-exercise disturbance at least as well as a morning spot measurement. For SWS staging, device-reported “deep sleep” should be treated as a moderate approximation (kappa ~0.2–0.5, best device at the upper end) rather than a polysomnography substitute, expected to degrade further on the fragmented, elevated-heart-rate nights that follow hard exercise. No validation study identified here specifically tested deep-sleep staging accuracy in a post-exercise paradigm: the recovery-monitoring literature validates HRV output while assuming staging accuracy, and the staging-validation literature omits a post-exercise stressor—leaving this a specific, tractable target for Section 8’s study designs.
8. Testable Predictions and Minimum Study-Design Requirements
8.1. Rationale and Scope of Operationalization
Section 2, Section 3, Section 4, Section 5, Section 6 and Section 7 identified a consistent but domain-specific pattern: strong, in one case causally established, evidence for a nocturnal, SWS-locked autonomic gate in the early post-exercise reactivation window and during SWS itself, alongside explicit gaps in the human circuit-level mechanism, the pharmacological/transcranial manipulation literature, the SWS-specific exercise dose-response curve, age-by-sex-by-training interactions, the SWS-specificity of clinical impairment, and the post-exercise validity of wearable staging. This section translates that pattern into six falsifiable predictions, one per guiding research question (Section 1.3), with each specifying its effect direction, detection conditions, and falsification criterion; no composite index or diagnostic score is proposed. Two predictions (P1, P3) directly discriminate the SWS-gate model from a conventional time-since-exercise model, by predicting a sleep-stage-timing effect (P1) or a discrete, sub-24 h threshold (P3); P4 discriminates indirectly, attributing demographic variation to differential SWS access rather than age or sex per se; P2, P5, and P6 test boundary conditions and measurement validity.
8.2. Testable Predictions (P1–P6)
The six predictions below are organized into two tiers. P1 and P3 are framework-defining: a negative result for either directly weakens the central claim that SWS causally gates post-exercise autonomic recovery. P2 and P5 are boundary-condition predictions that bear on the gate construct indirectly, by testing whether its apparent direction or clinical relevance survives a specific alternative explanation. P4 and P6 are translational/measurement predictions: they test conditions necessary for applying the framework (demographic generalizability; wearable measurability) rather than the core gating mechanism itself, and a negative result for either would not by itself falsify the framework, only limit its current applied scope. The sample-size and effect-size cut-offs given for each prediction below are illustrative: they follow from the standardized-effect assumptions stated alongside each one and from analogous effect sizes already reported elsewhere in this review, rather than from a formal a priori power calculation conducted for the specific design proposed, and should be read as anchoring what a meaningfully informative test would look like rather than as a prescribed minimum sample size for a grant or protocol.
P1—A human SWS-specific causal circuit is detectable with simultaneous EEG and autonomic recording. If the rodent-derived circuit reviewed in Section 2 (NTS → caudal ventrolateral medulla → RVLM/NA) has a human functional analog, then the non-invasive manipulation of vagal-afferent traffic (for example, transcutaneous auricular vagus nerve stimulation) timed to SWS onset, with concurrent polysomnography and beat-to-beat autonomic recording, should alter subsequent HRV within the same night in a dose-dependent manner. A positive result would establish stage-dependent autonomic responsiveness to vagal-afferent stimulation—consistent with, but not proof of, a human functional analog of the rodent NTS → RVLM/NA circuit—and any such design should include sham stimulation and a matched-condition control (an equivalent stimulation dose delivered at another sleep stage or time-of-night) to rule out non-specific stimulation effects. Falsification: A well-powered, EEG-confirmed trial finding no relationship between the timing or intensity of vagal-afferent stimulation during SWS and subsequent HRV would indicate that the rodent circuitry reviewed in Section 2 does not generalize to an accessible human mechanism, at least via this route. Cut-off: this specific test would be judged unsupported if the 95% CI for the stimulation-dose × HRV-change interaction includes zero at N ≥ 63 per condition (powered at 80%, α = 0.05, two-sided, to detect a between-condition standardized effect of d ≥ 0.5, consistent with the magnitude of dose-dependent HF-HRV change already reported for acoustic enhancement in Section 3.1). This also discriminates the gate model from a purely time-since-exercise account: the latter makes no prediction that stimulation timed specifically to SWS, as opposed to an equivalent stimulation dose delivered at another sleep stage or a matched time-of-night, should alter HRV. A stronger and more direct test of the causal claim for post-exercise recovery specifically would combine this circuit-probe logic with an exercise challenge: applying (or withholding) SWS-timed vagal-afferent stimulation on nights following a standardized exercise bout and comparing the resulting recovery trajectory against a no-exercise control night. This combined design—manipulating SWS after exercise and tracking recovery—has not been attempted in the literature reviewed here and is proposed as the single most direct test of the framework’s central causal claim. Basis: [13,23,25,26,27,28,29].
P2—Autonomic direction under SWS manipulation depends on the route, not merely on SWS quantity. Because acoustic enhancement and sodium-oxybate-based pharmacological enhancement of SWS produce opposite apparent autonomic directions (Section 3), the deciding factor is predicted to be the manipulation route and its confounds (transient stimulus-locked activation for acoustic; sodium load for oxybate), rather than SWS quantity itself. A GABAergic SWS enhancer free of the sodium-load confound specifically (for example, tiagabine, though not necessarily free of other central, respiratory, or hemodynamic effects common to sleep-modifying pharmacology more broadly) is predicted to reproduce the parasympathetic-gain direction seen with acoustic enhancement, not the pressor direction seen with oxybate. Falsification: A trial of a pharmacological SWS enhancer free of the sodium-load confound specifically (though not necessarily free of other central, respiratory, or hemodynamic off-target effects) that reproduces the oxybate-like pressor direction would indicate that route-specific confounds are not sufficient to explain the current directional discrepancy and that a more direct SWS-dose relationship with sympathetic tone should be considered instead. Cut-off: this specific test would be judged unsupported if the 95% CI for the difference in blood-pressure change between the sodium-load-confound-free enhancer and oxybate excludes the acoustic-enhancement direction, or includes zero, at N ≥ 63 per arm (same assumptions as P1). Basis: [3,10,38,41,42,43,44].
P3—Exercise-to-sleep timing is associated with the magnitude of SWS-phase autonomic disruption, with a possible but not yet established threshold near four hours. Building on the finding that exercise bouts ending four or more hours before sleep onset show no detectable association with nocturnal HRV or heart rate [48], SWS-phase-specific autonomic disruption (not only whole-night HRV) is predicted to scale with a shorter exercise-to-sleep interval; whether this relationship is genuinely discontinuous near the four-hour mark or, at least as plausibly, continuous and nonlinear (better described by restricted cubic splines or a generalized additive model than by a fixed cut-off) should be evaluated with continuous-interval modeling before a discrete threshold is tested or assumed. Falsification: A polysomnography-confirmed, SWS-segmented study finding a continuous, threshold-free dose-response relationship between exercise-to-sleep interval and SWS-phase autonomic disruption, with no discernible inflection near the four-hour mark, would disconfirm the discrete-threshold form of this prediction, though it would not disconfirm dose-dependence itself. Cut-off: this specific test would be judged unsupported if the 95% CI for the timing-threshold interaction term (pre- vs post-4-h exercise-to-sleep interval) includes zero at N ≥ 98 per arm (powered at 80% to detect a smaller, d ≥ 0.4, threshold effect, appropriate given that the SWS-segmented signal is expected to be more variable epoch-to-epoch than the whole-night signal it is derived from). Basis: [46,47,48,49,50,51,52,53].
P4—Fitness-matching substantially attenuates apparent age and sex differences in post-exercise SWS-phase autonomic recovery. Consistent with the finding that fitness-matching eliminates the apparent male advantage in post-exercise heart-rate recovery [69] and that active older men show recovery indistinguishable from active young men [63], a study that fitness-matches (rather than merely age- or sex-matches) participants is predicted to find that most of the apparent age and sex variation in SWS-phase autonomic recovery is attenuated relative to unmatched comparisons. Falsification: A fitness-matched design that still finds a large, statistically robust residual age or sex effect on SWS-phase autonomic recovery after controlling for aerobic capacity would indicate that fitness is not the dominant confound in this domain, contrary to the pattern seen in the broader (non-SWS-segmented) heart-rate recovery literature. Cut-off: this specific test would be judged unsupported if a large residual age or sex effect (partial η2 ≥ 0.06, a conventional ‘medium’ effect) survives at N ≥ 44 per cell after statistical adjustment for peak oxygen uptake (powered at 80%, d ≥ 0.6, consistent with the size of the fitness-attributable shift already reported for heart-rate recovery in Section 5.4). Basis: [60,61,62,63,64,65,66,67,68,69,70,71,72].
P5—In patients with OSA, autonomic impairment during sleep tracks the hypoxic burden more closely than SWS quantity. Given that OSA-related sympathetic activation correlates with the apnea-hypopnea index and oxygen desaturation rather than with body weight [74], and that CPAP normalizes brainstem sympathoexcitatory activity, together with hypoxia correction [76], within-patient variation in nocturnal autonomic impairment is predicted to track hypoxic burden (apnea-hypopnea index, oxygen desaturation index) more closely than it tracks SWS quantity or percentage once the hypoxic burden is statistically accounted for. Falsification: A study finding that SWS quantity independently predicts nocturnal autonomic impairment in OSA after fully accounting for hypoxic burden would indicate a genuine SWS-specific contribution in this clinical population, distinct from the hypoxia-driven mechanism proposed as dominant in Section 6. Such a finding would refine rather than falsify the broader framework, since it would be compatible with independent or interactive contributions of hypoxia and SWS rather than requiring a single dominant determinant; analyses should accordingly test both additive and multiplicative (hypoxic-burden × SWS quantity) terms rather than treating SWS quantity as an isolated predictor. Cut-off: this specific test would be judged unsupported if SWS quantity retains a significant independent partial correlation with nocturnal autonomic impairment (r ≥ 0.3) after full adjustment for hypoxic burden, at N ≥ 85 (powered at 80% to detect r = 0.3). Basis: [73,74,75,76,77,78,79,80].
P6—Wearable SWS-staging accuracy degrades specifically on post-exercise nights relative to matched control nights. Because consumer devices infer SWS from heart rate, HRV, and movement features that are themselves altered by preceding exercise [91], and because no validation study identified in this review has directly tested this scenario (Section 7.4), within-subject comparison of device-classified SWS against polysomnography is predicted to show measurably lower staging agreement (lower kappa) on nights following moderate-to-hard exercise than on matched non-exercise control nights in the same individuals. Falsification: A within-subject, polysomnography-referenced comparison finding no meaningful difference in staging agreement between post-exercise and control nights would indicate that wearable SWS staging is more robust to exercise-induced physiological perturbation than the mechanism proposed here. Cut-off: this specific test would be judged unsupported if the between-night difference in staging kappa (post-exercise vs. control) is smaller than 0.10 with its 95% CI excluding a 0.15 minimum clinically/analytically meaningful difference, at N ≥ 30 within-subject night-pairs. Basis: [87,88,89,90,91,92,93,94,95,96,97,98].
8.3. Candidate Study Designs
The six predictions cluster into three testable groups. P1–P3 (circuit-level mechanism, manipulation route, timing threshold) share a single combined design (Box 2). P4 and P5 share a structurally similar confounding problem—fitness masking an apparent age/sex effect, with hypoxic burden masking an apparent SWS-specific effect—and are presented as parallel, confound-controlled designs (Box 3). P6, wearable validity post-exercise, requires its own dedicated polysomnography comparison (Box 4). None presupposes the others; each is independently fundable.
Table 6 maps each prediction to its corresponding design group and the primary outcome tested, before the detailed minimum requirements for each design are presented in Box 2, Box 3 and Box 4.
Box 2. Minimum Requirements for a Combined Mechanism-and-Dose-Response Study (P1–P3).
Core design—within-subject, repeated-measures design combining full polysomnography (to isolate SWS from whole-night sleep), beat-to-beat autonomic recording (ECG-derived HRV, and where feasible microneurography or continuous blood pressure), and a standardized, quantified exercise stimulus varied orthogonally in intensity, duration, and time-to-sleep-onset, with hydration status, energy intake, and pre-exercise baseline autonomic measures standardized or recorded as covariates.
Minimum exercise-arm structure—at least three time-to-sleep-onset conditions spanning the hypothesized four-hour threshold (e.g., ≤1 h, ≈2–3 h, ≥4 h before sleep onset), crossed with at least two intensity levels, directly testing P3 rather than relying on wearable-derived, non-EEG-confirmed staging as in the largest existing dataset [48].
Circuit-probe arm (optional extension for P1)—addition of a non-invasive vagal-afferent stimulation condition timed to polysomnographically confirmed SWS onset, powered to detect a dose-dependent HRV effect, with stimulation-related arousals identified and reported as an intervention-fidelity check, and with a next-day follow-up measurement to capture whether any acute within-night HRV effect persists into the daytime recovery window.
Minimum reporting—SWS percentage and continuity metrics (not only total sleep time), exact stimulus-to-sleep timing, and pre-registered autonomic endpoints for the early-reactivation, nocturnal-SWS, and intermediate windows analyzed separately, given this literature’s demonstrated window-dependence; a stimulus-timing control condition able to separate the auditory-activation and SWS-mediated accounts (Section 3.1); and concurrent measurement of at least one candidate common-cause variable (core temperature, cortisol, catecholamines) to permit adjustment for the common-cause alternative (Section An Alternative, Common-Cause Account). The primary outcome for the combined post-exercise design should be specified as the multi-window recovery trajectory described above, not a single early- or SWS-window HRV value in isolation, consistent with how a positive, negative, or equivocal result should be interpreted (Section 8.4).
Box 3 addresses the two structurally parallel confounds identified in Section 5 and Section 6—fitness potentially masking the apparent age/sex effect, hypoxic burden potentially masking the apparent SWS-specific clinical effect—via confounder-controlled rather than simple group comparisons.
Box 3. Minimum Requirements for a Fitness-Matched Age/Sex Design (P4) and a Hypoxia-Controlled Clinical Design (P5).
P4 design—factorial recruitment across age (young vs. older) and sex (male vs. female), with participants matched on directly measured aerobic capacity (peak oxygen uptake) rather than on age or training history alone, and with SWS-segmented autonomic recovery as the primary outcome following a standardized exercise stimulus.
P5 design—within-patient, repeated-night observational or CPAP-titration design in OSA, with simultaneous polysomnographic SWS quantification, continuous hypoxic-burden metrics (apnea-hypopnea index, oxygen desaturation index, time below a defined saturation threshold), and beat-to-beat autonomic recording, analyzed with hypoxic burden and SWS quantity entered as independent predictors of nocturnal autonomic impairment.
Shared minimum reporting—explicit statistical control for the confound each design isolates (aerobic capacity for P4; hypoxic burden for P5), since both predictions’ contribution is separating a plausible confound from a genuine effect, not re-demonstrating the confounded association. Where feasible, designs should also report a candidate common-cause measure (evening core temperature or cortisol for P4; hypoxic burden already serves this role for P5).
Box 4. Minimum Requirements for a Post-Exercise Wearable Validation Study (P6).
Core design—within-subject comparison of at least one validated consumer wearable or nearable device against simultaneous polysomnography, across matched post-exercise and non-exercise control nights in the same individuals, with exercise dose standardized and quantified as in Box 2.
Primary outcome—epoch-level staging agreement (kappa) for SWS specifically, compared between post-exercise and control nights, powered to detect the degradation proposed in P6 rather than only overall night-level agreement.
Secondary outcome—device-derived nocturnal HRV accuracy under the same conditions, to determine whether HRV measurement validity (Section 7.1) degrades alongside, or independently of, staging accuracy on post-exercise nights.
This final design addresses a narrower, purely methodological question left open by Section 7: whether the wearable technology used to operationalize the first five predictions remains valid under the specific conditions they require.
8.4. Falsification Criteria, Consolidated
Taken together, the framework would be substantially weakened by any of the following: (i) a well-powered, EEG-confirmed vagal-afferent stimulation study finding no dose-dependent HRV effect timed to SWS, undermining the proposed human relevance of the rodent circuitry (Section 2); (ii) a pharmacological SWS enhancer free of the sodium-load confound reproducing a pressor rather than parasympathetic-gain direction, undermining P2’s route-specific attribution; (iii) an EEG-segmented dose-response study finding no association whatsoever between exercise-to-sleep timing and SWS-phase autonomic disruption, undermining P3’s timing-association claim entirely; (iv) a fitness-matched design retaining a large residual age or sex effect, undermining P4’s fitness attribution; (v) an SWS-quantity effect on OSA impairment surviving full control for hypoxic burden, which would refine rather than overturn P5’s hypoxia-primacy account by indicating an independent or interactive SWS contribution; (vi) no measurable staging-accuracy degradation on post-exercise versus control nights, undermining P6’s technological limitation. None would necessarily invalidate the broader distinction, established in Section 2 and Section 3, between SWS as a correlate of autonomic state and SWS as a causal gate for it; they would specifically narrow or revise the corresponding claim.
9. Discussion and Conclusions
9.1. Synthesis: Revisiting the Guiding Research Questions
The preceding sections developed and operationalized a conceptual framework addressing the six guiding questions introduced in Section 1.3. This section synthesizes the evidence for each question.
Regarding Q1 (circuit-level mechanism), a plausible multi-nodal brainstem circuit (NTS, RVLM/C1, NA cardiac-vagal neurons) is well characterized in rodents but remains unestablished as an SWS-specific causal pathway in humans, where evidence stays correlational (HRV and functional-connectivity studies) [1,2,13,16,17,18,19,23,24,25,26,27,28,29]; this species gap is the single most consequential limitation of Section 2’s mechanistic account.
Regarding Q2 (causal manipulations beyond acoustic enhancement), the evidence is strongest for deprivation/suppression paradigms (higher nocturnal blood pressure and blunted dipping [12]; reduced insulin sensitivity with an inferred autonomic mechanism [11]) and weakest for pharmacological and transcranial approaches, where a sodium-load confound reverses the apparent direction of sodium oxybate [41,42,43] and autonomic endpoints are largely untested elsewhere [44,45]; closed-loop acoustic enhancement remains the cleanest tool, with cross-study confirmation of its parasympathetic-gain direction [3,10].
Regarding Q3 (exercise dose-response), disruption scales with exercise magnitude but dissociates by intensity, duration, and timing; the most consistent single finding—one observational, non-EEG-confirmed wearable dataset (Section 4.1)—indicates no detectable association beyond roughly four hours pre-sleep [46,47,48,49], while genuinely SWS-segmented dose-response data remain sparse [50,51,52,53], and no study has combined dose, timing, and training status in one design [54,55,56,57,58,59].
Regarding Q4 (age and sex), aging degrades the coupling itself [60,61], but the associated slowing of recovery is substantially attenuated by fitness rather than age per se [62,63]; sex differences in sleep architecture are well documented [64,65,66,67], but post-exercise sex differences are contested and likewise largely explained by fitness rather than circulating hormones [68,69,70,71,72].
Regarding Q5 (clinical populations), evidence is strong and convergent for OSA, where impairment is well established and substantially reversed by CPAP, with reversibility on treatment withdrawal the clearest causal evidence in this review [73,74,75,76,77,78,79,80]—though the mechanism is predominantly intermittent hypoxia rather than SWS loss per se, limiting its direct bearing on the gating framework; evidence for insomnia and pure fragmentation is considerably weaker and inconsistent [81,82,83,84,85,86].
Regarding Q6 (wearable technology), consumer devices are genuinely valid for night-average HRV [87,88] but only fair-to-moderate for SWS staging [89,90,91,92,93,94,95], with no study directly testing staging accuracy in a post-exercise paradigm despite mechanistic reasons to expect degradation [91]; recovery-monitoring applications relying on HRV rather than precise staging appear to sidestep this limitation [96,97,98].
9.2. Implications for Practice
Although this review is conceptual rather than interventional, two provisional implications follow from the evidence synthesized above. First, post-exercise autonomic monitoring that relies on nocturnal or four-hour HRV, rather than precise SWS-stage classification, is better supported by the current validation evidence and should be preferred in applied recovery-monitoring contexts using consumer devices (Section 7). Second, the timing association identified in Section 4 (bouts ending approximately four or more hours before sleep onset showing no detectable nocturnal autonomic association in one large observational wearable dataset) is a plausible observational association rather than a scheduling heuristic and should not yet be treated as an actionable or validated threshold: it rests on a single dataset, non-EEG-confirmed sleep staging, no randomization, and evident confounding by who exercises late and why (late exercisers may differ systematically in chronotype, occupational schedule, or training load). We defer any practical recommendation until this association is tested directly in a polysomnography-confirmed, randomized design (P3, Section 8). Both implications should be treated as provisional pending the empirical tests proposed in Section 8 below.
9.3. Limitations
First, literature was identified using a targeted, question-driven strategy via Elicit, supplemented by a partial citation-network verification step via Scite, rather than a PRISMA-based systematic review, as detailed in the Literature Review Strategy and Scope Section. No formal risk-of-bias assessment was applied, and the evidence base included a number of conference and meeting abstracts, identified as such at first mention, whose findings should be weighted accordingly. Table 3 and Table 5 in particular rest on Elicit-only discovery and have not been cross-checked against a second bibliographic database.
Second, the circuit-level mechanism proposed in Section 2 rests predominantly on rodent evidence; the corresponding human causal circuit remains, at present, inferred rather than demonstrated, as explicitly stated in Section 2.6.
Third, independent citation-network verification (Scite), attempted for four foundational sources, produced a mixed and only partially informative outcome—ranging from genuine cross-confirmation to an unresolved indexing failure—reported in full in File S1; this should be read as a transparent account of a partially successful verification effort, not as a blanket validation of the sources involved.
Fourth, the OSA literature reviewed in Section 6, while the strongest clinical evidence available, reflects a mechanism (intermittent hypoxia and repetitive arousal) that is only partially specific to SWS loss, limiting the directness with which it can be read as confirming the SWS-specific gating framework proposed in this review.
Fifth, a common-cause alternative—in which an upstream perturbation shared by exercise and sleep (core temperature, catecholamines, cortisol, substrate, and fluid status) independently drives both the SWS change and the autonomic change, without SWS gating anything—is not excluded by the correlational evidence reviewed in Section 4, Section 5 and Section 6 and is only partially addressed by the causal manipulation evidence in Section 3 and by P1 in Section 8 (Section An Alternative, Common-Cause Account). Distinguishing the two accounts more completely is a priority for the designs proposed in Section 8, several of which (Box 2 and Box 3) now include explicit measurement or control of core temperature, catecholamines, or cortisol as candidate common-cause variables.
9.4. Conclusions
This review aimed to synthesize the fragmented literature on the relationship between slow-wave sleep and post-exercise cardiac autonomic recovery into a single conceptual framework. Three conclusions follow from the synthesis presented here.
First, heart rate variability is not a passive overnight average but tracks sleep stage in real time, with the strongest and most causally grounded evidence indicating that SWS specifically, rather than sleep in general, carries the parasympathetic-dominant, sympathetic-withdrawal signature associated with cardiovascular recovery.
Second, this SWS-autonomic coupling is hypothesized to function as a graded, window-specific gate on post-exercise recovery rather than as a uniform requirement: the strongest evidence concentrates in the early post-exercise reactivation phase and the nocturnal-SWS period itself, with considerably weaker support across the intermediate, multi-hour recovery window, and with domain-specific boundary conditions—exercise timing, training status, age, sex, and the presence of hypoxic sleep disorders—each modulating whether and how strongly the gate operates.
Third, the circuit-level mechanism underlying this coupling remains substantially inferred from rodent studies rather than being demonstrated in humans, and several evidentiary gaps—the pharmacological and transcranial manipulation literature, the SWS-segmented exercise dose-response curve, the integrative age-by-sex-by-fitness design, and the post-exercise validity of wearable SWS staging—define clear priorities for future research rather than settled questions.
Taken together, the framework proposed in this review—slow-wave sleep as a candidate physiological gate for post-exercise cardiac autonomic recovery—is offered as a testable, hypothesis-generating framework, not an established mechanism. Its value will be determined by whether the six falsifiable predictions and associated study designs proposed in Section 8 are supported, weakened, or shown to be inconsistent with the evidence by future empirical work.
The current evidence therefore supports an association between sleep stage and cardiac autonomic regulation, together with causal evidence that selected sleep-modifying interventions can alter nocturnal cardiovascular and HRV-derived outcomes (Section 3) [3,10,11,12]. However, the hypothesis that slow-wave sleep causally governs post-exercise cardiac autonomic recovery specifically has not yet been directly tested (Section 8, P1). Exercise-related nocturnal HRV changes may reflect SWS-dependent processes, shared upstream perturbations such as thermoregulatory, metabolic, endocrine, or respiratory factors (Section An Alternative, Common-Cause Account), or a combination of these mechanisms. Slow-wave sleep should therefore be presented as a plausible moderator and candidate mechanistic target for future work rather than as an established physiological gate. A definitive test requires randomized manipulation of SWS following standardized exercise, with EEG-confirmed sleep staging and integrated measurement of ECG, respiration, blood pressure, sleep continuity, and key common-cause variables—the combined design outlined in Box 2.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/physiologia6040056/s1, File S1: Full Elicit and PubMed search strings, search dates, and per-query record counts; File S2: Completed SANRA (Scale for the Assessment of Narrative Review Articles) checklist; File S3: Per-study evidence table (citation, species/population, design type, key finding, and evidentiary tier) and definition of the simplified evidentiary-strength tiers, for all 98 cited references.
Author Contributions
Conceptualization, methodology, validation, formal analysis, investigation, data curation, writing—original draft preparation, writing—review and editing, visualization, supervision: T.D., A.E.S. and A.V. All authors have read and agreed to the published version of the manuscript.
Funding
This review received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Acknowledgments
During the preparation of this manuscript, the authors used Elicit for literature identification, Scite for citation-network verification, and Paperpal (Cactus Communications, Mumbai, India) for English translation, grammar improvement, and proofreading support. The authors have carefully reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AI | Artificial Intelligence |
| CPAP | Continuous Positive Airway Pressure |
| ECG | Electrocardiography/Electrocardiogram |
| EEG | Electroencephalography/Electroencephalogram |
| GABA | Gamma-Aminobutyric Acid |
| HRV | Heart-Rate Variability |
| LPGi | Lateral Paragigantocellular Nucleus |
| MSNA | Muscle Sympathetic Nerve Activity |
| N3 | Stage 3 Non-Rapid-Eye-Movement Sleep (a Slow-Wave-Sleep Stage) |
| NA | Nucleus Ambiguus |
| NREM | Non-Rapid-Eye-Movement (Sleep) |
| NTS | Nucleus Tractus Solitarius (Nucleus of the Solitary Tract) |
| OSA | Obstructive Sleep Apnea |
| pNN50 | Percentage of Successive NN Intervals Differing by More Than 50 ms |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| REM | Rapid-Eye-Movement (Sleep) |
| RVLM | Rostral Ventrolateral Medulla |
| SWS | Slow-Wave Sleep |
| VO2max/VO2peak | Maximal/Peak Oxygen Uptake |
References
- Berlad, I.; Shlitner, A.; Ben-Haim, S.; Lavie, P. Power spectrum analysis and heart rate variability in Stage 4 and REM sleep: Evidence for state-specific changes in autonomic dominance. J. Sleep Res. 1993, 2, 88–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kong, S.D.X.; Gordon, C.J.; Hoyos, C.M.; Wassing, R.; D’Rozario, A.; Mowszowski, L.; Ireland, C.; Palmer, J.R.; Grunstein, R.R.; Shine, J.M.; et al. Heart rate variability during slow wave sleep is linked to functional connectivity in the central autonomic network. Brain Commun. 2023, 5, fcad129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grimaldi, D.; Papalambros, N.A.; Reid, K.J.; Abbott, S.M.; Malkani, R.G.; Gendy, M.; Iwanaszko, M.; Braun, R.I.; Sanchez, D.J.; Paller, K.A.; et al. Strengthening sleep–autonomic interaction via acoustic enhancement of slow oscillations. Sleep 2019, 42, zsz036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hani, A.H.; Laursen, P.B.; Said, A.; Martin, B. Nocturnal Heart Rate Variability Following Supramaximal Intermittent Exercise. Int. J. Sports Physiol. Perform. 2009, 4, 435–447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buchheit, M.; Simon, C.; Piquard, F.; Ehrhart, J.; Brandenberger, G. Effects of increased training load on vagal-related indexes of heart rate variability: A novel sleep approach. Am. J. Physiol. Heart Circ. Physiol. 2004, 287, H2813–H2818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dupuy, O.; Bérard, L.; Audiffren, M.; Bosquet, L. Night and postexercise cardiac autonomic control in functional overreaching. Appl. Physiol. Nutr. Metab. 2013, 38, 200–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schlagintweit, J.; Laharnar, N.; Glos, M.; Zemann, M.; Demin, A.V.; Lederer, K.; Penzel, T.; Fietze, I. Effects of sleep fragmentation and partial sleep restriction on heart rate variability during night. Sci. Rep. 2023, 13, 6202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stanley, J.; Peake, J.M.; Buchheit, M. Cardiac Parasympathetic Reactivation Following Exercise: Implications for Training Prescription. Sports Med. 2013, 43, 1259–1277. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papadakis, Z.; Forsse, J.S.; Peterson, M.N. Effects of High-Intensity Interval Exercise and Acute Partial Sleep Deprivation on Cardiac Autonomic Modulation. Res. Q. Exerc. Sport 2021, 92, 824–842. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Diep, C.; Ftouni, S.; Drummond, S.P.A.; Garcia-Molina, G.; Anderson, C. Heart rate variability increases following automated acoustic slow wave sleep enhancement. J. Sleep Res. 2022, 31, e13545. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tasali, E.; Leproult, R.; Ehrmann, D.A.; Van Cauter, E. Slow-wave sleep and the risk of type 2 diabetes in humans. Proc. Natl. Acad. Sci. USA 2008, 105, 1044–1049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sayk, F.; Teckentrup, C.; Becker, C.; Heutling, D.; Wellhöner, P.; Lehnert, H.; Dodt, C. Effects of selective slow-wave sleep deprivation on nocturnal blood pressure dipping and daytime blood pressure regulation. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2010, 298, R191–R197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yao, Y.; Barger, Z.; Saffari Doost, M.; Tso, C.F.; Darmohray, D.; Silverman, D.; Liu, D.; Ma, C.; Cetin, A.; Yao, S.; et al. Cardiovascular baroreflex circuit moonlights in sleep control. Neuron 2022, 110, 3986–3999.e6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, S.H.; Kwon, H.B.; Jin, H.W.; Yoon, H.; Lee, M.H.; Lee, Y.J.; Park, K.S. Weak closed-loop vibrational stimulation improves the depth of slow-wave sleep and declarative memory consolidation. Sleep 2021, 44, zsaa285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kwon, H.B.; Jeong, J.; Choi, B.; Park, K.S.; Joo, E.Y.; Yoon, H. Effect of closed-loop vibration stimulation on sleep quality for poor sleepers. Front. Neurosci. 2024, 18, 1456237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Zambotti, M.; Trinder, J.; Silvani, A.; Colrain, I.M.; Baker, F.C. Dynamic coupling between the central and autonomic nervous systems during sleep: A review. Neurosci. Biobehav. Rev. 2018, 90, 84–103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Eekelen, A.P.J.; Varkevisser, M.; Kerkhof, G.A. Cardiac Autonomic Activity During Human Sleep: Analysis of Sleep Stages and Sleep Cycles. Biol. Rhythm Res. 2003, 34, 493–502. [Google Scholar] [CrossRef] [Scilit]
- Yang, C.C.H.; Lai, C.-W.; Lai, H.Y.; Kuo, T.B.J. Relationship between electroencephalogram slow-wave magnitude and heart rate variability during sleep in humans. Neurosci. Lett. 2002, 329, 213–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silvani, A.; Dampney, R.A.L. Central control of cardiovascular function during sleep. Am. J. Physiol. Heart Circ. Physiol. 2013, 305, H1683–H1692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Billman, G.E. The LF/HF ratio does not accurately measure cardiac sympatho-vagal balance. Front. Physiol. 2013, 4, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heathers, J.A.J. Everything Hertz: Methodological issues in short-term frequency-domain HRV. Front. Physiol. 2014, 5, 177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reyes del Paso, G.A.; Langewitz, W.; Mulder, L.J.M.; van Roon, A.; Duschek, S. The utility of low frequency heart rate variability as an index of sympathetic cardiac tone: A review with emphasis on a reanalysis of previous studies. Psychophysiology 2013, 50, 477–487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, F.; Lv, Y.; Shi, F.; Li, S.; Guo, Z.; Yang, Y.; Chen, J.; Lu, J. The nucleus of solitary tract (NTS) synchronizes sleep-wake-state-dependent cortical activity through the parabrachial nucleus (PB) in rat. Sleep Med. 2024, 122, 45–50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Richard, C.A.; Rector, D.M.; Macey, P.M.; Ali, N.; Harper, R.M. Late-developing rostral ventrolateral medullary surface responses to cardiovascular challenges during sleep. Brain Res. 2003, 985, 65–77. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
- Souza, G.M.; Stornetta, D.S.; Abbott, S.B. The activation of C1 neurons during REM sleep is dependent on the arterial baroreflex. FASEB J. 2022, 36, R6010. [Google Scholar] [CrossRef] [Scilit]
- Benarroch, E.E. Interface between the autonomic and arousal systems. Auton. Neurosci. 2015, 192, 38. [Google Scholar] [CrossRef] [Scilit]
- Stettner, G.M.; Lei, Y.; Herr, K.B.; Kubin, L. Evidence That Adrenergic Ventrolateral Medullary Cells Are Activated whereas Precerebellar Lateral Reticular Nucleus Neurons Are Suppressed during REM Sleep. PLoS ONE 2013, 8, e62410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dergacheva, O.; Weigand, L.A.; Dyavanapalli, J.; Mares, J.; Wang, X.; Mendelowitz, D. Function and modulation of premotor brainstem parasympathetic cardiac neurons that control heart rate by hypoxia-, sleep-, and sleep-related diseases including obstructive sleep apnea. Prog. Brain Res. 2014, 212, 39–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dergacheva, O.; Wang, X.; Lovett-Barr, M.R.; Jameson, H.; Mendelowitz, D. The Lateral Paragigantocellular Nucleus Modulates Parasympathetic Cardiac Neurons: A Mechanism for Rapid Eye Movement Sleep-Dependent Changes in Heart Rate. J. Neurophysiol. 2010, 104, 685–694. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fatt, S.J.; Beilharz, J.E.; Joubert, M.; Wilson, C.; Lloyd, A.R.; Vollmer-Conna, U.; Cvejic, E. Parasympathetic activity is reduced during slow-wave sleep, but not resting wakefulness, in patients with chronic fatigue syndrome. J. Clin. Sleep Med. 2020, 16, 19–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Benarroch, E.E. Control of the cardiovascular and respiratory systems during sleep. Auton. Neurosci. 2019, 218, 54–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Porkka-Heiskanen, T.; Kalinchuk, A.V. Adenosine, energy metabolism and sleep homeostasis. Sleep Med. Rev. 2011, 15, 123–135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalinchuk, A.V.; McCarley, R.W.; Stenberg, D.; Porkka-Heiskanen, T.; Basheer, R. The role of cholinergic basal forebrain neurons in adenosine-mediated homeostatic control of sleep: Lessons from 192 IgG-saporin lesions. Neuroscience 2008, 157, 238–253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bjorness, T.E.; Dale, N.; Mettlach, G.; Sonneborn, A.; Sahin, B.; Fienberg, A.A.; Yanagisawa, M.; Bibb, J.A.; Greene, R.W. An Adenosine-Mediated Glial-Neuronal Circuit for Homeostatic Sleep. J. Neurosci. 2016, 36, 3709–3721. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tank, J.; Diedrich, A.; Hale, N.; Niaz, F.E.; Furlan, R.; Robertson, R.M.; Mosqueda-Garcia, R. Relationship between blood pressure, sleep K-complexes, and muscle sympathetic nerve activity in humans. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2003, 285, R208–R214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenlund, I.M.; Smoot, C.A.; Carter, J.R. Sex differences in blood pressure responsiveness to spontaneous K-complexes during stage II sleep. J. Appl. Physiol. 2020, 130, 491–497. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Diep, C.; Ftouni, S.; Manousakis, J.E.; Nicholas, C.L.; Drummond, S.P.A.; Anderson, C. Acoustic slow wave sleep enhancement via a novel, automated device improves executive function in middle-aged men. Sleep 2020, 43, zsz197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huwiler, S.; Carro-Domínguez, M.; Stich, F.; Sala, R.; Aziri, F.; Trippel, A.; Ryf, T.; Markendorf, S.; Niederseer, D.; Bohm, P.; et al. Slow waves during deep sleep support cardiac function. Curr. Issues Sport Sci. 2024, 9, 004. [Google Scholar] [CrossRef] [Scilit]
- Silvani, A.; Bojic, T.; Cianci, T.; Franzini, C.; Lodi, C.A.; Predieri, S.; Zoccoli, G.; Lenzi, P. Effects of Acoustic Stimulation on Cardiovascular Regulation During Sleep. Sleep 2003, 26, 201–205. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
- Ukraintseva, Y.V.; Liaukovich, K.M.; Saltykov, K.A.; Belov, D.A.; Nizhnik, A.N. Selective slow-wave sleep suppression affects glucose tolerance and melatonin secretion. The role of sleep architecture. Sleep Med. 2020, 67, 171–183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giannoccaro, M.P.; Donadio, V.; Plazzi, G.; Pizza, F.; Vandi, S.; Leta, V.; Liguori, R. Sympathetic and cardiovascular changes induced by Sodium oxybate treatment in patients with narcolepsy and cataplexy. Clin. Neurophysiol. 2013, 124, e218. [Google Scholar] [CrossRef] [Scilit]
- Ben-Joseph, R.H.; Somers, V.K.; Black, J.; D’Agostino, R.B., Jr.; Davis, M.; Macfadden, W.; Mues, K.E.; Jackson, C.; Ni, W.; Cook, M.N.; et al. Increased Risk of New-Onset Hypertension in Patients with Narcolepsy Initiating Sodium Oxybate: A Real-World Study. Mayo Clin. Proc. 2024, 99, 1710–1721. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, W.B.; Kovacs, R.J.; Alexander, J.K.; Baranak, C.; Nichols, D.A.; Fuller, D.S.; Dai, J.; Whalen, M.; Ajayi, A.; Hutchinson, B.; et al. Effects of High- Versus Low-Sodium Oxybate on Blood Pressure in Patients with Narcolepsy. Hypertension 2025, 82, 2162–2171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taranto-Montemurro, L.; Sands, S.A.; Edwards, B.A.; Azarbarzin, A.; Marques, M.; de Melo, C.M.; Eckert, D.J.; White, D.P.; Wellman, A. Effects of Tiagabine on Slow Wave Sleep and Arousal Threshold in Patients with Obstructive Sleep Apnea. Sleep 2017, 40, zsw052. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saebipour, M.R.; Joghataei, M.T.; Yoonessi, A.; Sadeghniiat-Haghighi, K.; Khalighinejad, N.; Khademi, S. Slow oscillating transcranial direct current stimulation during sleep has a sleep-stabilizing effect in chronic insomnia: A pilot study. J. Sleep Res. 2015, 24, 518–525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hynynen, E.; Vesterinen, V.; Rusko, H.; Nummela, A. Effects of Moderate and Heavy Endurance Exercise on Nocturnal HRV. Int. J. Sports Med. 2010, 31, 428–432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myllymäki, T.; Rusko, H.; Sysväoja, H.; Juuti, T.; Kinnunen, M.L.; Kyröläinen, H. Effects of exercise intensity and duration on nocturnal heart rate variability and sleep quality. Eur. J. Appl. Physiol. 2012, 112, 801–809. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leota, J.; Presby, D.M.; Le, F.; Czeisler, M.E.; Mascaro, L.; Capodilupo, E.R.; Wiley, J.F.; Drummond, S.P.; Rajaratnam, S.M.; Facer-Childs, E.R. Dose-response relationship between evening exercise and sleep. Nat. Commun. 2025, 16, 3297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamanaka, Y.; Hashimoto, S.; Takasu, N.N.; Tanahashi, Y.; Nishide, S.Y.; Honma, S.; Honma, K.I. Morning and evening physical exercise differentially regulate the autonomic nervous system during nocturnal sleep in humans. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2015, 309, R1112–R1121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bulckaert, A.; Exadaktylos, V.; Haex, B.; De Valck, E.; Verbraecken, J.; Berckmans, D. Elevated Variance in Heart Rate During Slow-Wave Sleep After Late-Night Physical Activity. Chronobiol. Int. 2011, 28, 282–284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kobayashi, M.; Kasahara, N.; Imai, A.; Goto, K. Partial reduction of parasympathetic nerve activity during sleep after endurance exercise under hypoxic conditions. Phys. Act. Nutr. 2025, 29, 35–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myllymäki, T.; Kyröläinen, H.; Savolainen, K.; Hokka, L.; Jakonen, R.; Juuti, T.; Martinmäki, K.; Kaartinen, J.; Kinnunen, M.-L.; Rusko, H. Effects of vigorous late-night exercise on sleep quality and cardiac autonomic activity. J. Sleep Res. 2011, 20, 146–153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramos-Campo, D.J.; Ávila-Gandia, V.; Luque, A.J.; Rubio-Arias, J.Á. Effects of hour of training and exercise intensity on nocturnal autonomic modulation and sleep quality of amateur ultra-endurance runners. Physiol. Behav. 2019, 198, 134–139. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldsmith, R.; Bigger, J., Jr.; Steinman, R.; Fleiss, J.L. Comparison of 24-hour parasympathetic activity in endurance-trained and untrained young men. J. Am. Coll. Cardiol. 1992, 20, 552–558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Casanova-Lizón, A.; Manresa-Rocamora, A.; Flatt, A.A.; Sarabia, J.M.; Moya-Ramón, M. Does Exercise Training Improve Cardiac-Parasympathetic Nervous System Activity in Sedentary People? A Systematic Review with Meta-Analysis. Int. J. Environ. Res. Public Health 2022, 19, 13899. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costa, J.A.; Brito, J.; Nakamura, F.Y.; Oliveira, E.M.; Rebelo, A.N. Effects of Late-Night Training on “Slow-Wave Sleep Episode” and Hour-by-Hour-Derived Nocturnal Cardiac Autonomic Activity in Female Soccer Players. Int. J. Sports Physiol. Perform. 2018, 13, 638–644. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thomas, C.; Jones, H.; Whitworth-Turner, C.; Louis, J. High-intensity exercise in the evening does not disrupt sleep in endurance runners. Eur. J. Appl. Physiol. 2020, 120, 359–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yuda, E.; Moriyama, Y.; Mori, T.; Yoshida, Y.; Kawahara, M.; Hayano, J. Acute effects of endurance exercise on nocturnal autonomic functions in sedentary subjects: A pilot study. J. Exerc. Rehabil. 2018, 14, 113–117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rusko, H.; Konttinen, N.; Uusitalo, A.; Hynynen, E. Heart Rate Variability during Night Sleep and after Awakening in Overtrained Athletes. Med. Sci. Sports Exerc. 2006, 38, 313–317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brandenberger, G.; Viola, A.U.; Ehrhart, J.; Charloux, A.; Geny, B.; Piquard, F.; Simon, C. Age-related changes in cardiac autonomic control during sleep. J. Sleep Res. 2003, 12, 173–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, P.; Naji, M.; Sattari, N.; Whitehurst, L.N.; Mednick, S.C. 0063 Age Related Changes in Central Autonomic Couplings During Sleep. Sleep 2020, 43, A26. [Google Scholar] [CrossRef] [Scilit]
- Beltrame, T.; Catai, A.M.; Rebelo, A.C.; Tamburus, N.Y.; Zuttin, R.S.; Takahashi, A.C.; Da Silva, E. Associations Between Heart Rate Recovery Dynamics with Estradiol Levels in 20 to 60 Year-Old Sedentary Women. Front. Physiol. 2018, 9, 360133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marôco, J.L.; Pinto, M.; Laranjo, S.; Santa-Clara, H.; Fernhall, B.; Melo, X. Cardiovagal Modulation in Young and Older Male Adults Following Acute Aerobic Exercise. Int. J. Sports Med. 2022, 43, 931–940. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baker, F.C.; Yuksel, D.; de Zambotti, M. Sex differences in sleep. In Encyclopedia of Sleep and Circadian Rhythms, 2nd ed.; Kushida, C.A., Ed.; Academic Press: Cambridge, MA, USA, 2023; pp. 138–145. [Google Scholar] [CrossRef] [Scilit]
- Ehlers, C.; Kupfer, D. Slow-wave sleep: Do young adult men and women age differently? J. Sleep Res. 1997, 6, 211–215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valladares, E.M.; Eljammal, S.M.; Motivala, S.; Ehlers, C.L.; Irwin, M.R. Sex differences in cardiac sympathovagal balance and vagal tone during nocturnal sleep. Sleep Med. 2008, 9, 310–316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Zambotti, M.; Javitz, H.; Franzen, P.L.; Brumback, T.; Clark, D.B.; Colrain, I.M.; Baker, F.C. Sex- and Age-Dependent Differences in Autonomic Nervous System Functioning in Adolescents. J. Adolesc. Health 2018, 62, 184–190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, C.-H.; Wang, J.-S. Gender-related Difference in Cardiac Autonomic Nervous Activity during Post-Exercise Recovery. FASEB J. 2016, 30, 1291.6. [Google Scholar] [CrossRef] [Scilit]
- Kappus, R.M.; Ranadive, S.M.; Yan, H.; Lane-Cordova, A.D.; Cook, M.D.; Sun, P.; Harvey, I.S.; Wilund, K.R.; Woods, J.A.; Fernhall, B. Sex differences in autonomic function following maximal exercise. Biol. Sex Differ. 2015, 6, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Richey, R.E.; Miner, J.A.; Miner, J.C.; Brunt, V.E.; Kaplan, P.F.; Halliwill, J.R.; Minson, C.T. Exogenous estradiol increases cardiovagal baroreflex sensitivity during a hypertensive stimulus in premenopausal young women. Am. J. Physiol. Heart Circ. Physiol. 2025, 329, H439–H449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramesh, S.; James, M.T.; Holroyd-Leduc, J.M.; Wilton, S.B.; Sola, D.Y.; Ahmed, S.B. Heart rate variability as a function of menopausal status, menstrual cycle phase, and estradiol level. Physiol. Rep. 2022, 10, e15298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gonzales, J.U.; Elavsky, S.; Cipryan, L.; Jandackova, V.; Burda, M.; Jandacka, D. Influence of sleep duration and sex on age-related differences in heart rate variability: Findings from program 4 of the HAIE study. Sleep Med. 2023, 106, 69–77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Somers, V.K.; Dyken, M.E.; Clary, M.P.; Abboud, F.M. Sympathetic Neural Mechanisms in Obstructive Sleep Apnea. Am. J. Hypertens. 1996, 9, 180A. [Google Scholar] [CrossRef] [Scilit]
- Grassi, G.; Mancia, G.; Corrao, G.; Seravalle, G.; Bonzani, M.; Biffi, A.; Quarti-Trevano, F. Neuroadrenergic activation in obstructive sleep apnea syndrome: A systematic review and meta-analysis. J. Hypertens. 2021, 39, 2281–2289, Erratum in J. Hypertens. 2021, 40, 196. https://doi.org/10.1097/HJH.0000000000003042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Narkiewicz, K.; Kato, M.; Phillips, B.G.; Pesek, C.A.; Davison, D.E.; Somers, V.K. Nocturnal Continuous Positive Airway Pressure Decreases Daytime Sympathetic Traffic in Obstructive Sleep Apnea. Circulation 1999, 100, 2332–2335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lundblad, L.C.; Fatouleh, R.H.; McKenzie, D.K.; Macefield, V.G.; Henderson, L.A. Brainstem activity changes associated with restored sympathetic drive following CPAP treatment in OSA subjects: A longitudinal investigation. J. Neurophysiol. 2015, 114, 893–901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonsignore, M.R.; Parati, G.; Insalaco, G.; Marrone, O.; Castiglioni, P.; Romano, S.; Di Rienzo, M.; Mancia, G.; Bonsignore, G. Continuous Positive Airway Pressure Treatment Improves Baroreflex Control of Heart Rate during Sleep in Severe Obstructive Sleep Apnea Syndrome. Am. J. Respir. Crit. Care Med. 2002, 166, 279–286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akashiba, T.; Minemura, H.; Yamamoto, H.; Kosaka, N.; Saito, O.; Horie, T. Nasal Continuous Positive Airway Pressure Changes Blood Pressure “Non-dippers” to “Dippers” in Patients with Obstructive Sleep Apnea. Sleep 1999, 22, 849–853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kufoy, E.; Palma, J.A.; Lopez, J.; Alegre, M.; Urrestarazu, E.; Artieda, J.; Iriarte, J. Changes in the Heart Rate Variability in Patients with Obstructive Sleep Apnea and Its Response to Acute CPAP Treatment. PLoS ONE 2012, 7, e33769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kohler, M.; Stoewhas, A.-C.; Ayers, L.; Senn, O.; Bloch, K.E.; Russi, E.W.; Stradling, J.R. Effects of Continuous Positive Airway Pressure Therapy Withdrawal in Patients with Obstructive Sleep Apnea: A Randomized Controlled Trial. Am. J. Respir. Crit. Care Med. 2011, 184, 1192–1199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Zambotti, M.; Covassin, N.; Sarlo, M.; De Min Tona, G.; Trinder, J.; Stegagno, L. Nighttime cardiac sympathetic hyper-activation in young primary insomniacs. Clin. Auton. Res. 2013, 23, 49–56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carter, J.R.; Grimaldi, D.; Fonkoue, I.T.; Medalie, L.; Mokhlesi, B.; Van Cauter, E. Assessment of sympathetic neural activity in chronic insomnia: Evidence for elevated cardiovascular risk. Sleep 2018, 41, zsy048, Correction in Sleep 2018, 41, zsy126. https://doi.org/10.1093/sleep/zsy126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jarrin, D.C.; Ivers, H.; Lamy, M.; Chen, I.Y.; Harvey, A.G.; Morin, C.M. Cardiovascular autonomic dysfunction in insomnia patients with objective short sleep duration. J. Sleep Res. 2018, 27, e12663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, W.; Jiang, B. Heart rate variability in patients with insomnia disorder: A systematic review and meta-analysis. Sleep Breath. 2023, 27, 1309–1313. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grimaldi, D.; Goldstein, M.; Carter, J. Insomnia and cardiovascular autonomic control. Auton. Neurosci. 2019, 220, 102554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, S.; Hentig, L.; Lawler, S.; Yang, L.; Barb, J.; Fink, A.; Maki, K. 0110 Sleep Fragmentation Elevates Blood Pressure and Alters Parasympathetic Activity During Slow Wave Sleep in Rats. Sleep 2026, 49, A48. [Google Scholar] [CrossRef] [Scilit]
- Kinnunen, H.; Rantanen, A.; Kenttä, T.; Koskimäki, H. Feasible assessment of recovery and cardiovascular health: Accuracy of nocturnal HR and HRV assessed via ring PPG in comparison to medical grade ECG. Physiol. Meas. 2020, 41, 04NT01. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vesterinen, V.; Rinkinen, N.; Nummela, A. A Contact-Free, Ballistocardiography-Based Monitoring System (Emfit QS) for Measuring Nocturnal Heart Rate and Heart Rate Variability: Validation Study. JMIR Biomed. Eng. 2020, 5, e16620. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schyvens, A.-M.; Van Oost, N.; Peters, B.; Aerts, J.-M.; Masci, F.; Neven, A.; Dirix, H.; Wets, G.; Ross, V.; Verbraecken, J. A performance validation of six commercial wrist-worn wearable devices for sleep stage scoring compared to polysomnography. Eur. Respir. J. 2025, 66, PA5621. [Google Scholar] [CrossRef] [Scilit]
- Miller, D.J.; Sargent, C.; Roach, G.D. A Validation of Six Wearable Devices for Estimating Sleep, Heart Rate and Heart Rate Variability in Healthy Adults. Sensors 2022, 22, 6317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chinoy, E.D.; Cuellar, J.A.; Huwa, K.E.; Jameson, J.T.; Watson, C.H.; Bessman, S.C.; Hirsch, D.A.; Cooper, A.D.; Drummond, S.P.A.; Markwald, R.R. Performance of seven consumer sleep-tracking devices compared with polysomnography. Sleep 2021, 44, zsaa291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Svensson, T.; Madhawa, K.; Nt, H.; Chung, U.; Kishi Svensson, A. Validity and reliability of the Oura Ring Generation 3 (Gen3) with Oura sleep staging algorithm 2.0 (OSSA 2.0) when compared to multi-night ambulatory polysomnography. Sleep Med. 2024, 115, 251–263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, T.; Cho, Y.; Cha, K.S.; Jung, J.; Cho, J.; Kim, H.; Kim, D.; Hong, J.; Lee, D.; Keum, M.; et al. Accuracy of 11 Wearable, Nearable, and Airable Consumer Sleep Trackers: Prospective Multicenter Validation Study. JMIR mHealth uHealth 2023, 11, e50983. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fonseca, P.; Weysen, T.; Goelema, M.; Møst, E.I.; Radha, M.; Scheurleer, C.L.; Van Den Heuvel, L.; Aarts, R.M. Validation of Photoplethysmography-Based Sleep Staging Compared with Polysomnography in Healthy Middle-Aged Adults. Sleep 2017, 40, zsx097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manners, J.; Kemps, E.; Lechat, B.; Catcheside, P.; Eckert, D.J.; Scott, H. Performance evaluation of an under-mattress sleep sensor versus polysomnography in >400 nights with healthy and unhealthy sleep. J. Sleep Res. 2025, 34, e14480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herzig, D.; Testorelli, M.; Olstad, D.S.; Erlacher, D.; Achermann, P.; Eser, P.; Wilhelm, M. Heart-Rate Variability During Deep Sleep in World-Class Alpine Skiers: A Time-Efficient Alternative to Morning Supine Measurements. Int. J. Sports Physiol. Perform. 2017, 12, 648–654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nuuttila, O.; Seipäjärvi, S.; Kyröläinen, H.; Nummela, A. Reliability and Sensitivity of Nocturnal Heart Rate and Heart-Rate Variability in Monitoring Individual Responses to Training Load. Int. J. Sports Physiol. Perform. 2022, 17, 1296–1303. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Delling, A.C.; Jakobsmeyer, R.; Coenen, J.; Christiansen, N.; Reinsberger, C. Home-Based Measurements of Nocturnal Cardiac Parasympathetic Activity in Athletes during Return to Sport after Sport-Related Concussion. Sensors 2023, 23, 4190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
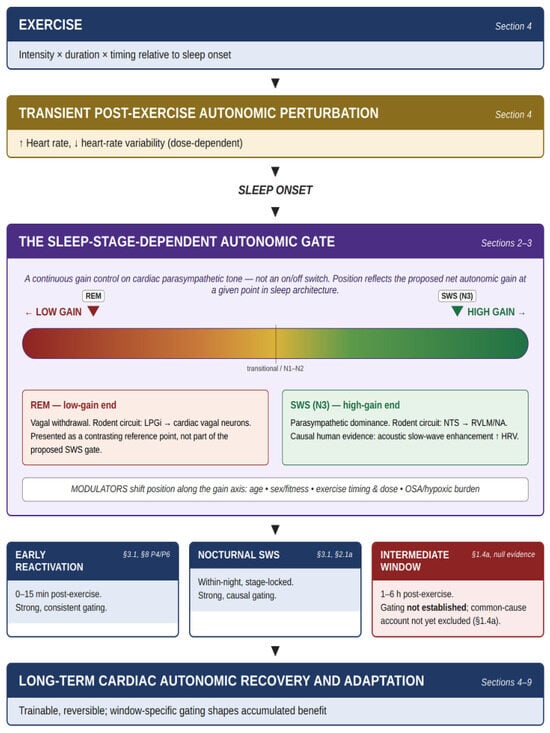
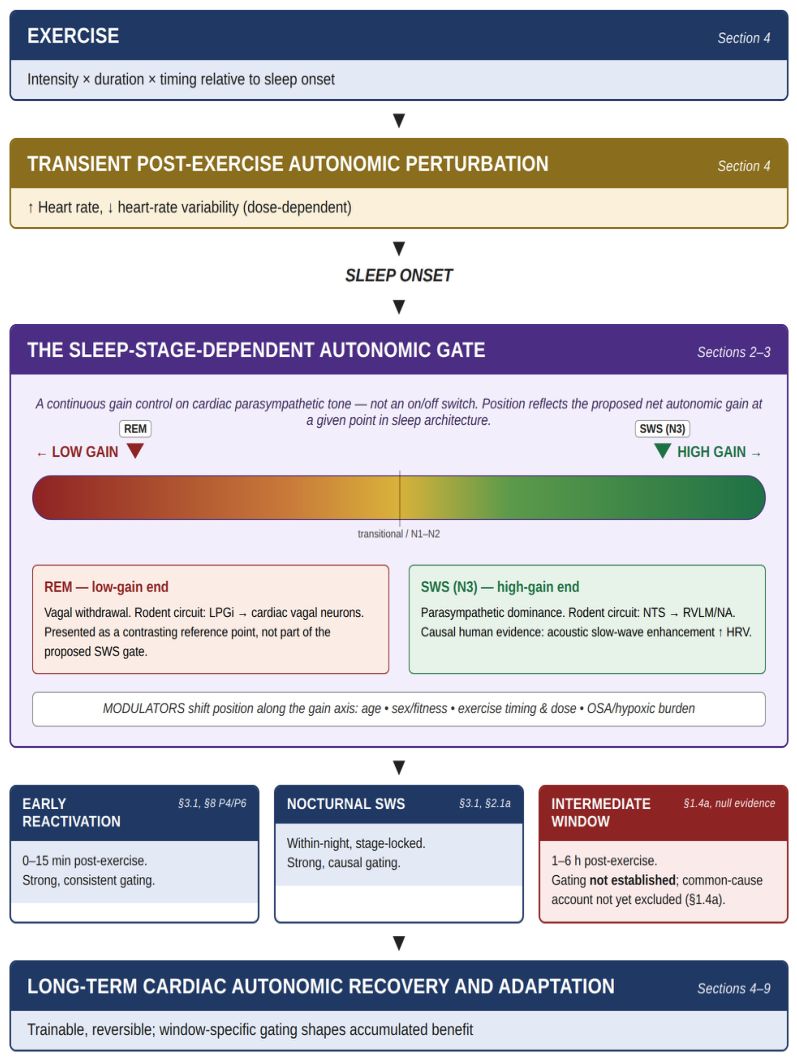

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.