


Abstract
The COVID-19 pandemic profoundly disrupted the lives of older adults, yet their experiences have remained underexplored. This paper draws on empirical evidence from a two-wave (W1 April–July 2020, W2 January–April 2021) qualitative study in the UK (n = 62) and a companion study in Colombia (n = 32), focusing on participants aged 60 and above. Data was analysed using constructivist grounded theory principles, leading to the development of an ecological theory of older adults’ well-being within the context of a health crisis at three interconnected levels: individual, community, and societal. Individual resources, such as adaptability and support systems, contributed to enhancing and maintaining their well-being. Community support and a sense of belonging were essential to meet the needs of people in later life, whilst necessary social health protection measures during the pandemic restricted social activities, further impacting well-being, mostly perceived as challenging. Cultural differences and societal support systems shaped participants’ experiences. The study emphasises the interdependence of the different levels in impacting older adults’ well-being, offers strategies for policy and practice, and advocates and contributes for the development of gerontological theories in the context of health crises.
1. Introduction
The global outbreak of COVID-19, caused by the novel coronavirus SARS-CoV-2, significantly disrupted daily life worldwide following its classification as a pandemic by the World Health Organisation in early 2020 [1]. While previous coronavirus epidemics—namely Severe Acute Respiratory Syndrome (SARS-CoV) and Middle East Respiratory Syndrome (MERS-CoV)—had emerged in earlier decades, their societal and lifestyle impacts were comparatively small [2]. At the initial stages of the COVID-19 crisis, there was limited understanding of the virus’s transmission dynamics and potential consequences, prompting governments to act swiftly to mitigate its spread and safeguard public health.
In response, the United Kingdom introduced a nationwide lockdown in March 2020, which persisted for approximately three months. Citizens were instructed to remain indoors except for essential activities such as purchasing groceries or seeking medical care. Non-essential businesses were mandated to close, and additional public health measures—including social distancing and mandatory face coverings in public spaces—were subsequently enforced. Comparable protective health measures were adopted by governments around the world.
People with heightened risk due to underlying health conditions, physical impairments, and age-related immune decline were categorised as vulnerable populations [3]. These factors increased their susceptibility to severe complications and elevated mortality rates associated with COVID-19 infection [4,5]. The heightened risk of severe illness from the virus and strict social distancing measures led to disruptions in essential social connections, distancing older adults from family and community interactions. As a result, many individuals’ lifestyles and social interactions were put on hold. These changes had been exacerbated by a rise in ageism, with prejudiced attitudes regarding the narrative of older adults’ vulnerability and restrictive measures directed at them [6]. For instance, policies stating that individuals aged 70 should not meet anyone or were legally prohibited from leaving their homes were implemented in the UK and globally [6,7].
The swift global spread of the novel SARS-CoV-2 virus, along with its initially uncertain effects on human health and the high mortality rates observed in the early weeks of the pandemic, instilled widespread fear and panic across the world [2,8,9]. Moreover, the protective health measures aimed to stop the spread of the virus also influenced people’s well-being by increasing social isolation and perceived loneliness [10,11], stress and anxiety across the population due to fears of infection, concerns about the health of loved ones, grief from loss, and the uncertainty caused by the pandemic [12].
This study was motivated by the unprecedented nature of the pandemic and early signs that indicated a heightened risk for older adults. Its primary objective was to investigate the lived experiences of older adults during the COVID-19 pandemic, with a particular focus on the psychological and societal impacts of the health crisis. The study aimed to identify new, evidence-based insights into these challenges faced by older adults.
To our knowledge, little was known about older adults’ experiences at the onset of the health crisis [13]. This gap in research emphasised the urgent need for theory development addressing the well-being of older adults during a health crisis, as recently suggested by Klausen [14]; see also [15,16,17].
3. Well-Being Discourse
Well-being, recognised as a vital aspect of human life, influences many domains, regardless of the ongoing debates about its definition [39]. Exploring well-being in the context of a pandemic is essential for a deeper understanding and being better prepared for future health crises [17]. Historically, theoretical discussions on well-being have been shaped by two contrasting perspectives: the hedonic and the eudaimonic approaches. Hedonic well-being centres on the pursuit of pleasure and immediate gratification, pointing towards experiences that elicit happiness and satisfaction in the present [40,41,42]. In contrast, eudaimonic well-being extends beyond transient pleasures, focusing on living a life of virtue, purpose, and personal growth. It underscores the importance of fulfilling one’s potential and cultivating a meaningful existence [41,42].
A universally accepted definition of well-being might not be achievable soon but generally includes contentment in key life areas such as occupational fulfilment, positive emotions, a sense of purpose, and overall life satisfaction, which is often reflected in the quality of social relationships [43,44]. While scholarly debates persist regarding the theoretical validity and applicability of these frameworks as discussed above, this study seeks to deepen the understanding of older adults’ lived experiences in order to better inform preparedness for future health crises. We address these challenging circumstances by asking the following research question:
How do the lived experiences of older adults during the COVID-19 pandemic inform the development of ageing-specific ecological theory and guide public health policies to address their unique needs in future health crises?
4. Research Context and Analytical Approach
This research study adopts a qualitative approach, specifically employing constructivist grounded theory [36], to examine the psychological and societal experiences of older adults. The authors aim to gain a deeper understanding of older adults’ experiences during the health crisis while also contributing to the development of theory, as advocated by Klausen [14]. Constructivist grounded theory is considered the most suitable methodology for this study because it allows for the creation of new knowledge and theory development, acknowledging the subjective interpretive nature of social phenomena, and deepening understanding of unexplored phenomena. Additionally, it ensures a nuanced, systematically rigorous, and reflective interpretation of the findings [36]. It is an iterative data collection and analysis process that applies inductive, deductive, and abductive reasoning to data analysis. The constant comparison strategy of data analysis informs theoretical sampling, leading to theoretical saturation or sufficiency [36,45]. More details can be found in Section 4.2.
Importantly, this study is part of a doctoral thesis and offers a detailed account of the research interest, influencing factors, and procedures. It includes a concise overview of the applied methodology of theory development, the role of sensitising concepts in guiding the inquiry, and the resulting theoretical framework. For further details, see Derrer-Merk [46]. Furthermore, this study forms part of a broader research initiative—the C19PRC project (COVID-19 Psychological Research Consortium Study|COVID-19 Psychological Research Consortium Study|The University of Sheffield) [47]. As such, there may be similarities in aspects such as methodology, context, ethical approvals, analysis, and participant quotations. These overlaps are expected and reflect standard practices within large-scale, ongoing research programmes like the C19PRC consortium. Importantly, the study acknowledges and cites the original sources to ensure transparency and address any potential concerns regarding duplication. By clearly referencing prior work and using quotation marks when using participant quotes, the authors maintain academic integrity and demonstrate responsible research conduct.
4.1. Psychological Research Consortium (C19PRC)
This study is a qualitative add-on study, nested within the COVID-19 Psychological Research Consortium (C19PRC, UK; https://www.sheffield.ac.uk/psychology-consortium-covid19, accessed on 15 January 2026), led by Prof. Richard P. Bentall (R.P.B.) [47]. Researchers at the University of Liverpool, led by Prof. Kate M. Bennett (KMB), conducted a qualitative study with this nationally representative sample to explore adults’ lived experiences during the pandemic.
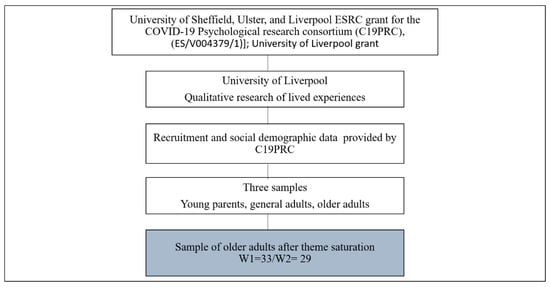
The first author’s qualitative research was particularly interested in older adults aged 65+, aiming to understand their unique experiences during the health crisis (see C19PRC project, Figure 1). Our primary interest of this study included examining changes in activities and emotional experiences at two-time points—at the pandemic’s onset (interview wave 1, W1) including 33 individuals (age range: 65–83, mean = 71, SD = 5) and one year later Wave 2 (W2) (Figure 1) including 29 individuals (11 men, 18 women).
Figure 1.
Context of UK data nested within the C19PRC project (see grey marking, this is relevant for this study).
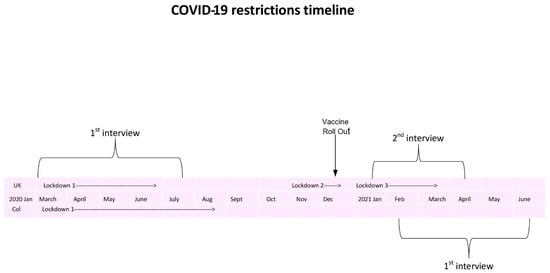
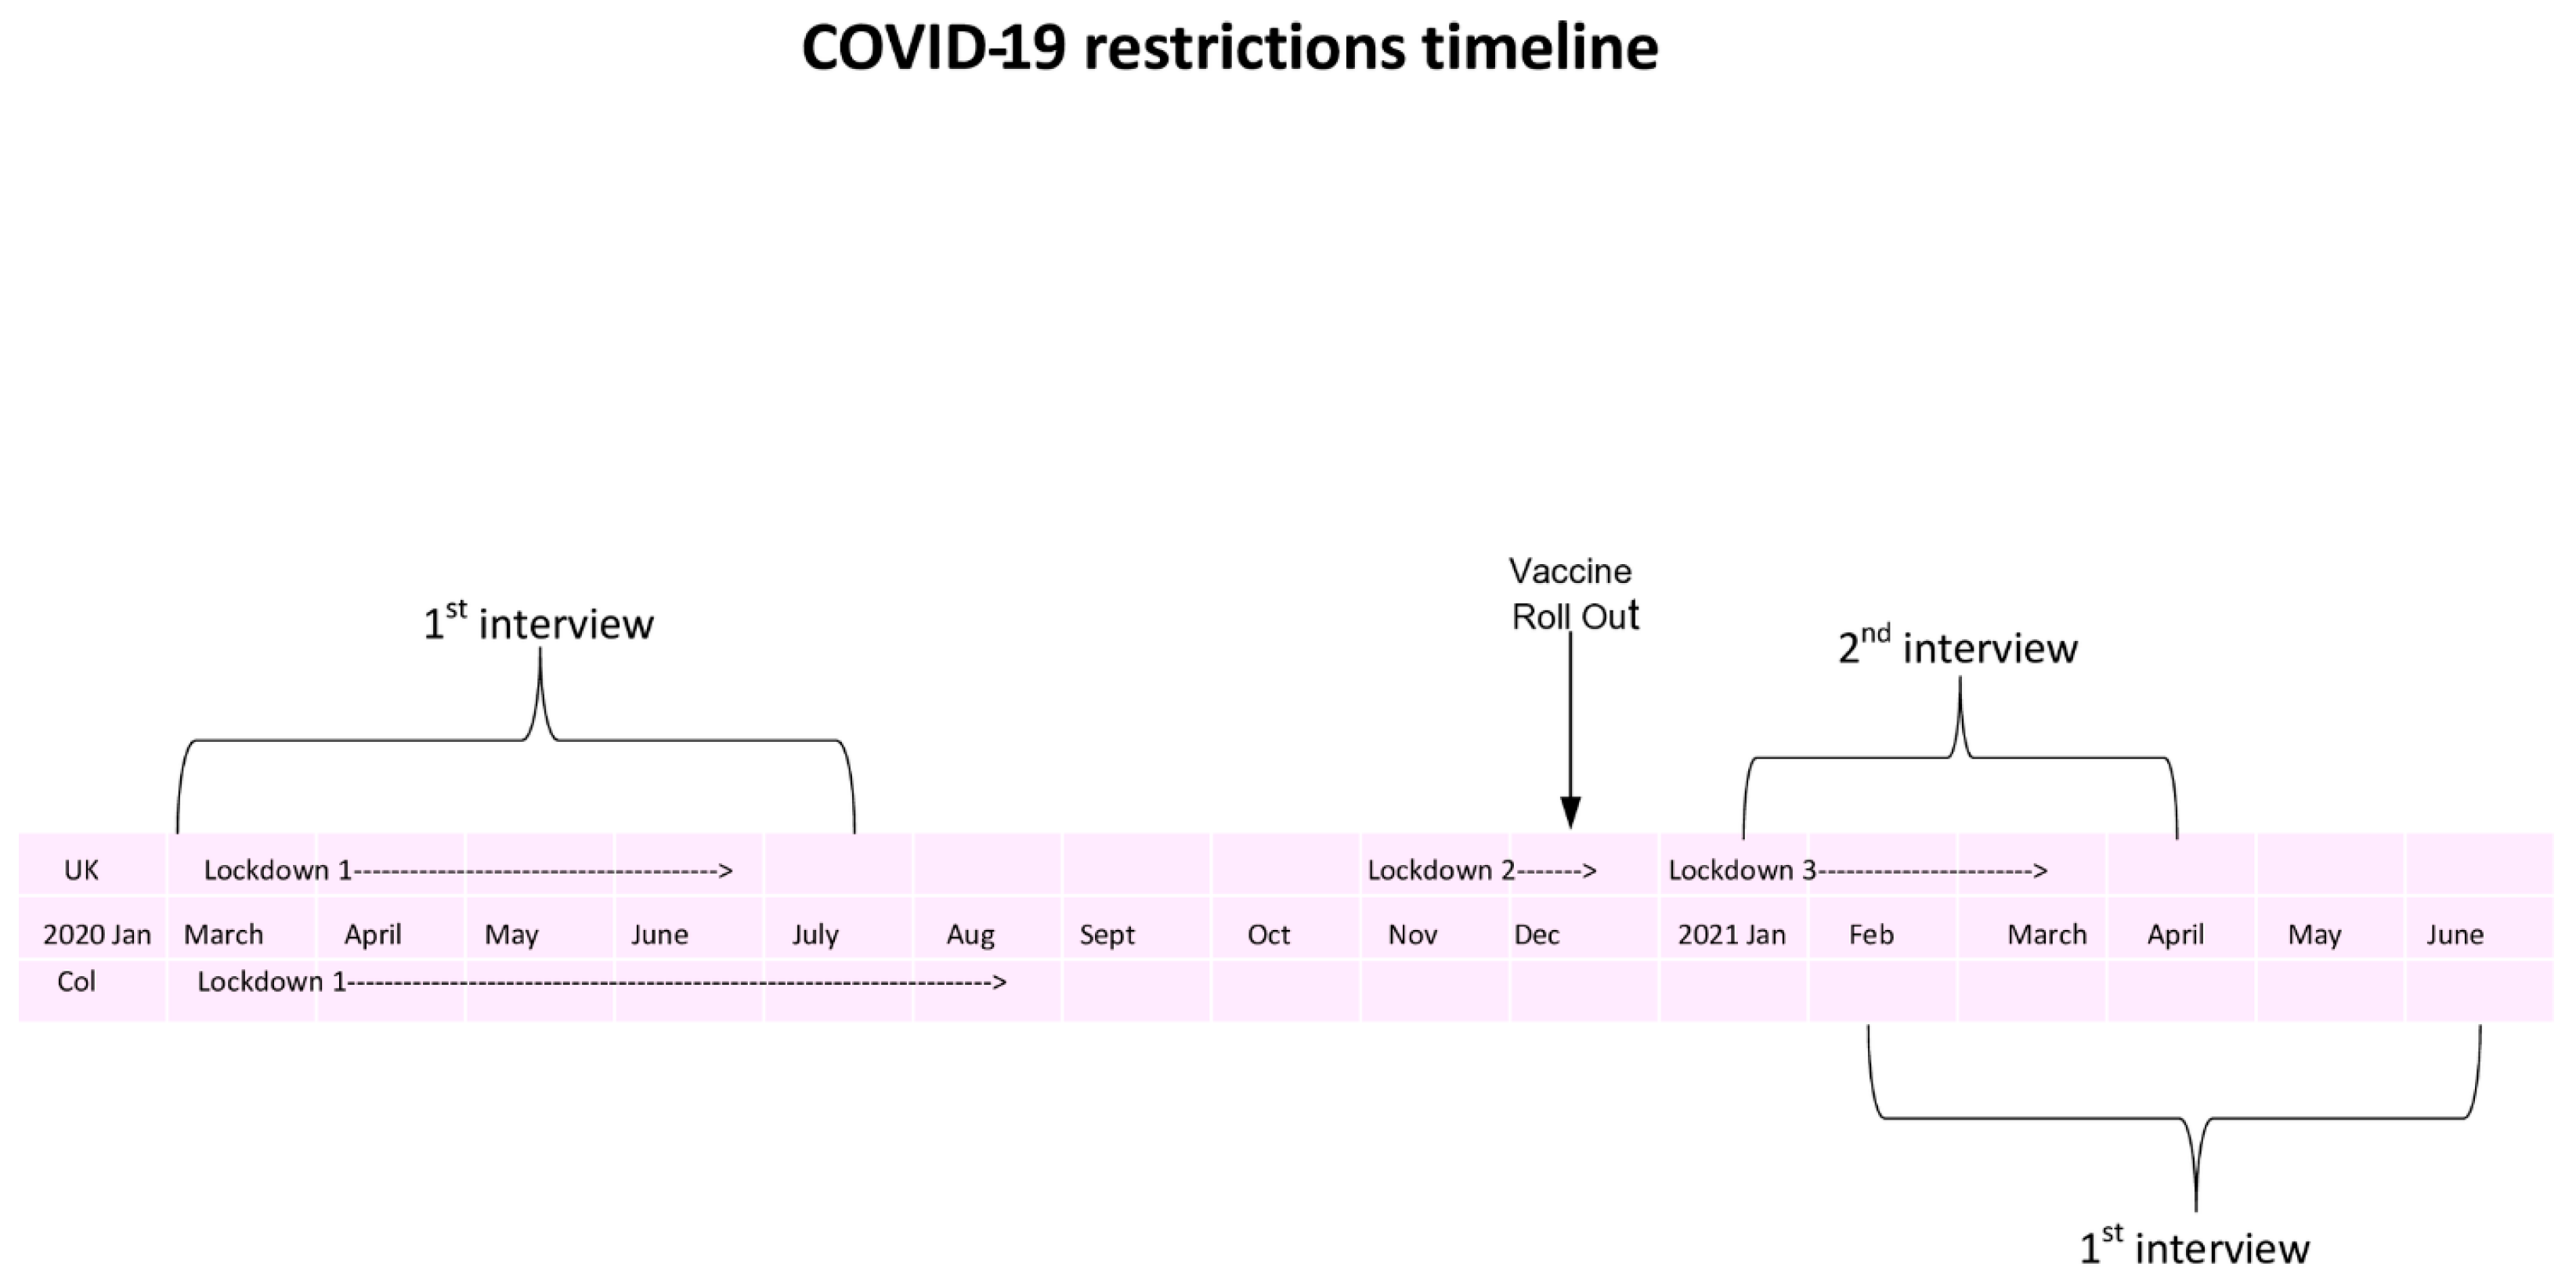
In collaboration with a colleague from Colombia (CO) (MFR), we included data from 32 interviews aged 63–95 (16 men and 16 women, mean = 69, SD = 9) based on the same interview schedule and conducted from January to June 2021, enriching the study with culturally specific insights. Please see the timeline of the lockdown and the interview dates in Figure 2. More details related to participants’ demographics can be seen in Supplementary Materials Table S1.
Figure 2.
Interview and restriction timeline related to COVID-19 from the UK and Colombia, 2020–June 2021. Adapted from Derrer-Merk et al. [46].
Figure 2: Broad lockdown timeline for the first year of the COVID-19 pandemic in both the UK and Colombia. Participants in the interviews reflected on the first year of the pandemic. Lockdown refers to the closure of all non-essential activities (shops, gyms, community centres, etc.). Adults aged 70 and over were advised to stay at home and self-isolate, and in Colombia, it was mandatory (March–July 2020), the protective emergency measures continued in Colombia until June 2022, where the use of masks was mandatory.
4.2. Applied Principles of Constructivist Grounded Theory
In this study, we adopt a constructivist grounded theory (CGT) approach, most suited to exploring under-researched phenomena such as older adults’ experiences during the COVID-19 pandemic. This approach accounts for individual experiences and values multiple realities [36]. Furthermore, it allows the systematic development of a theory grounded in lived experience, capturing a wide range of factors impacting older adults’ well-being during a rapidly changing global health crisis. CGT emphasises co-construction of knowledge between participants and researchers, acknowledging researcher positionality while generating rich, context-sensitive insights [36].
Interviews were conducted by telephone or online and lasted 30–60 min in both countries. Although the UK and Colombian samples differed in timing, they were treated as two contextual datasets informing the same emerging theory rather than as a formal cross-national comparison. Methodological alignment was ensured through the use of the same CGT approach and interview guide. Additionally, the Colombian researcher (M.F.R.) was previously trained by KMB. Our ongoing collaboration between the UK and Colombia offers a unique chance to explore the experiences of older adults during the COVID-19 pandemic in supporting the theory development. Furthermore, we followed the CGT principle of flexibility by keeping in mind that extraordinary circumstances require extraordinary approaches [48,49].
The novelty of this study lies in its longitudinal exploration of older adults’ experiences across two waves and integration of data from both countries to develop a substantive theory. Related outputs from this research have been published previously elsewhere [48,50,51,52]. Data analysis was inductive and iterative, guided by theoretical sensitivity and emergent sensitising concepts [53,54]. Theoretical sampling continued until sufficiency and saturation were reached, ensuring conceptual depth and no new insights emerged [45,55,56].
The analysis followed three CGT coding phases: initial, focused, and theoretical. Initial coding was conducted by the first author (UK data) and MFR (Colombian data). Focused coding and category refinement were carried out collaboratively with the supervisor in team meetings to discuss coding decisions and resolve disagreements. Theoretical coding integrated categories into higher-level themes to develop the substantive theory.
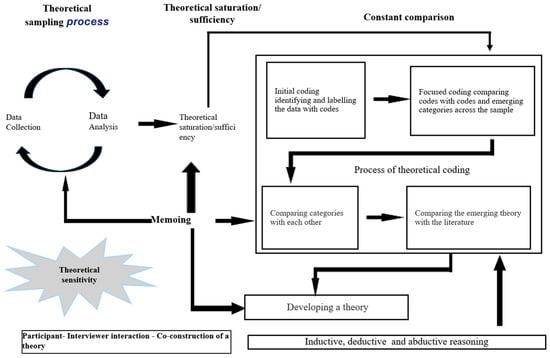
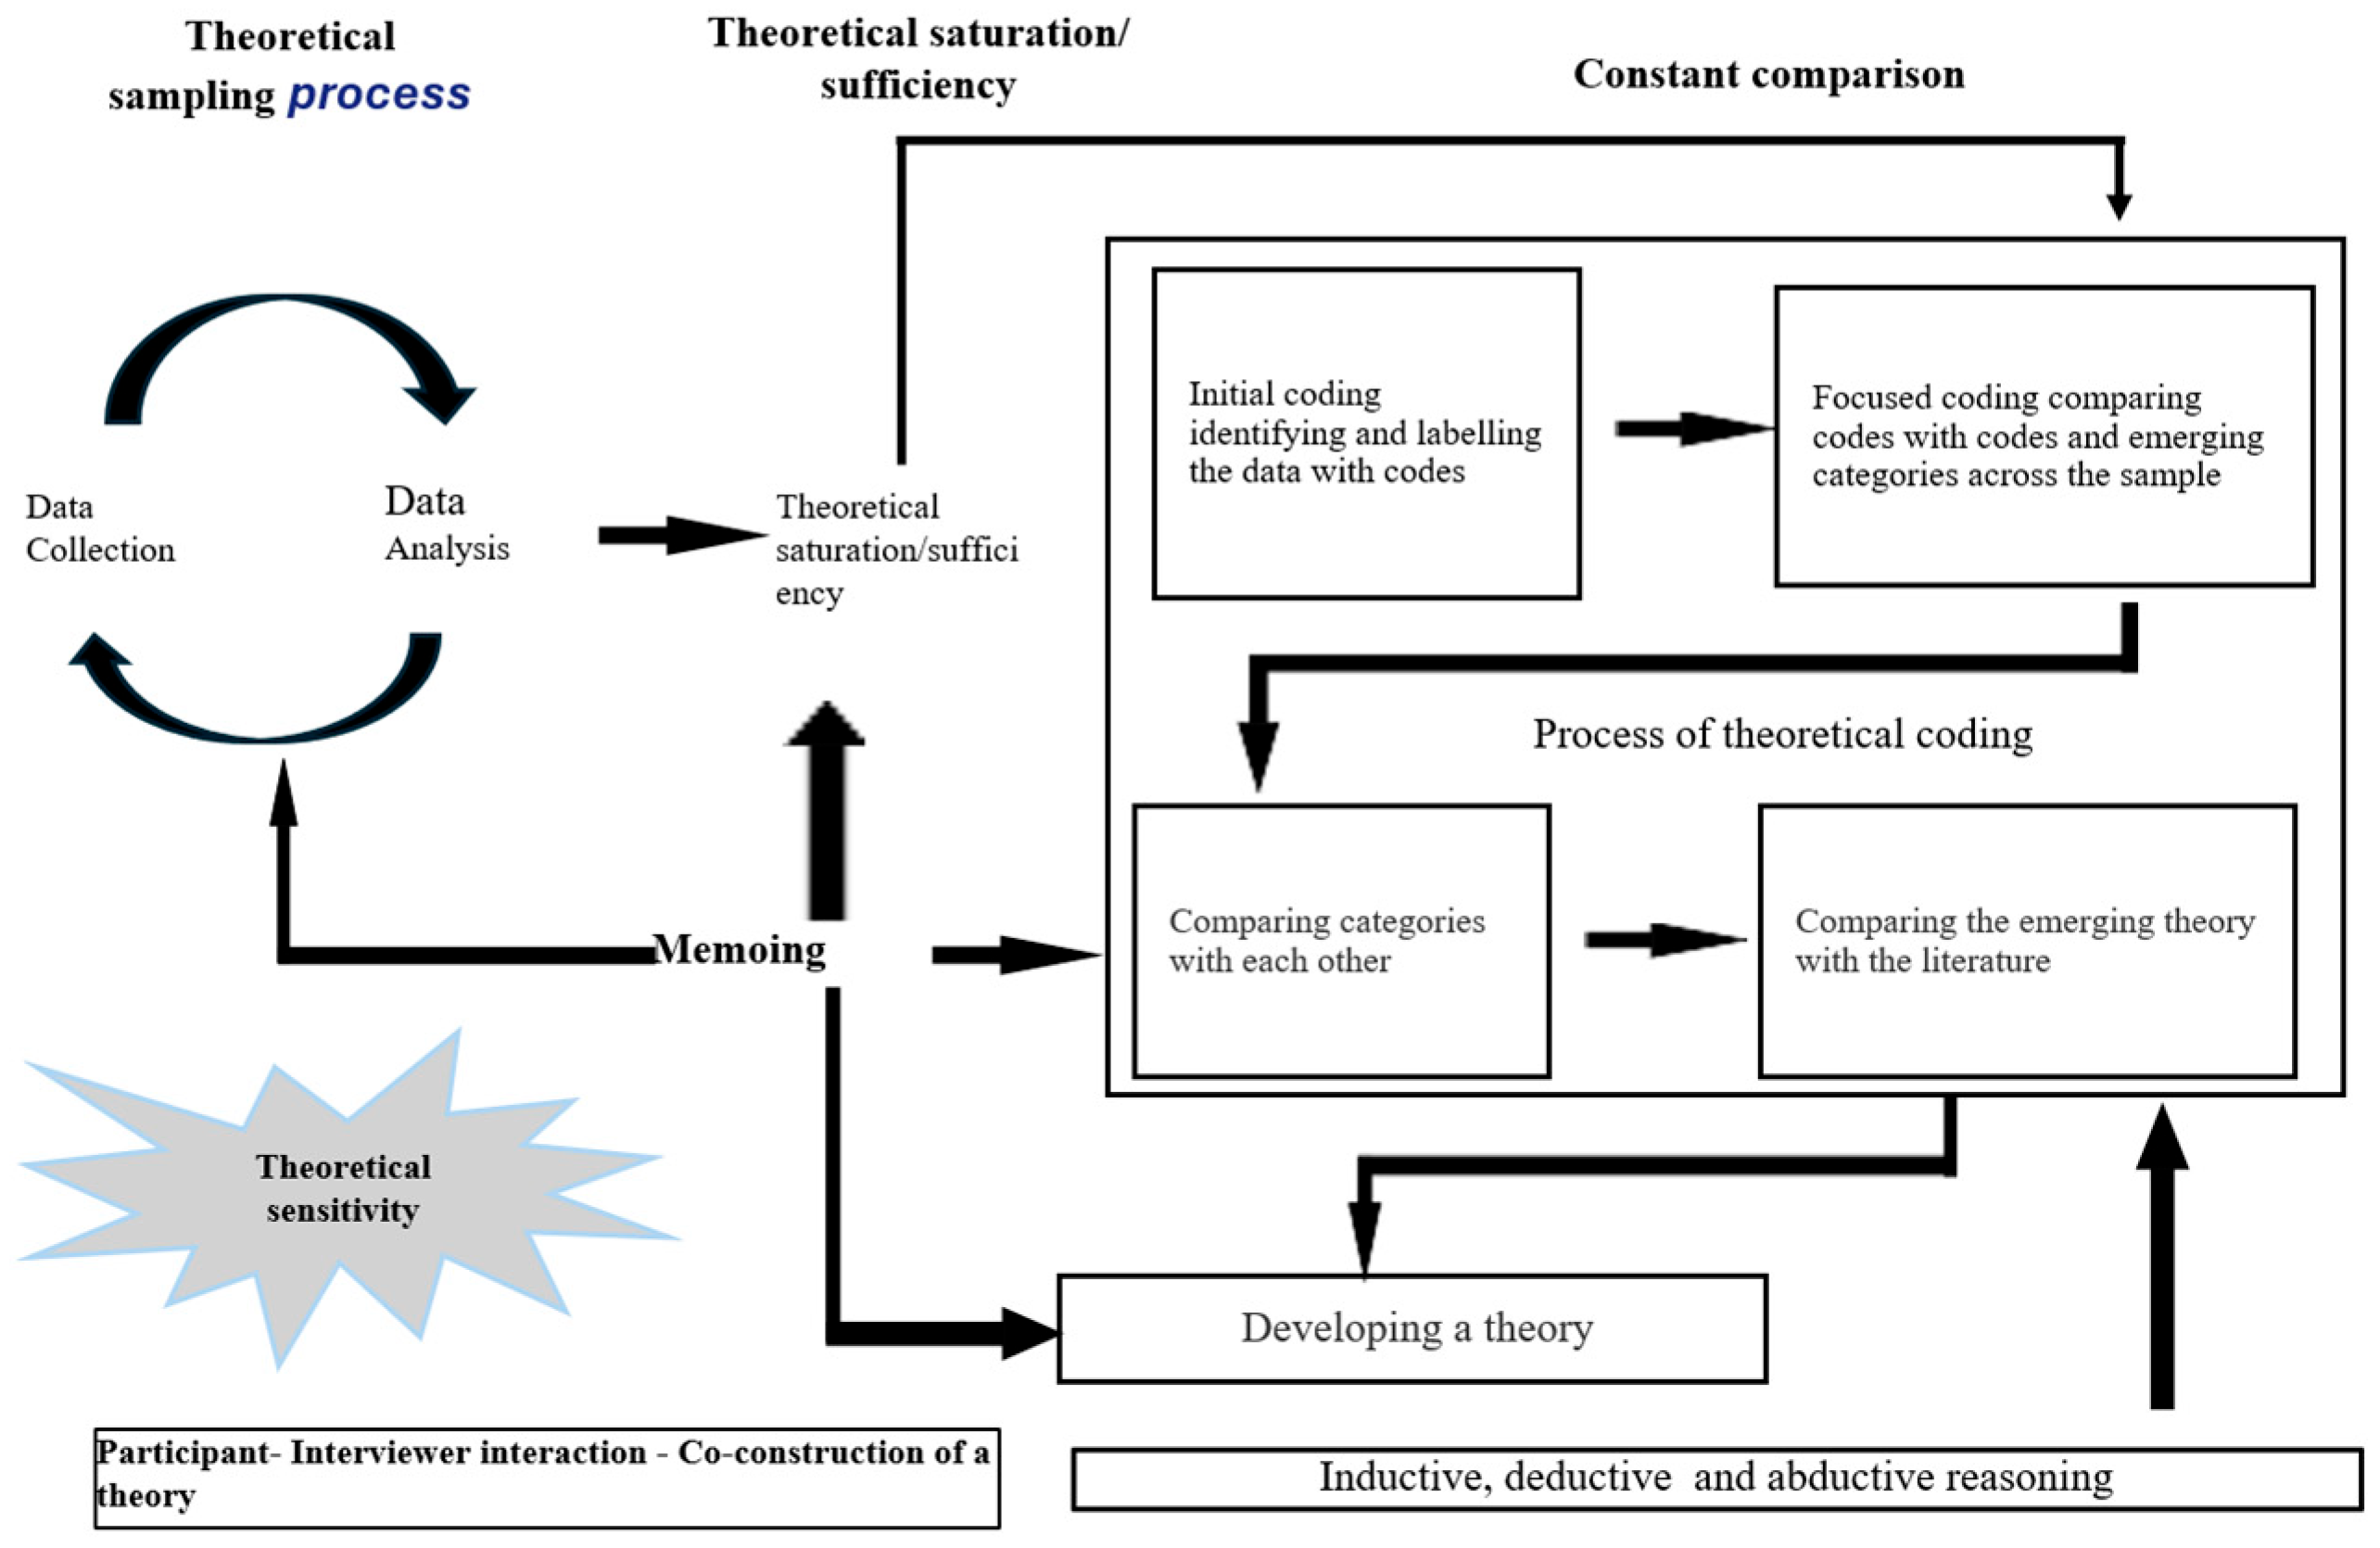
Constant comparison was applied to identify patterns, similarities, and differences across data. Inductive, deductive, and abductive reasoning supported higher-level abstraction and theory development by finding the best plausible explanation [36]. Reflexive memoing—through writing and visual mapping—supported analytic decisions and theoretical integration [36]. Furthermore, discussions and memoing ensured that the researchers’ positionality was thoroughly reflected upon. Figure 3 illustrates the iterative process of analysis and theory development (adapted from) [57].
Figure 3.
Iterative process of data analysis within CGT. (Adapted from Derrer-Merk et al. [57], originally jointly created by Derrer-Merk and Mulenga-Wincierz).
These principles foster an iterative, adaptable, reflective research approach and support the co-construction (between data and researcher) of the meaning-making process of participants’ data, guided by the question, “What does this mean?” [58,59].
Furthermore, this study adhered to quality criteria (trustworthiness) suggested by Charmaz & Thornberg [60]: credibility, originality, resonance, and usefulness. Credibility was supported through sufficient and diverse data, originality through the generation of novel insights into older adults’ pandemic experiences, resonance through close alignment between participants’ accounts, and usefulness through the theory’s capacity to illuminate individual and societal dimensions of lived experience. Together, these principles supported an iterative, reflexive analytic process and the development of a substantive CGT.
4.3. Analysis Guided by Sensitising Concepts
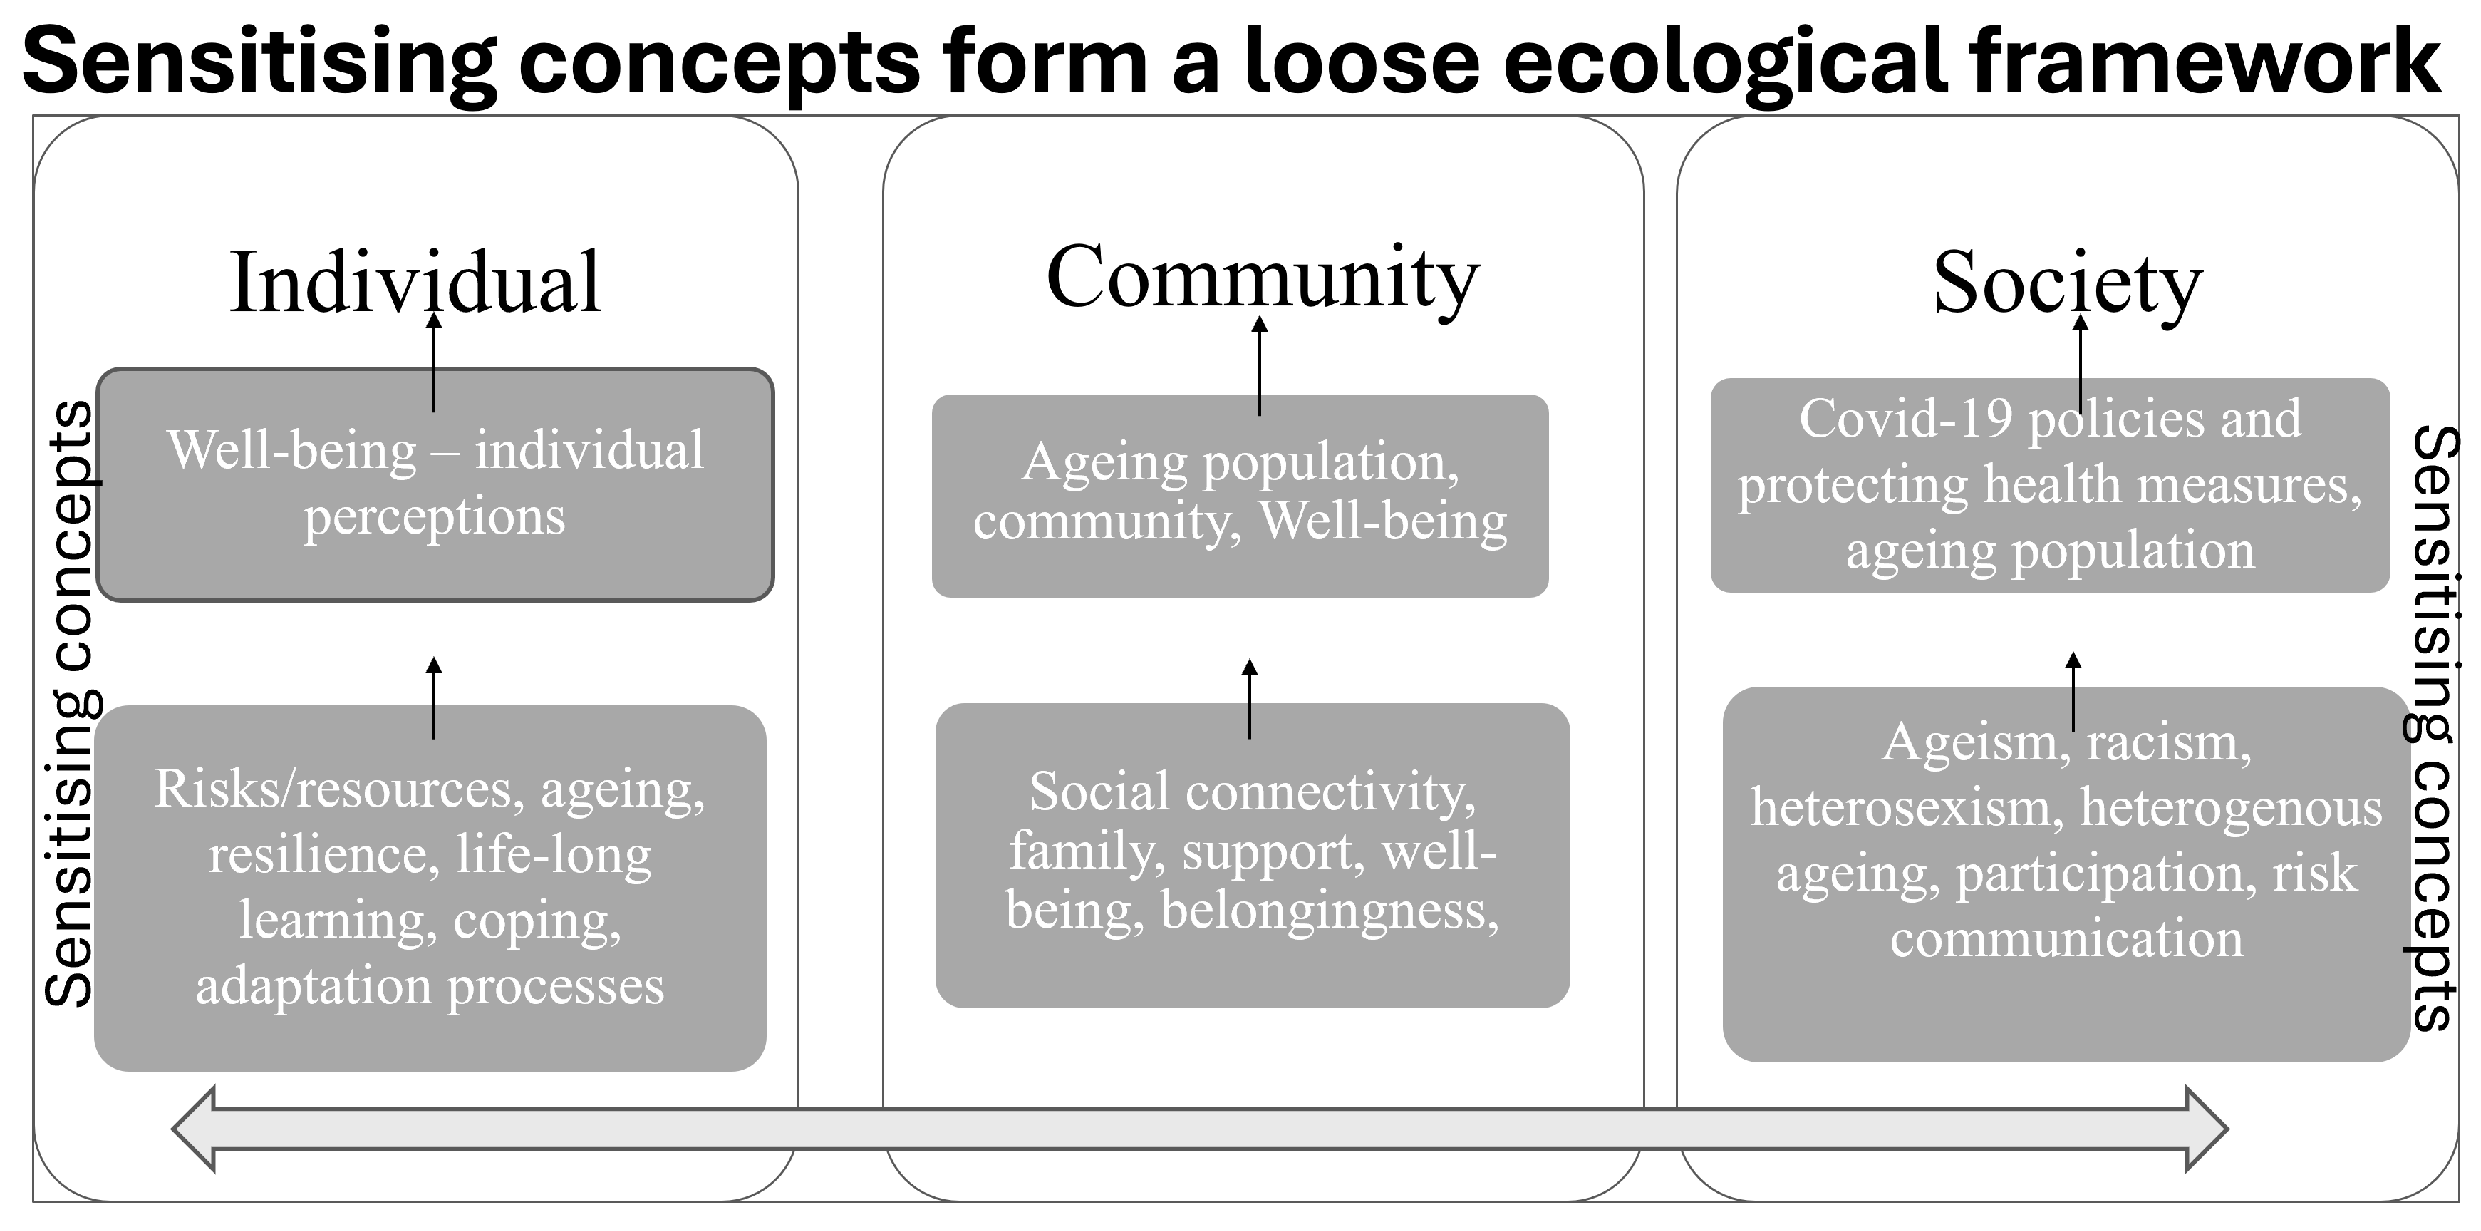
Constructivist grounded theory emphasises generating novel insights grounded in the data, guided by initial and emergent sensitising concepts [36]. Blumer [53] suggested applying sensitising concepts over definitive concepts as the latter might impose the data into existing frameworks instead of exploring the data. These sensitising concepts offer a “general sense of what is relevant”, Blumer [53] (p. 148) (see also [61]) and serve as a flexible and open approach to where the data leads. Thus, an iterative analytical process allows theory to emerge from the data, continually adapting as new patterns and insights unfold during analysis. The initial sensitising concepts (theoretical concepts known to the researcher that guide inquiry) in this study consisted of healthy ageing, well-being, and resilience, along with the emergent sensitising concepts during the analysis, which supported the development of the theory, as illustrated in Figure 4 within a loosely defined ecological framework.
Figure 4.
Sensitising concepts within a loosely defined ecological framework.
This study found that the notion of healthy ageing—rooted in principles of equality and inclusivity—was not a dominant theme among participants. Instead, narratives were primarily centred on experiences of social distancing and lockdowns. References to healthy ageing were mostly in the context of stereotyping (vulnerability) and discrimination [7,51,62]. Although resilience as advocated by Windle and Bennett [31] was initially considered as a sensitising concept, the theme of well-being emerged more prominently. Participants often articulated well-being in everyday language, yet their descriptions aligned with ecological understandings of health and adaptation [31]. Resilience became more apparent in discussions of belongingness and community cohesion [31,52]. The relationship between resilience and well-being is still a topic of debate [63]. However, data indicate that well-being—defined as the ability to adapt, experience a range of emotions, achieve life satisfaction, find purpose, and hold positive evaluations emerged as a key finding [43,44,64,65,66]. This suggests that resilience is one component within a larger framework that supports the well-being of older adults during the pandemic.
5. An Ecological Theory of Older Adults’ Well-Being in the Context of COVID-19
The analytical process undertaken in this study identified well-being as the most salient sensitising concept and the central theme emerging from the data. This underscores the profound impact of the COVID-19 pandemic on the psychological and social well-being of older adults. Although well-being lacks a universally accepted definition, our findings highlight its multifaceted nature. It includes elements like happiness and joy [64], especially during the pre-pandemic period. However, during the pandemic, there was a noticeable shift toward establishing new goals and finding purpose in life, but consistently mentioned the loss of joy from family gatherings and other valued activities. Participants adapted to new circumstances through purposeful activities such as online teaching and learning, exercising, and reading, and sustained meaningful relationships that supported their well-being despite the constraints of social distancing [7,44,48,64].
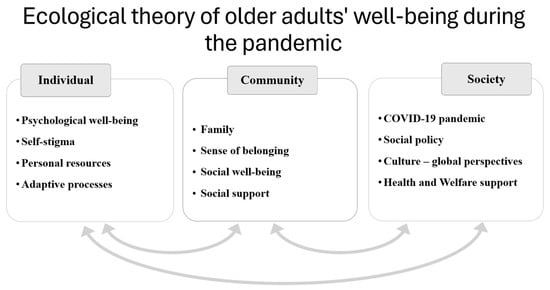
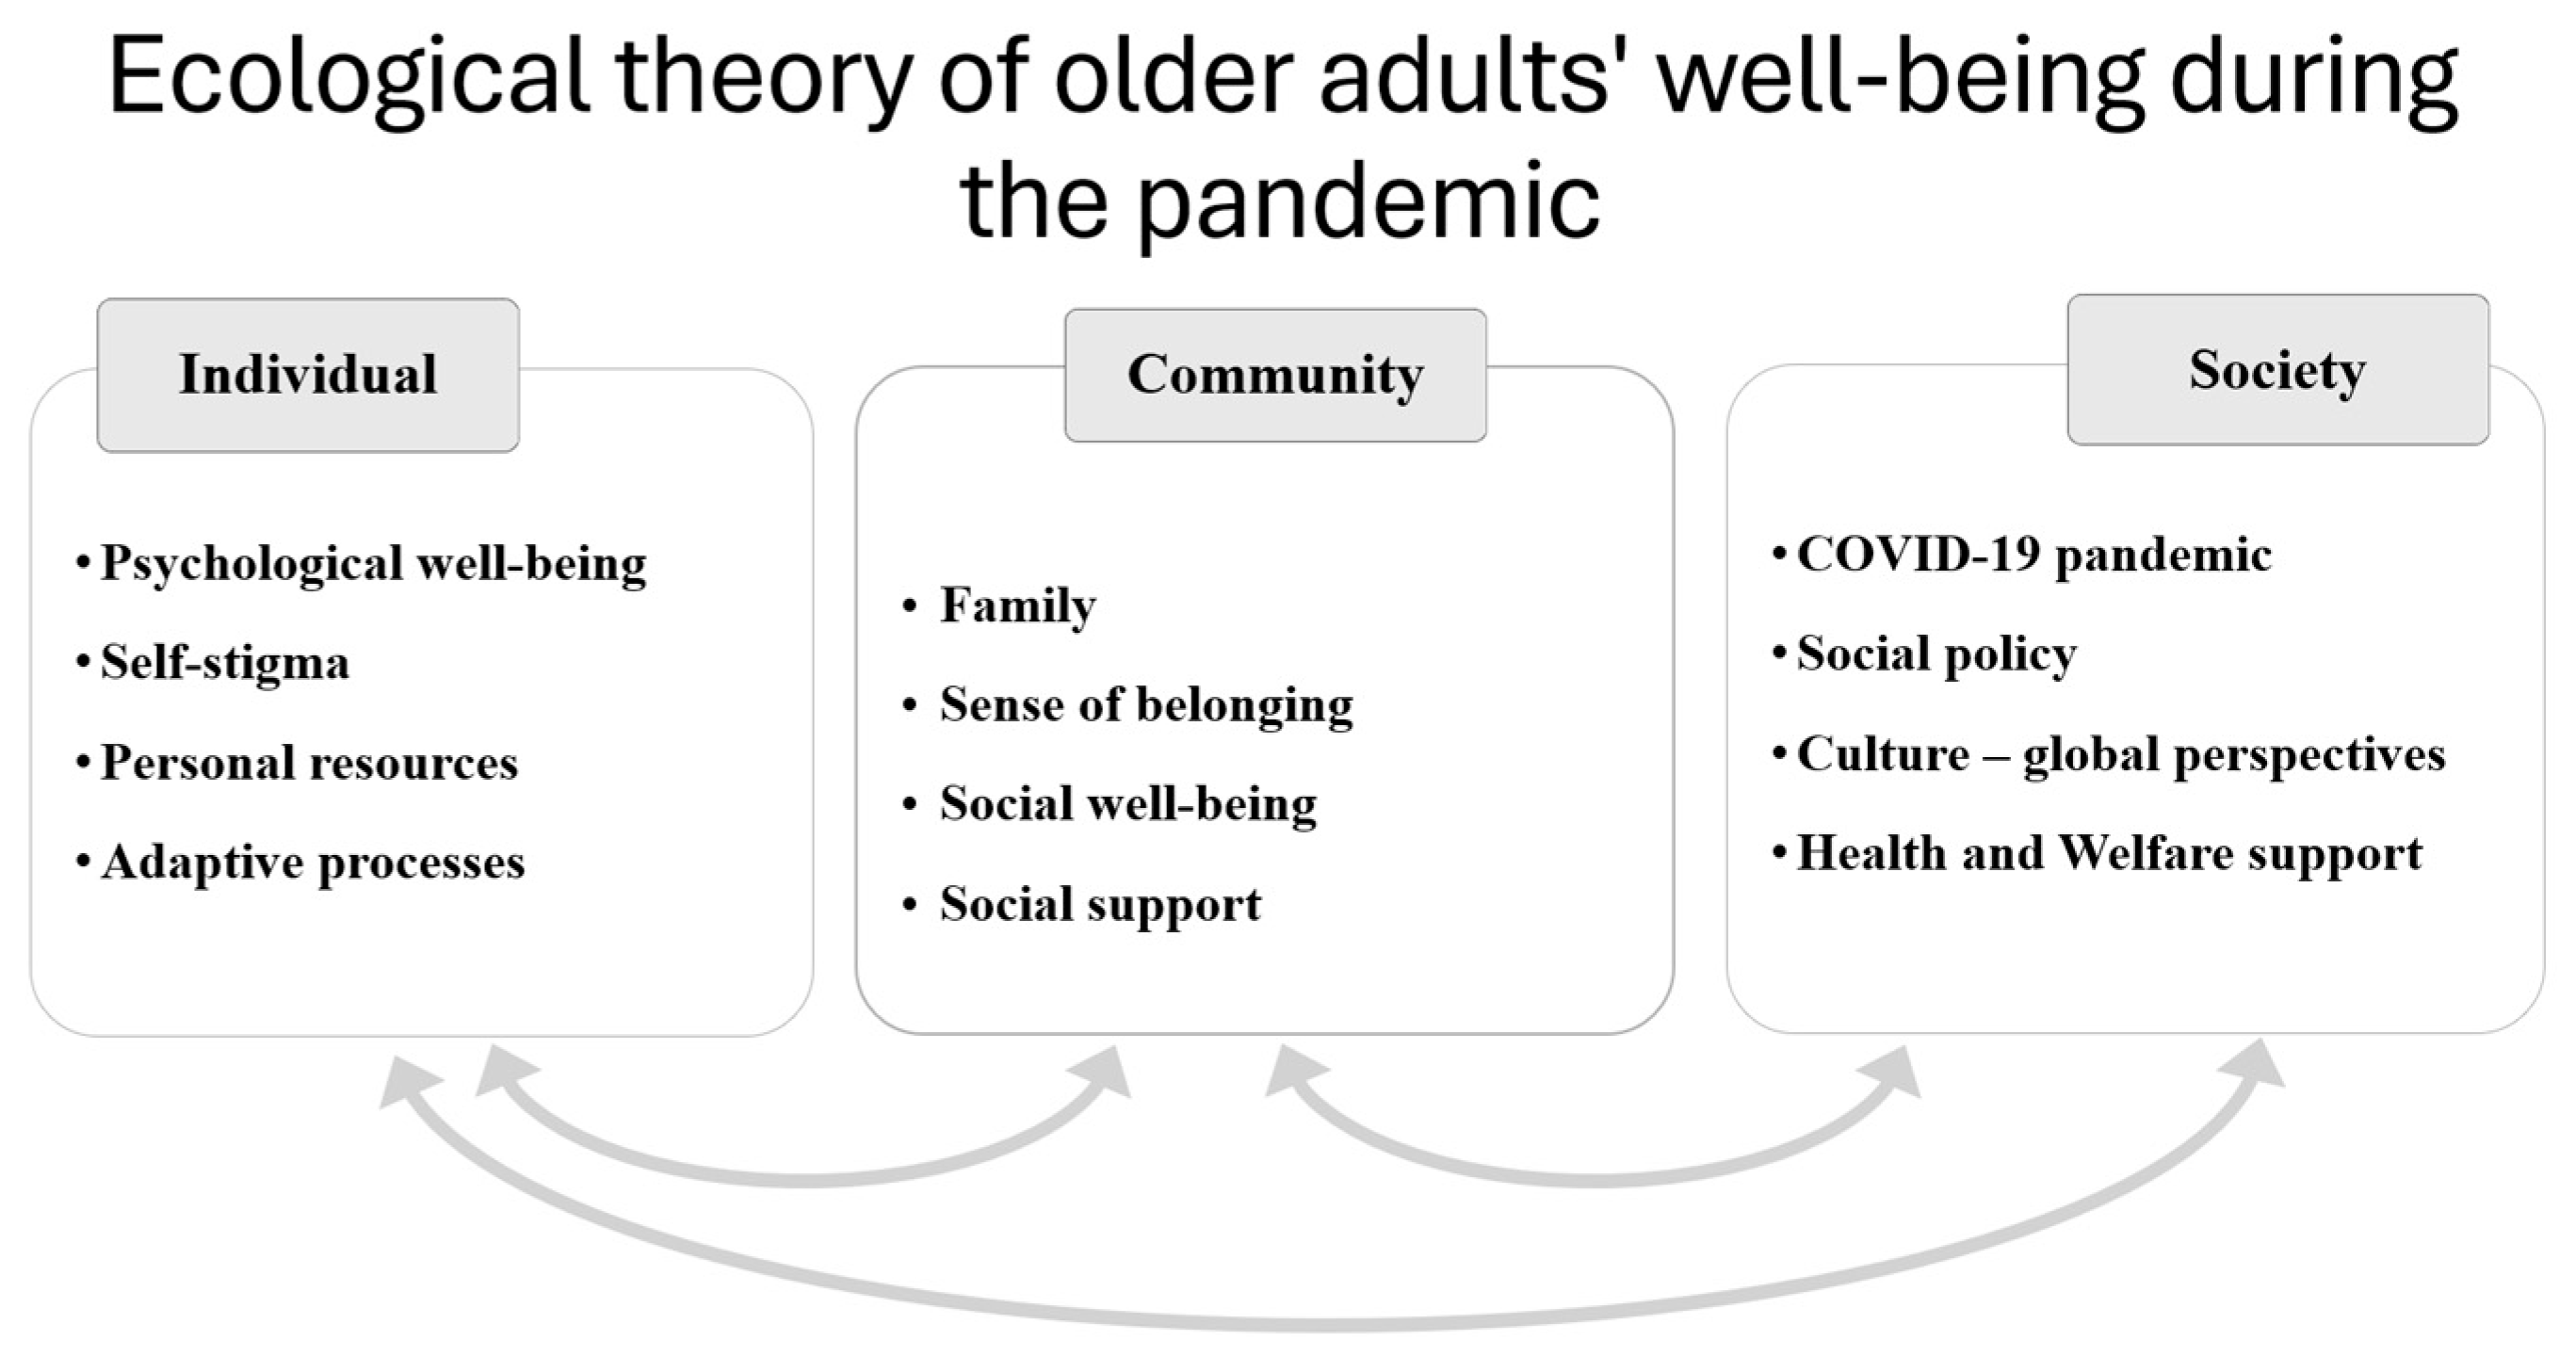
Instrumental and emotional support—both experienced and perceived—from family and friends emerged as critical for maintaining well-being [7,31,48,50,52,65]. The analysis further revealed an ecological structure—serving as a sensitising concept—rooted in Bronfenbrenner’s ecological systems theory and evolved through the contributions of Windle and Bennett [31]. This approach highlights the foundational elements of older adults’ lives, including personal resources, family and social relationships, community support systems, and the influence of pandemic-related policies on their well-being. These interrelated dimensions are visually represented in Figure 5.
Figure 5.
Ecological Theory of Older Adults’ Well-Being during the COVID-19 pandemic.
The following Box 1 illustrates a summary of the Theory of Older Adults Well-being during the COVID-19 pandemic.
Box 1. Theory Summary.
The well-being of older adults during the COVID-19 pandemic was fundamentally affected by the interconnected levels of the individual, community, and society. The societal context—including the pandemic itself, social policies, cultural values, global perspectives (vulnerability stereotype), and welfare support—shaped opportunities, values, norms, risks, and resources during the health crisis. These societal factors have a direct impact on the individual and community level. Community dynamics, in times of a health crisis, influence family relationships, social support systems, and the sense of belonging within families and communities. In turn, these community aspects impacted individual outcomes such as psychological well-being, adaptation strategies, and personal resources. Acknowledging that there are feedback loops across these levels, individuals’ adaptive strategies, resources and psychological well-being and community support, belongingness and social well-being can also influence the social and policy environments.
The Ecological Theory of Older Adults’ Well-Being in the context of COVID-19 highlights the dynamic interplay between individual, community, and societal factors. It demonstrates that well-being is developed through the interaction of personal capabilities, support systems, and social environments [22,44,65,67,68,69,70,71]. This interconnectedness will be explored further.
The following key quotes highlight the range of narratives, illustrating the diversity within the sample studied.
5.1. Individual Level
At the individual level, many participants talked about the adverse effects of the COVID-19 pandemic but also demonstrated the ability to adapt after one year of the health crisis [7,48]. This capacity for coping and adjustment over time was evident across diverse national contexts (and diverse individual experiences), suggesting that it may represent a universal resource for sustaining well-being, irrespective of personal or cultural differences [64,66]. Evidence is included from the UK and Colombia, as mentioned above:
“I tell you, I am a person who tries to handle things positively and when you are positive, nothing distresses you, nor does it make you sad.” (adaptive process; COSH03) [48] (p. 13).
“Well, you’ve got to take the rough with the smooth, haven’t you? (…) I’ve started trying getting the attitude now that, look, bad things, possibly/probably are going to happen, but look at the tremendous health I’ve had up to now. Try and put a good spin on it.” (Adaptive process; M10UKW2) [48] (p. 13).
These narratives are an example, irrespective of individual backgrounds, many older adults consistently exhibited a capacity for adaptation, even when faced with varying levels of resources and diverse life experiences. This ability to adapt highlights the importance of recognising the role of broader social and cultural contexts in shaping coping and adaptation processes among older adults [72,73].
For example, a participant from Colombia said:
“Right now the government has had a very important interest in the elderly (…) to avoid high mortality, and I think that if there has been more interest than before and it has made others think more about the older adults.” (Adaptive process; CO SH04) [51] (p. 911).
However, not all older adults adapted in the same way; some talked about the difficulties in navigating the challenges posed by the pandemic [74]. For example, a woman from the UK mentioned:
“Yes, pretty miserable overall. I have to keep geeing myself along and saying oh come on, let’s do something productive, let’s do. It’s quite hard getting motivated.” (Adaptive process; F1UKW2) [48] (p. 12).
Notably, many participants reported setting new goals during the lockdown, reflecting processes of meaning-making and the pursuit of purpose in life [48]. Collectively, these aspects were essential resources that supported older adults in navigating the challenges of the pandemic and contributed to their overall well-being during a period of significant adversity [22]. Many participants reflected on the prevailing societal narrative of vulnerability, often agreeing with the classification. However, this external labelling frequently led to shifts in self-perception, including altered self-authenticity and the internalisation of self-stigma. For instance, participant F16 UKW1 described the direct emotional impact of being officially categorised as ‘old’ by the UK government, noting how this designation influenced not only how she was perceived but also how she came to feel about herself.
“Well, reduced mobility because of arthritis, that made me feel old and also, I know this is before the lockdown, but as soon as the government told us that we were elderly, I felt it.” (Self-stigma; F16 UK W1) [51] (p. 914).
Others opposed the narrative, comparing their good health and fitness levels to younger generations. [7,51]. “I’ve always suffered from good health”. (Psychological well-being; M10 W2) [48] (p. 485).
Participants who internalised the societal classification of vulnerability often curtailed their independence, which in turn posed challenges to their overall well-being. As one participant noted, this self-limitation emerged as a direct consequence of being labelled as vulnerable:
“I can’t make myself go out, I’ll say that much now. I am literally too scared to go out”. (Psycholcological well-being; M8UK W1) [48] (p. 117).
This internalisation of self-stigma, which often resulted in self-restrictions, was also found earlier [75,76,77,78]. This finding underscores the dynamic interplay between individual, community, and societal levels during a health crisis, highlighting how these interconnected domains collectively shape experiences and responses.
5.2. Community Level
At the community level, the onset of the COVID-19 pandemic disrupted family relationships and support mechanisms, leading to a noticeable imbalance [65]. Social interactions were fundamentally altered, and support systems shifted from being largely reciprocal to predominantly one-directional, with older adults more often receiving than providing support. While receiving assistance was crucial during this period, many participants expressed a sense of loss in no longer being able to contribute—particularly through roles such as grandparenting—which diminished their sense of value and challenged their overall well-being [7,48,50].
“We miss them. They are 6 and 4. Well, yes, my wife has just said, we do talk to them on the phone and we’ve had messages from them. But no, we do miss them because they are nice children and we enjoy taking them out when we’ve taken them out”. (Family; M6UKW1) [50] (p. 10).
This finding brought to the fore that one-directional support may protect material well-being but still threatens psychological well-being via loss of agency/role. The disruption of family relationships—an essential source of well-being—led to a state of familial disequilibrium. These findings point toward the fundamental need of maintaining meaningful social connections, offering instrumental and emotional support and contributing to maintain well-being in later life, particularly during periods of crisis. This aligns with previous research emphasising the value of social ties in ageing populations [42,68,79,80]. Both experienced and perceived support emerged as vital resources for emotional regulation, adaptation, and overall well-being [7,31,48]. Participants frequently referred to supportive interactions such as frequent phone calls, online meetings, the presence of family when needed, and the convenience of shopping deliveries. These examples illustrate how support functions as a foundational resource, enhancing individual well-being and demonstrating the interconnectedness between community and individual aspects of well-being (see Figure 5).
“Yes, if I didn’t have my family. (Laughs) I would definitely be anxious or lonely. (Family, F11UKW2) [48] (p. 15).
Participants’ narratives revealed the multilayered role of social support in promoting both psychological and social well-being, illustrating the importance of meaningful social bonds and activities that serve as essential resources for fostering a sense of belonging [81,82]. For instance, participant F9 W2 described:
“I started going to dancing one afternoon, a tea dance, one afternoon a week and I found that was great, it was giving me exercise, I was meeting people, and of course all that stopped because of COVID” (Social well-being; F9UK W2) [52] (p. 14).
While many participants felt appreciated within their social networks, they also described a gradual weakening of physical and emotional proximity—particularly following the loss of close relationships. At the community level, both physical and emotional closeness were identified as essential for fostering a sense of belonging.
This study highlights that opportunity and motivation to seek and enact a sense of belonging—primarily through family relationships, social ties, and supportive interactions—were critical for maintaining well-being and resilience in a time of adversity, a theme consistently reflected across the data [52,83]. However, protective health measures, combined with the fear of becoming infected or transmitting the virus to loved ones, disrupted the sense of belonging for many. While opportunities for social interaction were restricted by external regulations, the internal reluctance to engage closely with others—even those emotionally important—further diminished motivation to maintain closeness. As a result, many individuals experienced a reduced sense of belonging, which in turn challenged their ability to adapt and maintain well-being.
These findings reinforce earlier research that highlights the essential need for social connectedness in promoting well-being in later life [80].
For instance, a Colombian participant said:
“It was a lot of confinement … it gave me a lot of monotony, boredom, and made me sick (…) That isolation factor seemed cruel and severe to me”. (Social well-being; CO SH05; p. 13) [51].
These findings align with earlier research that emphasises the importance of regular, emotionally supportive, meaningful, and physically close relationships in enhancing well-being in later life [42,48,68,80].
Findings at the community level emphasised that the fundamental need for psychological and social well-being is both universal and diverse—intensified during health crises and shaped by individual life experiences—as demonstrated in the systematic literature review by [7]. Moreover, the findings draw attention to the dynamic interplay between personal resources and meaningful social relationships within the community, highlighting how support mechanisms and social protective regulations influenced individuals’ well-being, particularly during times of health crisis.
5.3. Societal Level
The findings of this study, based on research conducted during the COVID-19 pandemic, are grounded in the societal level of the ecological framework of well-being [46]. During the pandemic, public health measures focused on protecting those identified as vulnerable—primarily older adults aged 70 and above, and individuals with pre-existing medical conditions or non-communicable diseases. This classification was informed by early data showing that these groups were at greater risk of severe illness or mortality if infected with the virus. Hence, risk communication and societal perceptions have shifted in many countries towards viewing older adults as needing protection and support. This perspective contributed to a narrative that underestimated their autonomy and ability to make independent, informed decisions [3,75,84]. CO SH02 told:
“Oh no, that you have to take care of them (older adults) (…), at this age one has more responsibility and one knows to care better than any 20-year-old kid (…) they annoyed me (…) (Social policy; CO SH02) [51] (p. 16).
Although well-intentioned, the classification of older adults as vulnerable led to paternalistic and age-based regulations. Many countries adopted this approach, which had already been subject to critical scrutiny [7,51,75,85].
Participants expressed mixed views on these regulations. While some perceived them as beneficial, others found them restrictive or even hostile. For example, one participant from the UK shared:
“I don’t think I fit the bill that needs to be cocooned yet. I possibly do medically, I don’t know, but I don’t mentally feel that I want to be cocooned. (Social policy; M4W1UK) [51] (p. 15).
In Colombia, initial mandatory regulations during the COVID-19 pandemic were perceived by some older adults as a form of increased societal recognition. However, this perception shifted over time, as older individuals were subjected to stricter limitations—such as being prohibited from exercising outdoors or leaving their home, restrictions not equally applied to the rest of the population. CO AH03 reported that:
“The pandemic made us visible … The president by a mandatory lockdown also made an acknowledgement that we existed, and later we had to reveal (legal action) ourselves so that they let us release from the lockdown, because it was too excessive (lockdown).” (Culture; CO AH03) [51] (p. 17).
Subsequently, many participants from Colombia perceived these age-based regulations as hostile or discriminatory, prompting legal challenges from a group of plaintiffs seeking to uphold human rights during the pandemic [Separated, Locked Down, and Unequal: The Grey Hair Revolution’s resistance to draconian quarantine in Colombia|OHRH]. In the UK, some participants appreciated the protective measures, interpreting them as a sign of being valued and cared for. However, others strongly rejected the label of vulnerability, expressing frustration at being categorised in a way that they felt diminished their autonomy and negatively affected their well-being. These findings align with Swift and Chasteen’s [6] research, which warned against the stereotyping, homogenisation, and stigmatisation of older adults—practices that can significantly undermine well-being in later life [7,51].
It is understood that cultural norms and values shape human experiences, as Henrich et al. [73] discuss in detail. As this study included two distinct cultural backgrounds the analysis identified notable differences for example, many participants in the UK found emotional support through companionship and positive sensory stimuli from pets [86], while the majority of Colombian participants found stress relief through religious faith and practices [7,87]. This finding highlights the interplay of individual adaptation resources and cultural differences.
The analysis in this study brought to the fore how paternalistic regulations during the COVID-19 pandemic contributed to a rise in ageism, and was particularly evident at the societal level, where protective measures, often well-intentioned, reinforced stereotypes and unequal treatment. As a result, many participants reported increased experiences of discrimination, and some described feeling marginalised, especially older people who were subject to restrictive policies and public narratives [88,89,90]. Age-based regulations and the categorisation of older adults as physically vulnerable contributed not only to physical restrictions but also to psychosocial challenges, including increased isolation and loneliness [11], and overall reduced well-being [7,51,84]. Whether these measures were advisory or mandatory, the persistent labelling of older adults as vulnerable often led to internalised stigma, self-imposed limitations, self-induced autonomy, and adverse effects on well-being [91].
These findings underscore the profound influence of public policy on individuals’ self-perception, behaviour, and mental health, particularly during a health crisis. They also highlight how intersecting societal challenges—such as ageism, social exclusion, and unequal access to resources—were intensified during the pandemic, placing additional burdens on older populations [88]. Importantly, the study illustrates the interconnectedness of individual, community, and societal factors, as reflected in the ecological model of older adults’ well-being. This became clear at the beginning of the pandemic and continued throughout, as participants shared how they received support from family members and the community. This support included having groceries delivered, receiving more frequent courtesy calls, being driven to medical appointments, and much more.
At the societal level, participants were directly affected by age-based regulations. These measures not only fostered new forms of discrimination but also restricted access to essential resources, such as healthcare services, opportunities to maintain family relationships and reciprocal support, and the ability to experience social belonging and sustain well-being [48]. The ecological framework developed in this study offers valuable insights for policymakers, emphasising the need for inclusive, supportive strategies in future health crises (for example, establishing decision-making groups, providing equal health support, maintaining social connectivity)—strategies that respect older adults’ autonomy, promote community cohesion, and strengthen social policies to enhance well-being in later life.
6. Conclusions
The analysis in this study brought to the fore a substantive Ecological Theory of Older Adults’ Well-Being in the context of the COVID-19 pandemic, developed through a qualitative synthesis of data from the C19PRC study, UK, and Colombia. This study is novel in that it integrates data from two countries experiencing rapidly changing health policies and viral threats, providing a cross-country empirical foundation.
To clarify the originality of this theory, it is useful to situate it in relation to existing frameworks. Bronfenbrenner’s ecological systems theory [92] highlights how environmental levels shape outcomes and was developed for child development. Although it was inspiring, it does not fully capture how older adults actively interpret and make meaning related to their experiences to maintain their well-being during a health crisis. Similarly, Windle and Bennett’s [31] ecological model of resilience functioned as an important sensitising concept; it emphasises adaptation to adversity in later life, whereas our theory positions resilience as one aspect of a broader understanding of well-being.
This theory extends traditional conceptualisations of well-being by demonstrating that both hedonic (joy and happiness) and eudaimonic (purpose and life satisfaction) dimensions were central to maintaining well-being in later life during the COVID-19 pandemic. However, the findings further indicate a shift in their relative salience, with eudaimonic well-being becoming more prominent under restrictive public health measures. Evidence from both countries showed that older adults sustained well-being through purposeful activities (eudaimonia) such as online meetings, intensifying reading and exercising, even as many mentioned the absence of joy associated with in-person contact with loved ones (hedonic). This finding also suggests that well-being is not only shaped by ecological contexts over time, as proposed by Bronfenbrenner [92] and by Windle and Bennett [31], but is also reconfigured by acute social disruptions, highlighting older adults’ active meaning-making in response to constrained environments.
More nuanced, this theory of older adults’ well-being during a pandemic highlights the dynamic interplay between individual, community, and societal factors in shaping their experiences. By examining the diverse and evolving challenges faced by older individuals, the study challenges prevailing stereotypes of older adults as inherently vulnerable and underscores the central role of meaningful relationships and physical proximity in maintaining well-being. In doing so, it contributes to a more nuanced appreciation of well-being in later life under conditions of adversity.
The findings reveal that older adults’ experiences were deeply embedded in their family structures, social engagements, and support networks, all of which were significantly disrupted by newly introduced health protection measures. Regardless of the constraints imposed by the pandemic, the enduring need for social connection, physical touch, and a sense of belonging remained evident. Physical distancing policies, while aimed at safeguarding health, often disrupted these connections, leading to compromised well-being such as loneliness [10].
Importantly, the study offers a critical lens on the broader societal impacts of health protection measures, particularly in relation to discrimination and intersectionality. The identification of ageism illustrates how overlapping forms of prejudice and stereotyping created distress for older adults during the crisis. This study challenges vulnerability and discriminatory narratives, highlighting the multifaceted nature of marginalisation [7].
At the same time, the study documents how many older adults actively responded to rapidly changing circumstances, demonstrating notable adaptability and strength. These responses contest the narrative of vulnerability and reflect a wide range of capacities and resources [48].
In conclusion, this research presents new insights through the development of an Ecological Theory of Older Adults’ Well-Being, specifically grounded in the context of COVID-19. It untangles the intricate interdependence of individual, community, and societal dimensions across time, marking a significant advancement in our understanding of well-being in older adults during health crises.
This ecological framework not only enriches the discourse on the well-being of older adults but also serves as a vital blueprint for future health crisis responses. It advocates for inclusive (community-centred planning, stakeholder involvement), rights-based approaches that prioritise older adults’ autonomy, enhance community cohesion, and stimulate social policies aimed at enriching well-being in later life. This novel perspective positions older adults not just as passive recipients of support but as active agents in shaping their own well-being during times of crisis.
These theoretical and empirical findings suggest that preparedness strategies for future health crises must address multiple levels simultaneously, strengthening both personal well-being and the social and structural supports that enable well-being.
Policy Recommendations for Supporting Older Adults include:
- ➢
- Foster Social Connectivity
The basic need of social connectivity and belongingness highlights that disruptions to social networks during the pandemic negatively affected well-being. Recommendation: create safe social spaces, digital access, and support networks such as support bubbles. Support measures should also integrate healthcare, mental health services, and opportunities for connection. Responsible actors: policymakers and community leaders.
- ➢
- Recognise resources and Empower Older Adults
The stereotype of older adults’ vulnerability often ignores their capacities. Recommendation: Acknowledge older adults’ adaptive strategies across cultures. Communicate risks balanced and clearly, avoiding labels, to empower informed decision-making. Responsible actors: the whole society, the media, the family, and policies.
- ➢
- Ensure Equity Through Inclusive Engagement
Health crises often exacerbate discrimination and marginalisation, as seen with the triage decisions, and increased anxiety among people in later life. Recommendation: engage older adults, communities, healthcare providers, and policymakers in co-designing health-protective measures. Address discrimination and marginalisation through intersectional, community-based approaches that ensure equitable support. Responsible actors: communities, healthcare providers, policymakers.
- ➢
- Adopt an Ecological approach [45]
Well-being and health encompass not only physical aspects but also a wide range of other factors. Recommendation: support well-being across physical, psychological, and social dimensions. Champion diversity and equity and apply tools like the WHO’s WICID (WHO-INTEGRATE COVID-19) framework to guide balanced, proportionate public health decisions. Responsible actors: policymakers, communities, the media.
By translating the ecological model of older adults’ well-being during the pandemic into concrete strategies, policymakers and community leaders can proactively support older adults’ well-being during future health crises, rather than responding reactively to social and psychological harms.
7. Limitations
Despite drawing on cross-cultural data, including a wide range and large number of participants, this study has notable limitations. UK’s Participants in this study were recruited via the C19PRC online survey, inherently excluding individuals without internet access. Consequently, the lived experiences of these populations may be underrepresented. Similarly, the data from Colombia do not represent the ageing population comprehensively due to the purposeful recruitment approach [48,51].
The analysis, grounded in constructivist grounded theory, maintained rigour through the thoughtful application of its principles, along with systematic reflection, ongoing discussions, and memoing. However, it is important to acknowledge that the researcher’s positionality influenced the process and is part of the constructivist grounded theory approach. However, the constant comparison technique does not ensure that two analysts independently analysing the same data will arrive at identical conclusions, as it involves subjective judgment and decision-making. Additionally, findings are contextually tied to the COVID-19 pandemic and might not be transferable to other social phenomena. Future research should use diverse and inclusive recruitment methods to address these limitations and test the proposed ecological framework in diverse contexts.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/jal6010018/s1: Table S1. Demographic data from the UK Wave 1, Wave 2, and Colombia.
Author Contributions
The following authors were responsible for data curation E.D.-M., K.M.B. and M.F.R.; formal analysis E.D.-M. and M.F.R.; funding acquisition K.M.B.; methodology, E.D.-M., M.F.R. and K.M.B.; supervision, K.M.B.; writing—original draft, E.D.-M.; review and editing, M.F.R., M.M.-W., A.N.-M. and K.M.B. All authors have read and agreed to the published version of the manuscript.
Funding
The initial stages of the C19PRC-research project were supported by start-up funds from the University of Sheffield (Department of Psychology, the Sheffield Methods Institute, and the Higher Education Innovation Fund via an Impact Acceleration grant administered by the university) and by the Faculty of Life and Health Sciences at Ulster University and the University of Liverpool. The research was subsequently supported by the Economic and Social Research Council (ESRC) under grant number ES/V004379/1. Interviews were conducted as part of the COVID-19 Psychological Research Consortium (C19PRC) Study (https://www.sheffield.ac.uk/psychology-consortium-covid19, accessed on 9 June 2025) and were funded by the University of Sheffield. Research undertaken in Colombia was not funded.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki. The UK’s ethical approval for the national representative study was granted by the University of Sheffield (ref: 033759) (approval date 17 March 2020). The qualitative sub-study was approved by the University of Liverpool (ref: 7632-7628) (approval date 31 March 2020). The Universidad El Bosque, Bogota-Colombia granted ethical approval for the data collection in Colombia (ref: 002-2021) (approval date 19 February 2021).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study, both verbally and in writing.
Data Availability Statement
Due to the nature of this research, participants of this study did not agree to their data being shared publicly. Data will be stored and backed up in line with the GDPR on a university drive, and it will be available only to the research team, who will be required to sign an agreement to keep the data stored only on their university computers in password-protected files. The data can be accessed on request via Brewer, Gayle (Ethics Committee), gbrewer@liverpool.ac.uk, from the University of Liverpool. The Colombian data that support the findings of this study are available from the second author, [MFR], upon reasonable request only.
Acknowledgments
The authors would like to thank the participants from the C19PRC and the participants from Colombia for giving a deep insight into their experience of the pandemic. Interviews were conducted as part of the C19PRC Study led by R.P.B.. The study in Colombia had support from the Universidad El Bosque, Bogota.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- World Health Organization (WHO). Opening Remarks at the Media Briefing on COVID-19; WHO: Geneva, Switzerland, 2020; Available online: https://www.who.int/news-room/speeches/item/who-director-general-s-opening-remarks-at-the-media-briefing-on-covid-19-12-february-2021 (accessed on 15 January 2026).
- Unwin, R. The 1918 influenza pandemic: Back to the future? Kidney Blood Press. Res. 2021, 46, 639–646. [Google Scholar] [CrossRef] [Scilit]
- Department of Health and Social Care (DHSC). Analysis of the Health, Economic and Social Effects of COVID-19 and the Approach to Tiering; DHSC: Cambridge, UK, 2020. Available online: https://assets.publishing.service.gov.uk/media/5fd9ee5ad3bf7f40cfeda349/Analysis_of_the_health_economic_and_social_effects_of_COVID-19_and_the_approach_to_tiering_FINAL_-_accessible_v2.pdf (accessed on 15 January 2026).
- Ayouni, I.; Maatoug, J.; Dhouib, W.; Zammit, N.; Fredj, S.B.; Ghammam, R.; Ghannem, H. Effective public health measures to mitigate the spread of COVID-19: A systematic review. BMC Public Health 2021, 21, 1015. [Google Scholar] [CrossRef] [Scilit]
- Levin, A.T.; Hanage, W.P.; Owusu-Boaitey, N.; Cochran, K.B.; Walsh, S.P.; Meyerowitz-Katz, G. Assessing the age specificity of infection fatality rates for COVID-19. Eur. J. Epidemiol. 2020, 35, 1123–1138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Swift, H.J.; Chasteen, A.L. Ageism in the time of COVID-19. Group Process. Intergroup Relat. 2021, 24, 246–252. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Reyes-Rodriguez, M.-F.; Soulsby, L.K.; Roper, L.; Bennett, K.M. Older adults’ experiences during the COVID-19 pandemic: A qualitative systematic literature review. BMC Geriatr. 2023, 23, 580. [Google Scholar] [CrossRef] [Scilit]
- Anwar, A.; Malik, M.; Raees, V.; Anwar, A. Role of mass media and public health communications in the COVID-19 pandemic. Cureus 2020, 12, e10453. [Google Scholar] [CrossRef] [Scilit]
- Agrawal, A.; Gindodiya, A.; Deo, K.A.; Kashikar, S.; Fulzele, P.; Khatib, N. A comparative analysis of the Spanish flu 1918 and COVID-19 pandemics. Open Public Health J. 2021, 14, 128–134. [Google Scholar] [CrossRef] [Scilit]
- Jain, S.; Dhall, M. Social isolation in COVID-19: Impact of loneliness and NCDs on mental and physical health of older adults. In Handbook of Aging, Health and Public Policy; Rajan, S.I., Ed.; Springer: Singapore, 2025. [Google Scholar] [CrossRef] [Scilit]
- Yang, F.; Gu, D. Strengthening social connections to address loneliness in older adults. Lancet Healthy Longev. 2025, 6, 100682. [Google Scholar] [CrossRef] [Scilit]
- Lagacé, M.; Bergeron, C.; O’Sullivan, T.; Oostlander, S.; Dangoisse, P.; Doucet, A.; Rodrigue-Rouleau, P. The Paradox of Protecting the Vulnerable; Routledge: London, UK, 2024. [Google Scholar] [CrossRef] [Scilit]
- Guzman, V.; Doyle, F.; Foley, R.; Craven, P.; Crowe, N.; Wilson, P.; Smith, A.; Hegarty, G.; Pertl, M.M. Socio-ecological determinants of older people’s mental health and well-being during COVID-19. Front. Public Health 2023, 11, 1148758. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Klausen, S.H. Understanding older adults’ well-being from a philosophical perspective. J. Happiness Stud. 2020, 21, 2629–2648. [Google Scholar] [CrossRef] [Scilit]
- Paltasingh, T. Theories and concepts in gerontology. In Disciplines and Discourses; Royal College of Surgeons in Ireland: Dublin, UK, 2015; pp. 19–38. [Google Scholar]
- Biggs, S.; Lowenstein, A.; Hendricks, J.; Katz, S. The need for theory: Critical approaches to social gerontology. In Critical Gerontological Theory; Springer: Cham, Switzerland, 2021; pp. 15–31. [Google Scholar]
- Kim, E.S.; Tkatch, R.; Martin, D.; MacLeod, S.; Sandy, L.; Yeh, C. Resilient Aging: Psychological Well-Being and Social Well-Being as Targets for the Promotion of Healthy Aging. Gerontol. Geriatr. Med. 2021, 7, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Harman, D. Aging: A theory based on free radical and radiation chemistry. J. Gerontol. 1956, 11, 298–300. [Google Scholar] [CrossRef] [Scilit]
- Harman, D. Free radical theory of aging: An update. Ann. N. Y. Acad. Sci. 2006, 1067, 10–21. [Google Scholar] [CrossRef] [Scilit]
- Peters, R. Ageing and the brain. Postgrad. Med. J. 2006, 82, 84–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Havighurst, R.J. Social roles, work, leisure, and education. In The Psychology of Adult Development and Aging; Eisdorfer, C., Lawton, M.P., Eds.; APA: Washington, DC, USA, 1973; pp. 598–618. [Google Scholar] [CrossRef] [Scilit]
- Baltes, P.B.; Baltes, M.M. Psychological perspectives on successful aging. In Successful Aging; Cambridge University Press: Cambridge, UK, 1990; pp. 1–34. [Google Scholar] [CrossRef] [Scilit]
- Lawton, M.P. Environment and other determinants of well-being in older people. Gerontologist 1983, 23, 349–357. [Google Scholar] [CrossRef] [Scilit]
- Wahl, H.-W.; Iwarsson, S.; Oswald, F. Aging well and the environment. Gerontologist 2012, 52, 306–316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Estes, C.L.; Binney, E.A.; Culbertson, R.A. The gerontological imagination. Int. J. Aging Hum. Dev. 1992, 35, 49–65. [Google Scholar] [CrossRef] [Scilit]
- Baars, J.; Dannefer, D.; Phillipson, C.; Walker, A. Introduction: Critical perspectives in gerontology. In Aging, Globalization and Inequality; Baywood: New York, NY, USA, 2006; pp. 1–14. [Google Scholar]
- Bernard, M.; Scharf, T. Critical perspectives on ageing societies. In Critical Perspectives on Ageing Societies; Policy Press: Bristol, UK, 2007; pp. 3–12. [Google Scholar]
- Hendricks, J.; Achenbaum, A. Historical development of theories of aging. In Handbook of Theories of Aging; Bengtson, V.L., Schaie, K.W., Eds.; Springer: New York, NY, USA, 1999; pp. 21–39. [Google Scholar]
- Feliciano, E.; Feliciano, A.; Palompon, D.; Boshra, A. Aging-related resiliency theory development. Belitung Nurs. J. 2022, 8, 4–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carstensen, L.L. The influence of a sense of time on human development. Science 2006, 312, 1913–1915. [Google Scholar] [CrossRef] [Scilit]
- Windle, G.; Bennett, K.M. Resilience and caring relationships. In The Social Ecology of Resilience; Ungar, M., Ed.; Springer: New York, NY, USA, 2011; pp. 219–232. [Google Scholar]
- Glaser, B.; Strauss, A. The Discovery of Grounded Theory; Aldine: New York, NY, USA, 1967. [Google Scholar]
- Timmermans, S. There’s more to dying than death. In The SAGE Handbook of Qualitative Methods in Health Research; Sage: London, UK, 2010; pp. 19–33. [Google Scholar] [CrossRef] [Scilit]
- Forde, A.I. The American Founding Documents and Democratic Social Change. Ph.D. Dissertation, Walden University, Minneapolis, MN, USA, 2023. [Google Scholar]
- Strauss, A.; Corbin, J. Basics of Qualitative Research; Sage: Newbury Park, CA, USA, 1990. [Google Scholar]
- Charmaz, K. Constructing Grounded Theory, 2nd ed.; Sage: London, UK, 2014. [Google Scholar]
- Charmaz, K. Constructing Grounded Theory: A Practical Guide Through Qualitative Analysis; Sage: London, UK, 2006. [Google Scholar]
- Crotty, M. The Foundations of Social Research; Sage: London, UK, 1998. [Google Scholar]
- Jarden, A.; Roache, A. What is well-being? Int. J. Environ. Res. Public Health 2023, 20, 5006. [Google Scholar] [CrossRef] [Scilit]
- Diener, E.; Suh, E.; Lucas, R.; Smith, H. Subjective well-being. Psychol. Bull. 1999, 125, 276–302. [Google Scholar] [CrossRef]
- Ryan, R.M.; Deci, E.L. On happiness and human potentials. Annu. Rev. Psychol. 2001, 52, 141–166. [Google Scholar] [CrossRef] [Scilit]
- Ryff, C.D. Happiness is everything, or is it? J. Pers. Soc. Psychol. 1989, 57, 1069–1081. [Google Scholar] [CrossRef]
- Diener, E. Subjective well-being. Am. Psychol. 2000, 55, 34–43. [Google Scholar] [CrossRef] [PubMed]
- Ryff, C.D.; Keyes, C.L.M. The structure of psychological well-being revisited. J. Pers. Soc. Psychol. 1995, 69, 719–727. [Google Scholar] [CrossRef]
- Dey, I. Qualitative Data Analysis; Routledge: London, UK, 2003. [Google Scholar]
- Derrer-Merk, E. What Were Older Adults’ Psychological and Societal Experiences During the COVID-19 Pandemic? Ph.D. Thesis, University of Liverpool, Liverpool, UK, 2025. [Google Scholar]
- McBride, O.; Butter, S.; Murphy, J.; Shevlin, M.; Hartman, T.K.; Hyland, P.; McKay, R.; Bennett, K.M.; Gibson-Miller, J.; Levita, L.; et al. Context, design and conduct of the longitudinal COVID-19 psychological research consortium study. Int. J. Methods Psychiatr. Res. 2021, 30, e1880. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Reyes-Rodriguez, M.-F.; Baracaldo, P.; Guevara, M.; Rodríguez, G.; Fonseca, A.-M.; Bentall, R.P.; Bennett, K.M. Adapting in later life during a health crisis —Loro Viejo Sí Aprende a Hablar: A Grounded Theory of Older Adults’ Adaptation Processes in the UK and Colombia. J. Ageing Longev. 2025, 5, 22. [Google Scholar] [CrossRef] [Scilit]
- Halkier, B. Questioning the “gold standard” in qualitative methods. In Methodological Reflections on Practice Oriented Theories; Springer: Cham, Switzerland, 2017. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Ferson, S.; Mannis, A.; Bentall, R.P.; Bennett, K.M. Older people’s family relationships during COVID-19. Ageing Soc. 2022, 44, 721–738. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Reyes-Rodriguez, M.; Salazar, A.; Guevara, M.; Rodríguez, G.; Fonseca, A.; Camacho, N.; Ferson, S.; Mannis, A.; Bentall, R.P.; et al. Is protecting older adults from COVID-19 ageism? J. Soc. Issues 2022, 78, 900–923. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Ferson, S.; Mannis, A.; Bentall, R.P.; Bennett, K.M. Belongingness challenged. PLoS ONE 2022, 17, e0276561. [Google Scholar] [CrossRef] [Scilit]
- Blumer, H. Symbolic Interactionism; Prentice Hall: Englewood Cliffs, NJ, USA, 1969. [Google Scholar]
- Glaser, B.G. Theoretical Sensitivity; Sociology Press: Mill Valley, CA, USA, 1978. [Google Scholar]
- Vasileiou, K.; Barnett, J.; Thorpe, S.; Young, T. Characterising and justifying sample size sufficiency in interview-based studies: Systematic analysis of qualitative health research over a 15-year period. BMC Med. Res. Methodol. 2018, 18, 148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tight, M. Saturation: An overworked and misunderstood concept? Qual. Inq. 2023, 30, 577–583. [Google Scholar] [CrossRef] [Scilit]
- Derrer-Merk, E.; Jain, L.; Noori-Kalkhoran, O.; Taylor, R.; Drury, M.; Stain, T.; Merk, B. From fishing village to atomic town. PLoS ONE 2024, 19, e0310144. [Google Scholar] [CrossRef] [Scilit]
- Birks, M.; Mills, J. Grounded Theory: A Practical Guide, 3rd ed.; Sage: London, UK, 2023. [Google Scholar]
- Saldaña, J. The Coding Manual for Qualitative Researchers; Sage: Thousand Oaks, CA, USA, 2021. [Google Scholar]
- Charmaz, K.; Thornberg, R. The pursuit of quality in grounded theory. Qual. Res. Psychol. 2021, 18, 305–327. [Google Scholar] [CrossRef] [Scilit]
- Bowen, G.A. Grounded theory and sensitizing concepts. Int. J. Qual. Methods 2006, 5, 12–23. [Google Scholar] [CrossRef] [Scilit]
- Guo, X.; Franco, O.H.; Laine, J.E. Accelerated ageing in the COVID-19 pandemic. Maturitas 2022, 157, 68–69. [Google Scholar] [CrossRef] [Scilit]
- Schultze-Lutter, F.; Schimmelmann, B.G.; Schmidt, S.J. Resilience, risk, mental health and well-being. Eur. Child Adolesc. Psychiatry 2016, 25, 459–466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Diener, E. Subjective well-being. In The Science of Well-Being; Springer: Dordrecht, The Netherlands, 2009; pp. 11–58. [Google Scholar] [CrossRef] [Scilit]
- Keyes, C.L.M. Social well-being. Soc. Psychol. Q. 1998, 61, 121–140. [Google Scholar] [CrossRef] [Scilit]
- Seligman, M.E.P.; Peterson, C. Positive clinical psychology. In A Psychology of Human Strengths; APA: Washington, DC, USA, 2003; pp. 305–317. [Google Scholar] [CrossRef] [Scilit]
- Carstensen, L.L. Evidence for a life-span theory of socioemotional selectivity. Curr. Dir. Psychol. Sci. 1995, 4, 151–156. [Google Scholar] [CrossRef] [Scilit]
- Carstensen, L.L. Socioemotional selectivity theory. Gerontologist 2021, 61, 1188–1196. [Google Scholar] [CrossRef] [Scilit]
- House, J.S.; Robbins, C.; Metzner, H.L. Social relationships and mortality. Am. J. Epidemiol. 1982, 116, 123–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ivankina, L.; Ivanova, V. Social well-being of elderly people. SHS Web Conf. 2016, 28, 01046. [Google Scholar] [CrossRef] [Scilit]
- Uzuki, T.; Konta, T.; Saito, R.; Sho, R.; Osaki, T.; Souri, M.; Watanabe, M.; Ishizawa, K.; Yamashita, H.; Ueno, Y.; et al. Social support status and mortality. BMC Public Health 2020, 20, 1630. [Google Scholar] [CrossRef] [Scilit]
- Gilleard, C.; Higgs, P. Cultures of Ageing; Prentice Hall: Harlow, UK, 2000. [Google Scholar]
- Henrich, J.; Blasi, D.E.; Curtin, C.M.; Davis, H.E.; Hong, Z.; Kelly, D.; Kroupin, I. A cultural species and its cognitive phenotypes. Rev. Philos. Psychol. 2023, 14, 349–386. [Google Scholar] [CrossRef] [Scilit]
- Jarego, M.; Tasker, F.; Costa, P.A.; Pais-Ribeiro, J.; Ferreira-Valente, A. Older adults’ adjustment to COVID-19 lockdowns. Curr. Psychol. 2024, 43, 26593–26607. [Google Scholar] [CrossRef] [Scilit]
- Ayalon, L. Ageism and intergenerational tension in COVID-19. Int. Psychogeriatr. 2020, 32, 1221–1224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, J.J.; Dalton, A.N.; Lee, J. The self under COVID-19: Social role disruptions, self-authenticity and present-focused coping. PLoS ONE 2021, 16, e0256939. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naughton, F.; Ward, E.; Khondoker, M.; Belderson, P.; Marie Minihane, A.; Dainty, J.; Hanson, S.; Holland, R.; Brown, T.; Notley, C. Health behaviour change during UK lockdown. Br. J. Health Psychol. 2021, 26, 624–643. [Google Scholar] [CrossRef] [Scilit]
- Voinea, C.; Wangmo, T.; Vică, C. Respecting older adults. J. Bioeth. Inq. 2022, 19, 213–223. [Google Scholar] [CrossRef] [Scilit]
- Keyes, C.L.; Shmotkin, D.; Ryff, C.D. Optimizing well-being. J. Pers. Soc. Psychol. 2002, 82, 1007–1022. [Google Scholar] [CrossRef]
- Yang, Q.; Wang, Y.; Tian, C.; Chen, Y.; Mao, J. Experiences of community-dwelling older adults during lockdown. J. Adv. Nurs. 2021, 77, 4805–4814. [Google Scholar] [CrossRef] [Scilit]
- Windle, G.; Bennett, K.M.; MacLeod, C. The Influence of Life Experiences on the Development of Resilience in Older People With Co-morbid Health Problems. Front. Med. 2020, 7, 502314. [Google Scholar] [CrossRef] [Scilit]
- Cohen, S.; McKay, G. Social support, stress and the buffering hypothesis. In Handbook of Psychology and Health; Erlbaum: Hillsdale, NJ, USA, 1984; pp. 253–267. [Google Scholar]
- Allen, K.-A.; Arslan, G.; Craig, H.; Arefi, S.; Yaghoobzadeh, A.; Nia, H.S. The psychometric evaluation of the sense of belonging instrument (SOBI) with Iranian older adults. BMC Geriatr. 2021, 21, 211. [Google Scholar] [CrossRef] [Scilit]
- Vasara, P.; Simola, A.; Olakivi, A. Narrating ageing during the COVID-19 pandemic. J. Aging Stud. 2023, 64, 101106. [Google Scholar] [CrossRef] [Scilit]
- Ehni, H.-J.; Wahl, H.-W. Six propositions against ageism. J. Aging Soc. Policy 2020, 32, 515–525. [Google Scholar] [CrossRef] [Scilit]
- von Humboldt, S.; Silva, S.; Leal, I. Older adults’ experiences of pet companionship. Educ. Gerontol. 2024, 50, 609–620. [Google Scholar] [CrossRef] [Scilit]
- Sisti, L.G.; Buonsenso, D.; Moscato, U.; Costanzo, G.; Malorni, W. Role of religions in the COVID-19 pandemic. Int. J. Environ. Res. Public Health 2023, 20, 1691. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramirez, L.; Monahan, C.; Palacios-Espinosa, X.; Levy, S.R. Intersections of ageism during COVID-19. J. Soc. Issues 2022, 78, 965–990. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sublett, J.; Bisconti, T. Benevolent ageism in older adults. Innov. Aging 2020, 4, 569. [Google Scholar] [CrossRef] [Scilit]
- Visintin, E.P. Contact with older people and ageism. J. Community Appl. Soc. Psychol. 2021, 31, 314–325. [Google Scholar] [CrossRef] [Scilit]
- Butler, R.N. Age-ism: Another form of bigotry. Gerontologist 1969, 9, 243–246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bronfenbrenner, U. Ecological systems theory. In Encyclopedia of Psychology; Kazdin, A.E., Ed.; Oxford University Press: Oxford, UK, 2000; Volume 3, pp. 129–133. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.