


Abstract
Background: The global prevalence of oral disease including dental caries varies significantly across different regions, and South Africa is no exception. Although dental caries is a major public health concern, it is largely preventable through the promotion of proper oral hygiene practices and screening. The study aimed to assess the oral health status of school children within selected primary schools in the Tshwane District, South Africa. Methods: The study used a quasi-experimental design employing a quantitative research approach, structured into three phases: a pre-test assessment, the implementation of the intervention, and a post-test evaluation. A total of 390 primary school learners from five selected schools underwent dental screening and were included in the study on a voluntary basis. Data analysis was conducted using IBM SPSS version 30, incorporating both descriptive and inferential statistical tools. Results: Prior to screening, 75.9% of participants exhibited dental caries, while only 24.1% showed no signs of tooth decay. Following the intervention, improvements in oral hygiene status were observed among participants. The proportion of children presenting with high plaque scores decreased markedly from 19.0% at baseline to 1.8% post-intervention. Similarly, the prevalence of poor oral hygiene declined from 30.1% pre-intervention to 16.2% after the intervention, indicating an overall enhancement in hygiene practices. The proportion of dmft in primary teeth recorded 37.3% pre intervention, higher than post intervention (23.2%). Additionally, the record of DMFT in permanent teeth (49.2%) pre-intervention compared to the post intervention (40.8%). The study reported a similar percentage on the treatment during pre and post intervention (75.9%). Conclusions: Dental screening intervention yielded promising short-term results, particularly in plaque reduction and caries detection. However, its long-term success hinges on integrating school efforts with parental support and improving access to follow-up dental care. A comprehensive, multi-stakeholder approach remains essential to ensure lasting oral health benefits for children.
1. Introduction
Oral health issues, including dental caries, periodontal diseases, and tooth loss, are not only major public health concerns but also have far-reaching effects on overall well-being and oral health-related quality of life [1,2]. Untreated dental caries continues to pose a substantial public health burden in various regions worldwide, particularly in Latin America and the Caribbean, where over two billion individuals, including a significant proportion of 12-year-olds, are affected [3]. Despite global efforts to curb this issue, the most recent findings from the Global Burden of Disease Study reveal that the worldwide prevalence of untreated dental caries has only declined by a marginal 4% over the last decade. This rate of reduction is notably slower than the more pronounced decrease observed over the preceding 30 years [4]. The modest decline has been largely attributed to increased awareness, often fostered through targeted oral health screening initiatives.
In Sub-Saharan Africa, similar challenges persist. Ref. [5] reported that, although the prevalence of dental caries in their study population did not significantly exceed national or regional averages, possibly due to local dietary patterns, critical oral health concerns remained. A substantial number of carious lesions were left untreated, and this was due to a lack of access to dental services. Untreated early childhood dental caries can lead to a variety of negative outcomes, most notably pain, along with other functional and quality-of-life impairments such as sleep disturbances and missing school. Children from socioeconomically disadvantaged backgrounds are especially susceptible to such conditions, as highlighted by [6,7].
If not addressed promptly, dental caries may adversely impact a child’s physical growth, cognitive development, systemic health, and general quality of life. While typically not life-threatening, untreated caries can progress to serious complications, such as abscess formation, cellulitis, premature tooth loss, and, in extreme cases, hospitalization or the administration of general anesthesia [5].
In the South African context, data from the National Oral Health Policy and Strategy (NOHPS) 2024–2035 indicates that approximately 60% of six-year-old children exhibit dental decay in their primary teeth, with 55% of these cases remaining untreated. Ref. [8] further established a statistically significant correlation between age and the Decayed, Missing, and Filled Teeth (DMFT) index, suggesting an age-related increase in the prevalence of untreated caries. Although dental caries is highly preventable through effective oral hygiene practices and improved dietary habits [9], it remains a pressing concern, especially among children. This underscores the urgent need for comprehensive oral health education and routine screening within school systems.
Furthermore, untreated dental caries is a widespread issue throughout South Africa’s nine provinces. In Gauteng province, for example, prevalence rates reach 37% among children aged 4–5 and rise to 50% among six-year-olds (NOHPS, 2024–2035). Although overall caries prevalence in South Africa appears moderate in comparison to global data, ref. [10] found that over 89% of affected children had untreated caries. Alarmingly, approximately 70% of dental caries in children aged 6, 12, and 15 remain unaddressed, with serious implications for their daily functioning. These include interference with eating, sleeping, school attendance, and, in severe cases, infection and the need for tooth extractions [11].
Given these challenges, prioritizing early oral health screening and preventive education are essential. Providing children with foundational dental care knowledge and practices during their formative years will instill lifelong oral hygiene habits, thereby mitigating the incidence and impact of oral diseases that are largely preventable. Promoting oral health literacy and preventive care among school-aged children is equally essential to improving long-term oral health outcomes and aligns with Sustainable Development Goal 3, which advocates good health and well-being for individuals across all age groups. Within the context of this study, it is important to implement a routine oral health screening among primary school learners to facilitate early detection, prompt management or referral of identified conditions, and to minimize the risk of complications arising from untreated oral disease.
2. Research Methods and Design
2.1. Study Design
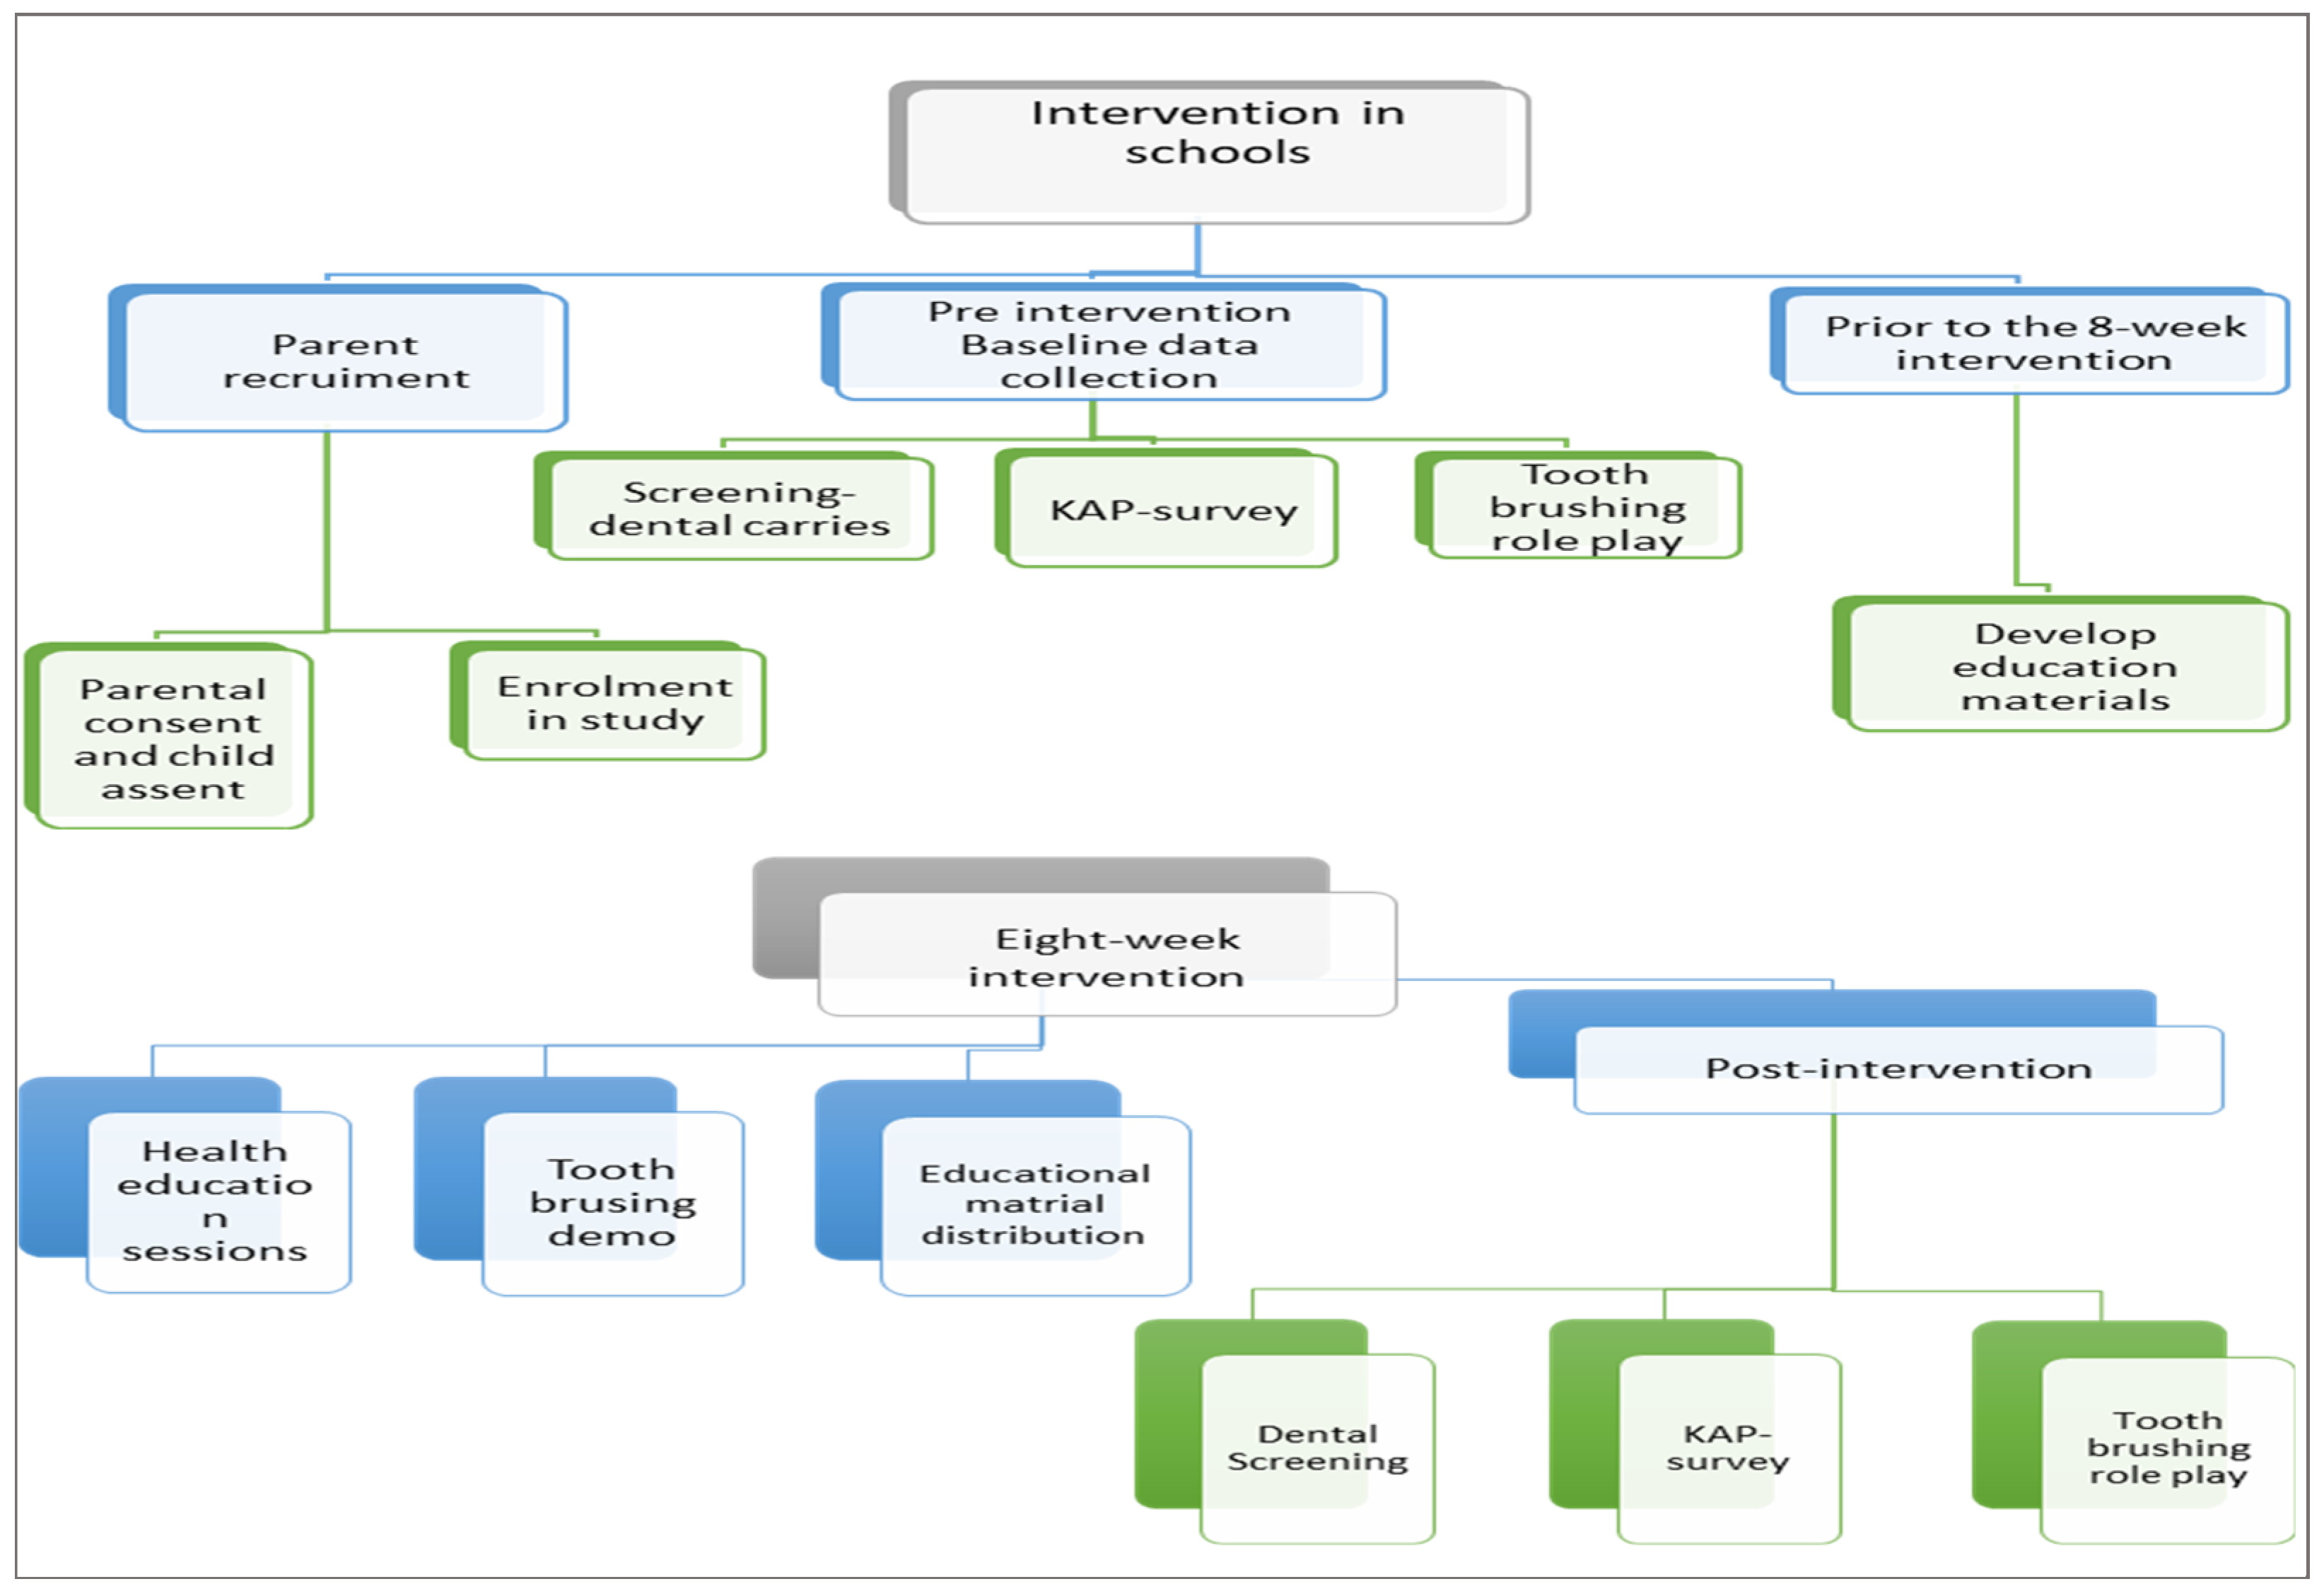
A quasi-experimental study design incorporating pre-intervention (pre-test), intervention, and post-intervention (post-test) phases was adopted to assess changes in the oral health status of primary school children in selected schools within Ga-Rankuwa, Tshwane District, South Africa. The design was chosen as it allows evaluation of intervention effects in a real-world school setting where randomisation was not feasible. Dental screening was conducted by dental professionals examining children’s mouths and teeth at school and letting parents know about their child’s oral condition and treatment needs. For children requiring treatment, personalized referral letters were given to children for them to attend dental appointments. The dental screening was supplemented with oral health motivation using oral health education material. The intervention included the age-appropriate oral health education sessions and supervised toothbrushing demonstrations to reinforce correct oral hygiene practices. Quantitative data were collected using structured clinical screening forms. The study design was summarized under Figure 1, accompanying schematic, outlining participant selection, allocation procedures, the intervention workflow, and the scheduled time points for outcome measurements.
Figure 1.
Methodological approach.
2.2. Setting
For this study, research activities were carried out in primary schools situated in Ga-Rankuwa, a township within the City of Tshwane, located in the Gauteng Province, South Africa. The City of Tshwane Metropolitan Municipality comprises three distinct school districts: Tshwane West, Tshwane North, and Tshwane South. The selected schools were located within the Tshwane West district and formed part of routine outreach services provided by Sefako Makgatho Health Sciences University (SMU) oral health program.
2.3. Study Population, Sample Size and Sampling
A purposive sampling technique was initially used to select five primary schools that were routinely serviced by the SMU oral health outreach program. Proportional allocation was applied based on school enrolment numbers to ensure balanced representation across schools. Learners were selected using a multistage sampling approach. Classes were first stratified by grade level, and then one class per grade was randomly selected using simple random sampling. All learners in selected classes were invited to participate, and inclusion was based on parental consent and child assent. Approximately 390 primary school children from Grades 3 to 7 participated in the study. The sample size was determined using a 95% confidence level and a 5% margin of error, based on an expected proportion derived from findings in similar school-based oral health studies. An allowance was included to account for possible non-response and incomplete data, ensuring that the final sample remained adequate for analysis.
2.4. Data Collection Process
Data were collected at baseline, one month, and two months post-intervention using standardized questionnaires and clinical screening forms administered by trained dental health professionals. Baseline findings informed the development of the educational intervention, while follow-up assessments were conducted to evaluate changes in participants’ knowledge after the intervention.
Oral examinations were conducted in classroom settings, with learners seated under adequate natural and/or artificial lighting to ensure proper visibility. Clinical assessments were performed by oral hygienists using sterile mouth mirrors and dental probes, in accordance with standard infection prevention and control procedures implemented by a qualified dental assistant. Dental caries was assessed using WHO diagnostic criteria and recorded as DMFT (permanent dentition) and dmft (primary dentition) indices. In addition, plaque accumulation was measured using a standardized plaque index for each participant.
To ensure consistency in measurements, two qualified oral hygienists underwent training prior to data collection, and calibration sessions were conducted through joint assessments to standardized scoring in line with WHO guidelines; however, formal inter- and intra-examiner reliability coefficients were not recorded.
The educational intervention was developed based on baseline findings and validated prior to implementation to ensure accuracy, clarity, and suitability for the target group. Validation was conducted through expert review involving oral health professionals, including dental therapists, oral hygienists, and public health practitioners, using the Delphi technique.
During the intervention phase, learners received age-appropriate oral health education supported by visual materials and demonstrations of correct toothbrushing techniques. The program consisted of four sessions delivered on separate days, each lasting approximately 45 min. The sessions focused on preventive oral health practices, including the circular toothbrushing technique, recommended brushing frequency, and the role of fluoride. Practical demonstrations were followed by observation of learners to reinforce correct brushing behavior and assess understanding.
2.5. Data Analysis
Data were entered into Microsoft Excel, cleaned, coded, and exported to IBM SPSS version 30 Statistics software for analysis. The Wilcoxon signed rank, Bowker’s and McNemar’s test for symmetry were performed to assess the oral health status and tooth decay of school children within selected primary schools before and after the intervention. A p-value of less than 0.05 was considered statistically significant.
2.6. Ethical Considerations
The University of Limpopo Research Ethics Committee approved the study protocol (TREC/123/2024: PG). Additionally, permissions to conduct the study were given by the Basic Department of Education, Gauteng Province, Tshwane West Circuit Management, and principals of the five selected primary schools. Written informed consent from parents/guardians and child assent were obtained before the study began. Participants were informed about voluntary participation and the right to withdraw during the research. The participants were fully informed about the purpose of the study and assured of anonymity and confidentiality. Alphabetical codes were used to identify the questionnaire data.
3. Results
3.1. Dental Health Outcomes of Children
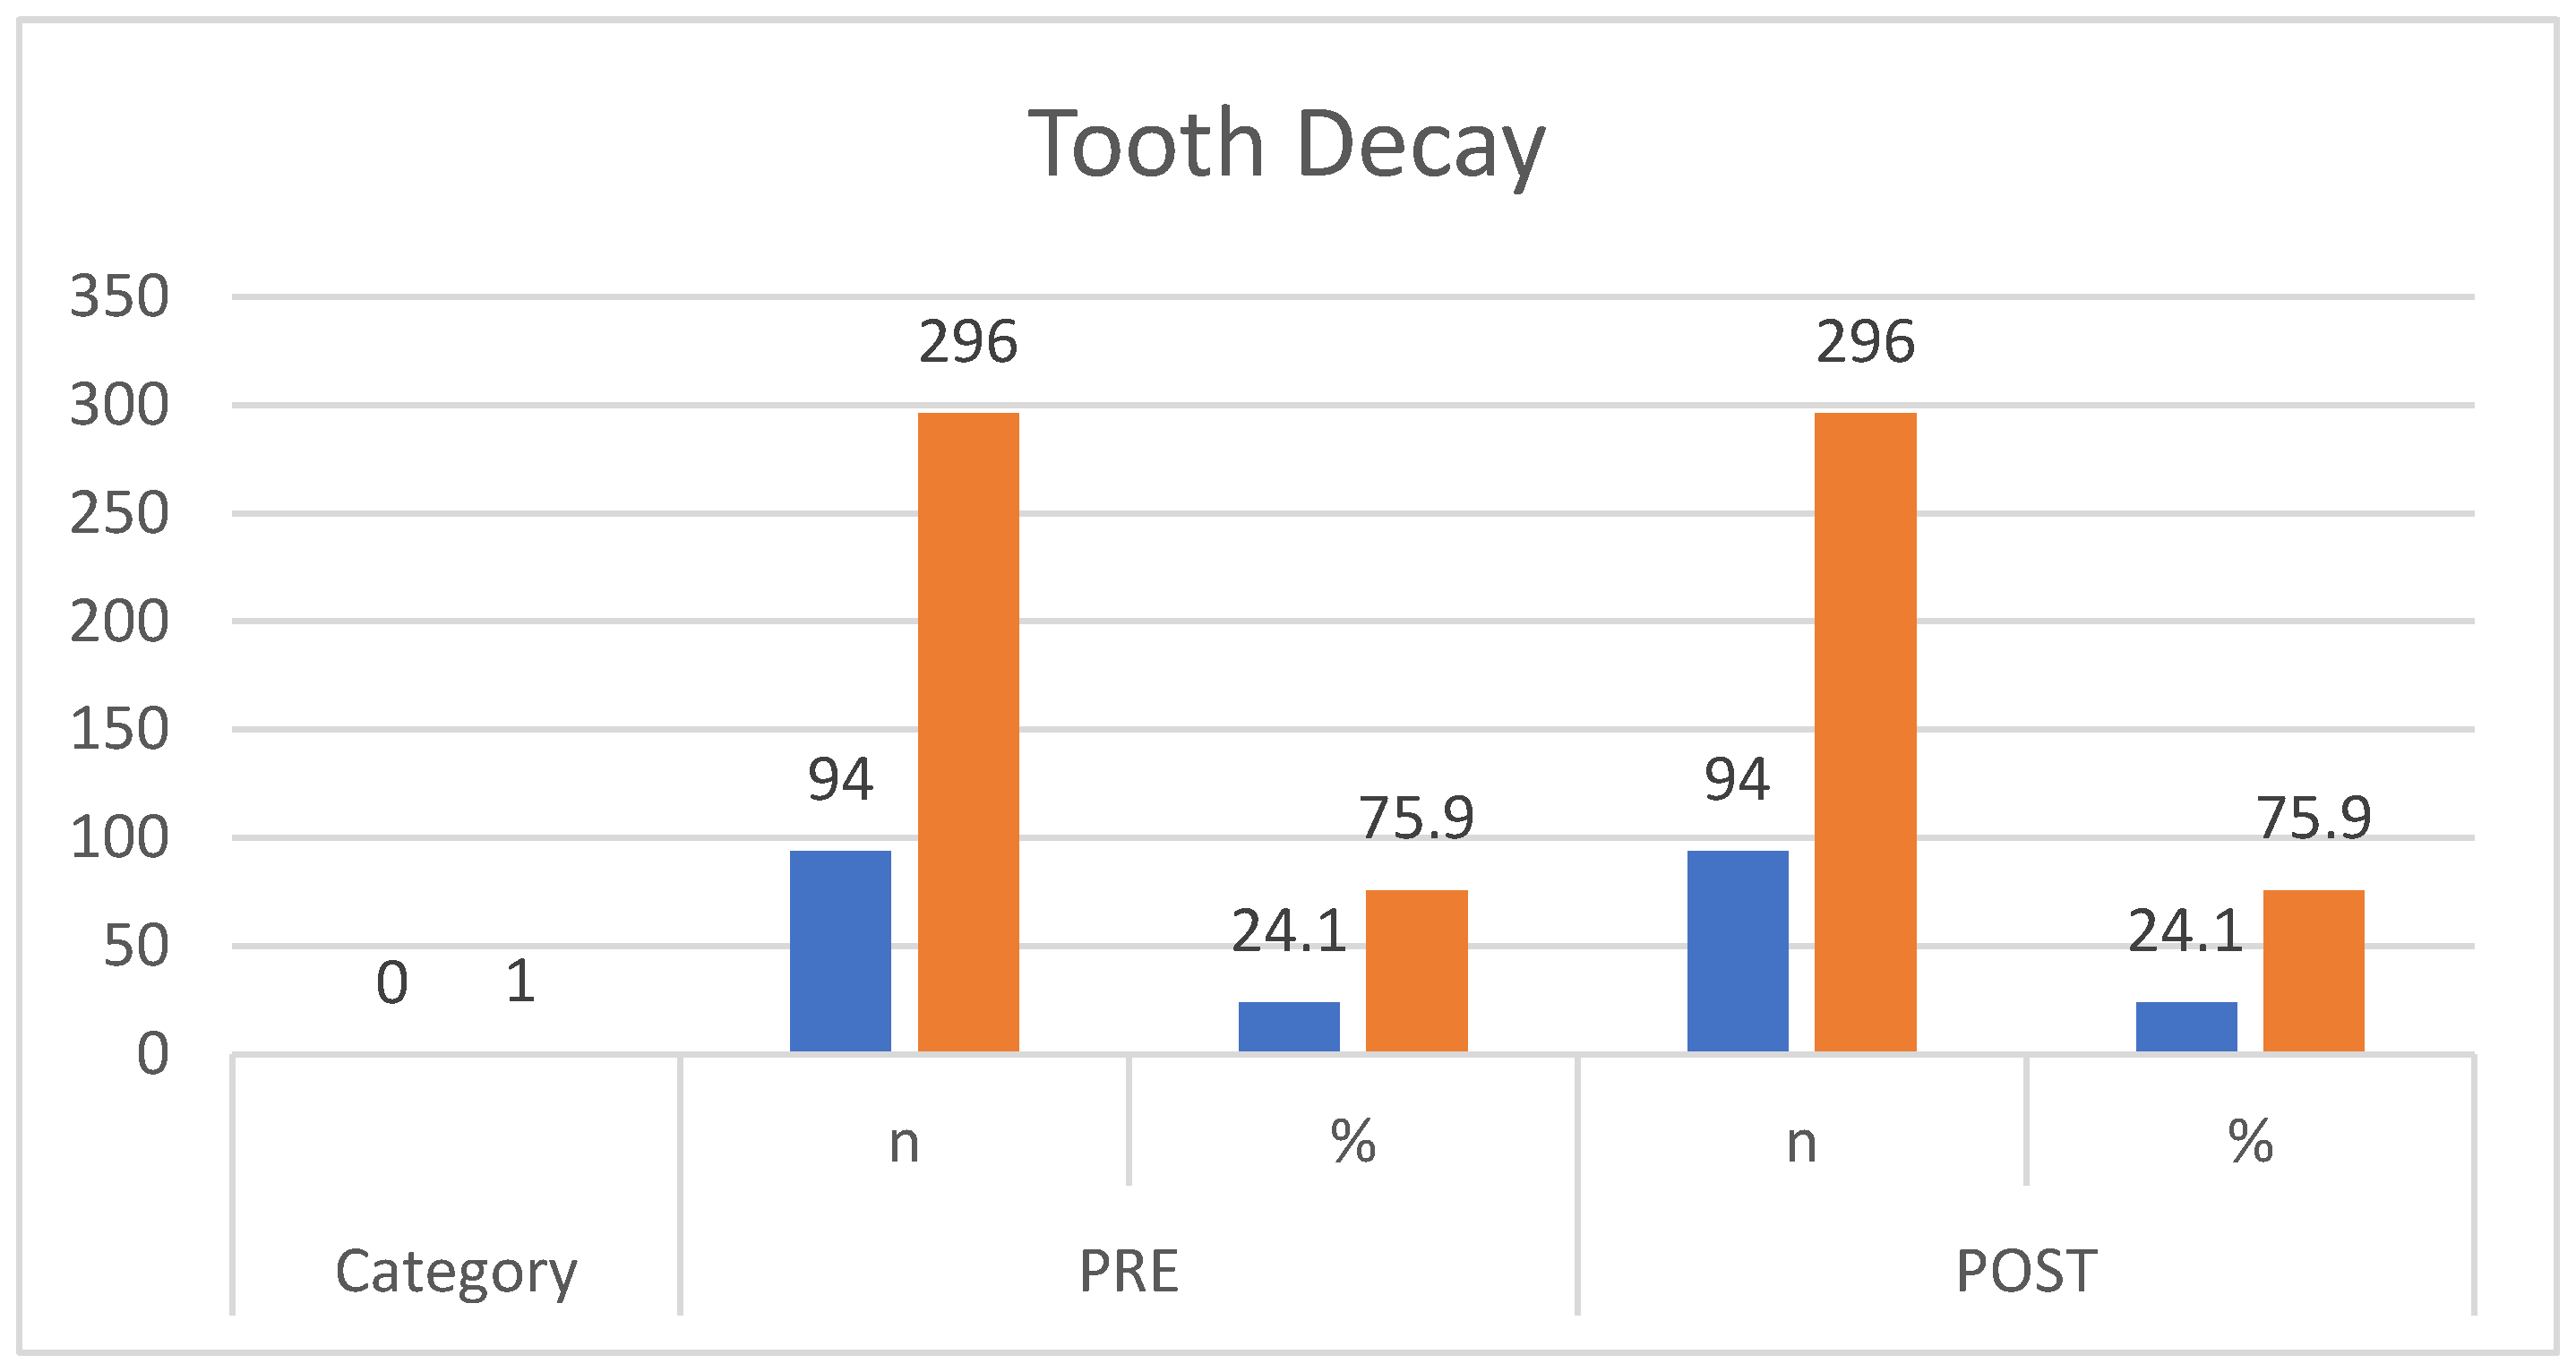
Figure 2 shows the proportion of children with tooth decay. Prior to screening, 75.9% of participants exhibited dental caries, while only 24.1% showed no signs of decay. Following the intervention, these proportions remained unchanged.
Figure 2.
Tooth decay report.
3.2. Plaque Index Scores
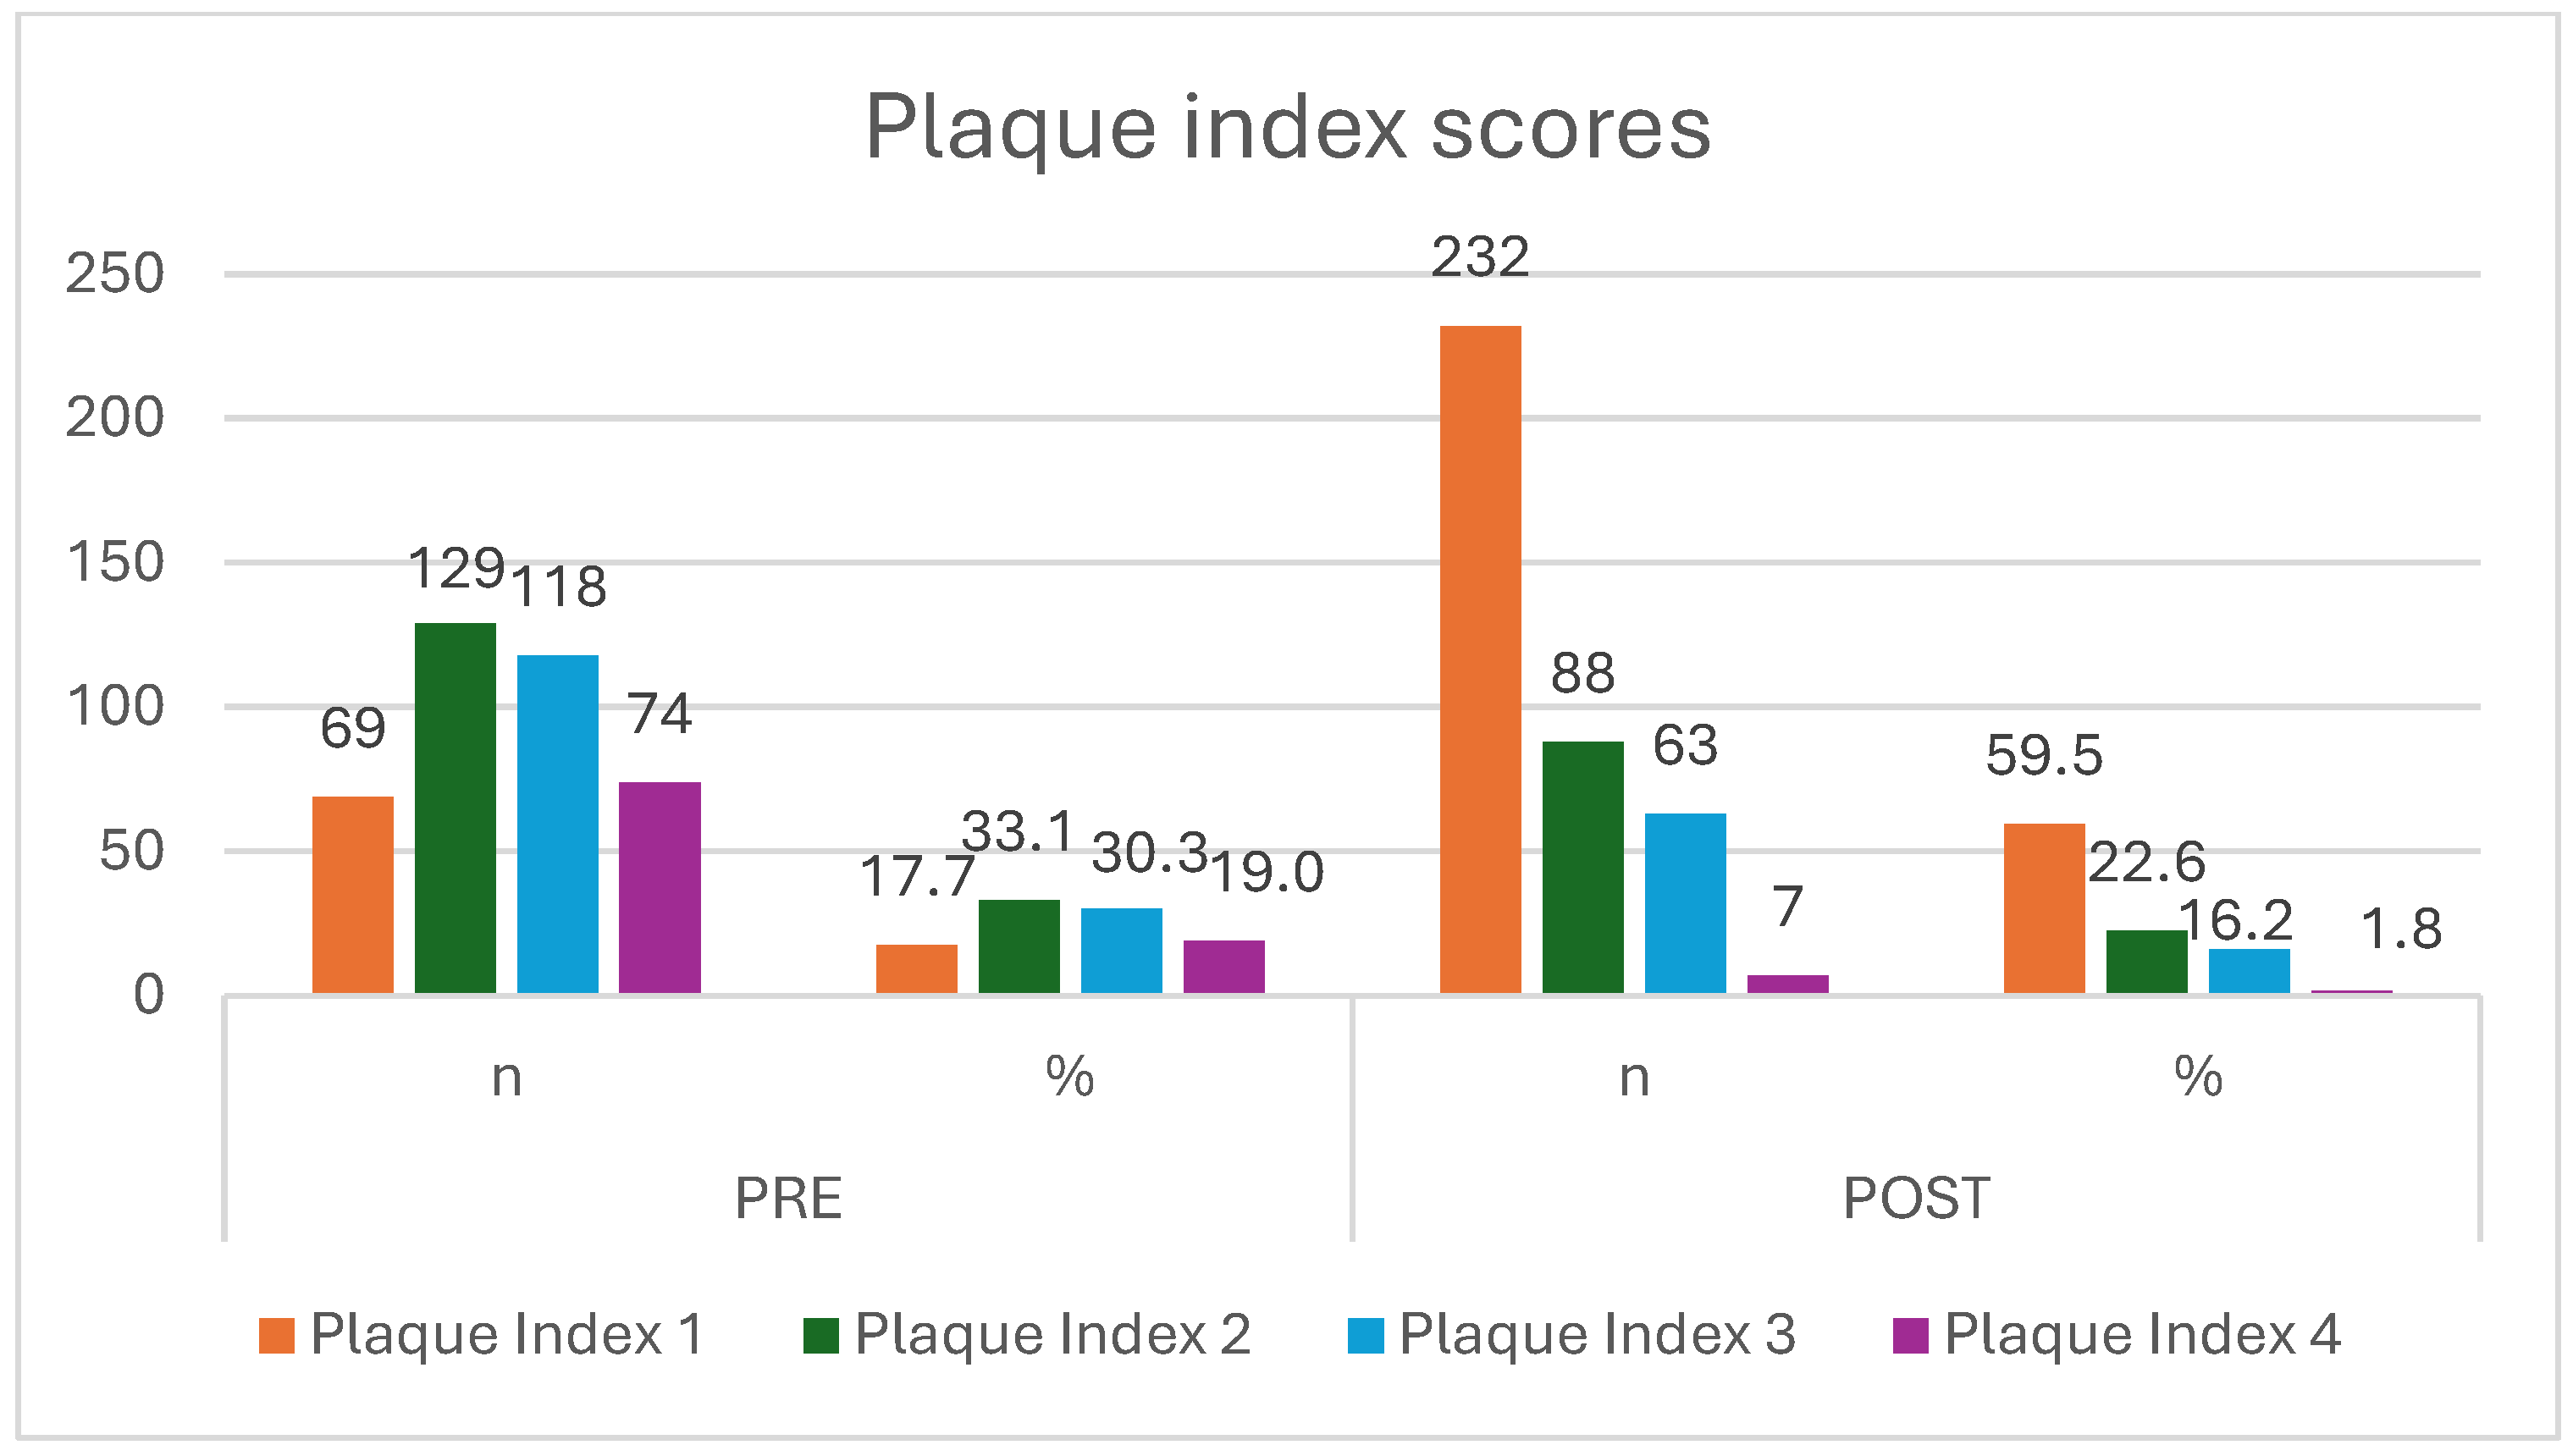
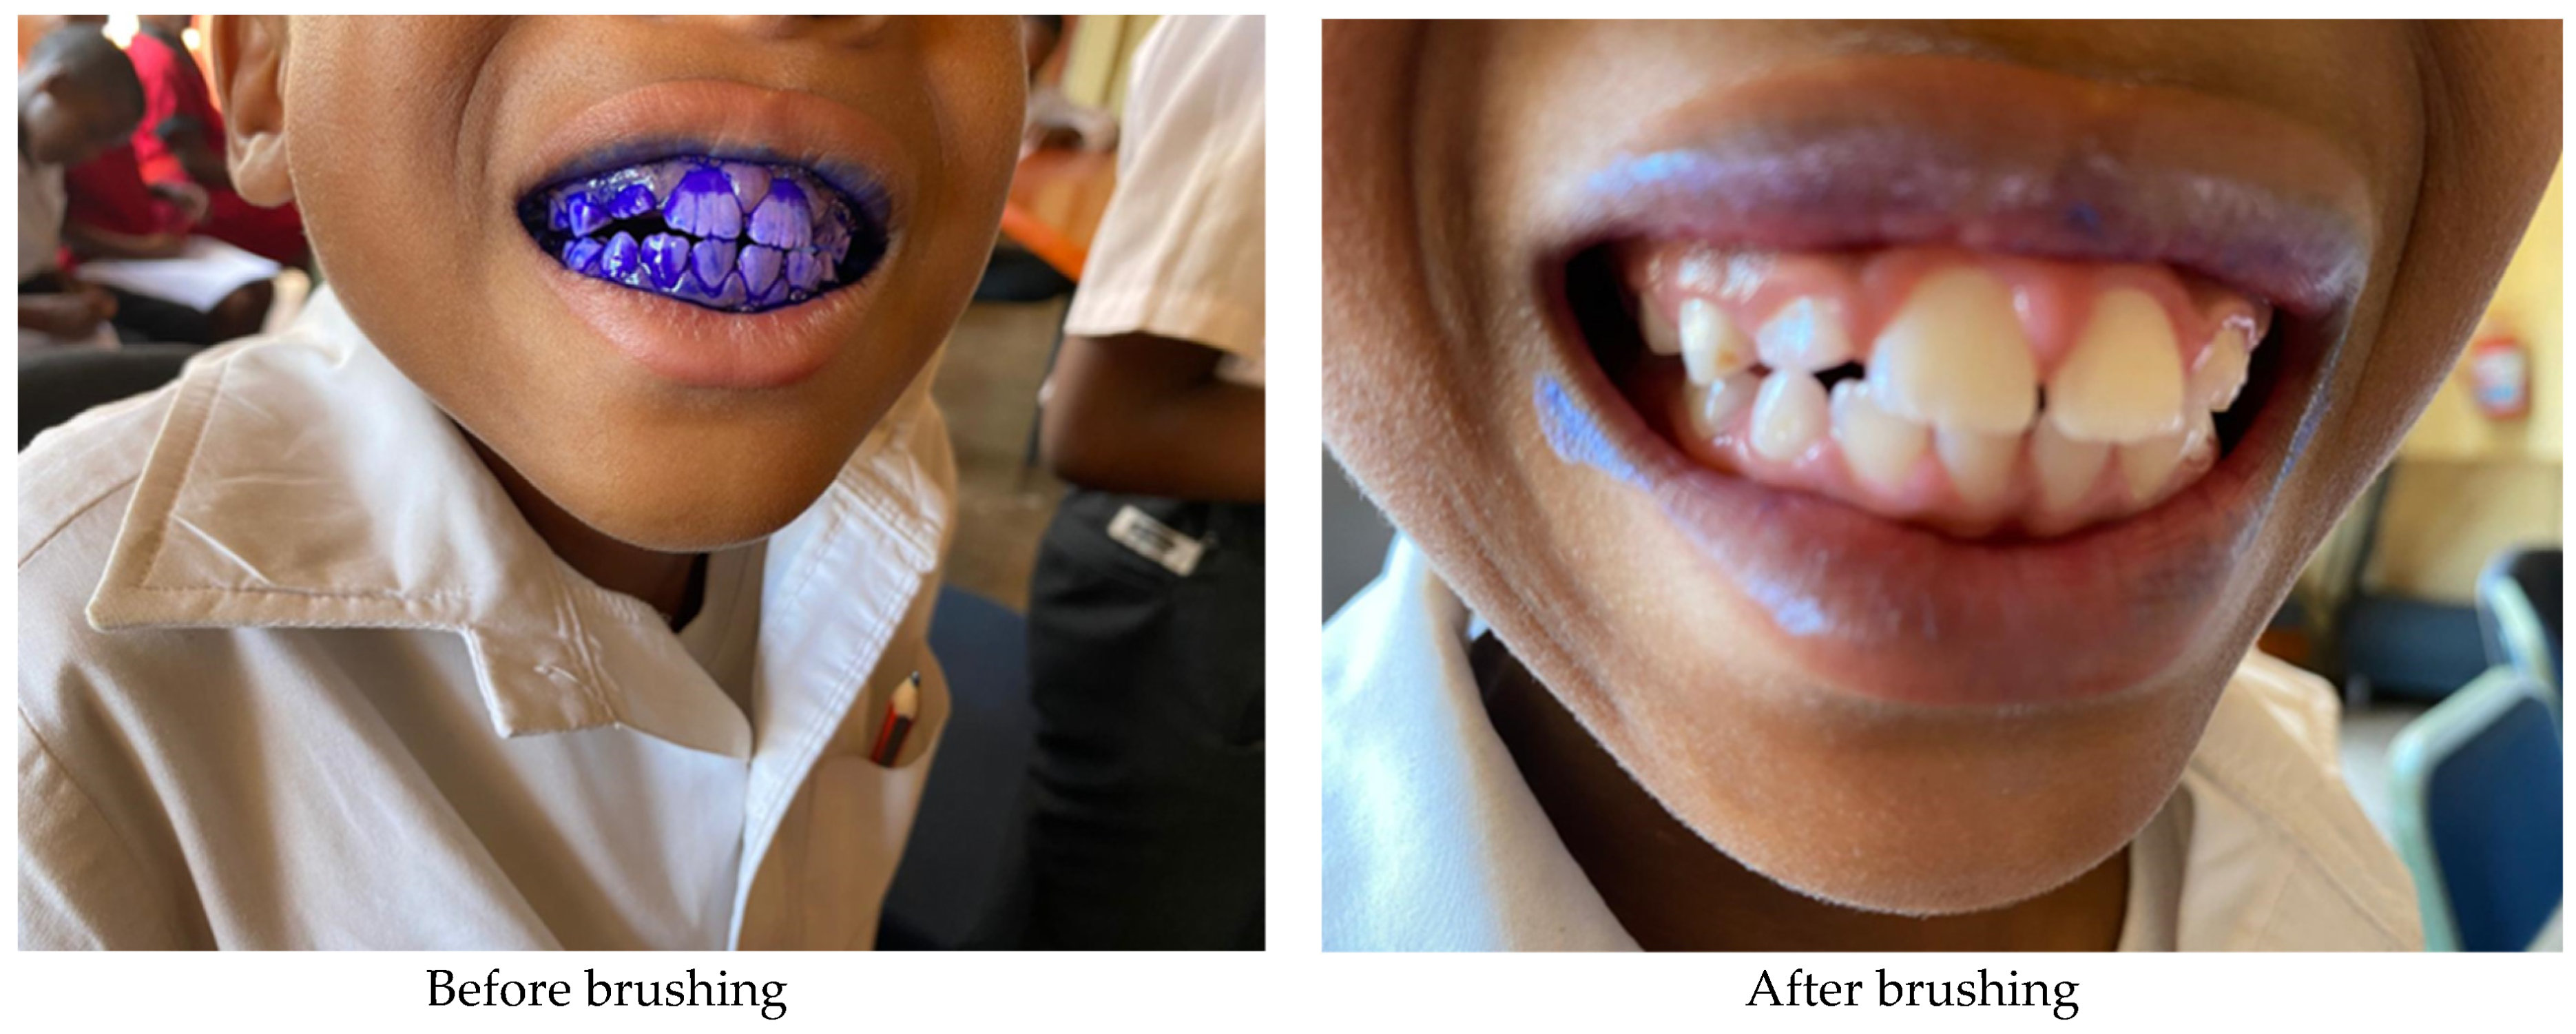
Plaque index scores of the participants are presented in Figure 3, while Figure 4 illustrates the clinical photographs depicting oral hygiene status before and after tooth brushing. The participants’ oral hygiene care improved after a reported high plaque score (n = 74; 19.0%) pre-intervention, which decreased (n = 7; 1.8%) post-intervention. The improvement was also displayed on those with optimum oral hygiene (n = 69; 17.7%) pre-intervention as compared to post-intervention (n = 232; 59.5%). Nevertheless, those with poor oral hygiene, as indicated in Figure 3, with 100% plaques score were 30.3% pre intervention as compared to reduced post intervention (n = 63; 16.2%).
Figure 3.
Plaque index scores.
Figure 4.
Clinical presentation of dental Plaque.
Decayed Missing Filling Teeth- DMFT/dmft Score
Table 1 shows zero recorded dmft/DMFT score pre- (63.1%) and post- (76.9%) intervention on dmft and pre- (50.8%) and post- (59.2%) intervention on DMFT during dental screening for children. The proportion of dmft in primary teeth recorded (37.3%) pre intervention higher than post intervention (23.2%). Additionally, the record of DMFT in permanent teeth pre-intervention (49.2%) compared to the post intervention (40.8%). However, there are no observable changes in the treatment during pre and post intervention (75.9%). Though the demand increased for extractions (31.3%), the need for preventative measures also increased post-intervention (74.7%). The referral pre-intervention (75.9%) as compared to post-intervention (39.2%).
Table 1.
Oral health screening outcomes (DMFT/dmft and related indicators) before and after intervention.
Table 2 shows the prevalence of dental caries remained unchanged at 75.9% pre- and post-intervention. McNemar’s test indicated no statistically significant difference between paired observations (p > 0.05).
Table 2.
Pre–post comparison of tooth decay status (n = 390).
Table 3 presents a Bowker’s test as the primary method for assessing redistribution across plaque categories, which then confirmed a statistically significant redistribution across plaque categories (χ2 = 146.26, p < 0.0001).
Table 3.
Transition of plaque index scores before and after intervention (n = 390).
4. Discussion
Oral health, though crucial to overall well-being, is often overlooked in public health. Dental issues, especially in children, can lead to long-term health and developmental challenges if not addressed early [1,2]. School-based screenings aim to identify problems early, yet their impact remains mixed. While they may improve awareness and hygiene behaviors [12,13], this study found no reduction in caries prevalence 75.9% of children had decay both before and after intervention, likely due to the absence of clinical treatment. However, evidence suggests that incorporating hands-on, skills-based education may help reduce caries and plaque [14]. Lasting improvements require comprehensive strategies that include not only education and screening but also treatment and follow-up [15,16]. This study addressed that gap by providing referrals, though its short duration may have limited measurable outcomes, reflecting a common challenge in brief interventions.
4.1. Effectiveness of Screening: A Case for Early Detection
The study revealed that 75.9% of children had dental caries both before and after the screening, reflecting a persistent lack of access to treatment. Globally, untreated dental caries remains a major health concern, especially among children from lower socioeconomic backgrounds who face greater vulnerability [3,6,7,15]. The long-term effects, ranging from pain and infection to impaired growth and development, are well documented [4,8].
While early screening has reduced total tooth loss by enabling timely referrals and preventive care like fluoride application [17], its effectiveness is questioned when not coupled with direct treatment. Identifying problems without addressing them often leads to worsening conditions, as emphasized by [18,19]. Still, screenings provide valuable data for planning and can guide preventive efforts, especially when integrated with supervised brushing and hygiene education [20,21]. In this study, increased demand for extractions (31.3%) and preventive care (47.7%) post-screening suggests improved awareness. However, the preference for extractions may reflect barriers such as cost, transport, or limited-service availability, often leading families to opt for quicker solutions [22]. With most public services focusing on extractions due to resource constraints [23], there is an urgent need to rebalance priorities toward prevention and oral health promotion. Continued research and inclusive policies can help shift the focus from curative care to long-term oral health improvement.
Screening Improves Oral Hygiene Practices in Children
The study recorded a significant drop in high plaque scores from 19.0% to 1.8% among children with poor oral hygiene (70–100% plaque index), indicating that school-based interventions can lead to immediate improvements in hygiene practices [24]. However, the decline in children classified with good oral hygiene from 33.1% to 22.6% raises concerns about the sustainability of these gains without continued support. Parental involvement, especially through practices like Parental Supervised Brushing (PSB), is critical to reinforce healthy routines. Yet, PSB often faces obstacles due to behavioral resistance and inconsistent home environments [25]. While schools can initiate behavioral change, long-term success relies more on parental guidance and intrinsic motivation [26]. Access to dental services also depends on socioeconomic factors, with higher parental education and awareness linked to more frequent dental visits for children [27,28]. In underserved areas, awareness alone may not lead to action due to cost and access barriers [29]. Without integration into broader social support systems from parents and other role players, initial improvements never last for longer. Regarding oral hygiene, parents are not just a good role model in terms of timing, frequency, and duration of tooth brushing but they should have knowledge and manage to demonstrate completely and effectively that brushing should be done [30,31]. Therefore, lasting oral health outcomes require a dual approach to school-based education supported by consistent parental engagement at home.
4.2. Plaque Control as Measure of Oral Hygiene Practices
A noticeable improvement in oral hygiene practices was observed following the implementation of oral health education and supervised toothbrushing sessions. Prior to the intervention, a significant portion of participants exhibited moderate plaque levels, with 19.0% falling into this category. Post-intervention, this figure declined dramatically to just 1.8%. Bowker’s test demonstrated a statistically significant redistribution across plaque index categories following the intervention, indicating that participants shifted disproportionately toward lower plaque categories after the intervention rather than remaining stable within the same category. Similarly, individuals classified as having a mild plague score increased from 17.7% before the intervention to 59.5% post intervention. Further analysis revealed that participants with an extensive plaque score, as indicated by a 100% plaque score, decreased from 30.3% before the intervention to 16.2% after the intervention. These outcomes reflect a substantial enhancement in oral hygiene standards among participants, attributable to the educational and brushing sessions as part of the practical measures introduced during the intervention phase.
The findings suggest that there was a significant improvement in plaque index scores following the intervention (p < 0.001). However, the Kappa statistic showed minimal agreement between pre- and post-intervention classifications, with the value of −0.0034. This pattern indicates that short-term educational interventions are effective in improving oral hygiene behaviors but may not immediately influence cumulative caries outcomes such as DMFT/dmft. Similar trends have been reported in recent studies, where school-based oral health education led to significant reductions in plaque levels but limited short-term changes in caries experience due to the chronic nature of the disease [32]. These findings highlight the importance of sustained interventions and the integration of preventive and clinical care to achieve long-term improvements in dental caries outcomes. The results reflect a significant enhancement of the participants’ oral hygiene following the intervention, contrary to the study conducted by [16], which reported the improvement in oral hygiene status and dental caries, but no reduction in plaque levels. However, these findings align with existing literature emphasizing the efficacy of educational interventions, including brushing up on improving oral hygiene and reducing plaque levels [33]. A similar study demonstrated a significant reduction in plaques using a Green Vermillion Index (GVI) from 3.52 to 2.64 one week after an educational program, with the lowest value of 1.44 observed at three months, although the population differs, as the study involves adolescents, while the current study was focused on middle childhood. In addition, a slight increase to 2.52 was noted at six months, underscoring the necessity for ongoing educational efforts to sustain oral health improvements [33]. Furthermore, there is a need for continuous assessment even after educational intervention is still a priority for the oral health practices and behaviors to change into a habit.
4.2.1. DMFT/dmft Scores: Indications of Systemic Gaps in Oral Health Care
The study revealed that a notable number of children recorded a dmft/DMFT score of zero, with post-intervention improvements observed. dmft zero scores increased from 63.1% to 76.9%, and DMFT zero scores rose from 50.8% to 59.2%. Although no clinical treatment was provided, this pattern is unlikely to reflect true reversal of existing decay. Instead, it may indicate early preventive effects of improved oral hygiene behaviors, particularly in children who were initially caries-free or had very early lesions not captured in DMFT scoring. Importantly, DMFT/dmft is a cumulative index and does not easily capture short-term changes, so improvements in “zero scores” are more plausibly explained by prevention of new lesions rather than elimination of existing disease. However, future study recommendations are the use of the International Caries Detection and Assessment System (ICDAS) because it can detect early and advanced caries in detail. Other case studies of dental caries in both primary and permanent teeth reported a decline (dmft > 0 from 37.3% to 23.2%; DMFT > 0 from 49.2% to 40.8%). While this indicates some positive shift, the higher prevalence compared to [4,11] findings underscores persistent challenges, especially in the absence of treatment pathways [18,19]. External factors such as reduced access to preventive care, poor oral hygiene and regional disparities in water fluoride levels [8] may have further influenced outcomes. These findings reinforce the call for stronger prevention-focused systems rather than curative-dominated services.
Although referrals declined post-intervention (from 75.9% to 39.2%), the importance of linking screening to functional dental care remains critical. Early preventive visits have been shown to reduce the need for operative procedures and studies in South Africa [22] urge a re-evaluation of oral health strategies to reduce extractions and improve child oral health, school attendance, and overall well-being with the similar sentiment that the Gauteng Department of Health Ministry must reevaluate current oral health programs to improve health service which will reduce the prevalence of dental caries and large quantity of extractions performed.
4.2.2. Limited Impact of Screening on Treatment Access
The consistent 75.9% treatment rate before and after screening highlights that identification alone does not improve access to care. Access factors include social, economic and political causes such as workforce shortages, limited facilities, and caregiver hesitancy, which continue to restrict treatment uptake, particularly in underserved communities, leading to negative outcomes and inequality in oral health services [34]. Critics argue that without financial subsidies, mobile dental clinics, or policy-driven interventions, screenings are merely observational rather than transformative [35]. Ref. [36] expressed that social determinants’ discrepancies, such as family condition and culture, health demands, affordability, and availability of services, can affect dental health access and equality, which contributes to the impact on oral health outcomes. Therefore, addressing these factors can improve access to dental services and pave the way for achieving universal health coverage. These social determinants result in underservices in poor and disadvantaged communities, causing a lack of access to dental services. Consequently, the reduced access resulted in a shift in treatment to more curative measures than preventive effects, which then affect OHRQoL outcomes because people suffer from pain, functional and psychological impact [11,20]. Similarly, low education contributes to lowering the odds of dental services access irrespective of oral health behavior and status [37]. A more effective strategy would involve coupling screening with accessible treatment, preventive services like school-based fluoride programs, and stronger parental involvement [14]. Advocates argue that screening raises awareness and facilitates early intervention, while critics highlight its inherent limitations in producing tangible health improvements without integrated treatment pathways. Only through such comprehensive measures can school-based dental programs translate awareness into measurable improvements in children’s oral health.
4.3. Strengths and Limitations
The initiative emphasized collaboration, drawing support from educators, healthcare professionals, and parents to ensure that the program was both practical and sustainable. Outcomes will be measured not only through changes in dental health indicators, such as plaque scores, but also through observable improvements in school children’s engagement and awareness, and improvement of oral health practices for children. The study findings should be interpreted with caution due to several limitations. The quasi-experimental design without a control group limits causal inference, as observed changes cannot be exclusively attributed to the intervention. The short follow-up period further constrains the ability to detect changes in cumulative outcomes such as DMFT/dmft. Potential selection and measurement biases may have influenced the results, despite efforts to standardize data collection procedures. Additionally, the study was conducted within a specific geographic context, which may limit the generalisability of the findings to other populations.
4.4. Implications
The findings from the study carry important implications for how oral health promotion and screening are approached within South African primary schools, particularly in under-resourced districts like Tshwane. By implementing a structured, context-sensitive educational intervention, the research not only highlighted existing gaps in oral hygiene practices but also demonstrated the potential for schools to act as meaningful platforms for preventive health care. The following important aspects were also addressed:
Repositioning Schools as Platforms for Preventive Health: The study reinforces the idea that schools are not merely sites of academic instruction but also crucial environments for health promotion. By embedding oral health education and dental screening into the everyday routines of primary school learners, the intervention demonstrated how early-life educational spaces can serve as powerful agents for establishing lifelong health habits.
Addressing Health Inequities Through School-Based Access: The study underscored how school-based interventions can help counterbalance inequities in access to oral healthcare, particularly in underserved communities like those within parts of Tshwane. In areas where clinics may be distant or financially inaccessible, the school offers a uniquely reachable and inclusive venue for care.
5. Conclusions
The results illustrate that the implementation of school-based oral health education and dental screening initiatives led to a marked reduction in high plaque levels among participating children. Although the intervention did not yield measurable changes in the status of existing tooth decay, notable progress was evident in the form of improved plaque control. These outcomes suggest a positive shift in daily oral hygiene behaviors and awareness. Nonetheless, the consistent rate of untreated cases, coupled with a growing demand for extractions and preventive services, points to persisting challenges in accessing follow-up clinical care. The sustainability of these gains appears closely linked to ongoing parental engagement and complementary support within the home environment. Overall, the findings emphasize the value of combining educational, preventive, and community-based efforts to strengthen oral health outcomes and ensure long-term benefits for school-aged children.
Author Contributions
E.M. conceptualized the manuscript and wrote the manuscript under the guidance of supervisor T.N. and co-supervisor D.T.G. who extensively reviewed the manuscript for improvement as part of the supervision. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no specific grant from any funding agency in the public, commercial or not-for-profit sectors.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the University of Limpopo Research Ethics Committee (protocol code: TREC/123/2024: PG and date of approval: 1 September 2024).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request.
Conflicts of Interest
There are no other conflicts of interest.
References
- Yactayo-Alburquerque, M.T.; Alen-Méndez, M.L.; Azañedo, D.; Comandé, D.; Hernández-Vásquez, A. Impact of oral diseases on oral health-related quality of life: A systematic review of studies conducted in Latin America and the Caribbean. PLoS ONE 2021, 16, e0252578. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duangthip, D.; Chu, C.H. Challenges in oral hygiene and oral health policy. Front. Oral Health 2020, 1, 575428. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sampaio, F.C.; Bönecker, M.; Paiva, S.M.; Martignon, S.; Ricomini Filho, A.P.; Pozos-Guillen, A.; Oliveira, B.H.; Bullen, M.; Naidu, R.; Guarnizo-Herreño, C.; et al. Dental caries prevalence, prospects, and challenges for Latin America and Caribbean countries: A summary and final recommendations from a Regional Consensus. Braz. Oral Res. 2021, 35, e056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- GBD 2017 Oral Disorders Collaborators; Bernabe, E.; Marcenes, W.; Hernandez, C.R.; Bailey, J.; Abreu, L.G.; Alipour, V.; Amini, S.; Arabloo, J.; Arefi, Z.; et al. Global, regional, and national levels and trends in burden of oral conditions from 1990 to 2017: A systematic analysis for the global burden of disease 2017 study. J. Dent. Res. 2020, 99, 362–373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olamide, O.; Oyapero, A.; Ashaolu, J.F.; Abe, A.; Boyede, G.O. Dental caries and oral health: An ignored health barrier to learning in Nigerian slums: A cross sectional survey. PAMJ-One Health 2022, 7, 13. [Google Scholar] [CrossRef] [Scilit]
- Teshome, A.; Muche, A.; Girma, B. Prevalence of dental caries and associated factors in East Africa, 2000–2020: Systematic review and meta-analysis. Front. Public Health 2021, 9, 645091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onyejaka, N.K.; Olatosi, O.O.; Ndukwe, N.A.; Amobi, E.O.; Okoye, L.O.; Nwamba, N.P. Prevalence and associated factors of dental caries among primary school children in South-East Nigeria. Niger. J. Clin. Pract. 2021, 24, 1300–1306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Radebe, M.; Singh, S. Investigating dental caries rates amongst sentenced prisoners in KwaZulu-Natal, South Africa. S. Afr. Dent. J. 2020, 75, 137–141. [Google Scholar] [CrossRef] [Scilit]
- Kitsaras, G.; Goodwin, M.; Kelly, M.P.; Pretty, I.A. Bedtime oral hygiene behaviours, dietary habits and children’s dental health. Children 2021, 8, 416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Molete, M. Children’s oral health in South Africa: Time for action. S. Afr. J. Child Health 2018, 12, 133. [Google Scholar] [CrossRef] [Scilit]
- Chikte, U.; Pontes, C.C.; Karangwa, I.; Kimmie-Dhansay, F.; Erasmus, R.; Kengne, A.P.; Matsha, T.E. Dental caries in a South African adult population: Findings from the Cape Town Vascular and Metabolic Health Study. Int. Dent. J. 2020, 70, 176–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karamehmedovic, E.; Petersen, P.E.; Agdal, M.L.; Virtanen, J.I. Improving oral health of children in four Balkan countries: A qualitative study among health professionals. Front. Oral Health 2023, 3, 1068384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sajid, M.; Javeed, M.; Jamil, M.; Munawar, M.; Khan, A.; Kouser, R. Assessment of oral health status and oral health education programmed in community living in rural area of Jahangirabaad of Multan. Med. J. South Punjab 2020, 1, 10–13. [Google Scholar] [CrossRef] [Scilit]
- Akera, P.; Kennedy, S.E.; Lingam, R.; Obwolo, M.J.; Schutte, A.E.; Richmond, R. Effectiveness of primary school-based interventions in improving oral health of children in low-and middle-income countries: A systematic review and meta-analysis. BMC Oral Health 2022, 22, 264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsai, E.; Walker, B.; Wu, S.C. Can oral cancer screening reduce late-stage diagnosis, treatment delay and mortality? A population-based study in Taiwan. BMJ Open 2024, 14, e086588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wen, P.; Chen, M.X.; Zhong, Y.J.; Dong, Q.Q.; Wong, H.M. Global burden and inequality of dental caries, 1990 to 2019. J. Dent. Res. 2022, 101, 392–399. [Google Scholar] [PubMed]
- Qin, X.; Zi, H.; Zeng, X. Changes in the global burden of untreated dental caries from 1990 to 2019: A systematic analysis for the Global Burden of Disease study. Heliyon 2022, 8, e10714. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, S.; Sridhar, S.; McIntosh, A.; Messow, C.-M.; Aguilera, E.M.; Del Pinto, R.; Pietropaoli, D.; Gorska, R.; Siedlinski, M.; Maffia, P.; et al. Periodontal therapy and treatment of hypertension-alternative to the pharmacological approach. A systematic review and meta-analysis. Pharmacol. Res. 2021, 166, 105511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davidson, K.W.; Barry, M.J.; Mangione, C.M.; Cabana, M.; Caughey, A.B.; Davis, E.M.; Donahue, K.E.; Doubeni, C.A.; Kubik, M.; Li, L.; et al. Screening and interventions to prevent dental caries in children younger than 5 years: US Preventive Services Task Force recommendation statement. Jama 2021, 326, 2172–2178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moghaddam, L.F.; Vettore, M.V.; Bayani, A.; Bayat, A.-H.; Ahounbar, E.; Hemmat, M.; Armoon, B.; Fakhri, Y. The Association of Oral Health Status, demographic characteristics and socioeconomic determinants with Oral health-related quality of life among children: A systematic review and Meta-analysis. BMC Pediatr. 2020, 20, 489. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Babaei, M.; Freeland-Graves, J.; Sachdev, P.K.; Wright, G.J. Influence of knowledge, attitudes, and behaviors of added sugars consumption on periodontal status in low-income women. Bull. Natl. Res. Cent. 2022, 46, 219. [Google Scholar] [CrossRef] [Scilit]
- Bhayat, A.; Madiba, T.K.; Nkambule, N.R. A three-year audit of dental services at primary health care facilities in gauteng, South Africa: 2017 to 2019. J. Int. Soc. Prev. Community Dent. 2020, 10, 452–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Molete, M.; Stewart, A.; Bosire, E.; Igumbor, J. The policy implementation gap of school oral health programmes in Tshwane, South Africa: A qualitative case study. BMC Health Serv. Res. 2020, 20, 338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petersen, P.E.; Baez, R.J.; Ogawa, H. Global application of oral disease prevention and health promotion as measured 10 years after the 2007 World Health Assembly statement on oral health. Community Dent. Oral Epidemiol. 2020, 48, 338–348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aliakbari, E.; Gray-Burrows, K.A.; Vinall-Collier, K.A.; Edwebi, S.; Marshman, Z.; McEachan, R.R.C.; Day, P.F. Home-based toothbrushing interventions for parents of young children to reduce dental caries: A systematic review. Int. J. Paediatr. Dent. 2021, 31, 37–79. [Google Scholar] [PubMed]
- Shitie, A.; Addis, R.; Tilahun, A.; Negash, W. Prevalence of dental caries and its associated factors among primary school children in Ethiopia. Int. J. Dent. 2021, 2021, 6637196. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.; Chen, W.; Lin, L.; Ma, H.; Huang, F. The prevalence of dental caries and its associated factors among preschool children in Huizhou, China: A cross-sectional study. Front. Oral Health 2024, 5, 1461959. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salama, F.; Alwohaibi, A.; Alabdullatif, A.; Alnasser, A.; Hafiz, Z. Knowledge, behaviours and beliefs of parents regarding the oral health of their children. Eur. J. Paediatr. Dent. 2020, 21, 103–109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ellakany, P.; Madi, M.; Fouda, S.M.; Ibrahim, M.; AlHumaid, J. The effect of parental education and socioeconomic status on dental caries among Saudi children. Int. J. Environ. Res. Public Health 2021, 18, 11862. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deinzer, R.; Shankar-Subramanian, S.; Ritsert, A.; Ebel, S.; Wöstmann, B.; Margraf-Stiksrud, J.; Eidenhardt, Z. Good role models? Tooth brushing capabilities of parents: A video observation study. BMC Oral Health 2021, 21, 469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berzinski, M.; Morawska, A.; Mitchell, A.E.; Baker, S. Parenting and child behaviour as predictors of toothbrushing difficulties in young children. Int. J. Paediatr. Dent. 2020, 30, 75–84. [Google Scholar] [PubMed]
- Nakre, P.D.; Harikiran, A.G. Effectiveness of oral health education programs: A systematic review. J. Int. Soc. Prev. Community Dent. 2013, 3, 103–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gurav, K.M.; Shetty, V.; Vinay, V.; Bhor, K.; Jain, C.; Divekar, P. Effectiveness of oral health educational methods among school children aged 5–16 years in improving their oral health status: A meta-analysis. Int. J. Clin. Pediatr. Dent. 2022, 15, 338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ngatemi, P.T.; Kasihani, N.N. Independence of Brushing Teeth to Free-Plaque Score in Preschool Children: A Cross-Sectional Study. Indian J. Forensic Med. Toxicol. 2021, 15, 3722–3727. [Google Scholar] [CrossRef] [Scilit]
- Soldo, M.; Matijević, J.; Ivanišević, A.M.; Čuković-Bagić, I.; Marks, L.; Borić, D.N.; Krmek, S.J. Impact of oral hygiene instructions on plaque index in adolescents. Cent. Eur. J. Public Health 2020, 28, 103–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Watt, R.G. Oral health inequalities—Developments in research, policy and practice over the last 50 years. Community Dent. Oral Epidemiol. 2023, 51, 595–599. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bala, R.; Sargaiyan, V.; Rathi, S.A.; Mankar, S.S.; Jaiswal, A.K.; Mankar, S.A. Mobile dental clinic for oral health services to underserved rural Indian communities. Bioinformation 2023, 19, 1383. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.