


Abstract
Psychological factors such as depression, anxiety, and loneliness significantly affect sleep quality, particularly among elderly individuals living in nursing homes. This study aimed to examine the relationship between sleep quality and depression, anxiety, and loneliness among elderly residents of nursing homes in Indonesia, as well as to explore the underlying pathway mechanisms. A quantitative cross-sectional design was used to assess correlational relationships among elderly individuals residing in nursing homes in Jakarta and Tangerang. Data were analyzed using JASP statistical software through descriptive, bivariate, and path analyses. The results demonstrated significant associations between poorer sleep quality and higher levels of loneliness, anxiety, and depression. Path analysis revealed a significant chain mediation pattern, in which loneliness was associated with higher anxiety levels, anxiety was associated with depressive symptoms, and depressive symptoms were associated with poorer sleep quality (β = −0.040, p = 0.045). These findings indicate that sleep disturbances in the elderly are statistically associated with interconnected psychological factors, highlighting the importance of comprehensive psychosocial interventions to improve sleep quality in this population.
1. Introduction
The global number of elderly adults has been steadily increasing. According to the United Nations Department of Economic and Social Affairs (UNDESA) World Population Ageing report, the number of people aged 65 years and older reached 703 million in 2019 and is expected to reach 1.5 billion by 2050 [1]. Asia is the region with the fastest-growing elderly population, particularly in countries such as Japan, South Korea, and China. In Indonesia, data from the 2020 Population Census indicate that elderly, which is adults aged 60 years and above, accounted for 10.8% of the total population, or approximately 29 million individuals. This proportion is expected to continue rising in line with increasing life expectancy [2].
The growing elderly population highlights the importance in healthcare and public welfare, including challenges in maintaining adequate sleep quality. Age-related physiological changes in sleep patterns, such as reduced sleep efficiency, increased nighttime awakenings, and alterations in circadian rhythms, predispose the elderly individuals to sleep disturbances [3,4]. Poor sleep quality in the elderly not only impairs function but also correlates to cognitive impairment, low immunity, mood disorders, and rising morbidity and mortality factors [5].
Some psychological factors play important roles in sleep quality, mainly depression, anxiety, and loneliness. A bidirectional relationship between depression and sleep disorders has been well established in epidemiological and longitudinal studies, demonstrating that depressive symptoms can worsen sleep quality, while chronic insomnia increases the risk of developing depression [6]. Anxiety contributes to sleep difficulties through mechanisms such as hyperarousal, rumination, and increased autonomic nervous system activity, which interfere with the initiation and maintenance of sleep [7]. Furthermore, loneliness also has a substantial impact on sleep quality in the elderly. Hawkley and Cacioppo (2010) reported that loneliness increases biological and emotional vigilance, disrupts stress regulation, and reduces feelings of safety, all of which may contribute to sleep disturbances [8]. These findings are supported by meta-analytic evidence demonstrating a strong association between loneliness and poor sleep quality across all age groups, including older adults [9,10].
In addition to psychological factors, demographic characteristics such as gender, education level, marital status, and social support influence sleep quality. Sleep problems are more prevalent among elderly women than men [11]. Furthermore, strong social relationships and support from family or community networks have been shown to improve sleep quality, particularly among elderly individuals who are emotionally vulnerable [12].
In Indonesia, research on the relationship between psychological states and sleep quality in the elderly, particularly those in nursing homes, is very sparse. Elderly adults in care institutions frequently experience environmental changes, restricted social connections, and perhaps diminished emotional support from family members, all of which might raise the risk of developing depression, anxiety, and loneliness. A previous study conducted in similar nursing homes identified significant associations between psychological distress and sleep disturbances in the elderly [13]. As a result, more research is needed to offer an empirical summary of the parameters related with sleep quality in the elderly in this setting.
The aim of this study is to investigate the association between sleep quality and depression, anxiety, loneliness, and demographic features among elderly nursing home patients in Indonesia. The findings are expected to provide a scientific foundation for the development of intervention programs or community-based services to promote sleep quality and overall well-being among elderly individuals living in nursing homes.
2. Materials and Methods
This study used a quantitative approach with cross-sectional design to analyze correlational relationship and path mechanism between variables of loneliness, anxiety, and depression on sleep quality in the elderly patient at a single measurement point. The study population consisted of elderly residents living in nursing homes in the Jakarta and Tangerang areas. Sampling was conducted using a purposive sampling technique, selecting elderly individuals who were functionally independent and had adequate communication skills. A total of 123 elderly participants from 15 nursing homes were included in the study.
The inclusion criteria were individuals aged ≥60 years who were willing to participate and provided informed consent. The exclusion criteria were participants who did not complete the questionnaire in full and those with cognitive impairments that could interfere with comprehension of the research instructions. Cognitive status was assessed using the Montreal Cognitive Assessment Indonesian Version (MoCA-INA), a 30-point cognitive screening tool evaluating domains including attention, executive function, memory, language, visuospatial ability, abstraction, and orientation. The assessment was administered individually by trained research personnel prior to questionnaire completion. In accordance with established cut-off recommendations, participants scoring below 26 were considered to have potential cognitive impairment and were excluded from further participation to ensure comprehension of the self-report instruments.
Data were collected using four standardized instruments translated into Indonesian, as follows:
- Generalized Anxiety Disorder-7 (GAD-7)
The GAD-7 [14] is used to measure anxiety levels, with a score of 0–4 indicating no anxiety, a score of 5–9 indicating mild anxiety, a score of 10–14 indicating moderate anxiety, and a score of 15–21 indicating severe anxiety. This can be categorized into two groups: a score < 5 indicating no anxiety, and a score ≥ 5 indicating anxiety. The Indonesian adaptation of the GAD-7 exhibits commendable psychometric characteristics, with validity coefficients between 0.648 and 0.800 (p < 0.01) and a Cronbach’s alpha of 0.867.
- Patient Health Questionnaire-9 (PHQ-9)
The PHQ-9 [15] was used to assess depression, with a score of 0–4 indicating no depression, a score of 5–9 indicating mild depression, a score of 10–14 indicating moderate depression, a score of 15–19 indicating moderate–severe depression, and a score of 20–27 indicating severe depression. These scores are categorized into two groups: a score < 5 indicating no depression, and a score ≥ 5 indicating depression. The Indonesian version has demonstrated satisfactory validity (r = 0.527) and internal consistency reliability (Cronbach’s alpha = 0.855).
- University of California, Los Angeles (UCLA) Loneliness Scale Version 3
Loneliness was assessed using the UCLA Loneliness Scale Version 3 [16]. The Indonesian version that was translated has shown good internal consistency, with a reported Cronbach’s alpha of 0.905. Scores of 20–34 indicate no loneliness, 35–49 indicating low loneliness, 50–64 indicating moderate loneliness, and 65–80 indicating severe loneliness. These scores are further categorized into two groups: a score of 20–34 indicating no loneliness and a score > 34 indicating loneliness.
- Pittsburgh Sleep Quality Index (PSQI)
Sleep quality was evaluated using the Pittsburgh Sleep Quality Index (PSQI) [17]. The Indonesian version has shown good internal consistency, with a Cronbach’s alpha of 0.72. The PSQI consists of 19 self-rated items grouped into seven components, generating a global score ranging from 0 to 21. A global score ≤ 5 indicates good sleep quality, whereas a score > 5 indicates poor sleep quality.
- Data Collection Procedure
The research instruments, originally developed in English, were translated into Indonesian and pre-tested to assess their reliability and validity. The finalized questionnaires were then administered in the form of a Google Form. Data collection was conducted by trained enumerators. The procedure began with an explanation of the study to potential participants, followed by the provision of written informed consent. Participants completed the questionnaires independently; however, enumerators provided assistance with reading or explaining instructions, when necessary, without influencing participants’ responses.
- Data Analysis
Data were analyzed using JASP statistical software version 0.95.4 through descriptive analysis, bivariate analysis, correlation matrix construction and Structural Equation Modeling (SEM)- based path analysis. The analysis began with univariate analysis to provide a comprehensive overview of the participants’ demographic characteristics and the frequency distribution of each psychological variable studied. Bivariate analysis using Pearson’s correlation test examined pairwise associations among loneliness, anxiety, depression, and sleep quality. A correlation matrix was subsequently generated to present the overall interrelationships among the study variables and to assess their suitability for further modeling. As the core step, this study applied path analysis with a Structural Equation Modeling (SEM) approach to test the proposed theoretical model. Prior to SEM estimation, assumptions were examined. Normality was assessed using skewness and kurtosis statistics. Multicollinearity was evaluated using variance inflation factor (VIF) and tolerance values. Sample adequacy was considered based on recommended SEM guidelines, which suggest a minimum ratio of 5–10 participants per estimated parameter.
Model fit was evaluated using multiple goodness-of-fit indices, including the chi-square statistic (χ2), Comparative Fit Index (CFI), Tucker–Lewis Index (TLI), Root Mean Square Error of Approximation (RMSEA), and Standardized Root Mean Square Residual (SRMR). Acceptable model fit was determined based on conventional thresholds (CFI and TLI ≥ 0.90; RMSEA ≤ 0.08; SRMR ≤ 0.08).
3. Results
3.1. Sleep Quality with Demography Characteristics
This study involved 123 elderly residents across 15 nursing homes in the Jakarta and Tangerang areas. The majority were women (98 participants), and most participants were aged 66–70 years (52%), followed by 71–90 years (44.7%). Over half of the residents had lived in the institution for 1–4 years (52.8%), while three participants were unable to recall their duration of residency. Overall, 71.5% of participants were categorized as having poor sleep quality, and 28.5% had good sleep quality (Table 1).
Table 1.
Sleep Quality on Demography Characteristic.
Bivariate analysis showed no significant association between sleep quality and age (p = 0.647), gender (p = 0.660), or duration of residency (p = 0.845). Poor sleep quality appeared more common among participants aged 71–90 years (47.7%); however, these differences were not statistically significant (Table 1).
3.2. Psychological Conditions and Sleep Quality
The distribution data shows that the majority of elderly people in nursing homes experience poor sleep quality, amounting to 88 people (71.5%). Regarding psychological conditions, the majority of participants are in the mild loneliness category (85.4%). As for anxiety, 62.6% of participants showed no symptoms of anxiety, but 37.4% of elderly people experienced mild to moderate anxiety. Meanwhile, regarding depression, 43.9% of participants were identified as having depressive symptoms with levels of severity varying from mild to moderate–severe (Table 2).
Table 2.
Descriptive Statistics of Research Variables.
3.3. Correlation Analysis Between Research Variables
Based on the Pearson correlation test to determine the initial linear relationship between latent variables (Table 3), the following relationship pattern was found:
Table 3.
Correlation Matrix of Loneliness, Depression, Anxiety and Sleep Quality in Elderly.
3.3.1. Relationship Between Research Variables and Sleep Quality
The depression variable showed a significant positive correlation with sleep quality (r = 0.351, p < 0.001), indicating that higher levels of depression increase the PSQI score (indicating poorer sleep quality). A similar finding was found for the anxiety variable, which had a significant positive correlation with sleep quality (r = 0.310, p < 0.001). Conversely, loneliness showed a very low and insignificant correlation with sleep quality directly (r = −0.043, p > 0.05) (Table 3).
3.3.2. Relationship Between Psychological Conditions
There was a very strong and significant positive correlation between anxiety and depression (r = 0.637, p < 0.001). These findings indicate that elderly people in nursing homes who experience anxiety tend to have a higher risk of also experiencing depressive symptoms (comorbidity) (Table 3).
3.3.3. Relationship Between Loneliness and Other Research Variables
Loneliness was found to have a significant correlation with depression (r = 0.430, p < 0.001) and anxiety (r = 0.332, p < 0.001) (Table 3). This direction reflects that the dimension of loneliness is closely related to fluctuations in the elderly’s emotional state (Table 4).
Table 4.
Coefficient pathway of direct effect, indirect effect, and total effect among loneliness, depression, anxiety, and sleep quality in elderly.
3.4. Path Analysis and Mediation Mechanism
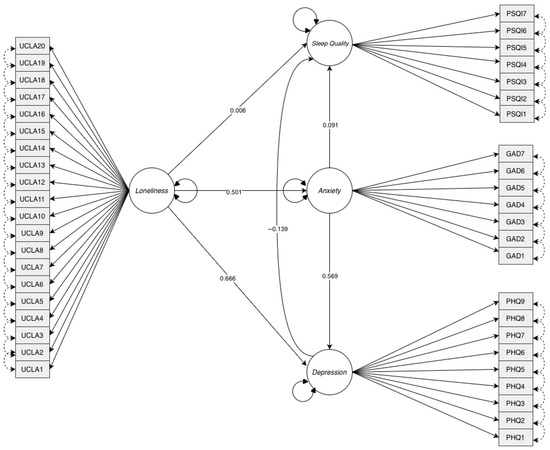
The data were analyzed with path analysis and confirmed that loneliness did not have a significant direct effect on sleep quality (p = 0.566). The effect of loneliness on sleep quality occurred entirely through an indirect pathway, or a full mediation. The mediation pathway through anxiety was found to be significant (β = 0.085, p = 0.004), as was the mediation pathway through depression (β = −0.053, p = 0.048) (Table 4). The most crucial finding was the existence of a chain mediation mechanism where path analysis revealed a significant chain mediation effect, wherein loneliness was associated with increased anxiety, which in turn was linked to depression, and ultimately related to poorer sleep quality in the elderly (β = −0.040, p = 0.045) (Figure 1).
Figure 1.
Path Analysis Illustrating the Effect of Loneliness on Sleep Quality through Anxiety and Depression in Elderly.
The structural model showed acceptable incremental fit (CFI = 0.931; TLI = 0.927; GFI = 0.917). However, the RMSEA (0.117) and SRMR (0.122) values were above conventional cut-off criteria. This discrepancy may be related to the relatively small sample size and the use of an observed-variable path model with limited degrees of freedom, which can influence absolute fit indices. Therefore, the structural coefficients were interpreted cautiously, with emphasis on the theoretical coherence and consistency of the estimated pathways (Figure 1).
4. Discussion
The results of this study indicate that 71.5% of elderly individuals residing in nursing homes experience poor sleep quality, a finding consistent with previous research. A meta-analysis by Vaquero-Álvarez et al. [12] reported a prevalence of sleep disorders ranging from 55% to 80% among elderly populations, particularly among those with psychological comorbidities [12]. Studies focusing on elderly individuals living in institutional settings have consistently shown a higher prevalence of poor sleep quality compared to those living in the community, likely due to reduced autonomy, rigid daily routines, and limited control over the sleep environment [2,3]. These findings support the view that institutionalization constitutes a contextual risk factor that amplifies the impact of psychological stress on sleep quality. In contrast, demographic variables such as age, gender, and duration of residence did not demonstrate statistically significant associations with sleep quality in this study.
4.1. Depression and Anxiety as Predictors of Sleep Quality
This study found that depression (r = 0.351) and anxiety (r = 0.310) were significantly associated with poorer sleep quality among elderly individuals living in nursing homes. These findings are consistent with the existing literature describing a strong bidirectional relationship between sleep disturbances and mood disorders [13]. A meta-analysis by Baglioni et al. [6] demonstrated that insomnia doubles the risk of subsequent depression, while depressive symptoms exacerbate sleep fragmentation and prolong sleep latency [6]. From a neurobiological perspective, both depression and anxiety contribute to sleep disturbances through activation of the hypothalamic–pituitary–adrenal (HPA) axis and elevated nocturnal cortisol secretion, which interferes with slow-wave sleep [18]. This mechanism is particularly relevant in elderly individuals, for whom homeostatic sleep regulation is already compromised due to aging.
4.2. Full Mediation Mechanism: Why Loneliness Does Not Directly Affect Sleep Quality
One of the key findings of this study is the absence of a statistically significant direct association between loneliness and sleep quality after accounting for anxiety and depression within the structural model, indicating a full mediation pattern. This finding supports the Social Hypervigilance Theory proposed by Hawkley and Cacioppo [8], which posits that loneliness does not directly impair physiological functioning but instead operates through heightened emotional and cognitive vigilance [8]. In the context of elderly individuals living in nursing homes, loneliness appears to increase vulnerability to anxiety and depression, which in turn become the primary determinants of sleep disturbance.
4.3. Chain Mediation: Loneliness → Anxiety → Depression → Sleep Quality
The most important finding of this study is the significant chain mediation pathway in which loneliness was associated with higher anxiety levels, anxiety was associated with depressive symptoms, and depressive symptoms were associated with poorer sleep quality (β = −0.040, p = 0.045). This result aligns with findings by Yu et al. [19], which emphasize that emotional well-being in elderly individuals is strongly influenced by long-term affective stability rather than objective social conditions alone. Lonely elderly individuals in nursing homes may experience persistent rumination and excessive worry related to health, dependency, or uncertainty about the future, manifesting as anxiety. When sustained, this anxiety can evolve into depressive symptoms characterized by helplessness and hopelessness, which are strongly associated with sleep disruption [18,19]. The rising sympathetic nervous system activity associated with these emotional states maintains physiological arousal, thereby impairing sleep initiation and maintenance [20].
The strong correlation between anxiety and depression observed in this study (r = 0.637) is consistent with the tripartite model of anxiety and depression proposed by Clark and Watson [21], which describes shared negative affect as a common underlying component of both conditions. In elderly individuals, this comorbidity is often chronic and contributes to persistent sleep disturbances [21].
4.4. Clinical and Policy Implications for Elderly Individuals in Nursing Homes
The finding that loneliness affects sleep quality entirely through psychological mediators has important clinical and policy implications. These findings suggest that interventions focusing exclusively on the physical sleep environment or pharmacological treatment for insomnia may be insufficient if coexisting psychological distress is not concurrently addressed. Evidence from intervention studies suggests that social support-based programs, group activities, and structured psychosocial interventions are more effective in improving sleep quality among elderly individuals than symptom-focused approaches alone [22].
Furthermore, the correlation matrix results indicate that depression has the strongest association with poor sleep quality compared to anxiety, underscoring the need to prioritize mental health interventions in nursing homes. Psychoeducational programs, routine screening for anxiety and depression, and the provision of meaningful social activities may help mitigate loneliness and disrupt the psychological cascade leading to sleep disturbances. Overall, these findings highlight that improving sleep quality among elderly individuals living in nursing homes requires a holistic approach that integrates psychosocial care alongside environmental and medical interventions.
4.5. Study Limitations
This study employed a cross-sectional design; causal relationships cannot be inferred. The use of purposive sampling may limit the external validity of the proposed model, as the findings may not be easily extrapolated to the broader elderly population beyond the nursing homes included in this study. Further research with larger, more representative samples, including cohort or longitudinal studies, is needed to clarify the temporal pathways and strengthen the generalizability of these findings. Furthermore, medical comorbidities and environmental sleep factors were not controlled for and may have influenced the observed associations.
5. Conclusions
Based on the findings from 123 elderly individuals residing in nursing homes, the majority of participants experienced poor sleep quality. Loneliness was not directly related to sleep quality; however, it was associated with anxiety and depressive symptoms, which in turn were associated with poorer sleep outcomes, consistent with the proposed mediation model. These findings underscore the importance of integrating psychosocial approaches into sleep management strategies in institutional settings. Interventions such as structured social activities, psychoeducation, and routine mental health screenings may be beneficial in addressing loneliness and emotional distress alongside conventional sleep-focused treatments. Future longitudinal research is needed to confirm the temporal stability of the proposed mediation pathway and to determine whether targeted psychosocial interventions can modify these associations.
Author Contributions
Conceptualization, S.H. and C.R.P.A.; methodology, S.H., C.R.P.A., H.C., I.L.G. and L.A.K.; software, H.C., I.L.G. and L.A.K.; validation, S.H., C.R.P.A. and J.R.W.; formal analysis, I.L.G. and H.C.; investigation, S.H., I.L.G., L.A.K. and J.B.; resources, S.H., H.C. and I.L.G.; data curation, I.L.G., L.A.K. and J.B.; writing—original draft preparation I.L.G., L.A.K. and J.B.; writing—review and editing, H.C., I.L.G. and J.B.; visualization, S.H., C.R.P.A. and H.C.; supervision, S.H. and C.R.P.A.; project administration, S.H. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was conducted in accordance with the Declaration of Helsinki and received ethical approval from the Institutional Review Board of Atma Jaya Catholic University of Indonesia (Approval code: 03/04/KEP-FKIKUAJ/2025 and Approval date: 7 April 2025).
Informed Consent Statement
Written informed consent has been obtained from the patient(s) to publish this paper.
Data Availability Statement
The data presented in this study are available on reasonable request from the corresponding author. The data are not publicly available due to privacy and ethical restrictions.
Acknowledgments
The authors would like to thank the nursing home management and staff for their cooperation during this study. The authors also acknowledge Atma Jaya Catholic University of Indonesia and Atma Jaya Teaching & Research Hospital, particularly the Department of Psychiatry and Behavioral Sciences, School of Medicine and Health Sciences; Department of Psychology and the Centre of Societal and Development Studies; and the Department of Neurology for their valuable collaboration, academic support, and institutional assistance in conducting this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| GAD-7 | Generalized Anxiety Disorder-7 |
| HPA | Hypothalamic–Pituitary–Adrenal |
| PHQ-9 | Patient Health Questionnaire-9 |
| PSQI | Pittsburgh Sleep Quality Index |
| r | Pearson correlation coefficient |
| β | Standardized regression coefficient |
| SEM | Structural Equation Modeling |
| UCLA | University of California, Los Angeles |
| UNDESA | United Nations Department of Economic and Social Affairs |
References
- United Nations Department of Economic and Social Affairs. World Population Ageing 2020 Highlights: Living Arrangements of Older Persons; United Nations: New York, NY, USA, 2020.
- Badan Pusat Statistik. Statistics of the Elderly Population 2021; Badan Pusat Statistik: Jakarta, Indonesia, 2021.
- Li, J.; Vitiello, M.V.; Gooneratne, N.S. Sleep in Normal Aging. Sleep Med. Clin. 2022, 17, 161–171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jaqua, E.E.; Hanna, M.; Labib, W.; Moore, C.; Matossian, V. Common Sleep Disorders Affecting Older Adults. Perm. J. 2022, 27, 122–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, J.; Ou, J.; Lu, X.; Wang, T.; Dang, W.; Ding, L.; Liu, Y.; Xu, J.; Yan, B.; Yu, H. Sleep Disorders and The Risk of Cognitive Decline or Dementia: An Updated Systematic Review and Meta-Analysis of Longitudinal Studies. J. Neurol. 2025, 272, 689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baglioni, C.; Battagliese, G.; Feige, B.; Spiegelhalder, K.; Nissen, C.; Voderholzer, U.; Lombardo, C.; Riemann, D. Insomnia as a predictor of depression: A meta-analytic evaluation of longitudinal epidemiological studies. J. Affect. Disord. 2011, 135, 10–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, K.; Xue, S. Effect of Cognitive Behavioral Therapy for Insomnia on Sleep Quality Among College Students: The Role of Hyperarousal And Dysfunctional Beliefs. Behav. Sleep Med. 2025, 23, 54–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hawkley, L.C.; Cacioppo, J.T. Loneliness matters: A theoretical and empirical review of consequences and mechanisms. Ann. Behav. Med. 2010, 40, 218–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kurt, A.A.; Bakır Aygar, B. The Mediating Role of Toxic Relationship Behaviors and Perceived Romantic Relationship Quality in the Relationship Between Loneliness and Life Satisfaction. Mersin Üniversitesi Eğitim Fakültesi Derg. 2025, 21, 617–630. [Google Scholar] [CrossRef] [Scilit]
- Griffin, S.C.; Williams, A.B.; Mladen, S.N.; Perrin, P.B.; Dzierzewski, J.M.; Rybarczyk, B.D. Reciprocal Effects Between Loneliness and Sleep Disturbance in Older Americans. J. Aging Health 2019, 32, 1156–1164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Osorio, R.S.; Martínez-García, M.Á.; Rapoport, D.M. Sleep Apnoea in The Elderly: A Great Challenge for the Future. Eur. Respir. J. 2022, 59, 2101649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rui, J.R.; Guo, J. Differentiating The Stress Buffering Functions of Perceived Versus Received Social Support. Curr. Psychol. 2023, 42, 13432–13442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hasan, S.; Ajisuksmo, C.R.P.; Widayanti, J.R. Anxiety, Cognitive Function, and Their Impact on Sleep Quality Among Older Adults Living in Nursing Homes in Jakarta and Tangerang. J. Sains Kesehat. 2025, 6, 151–160. [Google Scholar] [CrossRef] [Scilit]
- Spitzer, R.L.; Kroenke, K.; Williams, J.B.W.; Löwe, B. A brief measure for assessing generalized anxiety disorder: The GAD-7. Arch. Intern. Med. 2006, 166, 1092–1097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kroenke, K.; Spitzer, R.L.; Williams, J.B.W. The PHQ-9: Validity of a brief depression severity measure. J. Gen. Intern. Med. 2001, 16, 606–613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russell, D.W. UCLA Loneliness Scale (Version 3): Reliability, validity, and factor structure. J. Pers. Assess. 1996, 66, 20–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buysse, D.J.; Reynolds, C.F.; Monk, T.H.; Berman, S.R.; Kupfer, D.J. Pittsburgh Sleep Quality Index (PSQI). Available online: https://www.med.upenn.edu/cbti/assets/user-content/documents/Pittsburgh%20Sleep%20Quality%20Index%20(PSQI).pdf (accessed on 10 January 2026).
- Udi, O.A. Sleep, Neuroendocrine Disorders, and the Bidirectional Relationship between the Hypothalamic-Pituitary-Adrenal Axis: A Mini-Review. J. Appl. Sci. Environ. Manag. 2025, 29, 1217–1227. [Google Scholar]
- Yu, B.; Steptoe, A.; Chen, Y. Social Isolation, Loneliness, and All Cause Mortality: A Cohort Study of 35,254 Chinese Older Adults. J. Am. Geriatr. Soc. 2022, 70, 1717–1725. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mathentamo, Q.; Lawana, N.; Hlafa, B. Interrelationship Between Subjective Wellbeing and Health. BMC Public Health 2024, 24, 2213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clark, L.A.; Watson, D. Tripartite model of anxiety and depression: Psychometric evidence and taxonomic implications. J. Abnorm. Psychol. 1991, 100, 316–336. [Google Scholar] [CrossRef] [PubMed]
- Irwin, M.R.; Hoang, D.; Olmstead, R.; Sadeghi, N.; Breen, E.C.; Bower, J.E.; Cole, S. Tai Chi Compared with Cognitive Behavioral Therapy and The Reversal of Systemic, Cellular and Genomic Markers of Inflammation in Breast Cancer Survivors With Insomnia: A Randomized Clinical Trial. Brain. Behav. Immun. 2024, 120, 159–166. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.