


Abstract
Background/Objectives: Patients with poor sleep are at high risk of developing type II diabetes mellitus (T2DM). Since T2DM is linked to increased risk of obstructive sleep apnea (OSA), and Metformin is commonly used to treat T2DM, we examined how Metformin affects sleep stages in patients with concurrent T2DM and OSA-related symptoms of snoring and fatigue. Patients with T2DM on Metformin progressively develop increased insulin resistance associated with sleep disturbances and poor glycemic control. We therefore explored sleep pattern changes in patients with OSA symptoms and T2DM on Metformin, with a special focus on whether Metformin affects sleep architecture. Methods: Polysomnogram (PSG) data from patients with T2DM on Metformin was evaluated along with data on age, body-mass index (BMI), and biological sex. Data analysis included mean ± standard deviation, t-test with p < 0.05 taken as significant, and linear regression. Results: Patients with a BMI of less than 30 (non-obese) and taking Metformin exhibited a significantly shorter rapid eye movement sleep stage (REM) duration than patients on alternative therapies (p = 0.036). No such difference in REM was found for patients with a BMI of 30 or greater (obese) taking Metformin. While there was also no significant difference in slow-wave sleep stage (N3) duration with Metformin use, linear regression identified a moderate negative correlation between N3 and age in patients taking non-Metformin therapies (R2 = 0.4555). No significant correlations between sleep stage duration and patient sex, smoking status, or BMI greater than 30 were identified. Conclusions: Overall, patients with OSA and T2DM on Metformin had lower mean quantities of N3, and REM sleep compared to those not on Metformin. Non-obese patients with T2DM and OSA being treated with Metformin were observed to have less REM sleep, regardless of sex or smoking history. N3 and REM sleep are needed for the timely secretion of growth hormone and memory consolidation. Since Metformin is correlated with differences in N3 and REM sleep, it may contribute to the development of insulin resistance. Future studies are needed to explore potential causes for this relationship and how it may affect the treatment of T2DM.
Keywords:
diabetes; metformin; sleep apnea; sleep architecture; REM sleep; insulin resistance; N3 sleep; sleep stages 1. Introduction
According to the Centers for Disease Control and Prevention [1], in 2021, roughly 8.9% of the U.S. population—or about 29.7 million people—had been diagnosed with diabetes mellitus. Of the U.S. adults who have been diagnosed with diabetes, about 91.2% have type II diabetes mellitus (T2DM) [2]. In T2DM, the body may produce insulin, but the tissues are insulin-resistant, meaning that they cannot respond to that insulin. If untreated, T2DM can lead to a variety of health complications, including cardiovascular disease, kidney failure, peripheral neuropathy, and sleep disordered breathing (SDB).
Of these complications, SDB has a particularly interesting interplay with T2DM. SDB describes a spectrum of conditions that cause abnormal breathing during sleep, typically by affecting the upper airway [3]. One type of SDB called obstructive sleep apnea (OSA) is a disorder where the upper airway partially or completely collapses during sleep, which can lead to apneas (transient pauses in breathing), hypoxemia, and reduced quality and duration of sleep. Patients with OSA often present with snoring, daytime sleepiness, and fatigue [4].
In addition to having similar risk factors, including increased age, smoking, alcohol use, and elevated body-mass index (BMI) [5], OSA and T2DM may exacerbate one another [3,6,7,8]. For instance, poor sleep quality—such as frequent waking—has been associated with lower insulin sensitivity and glucose tolerance [7,9,10]. Furthermore, T2DM may affect the control of breathing and pharyngeal muscles, which can worsen OSA [6]. Notably, OSA is more common among people with T2DM than among the general population. The overall prevalence of OSA diagnosed by polysomnogram (PSG) among people with T2DM ranges from 58 to 86% [11]. However, there is some uncertainty about the true prevalence of OSA in patients with diabetes. Heffner et al. [12] found that only 18% of patients with T2DM were officially diagnosed with OSA by their primary care physician, although the investigators attributed this number to underdiagnosis.
Many of these patients with T2DM were likely prescribed the oral medication Metformin. According to the American Diabetes Association [13] Standards of Medical Care in Diabetes, Metformin is the first-line drug for treating T2DM in patients over the age of 10 years old. Metformin can be used as monotherapy or in combination with other antidiabetic medications, depending on the severity of diabetes. It works by improving insulin sensitivity, decreasing glucose production in the liver, and decreasing glucose absorption by the intestines [14]. Over the years, Metformin prescriptions have become more common. In 2000, FDA-approved prescriptions of Metformin numbered 2.27 per 1000 people in the U.S., but by 2015, this number had increased to 235 per 1000 people [15]. As of 2023, Metformin was being taken by over 200 million people worldwide [16].
Some of the rarer side effects of Metformin include insomnia and nightmares [17,18]. Although there is limited research on the mechanism behind these effects of Metformin, it has been well documented that diabetes and differential glycemic control affect sleep architecture–the organization and stages of sleep. A higher Hemoglobin A1c (HbA1c) has been associated with decreased rapid eye movement (REM) sleep latency (the time between falling asleep and the first REM cycle) [19] and decreased sleep efficiency (percent of time in bed that is spent asleep) [20]. However, there is conflicting data on the relationship between T2DM and sleep stage duration. While Pallayova et al. [21] found that people with T2DM experience decreased slow-wave (N3) sleep and increased REM sleep, a more recent study by Chen et al. [22] suggested the opposite, that T2DM leads to increased N3 and decreased REM. Additionally, our previous work investigating the effects of insulin on sleep architecture showed that insulin therapy was associated with reduced N3 and REM sleep, without differences between sexes in patients with high BMI [23,24]. It is important to note such changes to sleep architecture because healthy sleep architecture accounts for the various benefits of sleep. For example, the deep stages of non-REM sleep aid in tissue repair [25], and REM sleep is important for memory consolidation and learning [26].
Given the rise in Metformin prescriptions and the data indicating that both diabetes and Metformin affect sleep, the purpose of this study is to determine whether Metformin is associated with changes to sleep architecture in patients presenting with concurrent T2DM and OSA. Specifically, we aim to study the relationship between different phases of sleep and total sleep time in these patients.
2. Hypothesis
We hypothesize that Metformin affects sleep and influences sleep architecture. Thus, we sought to determine sleep architecture in patients with T2DM who were taking Metformin for metabolic control and showed sleep-disturbance symptoms of excessive daytime sleepiness, snoring, and fatigue.
3. Methods
We conducted a retrospective community-based cohort study that was approved by the California University of Science and Medicine IRB-HS-2020-11. Study participants included a diverse patient population in an underserved area in Southern California. PSG was medically indicated in these patients because of suspected sleep disorders, and patients were referred to the Sleep Clinic for evaluation and treatment by their primary care physicians [27].
Inclusion criteria included: (1) Adult patients 18 years of age or older, (2) Patients with T2DM and currently receiving treatment, and (3) Patients with T2DM undergoing overnight PSG only (without CPAP treatment) under technician observation in a sleep laboratory.
Exclusion criteria included: (1) Patients without a T2DM diagnosis, (2) Patients with T2DM but not taking either Metformin or Insulin, (3) Patients under 18 years of age, (4) Patients undergoing split night study or CPAP treatment, (5) Sleep studies that were less than 6 h long, and (6) Patients who consumed oxybate (Xyrem) on the night of study, as oxybates increase slow-wave sleep [28].
Patients underwent a six-channel electroencephalogram (EEG), electrooculogram (EOG), electromyogram (EMG), electrocardiogram (EKG), and pulse oximetry. Thoracic and abdominal respiratory effort was measured through respiratory inductance plethysmography (RIP) belts and body position. Air flow was monitored by a thermistor, and body position was monitored by body position sensors. Sleep staging was performed by an experienced sleep technician using American Academy of Sleep Medicine (AASM) [29] guidelines and verified by a physician, both of whom were blind to the study. Data on age, sex, BMI, and medications were collected. Light sleep (N1), deep sleep (N2), N3, and REM sleep stage data were analyzed. Each sleep stage was analyzed in relation to total sleep time (TST). Data analysis included the mean, t-test with statistical significance determined by p-value < 0.05, and linear regression. Because of logistical constraints, this study was conducted on a relatively small sample of patients (n = 51), and sleep stage data prior to their current diabetes treatment regimens were not available. Therefore, it is not possible to draw definitive causal inferences based solely on the available data, and any results should be interpreted as correlational.
4. Results
Among 29 patients taking Metformin, the duration of REM sleep was significantly shorter than that of the 22 control patients taking only non-Metformin diabetes therapy, such as Lantus or Novolog (p = 0.034, Table 1, Figure 1). There was no significant difference in N3 sleep between Metformin patients and non-Metformin patients on alternative diabetes therapy (p = 0.750, Table 1).
Table 1.
Patient sample data for age (in years), BMI (kg/m2), sleep stages, and total sleep time (in hours). SD = standard deviation.
Figure 1.
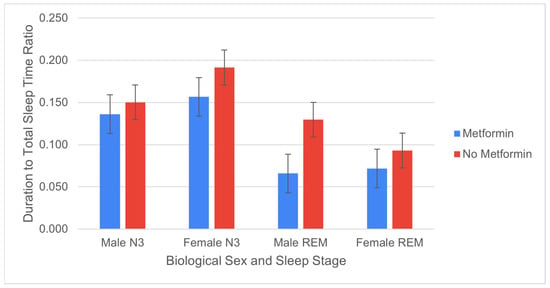
Average N3 and REM sleep duration between different biological sexes on Metformin. Shown here are the mean N3 and REM sleep stages represented as a ratio of sleep stage duration to total sleep time (hours). Blue = patients taking Metformin, red = patients not taking Metformin. Error bars signify standard error. No significant difference was found in either N3 or REM duration between male and female patients.
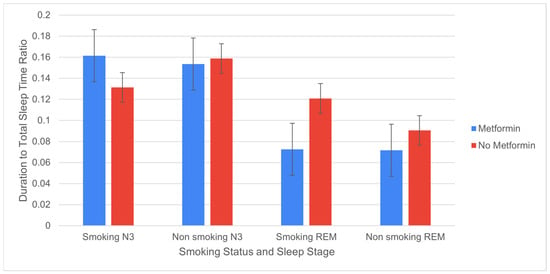
Of the 29 patients prescribed Metformin, 20 patients were female and 9 patients were male. There was no significant difference observed in either N3 or REM sleep time between sexes (Figure 1). Additionally, of the patients on Metformin, 13 patients had a prior smoking history or were active smokers, 14 had never smoked tobacco, and 2 had an unknown smoking history. There was no significant difference in either N3 or REM sleep duration between smokers and non-smokers (REM p = 0.969, N3 p = 0.865, Figure 2).
Figure 2.
Average N3 and REM sleep stage duration between patients with smoking history (current and former) and patients with no smoking history. The y-axis shows mean N3 and REM sleep stages represented as a ratio of sleep stage duration to TST (hours). Blue = patients taking Metformin, red = patients not taking Metformin. Error bars represent standard error. Four patients were excluded due to unknown smoking status (2 on Metformin, 2 not on Metformin). No significant difference was observed between patients with smoking versus non-smoking status.
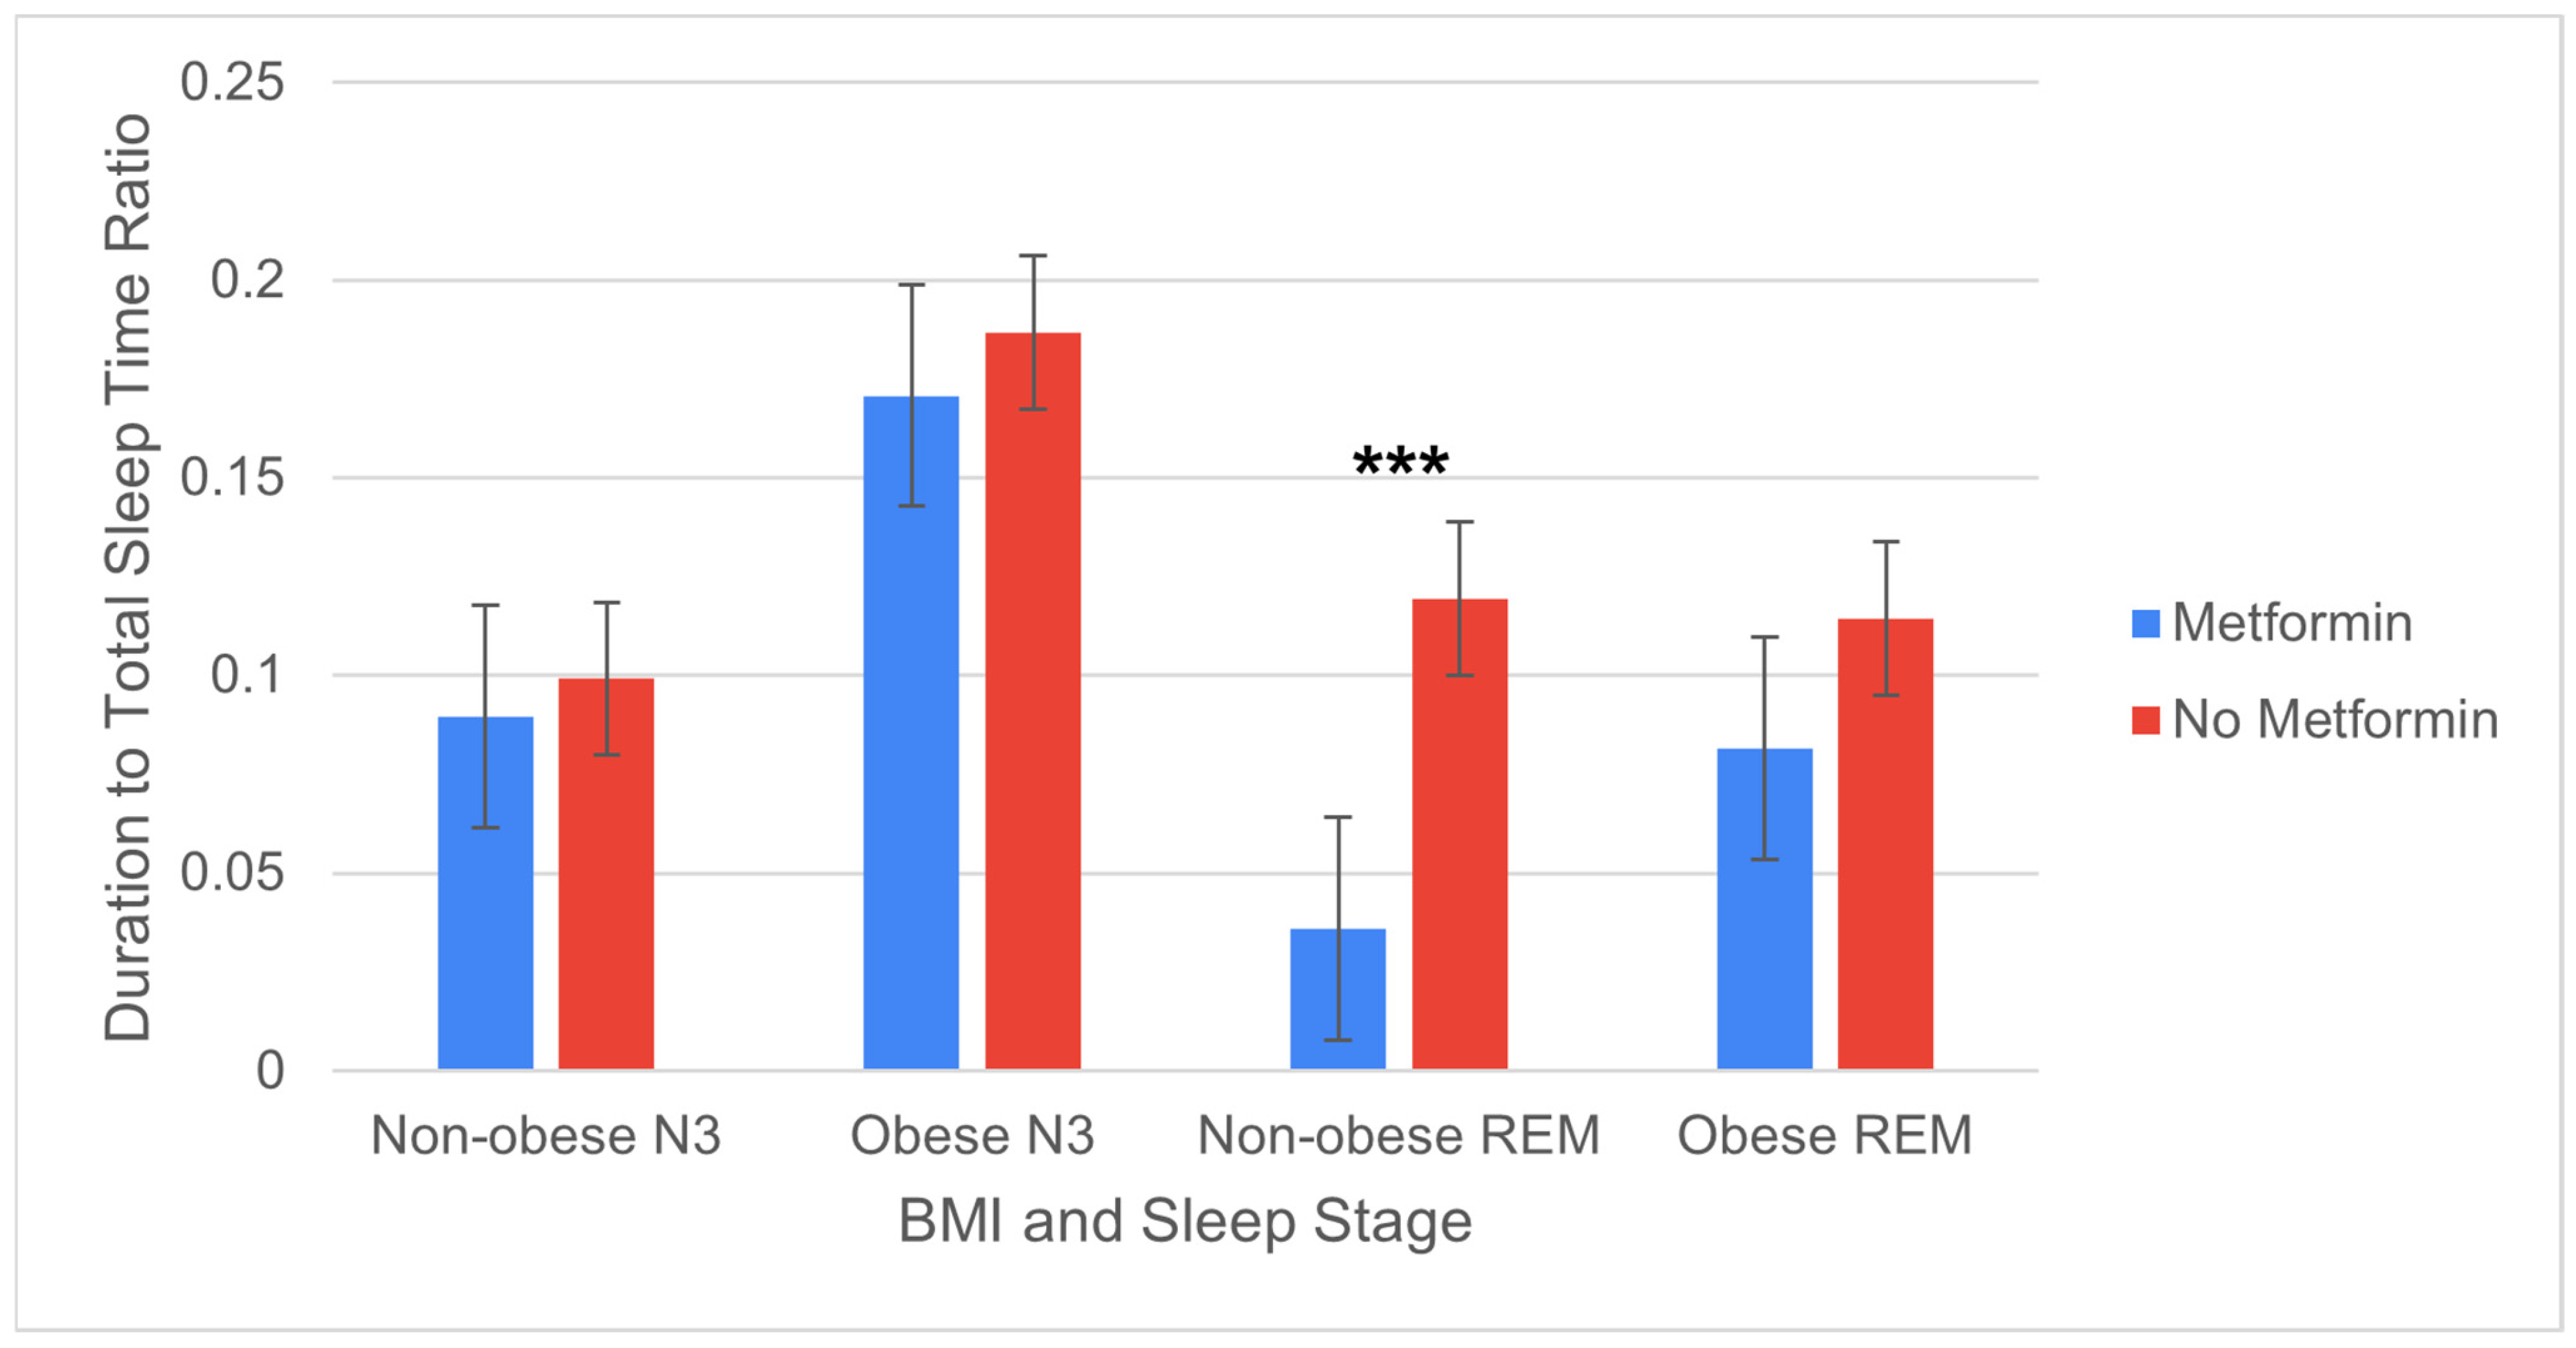
Using data from 12 patients with a BMI less than 30 (non-obese), of whom 7 patients were prescribed Metformin and 5 patients were not, we found that patients taking Metformin experienced significantly shorter durations of REM sleep than patients on alternative therapy (p = 0.036, Figure 3).
Figure 3.
Average N3 and REM sleep duration between non-obese (healthy, overweight) and obese patients. The y-axis shows mean N3 and REM sleep stages as a ratio of sleep stage duration to TST (hours). Blue = patients taking Metformin, red = patients not taking Metformin. Error bars indicate standard error. The asterisks (***) mark a statistically significant difference in REM sleep stage duration between non-obese patients on Metformin vs. not on Metformin (p = 0.036).
Using data from 36 patients with a BMI of 30 or greater (obese), of whom 20 patients were prescribed Metformin and 16 patients were not, we found no significant difference between the duration of REM sleep between Metformin patients and non-Metformin patients, although Metformin patients generally had a lower duration of REM sleep (Figure 3). In both patients with and without obesity, no significant difference in N3 sleep duration was observed between patients taking Metformin and those taking alternative therapies.
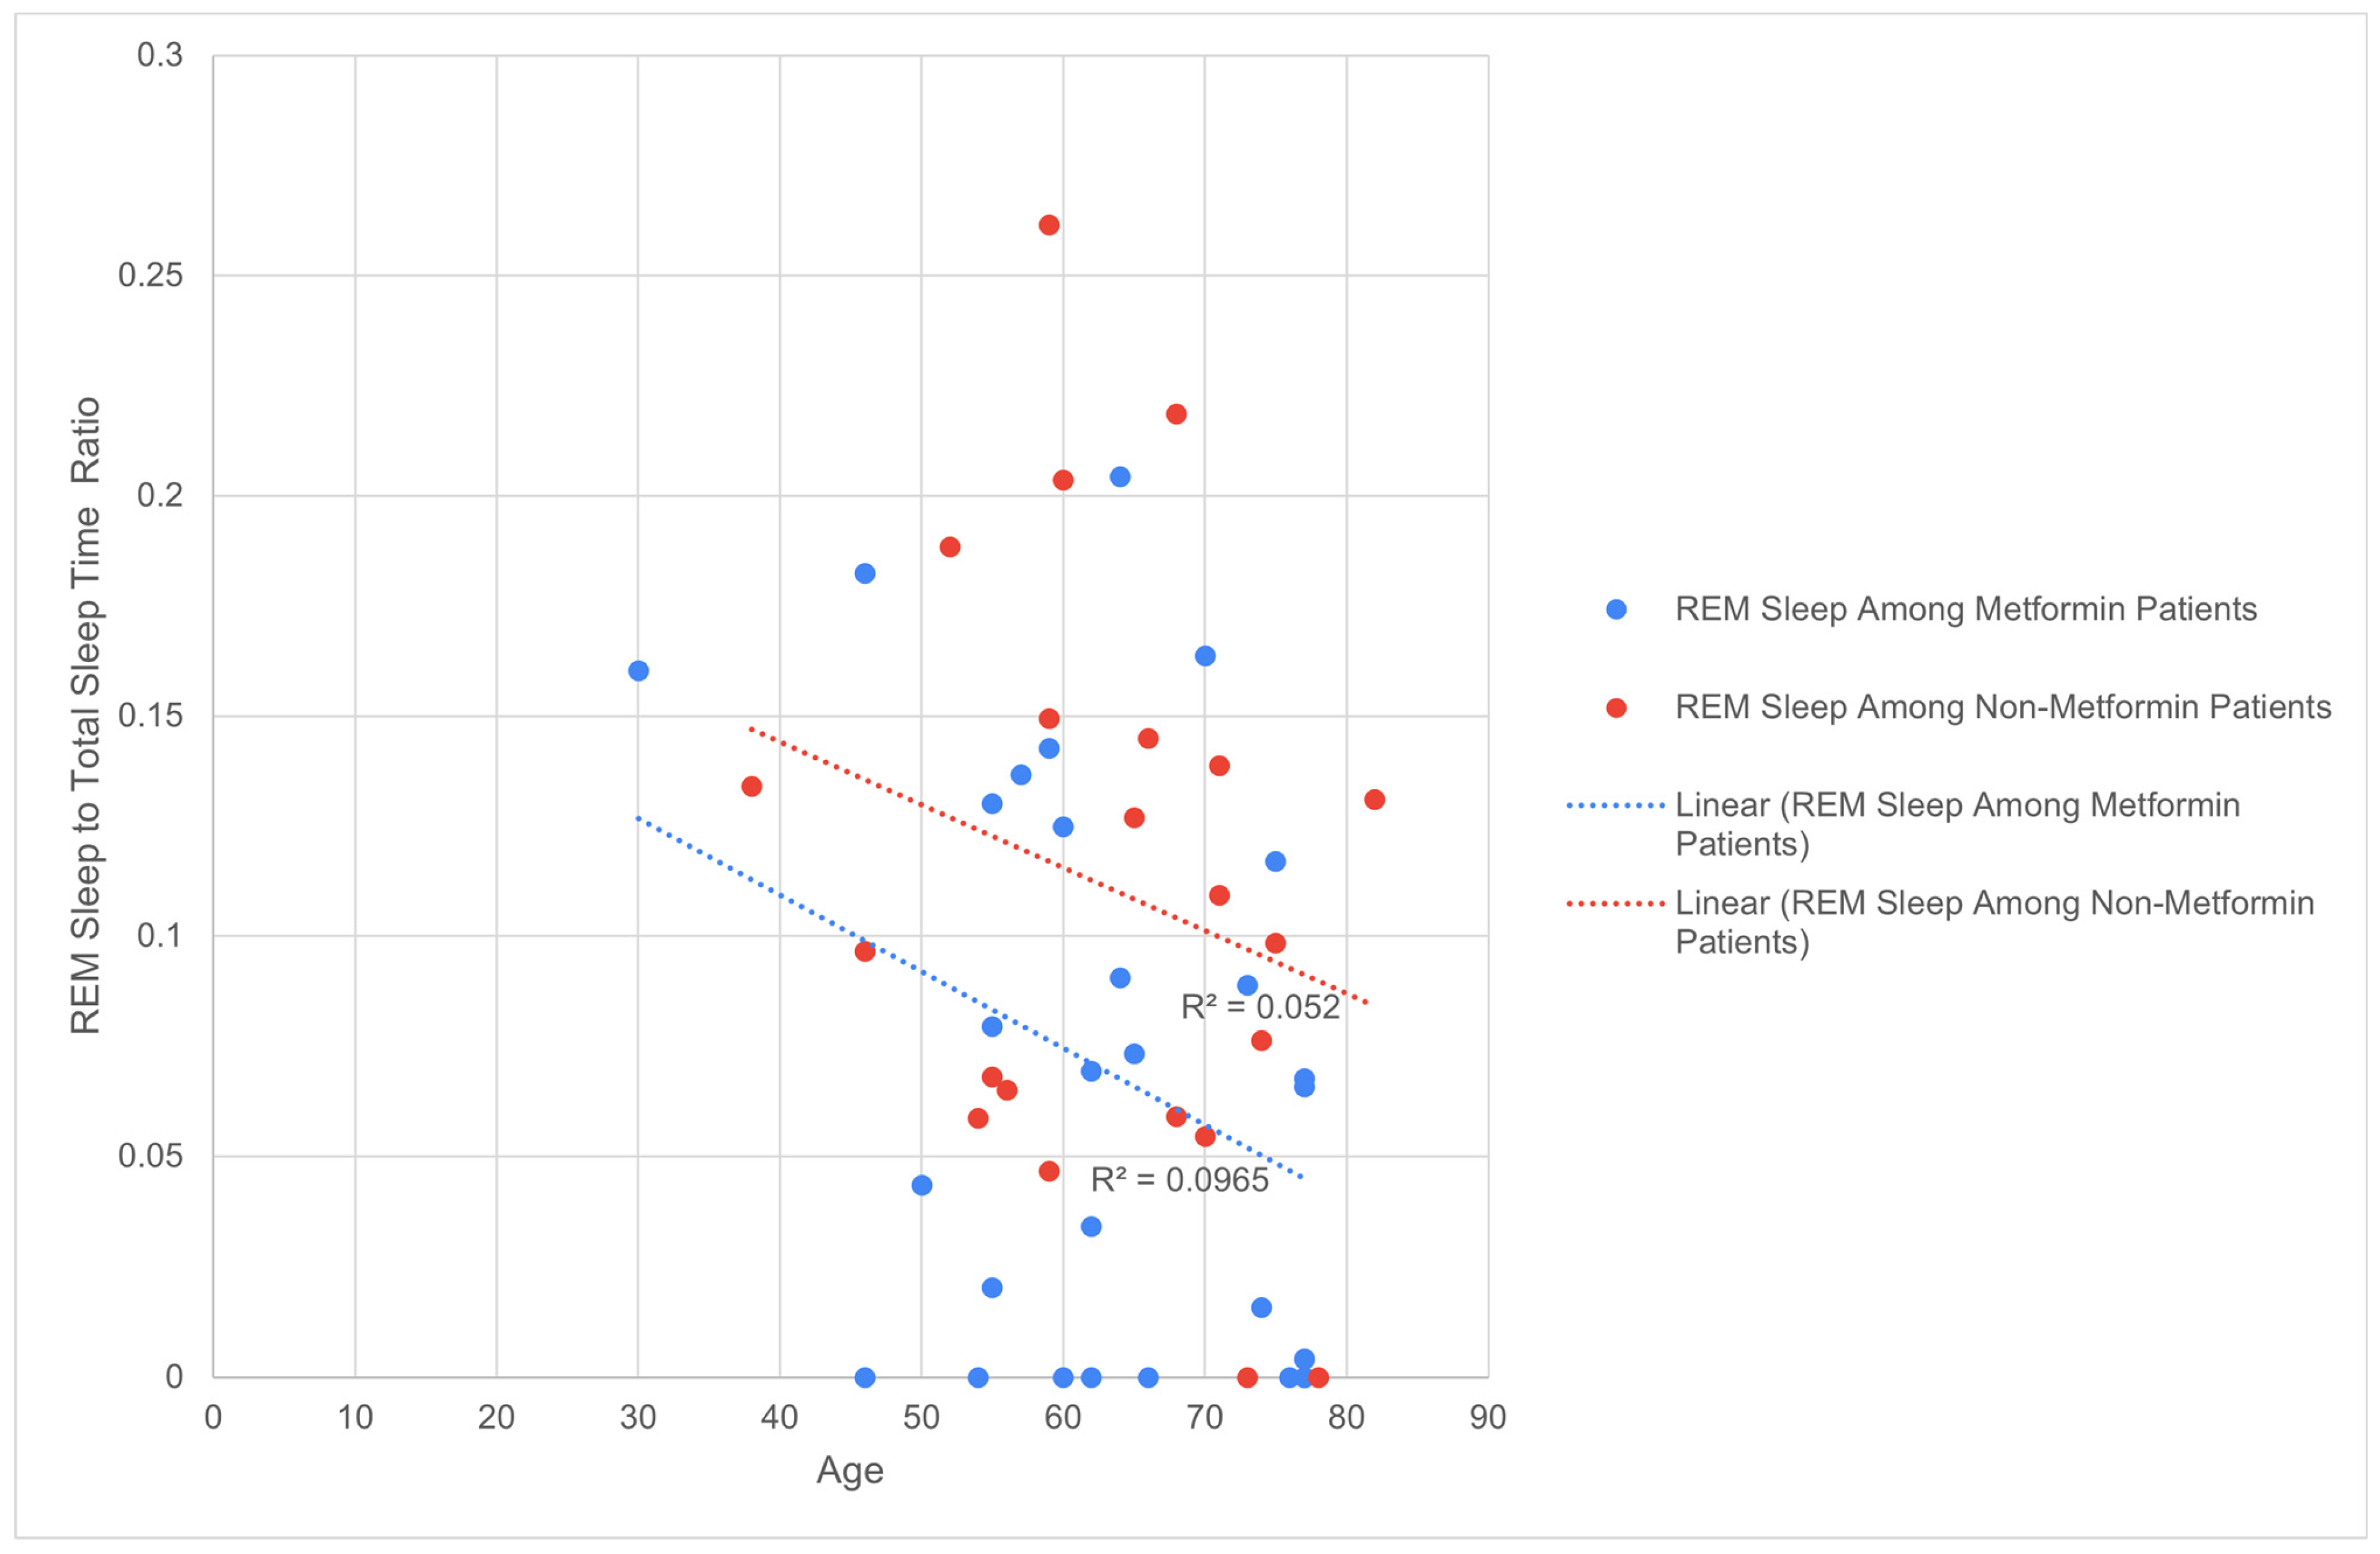
A linear regression analysis demonstrated that among patients using Metformin (R2 = 0.0965) and patients on alternative diabetes therapies (R2 = 0.052), REM sleep duration was not dependent on age (Figure 4).
Figure 4.
REM sleep vs. age (years) in Metformin and non-Metformin control patients. Amount of REM sleep is represented on the y-axis as a ratio of the duration of REM to TST. Blue = patients taking Metformin, red = patients not taking Metformin. Blue dotted line = linear association between REM sleep and age among patients on Metformin. Red dotted line = linear association between REM sleep and age among patients not on Metformin.
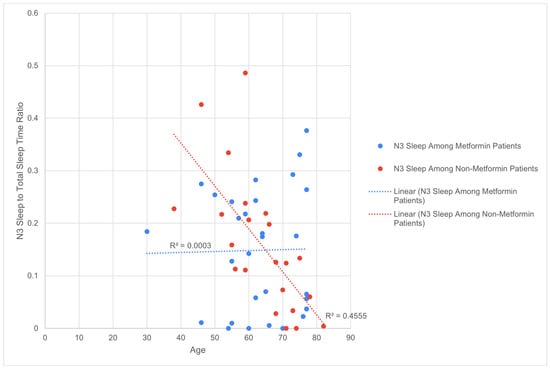
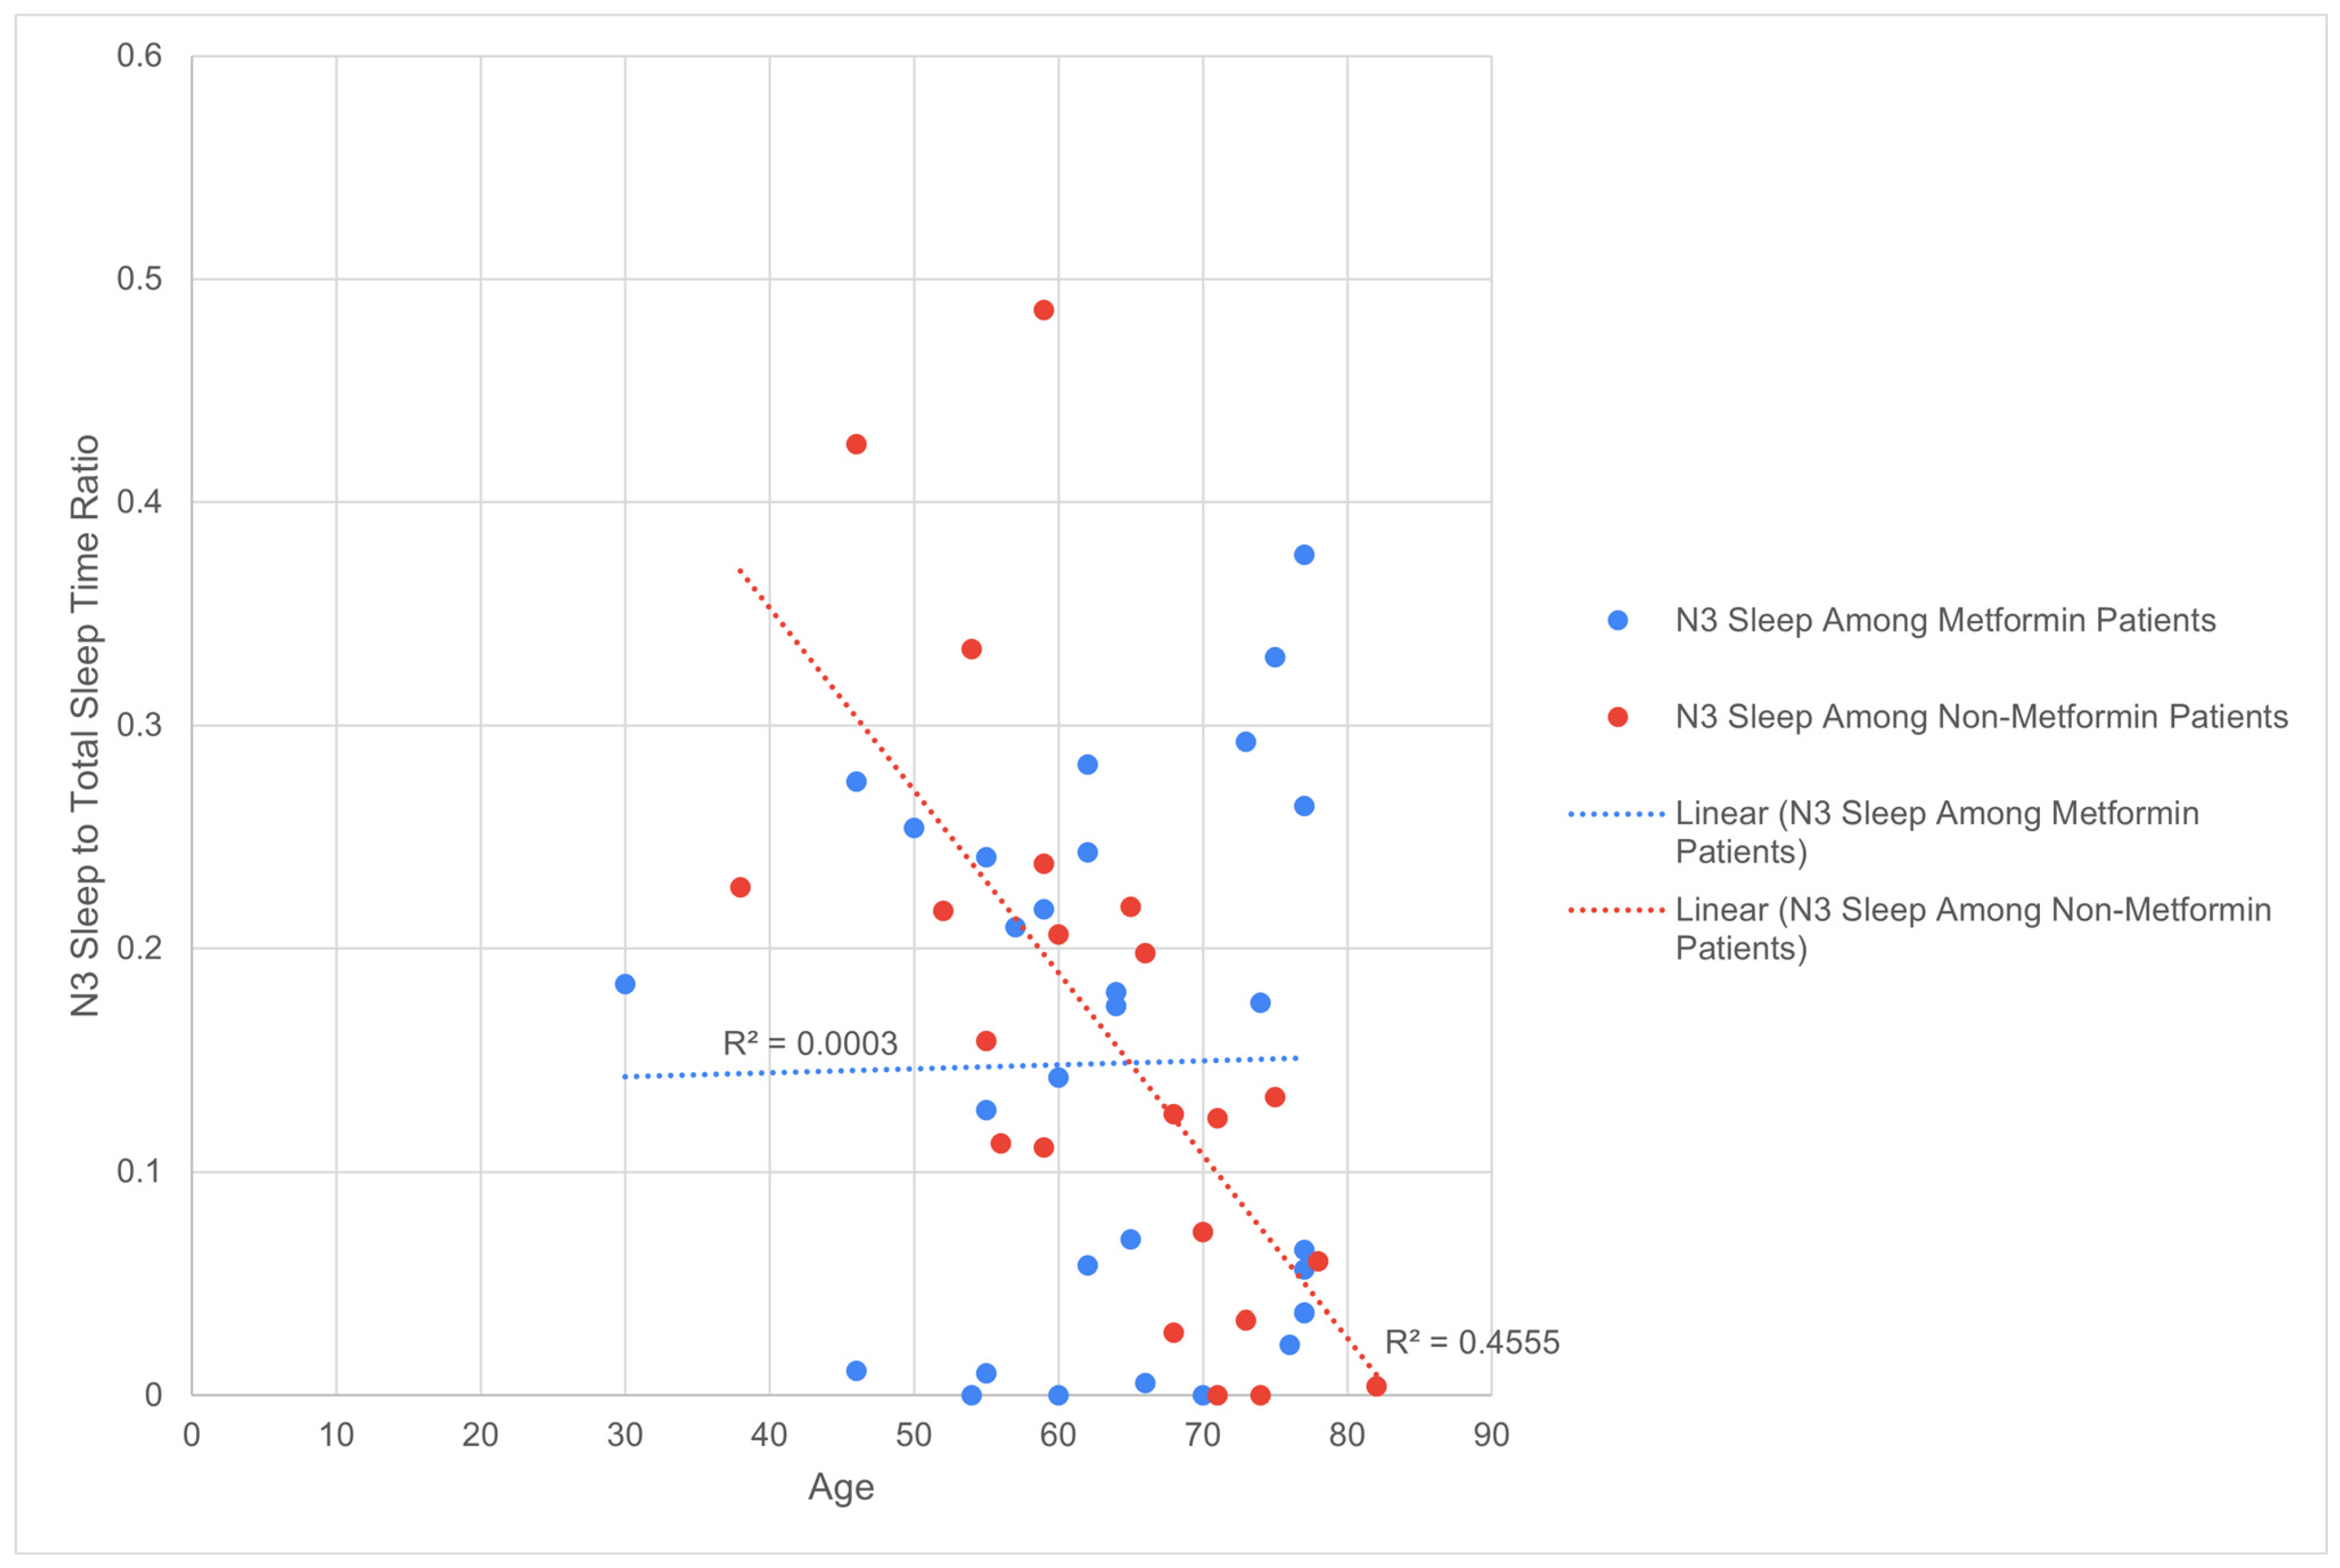
However, linear regression analysis also revealed a moderate inverse relationship between N3 sleep and age in non-Metformin patients (R2 = 0.4555) that does not appear in patients taking Metformin (R2 = 0.0003, Figure 5).
Figure 5.
N3 sleep vs. age (years) in Metformin and non-Metformin control patients. Amount of REM sleep is represented on the y-axis as a ratio of the duration of REM to TST. Blue = patients taking Metformin, Red = patients not taking Metformin. Blue dotted line = linear association between REM sleep and age among patients on Metformin. Red dotted line = linear association between REM sleep and age among patients not on Metformin.
5. Discussion
Both T2DM and OSA have been associated with noticeable effects on sleep architecture [30,31,32]. For instance, both T2DM and higher HbA1c scores have been correlated with a reduced duration of REM sleep [20,22,30,31,32]. But while at least three independent case reports have documented patients with T2DM experiencing recurrent nightmares with Metformin use [32,33,34], there is limited existing research on whether Metformin alters sleep architecture. To our knowledge, this study is one of the first to explore the relationship between T2DM, OSA, and Metformin and how they may jointly affect sleep architecture.
Our data show that the percentage of REM sleep was significantly lower in non-obese patients taking Metformin compared to those using other diabetes therapies. Meanwhile, there was no significant difference in the percentage of N3 sleep between patients taking Metformin versus those on alternative treatments. Likewise, neither biologic sex nor smoking status was associated with a significant difference in sleep stage duration. Together, these data suggest that Metformin is associated with altered sleep architecture, specifically lower REM sleep duration, independent of factors including sex or smoking status.
Based on these data, we postulate that interactions between Metformin use and REM sleep may have implications for treating diabetes in an aging population. REM is characterized by aperiodic neural activity, an unsynchronized signal without oscillations on EEG, and a recent study by Lendner et al. [35] demonstrated that this aperiodic activity is predictive of memory retention. It is also well-documented that aging is associated with changes in sleep architecture, specifically a decrease in REM sleep [36]. An even greater decrease in REM sleep has been observed in elderly patients with mild cognitive impairment or Alzheimer’s disease [37]. Our results suggest that patients with OSA and T2DM on Metformin may experience shorter durations of REM sleep. This difference may compound the already decreased REM seen in aging patients, thereby possibly impacting both their memory and quality of life. However, additional research is needed to establish a causal relation and clinical significance.
Of note, the data do not demonstrate a significant relationship between either REM or N3 sleep and sex, despite multiple prior studies showing that female patients without diabetes tend to spend more time in non-REM and less time in REM sleep than male patients [38,39]. One potential reason our data differ from the existing literature is that many of the female patients in our current study are older and peri- or postmenopausal, which is associated with a decline in female sex hormones. Additionally, all the patients in our study were diagnosed with T2DM, whereas past studies focused on populations without diabetes.
The lack of correlation between REM sleep and obesity was consistent with prior studies that found that obese and non-obese populations experienced similar durations of REM sleep [40]. While obesity is one of the strongest risk factors for OSA, people with obesity can have varying degrees of OSA severity. Of the U.S. adults who have been diagnosed with obesity, roughly 69% have some level of OSA, but only about 32% have moderate to severe OSA [41]. The different levels of OSA severity may, in turn, have different relationships with REM sleep duration. While severe OSA has been linked to a decrease in REM sleep in adolescents with obesity, mild OSA has been linked to an increase in REM [41,42]. It may be reasonable to attribute the similarities in REM sleep between obese and non-obese populations to the wide range of OSA severity among these patients. While our study was limited because OSA severity was not reported, this provides direction for future studies.
Additional limitations of this study include the relatively small sample size and the fact that the study population was derived from Southern California, which may narrow the generalizability of these findings. Moreover, while our data revealed correlations between Metformin use and changes in sleep architecture, further studies would be required to identify causal relationships and clinical significance, especially given that many patients were taking non-Metformin medications or may have had poor glycemic control that could also influence their sleep.
6. Conclusions
This study provides evidence that Metformin is associated with a shorter duration of REM sleep in patients with T2DM and OSA, which may indicate lower sleep quality in these patients regardless of sex, smoking history, and BMI. Future studies using larger populations are needed to explore potential causes for such an association and how it may affect the therapeutic options for patients with concurrent T2DM and sleep disorders.
Author Contributions
Conceptualization, M.V.; Methodology, M.V.; Formal analysis, K.M. and D.N.; Investigation, M.V.; Data curation, D.N.; Writing—original draft, K.M. and D.N.; Writing—review and editing, K.M., D.N. and M.V.; Supervision, M.V.; Project administration, M.V. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
We conducted a retrospective community-based cohort study that was approved by California University of Science and Medicine IRB-HS-2020-11, date 3 September 2020.
Informed Consent Statement
Patient consent was waived due to retrospective data.
Data Availability Statement
Data is available upon request from corresponding author M Varma.
Acknowledgments
Thank you to A Sahai, Trika Medical Inc., for his support and help with data collection. Support: CUSM Student Research Scholarship.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| BMI | Body Mass Index |
| N1, N2, N3 | Non-REM stages of sleep, from lighter to deep |
| OSA | Obstructive Sleep Apnea |
| PSG | Polysomnogram |
| REM | Rapid Eye Movement |
| T2DM | Type II Diabetes |
| TST | Total sleep time |
References
- Centers for Disease Control and Prevention. National Diabetes Statistics Report. 15 May 2024. Available online: https://www.cdc.gov/diabetes/php/data-research/index.html (accessed on 6 June 2024).
- Xu, G.; Liu, B.; Sun, Y.; Du, Y.; Snetselaar, L.G.; Hu, F.B.; Bao, W. Prevalence of diagnosed type 1 and type 2 diabetes among US adults in 2016 and 2017: Population based study. BMJ 2018, 362, k1497. [Google Scholar] [CrossRef] [Scilit]
- Punjabi, N.M.; Shahar, E.; Redline, S.; Gottlieb, D.J.; Givelber, R.; Resnick, H.E. Sleep Heart Health Study Investigators. Sleep-disordered breathing, glucose intolerance, and insulin resistance: The Sleep Heart Health Study. Am. J. Epidemiol. 2004, 160, 521–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pham, L.V.; Jun, J.; Polotsky, V.Y. Obstructive sleep apnea. Handb. Clin. Neurol. 2022, 189, 105–136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitra, A.K.; Bhuiyan, A.R.; Jones, E.A. Association and Risk Factors for Obstructive Sleep Apnea and Cardiovascular Diseases: A Systematic Review. Diseases 2021, 9, 88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kurnool, S.; McCowen, K.C.; Bernstein, N.A.; Malhotra, A. Sleep Apnea, Obesity, and Diabetes—An Intertwined Trio. Curr. Diabetes Rep. 2023, 23, 165–171. [Google Scholar] [CrossRef] [Scilit]
- Xu, H.; Liang, C.; Zou, J.; Yi, H.; Guan, J.; Gu, M.; Feng, Y.; Yin, S. Interaction between obstructive sleep apnea and short sleep duration on insulin resistance: A large-scale study: OSA, short sleep duration and insulin resistance. Respir. Res. 2020, 21, 151. [Google Scholar] [CrossRef] [Scilit]
- Aronsohn, R.S.; Whitmore, H.; Van Cauter, E.; Tasali, E. Impact of untreated obstructive sleep apnea on glucose control in type 2 diabetes. Am. J. Respir. Crit. Care Med. 2010, 181, 507–513. [Google Scholar] [CrossRef] [Scilit]
- Muraki, I.; Wada, H.; Tanigawa, T. Sleep apnea and type 2 diabetes. J. Diabetes Investig. 2018, 9, 991–997. [Google Scholar] [CrossRef] [Scilit]
- Rutters, F.; Nefs, G. Sleep and Circadian Rhythm Disturbances in Diabetes: A Narrative Review. Diabetes Metab. Syndr. Obes. Targets Ther. 2022, 15, 3627–3637. [Google Scholar] [CrossRef] [Scilit]
- Pamidi, S.; Tasali, E. Obstructive sleep apnea and type 2 diabetes: Is there a link? Front. Neurol. 2012, 3, 126. [Google Scholar] [CrossRef] [Scilit]
- Heffner, J.E.; Rozenfeld, Y.; Kai, M.; Stephens, E.A.; Brown, L.K. Prevalence of diagnosed sleep apnea among patients with type 2 diabetes in primary care. Chest 2012, 141, 1414–1421. [Google Scholar] [CrossRef] [Scilit]
- American Diabetes Association. Pharmacologic Approaches to Glycemic Treatment: Standards of Medical Care in Diabetes-2018. Diabetes Care 2018, 41, S73–S85. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.W.; He, S.J.; Feng, X.; Cheng, J.; Luo, Y.T.; Tian, L.; Huang, Q. Metformin: A review of its potential indications. Drug Des. Dev. Ther. 2017, 11, 2421–2429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Le, S.; Lee, G.C. Emerging Trends in Metformin Prescribing in the United States from 2000 to 2015. Clin. Drug Investig. 2019, 39, 757–763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Foretz, M.; Guigas, B.; Viollet, B. Metformin: Update on mechanisms of action and repurposing potential. Nat. Rev. Endocrinol. 2023, 19, 460–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Susilawati, E.; Levita, J.; Susilawati, Y.; Sumiwi, S.A. Review of the Case Reports on Metformin, Sulfonylurea, and Thiazolidinedione Therapies in Type 2 Diabetes Mellitus Patients. Med. Sci. 2023, 11, 50. [Google Scholar] [CrossRef] [Scilit]
- Wiwanitkit, S.; Wiwanitkit, V. Metformin and insomnia: An interesting story. Diabetes Metab. Syndr. 2011, 5, 160. [Google Scholar] [CrossRef] [Scilit]
- Yoda, K.; Inaba, M.; Hamamoto, K.; Yoda, M.; Tsuda, A.; Mori, K.; Imanishi, Y.; Emoto, M.; Yamada, S. Association between poor glycemic control, impaired sleep quality, and increased arterial thickening in type 2 diabetic patients. PLoS ONE 2015, 10, e0122521. [Google Scholar] [CrossRef] [Scilit]
- Abdelmaksoud, A.A.; Salah, N.Y.; Ali, Z.M.; Rashed, H.R.; Abido, A.Y. Disturbed sleep quality and architecture in adolescents with type 1 diabetes mellitus: Relation to glycemic control, vascular complications and insulin sensitivity. Diabetes Res. Clin. Pract. 2021, 174, 108774. [Google Scholar] [CrossRef] [Scilit]
- Pallayova, M.; Donic, V.; Gresova, S.; Peregrim, I.; Tomori, Z. Do differences in sleep architecture exist between persons with type 2 diabetes and nondiabetic controls? J. Diabetes Sci. Technol. 2010, 4, 344–352. [Google Scholar] [CrossRef] [Scilit]
- Chen, D.M.; Taporoski, T.P.; Alexandria, S.J.; Aaby, D.A.; Beijamini, F.; Krieger, J.E.; von Schantz, M.; Pereira, A.C.; Knutson, K.L. Altered sleep architecture in diabetes and prediabetes: Findings from the Baependi Heart Study. Sleep 2024, 47, zsad229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Varma, M.; Eghbali, M.; Hung, D.; Sahai, A. Effect of insulin on sleep architecture in diabetic patients with sleep apnea. Sleep Med. 2024, 115, S252. [Google Scholar] [CrossRef] [Scilit]
- Baranski, T.; Eghbali, M.; Sahai, A.; Varma, M. Gender differences in sleep architecture of diabetic patients on metformin with sleep apnea: An analysis of polysomnography studies. Sleep Med. 2024, 115, S106. [Google Scholar] [CrossRef] [Scilit]
- Henson, J.; Covenant, A.; Hall, A.P.; Herring, L.; Rowlands, A.V.; Yates, T.; Davies, M.J. Waking Up to the Importance of Sleep in Type 2 Diabetes Management: A Narrative Review. Diabetes Care 2024, 47, 331–343. [Google Scholar] [CrossRef] [Scilit]
- Peever, J.; Fuller, P.M. The Biology of REM Sleep. Curr. Biol. CB 2017, 27, R1237–R1248. [Google Scholar] [CrossRef] [Scilit]
- Varma, M.; Eghbali, M.; Hung, D.; Sahai, A. FRI636 sleep architecture in diabetic patients with sleep apnea on metformin. J. Endocr. Soc. 2023, 7, A459–A460. [Google Scholar] [CrossRef] [Scilit]
- Lapierre, O.; Montplaisir, J.; Lamarre, M.; Bedard, M.A. The effect of gamma-hydroxybutyrate on nocturnal and diurnal sleep of normal subjects: Further considerations on REM sleep-triggering mechanisms. Sleep 1990, 13, 24–30. [Google Scholar] [CrossRef] [Scilit]
- Moser, D.; Anderer, P.; Gruber, G.; Parapatics, S.; Loretz, E.; Boeck, M.; Kloesch, G.; Heller, E.; Schmidt, A.; Danker-Hopfe, H.; et al. Sleep classification according to AASM and Rechtschaffen & Kales: Effects on sleep scoring parameters. Sleep 2009, 32, 139–149. [Google Scholar] [CrossRef] [Scilit]
- Durak, B.; Gunduz Gurkan, C.; Özol, D.; Saraç, S. The Effect of Type-2 Diabetes Mellitus on Sleep Architecture and Sleep Apnea Severity in Patients With Obstructive Sleep Apnea Syndrome. Cureus 2024, 16, e61215. [Google Scholar] [CrossRef] [Scilit]
- Shahveisi, K.; Jalali, A.; Moloudi, M.R.; Moradi, S.; Maroufi, A.; Khazaie, H. Sleep Architecture in Patients With Primary Snoring and Obstructive Sleep Apnea. Basic Clin. Neurosci. 2018, 9, 147–156. [Google Scholar] [CrossRef] [Scilit]
- Yanto, T.A.; Huang, I.; Kosasih, F.N.; Lugito, N.P.H. Nightmare and Abnormal Dreams: Rare Side Effects of Metformin? Case Rep. Endocrinol. 2018, 2018, 7809305. [Google Scholar] [CrossRef] [Scilit]
- Voloshyna, D.; Sandhu, Q.I.; Khan, S.; Bseiso, A.; Mengar, J.; Nayudu, N.; Kumar, R.; Khemani, D.; Usama, M. An Unusual Association Between Metformin and Nightmares: A Case Report. Cureus 2022, 14, e28974. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Modi, B.; Suravajjala, D.P.; Case, J.; Velumani, P. Metformin-induced nightmares: An uncommon event. Cureus 2024, 16, e64251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lendner, J.D.; Niethard, N.; Mander, B.A.; van Schalkwijk, F.J.; Schuh-Hofer, S.; Schmidt, H.; Knight, R.T.; Born, J.; Walker, M.P.; Lin, J.J.; et al. Human REM sleep recalibrates neural activity in support of memory formation. Sci. Adv. 2023, 9, eadj1895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Espiritu, J.R. Aging-related sleep changes. Clin. Geriatr. Med. 2008, 24, 1–14. [Google Scholar] [CrossRef] [Scilit]
- Casagrande, M.; Forte, G.; Favieri, F.; Corbo, I. Sleep Quality and Aging: A Systematic Review on Healthy Older People, Mild Cognitive Impairment and Alzheimer’s Disease. Int. J. Environ. Res. Public Health 2022, 19, 8457. [Google Scholar] [CrossRef] [Scilit]
- Lok, R.; Qian, J.; Chellappa, S.L. Sex differences in sleep, circadian rhythms, and metabolism: Implications for precision medicine. Sleep Med. Rev. 2024, 75, 101926. [Google Scholar] [CrossRef] [Scilit]
- Morssinkhof, M.W.L.; van der Werf, Y.D.; van den Heuvel, O.A.; van den Ende, D.A.; van der Tuuk, K.; den Heijer, M.; Broekman, B.F.P. Influence of sex hormone use on sleep architecture in a transgender cohort. Sleep 2023, 46, zsad249. [Google Scholar] [CrossRef] [Scilit]
- Naufel, M.F.; Frange, C.; Andersen, M.L.; Girão, M.J.B.C.; Tufik, S.; Beraldi Ribeiro, E.; Hachul, H. Association between obesity and sleep disorders in postmenopausal women. Menopause 2018, 25, 139–144. [Google Scholar] [CrossRef] [Scilit]
- Messineo, L.; Bakker, J.P.; Cronin, J.; Yee, J.; White, D.P. Obstructive sleep apnea and obesity: A review of epidemiology, pathophysiology and the effect of weight-loss treatments. Sleep Med. Rev. 2024, 78, 101996. [Google Scholar] [CrossRef] [Scilit]
- Sever, O.; Kezirian, E.J.; Gillett, E.; Davidson Ward, S.L.; Khoo, M.; Perez, I.A. Association between REM sleep and obstructive sleep apnea in obese and overweight adolescents. Sleep Breath. 2019, 23, 645–650. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.