Article

Effect of Glycemic Management on Severity of Functional Impairment in Elderly Individuals with Type 2 Diabetes

1
Department of Endocrinology and Metabolism, School of Medical Sciences, University of Fukui, Fukui 910-1193, Japan
2
Department of Community Health Science, School of Medical Sciences, University of Fukui, Fukui 910-1193, Japan
*
Author to whom correspondence should be addressed.
Diabetology 2026, 7(4), 74; https://doi.org/10.3390/diabetology7040074
Submission received: 6 February 2026 / Revised: 16 March 2026 / Accepted: 30 March 2026 / Published: 3 April 2026

Abstract

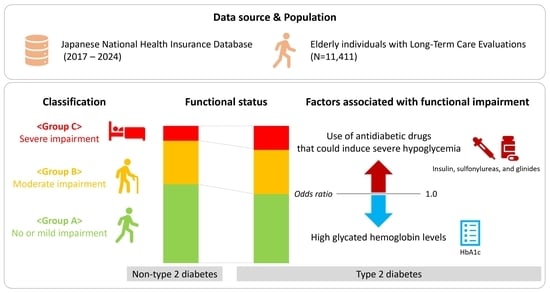
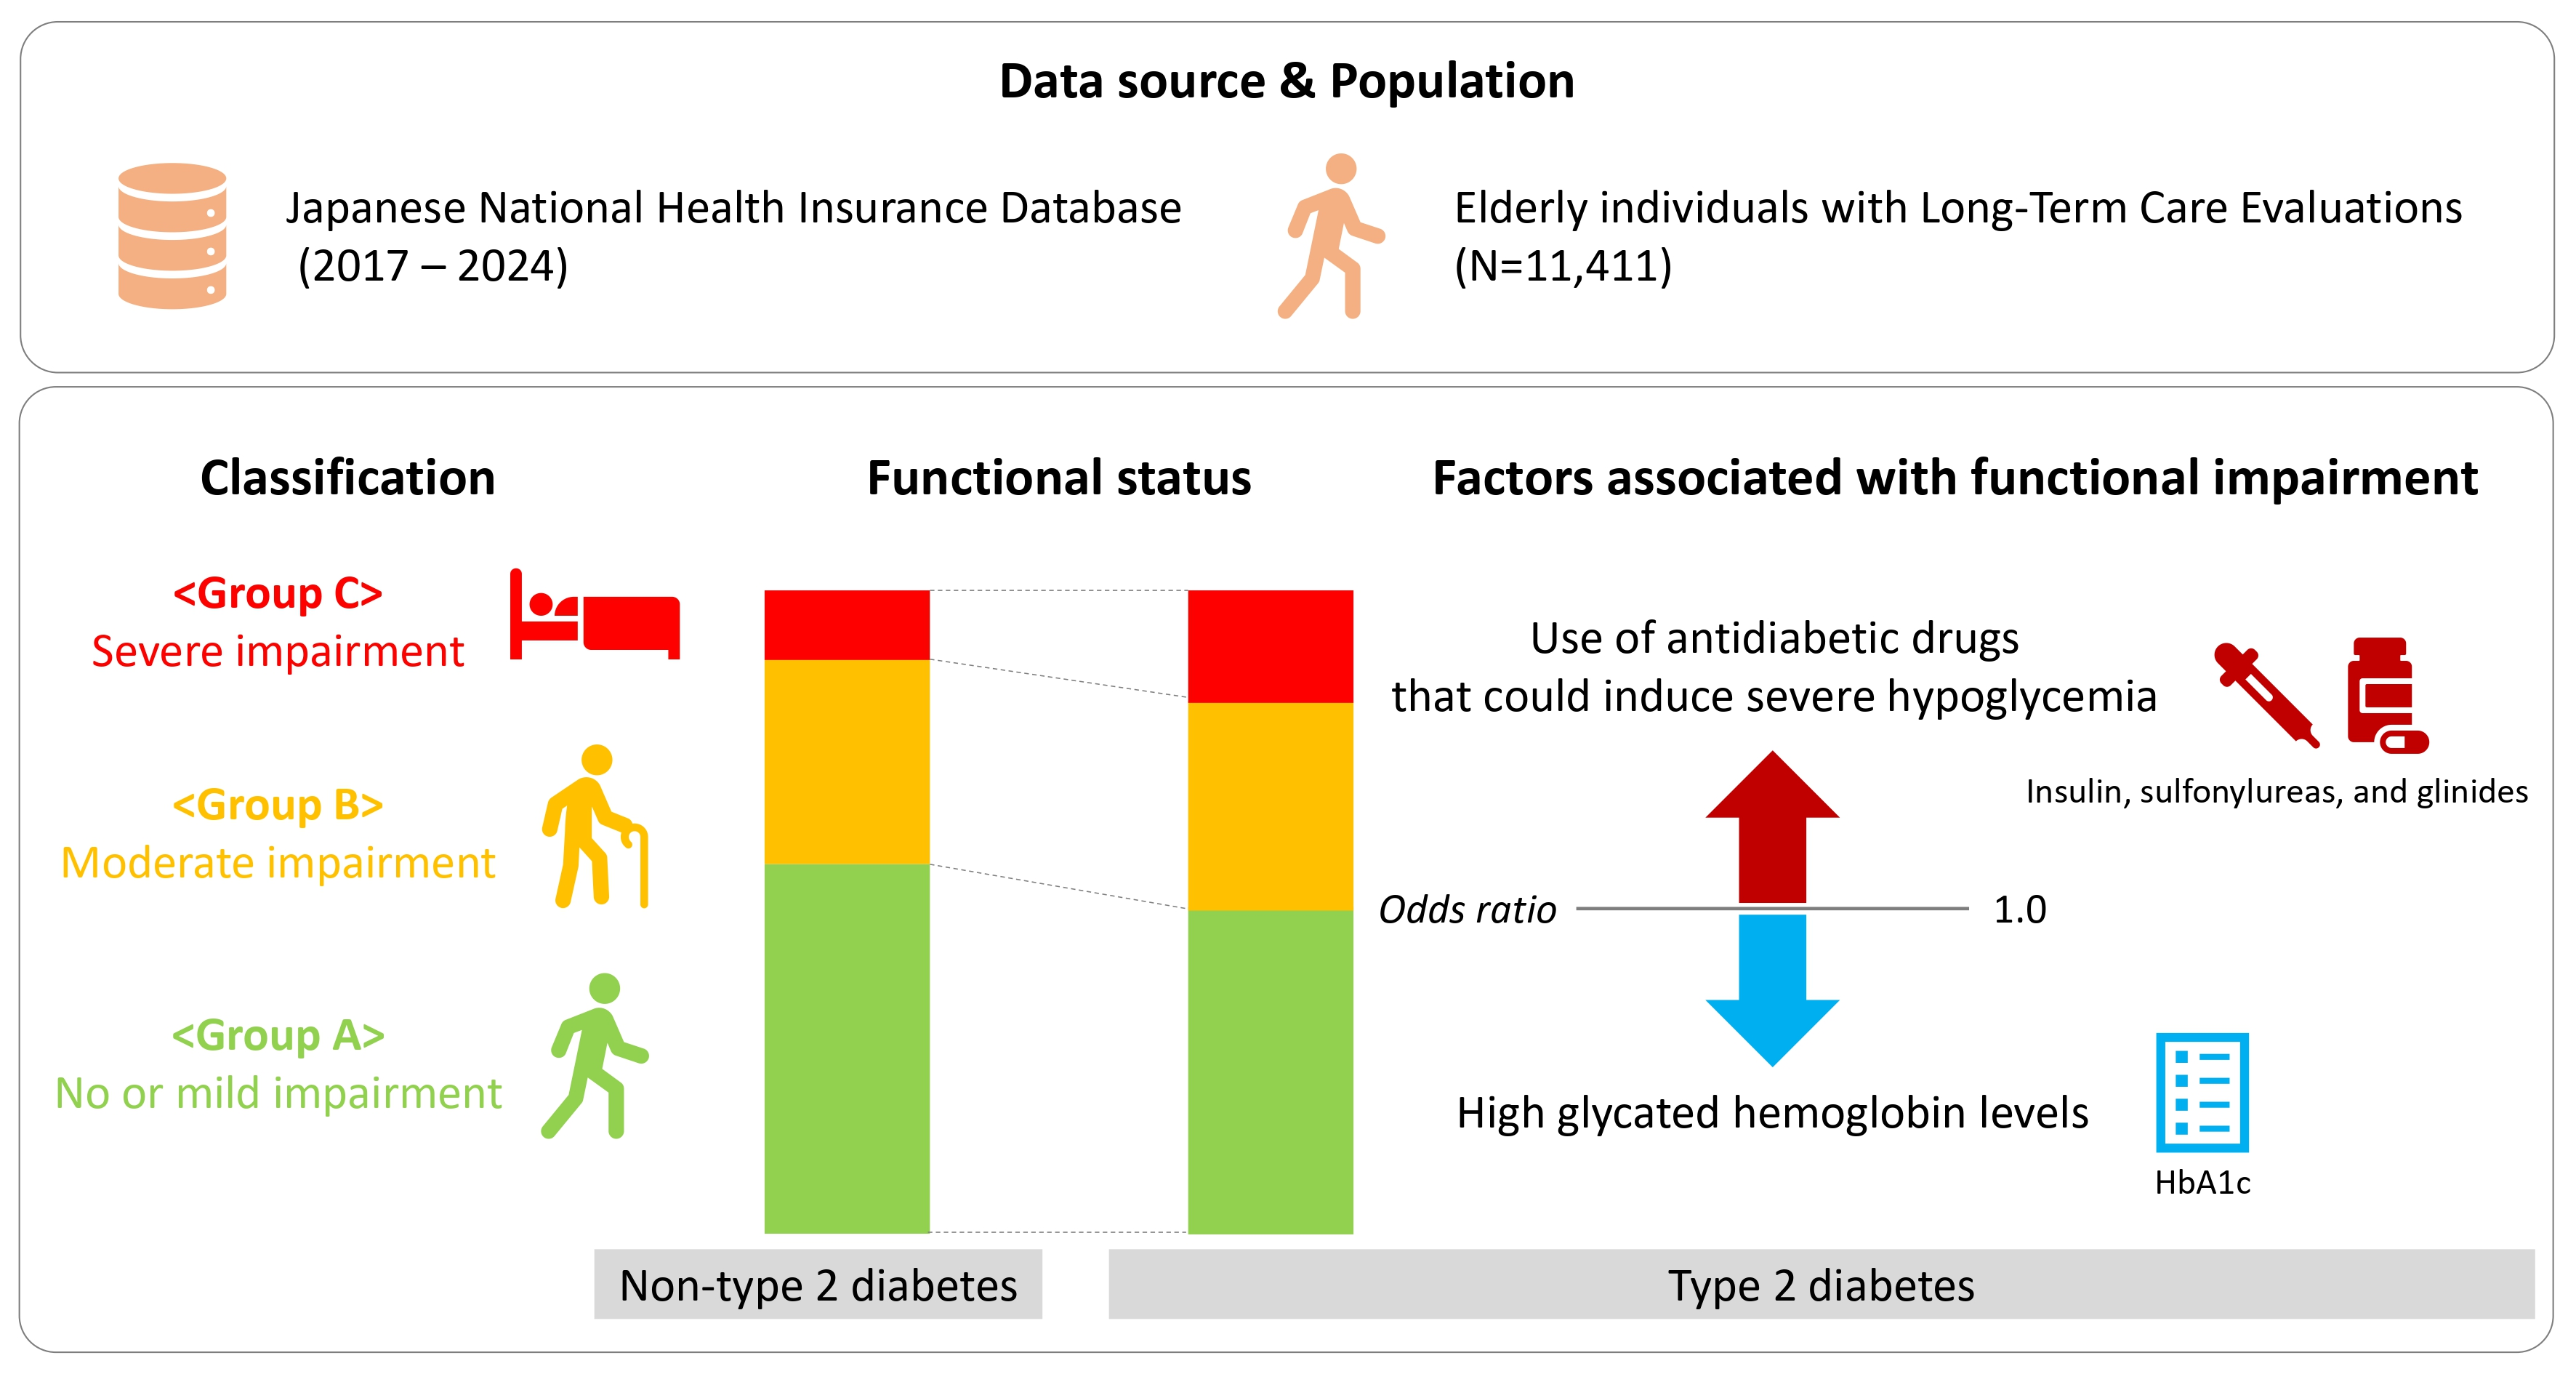
Background/Objectives: Diabetes threatens independent living among elderly individuals. However, the effects of glycemic management on the severity of functional impairment are unclear. This study aimed to elucidate the relationship between glycemic management and functional impairment severity in elderly individuals with type 2 diabetes (T2D). Methods: We used data from the Japanese National Health Insurance Database from 2017 to 2024. The database included 11,411 elderly individuals (≥65 years) with Long-Term Care Insurance evaluations. Functional status was classified into three categories based on independence—Group A (non-mild impairment), Group B (moderate impairment), and Group C (severe impairment). The factors associated with the severity of functional impairment in patients with T2D were elucidated. Results: The severity of functional impairment was significantly greater in patients with T2D than in those without T2D. In participants with T2D, low glycated hemoglobin (HbA1c) levels were associated with the severity of functional impairment (odds ratio [OR]: 0.78; p < 0.001). In contrast, the use of antidiabetic drugs that could induce severe hypoglycemia (high-risk drugs) was positively associated with the severity of functional impairment (Group A vs. B/C: OR: 1.42; p < 0.001; Group C vs. A/B: OR: 1.90; p < 0.001). The frequency of high-risk drug use increased as functional impairment increased. Conclusions: The use of high-risk drugs is associated with the severity of functional impairment in elderly individuals with T2D. Elucidating the factors associated with the severity of functional impairment in elderly individuals with T2D may contribute to maintaining their quality of life and reducing the economic burden on healthcare and long-term care systems.

Graphical Abstract

1. Introduction

The global population with diabetes was 529 million in 2021 and will exceed 1.31 billion by 2050 [1]. This increase is driven by obesity and aging. Improving glycemic management and quality of life (QOL) in elderly individuals with diabetes is an urgent global challenge.
Diabetes is a factor that threatens independent living in the elderly population. Elderly individuals with diabetes have approximately twice the risk of developing physical disabilities than those without diabetes [2]. Clinically, early intensive and strict glycemic control reduces the onset and progression of diabetic complications [3,4]. Elevated glycated hemoglobin (HbA1c) levels are associated with the onset of cardiovascular disease [5,6], and chronic hyperglycemia can impair physical function in elderly individuals with diabetes through stroke. Individuals with diabetes are more prone to developing Alzheimer’s disease and cerebrovascular dementia than those without diabetes [7], suggesting that diabetes induces cognitive dysfunction. This impairment is likely due to reduced cerebral blood flow caused by hyperglycemia and insulin resistance. Diabetes induces sarcopenia through several mechanisms, including decreased protein synthesis, increased protein degradation, ectopic fat accumulation, chronic inflammation, and mitochondrial dysfunction [8]. Advanced glycation end products (AGEs) have been reported to inhibit osteoblast function [9], indicating that hyperglycemia deteriorates bone quality. Consequently, individuals with diabetes have a higher risk of fractures and frailty than those without diabetes [10,11]. In contrast, hypoglycemia during diabetes treatment with antidiabetic drugs worsens cognitive function in elderly individuals with diabetes [7]. Hypoglycemia is an independent risk factor for frailty [12]. A meta-analysis reported that hypoglycemia not only significantly increases the risk of falls and fractures, but is also associated with an increased risk of cardiovascular events and mortality [13]. Therefore, both severe hyperglycemia and hypoglycemia appear to promote the onset and progression of cerebrovascular disease, dementia, fractures, and frailty, resulting in physical dysfunction in elderly individuals with diabetes [14,15]. Therefore, the American Diabetes Association (ADA) and the American Association of Clinical Endocrinology (AACE) guidelines recommend the relaxation of treatment goals based on comorbidities, physical function, and cognitive function in elderly individuals with diabetes [16,17]. However, it remains unclear which aspects of diabetes, such as glucose control and treatment using antidiabetic drugs, are associated with the physical and cognitive dysfunction of elderly individuals with diabetes. In this study, we elucidated the effect of glycemic management on the severity of functional impairment in elderly individuals with type 2 diabetes (T2D) using data from the Japanese health insurance database.

2. Materials and Methods

2.1. Data Extraction

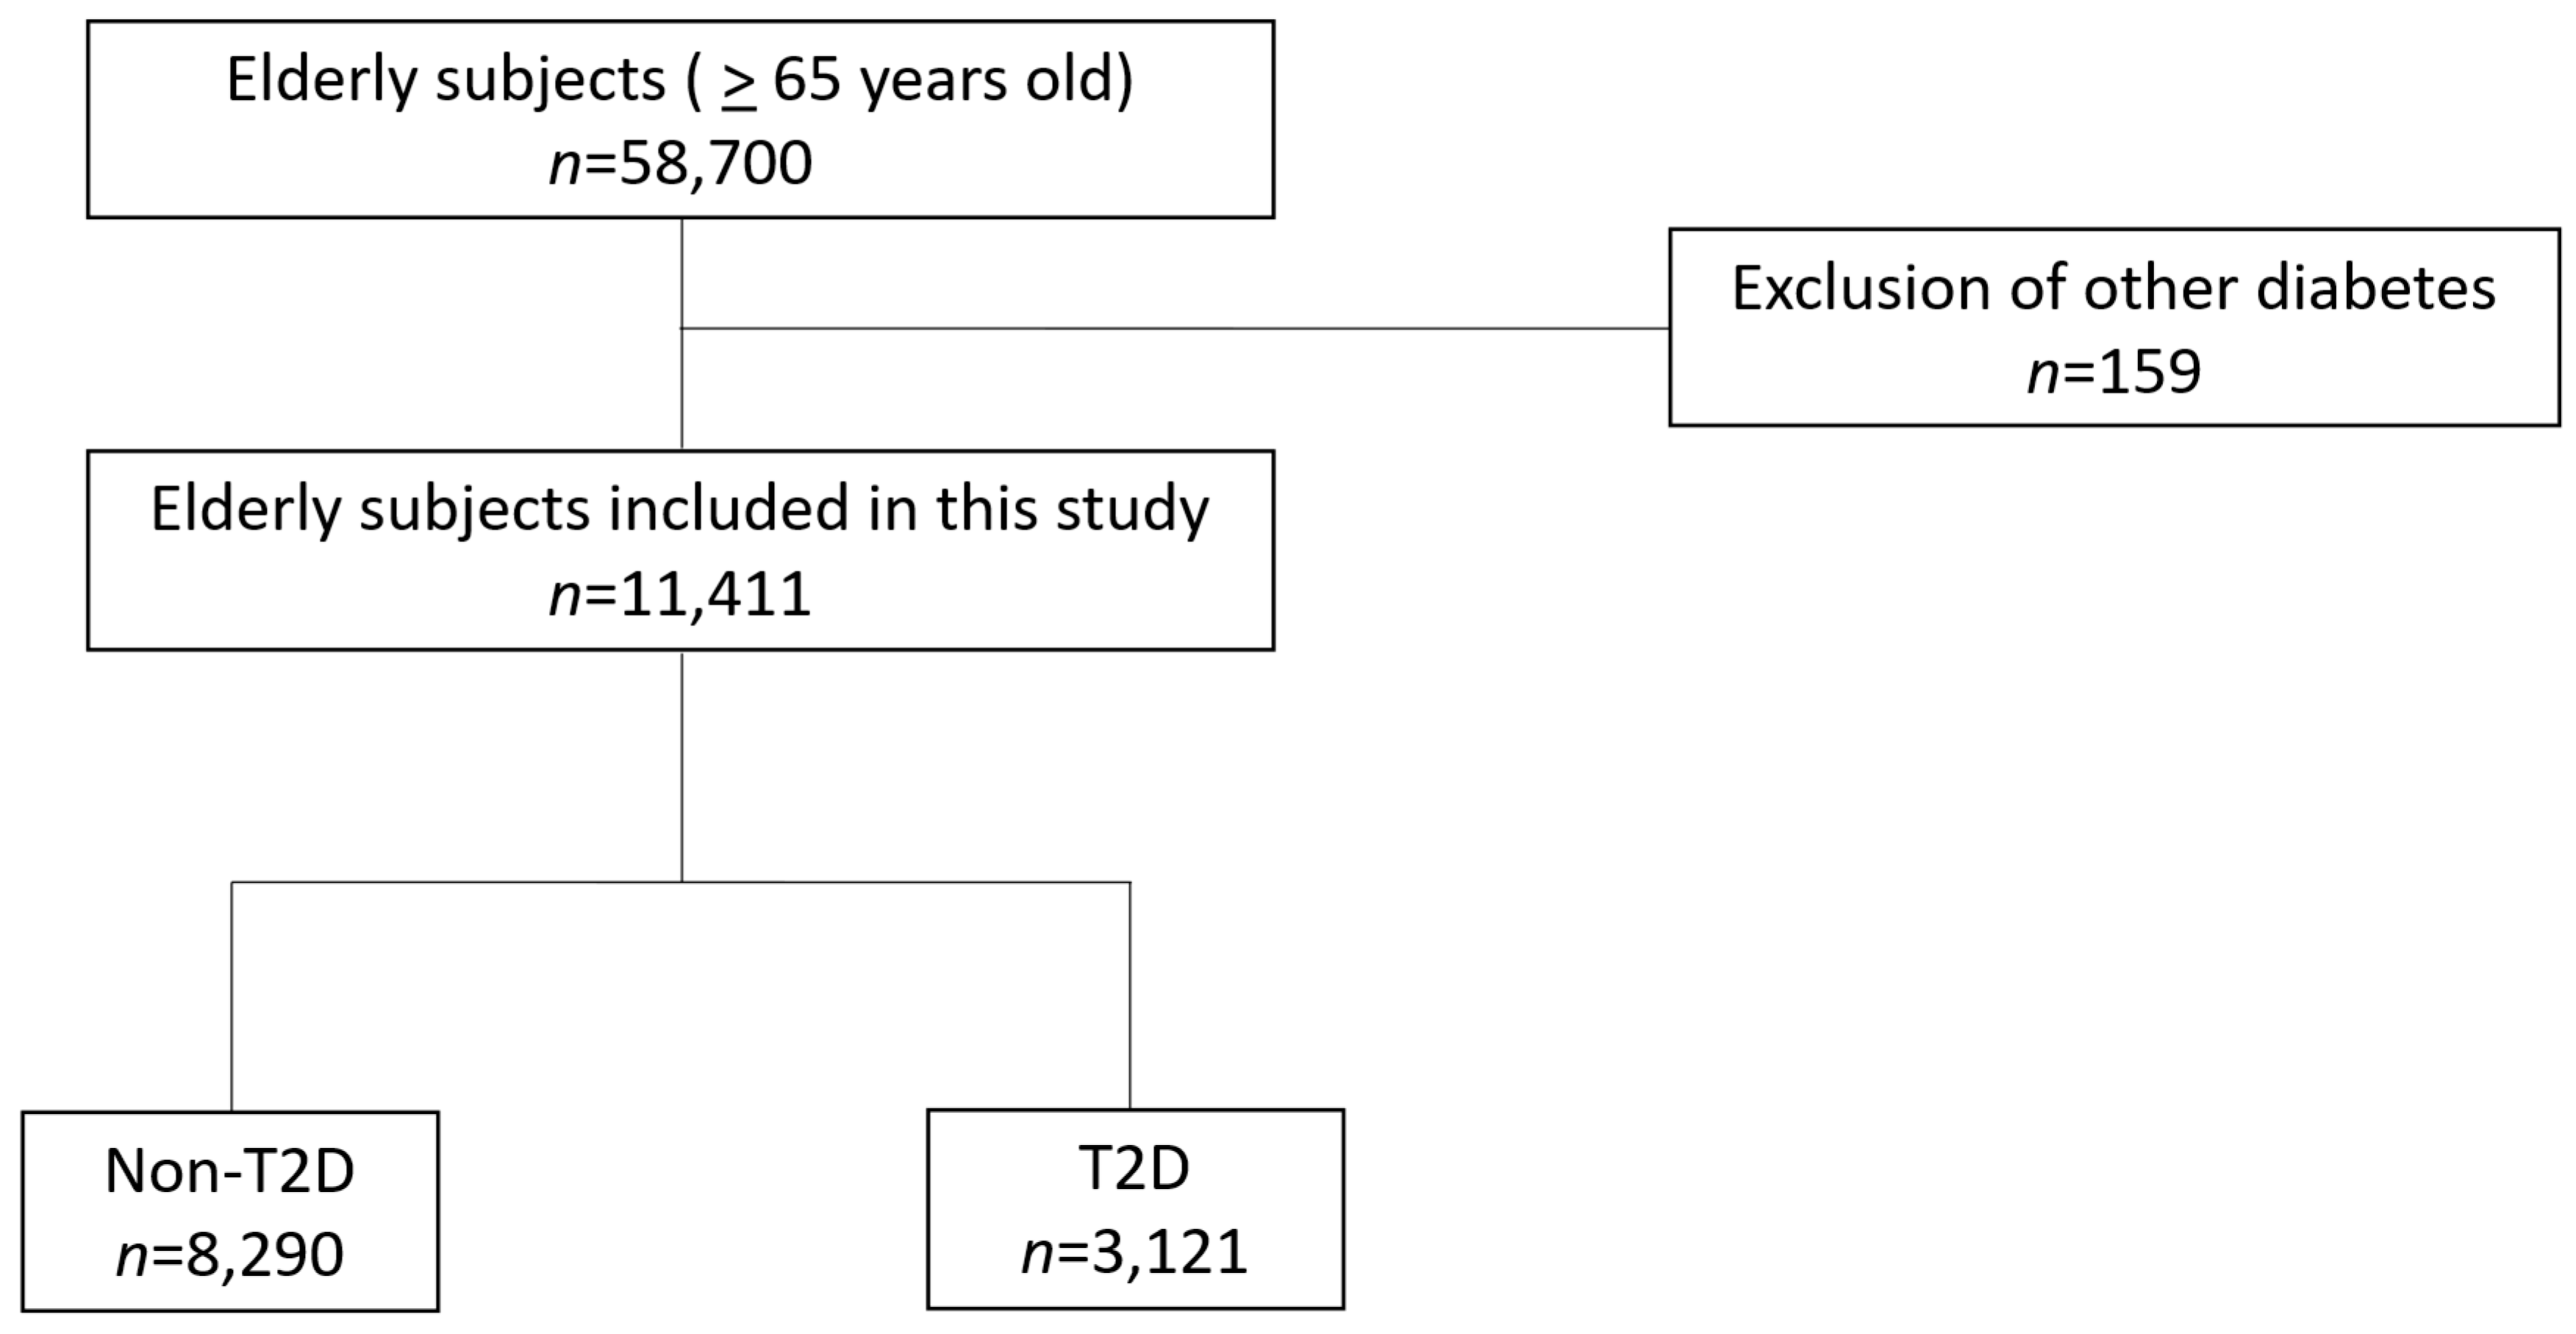
In this study, we used medical data from the Fukui Prefecture National Health Insurance Database (KDB) from 1 April 2017 to 31 March 2024. The number of elderly individuals aged 65 years or older with recorded evaluations of physical and cognitive function under public Long-Term Care Insurance (LTCI) was 58,700 (Figure A1). After excluding diseases that were clearly distinct from T2D based on diagnostic codes, such as type 1 diabetes (n = 159), 11,411 participants with available blood test data were included in the study. ADA guidelines specify HbA1c of 6.5% or higher as one of the diagnostic criteria for diabetes [18]. Individuals receiving pharmacological treatment for diabetes are also considered to have diabetes. Therefore, participants with HbA1c of 6.5% or higher and/or using antidiabetic drugs including insulin were diagnosed as having diabetes in this study. Functional Comorbidity Index (FCI) and Charlson Comorbidity Index (CCI) were calculated to evaluate comorbidities in the participants [19,20,21,22]. To prevent overestimation due to the presence of diabetes, FCI and CCI scores assigned for diabetes were excluded from the calculations (modified FCI (mFCI) and modified CCI (mCCI)). This study was approved by the Research Ethics Committee of University of Fukui (Approval number: 20240072).

2.2. Classification of Functional States

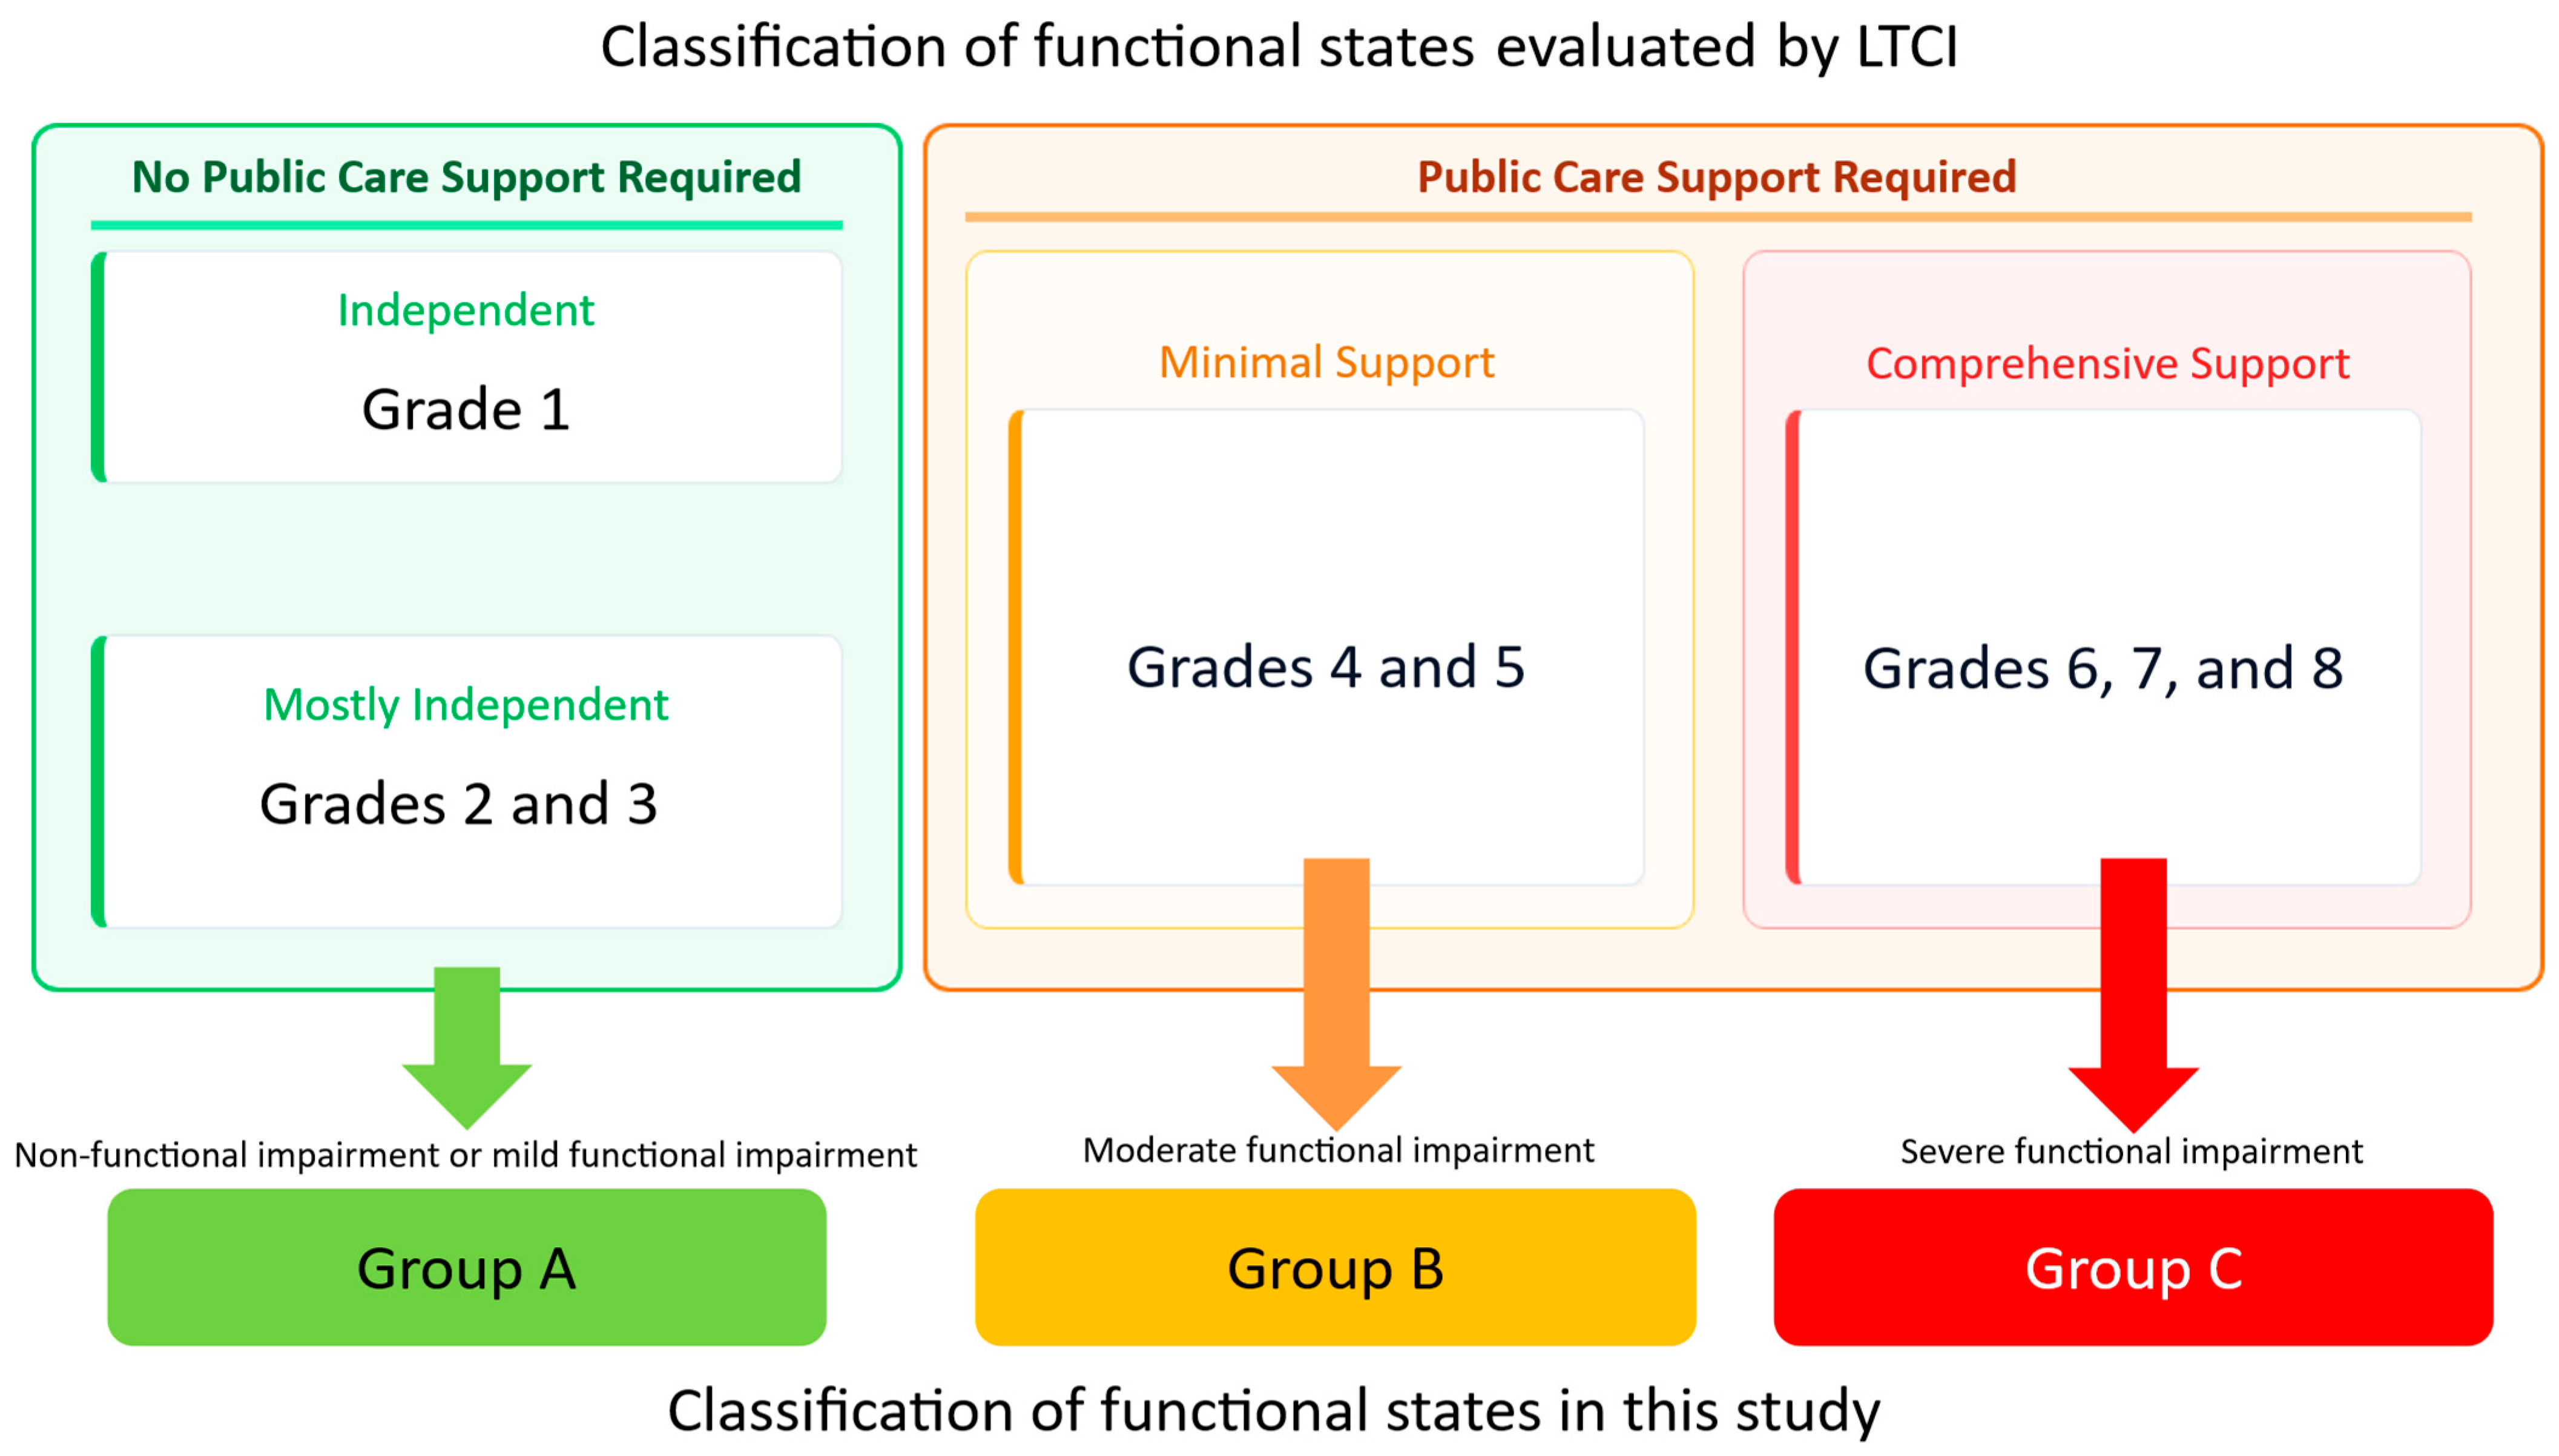
In the Japanese LTCI system, the Ministry of Health, Labour and Welfare officially defines eight grades of functional impairment, including physical and cognitive functions (Figure A2). Grade 1 is defined as independent. Grades 2 and 3 are defined as generally independent and do not require public care support. On the other hand, Grade 4 and above represent states requiring public care support. Specifically, individuals with Grades 4 and 5 require minimal support, while individuals with Grades 6, 7, and 8 require comprehensive support. In this study, we classified eight grades into three categories (groups A, B, and C) based on the degree of public support. Group A was defined as non-functional impairment or mild functional impairment (Grades 1, 2, and 3), Group B as moderate functional impairment (Grades 4 and 5), and Group C as severe functional impairment (Grades 6, 7, and 8). Group A was defined as non-functional impairment or mild functional impairment (grades 1, 2, and 3), Group B as moderate functional impairment (grades 4 and 5), and Group C as severe functional impairment (grades 6, 7, and 8).

2.3. Statistical Analysis

Categorical variables are presented as numbers or percentages while continuous variables are presented as means ± standard deviations (SDs). The chi-squared test was used to compare categorical variables. Student’s t-test was used to compare continuous variables. Holm’s method was applied to correct p values for multiple comparisons of baseline characteristics. Logistic regression analyses were performed separately for participants with and without T2D. The odds ratios (ORs) for moderate or greater functional impairment (groups B and C) were calculated relative to non-mild functional impairment (Group A). Furthermore, the OR for severe functional impairment (Group C) was calculated using moderate or mild functional impairment (Groups A or B) as the baseline. Age, sex, body mass index (BMI) [kg/m2], systolic blood pressure (BP) [mmHg], HbA1c [%], low-density lipoprotein cholesterol (LDL-C) [mg/dL], and estimated glomerular filtration rate (eGFR) [mL/min/1.7 m2] were used as explanatory variables. As many previous studies have shown that hypoglycemia is strongly associated with functional impairment [4,7,12,13,14,15], In ADA guidelines, sulfonylureas, meglitinides (glinides), and insulin are categorized as high-risk drugs that could induce severe hypoglycemia [23]. In T2D, the use of antidiabetic drugs was added to the explanatory variables for the analysis of ORs. All analyses were performed using the Statistical Package for SPSS (version 31.0; IBM Inc., Armonk, NY, USA).

3. Results

3.1. Characteristics of the Elderly Participants With or Without T2D

The number of participants with and without T2D was 3121 and 8290, respectively (Table 1). Participants with T2D were younger (p < 0.001), mainly male (p < 0.001), and had greater body weights and BMIs (p < 0.001) than those without T2D. There was no difference in systolic BP between the two groups (p = 0.684), although diastolic BP was significantly lower in T2D (p < 0.001). The levels of HbA1c, blood glucose, aspartate aminotransferase (AST), alanine aminotransferase (ALT), gamma-glutamyl transpeptidase (γGTP), and creatinine (Cre) were significantly higher in the participants with T2D than in those without T2D (p < 0.001); however, eGFR did not differ between the two groups (p = 0.684). These results were potentially related to complications and comorbidities such as metabolic dysfunction-associated steatotic liver disease (MASLD) and diabetic kidney disease (DKD) in participants with T2D. However, we could not identify these diseases from the database. Triglyceride levels were higher (p < 0.001), and high-density lipoprotein cholesterol (HDL-C) and LDL-C levels were lower (p < 0.001) in participants with T2D than in those without T2D. Red Blood cell (RBC) and hemoglobin (Hb) levels were significantly lower in participants with T2D than in those without T2D. The scores of mFCI and mCCI were significantly higher in participants with T2D than in those without T2D (p < 0.001), indicating that participants with T2D had a greater number of comorbidities compared to those without T2D. A total of 2954 participants with T2D (94.6%) received treatment with antidiabetic drugs. The main antidiabetic drugs used were dipeptidyl peptidase-4 (DPP-4) inhibitors (63.6%), insulin (53.8%), sodium glucose co-transporter 2 (SGLT2) inhibitors (31.9%), biguanides (31.5%), and glinides (11.9%). The usage rate of high-risk drugs, such as insulin, sulfonylureas, and glinides, was 62.3%.

3.2. Functional Status in Elderly Participants With or Without T2D

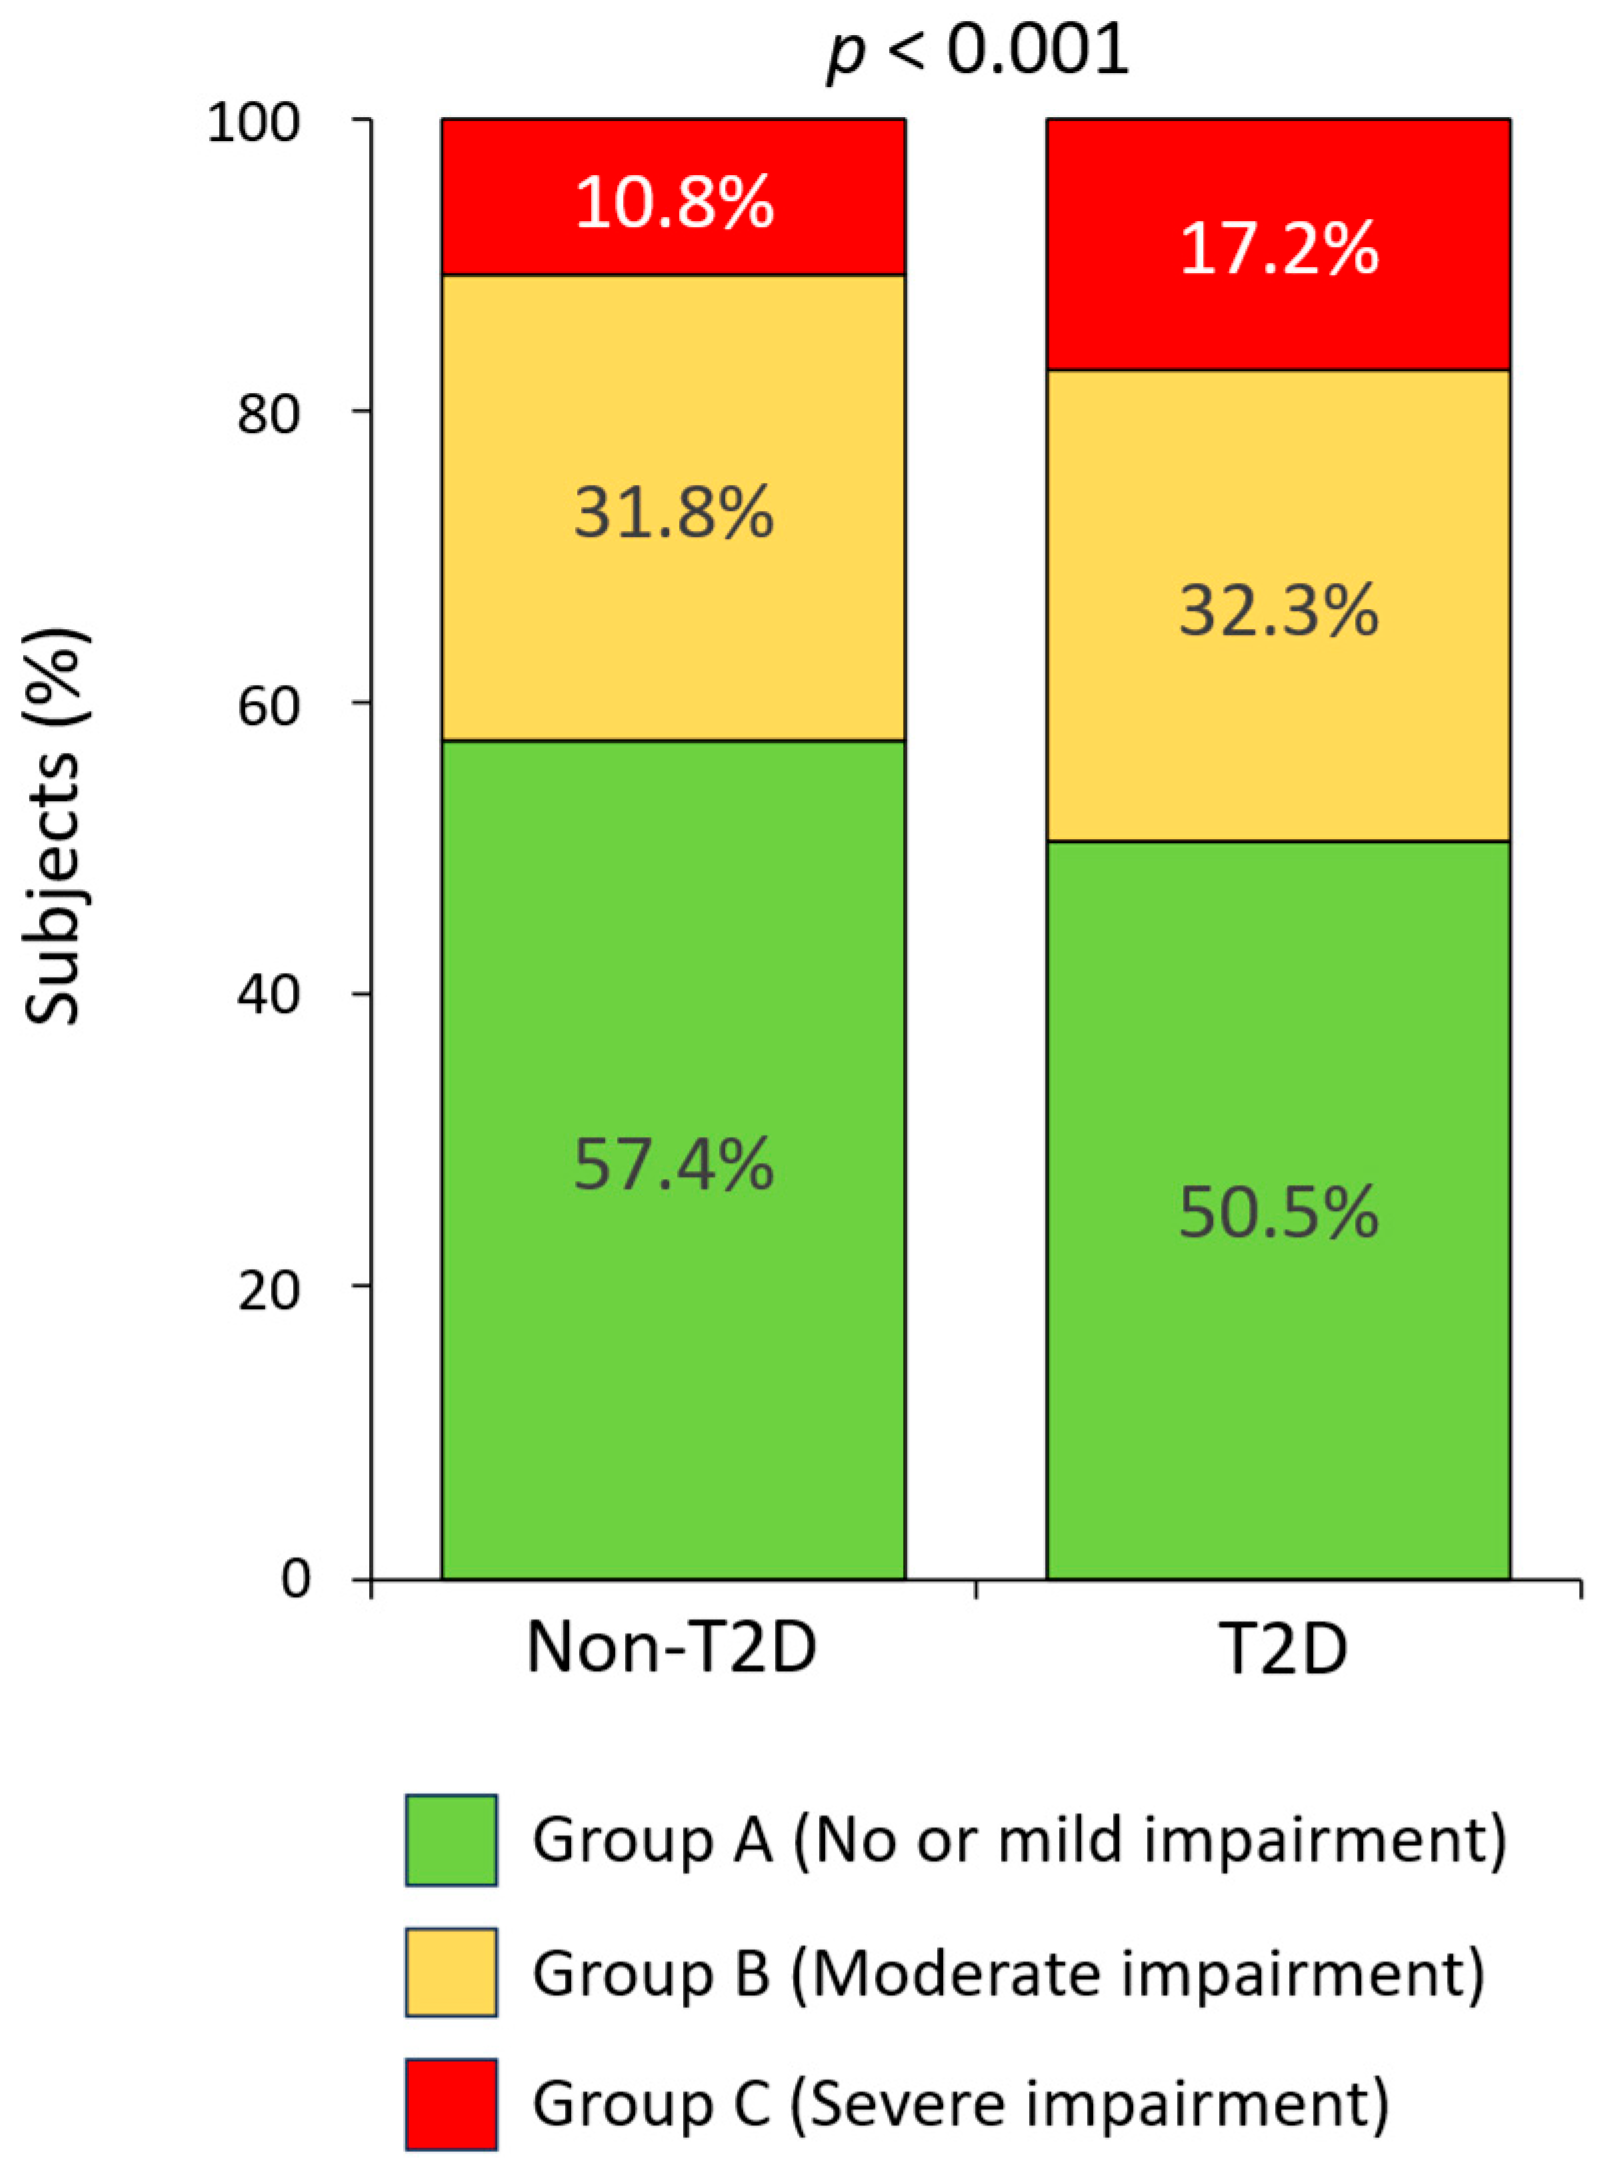
The functional status of participants without T2D in Group A, B, and C was 57.4%, 31.8%, and 10.8%, respectively (Figure 1). Among the participants with T2D, 50.5%, 32.3%, and 17.2% were in Groups A, B, and C, respectively. The severity of functional impairment was significantly greater in participants with T2D than in those without T2D (p < 0.001).

3.3. Factors Associated with Functional Impairment in Elderly Participants Without T2D

Functional impairment severity was greater in participants with T2D than in those without T2D (Figure 1). Factors associated with functional status in participants without T2D were evaluated (Table 2). Advanced age (OR: 1.02; 95% confidence interval [CI]: 1.01–1.02; p < 0.001) and high LDL-C levels (OR: 1.02; 95% CI: 1.01–1.04; p < 0.01) were positively associated with progression from non/mild functional impairment (Group A) to moderate or greater functional impairment (Group B or C). In contrast, female sex (OR: 0.49; 95% CI: 0.45–0.54; p < 0.001), high HbA1c levels (OR: 0.84; 95% CI: 0.73–0.97; p < 0.05), and high BMI (OR: 0.95; 95% CI: 0.94–0.96; p < 0.001) were negatively associated with progression to moderate or greater functional impairment (Group B or C).
High systolic BP (OR: 1.06; 95% CI: 1.02–1.09; p < 0.01) was positively associated with progression from moderate or mild functional impairment (Group A or B) to severe functional impairment (Group C). Conversely, female sex (OR: 0.41; 95% CI: 0.35–0.47; p < 0.001) and high HbA1c levels (OR: 0.79; 95% CI: 0.64–0.99; p < 0.05) were negatively associated with progression to severe functional impairment (Group C).

3.4. Factors Associated with Functional Impairment in Elderly Participants with T2D

Hypoglycemia has been implicated in cardiovascular events, fractures, and frailty [13]. Therefore, the use of high-risk drugs was evaluated as a factor affecting the functional status of patients with T2D (Table 3). Usage of high-risk drugs (OR: 1.42; 95% CI: 1.22–1.65; p < 0.001) and high systolic BP (OR: 1.05; 95% CI: 1.01–1.10; p < 0.001) were positively associated with progression from non/mild functional impairment (Group A) to moderate or severe functional impairment (Group B or Group C). In contrast, female sex (OR: 0.58; 95% CI: 0.50–0.67; p < 0.001) and high BMI (OR: 0.98; 95% CI: 0.96–1.00; p < 0.05) were negatively associated with progression to moderate or severe functional impairment (Group B or Group C).
Usage of high-risk drugs (OR: 1.90; 95% CI: 1.53–2.36; p < 0.001) and high systolic BP (OR: 1.06; 95% CI: 1.01–1.12; p < 0.05) were positively associated with progression from moderate or mild functional impairment (Group A or B) to severe functional impairment (Group C). Conversely, female sex (OR: 0.54; 95% CI: 0.44–0.66; p < 0.001), high HbA1c levels (OR: 0.78; 95% CI: 0.71–0.87; p < 0.001), and advanced age (OR: 0.98; 95% CI: 0.96–1.00; p < 0.05) were negatively associated with progression to severe functional impairment (Group C).

3.5. Frequency of High-Risk Drug Usage Among Elderly Participants with T2D

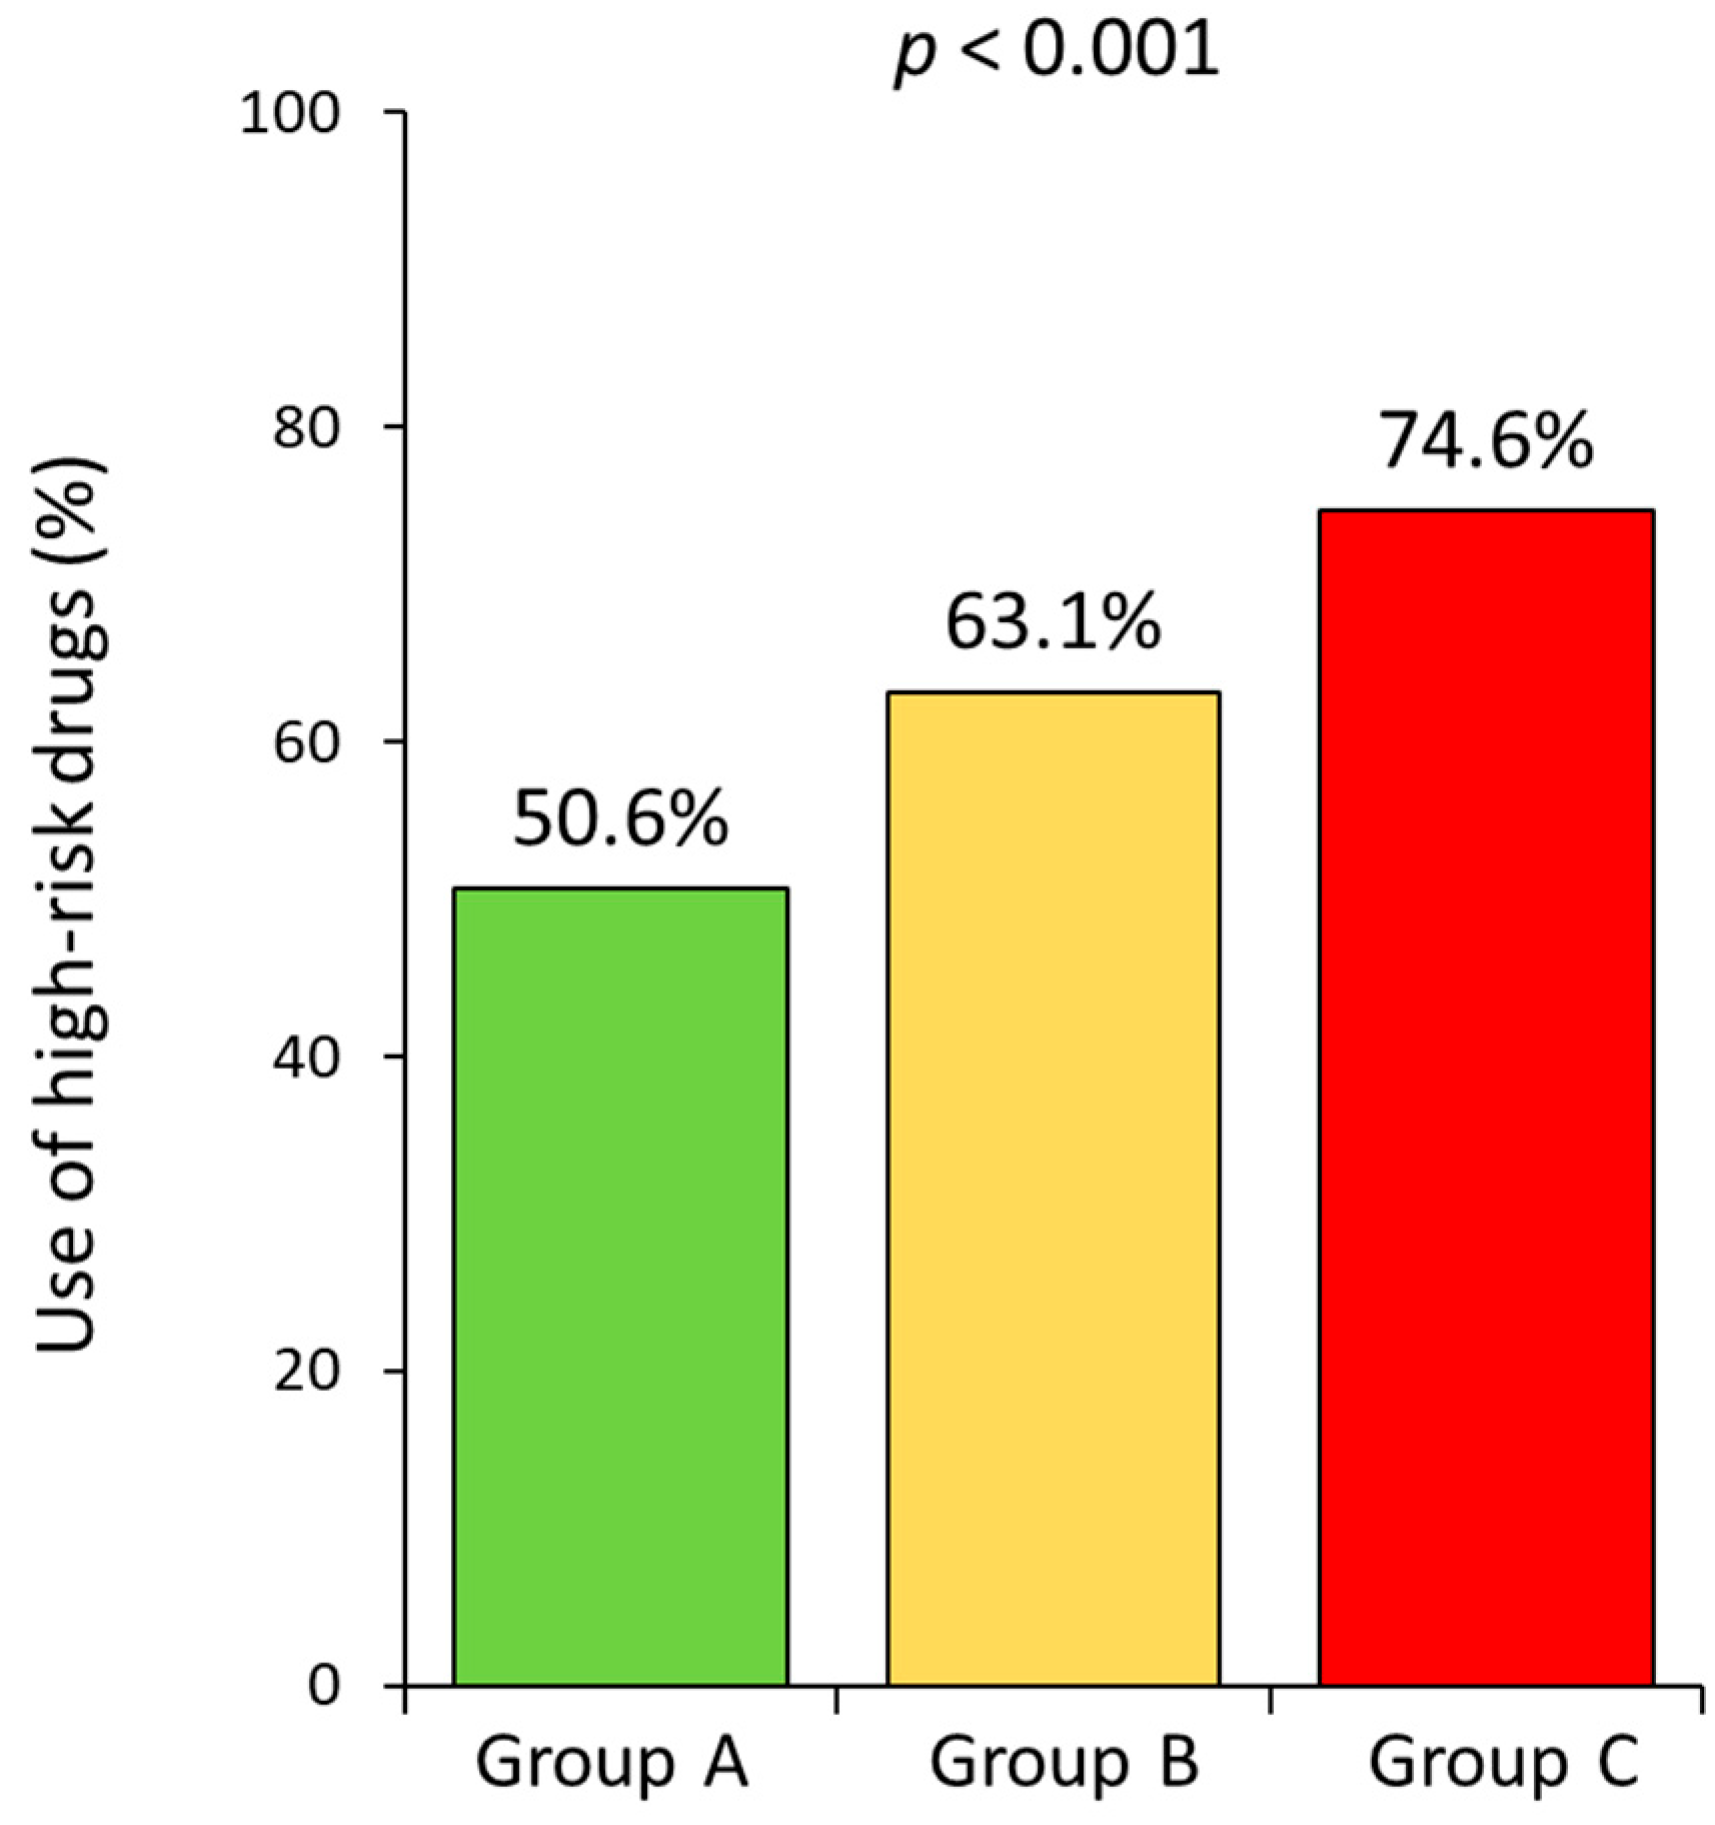
The use of high-risk drugs that can induce severe hypoglycemia was associated with the severity of functional impairment in elderly participants with T2D (Table 3). Therefore, we evaluated the frequency of high-risk drug use among the three functional status groups (Figure 2). The proportions of high-risk drug use in groups A, B, and C were 50.6%, 63.1%, and 74.6%, respectively (p < 0.001). This indicates that the proportion of high-risk drug use increased as functional impairment increased.

4. Discussion

In this study, we used a database from a super-aged society in Japan and elucidated the relationship between glycemic management and the severity of functional impairment in elderly individuals with T2D. A previous study using a Japanese database identified the factors associated with the onset of functional impairment [14]. They found that diabetes as well as low BMI (<18.5 kg/m2) were risk factors for the first onset of functional impairment (hazard ratio [HR]:1.63; 95% CI: 1.02–1.63, p = 0.043). Similarly, our results demonstrated that participants with T2D had a higher proportion of moderate or severe functional impairment than those without T2D (Figure 1). Moreover, we elucidated factors associated with the severity of functional impairment. Sex, HbA1c levels, and the use of high-risk drugs were found to be associated with the severity of functional impairment (Table 3).
Low HbA1c levels were associated with the severity of functional impairment in elderly participants with T2D; however, this was not the case for high HbA1c levels. In the present study, the average HbA1c level among participants with T2D was 6.6% (Table 1). Previous studies reported that HbA1c levels of 7.0–8.0% or higher were associated with an increased risk of cerebrovascular events [5,24]. In addition, a previous meta-analysis reported a U-curve for HbA1c levels in relation to all-cause mortality and frailty in both individuals with and without diabetes [25]. We introduced a squared term of HbA1c levels into the multivariable logistic regression model with severe functional impairment as the dependent variable. However, there was no statistical significance (p = 0.412). This result indicated that the relationship between HbA1c levels and the progression to severe functional impairment was not U-curve in this study population. In this study, the average HbA1c levels among participants with T2D were 6.6% (Table 1) and the participants with severe functional impairment due to poor glycemic control (high HbA1c levels) might be rarely included. Therefore, HbA1c levels may have a small influence on the onset and progression of diabetic complications and comorbidities in populations with low HbA1c levels, such as those included in this study. On the other hand, the use of high-risk drugs indicated severity of functional impairment (Group A vs. Group B or C: OR: 1.42; 95% CI: 1.22–1.65; p < 0.001, Group A or B vs. group C: OR: 1.90; 95% CI: 1.53–2.36; p < 0.001) (Table 3). We found that the frequency of high-risk drug use increased as functional impairment progressed (Figure 2). A previous study reported that 93% of hypoglycemic episodes recorded by continuous glucose monitoring were asymptomatic in elderly patients treated with insulin, even when HbA1c levels exceeded 8.0% [26]. It is well known that severe hypoglycemia increases the risks of fall, fracture, frailty, and various diabetic complications in individuals with diabetes [12,13,27,28,29,30,31]. Therefore, in this study population with low HbA1c levels, the use of high-risk drugs may be strongly associated with the severity of functional impairment.
Age is negatively associated with severe impairment (Table 3). In this study, the database consisted of results from annual health screenings was used. The participants were restricted to individuals capable of undergoing these screenings. Therefore, individuals with severe functional impairment residing in hospitals or nursing facilities might not have been included. This potential exclusion could have caused the negative correlation between age and the progression to severe functional impairment. Additionally, this study population was elderly participants with a mean age of 81 years. Survivorship bias might have also existed.
This study had several limitations. First, as it was a cross-sectional study, reverse causality cannot be ruled out. Future prospective studies on functional impairment in elderly individuals with T2D are required to clarify the causal relationship between functional impairment and use of the high-risk drugs. Second, our study may have had selection bias. As the participants were selected from the database of the Japanese insurance system, this study may have focused on participants who were relatively physically capable of undergoing health examinations. Finally, the duration of diabetes was not taken into account. A longer duration of diabetes potentially increases the risks of complications and functional decline. However, the database used in this study lacked information on the duration of diabetes. Therefore, we could not analyze our data after adjustment of the duration. The impairment of physical and cognitive functions associated with diabetes not only decreases QOL but also increases the economic burden on healthcare and long-term care systems. Cognitive impairment has been reported to significantly increase healthcare expenditure in elderly individuals with diabetes [32]. Another study demonstrated that physical frailty is an independent predictor of increased future healthcare costs for elderly individuals without diabetes [33]. Similarly, for individuals with diabetes, preventing complications and maintaining physical function are crucial not only for personal well-being but also for healthcare economics.

5. Conclusions

We found that the use of high-risk drugs is associated with the severity of functional impairment in elderly individuals with T2D; although this study is a cross-sectional study. Identifying factors associated with the severity of functional impairment in elderly individuals with diabetes through this study may contribute not only to maintaining their QOL, but also to reducing the economic burden on healthcare and long-term care systems.

Author Contributions

Conceptualization, K.U.; Methodology, K.U., R.S., M.I. and N.H.; Validation, N.H.; Formal Analysis, K.U., R.S., A.M., T.S., M.K., S.K., S.S. and Y.Z.; Investigation, R.S.; Writing—Original Draft Preparation, K.U. and N.H.; Writing—Review & Editing, K.U. and N.H. All authors have read and agreed to the published version of the manuscript.

Funding

This study was supported by grants from the Japan Society for the Promotion of Science (JSPS) and the Japan Association for Diabetes Education and Care.

Institutional Review Board Statement

This study was approved by the Ethics Committee of the Faculty of Medicine of Fukui University (approval number: 20240072, approval date: 1 August 2024).

Informed Consent Statement

Patient consent was waived due to the retrospective nature of the study. An opt-out approach was adopted to provide informed consent in accordance with the Japanese Ethical Guidelines for Medical and Health Research Involving Human Subjects. Information regarding the study was disclosed on the website of the Medical Research Support Center. The university received pseudonymized data from Fukui Prefecture. Identification of specific individuals was not possible as the university did not possess any correspondence tables. Consequently, data removal could not be performed even upon request for withdrawal of consent.

Data Availability Statement

The data presented in this study were not publicly available due to privacy and ethical restrictions. The datasets were provided by Fukui Prefecture and were analyzed following the official permission for use. Access was restricted to authorized researchers, and the data were not available for third-party distribution.

Conflicts of Interest

N. H. received scholarship grants from Tanabe Pharma Co., Ltd.; Terumo Co., Ltd.; Sanwa Kagaku Kenkyusho Co., Ltd.; and Abbott Japan LLC. The other authors declare no conflicts of interest.

Appendix A

Appendix A.1

Figure A1. Flowchart of data extraction from the Fukui Prefecture National Health Insurance Database (KDB). T2D, type 2 diabetes.
Diabetology 07 00074 g0a1

Appendix A.2

Figure A2. Classification of functional states. LTCI; Long-Term Care Insurance.
Diabetology 07 00074 g0a2

References

  1. Ong, K.L.; Stafford, L.K.; McLaughlin, S.A.; Boyko, E.J.; Vollset, S.E.; Smith, A.E.; Dalton, B.E.; Duprey, J.; Cruz, J.A.; Hagins, H.; et al. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050: A systematic analysis for the Global Burden of Disease Study 2021. Lancet 2023, 402, 203–234. [Google Scholar] [CrossRef] [Scilit]
  2. Wong, E.; Backholer, K.; Gearon, E.; Harding, J.; Freak-Poli, R.; Stevenson, C.; Peeters, A. Diabetes and risk of physical disability in adults: A systematic review and meta-analysis. Lancet Diabetes Endocrinol. 2013, 1, 106–114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet 1998, 352, 837–853. [Google Scholar] [CrossRef] [Scilit]
  4. Adler, A.I.; Coleman, R.L.; Leal, J.; Whiteley, W.N.; Clarke, P.; Holman, R.R. Post-trial monitoring of a randomised controlled trial of intensive glycaemic control in type 2 diabetes extended from 10 years to 24 years (UKPDS 91). Lancet 2024, 404, 145–155. [Google Scholar] [CrossRef] [Scilit]
  5. Shen, Y.; Shi, L.; Nauman, E.; Katzmarzyk, P.; Price-Haywood, E.; Bazzano, A.; Nigam, S.; Hu, G. Association between hemoglobin A1c and stroke risk in patients with type 2 diabetes. J. Stroke 2020, 22, 87–98. [Google Scholar] [CrossRef] [Scilit]
  6. Iwase, M.; Komorita, Y.; Ohkuma, T.; Fujii, H.; Ide, H.; Yoshinari, M.; Oku, Y.; Higashi, T.; Nakamura, U.; Kitazono, T. Incidence of stroke and its association with glycemic control and lifestyle in Japanese patients with type 2 diabetes mellitus: The Fukuoka diabetes registry. Diabetes Res. Clin. Pract. 2021, 172, 108518. [Google Scholar] [CrossRef] [Scilit]
  7. Cao, F.; Yang, F.; Li, J.; Guo, W.; Zhang, C.; Gao, F.; Sun, X.; Zhou, Y.; Zhang, W. The relationship between diabetes and the dementia risk: A meta-analysis. Diabetol. Metab. Syndr. 2024, 16, 101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Cleasby, M.E.; Jamieson, P.M.; Atherton, P.J. Insulin resistance and sarcopenia: Mechanistic links between common co-morbidities. J. Endocrinol. 2016, 229, R67–R81. [Google Scholar] [CrossRef] [Scilit]
  9. Hein, G.; Weiss, C.; Lehmann, G.; Niwa, T.; Stein, G.; Franke, S. Advanced glycation end product modification of bone proteins and bone remodelling: Hypothesis and preliminary immunohistochemical findings. Ann. Rheum. Dis. 2006, 65, 101–104. [Google Scholar] [CrossRef] [Scilit]
  10. Li, G.; Prior, J.C.; Leslie, W.D.; Thabane, L.; Papaioannou, A.; Josse, R.G.; Kaiser, S.M.; Kovacs, C.S.; Anastassiades, T.; Towheed, T.; et al. Frailty and risk of fractures in patients with type 2 diabetes. Diabetes Care 2019, 42, 507–513. [Google Scholar] [CrossRef] [Scilit]
  11. Luiz, M.M.; Máximo, R.O.; Oliveira, D.C.; Ramírez, P.C.; Souza, A.F.; Delinocente, M.L.B.; Cochar-Soares, N.; Steptoe, A.; Oliveira, C.; Alexandre, T.S. Could poor glycaemic control be a predictor of walking speed decline in older adults? Evidence from the English Longitudinal Study of Ageing. Diabetes Obes. Metab. 2024, 26, 2349–2358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Chao, C.T.; Wang, J.; Huang, J.W.; Chan, D.C.; Chien, K.L. Hypoglycemic episodes are associated with an increased risk of incident frailty among new onset diabetic patients. J. Diabetes Complicat. 2020, 34, 107492. [Google Scholar] [CrossRef] [Scilit]
  13. Mattishent, K.; Loke, Y.K. Meta-Analysis: Association between hypoglycemia and serious adverse events in older patients treated with glucose-lowering agents. Front. Endocrinol. 2021, 12, 571568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Fujihara, K.; Matsubayashi, Y.; Harada Yamada, M.; Kitazawa, M.; Yamamoto, M.; Kaneko, M.; Kodama, S.; Yahiro, T.; Tsutsui, A.; Kato, K.; et al. Combination of diabetes mellitus and lack of habitual physical activity is a risk factor for functional disability in Japanese. BMJ Open Diabetes Res. Care 2020, 8, e000901. [Google Scholar] [CrossRef] [Scilit]
  15. Melekin, A.; Sengupta, M.; Caffrey, C. Residential Care Community Resident Characteristics: United States, 2022; NCHS Data Brief; CDC/NCHS: Hyattsville, MD, USA, 2024; Volume 506, pp. 1–8. [Google Scholar] [CrossRef] [Scilit]
  16. Bajaj, M.; McCoy, R.G.; Balapattabi, K.; Bannuru, R.R.; Bellini, N.J.; Bennett, A.K.; Beverly, E.A.; Early, K.B.; ChallaSivaKanaka, S.; Echouffo-Tcheugui, J.B.; et al. 13. Older Adults: Standards of Care in Diabetes—2026. Diabetes Care 2026, 49, S277–S296. [Google Scholar] [CrossRef] [Scilit]
  17. Blonde, L.; Umpierrez, G.E.; Reddy, S.S.; McGill, J.B.; Berga, S.L.; Bush, M.; Chandrasekaran, S.; DeFronzo, R.A.; Einhorn, D.; Galindo, R.J.; et al. American Association of Clinical Endocrinology Clinical Practice Guideline: Developing a Diabetes Mellitus Comprehensive Care Plan—2022 Update. Endocr. Pract. 2022, 28, 923–1049. [Google Scholar] [CrossRef] [Scilit]
  18. Bajaj, M.; McCoy, R.G.; Balapattabi, K.; Bannuru, R.R.; Bellini, N.J.; Bennett, A.K.; Beverly, E.A.; Early, K.B.; ChallaSivaKanaka, S.; Echouffo-Tcheugui, J.B.; et al. 2. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes—2026. Diabetes Care 2026, 49, S27–S49. [Google Scholar] [CrossRef] [Scilit]
  19. Charlson, M.E.; Pompei, P.; Ales, K.L.; MacKenzie, C.R. A new method of classifying prognostic comorbidity in longitudinal studies: Development and validation. J. Chronic Dis. 1987, 40, 373–383. [Google Scholar] [CrossRef] [Scilit]
  20. Quan, H.; Sundararajan, V.; Halfon, P.; Fong, A.; Burnand, B.; Luthi, J.C.; Saunders, L.D.; Beck, C.A.; Feasby, T.E.; Ghali, W.A. Coding algorithms for defining comorbidities in ICD-9-CM and ICD-10 administrative data. Med. Care 2005, 43, 1130–1139. [Google Scholar] [CrossRef] [Scilit]
  21. Groll, D.L.; To, T.; Bombardier, C.; Wright, J.G. The development of a comorbidity index with physical function as the outcome. J. Clin. Epidemiol. 2005, 58, 595–602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Sears, J.M.; Rundell, S.D. Development and Testing of Compatible Diagnosis Code Lists for the Functional Comorbidity Index: International Classification of Diseases, Ninth Revision, Clinical Modification and International Classification of Diseases, 10th Revision, Clinical Modification. Med. Care 2020, 58, 1044–1050. [Google Scholar] [CrossRef] [Scilit]
  23. Bajaj, M.; McCoy, R.G.; Balapattabi, K.; Bannuru, R.R.; Bellini, N.J.; Bennett, A.K.; Beverly, E.A.; Early, K.B.; ChallaSivaKanaka, S.; Echouffo-Tcheugui, J.B.; et al. 9. Pharmacologic Approaches to Glycemic Treatment: Standards of Care in Diabetes—2026. Diabetes Care 2026, 49, S183–S215. [Google Scholar] [CrossRef] [Scilit]
  24. Yokote, K.; Suzuki, R.; Gouda, M.; Iijima, H.; Yamazaki, A.; Inagaki, M. Association between glycemic control and cardiovascular events in older Japanese adults with diabetes mellitus: An analysis of the Japanese medical administrative database. J. Diabetes Investig. 2021, 12, 2036–2045. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Cavero-Redondo, I.; Peleteiro, B.; Álvarez-Bueno, C.; Rodriguez-Artalejo, F.; Martínez-Vizcaíno, V. Glycated haemoglobin A1c as a risk factor of cardiovascular outcomes and all-cause mortality in diabetic and non-diabetic populations: A systematic review and meta-analysis. BMJ Open 2017, 7, e015949. [Google Scholar] [CrossRef] [Scilit]
  26. Munshi, M.N.; Segal, A.R.; Suhl, E.; Staum, E.; Desrochers, L.; Sternthal, A.; Giusti, J.; McCartney, R.; Lee, Y.; Bonsignore, P.; et al. Frequent hypoglycemia among elderly patients with poor glycemic control. Arch. Intern. Med. 2011, 171, 362–364. [Google Scholar] [CrossRef] [Scilit]
  27. Moffet, H.H.; Huang, E.S.; Liu, J.Y.; Parker, M.M.; Lipska, K.J.; Laiteerapong, N.; Grant, R.W.; Lee, A.K.; Karter, A.J. Severe hypoglycemia and falls in older adults with diabetes: The Diabetes & Aging Study. Diabet. Epidemiol. Manag. 2023, 12, 100162. [Google Scholar] [CrossRef] [Scilit]
  28. Conway, B.N.; Long, D.M.; Figaro, M.K.; May, M.E. Glycemic control and fracture risk in elderly patients with diabetes. Diabetes Res. Clin. Pract. 2016, 115, 47–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Shih, C.J.; Wu, Y.L.; Lo, Y.H.; Kuo, S.C.; Tarng, D.C.; Lin, C.C.; Ou, S.M.; Chen, Y.T. Association of hypoglycemia with incident chronic kidney disease in patients with type 2 diabetes: A nationwide population-based study. Medicine 2015, 94, e771. [Google Scholar] [CrossRef] [Scilit]
  30. Bain, S.C.; Klufas, M.A.; Ho, A.; Matthews, D.R. Worsening of diabetic retinopathy with rapid improvement in systemic glucose control: A review. Diabetes Obes. Metab. 2019, 21, 454–466. [Google Scholar] [CrossRef] [Scilit]
  31. Mohseni, S. Hypoglycemic neuropathy. Acta Neuropathol. 2001, 102, 413–421. [Google Scholar] [CrossRef] [Scilit]
  32. Guan, D.; Lewis, M.O.; Li, P.; Zhang, Y.; Zhang, P.; Tang, S.; Brown, J.; Guo, J.; Zhang, Y.; Shao, H. Incremental Burden on health-related quality of life, health service utilization and direct medical expenditures associated with cognitive impairment among non-institutionalized people with diabetes aged 65 years and older. Diabetes Obes. Metab. 2024, 26, 275–282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Ensrud, K.E.; Schousboe, J.T.; Kats, A.M.; Taylor, B.C.; Boyd, C.M.; Langsetmo, L. Incremental health care costs of self-reported functional impairments and phenotypic frailty in community-dwelling older adults: A prospective cohort study. Ann. Intern. Med. 2023, 176, 463–471. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Functional status of the elderly participants. The green, yellow, and red bars indicate groups A, B, and C, respectively. Group A, no or mild impairment; Group B, moderate impairment; and Group C, severe impairment; T2D, type 2 diabetes.
Diabetology 07 00074 g001
Figure 2. Frequency of high-risk drug usage in elderly participants with T2D. The green, yellow, and red bars indicate groups A, B, and C, respectively. Group A, no or mild impairment; Group B, moderate impairment; Group C, severe impairment; T2D, type 2 diabetes.
Diabetology 07 00074 g002
Table 1. Participant characteristics.
OverallNon-T2DT2Dp Value
Number11,41182903121-
Age (years old)81.0 (6.6)81.4 (6.7)80.1 (6.4)<0.001
Sex: Female (%)6826 (59.8)5369 (64.8)1457 (46.7)<0.001
Body weight (kg)53.1 (10.6)51.8 (10.2)56.4 (11.2)<0.001
BMI (kg/m2)22.6 (3.6)22.4 (3.5)23.4 (3.7)<0.001
SBP (mmHg)133.0 (18.8)132.9 (18.9)133.1 (18.6)0.684
DBP (mmHg)71.2 (11.6)71.5 (11.6)70.3 (11.7)<0.001
HbA1c (%)5.87 (0.74)5.60 (0.32)6.56 (1.03)<0.001
Blood glucose level (mg/dL)108.9 (32.5)100.4 (18.2)132.6 (48.1)<0.001
AST (U/L)24.8 (11.1)24.6 (9.7)25.6 (14.3)<0.001
ALT (U/L)18.0 (10.8)17.2 (9.3)20.2 (13.8)<0.001
γGTP (U/L)29.7 (44.0)27.6 (41.1)35.3 (50.5)<0.001
Cre (mg/dL)0.82 (0.40)0.80 (0.35)0.88 (0.51)<0.001
eGFR (mL/min/1.73 m2)62.4 (17.7)62.5 (16.9)62.1 (19.6)0.684
TG (mg/dL)115.6 (67.7)110.7 (61.9)128.5 (79.6)<0.001
HDL-C (mg/dL)61.1 (16.5)62.4 (16.5)57.6 (16.2)<0.001
LDL-C (mg/dL)109.6 (29.1)110.9 (28.6)106.1 (30.1)<0.001
RBC (×104/μL)404.28 (78.45)406.40 (62.57)398.65 (109.84)<0.001
Hb (g/dL)12.47 (2.43)12.56 (1.95)12.25 (3.38)<0.001
mFCI score5.9 ± 2.55.9 ± 2.56.2 ± 2.5<0.001
mCCI score6.8 ± 3.36.5 ± 3.27.6 ± 3.5<0.001
All data, except for sex, are shown as averages ± standard deviations (SDs). BMI, body mass index; BP, blood pressure; eGFR, estimated glomerular filtration rate; Cre, creatinine; LDL-C, low-density lipoprotein cholesterol; HDL-C, high-density lipoprotein cholesterol; RBC, red blood cell; Hb; hemoglobin, mFCI, Modified Functional Comorbidity Index (FCI); mCCI, Modified Charlson Comorbidity Index.
Table 2. Factors affecting functional status in participants without T2D.
Moderate or Severe ImpairmentSevere Impairment
OR [95% CI]p ValueOR [95% CI]p Value
Age (per 1 year)1.02 [1.01–1.02]<0.0011.00 [0.99–1.01]0.561
Sex: Female0.49 [0.45–0.54]<0.0010.41 [0.35–0.47]<0.001
BMI (per 1.0 kg/m2)0.95 [0.94–0.96]<0.0011.00 [0.98–1.02]0.769
Systolic BP (per 10 mmHg)1.02 [1.00–1.05]0.0581.06 [1.02–1.09]0.004
HbA1c (per 1.0%)0.84 [0.73–0.97]0.0160.79 [0.64–0.99]0.042
LDL-C (per 10.0 mg/dL)1.02 [1.01–1.04]0.0040.99 [0.96–1.01]0.273
eGFR (per 10 mL/min/1.73 m2)1.00 [0.97–1.03]0.9321.00 [0.96–1.04]0.959
OR, odds ratio; CI, confidence interval; BMI, body mass index; BP, blood pressure; LDL-C, low-density lipoprotein cholesterol; eGFR, estimated glomerular filtration rate; T2D, type 2 diabetes.
Table 3. Factors affecting functional status in participants with T2D.
Moderate or Severe ImpairmentSevere Impairment
OR [95% CI]p ValueOR [95% CI]p Value
Age (per 1 year)1.00 [0.99–1.01]0.9060.98 [0.96–1.00]0.010
Sex: Female0.58 [0.50–0.67]<0.0010.54 [0.44–0.66]<0.001
BMI (per 1.0 kg/m2)0.98 [0.96–1.00]0.0190.99 [0.97–1.02]0.697
Systolic BP (per 10 mmHg)1.05 [1.01–1.10]0.0071.06 [1.01–1.12]0.021
HbA1c (per 1.0%)1.02 [0.95–1.09]0.6080.78 [0.71–0.87]<0.001
LDL-C (per 10 mg/dL)1.02 [1.00–1.05]0.0941.02 [0.99–1.05]0.291
eGFR (per 10 mL/min/1.73 m2)1.00 [0.96–1.04]0.9131.01 [0.97–1.07]0.562
High-risk drug use1.42 [1.22–1.65]<0.0011.90 [1.53–2.36]<0.001
OR, odds ratio; CI, confidence interval; BMI, body mass index; BP, blood pressure; LDL-C, low-density lipoprotein cholesterol; eGFR, estimated glomerular filtration rate; T2D, type 2 diabetes.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.