


Abstract
Background: Diabetic retinopathy (DR) remains one of the most frequent and severe complications in patients with type 2 diabetes (T2DM), with significant implications for vision and quality of life. While classical screening methods are effective, they are not always accessible or systematically used. Sudoscan, a device that evaluates sweat gland function by measuring electrochemical skin conductance (ESC)—an indicator of chloride ion flow through sweat glands and a marker of peripheral autonomic nerve function—has recently attracted attention as a potential adjunct tool for risk assessment of microvascular complications. Objectives: In this cross-sectional study, we investigated its utility in identifying DR among 271 adults with T2DM. DR was diagnosed in 35.8% of patients, and those affected showed lower Sudoscan scores in the lower limbs and higher scores indicating cardiovascular autonomic neuropathy. Methods: Statistical analyses, including ROC curve evaluation and multiple linear regression, revealed moderate diagnostic accuracy and significant correlations between Sudoscan parameters and DR severity. Results: Our results suggest that Sudoscan could serve as a fast, painless, and informative screening tool, particularly valuable in settings with limited access to ophthalmologic services. Conclusions: Although it does not replace fundus examination, it may offer complementary insights and help stratify patients by risk level, guiding more targeted monitoring and intervention strategies.
1. Introduction
Diabetic retinopathy (DR) is one of the most common and serious complications of type 2 diabetes mellitus and remains a leading cause of blindness worldwide. It is estimated that approximately 30% of individuals with diabetes globally show signs of DR, with less than 10% developing sight-threatening lesions, such as proliferative diabetic retinopathy and/or diabetic macular oedema [1,2,3]. By 2045, the global number of patients with DR is projected to reach 160.5 million, with approximately 44.82 million at risk of vision loss [4].
The Diabetic Retinopathy Barometer Study revealed significant gaps in patient education, healthcare professional training, and access to affordable treatment. These challenges are particularly pronounced in low- and middle-income countries and among minority populations, where the burden of disease remains highest [5]. Additionally, studies suggest that individuals diagnosed with type 2 diabetes at a younger age may have increased susceptibility to developing DR [6].
Screening for diabetic retinopathy plays a critical role in preventing disease progression and vision loss. Common screening methods include fundus examination, retinal photography, and optical coherence tomography (OCT) imaging [7]. Diabetic retinopathy is classified into mild, moderate, and severe non-proliferative diabetic retinopathy (NPDR) and proliferative diabetic retinopathy (PDR), based on the extent of retinal microvascular abnormalities.
Sudoscan is a non-invasive device that evaluates sudomotor function by measuring electrochemical skin conductance (ESC), providing information regarding autonomic nervous system function. Its potential role in the evaluation of diabetic complications has recently attracted attention due to its simplicity, rapid execution, and non-invasive nature.
Recent studies have demonstrated associations between Sudoscan parameters and diabetic microvascular complications. One study evaluated Sudoscan as a screening tool for multiple complications in patients with type 2 diabetes and suggested potential utility in identifying neuropathy, chronic kidney disease, and cardiovascular autonomic neuropathy [8].
The present study was designed to evaluate Sudoscan-derived parameters in a clinically characterized real-world cohort of patients with type 2 diabetes and ophthalmologically confirmed diabetic retinopathy. Unlike previous studies primarily focused on isolated ESC measurements, this study explores the combined relationship between ESC values, Sudoscan composite risk scores, and validated clinical neuropathy scores in relation to diabetic retinopathy severity. Additionally, this study provides data from a Romanian population, a region where evidence regarding the association between sudomotor dysfunction and diabetic retinopathy remains limited. The aim is to investigate the potential role of integrated autonomic and peripheral neuropathy assessment as part of systemic microvascular risk evaluation in patients with type 2 diabetes.
2. Materials and Methods
2.1. Study Design and Ethics
This cross-sectional study was conducted between June 2019 and June 2020 at a single clinical center and included 271 patients. Ethical approval was obtained from the Ethics Committee of the Nicolae Malaxa Clinical Hospital in Bucharest, Romania (approval number 2145). Data were collected in accordance with the hospital’s standard of care for patients with type 2 diabetes mellitus (T2DM). All participants provided written informed consent for the collection and use of their medical data for research purposes. Patients were recruited from the Diabetes Department of the Nicolae Malaxa Clinical Hospital.
2.2. Study Population
Inclusion criteria were: patients attending outpatient consultations or hospitalized in the Diabetes Department during the study period, age > 18 years, overweight or obese individuals, confirmed diagnosis of type 2 diabetes, and signed informed consent. The inclusion of overweight and obese patients was based on the higher prevalence of metabolic and microvascular complications observed in this population, as well as the increased risk of autonomic dysfunction associated with excess adiposity. This approach was intended to allow a more focused evaluation of Sudoscan performance in a population at increased risk of diabetic complications. Exclusion criteria included: refusal to sign informed consent, presence of other diabetes types (type 1, latent autoimmune diabetes of adulthood, MODY), patients aged 18 or younger, pregnancy, history of malignancy in the past five years, prior stroke, history of myocardial infarction, lower limb amputations, chronic kidney disease predating the diagnosis of diabetes, and neuropathy due to other causes (e.g., alcoholism, vitamin B12 deficiency). Patients with stroke sequelae were excluded to avoid potential false positives in sensitivity testing and Sudoscan results. Patients with recent malignancies were excluded due to the risk of chemotherapy-induced neuropathy. Amputees were excluded since Sudoscan testing cannot be performed in such cases.
2.3. Clinical Assessment
Anthropometric data collected included height, weight, body mass index (BMI), waist circumference, waist-to-hip ratio, blood pressure in supine and standing positions, and heart rate in supine and standing positions, as well as smoking status.
2.4. Biochemical Parameters
Venous plasma samples were collected after an 8-h fast to assess: fasting glucose, glycated hemoglobin (HbA1c), serum creatinine, urinary albumin-to-creatinine ratio (ACR), total cholesterol, HDL, LDL, triglycerides, bilirubin, C-reactive protein, potassium, magnesium, chloride, sodium, calcium, urea, AST, ALT, and GGT. Estimated glomerular filtration rate (eGFR) was calculated using the MDRD equation. The ACR was determined from spot urine samples.
2.5. Assessment of Diabetic Retinopathy
Diabetic retinopathy (DR) was assessed by ophthalmological examination. Fundus examination was performed by a single ophthalmologist. The eye with more severe pathology was used for classification. DR was categorized as non-proliferative or proliferative. Patients with no such abnormalities were considered free of retinopathy.
2.6. Assessment of Peripheral Diabetic Neuropathy
Peripheral diabetic neuropathy was evaluated using the Toronto Clinical Scoring System, sudomotor function, and lower limb sensitivity testing. The Toronto protocol is validated against sural nerve biopsy and correlates well with electrophysiological testing. Symptoms such as pain, numbness, paresthesia, weakness, and upper limb involvement were recorded. Achilles and patellar reflexes were tested. Instrumental evaluations included temperature perception using TipTherm, pressure sensitivity using the 10 g Semmes–Weinstein monofilament, vibratory sensation with the Rydel–Seiffer tuning fork, and pain sensitivity using pinprick testing and the Neuropen.
2.7. Assessment of Chronic Kidney Disease (CKD)
CKD was classified based on eGFR and ACR. CKD was defined as eGFR < 60 mL/min/1.73 m2. Microalbuminuria was defined as ACR 30–300 mg/g and macroalbuminuria as ACR > 300 mg/g.
2.8. Assessment of Cardiovascular Autonomic Neuropathy (CAN)
CAN was assessed using the QTc interval from ECG and cardiovascular autonomic reflex tests (CARTs), including heart rate variability, Valsalva maneuver, orthostatic testing, and isometric exercise blood pressure response. The ESP-01-PA Ewing tester (MDE R&D, Budapest, Hungary) was used. Sudoscan also integrates algorithms combining electrochemical skin conductance with age to estimate CAN risk (Sudoscan-CAN score).
2.9. Evaluation of Sudomotor Function
Sudoscan is an FDA-approved non-invasive device used to assess sudomotor function by analyzing sweat gland activity in the hands and feet. The device measures electrochemical skin conductance (ESC) separately at the level of hands and feet and reports mean ESC values expressed in microSiemens (µS). In this study, mean feet ESC values were reported as lower limb scores, while mean hands ESC values were reported as upper limb scores. These parameters correspond to sudomotor function measurements described in previous studies as ESC/FESC values. In addition to raw ESC measurements, the device software integrates ESC with demographic and clinical variables (e.g., age, height, weight, HbA1c) to generate composite risk scores for nephropathy (Sudoscan Nephropathy Score) and cardiovascular autonomic neuropathy (Sudoscan-CAN). The procedure involves placing the hands and feet on electrodes for approximately three minutes. A low electrical stimulus activates the sweat glands, and the electrochemical response is measured. The procedure is fast, painless, and requires no special preparation.
2.10. Statistical Analysis
Statistical analysis was performed using IBM SPSS Statistics for Windows, Version 20.0 (Released 2011; IBM Corp., Armonk, NY, USA). Normally distributed continuous variables were reported as mean ± standard deviation (SD), while non-normally distributed variables were presented as median and interquartile range (IQR). Categorical variables were expressed as absolute numbers and percentages. Statistical significance was set at a 95% confidence level. ANOVA was used to compare quantitative variables across groups, and the χ2 test for categorical variables. To estimate the independent correlation between diabetic retinopathy and Sudoscan scores, multiple linear regression was applied. Diabetic retinopathy severity was treated as an ordered variable (absence of DR, NPDR, PDR). Multiple linear regression was used as an exploratory method to evaluate independent associations between Sudoscan parameters and increasing retinopathy severity. This approach was selected to quantify the direction and magnitude of associations rather than to construct predictive models. Non-normally distributed variables were log10-transformed to meet the assumptions of parametric testing.
3. Results
Patients were divided into three categories based on the presence and severity of diabetic retinopathy: without diabetic retinopathy (DR−), with non-proliferative diabetic retinopathy (NPDR), and with proliferative diabetic retinopathy (PDR). The results revealed statistically significant differences across several variables (Table 1).
Table 1.
Clinical Characteristics and Biochemical Parameters Stratified by the Presence and Severity of Diabetic Retinopathy.
For example, the mean age differed significantly between groups (p = 0.038), with patients in the NPDR group being generally older than those in the PDR group. The duration of diabetes was also significantly longer in patients with retinopathy (NPDR and PDR) compared to those without retinopathy (DR−) (p < 0.001). Regarding body mass index (BMI), significantly higher values were observed in the PDR group (p = 0.043), suggesting a potential association between retinopathy severity and obesity.
Metabolic parameters and renal function showed notable differences. Although blood glucose and HbA1c levels did not differ significantly between groups, the urinary albumin-to-creatinine ratio (ACR) was significantly higher in patients with proliferative diabetic retinopathy (p = 0.032), indicating more pronounced renal impairment in this group.
Clinical scores used to assess nerve damage (Toronto Score, Ewing Score, and Sudoscan Score) were significantly higher in patients with retinopathy, reflecting greater severity of neuropathic involvement in these groups (p < 0.001).
Both the Toronto and Ewing scores demonstrated significant intergroup differences, suggesting a strong correlation between these clinical indices and the presence of diabetic retinopathy.
The prevalence of diabetic retinopathy in the study population was 35.8% (n = 97). Among these patients, 85.6% (n = 83) had non-proliferative diabetic retinopathy, while 14.4% (n = 14) were diagnosed with proliferative diabetic retinopathy.
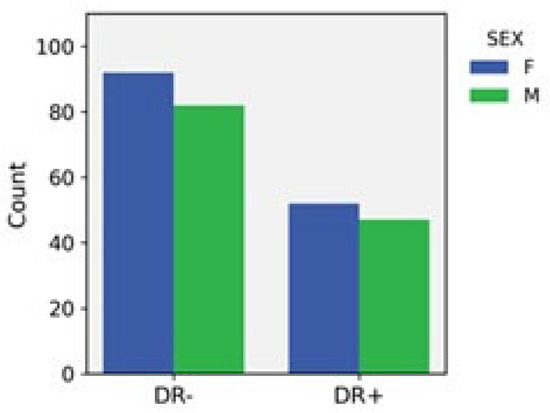
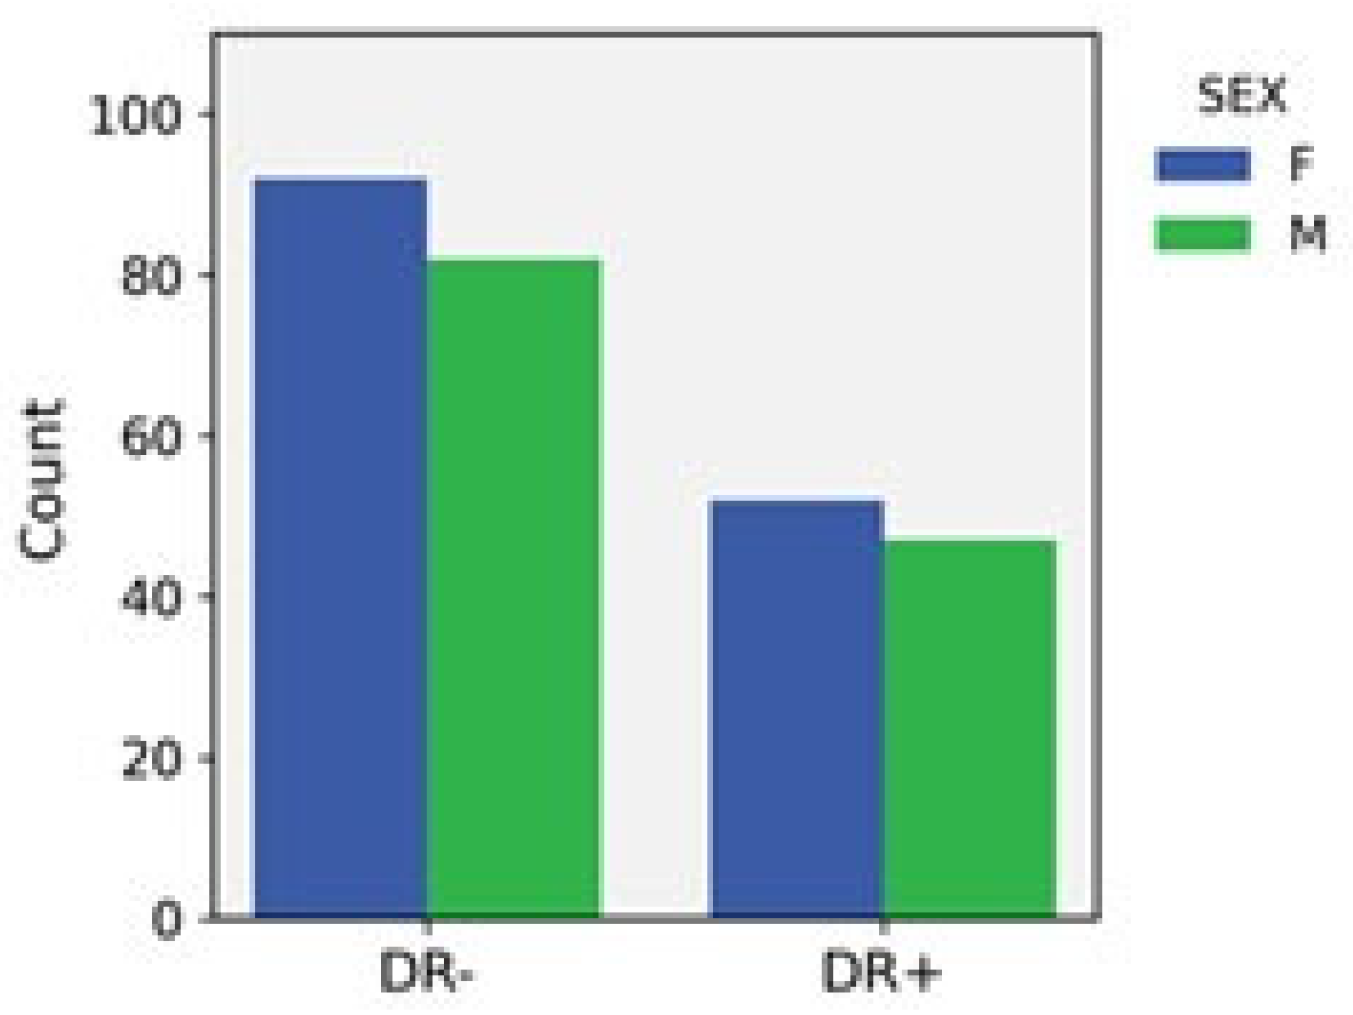
Female patients accounted for a higher number of DR cases, likely due to their greater representation in the study cohort (Figure 1).
Figure 1.
Presence of diabetic rethinopathy stratified by sex.
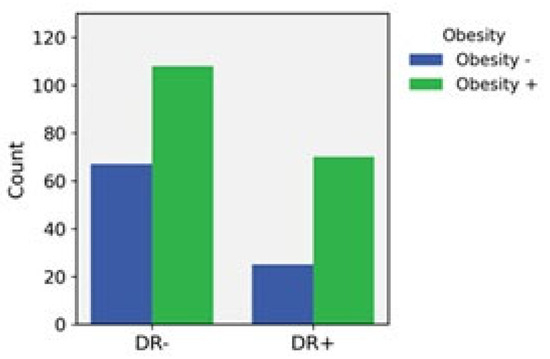
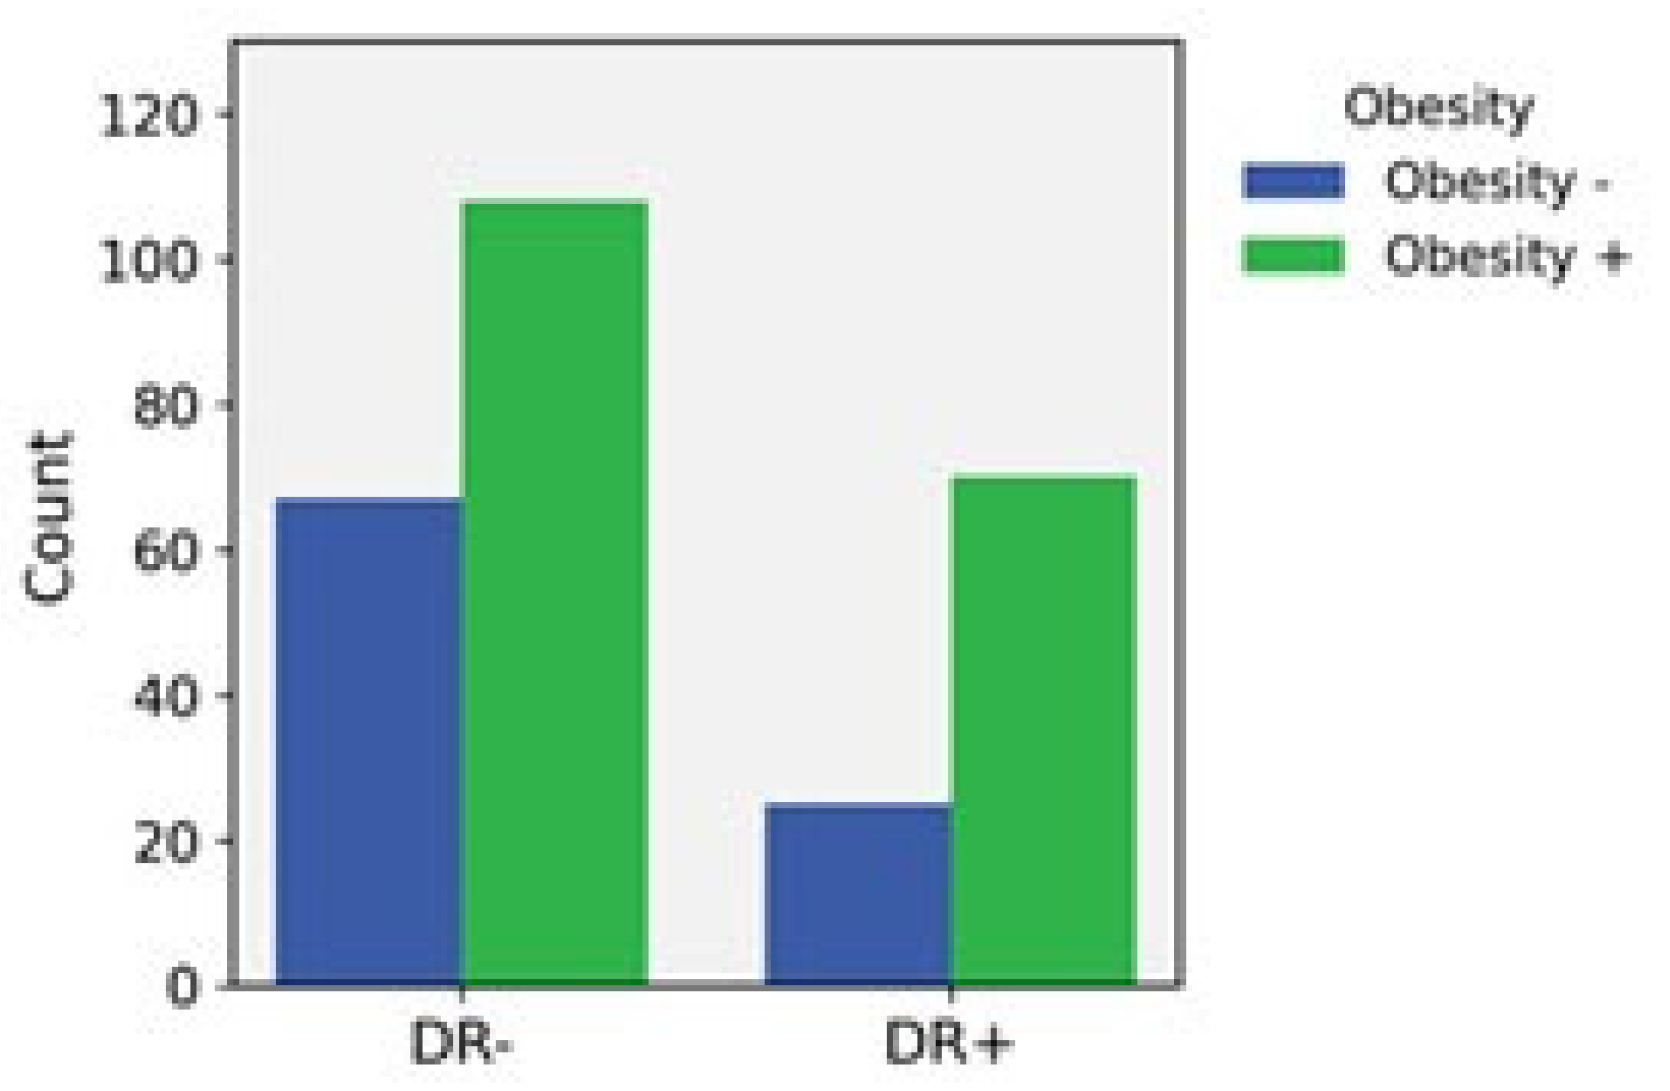
Obese individuals showed a higher prevalence of DR compared to non-obese participants (Figure 2).
Figure 2.
Presence of diabetic rethinopathy stratified by weight status.
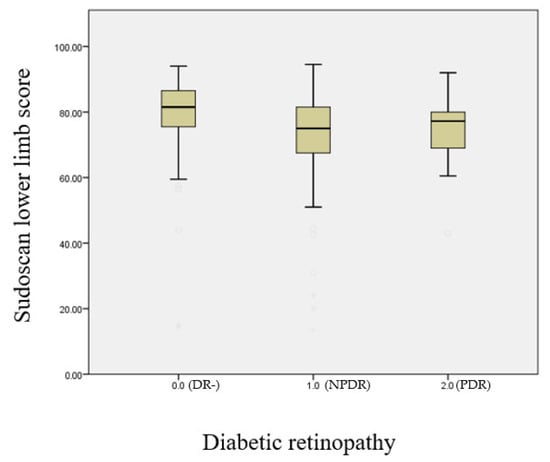
This boxplot illustrates the Sudoscan score for the lower limbs according to the presence and severity of diabetic retinopathy (Figure 3). A progressive decline in sudomotor function in the lower limbs is observed with increasing retinopathy severity (p < 0.001).
Figure 3.
Boxplot illustrating the relationship between the Sudoscan lower limb score and the severity of diabetic retinopathy.
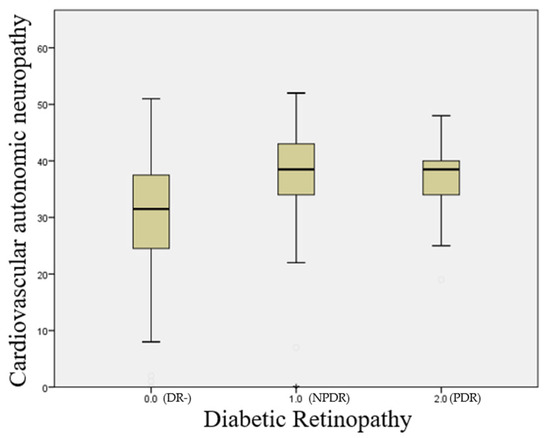
This boxplot illustrates the Sudoscan CAN score according to the presence and severity of diabetic retinopathy (Figure 4). A significant increase in the risk score for cardiovascular autonomic neuropathy is observed with increasing retinopathy severity (p < 0.001).
Figure 4.
Boxplot illustrating the relationship between the presence of cardiovascular autonomic neuropathy and the severity of diabetic retinopathy.
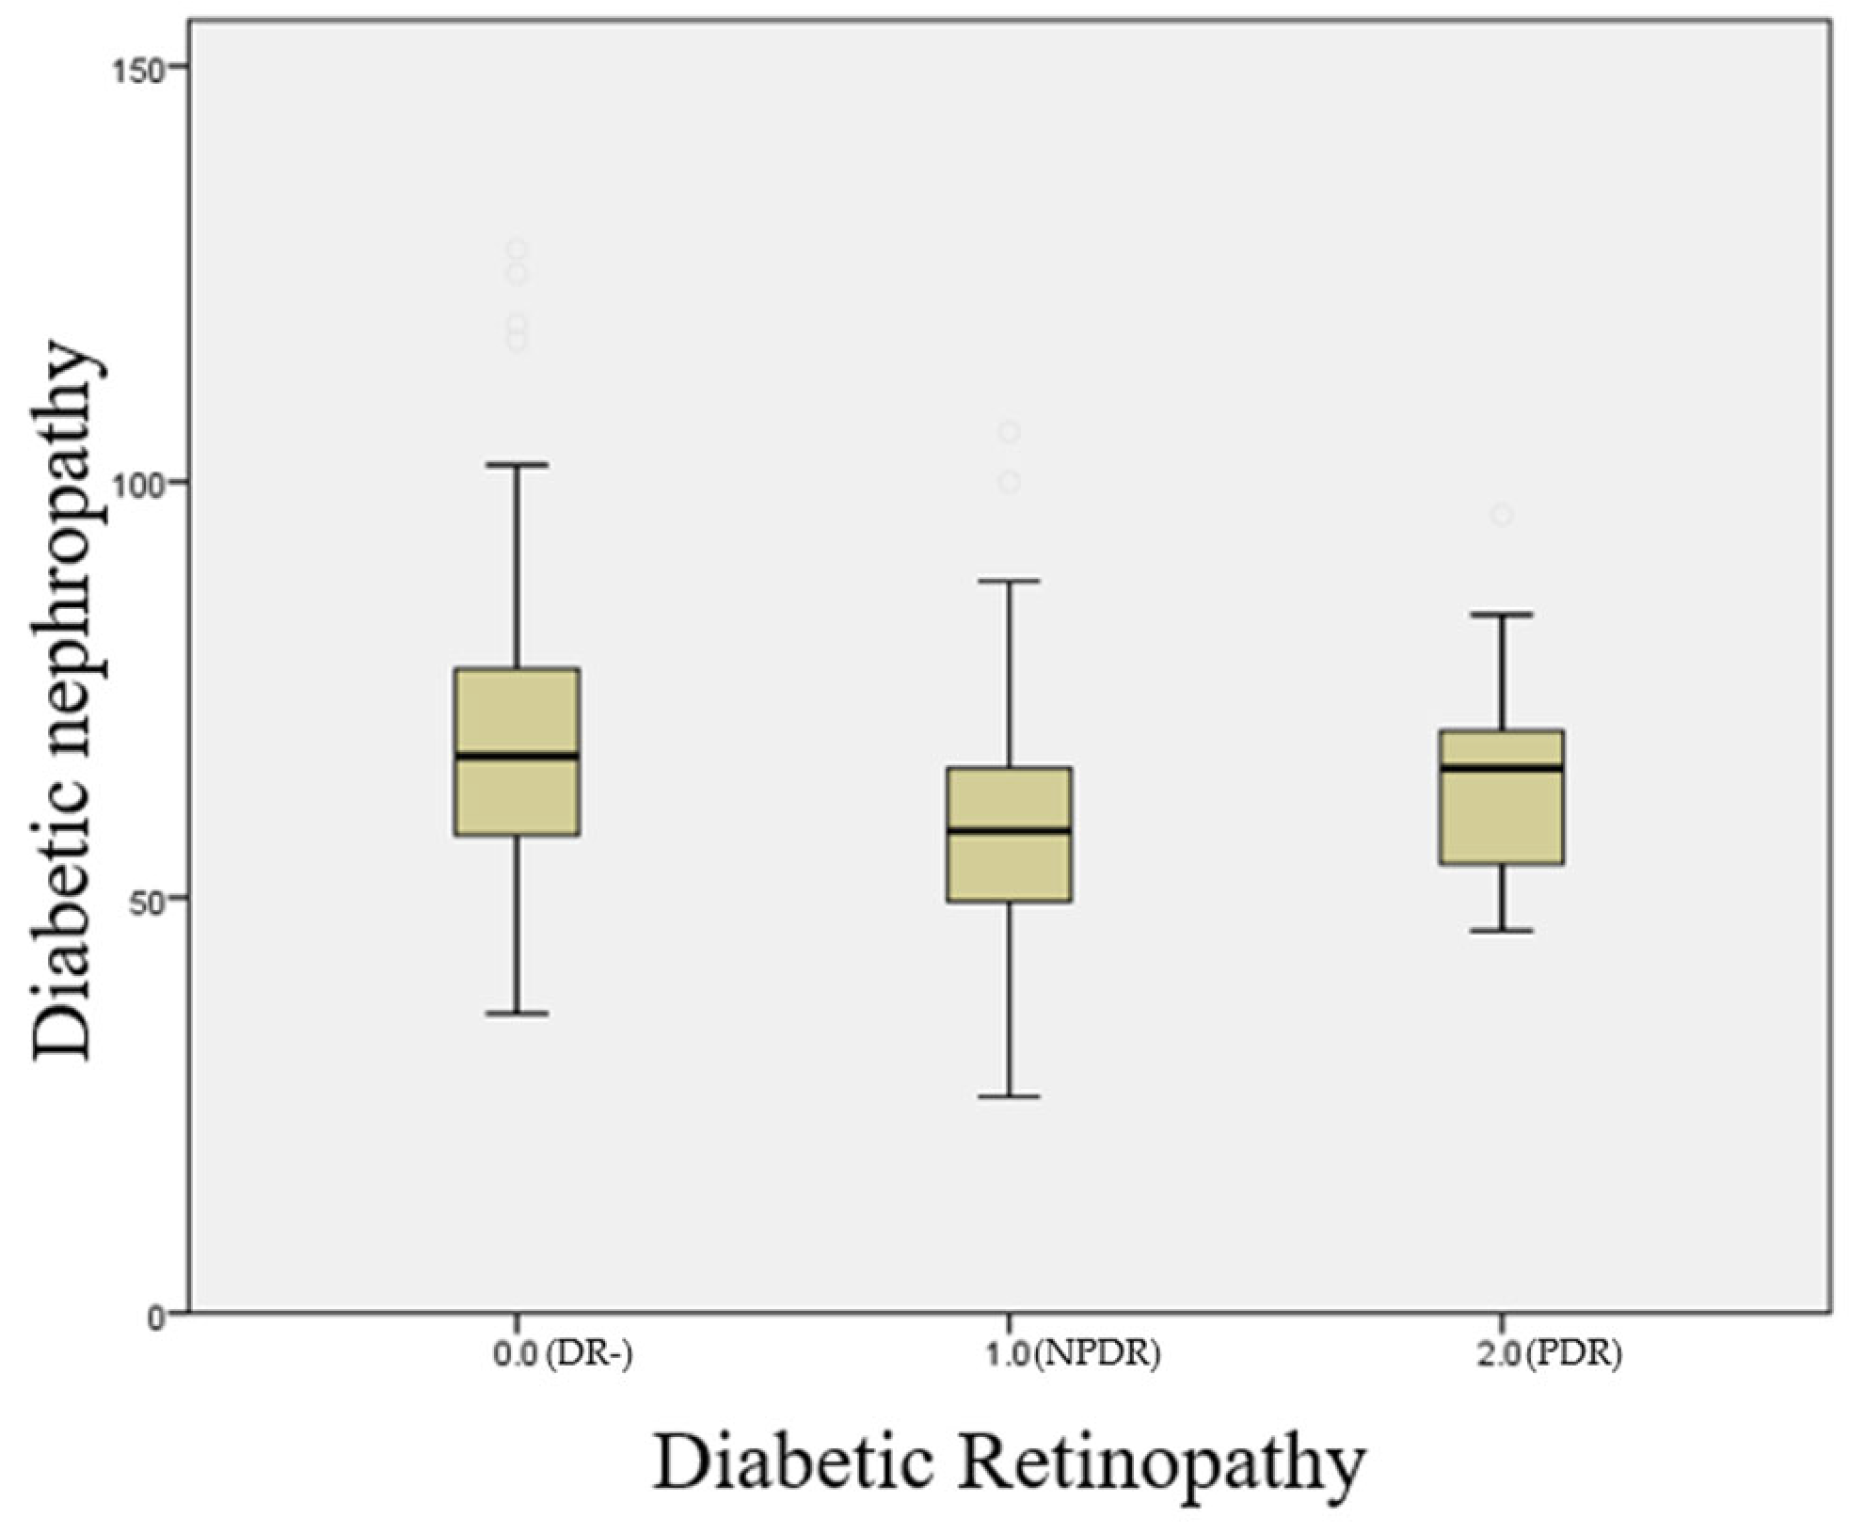
This boxplot illustrates the Sudoscan Nephropathy score according to the presence and severity of diabetic retinopathy (Figure 5). A significant increase in the risk score for diabetic nephropathy is observed with increasing retinopathy severity (p < 0.001).
Figure 5.
Boxplot illustrating the relationship between the presence of diabetic nephropathy and the severity of diabetic retinopathy.
Performance of Sudoscan in the Diagnosis of Diabetic Retinopathy
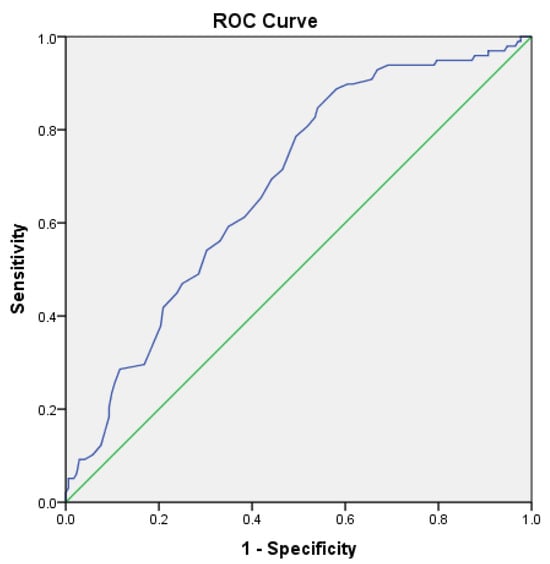
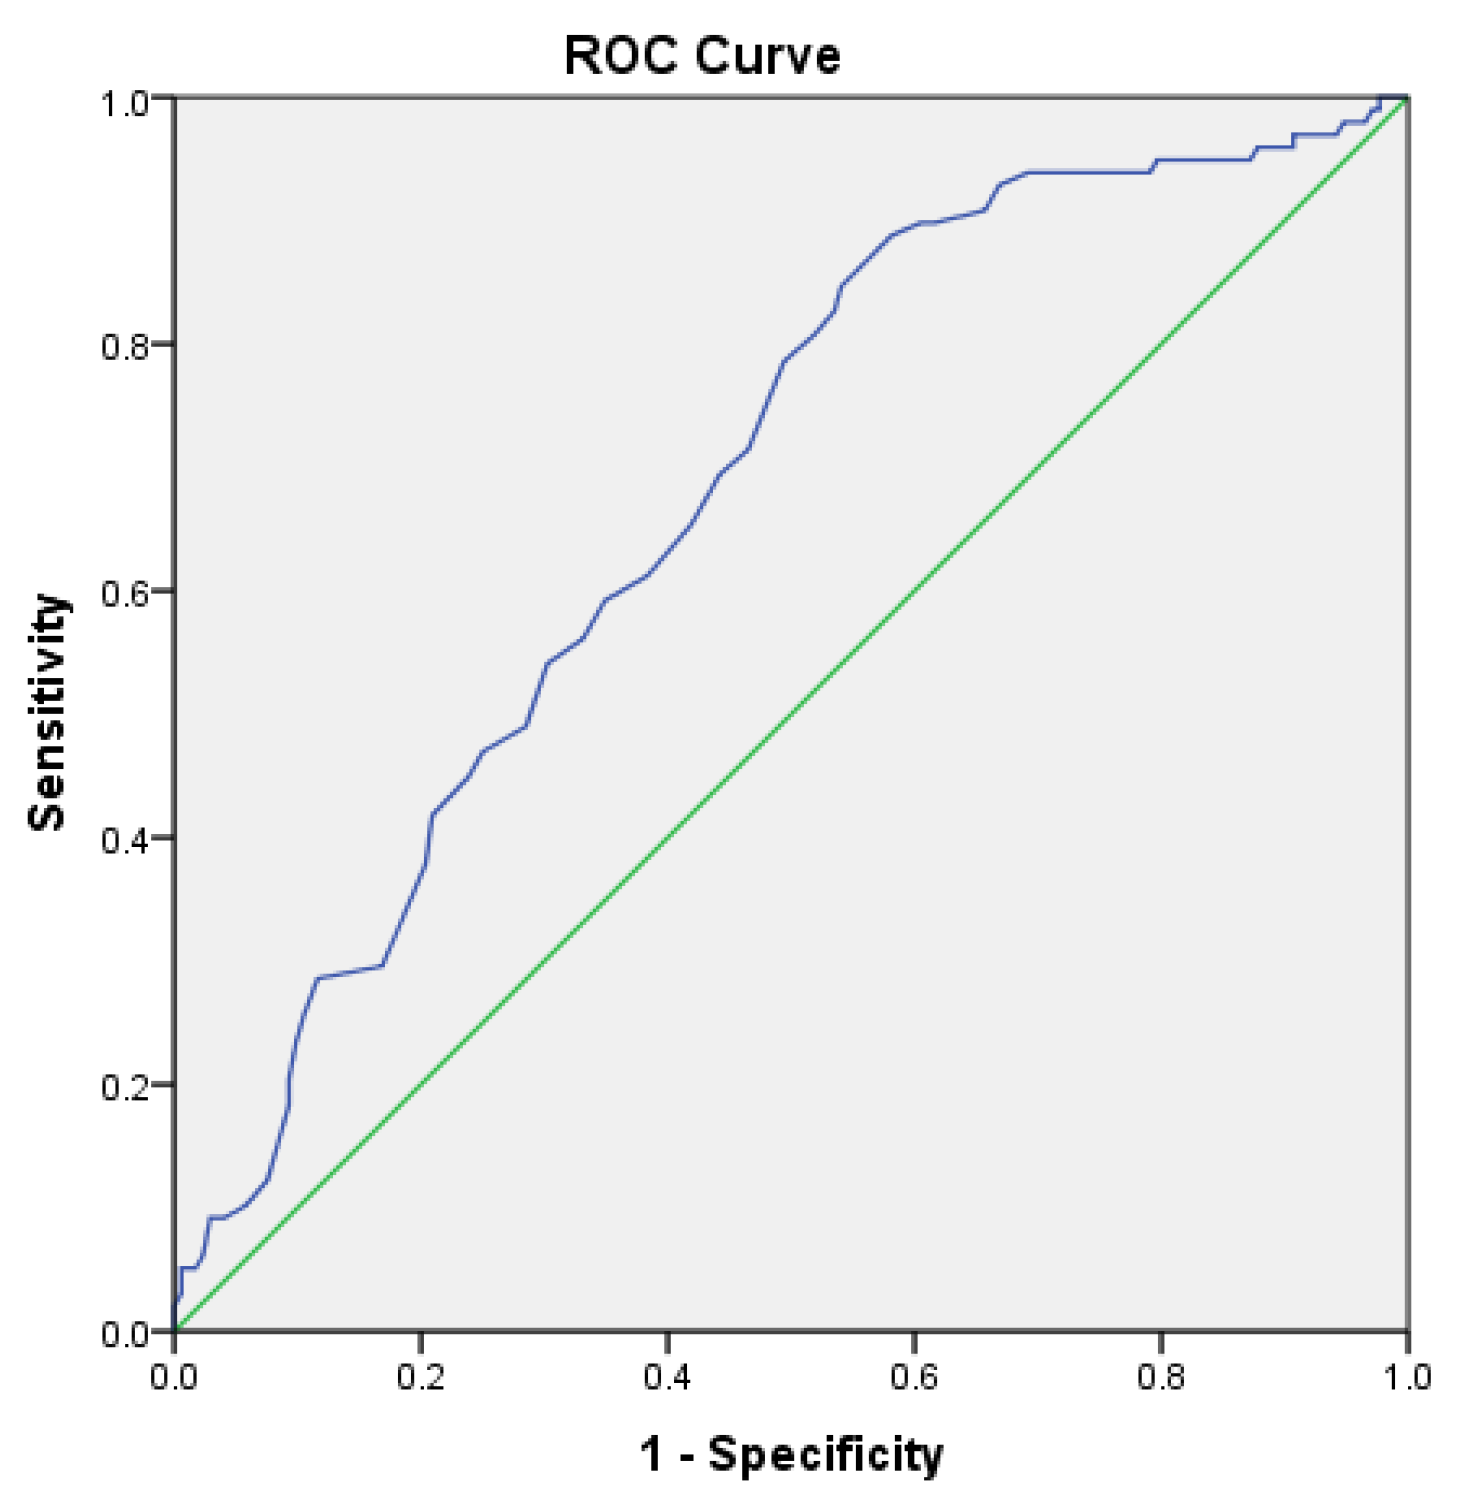
The area under the receiver operating characteristic (ROC) curve for the Sudoscan lower limb score in predicting diabetic retinopathy (Figure 6) was 0.672 (95% CI: 0.605–0.738). The cutoff value for the Sudoscan lower limb score was 81.75, with a sensitivity of 76.5% and a specificity of 50.3% for detecting diabetic retinopathy.
Figure 6.
ROC curve of the Sudoscan lower limb score in detecting diabetic retinopathy in patients with type 2 diabetes.
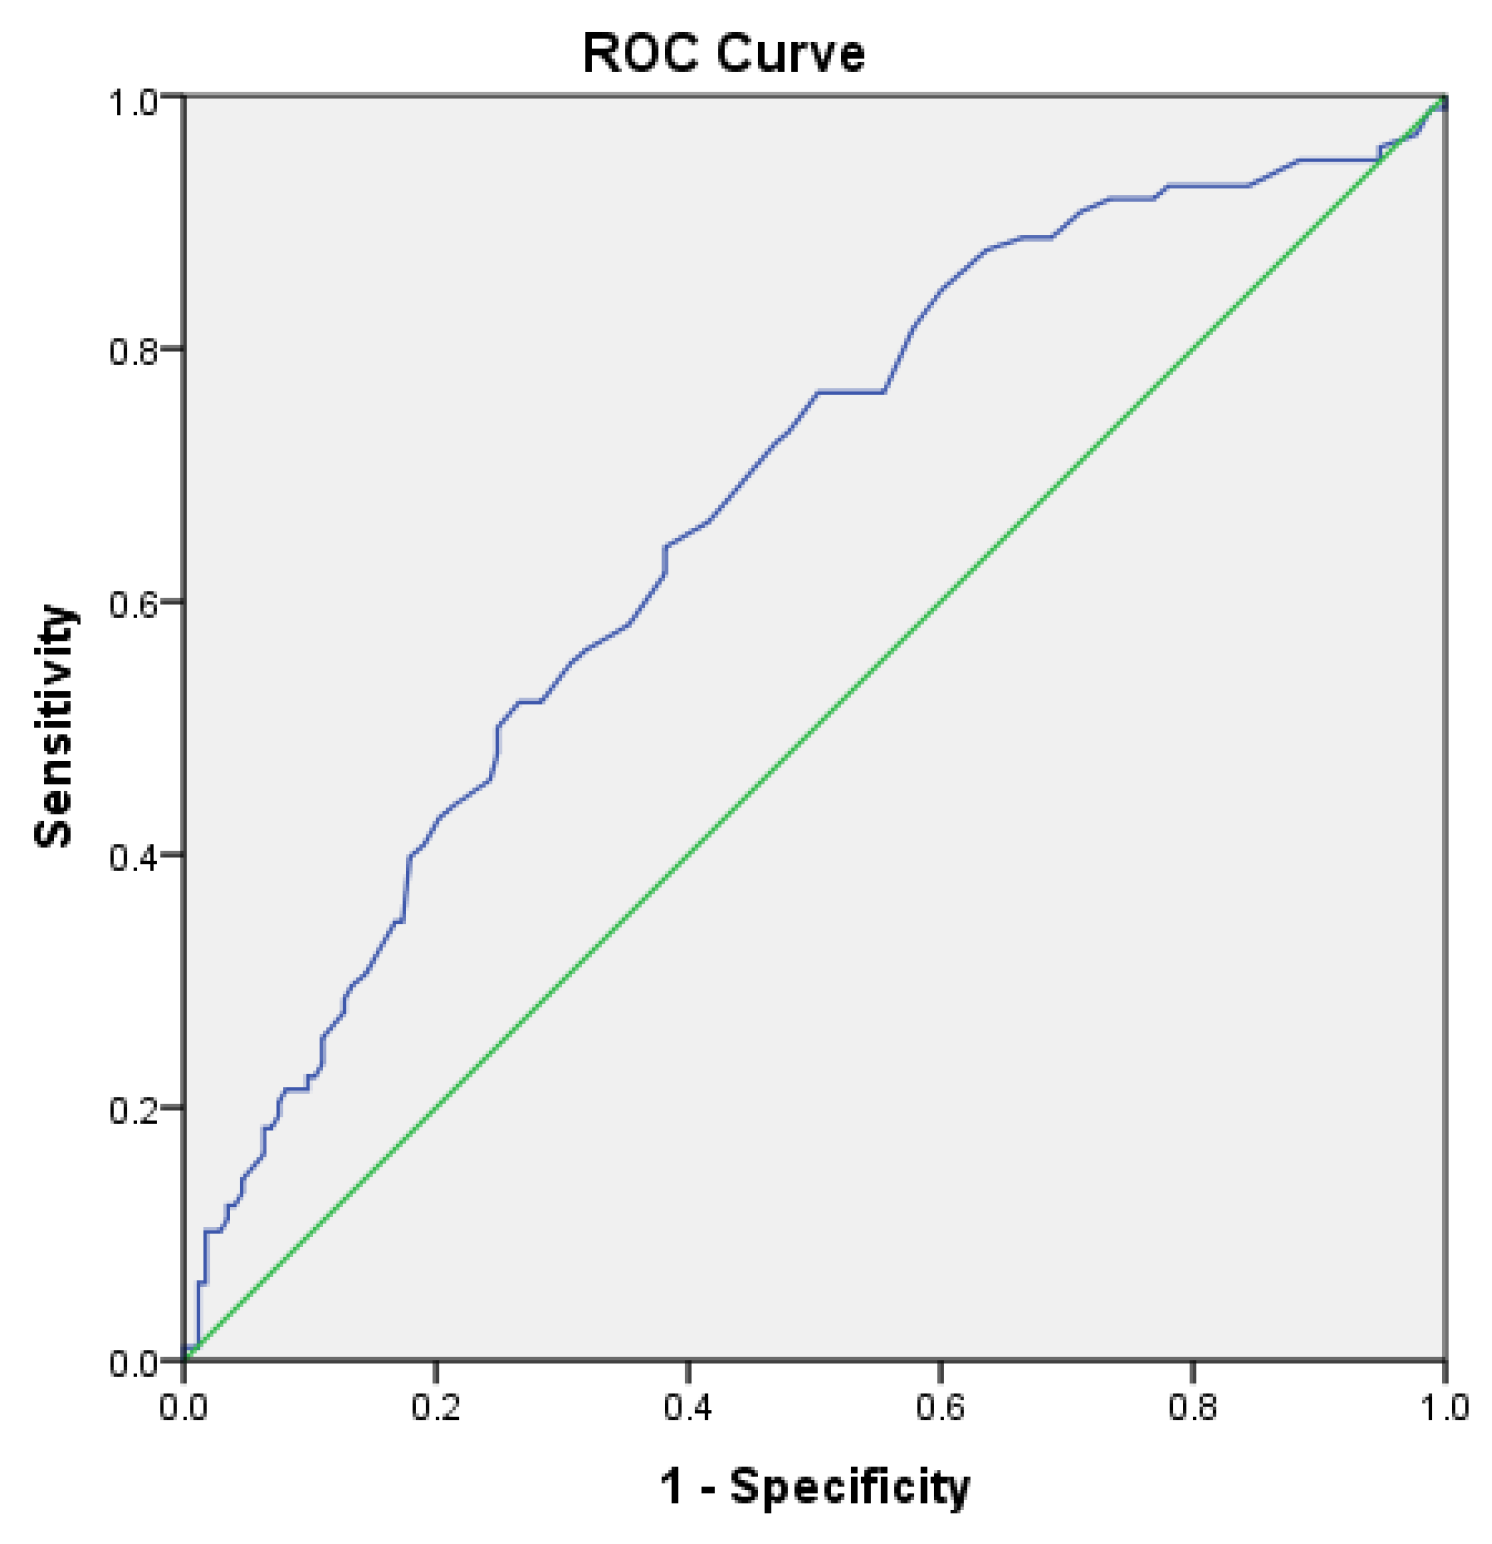
The area under the receiver operating characteristic (ROC) curve for the Sudoscan Nephropathy score in predicting diabetic retinopathy (Figure 7) was 0.679 (95% CI: 0.614–0.743). The cutoff value for the Sudoscan Nephropathy score was 69.5, with a sensitivity of 84.7% and a specificity of 54.1% for detecting diabetic retinopathy.
Figure 7.
ROC curve of the Sudoscan Nephropathy score in detecting diabetic retinopathy in patients with type 2 diabetes.
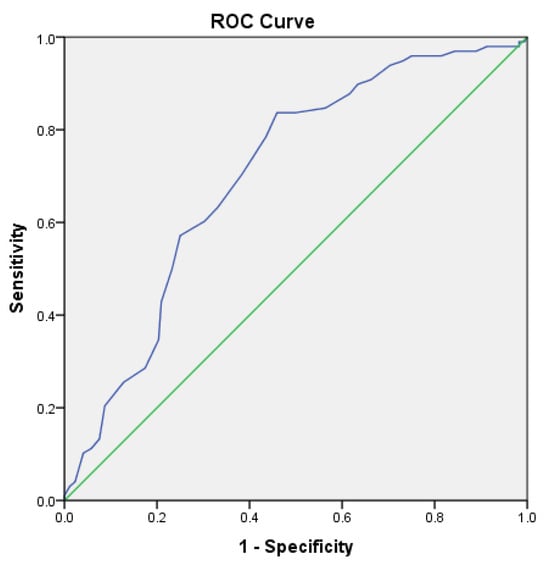
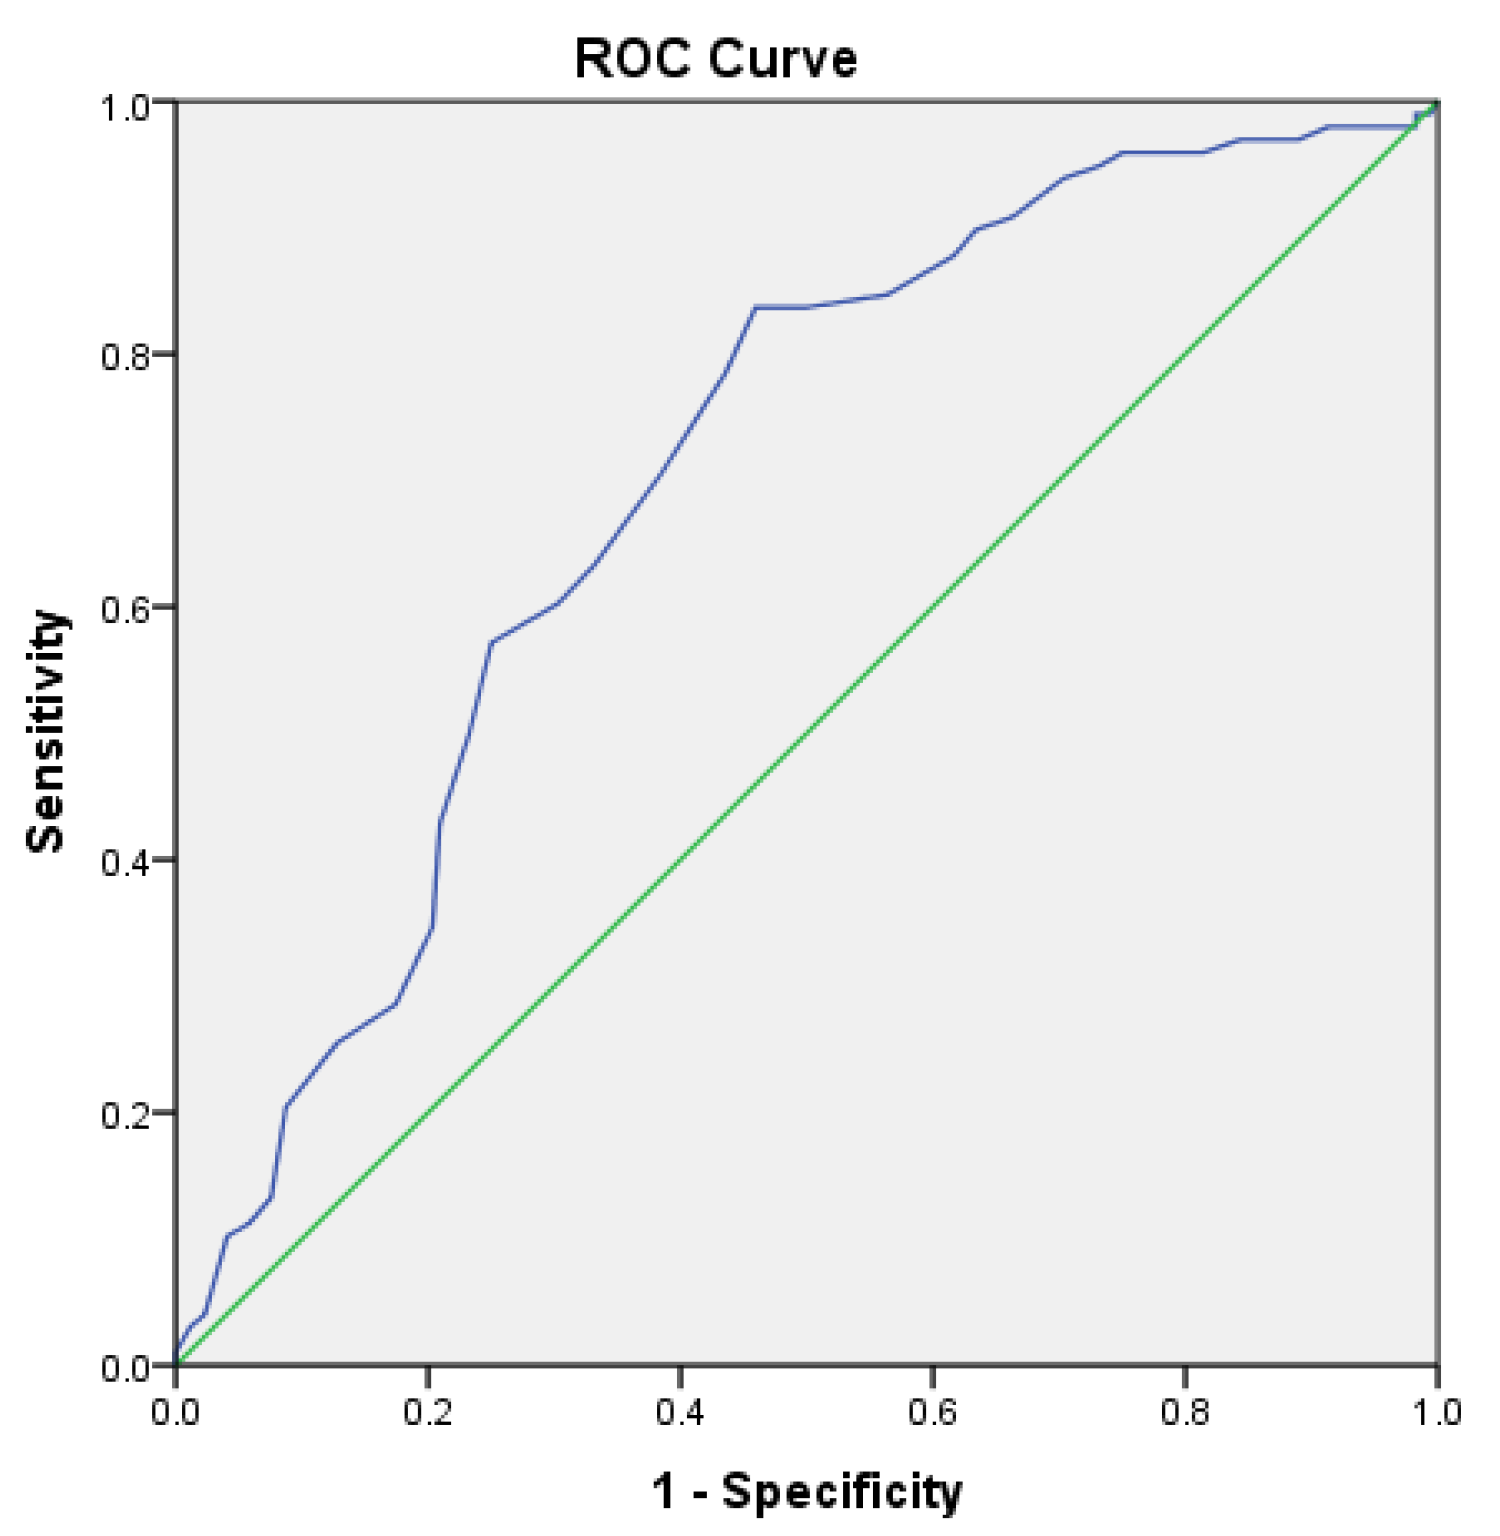
The area under the receiver operating characteristic (ROC) curve for the Sudoscan CAN score in predicting diabetic retinopathy (Figure 8) was 0.702 (95% CI: 0.639–0.765). The cutoff value for the Sudoscan CAN score was 32.5, with a sensitivity of 83.7% and a specificity of 45.9% for detecting diabetic retinopathy.
Figure 8.
ROC curve of the Sudoscan CAN score in detecting diabetic retinopathy in patients with type 2 diabetes.
The statistical analysis presented in Table 2 employs multiple linear regression to investigate the correlation between Sudoscan test variables and diabetic retinopathy in patients with type 2 diabetes.
Table 2.
Sudoscan Test Variables in Correlation with Diabetic Retinopathy in Patients with Type 2 Diabetes Using Multiple Linear Regression.
The multiple regression analysis revealed significant associations between the severity of diabetic retinopathy and several clinical and functional parameters. Lower Sudoscan scores in the lower limbs were correlated with more advanced stages of retinopathy, while higher scores indicating cardiovascular autonomic neuropathy (CAN), as well as elevated Ewing and Toronto clinical scores, were positively associated with retinopathy severity. In contrast, Sudoscan scores from the upper limbs and the nephropathy risk score did not show significant correlations. These findings suggest that lower limb sudomotor dysfunction and autonomic nervous system impairment may play a more prominent role in the progression of diabetic retinopathy than other peripheral or renal markers, highlighting the potential utility of these measures in risk stratification and early detection.
In conclusion, the Sudoscan lower limb score, Sudoscan CAN score, Ewing test score, and Toronto Clinical Score showed significant correlations with diabetic retinopathy, suggesting that these measures may be useful in evaluating and monitoring patients with type 2 diabetes for the early detection of diabetic retinopathy.
4. Discussion
A series of systematic reviews and clinical studies have demonstrated that Sudoscan provides reproducible measurements and moderate diagnostic accuracy in detecting diabetic microvascular complications. Previous studies confirmed the reliability of electrochemical skin conductance measurements and highlighted their role in assessing autonomic dysfunction and small fiber neuropathy. Several reports also support the clinical applicability of Sudoscan in screening diabetic complications, particularly in resource-limited settings. These findings collectively support the potential role of Sudoscan as a complementary tool in evaluating systemic diabetic microvascular disease [9,10,11,12].
In the present study, Sudoscan parameters were significantly associated with diabetic retinopathy severity in patients with type 2 diabetes. These findings are consistent with previous research demonstrating associations between sudomotor dysfunction and diabetic microvascular complications. For example, prior studies reported sensitivity and specificity values comparable to those observed in our cohort for identifying diabetic retinopathy [13]. Similarly, Lin et al. demonstrated that lower foot electrochemical skin conductance correlates significantly with diabetic retinopathy independently of neuropathy and nephropathy markers [8]. Wang and colleagues further reported that patients with sudomotor dysfunction (ESC < 60 µS) have a significantly increased risk of diabetic retinopathy, supporting the association between autonomic dysfunction and retinal microvascular damage [14].
Several studies have suggested that combining Sudoscan parameters with clinical assessment tools, such as neuropathy screening instruments or renal markers, may improve the detection of diabetic complications compared with individual diagnostic approaches [15,16]. These findings support the concept that diabetic microvascular complications often share common pathophysiological pathways and tend to progress in parallel.
According to the literature, traditional screening methods for diabetic retinopathy include fundus examination, retinal photography, and optical coherence tomography [17]. In the present study, Sudoscan demonstrated significant associations with diabetic retinopathy severity; however, the diagnostic performance was moderate, with AUC values ranging between 0.67 and 0.70. Therefore, Sudoscan should be interpreted as a potential adjunct tool for risk stratification and identification of patients who may benefit from ophthalmologic evaluation rather than a substitute for established retinal screening methods. Its non-invasive nature, rapid execution, and ease of use may support its role in clinical settings with limited access to ophthalmologic services [18]. Future prospective studies incorporating standardized retinal imaging are required to further validate the screening potential of Sudoscan in diabetic retinopathy.
Our results also demonstrated that the urinary albumin-to-creatinine ratio was significantly higher in patients with proliferative diabetic retinopathy, suggesting more advanced renal involvement in this group. These findings are consistent with previous studies indicating that renal dysfunction frequently parallels the severity of diabetic retinopathy and reflects the systemic nature of diabetic microangiopathy [19].
Although the duration of diabetes was significantly longer in patients with diabetic retinopathy, HbA1c values did not differ significantly between groups. This observation may reflect the cumulative effects of long-term glycemic exposure and the phenomenon of metabolic memory, suggesting that historical glycemic control may play a greater role in the development of microvascular complications than a single HbA1c measurement at the time of evaluation.
The Toronto and Ewing scores showed significant associations with diabetic retinopathy severity. These tests are validated tools for evaluating peripheral and cardiovascular autonomic neuropathy and are not specific diagnostic tools for retinal pathology. The observed association likely reflects shared microvascular and neurodegenerative mechanisms underlying diabetic complications rather than a direct role in retinopathy screening. These findings are consistent with previous studies emphasizing the importance of these scores in the assessment of diabetic neuropathy [20].
Our analysis also showed that lower limb Sudoscan scores were inversely correlated with diabetic retinopathy severity, suggesting that more severe sudomotor dysfunction is associated with advanced retinal disease. This observation supports previous reports indicating that sudomotor dysfunction reflects progressive autonomic nerve fiber damage and may parallel the progression of diabetic microvascular complications [21].
This study has several limitations that should be acknowledged. First, the single-center design may limit the external validity and generalizability of the findings to broader and more diverse populations. In addition, the inclusion of only overweight and obese patients may reduce the applicability of the results to lean individuals with type 2 diabetes. Second, the cross-sectional design does not allow causal relationships to be established between Sudoscan parameters and diabetic retinopathy severity. Another important limitation of this study is the absence of standardized retinal imaging documentation, such as fundus photography or optical coherence tomography, for independent image-based grading. Diabetic retinopathy diagnosis and classification were performed by an ophthalmologist based on clinical fundus examination, reflecting routine clinical practice. Although this approach ensures real-world applicability, the lack of standardized imaging may introduce interobserver variability and limit direct comparison with studies using photographic grading systems.
Moreover, diabetic retinopathy severity represents an ordinal outcome, and although linear regression was used for exploratory purposes, alternative ordinal regression models may provide additional insights in future studies. Additionally, diabetic retinopathy assessment was performed by a single ophthalmologist, which may introduce potential observer-related bias. Future multicenter, longitudinal studies are needed to validate these findings and further clarify the role of Sudoscan in risk stratification of patients with diabetic microvascular complications.
The present study expands existing knowledge by evaluating Sudoscan parameters alongside established clinical neuropathy scores in relation to diabetic retinopathy severity within a real-world clinical cohort. This integrative approach provides additional insight into the systemic nature of diabetic microvascular complications. Furthermore, the study contributes regional data from a Romanian population, which remains underrepresented in studies evaluating the association between sudomotor dysfunction and diabetic microvascular complications. These findings support the concept that combined autonomic and peripheral neuropathy assessment may contribute to comprehensive complication risk evaluation in patients with type 2 diabetes.
5. Conclusions
Sudoscan showed significant associations with the presence and severity of diabetic retinopathy in patients with type 2 diabetes. Although traditional ophthalmologic screening methods remain the gold standard, Sudoscan may represent a non-invasive complementary tool that could assist in identifying patients at increased risk of diabetic microvascular complications, including diabetic retinopathy.
Although fundus examinations remain the gold standard, the portability and non-invasiveness of Sudoscan make it particularly suitable for evaluation in rural areas or primary care settings with limited access to ophthalmologists [9].
Our findings are consistent with existing literature and suggest that Sudoscan parameters may contribute to risk stratification and clinical monitoring of patients with type 2 diabetes. Considering the moderate diagnostic performance observed, Sudoscan should be regarded as an adjunct rather than a replacement for established ophthalmologic screening techniques.
Further multicenter and longitudinal studies are needed to confirm these findings and to better define the role of Sudoscan in the integrated evaluation and monitoring of diabetic microvascular complications.
Author Contributions
Conceptualization, A.-E.N. and E.R.; methodology A.-E.N., C.D. and G.R.; software A.-E.N. and E.R.; validation, A.-E.N., C.D. and G.R.; formal analysis, A.-E.N. and E.R.; investigation, F.R., A.A.; resources, A.-E.N., E.R., C.D. and O.A.P.; data curation, C.S. and O.A.P.; writing—original draft preparation, A.-E.N. and E.R.; writing—review and editing, A.-E.N. and E.R., I.V.; visualization, F.R.; supervision, G.R.; project administration, A.-E.N.; funding acquisition, A.-E.N. All authors have read and agreed to the published version of the manuscript.
Funding
Publication of this paper was supported by the University of Medicine and Pharmacy Carol Davila, through the institutional program Publish not Perish.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board of “Nicolae Malaxa” Clinical Hospital, Bucharest, Romania (approval number 2145 on 7 March 2019).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Aggregated data supporting the conclusions of this study are available from the corresponding author upon reasonable request. Individual patient-level data are not publicly available due to privacy and institutional restrictions.
Acknowledgments
The authors would like to thank all study participants and the medical staff involved in patient evaluation and data collection.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| DR | Diabetic Retinopathy |
| T2DM | Type 2 Diabetes Mellitus |
| NPDR | Non-Proliferative Diabetic Retinopathy |
| PDR | Proliferative Diabetic Retinopathy |
| OCT | Optical Coherence Tomography |
| VEGF | Vascular Endothelial Growth Factor |
| BMI | Body Mass Index |
| HbA1c | Glycated Hemoglobin |
| ACR | Albumin-to-Creatinine Ratio |
| HDL | High-Density Lipoprotein |
| LDL | Low-Density Lipoprotein |
| eGFR | Estimated Glomerular Filtration Rate |
| CKD | Chronic Kidney Disease |
| CAN | Cardiovascular Autonomic Neuropathy |
| ECG | Electrocardiogram |
| CARTs | Cardiovascular Autonomic Reflex Tests |
| ESC | Electrochemical Skin Conductance |
| ROC | Receiver Operating Characteristic |
| CI | Confidence Interval |
| SD | Standard Deviation |
| IQR | Interquartile Range |
| FDA | Food and Drug Administration |
| MDRD | Modification of Diet in Renal Disease (equation) |
References
- Hashemi, H.; Rezvan, F.; Pakzad, R.; Ansaripour, A.; Heydarian, S.; Yekta, A.; Ostadimoghaddam, H.; Pakbin, M.; Khabazkhoob, M. Global and Regional Prevalence of Diabetic Retinopathy: A Comprehensive Systematic Review and Meta-Analysis. Semin. Ophthalmol. 2022, 37, 291–306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teo, Z.L.; Tham, Y.C.; Yu, M.; Chee, M.L.; Rim, T.H.; Cheung, N.; Bikbov, M.M.; Wang, Y.X.; Tang, Y.; Lu, Y.; et al. Global Prevalence of Diabetic Retinopathy and Projection of Burden through 2045: Systematic Review and Meta-Analysis. Ophthalmology 2021, 128, 1580–1591. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qi, X.; Zhu, Z.; Luo, H.; Schwartz, M.D.; Wu, B. Age at Diagnosis of Diabetes, Obesity, and the Risk of Dementia among Adult Patients with Type 2 Diabetes. PLoS ONE 2024, 19, e0310964. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, T.Y.; Tan, T.E. The Diabetic Retinopathy “Pandemic” and Evolving Global Strategies: The 2023 Friedenwald Lecture. Investig. Ophthalmol. Vis. Sci. 2023, 64, 47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- International Diabetes Federation. IDF Diabetes Atlas 2025. Available online: https://diabetesatlas.org/resources/idf-diabetes-atlas-2025/ (accessed on 17 June 2025).
- Wong, J.; Molyneaux, L.; Constantino, M.; Twigg, S.M.; Yue, D.K. Timing Is Everything: Age of Onset Influences Long-Term Retinopathy Risk in Type 2 Diabetes, Independent of Traditional Risk Factors. Diabetes Care 2008, 31, 1985–1990. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xiao, H.; Tang, J.; Zhang, F.; Liu, L.; Zhou, J.; Chen, M.; Li, M.; Wu, X.; Nie, Y.; Duan, J. Global Trends and Performances in Diabetic Retinopathy Studies: A Bibliometric Analysis. Front. Public Health 2023, 11, 1128008. [Google Scholar]
- Lin, K.; Wu, Y.; Liu, S.; Huang, J.; Chen, G.; Zeng, Q. The Application of Sudoscan for Screening Microvascular Complications in Patients with Type 2 Diabetes. PeerJ 2022, 10, e13089. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Novak, P. Electrochemical Skin Conductance: A Systematic Review. Clin. Auton. Res. 2019, 29, 17–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verdini, F.; Mengarelli, A.; Chemello, G.; Salvatori, B.; Morettini, M.; Göbl, C.; Tura, A. Sensors and Devices Based on Electrochemical Skin Conductance and Bioimpedance Measurements for the Screening of Diabetic Foot Syndrome: Review and Meta-Analysis. Biosensors 2025, 15, 73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vinik, A.I.; Erbas, T.; Casellini, C.M. Diabetic Cardiac Autonomic Neuropathy, Inflammation and Cardiovascular Disease. J. Diabetes Investig. 2013, 4, 4–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vittrant, B.; Ayoub, H.; Brunswick, P. From Sudoscan to Bedside: Theory, Modalities, and Application of Electrochemical Skin Conductance in Medical Diagnostics. Front. Neuroanat. 2024, 18, 1454095. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selvarajah, D.; Cash, T.; Davies, J.; Sankar, A.; Rao, G.; Grieg, M.; Pallai, S.; Gandhi, R.; Wilkinson, I.D.; Tesfaye, S. SUDOSCAN: A Simple, Rapid, and Objective Method with Potential for Screening for Diabetic Peripheral Neuropathy. PLoS ONE 2015, 10, e0138224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, M.; Chen, N.; Wang, Y.; Ni, J.; Lu, J.; Zhao, W.; Cui, Y.; Du, R.; Zhu, W.; Zhou, J. Association of Sudomotor Dysfunction with Risk of Diabetic Retinopathy in Patients with Type 2 Diabetes. Endocrine 2024, 84, 951–957. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oh, T.J.; Song, Y.; Jang, H.C.; Choi, S.H. SUDOSCAN in Combination with the Michigan Neuropathy Screening Instrument Is an Effective Tool for Screening Diabetic Peripheral Neuropathy. Diabetes Metab. J. 2022, 46, 319–326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- García-Ulloa, A.C.; Almeda-Valdes, P.; Cuatecontzi-Xochitiotzi, T.E.; Ramírez-García, J.A.; Díaz-Pineda, M.; Garnica-Carrillo, F.; González-Duarte, A.; Narayan, K.V.; Aguilar-Salinas, C.A.; Hernández-Jiménez, S. Detection of Sudomotor Alterations Evaluated by Sudoscan in Patients with Recently Diagnosed Type 2 Diabetes. BMJ Open Diabetes Res. Care 2022, 10, e003005. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- American Diabetes Association. 12. Retinopathy, Neuropathy, and Foot Care: Standards of Care in Diabetes—2024. Diabetes Care 2024, 47, S231–S243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vinik, A.I.; Nevoret, M.L.; Casellini, C.; Parson, H. Diabetic Neuropathy. Endocrinol. Metab. Clin. N. Am. 2013, 42, 747–787. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Orchard, T.J.; Forrest, K.Y.Z.; Ellis, D.; Becker, D.J. Cumulative Glycemic Exposure and Microvascular Complications in Insulin-Dependent Diabetes Mellitus: The Glycemic Threshold Revisited. Arch. Intern. Med. 1997, 157, 1851–1856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tesfaye, S.; Boulton, A.J.M.; Dyck, P.J.; Freeman, R.; Horowitz, M.; Kempler, P.; Lauria, G.; Malik, R.A.; Spallone, V.; Vinik, A.; et al. Diabetic Neuropathies: Update on Definitions, Diagnostic Criteria, Estimation of Severity, and Treatments. Diabetologia 2010, 53, 437–449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, A.G.; Russell, J.; Feldman, E.L.; Goldstein, J.; Peltier, A.; Smith, S.; Hamwi, J.; Pollari, D.; Bixby, B.; Howard, J.; et al. Lifestyle Intervention for Pre-Diabetic Neuropathy. Diabetes Care 2006, 29, 1294–1299. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.