


Abstract
Background: COVID-19 infection has been a major cause of hospitalization and mortality in the United States. Patients with liver cirrhosis may be especially vulnerable to severe outcomes of COVID-19 infection because of immune dysfunction, systemic inflammation, portal hypertension, and reduced physiological reserve. These factors can increase the risk of severe infection, multiorgan complications, and poor inpatient outcomes. Using the 2020–2022 United States National Inpatient Sample, this study evaluates the effect of cirrhosis among adults hospitalized with COVID-19. Methods: We performed a retrospective cohort study using the National Inpatient Sample (NIS) database. Adult hospitalizations with COVID-19 from 2020 to 2022 were included and stratified according to the presence or absence of cirrhosis. Using multivariable logistic regression analyses, we evaluated in-hospital mortality as the primary outcome. Secondary outcomes included the need for mechanical ventilation, septic shock, ARDS, ECMO utilization, acute kidney injury, renal replacement therapy, length of stay, and hospital charges. Results: A total of 5,934,565 hospitalized COVID-19 patients were included, of which 115,170 had concomitant cirrhosis. COVID-19 patients with cirrhosis had a higher in-hospital mortality than those without cirrhosis (16.8% vs. 11.3%; aOR 1.28; 95% CI 1.22–1.32). Patients with liver cirrhosis were also associated with higher odds of invasive mechanical ventilation, vasopressor use, and septic shock. Conclusions: Cirrhosis was independently associated with increased in-hospital mortality and complications including the need for invasive mechanical ventilation and septic shock in adults hospitalized with COVID-19. Although mortality associated with these patients has declined over time, they represent a high-risk group that requires close monitoring.
1. Introduction
Since its emergence in 2019, coronavirus disease 2019 (COVID-19), caused by severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), has become a major global health concern with significant morbidity and mortality [1]. Pre-existing chronic liver disease and cirrhosis may worsen the clinical course of COVID-19 by reducing physiological reserve and increasing susceptibility to infection, sepsis, renal dysfunction, multiorgan failure, prolonged hospitalization, and in-hospital mortality [2,3,4,5,6].
Liver cirrhosis is the end stage of chronic liver disease and is associated with progressive hepatic fibrosis, portal hypertension, impaired synthetic function, and reduced physiological reserve. In addition to hepatic dysfunction, cirrhosis is associated with immune dysregulation, systemic inflammation, bacterial translocation, and increased susceptibility to infections [5,6]. Patients with cirrhosis are therefore at higher risk for sepsis, septic shock, acute kidney injury requiring renal replacement therapy, and multiorgan failure during acute illnesses. Identifying these complications is clinically important because infections and systemic inflammatory states are common causes of decompensation and death in patients with cirrhosis [5,6].
Severe COVID-19 can lead to hypoxemic respiratory failure, cytokine-mediated inflammation, endothelial dysfunction, microvascular thrombosis, shock, acute kidney injury and sepsis-related multiorgan dysfunction [2,3]. In patients with cirrhosis, these acute systemic insults may precipitate hepatic decompensation and worsen already limited physiological reserve [2,3,5,6]. Furthermore, many patients with cirrhosis have coexisting conditions and risk factors, such as alcohol-related liver disease, metabolic syndrome, diabetes mellitus, chronic kidney disease, cardiovascular disease, malnutrition, and socioeconomic barriers to care. These factors may further increase the risk of severe inpatient outcomes when patients with cirrhosis are hospitalized with COVID-19 infection [4,7,8].
In the United States, large-scale national data evaluating the impact of cirrhosis on a broad range of inpatient outcomes among adults hospitalized with COVID-19 across the 2020–2022 pandemic period remain limited. Several observational studies, registry-based analyses, and meta-analyses have suggested that patients with cirrhosis and COVID-19 have higher rates of mortality compared with patients without cirrhosis [4,7,8]. Some studies have also shown that the severity of underlying liver disease is associated with worse outcomes in COVID-19 infection [4,8]. However, many earlier studies were limited by small sample sizes, selected registry populations, single center or multicenter cohorts, international variation in patient care, or a focus on the early pandemic period [6,7,8]. In addition, the clinical outcomes of COVID-19 changed over time because of vaccination, evolving treatment protocols, the availability of antiviral and immunomodulatory therapies, and the emergence of different SARS-CoV-2 variants [1,3].
Prior large-database analyses evaluated selected liver disease etiologies, including alcohol-associated liver disease, nonalcoholic steatohepatitis, alcoholic cirrhosis, and nonalcoholic steatohepatitis cirrhosis, among hospitalized patients with COVID-19; however, broader multi-year national data evaluating all-cause cirrhosis and multiple inpatient outcomes remain limited [9,10,11]. The National Inpatient Sample database, which is the largest all-payer inpatient database in the United States, includes hospitalizations from non-federal acute-care hospitals across different geographic regions, hospital sizes, and teaching settings [12]. We conducted a retrospective cohort study using the 2020–2022 National Inpatient Sample (NIS) database to evaluate the impact of liver cirrhosis on outcomes among adults hospitalized with COVID-19 infection.
2. Methods
2.1. Study Design and Data Source
We conducted a retrospective cohort study using the National Inpatient Sample (NIS) database covering the period from 1 January 2020 to 31 December 2022. The NIS is the largest publicly available all-payer inpatient database in the United States. The term ‘all-payer’ indicates that the database includes hospitalizations covered by Medicare, Medicaid, private insurance, as well as uninsured/self-pay hospitalizations. The NIS is derived from billing data submitted by hospitals to statewide data organizations across the United States and includes data from states representing more than 97% of the U.S. population.
2.2. Study Population
Patients admitted between January 2020 and December 2022 were included with the diagnosis of COVID-19 infection and cirrhosis, identified through International Classification of Diseases, 10th revision (ICD-10) codes. COVID-19 infection was identified using code U07.1, and cases were further stratified based on presence or absence of cirrhosis, which was identified by codes K70.30, K70.31, K74.60, K74.69, K74.3, K74.4, K74.5.
2.3. Outcomes and Variables
The main aim of this study was to investigate the impact of cirrhosis on COVID-19 infection. The primary outcome was in-hospital mortality among hospitalized patients with cirrhosis. Secondary outcomes included need for invasive mechanical ventilation and non-invasive ventilation (NIV), length of hospital stay (LOS) in days, acute kidney injury (AKI), septic shock, acute respiratory distress syndrome (ARDS), as well as needs for renal replacement therapy (RRT), vasopressors, and extracorporeal membrane oxygenation use (ECMO).
Patient-level variables included baseline demographic characteristics such as age, sex, race, median household income, and primary insurance payer. The comorbidity burden was assessed using the Charlson Comorbidity Index, which categorizes patients by the number and severity of their conditions (categorized as 0, 1, 2, ≥3). Hospital-level characteristics included geographic region, hospital location/teaching status, and hospital bed size.
2.4. Statistical Analysis
The patient information and data were analyzed using Stata/BE version 17.0 (StataCorp LLC, College Station, TX, USA). Since the NIS uses a complex design that incorporates stratification, clustering, and weighting of patient- and hospital-level data, this structure was accounted for throughout to generate nationally representative estimates, with comparisons made through survey-weighted linear regression and adjusted Wald tests. For categorical/dichotomous variables, we reported weighted percentages and applied the Rao–Scott corrected chi-square test. Initially, survey-weighted univariable regression analyses were performed to estimate crude associations between concurrent COVID-19 infection and each outcome. We then built survey-weighted multivariable logistic regression analyses to calculate adjusted odds ratios for mortality, invasive ventilation, non-invasive ventilation, vasopressors, septic shock, AKI, RRT, ARDS, and ECMO, while adjusted mean difference for length of stay and total charges were examined using survey-weighted multivariable linear regression analyses. Because length of stay and total hospital charges may have right-skewed distributions, sensitivity analyses were performed using log-transformed length of stay and a survey-weighted generalized linear model with a gamma distribution and log link for total hospital charges. All multivariable models adjusted for age, sex, race, median household income quartile, insurance status, and modified Charlson Comorbidity Index, excluding liver disease, hospital region, hospital location/teaching status, hospital bed size, hospital division, and calendar year. Differences in mortality across calendar years were evaluated using survey-weighted analyses. To assess whether the association between cirrhosis and in-hospital mortality varied over time, we additionally fitted a survey-weighted multivariable logistic regression model including an interaction term between cirrhosis and calendar year. Adjusted year-specific mortality probabilities were subsequently estimated using predictive margins. A p-value < 0.05 was considered statistically significant.
2.5. Ethical Considerations
The NIS contains de-identified, discharge-level data. Because this study used a publicly available de-identified database, institutional review board approval and individual informed consent were not required.
3. Results
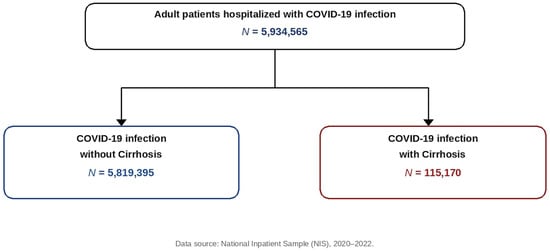
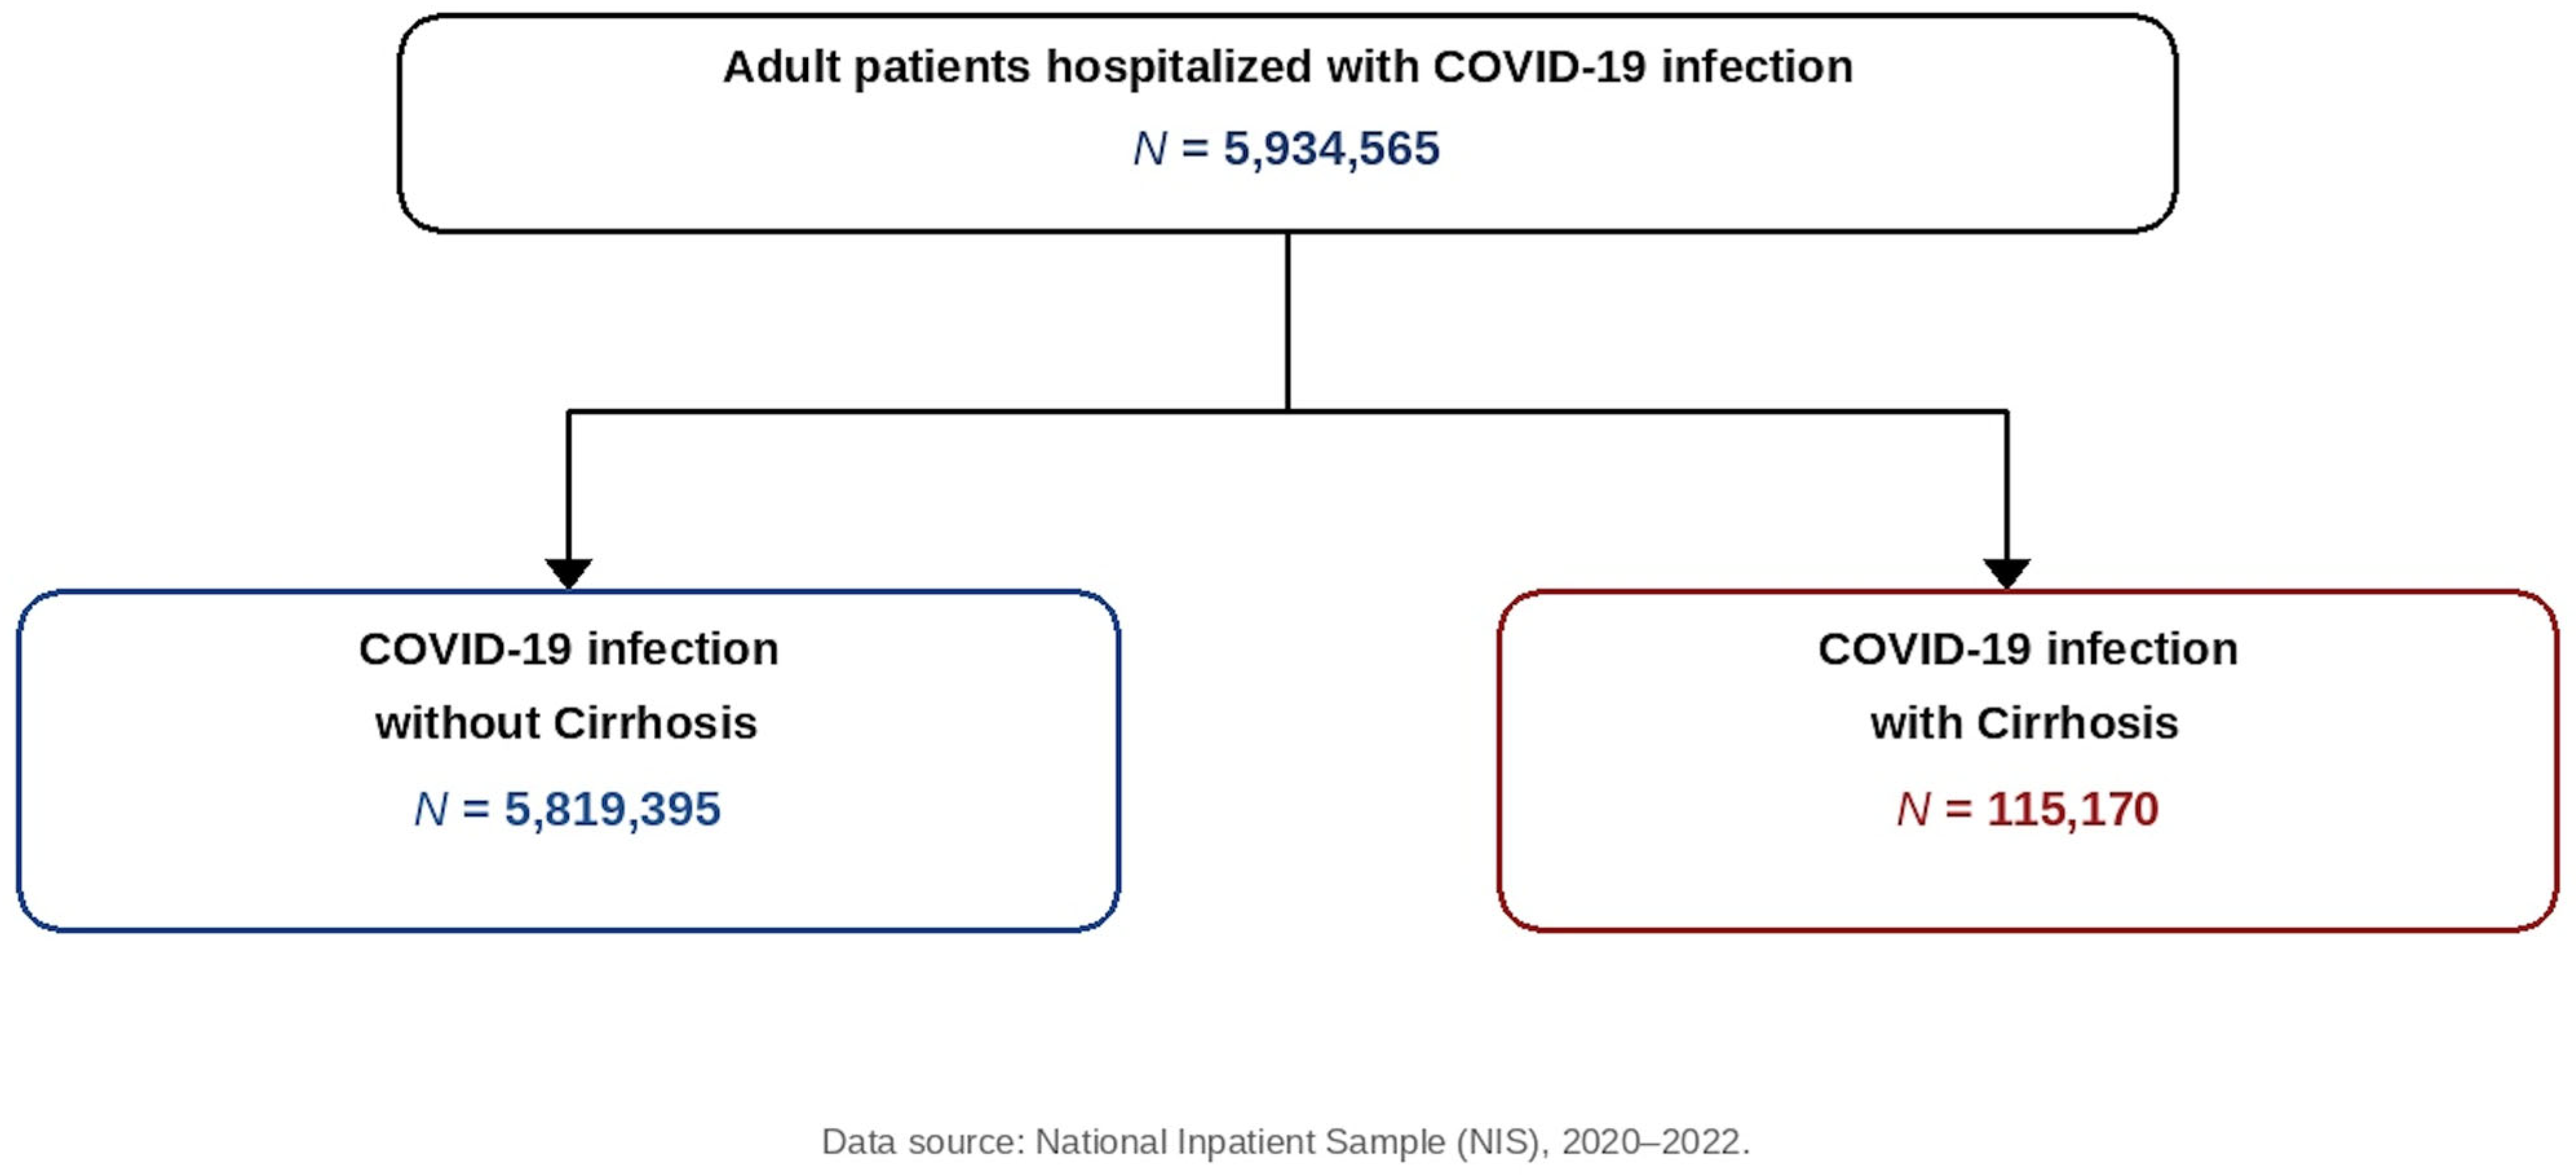
A total of 5,934,565 weighted adult COVID-19 hospitalizations and 2,478,514 weighted adult hospitalizations with cirrhosis were identified from the 2020–2022 National Inpatient Sample database. Patients hospitalized with COVID-19 were stratified according to the presence of cirrhosis; 115,170 had concomitant cirrhosis, whereas 5,819,395 did not have cirrhosis (Figure 1). Baseline demographic and hospital characteristics are summarized in Table 1. Patients with COVID-19 and concomitant cirrhosis had a mean age of 62.1 years compared with 62.7 years among those without cirrhosis. Males accounted for a greater proportion of hospitalizations among patients with cirrhosis (58.3% vs. 50.6%). Caucasians constituted the largest racial group in both cohorts (59.6% vs. 59.9%). The largest proportion of patients belonged to the lowest household income quartile (35.8% vs. 32.1%), followed by the second income quartile (26.5% vs. 26.9%). Medicare was the most common primary payer in patients with cirrhosis (52.7% vs. 53.4%), followed by private insurance (17.9% vs. 27.2%). Most patients had a Charlson Comorbidity Index of ≥3 (76.9% vs. 31.0%). Most hospitalizations occurred in the southern region (38.5% vs. 41.8%), followed by the west (25.3% vs. 18.9%). Most patients were admitted to urban teaching hospitals (75.0% vs. 70.3%), followed by urban non-teaching hospitals (17.2% vs. 19.0%), and to large hospitals (49.5% vs. 45.4%), followed by medium-sized hospitals (29.2% vs. 29.2%). Among hospital divisions, the South Atlantic accounted for the largest proportion of admissions (19.1% vs. 22.0%), followed by the Pacific (17.0% vs. 12.3%).
Figure 1.
Study population flow diagram.
Table 1.
Demographic and clinical characteristics of hospitalized patients with COVID-19 infection, stratified by cirrhosis.
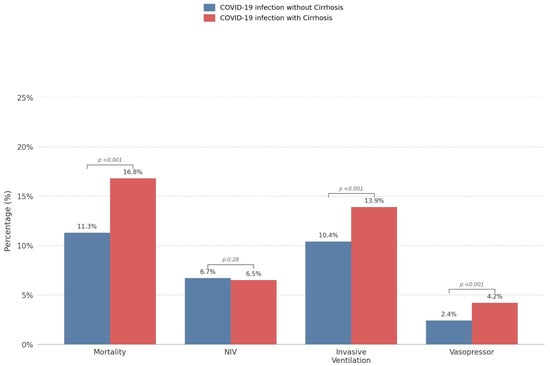
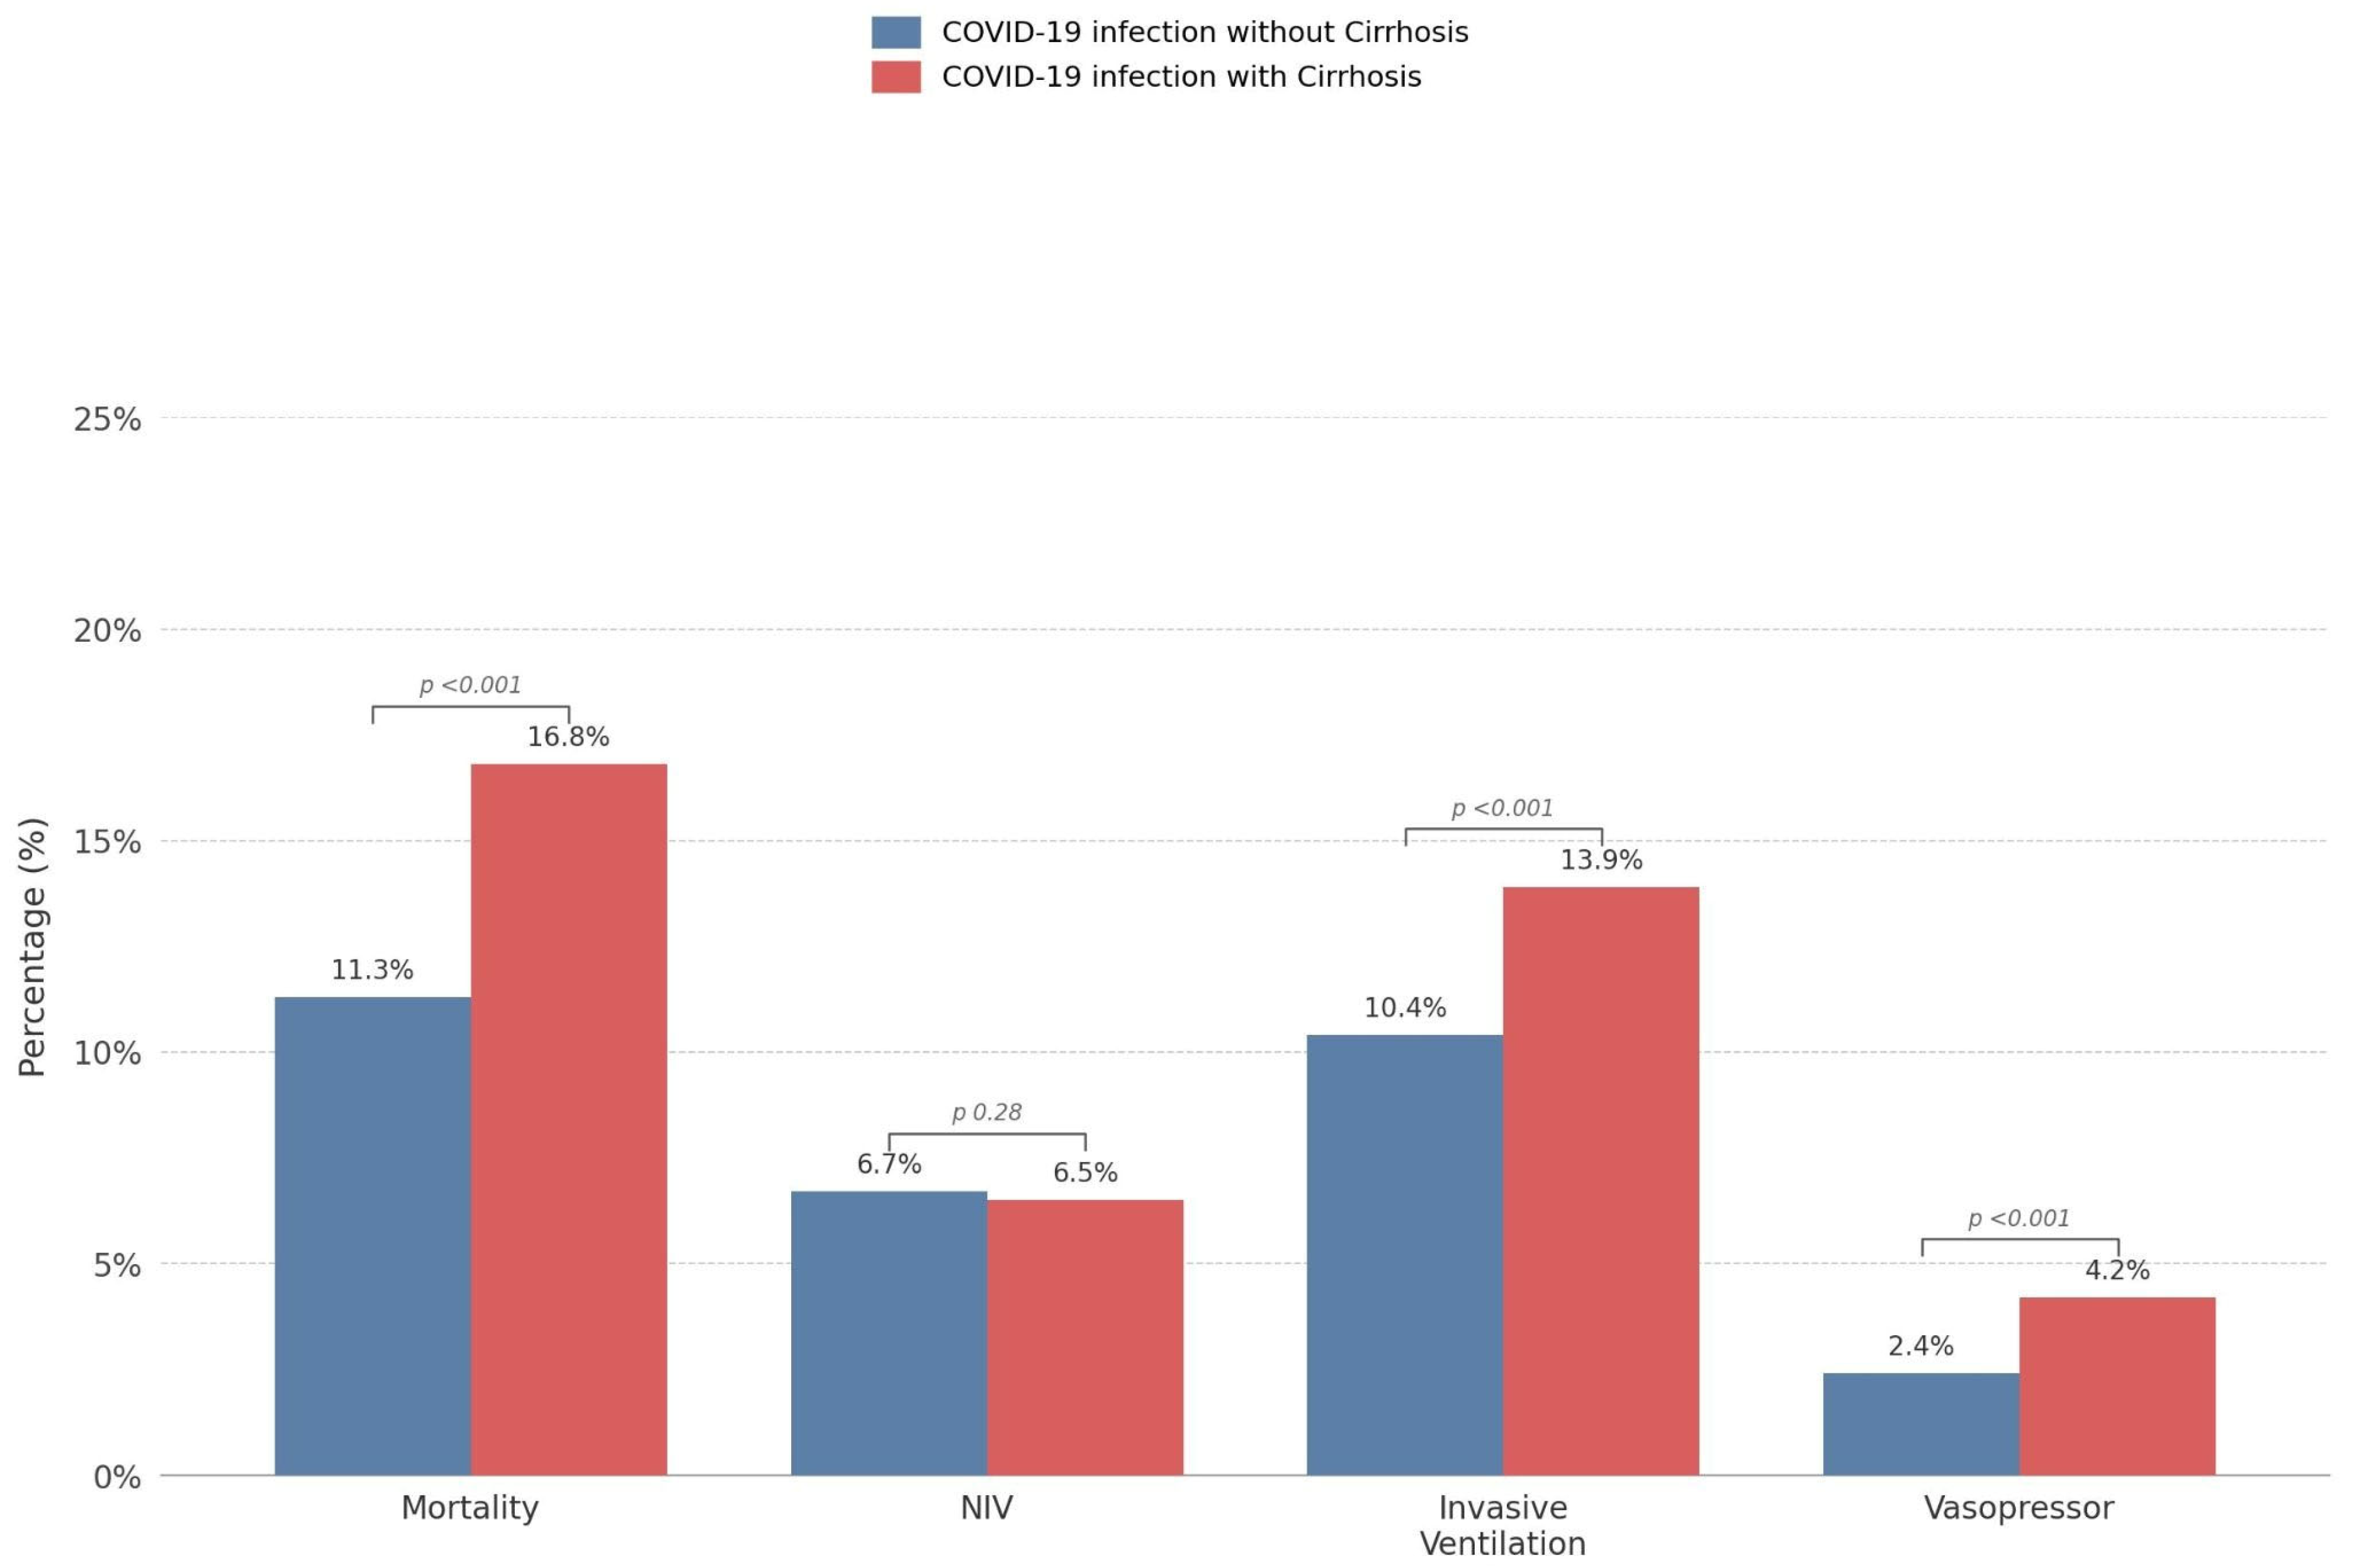
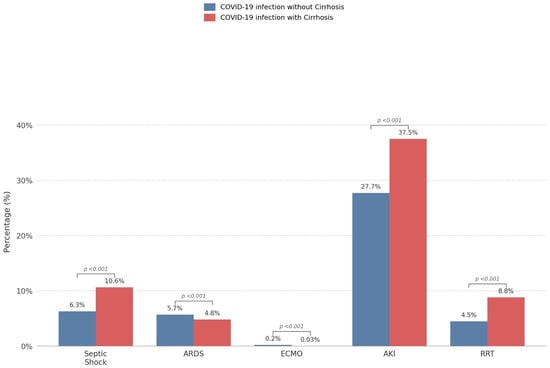
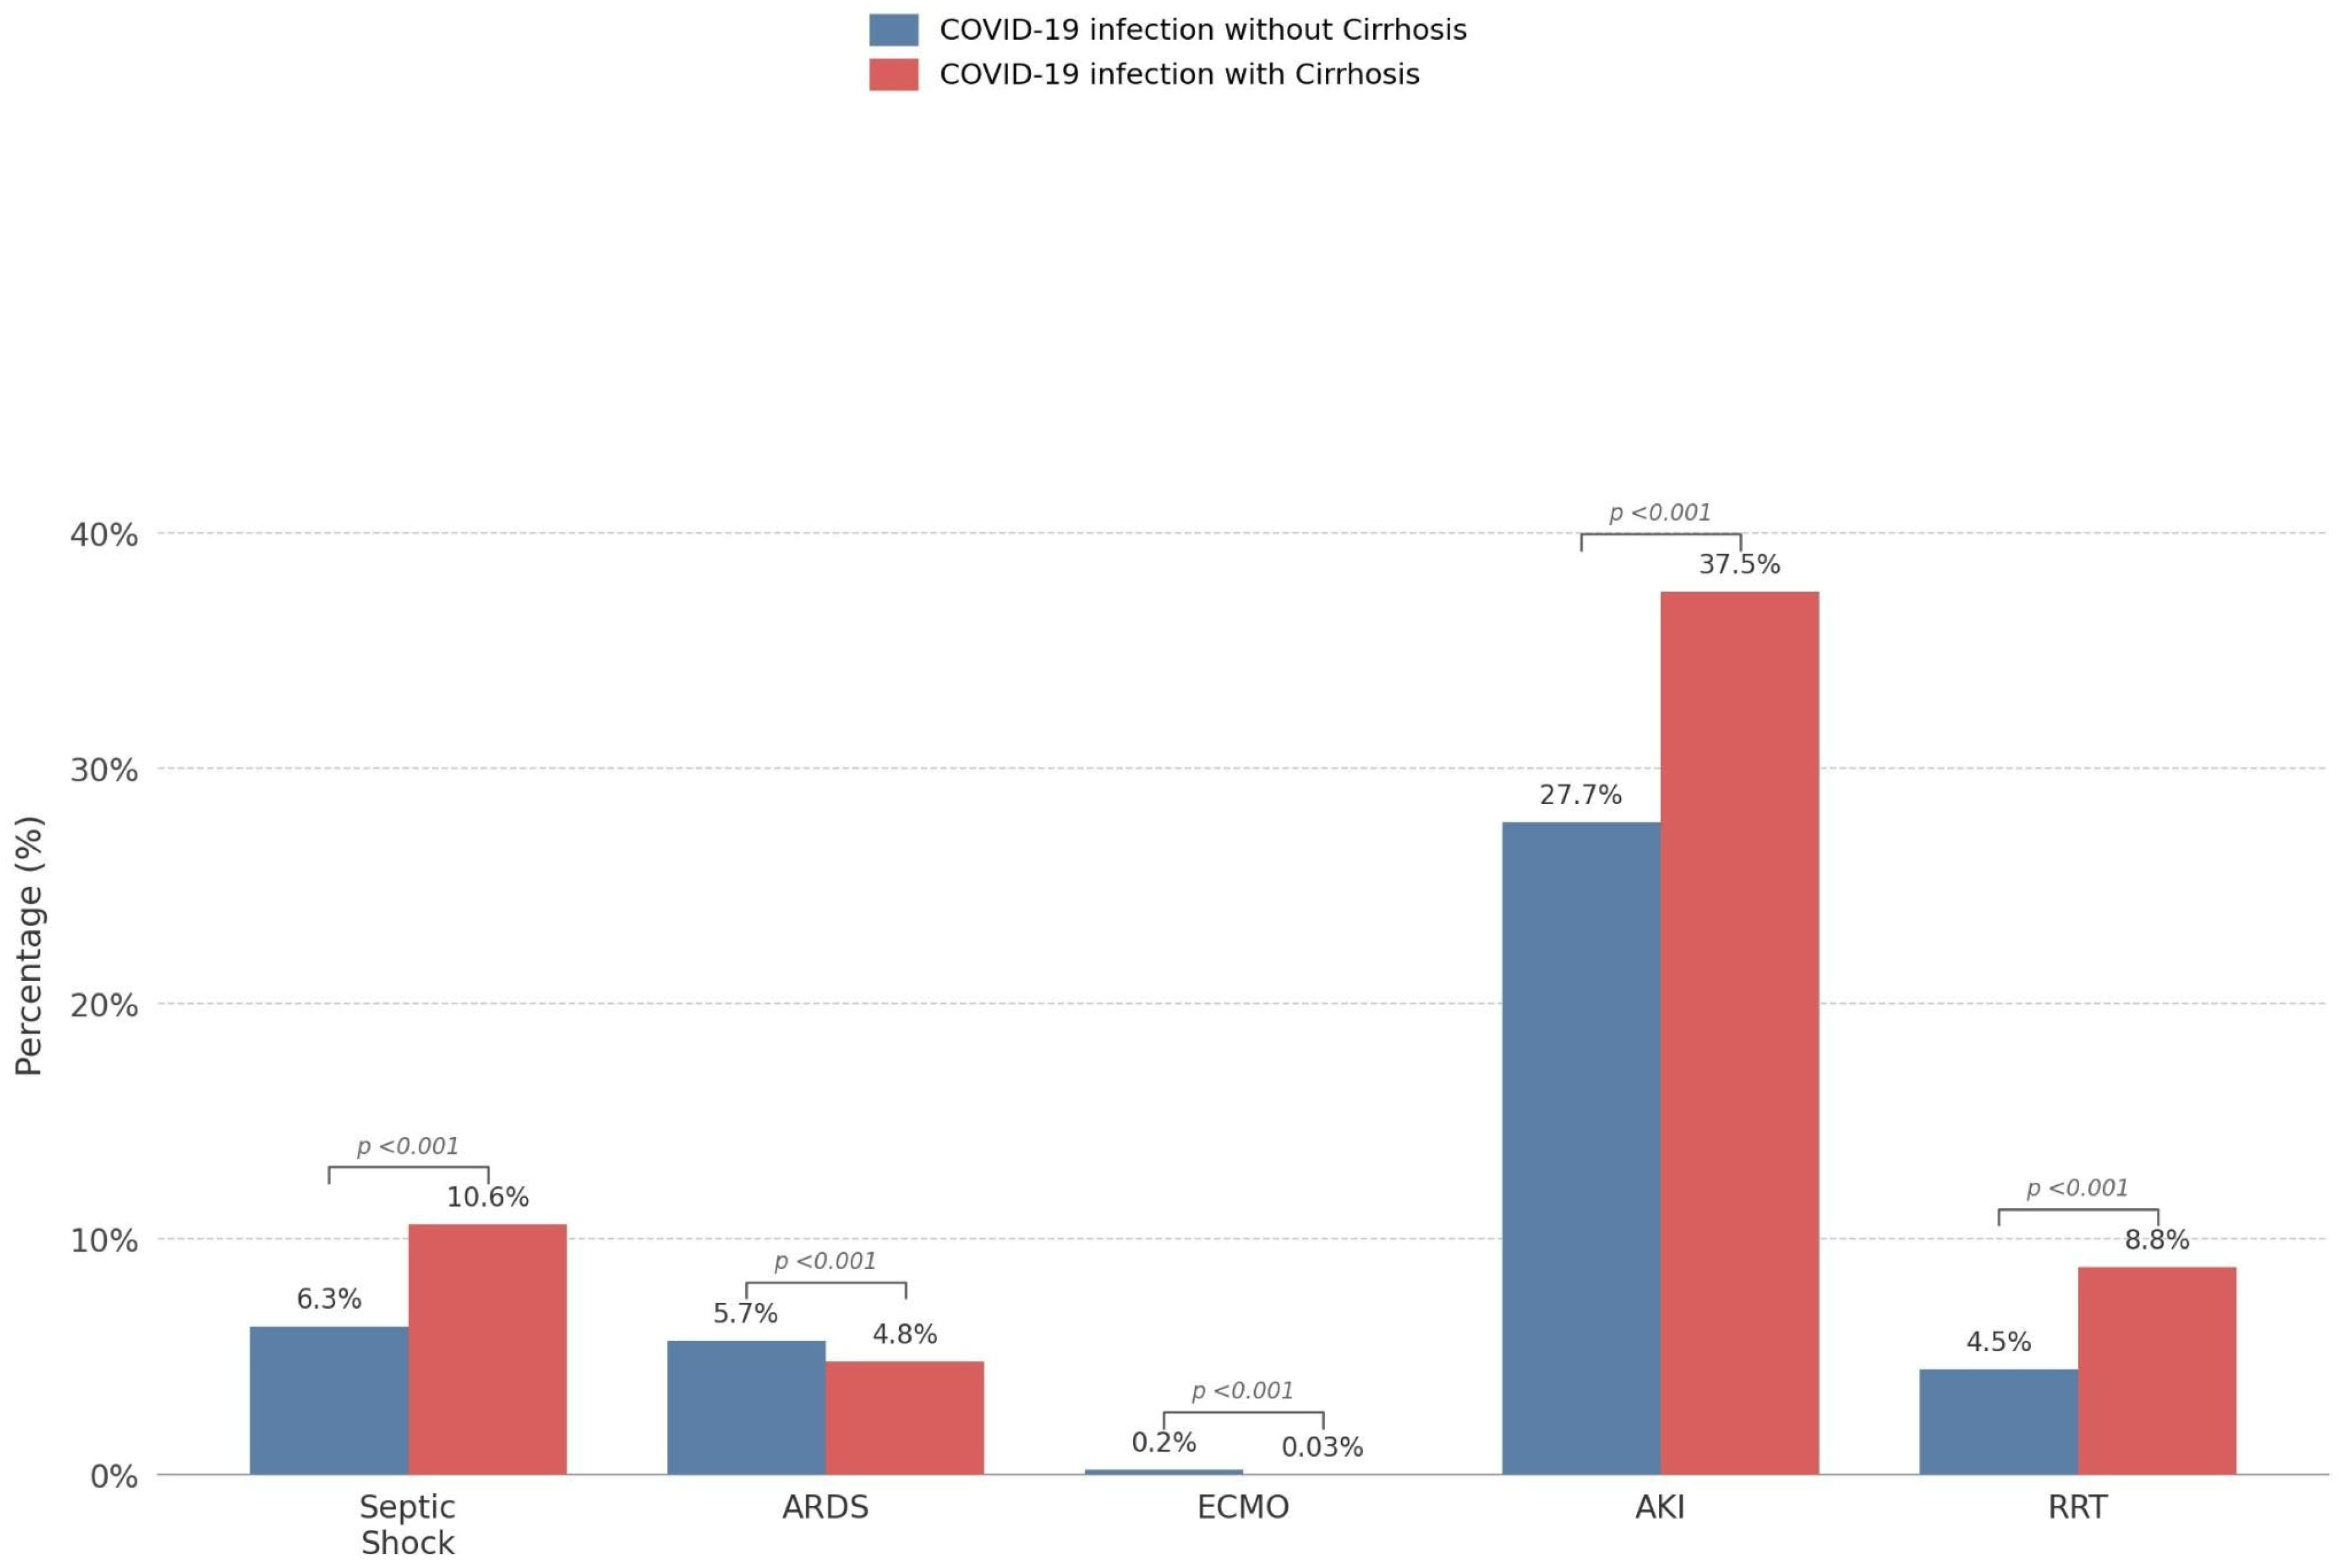
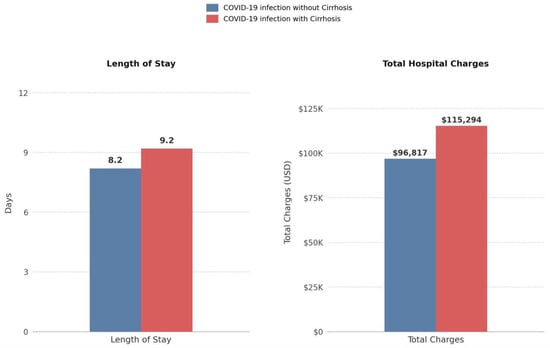
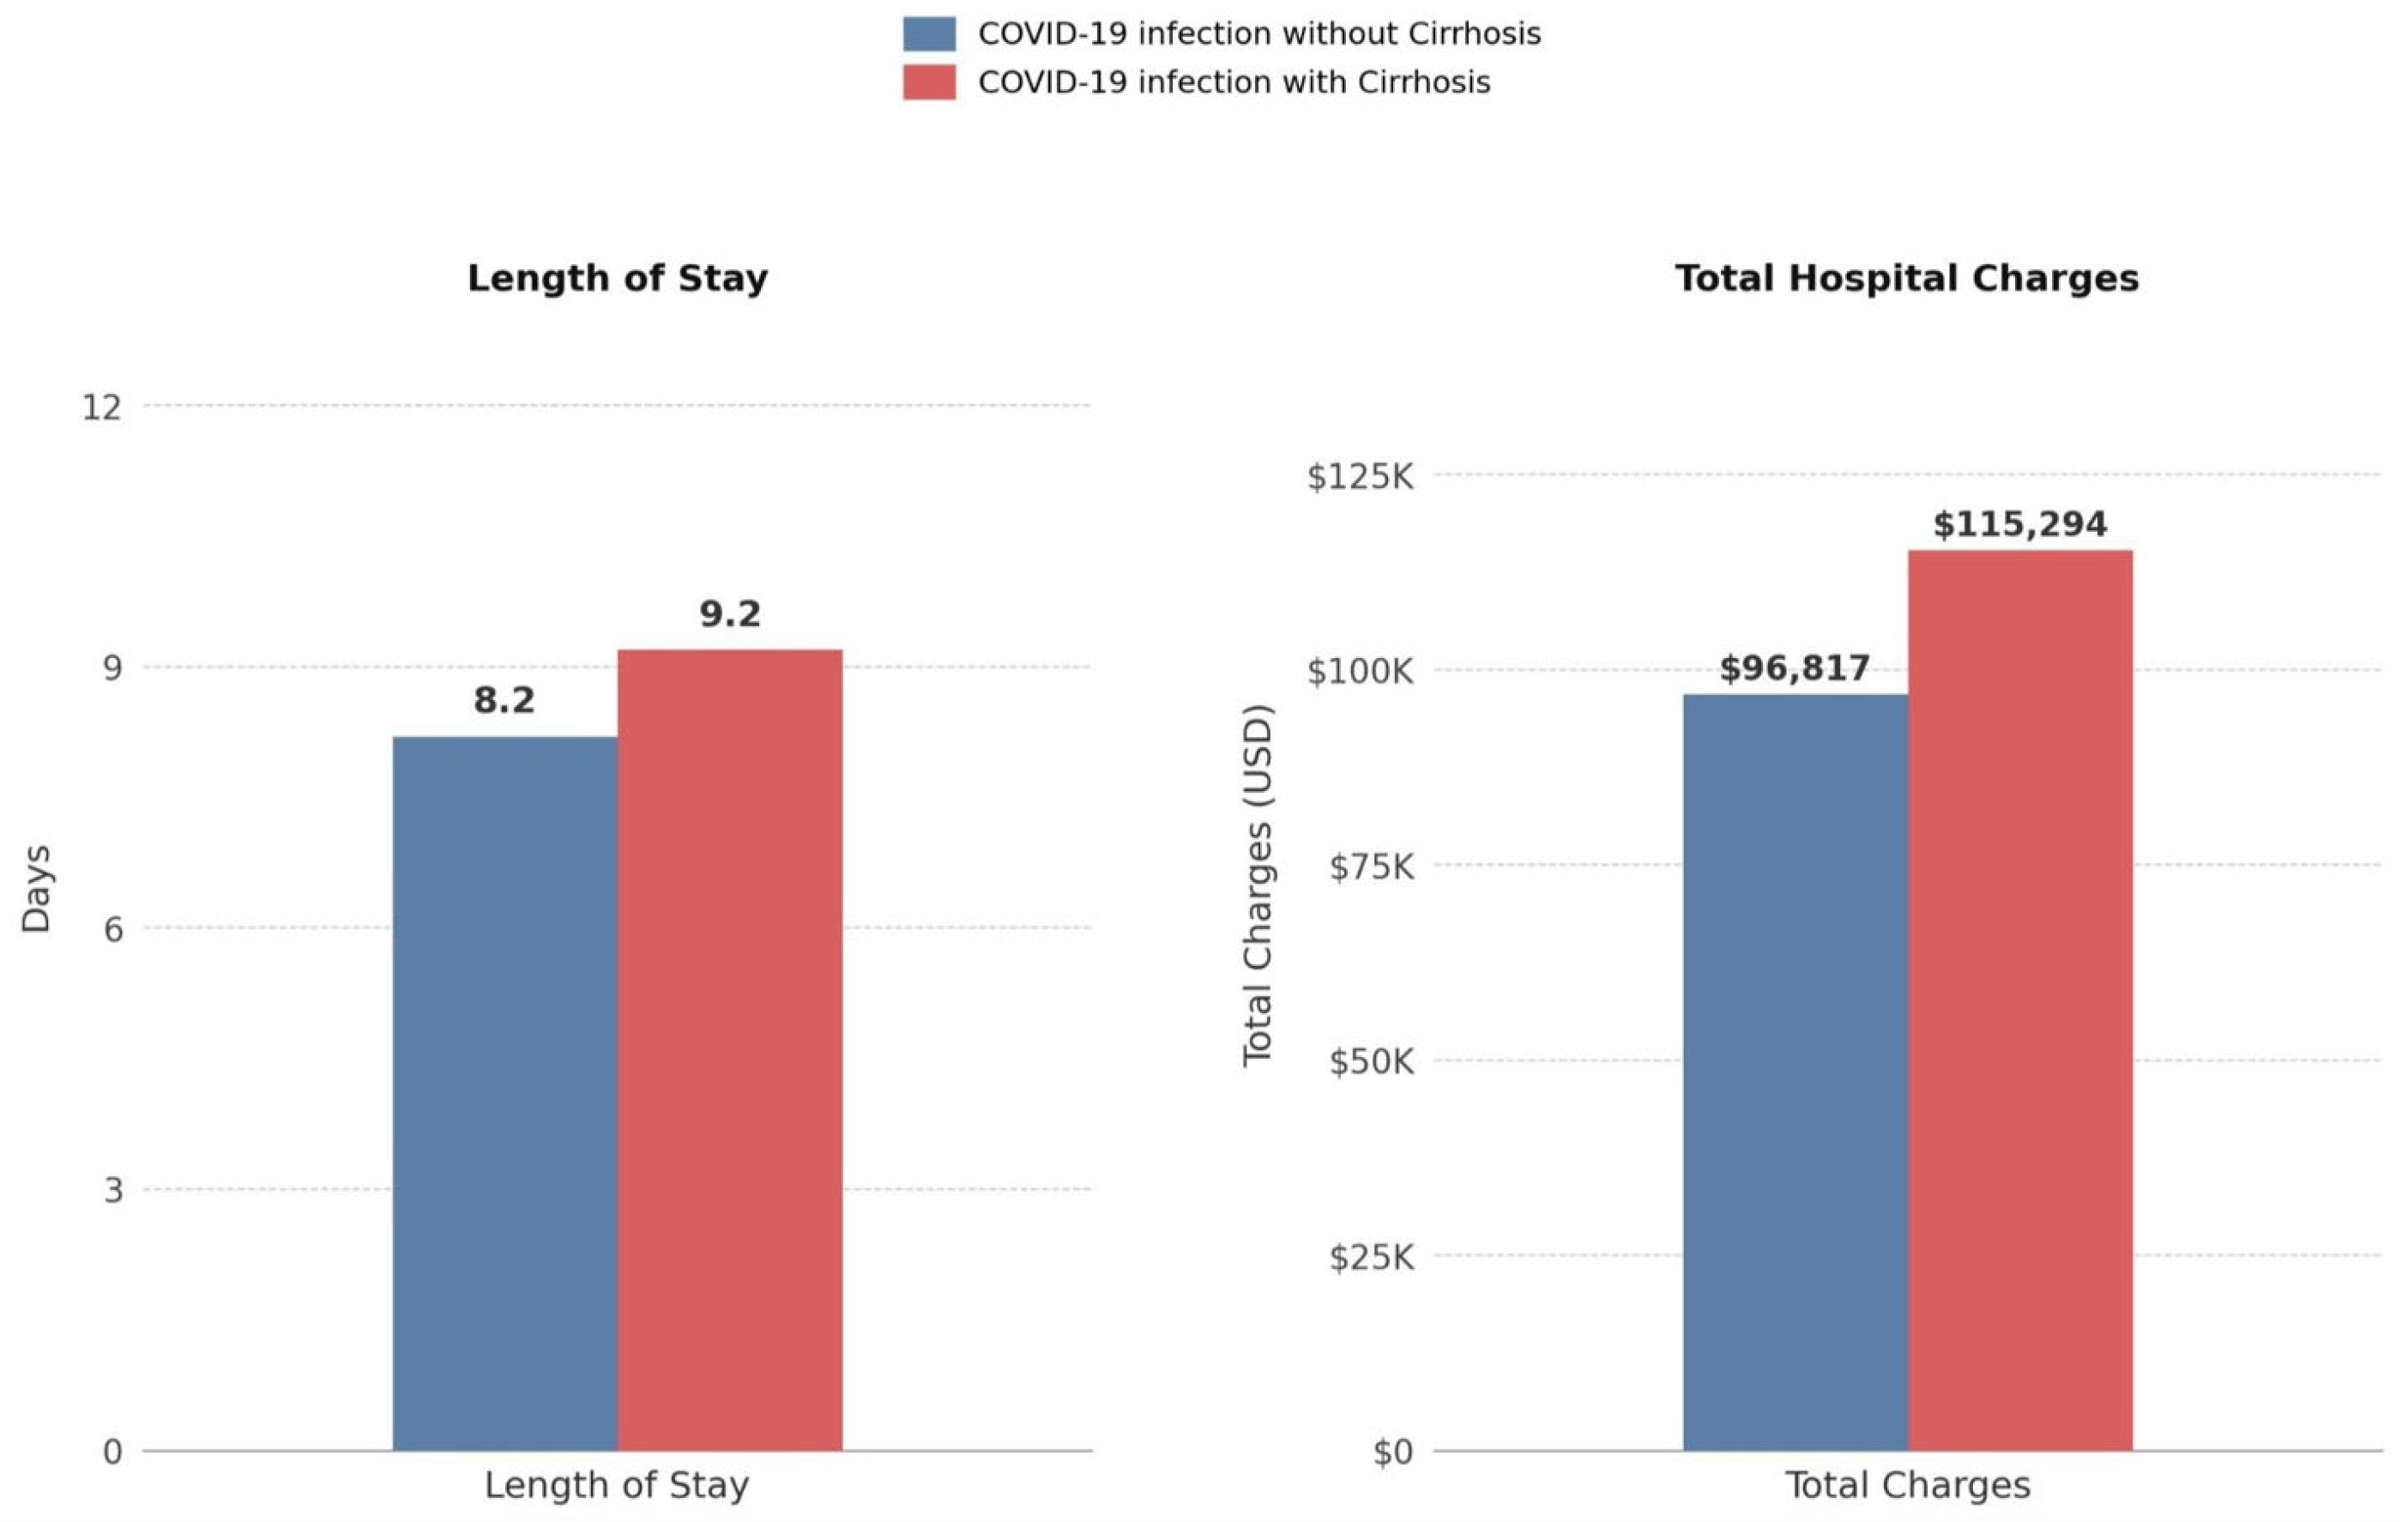
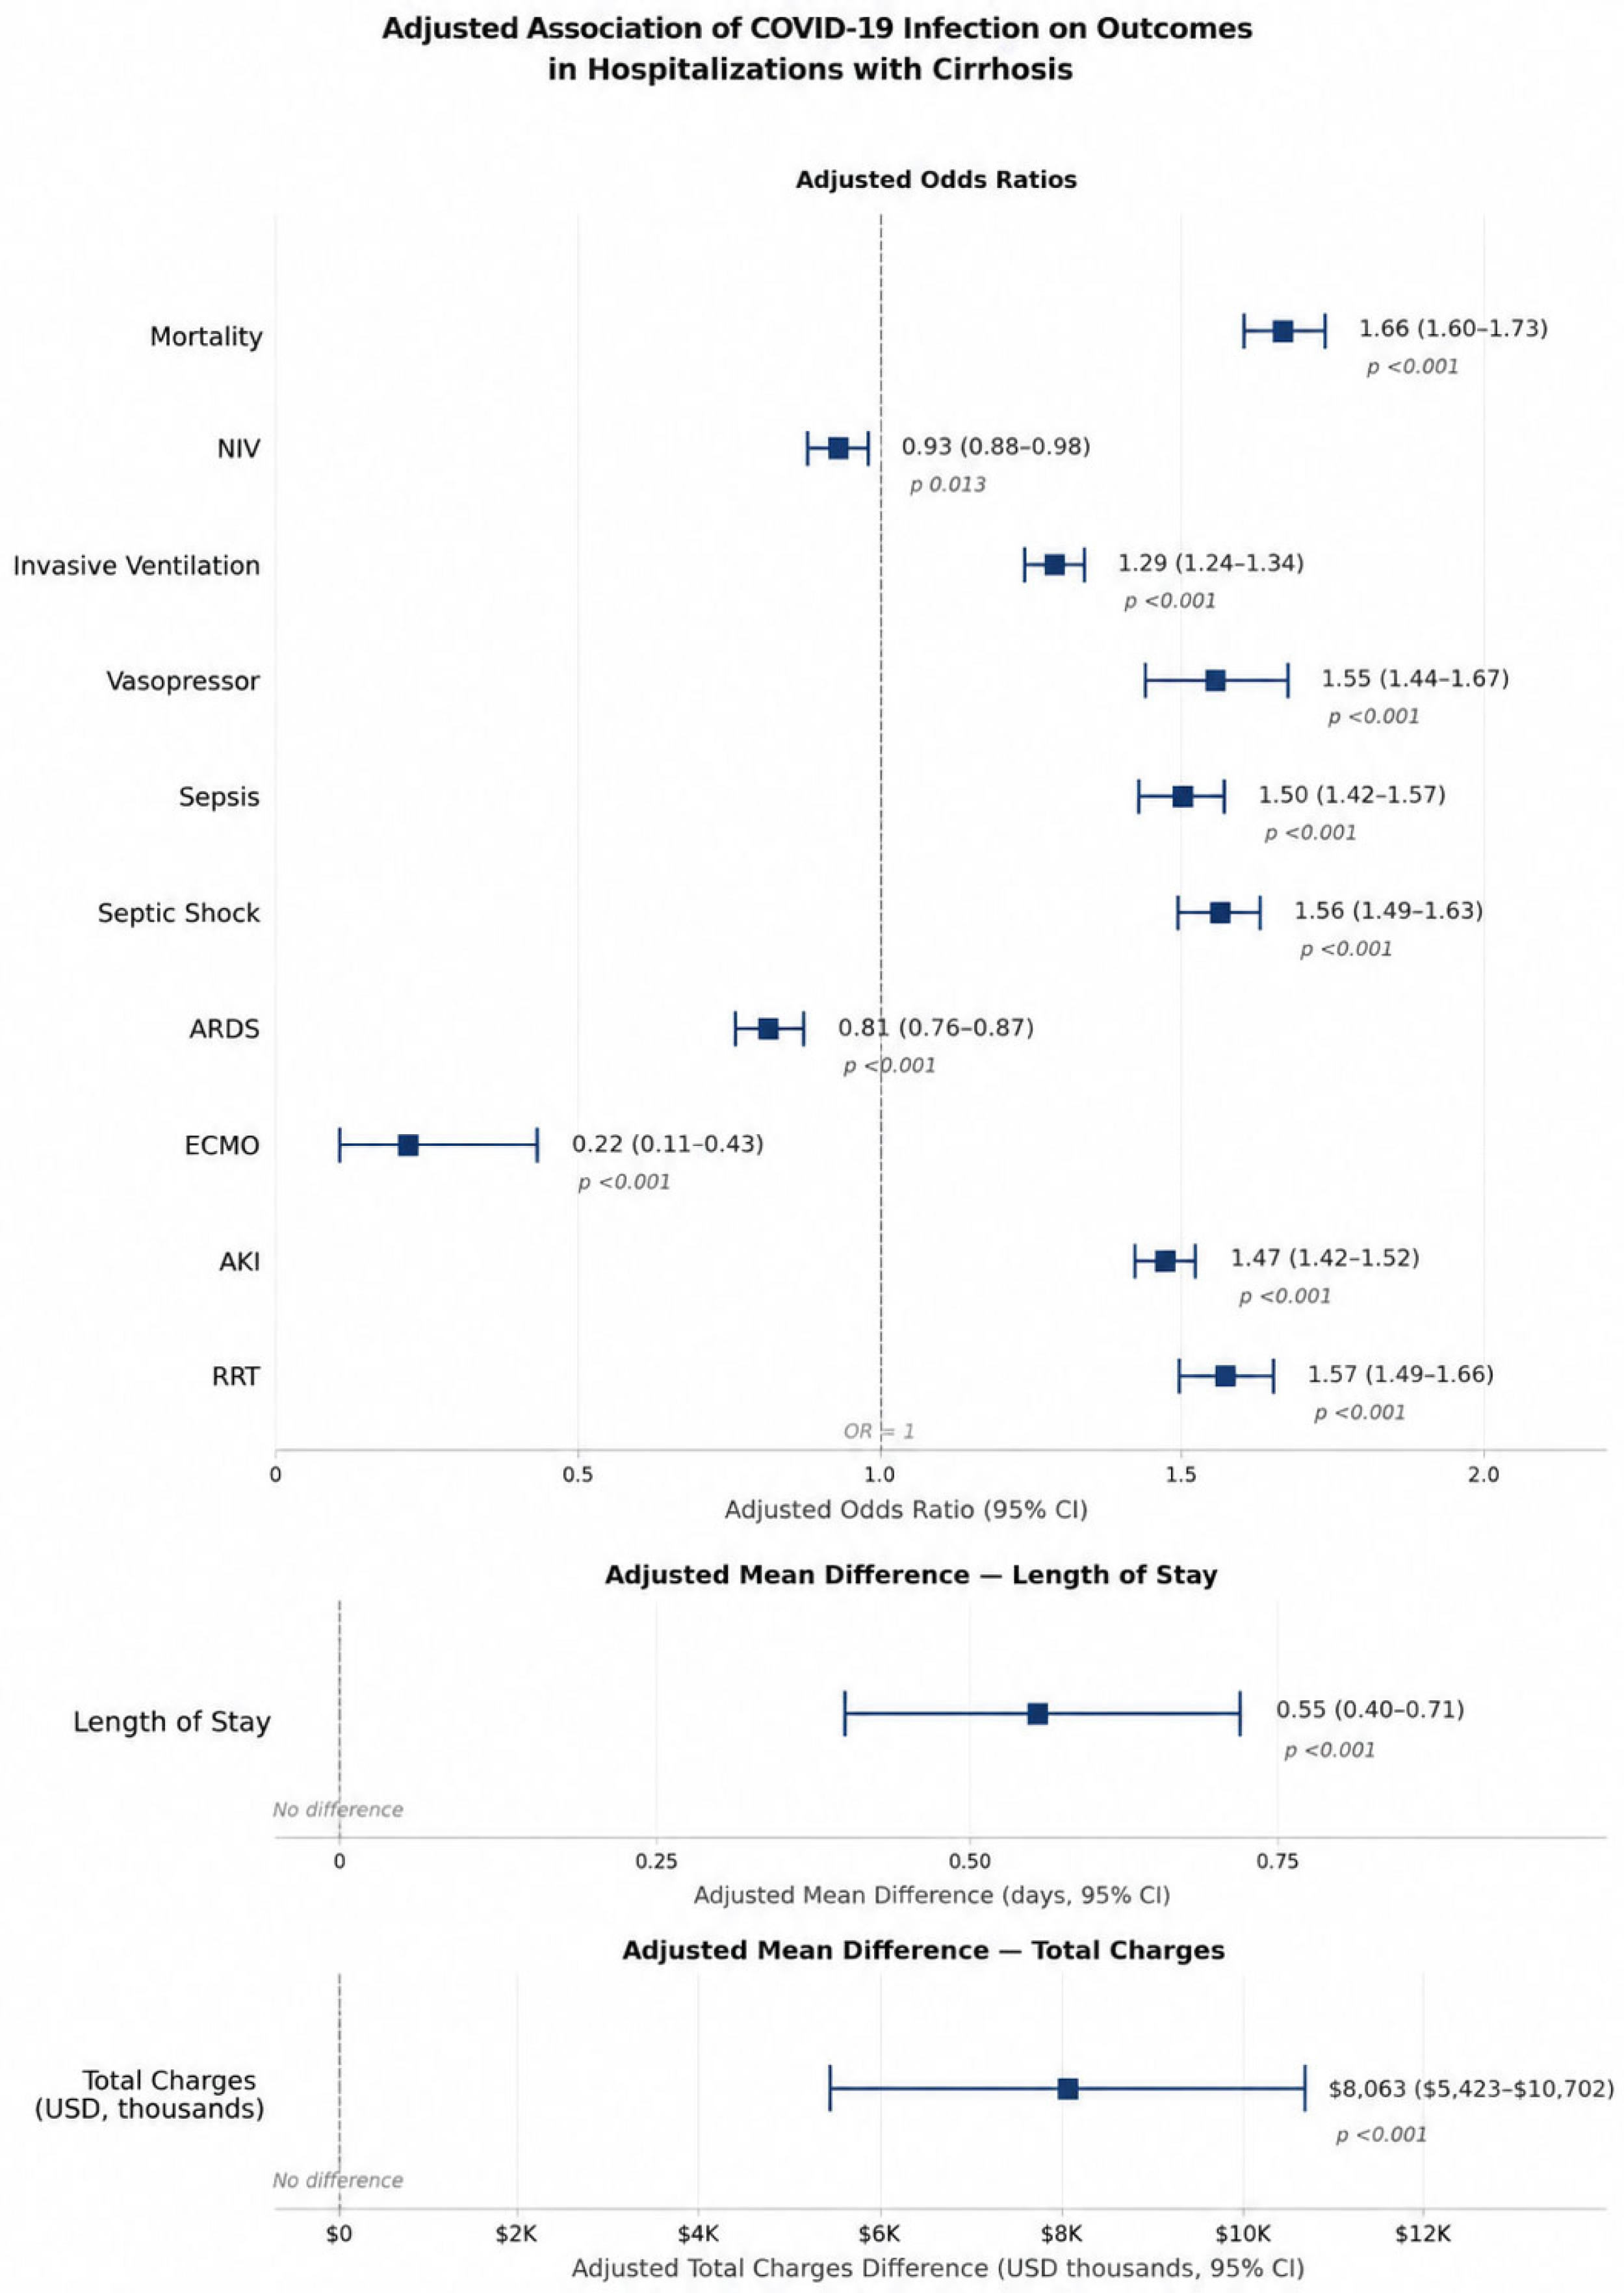
Compared with patients hospitalized with COVID-19 without cirrhosis, those with concomitant cirrhosis had higher in-hospital mortality (16.8% vs. 11.3%; aOR 1.28, 95% CI 1.22–1.32), invasive ventilation (13.9% vs. 10.4%; aOR 1.04, 95% CI 1.003–1.09), vasopressor use (4.2% vs. 2.4%; aOR 1.24, 95% CI 1.14–1.33), and septic shock (10.6% vs. 6.3%; aOR 1.24, 95% CI 1.18–1.30) (Figure 2 and Figure 3). Patients with COVID-19 and cirrhosis had higher unadjusted rates of acute kidney injury (37.5% vs. 27.7%) and renal replacement therapy (8.8% vs. 4.5%). After adjustment, cirrhosis was not independently associated with AKI (aOR 0.99, 95% CI 0.95–1.02) and was associated with lower odds of RRT (aOR 0.81, 95% CI 0.76–0.85). Patients with cirrhosis also demonstrated lower adjusted odds of NIV use (6.5% vs. 6.7%; aOR 0.77, 95% CI 0.73–0.82), ARDS (4.8% vs. 5.7%; aOR 0.73, 95% CI 0.68–0.78), and ECMO utilization (0.03% vs. 0.2%; aOR 0.19, 95% CI 0.10–0.39) (Figure 2 and Figure 3). Patients with cirrhosis had longer unadjusted hospital stays and higher unadjusted hospitalization charges. After multivariable adjustment, cirrhosis remained associated with a longer length of stay (adjusted mean difference 0.55 days, 95% CI 0.40–0.71) and higher total hospital charges (adjusted mean difference 8063 USD, 95% CI 5423–10,702 USD) (Figure 4 and Figure 5). Sensitivity analyses using log-transformed length of stay and a gamma-generalized linear model for hospital charges produced directionally consistent results (Supplementary Table S1).
Figure 2.
Clinical outcomes comparing mortality, non-invasive ventilation (NIV), invasive ventilation, and vasopressor use in patients with COVID-19 infection, with and without liver cirrhosis.
Figure 3.
Clinical outcomes comparing septic shock, acute respiratory distress syndrome (ARDS), extracorporeal membrane oxygenation (ECMO), acute kidney injury (AKI), and renal replacement therapy (RRT) in patients with COVID-19 infection, with and without liver cirrhosis.
Figure 4.
Length of hospital stay and total hospital cost for patients hospitalized with COVID-19 infection, with and without liver cirrhosis.
Figure 5.
Forest plot depicting adjusted odds ratios for mortality, non-invasive ventilation (NIV), invasive ventilation, vasopressor use, septic shock, acute respiratory distress syndrome (ARDS), extracorporeal membrane oxygenation (ECMO), acute kidney injury (AKI), renal replacement therapy (RRT), and adjusted mean differences for hospital length of stay and total hospital charges for patients with COVID-19 infection with liver cirrhosis.
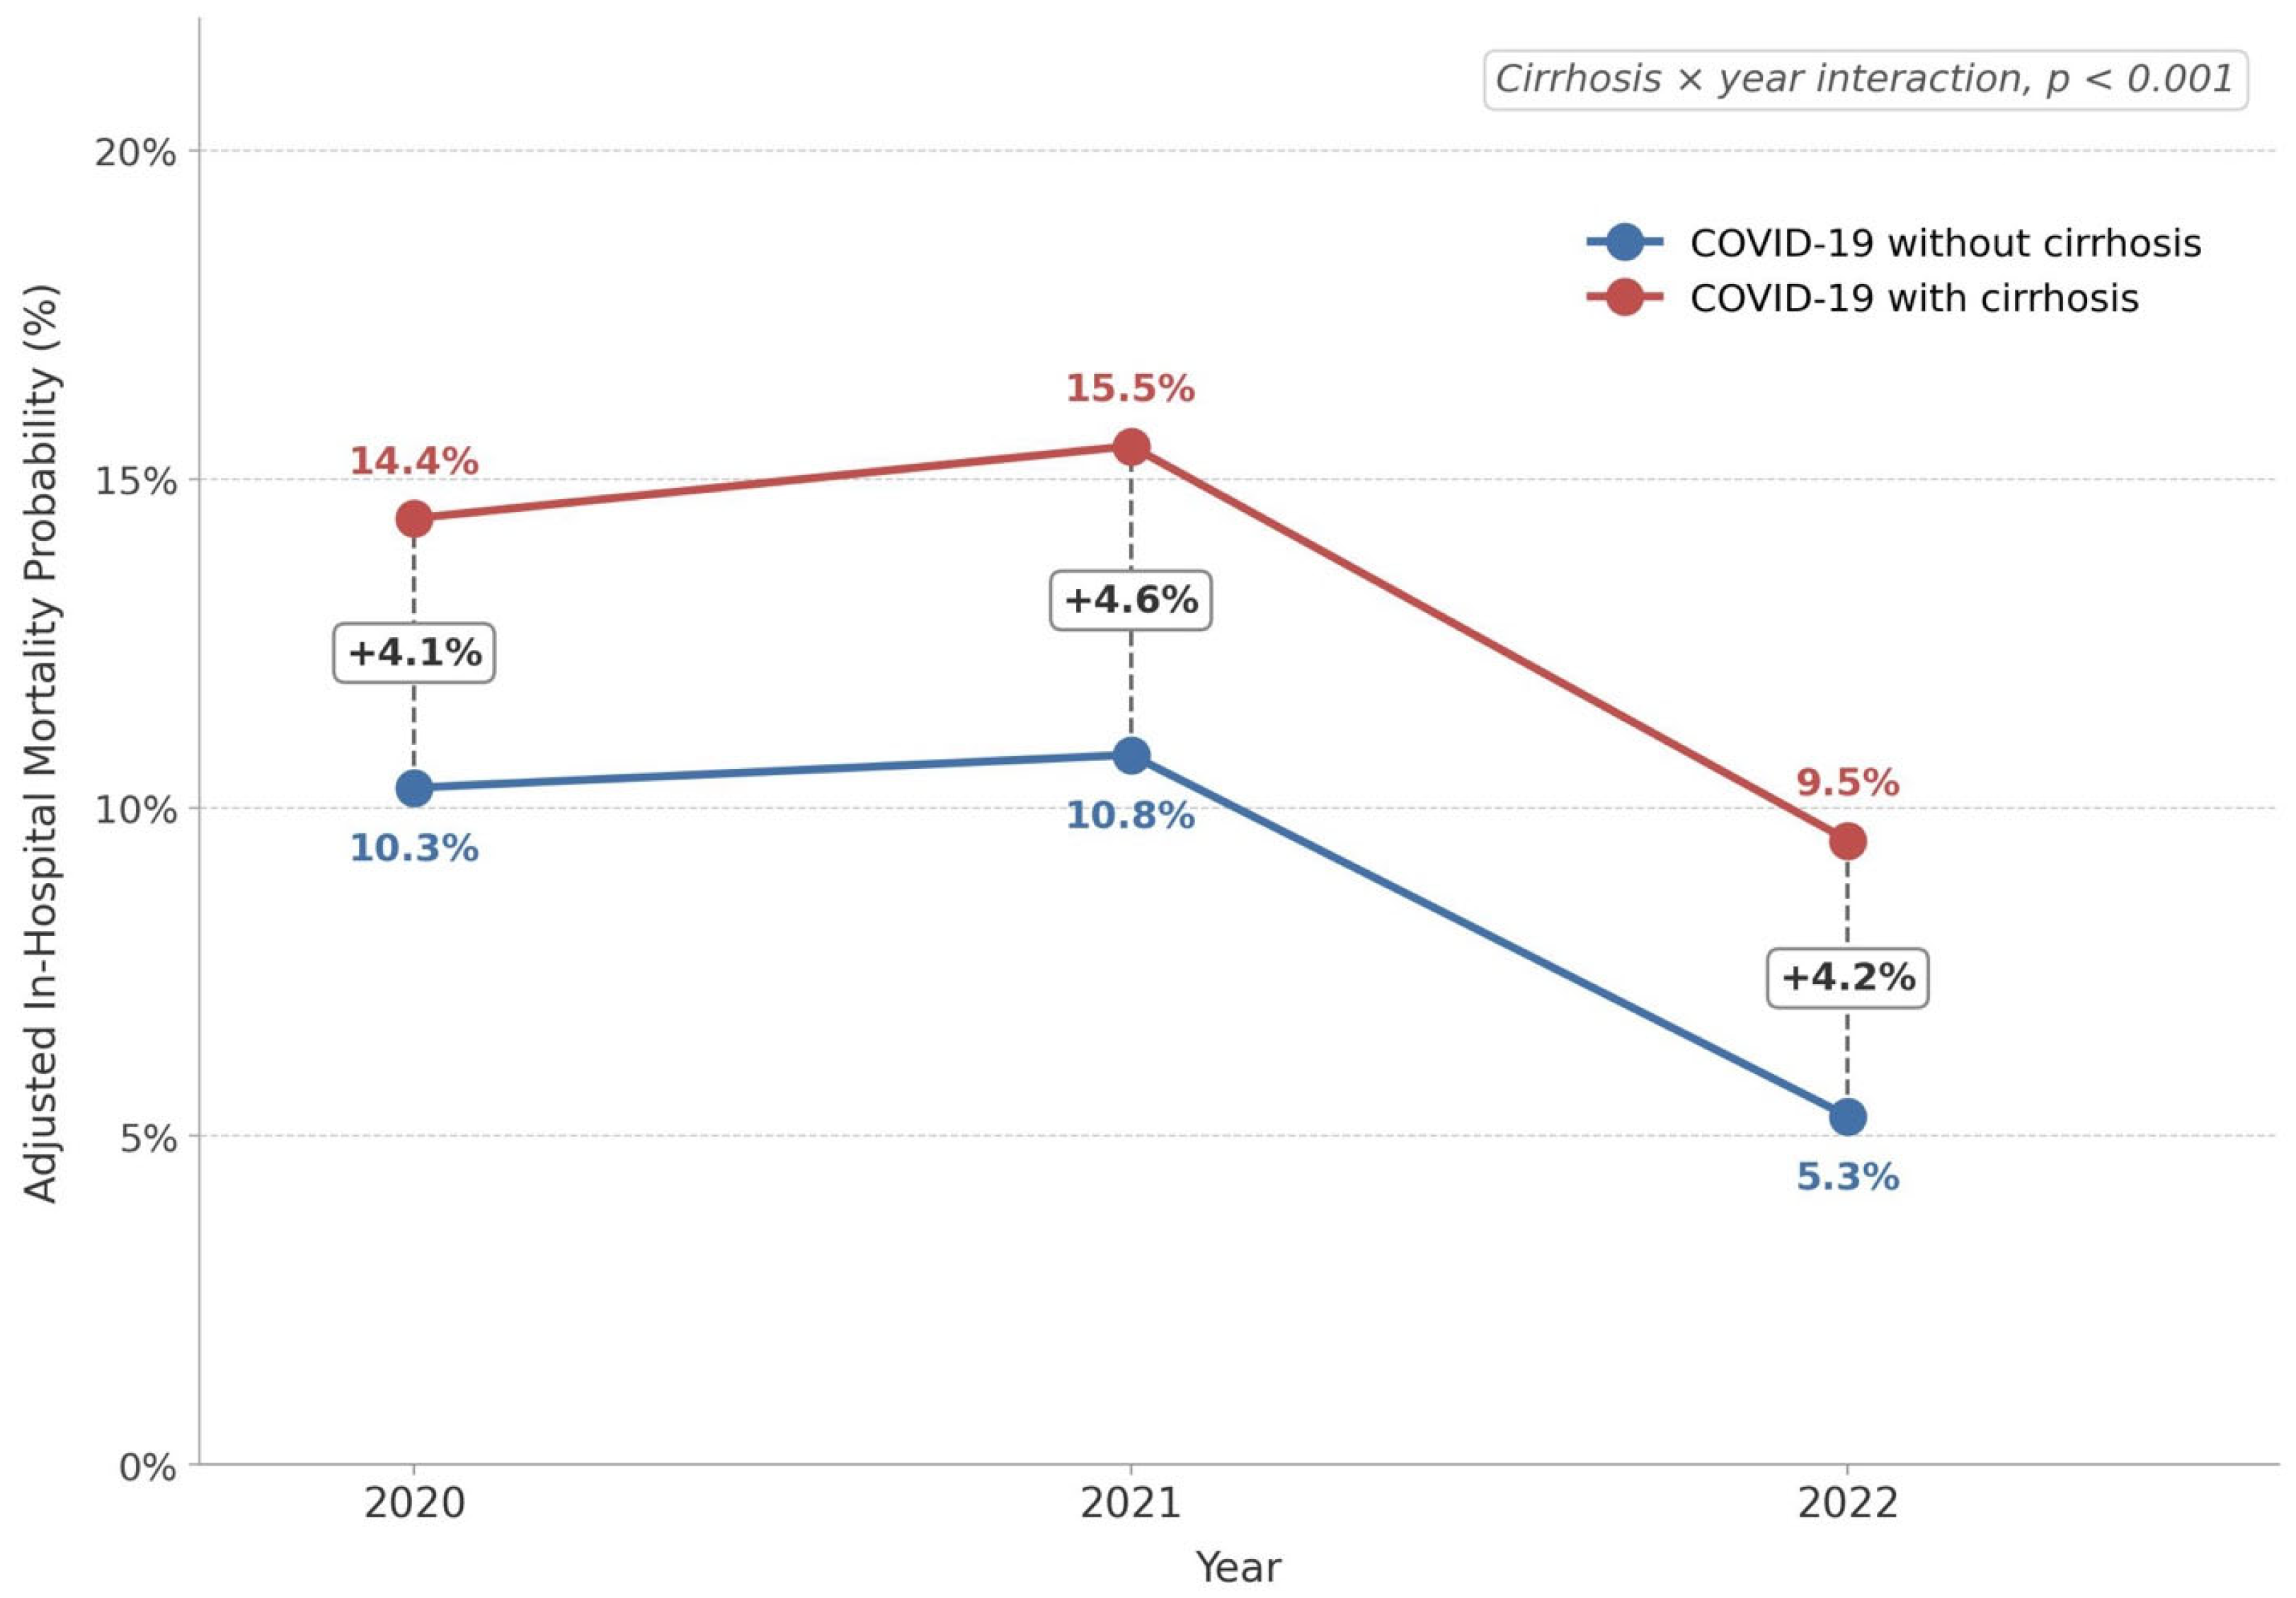
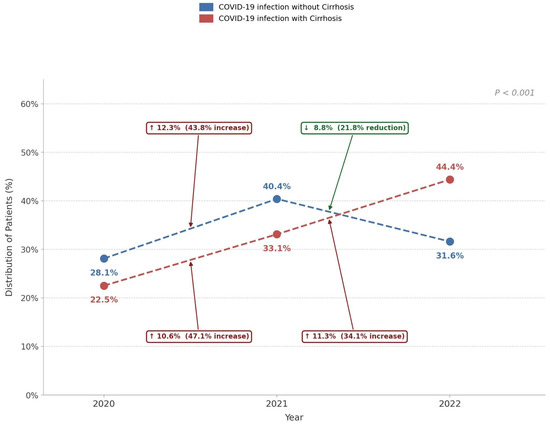
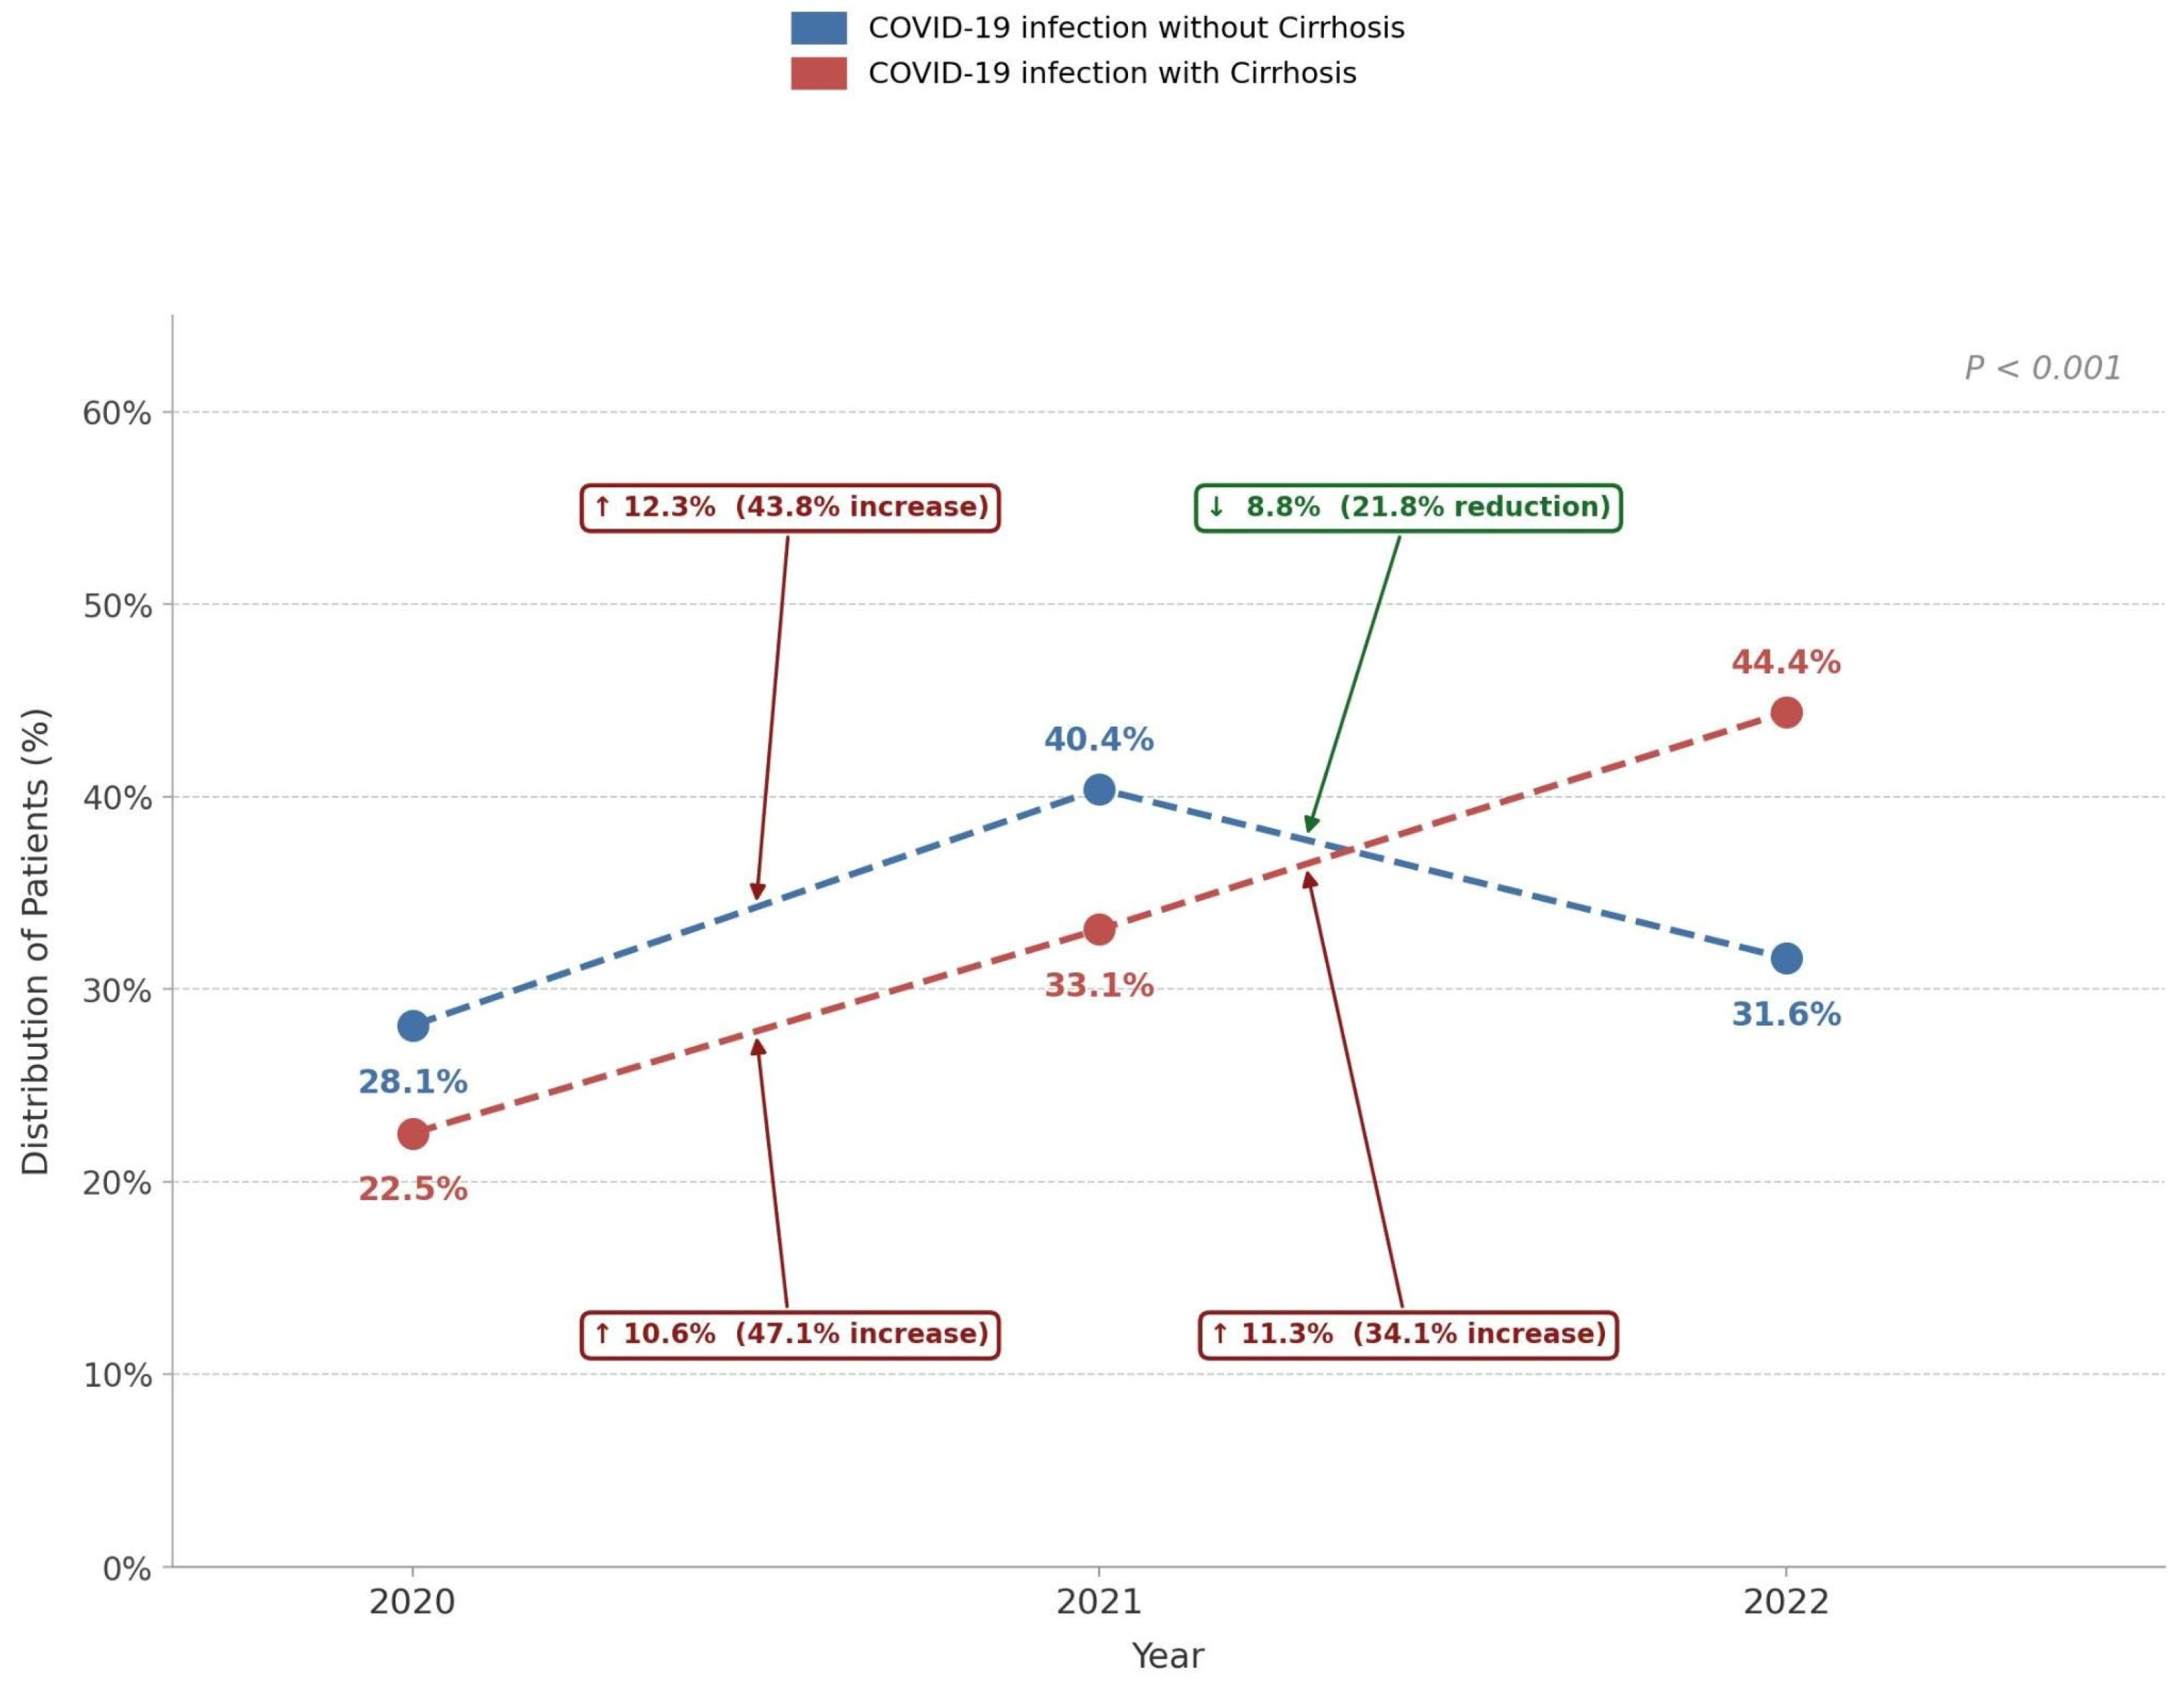
Temporal analysis showed that unadjusted in-hospital mortality among patients hospitalized with COVID-19 and concomitant cirrhosis was 19.4% in 2020, 20.2% in 2021, and 12.9% in 2022. After multivariable adjustment, the corresponding predicted in-hospital mortality probabilities were 14.4% in 2020, 15.5% in 2021, and 9.5% in 2022 (Figure 6; Supplementary Table S2). The interaction between cirrhosis and calendar year was statistically significant (p < 0.001), indicating that the association between cirrhosis and mortality varied across the study period (Figure 6; Supplementary Table S3). The annual distribution of hospitalizations within the study cohort differed according to cirrhosis status. Among COVID-19 hospitalizations without cirrhosis, 28.1% occurred in 2020, 40.4% in 2021, and 31.6% in 2022. Among COVID-19 hospitalizations with cirrhosis, 22.5% occurred in 2020, 33.1% in 2021, and 44.4% in 2022. These percentages represent the distribution of hospitalizations within the study cohort across calendar years and should not be interpreted as population-level hospitalization rates (Figure 7).
Figure 6.
Adjusted in-hospital mortality trends among patients hospitalized with COVID-19, with and without liver cirrhosis, from 2020 to 2022.
Figure 7.
Annual distribution of patients with COVID-19 infection and liver cirrhosis in the years 2020–2022.
4. Discussion
Liver cirrhosis is a major cause of global morbidity and mortality and is characterized by progressive hepatic dysfunction, immune dysregulation, and heightened susceptibility to severe infections [13,14]. Alcohol-associated liver disease and metabolic dysfunction-associated fatty liver disease are important contributors to the burden of chronic liver disease, while clinical and epidemiological studies have demonstrated that cirrhosis and portal hypertension represent significant public health concerns in the United States [15,16,17]. Severe COVID-19 can produce systemic and hepatic injury through dysregulated immune responses and multiorgan involvement [18,19,20,21]. While early studies reported mixed findings regarding the impact of chronic liver disease on COVID-19 severity [22], subsequent studies have demonstrated that underlying cirrhosis is associated with more severe COVID-19 and increased mortality [23,24,25,26]. This study addresses a key gap by using the 2020–2022 National Inpatient Sample (NIS) database to provide a comprehensive, multi-year national evaluation of all-cause cirrhosis and clinical outcomes in hospitalized COVID-19 patients.
Patients with cirrhosis may be particularly vulnerable to severe infections because of impaired physiological reserve, cirrhosis-associated immune dysfunction, and systemic inflammation [5,27]. This combination of systemic inflammation and immune dysfunction may increase susceptibility to severe infections and contribute to impaired vaccine responses [5,27,28,29,30,31]. Furthermore, cirrhosis-associated hemodynamic abnormalities and renal dysfunction may increase susceptibility to complications during severe systemic infections [32,33]. This combination of systemic inflammation and immune dysfunction may increase susceptibility to severe infections and contribute to impaired vaccine responses [5,27,28,29,30,31]. Although mRNA vaccination has been associated with reduced COVID-19 infection and hospitalization among patients with cirrhosis [30], persistent immune dysregulation may leave some patients vulnerable to breakthrough infection and exaggerated inflammatory responses. Severe COVID-19 may further amplify systemic inflammation, endothelial injury, and microvascular dysfunction [34]. These mechanisms may contribute to the higher mortality and septic shock observed among patients with cirrhosis in our study. However, because the NIS is an administrative database without detailed physiological or laboratory data, mechanistic explanations for the observed associations should remain cautious.
Some secondary outcomes demonstrated inverse adjusted associations, including lower odds of NIV, ARDS, ECMO, and RRT among patients with cirrhosis. These findings should be interpreted cautiously and should not be considered evidence of a biologically protective effect of cirrhosis. Because the NIS is an administrative database, residual confounding, differences in coding practices, treatment-selection effects, goals-of-care decisions, and differential eligibility for aggressive organ-support interventions may have influenced these associations. In particular, the use of ECMO, RRT, and ventilatory support may depend on clinical factors that are not captured in the NIS, including disease severity, transplant candidacy, frailty, contraindications, and patient or family preferences.
In contrast to the inverse associations observed for several organ-support outcomes, cirrhosis remained associated with a modestly longer adjusted length of stay and higher hospital charges. The adjusted mean difference in length of stay was 0.55 days, while adjusted hospital charges were approximately 8063 USD higher among patients with cirrhosis. Sensitivity analyses using log-transformed length of stay and a gamma-generalized linear model for hospital charges produced directionally consistent findings, supporting the robustness of these associations. These findings may reflect greater clinical complexity and resource utilization among hospitalized patients with cirrhosis, although residual confounding cannot be excluded.
A key contribution of this study is the evaluation of temporal changes in mortality among hospitalized patients with COVID-19 and cirrhosis. Unadjusted mortality remained elevated with minimal variation between 2020 (19.4%) and 2021 (20.2%), consistent with our preliminary analysis demonstrating increased mortality among hospitalized patients with cirrhosis and COVID-19 [35], before declining to 12.9% in 2022. After adjustment for demographic, clinical, and hospital-level characteristics, the corresponding predicted mortality probabilities were 14.4%, 15.5%, and 9.5%, respectively. The significant interaction between cirrhosis and calendar year suggests that the association between cirrhosis and mortality varied during the study period. This decline in mortality by 2022 may reflect multiple changes occurring during the pandemic, including improvements in clinical management, increasing vaccination rates, and the emergence of less virulent SARS-CoV-2 variants, consistent with findings from other nationwide NIS studies evaluating hospitalized patients with COVID-19 across different comorbid populations [36,37,38]. The annual distribution of hospitalizations within the study cohort also differed according to cirrhosis status. Among COVID-19 hospitalizations without cirrhosis, 28.1% occurred in 2020, 40.4% in 2021, and 31.6% in 2022, whereas among those with cirrhosis, 22.5%, 33.1%, and 44.4% occurred in 2020, 2021, and 2022, respectively. Patients with cirrhosis may have remained particularly vulnerable during the pandemic because of cirrhosis-associated immune dysfunction and impaired immune responses [5,27,28]. However, these percentages represent the distribution of hospitalizations within the NIS study cohort and should not be interpreted as population-level hospitalization rates, incidence, or changes in the overall burden of COVID-19 hospitalization among patients with cirrhosis.
5. Strengths and Limitations
A key strength of this study is the large sample size of the NIS database, which included up to 6 million hospitalizations and provided sufficient statistical power to evaluate yearly clinical trends. This study adds to the current literature in several ways. Many prior studies were limited to single-center cohorts, regional data, or early pandemic time periods [22,23,24,25,26]. The use of a nationally representative database also reduces the potential for single-center referral bias. Additionally, the large sample size enabled multivariate regression adjustments for complex baseline confounders, including socioeconomic factors and multiple comorbidity profiles. This improves the generalizability of our findings throughout diverse healthcare settings. Our study also included data from multiple time points, 2020 to 2022, during the dynamic and evolving landscape of COVID-19.
Our study has several limitations. The NIS database is derived from discharge-level data and relies on International Classification of Diseases, Tenth Revision, Clinical Modification (ICD-10-CM) administrative billing codes. Specific clinical information, such as Model for End-Stage Liver Disease (MELD) scores, Child–Pugh classifications, and detailed cirrhosis etiology, was not available for analysis. Furthermore, the NIS does not provide sufficient clinical detail to reliably distinguish compensated from decompensated cirrhosis or to characterize manifestations of hepatic decompensation. Consequently, we were unable to evaluate whether the association between cirrhosis and COVID-19 outcomes differed according to cirrhosis severity. The etiology of cirrhosis and associated treatments may also influence susceptibility to infection and clinical outcomes; however, medication exposure and detailed cirrhosis etiology could not be adequately evaluated using the NIS. In addition, long-term post-discharge outcomes could not be assessed because the database is limited to inpatient encounters. Although the NIS identifies in-hospital mortality, it does not provide a validated cause-of-death classification; therefore, respiratory-related mortality could not be distinguished from cirrhosis-related or other causes of death. While our study captures the broad association between cirrhosis and COVID-19 outcomes, future prospective studies are needed to determine whether specific cirrhosis phenotypes, etiologies, and disease severity pathways carry independent prognostic significance.
6. Future Directions
Future research should involve prospective multicenter studies to better characterize the complex interplay between cirrhosis severity, immune dysfunction, and COVID-19 outcomes. These studies should incorporate patient-level clinical data, including cirrhosis etiology, disease severity markers (such as MELD score and Child–Pugh classification), vaccination status, SARS-CoV-2 viral variants, and the timing and type of antiviral and immunomodulatory therapies. Integrating these variables with biomarkers of systemic inflammation, immune dysfunction, and hepatic injury may help identify high-risk patients and identify the mechanisms contributing to adverse outcomes in individuals with cirrhosis and COVID-19.
7. Conclusions
From a clinical perspective, our study demonstrates that cirrhosis is independently associated with increased in-hospital mortality and higher rates of severe systemic complications among patients hospitalized with COVID-19. Temporal changes in clinical outcomes over the course of the pandemic may be attributable to several factors, including widespread vaccination, improved clinical management protocols, and the emergence of SARS-CoV-2 variants with differing virulence. Early outpatient antiviral therapy, optimized vaccination strategies, and cirrhosis-specific preventive interventions remain essential to improve outcomes in this high-risk population.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/livers6050106/s1, Table S1: Sensitivity Analyses for Length of Stay and Total Hospital Charges Among Adults Hospitalized with COVID-19; Table S2: Adjusted In-Hospital Mortality Probabilities by Year and Cirrhosis Status Among Adults Hospitalized with COVID-19; Table S3: Cirrhosis x Year Interaction Model for In-Hospital Mortality Among Adults Hospitalized with COVID-19.
Author Contributions
Conceptualization, A.A.; Methodology, A.A., P.D., J.M.; Formal Analysis, A.A., D.D.; Data Curation, A.A., D.D.; Writing—Original Draft Preparation, A.A., V.S.V., J.M., D.D., A.S.V., P.D., R.A., D.K.; Writing—Review & Editing, A.A., V.S.V., J.M., P.D., D.D., A.S.V., R.A., D.K.; Supervision, A.A., J.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Ethical review and approval were not required for this study because it involved a secondary analysis of de-identified discharge data from the Healthcare Cost and Utilization Project (HCUP) National Inpatient Sample (NIS), obtained through the HCUP Central Distributor (certificate HCUP-28M71GVP5). The investigators had no direct interaction with individual patients and no access to identifiable private information. Under 45 CFR § 46.102(e)(1) of the Federal Policy for the Protection of Human Subjects (Common Rule), a human subject is defined as a living individual about whom an investigator obtains information or biospecimens through intervention or interaction, or obtains, uses, studies, analyzes, or generates identifiable private information or identifiable biospecimens. Accordingly, this study does not constitute human subjects research as defined under the Common Rule. All analyses were conducted in accordance with the HCUP Data Use Agreement and applicable federal regulations governing human subjects research.
Informed Consent Statement
Individual informed consent was not applicable because the analysis used de-identified secondary inpatient data and involved no direct patient participation.
Data Availability Statement
The NIS datasets used for this analysis are available from the HCUP Central Distributor subject to HCUP data-use requirements.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- World Health Organization. COVID-19 Epidemiological Update—24 December 2024; World Health Organization: Geneva, Switzerland, 24 December 2024. [Google Scholar]
- Marjot, T.; Webb, G.J.; Barritt, A.S., IV; Moon, A.M.; Stamataki, Z.; Wong, V.W.; Barnes, E. COVID-19 and liver disease: Mechanistic and clinical perspectives. Nat. Rev. Gastroenterol. Hepatol. 2021, 18, 348–364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marjot, T.; Eberhardt, C.S.; Boettler, T.; Belli, L.S.; Berenguer, M.; Buti, M.; Jalan, R.; Mondelli, M.U.; Moreau, R.; Shouval, D.; et al. Impact of COVID-19 on the liver and on the care of patients with chronic liver disease, hepatobiliary cancer, and liver transplantation: An updated EASL position paper. J. Hepatol. 2022, 77, 1161–1197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marjot, T.; Moon, A.M.; Cook, J.A.; Abd-Elsalam, S.; Aloman, C.; Armstrong, M.J.; Pose, E.; Brenner, E.J.; Cargill, T.; Catana, M.-A.; et al. Outcomes following SARS-CoV-2 infection in patients with chronic liver disease: An international registry study. J. Hepatol. 2021, 74, 567–577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albillos, A.; Martin-Mateos, R.; Van der Merwe, S.; Wiest, R.; Jalan, R.; Álvarez-Mon, M. Cirrhosis-associated immune dysfunction. Nat. Rev. Gastroenterol. Hepatol. 2022, 19, 112–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Albillos, A.; Lario, M.; Álvarez-Mon, M. Cirrhosis-associated immune dysfunction: Distinctive features and clinical relevance. J. Hepatol. 2014, 61, 1385–1396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Middleton, P.; Hsu, C.; Lythgoe, M.P. Clinical outcomes in COVID-19 and cirrhosis: A systematic review and meta-analysis of observational studies. BMJ Open Gastroenterol. 2021, 8, e000739. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bajaj, J.S.; Garcia-Tsao, G.; Biggins, S.W.; Kamath, P.S.; Wong, F.; McGeorge, S.; Shaw, J.; Pearson, M.; Chew, M.; Fagan, A.; et al. Comparison of mortality risk in patients with cirrhosis and COVID-19 compared with patients with cirrhosis alone and COVID-19 alone: Multicentre matched cohort. Gut 2021, 70, 531–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arumairaj, A.J.; Gupta, N.; Mattana, J.; Chaudhari, S.; Kumar, P.; Habtes, I. Determining the impact of alcoholic liver disease among patients hospitalized with COVID-19 infection: A nationwide analysis. Chest 2024, 166, A1781–A1782. [Google Scholar] [CrossRef] [Scilit]
- Arumairaj, A.; Gupta, N.; Mattana, J.; Chaudhari, S.; Kumar, P.; Habtes, I. Determining the impact of nonalcoholic steatohepatitis (NASH) on the severity of COVID-19 infection: A nationwide analysis. Chest 2024, 166, A2039–A2040. [Google Scholar] [CrossRef] [Scilit]
- Kapuria, D.; Gangu, K.; Chourasia, P.; Boba, A.; Nguyen, A.; Ryu, M.; Peicher, M.; Flores, M.; Chela, H.K.; Daglilar, E.S.; et al. COVID-19 alcoholic cirrhosis and non-alcoholic steatohepatitis cirrhosis outcomes among hospitalized patients in the United States: Insight from National Inpatient Sample Database. Trop. Med. Infect. Dis. 2022, 7, 421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Agency for Healthcare Research and Quality. HCUP National Inpatient Sample (NIS) Overview; Healthcare Cost and Utilization Project: Rockville, MD, USA, 2026. Available online: https://hcup-us.ahrq.gov/nisoverview.jsp (accessed on 2 August 2026).
- Goossens, N.; Nakagawa, S.; Hoshida, Y. Molecular prognostic prediction in liver cirrhosis. World J. Gastroenterol. 2015, 21, 10262–10273. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- GBD 2017 Cirrhosis Collaborators. The global, regional, and national burden of cirrhosis by cause in 195 countries and territories, 1990-2017: A systematic analysis for the Global Burden of Disease Study 2017. Lancet Gastroenterol. Hepatol. 2020, 5, 245–266. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Crabb, D.W.; Im, G.Y.; Szabo, G.; Mellinger, J.L.; Lucey, M.R. Diagnosis and Treatment of Alcohol-Associated Liver Diseases: 2019 Practice Guidance From the American Association for the Study of Liver Diseases. Hepatology 2020, 71, 306–333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eslam, M.; Sanyal, A.J.; George, J.; International Consensus Panel. MAFLD: A Consensus-Driven Proposed Nomenclature for Metabolic Associated Fatty Liver Disease. Gastroenterology 2020, 158, 1999–2014.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Younossi, Z.M.; de Avila, L.; Racila, A.; Nader, F.; Paik, J.; Henry, L.; Stepanova, M. Prevalence and predictors of cirrhosis and portal hypertension in the United States. Hepatology 2025, 82, 1229–1240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Puelles, V.G.; Lütgehetmann, M.; Lindenmeyer, M.T.; Sperhake, J.P.; Wong, M.N.; Allweiss, L.; Chilla, S.; Heinemann, A.; Wanner, N.; Liu, S.; et al. Multiorgan and Renal Tropism of SARS-CoV-2. N. Engl. J. Med. 2020, 383, 590–592. [Google Scholar] [CrossRef] [PubMed] [PubMed Central]
- Koçak Tufan, Z.; Kayaaslan, B.; Mer, M. COVID-19 and Sepsis. Turk. J. Med. Sci. 2021, 51, 3301–3311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wanner, N.; Andrieux, G.; Badia-I-Mompel, P.; Edler, C.; Pfefferle, S.; Lindenmeyer, M.T.; Schmidt-Lauber, C.; Czogalla, J.; Wong, M.N.; Okabayashi, Y.; et al. Molecular consequences of SARS-CoV-2 liver tropism. Nat. Metab. 2022, 4, 310–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, C.; Shi, L.; Wang, F.S. Liver injury in COVID-19: Management and challenges. Lancet Gastroenterol. Hepatol. 2020, 5, 428–430. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Lippi, G.; de Oliveira, M.H.S.; Henry, B.M. Chronic liver disease is not associated with severity or mortality in Coronavirus disease 2019 (COVID-19): A pooled analysis. Eur. J. Gastroenterol. Hepatol. 2021, 33, 114–115. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Qi, X.; Liu, Y.; Wang, J.; Fallowfield, J.A.; Wang, J.; Li, X.; Shi, J.; Pan, H.; Zou, S.; Zhang, H.; et al. COVID-Cirrhosis-CHESS Group. Clinical course and risk factors for mortality of COVID-19 patients with pre-existing cirrhosis: A multicentre cohort study. Gut 2021, 70, 433–436. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Moon, A.M.; Webb, G.J.; Aloman, C.; Armstrong, M.J.; Cargill, T.; Dhanasekaran, R.; Genescà, J.; Gill, U.S.; James, T.W.; Jones, P.D.; et al. High mortality rates for SARS-CoV-2 infection in patients with pre-existing chronic liver disease and cirrhosis: Preliminary results from an international registry. J. Hepatol. 2020, 73, 705–708. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Iavarone, M.; D’Ambrosio, R.; Soria, A.; Triolo, M.; Pugliese, N.; Del Poggio, P.; Perricone, G.; Massironi, S.; Spinetti, A.; Buscarini, E.; et al. High rates of 30-day mortality in patients with cirrhosis and COVID-19. J. Hepatol. 2020, 73, 1063–1071. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Singh, S.; Khan, A. Clinical Characteristics and Outcomes of Coronavirus Disease 2019 Among Patients with Preexisting Liver Disease in the United States: A Multicenter Research Network Study. Gastroenterology 2020, 159, 768–771.e3. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Bonnel, A.R.; Bunchorntavakul, C.; Reddy, K.R. Immune dysfunction and infections in patients with cirrhosis. Clin. Gastroenterol. Hepatol. 2011, 9, 727–738. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leise, M.D.; Talwalkar, J.A. Immunizations in chronic liver disease: What should be done and what is the evidence. Curr. Gastroenterol. Rep. 2013, 15, 300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Janocha-Litwin, J.; Simon, K. Recommended vaccinations for patients with chronic liver diseases. Clin. Exp. Hepatol. 2025, 11, 1–8. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- John, B.V.; Deng, Y.; Scheinberg, A.; Mahmud, N.; Taddei, T.H.; Kaplan, D.; Labrada, M.; Baracco, G.; Dahman, B. Association of BNT162b2 mRNA and mRNA-1273 Vaccines with COVID-19 Infection and Hospitalization Among Patients with Cirrhosis. JAMA Intern. Med. 2021, 181, 1306–1314. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Hasa, E.; Hartmann, P.; Schnabl, B. Liver cirrhosis and immune dysfunction. Int. Immunol. 2022, 34, 455–466. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Ginès, P.; Solà, E.; Angeli, P.; Wong, F.; Nadim, M.K.; Kamath, P.S. Hepatorenal syndrome. Nat. Rev. Dis. Primers 2018, 4, 23, Erratum in Nat. Rev. Dis. Primers 2018, 4, 33. https://doi.org/10.1038/s41572-018-0035-2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jung, C.Y.; Chang, J.W. Hepatorenal syndrome: Current concepts and future perspectives. Clin. Mol. Hepatol. 2023, 29, 891–908. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Zhou, K.; Chen, Y.; Pang, J.; Zhang, J.; Lu, J. The endothelial-immunothrombotic storm in viral sepsis: Lessons from COVID-19. Front. Immunol. 2026, 16, 1681764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arumairaj, A.J.; Gupta, N.; Mattana, J.; Chaudhari, S.; Poor, A. Determining the impact of cirrhosis on the severity of COVID-19 infection: A nationwide analysis. Chest 2024, 166, 2037A–2038A. [Google Scholar] [CrossRef] [Scilit]
- Arumairaj, A.; Dhanani, D.; Veluswamy, A.S.; Arun Kumar, A.K.M.; Perez Moscoso, J.A.; Mittal, J.; Prajapati, V.; Korpu, D.; Dhorajiya, P. Trends and Outcomes of Acute Liver Failure in Patients with COVID-19 Infection: Insights from United States National Inpatient Sample Analysis 2020–2022. Livers 2026, 6, 70. [Google Scholar] [CrossRef] [Scilit]
- Arumairaj, A.; Dhanani, D.; Shunmugam Veluswamy, A.; Tashrifwala, F.A.A.; Kuriti, M.; Kalluri, S.R.; Mariswamy Arun Kumar, A.K.; Mittal, J.; Korpu, D. Trends and outcomes of COVID-19 hospitalizations among patients with hypertension: Insights from United States National Inpatient Sample, 2020–2022. Cardiovasc. Med. 2026, 29, 39. [Google Scholar] [CrossRef] [Scilit]
- Arumairaj, A.; Dhorajiya, P.; Mittal, J.; Kuriti, M.; Vajjala, V.S.; Korpu, D.; Dhanani, D. Clinical outcomes and hospital resource utilization among hospitalized patients with diabetes mellitus and COVID-19 infection: Insights from United States National Inpatient Sample, 2020–2022. Diabetology 2026, 7, 184. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.