


Abstract
Background/Objectives: The aim of this study is to evaluate whether preoperative intra-articular corticosteroid injections (CSIs) are associated with an increased risk of reoperation following matrix-associated or autologous chondrocyte implantation (MACI/ACI). Secondary aims included comparing reoperation-free survival, patient-reported outcomes (PROMs), and patient acceptable symptom state (PASS) achievement. Methods: A retrospective cohort study was conducted on adults undergoing primary MACI/ACI between 2011 and 2023 at a single academic institution. Patients with documented CSI status and ≥2 years of follow-up were included. Exclusion criteria were prior MACI/ACI, osteochondral allograft transplantation, multi-ligament reconstruction, or inadequate follow-up. Propensity score matching (2:1, no steroid/steroid) based on age, sex, BMI, laterality, procedure type, and prior surgery yielded 138 matched patients (92 no steroid, 48 steroid). The primary outcome was ipsilateral reoperation, analyzed as a binary outcome, with Kaplan–Meier reoperation-free survival and restricted mean survival time (RMST). PROMs and PASS achievement were also assessed. Statistical significance was set at p < 0.05. Results: Baseline characteristics and follow-up (6.55 ± 3.74 vs. 6.73 ± 3.99 years; p = 0.80) were similar. Graft failure rates were identical (4.3% each; p = 1.00). Reoperation occurred in 21.7% of patients without CSI and 23.9% with CSI (p = 0.83). CSI was not associated with reoperation (adjusted OR 2.28; 95% CI 0.54–9.95; p = 0.26). No significant difference in reoperation-free survival or PROMs was observed. Conclusions: Preoperative intra-articular corticosteroid injections were not associated with increased reoperation risk, inferior reoperation-free survival, or worse functional outcomes following MACI/ACI.
1. Introduction
Knee preservation procedures such as matrix-induced autologous chondrocyte implantation (MACI) and autologous chondrocyte implantation (ACI) have become increasingly common, reflecting a shift toward biological restoration rather than joint replacement [1]. MACI treats focal articular cartilage defects by harvesting autologous chondrocytes from a non-weight-bearing region, expanding them in vitro, and reimplanting them within a resorbable collagen membrane to restore hyaline-like cartilage and preserve joint function, particularly in young, active patients [2]. Optimizing the biological environment for graft integration and durability remains critical as techniques evolve.
Intra-articular corticosteroid injections are widely used preoperatively for short-term pain relief and functional improvement. Although effective in reducing inflammation and pain, concerns persist regarding the adverse effects on cartilage and soft tissue healing [3,4]. Experimental studies suggest corticosteroids may impair proteoglycan synthesis, inhibit chondrocyte proliferation, and promote apoptosis, with repeated or high-dose exposure linked to cartilage softening and subchondral bone changes, raising concern for biologically sensitive procedures such as MACI or ACI [5].
Clinical studies evaluating preoperative corticosteroid injections have reported mixed results. Some suggest that injections administered close to surgery may increase postoperative infection or delayed healing, particularly in arthroplasty populations, whereas others report no differences in complications or functional outcomes when injections are given several months preoperatively [1,6,7]. Feng et al. reported that no significant differences were found at a mean 3-year follow-up in the retear rates, pain, range of motion, or glenohumeral structure on postoperative MRI scans after arthroscopic rotator cuff repair with or without preoperative CSIs [7]. Despite their frequent use before knee preservation procedures, evidence directly assessing the impact of corticosteroid injections on cartilage restoration outcomes remains limited, and existing studies are often heterogeneous in patient selection, injection timing, surgical technique, and use of matched controls.
Given these uncertainties, the purpose of this study was to evaluate the association between preoperative corticosteroid injection and reoperation, reoperation-free survival, patient-reported outcome measures (PROMs), and patient acceptable symptom state (PASS) achievement following MACI or ACI. We hypothesized that patients with preoperative corticosteroid exposure would demonstrate comparable mid- to long-term outcomes to those without injection.
2. Materials and Methods
2.1. Study Design and Data Collection
Institutional review board approval was obtained (IRB Protocol i19-01430). This single-center retrospective cohort study included patients who underwent MACI or ACI between 2011 and 2023 by eight fellowship-trained sports medicine surgeons. Patients were identified from institutional surgical databases and confirmed by electronic medical record review, yielding an initial cohort of 199 consecutive patients with systematically abstracted demographic, clinical, operative, and outcome data. Inclusion criteria were age ≥18 years, primary MACI or ACI for a symptomatic focal chondral defect refractory to nonoperative treatment, documented preoperative intra-articular corticosteroid injection status, and a minimum of 2 years of postoperative follow-up. Exclusion criteria included prior cartilage restoration procedures, incomplete operative data, concomitant multi-ligament knee reconstruction, and insufficient follow-up. Patients were stratified by preoperative corticosteroid injection exposure (steroid vs. no steroid).
2.2. Baseline Variables
Baseline variables included age, sex, body mass index, laterality, prior ipsilateral knee surgery, and whether cartilage restoration was performed in isolation or with concomitant procedures. Operative variables included the cartilage restoration technique (MACI vs. ACI), lesion location, and cartilage severity. Lesion location was categorized by anatomic region, and cartilage severity was recorded using Outerbridge grading based on operative reports and imaging review. Variables were selected a priori based on clinical relevance and the prior cartilage restoration literature.
2.3. Corticosteroid Injection Assessment
For patients receiving preoperative corticosteroid injections, timing relative to surgery, number of injections (single vs. multiple), and dose were abstracted when available. Due to heterogeneous injection practices and inconsistent documentation, corticosteroid exposure was analyzed as a binary variable (injection vs. no injection). Injection characteristics were summarized descriptively and were not modeled as independent predictors.
2.4. Surgical Technique and Rehabilitation
MACI and ACI were performed using contemporary cartilage restoration techniques, with ACI used earlier in the study period and MACI adopted after U.S. approval. Defects were prepared to stabilize vertical margins with preservation of subchondral bone. ACI involved implantation of cultured autologous chondrocytes beneath a secured collagen membrane, whereas MACI additionally used a membrane chondrocyte-seeded collagen scaffold fixed with fibrin glue with or without sutures. Concomitant procedures were performed as indicated. Postoperative rehabilitation followed standardized institutional protocols emphasizing graft protection, progressive range of motion, and staged return to weight-bearing, with adjustments based on lesion and concomitant procedures.
2.5. Outcomes and Follow-Up
The primary outcome was reoperation, defined as any subsequent ipsilateral knee surgery following MACI or ACI, analyzed as a binary outcome, with reoperation subtypes recorded. To better characterize the clinical significance of subsequent procedures, reoperations were further categorized as major or minor. Major reoperations included anterior cruciate ligament reconstruction (ACLR), osteochondral allograft transplantation (OCA), meniscal allograft transplantation (MAT), meniscectomy, tibial tubercle osteotomy (TTO), and total knee arthroplasty (TKA). Minor reoperations included irrigation and debridement (I&D), manipulation under anesthesia or lysis of adhesions (MUA/LOA), osteotomy hardware removal, chondroplasty, and synovectomy. Graft failure, defined as conversion to compartment-matched osteochondral allograft (OCA) or total knee arthroplasty (TKA), was prespecified as a subset of reoperation and reported descriptively. Secondary outcomes included reoperation-free survival and patient-reported outcome measures (PROMS).
Patient-reported outcome measures (PROMs) were obtained from institutional clinical databases and included the visual analog scale (VAS) for pain; Knee Injury and Osteoarthritis Outcome Score (KOOS) subscales (Symptoms, Pain, Activities of Daily Living, Sport/Recreation, and Quality of Life); International Knee Documentation Committee (IKDC) subjective score; Lysholm score; and Tegner activity scale (pre- and postoperative). Patient acceptable symptom state (PASS) achievement was assessed using established thresholds reported by Koch et al. (KSSTA, 2026), including Lysholm ≥ 61.5, IKDC ≥ 59.7, KOOS Symptoms ≥ 51.8, KOOS Pain ≥ 79.2, KOOS ADL ≥ 87.5, KOOS Sport ≥ 57.5, and KOOS Quality of Life ≥ 59.4 [8].
Mean follow-up was defined as time from surgery to study end or last available record. Clinical follow-up (time to last in-person visit) was used as the censoring point for time-to-event analyses.
2.6. Statistical Analysis and Propensity Score Matching
Propensity score matching was performed using logistic regression with injection status as the dependent variable and age, sex, body mass index, laterality, procedure type, and prior ipsilateral surgery as covariates. Patients were matched 2:1 (no steroid/steroid) using nearest-neighbor matching without replacement with a caliper of 0.2 standard deviations of the logit of the propensity score, with balance assessed by standardized mean differences (<0.10). Cartilage severity (Outerbridge grade) was not included in the propensity score model. Instead, Outerbridge grade was incorporated as an adjustment variable in subsequent multivariable regression analyses evaluating reoperation risk. Balance between matched cohorts was assessed using standardized mean differences (SMD), with values < 0.10 considered indicative of adequate covariate balance. Reoperation-free survival was analyzed using Kaplan–Meier methods with log-rank testing and restricted mean survival time (RMST). Reoperation and graft failure were evaluated using logistic regression adjusted for Outerbridge grade. PROMs were compared using Welch’s t-tests and multivariable linear regression, and categorical variables were compared using chi-square or Fisher’s exact tests. A priori power analysis was performed for the matched cohort using the observed control event rate. Statistical significance was set at p < 0.05, and analyses were performed in R version 4.5.3 (R Foundation for Statistical Computing, Vienna, Austria).
3. Results
3.1. Study Cohort
A retrospective review identified 199 patients who underwent MACI or ACI between 2011 and 2023. After applying eligibility criteria, 138 patients comprised the final propensity score-matched cohort (92 no steroid, 46 steroid). Baseline demographics, operative characteristics, lesion location, concomitant procedures, and cartilage severity were comparable between groups (Table 1). Mean age, sex distribution, body mass index, study follow-up, and clinical follow-up did not differ. MACI was the predominant procedure in both cohorts, and lesions most commonly involved the patella. With 92 patients in the no-steroid group and 46 in the steroid group, the study had 80% power (α = 0.05) to detect an approximate absolute event rate difference corresponding to an odds ratio of approximately 3.0. This analysis suggests that smaller differences in reoperation risk may not be detectable within the available sample size. Standardized mean differences confirmed improved balance after matching, with all covariates demonstrating SMD values < 0.10 in the matched cohort (Table 2).
Table 1.
Demographic, operative, and postoperative outcomes stratified by preoperative corticosteroid injection status.
Table 2.
Standardized mean differences before and after propensity score matching.
3.2. Preoperative CSI Characteristics
Among injected patients (n = 46), most injections occurred within 2 years before surgery (73.9%), including 34.8% within 1 year and 39.1% between 1 and 2 years. Fewer injections occurred ≥2 years preoperatively. Fourteen patients (30.4%) received multiple injections vs. 32 patients (69.6%) who received a single injection. Among cases with documented dosing (n = 23), the mean dose was 47 mg, most commonly 40 mg (82.6%), with 17.4% receiving 80 mg. Triamcinolone (41.3%) and methylprednisolone (10.9%) were the most frequently used agents.
3.3. Reoperation Rates and Subsequent Procedures
Reoperation rates were similar between groups (no steroid: 21.7% vs. steroid: 23.9%; p = 0.83), with identical graft failure rates (4.3% each; p = 1.00) (Table 1). When stratified by procedure severity, major reoperations occurred in 11 patients (12.0%) in the no-steroid group and 2 patients (4.3%) in the steroid group (p = 0.156). Minor reoperations occurred in 21 patients (22.8%) in the no-steroid group and 14 patients (30.4%) in the steroid group (p = 0.255).
In the no-steroid group, reoperations most commonly included chondroplasty and manipulation under anesthesia (MUA) or lysis of adhesions (LOA), whereas the steroid group more frequently underwent irrigation and debridement, MUA or LOA, and hardware removal. Notably, all four cases of postoperative wound infection requiring irrigation and debridement occurred exclusively in the corticosteroid injection cohort (8.7% vs. 0%; p = 0.011). In multivariable logistic regression adjusted for cartilage severity, preoperative corticosteroid injection was not independently associated with reoperation (adjusted OR, 2.28; 95% CI, 0.54–9.95; p = 0.255).
3.4. Reoperation-Free Survival
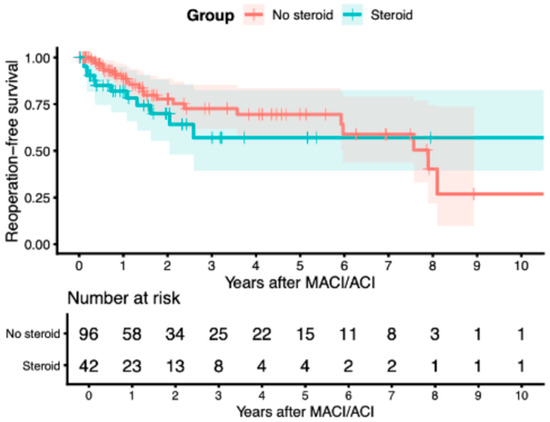
Kaplan–Meier analysis demonstrated no difference in reoperation-free survival (log-rank p = 0.53) (Figure 1). One-, two-, five-, and ten-year survival rates were 91.5%, 76.4%, 68.7%, and 34.6% in the no-steroid group versus 83.4%, 75.7%, 61.7%, and 59.3% in the steroid group, respectively. RMST was similar (7.68 vs. 8.63 years; p = 0.41).
Figure 1.
Kaplan–Meier curves depicting reoperation-free survivorship following MACI/ACI stratified by preoperative corticosteroid injection status. Shaded areas represent 95% confidence intervals, tick marks denote censoring, and numbers at risk are shown below the x-axis.
3.5. PROMs and PASS
PROMs were available for 103 patients (71 no steroid, 32 steroid) (Table 2). VAS pain and KOOS Symptoms, Pain, Activities of daily living, and Sport/Recreation scores did not differ (all p > 0.05). KOOS Quality of Life was lower in the steroid group (47.7 ± 23.9 vs. 57.9 ± 21.8; β = −10.18; p = 0.043). Preoperative Tegner scores were also lower in the steroid group (β = −1.05; p = 0.031), whereas postoperative Tegner, Lysholm, and IKDC scores were comparable. PASS achievement did not differ across Lysholm, IKDC, or any KOOS subscale (all p > 0.05).
Table 3 showing a comparison of patient-reported outcome measures following MACI/ACI in patients with and without preoperative corticosteroid injection. Values are presented as mean scores, and regression coefficients with 95% confidence intervals are shown for between-group comparisons. p < 0.05 was statistically significant *.
Table 3.
Comparison of patient-reported outcomes after MACI/ACI by preoperative corticosteroid injection status.
Table 4 shows patient acceptable symptom state (PASS) achievement following MACI/ACI in patients with and without preoperative corticosteroid injection. PASS thresholds were based on validated anchor-based criteria reported by Koch et al. (KSSTA, 2026) [8]. Values are presented as n/N (%), with odds ratios and 95% confidence intervals for between-group comparisons. Statistical significance was set at p < 0.05.
Table 4.
Patient acceptable symptom state (PASS) achievement rates by preoperative corticosteroid injection status following MACI/ACI.
4. Discussion
In this matched cohort, preoperative CSIs were not associated with inferior clinical outcomes following MACI or ACI. Patients who received CSIs demonstrated similar reoperation rates, reoperation-free survival, PROMs, and PASS achievement compared with those without injection, although lower preoperative Tegner scores in the CSI group suggest a greater baseline symptom burden. To our knowledge, this is the first study to directly evaluate the association between preoperative CSIs and outcomes after MACI or ACI.
Within the orthopedic literature, direct evidence regarding the impact of preoperative intra-articular CSIs on ACI or MACI outcomes remains limited, underscoring the need for further study. Although ACI and MACI provide durable improvements in knee pain and function with low long-term failure rates, advanced cartilage degeneration, degenerative changes at the time of implantation and a history of prior regenerative procedures are associated with worse outcomes [9,10,11,12]. To account for this confounder, cartilage severity was graded using the Outerbridge scale and was adjusted for in our regression analyses evaluating graft failure and reoperation risk [13]. Despite their symptomatic benefits, corticosteroid injections have been linked to increased cartilage loss and potential chondrotoxicity, raising concern for their use in cartilage repair procedures, likely due to corticosteroid-induced catabolic effects on cartilage [14,15,16,17].
This study was designed to address the concern that although CSIs may impair cartilage biology, their symptomatic benefits may not necessarily compromise the success of MACI or ACI. In the present cohort, preoperative CSI exposure was not associated with inferior outcomes. Graft failure rates were identical between groups (4.3% vs. 4.3%), and reoperation rates were comparable (23.9% vs. 21.7%). When stratified by procedure severity, there was no significant difference in major reoperations (4.3% vs. 12.0%) or minor reoperations (30.4% vs. 22.8%) in the steroid vs. no-steroid group. The overall reoperation rate in our cohort was consistent with the prior literature. Anigwe et al. reported a 30.4% reoperation rate at a mean 4.8-year follow-up among 2010 patients undergoing primary ACI, with most reoperations being minor procedures [18]. Reoperation-free survivorship did not differ between groups, with overlapping 95% confidence intervals at all time points (1 year: 83.4% vs. 91.5%; 2 year: 75.7% vs. 76.4%; 5 year: 61.7% vs. 68.7%; 10 year: 59.3% vs. 34.6%). The lower 10-year survivorship in the no-steroid group should be interpreted cautiously, as few patients remained at risk.
Corticosteroid exposure has also raised concern regarding perioperative complications, particularly surgical site infection. Prior studies suggest that injections administered close to surgery may increase infection risk, whereas injections given ≥1 month preoperatively are not associated with higher risk, with similar findings reported for meniscectomy, anterior cruciate ligament reconstruction, and shoulder arthroscopy [19,20,21,22,23]. Forsythe et al. reported that patients were five times more likely to return to the operating room for infection after arthroscopic meniscectomy if they had a CSI in the month before or multiple CSIs in the year before surgery and that this risk of infection was no longer significant if there was at least a 2-month interval between preoperative CSI and arthroscopic meniscectomy [20]. In the present cohort, four superficial wound infections requiring irrigation and debridement occurred, all in the corticosteroid group, although injections were administered ≥6 months preoperatively. Given the low event rate and inconsistency in the documentation of CSI injection dose, number, and frequency, these findings are insufficient to establish causality, and the effect of preoperative CSIs on infection risk following MACI or ACI remains unclear and warrants further prospective investigation.
Finally, no differences were observed in most PROMs or PASS achievement between groups. KOOS Quality of Life and Tegner preoperative activity scores were significantly lower in the corticosteroid cohort, suggesting reduced baseline activity. KOOS pain and function measures were also comparable between both groups. Collectively, these findings indicate that preoperative CSI use did not adversely affect subjective outcomes following cartilage restoration. Therefore, the findings of this study should be interpreted with caution due to the limited power and insufficient documentation on injection characteristics; hence, more robust studies are needed to support these findings.
Limitations
This study has several limitations. Its retrospective design introduces selection bias and unmeasured confounding, and the steroid cohort may have represented a more symptomatic population. Corticosteroid exposure was recorded only as a binary variable (yes/no) because documentation of injection timing, number, and frequency and dose was inconsistent. This represents a very important limitation, as the potential impact of corticosteroid injections on surgical outcomes likely depends on both timing relative to surgery and cumulative exposure, which was not included in our analysis. Collapsing these factors into a binary variable likely obscured clinically meaningful differences; for example, multiple injections administered shortly before surgery may carry a greater risk than a single injection performed months or years prior. In addition, the study is underpowered to detect modest differences between groups, as suggested by the wide confidence intervals, raising the possibility of a type II error. Finally, inclusion of both MACI and ACI procedures improves generalizability but limits procedure-specific analyses. Prospective studies with standardized documentation of injection characteristics and adequate statistical power are warranted to better define the relationship between preoperative corticosteroid injections and outcomes following cartilage restoration procedures.
5. Conclusions
Preoperative corticosteroid injections showed no association with increased reoperation risk, reduced survivorship, or inferior PROMs or PASS following knee MACI or ACI. However, given the study’s limited power, lack of detailed injection characteristics, and the use of a heterogeneous complication outcome, these findings should be interpreted cautiously, as further investigation is warranted.
Author Contributions
I.J., R.K.C., R.H., S.T.-T. and C.P. all contributed to writing—original draft preparation, writing—review and editing, data curation, validation, formal analysis, investigation, and methodology. E.J.S., L.M.J. and K.A.C. contributed to writing—review and editing, visualization, supervision, resources, project administration, methodology, investigation, and conceptualization. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was conducted in accordance with the Declaration of Helsinki, and the protocol was approved by the Ethics committee of NYU Langone Health Institutional Review Board, study number: i19-01430 on 27 September 2019.
Informed Consent Statement
Informed consent for participation is not required as per local legislation by the United States Department of Health and Human Services.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Acknowledgments
All authors contributed to writing—review and editing, data curation, formal analysis, investigation, methodology and conceptualization. The authors want to thank the clinical research coordinators, statisticians and administrative staff at the Department of Orthopaedic Surgery for their assistance with data collection, data analysis and chart review which made this retrospective analysis possible.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ACI | Autologous Chondrocyte Implantation |
| ACLR | Anterior Cruciate Ligament Reconstruction |
| BMI | Body Mass Index |
| CI | Confidence Interval |
| CSIs | Corticosteroid Injections |
| IKDC | International Knee Documentation Committee Subjective Score |
| I &D | Irrigation and Debridement |
| IRB | Institutional Review Board |
| KOOS | Knee Injury and Osteoarthritis Outcome Score |
| LOA | Lysis of Adhesions |
| MACI | Matrix-Associated or Autologous Chondrocyte Implantation |
| MAT | Meniscal Allograft Transplantation |
| MUA | Manipulation Under Anesthesia |
| OCA | Osteochondral Allograft Transplantation |
| OR | Odds Ratio |
| PASS | Patient Acceptable Symptom State |
| PROMs | Patient-Reported Outcome Measures |
| RSMT | Restricted Mean Survival Time |
| TKA | Total Knee Arthroplasty |
| TTO | Tibial Tubercle Osteotomy |
| VAS | Visual Analog Scale |
References
- Basad, E.; Wissing, F.R.; Fehrenbach, P.; Rickert, M.; Steinmeyer, J.; Ishaque, B. Matrix-induced autologous chondrocyte implantation (MACI) in the knee: Clinical outcomes and challenges. Knee Surg. Sports Traumatol. Arthrosc. 2015, 23, 3729–3735. [Google Scholar] [CrossRef] [Scilit]
- Hinckel, B.B.; Gomoll, A.H. Autologous Chondrocytes and Next-Generation Matrix-Based Autologous Chondrocyte Implantation. Clin. Sports Med. 2017, 36, 525–548. [Google Scholar] [CrossRef] [Scilit]
- Schumacher, H.R.; Chen, L.X. Injectable corticosteroids in treatment of arthritis of the knee. Am. J. Med. 2005, 118, 1208–1214. [Google Scholar] [CrossRef] [Scilit]
- Stone, S.; Malanga, G.A.; Capella, T. Corticosteroids: Review of the History, the Effectiveness, and Adverse Effects in the Treatment of Joint Pain. Pain Physician 2021, 24, S233–S246. [Google Scholar] [CrossRef] [Scilit]
- Wernecke, C.; Braun, H.J.; Dragoo, J.L. The Effect of Intra-articular Corticosteroids on Articular Cartilage: A Systematic Review. Orthop. J. Sports Med. 2015, 3, 2325967115581163. [Google Scholar] [CrossRef] [Scilit]
- Cooper, B.J.; Kesinger, A.; Welch, G.E.; Carroll, J.M.; Lutz, A.; Shanley, E.; Thigpen, C.A.; Tolan, S.J.; Kissenberth, M.J.; Pill, S.G. Judicious use of corticosteroid injections prior to shoulder arthroplasty does not compromise outcomes at a minimum of 2 years following surgery. J. Shoulder Elb. Surg. 2024, 33, S49–S54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, S.; Li, H.; Zhong, Y.; Xie, Y.; Chen, J.; Chen, Y.; Chen, S. Functional and Structural Outcomes After Arthroscopic Rotator Cuff Repair With or Without Preoperative Corticosteroid Injections. Am. J. Sports Med. 2023, 51, 733–742. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koch, K.; Trefzer, R.; Hariri, M.; Mick, P.; Walker, T.; Tsitlakidis, S.; Weishorn, J. The patient acceptable symptomatic state for commonly used outcome scores 10 years after matrix-associated autologous chondrocyte implantation. Knee Surg. Sports Traumatol. Arthrosc. 2026, 34, 64–71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nassar, J.E.; Guerin, G.; Keel, T.; Russo, R.; Familiari, F.; Tollefson, L.V.; LaPrade, R.F. Autologous chondrocyte implantation, matrix-induced autologous chondrocyte implantation, osteochondral autograft transplantation and osteochondral allograft improve knee function and pain with considerations for patient and cartilage defects characteristics: A systematic review and meta-analysis. Knee Surg. Sports Traumatol. Arthrosc. 2025, 33, 2745–2762. [Google Scholar] [CrossRef] [Scilit]
- Nawaz, S.Z.; Bentley, G.; Briggs, T.W.; Carrington, R.W.; Skinner, J.A.; Gallagher, K.R.; Dhinsa, B.S. Autologous chondrocyte implantation in the knee: Mid-term to long-term results. J. Bone Jt. Surg. 2014, 96, 824–830. [Google Scholar] [CrossRef] [Scilit]
- Wang, A.S.; Nagelli, C.V.; Lamba, A.; Saris, D.B.F.; Krych, A.J.; Hevesi, M. Minimum 10-Year Outcomes of Matrix-Induced Autologous Chondrocyte Implantation in the Knee: A Systematic Review. Am. J. Sports Med. 2024, 52, 2407–2414. [Google Scholar] [CrossRef] [Scilit]
- Wang, Z.; Credille, K.; Swindell, H.; McCormick, J.R.; Darbandi, A.; Alzein, M.; Dandu, N.; Cole, B.J.; Yanke, A.B. Concomitant Treatment of High-Grade Cartilage Lesions Mitigates Risk of Meniscal Allograft Transplant Failure. Arthroscopy 2024, 40, 1703–1713.e2. [Google Scholar] [CrossRef] [Scilit]
- Slattery, C.; Kweon, C.Y. Classifications in Brief: Outerbridge Classification of Chondral Lesions. Clin. Orthop. Relat. Res. 2018, 476, 2101–2104. [Google Scholar] [CrossRef] [Scilit]
- da Costa, B.R.; Hari, R.; Jüni, P. Intra-articular Corticosteroids for Osteoarthritis of the Knee. JAMA 2016, 316, 2671–2672. [Google Scholar] [CrossRef] [Scilit]
- Lemos, S.E. Editorial Commentary: Periarticular and Intra-Articular Injections May Do the Right Thing for Patients’ Pain but May Be the Wrong Thing for Their Articular Cartilage: Be Careful. Arthroscopy 2022, 38, 1996–1998. [Google Scholar] [CrossRef] [Scilit]
- Pelletier, J.-P.; Raynauld, J.-P.; Abram, F.; Dorais, M.; Paiement, P.; Martel-Pelletier, J. Intra-articular corticosteroid knee injection induces a reduction in meniscal thickness with no treatment effect on cartilage volume: A case-control study. Sci. Rep. 2020, 10, 13789. [Google Scholar] [CrossRef] [Scilit]
- Pirri, C.; Sorbino, A.; Manocchio, N.; Pirri, N.; Devito, A.; Foti, C.; Migliore, A. Chondrotoxicity of Intra-Articular Injection Treatment: A Scoping Review. Int. J. Mol. Sci. 2024, 25, 7010. [Google Scholar] [CrossRef] [Scilit]
- Anigwe, C.; Kucirek, N.K.; Feeley, B.T.; Ma, C.B.; Zhang, A.L.; Lansdown, D.A. Utilization of Autologous Chondrocyte Implantation in the Knee is Increasing While Reoperation Rates Are Decreasing Despite Increasing Preoperative Comorbidities. Arthroscopy 2023, 39, 1464–1471.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhattacharjee, S.; Lee, W.; Lee, M.J.; Shi, L.L. Preoperative corticosteroid joint injections within 2 weeks of shoulder arthroscopies increase postoperative infection risk. J. Shoulder Elb. Surg. 2019, 28, 2098–2102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forsythe, B.; Berlinberg, E.J.; Forlenza, E.M.; Oeding, J.F.; Patel, H.H.; Mascarenhas, R. Corticosteroid injections 2 months before arthroscopic meniscectomy increases the rate of postoperative infections requiring surgical irrigation and debridement. Knee Surg. Sports Traumatol. Arthrosc. 2022, 30, 3796–3804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forsythe, B.; Forlenza, E.M.; Agarwalla, A.; Cohn, M.R.; Lavoie-Gagne, O.; Lu, Y.; Mascarenhas, R. Corticosteroid Injections 1 Month Before Arthroscopic Meniscectomy Increase the Risk of Surgical-Site Infection. Arthroscopy 2021, 37, 2885–2890.e2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Remily, E.; Dubin, J.; Bains, S.S.; Monarrez, R.; Livesey, M.G.; Weir, T.B.; Hameed, D.; Ingari, J.V.; Gilotra, M.N.; Hasan, S.A. Preoperative Corticosteroid Injections Within 4 Weeks of Arthroscopic Shoulder Procedures Are Associated with Increased Postoperative Infection Rates. Arthroscopy 2024, 40, 277–283.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wainwright, J.D.; Gay, S.S.; Nguyen, A.; Weiss, W.M.; Wenke, J.C. Corticosteroid Injection up to 8 Weeks Before Anterior Cruciate Ligament Reconstruction Doubles the Incidence of Postoperative Infection. Arthroscopy 2025, 41, 4021–4025.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.