Autoimmune Hepatitis-like Syndrome in a Patient with Ankylosing Spondylitis: A Case Report


Abstract
1. Introduction and Clinical Significance
2. Case Presentation
- Autoantibodies (2 points): ANA ≥1:160 and anti-LC-1 positive.
- IgG (2 points): IgG 1825 mg/dL (>1.1 × ULN; laboratory ULN, 1600 mg/dL).
- Viral hepatitis excluded (2 points): HAV IgM negative, HBsAg/HBeAg negative, anti-HCV negative.
- Histology (0 points): Liver biopsy discussed but refused; no histological scoring component.

| Timepoint | Key Clinical Findings and Investigations | Management and Outcome |
|---|---|---|
| ~10 years prior | Chronic lumbar pain and limitation of spinal mobility began (history). | No specific treatment documented. |
| February 2024 | Several evaluations for polyarthralgia (per history). | - |
| ~3 months before admission | Insidious onset of polyarthralgia, fatigue/asthenia, dry cough, night sweats; ~20 kg weight loss over ~2 months. | - |
| 2 days before admission | Fever for two days prior to ED presentation. | - |
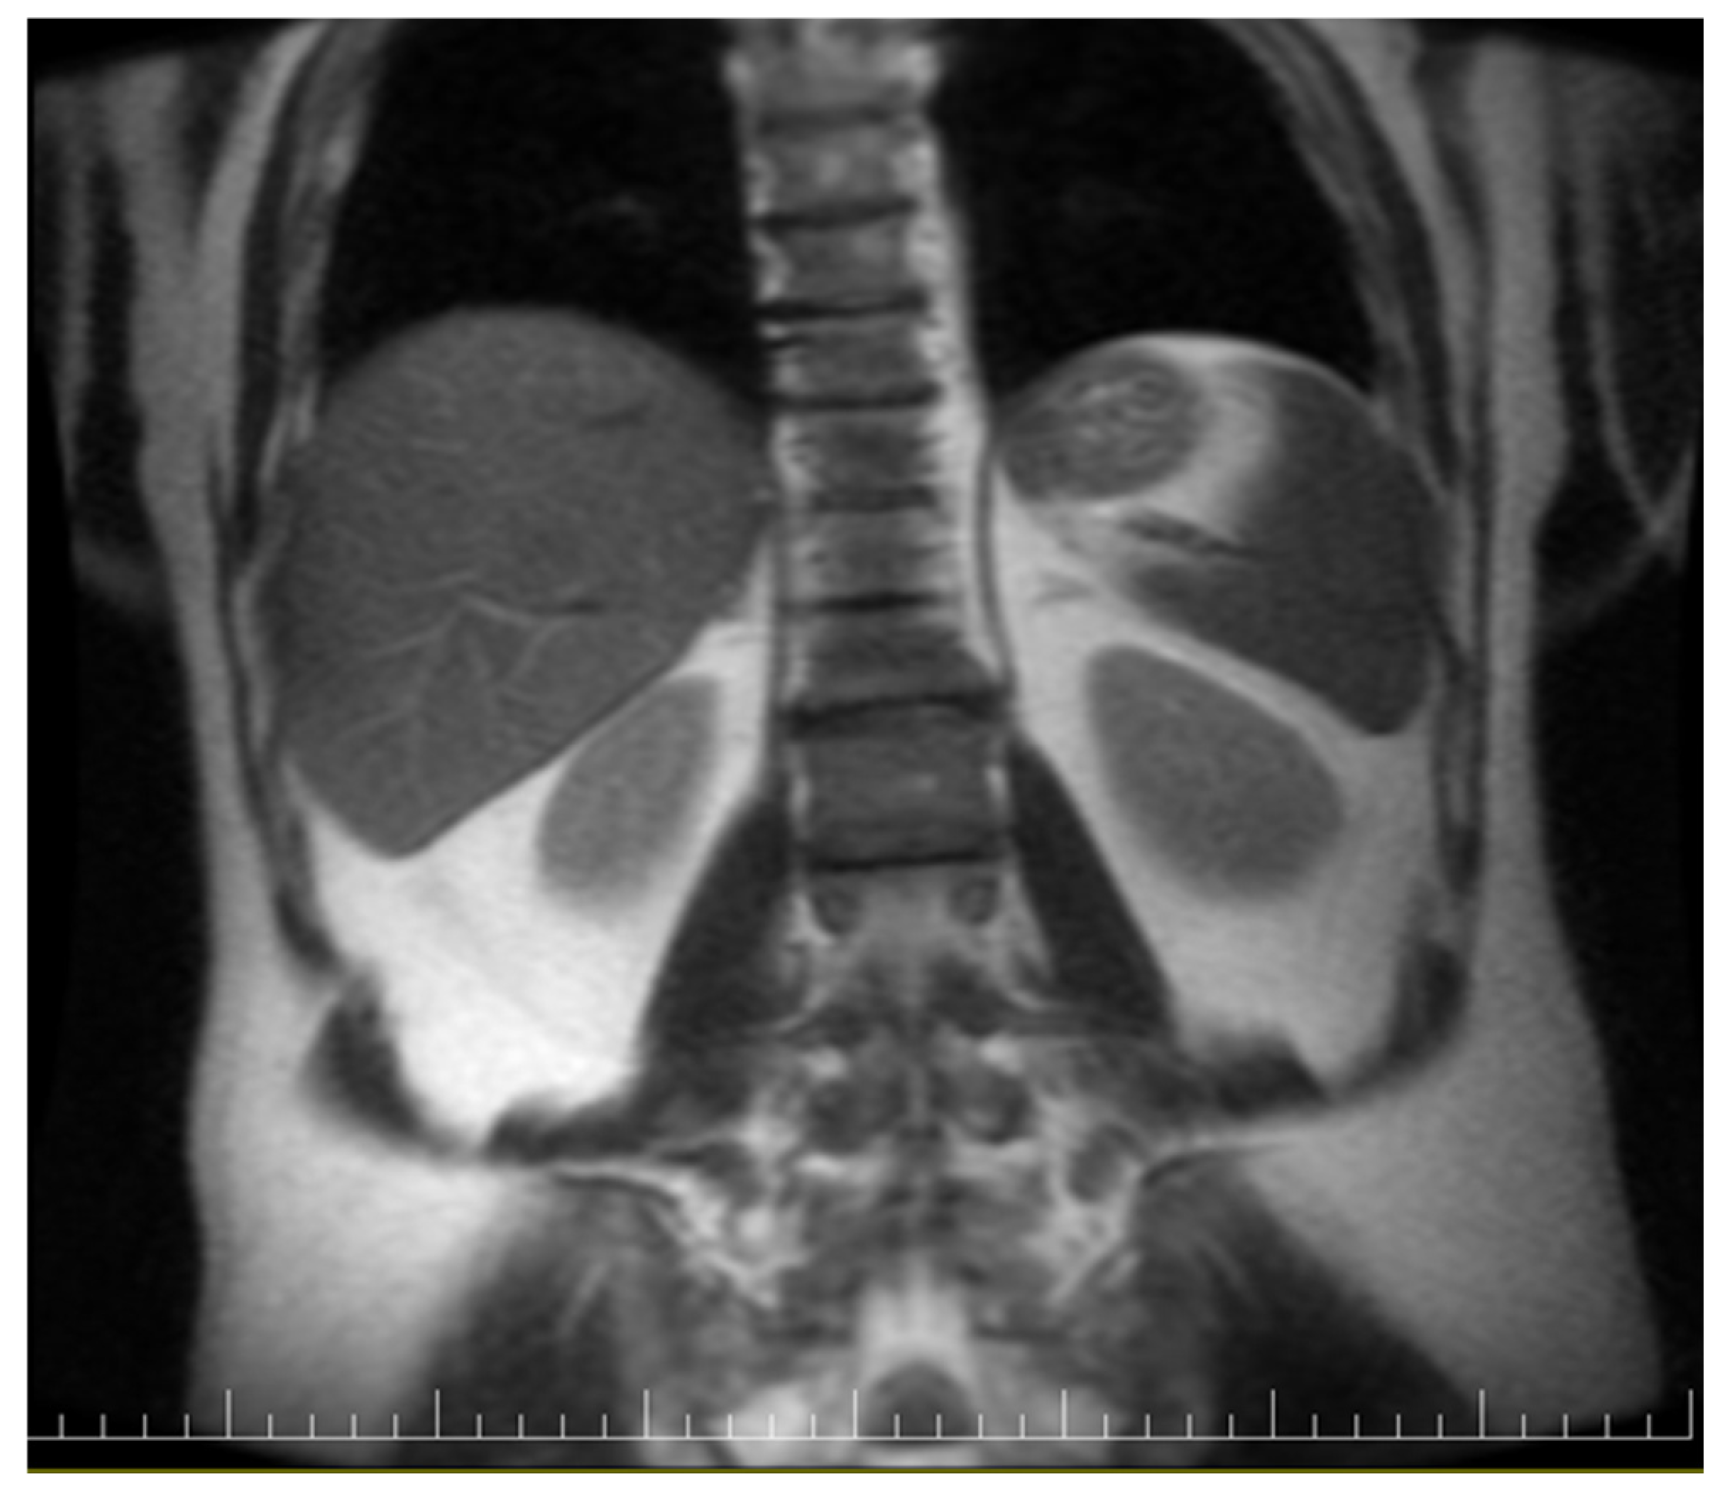
| Admission (inpatient day 0) | Exam: pallor; painful spine on percussion; limited/painful lower limb movement. Labs: markedly elevated inflammatory markers; severe anemia; thrombocytosis; mild transaminase elevation and cholestasis (Table 1). Abdominal ultrasound: no biliary obstruction or focal liver lesions. | Diagnostic workup initiated. |
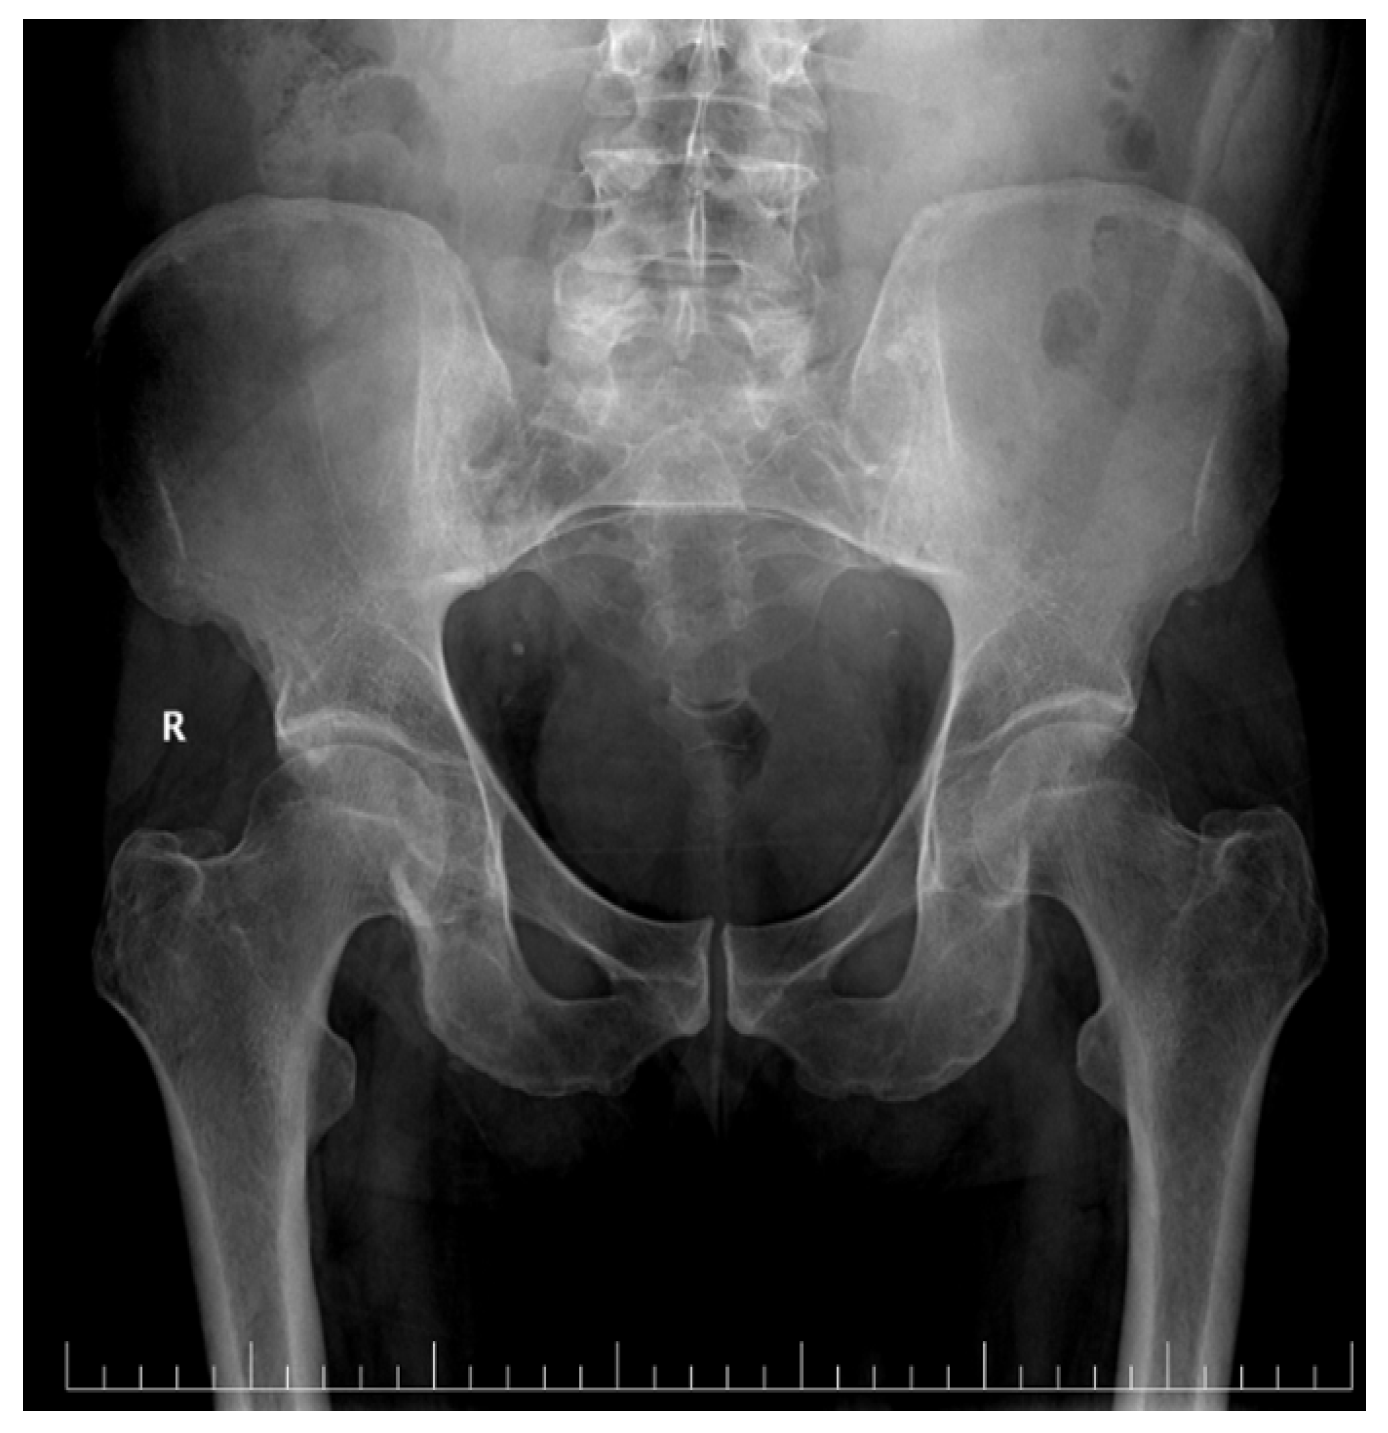
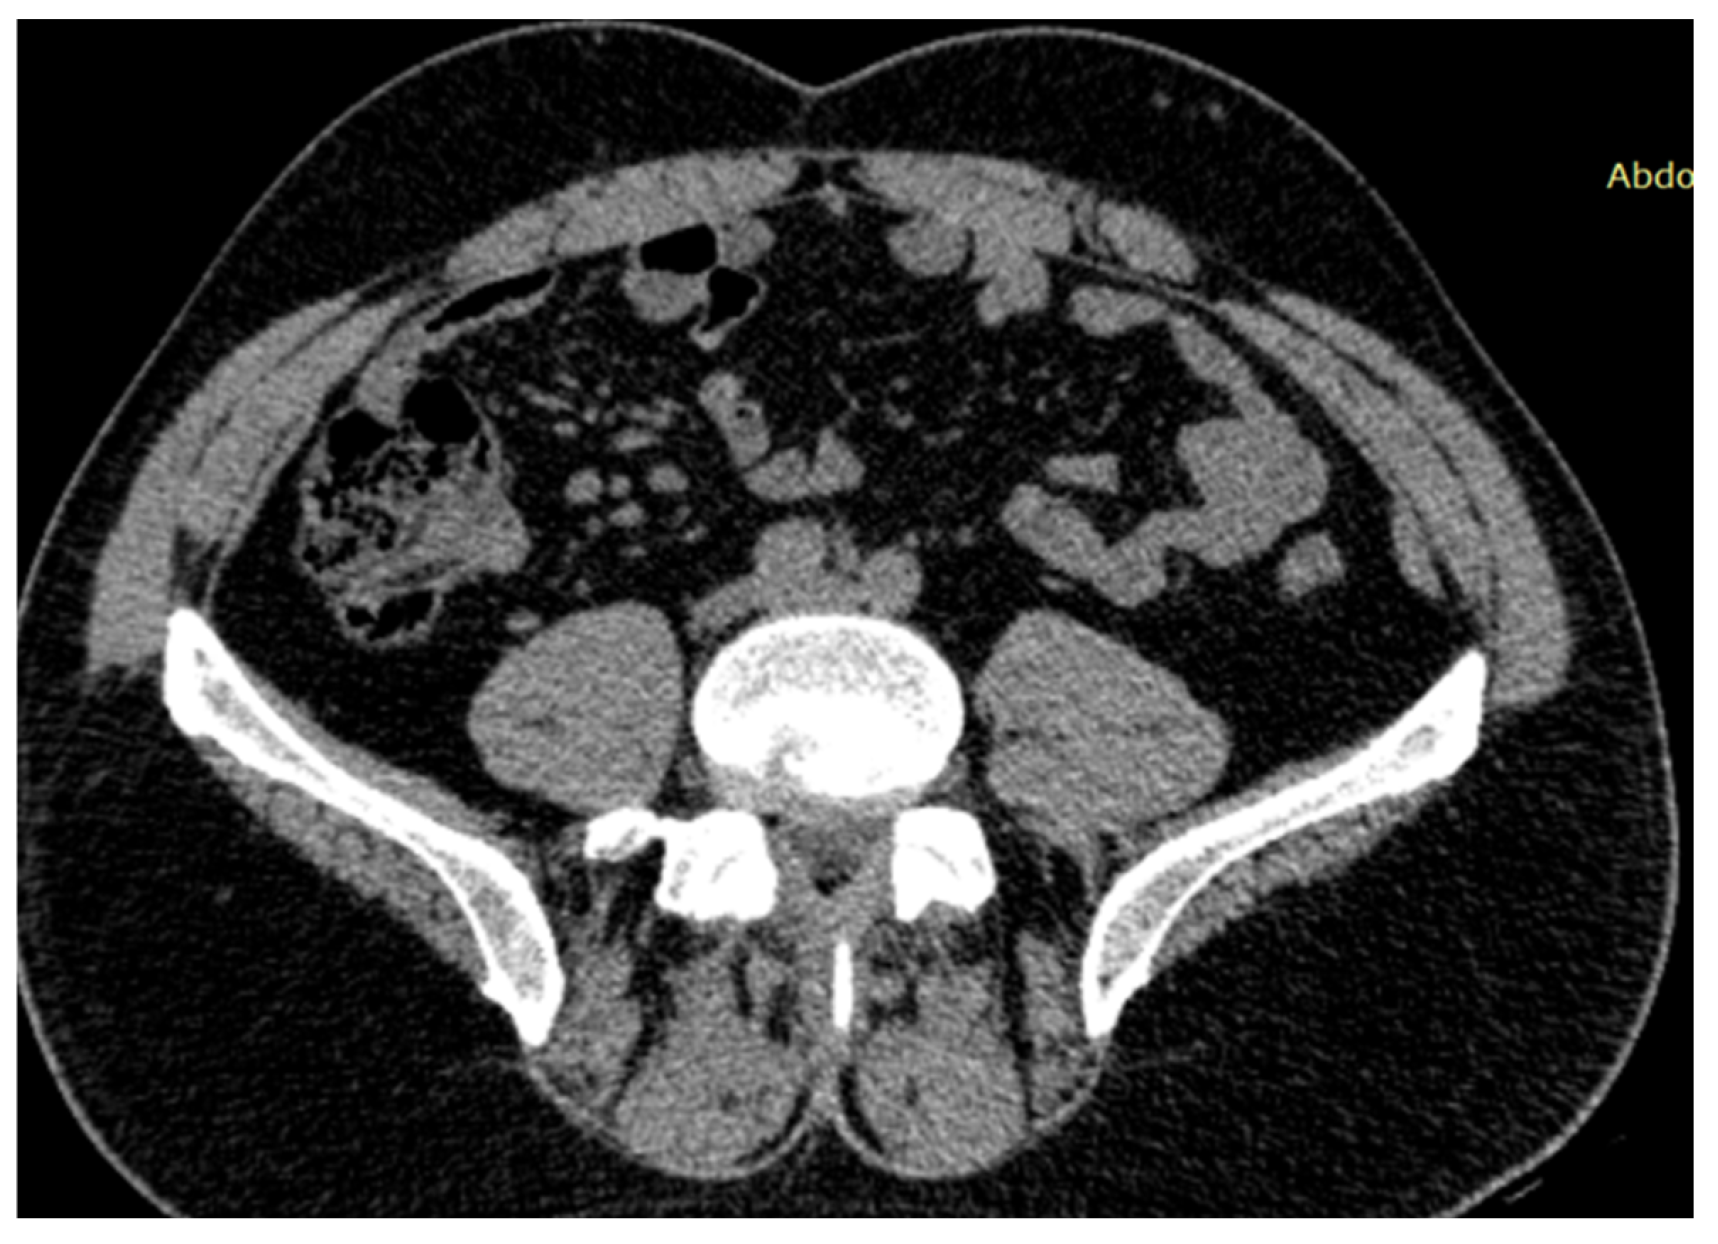
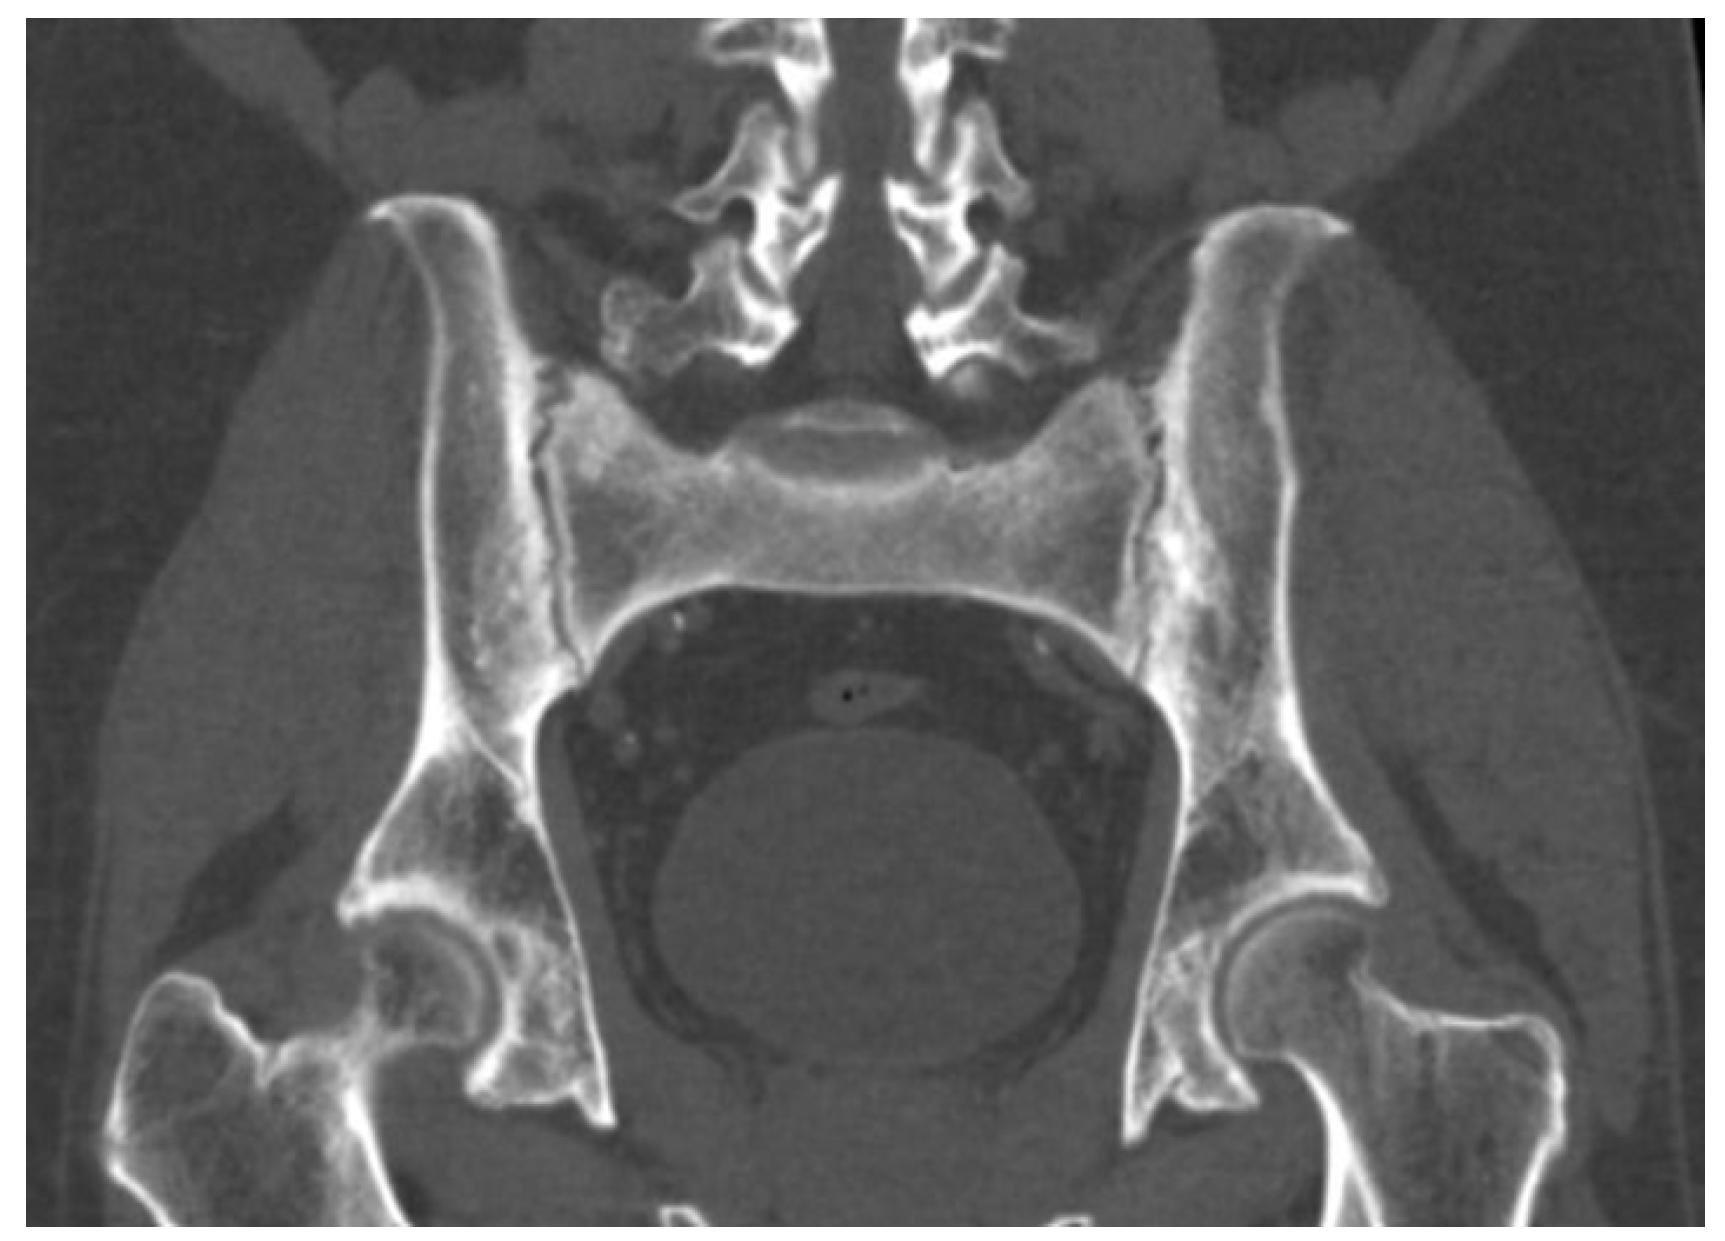
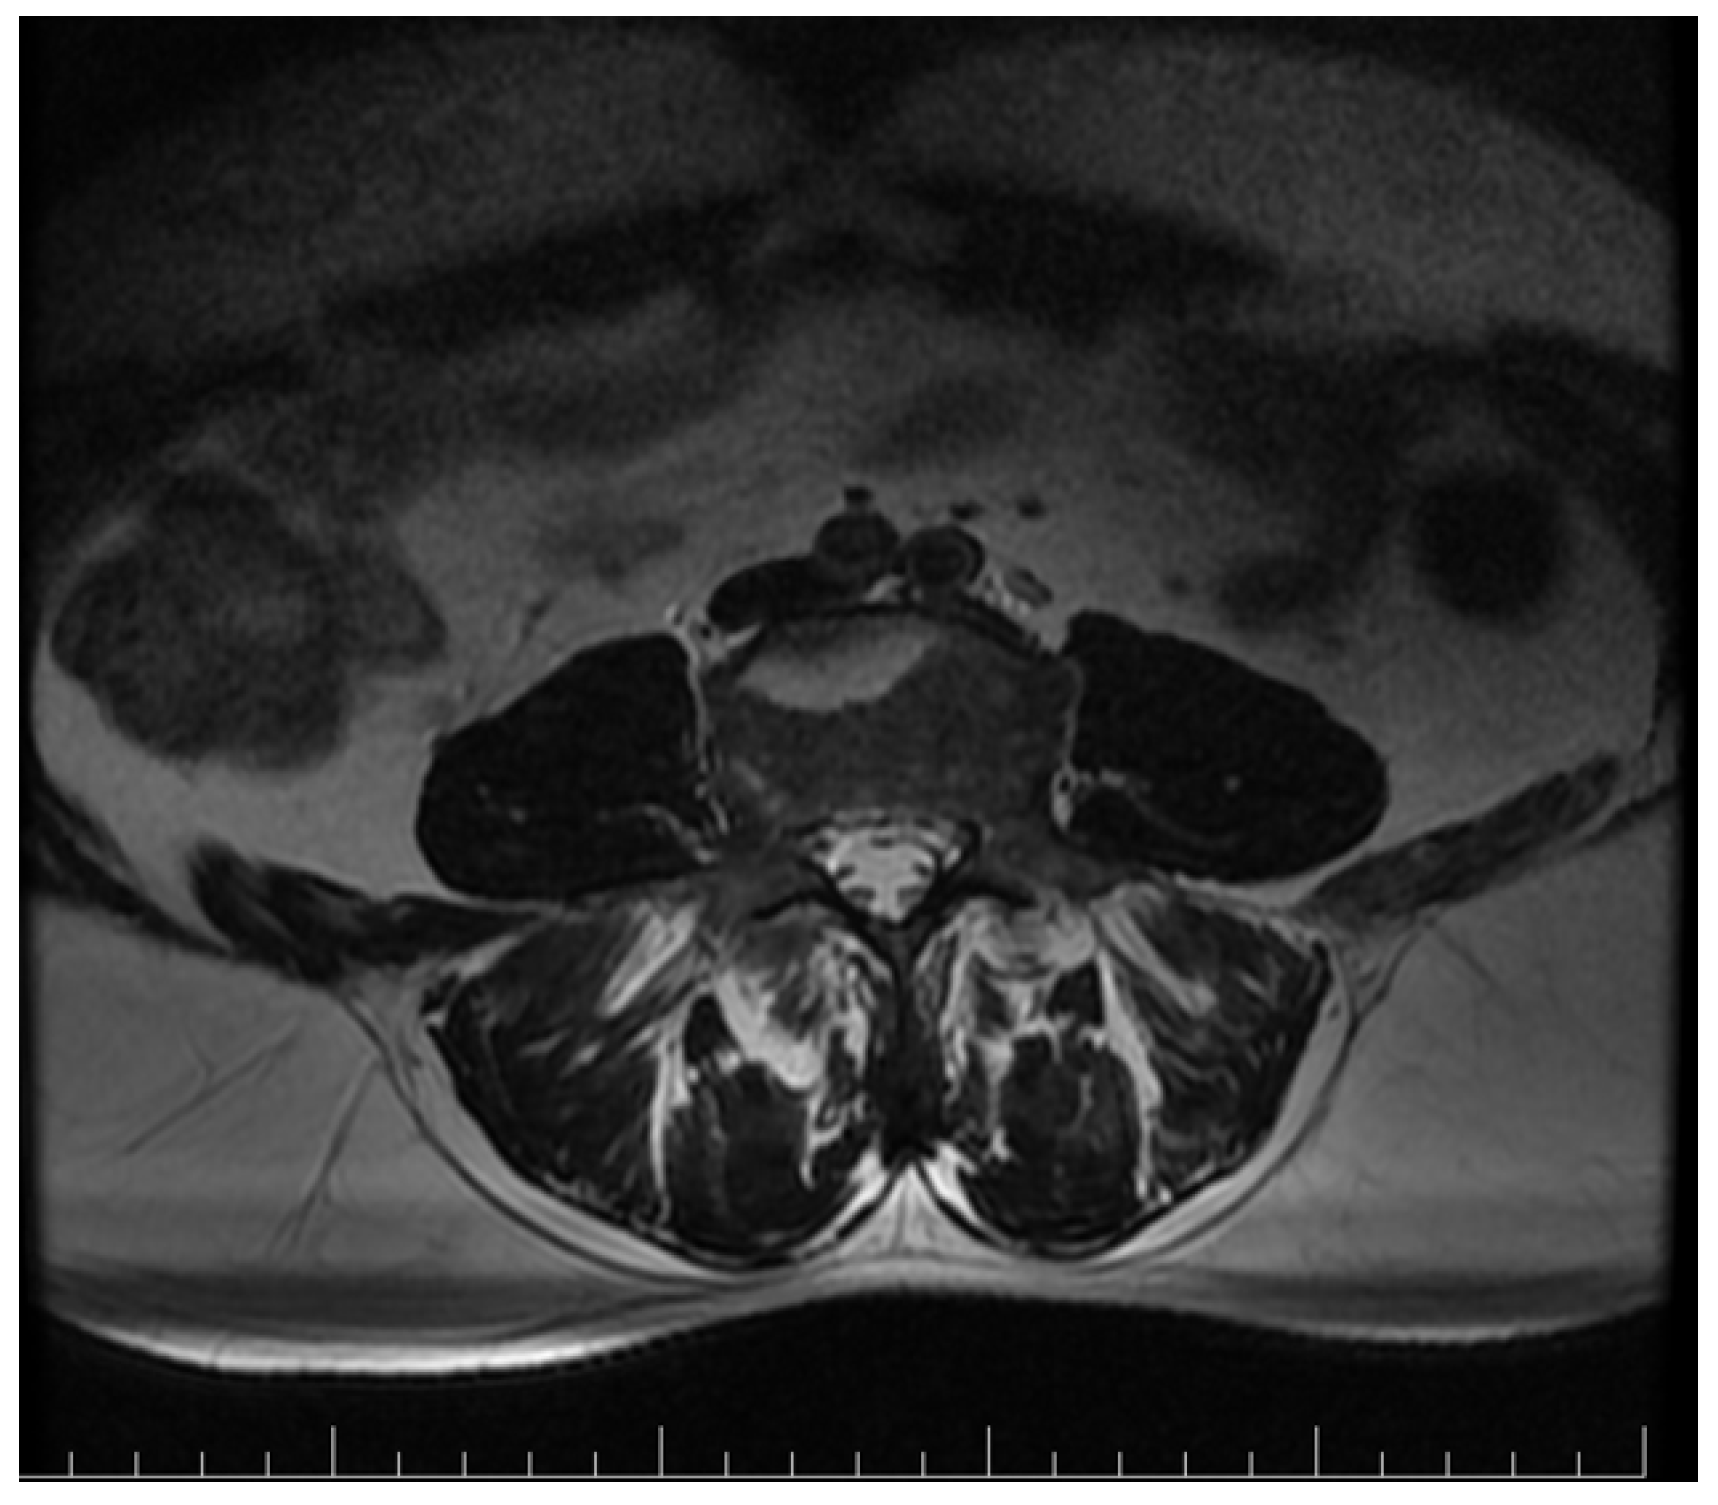
| Inpatient evaluation | Viral hepatitis excluded (HAV IgM, HBsAg/HBeAg, anti-HCV negative). Metabolic/hereditary testing normal (ferritin, urinary copper, A1AT). HLA-B27 positive. Autoimmune liver profile: ANA and anti-LC-1 positive; other liver autoantibodies negative. MRCP negative for PSC. SPEP: elevated gamma fraction; IgG 1825 mg/dL. Tumor markers (AFP, CA19-9, CEA, PSA) normal. GI screening: fecal calprotectin 71 µg/mL; EGD/colonoscopy with biopsies negative for IBD; small bowel MRI negative. Imaging: pelvic X-ray (right hip joint space narrowing); CT shows mesenteric inflammatory nodes + syndesmophytes and sacroiliac changes; pelvic MRI shows sacroiliitis with erosions and bone marrow edema + syndesmophytes. | Short-course prednisone 0.5 mg/kg/day for 5 days had been given for flare control and coincided with initial biochemical improvement, but pain (NRS 9) and CRP remained high. NSAIDs were then introduced. Rheumatology consult: mixed ankylosing spondyloarthritis; bilateral stage 2 sacroiliitis; recommends sulfasalazine and NSAIDs PRN. Liver biopsy discussed but refused. |
| Discharge/treatment plan | Inflammatory markers and liver tests improving by discharge (Table 1). | Sulfasalazine started 500 mg/day with weekly +500 mg titration to 4 g/day. Silymarin and essential amino acids prescribed. Because several interventions overlapped, subsequent normalization of liver tests was interpreted cautiously and not attributed to a single therapy. |
| 4-week follow-up | Liver enzymes normalized. | Symptoms completely alleviated. No adverse effects observed. Favorable biochemical follow-up maintained. |
| 3-month follow-up | Normal inflammatory markers and normal liver profile; asymptomatic. | Continued favorable outcome. |
3. Discussion
4. Limitations
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| AIH | Autoimmune hepatitis |
| AS | Ankylosing spondylitis |
| IBD | Inflammatory bowel disease |
| HLA | Human leukocyte antigen |
| INR | International normalized ratio |
| ESR | Erythrocyte sedimentation rate |
| CRP | C-reactive protein |
| ALT | Alanine aminotransferase |
| ALP | Alkaline phosphatase |
| AST | Aspartate aminotransferase |
| GGT | Gamma-glutamyl transferase |
| WBC | White blood cells |
| ANA | Antinuclear antibodies |
| LC-1 | Anti-liver cytosol type 1 antibodies |
| M2-3E | Antimitochondrial antibody fractions |
| PML | Promyelocytic leukemia protein |
| LKM-1 | Anti-liver kidney microsome type 1 |
| SLA/LP | Anti-soluble liver antigen/liver–pancreas |
| MRCP | Magnetic resonance cholangiopancreatography |
| HAV | Hepatitis A virus |
| HBsAg | Hepatitis B surface antigen |
| HBeAg | Hepatitis B e-antigen |
| HCV | Hepatitis C virus |
| EGD | Esophagogastroduodenoscopy |
| MRI | Magnetic resonance imaging |
| NSAID | Nonsteroidal anti-inflammatory drug |
| AFP | Alpha-fetoprotein |
| CA 19-9 | Carbohydrate antigen 19-9 |
| CEA | Carcinoembryonic antigen |
| PSA | Prostate-specific antigen |
References
- Braun, J.; Sieper, J. Ankylosing spondylitis. Lancet 2007, 369, 1379–1390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sieper, J.; Poddubnyy, D. Axial spondyloarthritis. Lancet 2017, 390, 73–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taurog, J.D.; Chhabra, A.; Colbert, R.A. Ankylosing spondylitis and axial spondyloarthritis. N. Engl. J. Med. 2016, 374, 2563–2574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harbord, M.; Annese, V.; Vavricka, S.R.; Allez, M.; Acosta, M.B.-D.; Borberg, K.; Burisch, J.; De Vos, M.; De Vries, A.-M.; Dick, A.D.; et al. The first European evidence-based consensus on extra-intestinal manifestations in inflammatory bowel disease. J. Crohns Colitis 2016, 10, 239–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vavricka, S.R.; Schoepfer, A.; Scharl, M.; Lakatos, P.L.; Navarini, A.; Rogler, G. Extraintestinal manifestations of inflammatory bowel disease. Inflamm. Bowel Dis. 2015, 21, 1982–1992. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Orchard, T.R. Management of arthritis in patients with inflammatory bowel disease. Gastroenterol. Hepatol. 2012, 8, 327–329. [Google Scholar]
- Mack, C.L.; Adams, D.; Assis, D.N.; Kerkar, N.; Manns, M.P.; Mayo, M.J.; Vierling, J.M.; Alsawas, M.; Murad, M.H.; Czaja, A.J. Diagnosis and management of autoimmune hepatitis in adults and children: 2019 practice guidance and guidelines from the American Association for the Study of Liver Diseases. Hepatology 2020, 72, 671–722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heneghan, M.A.; Yeoman, A.D.; Verma, S.; Smith, A.D.; Longhi, M.S. Autoimmune hepatitis. Lancet 2013, 382, 1433–1444. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozorio, G.; McGarity, B.; Bak, H.; Jordan, A.S.; Lau, H.; Marshall, C. Autoimmune hepatitis following infliximab therapy for ankylosing spondylitis. Med. J. Aust. 2007, 187, 524–526. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boberg, K.M.; Chapman, R.W.; Hirschfield, G.M.; Lohse, A.W.; Manns, M.P.; Schrumpf, E. International Autoimmune Hepatitis Group. Overlap syndromes: The International Autoimmune Hepatitis Group (IAIHG) position statement on a controversial issue. J. Hepatol. 2011, 54, 374–385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, D.; Wu, G.Y. Autoimmune hepatitis associated with other autoimmune diseases: A critical review. J. Clin. Transl. Hepatol. 2025, 13, 869–877. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manns, M.P.; Lohse, A.W.; Vergani, D. Autoimmune hepatitis—Update 2015. J. Hepatol. 2015, 62, S100–S111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schett, G.; Lories, R.J.; D’Agostino, M.-A.; Elewaut, D.; Kirkham, B.; Soriano, E.R.; McGonagle, D. Enthesitis: From pathophysiology to treatment. Nat. Rev. Rheumatol. 2017, 13, 731–741. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hennes, E.M.; Zeniya, M.; Czaja, A.J.; Parés, A.; Dalekos, G.N.; Krawitt, E.L.; Bittencourt, P.L.; Porta, G.; Boberg, K.M.; Hofer, H.; et al. Simplified criteria for the diagnosis of autoimmune hepatitis. Hepatology 2008, 48, 169–176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Association for the Study of the Liver. EASL Clinical Practice Guidelines on the management of autoimmune hepatitis. J. Hepatol. 2025, 83, 453–501. [Google Scholar] [CrossRef] [Scilit] [PubMed]


| Parameter | On Admission | Midway Evaluation | On Discharge | Reference Range | × ULN (On Admission) |
|---|---|---|---|---|---|
| WBC ×103/µL | 11.4 | 10.2 | 9.2 | 4–10 × 103/µL | 1.14 |
| Hemoglobin g/L | 75 | 94 | 97.2 | 130–170 g/L | 0.44 |
| Hematocrit % | 21.9 | 29.4 | 29.5 | 40–52% | 0.42 |
| Platelets ×103/µL | 638 | 659 | 576 | 150–400 × 103/µL | 1.59 |
| INR | 1.02 | 0.98 | 0.96 | 0.8–1.2 | 0 |
| Serum iron (µmol/L) | 4.06 | 10.2 | 24 | 10–30 µmol/L | 0.14 |
| ESR (mm/h) | 105 | 98 | 74 | 0–15 mm/h | 7 |
| CRP (mg/L) | 235.4 | 180.5 | 65.4 | 0–5 mg/L | 47.08 |
| Fibrinogen | 635 | 380 | 245 | 200–400 mg/dL | 1.59 |
| Serum proteins (g/L) | 62.5 | 69 | 71 | 64–83 g/L | 0.75 |
| Albumin (g/L) | 29.8 | 30.1 | 34 | 35–50 g/L | 0.6 |
| AST (U/L) | 85.45 | 25.2 | 19.3 | 0–40 U/L | 2.14 |
| ALT (U/L) | 109.6 | 58.4 | 24.5 | 0–41 U/L | 2.67 |
| ALP (U/L) | 417 | 258 | 179 | 40–130 U/L | 3.21 |
| GGT (U/L) | 246 | 95.2 | 45 | 8–61 U/L | 4.03 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Crăciun Ciorba, N.M.; Ciorba, I.M. Autoimmune Hepatitis-like Syndrome in a Patient with Ankylosing Spondylitis: A Case Report. Reports 2026, 9, 143. https://doi.org/10.3390/reports9020143
Crăciun Ciorba NM, Ciorba IM. Autoimmune Hepatitis-like Syndrome in a Patient with Ankylosing Spondylitis: A Case Report. Reports. 2026; 9(2):143. https://doi.org/10.3390/reports9020143
Chicago/Turabian StyleCrăciun Ciorba, Nicoleta Maria, and Ilie Marius Ciorba. 2026. "Autoimmune Hepatitis-like Syndrome in a Patient with Ankylosing Spondylitis: A Case Report" Reports 9, no. 2: 143. https://doi.org/10.3390/reports9020143
APA StyleCrăciun Ciorba, N. M., & Ciorba, I. M. (2026). Autoimmune Hepatitis-like Syndrome in a Patient with Ankylosing Spondylitis: A Case Report. Reports, 9(2), 143. https://doi.org/10.3390/reports9020143