


Abstract
Amyloidosis is a form of plasma cell dyscrasia of unknown etiology, pathologically characterized by the extracellular deposit of fibrils derived from the light chain of monoclonal immunoglobulin. The involvement of the airways is more common in primary amyloidosis and is classified into: tracheobronchial amyloidosis, nodular parenchymal, diffuse parenchymal. The tracheobronchial form is usually the most frequent and is characterized by the presence of multiple submucosal plaques or, more rarely, by pseudotumoral endobronchial masses. Symptoms in the initial phase may be silent, subsequently manifesting themselves with cough, dyspnea, hemoptysis.
1. Introduction
Amyloid must be understood as any substance that presents a green birefringence under polarized light, after Congo red staining, a fibrillar structure in electron microscopy. The deposit and infiltration of this substance constitutes Amyloidosis. Although at first it was believed that amyloid was a single substance, it is currently known that the proteins that constitute it are different, all similar to each other from a morphological point of view, but different from a biochemical point of view (Piacenza 1992). Various proteins of this type have been identified in various combinations (immunoglobulins). The most important are amyloid L (AL) and amyloid A (AA). L amyloidosis derives from light chain immunoglobulins and is therefore usually associated with an abnormal functioning of plasma cells (Prakash 1995), both localized in the lungs and as part of a systemic pathology such as multiple myeloma or macroglobulinemia. Amyloidosis A derives from an acute serum phase reagent (AAS) synthesized in the liver. The latter can form in various conditions, connective tissue diseases (in particular rheumatoid arthritis), chronic infections (in particular tuberculosis), bronchiectasis and some neoplasms (such as Hodgkin's lymphoma). Due to the great variety of clinical and pathological manifestations, amyloidosis has been classified above all in relation to its biochemical origin. The traditional classification provides for four main forms of disease: Primary amyloidosis, in which no associated pathology is recognized or there is a concomitant disorder of plasma cells (most often multiple myeloma); secondary amyloidosis, in which there is an underlying or identifiable chronic inflammatory disease, such as tuberculosis, bronchiectasis, rheumatic disease; hereditary amyloidosis, a relatively rare form that can be localized in a specific tissue such as a nerve; Senile amyloidosis which affects many organs and tissues and is usually found in people over seventy (Fraser et al. 2006). The involvement of the respiratory tract can be isolated or integrated in the framework of a systemic amyloidosis that involves all organs. The localized form is the most frequent. Respiratory amyloidosis can take three main and characteristic forms: tracheobronchial, nodular parenchymal (the nodules can be solitary located at the periphery of the lung or more often multiple), diffuse parenchymal (almost exclusively affects the interstitium and is characterized by an infiltration of the alveolar wall by the amyloid substance, especially around the capillaries). The tracheobronchial form is probably the most frequent. It manifests itself with the presence of multiple submucosal plaques in the lumen of the trachea and bronchi or more rarely with a pseudotumoral endobronchial mass of a friable consistency that is easy to bleed, with an irregular surface, generally of a pinkish-yellowish color (Piacenza 1992). Radiologically, the lesions of the respiratory tract are visible at the level of the trachea, the main bronchi and the lobar and segmental bronchi. They can be observed on standard radiological examination and better still on CT. They are characterized by a focal or diffuse thickening of the airways or they may present the appearance of multiple nodules that develop at the level of the tracheal wall, of the main, lobar, or segmental bronchi projecting into the lumen and can cause mild, moderate, or considerable entity. A rare and particular anomaly, called osteoplastic tracheopathy (characterized by diffuse or nodular ossification of the tracheobronchial mucosa) can be similar to tracheobronchial amyloidosis. As evidenced by some observations of amyloid deposits with histological studies of these tracheae, it can be said that osteoplastic tracheopathy is a late stage in the evolution of tracheobronchial amyloidosis (Grenier 1993).
2. Clinical Case
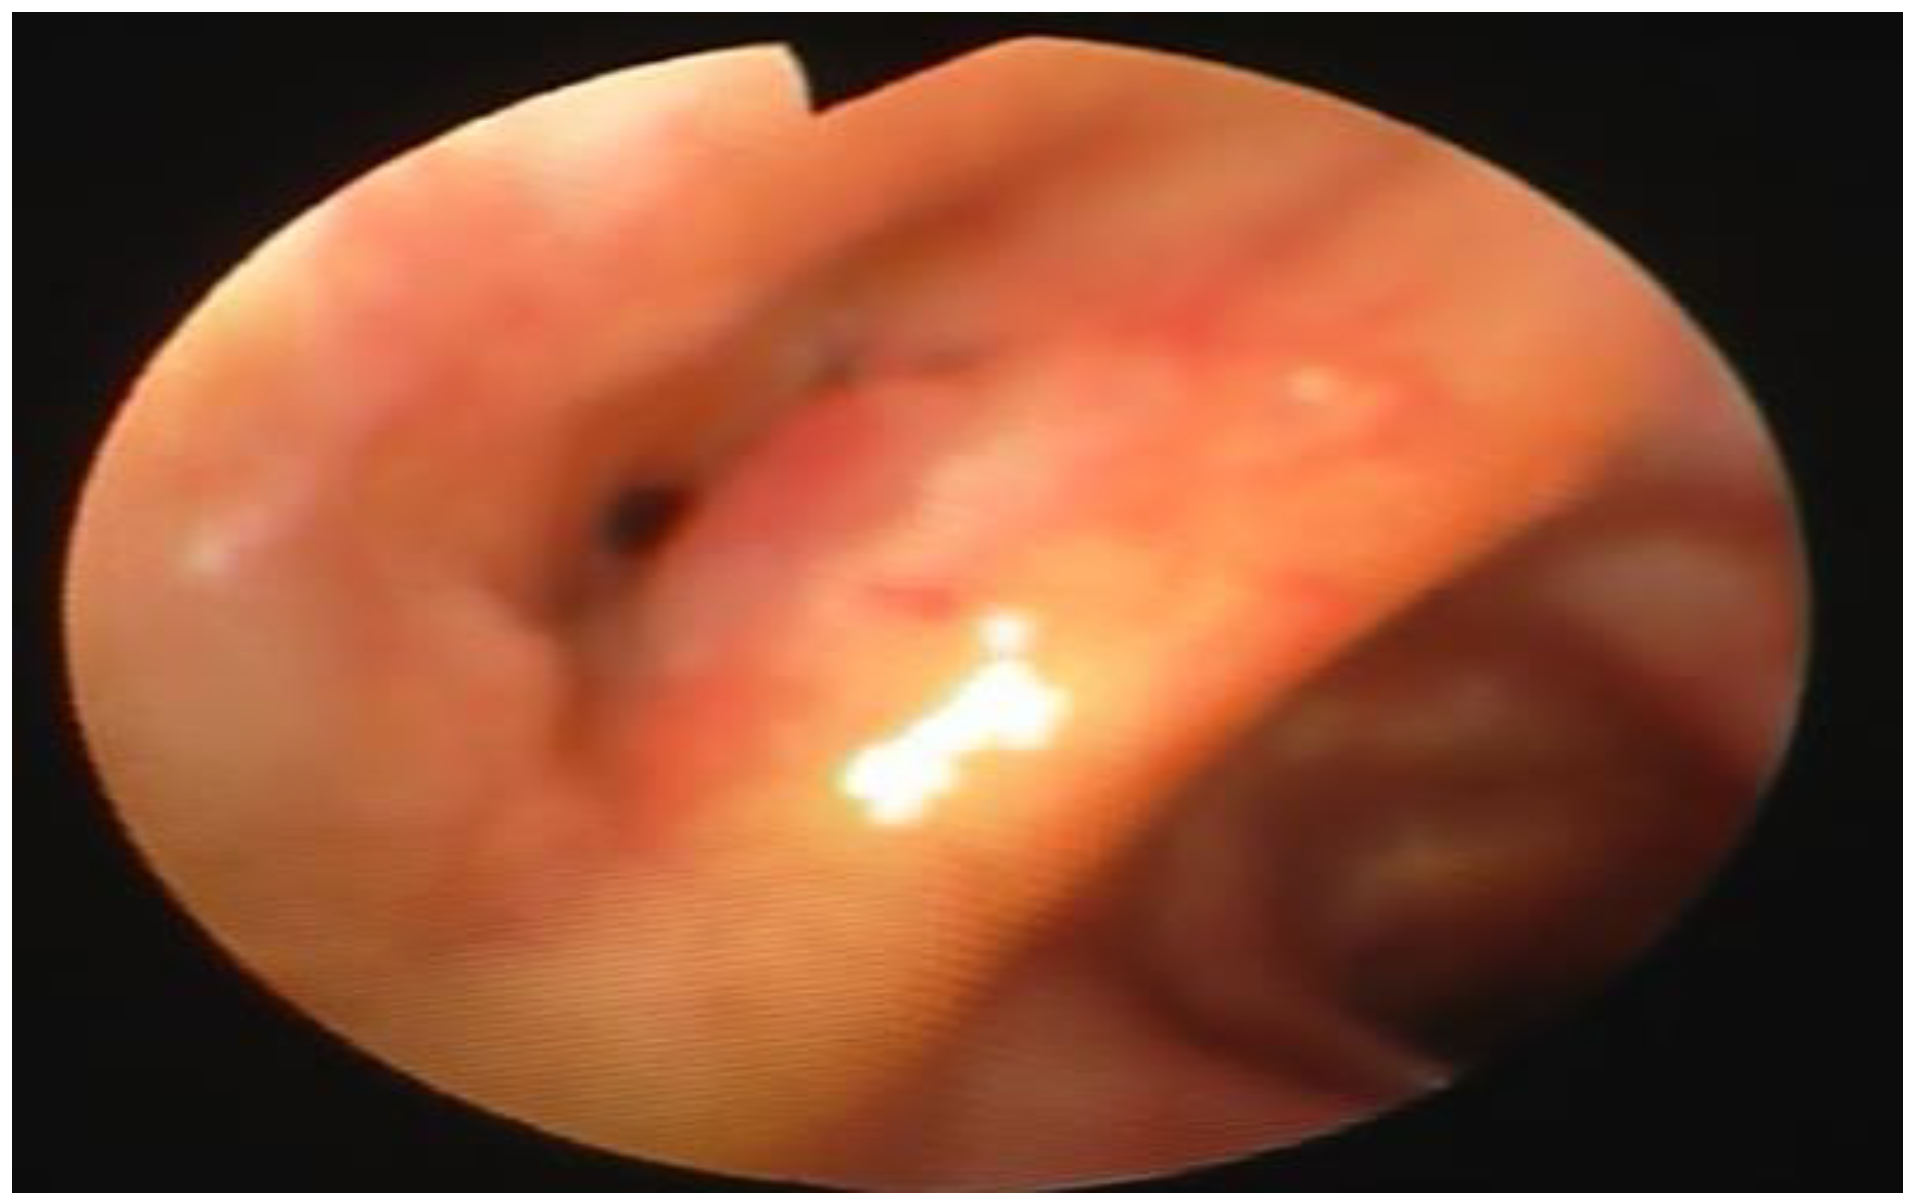
A 75-year-old woman, housewife, non-smoker, in good health until the age of 65 when, following the appearance of a symptomatology characterized by dry, persistent and resistant cough to antibiotic and anti-inflammatory therapy, she performed, upon request by a pulmonologist, a chest x-ray examination with a negative result. Bronchoscopy revealed a thickening of the bronchial mucosa at the level of the branches of the left lower lobe bronchus. Subsequently, in addition to the persistence of the cough, she presented recurrent episodes of productive cough (at times with the emission of blood-streaked sputum) she manifested fever and dyspnea of modest entity. In November 2010 she performed pneumological consultancy at the territorial Pneumo-physiology Service of Lecce, in that circumstance the specialist doctor requested chest x-ray and CT (Figure 1 and Figure 2). After these last examinations which revealed the presence of a left basal thickening, she was asked to perform fibrobronchoscopy. In the latter examination, the presence of nodular formations at the level of the tracheal part was found (Figure 5), occlusion of the left lower lobe bronchus due to the presence of a pseudotumoral mass (Figure 3), stenosis of the lingula and upper lore bronchus proper due to considerable thickening of the spur (Figure 4) and stenosis serrata of the middle lobar bronchus due to thickening of the mucosa (Figure 6). The biopsy examination was positive for tracheo-bronchial amyloidosis.
Figure 1.
Chest X-ray. Left positive basal pulmonary thickening.
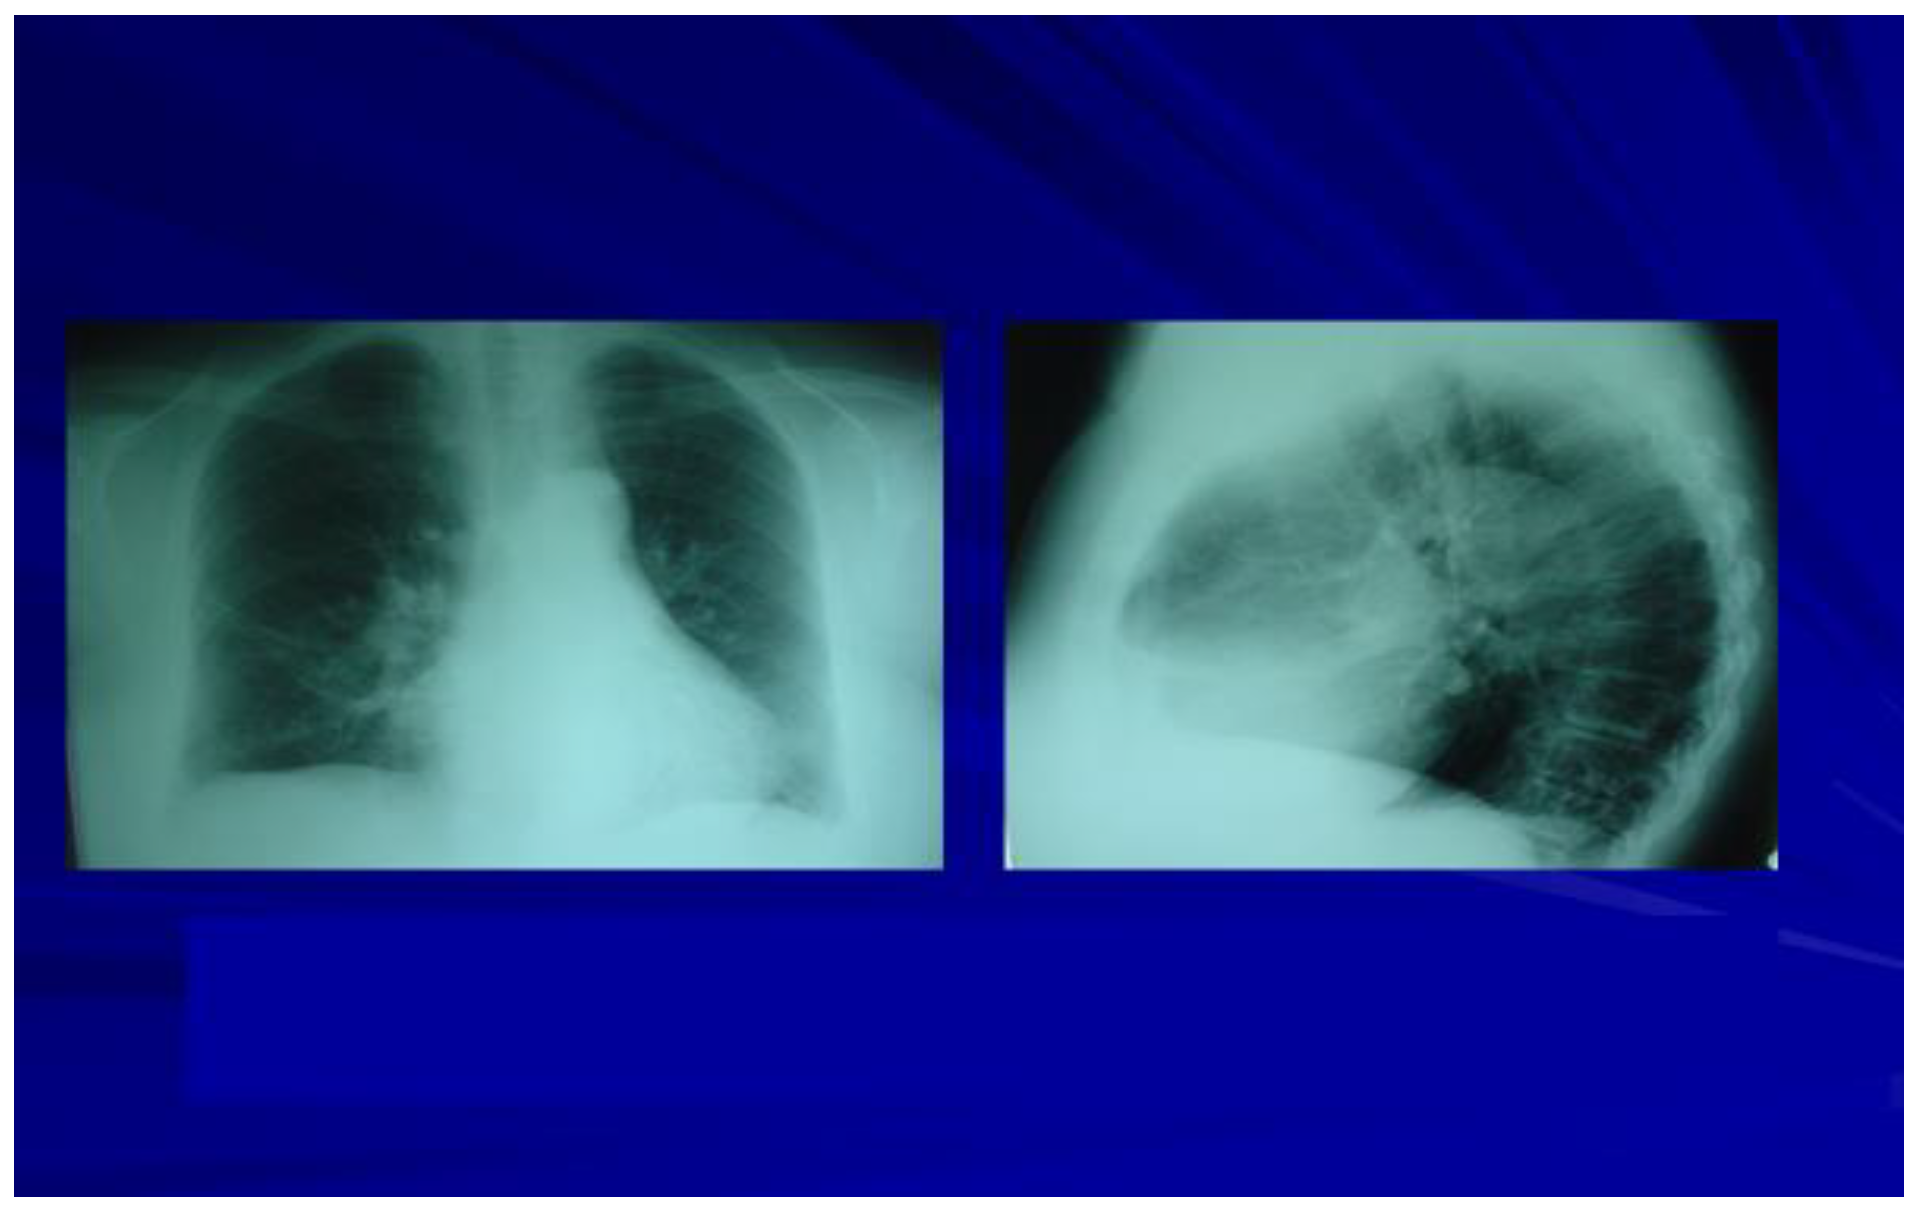
Figure 2.
Chest CAT. Left lower lobe pulmonary thickening. Marked stenosis of the left lower broncho-lobar.
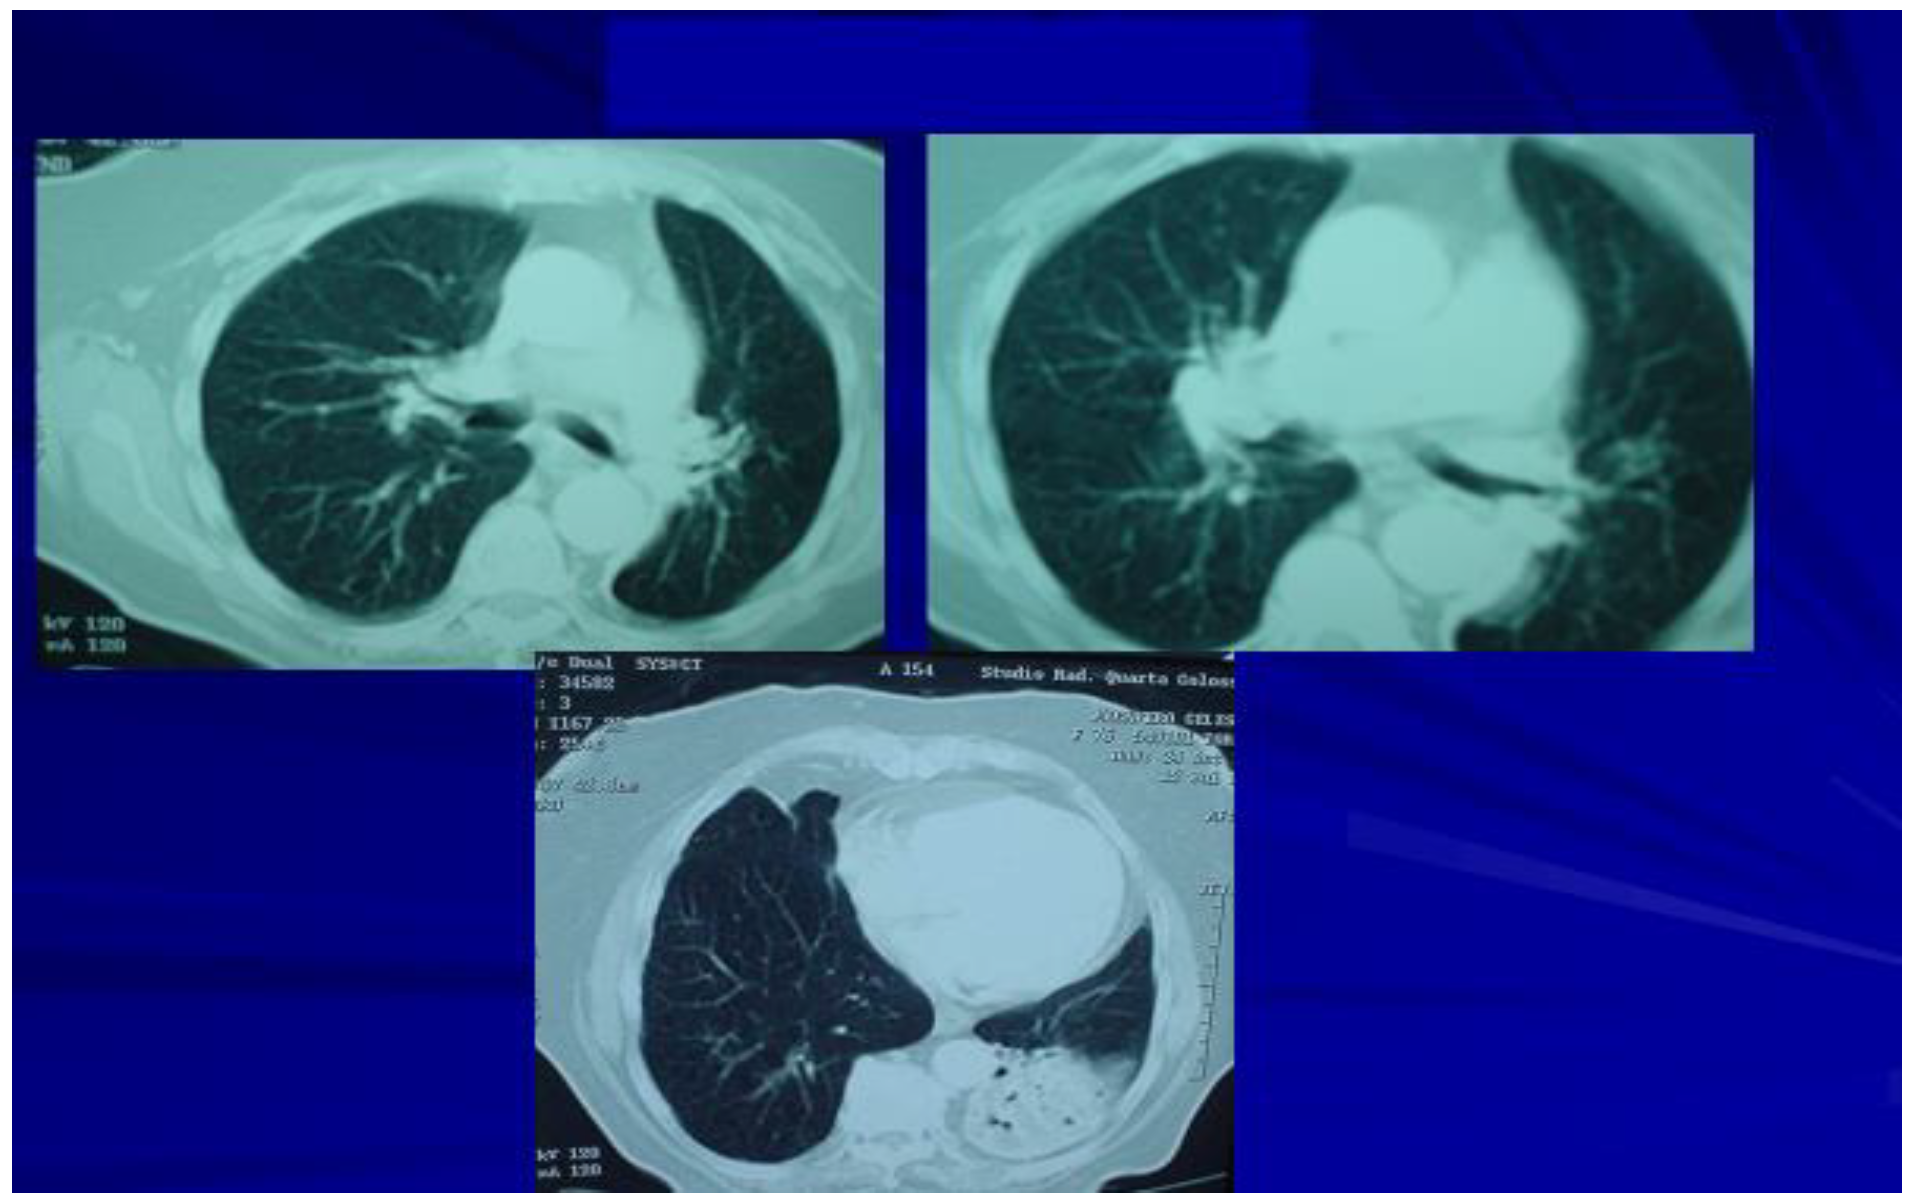
Figure 3.
Occlusion of the left lower lobe bronchus due to marked thickening of the mucosa.
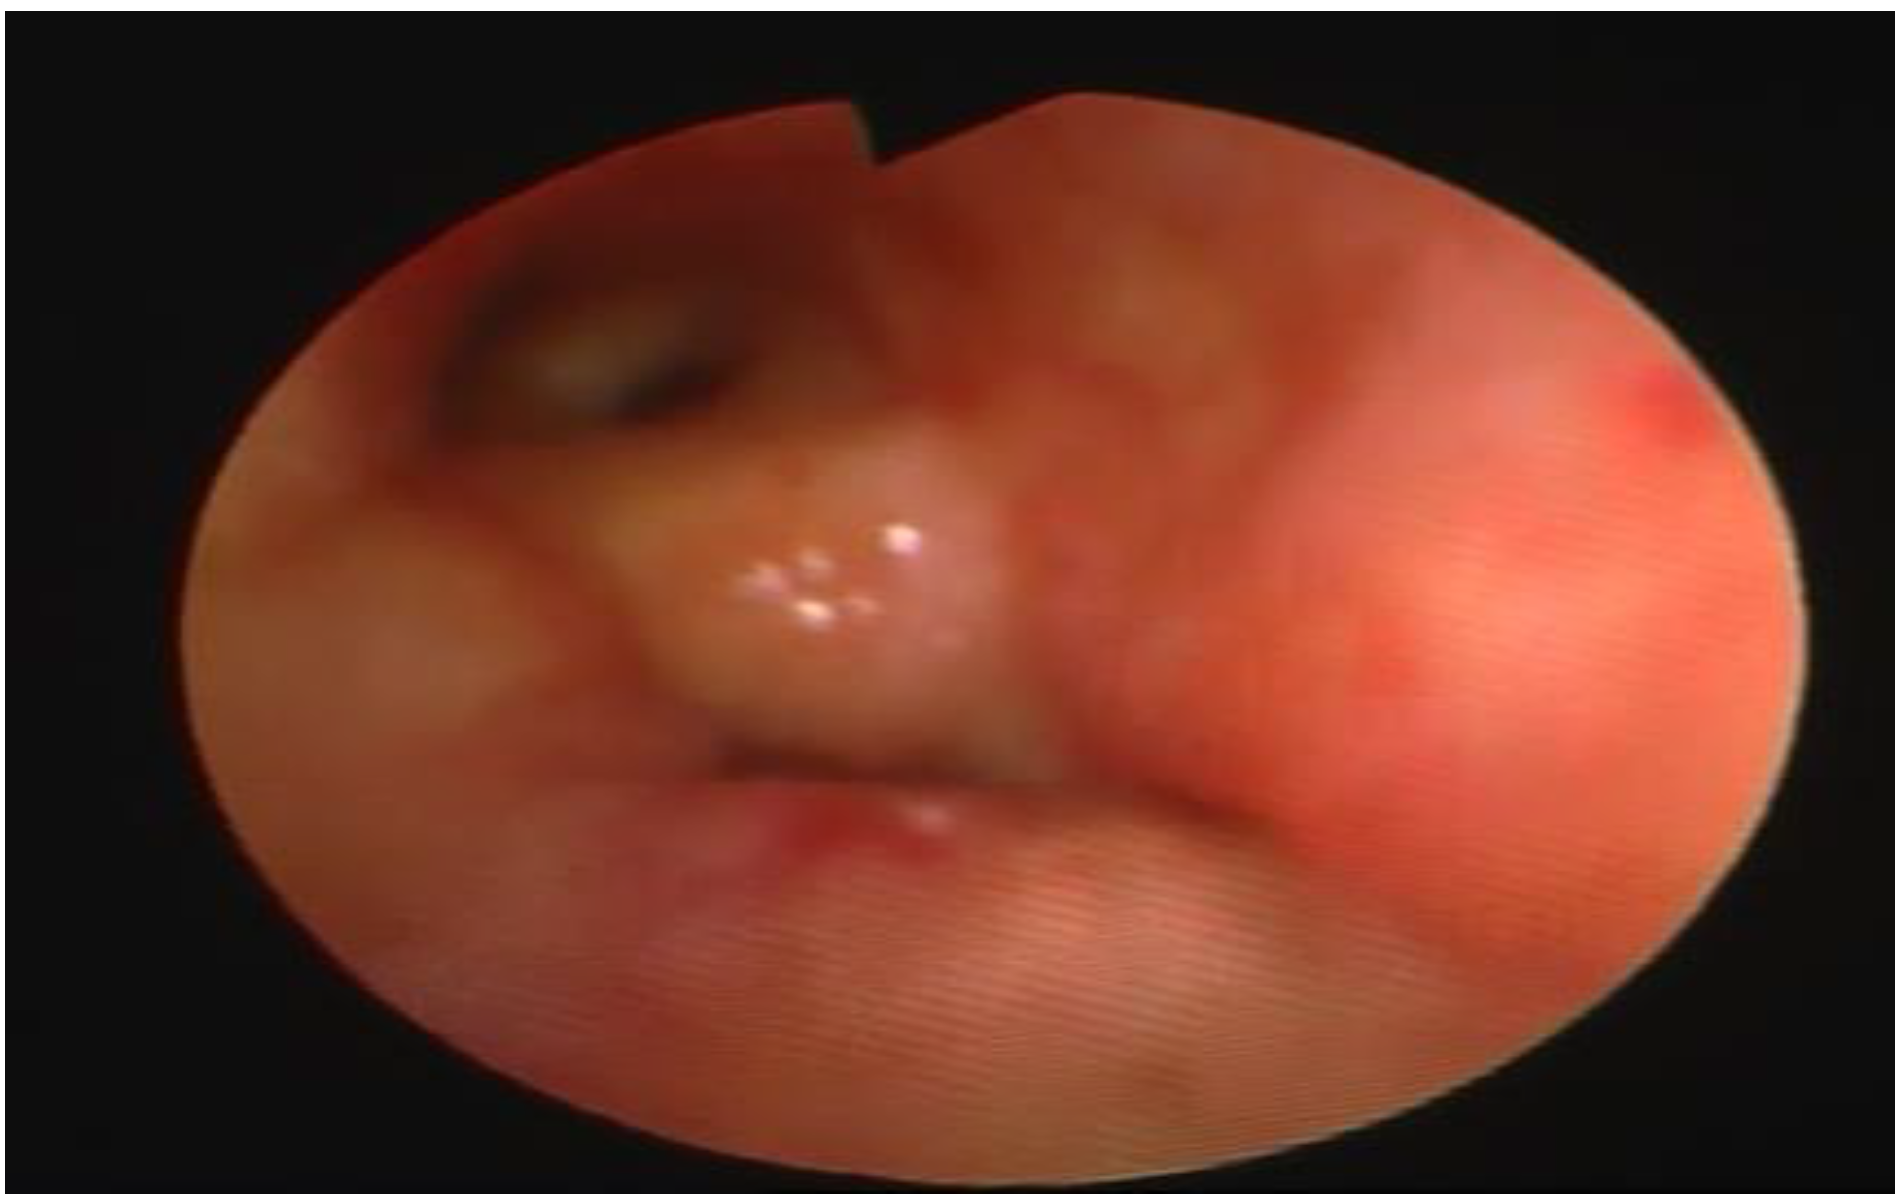
Figure 4.
Stenosis of the left upper lobe bronchus and of the lingula due to marked thickening of the spur.
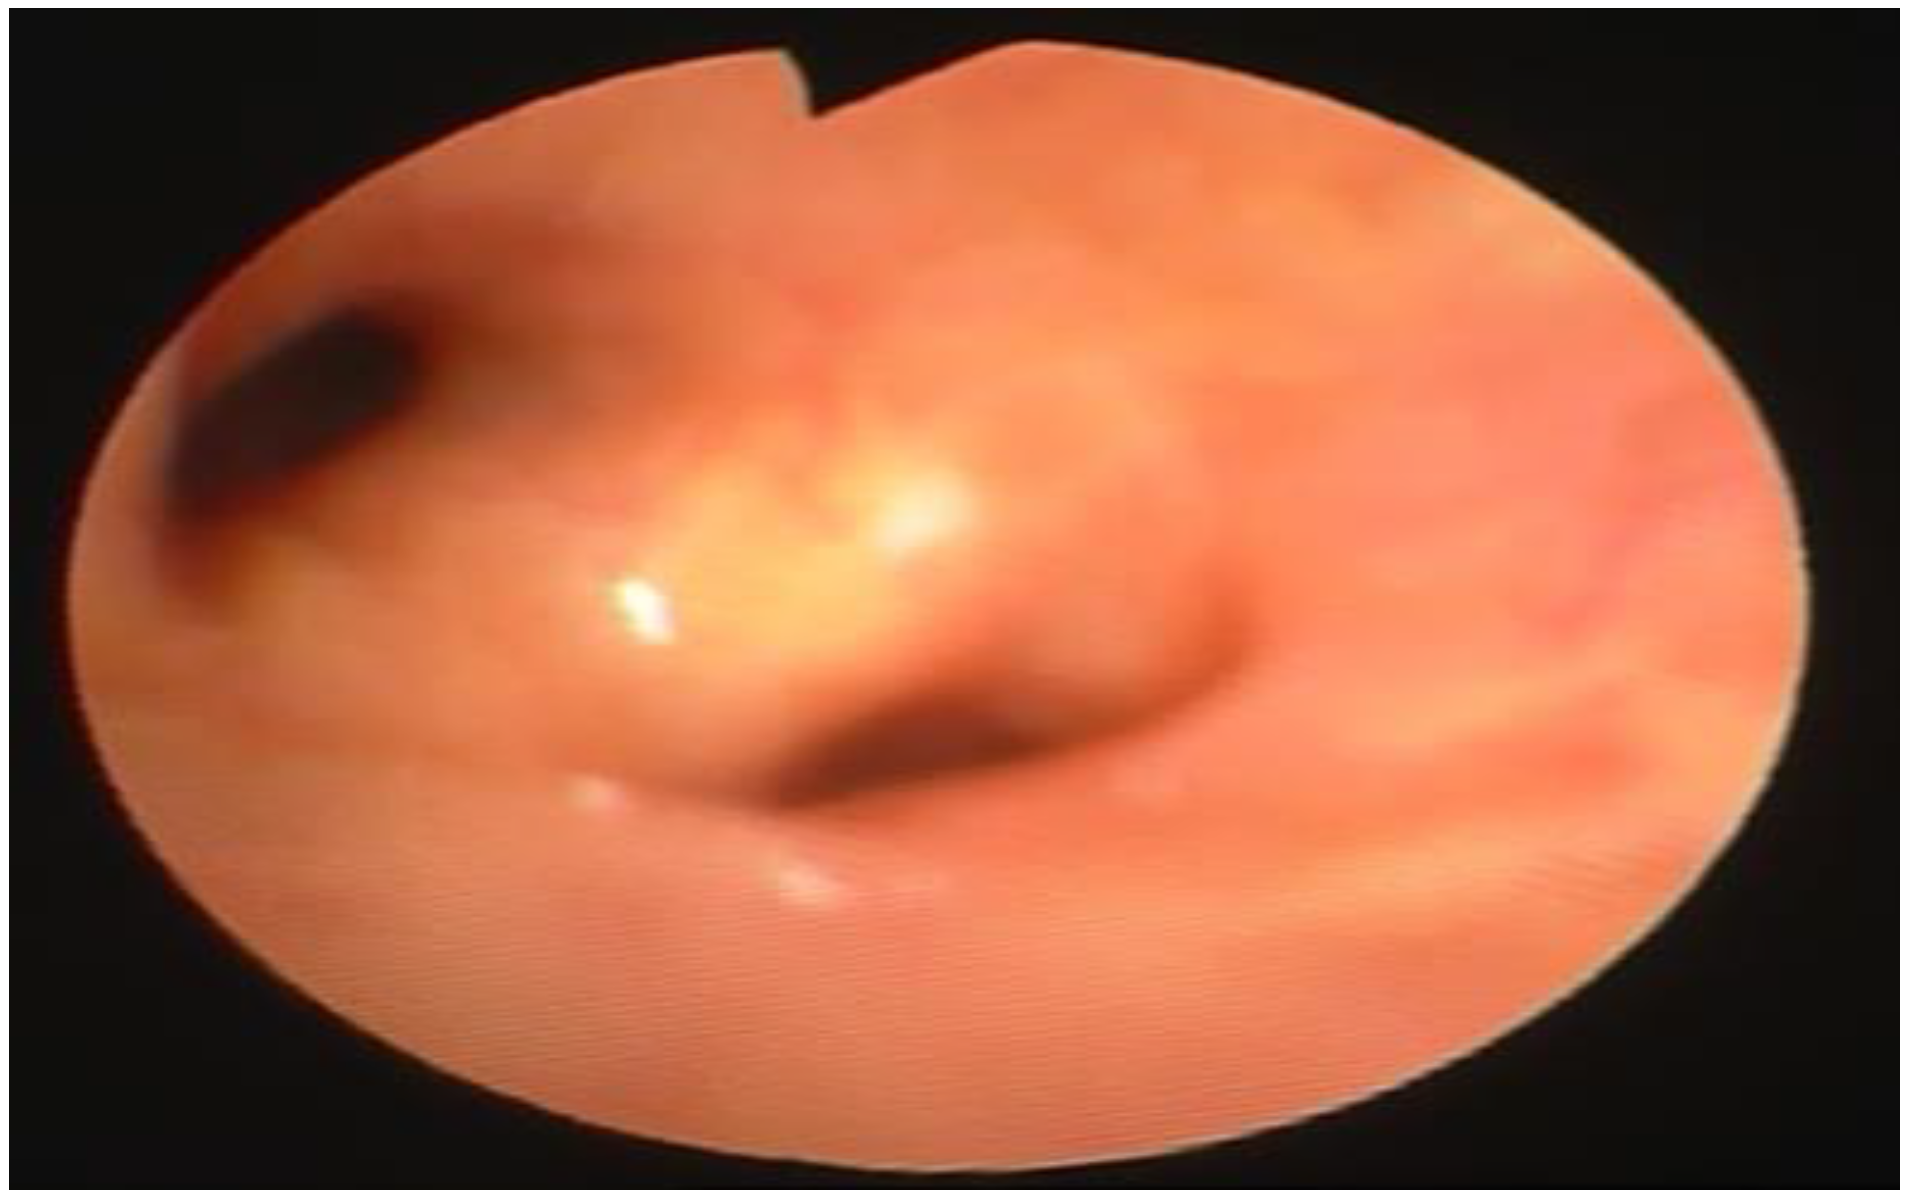
Figure 5.
Presence of nodular formations at the level of the tracheal wall of amyloid substance.
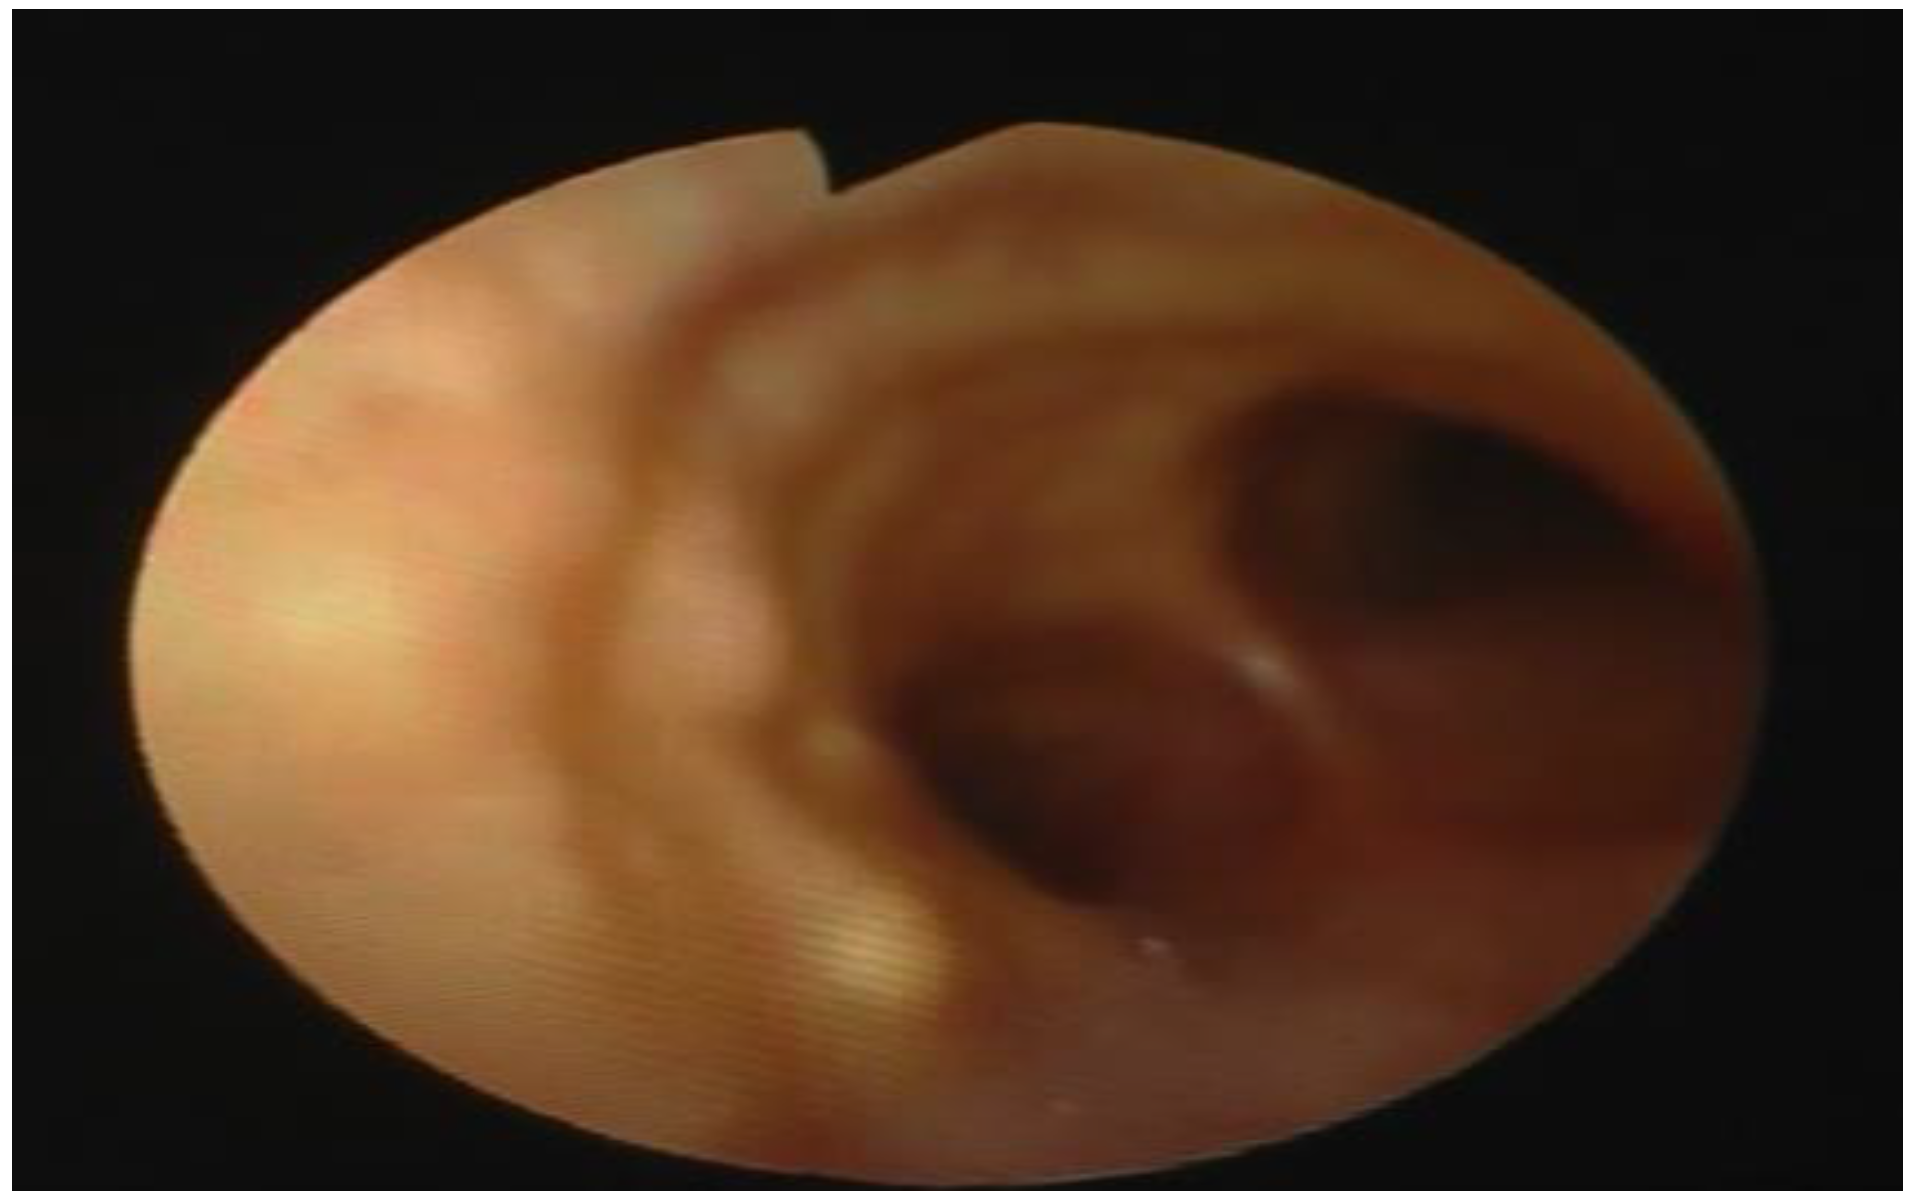
Figure 6.
Tight stenosis of the middle broncho-lobar for notable thickening of the spur between the middle and lower lobe bronchus.
3. Therapy
The YAG laser treatment allows a resection of the amyloid pathology with satisfactory results. Recently it has been seen that in patients with tracheobronchial amyloidosis refractory to YAG or stending laser therapy, discrete results can be obtained with 20 GY external pulse radiation therapy which can be repeated 2/3 times.
4. Conclusions
This very rare pathology is characterized as we have seen from the endoscopic and radiological point of view by the presence of multiple nodules, plaques or pseudotumoral masses of easily bleeding friable consistency that develop at the level of the tracheobronchial wall, causing stenosis and sometimes occlusion of some bronchial branches. The symptoms in the initial phase can be silent or manifest with recurrent episodes of bronchial exacerbation. Subsequently, the cough becomes persistent and dyspnea and hemoptysis appear. The execution of radiological examinations (chest x-ray and CT) and in particular of the fibrobronchoscopy with biopsy (better if performed in the initial phase) allows to formulate the diagnosis and to perform appropriate therapy with good results.
References
- Fraser, Colman, Muller, and Parè. 2006. Tracheobronchial Amyloidosis. In Chest Disease - Diagnostic Imaging and Clinical Evaluation. Milano: Elselvier. [Google Scholar]
- Grenier, Philippe. 1993. Tracheobronchial Amyloidosis. In Thoracic Images in Adults. Edited by Medical Moment Editor. [Google Scholar]
- Piacenza, Giovanni. 1992. Tracheobronchial Amyloidosis. In The Trachea. Edited by WR Alessandria Editions. [Google Scholar]
- Prakash, Udaya. 1995. Bronchoscopes - Amyloidosis - Tracheobronchial. Raven Press. [Google Scholar]
Copyright © 2020. This article is licensed under a Creative Commons Attribution 4.0 International License.