


Abstract
Background: The distribution of airborne allergens varies across climatic and ecological settings and may shape region-specific molecular sensitization profiles. Objective: To characterize component-level IgE sensitization in patients with allergic rhinitis and/or asthma recruited in four Argentine locations and to explore its relationship with clinical phenotype. Methods: This multicenter cross-sectional study included 377 patients with respiratory allergy and at least one positive skin prick test and/or positive sIgE. Serum specific IgE was measured using an ALEX multiplex. Regional profiles were summarized by allergen source and molecular component. The molecular sensitization burden across clinical phenotypes was assessed using Kruskal–Wallis tests and Spearman rank correlation. Results: The cohort comprised 100 patients from Buenos Aires, 105 from San Rafael-Mendoza, 62 from Santa Rosa-La Pampa, and 110 from Rosario-Santa Fe; 374 had allergic rhinitis and 186 had asthma. Mite components predominated in Buenos Aires, where Der p 1, Der p 2, Der p 23, and Der f 2. Rosario-Santa Fe and Santa Rosa-La Pampa showed intermediate mite sensitization. San Rafael-Mendoza displayed a pollen-dominant pattern, led by Ole e 1, Lol p 1, Phl p 1, and Sal k 1, together with the highest frequency of Alt a 1 recognition (32.4%). Fel d 1 was the leading epithelial component in all centers, whereas cockroach sensitization was infrequent and mainly represented by Bla g 9. Molecular sensitization burden differed across asthma phenotypes (p = 0.0127) and showed a weak positive monotonic association with asthma severity (Spearman ρ = 0.184, p = 0.0117). No corresponding association was observed for rhinitis (ρ = −0.067, p = 0.1949). Conclusions: Molecular profiling identified marked regional heterogeneity in aeroallergen sensitization across Argentina. These findings support geographically informed diagnostic assessment while emphasizing that molecular sensitization represents only one component of the broader allergen exposome.
1. Introduction
Allergic rhinitis and asthma are common chronic respiratory disorders whose expression reflects interactions between host susceptibility and environmental exposure. In Argentina, a national cross-sectional survey reported self-reported allergic rhinitis symptoms in 20.5% of participants aged 5–44 years, while pediatric studies have shown substantial geographical variability in rhinoconjunctivitis and asthma symptoms [1,2,3]. Local clinical series also indicate that aeroallergen sensitization is frequent among symptomatic children, although the relative contribution of mites, pollens, molds, and animal allergens differs between populations [4].
Environmental determinants are particularly relevant for airborne allergies. Temperature, precipitation, humidity, vegetation, land use, urbanization, and air pollution influence the abundance, seasonality, dispersion, and allergenic properties of pollen, fungal spores, and indoor allergens [5,6,7]. Argentina encompasses humid subtropical, temperate, semiarid, and arid environments over a large latitudinal and altitudinal range. Aerobiological observations have documented substantial regional and seasonal diversity but coordinated clinical–molecular data remain limited [5].
The exposome was introduced to describe the totality of non-genetic exposures across the life course [8]. In allergy, the external exposome includes aeroallergens, pollutants, climate, biodiversity, microbial environments, and lifestyle-related factors, whereas the internal exposome includes biological responses such as inflammation, oxidative stress, and immune regulation [9,10]. The present study does not measure the complete exposome. Rather, the serum IgE repertoire is interpreted as a biological imprint of one specific component of the external exposome: exposure and sensitization to airborne allergens.
Multiplex molecular diagnostics can simultaneously characterize IgE recognition of allergen extracts and individual components, helping distinguish genuine source sensitization from cross-reactivity and improving the resolution of geographical comparisons [11,12,13]. Previous studies used molecular mapping to examine the allergen exposome across atopic phenotypes and climate-matched populations, identifying marked differences in the contribution of major, mid-tier, and cross-reactive allergen molecules [11,12]. A subsequent multicenter study across four Peruvian cities further demonstrated that molecular sensitization patterns may vary according to regional climate classification [13].
Against this background, the objective of the present multicenter study was to characterize molecular IgE sensitization profiles in patients with allergic rhinitis and/or asthma recruited in Buenos Aires, San Rafael-Mendoza, Santa Rosa-La Pampa, and Rosario-Santa Fe. Secondary objectives were to compare the contribution of major aeroallergen sources between locations and to explore whether the number and distribution of recognized molecular components differed across age groups and ARIA- or GINA-defined clinical phenotypes.
Serum allergen-specific IgE was selected as the primary molecular biomarker because it provides allergen- and component-specific information suitable for mapping regional sensitization repertoires. This approach complements the extract-based skin prick test (SPT) and enables greater discrimination between genuine source sensitization and potentially cross-reactive molecular patterns.
2. Materials and Methods
2.1. Subjects
The study was conducted in four different Argentinian cities: Buenos Aires, Mendoza, Rosario-Santa Fe, and Santa Rosa-La Pampa. Patients aged 5 to 69 years, attending the participating medical services between April 2024 and September 2025, with symptoms of allergic rhinitis (AR) and/or asthma (A), were included in the study. Participants were recruited at each study site according to a common study protocol by the corresponding site investigators: J-F.M., E.G., M.d.G., M-I.A. and C.F. (Buenos Aires), M.I. (Mendoza), S.G. (Santa Rosa), and L.A. (Santa Fe). Written informed consent was obtained from all adult participants and from the parents or legal guardians of minors.
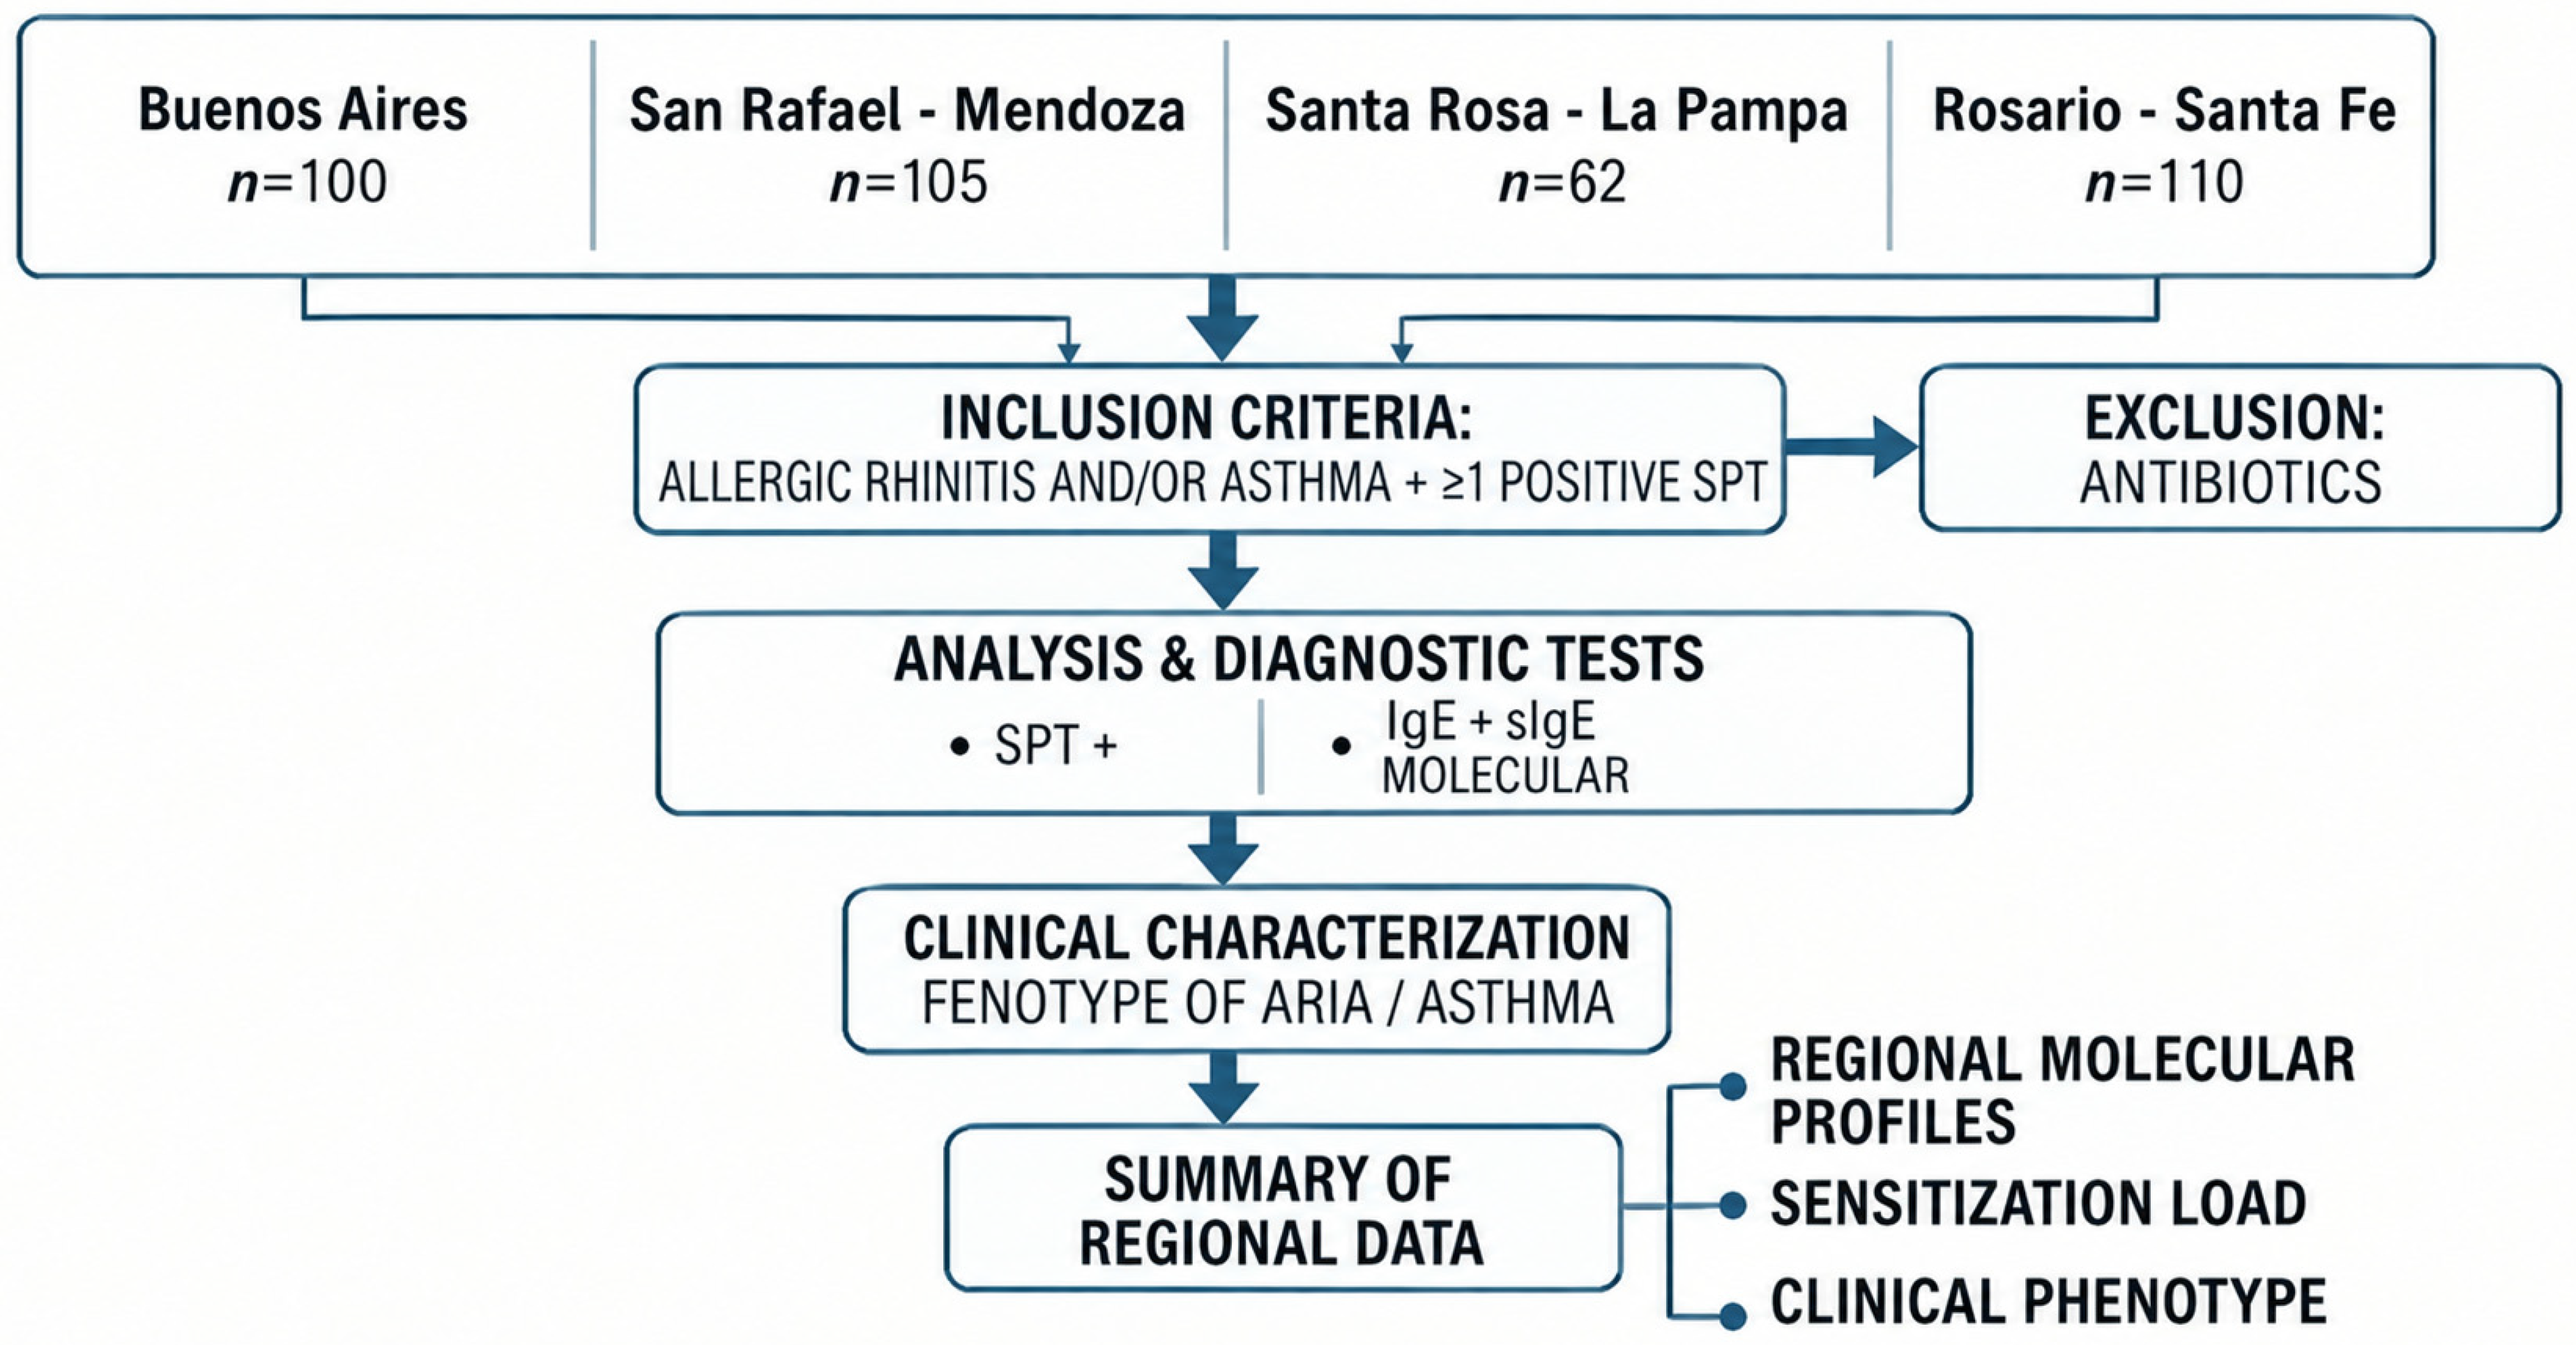
A total of 377 allergic patients were recruited according to predefined selection criteria. Eligibility required a confirmed diagnosis of allergy, determined through a positive SPT and/or specific IgE (sIgE) to one or more relevant aeroallergens (pollen, mites, molds, and/or pet dander). To meet the inclusion criteria, patients were required to have experienced clinical symptoms for at least three years after establishing local residency. Clinical data collected from patients’ medical records included clinical history and details about their medications. Patients who had undergone past or current allergen immunotherapy or treatment with monoclonal antibodies (biologics) were excluded, as well as pregnant and breastfeeding women. This investigation was reviewed and approved by the local Ethical Committee (code number 12685). An overview of the study design and the main methodological steps is presented in Figure 1.
Figure 1.
Flowchart of the study design and diagnostic workflow across regional centers in Argentina of molecular sensitization profiles and clinical phenotypes.
2.2. Skin Prick Test
Percutaneous testing was conducted according to European standards using a diagnostic panel (Inmunotek, Madrid, Spain) with standardized extracts, including mite extracts, mold extracts, cockroach extract, a mixture of six grass pollen extracts, and other pollen extracts such as olive, Artemisia, and Ambrosia, as well as cat and dog dander extracts. Histamine (10 mg/mL) and saline were used as positive and negative controls, respectively. As per standard procedure, antihistamines were discontinued one week before the SPT. Wheal diameters were measured 20 min after testing, considering positive results diameters greater than 3 mm.
2.3. Serological Analysis
Serum samples were collected from all the patients recruited, labeled with a unique code, stored at −40 °C, and thawed immediately before in vitro testing. Total IgE and specific IgE (sIgE) levels were measured using the ALEX MacroArray platform (MacroArray Diagnostics, Vienna, Austria) according to the manufacturer’s protocol. Total IgE levels were reported in international units per milliliter (IU/mL), and sIgE levels were expressed in kUA/L, with values ≥0.30 kUA/L considered positive.
The ALEX multiplex array contains 282 reagents, including 157 whole allergens and 125 molecular components.
2.4. Statistical Analysis
Statistical analyses and graphical representations were performed using GraphPad Prism version 10.4.1 (627) and R version 4.5.2, implemented in RStudio version 2025.05.1+513. Data processing and visualization in R version 4.6.1 were conducted using the dplyr, pheatmap, and ggplot2 packages.
Categorical variables were summarized as frequencies and percentages, whereas continuous variables were reported as median and range or mean ± standard deviation (SD), as appropriate. Regional sIgE profiles were represented in GraphPad Prism using heatmaps and bar plots showing mean sIgE concentrations ± SD, with individual patient values superimposed.
Molecular sensitization burden was defined as the number of components with recorded sIgE values >0.30 for each patient. Differences among clinical phenotypes were assessed using the Kruskal–Wallis test, followed by pairwise Wilcoxon rank-sum tests with Bonferroni correction. Associations between ordered clinical phenotypes and molecular sensitization burden were evaluated using Spearman’s rank correlation coefficient. A two-sided p value < 0.05 was considered statistically significant.
Boxplots with superimposed individual observations were generated using ggplot2. For phenotype-specific heatmaps, sIgE values were transformed as log10(sIgE + 1), without additional scaling. Patients were grouped according to their predefined clinical phenotype and hierarchically ordered within each group using Euclidean distance and complete-linkage clustering. Molecular components were hierarchically clustered across patients, and heatmaps were generated using heatmap.
During the preparation of this manuscript, the authors used ChatGPT (GPT-5.6; OpenAI, San Francisco, CA, USA) for editorial assistance to improve the manuscript’s clarity, grammar, and English-language translation. ChatGPT (GPT-5.6; OpenAI) was also used to assist in the creation of the graphical abstract. The authors reviewed and edited all AI-generated output and take full responsibility for the content of this publication.
3. Results
3.1. Demographic Features of Investigated Patients
The study included 377 participants: 100 from Buenos Aires, 105 from San Rafael-Mendoza, 62 from Santa Rosa-La Pampa, and 110 from Rosario-Santa Fe. Allergic rhinitis was recorded in 374 participants and asthma in 186; the two diagnoses were not mutually exclusive. All participants had at least one positive skin prick test to an aeroallergen and/or positive sIgE, and none had previously received or was receiving allergen immunotherapy or biologic therapy at enrollment. Demographic and clinical characteristics are summarized in Table 1.
Table 1.
Demographic and clinical characteristics of the study population by geographical location (n = 377).
3.2. Regional Molecular Sensitization Overview
Among the 377 participants, 335 (88.9%) showed sIgE levels ≥0.30 kUA/L to at least one of the 56 molecular components included in the analysis, whereas 42 (11.1%) did not recognize any of these components.
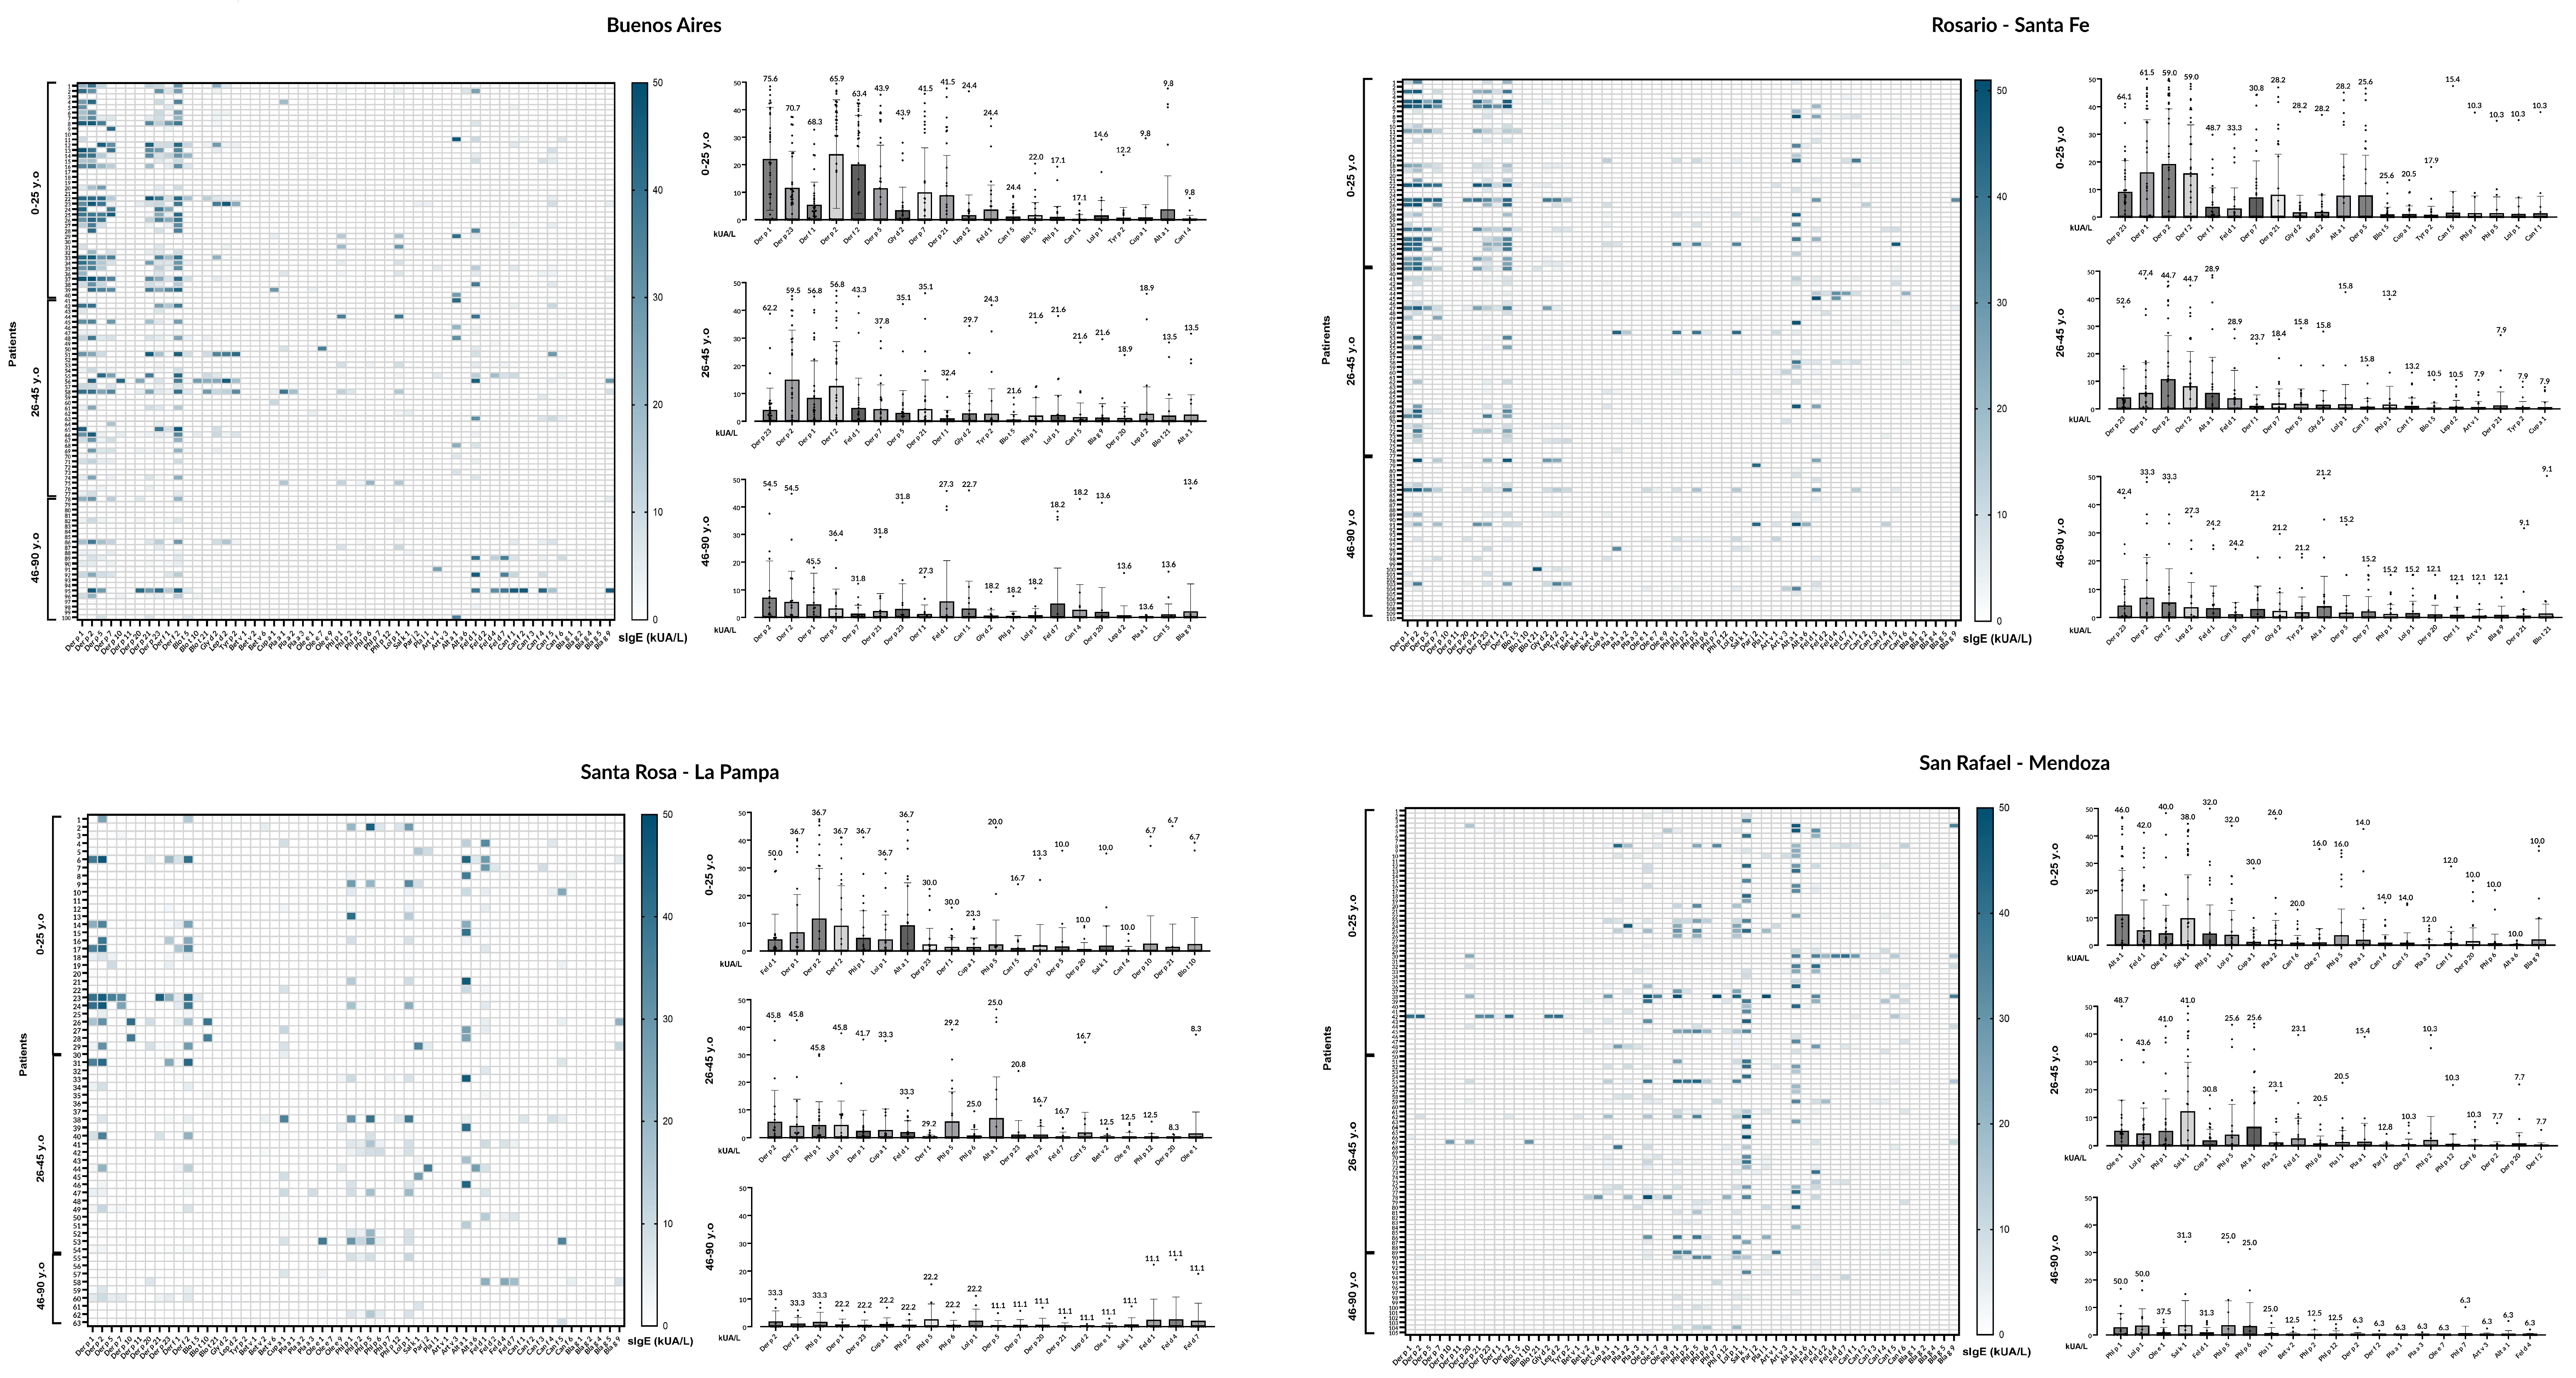
Mites were identified as the most prevalent source of sensitizing airborne allergens in the Buenos Aires population, regardless of the subjects’ underlying atopic condition. In contrast, in Mendoza, the main sensitizing allergens were pollens (Figure 2).
Figure 2.
Heatmap of the 20 most frequently identified molecular allergens in each region, along with their serodominance. Each panel corresponds to one recruitment center. In the heatmaps, rows represent individual patients ordered within the age strata 5–25, 26–45, and 46–69 years, columns represent allergen molecules, and color intensity represents serum specific IgE concentration (kUA/L). The adjacent plots display the 20 most prominent components within each age group.
3.3. Mites
Among the mite allergens, Dermatophagoides spp. were the predominant sensitizing airborne agents, and distinct geographic differences in sensitization patterns were observed. The highest prevalence of sensitization was observed in Buenos Aires (87% Dermatophagoides pteronyssinus and 82% Dermatophagoides farinae), followed by intermediate prevalences in Santa Rosa and Rosario, whereas the lowest prevalence was found in San Rafael. Furthermore, Buenos Aires had the highest prevalence of sensitization to Lepidoglyphus destructor, with 51% of participants showing a positive skin prick test, whereas the other three cities showed considerably lower sensitization rates (Table 2).
Table 2.
Prevalence of sensitization to four mite species, as determined by skin prick testing, in four Argentine cities. Values are expressed as percentages; values in parentheses indicate the number of participants with a positive skin prick test for each mite (n/N).
In Santa Rosa, La Pampa, the prevalence of sensitization to both Dermatophagoides species was identical, with 61.3% of the population showing a positive skin prick test. Furthermore, Santa Rosa showed the highest prevalence of sensitization to Blomia tropicalis, as determined by the skin prick test, with 51.6% of the population testing positive among the four cities.
Across all study regions, Dermatophagoides group 1 and group 2 allergens were the dominant molecular sensitizers, with Der p 2 showing the highest IgE levels, followed by Der p 1, Der f 2, and Der p 23. As shown in Table 3, these allergens also exhibited the highest frequencies of specific IgE recognition. In Buenos Aires, Der p 1 (62%), Der p 2 (61%), Der p 23 (59%), and Der f 2 (59%) were the most frequently recognized allergens, followed by Der f 1 (47%). A similar pattern was observed in Rosario, where Der p 23 (53.6%), Der p 2 (46.4%), Der f 2 (46.4%), and Der p 1 (44.5%) predominated. In Santa Rosa, Der p 2 and Der f 2 (40.3%), Der p 1 (37.1%), and Der p 23 (25.8%) remained the most frequently recognized allergens, whereas San Rafael exhibited an overall low frequency of molecular sensitization, with Der p 20 (7.6%), Der p 2, Der f 1, and Der f 2 (4.8%) being the most frequently recognized components. Both the magnitude of the IgE response and the proportion of sensitized individuals declined progressively from Buenos Aires to Rosario and Santa Rosa, reaching the lowest values in San Rafael.
Table 3.
Serum sIgE to mite molecular allergens by recruitment center. Data are the mean ± standard deviation (kUA/L); values in parentheses indicate the number of participants with positive sIgE for each component.
Sensitization to minor Dermatophagoides allergens was generally infrequent and of low intensity across all regions. Recognition of Der p 5, Der p 7, and Der p 21 was consistently lower than that observed for groups 1 and 2, although these components were more frequently detected in Buenos Aires and Rosario than in Santa Rosa and San Rafael. Sensitization to Der p 10 was uncommon in all four cities, while no patients showed specific IgE to Der p 11.
Recognition of Blomia tropicalis molecular allergens was also infrequent. Blo t 5 was the most commonly recognized Blomia component in Buenos Aires (19.0%) and Rosario (15.5%), whereas only one patient from Santa Rosa and none from San Rafael recognized this allergen (Table 3). Likewise, Blo t 10 and Blo t 21 showed low frequencies across all study sites. These findings contrast with the skin prick test results, particularly in Santa Rosa, where sensitization to the B. tropicalis extract was the highest among the four cities. This observation is plausible considering that the allergens responsible for sensitization are not included in the ALEX platform. Sensitization to Gly d 2 and Lep d 2 was predominantly observed in Buenos Aires and Rosario, whereas recognition of Tyr p 2 was less frequent overall.
Monosensitization to mite molecular allergens was uncommon in the study population. Among the 377 patients analyzed, only 32 (8.5%) were monosensitized to a single mite allergen. Der p 23 was the most frequent monosensitizing component, detected in 9 patients (2.4% of the total study population), In contrast, extensive polysensitization was observed in a substantial proportion of the cohort, with 44 out of the 377 patients (11.7%) showing specific IgE reactivity to nine or more mite molecular allergens.
3.4. Pollens
Sensitization to pollen molecular allergens was detected across all four study regions. The highest prevalence of positive responses by skin prick test (Table 4) was observed in San Rafael, particularly for the grass pollen mixture (65.7%) and Olea europaea (60.9%). Buenos Aires showed intermediate sensitization frequencies, with the grass pollen mixture (32.0%) representing the most frequently recognized extract. In contrast, Rosario displayed generally low sensitization rates for all pollen extracts tested, with olive pollen showing the highest prevalence (10.0%). In Santa Rosa, skin prick testing was not performed with the grass pollen mixture; however, high frequencies of sensitization were observed for Olea europaea (53.2%) and Ambrosia elatior (40.3%).
Table 4.
Prevalence of sensitization to three pollen species and a mixture of grass pollens, as determined by skin prick testing, in four Argentine cities. Values are expressed as percentages; values in parentheses indicate the number of participants with a positive skin prick test for each pollen (n/N).
Grass pollen allergens accounted for the highest sIgE levels across the Argentine cohort (Table 5). Although no individual molecular allergen met the definition of a major allergen (≥50% prevalence among pollen-sensitized individuals), Phl p 1 and Lol p 1 were the most frequently recognized components, each detected in 26.0% of patients.
Table 5.
Serological analysis. Mean (±standard deviation) of specific IgE levels (kUA/L) to pollen molecular allergens in patients from all four centers. Values in parentheses indicate the number of sensitized patients (n) for each allergen.
The predominant molecular sensitization profile comprised reactivity to one to four pollen allergens, which was observed in 152 out of the 377 study participants (40.3%). Within this group, 50 individuals (13.3%) were monosensitized, with Cup a 1 representing the most common sole sensitizing allergen (n = 10), followed by Art v 1 (n = 6).
Considerable geographical variability was observed in both the frequency of sensitization and the magnitude of the sIgE response. San Rafael showed the highest proportion of sensitized individuals, with 81.8% of the study population recognizing at least one pollen molecular allergen. This region also exhibited the broadest molecular sensitization profile, characterized by the highest mean sIgE levels across most pollen components. Besides the predominant recognition of the major grass pollen allergens Phl p 1 and Lol p 1 (38.1% and 39.0%, respectively), sensitization to olive (Ole e 1, 42.9%), Salsola kali (Sal k 1, 39.0%), and cypress (Cup a 1, 25.7%) was substantially more frequent than in the other study regions. Notably, Sal k 1 elicited the highest mean sIgE level among all pollen molecular allergens despite not being the most frequently recognized allergen.
Santa Rosa-La Pampa exhibited an intermediate sensitization profile, with 61.9% of individuals sensitized to at least one pollen molecular allergen. As in the other regions, grass pollen allergens predominated, with Phl p 1 and Lol p 1 recognized by 40.3% and 38.7% of the study population, respectively, with moderate sensitization to Cup a 1 (27.4%). Interestingly, despite the high prevalence of positive skin prick tests to Ambrosia elatior, sensitization to Amb a 1 and Amb a 4 was virtually absent, suggesting the involvement of other ragweed allergens.
Buenos Aires and Rosario-Santa Fe displayed the lowest frequencies of sensitization (40.0% and 32.0%, respectively) and shared a broadly similar molecular profile. In both locations, sensitization was mainly directed against the major grass pollen allergens Phl p 1 and Lol p 1.
Sensitization to Ole e 1 was detected not only in San Rafael but also in Buenos Aires, Rosario and Santa Rosa. In these three regions, the frequencies of sensitization and mean sIgE levels for Ole e 1 and Fra e 1 were remarkably similar.
3.5. Molds
Skin prick test results showed that Alternaria alternata was the predominant mold allergen in all study centers (Table 6), with the highest prevalence in San Rafael-Mendoza (33.3%) and Santa Rosa-La Pampa (32.3%), followed by Rosario-Santa Fe (21.8%) and Buenos Aires (12.0%). Sensitization to Aspergillus fumigatus, Cladosporium herbarum, and Penicillium notatum was considerably less frequent, with prevalence below 10% in most centers.
Table 6.
Prevalence of sensitization to four mold species by skin prick test in four Argentine cities (%; positive cases shown as n/N).
Regarding molecular sensitization, Alt a 1 was the dominant mold component in every location (Table 7). It was recognized by 34/105 participants in San Rafael-Mendoza (32.4%), 29/110 in Rosario-Santa Fe (26.4%), 17/62 in Santa Rosa-La Pampa (27.4%), and 10/100 in Buenos Aires (10.0%). Alt a 6 was infrequently recognized.
Table 7.
Serum sIgE to the displayed mold allergen molecules by recruitment center. Data are the mean ± standard deviation (kUA/L); values in parentheses indicate the number of participants with positive sIgE for each component.
3.6. Cat and Dog Dander
Skin prick testing showed similar sensitization patterns to cat and dog dander across centers. Dog dander sensitization ranged from 17.3% to 38.7%, while cat dander ranged from 7.3% to 37.1%, with the highest prevalence observed in Santa Rosa-La Pampa and San Rafael-Mendoza (Table 8).
Table 8.
Prevalence of sensitization to cat and dog dander by skin prick test in four Argentine cities (%; positive cases shown as n/N).
Although skin prick testing showed slightly higher sensitization rates to dog than cat dander, molecular analysis revealed a different pattern, with Fel d 1 being the most frequently recognized epithelial allergen in all centers (Table 9). Mean sIgE levels for Fel d 1 were also the highest among epithelial components. In contrast, sensitization to the remaining cat components was considerably less frequent. Fel d 7 was detected in 5 to 7 patients per center, whereas Fel d 4 and Fel d 2 showed low recognition rates. Fel d 2 was almost absent, with no positive patients in Buenos Aires and only 2 to 4 positive patients in the other centers.
Table 9.
Serum sIgE to cat and dog allergen molecules by recruitment center. Data are the mean ± standard deviation (kUA/L); values in parentheses indicate the number of participants with positive sIgE for each component.
Among the dog allergens, Can f 5 was the most frequently recognized component. Can f 1 was the second most frequent dog component, particularly in Buenos Aires. The remaining dog allergens, including Can f 2, Can f 3, Can f 4, and Can f 6, showed lower and more heterogeneous recognition frequencies across centers. When considering sensitization to at least one dog molecular allergen (Can f 1–6), the overall prevalence of molecular dog sensitization was 30.0% (113/377). By center, the prevalence was 32.0% (32/100) in Buenos Aires, 30.9% (34/110) in Rosario-Santa Fe, 27.4% (17/62) in Santa Rosa La Pampa, and 28.6% (30/105) in San Rafael Mendoza. Compared with skin prick testing, molecular sensitization was higher in Buenos Aires (32.0% vs. 23.0%) and Rosario-Santa Fe (30.9% vs. 17.3%), whereas lower prevalence was observed in Santa Rosa-La Pampa (27.4% vs. 38.7%) and San Rafael-Mendoza (28.6% vs. 33.3%).
3.7. Cockroaches
Skin prick testing showed highly variable sensitization to cockroach (Periplaneta americana) across centers. Sensitization ranged from 4.8% to 98.2%, with the highest prevalence observed in Rosario-Santa Fe and Santa Rosa-La Pampa (Table 10).
Table 10.
Prevalence of sensitization to cockroach by skin prick test in four Argentine cities (%; positive cases shown as n/N).
Although skin prick testing showed extremely high sensitization rates in these locations, molecular analysis revealed a starkly different pattern. Cockroach sensitization was infrequent and was mainly represented by Bla g 9, detected in 13/100 participants in Buenos Aires (13.0%), 7/110 in Rosario-Santa Fe (6.4%), 6/62 in Santa Rosa-La Pampa (9.7%), and 8/105 in San Rafael-Mendoza (7.6%) (Table 11). Mean sIgE levels for Bla g 9 ranged from 0.4 ± 3.2 to 1.3 ± 5.5 kUA/L across centers. Bla g 1 and Bla g 5 were not detected, and Bla g 2 and Bla g 4 were only sporadically recognized.
Table 11.
Serum sIgE to cockroach allergen molecules by recruitment center. Data are the mean ± standard deviation (kUA/L); values in parentheses indicate the number of participants with positive sIgE for each component.
3.8. Clinical Phenotypes and Molecular Sensitization Burden
Allergic rhinitis was present in nearly the entire cohort: 99 participants in Buenos Aires, 103 in San Rafael Mendoza, 62 in Santa Rosa La Pampa, and 110 in Rosario Santa Fe. Asthma was recorded in 41, 51, 51, and 43 participants, respectively (Table 12). Asthma therefore represented a larger proportion of the local cohort in Santa Rosa-La Pampa than in the other locations.
Table 12.
Number of patients with allergic rhinitis (AR) or allergic asthma (AA) by age group and geographical location.
When analyzed by age group, allergic rhinitis was more frequent in the younger and middle age ranges in Buenos Aires and Mendoza, whereas Santa Fe Rosario showed a notable number of rhinitis cases also among older adults aged 46–68 years (n = 33). Allergic asthma was particularly frequent among young patients from Mendoza (n = 27) and Santa Rosa-La Pampa (n = 24). In contrast, the lowest numbers of asthma cases in older adults were observed in Mendoza and Santa Rosa La Pampa.
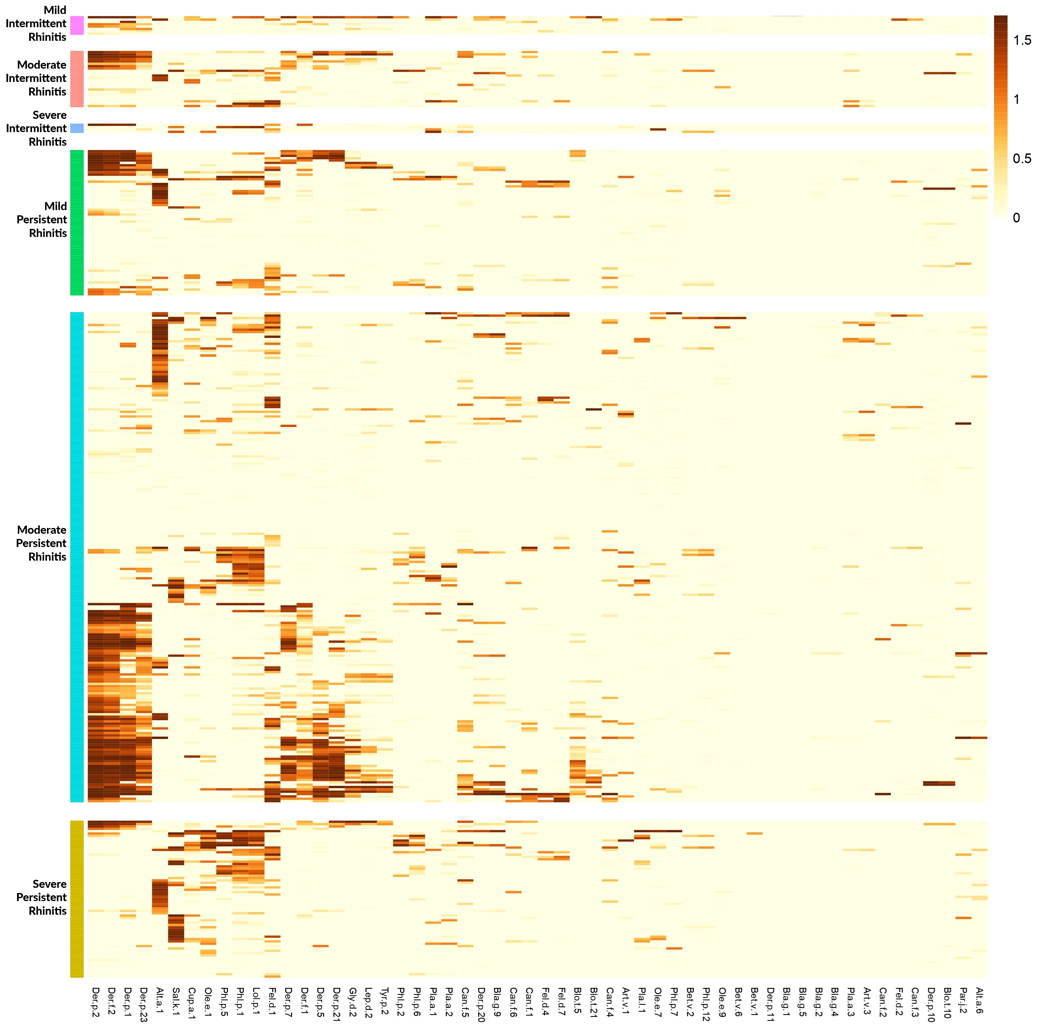
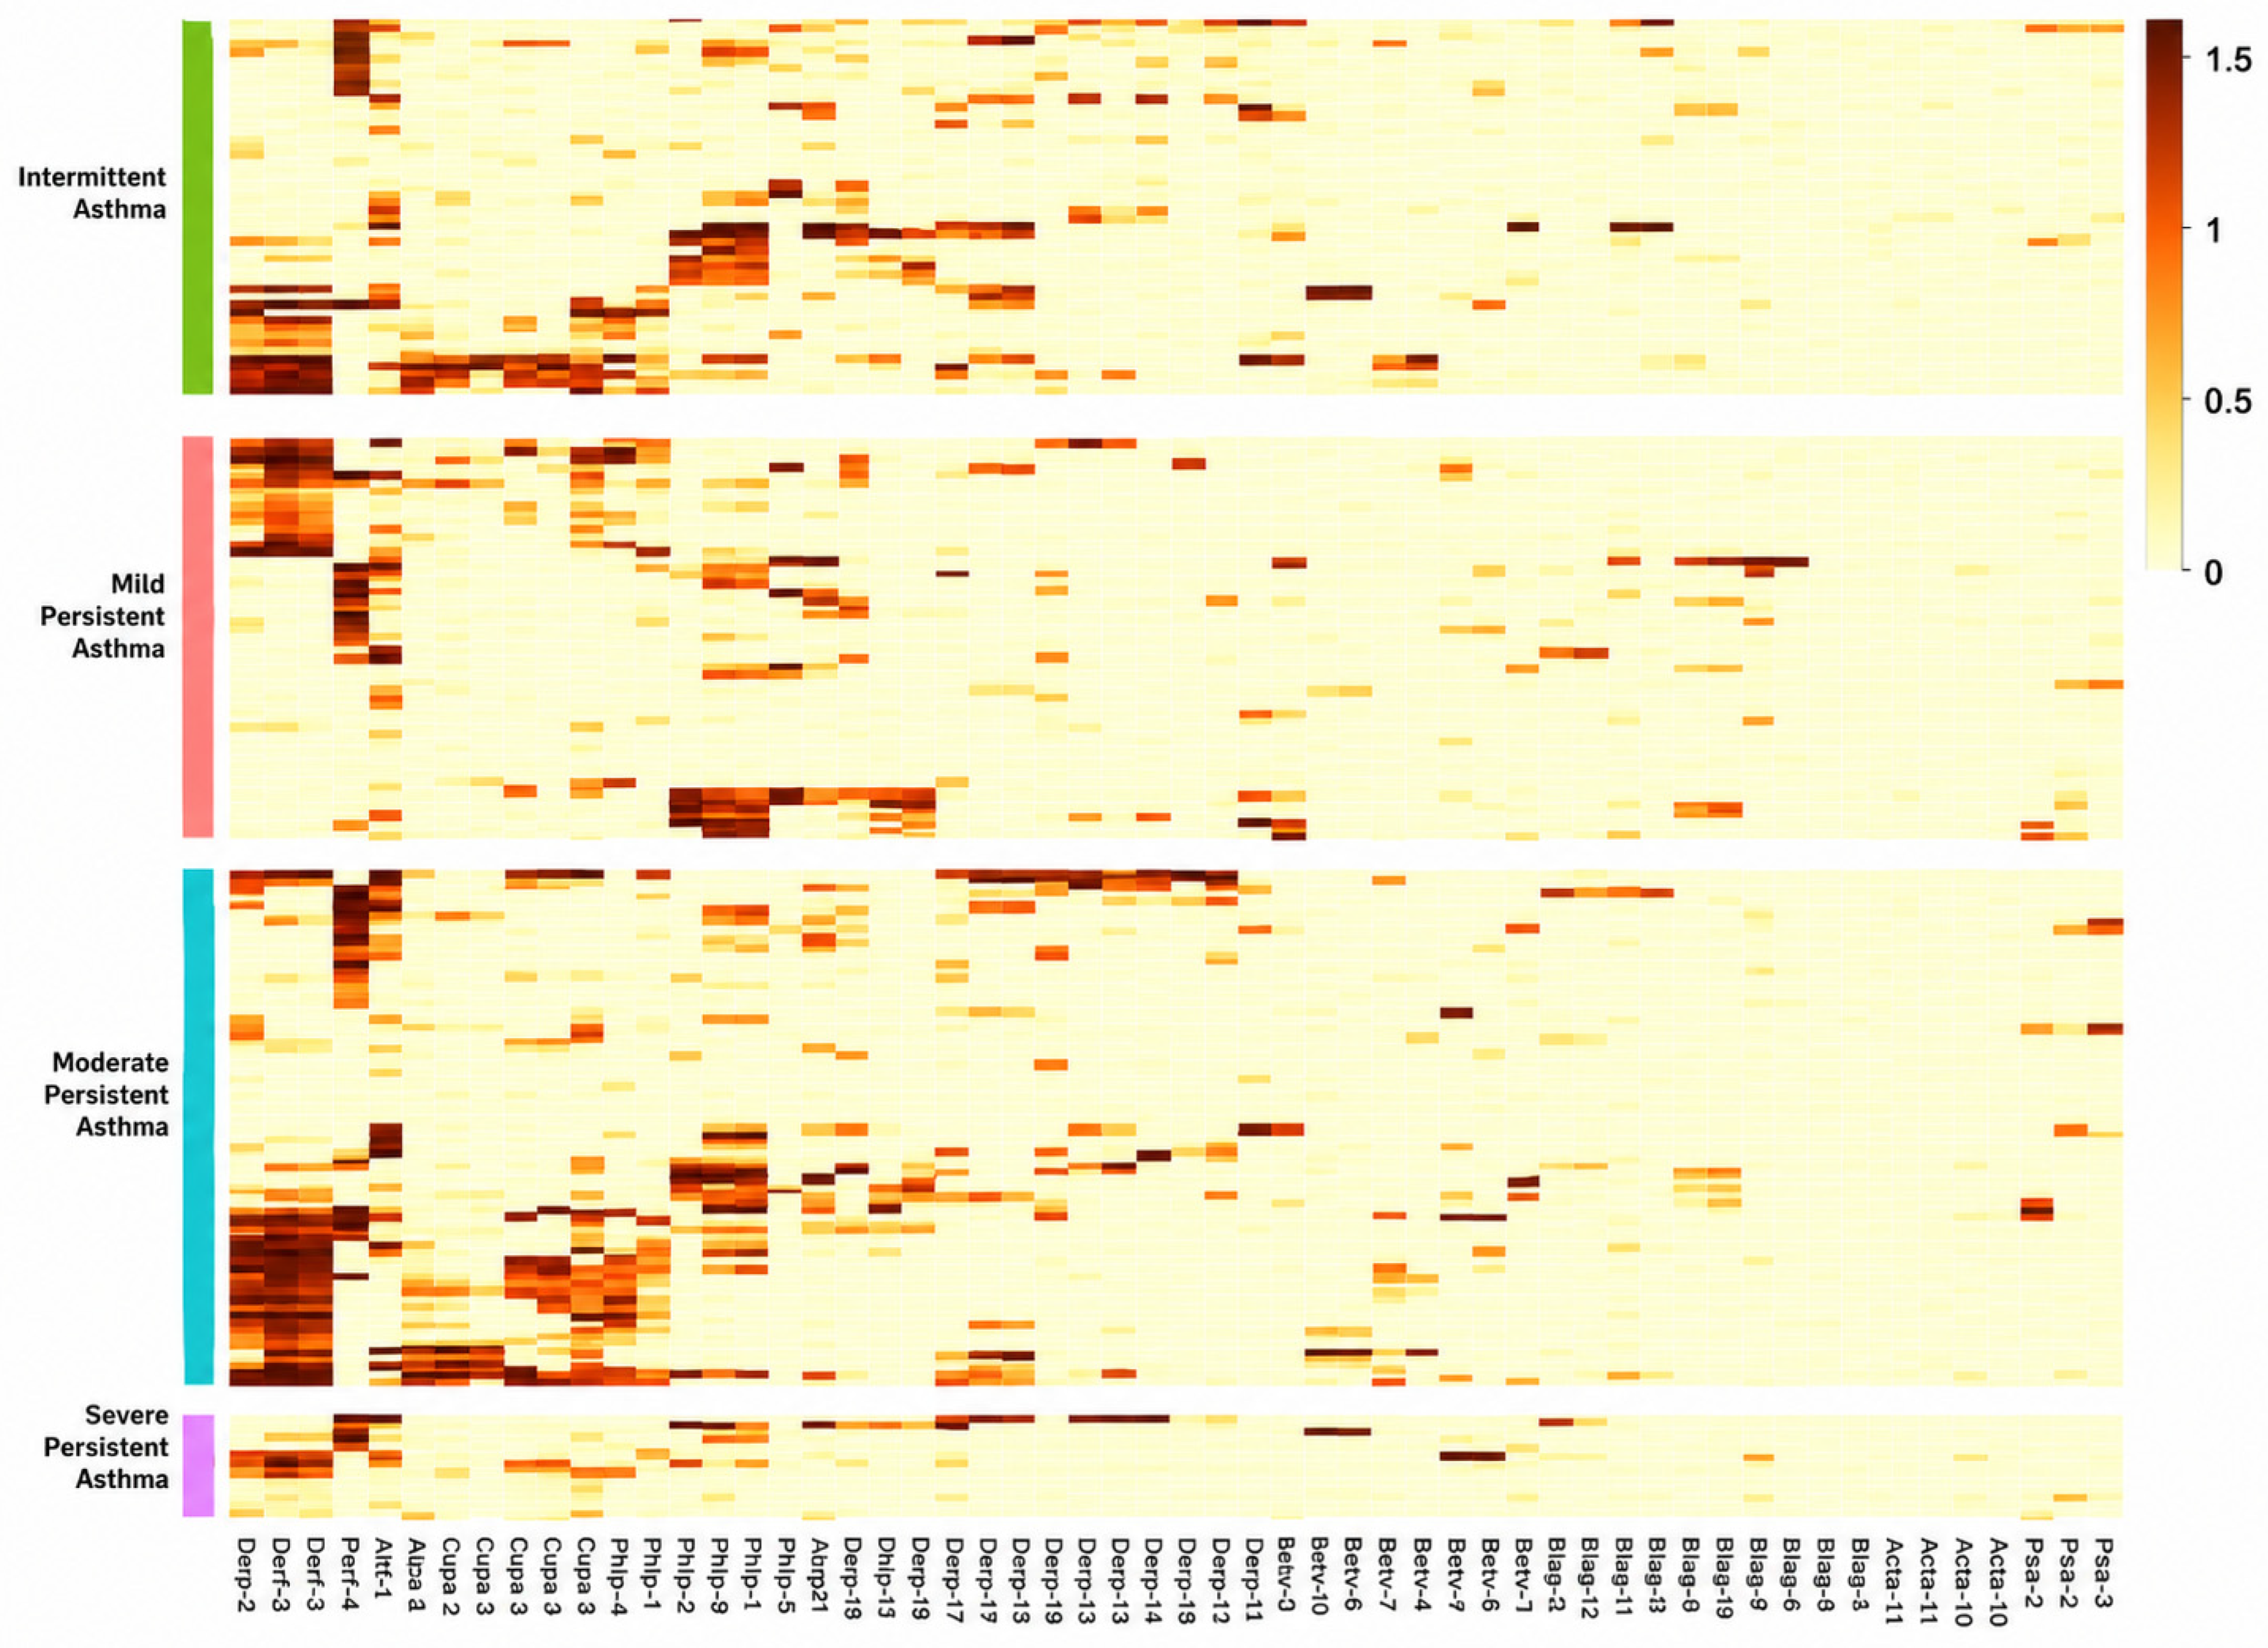
To evaluate the molecular sensitization profiles, patients were grouped along the vertical axis by clinical phenotype. Along the horizontal axis, molecular allergens were organized based on their co-sensitization patterns and similarities in sIgE reactivity levels.
In the rhinitis cohort (Figure 3), sensitization patterns were primarily driven by disease duration rather than severity alone. Patients with persistent phenotypes, specifically moderate persistent and severe persistent allergic rhinitis, showed a prominent cluster with high sIgE levels (signal intensity >1.5, dark orange bands). This predominant cluster was driven by broad co-sensitization to both major and minor components of house dust mites and storage mites (Der p 1, Der p 2, Der p 5, Der p 7, Der p 21, Der p 23, Der f 1, Tyr p 2, Lep d 2, and Gly d 2), alongside the fungal allergen Alt a 1 and cat uteroglobulin (Fel d 1). Additionally, a distinct secondary cluster was identified, defined by strong, isolated sensitization to Alt a 1. Interestingly, patients with the highest clinical severity, as severe persistent rhinitis, exhibited selective signal intensity restricted to discrete clusters of pollen allergens (Sal k 1, Cup a 1, Ole e 1, Phl p 1, Phl p 5, Lol p 1) and Alt a 1, a pattern also shared by a subgroup of individuals with moderate persistent rhinitis.
Figure 3.
Heatmap of molecular sensitization profiles in the rhinitis cohort (n = 374). Rows represent individual participants grouped by ARIA phenotype; columns represent allergen molecules ordered by hierarchical clustering. The color scale represents log-transformed sIgE [log(sIgE + 1)].
In contrast, the asthma cohort (Figure 4) displayed marked molecular heterogeneity across its clinical stages. The moderate persistent asthma phenotype emerged as the group with the highest immunological density (broadest and darkest bands), demonstrating extensive polysensitization to multiple major and minor house dust mite allergens. Furthermore, two smaller, well-defined clusters were observed, characterized by grass pollen allergens (Lol p 1, Phl p 1, Phl p 5) and Alt a 1, respectively. Conversely, patients with intermittent asthma exhibited much fainter, sparse, and dispersed signals across all tested components.
Figure 4.
Heatmap of molecular sensitization profiles in the asthma cohort (n = 186). Rows represent individual participants grouped by asthma phenotype; columns represent allergen molecules ordered by hierarchical clustering. The color scale represents log-transformed sIgE [log(sIgE + 1)].
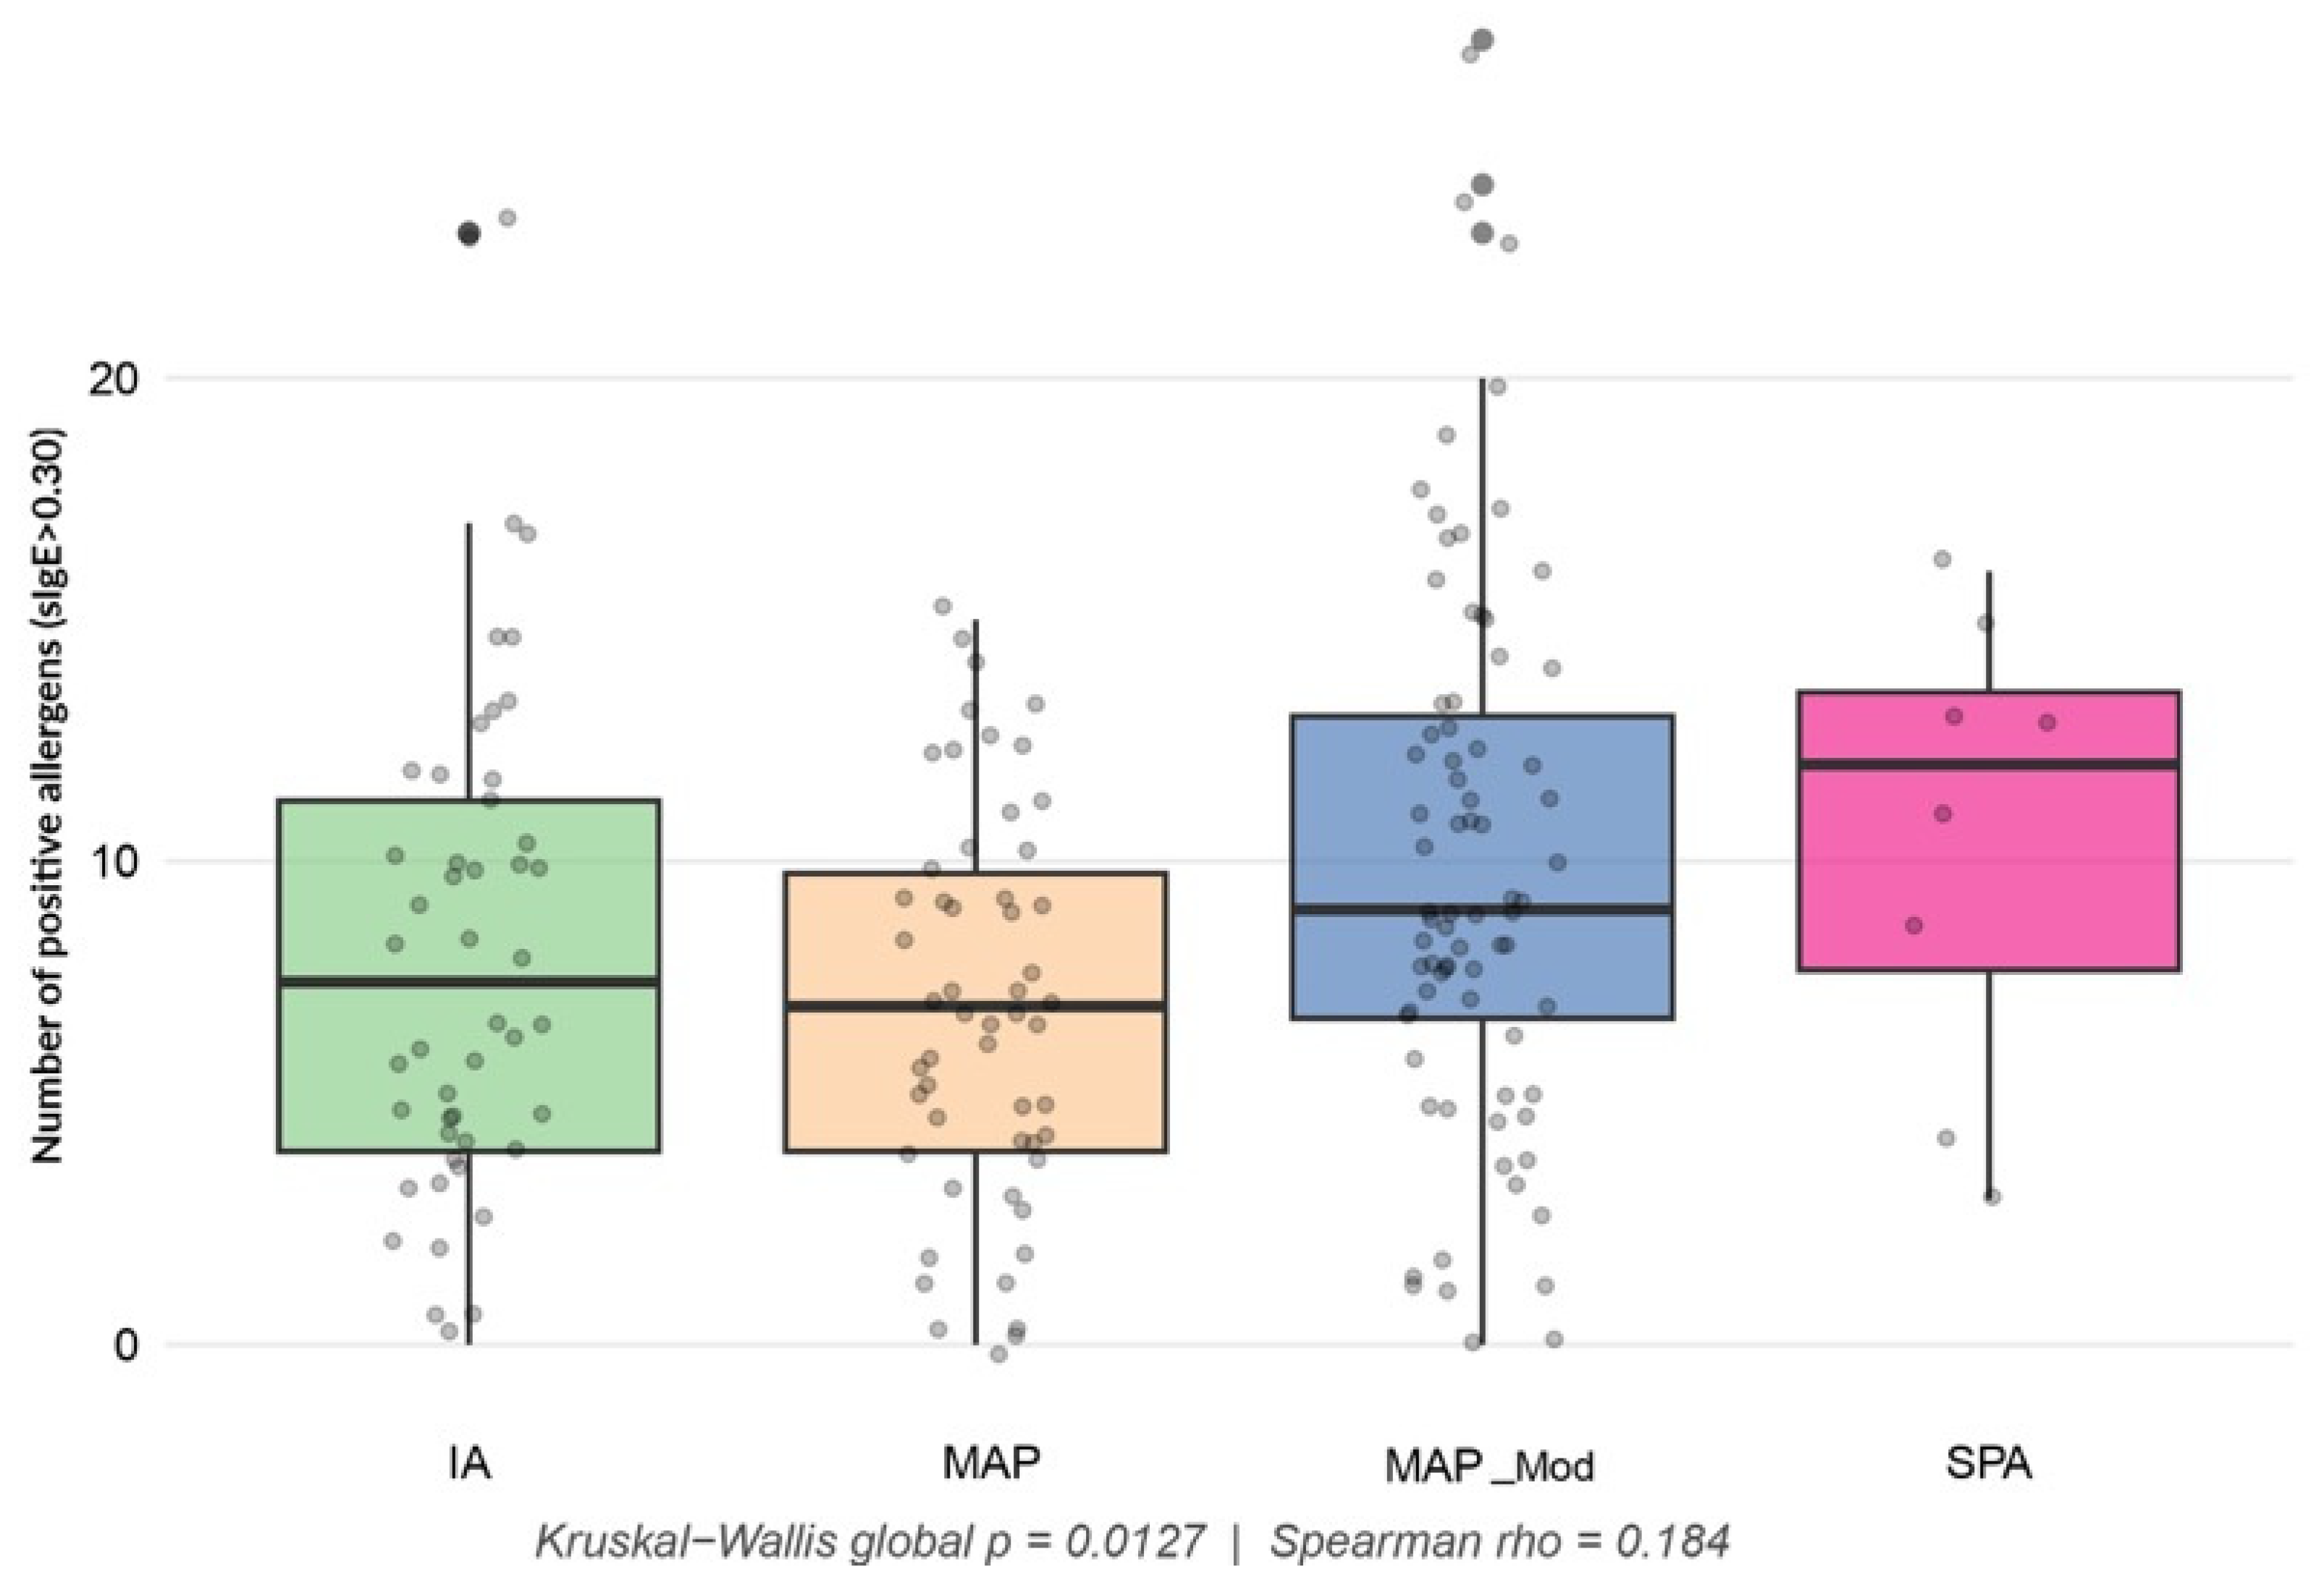
To assess whether the complexity of the molecular sensitization profile was associated with the severity of asthma, the total number of positive allergenic components per patient was quantified (Figure 5. The Kruskal–Wallis test confirmed the existence of statistically significant differences in the degree of polysensitization between the four clinical phenotypes (χ2 = 10.82, df = 3, p = 0.0127). Furthermore, Spearman’s rank correlation analysis demonstrated a significant positive linear trend between the clinical severity level and the number of recognized allergens (ρ = 0.184, p = 0.0117). Bonferroni-corrected post hoc paired comparisons revealed that the main statistical contrast was between the MAP and MAP_Mod phenotypes, with a significant increase in the molecular burden of the latter (p = 0.016). Although the SPA phenotype had the highest median polysensitization in the study (median = 12.0), paired comparisons with the other groups did not reach statistical significance (p > 0.05), a phenomenon attributable to the limited statistical power resulting from the small sample size of this critical subgroup (n = 8).
Figure 5.
Number of positive allergen molecules (sIgE ≥ 0.30 kUA/L) across asthma phenotypes (n = 186). Boxes show the median and interquartile range; whisker and point definitions should be specified. Kruskal–Wallis p = 0.0127; Spearman ρ = 0.184, p = 0.0117. IA, intermittent asthma; MAP, mild persistent asthma; MAP_Mod, moderate persistent asthma; SPA, severe persistent asthma.
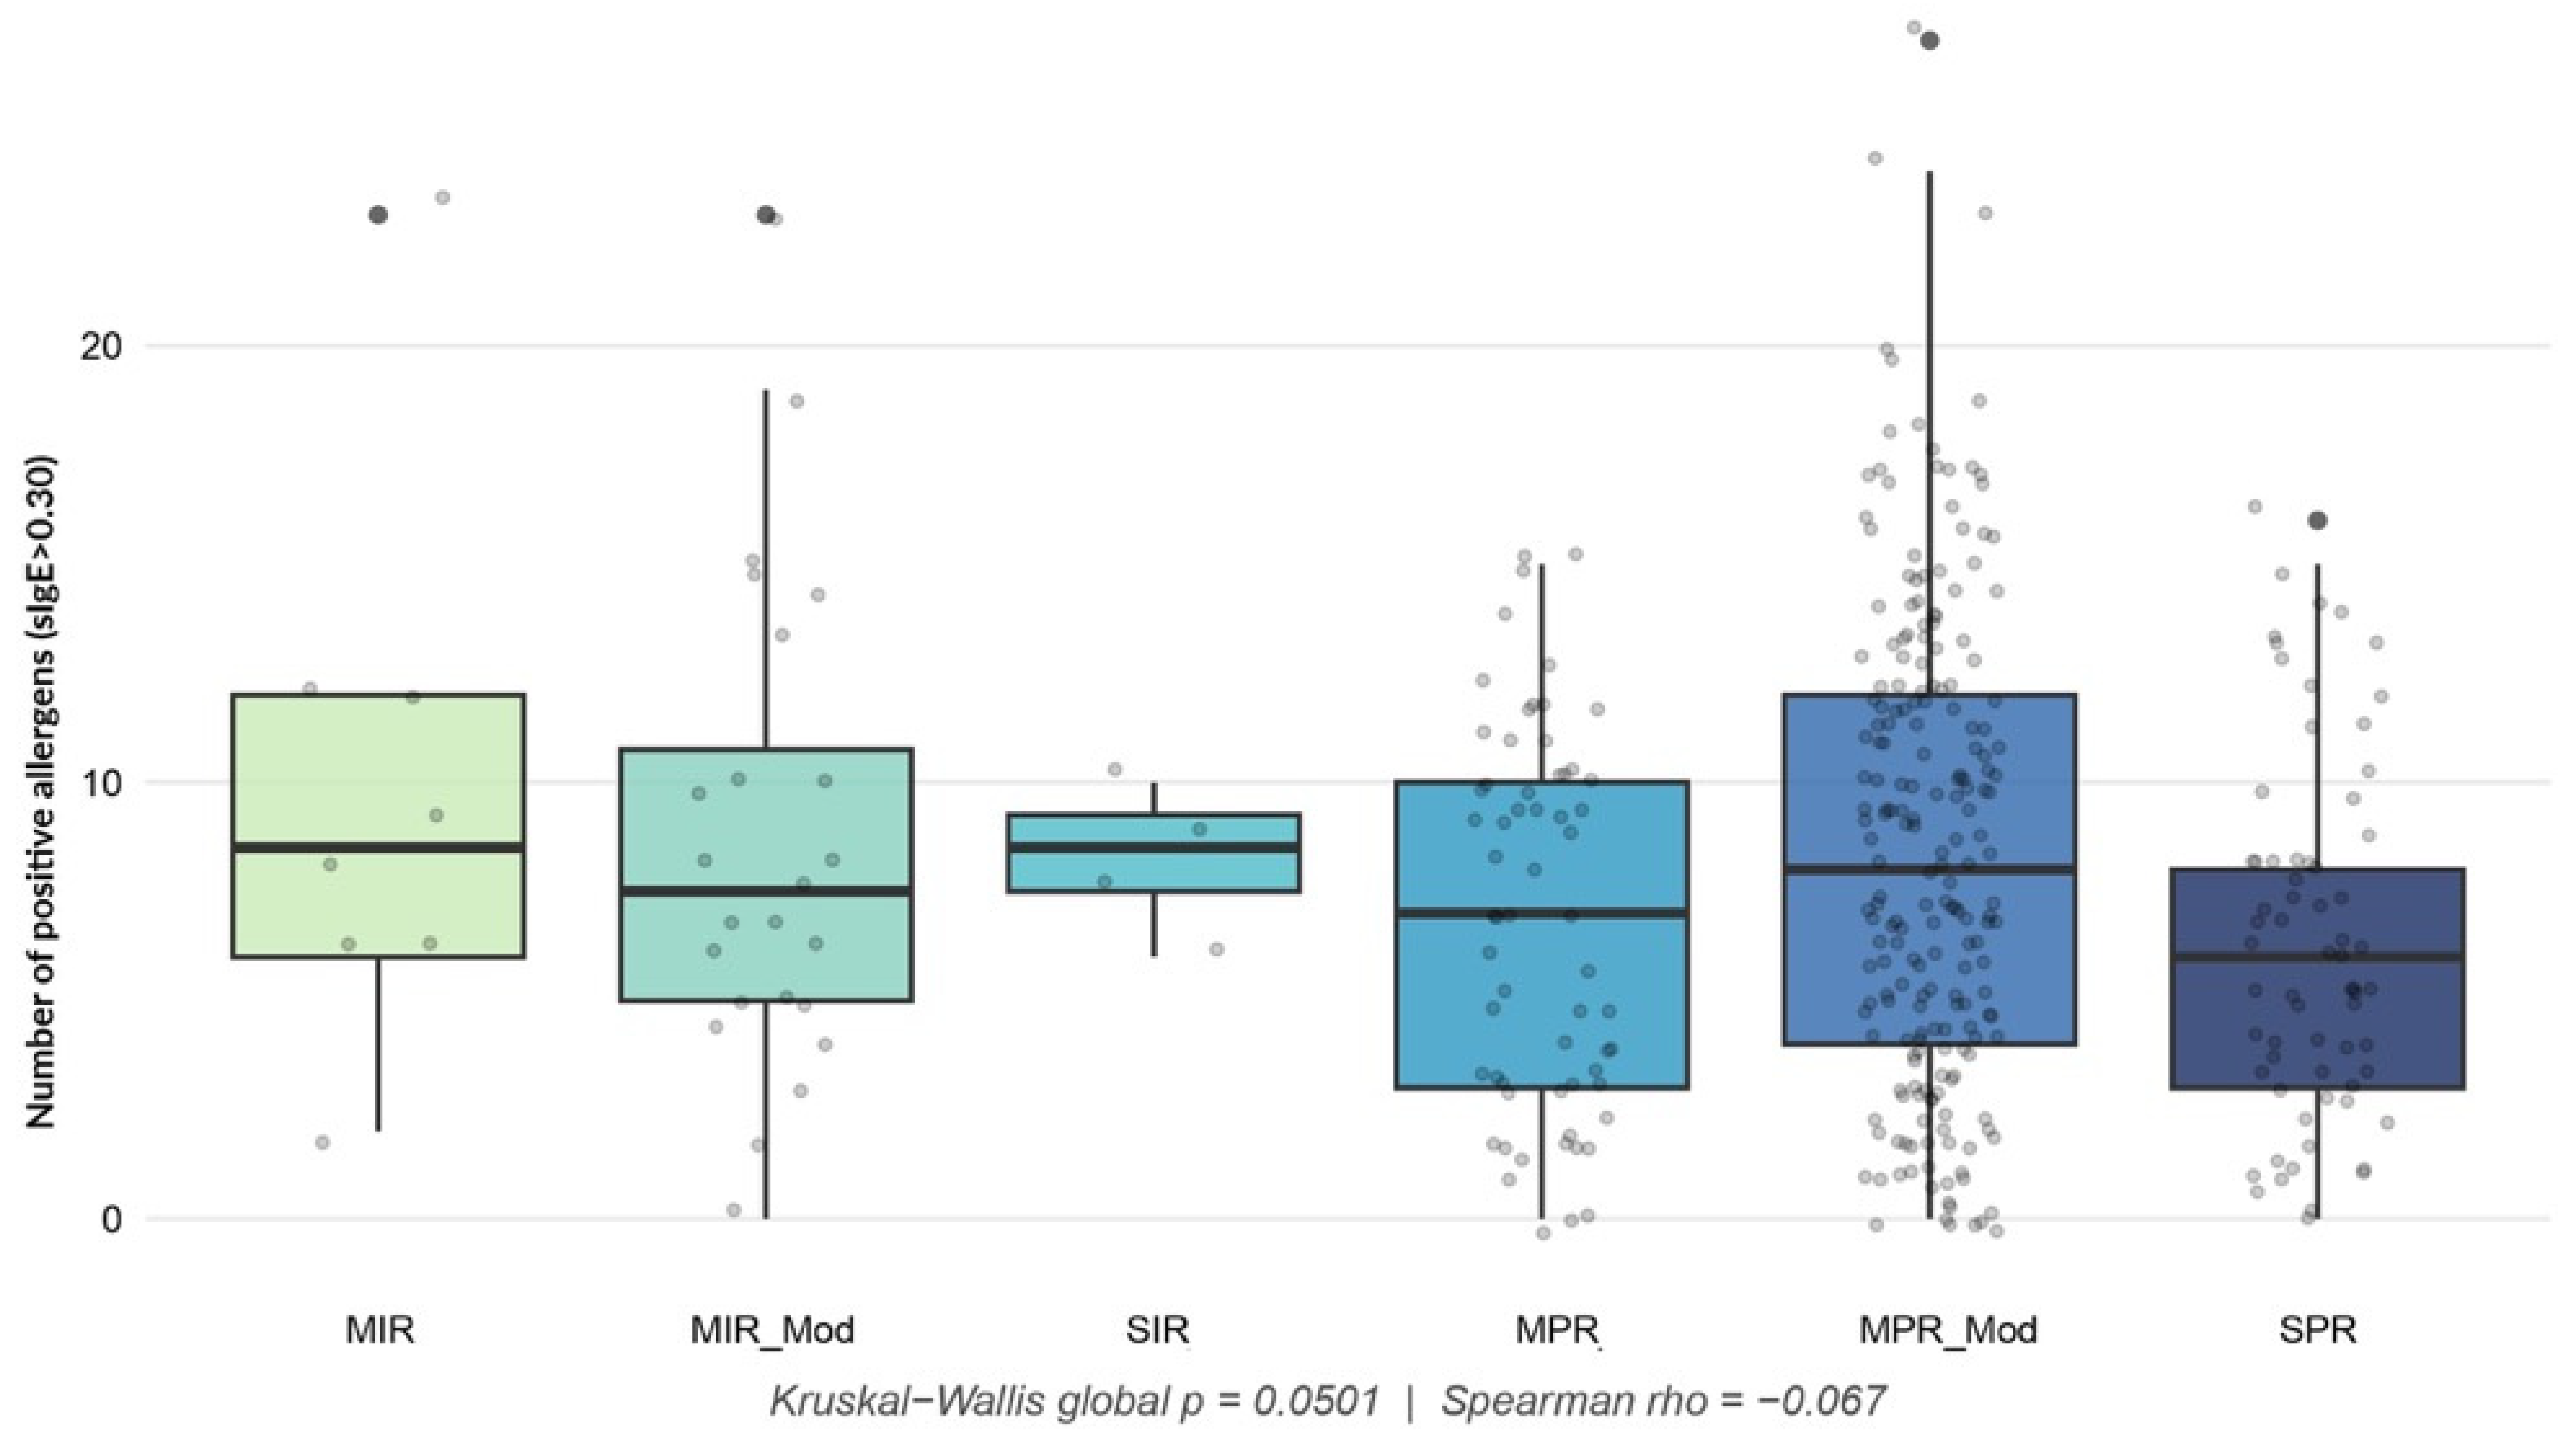
Unlike the findings in the asthma cohort, analysis of the molecular sensitization burden in patients with rhinitis (n = 374) did not show a linear association with the severity of nasal symptoms according to the ARIA classification (Figure 6). The overall Kruskal–Wallis test was at the threshold of statistical significance (χ2 = 11.07, df = 5, p = 0.0501), suggesting generalized homogeneity in the number of allergens recognized across the different clinical stages. This lack of progression was confirmed by Spearman’s trend test, which revealed no significant correlation between the severity of rhinitis and the number of positive molecular components (ρ = −0.067, p = 0.1949). Post hoc paired comparisons with Bonferroni correction showed no significant differences between any pair of phenotypes (p = 1.000 in most tests). Only a marginal, non-significant trend was observed when comparing the MPR_Mod group with the SPR group (p = 0.076).
Figure 6.
Number of positive allergen molecules (sIgE ≥ 0.30 kUA/L) across ARIA rhinitis phenotypes (n = 374). Boxes show the median and interquartile range; whisker and point definitions should be specified. Kruskal–Wallis p = 0.0501; Spearman ρ = −0.067, p = 0.1949. MIR, mild intermittent rhinitis; MIR_Mod, moderate intermittent rhinitis; SIR, severe intermittent rhinitis; MPR, mild persistent rhinitis; MPR_Mod, moderate persistent rhinitis; SPR, severe persistent rhinitis.
4. Discussion
4.1. Interpretation of the Principal Findings
This multicenter molecular study demonstrates geographical heterogeneity in aeroallergen sensitization among patients with allergic rhinitis and/or asthma recruited from four Argentine regions. The principal contrast was between the mite-dominant profile in Buenos Aires, also evident in Rosario-Santa Fe and Santa Rosa La Pampa, and the pollen-dominant profile in San Rafael-Mendoza. Alt a 1 and Fel d 1 were relevant across all centers. Notably, this study provides the first molecular assessment of Can f 5 sensitization in Argentina, identifying this component as a major contributor to dog sensitization across the evaluated regions. These findings extend previous molecular mapping studies conducted in different atopic phenotypes under subtropical exposure [11], climate-matched populations [12], four Peruvian cities [13], and multiple Spanish bioclimatic regions [14].
Molecular IgE repertoires should be interpreted as biological signatures of cumulative interactions between environmental exposure and host susceptibility rather than as direct measurements of allergen concentrations. Detectable sIgE demonstrates immune recognition but does not quantify current exposure or establish clinical relevance [15]. Within an exposome framework, the repertoire reflects exposure history together with epithelial integrity, immune regulation, previous residence, and individual susceptibility [16,17]. The geographical profiles are environmentally coherent but cannot establish causality.
Asthma severity showed a statistically significant but weak positive association with the number of recognized molecules, whereas no comparable relationship was observed for allergic rhinitis. Molecular polysensitization may contribute to asthma complexity but explains only limited clinical heterogeneity. In rhinitis, severity may depend more on the relevance and seasonality of the dominant allergen.
4.2. Regional Molecular Signatures and Environmental Context
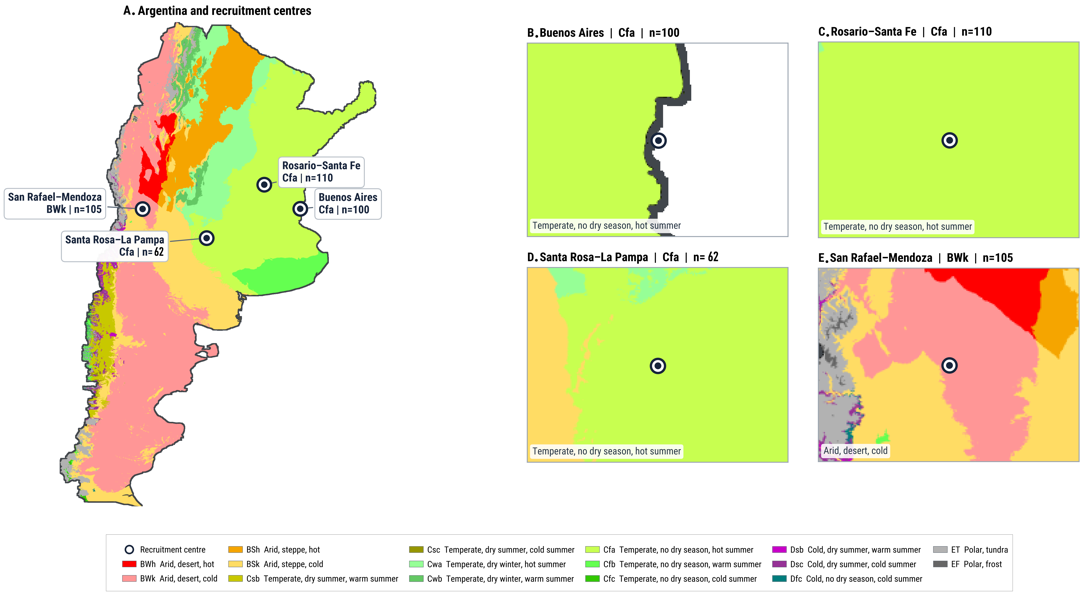
The four recruitment centers were situated within the 1991–2020 Köppen–Geiger classification to represent the long-term climatic context preceding recruitment, which occurred between January 2024 and September 2025 (Figure 7) [18]. The classification does not capture short-term anomalies and excludes irrigation, cultivated vegetation, housing microclimates, pollution, wildfire smoke, and occupational exposure. It should therefore be regarded as a contextual layer rather than an individual exposure metric or a sufficient explanation for the molecular profiles.
Figure 7.
Geographical location and Köppen–Geiger climate classification of the four Argentine recruitment regions. The background shows the 1991–2020 Köppen–Geiger climate classification (1-km resolution) according to Beck et al. (A). Buenos Aires (B), Rosario-Santa Fe (C), and Santa Rosa-La Pampa (D) are classified as Cfa, whereas San Rafael-Mendoza (E) is classified as BWk. Insets show the local climate surrounding each recruitment center. Adapted from [18]) under CC BY 4.0. ChatGPT (GPT-5.6; OpenAI) was also used to assist in the creation of and Figure 7.
4.2.1. Mite Sensitization and the Indoor Exposome
Buenos Aires displayed the strongest mite-dominant profile, characterized by Der p 1, Der p 2, Der p 23, and Der f 2. Rosario-Santa Fe and Santa Rosa-La Pampa showed intermediate profiles, whereas mite components were uncommon in San Rafael-Mendoza. The prominence of group 1, group 2, and Der p 23 allergens is consistent with their relevance in respiratory mite allergy [19,20]. Der p 23 may be particularly important in Argentina because greater recognition has been reported in Latin American than in Spanish mite-allergic populations [19].
Recognition of Der p 5, Der p 7, and Der p 21 indicates that the repertoire extended beyond the conventional major components. Such broad molecular profiles have been described in other populations [11,13,14,20]. Although molecular spreading may reflect sustained, intense, or early exposure, the cross-sectional design cannot determine timing or dose. Testing restricted to Der p 1 and Der p 2 could incompletely characterize some patients.
Storage-mite molecules, including Gly d 2, Lep d 2, and Tyr p 2, were also recognized. These findings may represent genuine co-sensitization, cross-reactivity among homologous group 2 allergens, or both.
Der p 11 was not detected in any population. Although initially proposed as a major allergen in selected mite-allergic patients with atopic dermatitis, subsequent evidence showed low and population-dependent recognition [21,22]. Its absence is therefore more likely to reflect limited and geographically variable sensitization than a specific association with respiratory phenotypes.
The Buenos Aires profile is plausible in a dense urban setting where outdoor climate interacts with indoor microenvironments. Mite proliferation is influenced more directly by humidity and temperature within bedding, mattresses, furniture, and poorly ventilated rooms than by city-level climatic averages; this explanation could also account for the high prevalence of mite sensitization observed in Santa Rosa. Pollution may act as a modifying coexposure rather than as the cause of mite-specific IgE. PM2.5 in Buenos Aires includes biomass burning, traffic, soil and road dust, construction, agricultural emissions, and industrial sources [23]. Rosario combines urban, industrial, port, and agro-industrial activities with episodic smoke from fires in the Paraná Delta [24]. These exposures cannot explain Der p-specific recognition but may amplify airway inflammation. Finally, the dry climate of Mendoza could explain the low prevalence of mite sensitization observed in our study.
4.2.2. Pollen Sensitization and Regional Vegetation
San Rafael-Mendoza exhibited the most extensive pollen-dominant profile, with frequent recognition of Ole e 1, Fra e 1, Phl p 1, Lol p 1, Sal k 1, Cup a 1, and plane-tree components. This pattern likely reflects the greater abundance of these pollen-producing plant species in San Rafael and is compatible with its irrigated semi-arid environment, where agriculture, urban planting, and ruderal vegetation provide diverse pollen sources. Low regional precipitation should not be equated with low pollen exposure: irrigation sustains vegetation, whereas dry and windy conditions may facilitate pollen release and dispersion.
Parallel recognition of Phl p 1 and Lol p 1 supports genuine grass-pollen sensitization, consistent with patterns reported in geographically heterogeneous populations [12,13,14]. Environmental pollen counts and airborne allergen concentrations are related but not equivalent. Atmospheric Phl p 1 and Phl p 5 concentrations do not always parallel total Poaceae pollen counts and may be influenced by meteorological conditions and pollutants [25].
The high frequency of Ole e 1 and Fra e 1 in San Rafael is compatible with substantial Oleaceae exposure, although the assay cannot identify the predominant species. Lower recognition of Ole e 7 and Ole e 9 suggests a profile mainly driven by Ole e 1-like proteins. Broader profiles involving these components have been associated with intense exposure and more severe respiratory disease [26]. Sal k 1 is consistent with exposure to Salsola or related Amaranthaceae, whereas Cup a 1 and plane-tree molecules may reflect planted urban or peri-urban vegetation.
Santa Rosa-La Pampa showed an intermediate profile combining mites with Phl p 1, Lol p 1, and Cup a 1. A local two-year survey identified 73 airborne pollen types, including Cupressaceae, Oleaceae, Platanus, Poaceae, and Amaranthaceae [27]. This agreement supports the interpretation that the IgE repertoire partly reflects regional vegetation.
Buenos Aires and Rosario-Santa Fe displayed the lowest frequencies of pollen sensitization and shared a broadly similar molecular profile, characterized by predominant sensitization to the major grass pollen allergens Phl p 1 and Lol p 1. This pattern is consistent with the aerobiological characteristics of both regions, where Poaceae pollen represents one of the major contributors to the atmospheric pollen load. The lower prevalence of sensitization to olive, cypress, and Salsola kali allergens compared with San Rafael is also in agreement with the more humid climate and the different composition of the regional vegetation.
Interestingly, sensitization to Ole e 1 was nevertheless detected in Buenos Aires, Rosario, and Santa Rosa despite the relatively limited abundance of olive trees in these regions. In contrast, ash (Fraxinus excelsior) is a common ornamental tree in all three cities. A plausible explanation is the well-established cross-reactivity between olive and ash pollens. Accordingly, Ole e 1 and Fra e 1 showed remarkably similar sensitization frequencies and mean sIgE levels across these regions, supporting the hypothesis that part of the observed Ole e 1 reactivity may reflect primary sensitization to ash pollen rather than genuine olive pollen sensitization.
4.2.3. Mold Sensitization and the Regional Fungal Exposome
Alt a 1 was the dominant fungal molecule in every region. Its distribution did not follow a simple humidity gradient, suggesting that fungal exposure depends on multiple environmental factors, including agricultural substrates, vegetation, short-term moisture, temperature, crop residues, wind, and spore-release conditions.
Alt a 1 is the dominant and most clinically informative molecular marker of genuine Alternaria alternata sensitization [28]. Its concentration in fungal extracts correlates with overall IgE-binding activity [29], while environmental levels of Alt a 1 have been associated with nasal and bronchial symptoms in sensitized patients [30]. Fungal diagnosis nevertheless remains complex because allergen expression may vary among strains, growth conditions, and source materials [28].
The high Alt a 1 recognition in San Rafael is compatible with an irrigated agricultural exposome. Alternaria can colonize crops, fruit, senescent leaves, and plant debris. Moisture may support fungal growth, whereas subsequent warm, dry, and windy conditions favor the aerosolization of dry conidia. Studies in the Southern Oasis of Mendoza identified Alternaria in the fungal microbiota of wine grapes [31]. These data document a plausible regional reservoir but not individual airborne exposure. Alt a 6 was infrequently recognized, although the restricted fungal panel may underestimate sensitization to other fungal molecules.
4.2.4. Animal Epithelia and Cockroach Components
Fel d 1 was the leading epithelial allergen in all centers and showed less regional variability than mites or pollens, consistent with widespread passive dissemination of cat allergen in homes without cats, schools, workplaces, vehicles, and public spaces. Among the dog molecules, Can f 5 was most frequently recognized, followed by Can f 1, although direct exposure and dog sex were not recorded.
Cockroach sensitization was uncommon and mainly represented by Bla g 9. Local species, housing conditions, and assay composition may influence detection. Because Bla g 9 is an arginine kinase with homologues in mites and other invertebrates, some responses may reflect cross-reactivity rather than primary cockroach sensitization.
4.3. Comparison with Previous Molecular Mapping Studies
The findings parallel molecular mapping studies performed in subtropical regions, climate-matched populations, Peru, and Spain [11,12,13,14]. Collectively, these investigations show that mite, pollen, fungal, and epithelial sensitization profiles differ substantially across geographical settings, even among patients sharing similar respiratory diagnoses.
Regional repertoires are likely shaped by interacting components of the external exposome—including climate, vegetation, irrigation, housing, occupation, urbanization, and pollution—rather than climate alone [16,17]. Buenos Aires may represent a predominantly urban indoor-mite environment; Rosario combines indoor allergens with port, agricultural, industrial, and wildfire-smoke exposures; Santa Rosa occupies an urban-agricultural transition zone; and San Rafael represents an irrigated semi-arid oasis with strong pollen and agricultural fungal signals. These are interpretative models, not measurements of personal exposure. Air pollution should mainly be considered an effect modifier capable of amplifying epithelial disruption and inflammation rather than a determinant of allergen-specific IgE [16,17].
4.4. Clinical and Therapeutic Implications
The regional differences have practical implications for precision diagnosis. In mite-dominant locations, assessment restricted to Der p 1 and Der p 2 could incompletely characterize patients recognizing Der p 23 [19,20] or additional mid-tier molecules such as Der p 5, Der p 7, and Der p 21 [11,14,20]. Molecular results should nevertheless be interpreted alongside exposure history, extract-based tests, and clinical symptoms. Although some of the molecular allergens assessed are considered less prevalent or less clinically relevant than conventionally recognized major allergens, their inclusion was intentional to provide a comprehensive characterization of the molecular sensitization profile and to capture potential geographical differences and cross-reactive patterns.
Discrepancies between in vivo skin prick testing (SPT) and in vitro molecular serum IgE evaluation emphasize that component-resolved diagnosis should complement rather than replace conventional testing. These discordances stem from fundamental differences between whole-extract tissue reactivity and circulating component-specific IgE, driven by unrepresented allergens in molecular panels, analytical sensitivity variations between skin and blood assays, cross-reactive IgE, or asymptomatic skin reactivity. In San Rafael-Mendoza, Ole e 1, Phl p 1, Lol p 1, Sal k 1, Cup a 1, and plane-tree molecules provide greater resolution than extract testing and may help distinguish genuine co-sensitization from panallergen-driven cross-reactivity. However, molecular positivity does not establish clinical relevance; symptom timing, pollen seasons, exposure history, and, where appropriate, provocation testing remain necessary.
Molecular diagnosis may improve allergen-immunotherapy selection by distinguishing genuine from cross-reactive sensitization and identifying clinically relevant sources [32]. Nevertheless, the patient’s IgE repertoire is not a direct measure of an immunotherapy product’s composition or potency. Alt a 1 recognition should prompt the assessment of symptom seasonality, lower-airway involvement, agricultural exposure, and periods of fungal-spore dispersion [28,30]. The weak association between molecular burden and asthma severity further indicates that polysensitization should be integrated with lung function, exacerbations, T2 biomarkers, adherence, smoking, occupation, dampness, mold, infections, and pollution.
4.5. Strengths, Limitations, and Future Directions
The principal strengths include the multicenter design, common eligibility framework, and standardized component-resolved assessment across four Argentine regions.
Limitations include the selected SPT-positive clinical cohort, cross-sectional design, differences in demographic and clinical composition among centers, and absence of multivariable adjustment. The high proportion of asthma in Santa Rosa-La Pampa may partly reflect referral or recruitment patterns and should not be interpreted as regional prevalence.
Environmental exposure was not measured directly. No contemporaneous pollen or fungal-spore counts, airborne allergen measurements, domestic mite sampling, pollution data, or individual geospatial information were linked to participants. The Köppen–Geiger map and regional studies provide context but cannot be assigned as personal exposures or establish causality [18,23,24,27,31]. Housing, indoor dampness, ventilation, pets, smoking, occupation, agricultural contact, and previous residence were not systematically recorded. Functional biomarkers such as basophil activation and markers of type-2 inflammation, including blood eosinophils and FeNO, were not assessed because the study was designed primarily to characterize allergen-specific molecular sensitization. The analysis was also restricted to components represented on the ALEX platform.
Future longitudinal studies should integrate molecular diagnosis with aerobiological monitoring, domestic mite sampling, pollution measurements, and personal exposure assessment. Residential geocoding could be combined with land use, irrigation, crops, traffic, industrial activity, and wildfire-smoke trajectories. Longitudinal symptoms, lung function, FeNO, eosinophils, and exacerbation records analyzed using multilevel models would help distinguish stable sensitization from clinically active exposure and clarify the contribution of the allergen exposome to respiratory disease.
5. Conclusions
This study identifies marked regional heterogeneity in molecular aeroallergen sensitization among patients with allergic rhinitis and/or asthma recruited in four Argentine locations. Mite components dominated in Buenos Aires and remained prominent in Rosario-Santa Fe and Santa Rosa-La Pampa, whereas San Rafael-Mendoza showed a pollen-dominant pattern with frequent recognition of Ole e 1, grass allergens (Phl p 1 and Lol p 1), Sal k 1, and Alt a 1. Fel d 1 was the leading epithelial component across centers, and cockroach sensitization was uncommon.
A broader molecular sensitization burden was weakly associated with asthma severity but not with rhinitis severity. These findings support geographically informed molecular assessment and provide a basis for future studies integrating clinical sensitization with direct environmental measurements. They should not be interpreted as population prevalence estimates or as evidence that regional climate caused the observed profiles.
Author Contributions
Conceptualization, J.F.M., R.G.-P. and F.P.; methodology J.F.M. and F.P.; investigation, J.F.M., M.I., S.G., L.A., E.G., M.d.G., M.I.A., M.C.F., E.A.-F., A.E.F., M.J.M., T.G.-D. and F.P.; writing—original draft preparation, J.F.M., A.E.F., M.J.M., T.G.-D., R.G.-P. and F.P.; writing—review and editing, J.F.M., M.I., S.G., L.A., E.G., M.d.G., M.I.A., M.C.F., E.A.-F., A.E.F., M.J.M., T.G.-D., R.G.-P. and F.P.; supervision, J.F.M. and F.P.; project administration, F.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was reviewed and approved by the Ethics Committee of Clinical Pharmacology-CIDEA, under approval number 12685 on 12 April 2024.
Informed Consent Statement
Written informed consent was obtained from the participants or legal guardians of all participating children under the age of 18 prior to their inclusion in the current investigation.
Data Availability Statement
The data that support the findings of this study are available from CIDEA, but restrictions apply to the availability of these data, which were used under license for the current study and so are not publicly available. Data are, however, available from the authors upon reasonable request and with permission of CIDEA.
Acknowledgments
During the preparation of this manuscript, the authors used ChatGPT (GPT-5.6; OpenAI) for editorial assistance to improve the manuscript’s clarity, grammar, and English-language translation. ChatGPT (GPT-5.6; OpenAI, San Francisco, CA, USA) was also used to assist in the creation of the graphical abstract and Figure 7. The authors reviewed and edited all AI-generated output and take full responsibility for the content of this publication.
Conflicts of Interest
F.P., E.A.-F., A.-E.F., M.-J.M., T.G-D. are employed by Inmunotek S.L. Laboratories, Madrid, Spain. The remaining authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
References
- Pawankar, R. Allergic diseases and asthma: A global public health concern and a call to action. World Allergy Organ. J. 2014, 7, 12. [Google Scholar] [CrossRef] [Scilit]
- Vázquez, D.; Medina, I.; Logusso, G.; Arias, S.; Gattolin, G.; Parisi, C. Cross-sectional survey about the prevalence of allergic rhinitis in Argentina: Study PARA. Rev. Alerg. Mex. 2019, 66, 55–64. [Google Scholar] [CrossRef] [Scilit]
- Solé, D.; Mallol, J.; Camelo-Nunes, I.C.; Wandalsen, G.F. Prevalence of rhinitis-related symptoms in Latin American children: Results of the International Study of Asthma and Allergies in Childhood (ISAAC) phase three. Pediatr. Allergy Immunol. 2010, 21, e127–e136. [Google Scholar] [CrossRef] [Scilit]
- Pendino, P.; Agüero, C.; Cavagnero, P.; Lopez, K.; Kriunis, I.; Molinas, J. Aeroallergen sensitization in wheezing children from Rosario, Argentina. World Allergy Organ. J. 2011, 4, 159–163. [Google Scholar] [CrossRef] [Scilit]
- Ramon, G.D.; Vanegas, E.; Felix, M.; Barrionuevo, L.B.; Kahn, A.M.; Bertone, M.; Reyes, M.S.; Gaviot, S.; Ottaviano, C.; Cherrez-Ojeda, I. Year-long trends of airborne pollen in Argentina: More research is needed. World Allergy Organ. J. 2020, 13, 100135. [Google Scholar] [CrossRef] [Scilit]
- D’Amato, G.; Chong-Neto, H.J.; Monge Ortega, O.P.; Vitale, C.; Ansotegui, I.; Rosario, N.; Haahtela, T.; Galan, C.; Pawankar, R.; Murrieta-Aguttes, M.; et al. The effects of climate change on respiratory allergy and asthma induced by pollen and mold allergens. Allergy 2020, 75, 2219–2228. [Google Scholar] [CrossRef] [Scilit]
- Annesi-Maesano, I.; Maesano, C.N.; Biagioni, B.; D’Amato, G.; Cecchi, L. Call to action: Air pollution, asthma, and allergy in the exposome era. J. Allergy Clin. Immunol. 2021, 148, 70–72. [Google Scholar] [CrossRef] [Scilit]
- Wild, C.P. Complementing the genome with an “exposome”: The outstanding challenge of environmental exposure measurement in molecular epidemiology. Cancer Epidemiol. Biomark. Prev. 2005, 14, 1847–1850. [Google Scholar] [CrossRef] [Scilit]
- Cecchi, L.; D’Amato, G.; Annesi-Maesano, I. External exposome and allergic respiratory and skin diseases. J. Allergy Clin. Immunol. 2018, 141, 846–857. [Google Scholar] [CrossRef] [Scilit]
- Renz, H.; Holt, P.G.; Inouye, M.; Logan, A.C.; Prescott, S.L.; Sly, P.D. An exposome perspective: Early-life events and immune development in a changing world. J. Allergy Clin. Immunol. 2017, 140, 24–40. [Google Scholar] [CrossRef] [Scilit]
- González-Pérez, R.; Poza-Guedes, P.; Pineda, F.; Galán, T.; Mederos-Luis, E.; Abel-Fernández, E.; Martínez, M.J.; Sánchez-Machín, I. Molecular mapping of allergen exposome among different atopic phenotypes. Int. J. Mol. Sci. 2023, 24, 10467. [Google Scholar] [CrossRef] [Scilit]
- González-Pérez, R.; Galván-Calle, C.A.; Galán, T.; Poza-Guedes, P.; Sánchez-Machín, I.; Enrique-Calderón, O.M.; Pineda, F. Molecular signatures of aeroallergen sensitization in respiratory allergy: A comparative study across climate-matched populations. Int. J. Mol. Sci. 2025, 26, 284. [Google Scholar] [CrossRef] [Scilit]
- Galván, C.A.; Durán, R.; Galán, T.; Abel-Fernández, E.; Canal-Solis, K.; González-Pérez, R.; Pineda, F. Patterns of Immunoglobulin E-Mediated Molecule Sensitization across Four Peruvian Cities: Exploring Relationships with Regional Climate Classifications. Int. Arch. Allergy Immunol. 2026, 187, 261–272. [Google Scholar] [CrossRef] [Scilit]
- González-Pérez, R.; Poza-Guedes, P.; Igea Aznar, J.M.; Segovia, C.R.; Montes, A.T.; Parra, B.F.; Vásquez-Suero, M.; Pulido, A.N.; Hernández, M.S.; Calderón, J.L.; et al. EXPOMOL: Precision medicine in allergic rhinitis and conjunctivitis—Integrative molecular mapping of the allergic exposome in Spain. J. Investig. Allergol. Clin. Immunol. 2026, 37. [Google Scholar] [CrossRef] [Scilit]
- Gevaert, P.; Wong, K.; Millette, L.A.; Carr, T.F. The Role of IgE in Upper and Lower Airway Disease: More Than Just Allergy! Clin. Rev. Allergy Immunol. 2022, 62, 200–215. [Google Scholar] [CrossRef] [Scilit]
- Amini, H.; Amini, M.; Wright, R.O. Climate change, exposome change, and allergy. Immunol. Allergy Clin. N. Am. 2024, 44, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Agache, I.; Balbin-Ramon, G.J.; Saenz, F.K.F.; Sola-Arnau, I.; Alonso-Coello, P.; Haahtela, T.; Traidl-Hoffmann, C.; O’MAhony, L.; Damialis, A.; Lauerma, A.; et al. The impact of environmental exposures on allergic diseases: A systematic review. Allergy 2025, 80, 3027–3042. [Google Scholar] [CrossRef] [Scilit]
- Beck, H.E.; McVicar, T.R.; Vergopolan, N.; Berg, A.; Lutsko, N.J.; Dufour, A.; Zeng, Z.; Jiang, X.; van Dijk, A.I.J.M.; Miralles, D.G. High-resolution 1-km Köppen–Geiger maps for 1901–2099 based on constrained CMIP6 projections. Sci. Data 2023, 10, 724. [Google Scholar] [CrossRef] [Scilit]
- Calzada, D.; Bartra, J.; Serrano, C.D.; Riggioni, S.; Moran, E.; Maselli, J.; Silva, D.; Ramirez, L.; Pascal, M.; Carnés, J.; et al. Differences in molecular sensitisation profiles between Spanish and Latin American mite-allergic patients. J. Investig. Allergol. Clin. Immunol. 2025, 35, 114–121. [Google Scholar] [CrossRef] [Scilit]
- Posa, D.; Perna, S.; Resch, Y.; Lupinek, C.; Panetta, V.; Hofmaier, S.; Rohrbach, A.; Hatzler, L.; Grabenhenrich, L.; Tsilochristou, O.; et al. Evolution and predictive value of IgE responses toward a comprehensive panel of house dust mite allergens during the first two decades of life. J. Allergy Clin. Immunol. 2017, 139, 541–549.e8. [Google Scholar] [CrossRef] [Scilit]
- Calderón, M.A.; Linneberg, A.; Kleine-Tebbe, J.; De Blay, F.; Hernandez Fernandez de Rojas, D.; Virchow, J.C.; Demoly, P. Respiratory allergy caused by house dust mites: What do we really know? J. Allergy Clin. Immunol. 2015, 136, 38–48. [Google Scholar] [CrossRef] [Scilit]
- Banerjee, S.; Resch, Y.; Chen, K.W.; Swoboda, I.; Focke-Tejkl, M.; Blatt, K.; Novak, N.; Wickman, M.; van Hage, M.; Ferrara, R.; et al. Der p 11 is a major allergen for house dust mite-allergic patients suffering from atopic dermatitis. J. Investig. Dermatol. 2015, 135, 102–109. [Google Scholar] [CrossRef] [Scilit]
- Lichtig, P.; Gelman Constantin, J.; Diaz Resquin, M.; Victorica, F.B.; Alessandrello, D.; Gómez, D.; Rössler, C.; de Oto, M.; Guerrero, R.E.; Bajano, H.; et al. Chemical characterisation and source apportionment of PM2.5 in Buenos Aires. Atmos. Environ. 2025, 353, 121236. [Google Scholar] [CrossRef] [Scilit]
- Valle Seijo, M.F.; Micheletti, M.I.; Otero, L.A.; Piacentini, R.D. Atmospheric pollutants over Rosario assessed by remote sensing: Influence of wildfires and COVID-19 restrictions. Remote Sens. Appl. Soc. Environ. 2024, 36, 101326. [Google Scholar] [CrossRef] [Scilit]
- Cabrera, M.; Subiza, J.; Fernández-Caldas, E.; Garzón García, B.; Moreno-Grau, S.; Subiza, J.L. Influence of environmental drivers on allergy to pollen grains in a case study in Spain (Madrid): Meteorological factors, pollutants, and airborne concentration of aeroallergens. Environ. Sci. Pollut. Res. Int. 2021, 28, 53614–53628. [Google Scholar] [CrossRef] [Scilit]
- Alcántara Villar, M.; Anaya Anaya, S.; López Guerrero, A.; Martínez Chamorro, A.; Garrido, C.R. Olive-pollen molecular sensitisation profiles and respiratory disease severity in Jaén. World Allergy Organ. J. 2025, 18, 101030. [Google Scholar] [CrossRef] [Scilit]
- Caramuti, V.E.; Naab, O.A.; Murray, M.G. First report of airborne pollen in Santa Rosa, La Pampa, Argentina: A 2-year survey. Aerobiologia 2014, 30, 293–305. [Google Scholar] [CrossRef] [Scilit]
- Gabriel, M.F.; Postigo, I.; Tomaz, C.T.; Martínez, J. Alternaria alternata allergens: Markers of exposure, phylogeny and risk of fungi-induced respiratory allergy. Environ. Int. 2016, 89–90, 71–80. [Google Scholar] [CrossRef] [Scilit]
- Asturias, J.A.; Arilla, M.C.; Ibarrola, I.; Eraso, E.; González-Rioja, R.; Martínez, A. A sensitive two-site enzyme-linked immunosorbent assay for measurement of the major Alternaria alternata allergen Alt a 1. Ann. Allergy Asthma Immunol. 2003, 90, 529–535. [Google Scholar] [CrossRef] [Scilit]
- Feo Brito, F.; Alonso, A.M.; Carnés, J.; Martín-Martín, R.; Fernández-Caldas, E.; Galindo, P.A.; Alfaya, T.; Amo-Salas, M. Correlation between Alt a 1 levels and clinical symptoms in Alternaria-monosensitised patients. J. Investig. Allergol. Clin. Immunol. 2012, 22, 154–159. [Google Scholar]
- Prendes, L.P.; Merín, M.G.; Zamora, F.A.; Courtel, C.; Vega, G.A.; Ferreyra, S.G.; Fontana, A.R.; Ramirez, M.L.; Morata, V.I. Alternaria, tenuazonic acid, and spoilage yeasts associated with wine grapes in the Southern Oasis of Mendoza. Fermentation 2025, 11, 536. [Google Scholar] [CrossRef] [Scilit]
- Matricardi, P.M.; Dramburg, S.; Potapova, E.; Skevaki, C.; Renz, H. Molecular diagnosis for allergen immunotherapy. J. Allergy Clin. Immunol. 2019, 143, 831–843. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.