- Article

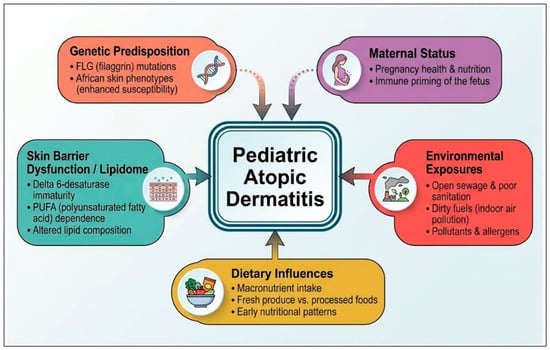
Atopic dermatitis (AD) is a prevalent pediatric inflammatory skin disorder. While AD prevalence has stabilized in high-income nations, it is rising rapidly in low-and middle-income countries due to urbanization and changing environmental factors. This study investigates AD prevalence and associated socio-demographic, environmental, and dietary factors among preschool children in Alexandra, an informal urban settlement in South Africa. A community-based, cross-sectional study was conducted among 3265 children under five years enrolled in early childhood development centers. Data were collected via parent-administered questionnaires using standardized International Study of Asthma and Allergies in Childhood criteria to assess AD status, along with socio-demographic, indoor/outdoor environmental, and dietary variables. Multivariate logistic regression determined adjusted odds ratios (AORs) for factors associated with AD. AD prevalence was 19.72%. Children aged 1 to 3 years (AOR = 2.24), those with a familial predisposition to asthma (AOR = 2.58), and those with a personal history of asthma (AOR = 3.62) had significantly higher odds of AD. Regarding environmental exposures, residing within 1 km of open sewage drastically increased AD odds (AOR = 3.61), as did exposure to indoor cats (AOR = 1.26) and dogs (AOR = 1.45). Conversely, using clean energy for cooking was strongly inversely associated with AD (AOR = 0.48). Dietary analysis revealed that high-frequency consumption of street vegetables (AOR = 2.19) and nuts (AOR = 1.36) was associated with increased AD odds, whereas frequent red meat (AOR = 0.52) and egg (AOR = 0.66) consumption showed protective associations. Pediatric AD is a significant public health burden in South African townships, heavily influenced by localized socio-ecological factors. Proximity to open sewage and reliance on dirty domestic fuels are major environmental correlates, while distinct, age-stratified dietary associations highlight the complex interplay of metabolic immaturity and urban environmental toxicity, underscoring the inadequacy of extrapolating HICs data to the settings of low-and middle-income countries. Future public health interventions must prioritize clean energy transitions and wastewater management to mitigate this growing burden.
16 November 2026