


Abstract
Periodontal disease (PD) is a multi-factorial condition that may lead to tissue destruction and tooth loss. Multirooted teeth are at high risk due to the furcation space where roots diverge, and new regenerative therapies are needed to support complete repair. This study assessed safety and preliminary efficacy of an injectable piezoelectric-based hydrogel (Ambrilux Dental Gel) in a canine model of ligature-induced PD. Animals were randomized to study treatment (n = 3) (two applications 28 days apart) or control (n = 3). Laboratory results were normal throughout the study. Radiographs demonstrated increase in furcation bone density in all treated animals by 28 days after first treatment, which continued following the second treatment. Control animals showed continued loss of bone or minimal regeneration. Quantitative CT showed treated animals had 37% greater furcation bone mineral density, 18% greater bone volume and 21% greater bone volume to tissue volume ratio compared to control. As a proof-of-concept evaluation with limited sample size, findings provide the first direct evidence that a degradable, piezo-based hydrogel is efficacious for PD treatment in large animals and can inform future, larger-scale studies. The ability of Ambrilux to promote bone growth in tooth furcations suggests it could be a safe and novel approach to PD.
1. Introduction
Periodontal disease (PD) is a chronic, multi-factorial condition that impacts two in five adults in the United States, with prevalence increasing with age [1]. It is characterized by increased bacterial colonization of the impacted teeth, followed by the generation of a substantial inflammatory response in the surrounding tissues. If left untreated or if treatment is not successful, PD may lead to the destruction of the bone and ligaments surrounding the tooth and subsequent loss of the tooth. PD requires ongoing supportive treatment, but tooth loss is common even with treatment; it was reported that over half of patients lost at least one molar over ten years of periodontal treatment [2].
The goal of periodontal treatment is to improve the tissue environment by reducing or eliminating dental plaque biofilm and calculus from the surface of the tooth, thereby stopping progression of tissue damage and ideally restoring healthy tissue. This can be accomplished through a broad range of non-surgical and surgical options, including scaling to remove supragingival bacterial plaque and calculus; comprehensive root planing to treat root surface irregularities or alterations; chemotherapeutic agents to address microbial pathogens or alter host response; resective procedures; and regenerative procedures [3]. Periodontal regenerative procedures include soft tissue grafts, bone replacement grafts, root biomodification, tissue regeneration, and combinations of these procedures. Severe cases of PD may require reconstructive procedures involving bone regeneration, augmentation of the upper or lower jaw, and implant site development.
Multirooted teeth, such as molars, are anatomically complex due to the presence of the furcation space where the roots of the tooth diverge. The furcation of a tooth, which plays an important role in stabilization, is difficult to reach and therefore more prone to plaque deposition and higher risk of bone loss. The degree of furcation involvement (FI) closely correlates with the long-term prognosis of the tooth, with chance of extraction increasing as FI increases. As defined by Glickman et al. [4], the classifications of FI are:
Class I: Incipient lesion, characterized by a supra-bony pocket and slight bone loss in the furcation area.
Class II: Loss of inter-radicular bone and pocket formation, but a portion of the alveolar bone and periodontal ligament remain intact.
Class III: Through-and-through lesion.
Class IV: Through-and-through lesion with gingival recession, leading to a clearly visible furcation area.
Furcation defects are particularly difficult to treat, and current therapy focuses on resective and regenerative therapies, with extraction as a last resort. Among these lesions, Class II and Class III furcation defects represent one of the most demanding clinical challenges due to their complex, multi-walled microanatomy. Current therapies, including open flap debridement, guided tissue regeneration and bone grafting, frequently result in incomplete regeneration and unpredictable clinical outcomes [5,6]. This therapeutic inconsistency is heavily driven by the limited accessibility of the defects, which severely hinders thorough surgical instrumentation and uniform graft adaptation. Further, standard scaffolds often fail to support adequate neovascularization, resulting in premature graft necrosis. Oral pathogens within the furcation also increase the risk of infection-associated failure, which halts tissue synthesis and destroys newly formed matrices. Finally, even when initial bone filling is achieved, conventional constructs lack the structural integration necessary to ensure long-term stability, frequently culminating in recurrent bone loss and long-term stability issues [7,8]. Overall, the current therapies available to address PD are limited by risks of incomplete regeneration, inadequate vascularization, infection-associated failure, and long-term stability issues. A consensus panel convened by the American Academy of Periodontology (AAP) Regeneration Workshop found that periodontal regeneration has been established as a viable treatment option for various furcation defects [9]. This panel also supported research to investigate novel regenerative approaches, as new regenerative therapies are needed to improve the complete resolution of furcation defects [9,10]. Based on the proof-of-concept data presented in this study, the use of bioactive hydrogels is in line with these recommendations.
To overcome the limitations of conventional scaffolds in adapting to complex oral defects, such as that noted in PD, multifunctional biomaterials have emerged as a cornerstone of modern regenerative dentistry [11]. The development of injectable hydrogels has advanced tissue engineering by offering minimally invasive delivery pathways and providing the ability to adapt to irregular anatomical spaces [12,13]. While early-stage hydrogels acted primarily as space fillers, new iterations of hydrogels are designed to provide critical 3D structural support that mimics the native extracellular matrix. Advanced hydrogels also offer the ability to act as drug delivery systems by regulating the release of bioactive signals, therapeutics or cells in a highly tunable manner [14,15]. As such, the ability of a degradable piezoelectric hydrogel to promote bone regeneration, both around the tooth, as well as with the difficult-to-treat furcation, represents an important advancement in regenerative dentistry.
One new approach harnesses the piezoelectric effect to induce tissue regeneration. Bone, cartilage, and collagen fibers are natural piezoelectric materials and therefore can generate an electric charge when subject to mechanical forces. The piezoelectric properties of bone are thought to play an important role in mediating natural remodeling of the tissue and assist in the repair of bone following injury [16]. A new regenerative therapy for PD that mimics the piezoelectric properties of bone to regenerate tissue is under development. Ambrilux Dental Gel (formerly known as PiezoGEL) Oral Biolife, Bethlehem, PA, USA), is a hydrogel placed in the periodontal pocket that is embedded with piezoelectric fillers designed for tissue regeneration through electrical stimulation. This hydrogel is administered directly into the periodontal pocket via a minimally invasive probe and subsequently light-cured to form an in situ graft. The primary functional mechanism of Ambrilux is mechanical [17]; the biocompatible piezoelectric ceramic fillers embedded in the gel are activated by natural biomechanical vibrations, such as those from chewing, jaw movements, and vocalizations, to produce the electrical charges necessary for stimulating osteogenic cells and promoting bone tissue regeneration. In addition, the hydrogel component (GelMA) provides an important physical scaffold for the recruitment and growth of bone cells.
Previous in vitro and rodent studies have examined both the mechanism and potential efficacy of Ambrilux. Roldan et al. demonstrated that Ambrilux promoted bone regeneration in a murine ligature-induced PD model [18]. This study also showed, using in vitro assay system, that mechanistimulation of bone marrow stem cells cultured in the presence of Ambrilux resulted in the expression of key genes involved in osteogenic differentiation. Recent work has also shown enhanced cell viability and odontogenic differentiation of human dental pulp stem cells, suggesting that Ambrilux may be of potential use in the setting of vital pulp therapy [19].
The current exploratory study was designed to examine the safety profile and efficacy signals of an injectable piezoelectric-based hydrogel in canines following the development of ligature-induced PD. The study objective was to generate key preliminary data and establish effect sizes for future, adequately powered confirmatory studies. In adherence with the ethical principles of animal research, the group sizes were restricted to the minimum required for establishing the initial dataset for evaluating early-stage efficacy and safety trends.
2. Results and Discussion
2.1. Safety Data
Health observations (general health, physical examination and final necropsy) were within normal results for all animals (control and treated) in the study. No adverse events were reported.
Comprehensive chemistry, hematology, and urinalysis were used to assess animal health and specific organ system health and assist in identifying any potential toxicities. The laboratory data for Days 1, 29 and 57 (Supplemental Tables S1–S3) showed normal results throughout the study, indicating that the subjects remained in good health throughout, and the study treatment did not elicit any untoward changes in the measured parameters.
2.2. Clinical Evaluations
Periodontal evaluations were performed on Day 56 before placement of ligatures, Day 1 after ligature removal, Day 29 and Day 57. The dataset derived from the in-life periodontal examinations is provided in Supplemental Tables S4 and S5. A review of the PI, GI, PPD, CAL, and BoP data did not show any appreciable trends between groups.
2.3. Radiographic Analysis
Radiographic analysis showed that at the end of the PD induction phase, all animals in both the control and treatment groups demonstrated multiple molars that showed moderate interproximal bone loss and furcation defects. This indicates that the ligature protocol utilized was successful in initiating a moderate degree of PD.
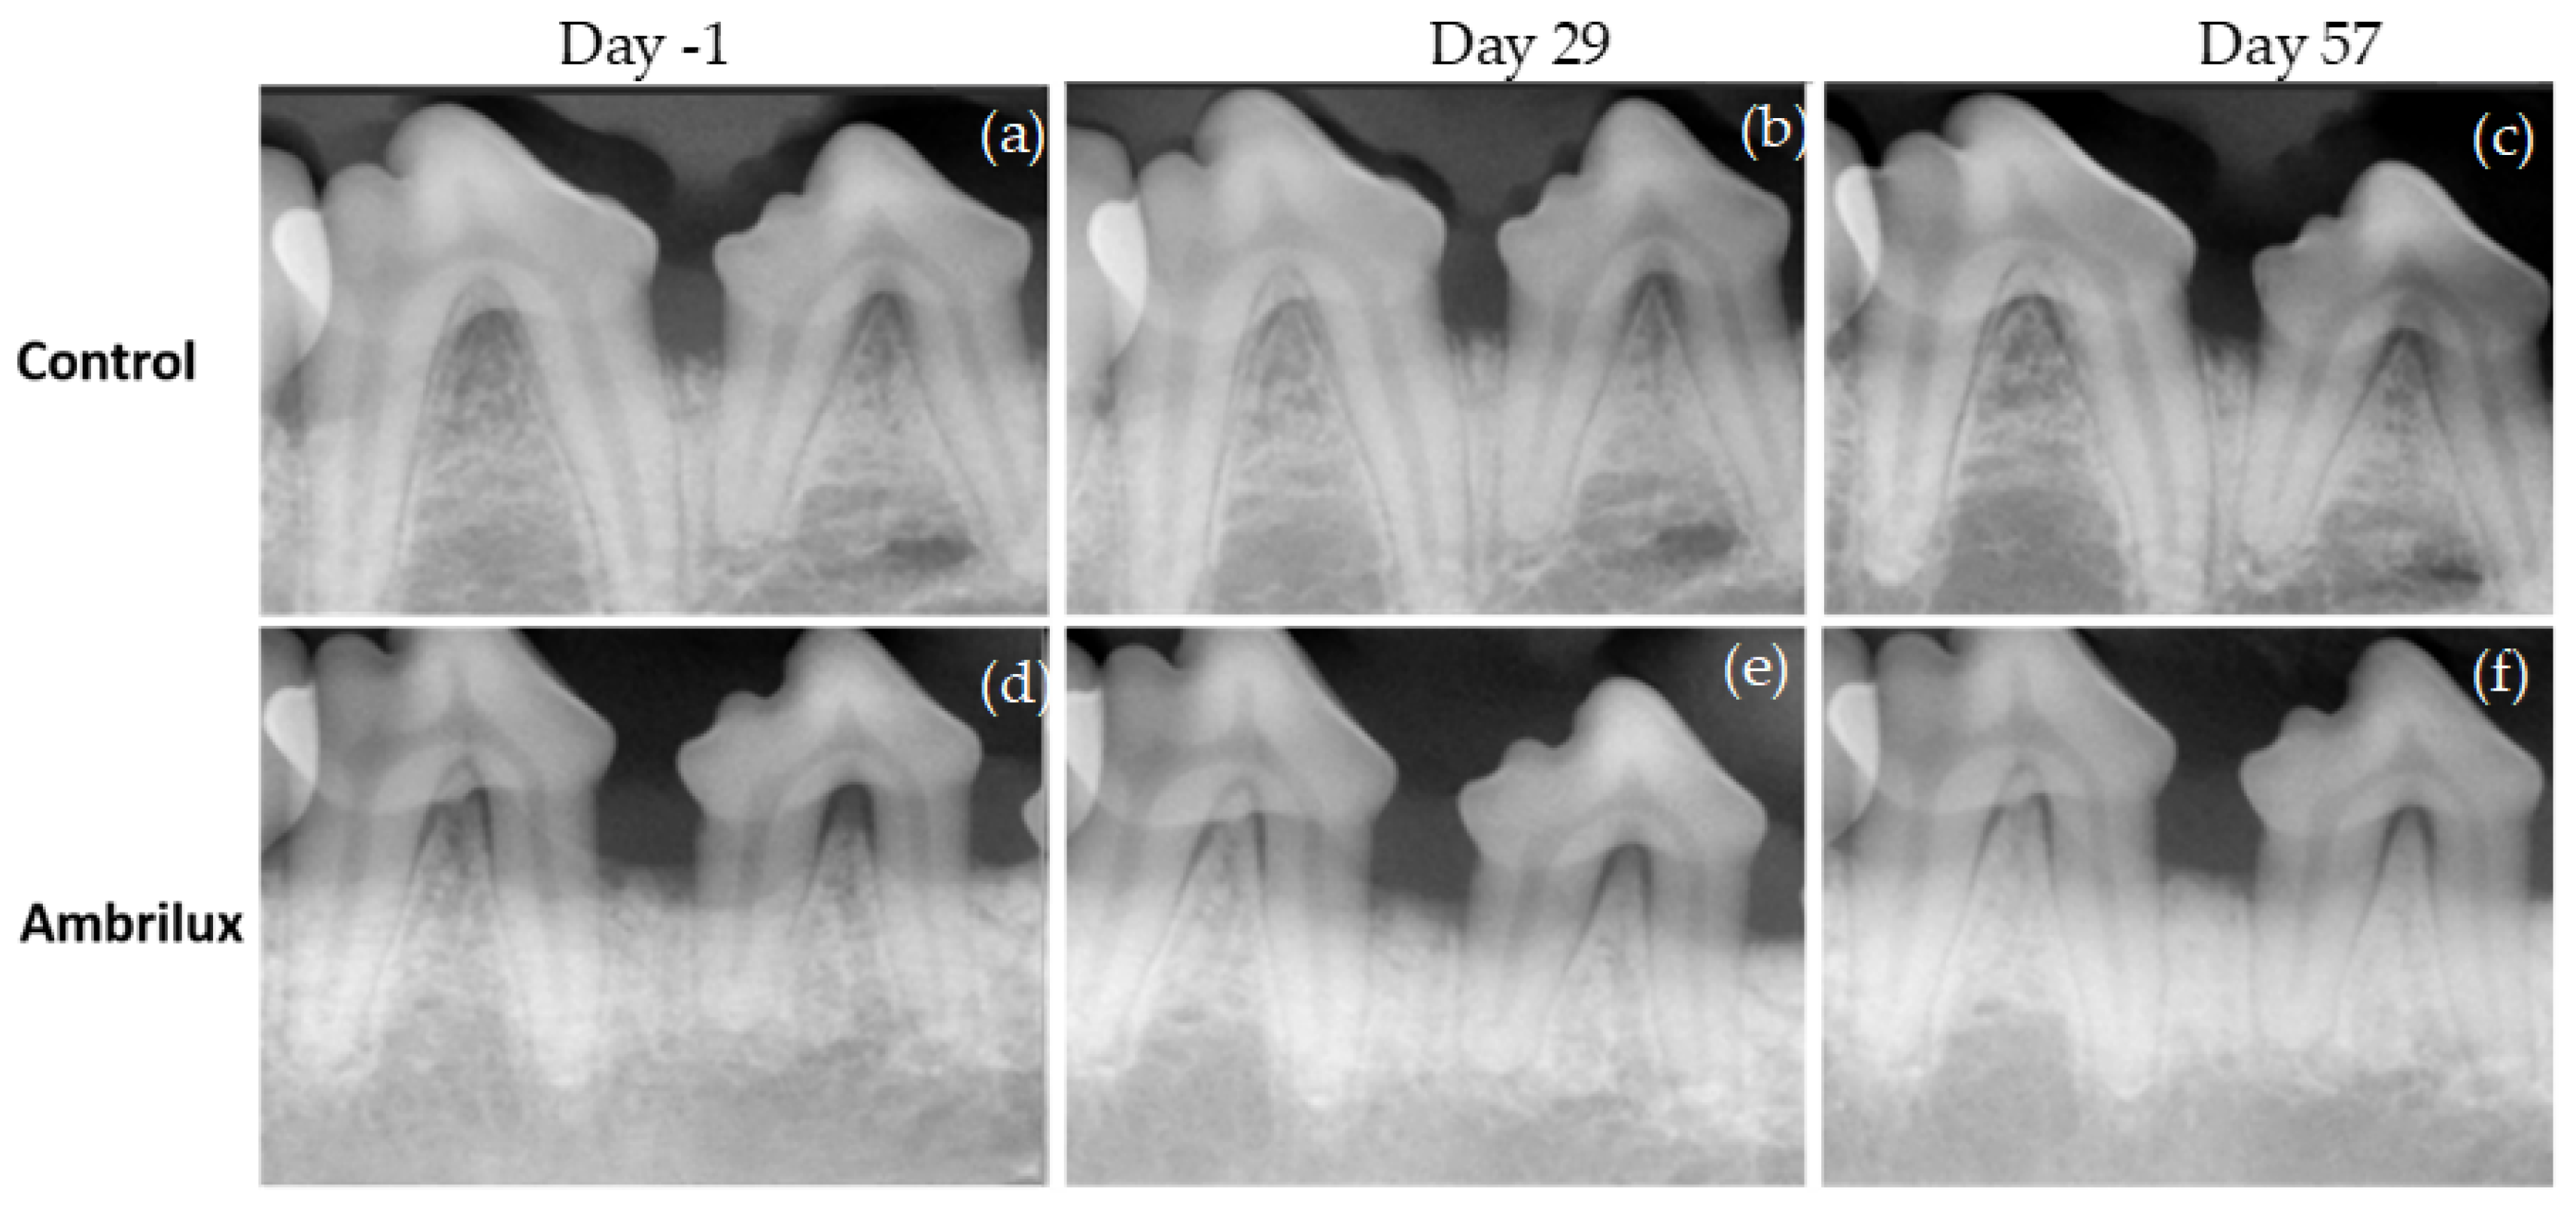
All the animals in the treatment group showed increasing radiopacity of the interproximal and furcation bone over time, with a corresponding decrease in the distance between the furcation fornix and base of the defect. Temporal analysis of radiographs showed that within 30 days post-application of the piezolectric gel, a notable bone growth response could be observed in the furcation region (Figure 1). Bone growth in the furcations of treated animals continued to be observed following the second application period. This degree of response was noted for all treated animals and was not observed in non-treated animals, in which either continuing bone loss or minimal bone regrowth in the furcations were observed by the end of the study.
Figure 1.
Temporal radiographs of control (588) (a–c) and Ambrilux-treated animal (913) (d–f). Images were obtained on Day 1 prior to Dose 1, Day 29 prior to Dose 2 and Day 57. The treated animal demonstrated increased bone formation, specifically in the tooth furcation.
2.4. Qualitative Histological Analysis
2.4.1. Proximal Regions
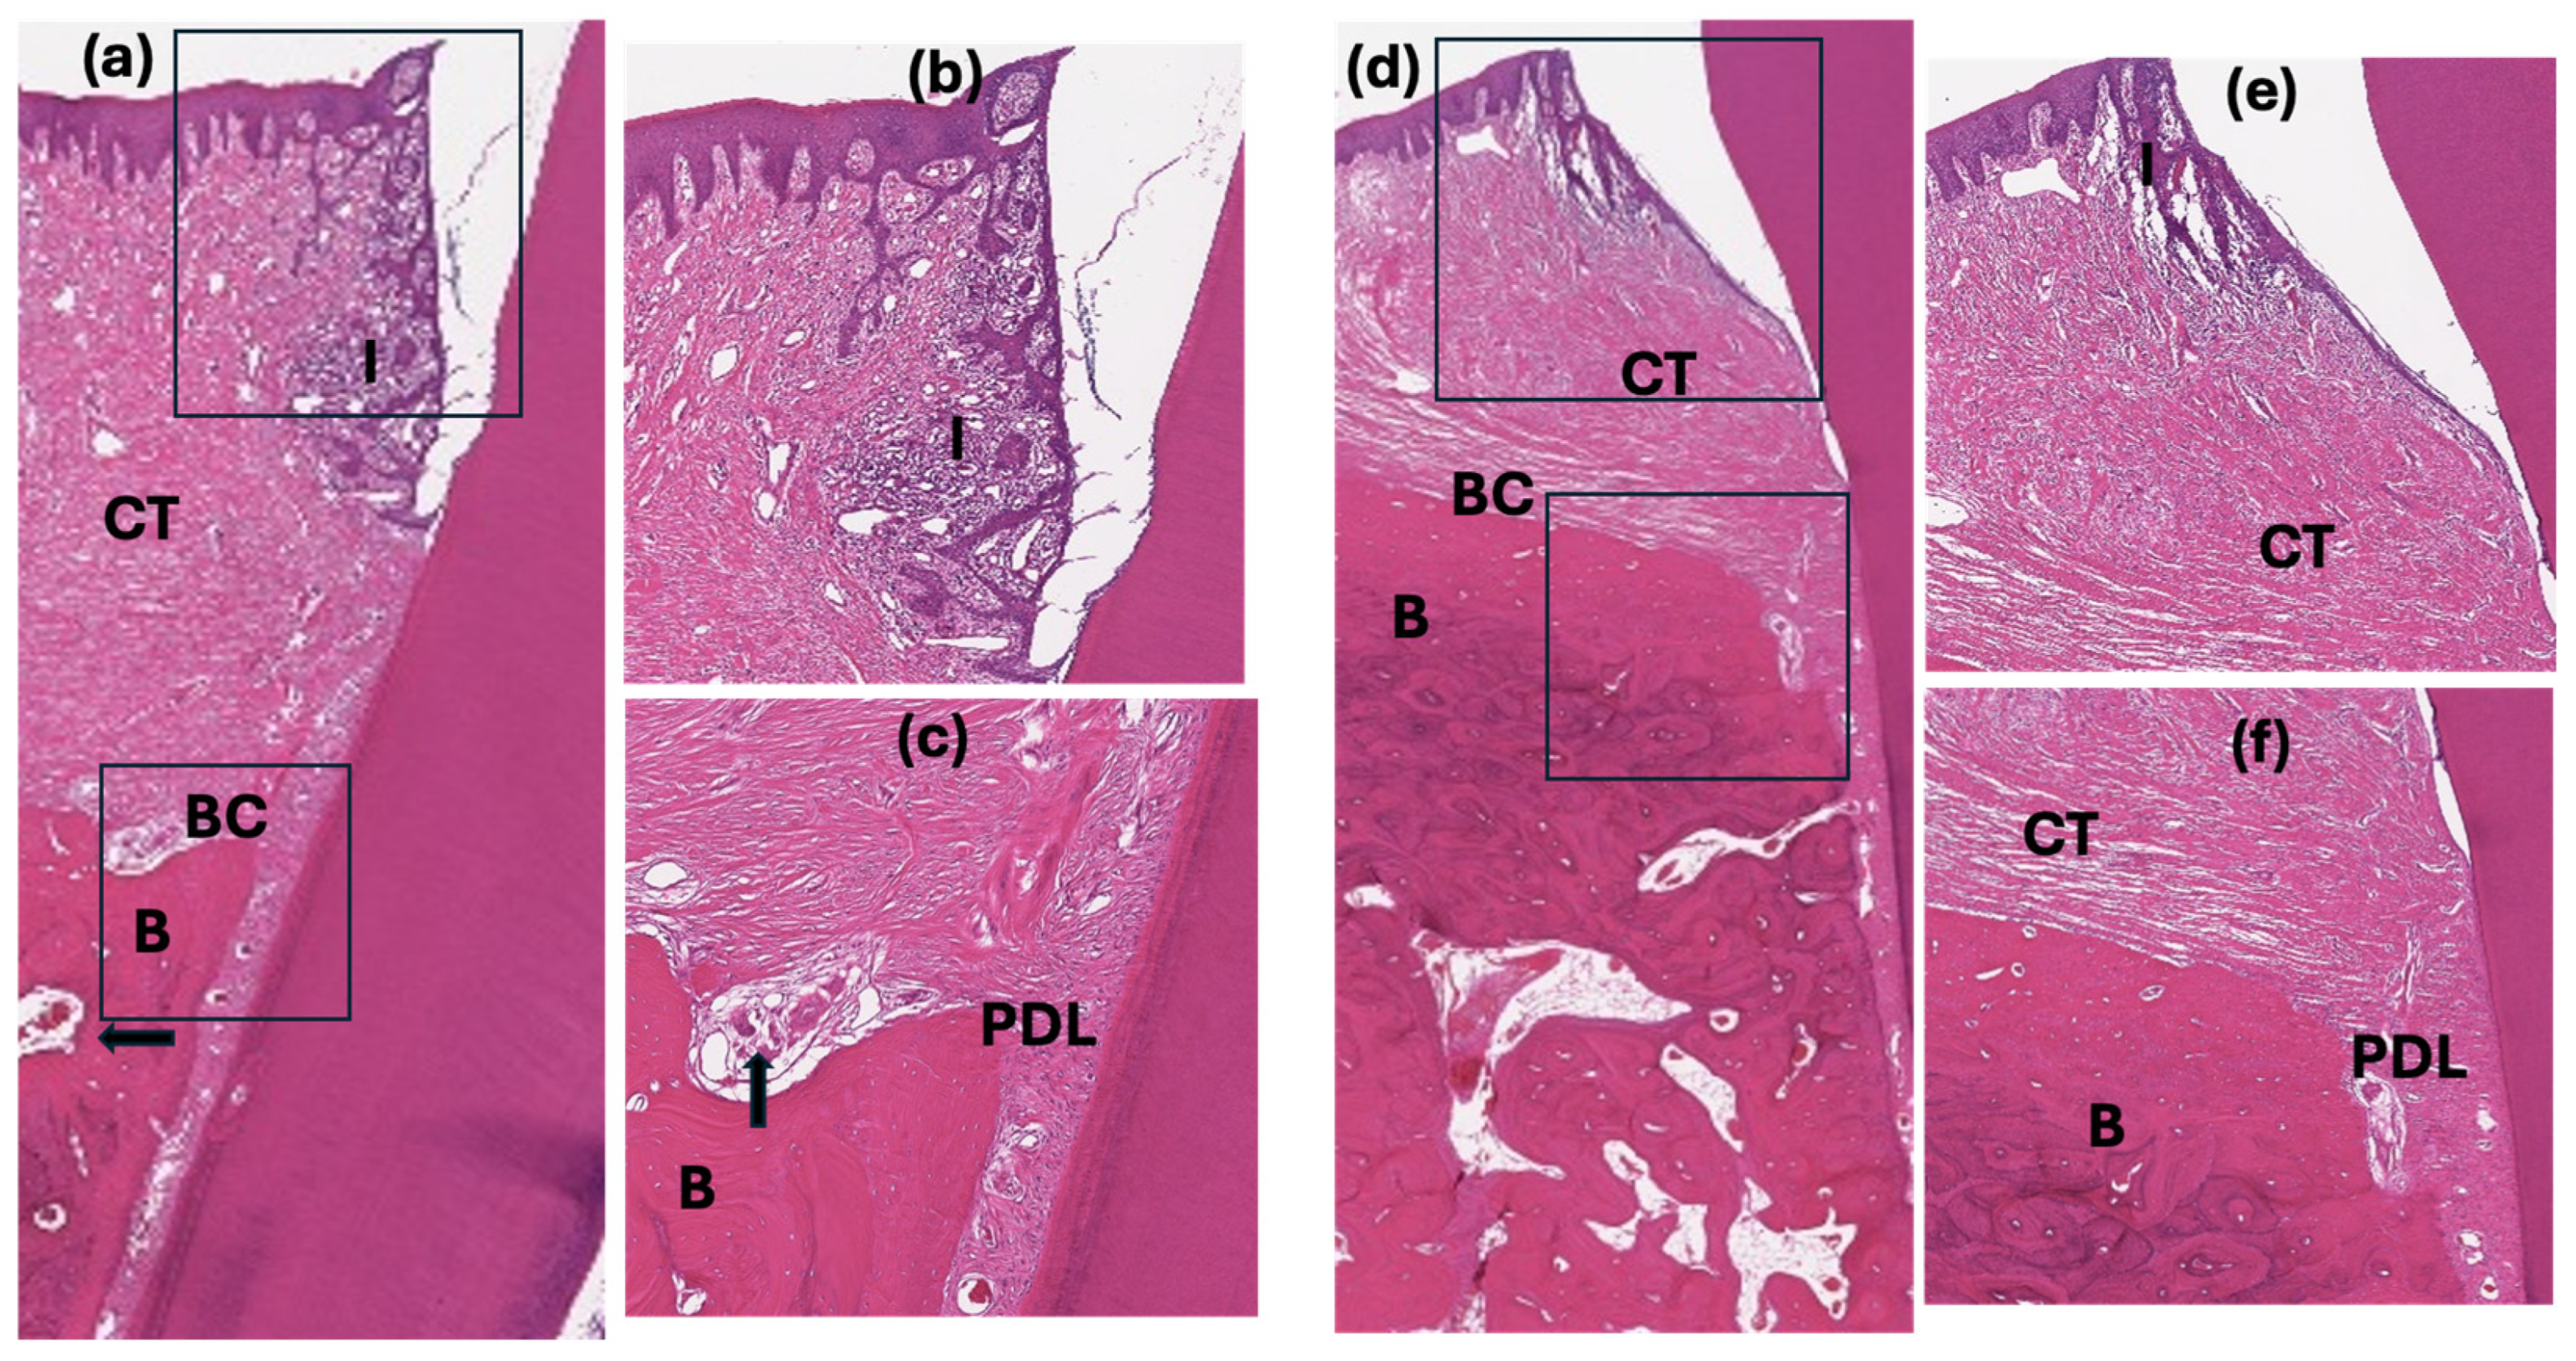
Qualitative histologic examination was utilized to determine the degree of inflammation and other morphologic changes to the periodontal tissues between those teeth where PD was induced (Figure 2). Tissues from control animals exhibited a thickened gingival epithelium (hyperplasia) with a moderate degree of inflammation, composed primarily of lymphocytes and neutrophils, in the surrounding regions. The connective tissue beneath the gingival layer was composed of disorganized collagen fibers containing fibroblastic cells with a high density of blood vessels. Numerous osteoclasts, indicative of active bone resorption, were noted in the alveolar bone of control animals. In contrast, treated animals exhibited greater organization in the collagen matrix with a notable decrease in the number of blood vessels as compared to control animals. Some areas of low-grade inflammation were present in the junctional epithelium. Few osteoclasts were noted in the alveolar bone of treated animals.
Figure 2.
Histopathology of H&E-stained canine periodontal tissue located between teeth 408 and 409 for control animal 834 (a–c) and Ambrilux-treated animal 892 (d–f). Outlined insets of (a,d) are shown at higher magnification views in (b,c) and (e,f), respectively. (a) Representative low magnification view of periodontium from control animal showing inflammation (I) in the gingiva and surrounding connective tissue (CT). Numerous osteoclasts may be noted in the alveolar bone (arrows). Higher magnification view (b) of the gingiva also shows an increase in tissue vascularity (c) Osteoclast nests (arrow) are indicative of active bone resorption. (d) Ambrilux-treated animal exhibited a greater degree of organization within the connective tissue with decreased blood vessels and reduced inflammation, (e) As highlighted in higher magnification view. (f) Osteoclast activity was also reduced. I, inflammation; CT, connective tissue; R, tooth root; AB, alveolar bone; BC, bone crest; PDL, periodontal ligament. Micrographs were obtained at magnifications of ×6 (a,d) and ×20 (b,c,e,f).
2.4.2. Tooth Furcations
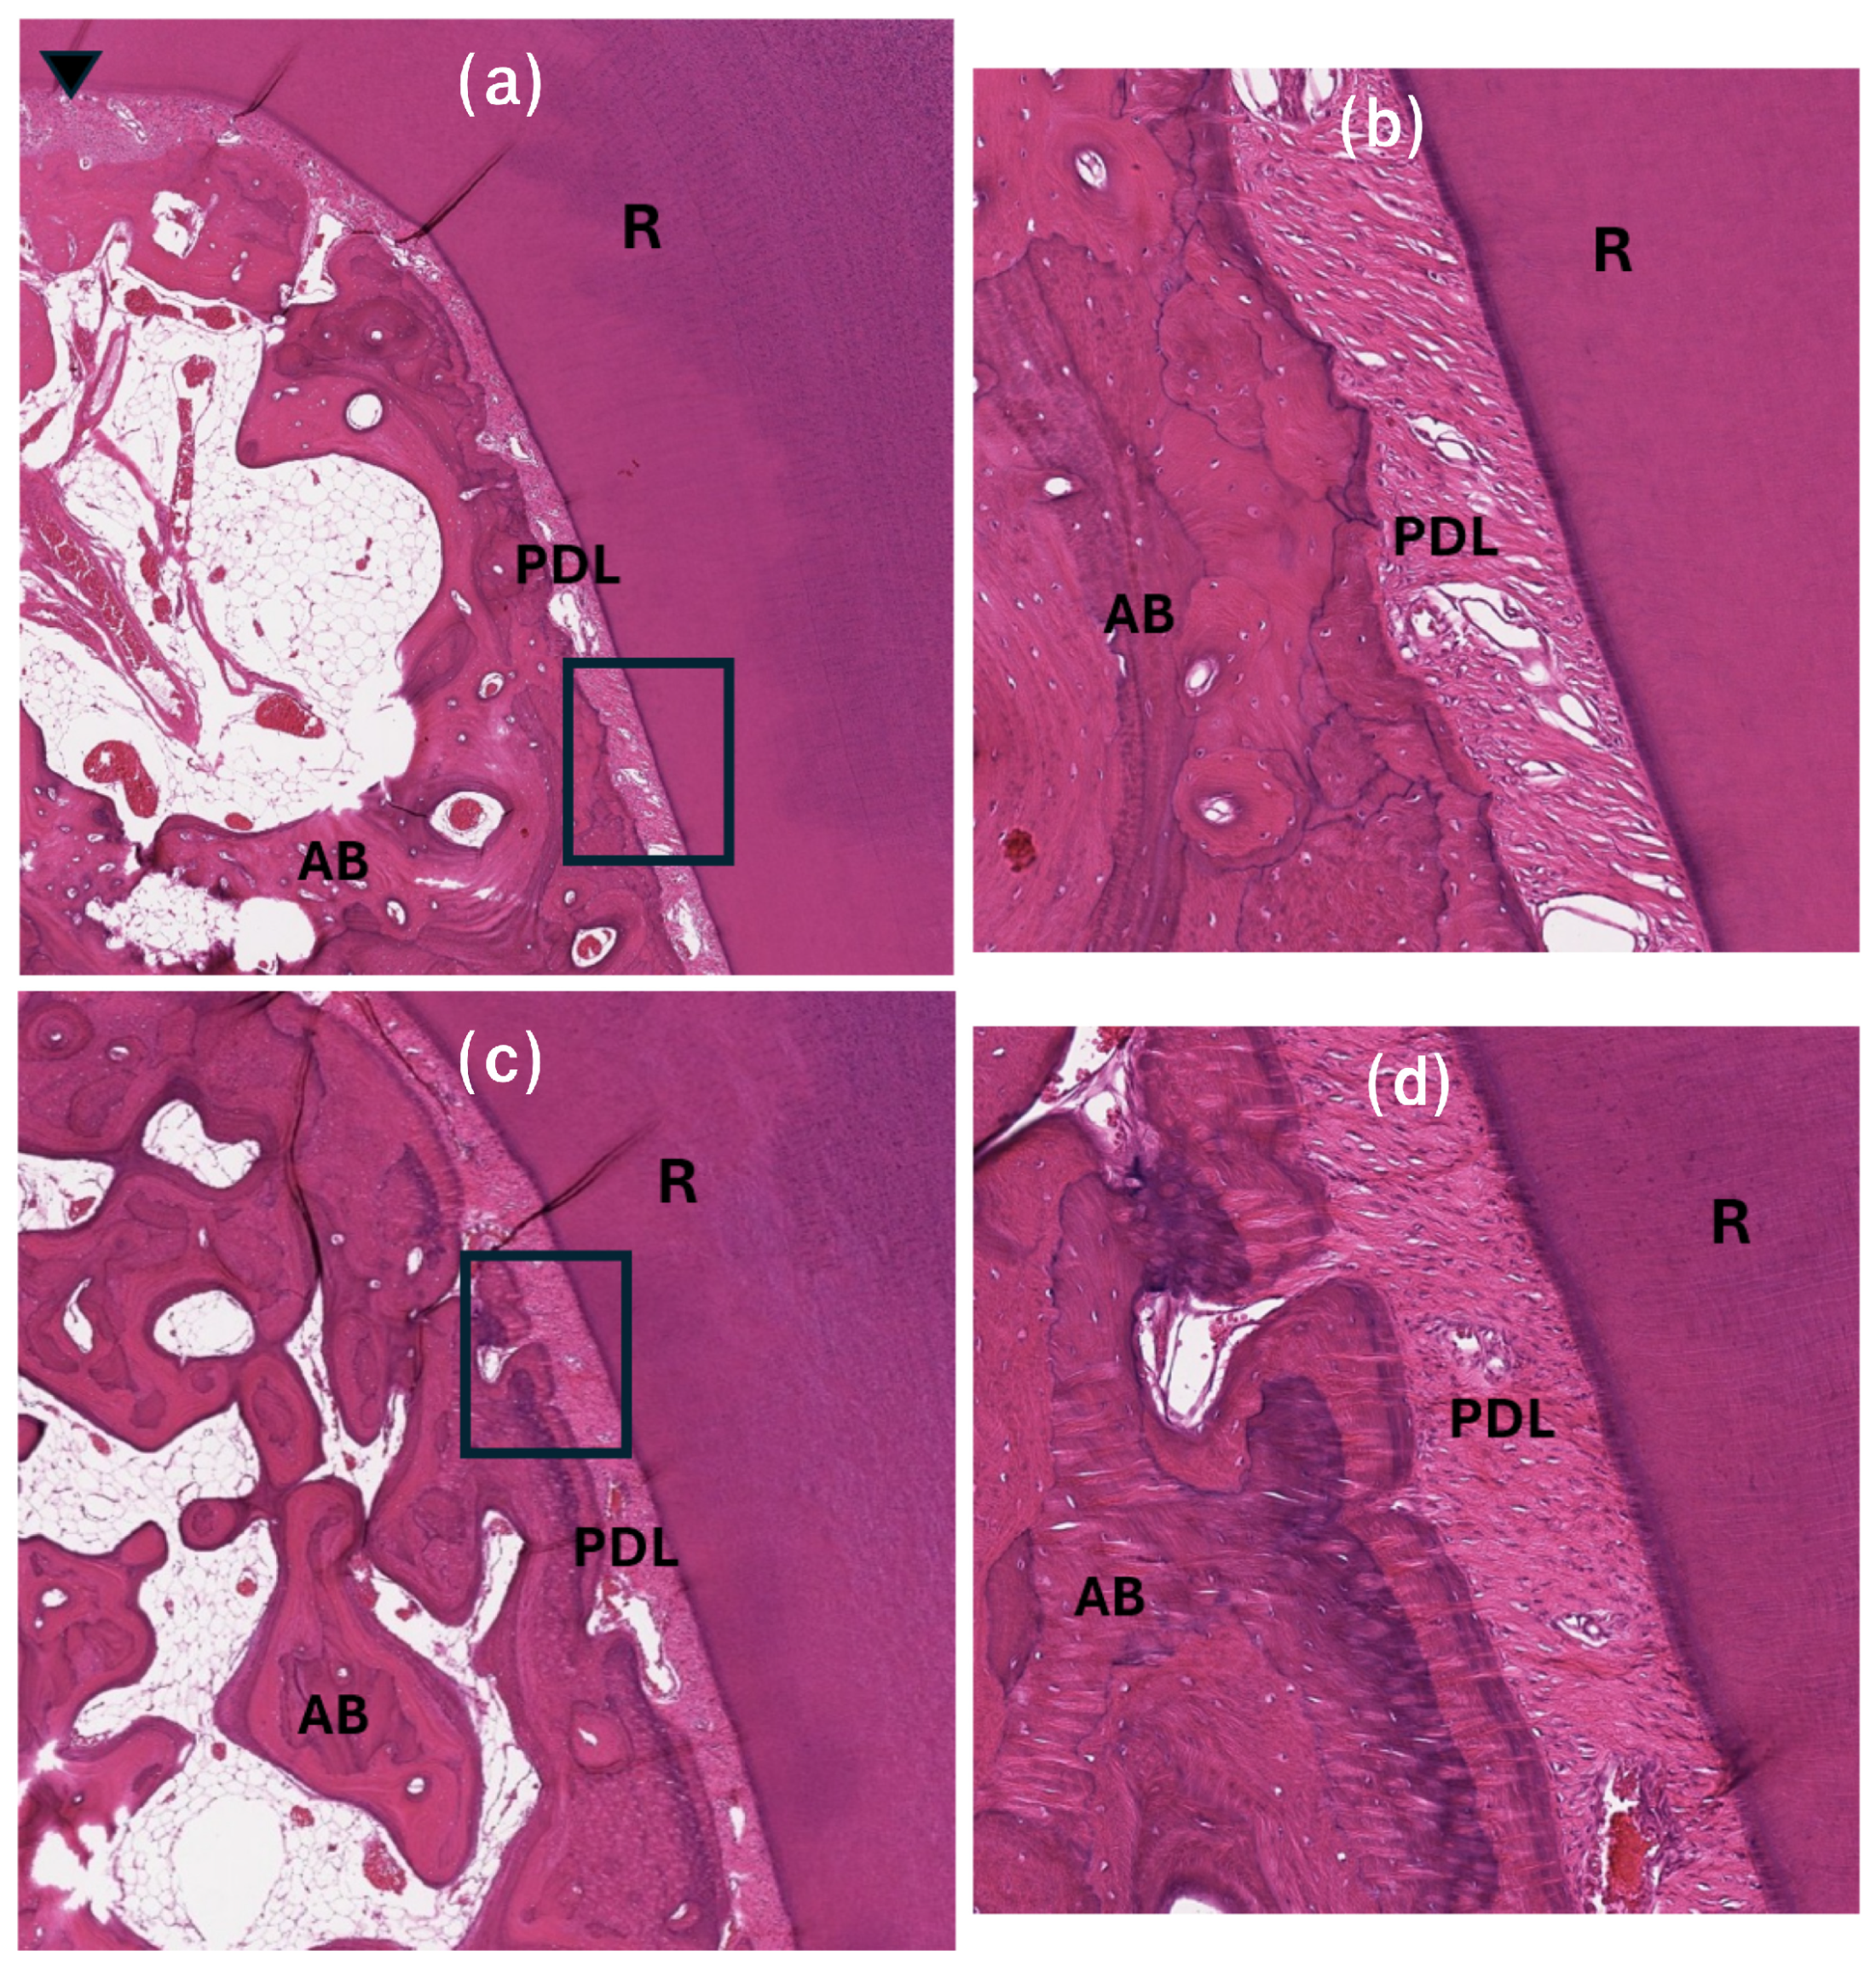
Histologic analysis of the furcation from tooth 409 was conducted to both determine the morphologic alterations to the periodontal ligament (PDL) and correlate the changes noted in CT to alterations in histopathology (Figure 3). The PDL in control animals exhibited loss of ligament structure, as characterized by the presence of disordered, ligament-like tissue composed primarily of loosely organized collagen fibers and fibroblasts with increased extracellular spacing. The internal zone of the PDL was found to contain numerous blood vessels of variable sizes and diminished vascular integrity, resulting in notable micro-hemorrhaging. Bone within the furcation of control animals may be characterized by the presence of multi-nucleated osteoclasts with an associated increase in bone resorption. Two out of three control animals exhibited replacement of bone in the fornix region with increased fibroblasts and granulation tissue and a limited number of inflammatory cells (Figure 3a).
Figure 3.
H&E-stained histology images highlighting the furcation periodontal ligament from (a) a control animal 323 and (c) Ambrilux-treated animal 892 (both tooth 409). Outlined insets of (a), (c) are shown at higher magnification view in (b) and (d), respectively. Severe degradation of the PDL was noted in control animals as compared to treated animals. Micrographs were obtained at magnifications of x6 (a,c) and ×20 (c,d).
In contrast to control subjects, Ambrilux-treated animals exhibited well-organized periodontal ligaments (PDLs) characterized by fibrous connective tissue and densely packed fibroblasts. Moderate-sized blood vessels were present within the ground substance, and PDL fiber bundles extended directly into the alveolar bone. Qualitative evaluation of the furcation areas revealed newly formed alveolar bone lined with osteoblasts, alongside mature lamellar bone. Inflammatory cell infiltration was minimal.
2.5. Micro-CT Analysis
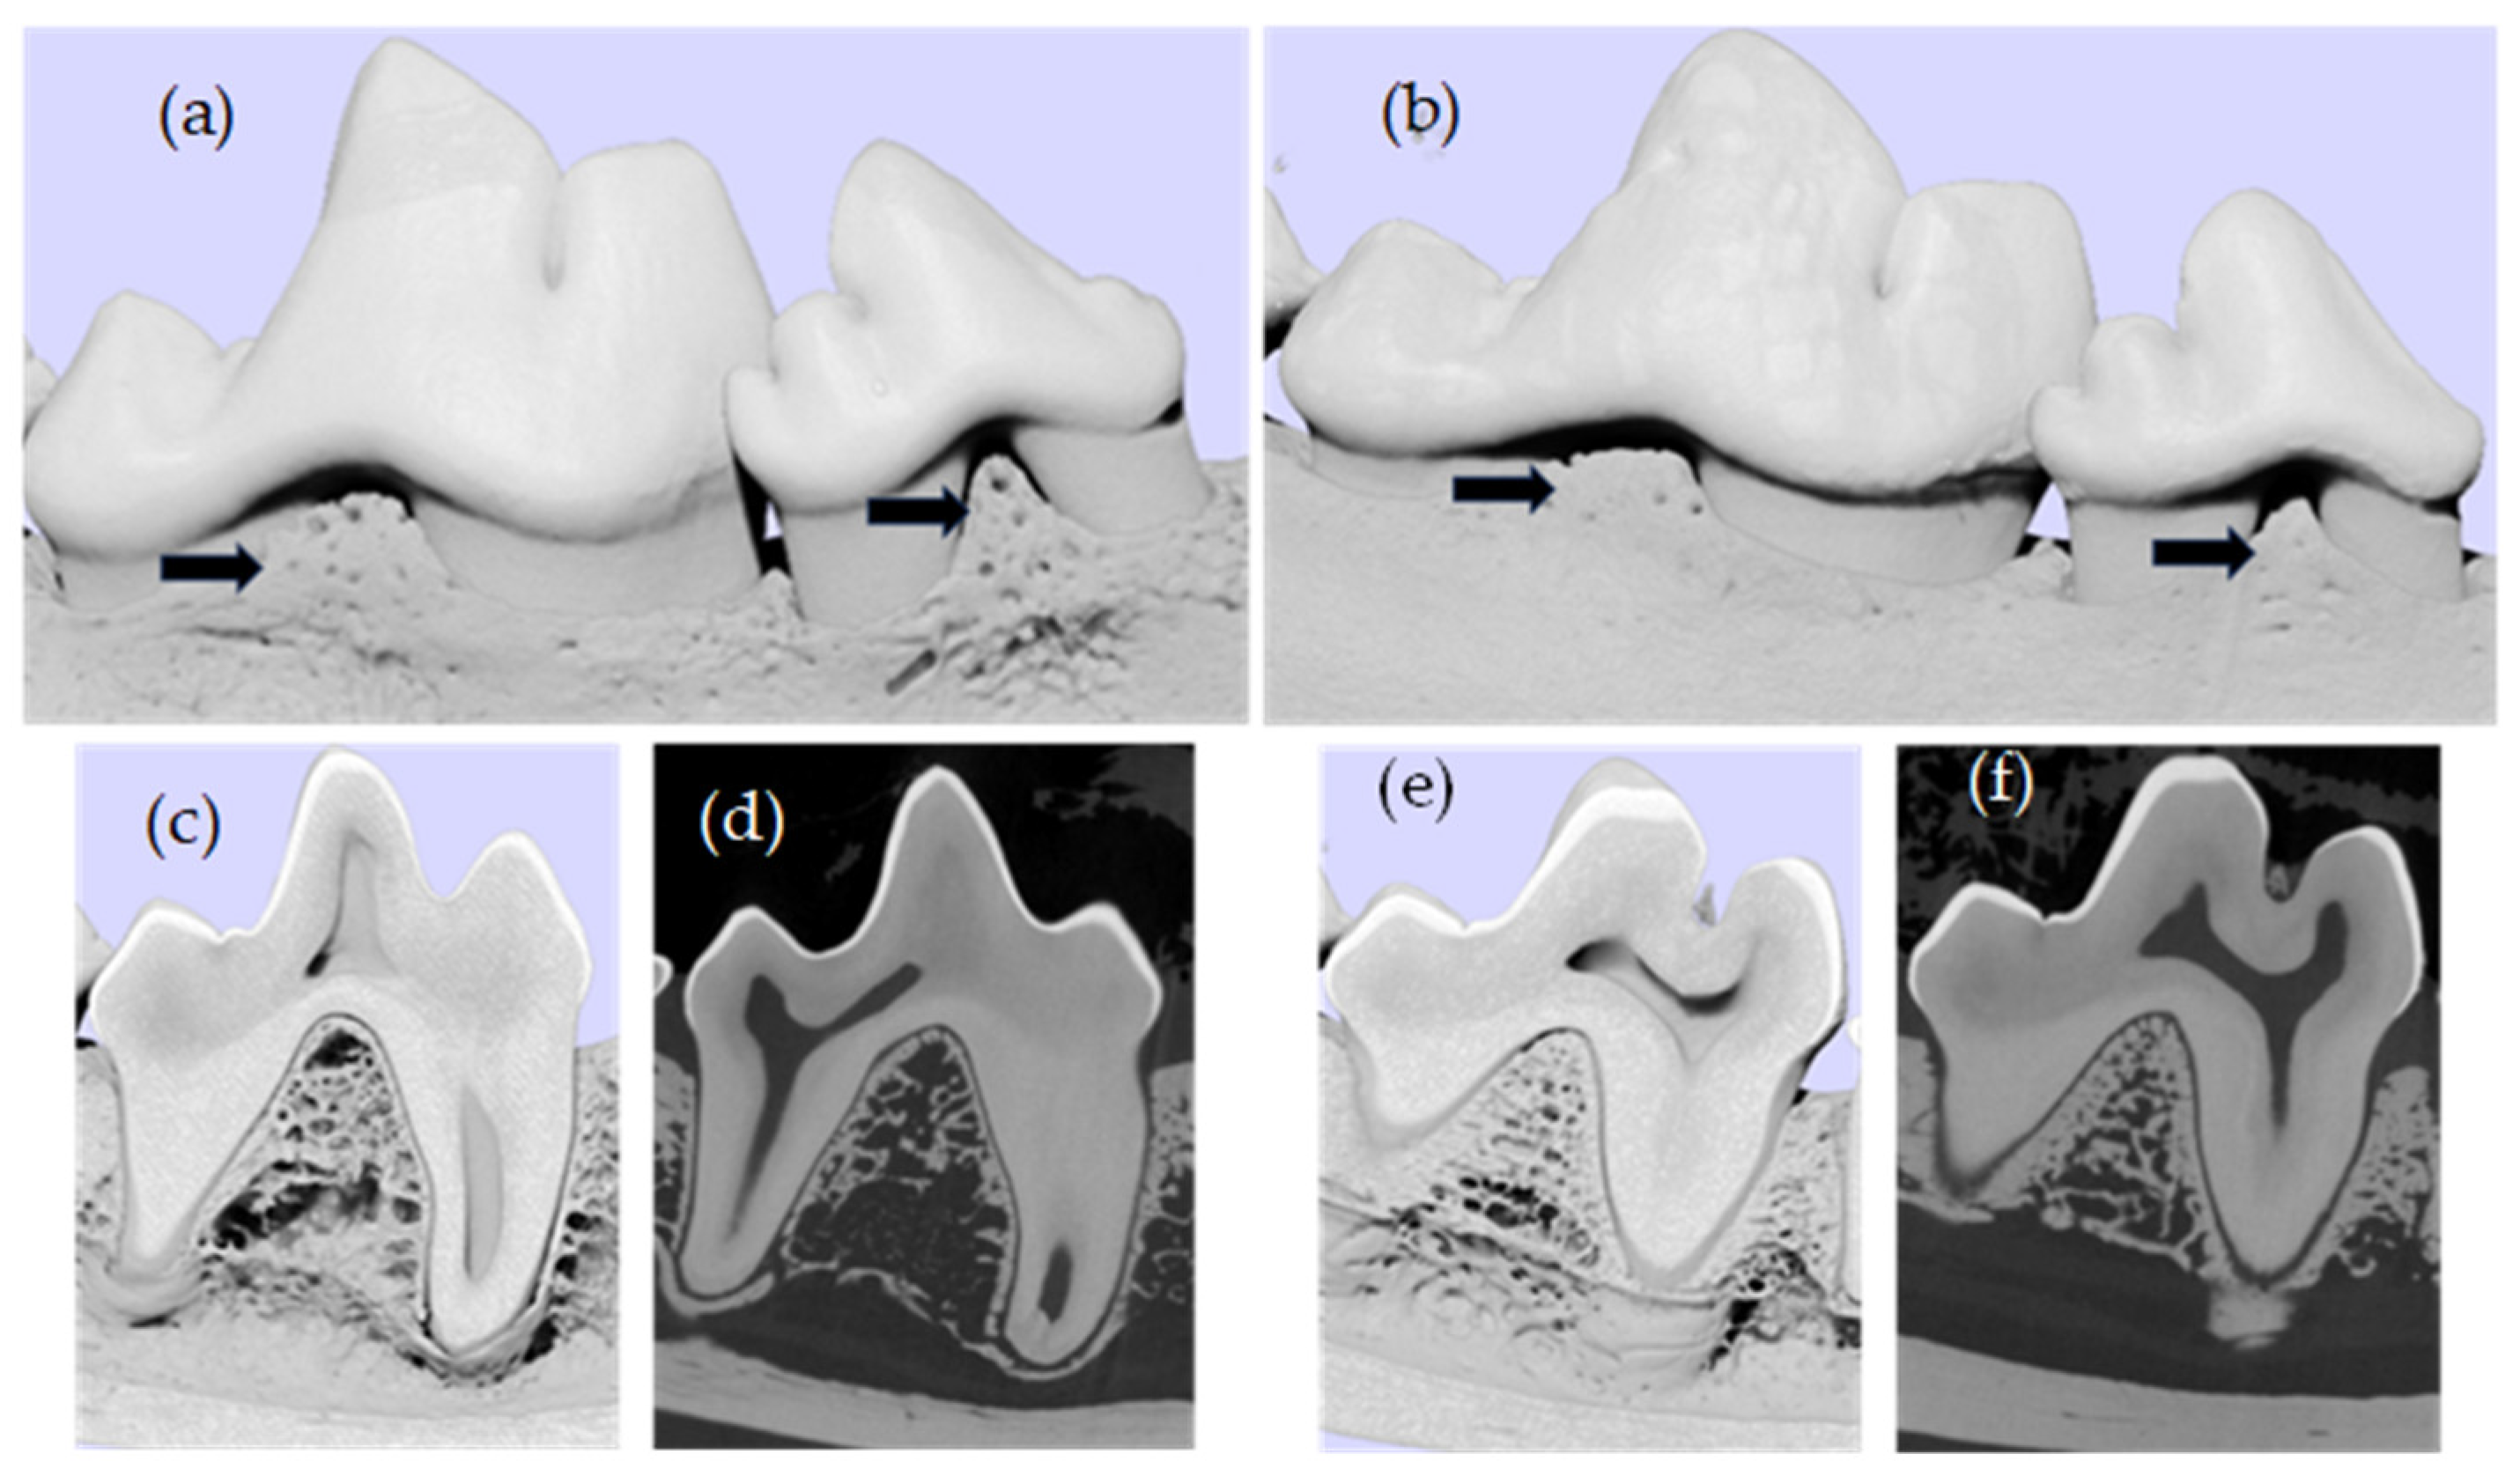
To further evaluate the ability of the study treatment to promote bone regeneration, micro-CT imaging was utilized to generate sagittal and 3D reconstructed (frontal and sagittal) images in animals in both the control and treatment groups (Figure 4). Analysis of frontal 3D reconstructions in animals of the treatment group had a smooth, less mottled appearance to the bone surface. The 2D and 3D sagittal views of the samples from the treated animal showed more profound bone density within the tooth furcation with thicker bone walls. In contrast, the control sites revealed an uneven bone surface topography in the furcation and proximal areas, indicative of active PD and subsequent bone loss. Sagittal section views (2D and 3D reconstructions) of the furcation showed a loss of bone density with wide alveolar spacing.
Figure 4.
Representative 3D and sagittal images of control (a,c,d) and Ambrilux-treated (b,e,f) animals (animals 323 and 913, respectively). The degree of bone loss (black arrows) in the external 3D view (a,b) is more pronounced in control samples as compared to treated samples. Internal 3D (c,e) and sagittal (d,f) images exemplify the increased bone formation in the furcation areas of treated animals.
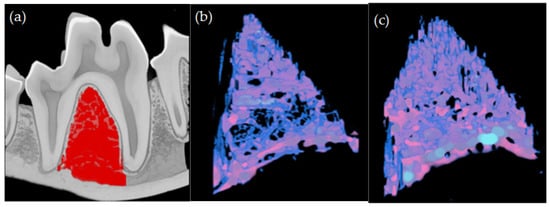
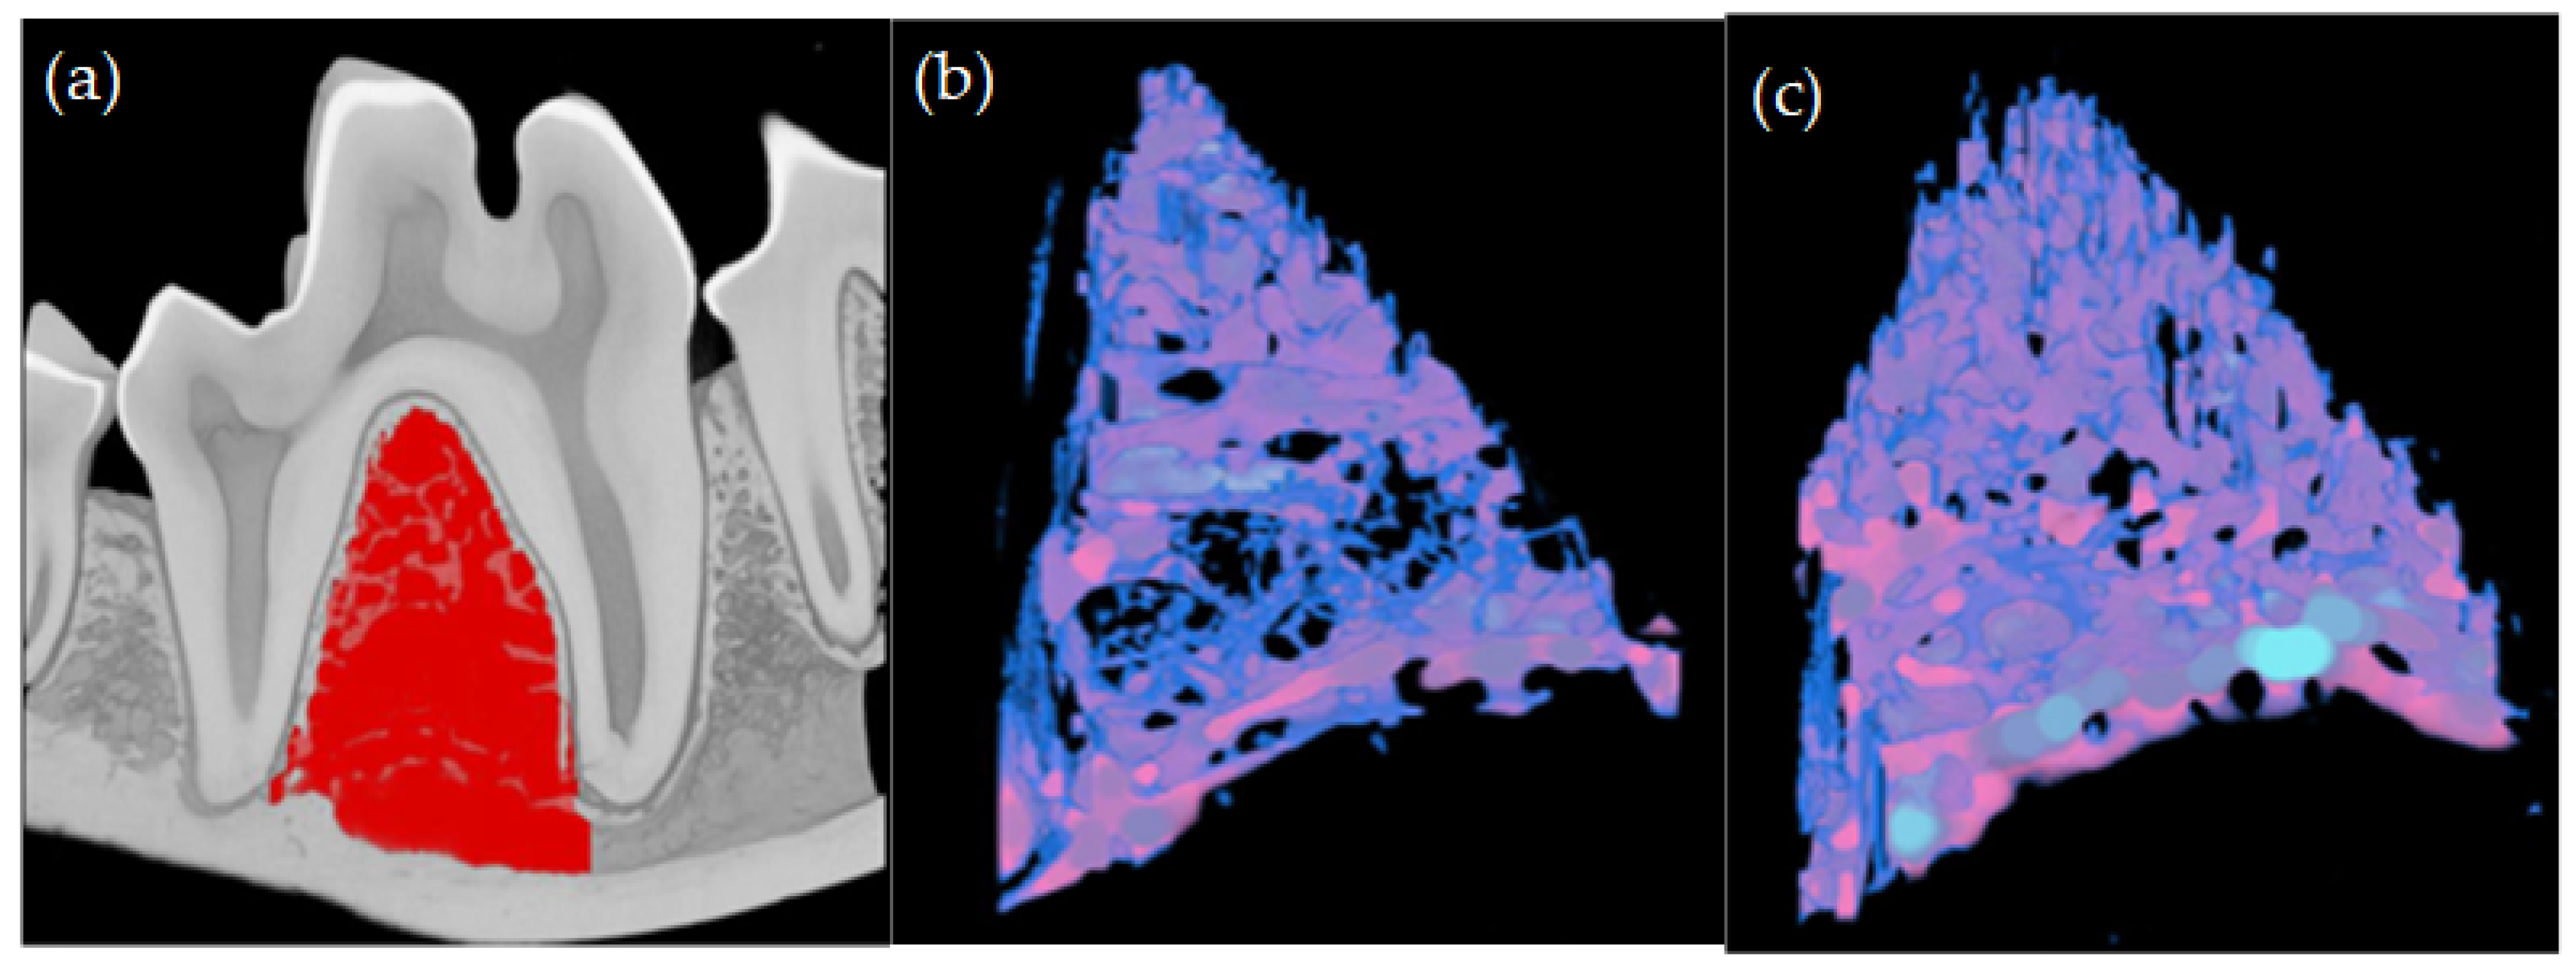
Quantitative analysis was also completed on the harvested jaw specimens, with the highlighted volume of interest (VOI) (Figure 5a) quantified for thickness, volume, and local bone mineral density (BMD). Representative heatmap images representing the registered VOI for a control animal and a treated animal are presented in Figure 5b and Figure 5c, respectively. Mean values for quantitative CT at furcation are shown in Table 1. Mean bone volume (BV) was markedly higher in the treatment group as compared to the control, with a similar difference observed for the BV/TV and bone mineral density (BMD). Trabecular measurements were consistent, with a greater degree of repair in treated animals as opposed to control animals. While trabecular thickness was similar between the groups, the treated animals had a notable increase in the number of trabeculae and a corresponding decrease in trabecular separation. Increased bone density was visually noted in treated animals at proximal areas as well, although quantitative analysis was not feasible due to inherent structural differences across animals. Because the small sample size compromises hypothesis testing reliability, p-values were excluded to avoid potential data misinterpretation.
Figure 5.
Volumetric analysis of the furcation of tooth 409. (a) Furcation area of tooth 409 representing the registered VOI for analysis. Bone within red highlighted volume of interest was quantified for thickness, volume, and local bone mineral density. (b) Representative image of furcation from a control animal (588). (c) Representative image of furcation from a treated animal (542).
Table 1.
Quantitative CT assessment of bone density, volume and trabecular parameters at furcation.
2.6. Discussion
The results of the current proof-of-concept study provide preliminary evidence that the tested piezoelectric-based hydrogel (Ambrilux, Oral Biolife, Bethlehem, PA, USA) is safe and has the potential to positively modulate periodontal wound healing and promote bone regrowth in a canine model of ligature-induced PD. These conclusions are based on quantitative and observational results. Quantitative CT was utilized to gauge bone regeneration and was conducted on the furcation areas of tooth 409. This tooth was chosen as the largest molar and therefore the most prominent tooth in the lower jaw, while teeth 407 and 408 are premolars. In dogs, tooth 409 is responsible for the highest bite pressures, and as such, subject to more severe wear and subsequent naturally occurring periodontal disease [20,21]. Analysis using quantitative CT showed that furcation bone volume was 37% higher in treated animals than in control animals, bone mineral density was over 18% higher, and the ratio of bone volume to tissue volume was 21% higher in treated animals. These data suggest that treatment with Ambrilux has the potential to regenerate bone in the furcation area. Temporal radiographic evidence showed that all treated animals demonstrated increasing radiopacity at the furcation area. In contrast, control animals demonstrated stable or worsening levels of disease. It was noted that 3/3 treated animals demonstrated bone regeneration over time, while in the control group, 2/3 animals showed continued bone loss, with one animal exhibiting no change. However, because of the low number of subjects, as well as the moderate degree of induced disease, we cannot definitively state that the injury was of critical size, and therefore cannot exclude the possibility of spontaneous/natural healing in either group. Histological findings support a lower degree of inflammation in treated animals, and potential modulation of the periodontal ligament tissues. It should be noted that while the histological data offers valuable insight into Ambrilux-induced cellular changes, the limited sample size precludes any definitive conclusions. Periodontal evaluations were performed throughout the study, but review of the data did not highlight appreciable differences, likely due to the small sample size, inherent variability of the measurements and/or moderate severity of the disease. Additional ad hoc analyses are needed to investigate trends in these evaluations and identify potential areas of improvement for future studies.
Furcation involvement in periodontal disease is a key pathologic and diagnostic feature, since bone loss in the furcation is an important predictive indicator of disease severity and clinical outcome (i.e., tooth loss) [22]. Bone loss at the furcation is apparent on radiographs as indicated by a decrease in radiopacity, which signifies that severe periodontal disease is present and will require significant and complex treatment [7,8,23] to save the affected tooth. Bone regeneration in the furcation area is a clinical challenge; thus, bone loss at the furcation was an important efficacy endpoint in this study. Various regenerative therapies have been investigated to address furcation defects, including bone grafts, guided tissue regeneration (GTR), application of growth factors and enamel matrix derivatives, and bone morphogenetic proteins, with variable clinical outcomes reported [7,8,10,23]. A consensus report from the AAP Regeneration Workshop reported that histological evidence of periodontal regeneration has been demonstrated in several studies for maxillary facial, mesial, distal, and mandibular facial or lingual Class II furcation defects [9]. However, evidence for periodontal regeneration for Class III defects (with through-and-through lesions) is limited to only case reports. The panel recommended that future research should focus emerging regenerative therapies that have the potential to enhance outcomes [9], including approaches like the current study treatment with piezoelectric properties that can promote bone regeneration and serve as a physical scaffold. The structural and physical properties of Ambrilux are conducive to meeting these goals. The piezoelectric component, as described in more detail below, serves to provide the stimulus to initiate stem cell differentiation and promote cell recruitment, while the GelMA hydrogel serves to provide a suitable scaffold for cell migration and maturation. Key to Ambrilux’s capacity to promote bone regeneration is its ability to gain full access to small anatomical regions such as difficult-to-access areas of the periodontal pocket and the tooth furcation. Comprehensive rheological and injectability analysis were utilized to determine the viscosity of Ambrilux. It was determined that, in the uncured form and at body temperature, the viscosity of Ambrilux is low, allowing it to access difficult-to-reach areas [18]. The ability to act as viscoelastic material means that Ambrilux behaves like an elastic solid (stretching and returning to shape) and a liquid [24]. These physical properties are complemented by the uniform dispersion of BTO nanoparticles within the fluid matrix, thereby avoiding the formation of aggregates.
The mechanotransduction framework that translates physical forces into cellular responses is essential for both the normal turnover and repair of numerous tissues. These endogenous piezoelectric fields are found in bone, cartilage and collagen fibers, and thus generate an electric charge when subject to mechanical forces. The piezoelectric properties of these tissues are thought to play an important role in mediating natural remodeling of the tissue and assisting in the repair of injury [25,26]. At the cellular level, the mechanism(s) by which the piezoelectric properties of bone facilitate bone repair have focused on how mechanical stimuli is converted to bioelectrical signals that impact target cells, primarily osteoprogenitors cells and osteocytes. In this regard, the release of negative charges by the piezomaterials in bone, and their subsequent interaction with voltage-gated calcium channels, specifically Piezo1 channels, appear to be the primary mechanism for initiation of bone formation/repair [16]. Piezo1 channels, which are found on several cell types, including stem cells and osteocytes, function as important mechanosensors in bone and serve to regulate bone formation, remodeling, and repair by modulating gene expression [27,28,29]. Under dynamic physical forces, such as mastication, the membrane bound Piezo1 channels undergo conformational changes that trigger a rapid influx of intracellular calcium (Ca2+). The influx of Ca2+ acts as a primary second messenger, shifting the intracellular microenvironment to activate downstream osteogenic pathways. Specifically, this influx upregulates key osteogenic transcription factors, such as Runt-related transcription factor 2 (RUNX2), which is essential for osteoblast commitment, alongside crucial matrix-associated genes, including Collagen Type I Alpha 1 Chain (COL1A1) and alkaline phosphatase (ALP) [30]. This cascade effectively drives the differentiation of target stem cells toward an osteogenic phenotype, accelerating extracellular matrix maturation and apatite nucleation [31,32].
Because native tissues such as bone generate electrical charges under mechanical load, interest has grown in “smart” piezoelectric biomaterials that convert physiological deformations (e.g., pressure fluctuations) into localized surface charges [33]. The development of these multifunctional biomaterials has shifted from usage as static, space-filling matrices to mechanically responsive hydrogels and piezoelectric regenerative scaffolds capable of translating physiological microenvironments into definitive regenerative cues [34,35,36,37]. Yang et al. utilized a fiber-reinforced, dual-network hydrogel system (OHADN fiber@Yoda1) to promote activation of PIEZO1 channels, resulting in increased bone volume in a rat alveolar bone defect model [34]. Furthermore, piezoelectric poly (L-lactic acid) (PLLA) embedded in a hydrogel matrix combined with a lubricating layer has been shown to promote osteochondral regeneration in vivo [36], and a motion-responsive, injectable, lubricative hydrogel with piezoelectric properties (PE-IAH) was shown to prevent post-surgical adhesions while accelerating tendon regeneration [37]. It should be noted that smart piezoelectric materials are not limited to complex hydrogel systems. For example, a matrix composed of modified decellularized tilapia skin, which is a fish by-product rich in type I collagen, generates significant piezoelectric output, making it a promising biomedical scaffold for soft tissue regeneration [38]. These exemplars, combined with other, similar studies, demonstrate that biophysical cues actively drive the commitment and osteogenic differentiation of target progenitor cells toward a mature bone-forming phenotype [39,40,41]. Incorporating such multifunctional platforms into periodontal treatment, such as that described in the present study, adds additional evidence as to how mechanical/electrical signaling pathways can accelerate functional tissue regeneration.
While our in vivo findings demonstrate the regenerative efficacy of Ambrilux, the precise underlying cellular/molecular mechanisms that mediate this effect remain to be fully elucidated. In vitro studies show that mechanically responsive biomaterials and piezoelectric scaffolds stimulate osteogenesis by activating mechanosensitive ion channels, most notably the Piezo1 calcium channel [16,42,43]. Because the current work did not include in vitro assays or molecular analyses, we cannot definitively conclude that Piezo1 activation mediated the outcomes noted in the present study. The observed tissue-level regeneration may drive from a combination of the scaffold’s structural support, physical regulation, and hypothesized downstream mechanotransduction pathways. Confirming the precise role of Piezo1-mediated signaling within this specific canine model requires future mechanistic studies. While the present study focused on determining the efficacy of Ambrilux in the setting of PD, previous in vitro and murine studies have sought to elucidate the cellular/intracellular mechanisms involved in promoting osteogenesis. Roldan et al. utilized an in vitro assay system to analyze changes in the expression of key genes involved in osteogenic differentiation [18]. These studies demonstrated that mechanostimulation of Ambrilux upregulates RUNX2, COL1A1, and ALP [18,42]. Activation of these genes suggests that the mechanostimulation and the subsequent release of physiologic microcurrents by this piezoelectric hydrogel may trigger the differentiation of target stems cells to an osteogenic phenotype. It should be noted that the aforementioned studies were conducted both in vitro and in a murine model of PD and therefore do not present definitive proof that these molecular interactions play a role in the present study. As such, further cellular/molecular-level investigations are required to definitively map and verify the mechanism of action within this specific canine model.
3. Conclusions
The canine ligature model is widely considered to be the “gold standard” of PD in in vivo modeling and was therefore chosen for the study based on the model’s high degree of translatability to the human disease. Anatomically, dogs and humans are similar in that dogs possess comparable tooth shapes, enamel–cementum junctions, and multirooted posterior teeth [44]. Similarities in the pathophysiology of disease also factored into selection of the canine ligature model. Specifically, the disease, in both settings, is driven by formation of bacterial biofilms (plaque) and subsequent amplification of the immune/inflammatory response, resulting in profound bone loss [45,46]. The translatability of the ligature model provides a meaningful degree of confidence that these data will translate to the human setting. While this exploratory study was not powered for definitive statistical analysis—thereby limiting absolute conclusions—it provides a valuable, semi-quantitative overview of bone regeneration in the challenging furcation environment that is similar in humans. These data establish foundational effect sizes to guide future, adequately powered confirmatory studies while adhering to ethical principles of animal reduction. To expand on these findings, future research will utilize fully powered, adequately controlled study designs to rigorously define the regenerative potential of Ambrilux within both bone and the periodontal ligament.
It should be reiterated that this is a proof-of-principle study, and while the initial results are promising, they must be interpreted with caution and considered as preliminary. The small sample size is clearly detrimental to the ability to conduct meaningful statistical analysis when examining the key parameters of bone growth. In addition, it is hypothesized that the low number of subjects contributed to the lack of notable differences in clinical periodontal parameters between the groups. This issue, coupled with inherent observer variability when obtaining these readouts, negatively impacted the interpretation of the clinical parameters. Lastly, the role that spontaneous bone healing plays in the data has yet to be determined. This not only represents a translational gap, as dogs have a greater osteogenic response than humans, but may also lead to overestimation of efficacy. Future large-scale randomized controlled trials using multiple treatment paradigms are planned to overcome these issues and provide a definitive degree of efficacy. Periodontal regenerative materials provide different forms of support for tissue healing. As mentioned previously, injectable hydrogels can conform to penetrate irregularly shaped tissues and serve as carriers for local delivery of bioactive agents, including growth factors [15]. In contrast, bioactive ceramics (i.e., hydroxyapatite, b-tricalcium phosphate) function to provide an osteoconductive framework, while polymeric scaffolds seek to provide distinct regions for bone and periodontal ligament formation [47,48]. Guided tissue regeneration membranes also act in a physical fashion by protecting the defect from soft tissue growth. Ambrilux combines an injectable GelMA scaffold with a piezoelectric material (BTO) that acts to form a device that provides both a degradable scaffold as well as non-pharmacologic mechanism to enhance bone growth [18]. Further differentiation between Ambrilux and other treatment options is that delivery of the treatment is non-surgical and rapid (approximately 2 min) administration. Despite sample size constraints, the robust bone growth observed in the treated furcation areas marks an advancement in treating these complex anatomical defects. Ultimately, these results provide critical baseline insights into both the safety and overall efficacy of piezoelectric hydrogels. This technology shows strong promise as a novel regenerative therapy to reverse bone loss in periodontal disease, particularly within challenging furcation defects.
4. Materials and Methods
4.1. Study Design
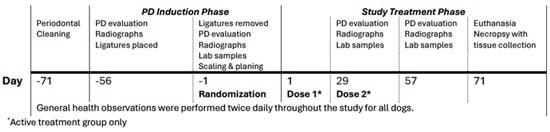
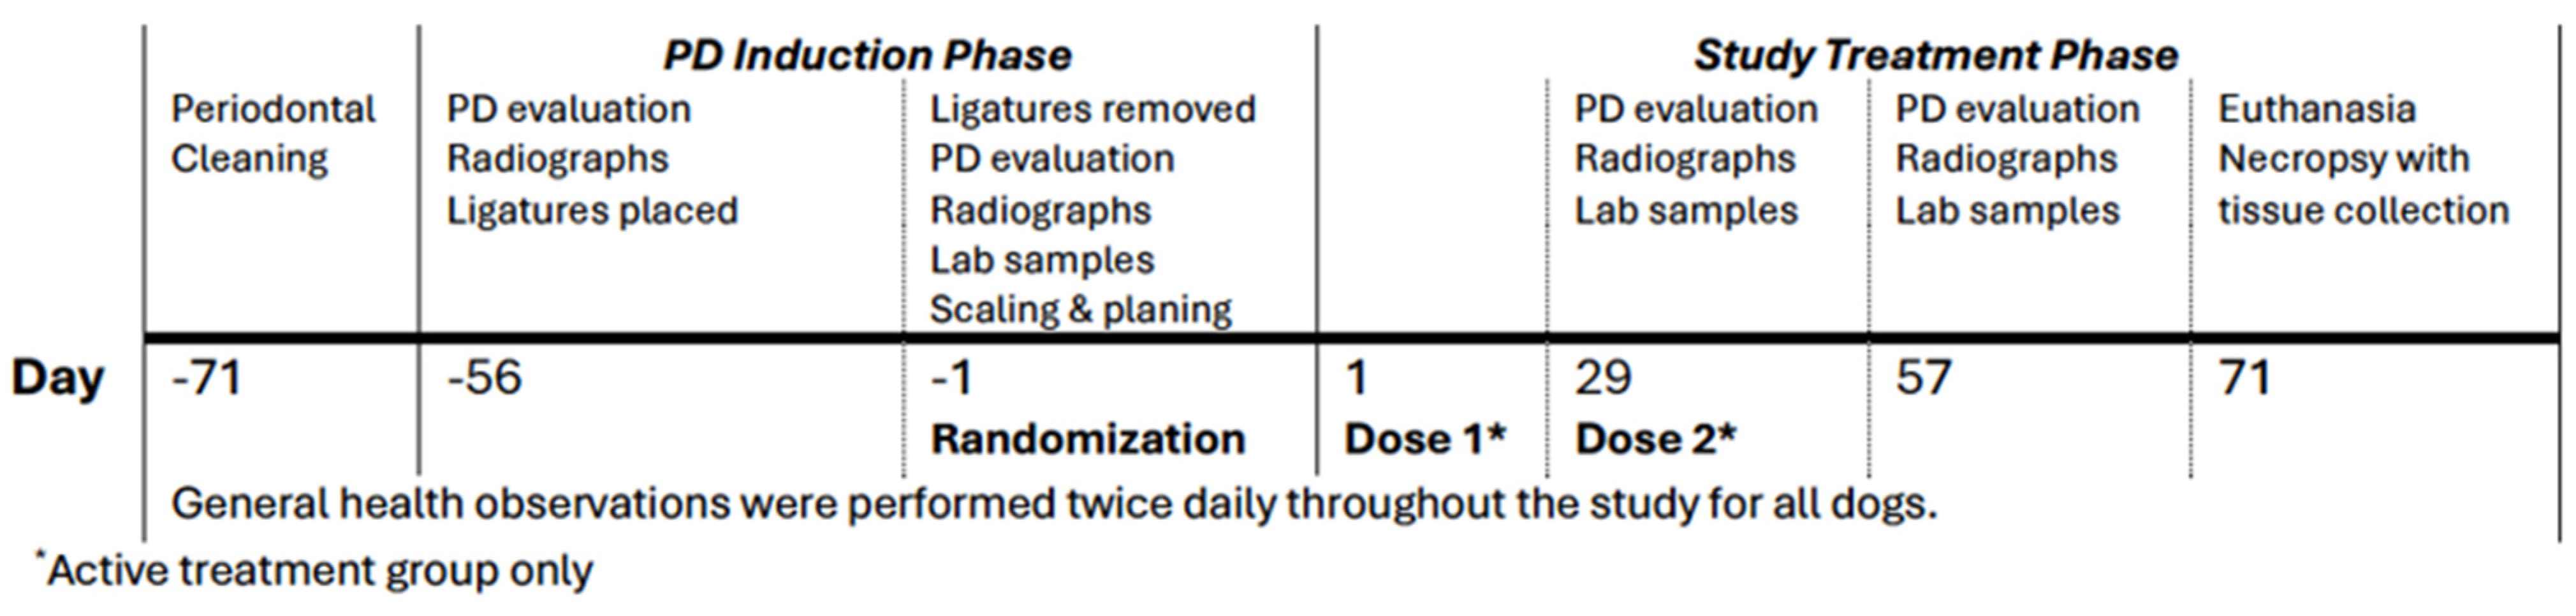
This preclinical study was conducted to examine the impact of a piezoelectric-based hydrogels (Ambrilux™, Oral Biolife, Bethlehem, PA, USA) on periodontal healing of teeth in canines following the development of ligature-induced PD. Periodontal disease was induced in six female beagle dogs over a period of 55 days. Animals were then randomized into two groups, with treated animals (n = 3) receiving two applications of the study treatment 28 days apart. Non-treated animals (n = 3) served as the control group. Periodontal repair was assessed in all animals by radiographic analysis at Day 1 (prior to study treatment), Day 29 (just prior to dose 2), and Day 57 (28 days after dose 2). Urine and blood samples were obtained at the end of the study for evaluation of safety parameters. All animals were sacrificed 70 days after the start of the study treatment phase, when tissue samples were harvested and subjected to quantitative computed tomography (CT) and histopathologic analysis. See Figure 6 for details on study design.
Figure 6.
Overview of study design.
4.2. Animals and Housing
All handling and treatment procedures involved in conducting this study were approved by the Institutional Animal Care and Use Committee (IACUC) (AC24017C; KAC24017.01C; KAC24017.02C) and in accordance with the Animal Welfare Act and the Guide for the Care and Use of Laboratory Animals [49].
Animals (non-pregnant female beagles) were allowed to acclimate to the housing, food and water for a minimum of 7 days. General health observations and physical examination were performed twice a day during the acclimation phase. Animals were housed in an Animal Biosafety Level (ABSL)-2 room where air is HEPA filtered both on intake and exhaust. The room was 40 × 32 feet and equipped with continuous environmental monitoring and automatic light timing systems. The dogs were housed in kennels providing a minimum of 12 square feet for each dog.
Feed was adjusted based on the stage of the protocol. Animals were fed Purina Pro Plan Veterinary Diets EN Gastroenteric bagged, hard dog food (Nestle Purina PetCare Company, St. Louis, MO, USA) throughout the acclimation period and up to placement of ligatures. Following placement of ligatures, a canned wet food formulation of Purina Pro Plan Veterinary Diets EN Gastroenteric was provided throughout the remainder of the study until ligature removal. Feed volume and changes were determined by the Attending Veterinarian.
4.3. Periodontal Preparation
Two weeks prior to induction of PD, the dogs were premedicated with acepromazine (0.05 mg/kg, subcutaneous (SQ) or intravenous (IV)) and hydromorphone (0.10 mg/kg, SQ or IV) and catheterized. General anesthesia was induced with propofol (to effect, IV). Following intubation, general anesthesia was maintained with oxygen and isoflurane. Periodontal instrumentation was then performed with ultrasonic and hand instruments, and the teeth were carefully polished. During this preparation phase, animals had their teeth brushed once daily for 1 min using a commercially available canine toothpaste (Virbac C.E.T. Enzymatic, Westlake, TX, USA). Daily brushing was continued until the beginning of the PD induction phase.
4.4. Periodontal Disease Induction
Ligatures were placed on teeth 407, 408, and 409 of the mandible using the methods described by Kim et al. [50]. These teeth, which form the bottom half of the carnassial apparatus, were chosen based on their role as the primary area of mastication and their similarity to human dental spaces [50]. While under general anesthesia, the gingival attachments of the teeth were incised using a number 11 scalpel blade and undermined until the pocket depth measured 3 mm with a straight elevator. Following undermining of the gingival attachment, a shallow notch was created on the mesial and distal aspects of each tooth using a burr to prevent slippage and facilitate retention of the ligatures. Lastly, a dental ligature wire twisted with a 2-0 braided silk suture was placed on each tooth. The knot of the ligature faced distally and was covered with a dental composite (3M™ Filtek™ Supreme Ultra Universal Restorative, Maplewood, MN, USA) to prevent iatrogenic damage to the oral cavity. Buprenorphine (0.015 mg/kg, SQ) was administered during anesthetic recovery following the placement of the ligatures. Then, the oral cavity was examined daily to confirm retention of each of the ligatures, which remained in place for 55 days. The ligatures were removed before the periodontal evaluation on Day 1 and were not replaced.
4.5. Periodontal Treatment
4.5.1. Fabrication of Piezoelectric Hydrogel
Ambrilux Dental Gel, formerly known as PiezoGEL was fabricated as previously described [12] by mixing 200 mg/mL gelatin methacryloyl hydrogel (GelMA; Advanced BioMatrix–5208, Carlsbad, CA, USA) with 9 mg/mL silanized tetragonal particles of BTO (US Nanomaterials (Houston, Texas, USA), US3830, 200 nm) and sterile phosphate-buffered saline (PBS). The size of the particles was 200 nm; they had a near-spherical shape and surface area of 6–7 m2/g. The photoinitiator lithium phenyl-2,4,6-trimethylbenzoyl phosphonate (LAP) (Advanced Biomaterials, 5269, Carlsbad, CA, USA) was added at a proportion of 0.35% wt of the solubilized GelMA. Lyophilized GelMA and PBS (70 °∆C) were mixed using a vortex mixer (Daigger Scientific, Vernon Hills, IL, USA) until the GelMA was fully solubilized. BTO particles were added during the continuous shaking of the mixture. Subsequently, LAP was dissolved in 100 μL of warm PBS (70 °∆C) and mixed with the dissolved GelMA/BTO mixture. The final loading fraction contained 9 mg/mL silanized BaTiO3 particles dispersed in 200 mg/mL GelMA, corresponding to 0.9 w/v BaTiO3.
Scanning electron microscopy (SEM) has previously demonstrated that the barium titanate nanoparticles are uniformly dispersed within the gelatin methacryloyl (GelMA) matrix, characteristically assembling into small 10 µm agglomerates. Complementary elemental analysis confirmed the composite’s material identity, detecting carbon, sodium, and chlorine—corresponding to the GelMA hydrogel framework—alongside baseline barium and titanium signatures [19].
Under cyclic compressive loading parameters designed to mimic masticatory pressures (3 N, 2 Hz) the product was found to exhibit mechanoelectric behavior, generating 10 mV/mm2 [18,19].
4.5.2. Randomization
Animals (n = 6) were randomized to either the active treatment group (scaling, root planing, and application of the piezolectric gel) or the control group (scaling and root planning only) at the end of the PD induction phase on Day 1. Randomization was performed by ranking the PD severity of all subjects based on the periodontal evaluation combined score of plaque index (PI), gingival index (GI), bleeding on probing (BoP), and the difference between the periodontal probing pocket depth (PPD) and the clinical attachment level (CAL). Dogs were then randomly assigned to a study group within independent permutations of the two treatments. Of the two dogs with the highest periodontal scores, one was randomly allocated to the study treatment group and the other to the control group. The same random allocation procedure was applied to the remaining two pairs of subjects. Randomization was performed within commercially available data software (Microsoft Excel).
4.5.3. Application of Study Treatment
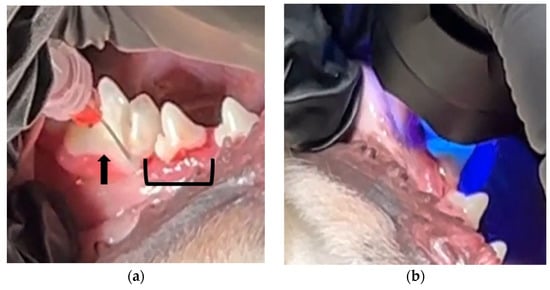
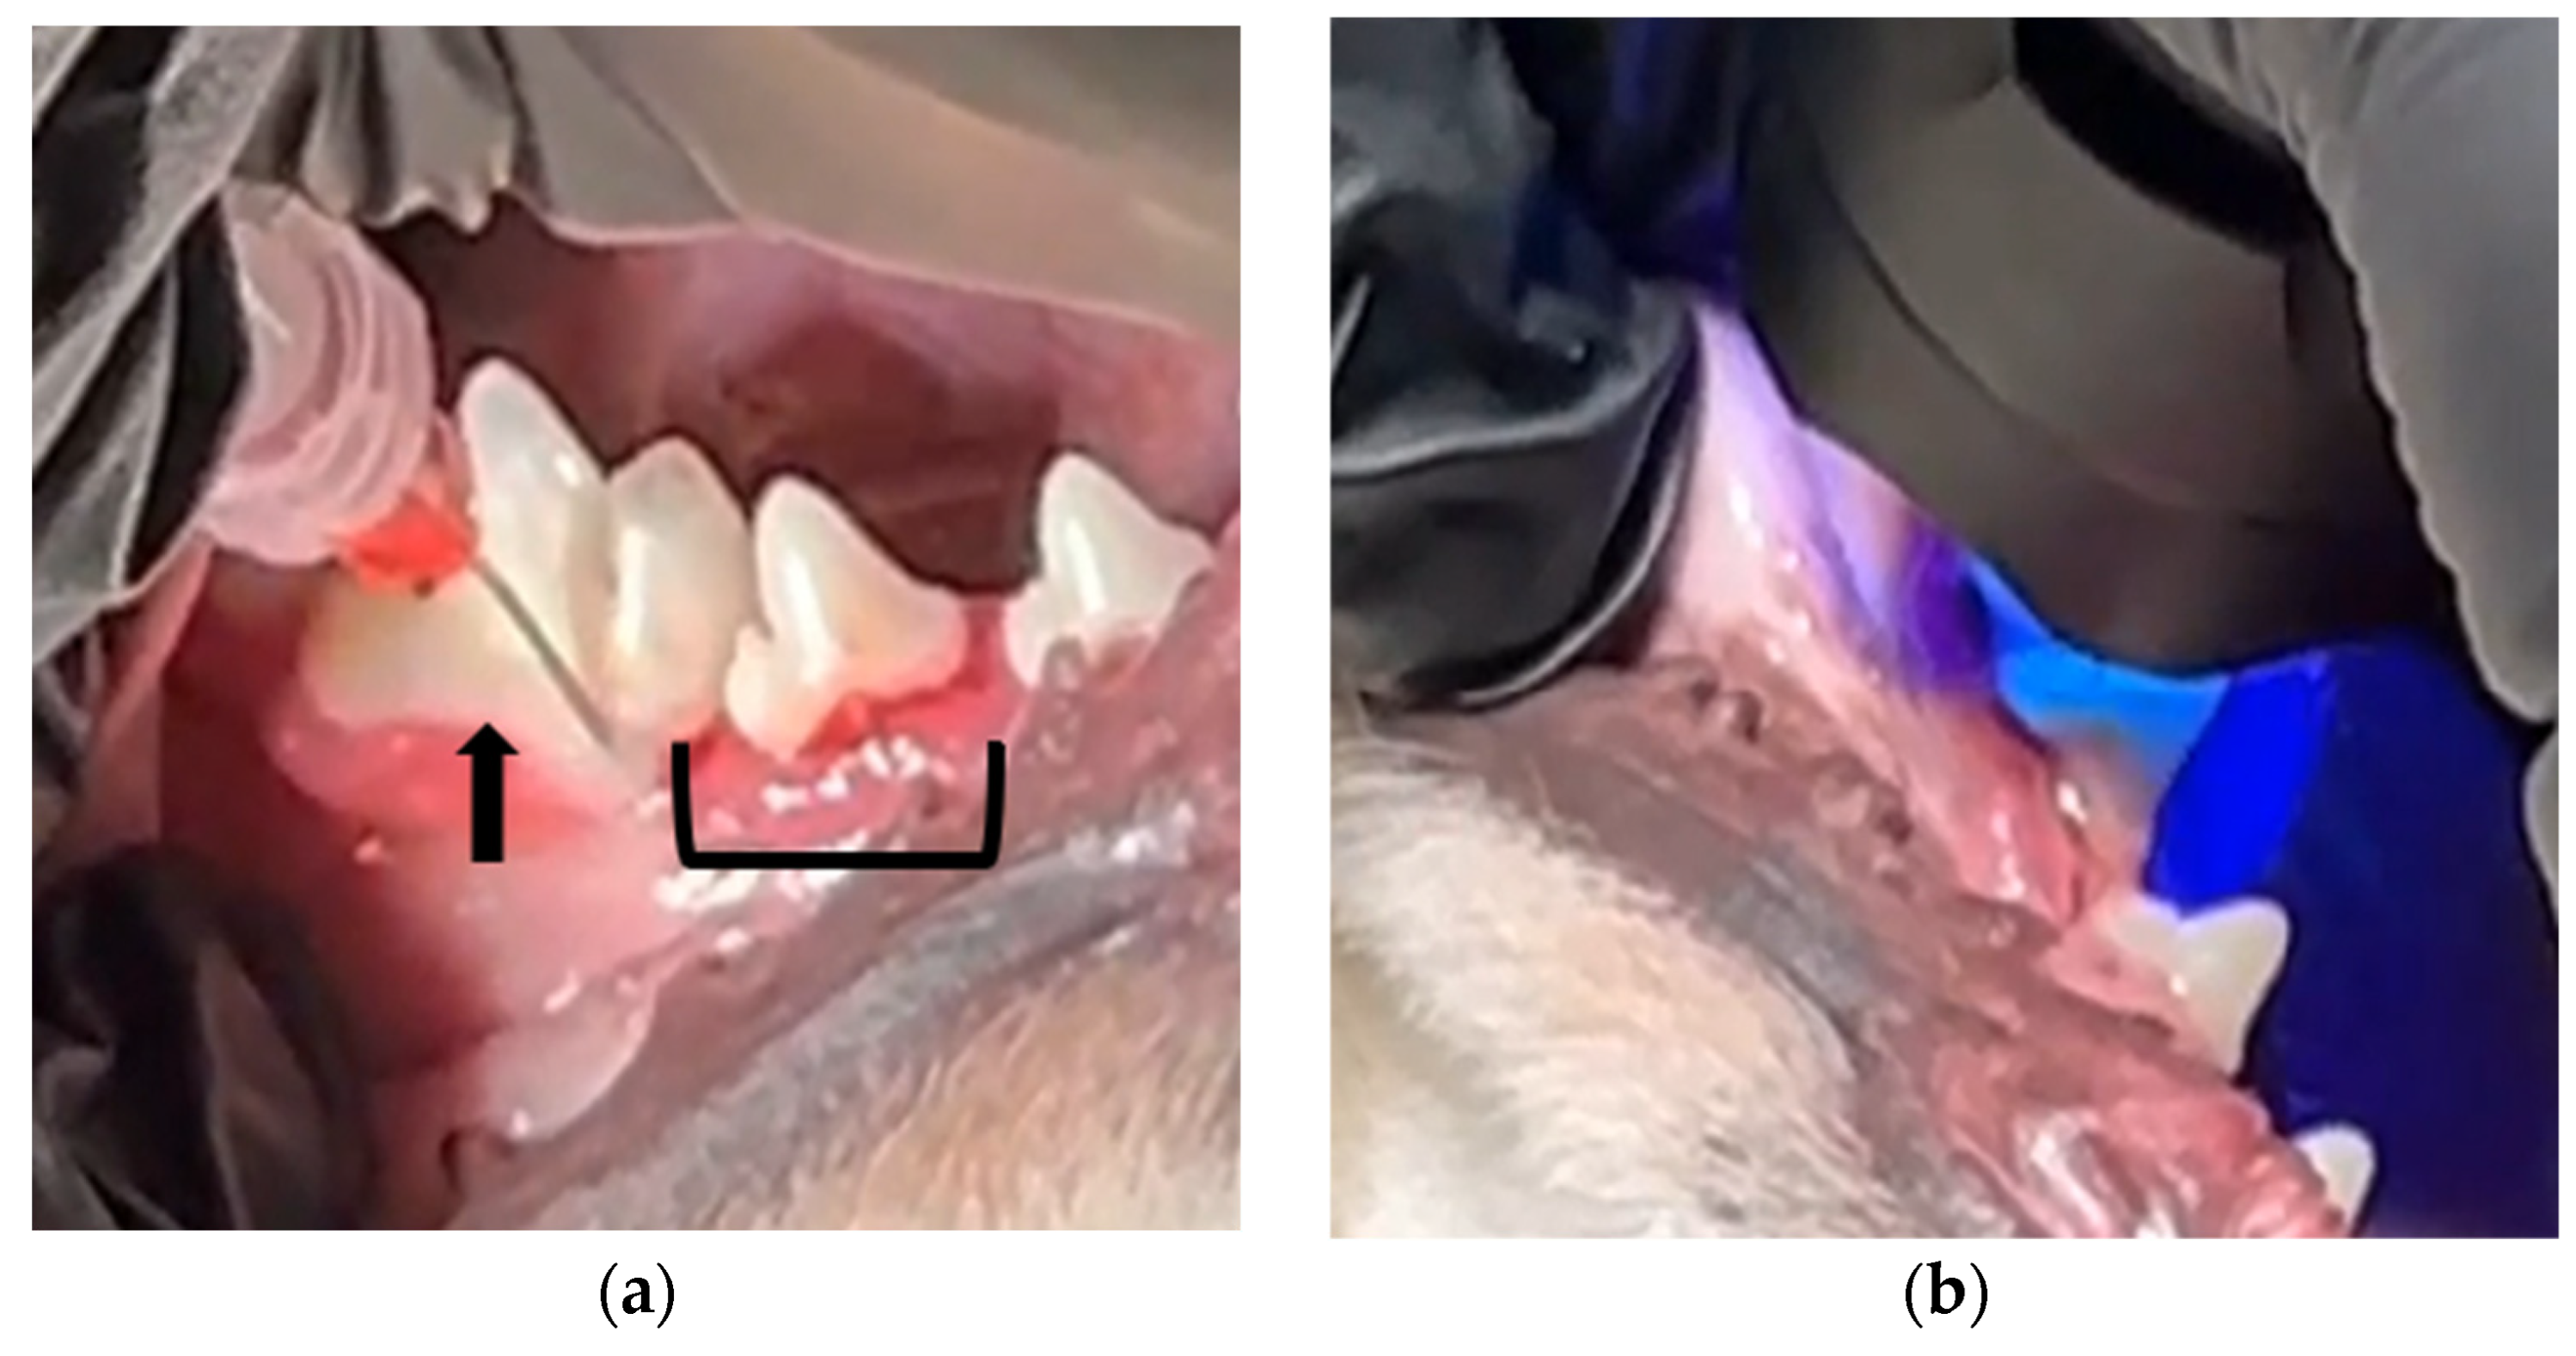
Application of the piezolectric gel was performed on Day 1 for animals in the active treatment group. Each dog received dexmedetomidine and butorphanol injectable anesthesia intravenously for the application of the study treatment and was monitored throughout sedation. The piezolectric gel was applied into the periodontal pocket using prefilled syringes and a 22-gauge dental application tip (Figure 7a). A new application device was used for each dog. Approximately 0.5 mL in total of the piezolectric gel was applied to the three teeth being studied until visible above the gingival margin. The gel was then cured with a LED light for 60 s (Figure 7b). Following curing, the periodontal pocket was covered with tissue adhesive (Vetbond, 3M, Maplewood, MN, USA) and allowed to dry. The second study treatment application occurred on Day 29 following the same procedure and was performed while the dogs were under general anesthesia for periodontal evaluations. The buccal surfaces of teeth 407, 408, and 409 were observed every 7 days after application by unmasked personnel to determine the retention of the study treatment. In addition, the retention of the study treatment was documented during necropsy on Day 71.
Figure 7.
(a) Application of Ambrilux to the periodontal pocket of teeth 407–409 following induction of ligature-induced PD. Excess Ambrilux (arrow) was removed prior to curing. The bracket represents an area of PD that has yet to be treated. (b) Curing of Ambrilux within the periodontal pocket using a standard UV light (395–405 nm) for approximately 60 s.
4.5.4. Masking
Masking was in effect during the treatment phase of the study and was accomplished by separation of functions. The Study Investigator and limited other personnel designated by the Investigator were unmasked and responsible for study treatment application and weekly post-application retention observations, while the Attending Veterinarian remained masked and was responsible for performing periodontal measurements subsequent to the study treatment application. During the treatment phase, routine general health observations were performed by masked personnel except on the morning of Day 60 when an unmasked individual performed general health observations. On Day 1 following morning general health observations, one member of the study staff was directed to become unmasked by the Study Investigator to assist with recovery from the injectable anesthesia used to facilitate treatment administration.
4.6. Study Assessments
4.6.1. Laboratory Analysis
Comprehensive chemistry, complete blood count, and urinalysis were conducted at IDEXX BioAnalytics (West Sacramento, CA, USA) to assess animal health and specific organ system health and to assist in identifying any potential toxicities. Venous blood samples were collected for hematology (CBC and serum chemistry) using a 20 ga × ¾ inch needle on Days 1, 29, and 57. Following collection, the blood was transferred into a 5 mL serum separator tube and a 3 mL K2EDTA tube. The K2EDTA tubes were placed on ice immediately after collection. The serum samples were allowed to clot for a minimum of 30 min before ambient centrifugation at 2000× g for 10 min. Following centrifugation, the serum was decanted into 2 aliquots (one primary and a backup). The K2EDTA tube and a serum aliquot were shipped on the day of collection.
4.6.2. Safety Assessment
General health observations were conducted twice daily throughout the study. As periodontal disease was induced in this study, observations localized to the oral cavity were not considered adverse events. Systemic sequalae secondary to periodontal disease with severity such that emergency intervention or observation beyond protocol specifications were recorded as adverse events and classified as mild, moderate, or severe.
4.6.3. Periodontal Evaluation
Because of the inherent variability in clinical scoring and the low number of animals per group, periodontal evaluations were conducted primarily to ensure onset and satisfactory progression of disease in each animal and to assure proper randomization of subjects prior to treatment. Periodontal evaluations were performed on Day 56 before placement of ligatures, Day 1 after ligature removal, and Day 29 and Day 57 while the subjects were under general anesthesia. The evaluation was performed using a scoring system that accounts for PI, GI, PPD, CAL, and BoP [51,52]. Scores ranged from 0 to 3 for PI, with 0 = none and 3 = abundant; and from 0 to 3 for GI, with 0 = no inflammation and 3 = severe inflammation. Measurement of PPD was defined as the distance between the gingival margin and the bottom of the probable pocket, and CAL was the distance between the enamel–cementum junction and the bottom of the probable pocket. A score of 0 indicated absence of bleeding within 10 s following probing, and a score of 1 indicated presence of bleeding.
Each of the parameters was evaluated at the disto-buccal site. Periodontal evaluations were performed by the same individual throughout the course of the study who was masked to treatment assignments.
4.6.4. Intraoral Radiographs
Digital intraoral radiographs were obtained to evaluate the temporal changes of alveolar bone loss after ligature application and subsequent administration of study treatment. Intraoral radiographs were captured using a handheld radiology unit (DEXIS NOMAD™ Pro 2, Quakertown, PA, USA) concurrent with the periodontal evaluations at the start and end of PD induction, 28 days after dose 1 (just prior to dose 2), and 28 days after dose 2. To ensure precise alignment of the digital sensor throughout the course of the study, dental molds were constructed for each individual animal using Braval VPS Putty (Patterson Dental, St. Paul, MN, USA). Briefly, putty was mixed according to instruction and placed into an adhesive-coated tray. The tray was inserted into the mouth and held in position until set. For each radiograph, the mold was inserted into the mouth, and the digital sensor placed in the same location on the mold.
Qualitative analysis of radiographs of the furcations of teeth 409 and 408 was conducted in a blinded manner and scored for changes in furcation bone radiopatency over time. Issues with superimposition of adjacent teeth in some animals precluded use of tooth 407.
4.6.5. Micro-CT Imaging
In order to limit variability, CT imaging, VOI and quantitative analysis were conducted by a single individual in a blinded fashion. For high-resolution micro-CT imaging, harvested jaw specimens were scanned with a SKYSCAN 1273 micro-CT system (Micro Photonics Inc, Allentown, PA, USA) at a resolution of 13.85 μm (achieved using 130 kV and 60 μA). Individual mandible samples were wrapped in gauze saturated with physiological saline and placed within a sealed plastic container to maintain hydration during imaging. Each sample was imaged with an isotropic voxel size of 25 μm using 120 kV and 300 μA X-ray settings with an exposure time of 501 ms per frame, with 4 frames averaged at each projection angle. Volumetric reconstructions were performed using NRecon 2 software (Bruker Corp, Billerica, MA, USA) before visualization of samples within Bruker’s DataViewer (v1.5.4) and CTVox (v3.3.0) programs. Quantitative assessment of bone in the furcation of tooth 409 was performed using a morphological escalator selection method to isolate the thinner trabecular bone within each furcation volume of interest. The morphological escalator is a fully automated, image-processing technique that is commonly utilized in CT bone morphometry and is packaged into the analysis software. We used the technique to help segment and delineate trabecular bone from surrounding dense cortical bone, thereby more accurately defining our region of interest.
After the tissue mineral density was determined, volumetric analysis of the volume of interest was determined. The mineralized tissue within the VOI was first segmented using an adaptive mean threshold applied in 2D with a round kernel, radius of 3, and constant of 1. A pre-thresholding step was also employed to minimize analysis processing time, defining all pixels with intensity values of less than 65 as non-mineralized and all pixels with intensity values of 75 or greater as mineralized. Thus, the adaptive threshold was used to decide on the classification of each pixel falling between 66 and 74.
After segmentation, a despeckle function was applied in 2D to remove all black speckles less than 7 pixels in area, followed by a repeat of the function again at the same selection criteria but now focused on white pixels in the dataset less than 7 pixels in area. After these cleanup steps, a volumetric analysis was completed on the dataset in 3D, which captured the VOI volume, mineralized tissue volume, surface area, mineralized tissue thickness, and open space thickness among other reported values.
4.6.6. Qualitative Histology
Qualitative histology, as opposed to quantitative histology, was utilized due to the small sample size and associated statistical limitations. Histopathologic analysis focused on both the proximal regions of the teeth and the furcation of tooth 409.
Following CT analysis, samples were decalcified in 22% formic acid until suitable for sectioning, processed using routine histologic processing techniques, embedded in paraffin, and cut at 4 μm thickness. Sections were stained with Hematoxylin and Eosin (H & E) and examined using the Aperio ImageScope (Version 12.3.3) digital pathology system (Leica Biosystems, Deer Park, IL, USA).
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/gels12111007/s1: Supplemental Table S1. Clinical chemistry results; Supplemental Table S2. Hematology results—blood count; Supplemental Table S3. Urinalysis results; Supplemental Table S4. Periodontal evaluations for treated animals (disto-buccal); Supplemental Table S5. Periodontal evaluations for control animals (disto-buccal).
Author Contributions
K.S.K.: study conceptualization, project administration, supervision, data interpretation, writing—first draft, and writing—review and editing. R.B.D.S.: data interpretation and writing—review and editing. All authors have read and agreed to the published version of the manuscript.
Funding
This preclinical study was funded by Oral Biolife (MVS 24017).
Institutional Review Board Statement
The animal study protocol was approved by the Midwest Veterinary Services (Manhattan, Kansas) Institutional Animal Care and Use Committee (IACUC) on 1 March 2024 (AC24017C; KAC24017.01C; KAC24017.02C).
Informed Consent Statement
Not applicable.
Data Availability Statement
Some datasets presented in this article are not readily available because of technical limitations. The available datasets are included in the Supplementary Materials. Further inquiries can be directed to the corresponding author.
Acknowledgments
The authors wish to thank the following for their support: Pascal Kunz for creating individualized molds for the study animals to ensure consistent radiographs over time, and for support with data interpretation; Midwest Veterinary Services for conducting the preclinical study, funded by Oral Biolife; and Maria Paluselli for medical writing support, funded by Oral Biolife.
Conflicts of Interest
Dr. Kilgore serves as a consultant to Oral Biolife as Chief Scientific Officer. Dr. Santana serves as a consultant on the Oral Biolife Scientific Advisory Board.
Abbreviations
The following abbreviations are used in this manuscript:
| AAP | American Academy of Periodontology |
| ABSL | Animal Biosafety Level |
| ALP | alkaline phosphatase |
| BoP | bleeding on probing |
| BMD | bone mineral density |
| BTO | barium titanate |
| BV | bone volume |
| CAL | clinical attachment level |
| CBC | complete blood count |
| COL1A1 | Collagen Type I Alpha 1 Chain |
| CT | computed tomography |
| FDA | Food and Drug Administration |
| FI | furcation involvement |
| GI | gingival index |
| GTR | guided tissue regeneration |
| H&E | Hematoxylin and Eosin |
| HEPA | High-Efficiency Particulate Air |
| IACUC | Institutional Animal Care and Use Committee |
| IV | intravenous |
| K2EDTA | dipotassium ethylenediaminetetraacetic acid |
| PD | periodontal disease |
| PDL | periodontal ligament |
| PE-IAH | Piezoelectric Injectable Anti-Adhesive Hydrogel |
| PI | plaque index |
| PLLA | poly (L-lactic acid) |
| PPD | periodontal probing pocket depth |
| ROS | reactive oxygen species |
| RUNX2 | runt-related transcription factor 2 |
| SQ | subcutaneous |
| TV | total volume |
| VOI | volume of interest |
References
- National Institute of Health, Dental and Craniofacial Research. Periodontal Disease in Adults (Age 30 or Older). Available online: https://www.nidcr.nih.gov/research/data-statistics/periodontal-disease/adults (accessed on 30 April 2026).
- Dannewitz, B.; Zeidler, A.; Hüsing, J.; Saure, D.; Pfefferle, T.; Eickholz, P.; Pretzl, B. Loss of molars in periodontally treated patients: Results 10 years and more after active periodontal therapy. J. Clin. Periodontol. 2016, 43, 53–62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenwell, H.; Committee on Research, Science and Therapy; American Academy of Periodontology. Position Paper Guidelines for Periodontal Therapy. J. Periodontol. 2001, 72, 1624–1628. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Glickman, I. Clinical Periodontology: Prevention, Diagnosis, and Treatment of Periodontal Disease in the Practice of General Dentistry, 4th ed.; Saunders: Philadelphia, PA, USA, 1972; pp. 242–245. [Google Scholar]
- Carnevale, G.; Pontoriero, R.; Hurzeler, M.B. Management of furcation involvement. Periodontology 2000 1995, 9, 69–89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Georgiou, G.O.; Tarallo, F.; Marchetti, E.; Bizzarro, S. Overview of the Effect of Different Regenerative Materials in Class II Furcation Defects in Periodontal Patients. Materials 2022, 15, 3194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Santana, R.B.; Gusman, H.C.; E Van Dyke, T. The response of human buccal maxillary furcation defects to combined regenerative techniques--two controlled clinical studies. J. Int. Acad. Periodontol. 1999, 1, 69–77. [Google Scholar] [PubMed]
- Santana, R.B.; de Mattos, C.M.L.; Van Dyke, T. Efficacy of Combined Regenerative Treatments in Human Mandibular Class II Furcation Defects. J. Periodontol. 2009, 80, 1756–1764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reddy, M.S.; Aichelmann-Reidy, M.E.; Avila-Ortiz, G.; Klokkevold, P.R.; Murphy, K.G.; Rosen, P.S.; Schallhorn, R.G.; Sculean, A.; Wang, H. Periodontal Regeneration—Furcation Defects: A Consensus Report From the AAP Regeneration Workshop. J. Periodontol. 2015, 86, S131–S133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sanz, M.; Jepsen, K.; Eickholz, P.; Jepsen, S. Clinical concepts for regenerative therapy in furcations. Periodontology 2000 2015, 68, 308–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chelu, M.; Popa, M.; Moreno, J.M.C. Next-Generation Natural Hydrogels in Oral Tissue Engineering. Pharmaceutics 2025, 17, 1256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kammona, O.; Tsanaktsidou, E. Recent Advances in Hydrogels for Tissue Engineering Applications. Gels 2026, 12, 454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, X.; Li, J.; Wu, Y.; Xu, L. Recent advancements in hydrogels as novel tissue engineering scaffolds for dental pulp regeneration. Int. J. Biol. Macromol. 2024, 264, 130708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dal-Fabbro, R.; Daghrery, A.; Anselmi, C.; Soares, I.P.M.; dos Reis-Prado, A.H.; de Oliveira, P.H.C.; Bottino, M.C. Recent Advances in Injectable Hydrogel Biotherapeutics for Regenerative Dental Medicine. Macromol. Biosci. 2025, 25, e00096. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yin, B.; Dodda, J.M.; Wong, S.H.D.; Roshan Deen, G.; Bate, J.S.; Pachauri, A.; Shiroud Heidari, B.; Kovářík, T.; Luo, C.-A.; Tsai, S.-W. Smart injectable hydrogels for periodontal regeneration: Recent advancements in biomaterials and biofabrication strategies. Mater. Today Bio. 2025, 32, 101855. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heng, B.C.; Bai, Y.; Li, X.; Meng, Y.; Lu, Y.; Zhang, X.; Deng, X. The bioelectrical properties of bone tissue. Anim. Model. Exp. Med. 2023, 6, 120–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kao, F.-C.; Chiu, P.-Y.; Tsai, T.-T.; Lin, Z.-H. The application of nanogenerators and piezoelectricity in osteogenesis. Sci. Technol. Adv. Mater. 2019, 20, 1103–1117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roldan, L.; Montoya, C.; Solanki, V.; Cai, K.Q.; Yang, M.; Correa, S.; Orrego, S. A Novel Injectable Piezoelectric Hydrogel for Periodontal Disease Treatment. ACS Appl. Mater. Interfaces 2023, 15, 43441–43454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Solanki, V.; Montoya, C.; Neelakantan, P.; Yang, M.; Orrego, S. Injectable Piezoelectric Hydrogel for Vital Pulp Therapy. J. Funct. Biomater. 2025, 16, 452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cunha, E.; Tavares, L.; Oliveira, M. Revisiting Periodontal Disease in Dogs: How to Manage This New Old Problem? Antibiotics 2022, 11, 1729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Morrow, C. Extraction of a mandibular first molar tooth (409) in a dog. Can. Vet. J. 2010, 51, 416–420. [Google Scholar] [PubMed]
- Santana, R.B.; Uzel, M.I.; Gusman, H.; Gunaydin, Y.; Jones, J.A.; Leone, C.W. Morphometric Analysis of the Furcation Anatomy of Mandibular Molars. J. Periodontol. 2004, 75, 824–829. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Miranda, J.L.C.; Santana, C.M.M.; Santana, R.B. Influence of Endodontic Treatment in the Post-Surgical Healing of Human Class II Furcation Defects. J. Periodontol. 2013, 84, 51–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vijayakanth, T.; Shankar, S.; Finkelstein-Zuta, G.; Rencus-Lazar, S.; Gilead, S.; Gazit, E. Perspectives on recent advancements in energy harvesting, sensing and bio-medical applications of piezoelectric gels. Chem. Soc. Rev. 2023, 52, 6191–6220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deng, X.; Zhuang, Y.; Cui, J.; Wang, L.; Zhan, H.; Wang, X.; Lin, K.; Yuan, C. Open Challenges and Opportunities in Piezoelectricity for Tissue Regeneration. Adv. Sci. 2025, 12, e10349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evans, R.D.L.; Foltz, D.; Foltz, K. Electrical Stimulation with Bone and Wound Healing. Clin. Podiatr. Med. Surg. 2001, 18, 79–95. [Google Scholar] [CrossRef] [Scilit]
- Wang, L.; You, X.; Lotinun, S.; Zhang, L.; Wu, N.; Zou, W. Mechanical sensing protein PIEZO1 regulates bone homeostasis via osteoblast-osteoclast crosstalk. Nat. Commun. 2020, 11, 282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Y.; Tian, H.; Hu, Y.; Cao, Y.; Song, H.; Lan, S.; Dai, Z.; Chen, W.; Zhang, Y.; Shao, Z.; et al. Mechanosensitive Piezo1 is crucial for periosteal stem cell-mediated fracture healing. Int. J. Biol. Sci. 2022, 18, 3961–3980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Sun, Y.-X.; Li, J. The role of mechanosensor Piezo1 in bone homeostasis and mechanobiology. Dev. Biol. 2022, 493, 80–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komori, T. Roles of Runx2 in Skeletal Development. In RUNX Proteins in Development and Cancer; Springer Nature: Singapore, 2017; pp. 83–93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, L.; Wang, X.; Ji, N.; Li, H.M.; Cai, S.X. [Mechanisms of the mechanically activated ion channel Piezo1 protein in mediating osteogenic differentiation of periodontal ligament stem cells via the Notch signaling pathway]. Hua Xi Kou Qiang Yi Xue Za Zhi 2020, 38, 628–636. [Google Scholar] [CrossRef] [PubMed]
- Li, X.; Han, L.; Nookaew, I.; Mannen, E.; Silva, M.J.; Almeida, M.; Xiong, J. Stimulation of Piezo1 by mechanical signals promotes bone anabolism. eLife 2019, 8, e49631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zaszczyńska, A.; Zabielski, K.; Gradys, A.; Kowalczyk, T.; Sajkiewicz, P. Piezoelectric Scaffolds as Smart Materials for Bone Tissue Engineering. Polymers 2024, 16, 2797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.; Li, R.; Wang, X.; Lu, D.; Li, W.; Wang, Y. Mechanically tunable fiber-based hydrogel activates PIEZO1-integrin axis for enhanced bone repair. J. Nanobiotechnol. 2025, 23, 603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baghdadi, M.B.; Houtekamer, R.M.; Perrin, L.; Rao-Bhatia, A.; Whelen, M.; Decker, L.; Bergert, M.; Pérez-Gonzàlez, C.; Bouras, R.; Gropplero, G.; et al. PIEZO-dependent mechanosensing is essential for intestinal stem cell fate decision and maintenance. Science 2024, 386, eadj7615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, D.; Li, L.; Cui, X.; Yang, B.; Pei, B.; Li, J.; Luo, R.; Zhang, Y.; Li, Y.; Zhao, Y. Synergistic Piezoelectricity and Lubrication in an Injectable Hydrogel for Osteochondral Regeneration. Adv. Funct. Mater. 2026, 36, e75561. [Google Scholar] [CrossRef] [Scilit]
- Cheng, S.; Yang, J.; Song, J.; Cao, X.; Zhou, B.; Yang, L.; Li, C.; Wang, Y. A motion-responsive injectable lubricative hydrogel for efficient Achilles tendon adhesion prevention. Mater. Today Bio. 2025, 4, 101458. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.; Jiang, X.; Li, R.; Pan, J.; Yang, B.; Zhou, X.; Huang, X.; Liu, J.; Li, T.; Wu, S. An innovative gas foaming-assisted decellularizing strategy to construct decellularized tilapia skin matrix with improved porosity, piezoelectricity, and biocompatibility. Biomater. Adv. 2026, 186, 214932. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, S.; Huang, L.; Chen, W.; Chen, Q.; Liu, X.; Su, D.; Xiao, L.; Zhou, D.; Zhang, J.; Jiang, L.B.; et al. Piezoelectric Hydrogel with Self-Powered Biomechanical Stimulation Enhances Bone Regeneration. Acta Biomater. 2025, 195, 117–133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, R.; Zhuang, Y.; Yang, H.; Dong, Q.; Wang, S.; Zhang, J.; Chen, Y. Piezo1-mediated mechanotransduction in bone formation and fracture repair. Biochem. Biophys. Rep. 2026, 48, 102767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Stefanello, S.T.; Shahin, V.; Qian, Y. From Mechanoelectric Conversion to Tissue Regeneration: Translational Progress in Piezoelectric Materials. Adv. Mater. 2025, 37, e2417564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yue, W.; Zhang, W.; Zhang, J.; Qin, W.; Bie, X.; Zhao, Y.; Xu, G. The Role of Piezoelectric Materials in Bone Remodeling and Repair: Mechanisms and Applications. Int. J. Nanomed. 2025, 20, 11593–11616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shao, B.; He, Y.; Wang, G.; Liu, Z.; Wang, S. Harnessing piezoelectricity for bone tissue engineering: Recapitulating the electrophysiological microenvironment through smart biomaterials. Front. Bioeng. Biotechnol. 2026, 14, 1867122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kantarci, A.; Hasturk, H.; Van Dyke, T.E. Animal models for periodontal regeneration and peri-implant responses. Periodontology 2000 2015, 68, 66–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hajishengallis, G.; Lamont, R.J.; Graves, D.T. The enduring importance of animal models in understanding periodontal disease. Virulence 2015, 6, 229–235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Glowacki, A.J.; Yoshizawa, S.; Jhunjhunwala, S.; Vieira, A.E.; Garlet, G.P.; Sfeir, C.; Little, S.R. Prevention of inflammation-mediated bone loss in murine and canine periodontal disease via recruitment of regulatory lymphocytes. Proc. Natl. Acad. Sci. USA 2013, 110, 18525–18530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daghrery, A.; Bottino, M.C. Advanced biomaterials for periodontal tissue regeneration. Genesis 2022, 60, e23501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, C.H. Biomaterial-Based Approaches for Regeneration of Periodontal Ligament and Cementum Using 3D Platforms. Int. J. Mol. Sci. 2019, 20, 4364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- National Research Council (US) Committee for the Update of the Guide for the Care and Use of Laboratory Animals. Guide for the Care and Use of Laboratory Animals, 8th ed.; National Academies Press (US): Washington, DC, USA, 2011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, S.E.; Lee, E.R.; Lee, Y.; Jeong, M.; Park, Y.W.; Ahn, J.S.; Ahn, J.T.; Seo, K. A modified method for inducing periodontitis in dogs using a silk-wire twisted ligature. J. Vet. Sci. 2012, 13, 193–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Löe, H.; Silness, J. Periodontal Disease in Pregnancy I. Prevalence and Severity. Acta Odontol. Scand. 1963, 21, 533–551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wennström, J.L.; Newman, H.N.; MacNeill, S.R.; Killoy, W.J.; Griffiths, G.S.; Gillam, D.G.; Krok, L.; Needleman, I.G.; Weiss, G.; Garrett, S. Utilisation of locally delivered doxycycline in non-surgical treatment of chronic periodontitis. J. Clin. Periodontol. 2001, 28, 753–761. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.