


Abstract
Bioresorbable scaffolds (BRS; also referred to as bioresorbable vascular scaffolds, BVS) represent a promising approach in interventional cardiology, offering theoretical advantages such as temporary mechanical support followed by complete resorption. However, clinical experience has revealed challenges, including late-stage scaffold thrombosis and heterogeneous scaffold discontinuity during degradation, prompting investigation into host immune responses. Neutrophil extracellular traps (NETs), which are network-like structures composed of decondensed chromatin decorated with antimicrobial proteins, have emerged as critical mediators of vascular inflammation and thrombosis. This review explores the intersection between NET biology and BRS performance, investigating how NETosis affects biocompatibility, degradation kinetics, and device-related complications. We discuss the molecular mechanisms that trigger neutrophil activation and NET formation in scaffold materials, the effect of NET components on polymeric and metallic scaffold degradation, and emerging biomarkers to monitor NET-mediated complications. We also evaluate therapeutic strategies targeting NET pathways, including DNase-based therapies, peptidylarginine deiminase 4 (PAD4) inhibitors, and anti-inflammatory coatings that can optimize next-generation BRS outcomes. Understanding the immunological environment surrounding bioresorbable vascular devices is crucial for developing scaffolds that deliver predictable degradation while minimizing adverse inflammatory responses.
1. Introduction
Bioresorbable scaffolds (BRS; also called bioresorbable vascular scaffolds, BVS) were developed to address the limitations of permanent metallic stents, including persistent foreign body response, impaired vasomotor function, and late stent thrombosis [1,2]. The concept of a temporary scaffold that provides initial mechanical support during vessel healing and is then fully absorbed offers theoretical advantages, including restoration of physiological vascular function and elimination of long-term device-related complications [3].
The first-generation Absorb bioresorbable vascular scaffold (Abbott Vascular), composed of poly-L-lactic acid (PLLA) with an everolimus-releasing coating, received regulatory approval based on promising early clinical results [4]. However, long-term follow-up revealed unexpectedly high scaffold thrombosis rates compared to contemporary drug-eluting stents, leading to its withdrawal from the market in 2017 [5,6]. Subsequent analyses identified multiple contributing factors, including scaffold design features (thick struts, limited expansion capacity), implantation technique, and patient selection [7,8]. Importantly, the biological response to the degraded scaffold material emerged as a critical, yet not fully understood determinant of outcomes.
Neutrophil extracellular traps (NETs) have recently been recognized as important mediators of cardiovascular pathology [9,10]. These network-like structures, composed of decondensed chromatin coated with granular proteins including myeloperoxidase (MPO), neutrophil elastase (NE), and cathelicidins, were initially identified as an antimicrobial defense mechanism [11]. However, abnormal or excessive NET formation contributes to thrombosis, inflammation, and tissue damage in various cardiovascular conditions [12,13].
This review investigates how neutrophil activation and NETosis affect scaffold biocompatibility, degradation kinetics, and clinical outcomes by examining the emerging evidence linking NET biology to BRS performance. We discuss potential biomarkers for monitoring NET-related complications and evaluate treatment strategies that could improve next-generation scaffold designs.
This narrative review was conducted following an extensive literature search in PubMed, Scopus, and Web of Science databases between January 2004 and January 2026. Search terms included combinations of ‘bioresorbable scaffold’, ‘bioresorbable vascular scaffold’, ‘bioresorbable stent’, ‘PLLA scaffold’, ‘magnesium scaffold’, ‘neutrophil extracellular traps’, ‘NETs’, ‘NETosis’, ‘immunothrombosis’, and ‘stent thrombosis’. Original English research articles, systematic reviews, and meta-analyses examining scaffold biomaterials, neutrophil biology, NET formation mechanisms, and cardiovascular thrombosis were included. Reference lists of key articles were manually scanned to identify additional relevant publications. Studies were selected based on their relevance to the intersection of NET biology and bioresorbable scaffold performance, and their emphasis on mechanistic information and translational implications.
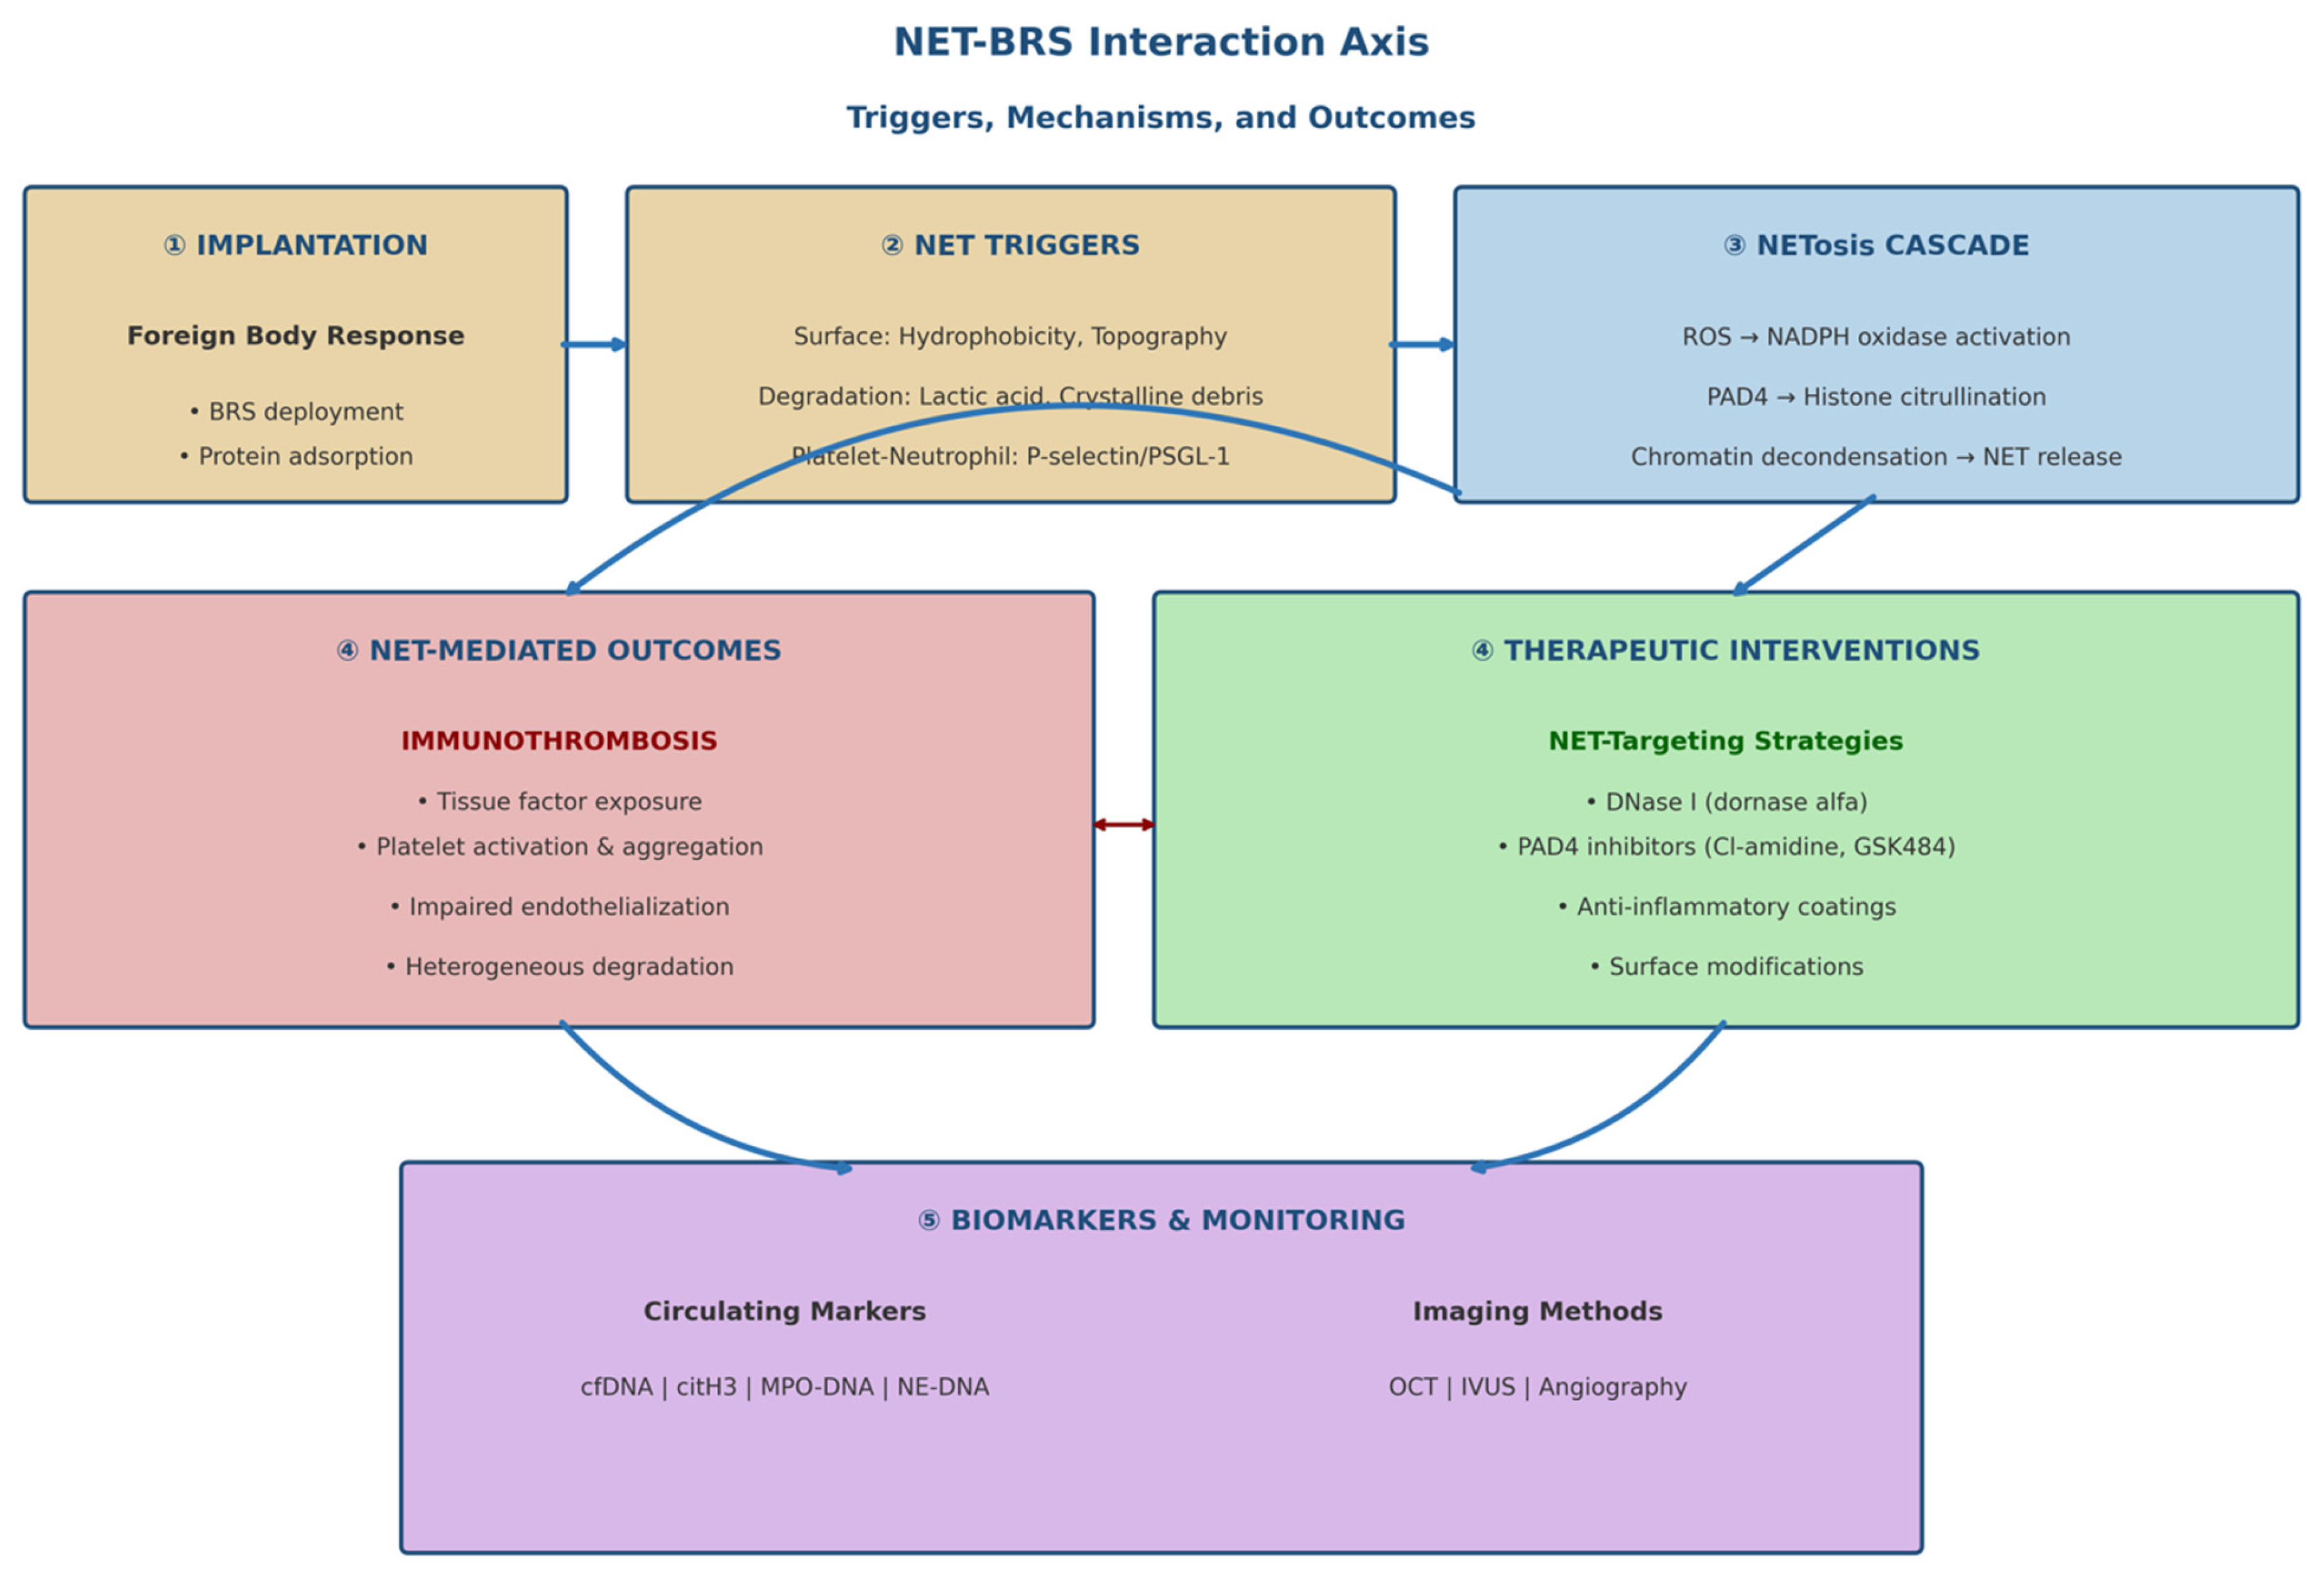
To provide an integrated overview of the mechanisms discussed in this review, the interactions between bioresorbable scaffolds, neutrophil activation, NET formation, and downstream clinical consequences are schematically summarized in Figure 1.
Figure 1.
Neutrophil extracellular trap (NET)—bioresorbable scaffold (BRS) interaction axis: triggers, mechanisms, and outcomes. Schematic diagram illustrating the NET-BRS interaction axis. The figure shows: (1) the initial foreign body response following BRS implantation and protein adsorption; (2) NET triggers including scaffold surface properties (hydrophobicity, topography), degradation products (lactic acid, crystalline residues, metal ions), and platelet–neutrophil interactions via the P-selectin/PSGL-1 pathway; (3) the NETosis cascade via ROS production, NADPH oxidase activation, PAD4-mediated histone citrullination, and chromatin decondensation; (4) NET-mediated outcomes including immunothrombosis (tissue factor exposure, platelet activation), impaired endothelialization, heterogeneous degradation, and mechanical instability—along with therapeutic intervention points (DNase, PAD4 inhibitors, anti-inflammatory coatings, surface modifications); (5) circulating biomarkers (cfDNA, citH3, MPO-DNA, NE-DNA) and imaging methods for monitoring.
2. Bioresorbable Scaffolds: Current Status and Clinical Challenges
2.1. Evolution of Bioresorbable Technology
The development of bioresorbable scaffolds has followed two main material platforms: polymeric scaffolds based on polylactic acid derivatives and metallic scaffolds using magnesium alloys [14]. PLLA-based scaffolds, exemplified by Absorb BVS, produce lactic acid, which enters the Krebs cycle by degrading through hydrolytic cleavage of ester bonds [15]. Complete resorption typically takes 3–4 years, during which time the scaffold transforms from a mechanically supportive structure into an amorphous mass before final clearance [16].
Magnesium-based scaffolds offer faster degradation kinetics compared to PLLA (typically 9–12 months, compared to 3–4 years for PLLA), while iron-based and zinc alloy platforms provide moderate degradation profiles (12–24 months) [17]. The Magmaris scaffold (Biotronik) represents the most advanced clinical version, featuring a magnesium alloy backbone with a bioresorbable polymer coating that elutes sirolimus [18]. Hybrid approaches combining polymeric and metallic components are also being investigated [19]. Table 1 summarizes the main classes of biodegradable exoskeleton materials, their degradation mechanisms, and related immunity and NET considerations.
Table 1.
Bioresorbable Scaffold Materials and Immuno–Degradation Properties.
Zinc alloy scaffolds have emerged as a promising alternative platform offering intermediate degradation rates (typically 12–24 months) between magnesium and polymeric platforms [23]. Zinc exhibits favorable biocompatibility, with Zn2+ ions playing essential roles in numerous enzymatic processes and cellular functions. Recently developed Zn-Mg and Zn-Li alloy formulations have demonstrated improved mechanical properties while maintaining suitable corrosion rates for vascular applications [24]. Zinc corrosion products are generally well tolerated, and slower and more homogeneous degradation compared to magnesium can reduce the risk of mechanical failure during the absorption period.
Iron-based scaffolds provide excellent mechanical strength similar to permanent stainless-steel stents, and degradation occurs via oxidative corrosion over 12–24 months [25]. Degradation products (primarily iron oxides) are cleared by macrophages via established cellular iron recycling pathways. However, concerns regarding local iron accumulation, potential inflammatory effects of iron oxide particles, and relatively slow degradation rate necessitate further research [26]. While early clinical experiences with iron-based scaffolds have shown promising results, long-term data are yet to be collected.
2.1.1. Scaffold Fabrication and Characterization Methods
The fabrication of bioabsorbable scaffolds utilizes various techniques depending on the material platform. Polymeric scaffolds are typically produced by extruding polymer tubes, followed by precision laser cutting to create a support pattern [14,15]. Alternative approaches include electrospinning to create fibrous scaffolds and three-dimensional printing using melt deposition modeling or stereolithography for complex geometries [28]. Metallic scaffolds (magnesium, zinc, iron) are produced by casting, extrusion followed by laser cutting, or photochemical etching [17,25].
Surface modification techniques are used to enhance biocompatibility and control drug release. These include plasma treatment, chemical grafting of hydrophilic polymers, and application of drug-delivering coatings [29,30]. Characterization of scaffold materials involves multiple analytical methods: Fourier-transform infrared spectroscopy (FTIR) for chemical composition analysis, nuclear magnetic resonance (NMR) spectroscopy for molecular structure determination, scanning electron microscopy (SEM) for surface morphology and support size assessment, and mechanical tests for radial strength and rebound properties [14,19]. Quality control protocols typically include accelerated degradation tests, biocompatibility tests, and drug release kinetics studies.
2.1.2. Scaffold Absorption Process
The absorption of bioabsorbable scaffolds goes through different stages depending on the type of material. For PLLA-based scaffolds, degradation occurs through hydrolytic cleavage of ester bonds in a four-stage process [15,16]:
Phase 1 (Hydration): Water penetrates the polymer matrix, initiating the degradation process. This phase typically occurs within the first few weeks after implantation.
Phase 2 (Strength Loss): Molecular weight decreases through random chain breakage while maintaining scaffold structural integrity. Radial strength begins to decrease in this phase (3–12 months).
Phase 3 (Mass Loss): Polymer degradation occurs with the formation of oligomers and monomers. Cellular clearance of degradation products begins, and scaffold discontinuity may become apparent in imaging (12–24 months).
Phase 4 (Complete Absorption): Lactic acid is converted to carbon dioxide and water via the Krebs cycle. For PLLA scaffolds, complete absorption usually takes 3–4 years.
Magnesium-based scaffolds undergo corrosion-mediated degradation, releasing magnesium ions and hydrogen gas according to the reaction: Mg + 2H2O → Mg(OH)2 + H2 [17]. The resulting magnesium hydroxide layer provides temporary corrosion protection before gradual dissolution. Complete absorption usually occurs within 9–12 months.
Iron-based scaffolds decompose via oxidative corrosion, subsequently forming iron oxides (mainly Fe2O3 and Fe3O4), which are then cleared by macrophages within 12–24 months [25]. Zinc alloy scaffolds exhibit moderate degradation kinetics (12–24 months) via corrosion mechanisms similar to magnesium, but hydrogen release is reduced and degradation patterns are more homogeneous [23,24].
2.1.3. Advantages and Disadvantages of Biologically Absorbable Scaffolds
Biologically absorbable scaffolds offer several theoretical advantages over permanent metallic stents:
- (1)
- Restoration of vasomotor function after scaffold absorption enables physiological vascular responses to vasoactive stimuli and potentially reduces the risk of late-stage adverse events.
- (2)
- Elimination of the persistent foreign body reduces the theoretical risk of very late-stage stent thrombosis and allows for future surgical revascularization options without permanently caged vascular segments.
- (3)
- Facilitates positive vascular remodeling and potential late-stage lumen recovery after scaffold absorption.
- (4)
- Potential to shorten the duration of dual antiplatelet therapy after complete scaffold absorption.
- (5)
- Compatibility with non-invasive imaging methods (MRI, CT) without artifact formation from permanent metallic implants [3,7]. However, significant disadvantages have limited clinical use:
- (1)
- Thicker support profiles (approximately 150 μm for Absorb, compared to 80 μm for contemporary drug-eluting stents) result in greater flow disturbance and increased thrombogenic potential.
- (2)
- Lower radial strength compared to metallic stents, requiring careful lesion preparation and precise vessel sizing.
- (3)
- Long degradation period (3-4 years for PLA), during which thrombotic risk persists and device-related complications may occur.
- (4)
- Strict vessel sizing protocols, technical requirements during implantation including mandatory pre-dilatation and post-dilatation requirements.
- (5)
- Higher device cost compared to contemporary metallic stents.
- (6)
- Higher scaffold thrombosis rates have been observed in clinical trials compared to metallic drug-eluting stents [5,31,32].
2.2. Clinical Experience and Complications
The ABSORB III trial (n = 2008), comparing Absorb BVS with Xience everolimus-eluting metallic stents, initially demonstrated equivalent target lesion failure rates at one year [33]. However, extended follow-up revealed significantly higher rates of target lesion failure and device thrombosis with BVS, particularly between one and three years post-implantation [5]. The ABSORB IV trial (n = 2604 patients) and the BIOSOLVE-II trial (n = 123 patients, magnesium scaffold) provided additional safety and efficacy data. Meta-analyses encompassing over 10,000 patients demonstrated that scaffold thrombosis rates were approximately 2–3 times higher than with contemporary drug-eluting stents [31,32].
Several mechanisms have been proposed to explain the high thrombotic risk. Thick scaffold struts (approximately 150 μm for Absorb, compared to 80 μm for current metallic DES) create larger flow disturbances and a greater potential for platelet activation [34]. Scaffold discontinuity during degradation may expose thrombogenic material to the bloodstream [35]. In addition, the inflammatory response to the degradation of the polymer, including neutrophil recruitment and activation, can create a prothrombotic environment that persists throughout the prolonged absorption period [36,37].
3. Neutrophil Extracellular Traps: Biology and Cardiovascular Implications
3.1. NET Formation Mechanisms
NETosis, the process of NET formation, can occur via multiple pathways with different kinetics and outcomes [38]. The classical pathway, suicide NETosis, involves the formation of reactive oxygen species (ROS) via NADPH oxidase, the transport of granular proteins to the nucleus, and histone citrullination mediated by peptidylarginine deiminase 4 (PAD4) [39]. Citrullination promotes chromatin decondensation by neutralizing histone charges. This is followed by nuclear membrane breakdown, and the rupture of the plasma membrane allows chromatin to mix with cytoplasmic and granular contents before releasing the NET structure [40].
Vital NETosis represents an alternative pathway in which NETs are typically released from living neutrophils via vesicular mechanisms [41]. This process occurs more quickly (while it takes hours for suicidal NETosis, it takes minutes here) and allows neutrophils to retain their antimicrobial functions. The relative contribution of these pathways to biomaterial-induced NETosis remains incompletely characterized and represents an important area for future investigation. Standardized methods for characterizing biomaterial-induced NETosis include the following: flow cytometry-based quantification of citrullinated histone-positive neutrophils; immunofluorescence microscopy for NET visualization using anti-MPO and DNA staining; ELISA-based measurement of NET-specific markers (MPO-DNA complexes, citH3); and real-time impedance-based monitoring of NETosis kinetics [42,43,44]. Consensus protocols for these assays are currently under development to enable cross-study comparisons.
3.2. NETs in Cardiovascular Thrombosis
NETs contribute to thrombosis through multiple mechanisms. The DNA backbone provides a scaffold for platelet adhesion and activation, while histones directly activate platelets and damage endothelial cells [45,46]. NET-associated tissue factor initiates the extrinsic coagulation cascade, and NET components, including elastase, increase coagulation activity by inactivating tissue factor pathway inhibitor (TFPI) [47]. Histopathological analysis of thrombus aspirates from patients with stent thrombosis by the PRESTIGE consortium revealed the clinical significance of NET presence in 23% of cases [12]. In acute myocardial infarction, circulating NET markers are associated with infarction size and adverse outcomes [48,49]. NETs have been identified in coronary thrombi, and their presence is associated with impaired microvascular perfusion following percutaneous intervention [50]. These observations suggest that therapies targeting NETs may improve outcomes in acute coronary syndromes and potentially in device-associated thrombosis.
3.3. NETs and Endothelial Dysfunction
NET components exert direct cytotoxic effects on endothelial cells. Histones, particularly H3 and H4, cause endothelial cell death through mechanisms involving calcium influx, mitochondrial dysfunction, and inflammatory signal activation [51]. Neutrophil elastase increases vascular permeability by degrading endothelial junction proteins. These effects may be particularly important in the context of BRS, where the endothelial sheath is necessary to isolate thrombogenic scaffold material from the bloodstream and prevent late scaffold thrombosis [51,52].
4. Effect of NETosis on Bioresorbable Scaffold Performance
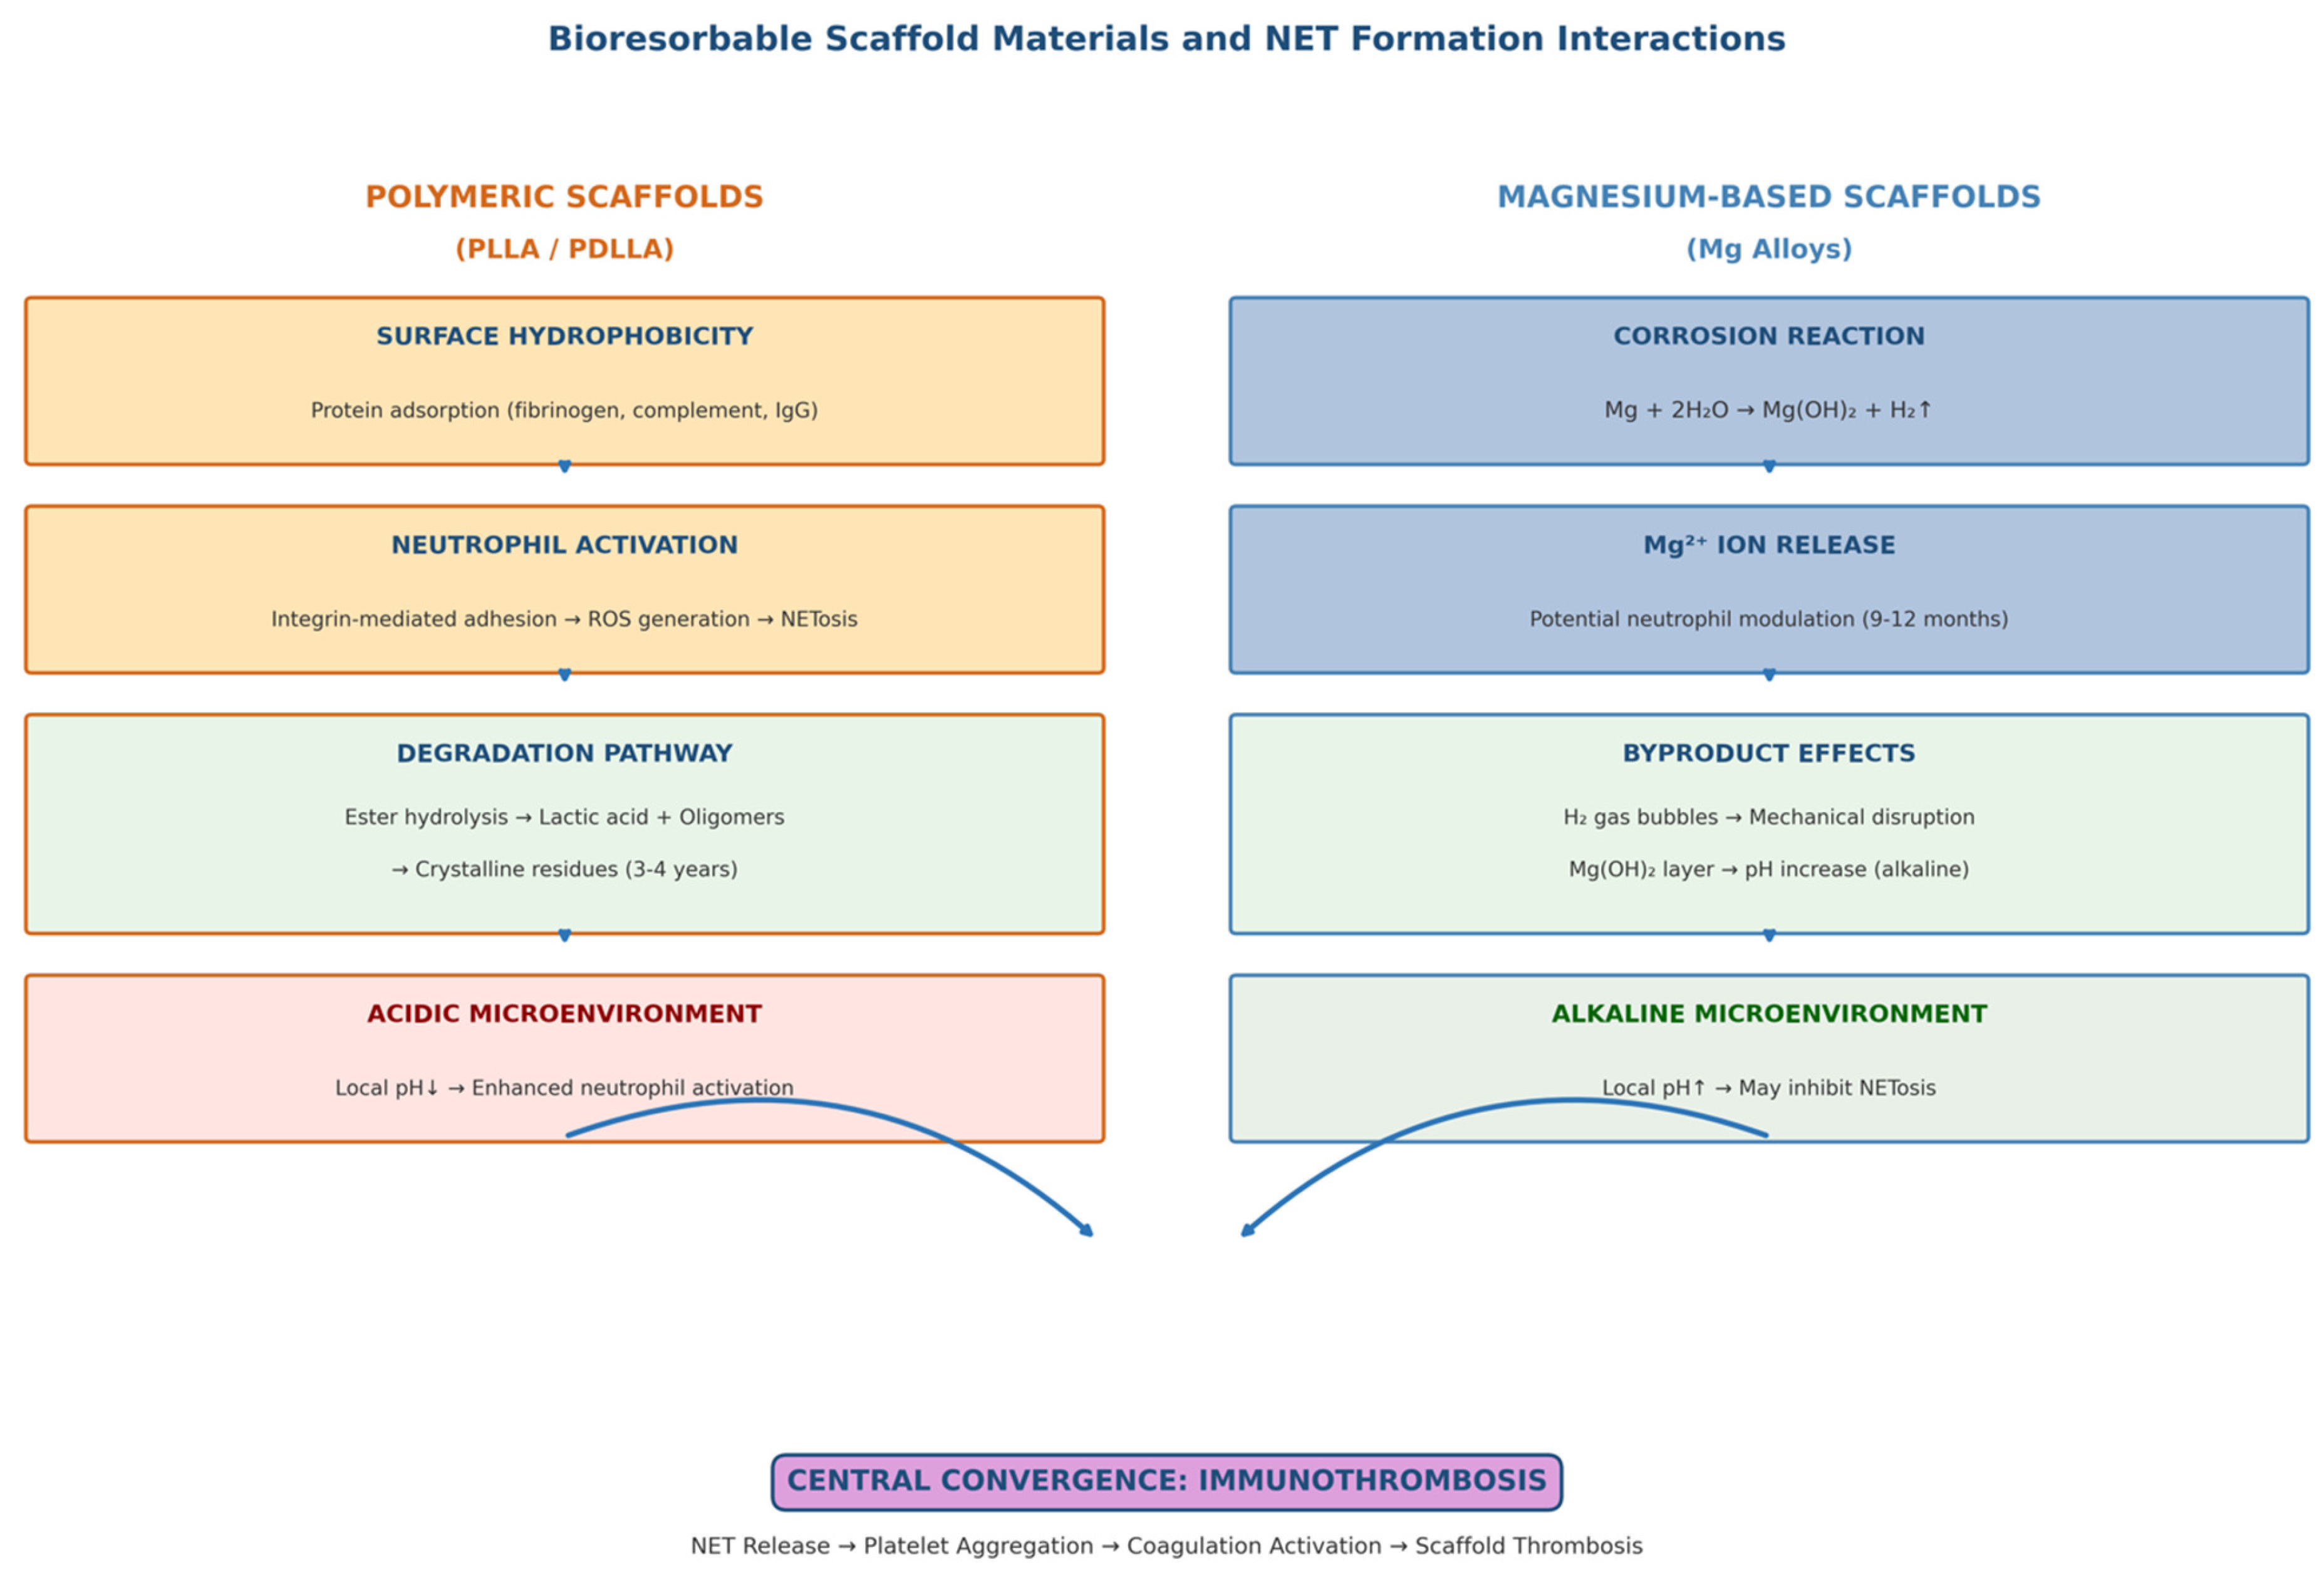
Since the composition of the scaffold material critically determines local immune responses, Figure 2 illustrates the different ways in which polymeric and magnesium-based bioabsorbable scaffolds interact with neutrophils and promote NET formation.
Figure 2.
Interactions between bioresorbable scaffold materials and NET formation. Dual-panel schematic comparing immune interactions of polymeric and metallic scaffolds. (Left Panel) (Polymeric Scaffolds-PLLA/PDLLA): Surface hydrophobicity → protein adsorption (fibrinogen, complement) → neutrophil adhesion via integrin receptors → ROS generation → NETosis; Degradation pathway: ester hydrolysis → lactic acid + oligomers → crystalline residues → macrophage/neutrophil activation → inflammatory amplification; Acidic microenvironment effects on local pH and neutrophil function. (Right Panel) (Magnesium-Based Scaffolds): Corrosion reaction (Mg + 2H2O → Mg(OH)2 + H2) → Mg2+ ion release → potential neutrophil modulation; Hydrogen gas bubble formation → mechanical disruption; Hydroxide layer formation → pH increase → alkaline microenvironment effects. Central Convergence: Both pathways lead to NET release, platelet aggregation, coagulation activation, and immunothrombosis.
4.1. Biomaterial-Induced NET Formation
The interaction between neutrophils and biomaterial surfaces is governed by protein adsorption, surface topography, and chemical properties. Upon contact with blood, scaffolds rapidly acquire a protein corona dominated by fibrinogen, complement components, and immunoglobulins [21,53,54]. These adsorbed proteins facilitate neutrophil adhesion via integrin receptors and trigger activation pathways that can lead to NETosis [55,56].
Biomaterial surface properties, including hydrophobicity and topography, can promote neutrophil activation and NET formation, which is important for PLA-based scaffold platforms [57]. Importantly, Xie et al. demonstrated that modification of PLA with carbon monoxide (CO)-loaded iron-based metal–organic frameworks (FeMOFs) significantly reduced NET release by decreasing intracellular ROS production [6]. This suggests that scaffold material properties can be designed to modulate the NET response. Scaffold degradation products can provide additional NETosis triggers. Lactic acid accumulation during PLLA hydrolysis creates an acidic microenvironment that can enhance neutrophil activation [4,15,20]. Crystalline degradation intermediates formed by the conversion of the amorphous polymer into crystalline residues can function as particle triggers, such as monosodium urate or cholesterol crystals [58]. For magnesium scaffolds, hydrogen gas formation during corrosion causes mechanical degradation, while the released magnesium ions can modulate neutrophil function through effects on intracellular signaling [22].
4.2. Effects of NETs on Scaffold Degradation Kinetics
NET components can directly influence scaffold degradation through enzymatic and chemical mechanisms. Neutrophil elastases and other proteases released during NETosis can accelerate polymer chain breakage, potentially creating heterogeneous degradation patterns [59]. The acidic pH created through respiratory burst activity by active neutrophils can locally enhance the hydrolytic degradation of polyester-based scaffolds [60]. For magnesium scaffolds, chloride ions in NET-associated DNA can accelerate corrosion by disrupting the protective surface layers [61]. Conversely, the alkaline environment created by the formation of magnesium hydroxide during corrosion can theoretically neutralize acidic conditions that support neutrophil activation, thereby inhibiting NETosis. These complex interactions between scaffold chemistry and NET biology are not yet fully characterized and represent important areas for future research.
4.3. NETs as Mediators of Scaffold Thrombosis
The prothrombotic properties of NETs are particularly concerning in the context of BRS, where thrombotic complications represent the primary clinical limitation. NETs can integrate scaffold struts and form a matrix that supports platelet aggregation and fibrin formation [62]. Histone-mediated endothelial damage can delay the protective endothelial sheath necessary for scaffold integration and prolong the thrombotic fragility window [63].
The temporal relationship between scaffold disruption and NET-mediated thrombotic risk deserves special attention. Clinical data show that the risk of BRS thrombosis peaks during the degradation phase, when scaffold discontinuity exposes the inner surfaces and releases degradation products [64]. This timing coincides with sustained inflammatory activity surrounding the degrading device, suggesting a mechanistic link between inflammation-induced NETosis and late thrombotic events [65,66].
5. Biomarkers for Monitoring NET-Mediated Complications
5.1. Circulating NET Biomarkers
Extracellular DNA (cfDNA) represents the most easily measurable component of NETs, as NETs release significant amounts of extracellular DNA during their formation. High plasma cfDNA levels have been associated with adverse outcomes in acute coronary syndromes and correlate with infarct severity [67,68,69]. However, cfDNA is not specific to NETosis, as it can also arise from other forms of cell death, including apoptosis and necrosis. More specific NET markers include citrullinated histones (particularly citrullinated H3 or citH3) produced during NETosis, particularly via PAD4 activity [39,67]. MPO-DNA complexes formed when myeloperoxidase remains associated with extracellular DNA provide another relatively specific marker of NET formation [68].
Neutrophil elastase-DNA complexes (NE-DNA) and calprotectin have also been investigated as NET biomarkers. Recent studies have shown that composite biomarker panels containing multiple NET markers can provide superior prognostic information compared to individual markers [68]. The development of standardized assays for determining NET quantification remains an active area of research, with ELISA-based methods, flow cytometry, and imaging approaches all being investigated [42,43,44].
5.2. Imaging Approaches for NET Detection
Non-invasive imaging of NET accumulation in scaffold regions represents an attractive but technically challenging goal. Intravascular imaging methods, including optical coherence tomography (OCT) and intravascular ultrasound (IVUS), can assess scaffold integrity and thrombus presence but cannot specifically identify NET components [70]. Research efforts are exploring molecular imaging approaches that can visualize NET-specific targets in vivo, but these remain at the experimental stage [71].
6. Therapeutic Strategies Targeting NET Pathways
Table 2 summarizes the key NET-inducing mechanisms, relevant biomarkers, and potential therapeutic modulation strategies related to biodegradable scaffolds.
Table 2.
NET triggers, biomarkers, and therapeutic modulation strategies in bioresorbable scaffolds.
6.1. DNase-Based Therapies
Deoxyribonuclease (DNase) enzymes, which degrade extracellular DNA, offer a direct approach to NET clearance. DNase I, available as recombinant dornase alfa (Pulmozyme), has been extensively studied for its NET-degrading properties. Animal studies have shown that DNase therapy reduces thrombus formation and improves outcomes in myocardial infarction models. Improved DNase variants with enhanced stability and activity are under development [72,73,74].
6.2. PAD4 Inhibitors
Peptidylarginine deiminase 4 (PAD4), the enzyme responsible for histone citrullination during NETosis, represents an attractive therapeutic target. Mice deficient in PAD4 show reduced NET formation and protection from thrombosis in various models [75]. Small-molecule PAD4 inhibitors have been developed and have shown efficacy in preclinical studies [76,77]. These agents could theoretically prevent NET formation while preserving other neutrophil functions and potentially offer a better safety profile than complete neutrophil depletion.
Recent studies have aimed to achieve localized NETosis inhibition while minimizing systemic effects by investigating nanoparticle-mediated delivery of PAD4 inhibitors to sites of vascular damage [78]. This approach may be particularly important for scaffold applications, where inflammation is concentrated at the device–tissue interface. However, the clinical development of PAD4 inhibitors is in its early stages, and their safety in the context of cardiovascular disease requires careful evaluation.
6.3. Anti-Inflammatory Approaches
Several established anti-inflammatory agents have shown effects on NET formation. Colchicine, which inhibits microtubule polymerization and neutrophil activation, has been shown to reduce NET formation in vitro and improve outcomes after myocardial infarction in the COLCOT study [79,80]. Metformin, commonly used in diabetes treatment, reduces NETosis through AMPK-dependent mechanisms [81]. Although statins are sometimes reported to increase NET formation, they can also exhibit protective effects through pleiotropic anti-inflammatory effects [82,83].
6.4. Surface Engineering Approaches
Modification of scaffold surfaces to reduce NETogenic potential offers a device-centric approach to limiting NET-mediated complications. Strategies investigated include hydrophilic coatings that reduce protein adsorption and neutrophil activation [29], phosphorylcholine-based zwitterionic surfaces that mimic cell membrane chemistry [30], and controlled release of anti-inflammatory agents from the scaffold surface. The aforementioned FeMOF/CO system represents an innovative approach that combines surface modification with therapeutic gas delivery [6]. Carbon monoxide, at controlled low concentrations, exhibits anti-inflammatory effects by reducing ROS production and inhibiting NETosis. Similar strategies involving nitric oxide donors or other anti-inflammatory molecules can further enhance the biocompatibility of the scaffold [84]. The challenge is to ensure sustained release during the long-term degradation period while maintaining the mechanical integrity of the scaffold.
7. Current Gaps and Methodological Limitations
Despite the increasing acceptance of the role of NETs in BRS complications, several critical deficiencies limit our current understanding and clinical practice:
- •
- Lack of standardized NET assays: There is no consensus on optimal methods for determining NET quantification in clinical samples; variable sensitivity and specificity across different test platforms limit comparability between studies.
- •
- Limited human pathology data: Few studies have directly examined the presence and burden of NETs in relation to BRS impairment status. Much of the evidence linking NETs to stent complications is inferential or derived from samples of metallic stent thrombosis.
- •
- Confounding factors: The contribution of dual antiplatelet therapy (DAPT) intensity, implantation technique, lesion complexity, and patient-specific inflammatory profiles makes it difficult to isolate the impact of NET-specific effects on stent outcomes.
- •
- Animal model limitations: Current animal models do not fully replicate human coronary flow dynamics, atherosclerotic plaque composition, or the chronic inflammatory environment present in patients with coronary artery disease.
- •
- Lack of direct NETogenicity comparisons: Systematic comparisons of the NET-inducing potential among different BRS materials (PLLA, PCL, magnesium alloys) and surface modifications are lacking.
Addressing these shortcomings will require coordinated multicenter biobanking studies, the development of consensus testing protocols, and the integration of NET assessments into future BRS clinical trials.
8. Future Directions
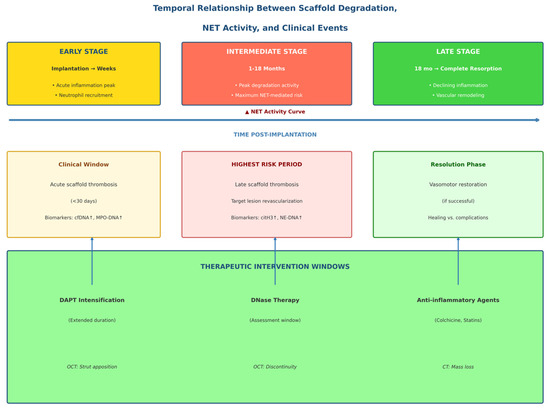
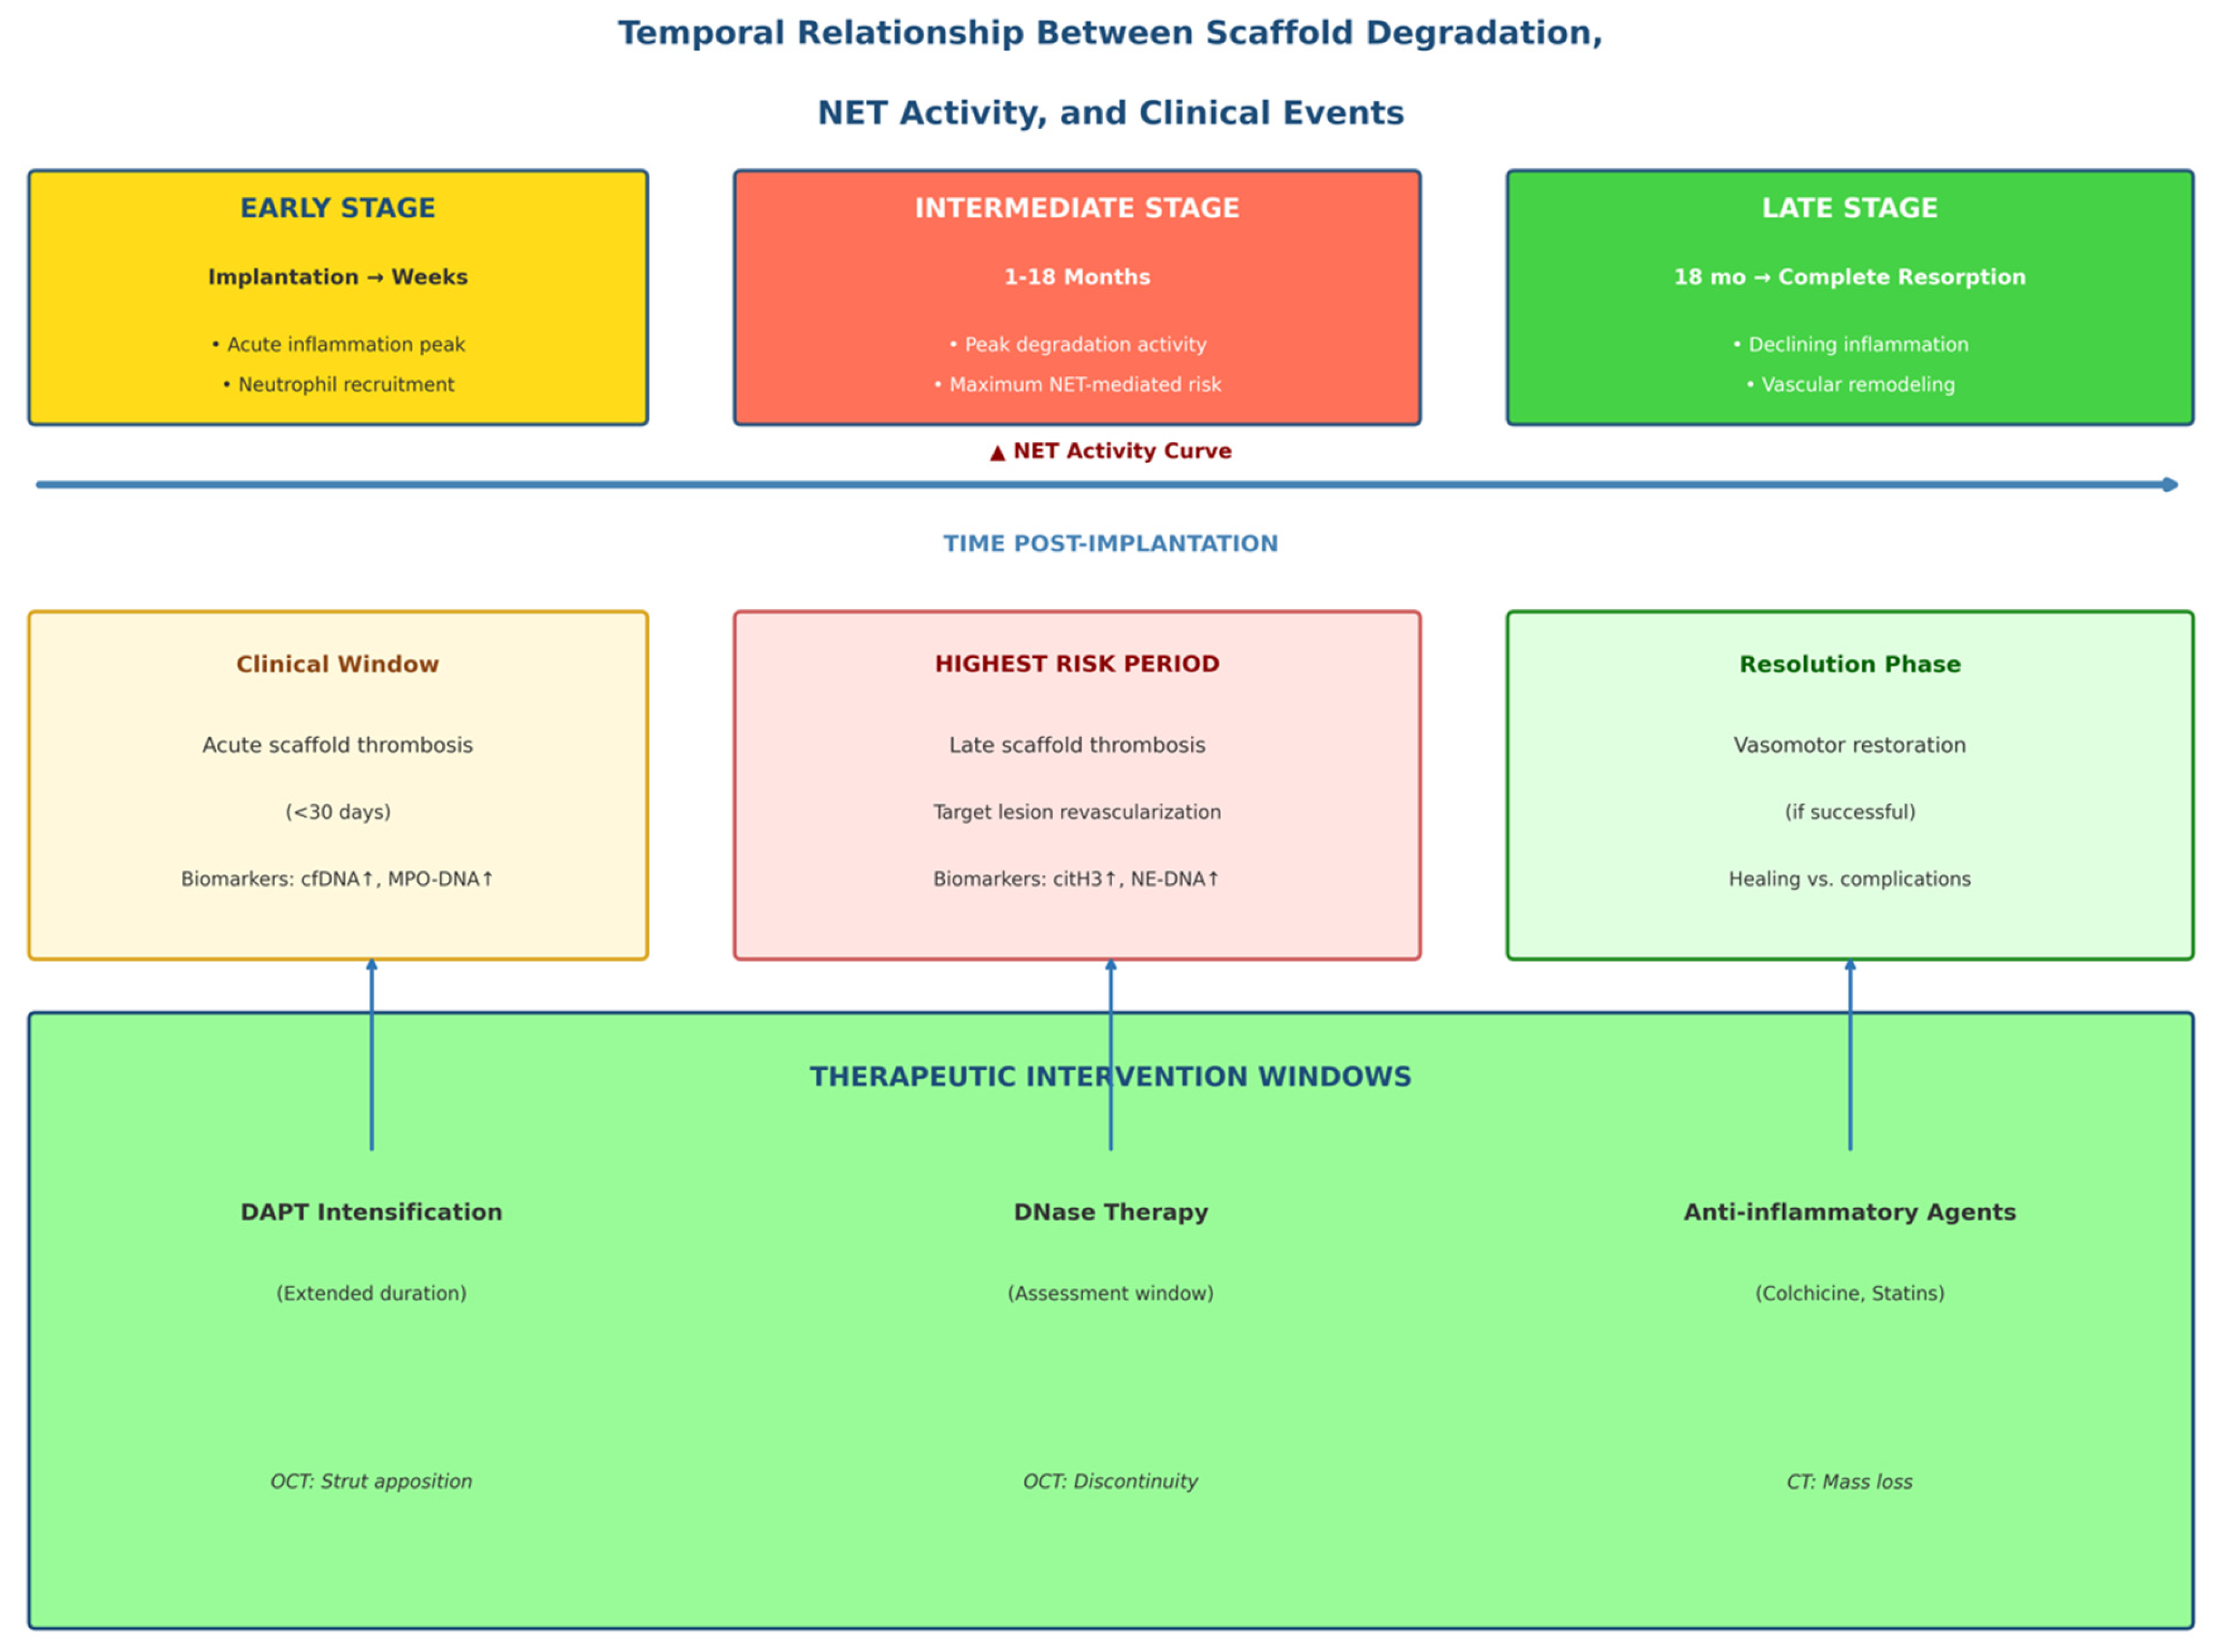
To place NET-mediated processes within a clinically meaningful temporal framework, Figure 3 illustrates the evolving relationship between scaffold degradation, NET activity, biomarker dynamics, and device-related clinical events at different stages post-implantation.
Figure 3.
Temporal relationship between scaffold deterioration, NET activity, and clinical events. Timeline-style diagram showing the three phases of scaffold–tissue interaction. Early Stage (implantation → weeks): Acute inflammation peak; neutrophil recruitment due to procedural trauma; initial protein adsorption and foreign body response; elevation in basal NET activity; clinical window for acute scaffold thrombosis (<30 days). Biomarker overlap: elevated cfDNA, MPO-DNA. Imaging window: OCT for strut apposition. Intermediate Stage (1–18 months): Peak degradation activity; sustained inflammatory cell infiltration; maximum NET-mediated thrombogenic risk; heterogeneous scaffold discontinuity; bulk erosion of polymer matrix. Biomarker overlap: citH3, NE-DNA complexes. Clinical events: late scaffold thrombosis, target lesion revascularization. Late Stage (18 months → complete resorption): Declining inflammation; Progressive scaffold mass loss; vascular remodeling; restoration of vasomotor function (if successful). Clinical outcome: healing vs. persistent complications. The treatment intervention timeline indicates optimal time intervals for DAPT intensification, DNase therapy assessment, anti-inflammatory agents, surface modification effects.
The integration of NET biology into BRS development opens up various avenues for future research and device optimization. Next-generation scaffold design should incorporate immunological considerations in addition to traditional mechanical and chemical optimization. This may involve systematically screening the NETogenic potential of candidate materials during preclinical development using standardized in vitro tests and appropriate animal models [85,86].
Reducing support thickness through improved materials and fabrication techniques can reduce inflammatory stimulation while maintaining mechanical performance [87]. Advances in layered fabrication allow for complex geometries that can distribute mechanical stress more homogeneously and reduce localized inflammation [28]. Hybrid scaffold designs combining the advantages of different materials, such as metallic cores and polymeric coatings, offer additional possibilities to optimize both mechanical and biological performance [27].
Personalized approaches to scaffold selection and adjuvant therapy present another frontier. Patients with high baseline NET markers or genetic variants affecting NETosis pathways may benefit from intensified anti-inflammatory therapy or alternative revascularization strategies. The development of point-of-care NET tests can enable real-time risk stratification and treatment optimization.
Finally, lessons learned from the BRS development process regarding immune responses to degradable materials have implications beyond cardiovascular devices. Similar principles apply to other implantable medical devices, tissue engineering scaffolds, and drug delivery systems. A deeper understanding of NET–biomaterial interactions can shed light on the design of next-generation implantable devices in multiple therapeutic areas [88]. To highlight the environmental significance of NET biology for scaffold therapy, Table 3 summarizes NET-related clinical complications, potential monitoring strategies, and the current state of clinical evidence.
Table 3.
Clinical Effects and Monitoring Strategies Associated with NET in Scaffold Therapy.
9. Conclusions
The interaction between neutrophil extracellular traps and bioresorbable scaffolds represents a significant and understudied aspect of device biocompatibility. Evidence increasingly suggests that NETosis contributes to scaffold-related complications, including thrombosis, delayed healing, and heterogeneous degradation. Understanding these immunological mechanisms is essential for the development of next-generation scaffolds that deliver on the promise of transient mechanical support followed by complete, seamless absorption. Therapeutic strategies targeting NET pathways, including DNase enzymes, PAD4 inhibitors, and anti-inflammatory agents, offer potential approaches to mitigate NET-mediated complications. Device-centric strategies focusing on surface engineering and material selection can reduce the NETogenic potential of scaffolds at the source. The optimal approach likely combines both systemic and local interventions tailored to individual patient risk profiles.
Future research should prioritize the standardization of NET measurement methodologies, the systematic characterization of NET–material interactions for candidate scaffold materials, and the integration of NET biomarkers into clinical trial outcome points. Collaboration among immunologists, materials scientists, and interventional cardiologists will be essential to translate these findings into improved clinical outcomes for patients receiving bioresorbable vascular scaffolds.
Author Contributions
R.D. and N.A. designed the study, drafted the manuscript, and supervised and edited it. N.A. wrote the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study.
Acknowledgments
We thank the reviewers for their valuable feedback which helped improve the manuscript.
Conflicts of Interest
R.D. serve as president of the INVAMED Institute for Medical Innovation. N.A. is retired and works as a volunteer consultant for Med-International UK Health Agency Ltd.
References
- Iqbal, J.; Serruys, P.W.; Silber, S.; Kelbaek, H.; Richardt, G.; Morel, M.-A.; Negoita, M.; Buszman, P.E.; Windecker, S. Comparison of Zotarolimus- and Everolimus-Eluting Coronary Stents. Circ. Cardiovasc. Interv. 2015, 8, e002230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mauri, L.; Kereiakes, D.J.; Yeh, R.W.; Driscoll-Shempp, P.; Cutlip, D.E.; Steg, P.G.; Normand, S.-L.T.; Braunwald, E.; Wiviott, S.D.; Cohen, D.J.; et al. Twelve or 30 Months of Dual Antiplatelet Therapy After Drug-Eluting Stents. N. Engl. J. Med. 2014, 371, 2155–2166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Serruys, P.W.; Garcia-Garcia, H.M.; Onuma, Y. From Metallic Cages to Transient Bioresorbable Scaffolds: Change in Paradigm of Coronary Revascularization in the Upcoming Decade? Eur. Heart J. 2011, 33, 16–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Serruys, P.W.; Chevalier, B.; Dudek, D.; Cequier, A.; Carrié, D.; Iniguez, A.; Dominici, M.; van der Schaaf, R.J.; Wasungu, L.; Veldhof, S.; et al. A Bioresorbable Everolimus-Eluting Scaffold Versus a Metallic Everolimus-Eluting Stent for Ischaemic Heart Disease Caused by De-Novo Native Coronary Artery Lesions (ABSORB II): An Interim 1-Year Analysis of Clinical and Procedural Secondary Outcomes from a Randomised Controlled Trial. Lancet 2015, 385, 43–54. [Google Scholar] [CrossRef] [Scilit]
- Stone, G.W.; Abizaid, A.; Onuma, Y.; Seth, A.; Gao, R.; Ormiston, J.; Kimura, T.; Chevalier, B.; Ben-Yehuda, O.; Dressler, O.; et al. Effect of Technique on Outcomes Following Bioresorbable Vascular Scaffold Implantation. J. Am. Coll. Cardiol. 2017, 70, 2863–2874. [Google Scholar] [CrossRef] [Scilit]
- Xie, Y.; Chi, M.; Yang, X.; Dong, R.; Yang, A.; Yin, A.; Weng, Y. FeMOFs/CO Loading Reduces NETosis and Macrophage Inflammatory Response in PLA Based Cardiovascular Stent Materials. Regen. Biomater. 2024, 12, rbae140. [Google Scholar] [CrossRef] [Scilit]
- Onuma, Y.; Serruys, P.W. Bioresorbable Scaffold. Circulation 2011, 123, 779–797. [Google Scholar] [CrossRef] [Scilit]
- Puricel, S.; Cuculi, F.; Weissner, M.; Schmermund, A.; Jamshidi, P.; Nyffenegger, T.; Binder, H.; Eggebrecht, H.; Münzel, T.; Cook, S.; et al. Bioresorbable Coronary Scaffold Thrombosis: Multicenter Comprehensive Analysis of Clinical Presentation, Mechanisms, and Predictors. J. Am. Coll. Cardiol. 2016, 67, 921–931. [Google Scholar] [CrossRef] [Scilit]
- Borissoff, J.I.; Joosen, I.A.; Versteylen, M.O.; Brill, A.; Fuchs, T.A.; Savchenko, A.S.; Gallant, M.; Martinod, K.; ten Cate, H.; Hofstra, L.; et al. Elevated Levels of Circulating DNA and Chromatin Are Independently Associated with Severe Coronary Atherosclerosis and a Prothrombotic State. Arterioscler. Thromb. Vasc. Biol. 2013, 33, 2032–2040. [Google Scholar] [CrossRef] [Scilit]
- Adamidis, P.; Pantazi, D.; Moschonas, I.; Liberopoulos, E.; Tselepis, A. Neutrophil Extracellular Traps (NETs) and Atherosclerosis: Does Hypolipidemic Treatment Have an Effect? J. Cardiovasc. Dev. Dis. 2024, 11, 72. [Google Scholar] [CrossRef] [Scilit]
- Ardic, N.; Dinc, R. Neutrophil Extracellular Traps and Microglia/Macrophages Interactions in Stroke: From Thromboinflammation to Immunotherapy. Front. Immunol. 2026, 17, 1752471. [Google Scholar] [CrossRef] [Scilit]
- Riegger, J.; Byrne, R.A.; Joner, M.; Chandraratne, S.; Gershlick, A.H.; Berg, J.M.T.; Adriaenssens, T.; Guagliumi, G.; Godschalk, T.C.; Neumann, F.-J.; et al. Histopathological Evaluation of Thrombus in Patients Presenting with Stent Thrombosis. A Multicenter European Study: A Report of the Prevention of Late Stent Thrombosis by an Interdisciplinary Global European Effort Consortium. Eur. Heart J. 2015, 37, 1538–1549. [Google Scholar] [CrossRef] [Scilit]
- Stakos, D.A.; Kambas, K.; Konstantinidis, T.; Mitroulis, I.; Apostolidou, E.; Arelaki, S.; Tsironidou, V.; Giatromanolaki, A.; Skendros, P.; Konstantinides, S.; et al. Expression of Functional Tissue Factor by Neutrophil Extracellular Traps in Culprit Artery of Acute Myocardial Infarction. Eur. Heart J. 2015, 36, 1405–1414. [Google Scholar] [CrossRef] [Scilit]
- McMahon, S.; Bertollo, N.; Cearbhaill, E.D.O.; Salber, J.; Pierucci, L.; Duffy, P.; Dürig, T.; Bi, V.; Wang, W. Bio-Resorbable Polymer Stents: A Review of Material Progress and Prospects. Prog. Polym. Sci. 2018, 83, 79–96. [Google Scholar] [CrossRef] [Scilit]
- Forrestal, B.; Case, B.C.; Yerasi, C.; Musallam, A.; Chezer-Azerrad, C.; Waksman, R. Bioresorbable Scaffolds: Current Technology and Future Perspectives. Rambam Maimonides Med. J. 2020, 11, e0016. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onuma, Y.; Serruys, P.W.; Perkins, L.; Okamura, T.; Gonzalo, N.; Garcia-Garcia, H.M.; Regar, E.; Kamberi, M.; Powers, J.; Rapoza, R.; et al. Intracoronary Optical Coherence Tomography and Histology at 1 Month and 2, 3, and 4 Years after Implantation of Everolimus-Eluting Bioresorbable Vascular Scaffolds in a Porcine Coronary Artery Model. Circulation 2010, 122, 2288–2300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haude, M.; Ince, H.; Abizaid, A.; Toelg, R.; Lemos, P.A.; von Birgelen, C.; Christiansen, E.H.; Wijns, W.; Neumann, F.-J.; Kaiser, C.; et al. Safety and Performance of the Second-Generation Drug-Eluting Absorbable Metal Scaffold in Patients with De-Novo Coronary Artery Lesions (BIOSOLVE-II): 6 Month Results of a Prospective, Multicentre, Non-Randomised, First-In-Man Trial. Lancet 2016, 387, 31–39. [Google Scholar] [CrossRef] [Scilit]
- Haude, M.; Ince, H.; Kische, S.; Toelg, R.; Van, N.M.; Verheye, S.; von Birgelen, C.; Christiansen, E.H.; Barbato, E.; Garcia-Garcia, H.M.; et al. Sustained Safety and Performance of the Second-Generation Sirolimus-Eluting Absorbable Metal Scaffold: Pooled Outcomes of the BIOSOLVE-II and -III Trials at 3 Years. Cardiovasc. Revascularization Med. 2020, 21, 1150–1154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dobrzyńska-Mizera, M.; Dodda, J.M.; Liu, X.; Knitter, M.; Oosterbeek, R.N.; Salinas, P.; Pozo, E.; Ferreira, A.M.; Sadiku, E.R. Engineering of Bioresorbable Polymers for Tissue Engineering and Drug Delivery Applications. Adv. Healthc. Mater. 2024, 13, e2401674. [Google Scholar] [CrossRef] [Scilit]
- Capuana, E.; Lopresti, F.; Ceraulo, M.; La Carrubba, V. Poly-l-Lactic Acid (PLLA)-Based Biomaterials for Regenerative Medicine: A Review on Processing and Applications. Polymers 2022, 14, 1153. [Google Scholar] [CrossRef] [Scilit]
- Erbel, R.; Di Mario, C.; Bartunek, J.; Bonnier, J.; de Bruyne, B.; Eberli, F.R.; Erne, P.; Haude, M.; Heublein, B.; Horrigan, M.; et al. Temporary Scaffolding of Coronary Arteries with Bioabsorbable Magnesium Stents: A Prospective, Non-Randomised Multicentre Trial. Lancet 2007, 369, 1869–1875. [Google Scholar] [CrossRef] [Scilit]
- Zberg, B.; Uggowitzer, P.J.; Löffler, J.F. MgZnCa Glasses without Clinically Observable Hydrogen Evolution for Biodegradable Implants. Nat. Mater. 2009, 8, 887–891. [Google Scholar] [CrossRef] [Scilit]
- Bowen, P.K.; Drelich, J.; Goldman, J. Zinc Exhibits Ideal Physiological Corrosion Behavior for Bioabsorbable Stents. Adv. Mater. 2013, 25, 2577–2582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Venezuela, J.; Dargusch, M.S. The Influence of Alloying and Fabrication Techniques on the Mechanical Properties, Biodegradability and Biocompatibility of Zinc: A Comprehensive Review. Acta Biomater. 2019, 87, 1–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, Y.F.; Gu, X.N.; Witte, F. Biodegradable Metals. Mater. Sci. Eng. R Rep. 2014, 77, 1–34. [Google Scholar] [CrossRef] [Scilit]
- Kraus, T.; Fischerauer, S.; Hänzi, A.C.; Uggowitzer, P.J.; Löffler, J.F.; Weinberg, A. Magnesium Alloys for Temporary Implants in Osteosynthesis: In Vivo Studies of Their Degradation and Interaction with Bone. Acta Biomater. 2012, 8, 1230–1238. [Google Scholar] [CrossRef] [Scilit]
- Bourazana, A.; Briasoulis, A.; Kourek, C.; Kuno, T.; Leventis, I.; Pantsios, C.; Androutsopoulou, V.; Spiliopoulos, K.; Giamouzis, G.; Skoularigis, J.; et al. Bioresorbable Scaffolds for Coronary Revascularization: From Concept to Clinical Maturity. J. Cardiovasc. Dev. Dis. 2025, 13, 2. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Shi, Y.; Lu, Y.; Li, X.; Zhou, J.; Zadpoor, A.A.; Wang, L. Additive Manufacturing of Vascular Stents. Acta Biomater. 2023, 167, 16–37. [Google Scholar] [CrossRef] [Scilit]
- Yao, S.; Yan, H.; Tian, S.; Luo, R.; Zhao, Y.; Wang, J. Anti-Fouling Coatings for Blood-Contacting Devices. Smart Mater. Med. 2024, 5, 166–180. [Google Scholar] [CrossRef] [Scilit]
- Ishihara, K. Blood-Compatible Surfaces with Phosphorylcholine-Based Polymers for Cardiovascular Medical Devices. Langmuir 2018, 35, 1778–1787. [Google Scholar] [CrossRef] [Scilit]
- Ali, Z.A.; Serruys, P.W.; Kimura, T.; Gao, R.; Ellis, S.G.; Kereiakes, D.J.; Onuma, Y.; Simonton, C.A.; Zhang, Z.; Stone, G.W. 2-Year Outcomes with the Absorb Bioresorbable Scaffold for Treatment of Coronary Artery Disease: A Systematic Review and Meta-Analysis of Seven Randomised Trials with an Individual Patient Data Substudy. Lancet 2017, 390, 760–772. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bangalore, S.; Bezerra, H.G.; Rizik, D.G.; Armstrong, E.J.; Samuels, B.; Naidu, S.S.; Grines, C.L.; Foster, M.T.; Choi, J.W.; Bertolet, B.D.; et al. The State of the Absorb Bioresorbable Scaffold. JACC Cardiovasc. Interv. 2017, 10, 2349–2359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ellis, S.G.; Kereiakes, D.J.; Metzger, D.C.; Caputo, R.P.; Rizik, D.G.; Teirstein, P.S.; Litt, M.R.; Kini, A.; Kabour, A.; Marx, S.O.; et al. Everolimus-Eluting Bioresorbable Scaffolds for Coronary Artery Disease. N. Engl. J. Med. 2015, 373, 1905–1915. [Google Scholar] [CrossRef] [Scilit]
- Sotomi, Y.; Suwannasom, P.; Serruys, P.; Onuma, Y. Possible Mechanical Causes of Scaffold Thrombosis: Insights from Case Reports with Intracoronary Imaging. EuroIntervention 2017, 12, 1747–1756. [Google Scholar] [CrossRef] [Scilit]
- Yamaji, K.; Ueki, Y.; Souteyrand, G.; Daemen, J.; Wiebe, J.; Nef, H.; Adriaenssens, T.; Loh, J.P.; Lattuca, B.; Wykrzykowska, J.J.; et al. Mechanisms of Very Late Bioresorbable Scaffold Thrombosis: The INVEST Registry. J. Am. Coll. Cardiol. 2017, 70, 2330–2344. [Google Scholar] [CrossRef] [Scilit]
- Wang, H.; Kim, S.J.; Lei, Y.; Wang, S.; Wang, H.; Huang, H.; Zhang, H.; Tsung, A. Neutrophil Extracellular Traps in Homeostasis and Disease. Signal Transduct. Target. Ther. 2024, 9, 235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kolaczkowska, E.; Kubes, P. Neutrophil Recruitment and Function in Health and Inflammation. Nat. reviews. Immunol. 2013, 13, 159–175. [Google Scholar] [CrossRef] [Scilit]
- Fuchs, T.A.; Abed, U.; Goosmann, C.; Hurwitz, R.; Schulze, I.; Wahn, V.; Weinrauch, Y.; Brinkmann, V.; Zychlinsky, A. Novel Cell Death Program Leads to Neutrophil Extracellular Traps. J. Cell Biol. 2007, 176, 231–241. [Google Scholar] [CrossRef] [Scilit]
- Dinc, R.; Ardic, N. Molecular and Cellular Mechanisms of Neutrophil Extracellular Traps in Cardiovascular Diseases: From NET Formation to Mechanistic Therapeutic Targeting. Biocell 2025, 50, 5. [Google Scholar] [CrossRef] [Scilit]
- Papayannopoulos, V.; Metzler, K.D.; Hakkim, A.; Zychlinsky, A. Neutrophil Elastase and Myeloperoxidase Regulate the Formation of Neutrophil Extracellular Traps. J. Cell Biol. 2010, 191, 677–691. [Google Scholar] [CrossRef] [Scilit]
- Duewell, P.; Kono, H.; Rayner, K.J.; Sirois, C.M.; Vladimer, G.; Bauernfeind, F.G.; Abela, G.S.; Franchi, L.; Nuñez, G.; Schnurr, M.; et al. NLRP3 Inflamasomes Are Required for Atherogenesis and Activated by Cholesterol Crystals That Form Early in Disease. Nature 2010, 464, 1357–1361. [Google Scholar] [CrossRef] [Scilit]
- Xu, X.; Wu, Y.; Xu, S.; Yin, Y.; Ageno, W.; De Stefano, V.; Zhao, Q.; Qi, X. Clinical Significance of Neutrophil Extracellular Traps Biomarkers in Thrombosis. Thromb. J. 2022, 20, 63. [Google Scholar] [CrossRef] [Scilit]
- Stoimenou, M.; Tzoros, G.; Skendros, P.; Chrysanthopoulou, A. Methods for the Assessment of NET Formation: From Neutrophil Biology to Translational Research. Int. J. Mol. Sci. 2022, 23, 15823. [Google Scholar] [CrossRef] [Scilit]
- Barbu, E.; Dominical, V.; Mendelsohn, L.; Thein, S. An Imaging Flow Cytometry Method to Measure Citrullination of H4 Histone as a Read-out for Neutrophil Extracellular Traps Formation. Bio Protoc. 2021, 11, e3927. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fuchs, T.A.; Brill, A.; Duerschmied, D.; Schatzberg, D.; Monestier, M.; Myers, D.D.; Wrobleski, S.K.; Wakefield, T.W.; Hartwig, J.H.; Wagner, D.D. Extracellular DNA Traps Promote Thrombosis. Proc. Natl. Acad. Sci. USA 2010, 107, 15880–15885. [Google Scholar] [CrossRef] [Scilit]
- Martinod, K.; Wagner, D.D. Thrombosis: Tangled up in NETs. Blood 2014, 123, 2768–2776. [Google Scholar] [CrossRef] [Scilit]
- Massberg, S.; Grahl, L.; von Bruehl, M.-L.; Manukyan, D.; Pfeiler, S.; Goosmann, C.; Brinkmann, V.; Lorenz, M.; Bidzhekov, K.; Khandagale, A.B.; et al. Reciprocal Coupling of Coagulation and Innate Immunity via Neutrophil Serine Proteases. Nat. Med. 2010, 16, 887–896. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mangold, A.; Alias, S.; Scherz, T.; Hofbauer, T.; Jakowitsch, J.; Panzenböck, A.; Simon, D.; Laimer, D.; Bangert, C.; Kammerlander, A.; et al. Coronary Neutrophil Extracellular Trap Burden and Deoxyribonuclease Activity in ST-Elevation Acute Coronary Syndrome Are Predictors of ST-Segment Resolution and Infarct Size. Circ. Res. 2015, 116, 1182–1192. [Google Scholar] [CrossRef] [Scilit]
- Helseth, R.; Solheim, S.; Arnesen, H.; Seljeflot, I.; Opstad, T.B. The Time Course of Markers of Neutrophil Extracellular Traps in Patients Undergoing Revascularisation for Acute Myocardial Infarction or Stable Angina Pectoris. Mediat. Inflamm. 2016, 2016, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Teeling, P.; Mackaay, C.; Ploegmakers, H.; van der Loos, C.; Daemen, M.; de Winter, R.; van der Wal, A.; de Boer, O. Neutrophils, Neutrophil Extracellular Traps and Interleukin-17 Associate with the Organisation of Thrombi in Acute Myocardial Infarction. Thromb. Haemost. 2013, 109, 290–297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saffarzadeh, M.; Juenemann, C.; Queisser, M.A.; Lochnit, G.; Barreto, G.; Galuska, S.P.; Lohmeyer, J.; Preissner, K.T. Neutrophil Extracellular Traps Directly Induce Epithelial and Endothelial Cell Death: A Predominant Role of Histones. PLoS ONE 2012, 7, e32366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ushakumari, C.J.; Zhou, Q.L.; Wang, Y.-H.; Na, S.; Rigor, M.C.; Zhou, C.Y.; Kroll, M.K.; Lin, B.D.; Jiang, Z.Y. Neutrophil Elastase Increases Vascular Permeability and Leukocyte Transmigration in Cultured Endothelial Cells and Obese Mice. Cells 2022, 11, 2288. [Google Scholar] [CrossRef] [Scilit]
- Dinc, R.; Ardic, N. Bioinspired Coronary Stents: A Technological Perspective on Exosome-Mimetic Nanoengineering and Mini-Review of Existing Platforms. Rev. Cardiovasc. Med. 2025, 26, 42781. [Google Scholar] [CrossRef] [Scilit]
- Fernandez-Medina, T.; Vaquette, C.; Gomez-Cerezo, M.N.; Ivanovski, S. Characterization of the Protein Corona of Three Chairside Hemoderivatives on Melt Electrowritten Polycaprolactone Scaffolds. Int. J. Mol. Sci. 2023, 24, 6162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abaricia, J.O.; Shah, A.H.; Chaubal, M.; Hotchkiss, K.M.; Olivares-Navarrete, R. Wnt Signaling Modulates Macrophage Polarization and Is Regulated by Biomaterial Surface Properties. Biomaterials 2020, 243, 119920. [Google Scholar] [CrossRef] [Scilit]
- Shahzad, A.; Ni, Y.; Yang, Y.; Liu, W.; Teng, Z.; Bai, H.; Liu, X.; Sun, Y.; Xia, J.; Cui, K.; et al. Neutrophil Extracellular Traps (NETs) in Health and Disease. Mol. Biomed. 2025, 6, 130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selders, G.S.; Fetz, A.E.; Radic, M.Z.; Bowlin, G.L. An Overview of the Role of Neutrophils in Innate Immunity, Inflammation and Host-Biomaterial Integration. Regen. Biomater. 2017, 4, 55–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bergsma, J. Late Degradation Tissue Response to Poly(?-Lactide) Bone Plates and Screws. Biomaterials 1995, 16, 25–31. [Google Scholar] [CrossRef] [Scilit]
- Lyu, S.; Untereker, D. Degradability of Polymers for Implantable Biomedical Devices. Int. J. Mol. Sci. 2009, 10, 4033–4065. [Google Scholar] [CrossRef] [Scilit]
- Chu, C.C. Degradation Phenomena of Two Linear Aliphatic Polyester Fibres Used in Medicine and Surgery. Polymer 1985, 26, 591–594. [Google Scholar] [CrossRef] [Scilit]
- Xin, Y.; Hu, T.; Chu, P.K. In Vitro Studies of Biomedical Magnesium Alloys in a Simulated Physiological Environment: A Review. Acta Biomater. 2011, 7, 1452–1459. [Google Scholar] [CrossRef] [Scilit]
- Zhou, Y.; Xu, Z.; Liu, Z. Impact of Neutrophil Extracellular Traps on Thrombosis Formation: New Findings and Future Perspective. Front. Cell. Infect. Microbiol. 2022, 12, 910908. [Google Scholar] [CrossRef] [Scilit]
- Gupta, A.K.; Joshi, M.B.; Philippova, M.; Erne, P.; Hasler, P.; Hahn, S.; Resink, T.J. Activated Endothelial Cells Induce Neutrophil Extracellular Traps and Are Susceptible to NETosis-Mediated Cell Death. FEBS Lett. 2010, 584, 3193–3197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Räber, L.; Koskinas, K.C.; Yamaji, K.; Taniwaki, M.; Roffi, M.; Holmvang, L.; Garcia Garcia, H.M.; Zanchin, T.; Maldonado, R.; Moschovitis, A.; et al. Changes in Coronary Plaque Composition in Patients with Acute Myocardial Infarction Treated with High-Intensity Statin Therapy (IBIS-4). JACC Cardiovasc. Imaging 2019, 12, 1518–1528. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joner, M.; Finn, A.V.; Farb, A.; Mont, E.K.; Kolodgie, F.D.; Ladich, E.; Kutys, R.; Skorija, K.; Gold, H.K.; Virmani, R. Pathology of Drug-Eluting Stents in Humans: Delayed Healing and Late Thrombotic Risk. J. Am. Coll. Cardiol. 2006, 48, 193–202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kotani, J.; Awata, M.; Nanto, S.; Uematsu, M.; Oshima, F.; Minamiguchi, H.; Mintz, G.S.; Nagata, S. Incomplete Neointimal Coverage of Sirolimus-Eluting Stents. J. Am. Coll. Cardiol. 2006, 47, 2108–2111. [Google Scholar] [CrossRef] [Scilit]
- Dinc, R.; Ardic, N. AI-Driven Decision Making for Intravascular Device Selection in Aortic Disease. Current Insights and Prospects. Front. Cardiovasc. Med. 2025, 12, 1585299. [Google Scholar] [CrossRef] [Scilit]
- Hally, K.E.; Parker, O.M.; Brunton-O’Sullivan, M.M.; Harding, S.A.; Larsen, P.D. Linking Neutrophil Extracellular Traps and Platelet Activation: A Composite Biomarker Score for Predicting Outcomes after Acute Myocardial Infarction. Thromb. Haemost. 2021, 121, 1637–1649. [Google Scholar] [CrossRef] [Scilit]
- Cui, M.; Fan, M.; Jing, R.; Wang, H.; Qin, J.; Sheng, H.; Wang, Y.; Wu, X.; Zhang, L.; Zhu, J.; et al. Cell-Free Circulating DNA: A New Biomarker for the Acute Coronary Syndrome. Cardiology 2013, 124, 76–84. [Google Scholar] [CrossRef] [Scilit]
- Prati, F.; Regar, E.; Mintz, G.S.; Arbustini, E.; Di Mario, C.; Jang, I.-K.; Akasaka, T.; Costa, M.; Guagliumi, G.; Grube, E.; et al. Expert Review Document on Methodology, Terminology, and Clinical Applications of Optical Coherence Tomography: Physical Principles, Methodology of Image Acquisition, and Clinical Application for Assessment of Coronary Arteries and Atherosclerosis. Eur. Heart J. 2010, 31, 401–415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ntziachristos, V.; Ripoll, J.; Wang, L.V.; Weissleder, R. Looking and Listening to Light: The Evolution of Whole-Body Photonic Imaging. Nat. Biotechnol. 2005, 23, 313–320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Savchenko, A.S.; Borissoff, J.I.; Martinod, K.; De Meyer, S.F.; Gallant, M.; Erpenbeck, L.; Brill, A.; Wang, Y.; Wagner, D.D. VWF-Mediated Leukocyte Recruitment with Chromatin Decondensation by PAD4 Increases Myocardial Ischemia/Reperfusion Injury in Mice. Blood 2014, 123, 141–148. [Google Scholar] [CrossRef] [Scilit]
- Ge, L.; Zhou, X.; Ji, W.-J.; Lu, R.-Y.; Zhang, Y.; Zhang, Y.-D.; Ma, Y.-Q.; Zhao, J.-H.; Li, Y.-M. Neutrophil Extracellular Traps in Ischemia-Reperfusion Injury-Induced Myocardial No-Reflow: Therapeutic Potential of DNase-Based Reperfusion Strategy. Am. J. Physiology. Heart Circ. Physiol. 2015, 308, H500–H509. [Google Scholar] [CrossRef] [Scilit]
- Razia, S.; Takeshita, H.; Inoue, K.; Iida, R.; Ueki, M.; Yasuda, T. Unveiling Human DNase II: Molecular Characterizations, Gene Insights and Functional Implications. Leg. Med. 2024, 71, 102505. [Google Scholar] [CrossRef] [Scilit]
- Martinod, K.; Demers, M.; Fuchs, T.A.; Wong, S.L.; Brill, A.; Gallant, M.; Hu, J.; Wang, Y.; Wagner, D.D. Neutrophil Histone Modification by Peptidylarginine Deiminase 4 Is Critical for Deep Vein Thrombosis in Mice. Proc. Natl. Acad. Sci. USA 2013, 110, 8674–8679. [Google Scholar] [CrossRef] [Scilit]
- Lewis, H.D.; Liddle, J.; Coote, J.E.; Atkinson, S.J.; Barker, M.D.; Bax, B.D.; Bicker, K.L.; Bingham, R.P.; Campbell, M.; Chen, Y.H.; et al. Inhibition of PAD4 Activity Is Sufficient to Disrupt Mouse and Human NET Formation. Nat. Chem. Biol. 2015, 11, 189–191. [Google Scholar] [CrossRef] [Scilit]
- Holthaus, M.; Xiong, X.; Eghbalzadeh, K.; Großmann, C.; Geißen, S.; Piontek, F.; Mollenhauer, M.; Abdallah, A.T.; Kamphausen, T.; Rothschild, M.; et al. Loss of Peptidylarginine Deiminase 4 Mitigates Maladaptive Cardiac Remodeling after Myocardial Infarction through Inhibition of Inflammatory and Profibrotic Pathways. Transl. Res. 2025, 280, 1–16. [Google Scholar] [CrossRef] [Scilit]
- Molinaro, R.; Yu, M.; Sausen, G.; Bichsel, C.A.; Corbo, C.; Folco, E.J.; Lee, G.Y.; Liu, Y.; Tesmenitsky, Y.; Shvartz, E.; et al. Targeted Delivery of Protein Arginine Deiminase-4 Inhibitors to Limit Arterial Intimal NETosis and Preserve Endothelial Integrity. Cardiovasc. Res. 2021, 117, 2652–2663. [Google Scholar] [CrossRef] [Scilit]
- Leung, Y.Y.; Yao Hui, L.L.; Kraus, V.B. Colchicine—Update on Mechanisms of Action and Therapeutic Uses. Semin. Arthritis Rheum. 2015, 45, 341–350. [Google Scholar] [CrossRef] [Scilit]
- Tardif, J.-C.; Kouz, S.; Waters, D.D.; Bertrand, O.F.; Diaz, R.; Maggioni, A.P.; Pinto, F.J.; Ibrahim, R.; Gamra, H.; Kiwan, G.S.; et al. Efficacy and Safety of Low-Dose Colchicine after Myocardial Infarction. N. Engl. J. Med. 2019, 381, 2497–2505. [Google Scholar] [CrossRef] [Scilit]
- Menegazzo, L.; Scattolini, V.; Cappellari, R.; Bonora, B.M.; Albiero, M.; Bortolozzi, M.; Ceolotto, G.; de Kreutzeberg, S.V.; Avogaro, A.; Fadini, G.P. The Antidiabetic Drug Metformin Blunts NETosis in Vitro and Reduces Circulating NETosis Biomarkers in Vivo. Acta Diabetol. 2018, 55, 593–601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chow, O.A.; von Köckritz-Blickwede, M.; Taylor Bright, A.; Hensler, M.E.; Zinkernagel, A.S.; Cogen, A.L.; Gallo, R.L.; Monestier, M.; Wang, Y.; Glass, C.K.; et al. Statins Enhance Formation of Phagocyte Extracellular Traps. Cell Host Microbe 2010, 8, 445–454. [Google Scholar] [CrossRef] [Scilit]
- Lapponi, M.J.; Carestia, A.; Landoni, V.I.; Rivadeneyra, L.; Etulain, J.; Negrotto, S.; Pozner, R.G.; Schattner, M. Regulation of Neutrophil Extracellular Trap Formation by Anti-Inflammatory Drugs. J. Pharmacol. Exp. Ther. 2013, 345, 430–437. [Google Scholar] [CrossRef] [Scilit]
- Gong, S.; Li, Y.; Yan, K.; Shi, Z.; Leng, J.; Bao, Y.; Ning, K. The Crosstalk between Endothelial Cells, Smooth Muscle Cells, and Macrophages in Atherosclerosis. Int. J. Mol. Sci. 2025, 26, 1457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boehler, R.M.; Graham, J.G.; Shea, L.D. Tissue Engineering Tools for Modulation of the Immune Response. BioTechniques 2011, 51, 239–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valchanov, P.; Yaneva, Y.; Pavlov, S.; Kontny, A.; Dikova, T. The Concept of the Optimal Bioscaffold: Parameters, Problems, and Their Resolution through Additive Manufacturing. Biomedicines 2025, 13, 2688. [Google Scholar] [CrossRef] [Scilit]
- Grundeken, M.J.; Beijk, M.A. A Narrative Review of Ultrathin-Strut Drug-Eluting Stents: The Thinner the Better? Heart Int. 2021, 15, 84. [Google Scholar] [CrossRef] [Scilit]
- You, D.; Lin, L.; Dong, M.; Wu, Y.; Hu, Y.; Hu, X.; Shao, Y.; Xie, Y.; Xu, M.; Chen, G.; et al. Recent Advances in Shape Memory Polymers for Biomedical Applications: Bridging Macro- and Micro-Scale Effects. Smart Mater. Med. 2025, 6, 240–269. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.