


Abstract
Objective: In utero inflammation is associated with bronchopulmonary dysplasia (BPD) in preterm infants. We hypothesized that maternal tobacco exposure (TE) might induce placental neutrophil infiltration, increasing the risk for BPD. Study design: We compared the composite outcome of BPD and death in a prospective pilot study of TE and no-TE mothers and their infants born <32 weeks. Placental neutrophil infiltration was approximated by neutrophil gelatinase-associated lipocalin (NGAL) ELISA, and total RNA expression was analyzed via NanoString© (Seattle, WA, USA). Result: Of 39 enrolled patients, 44% were classified as tobacco exposure. No significant difference was noted in the infant’s composite outcome of BPD or death based on maternal tobacco exposure. NGAL was higher in placentas of TE vs. non-TE mothers (p < 0.05). Placental RNA analysis identified the upregulation of key inflammatory genes associated with maternal tobacco exposure. Conclusion: Tobacco exposure during pregnancy was associated with increased placental neutrophil markers and upregulated inflammatory gene expression. These findings were not associated with BPD.
1. Introduction
Tobacco exposure (TE) during pregnancy is highly prevalent in the United States. As reported by the Center for Disease Control and Prevention (CDC) in 2016, 7.2% of mothers smoked cigarettes during pregnancy [1]. It is well recognized that maternal tobacco use during pregnancy is linked to many negative outcomes for infants, including low birthweights, preterm birth, preterm prolonged rupture of membrane (PPROM), and other birth defects [2,3,4,5].
Recently, Antonucci et al. indicated that in utero exposure to smoking is an independent risk factor for the development of bronchopulmonary dysplasia (BPD) in premature infants born weighing less than 1500 g [6]. BPD is the most prevalent sequela of preterm birth, affecting 10,000–15,000 infants annually in the United States [7]. Known postnatal risk factors for the disease include hyperoxia, mechanical ventilation, patent ductus arteriosus (PDA), and sepsis; antenatal risk factors include chorioamnionitis, preeclampsia, and hypertension [8,9,10,11,12].
Neutrophil gelatinase-associated lipocalin (NGAL) is a glycoprotein found predominantly in neutrophil granules. NGAL is normally expressed at low levels but is often elevated in the blood, bronchoalveolar lavage (BAL) fluid, and sputum in adults with lung diseases, such as asthma and chronic obstructive pulmonary disease (COPD) [13]. Notably, serum levels of NGAL at birth are significantly higher in preterm infants who develop BPD than in those who do not [14], suggesting a potential role for NGAL as a biomarker for BPD.
Little is known about the mechanism by which maternal tobacco exposure is associated with the development of BPD. A previous study demonstrated a higher number of neutrophils within the placentas of mothers who smoked during pregnancy; however, the incidence of bacterial infection in that group was higher, confounding the results [15]. Recent reviews have focused on injury and its contribution to fetal lung development, identifying inflammation and tobacco exposure as major contributors [16]. In addition, a meta-analysis of tobacco smoking during pregnancy showed significant association with BPD at a postmenstrual age of 36 weeks [17]. Finally, the adverse effects of maternal tobacco exposure are supported by epidemiological and animal studies, which demonstrate disrupted pulmonary development [18,19,20]. These observations taken together establish a link between maternal tobacco exposure and BPD and raise the possibility that neutrophils play a key role in the mechanism, with elevated levels in preterm infants who develop BDP.
To further understand the effect of antenatal tobacco exposure and its association with the development of BPD, we compared placental and infant characteristics of tobacco exposure and non-tobacco exposure mothers. Our hypothesis is two-fold; (1) we hypothesized that maternal tobacco exposure would result in increased inflammatory neutrophil infiltration of the placenta of preterm infants <32 weeks gestation, and (2) we hypothesize that infants <32 weeks gestation with tobacco exposure will subsequently be at increased risk for developing BPD. Therefore, we sought to achieve two aims/objectives in our study. The first was to identify increased neutrophil infiltration in the placenta of mothers with tobacco exposure (primary outcome). The second was to follow these infants for the composite outcome of BPD or death (secondary outcome).
2. Materials and Methods
Study design: This pilot prospective, observational study was conducted between October 2018 and December 2019 and was approved by the Institutional Review Board at the University of Oklahoma Health Sciences Center (OUHSC). Written informed consent was obtained for the mother and newborn either prior to delivery or within 24 h post-delivery. Following consent, a 9-item maternal questionnaire for self-identification of tobacco exposure during pregnancy was completed (Figure A1). Our maternal questionnaire on tobacco use was internally validated in a previous study, where cotinine levels (a nicotine metabolite) were detectable only in mothers who reported tobacco exposure [21]. Patients were stratified into two groups: TE mothers and non-TE mothers.
Study population: Participants included mothers and their preterm infants born at a gestational age of <32 weeks. Infants were excluded based on known major congenital anomalies, maternal concern for infection (e.g., clinical chorioamnionitis), maternal fever >38 °C 24 h before delivery, presence of meconium-stained fluid, maternal history of impaired immunity, or a concomitant medical condition impacting inflammatory response.
Data collection: Data were de-identified and prospectively collected and managed using a data collection sheet at OUHSC. Maternal and neonatal demographic characteristics were collected via chart review. The secondary outcome was a composite of BPD or death endpoints. BPD status was assessed at 36 weeks postmenstrual age (PMA) using the National Institutes of Health (NIH) workshop definition [22]. Mild BPD is defined as breathing room air at 36 weeks corrected or time of discharge, moderate BPD is defined as needing <30% oxygen at 36 weeks corrected/discharge, whereas severe BPD is defined as needing >30% O2 at 36 weeks corrected age/discharge. For the purpose of this study, infants were defined as having the presence or absence of BPD; absence of BPD was defined as no or mild BPD, and the presence of BPD was defined as moderate to severe BPD [22]. Additional outcomes included necrotizing enterocolitis (NEC), intraventricular hemorrhage (IVH), retinopathy of prematurity (ROP), PDA, and sepsis. A mother was considered to have received antenatal corticosteroids if she received a full or partial betamethasone or dexamethasone course. Intrauterine growth restriction (IUGR) was defined as intrauterine estimated fetal weight less than the 10th percentile. PPROM was defined as having membranes ruptured for more than 18 h. Samples from the placenta from both groups were evaluated for histological chorioamnionitis by one of two pathologists blinded to maternal tobacco exposure status. Positive tobacco exposure was defined as maternal ‘daily’ to ‘almost daily’ active smoking or ‘daily’ to ‘almost daily’ secondhand smoke exposure, as reported on the maternal tobacco exposure questionnaire (Figure A1).
To determine the contribution of tobacco exposure to the development of BPD, the groups were further subdivided into (1) TE mothers with infants developing BPD (BPD TE group); (2) non-TE mothers with infants developing BPD (BPD No TE group); (3) TE mothers with infants not developing BPD (No BPD TE group); and (4) non-TE mothers with infants not developing BPD (No BPD No TE group).
Sample collection: Fresh placenta tissue samples were collected within 24 h of delivery. Three full-thickness sections of placenta parenchyma (including fetal and maternal surfaces), one section of extraplacental membrane roll, and two sections of the umbilical cord (proximal and distal) were collected and fixed in 10% formalin for routine histopathological examination and diagnosis. One full-thickness section was split and preserved for both RNA analysis (RNAlater™, Invitrogen, Carlsbad, CA, USA) and protein analysis (snap-frozen in liquid nitrogen). All samples were stored at −80 °C until further analysis.
Immunohistochemistry (IHC): IHC was performed according to the manufacturer’s protocols using a Leica Bond-IIITM Polymer Refine Detection System (DS 9800). Formalin-fixed paraffin-embedded (FFPE) tissues were sectioned at the desired thickness (4 µm) and mounted on positively charged slides. The slides were dried overnight at room temperature and incubated at 60 °C for 45 min, followed by deparaffinization and rehydration in an automated multi-stainer (Leica ST5020). Subsequently, slides were transferred to the Leica Bond-IIITM and treated for antigen retrieval at 100 °C for 20 min in a retrieval solution, at either pH 6.0 or 9.0. Endogenous peroxidase was blocked using a peroxidase-blocking reagent, followed by 60 min of incubation with NGAL antibody (Catalog #711280, ThermoFisher Scientific, Waltham, MA, USA) diluted 1:100. Post-primary IgG-linker and/or poly-HRP IgG reagents were used as the secondary antibody. Detection was accomplished via the chromogen 3,3′-diaminobenzidine tetrahydrochloride (DAB), and counterstained with hematoxylin. Completed slides were dehydrated (Leica ST5020) and mounted (Leica MM24). The antibody-specific positive control and negative control (omission of primary antibody) were parallel stained. Additionally, two pathologists blinded to smoking and BPD status semi-quantitatively scored based on anatomical location, with scores from zero to four: score ‘0′ signifying no staining; score ‘1′ for 1–10 positive cells/per high power field (HPF); score ‘2′ for 11–50 positive cells/HPF; score ‘3′ for 51–75 positive cells/HPF; and score ‘4′ for >75/HPF.
Protein analysis and enzyme-linked immunosorbent assay (ELISA): ELISA was used to quantify NGAL (Catalog #036RUO, BioPorto Diagnostics A/S, Hellerup, Denmark) following the manufacturer’s instructions. Briefly, frozen placental tissue was mechanically homogenized using a BeadBeater (Next Advance Inc., Troy, NY, USA) in a buffer containing phosphatase, protease inhibitors (Catalog #524625 and #535140, Millipore, Burlington, MA, USA) and PMSF (Sigma-Aldrich, St. Louis, MO, USA). Results were normalized to total protein concentration determined by bicinchoninic acid (BCA) assay (Catalog #23227, Pierce Biotechnology, Rockford, IL, USA).
Total RNA analysis/NanoString©: A random subset of 12 patients from the four subgroups (n = 3/group): BPD, TE group; BPD, no TE group; no BPD, TE group; and no BPD, no TE group. A BeadBeater was used to homogenize placental tissue mechanically. Total RNA was extracted per the manufacturer’s protocols using a Zymo Quick-RNA MidiPrep kit (Catalog #R1056, Zymo Research, Irvine, CA, USA). Total RNA, between 25 ng and 300 ng, was loaded onto a nCounter® Human Immunology v2 Panel (Catalog #XT-CSO-HIM2-12, NanoString, Seattle, WA, USA). This panel consisted of 594 genes of interest and 15 internal reference genes. Data were analyzed using nCounter Analysis and nCounter Advanced Analysis software. RCC output files were imported into NanoString nSolver 4.0. Default quality control (QC) settings were used to verify the quality of all data (>95% of fields of view [FOV] and binding densities between 0.2 and 0.5). The background was corrected by subtracting the mean value of 8 engineered RNA negative control sequences from the raw counts of all genes. The geometric mean was calculated for the 15 housekeeping genes, and the nine genes with the lowest coefficient of variation were used to normalize the data. Genes with mean normalized counts of less than 50 were excluded from the analysis. The control group was defined as No TE or No BPD No TE for subgroup analysis. Gene expressions are estimated to have a log2-fold change, holding all other variables constant. The 95% confidence intervals (CI) for the log2-fold change and the p values are reported. A 1.2-fold change was selected as the differential threshold.
Given the unpredictable nature of preterm deliveries, we allowed up to 24 h for placenta collection. Once collected, the placenta was immediately placed at 4 °C. The pathologist then collected full-thickness sections and stored these at −80 °C or preserved with RNAlaterTM. Although we allowed up to 24 h for placenta collection in our protocol, the majority of samples were collected within 2–12 h. This methodology allows for collection of high-quality RNA from placentas stored at 4 °C or even room temperature for up to 48 h prior to being transferred to stabilizing solution, such as RNAlaterTM [23].
Statistical methods: Our study is a pilot/preliminary study on a topic where there is little known on the association between inflammation within the placenta and development of BPD in preterm neonates. While we have directional hypotheses, we felt it would be inappropriate to quantify an effect size given the paucity of research on the topic. Descriptive statistics were computed for demographic and clinical variables. Comparisons of categorical variables between patients developing BPD or death and those who did not were evaluated with Fisher’s exact test. Continuous variables were assessed for normality, then compared between groups using a Kruskal–Wallis test or Student’s t-test, as appropriate. Frequencies and percentages were reported for categorical variables across BPD status. Count means and standard deviations are reported for continuous variables. Statistical significance is defined, in all experiments, as p < 0.05.
3. Results
In total, 95 mothers were screened, and 49 mothers were approached for study enrollment based on the inclusion and exclusion criteria. Eight mothers declined and two approached mothers aged out of this study (delivered baby >32 weeks gestation). Demographic characteristics for the remaining 39 patients were stratified by the presence and absence of tobacco exposure (Table 1), as well as by the presence or absence of the composite outcome of BPD or death (Table A1). Of enrolled mothers, 43.6% reported tobacco exposure during pregnancy (Table 1 and Table A2). Of these tobacco exposure mothers, two reported the exposure was via secondhand smoke.
Table 1.
Maternal and Neonatal Demographic Data by Composite Outcome.
No differences in birth weight, birth length, head circumference, gestational age, gender, maternal ethnicity, antenatal steroid, mode of delivery, intubation in delivery room, intubated in NICU, PDA medical or surgical treatment, IVH grade 3 or 4, ROP, IUGR <10th percentile, or death or BPD were noted with maternal tobacco exposure. There was an association with maternal age (p = 0.048), with tobacco exposure mothers being slightly older (Table 1). When comparing tobacco exposure mothers, no differences in diabetes status, maternal hypertension, prolong rupture of membranes, chorioamnionitis, antepartum hemorrhage, marijuana, or other illicit drug use were present (Table 2). No differences in the incidence of NEC, or sepsis based on maternal tobacco exposure were noted.
Table 2.
Maternal Complications and Tobacco Exposure by Composite Outcome.
As expected, infants with the composite outcome of BPD or death had significantly lower (p < 0.001) birth weight, length, head circumference, and gestational age compared with the No BPD group. Additionally, more infants in the composite outcome required intubation in the delivery room (p = 0.001) or the NICU (p < 0.001), required medical management of PDA (p = 0.01), and developed threshold ROP (p = 0.017) compared to the No BPD group (Table A1). The remainder of the maternal and neonatal demographic characteristics did not differ between groups. From the maternal perspective, we found no significant association between tobacco exposure status and maternal complications, with the exception of increased incidence of antepartum hemorrhage in the composite outcome group (p = 0.003) (Table A2).
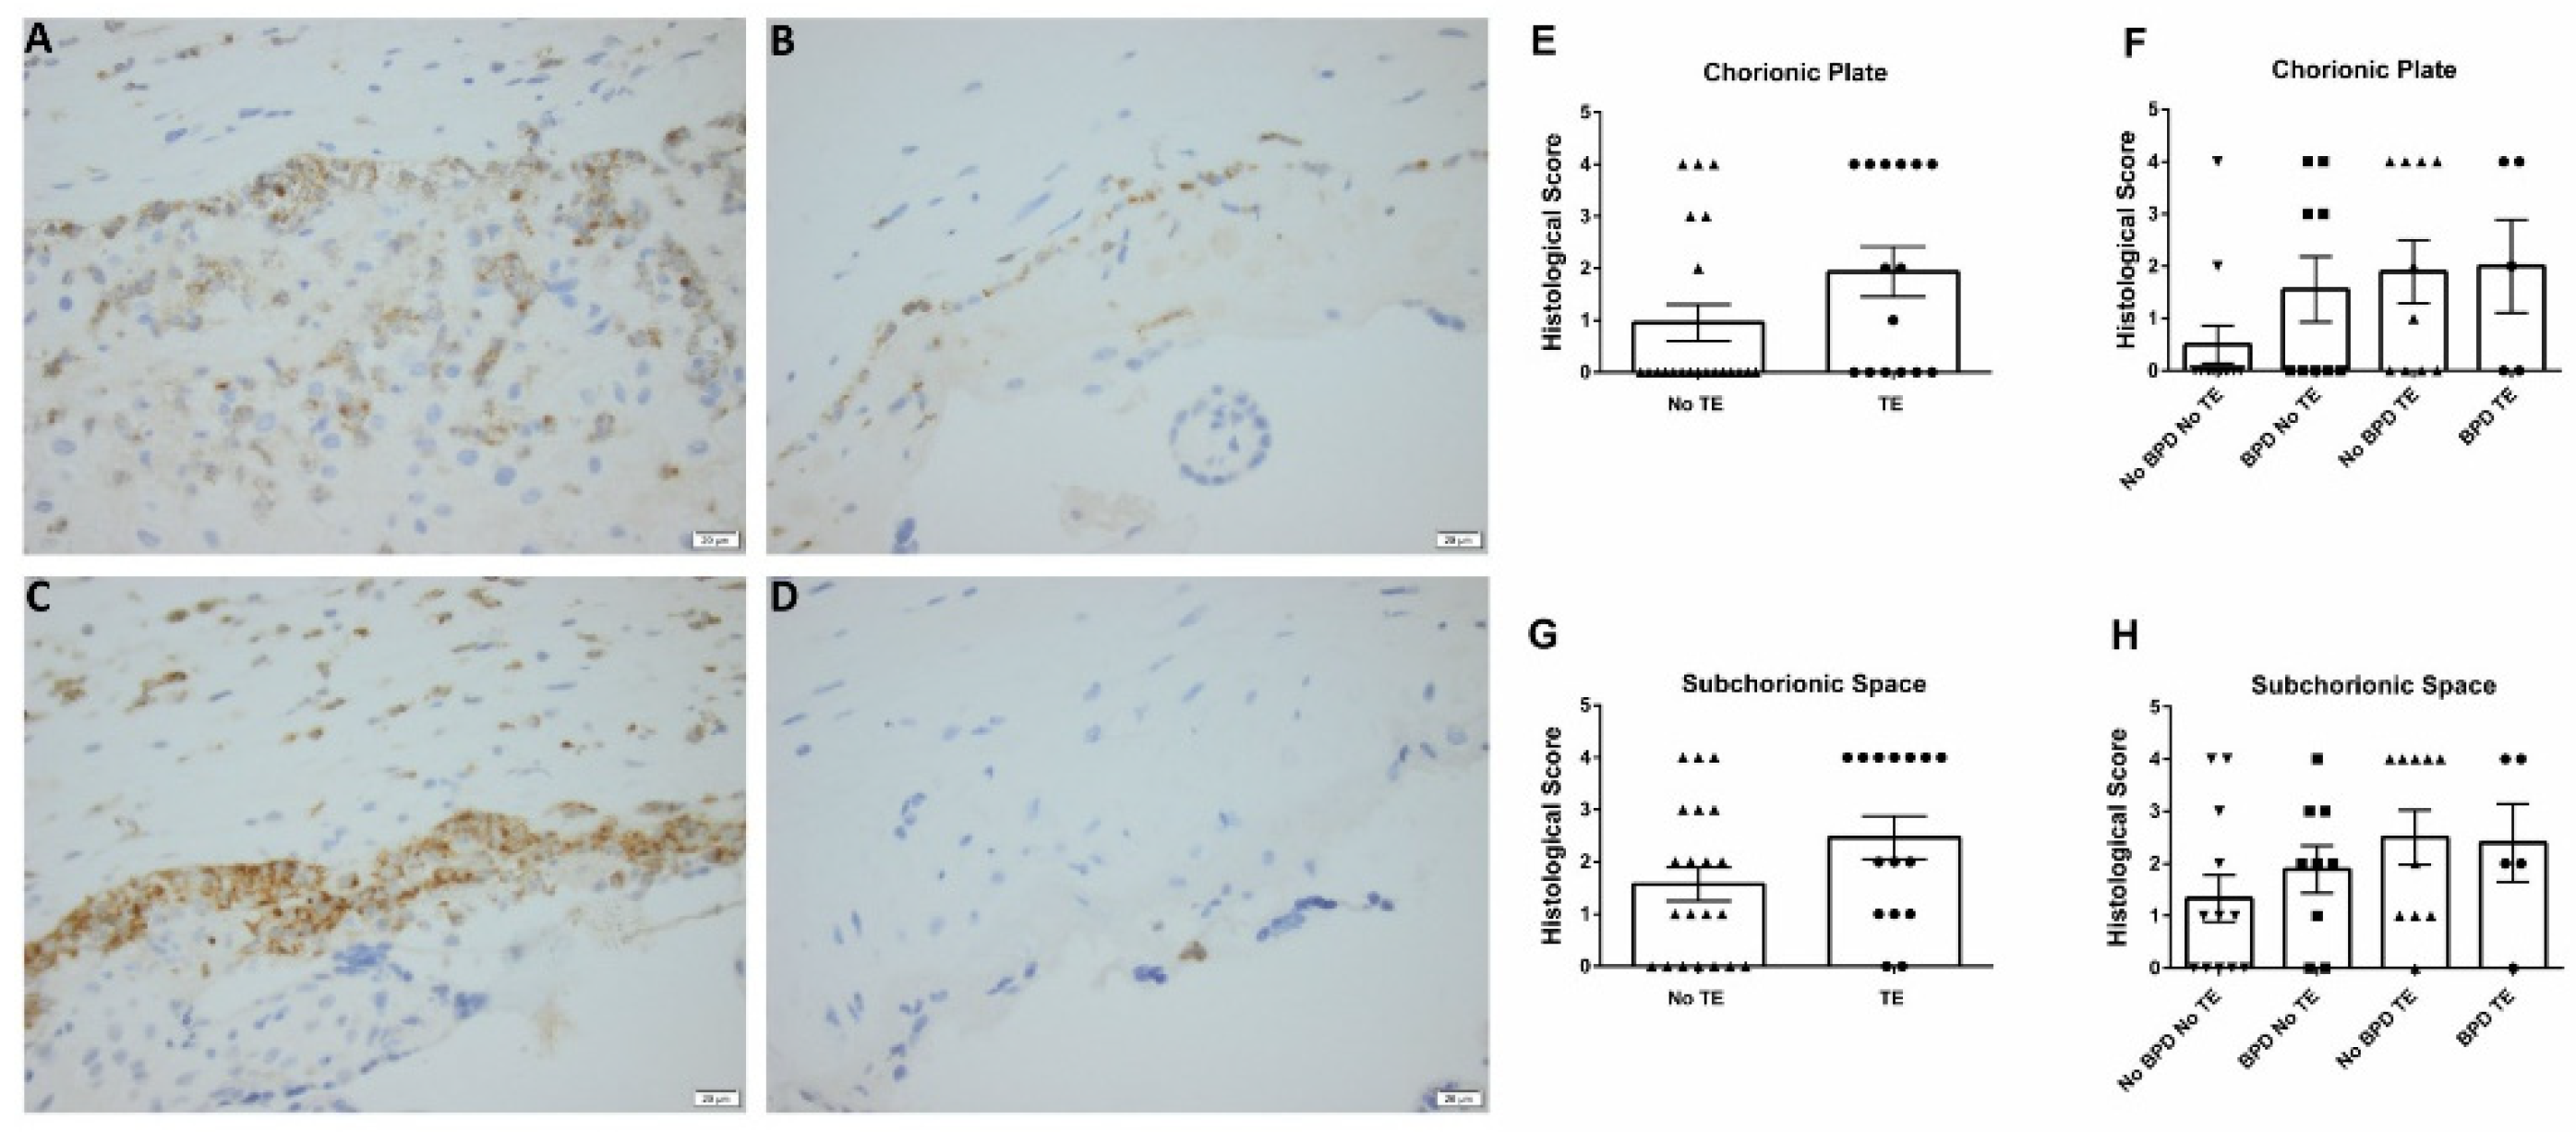
While there was no association between maternal tobacco exposure and an infant’s risk for developing BPD, IHC of placental tissues showed a higher expression of NGAL in the fetal surfaces and upper portion of the placenta parenchyma of tobacco exposure mothers (Figure 1A,C) compared to those of No TE (Figure 1B,D) mothers. The IHC for the BPD TE group (Figure 1A) showed higher expression of NGAL as compared to the BPD No TE group (Figure 1B). Regardless of BPD status, NGAL was highly expressed in the TE groups (BPD TE and No BPD TE) compared to the No TE group (BPD No TE and No BPD No TE). Additionally, NGAL intensity staining scores were higher in the chorionic plate and subchorionic space of placentas from tobacco exposure mothers, regardless of BPD status, though these differences did not reach statistical significance (Figure 1E,G; p = 0.065 and p = 0.091, respectively).
Figure 1.
Representative diaminobenzidine (brown) and hematoxylin (blue) staining (A–D, 400X magnification), and staining quantification (E–H) for placental NGAL. (A) BPD, TE group (n = 5), with strong (3 to 4+) NGAL-positive staining in a chorionic plate and subchorionic space. (B) BPD, no TE group (n = 9), with mild (1–2+) NGAL-positive staining only in subchorionic space. (C) No BPD, TE group (n = 10), with strong (3–4+) NGAL-positive staining in the chorionic plate and subchorionic space. (D) No BPD, no TE group (n = 12), with rare (0–1+) NGAL-positive staining only in subchorionic space. (E,F) Quantification of chorionic plate staining stratified by maternal smoking status and subgroup analysis. (G,H) Quantification of subchorionic space staining stratified by maternal smoking status and subgroup analysis. NGAL—neutrophil gelatinase-associated lipocalin, BPD—bronchopulmonary dysplasia, and TE—tobacco exposure.
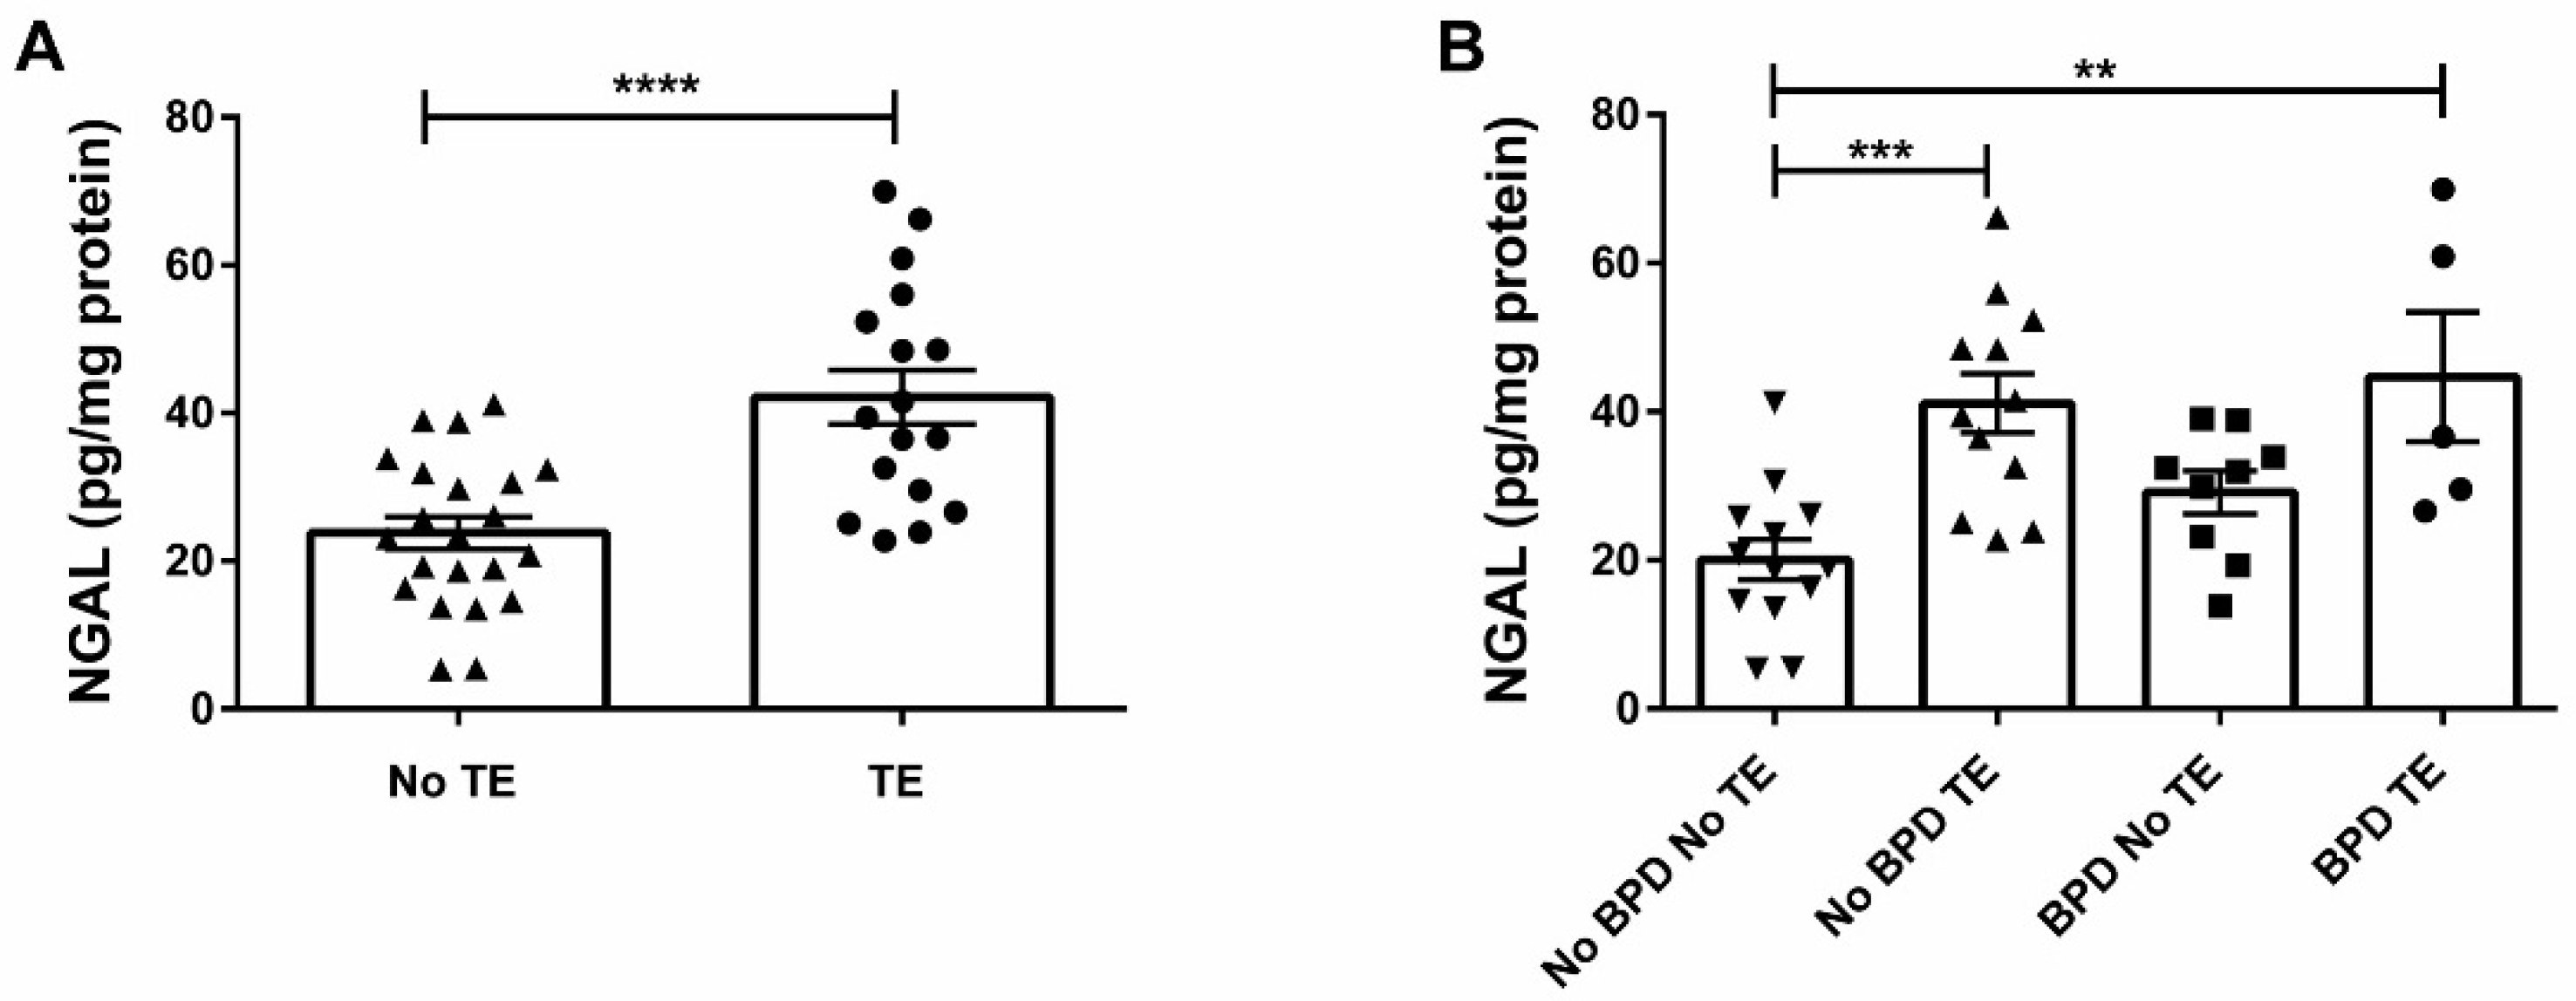
To confirm these histological findings, NGAL ELISA was performed in each of the four subgroups. As shown in Figure 2A, NGAL levels were significantly higher in the placentas of tobacco exposure compared to No TE mothers (p < 0.0001). Further subgroup analysis based on BPD outcomes showed that NGAL levels were significantly higher in infants of the BPD TE group compared to No BPD No TE infants (Figure 2B, p < 0.01). Notably, BPD No TE group also had significantly higher levels of NGAL as compared to No BPD No TE infants (Figure 2B, p < 0.001). Altogether, these data suggest that tobacco exposure during pregnancy is associated with increased neutrophil activation/infiltration in the placenta, and levels of neutrophil activation/infiltration are increased further still in the placentas of tobacco exposure infants developing BPD.
Figure 2.
ELISA for NGAL within placental tissue comparing (A) TE status and further comparing (B) TE and BPD status. (A) Compares TE group (n = 17) and No TE group (n = 22)—the NGAL is significantly higher in the TE group compared to No TE group (**** p < 0.0001). (B) Further subgroup analysis based on BPD status had significantly higher NGAL in the BPD TE group compared to No BPD No TE group (** p < 0.01). BPD No TE group also had significantly higher levels of NGAL as compared to No BPD No TE infants (*** p < 0.001). ELISA—enzyme-linked immunosorbent assay, NGAL—neutrophil gelatinase-associated lipocalin, BPD—bronchopulmonary dysplasia, and TE—tobacco exposure.
Next, the immune placental transcriptome from a subset of infants from all four subgroups was profiled using the NanoString nCounter™ Immunology Panel. Comparing BPD TE to No BPD No TE, 22 genes were significantly differentially expressed (Table 3) out of a total of 594 genes of potential interest (Table A3). Notably, transcript levels for the chemokines IL8 and CXCL10, the inflammatory molecules SA100A8/9, and the receptor CD44 were significantly upregulated in BPD TE compared to No BPD No TE infants (Table 3; p < 0.05), influencing cell signaling and inflammatory cytokine pathways (e.g., Figure A2). No other significant differences were found between the groups. We further compared the subgroups based on the neonatal outcome of BPD. Similarly, gene expression for CXCL8, CXCL10 were upregulated in the TE BPD group compared to no TE no BPD group.
Table 3.
Significantly Differential Gene Expressions (TE vs. No TE).
4. Discussion
Bronchopulmonary dysplasia, a disease primarily affecting preterm infants, can be a challenge to manage both acutely and in the long term, as there are many persistent complications affecting patients and their families [24,25]. In this study, we sought to investigate whether tobacco exposure during pregnancy is a risk factor for developing BPD. Specifically, we questioned whether neutrophil activation/infiltration occurs in the placentas of tobacco exposure mothers and if this infiltration of neutrophils to the placenta is associated with the development of BPD or death, as a composite outcome, in preterm infants.
NGAL, neutrophil gelatinase-associated lipocalin, is a 25 kDa lipocalin originally purified from activated human neutrophils. This molecule is now known to be secreted by a variety of immune cells, hepatocytes, adipocytes, and renal tubular cells [26]. In the placenta, NGAL staining has been associated with inflammation and intra-amniotic infections [26]. NGAL levels in the plasma have also been associated with the development of BPD in preterm infants [14]. In this study, we showed for the first time that NGAL staining and NGAL protein levels are higher in the placentas of tobacco exposure mothers compared to those of No tobacco exposure mothers. Using IHC, NGAL staining was specifically high in the amniochorionic membrane and intervillous space, suggesting the presence of neutrophil activation on both the maternal and fetal surfaces. Levels of NGAL measured by ELISA in placenta homogenates were higher in BPD tabacco exposure infants compared to No BPD tobacco exposure infants. Notably, we found no difference in pathologically diagnosed chorioamnionitis or funisitis between the BPD and No BPD groups, suggesting that the observed elevated NGAL levels could be secondary to maternal tobacco exposure.
The potential physiological mechanisms associating maternal tobacco exposure with increased placental NGAL are currently unknown. However, it is reasonable to assume that tobacco exposure during pregnancy results in increased inflammation and immune cell activation, both systemically and at the placenta [27]. Immune cell activation would result in the release of inflammatory cytokines and chemotactic factors [28], potentially affecting the maturation of the fetal lungs. Previous studies have confirmed an association of elevated levels of pro-inflammatory cytokines (interleukin 6 [IL-6], tumor necrosis factor-alpha [TNF-α], IL-1β, and IL-8) in amniotic fluid 5 days preceding delivery with the development of BPD, suggesting that the mechanism responsible for BPD may begin before birth [29].
To determine if tobacco exposure is associated with increased inflammation in the placenta, we profiled the placental tissues as from tobacco exposure and no tobacco exposure mothers using the nCounter® Immunology NanoString Panel, which includes over 500 immunology genes involved with activation of the inflammatory cascade, including neutrophils, natural killer cell, B cell, and T cell activation, as well as various genes responsible for complement activation. Notably, IL8 and CXCL10 mRNA were significantly upregulated in tobacco exposure compared to no tobacco exposure placenta. Both genes encode chemokines known to recruit immune cells, including neutrophils, and are associated with inflammation in the placenta [28,30]. Additionally, the SA100A8 and SA100A9 genes, upregulated in tobacco exposure placentas, encode inflammatory proteins previously shown to play a role in pregnancy loss and other complications, such as preeclampsia [31]. These expression differences further support our suggestion that maternal tobacco exposure is associated with placental inflammation, at least at the transcript level.
Surprisingly, we found no association between maternal tobacco exposure and the incidence of BPD in preterm infants born <32 weeks gestation. This lack of association could be due to the small sample size, as well as a multitude of factors known to be involved in the pathogenesis of BPD [24]. Though a previous study showed a potential association of BPD with maternal tobacco exposure, the majority of the literature indicates that maternal smoking during pregnancy is not an independent risk factor for BPD development, after controlling for additional variables [6,8,32,33]. With the exception of antepartum hemorrhage incidence, which was significantly higher in the composite outcome group compared to the No BPD group (46.7% vs. 4.2%; p = 0.003), we found no difference in known risk factors for BPD, including maternal hypertension, PPROM, and chorioamnionitis [8,9,10,11,12]. In line with other studies [7], infants with the composite outcome of BPD or death had a lower gestational age and birth weight compared to infants in the No BPD group. Composite outcome infants also required more medical interventions, such as intubation after birth, medical management of PDA, and development of threshold ROP.
Our pilot study is subject to several limitations. First, maternal tobacco exposure status was based on a self-reported questionnaire rather than biochemical measurement, such as levels of cotinine, a nicotine metabolite. We previously showed that serum cotinine levels were significantly higher in cord blood of self-reported smokers than in cord blood of non-smokers, suggesting that self-reporting smoking status could be adequate in our patient population [21]. Secondly, we did not account for the amount of tobacco exposure (e.g., number of cigarettes smoked per day, or passive versus active smoking) in our results. It is possible that active smoking has a stronger association with placental pathology than passive tobacco exposure. Third, due to the small sample size, we focused on the clinically relevant outcome of moderate to severe BPD and did not adjust for the multiple confounding variables that contribute to the development of BPD. Lastly, our focus in this study was primarily on neutrophil activation. We did not evaluate the effect of tobacco exposure on activation or placental infiltration of other leukocytes.
Our studies provide direct evidence that maternal tobacco exposure leads to neutrophil infiltration into the placenta. One possible implication of this observation is an increased inflammatory environment which could amplify other risk factors, chorioamnionitis, preeclampsia, high oxygen or mechanical ventilation, resulting in the development of BPD [16]. Additional studies need to be carried out focusing on other leukocytes present in the placenta and the cytokines the neonate is exposed to that could contribute to inflammatory injury in the developing lungs. Further, an additional larger study should be carried out to determine if an increase neutrophil infiltration into the placenta due to tobacco exposure is predictive of BPD.
5. Conclusions
In conclusion, our studies provide direct evidence that maternal tobacco exposure leads to neutrophil infiltration into the placenta. One possible implication of this observation is an increased inflammatory environment which could amplify other risk factors, chorioamnionitis, preeclampsia, high oxygen or mechanical ventilation, resulting in the development of BPD [16]. Additional studies need to be carried out focusing on other leukocytes present in the placenta and the cytokines the neonate is exposed to that could contribute to inflammatory injury in the developing lungs. Further, an additional larger study should be carried out to determine if an increase neutrophil infiltration into the placenta due to tobacco exposure is predictive of BPD.
Author Contributions
D.M.B. designed the protocol, collected data, and prepared the manuscript. Z.Y. and H.H.T. performed the standard histological analysis of placentas and IHC and NGAL. scoring. H.C. participated in the design and manuscript editing. K.Y.B. performed experiments and edited the manuscript. A.M. designed the protocol, supervised the project, analyzed the data, and edited the manuscript. J.V.E. participated in the study design, protocol design, supervised the project, performed the experiments, analyzed the data and edited the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding; it was funded by University of Oklahoma Neonatal Section, Fellow Research Grant.
Institutional Review Board Statement
This study was conducted according to the guidelines of the Declaration of Helsinki, and approved by the Institutional Review Board of The University of Oklahoma Health Sciences Center (9394 approved 23 August 2018).
Informed Consent Statement
Informed consent was obtained from all subjects involved in this study.
Data Availability Statement
Data is available on request.
Acknowledgments
We would like to thank the mothers and their infants who participated in our study. This study was funded by the Neonatal Section, at the University of Oklahoma, Fellow Research Grant. We would like to thank the Neonatal-Perinatal Medicine research team, Michael P. Anderson, PhD who assisted with statistical analysis, and Kathy Kyler who helped editing.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Figure A1.
Following consent, a maternal tobacco exposure questionnaire was administered within 24 h of delivery to self-identify TE during pregnancy.

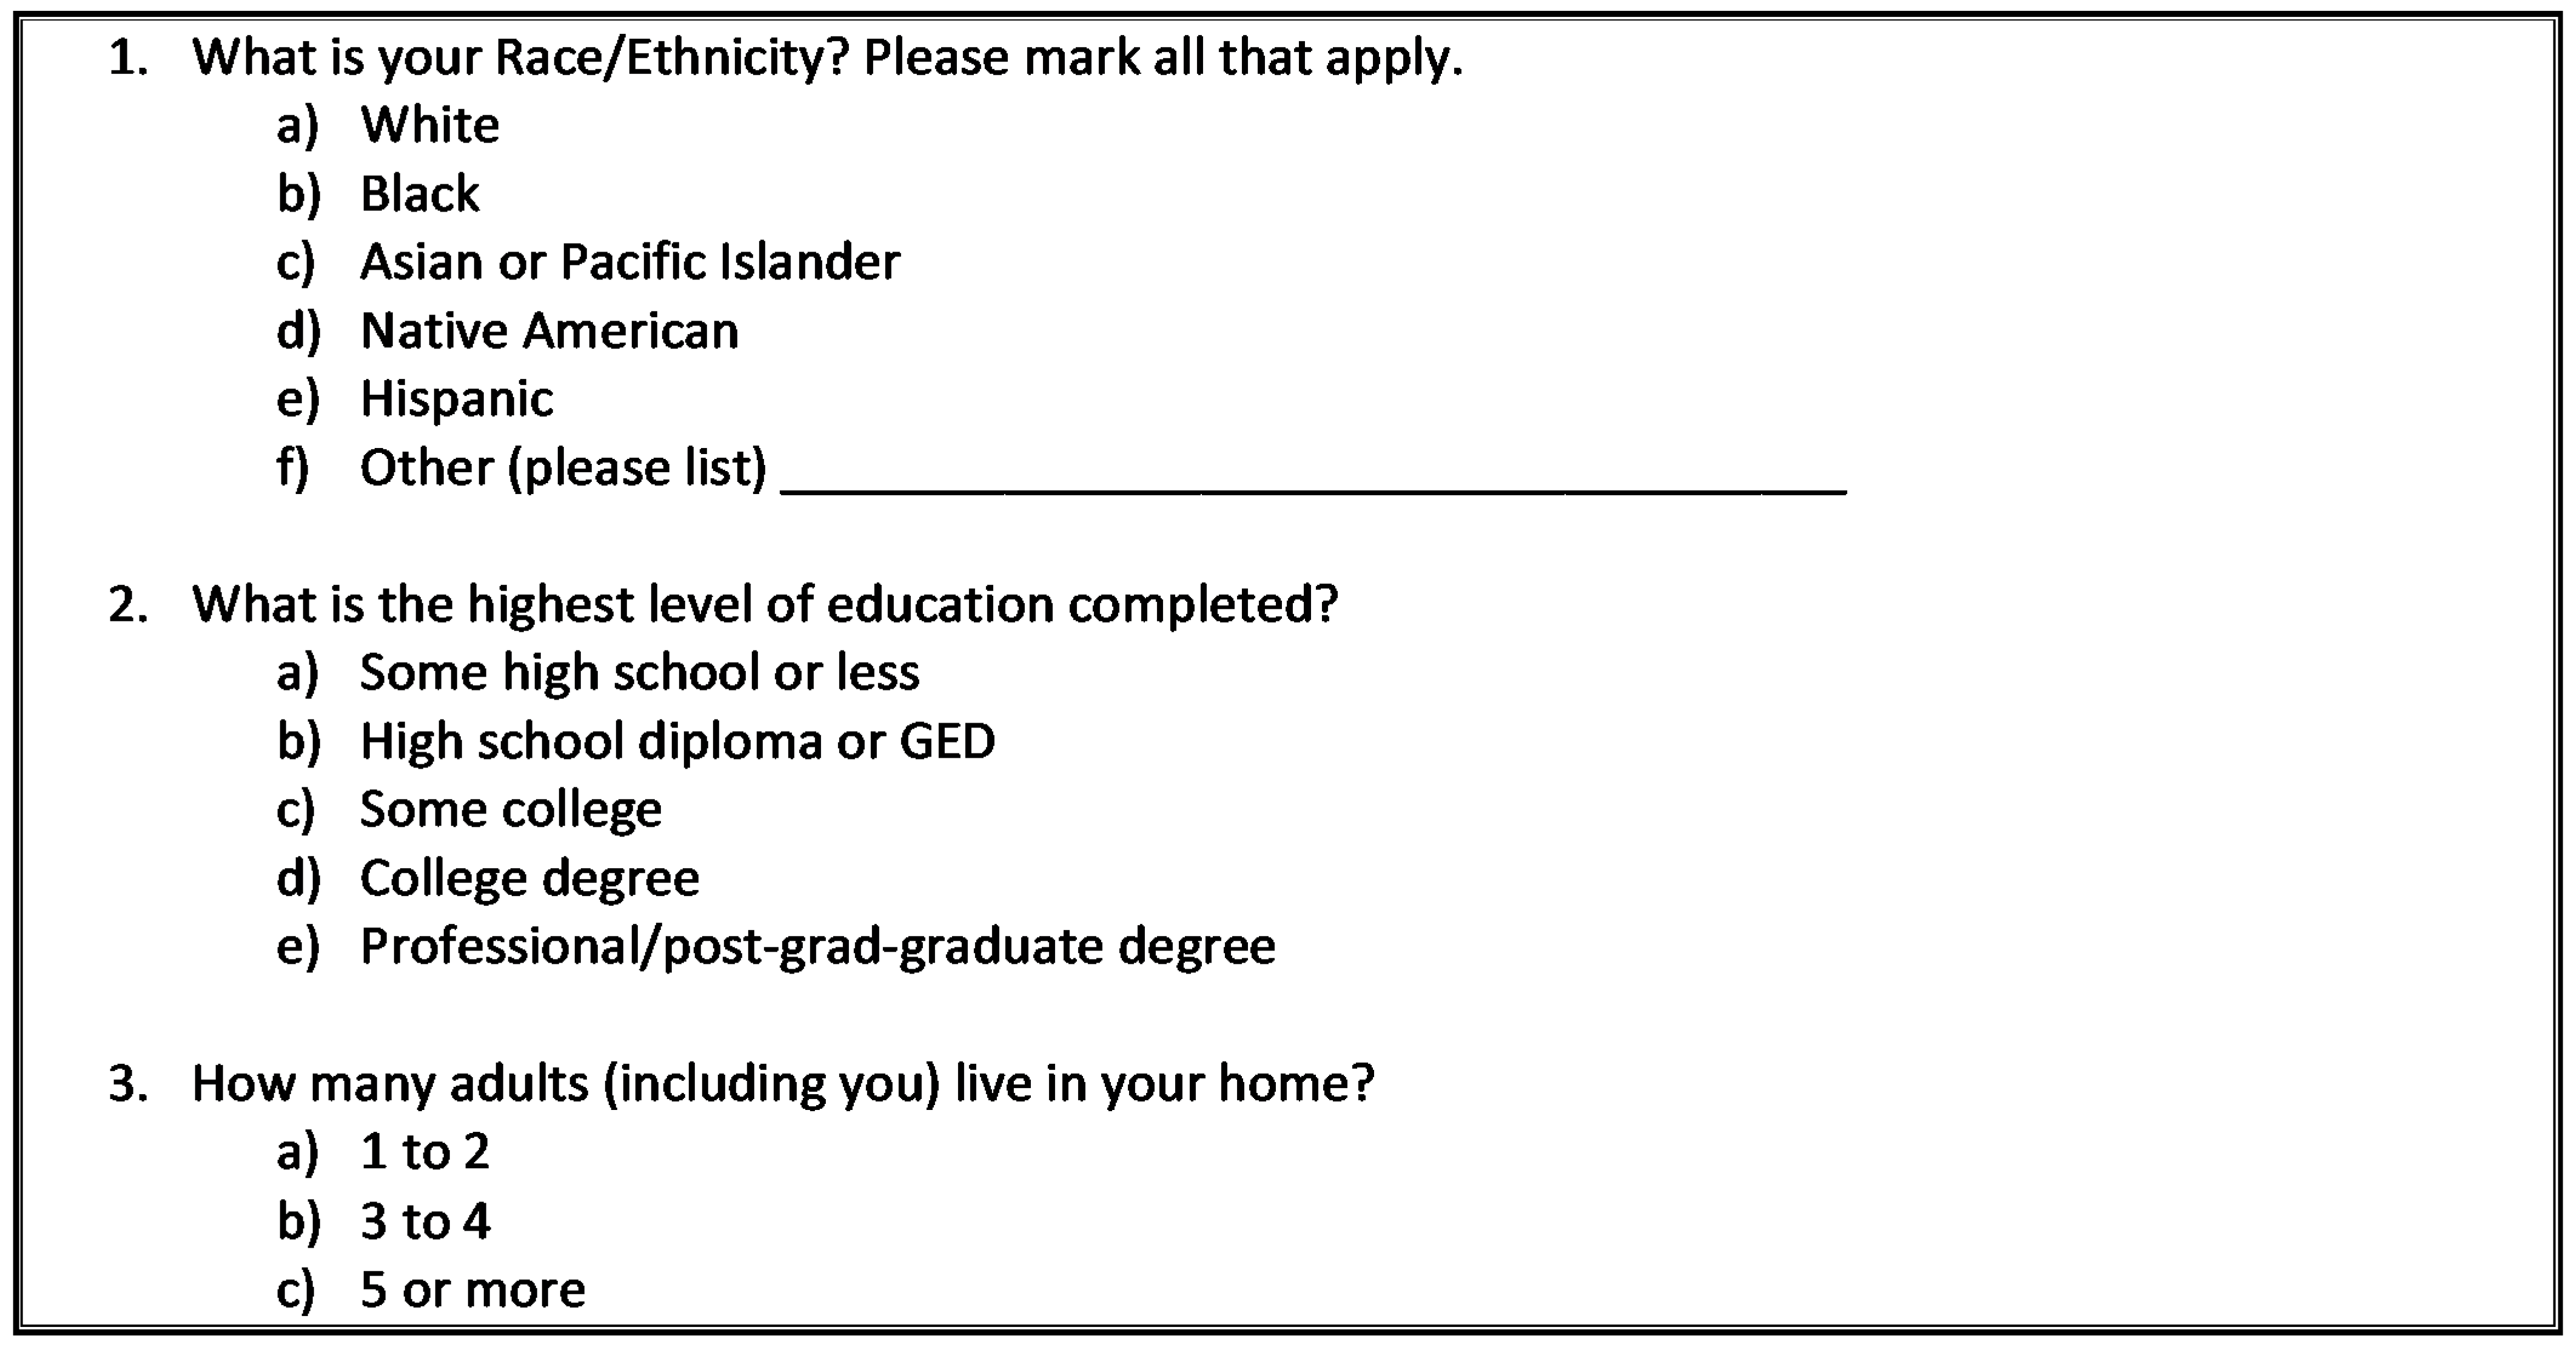
Figure A2.
NanoString nSolver® pathway analysis indicating upregulation (yellow) and downregulation (blue) of genes encoding interactions between cytokines and cytokine receptors in BPD TE placentas compared to No BPD No TE.
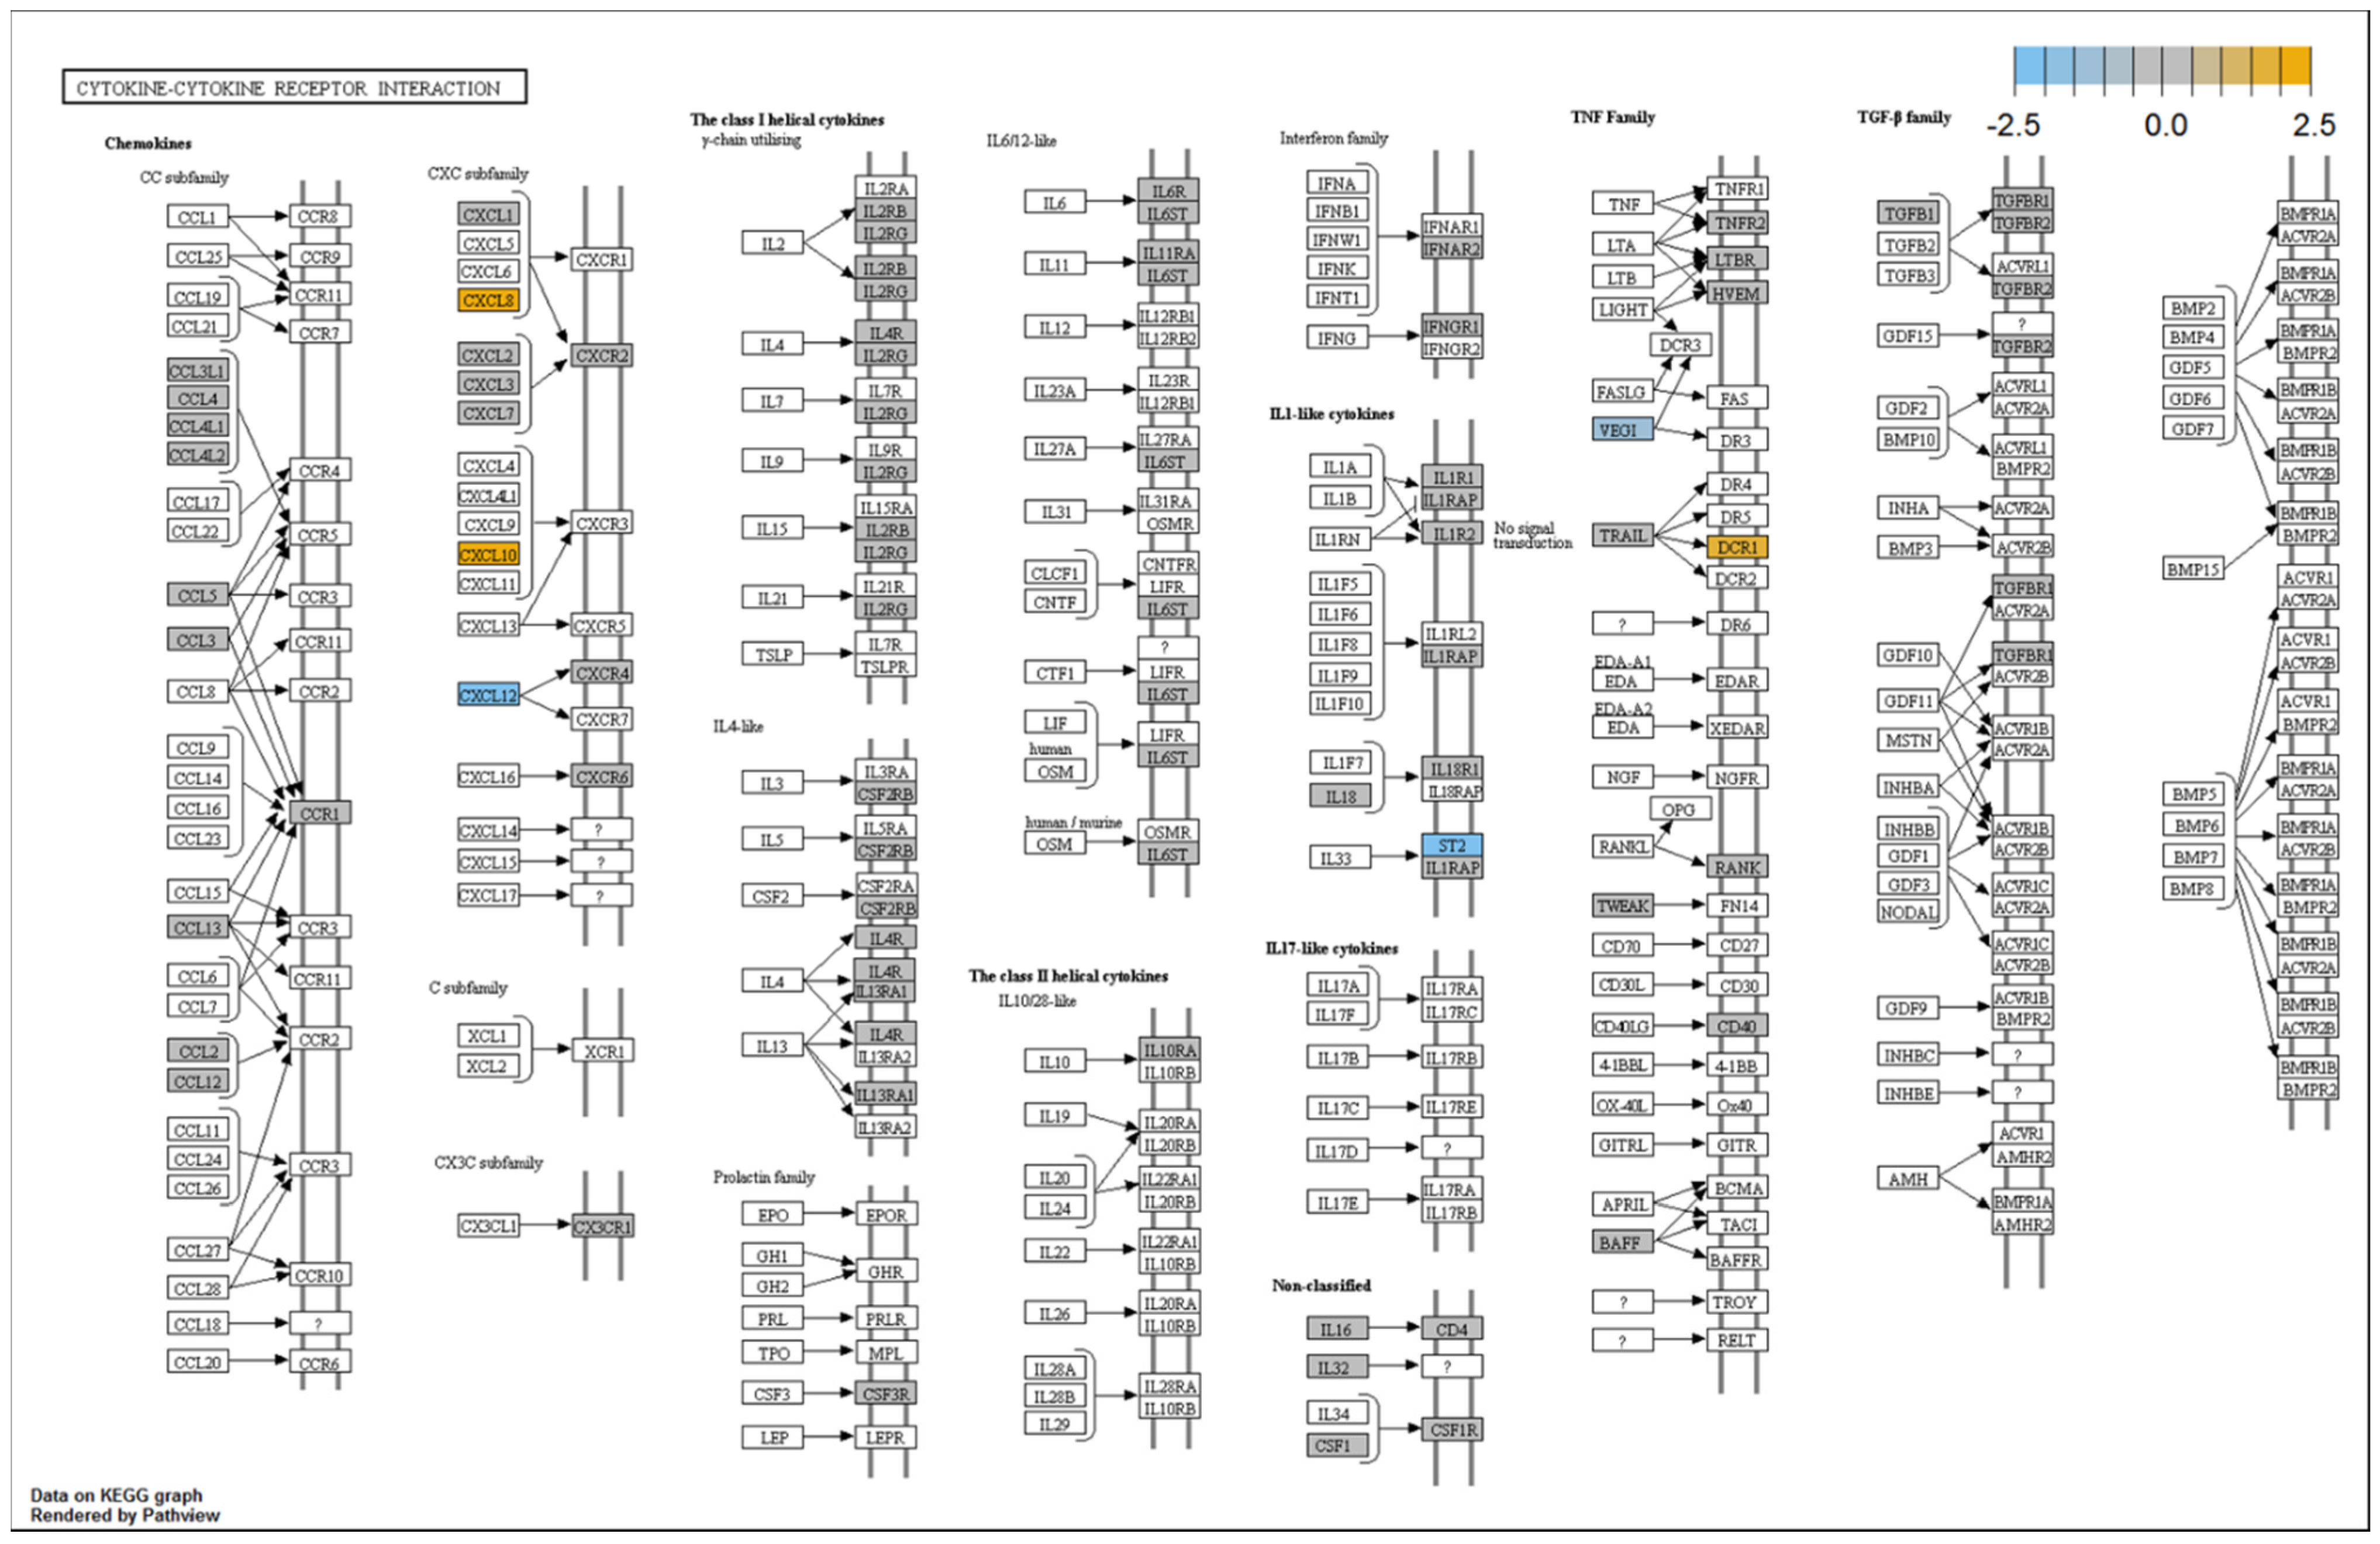
Table A1.
Maternal and Neonatal Demographic Data by Composite Outcome.
Table A2.
Maternal Complications and Tobacco Exposure by Composite Outcome.
Table A3.
NanoString Gene Expressions (BPD TE vs. No BPD No TE).
References
- Drake, P.; Driscoll, A.K.; Mathews, T.J. Cigarette Smoking During Pregnancy; NCHS Data Brief: Hyattsville, MD, USA, 2018; pp. 1–8. [Google Scholar]
- Spencer, K.; Cowans, N.J. Accuracy of self-reported smoking status in first trimester aneuploidy screening. Prenat. Diagn. 2013, 33, 245–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kyrklund-Blomberg, N.B.; Cnattingius, S. Preterm birth and maternal smoking: Risks related to gestational age and onset of delivery. J. Obstet. Gynaecol. 1998, 179, 1051–1055. [Google Scholar] [CrossRef] [Scilit]
- Nicoletti, D. Maternal smoking during pregnancy and birth defects in children: A systematic review with meta-analysis. Cad. Saude Publica 2014, 30, 2491–2529. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hackshaw, A.; Rodeck, C.; Boniface, S. Maternal smoking in pregnancy and birth defects: A systematic review based on 173 687 malformed cases and 11.7 million controls. Hum. Reprod. Update 2011, 17, 589–604. [Google Scholar] [CrossRef] [Scilit]
- Antonucci, R.; Contu, P.; Porcella, A.; Atzeni, C.; Chiappe, S. Intrauterine smoke exposure: A new risk factor for bronchopulmonary dysplasia? J. Perinat. Med. 2004, 32, 272–277. [Google Scholar] [CrossRef] [Scilit]
- Jensen, E.A.; Schmidt, B. Epidemiology of bronchopulmonary dysplasia. Birth Defects Res. Part A Clin. Mol. Teratol. 2014, 100, 145–157. [Google Scholar] [CrossRef] [Scilit]
- Morrow, L.A.; Wagner, B.D.; Ingram, D.A.; Poindexter, B.B.; Schibler, K.; Cotten, C.M.; Dagle, J.; Sontag, M.K.; Mourani, P.M.; Abman, S.H. Antenatal Determinants of Bronchopulmonary Dysplasia and Late Respiratory Disease in Preterm Infants. Am. J. Respir. Crit. Care Med. 2017, 196, 364–374. [Google Scholar] [CrossRef] [Scilit]
- Watterberg, K.L.; Demers, L.M.; Scott, S.M.; Murphy, S. Chorioamnionitis and Early Lung Inflammation in Infants in Whom Bronchopulmonary Dysplasia Develops. Pediatrics 1996, 97, 210–215. [Google Scholar] [CrossRef] [Scilit]
- Hansen, A.R.; Barnés, C.M.; Folkman, J.; McElrath, T.F. Maternal Preeclampsia Predicts the Development of Bronchopulmonary Dysplasia. J. Pediatrics 2010, 156, 532–536. [Google Scholar] [CrossRef] [Scilit]
- Eriksson, L.; Haglund, B.; Odlind, V.; Altman, M.; Ewald, U.; Kieler, H. Perinatal conditions related to growth restriction and inflammation are associated with an increased risk of bronchopulmonary dysplasia. Acta Paediatr. 2015, 104, 259–263. [Google Scholar] [CrossRef] [Scilit]
- Gemmell, L.; Martin, L.; Murphy, K.E.; Modi, N.; Håkansson, S.; Reichman, B.; Lui, K.; Kusuda, S.; Sjörs, G.; Mirea, L.; et al. Hypertensive disorders of pregnancy and outcomes of preterm infants of 24 to 28 weeks’ gestation. J. Perinatol. 2016, 36, 1067–1072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, S.; Venge, P. Lipocalins as biochemical markers of disease. Biochim. Biophys. Acta (BBA)-Protein Struct. Mol. Enzymol. 2000, 1482, 298–307. [Google Scholar] [CrossRef] [Scilit]
- Inoue, H.; Ohga, S.; Kusuda, T.; Kitajima, J.; Kinjo, T.; Ochiai, M.; Takahata, Y.; Honjo, S.; Hara, T. Serum neutrophil gelatinase-associated lipocalin as a predictor of the development of bronchopulmonary dysplasia in preterm infants. Early Hum. Dev 2013, 89, 425–429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naeye, R.L. Effects of maternal cigarette smoking on the fetus and placenta. BJOG. Int. J. Obstet. 1978, 85, 732–737. [Google Scholar] [CrossRef] [Scilit]
- Jobe, A.H. Mechanisms of lung injury and bronchopulmonary dysplasia. Am. J. Perinatol. 2016, 33, 1076–1078. [Google Scholar] [CrossRef] [Scilit]
- Gonzalez-Luis, G.E.; Westering-Kroon, E.V.; Villamor-Martinez, E.; Huizing, M.J.; Kilani, M.A.; Kramer, B.W.; Villamor, E. Tobacco smoking during pregnancy is associated with increased risk of moderate/severe bronchopulmonary dysplasia: A systematic review and Meta-Analysis. Front. Pediatrics 2020, 8, 160. [Google Scholar] [CrossRef] [Scilit]
- Gibbs, K.; Collaco, J.M.; McGrath-Morrow, S.A. Impact of tobacco smoke and nicotine exposure on lung development. Chest 2016, 149, 552–561. [Google Scholar] [CrossRef] [Scilit]
- Been, J.V.; Millett, C. Reducing the global burden of preterm births. Lancet Glob. Health 2019, 7, 414. [Google Scholar] [CrossRef] [Scilit]
- Wagijo, M.A.; Sheikh, A.; Duijts, L.; Been, J.V. Reducing tobacco smoking and smoke exposure to prevent preterm birth and its complications. Paediatr. Respir. 2017, 22, 3–10. [Google Scholar] [CrossRef] [Scilit]
- Lauren Comarda, J.E. Maternal Tobacco Exposure Leads to Cytokine Dysregulation in Placental Membranes Stimulated with Lipopolysaccharide. In Proceedings of the Pediatric Academic Society, Toronto, ON, Canada, 18 September 2018; pp. 397–412. [Google Scholar]
- Jobe, A.H.; Bancalari, E. Bronchopulmonary dysplasia. Am. J. Respir. Crit. Care Med. 2001, 163, 1723–1729. [Google Scholar] [CrossRef] [Scilit]
- Fajardy, I.; Moitrot, E.; Vambergue, A.; Vandersippe-Millot, M.; Deruelle, P.; Rousseaux, J. Time course analysis of RNA stability in human placenta. BMC Mol. Biol. 2009, 10, 21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davidson, L.M.; Berkelhamer, S.K. Bronchopulmonary Dysplasia: Chronic Lung Disease of Infancy and Long-Term Pulmonary Outcomes. J. Clin. Med. 2017, 6, 4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheong, J.L.Y.; Doyle, L.W. An update on pulmonary and neurodevelopmental outcomes of bronchopulmonary dysplasia. Semin. Perinatol. 2018, 42, 478–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tadesse, S.; Luo, G.; Park, J.S.; Kim, B.J.; Snegovskikh, V.V.; Zheng, T.; Hodgson, E.J.; Arcuri, F.; Toti, P.; Parikh, C.R.; et al. Intra-amniotic infection upregulates neutrophil gelatinase-associated lipocalin (NGAL) expression at the maternal-fetal interface at term: Implications for infection-related preterm birth. Reprod. Sci. 2011, 18, 713–722. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.; Taneja, V.; Vassallo, R. Cigarette smoking and inflammation: Cellular and molecular mechanisms. J. Dent. Res. 2012, 91, 142–149. [Google Scholar] [CrossRef] [Scilit]
- Gonçalves, R.B.; Coletta, R.D.; Silvério, K.G.; Benevides, L.; Casati, M.Z.; da Silva, J.S.; Nociti, F.H. Impact of smoking on inflammation: Overview of molecular mechanisms. Inflamm. Res. 2011, 60, 409–424. [Google Scholar] [CrossRef] [Scilit]
- Yoon, B.H.; Romero, R.; Jun, J.K.; Park, K.H.; Park, J.D.; Ghezzi, F.; Kim, B.I. Amniotic fluid cytokines (interleukin-6, tumor necrosis factor-alpha, interleukin-1 beta, and interleukin-8) and the risk for the development of bronchopulmonary dysplasia. Am. J. Obstet. Gynecol. 1997, 177, 825–830. [Google Scholar] [CrossRef] [Scilit]
- Shimoya, K.; Moriyama, A.; Matsuzaki, N.; Ogata, I.; Koyama, M.; Azuma, C.; Saji, F.; Murata, Y. Human placental cells show enhanced production of interleukin (IL)-8 in response to lipopolysaccharide (LPS), IL-1 and tumour necrosis factor (TNF)-alpha, but not to IL-6. Mol. Hum. Reprod. 1999, 5, 885. [Google Scholar] [CrossRef] [Scilit]
- Nair, R.R.; Khanna, A.; Singh, K. Role of inflammatory proteins S100A8 and S100A9 in pathophysiology of recurrent early pregnancy loss. Placenta 2013, 34, 824–827. [Google Scholar] [CrossRef] [Scilit]
- Isayama, T.; Shah, P.S.; Ye, X.Y.; Dunn, M.; Da Silva, O.; Alvaro, R.; Lee, S.K. Adverse Impact of Maternal Cigarette Smoking on Preterm Infants: A Population-Based Cohort Study. Am. J. Perinatol. 2015, 32, 1105–1111. [Google Scholar] [CrossRef] [Scilit]
- Spinillo, A.; Ometto, A.; Stronati, M.; Piazzi, G.; Iasci, A.; Rondini, G. Epidemiologic association between maternal smoking during pregnancy and intracranial hemorrhage in preterm infants. J. Pediatrics 1995, 127, 472–478. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).