


Highlights
What are the main findings?
- Dental caries affected 95.5% of schoolchildren, and nearly half presented severe disease.
- Objectively measured brushing efficacy was not significantly associated with severe dental caries.
What are the implications of the main findings?
- Current brushing performance alone may not adequately identify children at high risk of severe dental caries.
- Caries prevention should combine effective toothbrushing with dietary, fluoride, behavioral, and broader preventive strategies.
Abstract
Background: Although toothbrushing is widely recognized as a cornerstone of caries prevention, oral hygiene has traditionally been assessed using self-reported frequency or categorical plaque indices. Evidence regarding the relationship between objectively quantified brushing efficacy and cumulative caries severity remains limited. This study evaluated the association between a quantitative brushing efficacy index and dental caries severity among schoolchildren. Methods: A cross-sectional analytical study was conducted among 200 schoolchildren examined during a community dental campaign in 2025. Caries was assessed using Decayed, Missing, and Filled Teeth indices following Word Health Organization criteria. Severe caries was defined as Decayed, Missing, and Filled Teeth ≥ 5. Oral hygiene was measured using a brushing efficacy index, expressed as the percentage of biofilm removed after supervised brushing. Associations were evaluated using chi-square tests and logistic regression models adjusted for age and sex. Results: Caries prevalence was 95.5%, with a mean Decayed, Missing, and Filled Teeth of 4.99 ± 2.96. Severe caries was observed in 49% of participants. No statistically significant differences were found across tertiles of brushing efficacy (χ2 (2) = 2.18; p = 0.336). In regression analysis, each 10% increase in brushing efficacy was not significantly associated with severe caries (adjusted OR = 0.92; 95% CI: 0.81–1.03; p = 0.154). Conclusions: Dental caries prevalence was high in this population, and nearly half of the participants presented severe caries. Quantitative brushing efficacy was not significantly associated with severe dental caries after adjustment for age and sex.
1. Background
Dental caries remains one of the most prevalent chronic diseases affecting children worldwide and continues to represent a major public health challenge despite being largely preventable [1,2,3]. Untreated caries may result in pain, infection, impaired mastication, reduced quality of life, school absenteeism, and increased healthcare costs. The burden of the disease is disproportionately concentrated in socially vulnerable populations, where limited access to preventive services, oral health education, and fluoride exposure contribute to persistently high prevalence rates [2]. Consequently, reducing the burden of childhood dental caries remains a global public health priority.
Dental caries is a multifactorial disease resulting from the interaction of microbial biofilm, fermentable carbohydrates, host susceptibility, saliva, fluoride exposure, and behavioral and socioeconomic determinants [3,4]. Regular toothbrushing with fluoridated toothpaste is a central preventive measure because it disrupts dental biofilm and enhances topical fluoride delivery [5,6]. Associations between oral hygiene and caries have been reported in pediatric populations, although their magnitude varies according to contextual and individual risk factors [7,8,9]. Although toothbrushing is recognized as an essential preventive measure, its assessment in epidemiological research has traditionally relied on indirect indicators such as self-reported brushing frequency, caregiver questionnaires, or categorical plaque indices [10]. Evidence regarding the relationship between objectively quantified brushing efficacy and cumulative dental caries experience remains limited. This distinction is relevant because caries reflects cumulative exposure to biological, behavioral, and environmental determinants, whereas a supervised brushing assessment captures oral-hygiene performance at a specific point in time [11]. Consequently, the extent to which a quantitative brushing-efficacy index is associated with caries severity remains uncertain.
Clarifying this relationship has clinical and public health relevance. Quantitative brushing assessment may provide complementary information about oral-hygiene performance, but caries prevention and risk assessment require consideration of multiple determinants, including fluoride exposure, diet, previous disease experience, and social context [12,13,14,15].
Therefore, the aim of this study was to determine the prevalence and severity of dental caries among schoolchildren and to evaluate the association between an objectively measured quantitative brushing efficacy index and severe dental caries in a population with a high burden of disease.
2. Materials and Methods
2.1. Study Design and Participants
A cross-sectional analytical study was conducted among 200 schoolchildren who participated in a community oral health campaign in Quito, Pichincha, Ecuador. Data collection was carried out over an 18-month period between September 2024 and December 2025. The campaign was organized to provide preventive and diagnostic dental services to school-aged children.
Participants were consecutively recruited throughout the campaign to minimize selection bias. Children were eligible if they presented mixed or permanent dentition and had complete clinical examination records. Children with incomplete clinical data, systemic diseases affecting oral health assessment, or conditions preventing adequate oral examination were excluded.
2.2. Ethical Considerations
The study was conducted in accordance with the ethical principles of the Declaration of Helsinki and was approved by the Ethics Committee of Universidad de Las Américas (approval code: 170520250813). Written informed consent was obtained from parents or legal guardians, and written assent was obtained from all participating children before the clinical examination. Participant confidentiality and anonymity were maintained throughout the study.
2.3. Clinical Examination
All clinical examinations were performed under natural light using sterile mouth mirrors and WHO periodontal probes. Before data collection, the examiner completed theoretical and clinical calibration sessions to ensure consistency in the diagnosis of dental caries. Intra-examiner agreement was evaluated using Cohen’s Kappa coefficient, demonstrating excellent reproducibility (κ = 0.90).
Dental caries was assessed according to World Health Organization (WHO) diagnostic criteria using the DMFT index for permanent dentition and the dmft index for primary dentition [6]. For the present analysis, severe dental caries was operationally defined as a combined DMFT/dmft score of ≥5.
2.4. Quantitative Assessment of Brushing Efficacy
Oral-hygiene performance was objectively assessed using a quantitative brushing efficacy index based on the percentage of dental biofilm removed after supervised toothbrushing.
At baseline, dental plaque was disclosed using a plaque-disclosing solution (Ditonos®, Eufar, Cali, Colombia, 10 mL). Participants were subsequently instructed to brush their teeth for 2 min under direct professional supervision using a standardized soft-bristle pediatric toothbrush (Colgate® Bogotá, Colombia) and a fluoridated toothpaste containing 1450 ppm fluoride (1450 μg/g fluoride). Dental plaque was quantified using the O’Leary Plaque Control Record (PCR) following application of a plaque-disclosing solution. Disclosed plaque was assessed on four surfaces of each tooth (mesial, distal, buccal, and lingual/palatal), and the presence or absence of plaque was recorded for each surface. Plaque assessments were performed by trained dental students under professional supervision. Before data collection, the examiners underwent standardized training and calibration for plaque assessment to ensure consistency in plaque recording. For each participant, the same examiner performed both the baseline and post-brushing plaque assessments, using the same scoring protocol. Before brushing, all participants received standardized instructions to brush all tooth surfaces for two minutes. No specific named toothbrushing technique was prescribed. Participants were allowed to use their usual brushing movements while ensuring coverage of all accessible tooth surfaces. Brushing was performed under direct professional supervision to standardize brushing duration and adherence to the instructions. Following toothbrushing, plaque disclosure was repeated and the percentage of biofilm removed was calculated using the predefined brushing efficacy index. Higher percentages indicated greater brushing effectiveness. The brushing efficacy index was calculated as the percentage reduction in disclosed dental biofilm after supervised toothbrushing using the following formula:
Brushing efficacy (%) = [(Baseline plaque score − Post-brushing plaque score)/Baseline plaque score] × 100
This quantitative approach provided an objective measure of oral-hygiene performance, reducing the limitations associated with self-reported toothbrushing frequency or categorical plaque indices.
2.5. Statistical Analysis
Statistical analyses were performed using IBM SPSS Statistics for Windows, Version 29.0 (IBM Corp., Armonk, NY, USA). Continuous variables were summarized using means and standard deviations, whereas categorical variables were expressed as frequencies and percentages. Brushing efficacy was analyzed both as a continuous variable and after categorization into tertiles for descriptive comparisons. Differences in the prevalence of severe dental caries across brushing efficacy tertiles were evaluated using Pearson’s chi-square test. To investigate the independent association between brushing efficacy and severe dental caries, multivariable logistic regression models were constructed. A threshold of DMFT/dmft ≥ 5 was selected to identify children with a high cumulative burden of dental caries. Severe dental caries (DMFT/dmft ≥ 5) was entered as the dependent variable, while brushing efficacy was modeled as a continuous predictor expressed per 10% increase in biofilm removal. Age and sex were included in the multivariable model as potential confounding variables based on their established association with dental caries reported in previous epidemiological studies. Adjusted odds ratios (ORs) with 95% confidence intervals (95% CIs) were calculated, and statistical significance was established at p < 0.05.
3. Results
The sample included 200 schoolchildren (mean age: 9.12 ± 0.76 years; 53.5% female).
3.1. Caries Prevalence and Severity
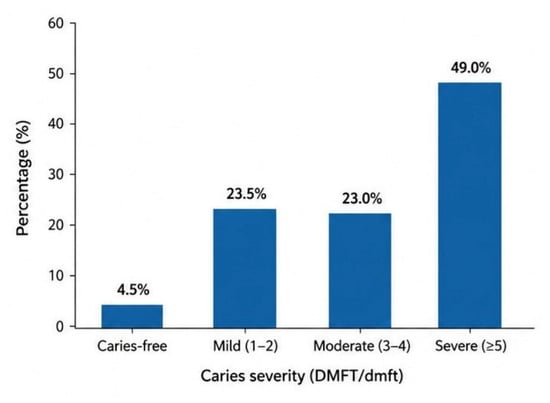
Caries prevalence was 95.5%. The mean DMFT/dmft index was 4.99 ± 2.96 (Table 1), with a higher contribution from primary dentition. Severe caries (≥5) was observed in 49% of participants. The distribution of caries severity is presented in Table 2 and illustrated in Figure 1.
Table 1.
Dental caries experience in the 200 schoolchildren according to permanent, primary, and combined dentition indices. Values are presented as mean ± standard deviation (SD).
Table 2.
Distribution of dental caries severity among the 200 schoolchildren according to the combined DMFT/dmft index. Caries severity was categorized as caries-free (0), mild (1–2), moderate (3–4), and severe (≥5). Values are presented as the number of participants (n) and percentage (%).
Figure 1.
Distribution of dental caries severity among the 200 schoolchildren according to the combined DMFT/dmft index. Caries severity was categorized as caries-free (0), mild (1–2), moderate (3–4), and severe (≥5). DMFT refers to decayed, missing, and filled permanent teeth, whereas dmft refers to decayed, missing, and filled primary teeth. Percentages represent the proportion of participants in each severity category.
3.2. Brushing Efficacy and Association with Caries
No statistically significant differences in the prevalence of severe dental caries (DMFT/dmft ≥ 5) were observed across brushing-efficacy categories (p = 0.336). In logistic regression analysis, brushing efficacy, modeled as a continuous variable per 10% increase in biofilm removal, was not significantly associated with severe dental caries (adjusted OR = 0.92; 95% CI: 0.81–1.03; p = 0.154) (Table 3).
Table 3.
Logistic regression analysis of the association between brushing efficacy and severe dental caries (DMFT/dmft ≥ 5) among the 200 schoolchildren. Odds ratios (ORs) are reported per 10% increase in brushing efficacy, with 95% confidence intervals (CIs) and p-values. The adjusted model was controlled for age and sex.
4. Discussion
This study investigated the association between an objectively measured quantitative brushing efficacy index and dental caries severity among schoolchildren living in a population with a high burden of disease. Brushing efficacy was not significantly associated with severe dental caries after adjustment for age and sex. The study also confirmed a very high prevalence of dental caries (95.5%), with nearly half of participants meeting the operational definition of severe caries. Childhood caries prevalence varies substantially across populations and geographic settings [13,14], emphasizing the importance of interpreting the present findings within the specific context in which the study population was recruited.
The absence of a statistically significant association between brushing efficacy and severe caries should not be interpreted as evidence that toothbrushing lacks preventive value. Dental caries is a cumulative, multifactorial disease reflecting long-term interactions among dental biofilm, fermentable carbohydrate exposure, fluoride availability, host-related factors, and broader behavioral and socioeconomic determinants [3,4]. In contrast, brushing efficacy in the present study was measured during a single supervised session and therefore represents current biofilm-removal performance rather than habitual oral-hygiene behavior over time. This temporal difference may partly explain the absence of an independent association with cumulative caries experience. Contemporary ecological concepts emphasize dynamic changes within the dental biofilm rather than plaque accumulation alone [4,5]. Mechanical biofilm disruption remains an important component of prevention, particularly when combined with fluoride exposure [7]. Evidence from pediatric populations also illustrates the contribution of heterogeneous clinical, nutritional, behavioral, and social determinants to caries experience [8,10,15,16,17,18,19]. Preventive trials in high-risk child populations further support multifactorial approaches rather than reliance on a single behavioral measure [11,12,20]. Accordingly, quantitative brushing assessment should be considered one component of a broader caries-risk and preventive framework [17].
The objective quantification of biofilm removal is a methodological strength of the present study because it provides a direct measure of brushing performance under standardized conditions. However, the study was not designed to validate the brushing-efficacy index as a stand-alone caries-risk assessment instrument. Future longitudinal studies should determine whether repeated quantitative assessments of brushing performance contribute additional predictive information beyond established caries-risk indicators.
5. Limitations
Several limitations should be considered when interpreting these findings. First, the cross-sectional design precludes assessment of temporality or causal relationships between brushing performance and caries development. Second, brushing efficacy was evaluated during a single professionally supervised session and therefore represents immediate biofilm-removal performance under standardized conditions rather than habitual toothbrushing behavior at home. Performance may also have been influenced by observation during the procedure (Hawthorne effect). Third, potentially important determinants of caries, including dietary sugar exposure, habitual fluoride exposure, socioeconomic status, parental education or supervision, and previous preventive dental care, were not measured and could therefore not be included as covariates. Accordingly, residual confounding cannot be excluded, and the adjusted estimates should be interpreted as controlled only for age and sex. Finally, recruitment through a community oral-health campaign may limit the external validity of the findings to other schoolchild populations. Additionally, sensitivity analyses using alternative thresholds for severe caries could not be performed retrospectively; therefore, the findings should be interpreted in relation to the prespecified operational definition of severe caries (DMFT/dmft ≥ 5).
6. Conclusions
This study found a high prevalence of dental caries among the evaluated schoolchildren, with nearly half presenting severe caries. Objectively measured brushing efficacy was not significantly associated with severe dental caries after adjustment for age and sex. Within the limitations of this cross-sectional study, current brushing efficacy alone was not associated with cumulative caries severity in this population.
Author Contributions
Conceptualization: B.V. and A.A.M. Methodology: B.V., A.C.H. and D.Q.F. Investigation: A.C.H., A.A.M. and M.R.T. Formal analysis: D.Q.F. and B.V. Writing—original draft: B.V. and A.A.M. Writing—review and editing: All authors. Supervision: B.V. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the ethical principles of the Declaration of Helsinki and was approved by the Ethics Committee of Universidad de Las Américas (approval code: 170520250813; approval date: 4 September 2024).
Informed Consent Statement
The legal representatives accepted and signed the informed consent.
Data Availability Statement
The individual-level analytical dataset used for the originally reported analyses is no longer available. Archived study materials and source clinical records remain retained by the research team. The archived version of the manuscript and associated tables and figures is available in Zenodo (https://doi.org/10.5281/zenodo.19964792).
Acknowledgments
The authors would like to thank Universidad de Las Américas for supporting the publication process.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| DMFT | Decayed, Missing, and Filled Teeth in the permanent dentition |
| dmft | decayed, missing, and filled teeth in the primary dentition |
| OR | Odds Ratio |
| WHO | World Health Organization |
References
- Songa, M.A.S.; Saliba, N.A.; Saliba, T.A.; Chiba, F.Y.; Moimaz, S.A.S. Analysis of the Dental Caries Epidemiological Profile in Children of Benguela City, Angola. Oral Health Prev. Dent. 2022, 20, 141–148. [Google Scholar] [CrossRef] [Scilit]
- Maklennan, A.; Borg-Bartolo, R.; Wierichs, R.J.; Esteves-Oliveira, M.; Campus, G. A Systematic Review and Meta-Analysis on Early-Childhood-Caries Global Data. BMC Oral Health 2024, 24, 835. [Google Scholar] [CrossRef] [Scilit]
- Pitts, N.B.; Zero, D.T.; Marsh, P.D.; Ekstrand, K.; Weintraub, J.A.; Ramos-Gomez, F.; Tagami, J.; Twetman, S.; Tsakos, G.; Ismail, A. Dental Caries. Nat. Rev. Dis. Primers 2017, 3, 17030. [Google Scholar] [CrossRef] [Scilit]
- Takahashi, N.; Nyvad, B. The Role of Bacteria in the Caries Process: Ecological Perspectives. J. Dent. Res. 2011, 90, 294–303. [Google Scholar] [CrossRef] [Scilit]
- Marsh, P.D. Contemporary Perspective on Plaque Control. Br. Dent. J. 2012, 212, 601–606. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Oral Health Surveys: Basic Methods, 5th ed.; World Health Organization: Geneva, Switzerland, 2013; ISBN 978-92-4-154864-9. [Google Scholar]
- Walsh, T.; Worthington, H.V.; Glenny, A.M.; Marinho, V.C.C.; Jeroncic, A. Fluoride Toothpastes of Different Concentrations for Preventing Dental Caries. Cochrane Database Syst. Rev. 2019, 3, CD007868. [Google Scholar] [CrossRef] [Scilit]
- Salim, N.A.; Alamoush, R.A.; Al-Abdallah, M.M.; Al-Asmar, A.A.; Satterthwaite, J.D. Relationship between Dental Caries, Oral Hygiene and Malocclusion among Syrian Refugee Children and Adolescents: A Cross-Sectional Study. BMC Oral Health 2021, 21, 629. [Google Scholar] [CrossRef] [Scilit]
- Kimmie-Dhansay, F.; Nkambule, N.R.; Schoonraad, N.; Albougy, H.; Bhayat, A. Prevalence of Early Childhood Caries in Africa: A Systematic Review. Int. J. Paediatr. Dent. 2026, 36, 157–186. [Google Scholar] [CrossRef] [Scilit]
- Akbeyaz Şivet, E.; Sezer, B.; Atmaca, N.; Hüseynova, N.; Kargül, B. Evaluation of the Effect of Dental Caries, Oral Hygiene, and Treatment Need on Oral Health-Related Quality of Life among Turkish Orphan Children and Adolescents. BMC Oral Health 2025, 25, 134. [Google Scholar] [CrossRef] [Scilit]
- Ju, X.; Mittinty, M.N.; Smithers, L.; Jamieson, L. Early Childhood Caries Intervention in Aboriginal Australian Children: A Cross-in Randomized Trial. JDR Clin. Trans. Res. 2024, 9, 239–247. [Google Scholar] [CrossRef] [Scilit]
- Jamieson, L.M.; Smithers, L.G.; Hedges, J.; Mills, H.; Kapellas, K.; Ha, D.; Do, L.G.; Ju, X. Follow-up of Intervention to Prevent Dental Caries among Indigenous Children in Australia: A Secondary Analysis of a Randomized Clinical Trial. JAMA Netw. Open 2019, 2, e1915611. [Google Scholar] [CrossRef] [Scilit]
- Rai, A.; Sundas, S.; Dhakal, N.; Khapung, A. Assessment of Dental Caries Based on ICDAS and WHO Criteria: A Comparative Study. Int. J. Paediatr. Dent. 2024, 34, 77–84, Correction in Int. J. Paediatr. Dent. 2024, 34, 940. [Google Scholar] [CrossRef] [Scilit]
- Zhou, N.; Ding, H.; Liu, J.; Chen, J.; Zhang, S.; Chu, C.H. Dental Caries Status among Yi Preschool Children in Yunnan Province, China: A Cross-Sectional Study. Int. J. Environ. Res. Public Health 2021, 18, 8393. [Google Scholar] [CrossRef] [Scilit]
- Shi, R.; Lin, C.; Li, S.; Deng, L.; Lin, Z.; Xiu, L. Obesity Is Negatively Associated with Dental Caries among Children and Adolescents in Huizhou: A Cross-Sectional Study. BMC Oral Health 2022, 22, 76. [Google Scholar] [CrossRef] [Scilit]
- Yohana, S.; Indriyanti, R.; Suryanti, N.; Rahayuwati, L.; Juniarti, N.; Setiawan, A. Caries Experience among Children with History of Neonatal Stunting. Eur. J. Dent. 2023, 17, 687–692. [Google Scholar] [CrossRef] [Scilit]
- Gallione, C.; Bassi, E.; Cattaneo, A.; Busca, E.; Basso, I.; Dal Molin, A. Oral Health Care: A Systematic Review of Clinical Practice Guidelines. Nurs. Health Sci. 2025, 27, e70027. [Google Scholar] [CrossRef] [Scilit]
- Cao, Z.; Yu, R.; Ma, J.; Zhang, Y.; Dong, X.; Fan, L. Association between Early Childhood Caries and Anthropometric Growth and Nutritional Status in Preschool Children: A Cross-Sectional Study. Front. Pediatr. 2025, 13, 1623666. [Google Scholar] [CrossRef] [Scilit]
- Guo, P.; Zou, C.; An, N.; Huang, J.; Yang, J.; Lu, Q. Emotional Symptoms, Dietary Patterns and Dental Caries: A Cross-Sectional Study in Adolescents. Oral Dis. 2024, 30, 2653–2662. [Google Scholar] [CrossRef] [Scilit]
- Ju, X.; Hedges, J.; Haag, D.G.; Soares, G.H.; Smithers, L.G.; Jamieson, L.M. Early Childhood Caries Intervention in Aboriginal Australian Children: Follow-Up at Child Age 9 Years. PLoS ONE 2025, 20, e0317024. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.