


Abstract
Background: Gamma Knife radiosurgery (GKS) is widely used for the management of intracranial disorders. Emerging evidence suggests that incorporating the biological effective dose (BED) into GKS planning may improve the prediction of treatment efficacy and toxicity. This review aims to evaluate the role of BED in GKS across multiple intracranial indications. Methods: A qualitative review of published clinical studies was performed to assess the application of BED models in GKS for pituitary adenomas, vestibular schwannomas, meningiomas, arteriovenous malformations (AVMs), trigeminal neuralgia, and other disorders. The relationships between BED, treatment outcomes, and adverse effects were compared across indications. Results: The association between BED and clinical outcomes was most consistent in AVMs, where higher BED correlated closely with obliteration rates. In other diseases, BED-based analyses showed promising but variable predictive value. Notably, BED-derived parameters demonstrated improved prediction of post-GKS hypopituitarism in pituitary adenomas and AVM obliteration compared with physical dose alone. However, most available evidence was derived from retrospective studies. Conclusions: BED may serve as a valuable complement to conventional physical dose metrics in GKS planning, but its ability to replace physical dose remains uncertain. Prospective studies and histology-specific radiobiological parameter validation are required to establish the routine clinical utility of BED.
1. Introduction
Gamma knife radiosurgery (GKS) is a widely used radiotherapy technique for treating intracranial disorders. It is now indicated for a large variety of diseases, including pituitary tumors, vestibular schwannomas, arteriovenous malformations (AVMs), meningiomas, metastases, and functional disorders [1,2,3,4,5]. GKS delivers a single, high-dose radiation treatment with submillimeter precision, which minimizes damage to adjacent healthy tissue [1]. Although previous studies have identified the recommended range of physical doses for various indications, determining the optimal radiation dose to maximize treatment efficacy while minimizing adverse effects remains a significant challenge.
Increasing evidence suggests that incorporating the biological effective dose (BED) into GKS treatment plans may enhance outcomes [6,7]. The concept of BED, introduced in 1989, quantifies the biological effectiveness of radiotherapy treatments [8], accounting for cellular DNA repair during radiation exposure [9]. While BED has been widely used in conventional fractionated radiotherapy, a model suitable for BED calculations in GKS was not proposed until recent years [10]. Moreover, rising interest in dose-rate modeling, the early integration of radiobiological parameters into contemporary treatment-planning systems, and the increasing availability of longitudinal outcome datasets have collectively renewed attention to BED-based approaches in GKS. These developments provide an opportunity to reassess how biological dose modeling may enhance treatment. Interest in integrating BED into radiosurgery planning has grown, with several studies examining its effects on GKS across various diseases [11,12,13]. However, no prior work has systematically summarized the evidence on BED across multiple GKS indications using a consistent radiobiological framework. To address this gap, we conducted a comprehensive literature review to evaluate the relationship between BED and treatment outcomes across diverse GKS applications, aiming to clarify the current evidence base and identify future directions for integrating BED into radiosurgery practice.
2. Methods
The PubMed-Medline, Ovid-Embase, and Cochrane Library databases were searched on 23 September 2025. The search strategy used the following terms: [“Gamma Knife” OR “GKS” OR “radiosurgery”] AND [“biological effective dose” OR “BED” OR “biologically effective dose”]. Only literature published in English was included.
The inclusion criteria were as follows: (a) GKS was performed for neurosurgical or neurofunctional diseases, (b) the effects of BED on the efficacy and/or safety outcomes of GKS were reported, and (c) BED calculation was based on the biexponential DNA repair model. While the traditional linear-quadratic (LQ) model is commonly used to estimate BED, it assumes a single exponential repair process and neglects sublethal damage repair during irradiation [14]. This simplification may not be suitable for GKS, where high-dose radiation is delivered over extended time periods [15]. In contrast, the biexponential DNA repair model accounts for both fast and slow repair kinetics, offering a more accurate representation of biological response by considering ongoing DNA repair during treatment [16]. Therefore, only studies that employed the biexponential model for BED estimation were included in this review. The BED formulation was presented in Supplementary Materials.
The exclusion criteria were: (a) full text was unavailable, (b) reviews, meta-analyses, conference abstracts, or commentary letters were excluded, and (c) studies that did not describe the BED model were excluded.
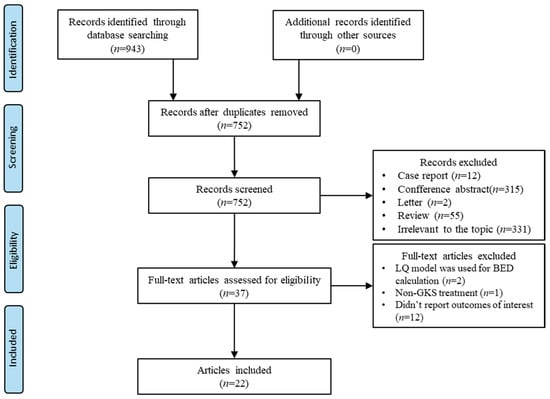
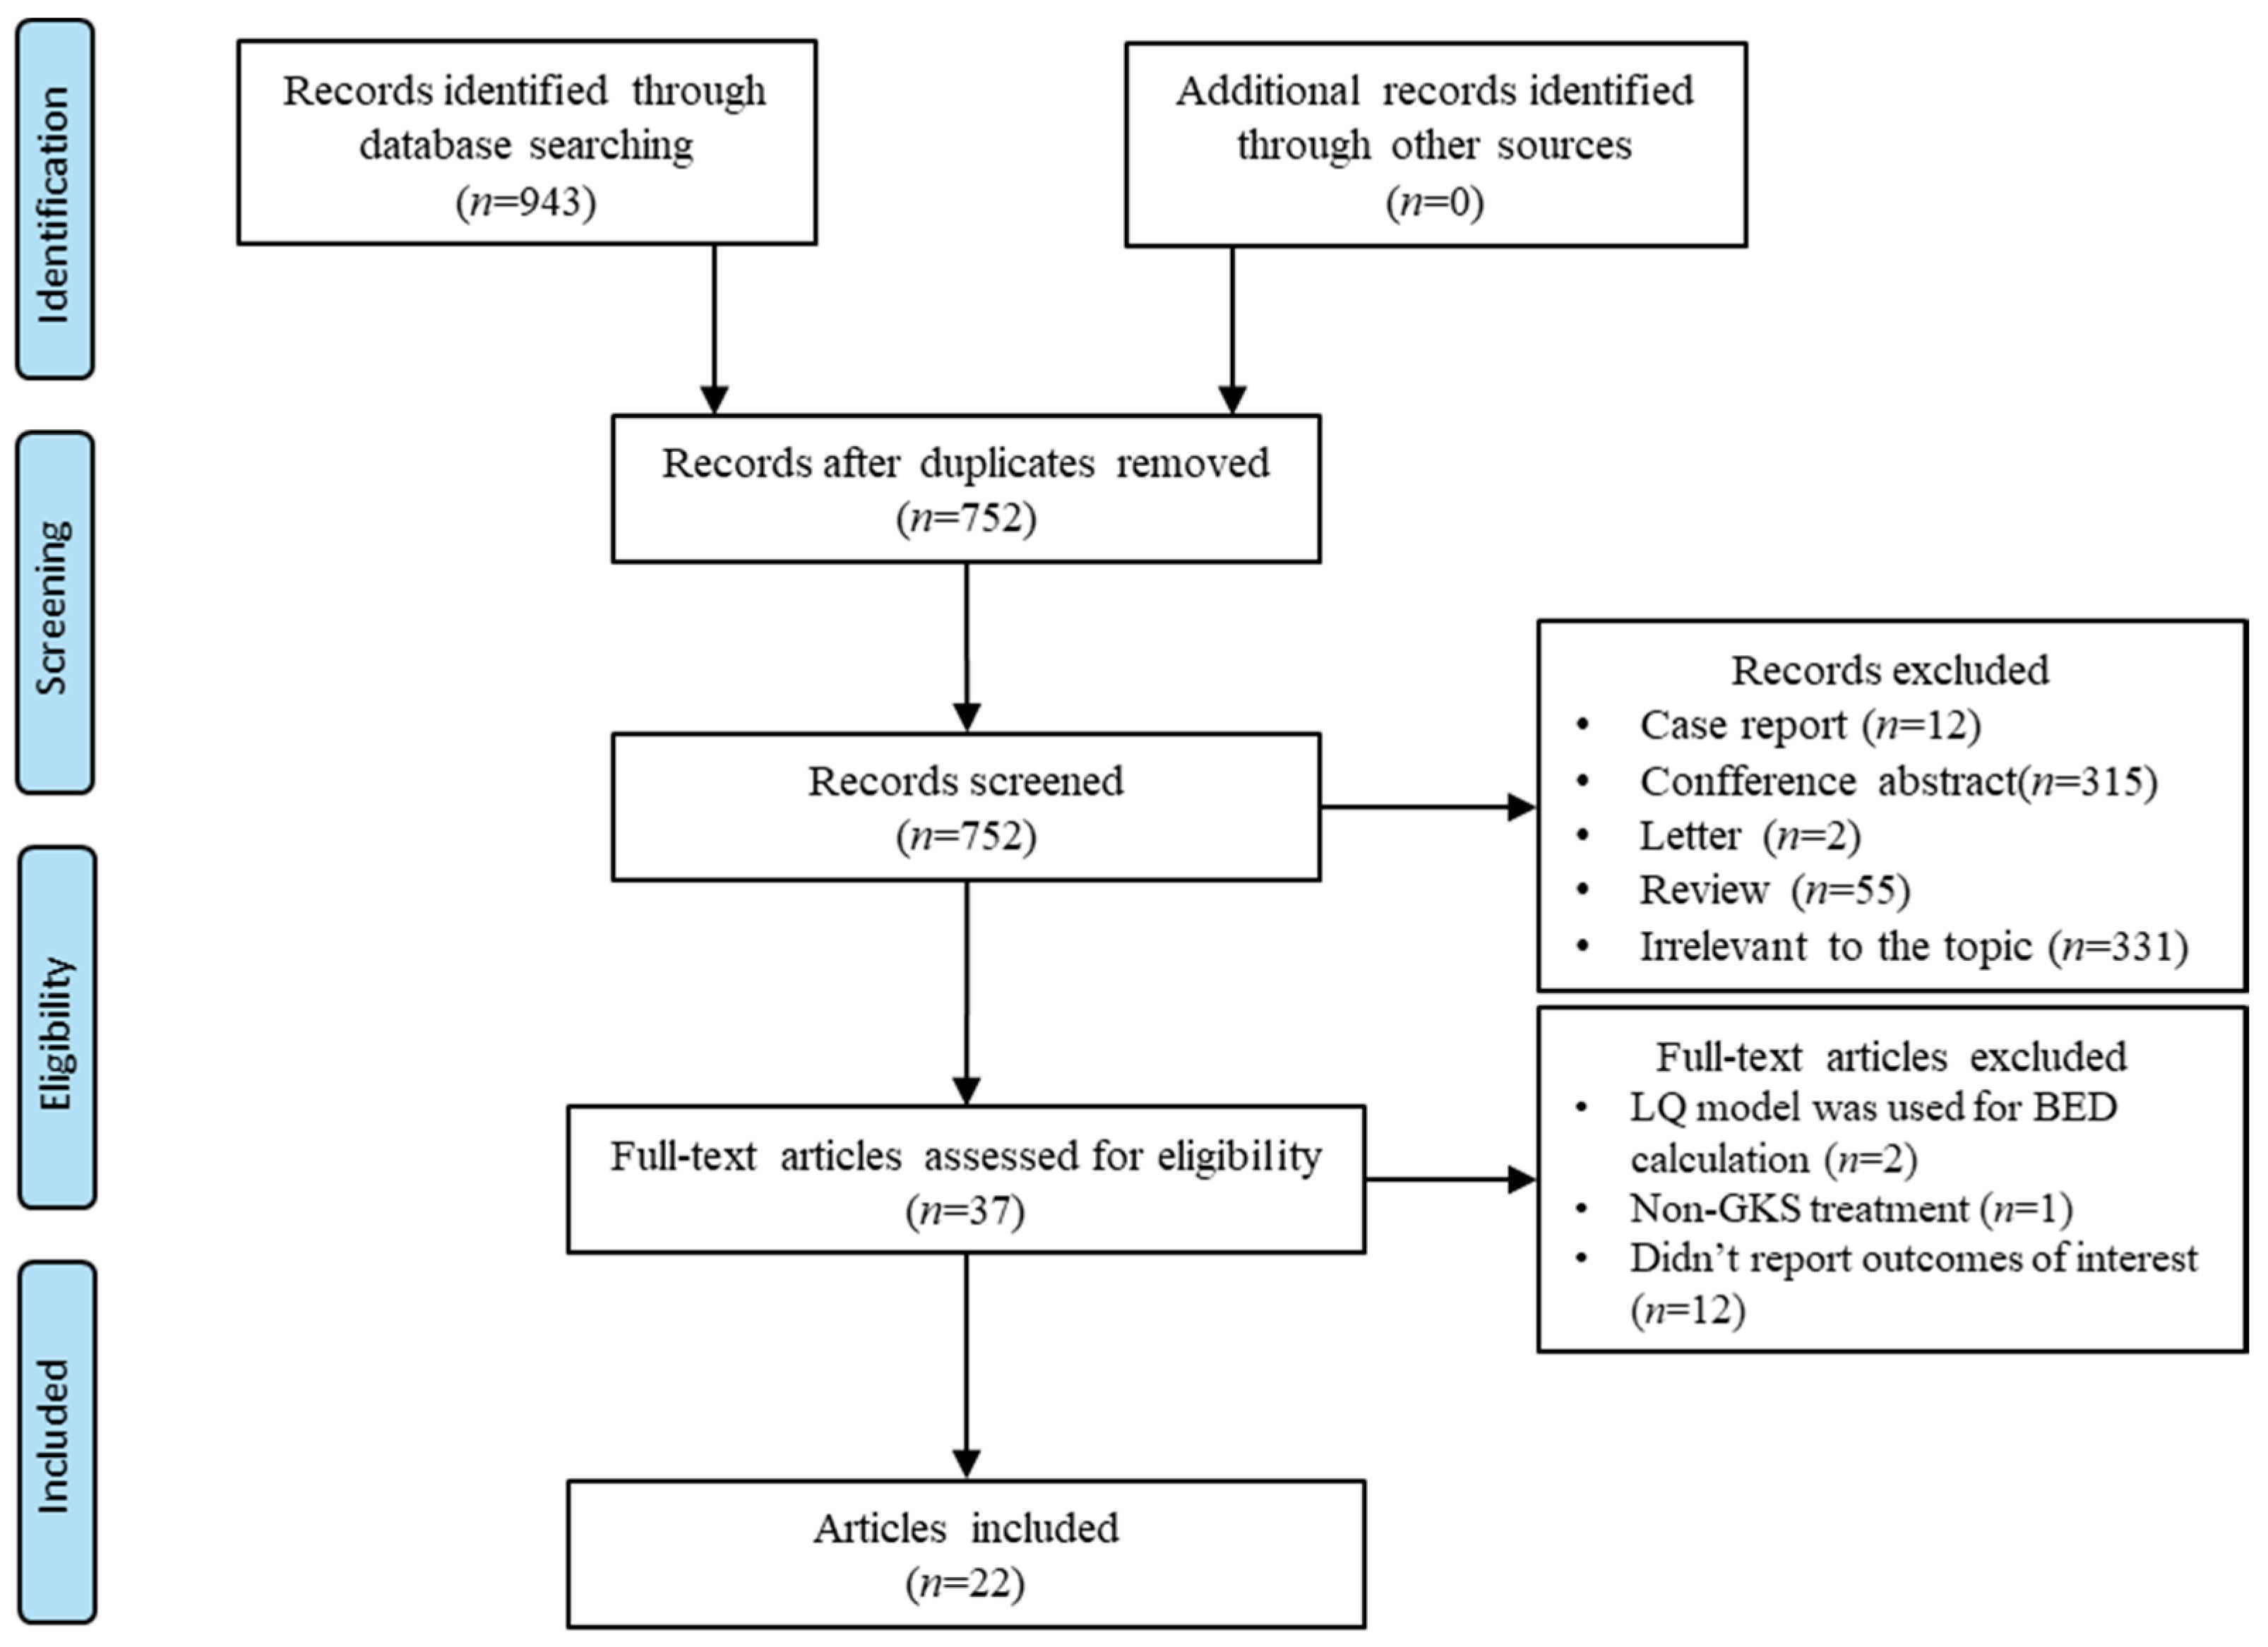
Literature selection and data extraction were performed independently by two reviewers (H.D., Q.W.). The reviewers screened the initial literature by reading the titles and abstracts. Eligible studies were then further evaluated through full-text reading by the same two reviewers. Discrepancies were first addressed through structured discussion to reach consensus; if disagreements persisted, a senior author (W.W. or S.Y.) served as an adjudicator to provide the final decision. The senior authors (W.W., S.Y.) were consulted when any inconsistencies and conflicts emerging. For each included study, the following data were extracted: the first author’s name, publication year, study type, baseline patient characteristics, disease type, GKS techniques, physical dose, BED, and other relevant data. Based on the GKS indications covered in the included studies, we collected all research findings related to the efficacy and safety of GKS, including but not limited to biochemical remission of pituitary tumors, changes in tumor volume, AVM obliteration, relief of trigeminal neuralgia, new-onset hypopituitarism, hearing loss, radiation-induced brain edema, and facial sensory loss. To assess the methodological quality and risk of bias of the included observational studies, we applied an adapted version of the Newcastle–Ottawa Scale (NOS), evaluating study selection, comparability, and outcome ascertainment. The results of this assessment are summarized in Supplementary Table S1. A total of 22 studies were included in this review. The selection process is depicted in the flow chart in Figure 1. The diseases covered in these studies included pituitary adenoma (n = 6) [12,17,18,19,20,21], meningioma (n = 3) [22,23,24], vestibular schwannomas (n = 4) [13,25,26,27], arteriovenous malformations (AVM) (n = 3) [7,11,28], melanoma brain metastases (n = 1) [29], trigeminal neuralgia (n = 4) [6,30,31,32], and essential tremor (n = 1) [33]. The characteristics of included studies are listed in Table 1. The Effects of BED and physical dose on treatment outcomes are presented in Table 2. This review was not registered in PROSPERO or other systematic review registries, which should be considered a methodological limitation. Table S3: PRISMA 2020 Checklist see the Supplementary Materials.
Figure 1.
Flow diagram summarizing the process of literature selection.
Table 1.
Characteristics of included studies.
Table 2.
Effects of BED/physical dose on treatment outcomes.
3. Results
3.1. Pituitary Adenoma
Among the studies that included pituitary adenoma, three focused on acromegaly, two on Cushing’s disease, and one on multiple pituitary adenomas. For acromegaly, the results from different centers were generally consistent. Two studies identified BED as a significant predictor of biochemical remission after GKS. Dumot et al. reported that the probability of biochemical remission in patients receiving a BED > 170 Gy2.47 was twice that of those receiving a lower BED (HR: 2.02, 95% CI: 1.06–3.86, p = 0.03) [21]. In a study by Graffeo et al., BED was significant for biochemical remission both as a continuous variable (HR: 1.01, 95% CI: 1.00–1.02, p = 0.02) and as a binary variable (BED > 200 Gy2.47, HR: 2.72, 95% CI: 1.36–5.13, p < 0.01) [17]. Another study showed that the higher BED group tended to have better endocrine remission at 9 years (70.2% vs. 48.2%, p > 0.05) [18]. Although the difference did not reach statistical significance, this qualitative trend aligned with the findings of the other two studies. Neither BED nor physical dose was significantly associated with post-GKS hypopituitarism.
For Cushing’s disease, both studies had rather limited sample sizes. Our center reported a significantly higher endocrine remission rate in the higher BED group (>205 Gy2.47) at 2 years after GKS (72.7% vs. 35.1%, p = 0.04) [12]. Balossier et al. presented a similar trend, though the difference was not statistically significant [19]. Graffeo et al. included a cohort with both secreting and non-secreting tumors. Their results indicated that mean gland BED, rather than BED alone, was significantly associated with post-GKS hypopituitarism (HR: 1.03, 95% CI: 1.02–1.05, p < 0.001) [20]. However, neither physical dose nor BED nor mean gland BED were associated with treatment success. Additionally, although mean gland dose was a predictor of post-GKS hypopituitarism (HR: 1.31, 95% CI: 1.16–1.47, p < 0.001), the BED-based model demonstrated better predictive efficacy compared to physical dose-based models.
3.2. Meningioma
Huo et al. reported the largest meningioma cohort (n = 336) among the included studies [23]. The effects of BED on local tumor control varied across different WHO grades. In a cohort of 354 grade I lesions, a BED > 50 Gy2.47 was significantly associated with a lower incidence of local failure (p < 0.01). Similarly, another study involving 91 cases of parasellar meningioma (WHO grade I or presumed grade I) also found that BED was a significant predictor of local control (HR: 0.96, 95% CI: 0.92–1.00, p = 0.03) [24]. However, Dedeciusova et al. reported mixed results, finding no significant association between BED and clinical improvement or tumor control [22]. Their study, which included only 46 cases, may have lacked sufficient statistical power to detect a significant effect. Notably, none of the included studies addressed the impact of BED on the safety of GKS.
3.3. Vestibular Schwannomas
The studies on vestibular schwannomas showed heterogeneous results. The largest cohort study failed to find a significant association between BED and either tumor control or symptomatic edema [25]. However, Tuleasca et al. reported a significantly positive association between BED and tumor volume changes (β = −0.17, p < 0.01) [13]. Additionally, Tuleasca et al. explored the relationship between BED at specific sites and hearing decline. Both tumor BED and mean cochlea BED were significantly related to hearing decline at various time points [26,27]. Interestingly, mean cochlea dose, rather than tumor dose, was significantly associated with hearing decline at 24 months.
3.4. Arteriovenous Malformation
All three included studies indicated that BED was a significant predictor of AVM obliteration after GKS. Nesvick et al. reported that the probability of obliteration in patients with a BED > 133 Gy2.47 increased by 52% compared to those receiving a lower BED (HR: 1.52, 95% CI: 1.19–1.95, p < 0.01) [11]. In another study, patients with a BED > 180 Gy2.47 had more than twice the probability of obliteration (HR: 2.11, 95% CI: 1.30–3.40, p < 0.01) [28]. Tuleasca et al. developed a predictive model for AVM obliteration after GKS, which showed that BED was the strongest predictor of obliteration in unruptured AVMs (HR: 1.015, 95% CI: 1.001–1.029, p = 0.03) [7]. Additionally, they found that BED had greater predictive power than physical dose. Although Nesvick et al. reported on the largest cohort, their study did not address the effects of BED on the safety of GKS. The other two studies showed that neither BED nor physical dose were significantly associated with post-GKS complications.
3.5. Trigeminal Neuralgia and Other Indications
Tuleasca et al. reported the earliest results of BED on TN. They observed a trend of increasing hypoesthesia with higher BED, but did not find a definitive relationship between BED and pain relief [30]. The following studies showed that effects of BED on TN may vary for different trigeminal nerve target. A multicenter cohort including 871 cases of type 1 TN showed that a BED ≥ 2100 Gy2.47 was significantly associated with initial pain relief for the distal target (HR: 1.46, 95% CI: 1.05–2.03, p = 0.03) [6]. For the proximal target, physical dose rather than BED was a significant predictor of initial pain relief (HR: 1.79, 95% CI: 1.05–3.05, p = 0.03). However, neither BED nor maximal dose was associated with post-GKS sensory dysfunction for either proximal or distal target. Similarly, results of our center also showed target heterogeneity of BED [32]. For patients with distal targets, BED was a significant predictor of treatment failure (OR: 0.996, 95% CI: 0.992–0.999, p = 0.02) and post-GKS complications (OR: 1.002, 95% CI: 1.000–1.004, p = 0.01). BED did not significantly influence outcomes in the proximal target subgroup, either for treatment failure or complications. Tang et al. combined BED with target volumes to explore the association between BED coverage and treatment outcomes [31]. The results indicated that V%CN V-BED1000, rather than BED alone, was a significant predictor of pain relief (OR: 1.05, 95% CI: 1.04–1.07, p < 0.01), quality of life (OR: 1.05, 95% CI: 1.04–1.07, p < 0.01), and medication withdrawal (OR: 1.05, 95% CI: 1.04–1.05, p < 0.01). Additionally, the maximal BED received by the brainstem was a significant predictor of post-GKS complications (OR: 1.06, 95% CI: 1.05–1.06, p < 0.01).
Only one study reported results on essential tremor (ET) [33]. Increasing BED was associated with improvement in the ET rating scale (β = −0.029, p = 0.04). Adverse radiation events tended to occur in cases receiving high BED (>4500 Gy2.47). Zubatkina et al. used multiple α/β ratios (3, 5, 10, 15) to calculate BED in melanoma brain metastases [29]. BED, based on various α/β ratios, was significantly associated with local control after GKS. Furthermore, BED calculated with an α/β ratio of 15 demonstrated better predictive efficacy for local control compared to the margin dose (AUC: 0.85 vs. 0.79). Neither BED nor margin dose was significantly associated with radiation necrosis. The interpretive strength of findings for essential tremor and melanoma brain metastases is limited, as each indication was represented by only a single eligible study. Consequently, conclusions for these categories should be regarded as preliminary, and additional standardized, high-quality investigations are required to validate these observations.
4. Discussion
Our review indicates that BED may play a meaningful role in influencing clinical outcomes across a variety of GKS indications. The most consistent findings were observed for AVMs, where all studies identified BED as a significant predictor of obliteration. Results for pituitary adenomas also showed a relatively coherent pattern, with multiple studies demonstrating associations or trends between BED and endocrine remission, while mean gland BED emerged as a predictor of post-GKS hypopituitarism. In contrast, for indications such as TN, meningioma, and VS, study findings were more variable, likely reflecting differences in target selection, coverage metrics, and study methodology. The limited evidence available for essential tremor and melanoma brain metastases should be interpreted cautiously, as each was represented by a single study. We have summarized the indication-specific BED thresholds in the Supplementary Table S2.
Early radiobiological work quickly recognized that treatment outcomes depend not only on the physical dose but also on its biological effectiveness [14]. Currently, BED is widely applied in conventional fractionated radiotherapy, where numerous clinical series have linked higher BED values to improved tumor control and survival across various diseases [34,35,36]. However, unlike conventional radiotherapy, GKS delivers a very high dose through single or multiple isocenters over a long period of time. This generates steep intracranial dose gradients, allowing DNA repair to begin during—rather than after—irradiation. A variety of studies suggest that the administration of a single, high dose of radiation in vivo has a much greater effect than that which would be predicted from the LQ model using the coefficients calculated from conventional in vitro dose/fractions [15]. Modeling studies have shown that the LQ-based BED can misestimate biological effects in GKS [37,38]. To address this, Jones et al. introduced a biexponential, time-corrected BED framework for GKS, which explicitly accounts for both fast and slow DNA repair kinetics during protracted single-session treatments [10]. All studies included adopted this BED model, which helped reduce bias and heterogeneity.
The physical dose used in GKS varied substantially across indications, and dose selection is still largely empirical. Due to the varying dose rate of Co60, the delivery time for a given physical dose can differ considerably. Sublethal DNA damage begins to repair while irradiation is still ongoing [10]. Therefore, the same prescribed dose in GKS may produce different biological effects, especially when the dose rate varies widely. Some studies have explored the impact of dose rate. Lee et al. and Barzaghi et al. reported that a higher dose rate was associated with a lower likelihood of recurrence for TN [39,40]. Huo et al. found that meningioma patients treated with lower dose rates had a higher incidence of local failure compared to those treated with higher dose rates. However, Tuleasca et al. found no significant association between dose rate and AVM obliteration or post-SRS complications [7]. The introduction of BED in GKS allows for dose–time compensation that physical dosimetry fails to account for. Notably, three studies directly compared BED with physical dose and showed that BED provided superior predictive performance for hypopituitarism, AVM obliteration, and local control in melanoma brain metastases [7,20,29]. This potential advantage suggests that clinicians may benefit from consciously incorporating BED into GKS planning. Some low-level evidence even suggested a specific BED range for certain indications, though these BED ranges require further validation [21,33]. Additionally, BED may offer personalized dose constraints for organs at risk. For example, incorporating BED into planning has been shown to refine cochlear and brainstem limits and correlate more closely with hearing preservation outcomes after vestibular schwannoma GKS than physical dose alone [27].
Several studies highlighted that BED-derived parameters such as volume-based BED coverage and mean gland BED, may better characterize the biological distribution of dose than gross BED [20,31]. For instance, the use of mean gland BED rather than gross lesion BED underscores the differing radiosensitivities of surrounding anatomical structures and reinforces the importance of sparing critical tissues during GKS planning. Likewise, volume-based BED coverage reflects not only the existence of an effective BED threshold but also the necessity of achieving adequate biological dose coverage across the target, combining both dose adequacy and spatial distribution into a single metric. Together, these multidimensional BED-derived parameters may offer a potentially more predictive framework than gross BED alone, although further validation is still required. Current commercial GKS planning systems do not natively compute BED, but BED-based corrections can be implemented via exported dose-rate data, custom calculation modules, or research-grade plugins. Incorporating BED requires familiarity with radiobiological modeling, which introduces a learning curve for clinicians. However, the increasing availability of automated BED calculators and scripting interfaces makes that practical implementation is feasible.
One of the limitations is that the same radiobiological parameters were used for BED estimation across different histological types. For instance, the α/β ratio for normal brain tissue was assumed to be 2.47 Gy [41], and all studies, except for that on melanoma brain metastases, used 2.47 Gy as the α/β ratio. While this approach serves as a compromise due to the current lack of histology-specific parameters, it introduces potential systematic errors when applying BED in GKS. According to the BED formulation, Underspecifying α/β leads to an overestimation of BED, whereas overspecifying it causes underestimation. Using a uniform α/β ratio of 2.47 Gy across diverse histologies may distort the magnitude of BED, alter BED–outcome correlations, and destabilize disease-specific BED thresholds, underscoring the importance of deriving histology-specific radiobiological parameters. Zubatkina et al. explored various α/β ratios in BED estimation and found that α/β ratios of 10 Gy and 15 Gy might be more appropriate for melanoma brain metastases based on clinical outcomes [29]. Reverse outcome-based modeling may therefore offer a feasible and informative strategy for establishing histology-specific radiobiological parameters. However, such analyses require large, well-characterized cohorts with standardized definitions of endpoints and harmonized dose-time reporting, necessitating multi-center collaboration. Importantly, clinically derived α/β ratios should ideally be cross-validated with parameters obtained from biological experiments, which may help refine BED estimation and improve the robustness of radiobiological modeling in GKS. Finally, substantial heterogeneity existed across studies. Variability in study design (single-center vs. multicenter cohorts), inconsistency in outcome definitions and the use of different GKS platforms across institutions may all introduce methodological inconsistency. Moreover, marked variation in follow-up duration and baseline characteristics, including age distribution and sex ratio, further complicates direct comparison. These differences may partially explain the inconsistency of findings for certain indications.
Overall, BED appears to be a significant factor across a wide range of GKS indications. This observation suggests that BED-driven optimization could serve as a unifying framework for GKS planning. While integrating BED into treatment planning offers valuable biological insights and may complement traditional physical dose parameters, whether BED can ultimately replace physical dose as the primary planning metric remains uncertain. All of the supporting evidence is retrospective and rarely incorporates prospectively collected data on toxicity or treatment efficacy endpoints. Prospective studies are essential to determine whether BED-optimized plans improve outcomes compared to standard physical dose prescriptions.
5. Conclusions
Our review suggests that BED may play a meaningful role in influencing clinical outcomes across a range of GKS indications. Among these, the association between BED and treatment efficacy is most consistent in AVMs, where BED aligns closely with obliteration rates. For other indications, including vestibular schwannoma and meningioma, these results remain more variable, though several studies support the potential utility of BED. While integrating BED into treatment planning offers valuable biological insights and may complement traditional physical dose parameters, whether BED can ultimately replace physical dose as the primary planning metric remains uncertain. Further research is needed to determine histology-specific radiobiological parameters for more precise BED estimation and to validate the routine clinical utility of BED through prospective studies especially those incorporating standardized toxicity endpoints, functional outcome measures, and harmonized radiobiological reporting.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/jcm15010381/s1, Supplementary Table S1: Adapted Newcastle–Ottawa Scale (NOS) for Observational Studies Included in the Review; Supplementary Table S2: Key BED Thresholds Across GKS Indications; Supplementary methods 1: the adapted version of the Newcastle–Ottawa Scale (NOS); Supplementary methods 2: the BED formulation; Supplementary Table S3: PRISMA 2020 Checklist [42].
Author Contributions
H.D., X.H. and Q.W. contributed equally to this work. Conceptualization, H.D., X.H., Q.W., Y.G., M.W. (Mengqi Wang), Y.W., X.S., M.W. (Maoyu Wang), W.P., S.Y. and W.W.; data curation, H.D., Q.W., Y.G., M.W. (Mengqi Wang), Y.W., X.S., M.W. (Maoyu Wang) and W.P.; writing—original draft preparation, H.D. and X.H.; writing—review and editing, S.Y. and W.W. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data are contained within the article.
Acknowledgments
The authors thank all participants and all investigators.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Leksell, L. Stereotactic radiosurgery. J. Neurol. Neurosurg. Psychiatry 1983, 46, 797–803. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tuleasca, C.; Régis, J.; Sahgal, A.; De Salles, A.; Hayashi, M.; Ma, L.; Martínez-Álvarez, R.; Paddick, I.; Ryu, S.; Slotman, B.J.; et al. Stereotactic radiosurgery for trigeminal neuralgia: A systematic review. J. Neurosurg. 2019, 130, 733–757. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahajan, U.V.; Desai, A.; Shost, M.D.; Cai, Y.; Anthony, A.; Labak, C.M.; Herring, E.Z.; Wijesekera, O.; Mukherjee, D.; Sloan, A.E.; et al. Stereotactic radiosurgery and resection for treatment of multiple brain metastases: A systematic review and analysis. Neurosurg. Focus 2022, 53, E9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kondziolka, D. Functional radiosurgery. Neurosurgery 1999, 44, 12–20; discussion 20–12. [Google Scholar] [CrossRef] [Scilit]
- Marchetti, M.; Sahgal, A.; De Salles, A.A.F.; Levivier, M.; Ma, L.; Paddick, I.; Pollock, B.E.; Regis, J.; Sheehan, J.; Suh, J.H.; et al. Stereotactic Radiosurgery for Intracranial Noncavernous Sinus Benign Meningioma: International Stereotactic Radiosurgery Society Systematic Review, Meta-Analysis and Practice Guideline. Neurosurgery 2020, 87, 879–890. [Google Scholar] [CrossRef] [Scilit]
- Warnick, R.E.; Paddick, I.; Mathieu, D.; Adam, E.; Iorio-Morin, C.; Leduc, W.; Hamel, A.; Johnson, S.E.; Bydon, M.; Niranjan, A.; et al. The relevance of biologically effective dose for pain relief and sensory dysfunction after Gamma Knife radiosurgery for trigeminal neuralgia: An 871-patient multicenter study. J. Neurosurg. 2024, 141, 461–473. [Google Scholar] [CrossRef] [Scilit]
- Tuleasca, C.; Peciu-Florianu, I.; Leroy, H.A.; Vermandel, M.; Faouzi, M.; Reyns, N. Biologically effective dose and prediction of obliteration of unruptured arteriovenous malformations treated by upfront Gamma Knife radiosurgery: A series of 149 consecutive cases. J. Neurosurg. 2021, 134, 1901–1911. [Google Scholar] [CrossRef] [Scilit]
- Fowler, J.F. 21 years of biologically effective dose. Br. J. Radiol. 2010, 83, 554–568. [Google Scholar] [CrossRef] [Scilit]
- Millar, W.T.; Hopewell, J.W.; Paddick, I.; Lindquist, C.; Nordstron, H.; Lidberg, P.; Garding, J. The role of the concept of biologically effective dose (BED) in treatment planning in radiosurgery. Phys. Med. 2015, 31, 627–633. [Google Scholar] [CrossRef] [Scilit]
- Jones, B.; Hopewell, J.W. Modelling the influence of treatment time on the biological effectiveness of single radiosurgery treatments: Derivation of “protective” dose modification factors. Br. J. Radiol. 2019, 92, 20180111. [Google Scholar] [CrossRef] [Scilit]
- Nesvick, C.L.; Graffeo, C.S.; Brown, P.D.; Link, M.J.; Stafford, S.L.; Foote, R.L.; Laack, N.N.; Pollock, B.E. The Role of Biological Effective Dose in Predicting Obliteration After Stereotactic Radiosurgery of Cerebral Arteriovenous Malformations. Mayo Clin. Proc. 2021, 96, 1157–1164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, Y.; Wang, M.; Wu, Y.; Deng, H.; Xu, Y.; Ren, Y.; Wang, C.; Wang, W. Gamma Knife Radiosurgery for Cushing’s Disease: Evaluation of Biological Effective Dose from a Single-Center Experience. J. Clin. Med. 2023, 12, 1288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tuleasca, C.; Faouzi, M.; Maeder, P.; Maire, R.; Knisely, J.; Levivier, M. Biologically effective dose correlates with linear tumor volume changes after upfront single-fraction stereotactic radiosurgery for vestibular schwannomas. Neurosurg. Rev. 2021, 44, 3527–3537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fowler, J.F. The linear-quadratic formula and progress in fractionated radiotherapy. Br. J. Radiol. 1989, 62, 679–694. [Google Scholar] [CrossRef] [Scilit]
- Kirkpatrick, J.P.; Meyer, J.J.; Marks, L.B. The linear-quadratic model is inappropriate to model high dose per fraction effects in radiosurgery. Semin. Radiat. Oncol. 2008, 18, 240–243. [Google Scholar] [CrossRef] [Scilit]
- Hopewell, J.W.; Millar, W.T.; Lindquist, C. Radiobiological principles: Their application to γ knife therapy. Prog. Neurol. Surg. 2012, 25, 39–54. [Google Scholar] [CrossRef] [Scilit]
- Graffeo, C.S.; Donegan, D.; Erickson, D.; Brown, P.D.; Perry, A.; Link, M.J.; Young, W.F.; Pollock, B.E. The Impact of Insulin-Like Growth Factor Index and Biologically Effective Dose on Outcomes After Stereotactic Radiosurgery for Acromegaly: Cohort Study. Neurosurgery 2020, 87, 538–546. [Google Scholar] [CrossRef] [Scilit]
- Balossier, A.; Tuleasca, C.; Cortet-Rudelli, C.; Soto-Ares, G.; Levivier, M.; Assaker, R.; Reyns, N. Gamma Knife radiosurgery for acromegaly: Evaluating the role of the biological effective dose associated with endocrine remission in a series of 42 consecutive cases. Clin. Endocrinol. 2021, 94, 424–433. [Google Scholar] [CrossRef] [Scilit]
- Balossier, A.; Tuleasca, C.; Cortet-Rudelli, C.; Soto-Ares, G.; Levivier, M.; Assaker, R.; Reyns, N. Gamma Knife surgery for recurrent or persistent Cushing disease: Long-term results and evaluation of biological effective dose in a series of 26 patients. Swiss Med. Wkly. 2021, 151, w20520. [Google Scholar] [CrossRef] [Scilit]
- Graffeo, C.S.; Perry, A.; Link, M.J.; Brown, P.D.; Young, W.F.; Pollock, B.E. Biological Effective Dose as a Predictor of Hypopituitarism After Single-Fraction Pituitary Adenoma Radiosurgery: Dosimetric Analysis and Cohort Study of Patients Treated Using Contemporary Techniques. Neurosurgery 2021, 88, E330–E335. [Google Scholar] [CrossRef] [Scilit]
- Dumot, C.; Schlesinger, D.; Mantziaris, G.; Dayawansa, S.; Xu, Z.; Sheehan, J.P. Role of biological effective dose for prediction of endocrine remission in acromegaly patients treated with stereotactic radiosurgery. Pituitary 2023, 26, 124–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dedeciusova, M.; Komarc, M.; Faouzi, M.; Levivier, M.; Tuleasca, C. Tumor control and radiobiological fingerprint after Gamma Knife radiosurgery for posterior fossa meningiomas: A series of 46 consecutive cases. J. Clin. Neurosci. 2022, 100, 196–203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huo, M.; Rose, M.; van Prooijen, M.; Cusimano, M.D.; Laperriere, N.; Heaton, R.; Gentili, F.; Payne, D.; Shultz, D.B.; Kongkham, P.; et al. Importance of Cobalt-60 Dose Rate and Biologically Effective Dose on Local Control for Intracranial Meningiomas Treated with Stereotactic Radiosurgery. Neurosurgery 2022, 90, 140–147. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaaban, A.; Pham, D.; Tos, S.M.; Mantziaris, G.; Schlesinger, D.; Sheehan, J.P. Biological effective dose as a predictor of local tumor control in stereotactic radiosurgery treated parasellar meningioma patients. J. Neurooncol. 2024, 170, 377–385. [Google Scholar] [CrossRef] [Scilit]
- Villafuerte, C.J.; Shultz, D.B.; Laperriere, N.; Gentili, F.; Heaton, R.; van Prooijen, M.; Cusimano, M.D.; Hodaie, M.; Schwartz, M.; Berlin, A.; et al. Radiation Dose Rate, Biologically Effective Dose, and Tumor Characteristics on Local Control and Toxicity After Radiosurgery for Acoustic Neuromas. World Neurosurg. 2021, 152, e512–e522. [Google Scholar] [CrossRef] [Scilit]
- Tuleasca, C.; Toma-Dasu, I.; Duroux, S.; Starnoni, D.; George, M.; Maire, R.; Daniel, R.T.; Patin, D.; Schiappacasse, L.; Dasu, A.; et al. The Relevance of Biologically Effective Dose for Hearing Preservation After Stereotactic Radiosurgery for Vestibular Schwannomas: A Retrospective Longitudinal Study. Neurosurgery 2023, 92, 1216–1226. [Google Scholar] [CrossRef] [Scilit]
- Tuleasca, C.; Toma-Dasu, I.; Duroux, S.; George, M.; Maire, R.; Daniel, R.T.; Patin, D.; Schiappacasse, L.; Dasu, A.; Faouzi, M.; et al. Impact of the Mean Cochlear Biologically Effective Dose on Hearing Preservation After Stereotactic Radiosurgery for Vestibular Schwannoma: A Retrospective Longitudinal Analysis. Neurosurgery 2024, 94, 174–182. [Google Scholar] [CrossRef] [Scilit]
- Grogan, D.; Dumot, C.; Tewari, A.; Mantziaris, G.; Dayawansa, S.; Schlesinger, D.; Sheehan, J. Biologically Effective Dose and Prediction of Obliteration of Arteriovenous Malformations in Pediatric Patients Treated by Gamma Knife Radiosurgery. Neurosurgery 2024, 94, 614–621. [Google Scholar] [CrossRef] [Scilit]
- Zubatkina, I.; Toma-Dasu, I.; Dasu, A.; Levivier, M.; Tuleasca, C.; Ivanov, P. Clinically Driven Alpha/Beta Ratios for Melanoma Brain Metastases and Investigation of Biologically Effective Dose as a Predictor for Local Control After Radiosurgery: A Proof of Concept in a Retrospective Longitudinal Series of 274 Consecutive Lesions. Neurosurgery 2024, 94, 423–430. [Google Scholar] [CrossRef] [Scilit]
- Tuleasca, C.; Paddick, I.; Hopewell, J.W.; Jones, B.; Millar, W.T.; Hamdi, H.; Porcheron, D.; Levivier, M.; Régis, J. Establishment of a Therapeutic Ratio for Gamma Knife Radiosurgery of Trigeminal Neuralgia: The Critical Importance of Biologically Effective Dose Versus Physical Dose. World Neurosurg. 2020, 134, e204–e213. [Google Scholar] [CrossRef] [Scilit]
- Tang, K.; Zhang, N.; Yuan, X.; Chu, L.; Qian, Z.; Li, Y. Radiosurgical Biologically Effective Dose on Trigeminal Root Division and Section for Outcomes of Idiopathic Trigeminal Neuralgia Type 1: A Multicentre Retrospective Cohort Study. World Neurosurg. 2025, 193, 975–1001. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deng, H.; Gao, Y.; Wu, Y.; Wang, M.; Xiao, L.; Chen, R.; Zhang, Z.; Pan, W.; Wang, W. Differential impact of biologically effective dose in distal versus proximal gamma knife targets for trigeminal neuralgia. Front. Neurol. 2025, 16, 1614981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tuleasca, C.; Carey, G.; Barriol, R.; Touzet, G.; Dubus, F.; Luc, D.; Carriere, N.; Reyns, N. Impact of biologically effective dose on tremor decrease after stereotactic radiosurgical thalamotomy for essential tremor: A retrospective longitudinal analysis. Neurosurg. Rev. 2024, 47, 73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Plataniotis, G.A.; Dale, R.G. Biologically effective dose-response relationship for breast cancer treated by conservative surgery and postoperative radiotherapy. Int. J. Radiat. Oncol. Biol. Phys. 2009, 75, 512–517. [Google Scholar] [CrossRef] [Scilit]
- Moreno, A.C.; Fellman, B.; Hobbs, B.P.; Liao, Z.; Gomez, D.R.; Chen, A.; Hahn, S.M.; Chang, J.Y.; Lin, S.H. Biologically Effective Dose in Stereotactic Body Radiotherapy and Survival for Patients with Early-Stage NSCLC. J. Thorac. Oncol. 2020, 15, 101–109. [Google Scholar] [CrossRef] [Scilit]
- Farooqi, A.; Ludmir, E.B.; Mitchell, K.G.; Antonoff, M.B.; Tang, C.; Lee, P.; Chang, J.; Elamin, Y.; Gomez, D.R.; Gandhi, S.J. Increased biologically effective dose (BED) to the primary tumor is associated with improved survival in patients with oligometastatic NSCLC. Radiother. Oncol. 2021, 163, 114–118. [Google Scholar] [CrossRef] [Scilit]
- Kocher, M.; Treuer, H.; Voges, J.; Hoevels, M.; Sturm, V.; Müller, R.P. Computer simulation of cytotoxic and vascular effects of radiosurgery in solid and necrotic brain metastases. Radiother. Oncol. 2000, 54, 149–156. [Google Scholar] [CrossRef] [Scilit]
- Leith, J.T.; Cook, S.; Chougule, P.; Calabresi, P.; Wahlberg, L.; Lindquist, C.; Epstein, M. Intrinsic and extrinsic characteristics of human tumors relevant to radiosurgery: Comparative cellular radiosensitivity and hypoxic percentages. Acta Neurochir. Suppl. 1994, 62, 18–27. [Google Scholar] [CrossRef] [Scilit]
- Barzaghi, L.R.; Albano, L.; Scudieri, C.; Gigliotti, C.R.; Del Vecchio, A.; Mortini, P. Factors affecting long-lasting pain relief after Gamma Knife radiosurgery for trigeminal neuralgia: A single institutional analysis and literature review. Neurosurg. Rev. 2021, 44, 2797–2808. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.Y.; Sandhu, S.; Miller, D.; Solberg, T.; Dorsey, J.F.; Alonso-Basanta, M. Higher dose rate Gamma Knife radiosurgery may provide earlier and longer-lasting pain relief for patients with trigeminal neuralgia. J. Neurosurg. 2015, 123, 961–968. [Google Scholar] [CrossRef] [Scilit]
- Pop, L.A.; Millar, W.T.; van der Plas, M.; van der Kogel, A.J. Radiation tolerance of rat spinal cord to pulsed dose rate (PDR-) brachytherapy: The impact of differences in temporal dose distribution. Radiother. Oncol. 2000, 55, 301–315. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.