


Abstract
Background: This study aimed to investigate the associations between sex and the relative effect of rhythm control over rate control in patients with atrial fibrillation. Methods: We used the National Health Insurance Service database to select patients treated for atrial fibrillation within one year after diagnosis. The primary composite outcome comprised cardiovascular death, ischemic stroke, heart failure hospitalization, or acute myocardial infarction. Results: During the mean follow-up (4.9 ± 3.2 years), the benefit of rhythm control over rate control on the primary composite outcome became statistically insignificant after 3 months from atrial fibrillation diagnosis in women while remained steadily until 12 months in men. The risk of primary composite outcome for rhythm control was lower than that for rate control in both sexes if it was initiated within 6 months (men: HR = 0.86, 95%CI = 0.79–0.94; women: HR = 0.85, 95%CI = 0.78–0.93; P for interaction = 0.844). However, there was significant interaction between sex and the relative effect of rhythm control if it was initiated after 6 months (men: HR = 0.72, 95%CI = 0.52–0.99; women: HR = 1.32, 95%CI = 0.92–1.88; P for interaction = 0.018). Conclusion: Rhythm control resulted in lower risk of primary composite outcome than rate control in both sexes; however, the treatment initiation at an earlier stage might be considered in women.
1. Introduction
Atrial fibrillation (AF) is associated with increased risks of stroke, congestive heart failure (HF), and mortality [1]. Rhythm control and rate control are representative treatment strategies for atrial fibrillation and previous randomized trials have attempted to demonstrate differences in long-term outcomes between the two strategies. The landmark Atrial Fibrillation Follow-up Investigation of Sinus Rhythm Management (AFFIRM) trial reported no significant differences between these two strategies with respect to mortality and stroke incidence [2,3,4]. Similarly, a meta-analysis of randomized clinical trials comparing rate and rhythm control showed no significant differences in the risk of all-cause death [5]. In contrast, recent studies have demonstrated that early rhythm control (defined as rhythm control initiated ≤12 months from AF diagnosis) compared to rate control in patients with AF is associated with a lower risk of the first primary outcome, comprising stroke, HF hospitalization, acute coronary syndrome, and cardiovascular death [6,7,8].
Many studies highlighten sex differences in the epidemiology, pathophysiology, and prognosis of AF [1]. In this regard, several studies have demonstrated that despite the tendency of women to be more symptomatic compared to men, they are less likely to undergo rhythm control [9,10,11,12]. In women with AF, the use of antiarrhythmic drugs (AADs) were associated with higher rate of life-threatening adverse events [13]. Moreover, female sex was associated with higher AF recurrence rates after radiofrequency ablation compared to male sex, which may influence the effectiveness of AF treatment [14]. However, the effect of sex differences on outcomes of rhythm and rate control has not been well elucidated yet. Similarly, it is not clear whether the effect of timing of treatment initiation (duration from AF diagnosis to the first initiation of rhythm or rate control) on outcomes is affected by sex differences. Therefore, this study was designed to analyze the effect of sex on the comparative effectiveness of early rhythm control over rate control and clarify whether sex makes a difference in the timing of treatment initiation to improve cardiovascular outcomes.
2. Methods
2.1. Study Design and Population
This retrospective cohort study was based on the National Health Claims Database established by the National Health Insurance Service (NHIS) of Korea, which incorporates the data of 558,147 participants recruited from a total of 5.5 million individuals aged ≥60 years included in the database.
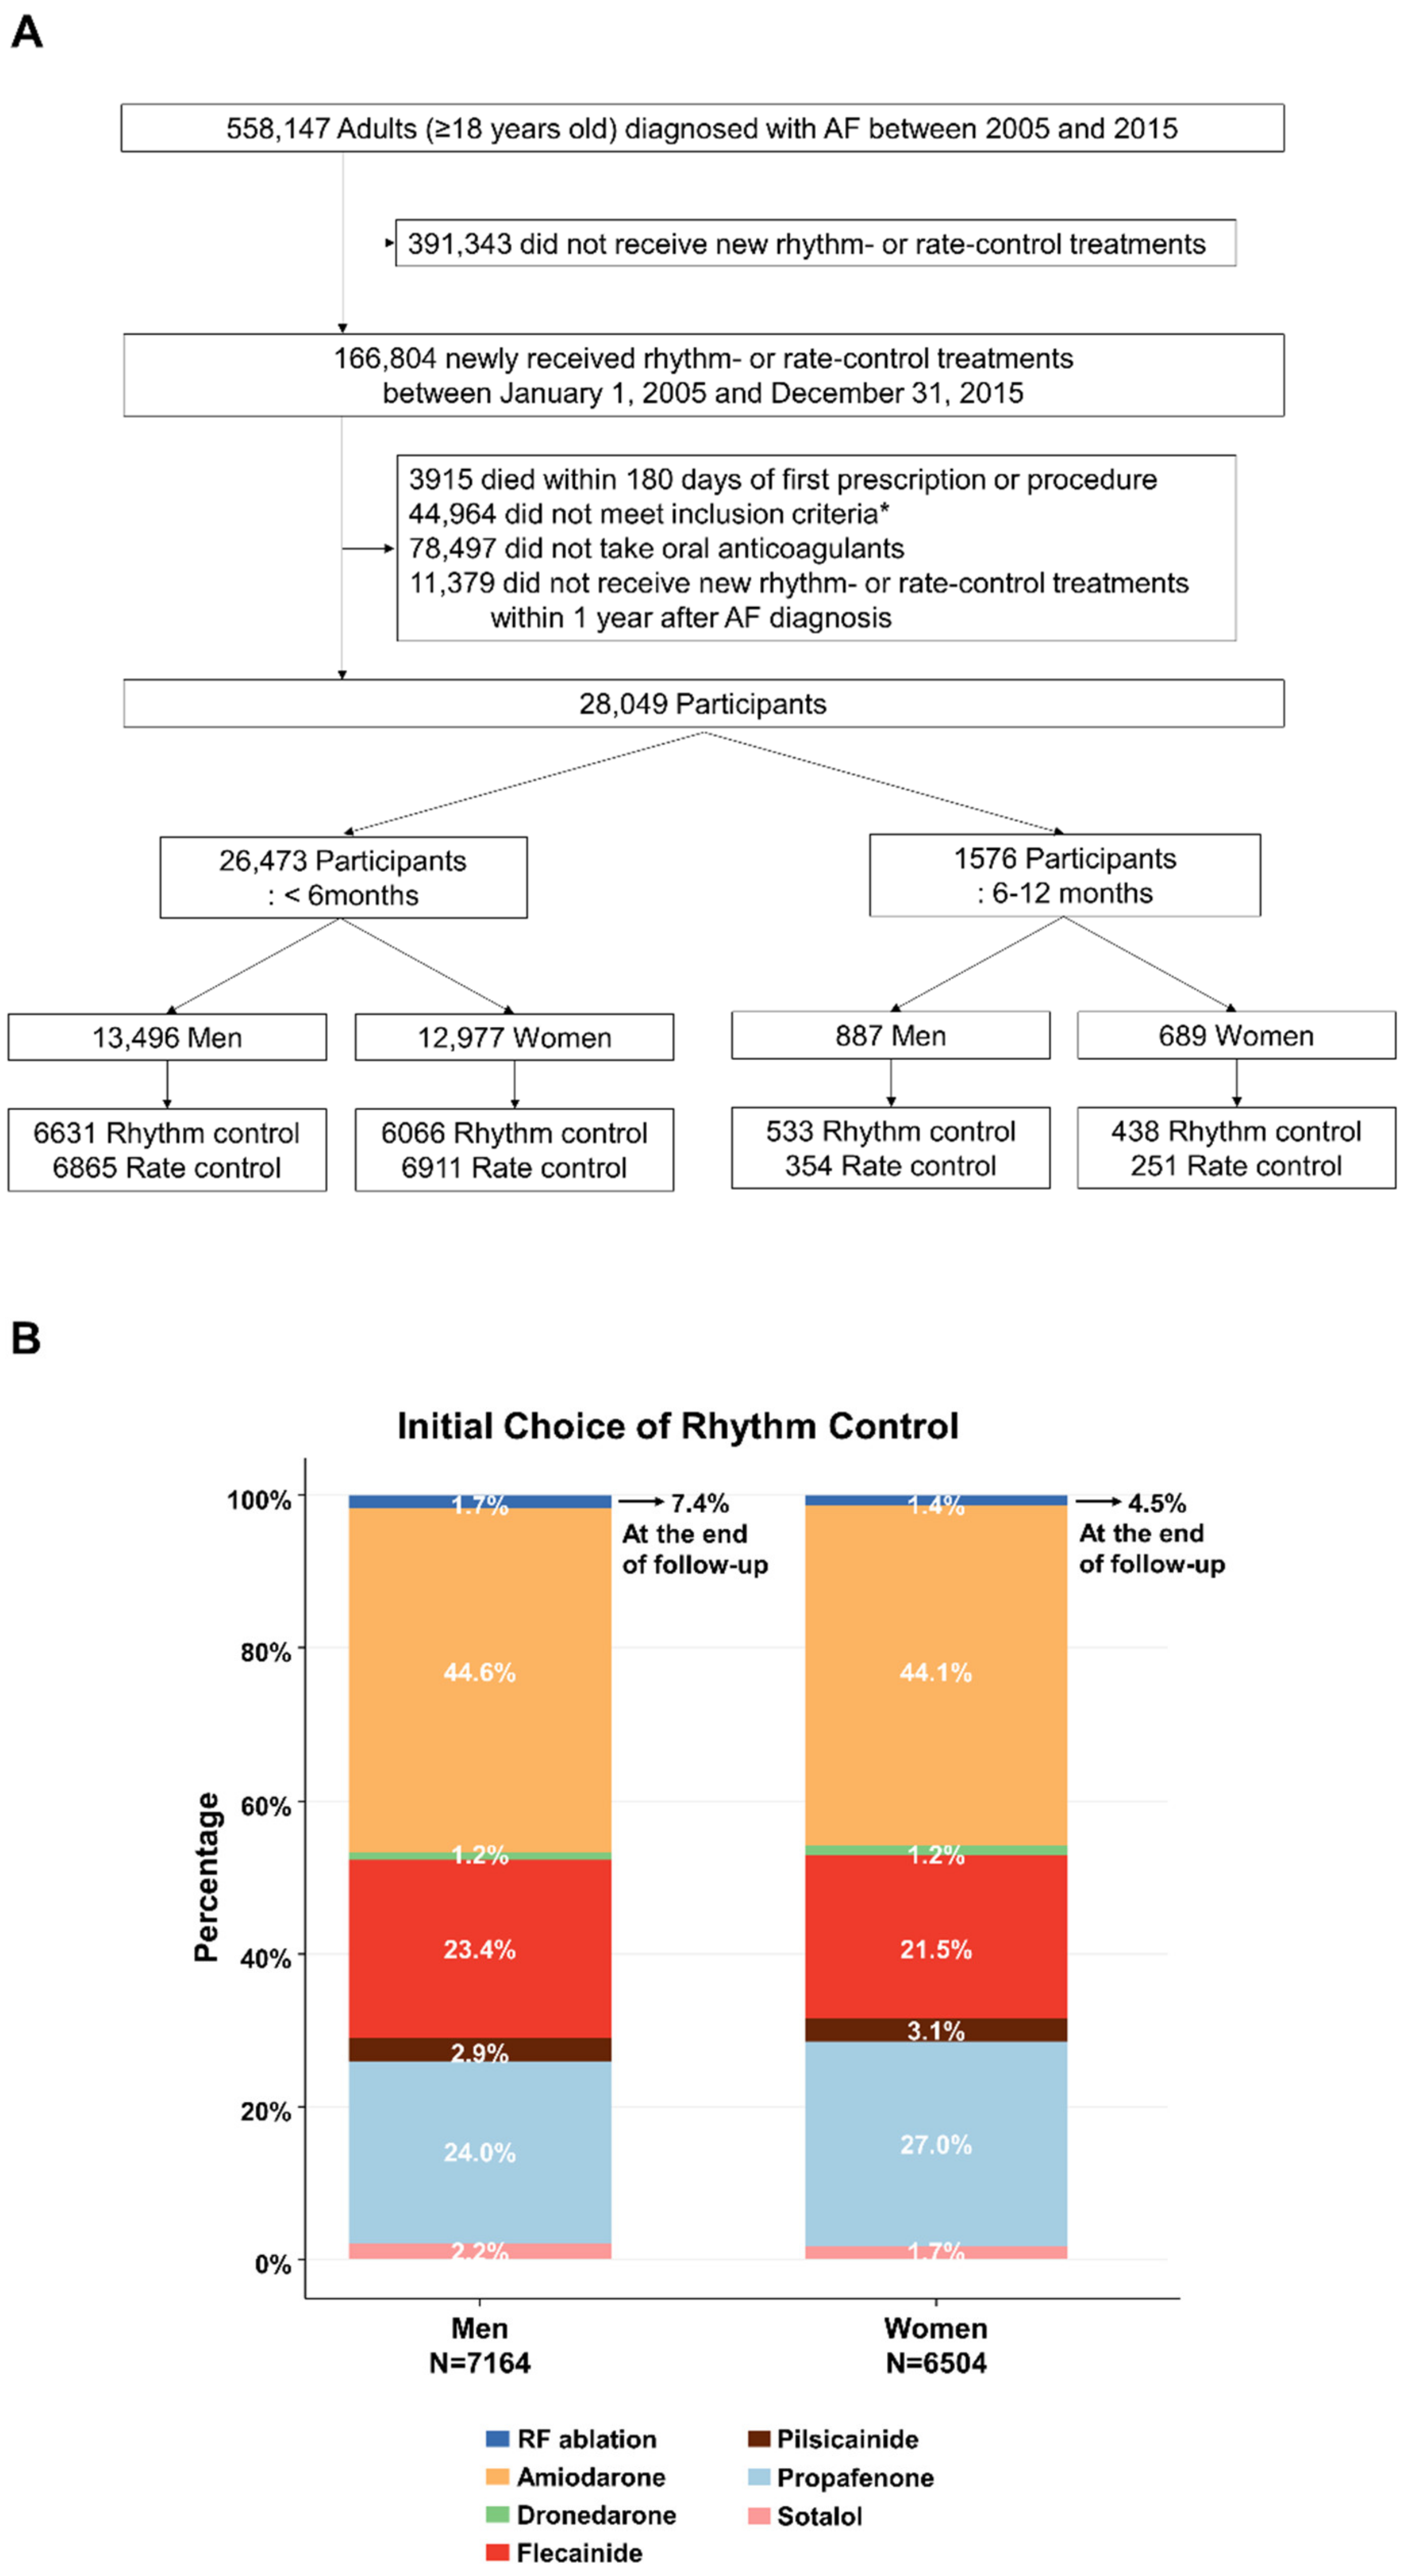
Supplementary Table S1 presents the details of this study design. Adults (age ≥18 years) who were treated for AF within one year after AF diagnosis between 1 January 2005 and 31 December 2015, were screened. Inclusion criteria were as follows: individuals aged ≥ 75 years; individuals with a previous transient ischemic attack or stroke; and those who at least met two of the following criteria: age ≥ 65 years, women, hypertension, diabetes mellitus, HF, previous myocardial infarction (MI), or chronic kidney disease [6,8]. Accordingly, patients were excluded from the study if within a six-month period from the initiation of AF treatment, did not receive adequate oral anticoagulants (for at least three months) or died. (Figure 1A).
Figure 1.
Flow chart. Selection of study participants (A) and initial rhythm control strategies according to sex and the timing of treatment initiation (B). * Age ≥ 75 years, previous transient ischemic attack or stroke, or two of the following criteria: age ≥ 65 years, women, hypertension, diabetes mellitus, heart failure, previous myocardial infarction, or chronic kidney disease. AF, atrial fibrillation.
The Tenth Revision of International Classification of Disease (ICD-10) code I48 was used to define AF. The positive predictive value for AF diagnosis was 94.1% in the NHS database [15]. We adopted a new-user and intention-to-treat design to compare outcomes of rhythm- or rate control. Patients who have never been prescribed the drugs of interest or undergone radiofrequency ablation for AF were regarded as new users. Intention-to-treat with rhythm control was defined as performance of radiofrequency ablation or over three-months’ administration of any AADs within the six-month period since the first prescription. Intention to treat with rate control was defined as a prescription any rate control drugs for at least three months within a six-month period since the first prescription, without pre-scription of AADs and radiofrequency ablation. Accordingly, patients who had received both rhythm- and rate control simultaneously were regarded as the rhythm control group. Claim codes for antiarrhythmic- and rate control drugs, and radiofrequency ablation are demonstrated in Supplementary Table S2. To assess the effect of the timing of treatment initiation, patients were divided into two groups as following: AF treatment initiation <6 months group and ≥6 months group after AF diagnosis.
2.2. Outcome and Follow-Up
The primary composite outcome constituted of is chemic stroke, HF hospitalization, acute MI, and cardiovascular death. We also examined the risks of each component of the primary composite outcome. The definition of the outcomes is detailed in Supplementary Table S3. The composite safety outcome consisted of all-cause death, intracranial or gastrointestinal bleeding that required hospital admission, or prespecified serious adverse events related to rhythm control. Accordingly, cardiac tamponade, syncope, sick sinus syndrome, atrioventricular block, pacemaker implantation, and sudden cardiac arrest were defined as prespecified serious adverse events related to rhythm control. The study outcomes were followed up from 180 days after the first recorded prescription or procedure until December 31, 2016, or death. Details of the variables are also presented in Supplementary Table S2.
2.3. Statistical Analysis
Descriptive data were reported as means (standard deviations) for continuous variables and numbers (percentages) for categorical variables. After dividing into two groups according to treatment initiation, overlap weighting based on a propensity score (ps) was used to assess the differences in baseline characteristics between the rhythm- and rate control groups among men and women, respectively. The propensity score, which indicates the probability of being assigned to a rhythm control group, was calculated by logistic regression analysis based on socio-demographic factors, AF duration, year in which treatment was initiated, level of care at which the AF treatment was provided, clinical risk scores, medical history, and concurrent medication use (variables in Table 1). Continuous variables were modelled as cubic spline functions. Supplementary Figure S1 depicted the distribution of propensity scores before and after overlap weighting, respectively. The overlap weight was calculated as ‘1-ps’ in rhythm control groups and as ‘ps’ in rate control groups [16]. A standardized mean difference < 0.1 was considered to indicate acceptable differences in all baseline variables between the two groups. Competing risk regression by the Fine and Gray method was used to consider all-cause death as a competing event when estimating the risks of clinical outcomes [17]. Cofactors with a standardized mean difference of 0.1 or more after weighting were included as covariates in the competing risk regression analysis. Schoenfeld residuals were used to evaluate the proportional hazards assumption and violation of the assumption was not found. To explore the treatment timing-dependent effect of rhythm control on the out-comes, Cox proportional hazards models were fit to the entire weighted study population using an interaction term for the treatment timing after AF diagnosis (modelled as a natural spline) and treatment (rhythm- or rate control). Standard errors were estimated using 1,000 bootstrap replicates. Statistical analyses were performed by SAS, version 9.3 (SAS Institute, Cary, NC, USA) and R version 4.1.0 (The R Foundation, www.R-project.org (accessed on 1 September 2021)).
Table 1.
Baseline characteristics of men and women treated with rhythm- or rate control before overlap weighting.
2.4. Sensitivity Analyses
First, one-to-one ps matching (without replacement with a caliper of 0.01) was used instead of overlap weighting. Second, we performed an analysis after including patients treated with AADs as the initial choice of rhythm control. Third, we performed falsification analysis to measure systematic bias in this study by employing 24 pre-specified falsification endpoints, with true hazard ratios of 1.
3. Results
3.1. Baseline Characteristics
Among 28,049 patients who underwent AF treatment within 1 year from AF diagnosis, 14,383 (51.3%) were men. Compared to men, women were older (68.5 ± 11.4 vs. 66.0±11.2 years, p < 0.001) and had a higher CHA2DS2-VASc score (4.3 ± 1.7 vs. 3.4 ± 1.4, p < 0.001) (Table 1). Further, the time period between the treatment initiation and AF diagnosis was shorter for women (0.9 ± 2.2 vs. 1.1 ± 2.3 months, p < 0.001), and they were less treated with rhythm control (47.6% vs. 49.8%, p < 0.001).
Among the initial rhythm control strategies, amiodarone accounted for the largest portion (2874 [44.1%] of 6504 women and 3193 [44.6%] of 7164 men), followed by propafenone and flecainide (Figure 1B). Radiofrequency ablation was performed in 88 (1.4%) of women and 120 (1.7%) of men at the time of enrollment and was eventually per-formed in 294 (4.5%) of women and 530 (7.4%) of men until the end of follow-up, respectively.
Baseline characteristics of men and women treated with rhythm- or rate control be-fore and after overlap weighting are presented in Table 1 and Table 2. Compared to rate-control patients, rhythm-control patients were younger and tended to have a higher prevalence of comorbidities for both men and women. After weighting, all baseline characteristics were well-balanced between rhythm- and rate control group in both sexes.
Table 2.
Baseline characteristics of men and women treated with rhythm- or rate control after overlap weighting.
3.2. Sex Difference of the Primary Composite Outcome according to the Timing of Rhythm Control
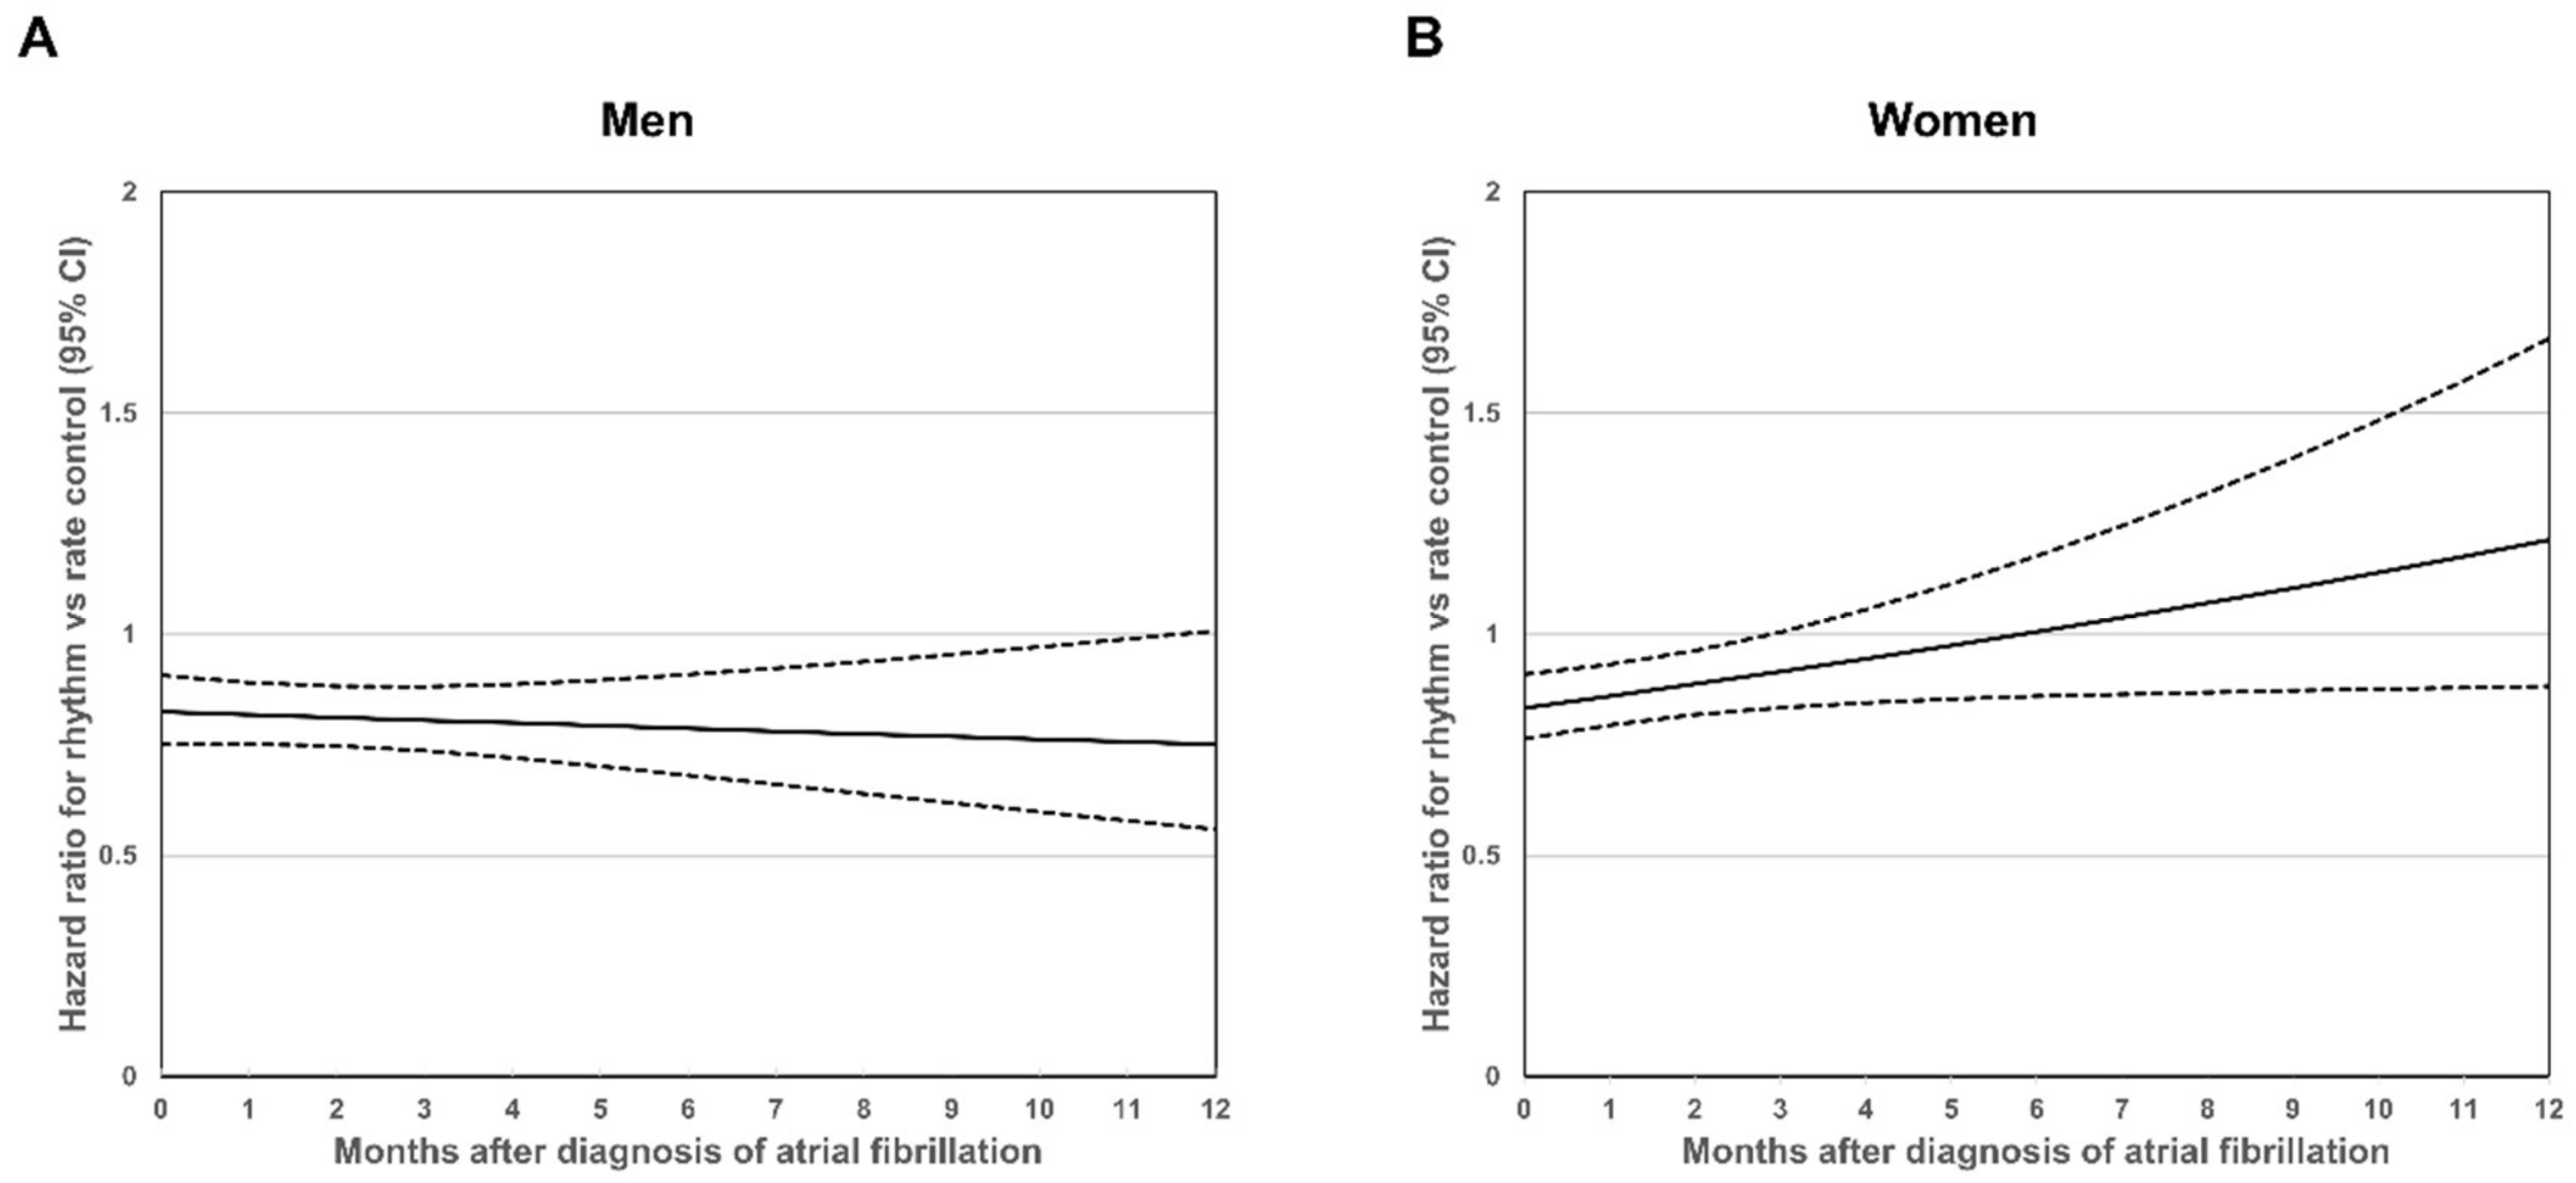
The mean follow-up times were 4.9±3.2 years. Cox proportional hazard models with an interaction term showed that women had a linear relationship, wherein the relative effect of rhythm control over rate control on the primary composite outcome became attenuated as the timing of treatment initiation was delayed (Figure 2A, B). Rhythm control was associated with a significantly lower risk of the primary composite outcome compared to rate control if it was initiated within 3 months from AF diagnosis; however, the benefit be-came statistically insignificant after 3 months. On the other hand, in men, relative effect of rhythm control over rate control on the primary composite outcome was maintained until 12 months after AF diagnosis.
Figure 2.
Relationship between treatment timing and primary composite outcome risk. Data shown are within 1 year after the first diagnosis of atrial fibrillation. (A) Men. (B) Women. Hazard ratio = 1 means an equal risk of outcomes in participants treated with rhythm- and rate-control. Dashed black lines show the 95% confidence interval.
In the group with AF treatment initiated within 6 months after the first diagnosis of AF, the risk of primary composite outcome for rhythm control tended to be lower than that of rate control in both the sexes (men: HR = 0.86, 95% CI, 0.79–0.94, P = 0.001; women: HR = 0.85, 95% CI, 0.78–0.93, P < 0.001; P for interaction = 0.844) (Table 3). In the group with AF treatment initiated after 6 months, significant interaction was demonstrated between sex and the relative effect of rhythm control over rate control (men: HR = 0.72, 95% CI, 0.52–0.99, P = 0.045; women: HR = 1.32, 95% CI, 0.92–1.88, P = 0.134; P for interaction = 0.018).
Table 3.
Relative effect of rhythm control over rate control on primary composite outcome after overlap weighting.
The relative effects of rhythm control over rate control on the individual outcomes are presented in Table 4. Among the individual cardiovascular outcomes, there was a significant interaction between the relative effect of rhythm control over rate control on the prevention of ischemic stroke and sex.
Table 4.
Relative effect of rhythm control over rate control on individual components of the primary composite outcome after overlap weighting.
The relative effects of rhythm control over rate control on safety outcomes are presented in Supplementary Table S4. There was a trend of the composite safety outcome towards an increased risk in women and reduced risk in men, irrespective of timing of treatment initiation (<6 months: HR = 0.97 in men, HR = 1.10 in women, p for interaction = 0.040; ≥6 months: HR = 0.85 in men, HR = 1.27 in women, p for interaction = 0.093).
3.3. Sensitivity Analyses
Among the patients in whom AF treatment was initiated ≥6 months, significant interaction between sex and the relative effect of rhythm control over rate control on the primary composite outcome was consistently observed in one-to-one ps matching analysis (Supplementary Table S5). Enrollment of patients taking AADs as the initial strategy of rhythm control showed consistent results (Supplementary Table S6). In the analyses of 24 falsification endpoints, the 95% CIs of the associations of rhythm control with each end-point covered 1 in 24 (100%) endpoints (Supplementary Table S7).
4. Discussion
4.1. Main Findings
The principal findings of this nationwide cohort study that categorized patients according to sex and the timing of treatment initiation were as follows. First, as treatment initiation was delayed, the relative effect of rhythm control over rate control on primary composite outcome was attenuated gradually in women while remained steadily until 12 months in men. Second, among patients who received AF treatment after 6 months from AF diagnosis, there were significant interactions between sex and relative effects of rhythm control over rate control on the primary composite outcome. Third, compared to rate control, rhythm control showed a trend towards an increased risk of the composite safety outcome in women, irrespective of timing of treatment initiation.
4.2. Sex Differences in Benefits and Harms of Rhythm Control
AF is a common arrhythmic disease with a higher prevalence in men than in women; however, stroke and mortality risk are significantly higher in women than in men [18,19]. Sex differences in outcomes of rhythm control over rate control were investigated in subgroup analyses of previous trials. The AFFIRM trial showed that mortality rates between rhythm- and rate control did not differ by sex [3]. In comparison, the RACE trial showed that rhythm control was associated with a higher incidence of the primary outcome compared to rate control in women, not in men [13]. Recently, the EAST-AFNET 4 and Kim et al. reported that in comparison with usual care or rate control irrespective of sex, rhythm control initiated within 12 months from AF diagnosis lowered the risk of the first primary outcome (i.e., ischemic stroke, HF hospitalization, acute MI, and cardiovascular death) [6,8]. However, the aforementioned trials did not show the relationship between the outcome of rhythm control and timing of AF treatment initiation in men and women, respectively.
4.3. Earlier Rhythm Control Therapy Is Needed in Women
The present study’s findings show that the relative effects of rhythm control over rate control on the primary composite outcome was reversed in women after 6 months from AF diagnosis. Significant interactions in the group that received AF treatment within 6–12 months from AF diagnosis mainly originated from the interaction between sex and relative effect of rhythm control over rate control on ischemic stroke. In a previous randomized controlled trial, which showed that rhythm control offered no advantage or significant disadvantage for ischemic stroke over rate control irrespective of sex, most patients al-ready had AF for >2 years [20]. In the RACE trial, rhythm control led to more thromboembolic complications in women, whereas the opposite trend was observed in men. However, a recent large cohort study reported that rhythm control was associated with a reduced risk of ischemic stroke when it was prescribed within 7 days from AF diagnosis regardless of sex [21]. This finding also supported the results of this study in the group that received AF treatment <6 months from AF diagnosis.
Precise mechanisms of sex differences in outcomes of rhythm over rate control have not been fully elucidated yet. The possible explanation for the waning of relative efficacy of early rhythm-control therapy is that women are older than men at the initial treatment for AF. This finding is consistent with those of previous reports, although women’s symptoms and quality of life were poorer than those of men. Further, they were referred later and were less likely to undergo rhythm control [9,10,11,12]. However, a significant interaction between sex and the primary composite outcome was still noted even after weighing age and comorbidities. Among patients treated with catheter ablation, women had a significantly smaller mean voltage, slow conduction velocity, and greater proportion of complex fractionated signals in the left atrium compared to men [22]. Since atrial remodeling progresses gradually over time, women may have a narrower window to obtain benefits from rhythm control because they already have more advanced atrial remodeling at the time of AF treatment initiation.
4.4. Increased Safety Outcome by Rhythm Control in Women
In this study, compared with men, women had a higher risk of the composite safety outcome and adverse event related to rhythm control. Previous studies have reported comparable results for adverse events related to rhythm control. One study demonstrated that AADs tended to increase risks of torsades de pointes and sick sinus syndrome more in women compared to men [23]. Additionally, as use of catheter ablation has been increased during the last few decades, female sex has become a predictor of in-hospital complications for any cardiac arrhythmia [24]. A large retrospective study reported that women tended to have higher risks of access site complications, cardiac tamponade and pericardial effusions, and postoperative bleeding requiring transfusions [25,26,27]. Therefore, even if rhythm control can be initiated at an earlier stage, the benefit of rhythm control in women with AF must be balanced against the risk of adverse event related to rhythm control.
4.5. Study Limitations
This study has several limitations. First, a claims-based database was used; hence, it is not possible to evaluate the changes in AF burden before and after AF treatment, the tar-get heart rate for rate control, and the number of patients who had reached the target heart rate. Moreover, AF diagnosis and treatment strategies were defined by ICD-10 or claim codes only; therefore, it was not possible to obtain the data regarding the AF type (paroxysmal vs. non-paroxysmal), and the presence of symptoms (symptomatic vs. asymptomatic); thus, the role of AF type and the symptom status as contributors to long-term out-comes remain unknown.
Second, the findings from this observational study cannot establish causality due to unmeasured or residual confounding factors. In this study, the vast majority of patients received warfarin. Among patients treated with warfarin, the higher incidence of stroke in women could be related to a lower time in therapeutic range compared to men [28,29]. The frequency of warfarin use and labile international normalized ratio values also can explain the trend towards higher bleeding events in women in the rhythm control group [28]. Therefore, results in population treated with direct anticoagulants are additionally required. Moreover, uncontrolled lifestyle factors (such as obesity, alcohol intake, and exercise habit) might lead to the detrimental long-term outcomes in patients with AF, and it was not possible to determine their effect.
Third, radiofrequency ablation was performed as an initial rhythm control strategy in only 1.7% of men and 1.4% of women, which were significantly lower compared to the 7% in the EAST-AFNET 4 trial. The cause of this phenomenon was that the national health insurance had reimbursed the cost of treatment only to patients who were diagnosed as drug-refractory AF or could not maintain AADs due to drug-related side effects, tachycardia-bradycardia syndrome, or other conditions [6]. Considering the superiority of radiofrequency ablation over AADs for maintenance of sinus rhythm, the absence of a reasonable portion of patients treated with ablation might have significantly limited the impact of the outcomes of this study. In addition, the reduced benefit of “rhythm control therapy” in women might be attributable to AAD therapy issues rather than rhythm control strategy, as AADs carries higher risk of proarrhythmia and toxicity compared to both ablation and rate control therapy, particularly in women Therefore, further randomized trials are necessary to reflect the long-term efficacy of ablation strategy [30,31].
Fourth, the specific reasons for choosing rhythm control over rate control, and immediate over delayed initiation of treatment are difficult to be evaluated because these decisions vary by physicians. Accordingly, this ambiguity might have caused potential bias. Nevertheless, the results of the falsification analysis showed that systematic bias was less likely to exist, and sufficient overlap of propensity scores were identified between rhythm- and rate control groups, which proves the balance between the two therapies.
Fifth, since we excluded patients with AF who did not undergo therapy or who had a history of AF treatment, the proportions of treatment strategies in this study may not reflect the preferences in real-world practice. Sixth, this study enrolled only high-risk patients with a mean CHA2DS2-VASc score of 3.3 using inclusion criteria similar to that of EAST-AFNET 4. Thus, further investigation is warranted to elucidate sex differences in effects of rhythm control over rate control in low-risk patients.
Finally, in this study, the mean period between treatment initiation and AF diagnosis was 1.0 ± 2.2 month and only 5% of the patients were treated between 6 and 12 months after AF diagnosis. Therefore, repeated studies will be required to solidify the conclusion that sex differences influence the outcomes if AF treatment is delayed.
5. Conclusions
Among patients who underwent rhythm or rate control within one year after AF diagnosis, lower risk tendency of primary composite outcome was shown in rhythm control than rate control in both sexes. However, as treatment initiation was delayed, the benefit of early rhythm control was attenuated gradually in women, while it was maintained in men. Therefore, in women, rhythm control might be taken into consideration at an earlier stage with a careful assessment of the balance between its benefit and risk of adverse event.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/jcm11174991/s1, Figure S1: Distributions of the propensity scores in men (A) and women (B) before and after overlap weighting; Table S1: Summary of strategies for emulating target trial. Table S2: Definitions and ICD–10 codes used for defining comorbidities, rate- and rhythm-control methods for atrial fibrillation. Table S3: Definitions and ICD-10 codes used for defining study outcomes. Table S4: Baseline characteristics of men and women treated with rhythm- or rate control before overlap weighting. Table S5: Baseline characteristics of men and women treated with rhythm- or rate control after overlap weighting. Table S6: Relative effect of rhythm over rate control on safety outcomes. Table S7: The relative effect of rhythm control over rate control on primary composite outcome in men and women after 1:1 propensity score matching. Table S8: The relative effect of anti–arrhythmic drugs over rate control on primary composite outcome in men and women according to timing of treatment initiation. Table S9: Risk of 24 falsification endpoints in weighted male and female patients undergoing rhythm control compared with rate control.
Author Contributions
Conceptualization, J.-H.S., P.-S.Y. and B.J.; Data curation, D.K., E.J. and P.-S.Y.; Formal analysis, D.-S.K., D.K., P.-S.Y. and B.J.; Funding acquisition, B.J.; Investigation, D.-S.K., D.K., E.J., P.-S.Y. and B.J.; Methodology, D.-S.K., D.K., H.T.Y., T.-H.K., J.-H.S., P.-S.Y. and B.J.; Project administration, H.T.Y., T.-H.K., H.-N.P., J.-H.S., M.-H.L., P.-S.Y. and B.J.; Resources, E.J., P.-S.Y. and B.J.; Supervision, D.K., H.T.Y., T.-H.K., H.-N.P., J.-H.S., M.-H.L. and B.J.; Writing—original draft, D.-S.K., D.K., P.-S.Y. and B.J.; Writing—review & editing, D.-S.K., P.-S.Y. and B.J. All authors have read and agreed to the published version of the manuscript.
Funding
This research was supported by grants from the Patient-Centered Clinical Research Coordinating Center funded by the Ministry of Health & Welfare, Republic of Korea (grant numbers: HC19C0130).
Institutional Review Board Statement
This study was approved by the Institutional Review Board of the Yonsei University Health System (approval number: 4-2016-0179) and complied with the requirements of the Declaration of Helsinki. All patients provided written informed consent.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the NHIS cohort.
Data Availability Statement
The data presented in the study are openly available from NHIS.
Acknowledgments
The authors would like to thank the NHIS for their co-operation. We also would like to thank Na-hye Kim for her linguistic assistance.
Conflicts of Interest
Boyoung Joung has served as a speaker for Bayer, BMS/Pfizer, Medtronic, and Daiichi-Sankyo and received research funds from Medtronic and Abbott. No fees have been received directly or personally. The remaining authors have nothing to declare.
Abbreviations
| AF | atrial fibrillation, |
| AFFIRM | Atrial Fibrillation Follow-up Investigation of Sinus Rhythm Management |
| CI | confidence interval |
| EAST-AFNET 4 | Early Treatment of Atrial Fibrillation for Stroke Prevention Trial |
| HF | heart failure |
| HR | hazard ratio |
| ICD-10 | International Classification of Disease, Tenth Revision |
| MI | myocardial infarction |
| NHIS | National Health Insurance Service |
| vs. | versus |
References
- Hindricks, G.; Potpara, T.; Dagres, N.; Arbelo, E.; Bax, J.J.; Blomström-Lundqvist, C.; Boriani, G.; Castella, M.; Dan, G.A.; Dilaveris, P.E.; et al. 2020 esc guidelines for the diagnosis and management of atrial fibrillation developed in collaboration with the european association for cardio-thoracic surgery (eacts): The task force for the diagnosis and management of atrial fibrillation of the european society of cardiology (esc) developed with the special contribution of the european heart rhythm association (ehra) of the esc. Eur. Heart J. 2021, 42, 373–498. [Google Scholar] [PubMed]
- Van Gelder, I.C.; Hagens, V.E.; Bosker, H.A.; Kingma, J.H.; Kamp, O.; Kingma, T.; Said, S.A.; Darmanata, J.I.; Timmermans, A.J.; Tijssen, J.G.; et al. A comparison of rate control and rhythm control in patients with recurrent persistent atrial fibrillation. N. Engl. J. Med. 2002, 347, 1834–1840. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wyse, D.G.; Waldo, A.L.; DiMarco, J.P.; Domanski, M.J.; Rosenberg, Y.; Schron, E.B.; Kellen, J.C.; Greene, H.L.; Mickel, M.C.; Dalquist, J.E.; et al. A comparison of rate control and rhythm control in patients with atrial fibrillation. N. Engl. J. Med. 2002, 347, 1825–1833. [Google Scholar] [PubMed]
- Roy, D.; Talajic, M.; Nattel, S.; Wyse, D.G.; Dorian, P.; Lee, K.L.; Bourassa, M.G.; Arnold, J.M.; Buxton, A.E.; Camm, A.J.; et al. Rhythm control versus rate control for atrial fibrillation and heart failure. N. Engl. J. Med. 2008, 358, 2667–2677. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Testa, L.; Biondi-Zoccai, G.G.; Dello Russo, A.; Bellocci, F.; Andreotti, F.; Crea, F. Rate-control vs. Rhythm-control in patients with atrial fibrillation: A meta-analysis. Eur. Heart J. 2005, 26, 2000–2006. [Google Scholar] [CrossRef] [Scilit]
- Kirchhof, P.; Camm, A.J.; Goette, A.; Brandes, A.; Eckardt, L.; Elvan, A.; Fetsch, T.; van Gelder, I.C.; Haase, D.; Haegeli, L.M.; et al. Early rhythm-control therapy in patients with atrial fibrillation. N. Engl. J. Med. 2020, 383, 1305–1316. [Google Scholar] [CrossRef] [Scilit]
- Kim, D.; Yang, P.S.; You, S.C.; Jang, E.; Yu, H.T.; Kim, T.H.; Pak, H.N.; Lee, M.H.; Lip, G.Y.H.; Sung, J.H.; et al. Comparative effectiveness of early rhythm control versus rate control for cardiovascular outcomes in patients with atrial fibrillation. J. Am. Heart Assoc. 2021, 10, e023055. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, D.; Yang, P.S.; You, S.C.; Sung, J.H.; Jang, E.; Yu, H.T.; Kim, T.H.; Pak, H.N.; Lee, M.H.; Lip, G.Y.H.; et al. Treatment timing and the effects of rhythm control strategy in patients with atrial fibrillation: Nationwide cohort study. BMJ 2021, 373, n991. [Google Scholar] [CrossRef] [Scilit]
- Piccini, J.P.; Simon, D.N.; Steinberg, B.A.; Thomas, L.; Allen, L.A.; Fonarow, G.C.; Gersh, B.; Hylek, E.; Kowey, P.R.; Reiffel, J.A.; et al. Differences in clinical and functional outcomes of atrial fibrillation in women and men: Two-year results from the orbit-af registry. JAMA Cardiol. 2016, 1, 282–291. [Google Scholar] [CrossRef] [Scilit]
- Schnabel, R.B.; Pecen, L.; Ojeda, F.M.; Lucerna, M.; Rzayeva, N.; Blankenberg, S.; Darius, H.; Kotecha, D.; Caterina, R.; Kirchhof, P. Gender differences in clinical presentation and 1-year outcomes in atrial fibrillation. Heart 2017, 103, 1024–1030. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.M.; Kim, T.H.; Cha, M.J.; Park, J.; Park, J.K.; Kang, K.W.; Shim, J.; Uhm, J.S.; Kim, J.; Park, H.W.; et al. Gender-related differences in management of nonvalvular atrial fibrillation in an asian population. Korean Circ. J. 2018, 48, 519–528. [Google Scholar] [CrossRef] [Scilit]
- Kim, M.H.; You, S.C.; Sung, J.H.; Jang, E.; Yu, H.T.; Kim, T.H.; Pak, H.N.; Lee, M.H.; Yang, P.S.; Joung, B. Safety and long-term outcomes of catheter ablation according to sex in patients with atrial fibrillation: A nationwide cohort study. Int. J. Cardiol. 2021, 338, 95–101. [Google Scholar] [CrossRef] [Scilit]
- Rienstra, M.; Van Veldhuisen, D.J.; Hagens, V.E.; Ranchor, A.V.; Veeger, N.J.; Crijns, H.J.; Van Gelder, I.C. Gender-related differences in rhythm control treatment in persistent atrial fibrillation: Data of the rate control versus electrical cardioversion (race) study. J. Am. Coll. Cardiol. 2005, 46, 1298–1306. [Google Scholar] [CrossRef] [Scilit]
- Zylla, M.M.; Brachmann, J.; Lewalter, T.; Hoffmann, E.; Kuck, K.H.; Andresen, D.; Willems, S.; Eckardt, L.; Tebbenjohanns, J.; Spitzer, S.G.; et al. Sex-related outcome of atrial fibrillation ablation: Insights from the german ablation registry. Heart Rhythm 2016, 13, 1837–1844. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.S.; Ae Kong, K.; Kim, D.; Lim, Y.M.; Yang, P.S.; Yi, J.E.; Kim, M.; Kwon, K.; Bum Pyun, W.; Joung, B.; et al. Clinical implication of an impaired fasting glucose and prehypertension related to new onset atrial fibrillation in a healthy asian population without underlying disease: A nationwide cohort study in korea. Eur. Heart J. 2017, 38, 2599–2607. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, F.; Morgan, K.L.; Zaslavsky, A.M. Balancing covariates via propensity score weighting. J. Am. Stat. Assoc. 2018, 113, 390–400. [Google Scholar] [CrossRef] [Scilit]
- Fine, J.P.; Gray, R.J. A proportional hazards model for the subdistribution of a competing risk. J. Am. Stat. Assoc. 1999, 94, 496–509. [Google Scholar] [CrossRef]
- Bushnell, C.; McCullough, L.D.; Awad, I.A.; Chireau, M.V.; Fedder, W.N.; Furie, K.L.; Howard, V.J.; Lichtman, J.H.; Lisabeth, L.D.; Piña, I.L.; et al. Guidelines for the prevention of stroke in women: A statement for healthcare professionals from the american heart association/american stroke association. Stroke 2014, 45, 1545–1588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Emdin, C.A.; Wong, C.X.; Hsiao, A.J.; Altman, D.G.; Peters, S.A.; Woodward, M.; Odutayo, A.A. Atrial fibrillation as risk factor for cardiovascular disease and death in women compared with men: Systematic review and meta-analysis of cohort studies. BMJ 2016, 532, h7013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Connolly, S.J.; Camm, A.J.; Halperin, J.L.; Joyner, C.; Alings, M.; Amerena, J.; Atar, D.; Avezum, Á.; Blomström, P.; Borggrefe, M.; et al. Dronedarone in high-risk permanent atrial fibrillation. N. Engl. J. Med. 2011, 365, 2268–2276. [Google Scholar] [CrossRef] [Scilit]
- Tsadok, M.A.; Jackevicius, C.A.; Essebag, V.; Eisenberg, M.J.; Rahme, E.; Humphries, K.H.; Tu, J.V.; Behlouli, H.; Pilote, L. Rhythm versus rate control therapy and subsequent stroke or transient ischemic attack in patients with atrial fibrillation. Circulation 2012, 126, 2680–2687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patel, D.; Mohanty, P.; Di Biase, L.; Sanchez, J.E.; Shaheen, M.H.; Burkhardt, J.D.; Bassouni, M.; Cummings, J.; Wang, Y.; Lewis, W.R.; et al. Outcomes and complications of catheter ablation for atrial fibrillation in females. Heart Rhythm 2010, 7, 167–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Makkar, R.R.; Fromm, B.S.; Steinman, R.T.; Meissner, M.D.; Lehmann, M.H. Female gender as a risk factor for torsades de pointes associated with cardiovascular drugs. JAMA 1993, 270, 2590–2597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hosseini, S.M.; Rozen, G.; Saleh, A.; Vaid, J.; Biton, Y.; Moazzami, K.; Heist, E.K.; Mansour, M.C.; Kaadan, M.I.; Vangel, M.; et al. Catheter ablation for cardiac arrhythmias: Utilization and in-hospital complications, 2000 to 2013. JACC Clin. Electrophysiol. 2017, 3, 1240–1248. [Google Scholar] [CrossRef] [Scilit]
- Bollmann, A.; Ueberham, L.; Schuler, E.; Wiedemann, M.; Reithmann, C.; Sause, A.; Tebbenjohanns, J.; Schade, A.; Shin, D.I.; Staudt, A.; et al. Cardiac tamponade in catheter ablation of atrial fibrillation: German-wide analysis of 21 141 procedures in the helios atrial fibrillation ablation registry (safer). Europace 2018, 20, 1944–1951. [Google Scholar] [CrossRef] [Scilit]
- Elayi, C.S.; Darrat, Y.; Suffredini, J.M.; Misumida, N.; Shah, J.; Morales, G.; Wilson, W.; Bidwell, K.; Czarapata, M.; Parrott, K.; et al. Sex differences in complications of catheter ablation for atrial fibrillation: Results on 85,977 patients. J. Interv. Card. Electrophysiol. 2018, 53, 333–339. [Google Scholar] [CrossRef] [Scilit]
- Yao, R.J.R.; Macle, L.; Deyell, M.W.; Tang, L.; Hawkins, N.M.; Sedlak, T.; Nault, I.; Verma, A.; Khairy, P.; Andrade, J.G. Impact of female sex on clinical presentation and ablation outcomes in the circa-dose study. JACC Clin. Electrophysiol. 2020, 6, 945–954. [Google Scholar] [CrossRef] [Scilit]
- Pancholy, S.B.; Sharma, P.S.; Pancholy, D.S.; Patel, T.M.; Callans, D.J.; Marchlinski, F.E. Meta-analysis of gender differences in residual stroke risk and major bleeding in patients with nonvalvular atrial fibrillation treated with oral anticoagulants. Am. J. Cardiol. 2014, 113, 485–490. [Google Scholar] [CrossRef] [Scilit]
- Pokorney, S.D.; Simon, D.N.; Thomas, L.; Fonarow, G.C.; Kowey, P.R.; Chang, P.; Singer, D.E.; Ansell, J.; Blanco, R.G.; Gersh, B.; et al. Patients’ time in therapeutic range on warfarin among us patients with atrial fibrillation: Results from orbit-af registry. Am. Heart J. 2015, 170, 141–148, 148.e141. [Google Scholar] [CrossRef] [Scilit]
- Jaïs, P.; Cauchemez, B.; Macle, L.; Daoud, E.; Khairy, P.; Subbiah, R.; Hocini, M.; Extramiana, F.; Sacher, F.; Bordachar, P.; et al. Catheter ablation versus antiarrhythmic drugs for atrial fibrillation: The a4 study. Circulation 2008, 118, 2498–2505. [Google Scholar] [CrossRef] [Scilit]
- Mont, L.; Bisbal, F.; Hernández-Madrid, A.; Pérez-Castellano, N.; Viñolas, X.; Arenal, A.; Arribas, F.; Fernández-Lozano, I.; Bodegas, A.; Cobos, A.; et al. Catheter ablation vs. Antiarrhythmic drug treatment of persistent atrial fibrillation: A multicentre, randomized, controlled trial (sara study). Eur. Heart J. 2014, 35, 501–507. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).