


Abstract
On-treatment platelet reactivity in clopidogrel-treated patients can be measured with several platelet function tests (PFTs). However, the agreement between different PFTs is only slight to moderate. Polymorphisms of the CYP2C19 gene have an impact on the metabolization of clopidogrel and, thereby, have an impact on on-treatment platelet reactivity. The aim of the current study is to evaluate the differential effects of the CYP2C19 genotype on three different PFTs. Methods: From a prospective cohort study, we included patients treated with clopidogrel following percutaneous coronary intervention (PCI). One month after PCI, we simultaneously performed three different PFTs; light transmission aggregometry (LTA), VerifyNow P2Y12, and Multiplate. In whole EDTA blood, genotyping of the CYP2C19 polymorphisms was performed. Results: We included 308 patients treated with clopidogrel in combination with aspirin (69.5%) and/or anticoagulants (33.8%) and, based on CYP2C19 genotyping, classified them as either extensive (36.4%), rapid (34.7%), intermediate (26.0%), or poor metabolizers (2.9%). On-treatment platelet reactivity as measured by LTA and VerifyNow is significantly affected by CYP2C19 metabolizer status (p < 0.01); as metabolizer status changes from rapid, via extensive and intermediate, to poor, the mean platelet reactivity increases accordingly (p < 0.01). On the contrary, for Multiplate, no such ordering of metabolizer groups was found (p = 0.10). Conclusions: For VerifyNow and LTA, the on-treatment platelet reactivity in clopidogrel-treated patients correlates well with the underlying CYP2C19 polymorphism. For Multiplate, no major effect of genetic background could be shown, and effects of other (patient-related) variables prevail. Thus, besides differences in test principles and the influence of patient-related factors, the disagreement between PFTs is partly explained by differential effects of the CYP2C19 genotype.
1. Introduction
Dual antiplatelet therapy with aspirin and a P2Y12 receptor blocker (clopidogrel, prasugrel, or ticagrelor) is the cornerstone of antithrombotic therapy preventing recurrent cardiovascular events in patients undergoing percutaneous coronary intervention (PCI) [1]. Although guidelines favor more potent next-generation P2Y12 inhibitors, such as ticagrelor and prasugrel, in acute coronary syndrome (ACS) patients [1,2], clopidogrel remains the most widely prescribed P2Y12 inhibitor, partly due to clinical and economic factors [3]. There is substantial variability in pharmacodynamic action of clopidogrel, which translates into variation in clopidogrel effectiveness after PCI [4,5]. Besides several contributing clinical factors, this variability is partly explained by genetic polymorphisms encoding cytochrome P450 (CYP) 2C19, the hepatic enzyme involved in biotransformation of the prodrug clopidogrel to its active metabolite [6]. The hepatic conversion of clopidogrel to its active metabolite is a two-step biotransformation process. Because 85% of the prodrug clopidogrel is inactivated by esterases after intestinal absorption, only 15% is available for transformation to the active metabolite, for which the hepatic CYP2C19 enzyme is a key determinant. The gene that codes the CYP2C19 enzyme is highly polymorphic, and over 30 gene alleles have been identified [7]. The CYP2C19*1 allele is the most prevalent and represents a normal activity allele. CYP2C19*2 and CYP2C19*3 alleles are the most frequently observed polymorphisms leading to a complete loss of enzyme activity, with reduced clopidogrel conversion. This results in higher residual platelet reactivity [5,8,9,10] and is associated with a higher incidence of major adverse cardiovascular and cerebrovascular events [4,5,6,9,10,11]. On the other hand, the CYP2C19*17 allelic variant represents a gain-of-function mutation that leads to increased catalytic activity and increased production of active metabolites, which might result in more pronounced platelet inhibition, higher bleeding risk, and lower risk for ischemic events with clopidogrel [12,13,14,15]. However, other studies have reported no significant association between the *17 allele and ischemic and bleeding outcomes after accounting for the *2 allele, so its clinical relevance is still controversial [16,17]. In contrast to clopidogrel, the CYP2C19 genotype does not impact the clinical effects of prasugrel or ticagrelor, for which clinical trials have shown the superiority over clopidogrel in reducing ischemic events, although accompanied by higher bleeding risks [18,19].
Especially in patients with multiple clinical risk factors, clinicians will have to weigh the bleeding and ischemic risks to individualize treatment decisions following PCI [20]. Platelet function tests (PFTs) could guide such decisions; however, although personalized treatment strategies based on PFTs have been evaluated, all have failed to show significant clinical benefit [21,22,23]. Moreover, multiple PFTs using different techniques are available, but previous studies have shown that the agreement between different PFTs is only slight to moderate, leading to conflicting results [24,25,26,27,28]. More recently, studies evaluating pharmacogenomic-based tailoring of P2Y12 inhibitors seemed to be more promising [29,30,31,32].
The aim of the current study is to evaluate the differential effects of CYP2C19 genotypes on three different platelet function tests. Understanding the relationship between PFTs and genetic polymorphisms is important in the interpretation of the disagreement between these PFTs and determination of optimal antiplatelet therapy in high-risk patients, and it could help to explain the disappointing PFT-tailoring studies in comparison to the more promising pharmacogenomic approach.
2. Materials and Methods
This prospective cohort study is conducted at the Thrombosis Expertise Centre in the Maastricht University Medical Center (MUMC+) in the Netherlands. The study was reviewed and approved by the medical ethical committee of the MUMC+ (NL38767.068.11, METC number 11-2-096), and all patients provided written informed consent.
2.1. Study Population
Patients were selected from a cohort of high-risk patients with dual or triple antithrombotic therapy after PCI. This prospective cohort study is extensively described elsewhere [33]. In brief, all patients underwent PCI (either elective or following ACS) and were classified as high-risk patients by the presence of ≥3 predefined risk factors (Table A1). Patients either had dual antithrombotic therapy (a P2Y12 inhibitor plus aspirin or anticoagulants) or triple therapy (a combination of a P2Y12 inhibitor, aspirin, and anticoagulants) in the case of concomitant atrial fibrillation. For the current research question, we only selected the patients on clopidogrel for whom CYP2C19 analysis had been performed by June 2018. Exclusion criteria were previously diagnosed platelet function disorders, a new ischemic event or coronary revascularization procedure ≤7 days, confirmed noncompliance, or signs of active infection.
2.2. Laboratory Measurements
On-treatment platelet reactivity was measured using three different PFTs. Blood for all these PFTs was drawn simultaneously 1–2 months after PCI, together with the sample needed for genotyping of the CYP2C19 polymorphisms. Furthermore, we measured blood count and renal function.
2.2.1. Multiple Electrode Impedance Aggregometry by Multiplate
Blood was collected in Hirudin Blood Tubes (3 mL, Double Wall; Verum Diagnostica GmbH, Munich, Germany). Adenosine diphosphate (ADP, 6.4 uM)-induced platelet aggregation was measured by the Multiplate analyzer (Dynabyte, Munich, Germany), according to the manufacturer’s instructions. The Multiplate analyzer is a multiple electrode impedance aggregometer that measures platelet aggregation in whole blood. Results are expressed as arbitrary aggregation units (AU).
2.2.2. VerifyNow
Blood was collected in 3.2% sodium citrate Vacuette partial-fill tubes (2 mL; Greiner Bio-One, GmbH, Kremsmuntster, Austria). VerifyNow P2Y12 assay (Accumetrics Inc, San Diego, CA, USA) was performed according to the manufacturer’s instructions. This is a turbidimetric-based optical detection system, in which whole blood is added to a device using fibrinogen-coated microbeats. After addition of an agonist (20 µmol/L ADP–22 nmol/L prostaglandin E1), the increase in light transmittance is detected to measure platelet agglutination, and results are expressed in P2Y12 reaction units (PRU).
2.2.3. Light Transmission Aggregometry (LTA)
Blood was collected in 3.2% sodium citrate Vacuette tubes (9 mL; Greiner Bio-One). For preparation of platelet-rich plasma, blood was centrifuged at 170× g for 10 min at 18 °C. For preparation of platelet-poor plasma, citrated blood was centrifuged at 2500× g for 5 min and then at 10,000× g for 10 min at 18 °C. Platelet count in platelet-rich plasma was adjusted with autologous platelet-poor plasma to 250 × 109 platelets/L. ADP (20 μmol/L, Chrono-Par, CH 384) was added at 37 °C. The main result was the percentage of maximal platelet aggregation.
2.2.4. CYP2C19 Analysis
From whole EDTA blood, genomic DNA for genetic analysis was isolated with the MagNa Pure 96 DNA isolation system (Roche Diagnostics, Mannheim, Germany) according to the manufacturer’s instructions. Using the LightCycler® (Roche Diagnostics), genotyping of the CYP2C19 polymorphism was performed using a FRET LightMix® assay (TIB MOLBIOL, Berlin, Germany). Genotypes were determined blinded without knowledge of platelet aggregation values. CYP variants were grouped according to the guideline of the Clinical Pharmacogenetic Implementation Consortium (CPIC) [8,34]; CYP2C19 *1/*1 is referred to as normal or extensive metabolizer (EM), genotypes with one loss-of function allele (CYP2C19 *1/*2, *1/*3 or *2/*17) were assembled under the term ‘intermediate metabolizer’ (IM), and the genotype with two loss-of-function alleles (CYP2C19 *2/*2) is referred to as ‘poor metabolizer’ (PM). The last group consists of the genotypes CYP2C19 *1/*17 and *17/*17, and is referred to as ‘rapid metabolizers’ (RM).
2.3. Statistical Analysis
Continuous variables are expressed as either mean with standard deviation (SD) for normally distributed traits or median with interquartile range (IQR) otherwise. Categorical variables are expressed as counts and percentages. The distribution of the data was estimated using visual inspection of histograms and confirmed using the Shapiro–Wilk test. To compare categorical variables between the metabolizer groups, the Chi-square test was used, with Fisher’s Exact Test when applicable. Normally distributed continuous variables were compared between metabolizer groups using ANOVA. The Jonckheere–Terpstra test for ordered alternatives was used to test for statistically significant ordinal trends between the metabolizer groups and for pairwise comparison of the different metabolizer groups compared to extensive metabolizers (reference category), with Bonferroni post-test to correct for multiple testing. Multivariable linear regression analysis was performed to adjust for other factors influencing platelet reactivity. Variables were included in the model based on existing literature or if univariate analysis indicated the variable to be associated with at least one of the platelet function tests at p < 0.20. Presence of multicollinearity was checked using variation inflation factors. Simple correlation between the three platelet function tests was assessed with Pearson correlation coefficients (ρ). A value of p < 0.05 was considered to be statistically significant. Statistical analyses were performed with IBM SPSS statistics version 25.0 and GraphPad Prism version 5.
3. Results
3.1. Baseline Characteristics
From the total cohort of 524 patients [33], 308 patients met the inclusion criteria and were included in this analysis. Baseline characteristics of the study population are shown in Table 1. Mean age is 75.2 (8.5) years, with 41.2% being female. All patients were treated with clopidogrel (100%) in combination with aspirin (69.5%) and/or anticoagulants (33.8%).
Table 1.
Baseline characteristics for the different metabolizer groups.
Table 2 shows the distribution of CYP2C19 polymorphisms in our population, with 36.4% extensive (normal) metabolizers (*1/*1). About 34.7% of our population was classified as rapid metabolizers (*1/*17 or *17/*17), whereas 26.0% was intermediate metabolizers (*1/*2, *2/*17 or *1/*3), and 9 patients (2.9%) turned out to be poor metabolizers (*2/*2).
Table 2.
Distribution of CYP2C19 polymorphisms in study population.
3.2. Agreement between Platelet Function Tests
All 3 platelet function tests were measured simultaneously after a median of 46 (37–59) days post-PCI. Simple correlation between platelet reactivity values was moderate for the 3 platelet function tests: ρ = 0.566 (p < 0.0001) for the correlFation between VerifyNow and LTA, ρ = 0.493 (p < 0.0001) for VerifyNow and Multiplate, and ρ = 0.423 (p < 0.0001) for LTA and Multiplate.
3.3. Residual Platelet Reactivity per Group of CYP2C19 Metabolism
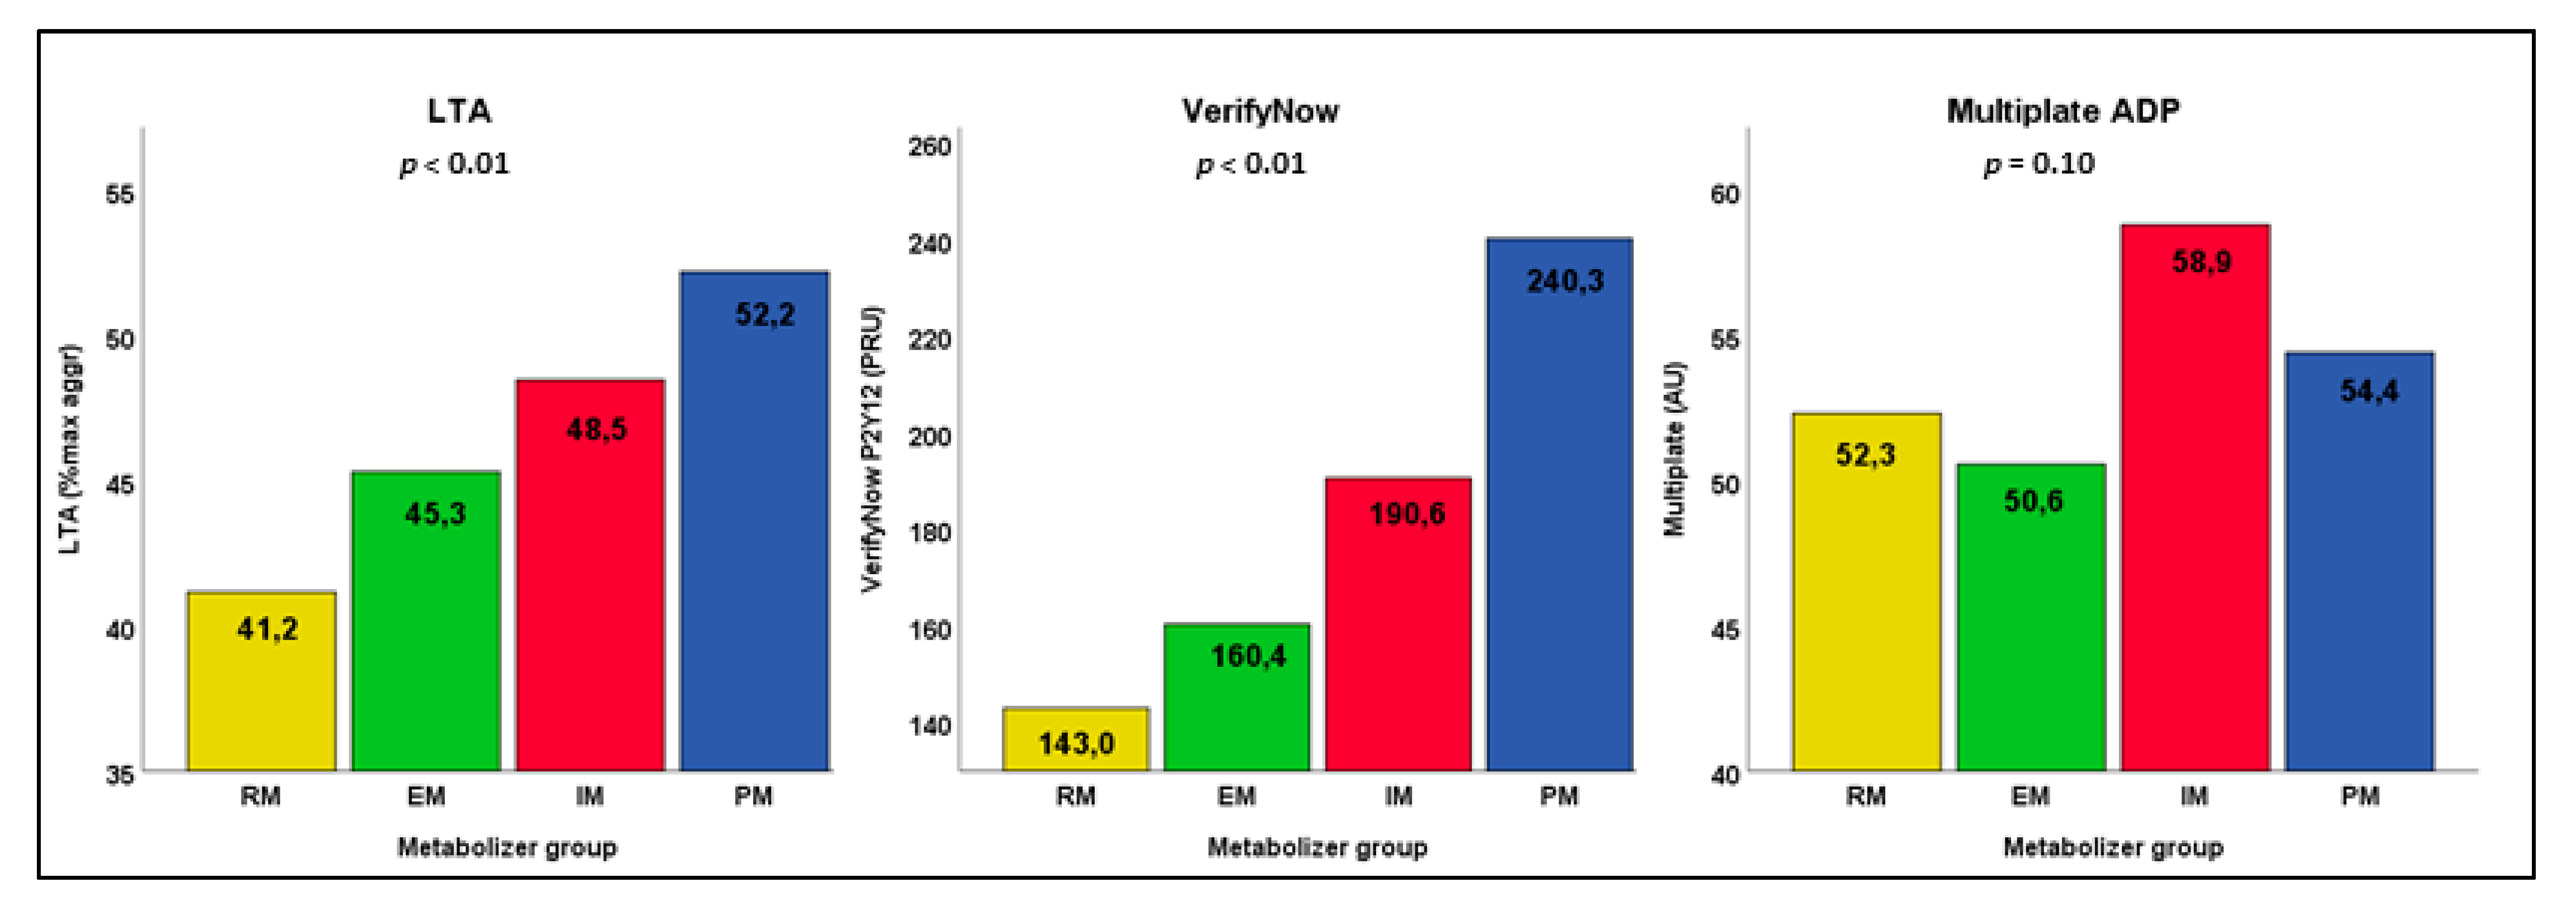
Mean values of residual platelet reactivity per group of CYP2C19 metabolism as measured by LTA VerifyNow and Multiplate are shown in Figure 1. For LTA, the intermediate and poor metabolizers have higher residual platelet reactivity as compared to extensive metabolizers, whereas the rapid metabolizers have the lowest on-treatment platelet reactivity. The residual platelet reactivity as measured by the LTA is significantly affected by CYP2C19 metabolizer status (p < 0.01). A Jonckheere–Terpstra test for ordered alternatives showed that there was a statistically significant trend of higher platelet reactivity with consecutive metabolizer groups; as metabolizer status changes from rapid, via extensive and intermediate, to poor, the mean LTA value increases accordingly (p < 0.01) (Table 3).
Figure 1.
Mean platelet reactivity as measured by three platelet function tests in the clopidogrel group expressed per group of CYP2C19 metabolism. Differences in platelet reactivity per group of CYP2C19 metabolism were measured using ANOVA. Poor metabolizers (PM) have genotype CYP2C19*2/*2, intermediate metabolizers (IM) CYP2C19*1/*2, *1/*3, or *2/*17, extensive metabolizers (EM) CYP2C19*1/*1, and rapid metabolizers (RM) CYP2C19*1/*17 or *17/*17.
Table 3.
Mean platelet reactivity as measured by the three platelet function tests, expressed per group of CYP2C19 metabolism.
The same applies to the VerifyNow test; residual platelet reactivity is significantly affected by CYP2C19 metabolizer status (p < 0.01), with a statistically significant trend of higher platelet reactivity when metabolizer status changes from rapid, extensive, intermediate to poor metabolizer (p < 0.01).
Contrary to the LTA and VerifyNow, for the Multiplate no such trend can be found; mean residual platelet reactivity is not significantly different (p = 0.10) between the metabolizer groups. Additionally, the Jonckheere–Terpstra test showed no statistically significant ordering of the metabolizer groups (p = 0.10).
3.4. Effect of Metabolizer Status on Platelet Reactivity
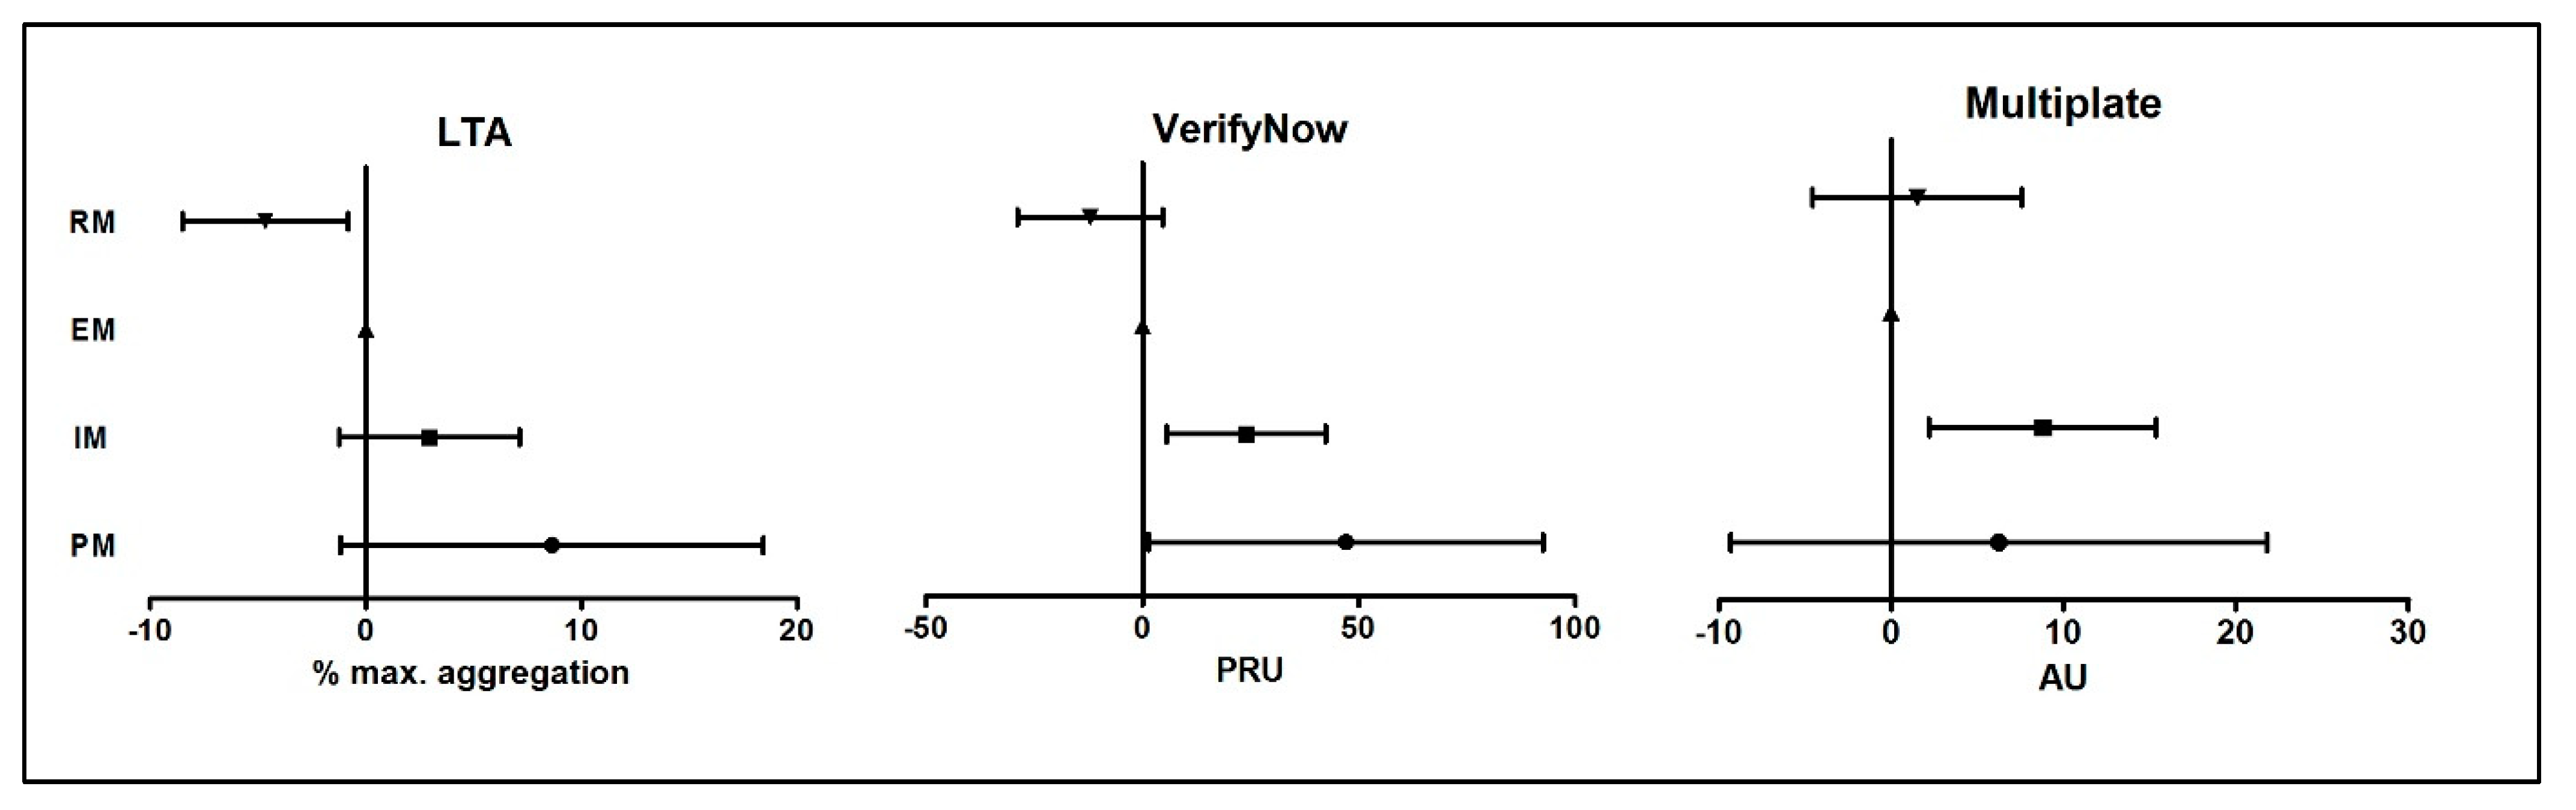
Figure 2 shows the effect of the different metabolizer groups on the residual platelet reactivity as measured by LTA, VerifyNow, and Multiplate. Platelet reactivity in this multivariable model was adjusted for age, body weight, diabetes, renal insufficiency, previous stroke, current smoking, concomitant use of (es-)omeprazole, hemoglobin, platelet count, and use of aspirin and/or anticoagulants, based on results of the univariate analysis (Table A2). In this adjusted model, poor metabolizer status is associated with a nonsignificant increase of 8.8% in maximal aggregation in the LTA (Beta: 8.8; 95% CI: −1.0–18.6; p = 0.08) as compared to the EM group, whereas a rapid metabolizer status will lead to a decrease of 4.6% (Beta: −4.6; 95% CI: −8.5–−0.8; p = 0.02) in maximum aggregation of LTA. Compared to the wild type (EM), poor and intermediate metabolizer status is associated with an increase of 48.3 PRU (Beta: 48.3; 95% CI: 2.4–94.3; p = 0.04) and 22.5 PRU (Beta: 22.5; 95% CI: 4.0–40.9; p = 0.02) in VerifyNow, respectively (Table A2). As can be appreciated from Figure 2, the metabolizer status affects platelet reactivity as measured by both LTA and VerifyNow following an ordinal order; PM and IM status is associated with a (numerical) platelet reactivity increase and RM status with a (numerical) decrease. However, no such ordinal order could be found for the association of metabolizer status with platelet reactivity as measured by Multiplate.
Figure 2.
Different metabolizer groups as predictor of residual platelet reactivity in multivariate linear regression analysis. Partial regression coefficients (B) with 95% confidence interval for metabolizer group as predictor of residual platelet reactivity as measured by the 3 platelet function tests. Extensive metabolizers (EM) are the reference group. Abbreviations: PM, poor metabolizer; IM, intermediate metabolizer; EM, extensive metabolizer; RM, rapid metabolize. Max. aggregation, percentage of maximum aggregation; PRU, P2Y12 reaction units; AU, aggregation units.
3.5. Relative Importance of Metabolizer Status on Platelet Reactivity
Besides this effect of metabolizer status on differences in platelet reactivity between the PFTs, these differences are also explained by several clinical risk factors. Because the regression coefficients of all variables in the multivariable model are expressed in different measurement units, direct comparison of variables is difficult. Therefore, we calculated the standardized regression coefficients (beta weights) so that the effect of both patient-related factors and the metabolizer status on the platelet reactivity could be compared, giving a crude indication of the relative importance of the different variables (Table 4). This indicates that the variables with the strongest effect on platelet reactivity measured by LTA are metabolizer group (beta weight: 0.227), hemoglobin (beta weight: 0.155), and aspirin use (beta weight: −0.139). For VerifyNow, the variables with the strongest effect on platelet reactivity are hemoglobin (beta weight: −0.337), platelet count (beta weight: −0.268), and metabolizer group (beta weight: 0.212), respectively. However, for platelet reactivity as measured by Multiplate, the metabolizer group status (beta weight: 0.110) is not among the most important variables, which are platelet count (beta weight: 0.265), previous stroke (beta weight: 0.163), and concomitant use of (es-) omeprazole (beta weight 0.156).
Table 4.
Standardized regression coefficients (beta weights) of the multivariable model indicating the relative importance of the different variables on platelet reactivity as measured by the platelet function tests.
4. Discussion
In this study, we investigated the differential impact of CYP2C19 allelic variants on ADP-induced platelet aggregation as measured by three different platelet function tests in high-risk patients on clopidogrel. According to the Clinical Pharmacogenetics Implementation Consortium (CPIC) guidelines, patients in our study were divided into four metabolizer groups: poor, intermediate, extensive, and rapid metabolizers. The distribution of patients within these metabolizer groups is in line with previous reports in a European population [8]. We showed that residual platelet reactivity as measured by VerifyNow and LTA follows an ordinal trend for the different metabolizer groups, whereas for the Multiplate test, no such trend could be shown, suggesting that the genetic background has little effect on residual platelet reactivity as measured by the Multiplate assay.
Genetic variation in CYP2C19 is certainly not the only factor that determines the response to clopidogrel. Previous studies have revealed that the CYP2C19*2 polymorphism accounted for only 5–12% of clopidogrel variability in platelet reactivity [6,35]. Other factors, such as body weight, age, health conditions, and concomitant medication, also influence patients’ response to clopidogrel [35]. Although the CYP2C19*2 loss-of-function polymorphism was the strongest predictor of high on-treatment platelet reactivity in the study by Hochholzer et al., the CYP2C9*2 carrier status, together with demographic and clinical predictors for high on-clopidogrel platelet reactivity, could only explain 11.5% of residual platelet reactivity in this study [35]. This indicates that there are still some relevant factors interfering with clopidogrel response that are yet unknown. These known and unknown specific patient-related factors have a differential influence on the results of ex vivo PFTs [36]. Our data suggest that in the Multiplate test, these patient-related factors might prevail and that genetic background only plays a minor role. Comparing the beta weights of the different variables, we showed indeed that the influence of factors such as platelet count, previous stroke, and concomitant medication is more pronounced in the Multiplate test, whereas metabolizer status had less effect on platelet reactivity as measured by this assay. In a previous study, we already showed that the agreement between various PFTs is only slight to moderate and that PFTs may be affected by different factors to a variable degree [24]. The current study adds the underlying CYP2C19 allelic variation as one of these factors that might further explain this disagreement between platelet function tests.
Another factor to consider when interpreting our findings is the differences between test principles. Multiplate and VerifyNow are whole-blood tests, whereas in LTA, platelet aggregation is assessed in platelet-rich plasma. Moreover, the assays differ in anticoagulant used in the test tubes. Multiplate is performed in hirudin-anticoagulated blood, compared to citrated blood for LTA and VerifyNow. The low calcium environment in citrated blood compared to hirudin blood could attenuate platelet aggregation [37]. Furthermore, the VerifyNow test includes prostaglandin E1 to suppress the platelet activation contribution of ADP binding to the P2Y1 receptor (which is unaffected by clopidogrel administration), and thereby, the assay selectively measures the ADP-P2Y12 pathway [38,39]. VerifyNow is an aggregation-based test using fibrinogen-coated beads, whereas LTA depends completely on the aggregation of platelets in the plasma environment. Lastly, the Multiplate test is based on the measurement of the increase in electrical impedance when platelets adhere and aggregate on two silver-coated copper wires. Thus, aggregation in Multiplate and VerifyNow takes place on surfaces, whereas in LTA, aggregation occurs more or less in a liquid phase [40].
Our findings are in concordance with Harmsze et al., who evaluated the impact of genotypes on on-treatment platelet reactivity as measured by LTA and VerifyNow [41]. Similar to our results, they found for both assays a decreasing trend in residual platelet reactivity comparing PM, IM, EM, and RM groups. However, in this study, the Multiplate assay was not evaluated. Another study that found differences in correlation with genetic background between two different platelet function assays studied the effect of CYP2C19*17 in 598 ACS patients after loading dose and observed a significant impact of the *17 carriage on clopidogrel responsiveness when measured with vasodilator-stimulated phosphoprotein (VASP) assay, but not with LTA measurements [42]. Platelet response in LTA was assessed using 10 μmol ADP compared to 20 μmol ADP in our assay, and, contrary to our study, they did not evaluate the loss-of-function allelic variants and did not compare different metabolizer groups. Finally, Gremmel et al. investigated the influence of CYP2C9 allelic variants on ADP-induced platelet aggregation was determined by five different PFTs, including LTA, Multiplate, and VerifyNow. Although investigating the differential impact of CYP2C9 allelic variants instead of CYP2C19, their findings were comparable to ours; a significantly higher platelet reactivity was found for patients with loss-of-function status compared to the normal-function genotype using the VerifyNow assay or LTA, while results did not differ for the Multiplate assay [43].
Recently, several studies evaluated pharmacogenomic testing as an approach of personalized antiplatelet drug administration by either escalation or de-escalation of P2Y12 inhibitor therapy based on CYP2C19 allelic variants [29,30,44,45]. The POPular Genetics trial demonstrated that a personalized approach using genetic testing to de-escalate to clopidogrel was noninferior to standard treatment with either ticagrelor or prasugrel in terms of the primary composite outcome net clinical benefit (consisting of all-cause death, recurrent MI, definite stent thrombosis, stroke, and PLATO major bleeding), while it was superior in reducing combined major and minor bleedings [29]. A meta-analysis of eight randomized controlled trials, including the recently published TAILOR-PCI trial [30], confirmed that in patients with CYP2C19, loss-of function allele prescription of ticagrelor and prasugrel compared to clopidogrel resulted in a significant reduction in ischemic events (RR: 0.70; 95% CI: 0.59–0.83) but not in noncarriers of these alleles (RR: 1.0; 95% CI: 0.80–1.25) [32].
Current guidelines recommend risk stratification for tailoring individual treatment strategies [46,47]. Both platelet function testing and genotyping can provide useful prognostic insights, but trials evaluating treatment strategies have produced mixed results. Pharmacogenomic testing could be an attractive approach because treatment decisions can be made before the start of antiplatelet therapy, unlike with PFT, and the genotype does not change over time, unlike the phenotype of platelet reactivity [48,49]. One of the major limitations of PFTs is the great variability of the results, as is also shown in our study, and this could be overcome by genetic testing. On the other hand, the information derived from genotyping cannot be taken as a surrogate for PFT to assess antiplatelet drug responses, as genetic variants are just one influential factor affecting clopidogrel activity, and numerous epigenetic factors such as comorbidities, gastrointestinal absorption, drug interactions, and adherence are also important determinants. Thus, insight into the relationship between PFT results and genetics, as provided by this study, remains useful in further optimization of antiplatelet strategies. Furthermore, our findings could be of value to laboratories without the opportunity of performing genetic tests or that have to make a choice in the multitude of PFTs.
Important strengths of our study include the careful evaluation of included patients and the concomitant comparison of three different PFTs. Tests were performed 1–2 months after PCI, when a stable situation had been reached, not only in the inflammatory response to stent placement but also in individual clopidogrel response, and an influence of time from clopidogrel loading to platelet function testing could be excluded. A limitation of this study is that we did not assess plasma levels of the active metabolite of clopidogrel, which could have provided more mechanistic insight into the observed platelet response and correlation with the genetic background.
5. Conclusions and Future Remarks
In the near future, studies will keep focusing on the role of platelet function testing and genotyping to guide decision making in (high-risk) patients on antiplatelet therapy. In this study, we have shown that the disagreement between PFTs is partly explained by differences in correlation with genetic background. For Multiplate, no major effect of genetic background could be shown, whereas for VerifyNow and LTA, the residual platelet reactivity in patients treated with clopidogrel correlates well with the underlying CYP2C19 polymorphism. Understanding the (dis-) agreement between these different PFTs and how this relates to genetic variation in CYP2C19 will help us in the interpretation of these future clinical trials focusing on personalizing antiplatelet therapy.
Author Contributions
R.H.O., P.E.J.v.d.M., M.J.A.V., L.F.V., Y.M.C.H., J.M.t.B. and H.t.C. initiated the project. H.t.C. is the PI of the cohort. R.H.O., R.R.K.H., and M.J.A.V. coordinated the data entry. B.T.A.d.G. assisted with statistical analysis. R.H.O. was responsible for data management, statistical analysis, and wrote the manuscript. P.A.H.M.W. and R.R.K.H. were responsible for laboratory analyses, while Y.M.C.H. and O.B. coordinated all laboratory analyses. All authors revised the manuscript critically for important intellectual content. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by the Thrombosis Expertise Centre at the Heart and Vascular Centre of Maastricht University Medical Centre (MUMC+) in the Netherlands. This research received no specific grant from any funding agency or commercial sector.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki, and approved by the Institutional Review Board (or Ethics Committee) of Maastricht University Medical Centre (NL38767.068.11, METC Number 11-2-096).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data presented in this study are available on reasonable request from the corresponding author.
Acknowledgments
We thank all patients for their commitment and all laboratory personnel and medical students who helped in some way or another.
Conflicts of Interest
R.H.O. reports advisory and speakers fees from Leo Pharma, Portola, and Bayer, all outside the submitted work. J.M.t.B. reports advisory, consulting, and speaker fees from AstraZeneca, Eli Lilly, Daiichi Sankyo, the Medicines Company, Accumetrics, Boehringer Ingelheim, BMS, Pfizer, Bayer, and Ferrer, and received institutional research grants from ZonMw and AstraZeneca, all outside the submitted work. H.t.C. reports research support from Bayer and Pfizer/BMS, participated in advisory boards for Bayer, Pfizer/BMS, and Daiichi Sankyo, and grants from Dutch Heart Foundation (CVON, CONTRAST), Eu-Marie Curie ITN (TAPAS, TICARDIO), and Regmed XB. H.t.C. is a consultant for Alveron, a shareholder in Coagulation Profile, and an unpaid chairman of the Federation of Dutch Anticoagulation Clinics, all outside the submitted work. P.E.J.v.d.M., R.R.K.H., P.A.H.M.W., B.T.A.d.G., L.F.V., O.B., and Y.M.C.H. declare no conflict of interest.
Appendix A
Table A1.
Inclusion and exclusion criteria.
Table A2.
Partial regression coefficients of variables for LTA, VerifyNow, and Multiplate in univariate and multivariate analysis.
References
- Neumann, F.J.; Sousa-Uva, M.; Ahlsson, A.; Alfonso, F.; Banning, A.P.; Benedetto, U.; Byrne, R.A.; Collet, J.P.; Falk, V.; Head, S.J.; et al. 2018 ESC/EACTS Guidelines on myocardial revascularization. Eur. Heart J. 2019, 40, 87–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amsterdam, E.A.; Wenger, N.K.; Brindis, R.G.; Casey, D.E., Jr.; Ganiats, T.G.; Holmes, D.R., Jr.; Jaffe, A.S.; Jneid, H.; Kelly, R.F.; Kontos, M.C.; et al. 2014 AHA/ACC guideline for the management of patients with non-ST-elevation acute coronary syndromes: A report of the American College of Cardiology/American Heart Association Task Force on Practice Guidelines. Circulation 2014, 130, e344–e426. [Google Scholar] [CrossRef] [Scilit]
- Dayoub, E.J.; Seigerman, M.; Tuteja, S.; Kobayashi, T.; Kolansky, D.M.; Giri, J.; Groeneveld, P.W. Trends in Platelet Adenosine Diphosphate P2Y12 Receptor Inhibitor Use and Adherence Among Antiplatelet-Naive Patients After Percutaneous Coronary Intervention, 2008–2016. JAMA Intern. Med. 2018, 178, 943–950. [Google Scholar] [CrossRef] [Scilit]
- Mega, J.L.; Simon, T.; Collet, J.P.; Anderson, J.L.; Antman, E.M.; Bliden, K.; Cannon, C.P.; Danchin, N.; Giusti, B.; Gurbel, P.; et al. Reduced-function CYP2C19 genotype and risk of adverse clinical outcomes among patients treated with clopidogrel predominantly for PCI: A meta-analysis. JAMA 2010, 304, 1821–1830. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sibbing, D.; Stegherr, J.; Latz, W.; Koch, W.; Mehilli, J.; Dorrler, K.; Morath, T.; Schomig, A.; Kastrati, A.; von Beckerath, N. Cytochrome P450 2C19 loss-of-function polymorphism and stent thrombosis following percutaneous coronary intervention. Eur. Heart J. 2009, 30, 916–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shuldiner, A.R.; O’Connell, J.R.; Bliden, K.P.; Gandhi, A.; Ryan, K.; Horenstein, R.B.; Damcott, C.M.; Pakyz, R.; Tantry, U.S.; Gibson, Q.; et al. Association of cytochrome P450 2C19 genotype with the antiplatelet effect and clinical efficacy of clopidogrel therapy. JAMA 2009, 302, 849–857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scott, S.A.; Sangkuhl, K.; Shuldiner, A.R.; Hulot, J.S.; Thorn, C.F.; Altman, R.B.; Klein, T.E. PharmGKB summary: Very important pharmacogene information for cytochrome P450, family 2, subfamily C, polypeptide 19. Pharm. Genom. 2012, 22, 159–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scott, S.A.; Sangkuhl, K.; Stein, C.M.; Hulot, J.S.; Mega, J.L.; Roden, D.M.; Klein, T.E.; Sabatine, M.S.; Johnson, J.A.; Shuldiner, A.R.; et al. Clinical Pharmacogenetics Implementation Consortium guidelines for CYP2C19 genotype and clopidogrel therapy: 2013 update. Clin. Pharmacol. Ther. 2013, 94, 317–323. [Google Scholar] [CrossRef] [Scilit]
- Simon, T.; Verstuyft, C.; Mary-Krause, M.; Quteineh, L.; Drouet, E.; Meneveau, N.; Steg, P.G.; Ferrieres, J.; Danchin, N.; Becquemont, L.; et al. Genetic determinants of response to clopidogrel and cardiovascular events. N. Engl. J. Med. 2009, 360, 363–375. [Google Scholar] [CrossRef] [Scilit]
- Mega, J.L.; Close, S.L.; Wiviott, S.D.; Shen, L.; Hockett, R.D.; Brandt, J.T.; Walker, J.R.; Antman, E.M.; Macias, W.; Braunwald, E.; et al. Cytochrome p-450 polymorphisms and response to clopidogrel. N. Engl. J. Med. 2009, 360, 354–362. [Google Scholar] [CrossRef] [Scilit]
- Collet, J.P.; Hulot, J.S.; Pena, A.; Villard, E.; Esteve, J.B.; Silvain, J.; Payot, L.; Brugier, D.; Cayla, G.; Beygui, F.; et al. Cytochrome P450 2C19 polymorphism in young patients treated with clopidogrel after myocardial infarction: A cohort study. Lancet 2009, 373, 309–317. [Google Scholar] [CrossRef] [Scilit]
- Sibbing, D.; Koch, W.; Gebhard, D.; Schuster, T.; Braun, S.; Stegherr, J.; Morath, T.; Schomig, A.; von Beckerath, N.; Kastrati, A. Cytochrome 2C19* 17 allelic variant, platelet aggregation, bleeding events, and stent thrombosis in clopidogrel-treated patients with coronary stent placement. Circulation 2010, 121, 512–518. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Tang, H.L.; Hu, Y.F.; Xie, H.G. The gain-of-function variant allele CYP2C19*17: A double-edged sword between thrombosis and bleeding in clopidogrel-treated patients. J. Thromb. Haemost. 2012, 10, 199–206. [Google Scholar] [CrossRef] [Scilit]
- Gross, L.; Trenk, D.; Jacobshagen, C.; Krieg, A.; Gawaz, M.; Massberg, S.; Baylacher, M.; Aradi, D.; Stimpfle, F.; Hromek, J.; et al. Genotype-Phenotype Association and Impact on Outcomes following Guided De-Escalation of Anti-Platelet Treatment in Acute Coronary Syndrome Patients: The TROPICAL-ACS Genotyping Substudy. Thromb. Haemost. 2018, 118, 1656–1667. [Google Scholar] [CrossRef] [Scilit]
- Tiroch, K.A.; Sibbing, D.; Koch, W.; Roosen-Runge, T.; Mehilli, J.; Schomig, A.; Kastrati, A. Protective effect of the CYP2C19*17 polymorphism with increased activation of clopidogrel on cardiovascular events. Am. Heart J. 2010, 160, 506–512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, C.R.; Thomas, C.D.; Beitelshees, A.L.; Tuteja, S.; Empey, P.E.; Lee, J.C.; Limdi, N.A.; Duarte, J.D.; Skaar, T.C.; Chen, Y.; et al. Impact of the CYP2C19*17 Allele on Outcomes in Patients Receiving Genotype-Guided Antiplatelet Therapy After Percutaneous Coronary Intervention. Clin. Pharmacol. Ther. 2021, 109, 705–715. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewis, J.P.; Stephens, S.H.; Horenstein, R.B.; O’Connell, J.R.; Ryan, K.; Peer, C.J.; Figg, W.D.; Spencer, S.D.; Pacanowski, M.A.; Mitchell, B.D.; et al. The CYP2C19*17 variant is not independently associated with clopidogrel response. J. Thromb. Haemost. 2013, 11, 1640–1646. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wallentin, L.; Becker, R.C.; Budaj, A.; Cannon, C.P.; Emanuelsson, H.; Held, C.; Horrow, J.; Husted, S.; James, S.; Katus, H.; et al. Ticagrelor versus clopidogrel in patients with acute coronary syndromes. N. Engl. J. Med. 2009, 361, 1045–1057. [Google Scholar] [CrossRef] [Scilit]
- Wiviott, S.D.; Braunwald, E.; McCabe, C.H.; Montalescot, G.; Ruzyllo, W.; Gottlieb, S.; Neumann, F.J.; Ardissino, D.; De Servi, S.; Murphy, S.A.; et al. Prasugrel versus clopidogrel in patients with acute coronary syndromes. N. Engl. J. Med. 2007, 357, 2001–2015. [Google Scholar] [CrossRef] [Scilit]
- Sibbing, D.; Aradi, D.; Alexopoulos, D.; Ten Berg, J.; Bhatt, D.L.; Bonello, L.; Collet, J.P.; Cuisset, T.; Franchi, F.; Gross, L.; et al. Updated Expert Consensus Statement on Platelet Function and Genetic Testing for Guiding P2Y12 Receptor Inhibitor Treatment in Percutaneous Coronary Intervention. JACC Cardiovasc. Interv. 2019, 12, 1521–1537. [Google Scholar] [CrossRef] [Scilit]
- Price, M.J.; Berger, P.B.; Teirstein, P.S.; Tanguay, J.F.; Angiolillo, D.J.; Spriggs, D.; Puri, S.; Robbins, M.; Garratt, K.N.; Bertrand, O.F.; et al. Standard- vs high-dose clopidogrel based on platelet function testing after percutaneous coronary intervention: The GRAVITAS randomized trial. JAMA 2011, 305, 1097–1105. [Google Scholar] [CrossRef] [Scilit]
- Collet, J.P.; Cuisset, T.; Range, G.; Cayla, G.; Elhadad, S.; Pouillot, C.; Henry, P.; Motreff, P.; Carrie, D.; Boueri, Z.; et al. Bedside monitoring to adjust antiplatelet therapy for coronary stenting. N. Engl. J. Med. 2012, 367, 2100–2109. [Google Scholar] [CrossRef] [Scilit]
- Cayla, G.; Cuisset, T.; Silvain, J.; Leclercq, F.; Manzo-Silberman, S.; Saint-Etienne, C.; Delarche, N.; Bellemain-Appaix, A.; Range, G.; El Mahmoud, R.; et al. Platelet function monitoring to adjust antiplatelet therapy in elderly patients stented for an acute coronary syndrome (ANTARCTIC): An open-label, blinded-endpoint, randomised controlled superiority trial. Lancet 2016, 388, 2015–2022. [Google Scholar] [CrossRef] [Scilit]
- Vries, M.J.; Bouman, H.J.; Olie, R.H.; Veenstra, L.F.; Zwaveling, S.; Verhezen, P.W.; Ten Cate-Hoek, A.J.; Ten Cate, H.; Henskens, Y.M.; van der Meijden, P.E. Determinants of agreement between proposed therapeutic windows of platelet function tests in vulnerable patients. Eur. Heart J. Cardiovasc. Pharmacother. 2016, 3, 11–17. [Google Scholar] [CrossRef] [Scilit]
- Lordkipanidze, M.; Pharand, C.; Nguyen, T.A.; Schampaert, E.; Palisaitis, D.A.; Diodati, J.G. Comparison of four tests to assess inhibition of platelet function by clopidogrel in stable coronary artery disease patients. Eur. Heart J. 2008, 29, 2877–2885. [Google Scholar] [CrossRef] [Scilit]
- Gremmel, T.; Steiner, S.; Seidinger, D.; Koppensteiner, R.; Panzer, S.; Kopp, C.W. Comparison of methods to evaluate clopidogrel-mediated platelet inhibition after percutaneous intervention with stent implantation. Thromb. Haemost. 2009, 101, 333–339. [Google Scholar]
- Paniccia, R.; Antonucci, E.; Gori, A.M.; Marcucci, R.; Giglioli, C.; Antoniucci, D.; Gensini, G.F.; Abbate, R.; Prisco, D. Different methodologies for evaluating the effect of clopidogrel on platelet function in high-risk coronary artery disease patients. J. Thromb. Haemost. 2007, 5, 1839–1847. [Google Scholar] [CrossRef] [Scilit]
- Paniccia, R.; Antonucci, E.; Maggini, N.; Miranda, M.; Gori, A.M.; Marcucci, R.; Giusti, B.; Balzi, D.; Prisco, D.; Abbate, R. Comparison of methods for monitoring residual platelet reactivity after clopidogrel by point-of-care tests on whole blood in high-risk patients. Thromb. Haemost. 2010, 104, 287–292. [Google Scholar] [CrossRef] [Scilit]
- Claassens, D.M.F.; Vos, G.J.A.; Bergmeijer, T.O.; Hermanides, R.S.; van’t Hof, A.W.J.; van der Harst, P.; Barbato, E.; Morisco, C.; Tjon Joe Gin, R.M.; Asselbergs, F.W.; et al. A Genotype-Guided Strategy for Oral P2Y12 Inhibitors in Primary PCI. N. Engl. J. Med. 2019, 381, 1621–1631. [Google Scholar] [CrossRef] [Scilit]
- Pereira, N.L.; Farkouh, M.E.; So, D.; Lennon, R.; Geller, N.; Mathew, V.; Bell, M.; Bae, J.H.; Jeong, M.H.; Chavez, I.; et al. Effect of Genotype-Guided Oral P2Y12 Inhibitor Selection vs Conventional Clopidogrel Therapy on Ischemic Outcomes After Percutaneous Coronary Intervention: The TAILOR-PCI Randomized Clinical Trial. JAMA 2020, 324, 761–771. [Google Scholar] [CrossRef] [Scilit]
- Hulot, J.S.; Chevalier, B.; Belle, L.; Cayla, G.; Khalife, K.; Funck, F.; Berthier, R.; Piot, C.; Tafflet, M.; Montalescot, G.; et al. Routine CYP2C19 Genotyping to Adjust Thienopyridine Treatment After Primary PCI for STEMI: Results of the GIANT Study. JACC Cardiovasc. Interv. 2020, 13, 621–630. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pereira, N.L.; Rihal, C.; Lennon, R.; Marcus, G.; Shrivastava, S.; Bell, M.R.; So, D.; Geller, N.; Goodman, S.G.; Hasan, A.; et al. Effect of CYP2C19 Genotype on Ischemic Outcomes During Oral P2Y12 Inhibitor Therapy: A Meta-Analysis. JACC Cardiovasc. Interv. 2021, 14, 739–750. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olie, R.H.; Van der Meijden, P.E.J.; Vries, M.J.A.; Veenstra, L.; van’t Hof, A.W.J.; Ten Berg, J.M.; Henskens, Y.M.C.; Ten Cate, H. Antithrombotic therapy in high-risk patients after percutaneous coronary intervention; study design, cohort profile and incidence of adverse events. Neth. Heart J. 2021. [Google Scholar] [CrossRef] [Scilit]
- Bank, P.C.D.; Caudle, K.E.; Swen, J.J.; Gammal, R.S.; Whirl-Carrillo, M.; Klein, T.E.; Relling, M.V.; Guchelaar, H.J. Comparison of the Guidelines of the Clinical Pharmacogenetics Implementation Consortium and the Dutch Pharmacogenetics Working Group. Clin. Pharmacol. Ther. 2018, 103, 599–618. [Google Scholar] [CrossRef] [Scilit]
- Hochholzer, W.; Trenk, D.; Fromm, M.F.; Valina, C.M.; Stratz, C.; Bestehorn, H.P.; Buttner, H.J.; Neumann, F.J. Impact of cytochrome P450 2C19 loss-of-function polymorphism and of major demographic characteristics on residual platelet function after loading and maintenance treatment with clopidogrel in patients undergoing elective coronary stent placement. J. Am. Coll. Cardiol. 2010, 55, 2427–2434. [Google Scholar] [CrossRef] [Scilit]
- Gremmel, T.; Steiner, S.; Seidinger, D.; Koppensteiner, R.; Panzer, S.; Kopp, C.W. The influencing factors for clopidogrel-mediated platelet inhibition are assay-dependent. Thromb. Res. 2011, 128, 352–357. [Google Scholar] [CrossRef] [Scilit]
- Wallen, N.H.; Ladjevardi, M.; Albert, J.; Broijersen, A. Influence of different anticoagulants on platelet aggregation in whole blood; a comparison between citrate, low molecular mass heparin and hirudin. Thromb. Res. 1997, 87, 151–157. [Google Scholar] [CrossRef] [Scilit]
- van Werkum, J.W.; Harmsze, A.M.; Elsenberg, E.H.; Bouman, H.J.; Ten Berg, J.M.; Hackeng, C.M. The use of the VerifyNow system to monitor antiplatelet therapy: A review of the current evidence. Platelets 2008, 19, 479–488. [Google Scholar] [CrossRef] [Scilit]
- Hulshof, A.M.; Vries, M.; Verhezen, P.; Wetzels, R.; Haartmans, M.; Olie, R.; Ten Cate, H.; Henskens, Y. The Influence of Prostaglandin E1 and Use of Inhibitor Percentage on the Correlation between the Multiplate and VerifyNow in Patients on Dual Antiplatelet Therapy. Platelets 2020, 32, 463–468. [Google Scholar] [CrossRef] [Scilit]
- Sibbing, D.; Braun, S.; Jawansky, S.; Vogt, W.; Mehilli, J.; Schomig, A.; Kastrati, A.; von Beckerath, N. Assessment of ADP-induced platelet aggregation with light transmission aggregometry and multiple electrode platelet aggregometry before and after clopidogrel treatment. Thromb. Haemost. 2008, 99, 121–126. [Google Scholar] [CrossRef] [Scilit]
- Harmsze, A.M.; van Werkum, J.W.; Hackeng, C.M.; Ruven, H.J.; Kelder, J.C.; Bouman, H.J.; Breet, N.J.; Ten Berg, J.M.; Klungel, O.H.; de Boer, A.; et al. The influence of CYP2C19*2 and *17 on on-treatment platelet reactivity and bleeding events in patients undergoing elective coronary stenting. Pharm. Genom. 2012, 22, 169–175. [Google Scholar] [CrossRef] [Scilit]
- Frere, C.; Cuisset, T.; Gaborit, B.; Alessi, M.C.; Hulot, J.S. The CYP2C19*17 allele is associated with better platelet response to clopidogrel in patients admitted for non-ST acute coronary syndrome. J. Thromb. Haemost. 2009, 7, 1409–1411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gremmel, T.; Kopp, C.W.; Seidinger, D.; Koppensteiner, R.; Panzer, S.; Sunder-Plassmann, R.; Mannhalter, C.; Steiner, S. Differential impact of cytochrome 2C9 allelic variants on clopidogrel-mediated platelet inhibition determined by five different platelet function tests. Int. J. Cardiol. 2013, 166, 126–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Notarangelo, F.M.; Maglietta, G.; Bevilacqua, P.; Cereda, M.; Merlini, P.A.; Villani, G.Q.; Moruzzi, P.; Patrizi, G.; Malagoli Tagliazucchi, G.; Crocamo, A.; et al. Pharmacogenomic Approach to Selecting Antiplatelet Therapy in Patients With Acute Coronary Syndromes: The PHARMCLO Trial. J. Am. Coll. Cardiol. 2018, 71, 1869–1877. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, X.; Ma, Y.T.; Yang, Y.N.; Li, X.M.; Zheng, Y.Y.; Ma, X.; Fu, Z.Y.; Ba, B.; Li, Y.; Yu, Z.X.; et al. Personalized antiplatelet therapy according to CYP2C19 genotype after percutaneous coronary intervention: A randomized control trial. Int. J. Cardiol. 2013, 168, 3736–3740. [Google Scholar] [CrossRef] [Scilit]
- Levine, G.N.; Bates, E.R.; Bittl, J.A.; Brindis, R.G.; Fihn, S.D.; Fleisher, L.A.; Granger, C.B.; Lange, R.A.; Mack, M.J.; Mauri, L.; et al. 2016 ACC/AHA Guideline Focused Update on Duration of Dual Antiplatelet Therapy in Patients with Coronary Artery Disease: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines: An Update of the 2011 ACCF/AHA/SCAI Guideline for Percutaneous Coronary Intervention, 2011 ACCF/AHA Guideline for Coronary Artery Bypass Graft Surgery, 2012 ACC/AHA/ACP/AATS/PCNA/SCAI/STS Guideline for the Diagnosis and Management of Patients With Stable Ischemic Heart Disease, 2013 ACCF/AHA Guideline for the Management of ST-Elevation Myocardial Infarction, 2014 AHA/ACC Guideline for the Management of Patients With Non-ST-Elevation Acute Coronary Syndromes, and 2014 ACC/AHA Guideline on Perioperative Cardiovascular Evaluation and Management of Patients Undergoing Noncardiac Surgery. Circulation 2016, 134, e123–e155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collet, J.P.; Thiele, H.; Barbato, E.; Barthelemy, O.; Bauersachs, J.; Bhatt, D.L.; Dendale, P.; Dorobantu, M.; Edvardsen, T.; Folliguet, T.; et al. 2020 ESC Guidelines for the management of acute coronary syndromes in patients presenting without persistent ST-segment elevation. Eur. Heart J. 2020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cavallari, L.H.; Lee, C.R.; Beitelshees, A.L.; Cooper-DeHoff, R.M.; Duarte, J.D.; Voora, D.; Kimmel, S.E.; McDonough, C.W.; Gong, Y.; Dave, C.V.; et al. Multisite Investigation of Outcomes with Implementation of CYP2C19 Genotype-Guided Antiplatelet Therapy After Percutaneous Coronary Intervention. JACC Cardiovasc. Interv. 2018, 11, 181–191. [Google Scholar] [CrossRef] [Scilit]
- Price, M.J.; Angiolillo, D.J. Pharmacogenomic Testing to Select Antiplatelet Therapy. J. Am. Coll. Cardiol. 2018, 71, 1878–1881. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).