


Abstract
Thyroid hormones (THs) are master controllers in the endocrine system and have drawn considerable attention from the research community due to their associations with neurodegenerative diseases as well. In this review article, we present a comprehensive summary of the physiological functions and pathogenic mechanisms of THs in the regulation of several representative neurodegenerative diseases. Our study particularly focuses on Alzheimer’s disease (AD), Parkinson’s disease (PD), and multiple sclerosis (MS). AD is the most common cause of dementia, primarily caused by tau protein tangles inside nerve cells and β-amyloid plaques outside, which lead to nerve cell death and brain atrophy. PD is primarily a movement disorder. The degeneration of dopaminergic neurons in the brain impairs the brain’s control over muscle activity. MS is usually considered to be an autoimmune demyelinating disease, but it has been found that MS also presents with secondary neurodegenerative pathology, including axonal loss and neuronal damage. In this review, the effects of TH on the pathogeneses of AD, PD, and MS are discussed in detail, with a focus on the following potential mechanisms: neuroprotection, neurogenesis, oxidative stress, and inflammatory response. In addition, we conduct an in-depth review of the possible clinical applications of TH, TH analogs, and thyrotropin-releasing hormone (TRH) in the treatment of AD, PD, and MS based on recent preclinical and clinical studies. By integrating experimental, clinical, and epidemiological results on the effects of TH on neurodegeneration, the present review constructs a theoretical basis for the involvement of TH in the pathogeneses of these diseases in detail. We believe that this basis will be useful for clinical diagnosis and treatment.
1. Introduction
Thyroid hormones (THs) are endocrine regulatory molecules secreted by the thyroid gland, which are critical for the body’s metabolism and growth and development. They are iodinated tyrosine derivatives, mainly including two active forms, thyroxine (T4) and triiodothyronine (T3) [1,2]. They belong to iodinated aromatic amino acid derivatives. Under physiological conditions, they exist as zwitterions and exhibit lipophilicity, a property that influences their distribution in the body [3]. In the blood, they primarily bind to specific plasma proteins for transport and exhibit high affinity for nuclear receptors [4]. THs are widely involved in the regulation of various physiological processes such as metabolism, growth, development, and the functioning of the central nervous system (CNS). A vast body of literature has reported their important roles in brain development and protection of neuronal integrity. Among the CNS, THs modulate the expression profile of genes involved in neurogenesis, myelination, and synaptogenesis, which are responsible for the proper assembly and functioning of neuronal circuits [5]. The cerebrospinal fluid (CSF), which bathes the brain and spinal cord, contains unbound and transthyretin-bound TH—involved in brain maturation and metabolism, as well as other metabolic THs [5]. In the CNS, THs are involved in energy metabolism and thermogenesis through modulation of the processes of cellular respiration and mitochondrial function, which differ from those observed in peripheral tissues [6]. Moreover, the hypothalamus–pituitary–thyroid (HPT) axis is responsible for the rigorous control of systemic TH levels, which is regulated by feedback inhibition of thyroid-stimulating hormone (TSH) and TRH secretion from the hypothalamus [7].
The thyroid hormone (TH) signaling network relies on transmembrane transport and deiodinase-mediated local metabolism (converting T4 to active T3) to regulate intracellular hormone levels [8,9,10]. Its mechanism of action encompasses genomic pathways—where T3 binds to tissue-specific nuclear receptor subtypes (TRα and TRβ) to regulate gene transcription, as well as transcription-independent rapid signaling cascades. The integration of this dual mechanism precisely maintains the body’s development, energy metabolism, and systemic homeostasis [11,12,13].
Thyroid hormone receptors (TRs) are essential for maintaining metabolic homeostasis and modulate the functioning of different organ systems, including the CNS [7]. TRs, which are ligand-dependent transcription factors, mediate most of TH’s actions and play a crucial role in maintaining metabolic homeostasis while broadly regulating the functions of various organ systems, including the CNS [14,15]. TRs exhibit a complex expression pattern in the CNS. They play a central role in many key brain functions such as neurodevelopment, myelination, energy homeostasis, behavioral plasticity, and circadian rhythms through regulation of gene transcription. Dysregulation of their signaling pathways is associated with various neurodevelopmental disorders, mental illnesses, and demyelinating lesions, and agonists targeting specific TR subtypes have emerged as a promising new strategy for treating metabolic, genetic, and inflammatory neurological diseases [16,17,18].
Therefore, the relationship between THs and the function of the CNS further demonstrate the important role of these hormones on neuronal plasticity and neurotransmission as well as oxidative phosphorylation, which are required for the proper states of cognition and emotion [19].
Neurodegenerative diseases (NDDs) are marked by a decline in neuronal integrity that includes several pathologic conditions such as oxidative stress, neuroinflammation, mitochondrial dysfunction, protein misfolding, and neuronal apoptosis, which lead to the decrement of cognitive and motor functions in AD, PD, Huntington’s disease, and MS [20,21]. The CNS is particularly vulnerable to defects in oxidative phosphorylation and mitochondrial function, which are aggravated by aging and diseases, finally compromising neuronal survival and synaptic integrity [19].
Thyroid hormone (TH) modulates the different underlying pathogenic mechanisms. Any increase or decrease in TH levels can induce defects in neurotransmission, increased oxidative stress, and altered glucose metabolism in the brain, potentially leading to cognitive deficits and acceleration of the neurodegenerative process [22,23]. The HPT axis is closely related to neuronal systems, and in PD, the abnormal regulation of TH has been related to the severity and progression of the disease, probably due to the involvement of similar genetic and molecular traits with PD and thyroid disorders [24]. These features include mitochondrial dysfunction, elevated oxidative stress levels, and abnormal glucose metabolism, which play crucial roles in the neurodegenerative pathology of PD [25,26]. Specifically, the pathogenesis of PD significantly overlaps with age-related biological changes, such as impaired mitochondrial function and oxidative stress, which are also hallmarks of cellular senescence [25]. Meanwhile, PD patients exhibit varying degrees of disorders of glucose metabolism at different stages of the disease, involving multiple key processes such as glycolysis and the tricarboxylic acid cycle [26]. Deficiencies in these cellular metabolic functions are considered key factors contributing to neuronal death and abnormal immune-inflammatory responses in PD [27]. Since THs are core hormones regulating mitochondrial function, redox balance, and glucose metabolism, genetic variations or molecular dysregulations modulating these common pathways may simultaneously influence susceptibility to PD and thyroid diseases, as well as their progression, constituting a similar molecular basis for both [26]. There is a feedback loop between thyroid dysfunction and neurodegeneration. Variability in the signaling of THs can contribute to the onset of NDDs and, conversely, the emergence of NDDs can modulate TH signaling with a vicious circle that promotes disease progression [23]. In addition, neuroendocrine components, such as neuropeptides and hormone receptors, play important roles in neuroprotection and neuronal survival. Therefore, the roles of TH in the pathogenesis of CNS disorders need to be elucidated [28,29].
In recent years, abnormal thyroid hormone levels have been connected with neurodegenerative disorders. Hypothyroidism and hyperthyroidism are associated with cognitive decline and changes in the levels of biomarkers, such as amyloid-β(Aβ) peptides and tau proteins [23,30]. The validity of these findings is further supported by animal studies. For example, changes in the levels of TH, which can happen during development or be induced in animals, lead to lifelong deficits in glial function, which in turn cause enduring impairments in neurogenesis and cognition [31]. In addition, THR and TRs exhibit distinct expression patterns in the brain, which implies that the specific roles of thyroid hormone receptor isoforms in neuronal development and metabolism exist and might profoundly affect the vulnerability to different diseases and the effectiveness of treatments [29,32]. Sobetirome, a thyroid hormone analog, and its CNS-targeting prodrugs, which are selective TRβ agonists, exhibit great potential in promoting remyelination and altering neurodegenerative pathology in preclinical studies [16]. Moreover, environmental toxins and pharmacological agents affect thyroid hormone transport and metabolism. This disruption provides further evidence for the complexity of maintaining thyroid hormone homeostasis in the CNS and its consequences for health [33,34]. Taken together, these advances indicate the increasing awareness of TH and their signaling pathways as critical components in the pathogenesis of NDs and as potential targets for new therapies. This review summarizes recent advances in the field of TH’ roles in NDs. It discusses their mechanisms, effects on pathogenic processes, signaling pathways, receptor isoforms, and therapies with the aim of bridging research and clinical applications for new treatments.
2. The Biosynthesis of TH and HP
The synthesis of TH is a complex process that requires iodine and is mediated by thyroglobulin (Tg). This process is controlled by the hypothalamic–pituitary–thyroid (HPT) axis through positive and negative feedback mechanisms such as TRH and TSH. In addition, the iodide transport into the thyroid gland through the sodium-iodide symporter, or the oxidation of iodide and the subsequent incorporation into Tg by thyroid peroxidase and this process need the hydrogen peroxide synthesized by dual oxidase. Finally, iodinated Tg is subjected to proteolytic cleavage to release T4 and T3 into the bloodstream. The regulation of thyroid hormone synthesis is characterized by feed-forward and feedback mechanisms that include the Wolff–Chaikoff effect, which aims to reduce hormone production when there is excess iodide (TG feedback) and, in turn, feedback from TSH receptor [35,36]. The HPT axis stimulates the pituitary gland to release TSH through the secretion of TRH from the hypothalamus, thereby promoting the synthesis and secretion of thyroid hormones (T4 and T3) by the thyroid gland. The T4 and T3 in circulation regulate the secretion of TRH and TSH through negative feedback, maintaining hormonal balance. When the level of thyroid hormones decreases, the production of TRH and TSH increases; conversely, it is inhibited. Other factors can also regulate this axis [37]. Transcription factors PAX8 and NKX2.1 play a key role in the regulation of expression of the Tg gene. On the other hand, post-translational modifications and transport steps are responsible for proper folding and functioning of Tg and other proteins involved in hormone synthesis. The chaperone protein GRP170 is located in the endoplasmic reticulum and is crucial for the maturation of the TSH receptor. Its absence may be associated with improper folding of the receptor, thereby reducing the reactivity of the thyroid [36] https://pubmed.ncbi.nlm.nih.gov/25146893/, accessed on 1 November 2025. Moreover, hydrogen sulfide (H2S) generated by cystathionine β-synthase (CBS) situated in thyrocytes, enhances thyroid hormone synthesis by increasing the level of sirtuin-1 (SIRT1), which in turn enhances expression of other key proteins, such as TPO, NIS, Pendrin or MCT8. Thus, gasotransmitters also play a very important role in thyroid function [38]. Environmental pollutants, such as bisphenol derivatives or per- and polyfluoroalkyl substances (PFAS), induce disturbances in thyroid hormone production through improper functioning of the iodide absorption process, iodination of Tg or synthesis of T4. Particularly, excess of iodide leads to activation of XBP1 and unfolded protein response, which negatively influences thyroid function, especially in case of iodine deficiency [39]. HPT axis regulates the release of TSH from pituitary gland, through feedback from TH concentration and models simulating the TSH variations and cross-relationships are important for the process of maintenance of homeostasis.
The thyroid gland has autonomous regulation of hormone output through both feed-forward and feedback regulation, irrespective of the pituitary gland, and this regulation is elaborate. Thyroid follicular cells are adaptive, as shown in models of congenital hypothyroidism which demonstrated that follicular cells can survive ER stress-induced apoptosis. Thus, thyroid cells maintain some T4 production through unknown means involving iodinated Tg released from lysed thyrocytes within the follicular lumen [40]. Newly emerged ex vivo and in vitro techniques such as three-dimensional thyroid organoids and Transwell cultures using primary human thyrocytes have greatly improved thyroid differentiation and hormone production studies, greatly resembling the in vivo tissue environment. Nrf2 signaling pathway is involved in the antioxidant defense of the thyroid and in the processing of Tg, maintaining thyroid function under oxidative stress: redox homeostasis and hormone synthesis are linked [41]. Production and secretion of TH are meticulously regulated by an interplay involving iodine metabolism, production of Tg and various activities, and feedback signals from the HPT axis. These processes are modulated by intrinsic thyroid regulation and other hormones as well as environmental effects. The discovery of new pathways such as Nrf2 demonstrates the complexity of thyroid regulation; it also reminds us of the importance of understanding these processes to guide further studies toward developing new therapies for thyroid diseases as well as the impact of environmental factors on thyroid health [42] (Figure 1).
Figure 1.
Schematic diagram of thyroid hormone synthesis, secretion and regulatory mechanisms. (PAX8: Paired Box Gene 8; Nrf2: Nuclear factor erythroid 2-related factor 2; NIS: Sodium-Iodide Symporter; TPO: Thyroid Peroxidase; TG: Thyroglobulin).
3. The Physiological Roles of TH and HPT
Thyroid hormones (THs) and the hypothalamic–pituitary–thyroid (HPT) axis have extensive and crucial physiological functions [37]. Thyroid hormones are essential for the development of the nervous system, linear growth, energy metabolism, and thermogenesis [37]. Metabolically, they regulate the liver’s nutrient metabolism, fluid balance, and cardiovascular system functions. Specifically, thyroid hormones are vital for maintaining metabolic balance in the liver and systemic metabolic balance [43]. Dysregulation of the HPT axis can lead to hepatic metabolic disorders, affecting lipid metabolism, glucose regulation, and protein synthesis. Reduced circulating and intrahepatic thyroid hormone concentrations can increase the risk of metabolic dysfunction-related fatty liver diseases by inducing lipotoxicity, inflammation, and fibrosis [43]. At the cellular level, the effects of thyroid hormones are primarily mediated by nuclear TRs, achieved by altering gene expression. T3 is the preferred ligand for THR. T4, which is approximately 100 times more concentrated in serum, is activated through conversion to T3 by 5′-deiodinase outside the thyroid. The regulation of deiodinases and thyroid hormone transporters on cell membranes, particularly the control of T3 availability, is fundamental to the action of thyroid hormones. Furthermore, studies have found that thyroid hormones may serve as a temporal cue for the central biological clock, with hypothyroidism altering the expression of clock genes in the suprachiasmatic nucleus, body temperature, and metabolic rhythmicity [44].
4. Thyroid Hormones and the HPT Axis in Neurodevelopment
4.1. The Roles of TH and HPT in Neurodevelopment
Thyroid hormones (THs), consisting of T4 and T3, are crucial for brain development and neuronal function. THs are involved in neuronal differentiation, migration, synapse formation, and myelination of nerve fibers. The timing and quantity of thyroid hormone availability are important because both hypothyroidism and hyperthyroidism during certain periods of development can result in severe neurological deficits [45,46,47]. THs act through genomic pathways involving nuclear TRs as well as through non-genomic actions associated with interactions with the neuronal plasma membrane to regulate the proliferation, maturation, and metabolic activities of neural progenitor cells [48,49,50].
The action of TH in the CNS is also modulated by transport proteins and deiodinases that affect the availability and movement of THs in different brain regions [51,52]. Variants in the genes encoding transporters and enzymes involved in thyroid hormone metabolism can lead to defects in myelination and oligodendrocyte development and may cause lifelong neurological impairments (e.g., in syndromes caused by MCT8 deficiency) [52]. The pattern of spatial and temporal expression of these factors makes the localized action of TH signaling particularly important.
Multiple in vitro studies have shown that environmental pollutants can interfere with thyroid hormone signaling and adversely affect gene expression and brain development [53,54,55,56]. Such observations support the idea that the developing brain is susceptible to changes in thyroid hormone levels and that THs play an important role in brain development, including the processes of dendritic arborization, axonal growth, and myelination at the neuronal level. At the cellular level, THs exert significant effects on neuronal function by modulating the properties of synapses and synaptic plasticity. In a more mature brain, THs affect both the excitatory and inhibitory components of synaptic activity, particularly in cortical circuits, thereby influencing cognitive functions and behaviors [57,58]. THs also promote maturation of some neuronal subtypes, such as GABAergic interneurons, which may help to establish inhibitory tone and overall stability of neuronal circuits [59]. In addition, THs modulate the expression of neurotrophic factors, such as brain-derived neurotrophic factor (BDNF), which is involved in processes of learning and memory, thus linking thyroid function to cognitive outcomes [60].
Thyroid hormone (TH) and other metabolic factors influence neuronal development. Low iron levels affect TH-regulated gene expression in hippocampal neurons, indicating their interdependence and the requirement for their coordinated regulation in energy metabolism and neuronal development [61]. Furthermore, THs are essential for the proliferation and functional activities of hypothalamic neurons that mediate energy balance and feeding behavior. This indicates their key role in the relationship between the endocrine and nervous systems [62]. THs are essential for brain development and function, they stimulate the growth and myelination of neurons, their actions are modulated by transporters and deiodinases; any abnormalities in these processes can lead to neurodevelopmental disorders, so it is important that appropriate levels of these hormones are maintained and suitable therapies found [46,52,53,57,62].
4.2. TH Receptors and Their Signal Transduction Pathways
Thyroid hormone (TH) enter the target cell and mediate their physiologic effects through genomic mediated by TH receptors, TRs, which bind to DNA and regulate gene transcription, essential for the development of the nervous system and the correct functioning of the mature brain [63,64]. Corepressors such as NCOR1 and NCOR2 repress gene expression in the absence of hormones; however, when hormones are present, coactivators such as SRC-1 enhance gene expression and fine-tune gene expression through histone modification [65]. Importantly, mutations in the TR genes lead to TH resistance syndrome [66,67].
Thyroid hormone (TH) also mediate rapid non-genomic signaling through integrin αvβ3 receptor, which modulates the intracellular signaling pathways such as MAPK/ERK1/2 and PI3K/AKT, which are crucial for the regulation of cell proliferation, survival, angiogenesis, and metabolism, playing an important role in neuroprotection after the cerebral injuries [68,69,70,71]. For example, T4 binding and signaling through integrin αvβ3 lead to the activation of MAPK/ERK1/2 signaling cascade, which plays a pro-survival role in neurons and modulates the expression of genes involved in the processes of oncogenesis and NDDs [72,73]. Therefore, environmental pollutants with TH activity (such as TDCPP), which could enter the cell and bind to integrin αvβ3 receptor, could modulate the intracellular signaling pathways described above and induce neurodevelopmental toxicity [74,75].
G protein-coupled receptors (GPCRs) transmit cellular signals in response to diverse stimuli, including thyroid stimulating hormone receptor (TSHR), which is involved in TH signaling and activates G protein pathways, which modulate cell growth and differentiation in thyroid and in brain [76,77]. Notably, signaling of TSHR is linked to specific cognitive functions and the preservation of synaptic structures since cognitive deficits were observed in TSHR-knockout mice and therefore is important for neuronal health. Moreover, the idea of compartmentalized GPCR signaling suggests that GPCRs could send signals from different intracellular compartments, such as endosomes and Golgi apparatus, which adds another level of complexity to the understanding of the mechanisms regulating TH-related signal transduction and development of therapeutic strategies [78,79,80].
In summary, TH signaling through receptors and integrin αvβ3 has important effects in the CNS because it modulates other processes in the brain such as dendritogenesis, neuritogenesis, and synaptic plasticity. It has been reported that nuclear TR activation and signaling pathways involving FAK-Akt and ERK1/2 are necessary for these processes [69]. Astrocytes effective interaction with neurons through these signaling pathways are necessary for a proper neuronal development and function, highlighting the relevance of coordinated cellular communication with other cells [81,82]. TRs modulate the expression of genes, but also activate signaling pathways non-genomic that play an important role in neurodevelopment and metabolism, which are of great importance in the face of NDDs and brain injuries [83,84,85]. Neurological sciences represent an opportunity to know these interactions to achieve a better use of TH as therapy.
5. The Roles of TH and HPT in NDDs
5.1. Thyroid Hormone and Alzheimer’s Disease
Thyroid hormones (THs) markedly influence AD through their effects on Aβ metabolism, tau phosphorylation, neuroinflammation, and oxidative stress mechanisms that are essential for maintaining synaptic homeostasis and neuronal survival. THs modulate amyloid and tau pathologies, control neuroinflammatory responses, and maintain the levels of oxidative stress. In summary, thyroid disturbance affects AD pathogenesis by inducing oxidative stress and mitochondrial dysfunction, which lead to cognitive decline.
Hypothyroidism and hyperthyroidism are associated with an increased risk of AD. Prevalence of hypothyroidism was much higher in AD patients than in controls [86]. The rate of clinical hypothyroidism and clinical hyperthyroidism were similar between AD patients and control subjects; however, alternative analyses revealed that overt hypothyroidism may protect against AD development and that hyperthyroidism may increase the risk of AD dementia [87]. These results imply that TH exerts a complicated effect on AD pathogenesis, which is supported by the Korean study on the prevalence of different thyroid disorders among AD patients [88,89]. Currently, evidence suggests that thyroid disturbance may increase AD risk by enhancing hypothyroidism and hyperthyroidism, which highlights the necessity of assessing thyroid function and promoting further studies on its effect on the progression of AD. A deviation in the levels of THs even within the so-called “normal” range is linked to the pathophysiology of AD. It has been demonstrated that patients present with changed FT4, and T3/T4 ratios, suggesting a disturbance in the conversion of T4 to T3, which may harmfully affect selected brain regions involved in AD [90]. In addition, reduced serum levels of T3 have been linked to an increased cerebrospinal amyloid burden and cognitive decay, underlining the important role of THs in Aβ-related pathology [91,92]. It has been reported that hypothyroidism is highly expressed in subjects with AD, indicating the presence of a positive loop in which hypothyroidism could be both a reason and an effect of the underlying pathological program of AD [23,93]. Additionally, autoimmune thyroid disease has been linked to greater amyloid and tau pathologies, regardless of hormone concentrations, indicating other potential pathways by which thyroid dysfunction may contribute to the progression of AD [94].
Hypothyroidism promotes AD progression by increasing amyloid-beta levels, facilitating tau phosphorylation, and impairing memory functions; meanwhile, AD pathology impairs TH metabolism, thereby forming a positive feedback loop [95,96]. In contrast, hyperthyroidism aggravated cognitive deficits and amyloid-beta accumulation by enhancing neuroinflammation and necroptosis (a programmed cell death process), suggesting that immune pathways may explain the increased AD risk due to TH disturbance. Irregularities in the levels of TH may promote amyloid-beta accumulation due to interference with the proper functioning of microglia. This is supported by the results obtained in murine models of Alzheimer’s, in which hypothyroidism results in detrimental effects on innate immune responses and an amplification of amyloid pathology [97]. In addition, THs are involved in tau pathology. The increased levels of free T3 and FT4 serum levels show a stronger association with the Aβ–tau burden, suggesting that THs may induce tau phosphorylation and aggregation in an Aβ-dependent manner [98]. The hyperphosphorylation of tau may be induced by impaired insulin signaling and increased activity of glycogen synthase kinase-3 beta (GSK-3β). The relationship between THs and neuroinflammation is also illustrated by the regulation of pyroptosis pathways. One of the most striking features of synaptic dysfunction is a lack of TH, which greatly modulates the expression of synaptic proteins and perturbs neurotransmission. Perturbed neurotransmission enhances cognitive impairments and neurodegeneration, forming a positive feedback loop in which thyroid deficiency induces neurodegeneration that, in turn, further impairs TH balance [97]. TH and AD pathology are not merely causally related; instead, they constitute a “vicious cycle” [23]. On the one hand, primary hypothyroidism can contribute to the onset and progression of AD through various pathways, such as inducing Aβ production, promoting tau protein hyperphosphorylation, triggering oxidative stress and endoplasmic reticulum stress, damaging mitochondrial function, and inhibiting BDNF [95]. On the other hand, the neurodegenerative lesions of AD itself, especially the accumulation of Aβ and phosphorylated tau protein, can in turn disrupt the metabolism, transport, and signaling of TH in the brain, resulting in secondary hypothyroidism within local brain tissue, which further exacerbates neuronal damage and cognitive decline [23,95]. This bidirectionally reinforcing relationship makes thyroid dysfunction both a risk factor for AD and possibly a result of its pathological progression. In total, these results highlight the important role of TH in the pathophysiology of AD, especially TH’s impact on amyloid-beta (Ab) metabolism and tau pathology; phosphorylation, neuroinflammation and oxidative stress are critical factors.
Interestingly, TH derivatives such as 3-iodothyronamine may correct AD pathogenesis by restoring synaptic functionality, which may provide new insights for the treatment of AD [99,100]. TH supplementation may correct the above-mentioned irregularities and enhance the activity of the anti-apoptotic protein Bcl-2, thus potentially diminishing tau-related pathology and neuronal apoptosis in models of AD [101]. For example, T3 supplementation may reduce the expression of microglial markers and pro-inflammatory cytokines in the hippocampus, and increase the expression of anti-apoptotic proteins, such as Bcl-2, to protect neurons [101,102]. For example, intranasal lithium treatment, which exerts effects on signaling related to THs, may effectively suppress pyroptosis and inflammatory responses in the cerebral environment of mouse models of AD [101,103]. Strategies targeting the modulation of TH signaling pathways may provide a promising way to slow down or prevent the progression of AD by recovering these vital protective effects (Figure 2).
Figure 2.
Mechanism of TH regulation in AD.
5.2. Thyroid Hormone and Parkinson’s Disease
Thyroid hormones (THs) are responsible for modulating lipid metabolism and cerebral blood flow, which are of great importance in relation to PD. TSH may represent the link between peripheral metabolism and the CNS, which, in turn, modulates the energy balance and cellular homeostasis. Alterations in lipid metabolism are involved in NDDs, such as PD, potentially promoting neuroinflammation and increasing neuronal susceptibility [98]. Moreover, metabolic disturbances caused by hypothyroidism (such as obesity, increased cholesterol levels, and anemia) may complicate the pathology of PD by disturbing cerebral blood circulation and promoting oxidative stress [24]. Neuroimaging combined with microstructural analyses and molecular investigations have shown that there is dysfunction in the hypothalamus of PD patients. For instance, the mean kurtosis in particular hypothalamic subregions was decreased, and such changes were associated with TH levels and clinical manifestations. Such changes could be detected at the early stages of the disease and in patients with probable REM sleep behavior disorder (pRBD), which indicates that hypothalamic dysfunction may participate in the development of PD [96]. THs, namely T4 and T3, coordinate energy metabolism by modulating the metabolism of glucose, lipids, and proteins in different tissues. Dysregulation in the thyroid–liver axis has been implicated in the pathogenesis of metabolic disorders such as metabolic dysfunction-associated steatohepatitis (MASH) and early metabolic changes in PD [93]. In subjects diagnosed with MASH, increased serum levels of TSH and free triiodothyronine (FT3) and decreased FT4 levels independently predict the likelihood of developing MASH. These results suggest that an imbalance in TH could contribute to the sequestration of hepatic lipids and the promotion of inflammation [104].
It is known that there is a change in thyroid function in patients with PD; namely, the levels of FT3 are reduced, and TSH levels are increased, especially in patients who have cognitive impairment, which indicates that thyroid function may affect the severity of the disease [87]. In addition, thyroid dysfunctions encompassing hypothyroidism and hyperthyroidism are significantly associated with an increased risk of PD. Distinct associations with gender and age have been found. For instance, older males showed a stronger association with hypothyroidism, while hyperthyroidism was more common in younger females with PD [88]. TH abnormalities may help to explain PD and its motor as well as non-motor symptoms through their biological pathways. Thyroid dysfunction may mimic movement disorders such as PD, since hypothyroidism may present hypokinetic signs, and tremor is associated with hyperthyroidism. Therefore, it is possible to suggest that there is an association between thyroid hormonal imbalance and motor control [92]. In other words, for instance, in patients who are diagnosed with PD, different TH levels (particularly, a reduction in T3 and high TSH levels are associated with more severe motor symptoms and disease progression. So, it is evident that thyroid state has a great impact on the severity of PD [97]. Additionally, other non-motor symptoms, such as cognitive impairment, anxiety, and depression, have also been associated with TH variations in patients with PD. Thus, it has been demonstrated that low serum free T4 concentrations are significantly associated with cognitive decline in PD patients, and an integrated study of TSH, FT3, and free thyroxine may represent crucial biomarkers for cognitive impairment in elderly patients [87]. These clinical observations demonstrate the multiple and complex roles that TH assume in the symptomatology of PD, going beyond the well-known motor-related phenotypes. Serum TH and TH responsiveness markers are associated with components of the metabolic syndrome, such as insulin resistance and obesity. Moreover, FT3 and FT3/FT4 ratio are associated with different phenotypes of obesity, while TSH levels are associated with disturbances in glucose metabolism [105,106,107]. However, the results of Mendelian randomization studies have not found a causal relationship between thyroid dysfunction and the development of PD. Suggesting they may be contributing factors or modulators of disease progression rather than the primary etiological agents [91]. Despite the known correlations, Mendel randomization studies have not provided support for the causality between thyroid dysfunction and PD. This suggests that thyroid abnormalities may play the role of modifiers that may influence the severity and progression of PD rather than being the primary cause for the pathogenesis [91].
Therefore, it is essential to maintain a balance of TH as a basic pathophysiological mechanism involved in PD. Genetic studies have revealed associations between PD and thyroid disorders through shared susceptibility loci and immune pathways. It has been found that risk-associated loci affect the functions of thyroid and support the notion that immune dysregulation plays an important role in the coexistence of PD and thyroid disorders [89]. Furthermore, it has been found that the NR4A2 gene belonging to steroid-TH-retinoid receptor superfamily is correlated with the neurodegenerative process and movement disorder, indicating that TH signaling pathways may be involved in the pathogenesis of PD [95]. In addition, the autonomic denervation of the thyroid gland (shown by the reduced uptake in cardiac MIBG scintigraphy, an imaging method for the visualization of the thyroid gland by measuring the uptake of the radiopharmaceutical cardiac MIBG, which is a specific marker for sympathetic nerve function) is associated with the systemic metabolic changes induced by the PD, i.e., the TH levels were reduced, and the fatty acid β-oxidation regulated by the thyroid–liver axis was impaired. This autonomic dysfunction may break the normal feedback of the HPT axis and the release of TH (as shown in the extensive effects induced by the disease in the brain and body) [99,100]. Mechanisms of dopaminergic system–HPT axis cross talk. Regulatory mechanisms are disrupted in dopaminergic system–HPT axis, and the degree of disruption may be associated with the degree of PD and its motor complications. Autonomic denervation of the thyroid gland may be responsible for the dysfunction of the sympathetic nervous system to impair the secretion of TH. This dysfunction may cause metabolic disorders and unbalance, accelerating the course of PD [99,100]. Disruption of the autonomic–thyroid axis may impair β-oxidation of fatty acids in the liver. Illustration of the broken communication between the two organs represents an early biomarker for PD [99]. Moreover, genetic studies have shown the connected molecular pathways involved in the association between PD and thyroid disorders. It has been suggested that immune-related mechanisms play a critical role in the association between these two disorders, because many single nucleotide polymorphisms (SNPs) associated with susceptibility to PD also are associated with thyroid function, probably through immune-mediated pathways, so they may have an immunopathogenic basis [101]. The NR4A2 gene belongs to the steroid-TH-retinoid receptor superfamily and has been implicated in the pathogenesis of diverse human diseases, including neurodevelopmental, and neurodegenerative disorders such as PD [95]. The role of TH in PD not only affects metabolism and neural regulation but may also exacerbate pathology by interfering with basic cellular processes such as protein homeostasis and neuronal cell membrane function. Research indicates that the conformational stability of proteins is crucial for their function, and environmental factors such as pH changes can cause proteins to irreversibly transition from their native conformation to a denatured state [102]. Furthermore, TH is critical for regulating the physical properties of neuronal cell membranes. For example, the activity of membrane-bound enzymes (such as (Na+/K+)-ATPase) is highly dependent on the fluidity of their phospholipid environment, and components like cholesterol can alter this fluidity and significantly affect enzyme activity and temperature response curves [103]. TH imbalance may similarly change the lipid composition and fluidity of neuronal membranes, thereby affecting membrane protein function, signal transduction, and cellular homeostasis, providing a potential cellular biological basis for TH abnormalities exacerbating neuronal dysfunction in PD [103]. Impaired β-oxidation of fatty acids is an early manifestation of reduced β3-oxidation of fatty acids in PD, which is regulated by TH and thyroid deiodinase enzymes involved in modulating TH availability in the liver [94]. Moreover, microRNAs could epigenetically regulate the TH signaling in liver by targeting THRB and DIO1, which may contribute to the development of acquired hepatic resistance to TH in the progression of MASH. These molecular results further support the notion that the regulation of metabolism by TH is finely tuned in disease conditions [108]. Furthermore, intracellular TH metabolism, regulated by deiodinases and transcription factors such as FoxO1, is involved in cardiomyocyte hypertrophy and energy metabolism, which implies that TH signaling may also modulate metabolic tissues other than the liver [105,109]. There is reciprocal interaction between the regulation of dopamine and the activity of TH in PD [24,90].
Thyroid hormone (TH) and regulatory peptides are potential promising therapeutic options for PD due to their neuroprotective effects [86]. Pharmacological interventions to the dopaminergic system may maintain the balance of the HPT axis. For example, levodopa can normalize TSH and TH levels in patients with resistant PD and may be able to help to restore balance in the HPT axis and resolve PD-associated endocrine disorders [90]. Therefore, it is worth exploring biomarkers and potential treatments targeting the restoration of balance in the HPT axis. Furthermore, dopaminergic therapies (L-DOPA) used in the treatment of PD not only ameliorate motor symptoms but also modulate thyroid function by normalizing TSH and T3 hormone levels. These observations indicate the close interactions between neurological medications and endocrine regulation in the process of PD. However, based on the clinical evidence and molecular studies, it can be postulated that disturbances in the regulation of TH may affect various symptoms of PD and therefore represents an important target which needs to be corrected. Rectifying the TH levels imbalance may improve both motor and non-motor symptoms and possibly affect the progression of the disease. This indicates the need for further exploration for the relationships between thyroid function and PD as well as the development of individualized management. These results further support the possibility of developing new therapies targeting TH pathways to correct the disturbance in metabolism.TH replacement therapy with Levothyroxine is effective in hypothyroidism treatment. However, thyroid function-based individual dose-tailoring is necessary to prevent potential overtreatment or under treatment [110]. Selective THRB agonists, so called thyromimetics, may represent an innovative treatment option for hepatic diseases, such as hepatic steatosis or MASH. Recently, resmetirom was approved by the FDA [111,112]. In addition, the use of nanoparticle drug delivery systems improved the liver-targeting efficiency and the treatment efficacy of thyromimetics, which in turn facilitated the resolution of obesity-induced metabolic complications without impairing thyroid function overall [113].
5.3. TH and MS and Other Neurodegenerative Diseases
Thyroid hormone (TH) level plays a critical role in both demyelination and remyelination process. Demyelination is more pronounced in hypothyroid rats than in euthyroid controls, suggesting that THs have a protective effect against demyelination [95,96,99]. Based on the regulation of immune-related genes by TH and their impact on the neuroinflammatory environment, TH deficiency may exacerbate neuroinflammation and disease progression by promoting the expansion of pathogenic immune subsets such as Eomesodermin+ helper T cells (Eomes+ Th) [92]. This indicates that TH signaling plays an important role in maintaining immune homeostasis in the CNS, and its dysregulation may contribute to the development of neurodegenerative lesions. Therefore, TH deficiency may promote MS and other NDDs by disrupting the homeostasis of the neuro-immune-metabolic network, including affecting metal ion balance and the oxidative stress and inflammatory pathways they mediate [97]. Deficiency of TH is increasingly being recognized to contribute to the development of NDDs such as AD, PD, Huntington’s disease (HD), and MS. This is due to the important roles that THs play during brain maturation and neuronal protection. With respect to HD, the absence of THs may prolong disease progression due to increased neuronal vulnerability, although there is limited research studying THs and its pathophysiology with HD [101]. The pathological correlation between TH deficiency and MS is further supported by observations indicating that low TH levels result in incomplete remyelination and persistent neurological defects [102]. In addition to directly affecting the CNS, alterations in TH functions may also worsen systemic inflammation and immune dysregulation, which may facilitate the progression of diseases such as MS, where immune-mediated processes play a major role. Deficiency in THs induce NDDs such as Huntington’s and MS by neuronal survival and myelin integrity, which involves aspects of cellular energy metabolism and oxidative stress and immune dysregulation. TH is crucial for maintaining immune balance, and its deficiency may lead to the expansion of pathogenic T helper cell subsets. suggesting that TH may influence the progression of various NDDs by regulating such cells. These findings indicate that TH deficiency promotes neurodegenerative lesions through multiple mechanisms, including direct action on glial cells, indirect effects on the function of specific immune cells, and disruption of the homeostasis of the neuro-immune-metabolic network.
Thyroid hormone (TH) affect the myelination process in the CNS by interaction with nuclear receptors. TH receptor have been implicated in oligodendrocyte precursor cell differentiation into mature oligodendrocytes that produce or re-myelinate myelin and oligodendrocytes in MS [86]. TH receptors activation leads to the up-regulation of transcription of genes encoding myelin proteins and facilitate myelin protein synthesis and maintenance of myelin sheath [87,88,89]. The molecular mechanisms underlying Sob-AM2 actions include both genomic effects on myelin-related genes and non-genomic signaling pathways. TH may act through the integrin receptors on oligodendroglial cells and induce specific signaling cascades that promote oligodendrocyte maturation and myelin sheath development [90]. These pathways may be involved in integrating specific extracellular signals and coupling them with intracellular metabolic activity and growth factors, which in turn promote differentiation of OPCs into myelinating OLs during the remyelination process. Additionally, TH has been shown to regulate many immune-related genes, including TREM2, and therefore suggests that when TRs are activated there are significant changes in the neuroinflammatory environment that likely plays a role in the pathophysiology of demyelinating diseases [91]. In addition, THs are involved in maintaining the balance of trace elements (such as zinc), and zinc deficiency disrupts the balance among Th1/Th2/Th17 cells, which is considered one of the pathogenic mechanisms of MS [97]. THs are required for the maturation of oligodendrocytes and myelin synthesis in MS. TH receptors mediate remyelination and maintain myelin integrity; hence TH receptors may serve as potential targets for remyelination in MS and other disorders [18,21]. THs are essential for the expression of genes involved in neurogenesis and energy metabolism; any abnormalities in TH levels will lead to NDDs. Furthermore, THs play a major role in regulating systemic metabolic functions such as fatty acid β-oxidation. Investigators have implicated TRH as a promoter of TH secretion [93]. Neuroprotective effects of TRH have been demonstrated through its ability to activate the PI3K/AKT pathway and protect neurons against excitotoxic conditions [28]. In addition to the effects on classic pathways such as myelination and cellular energy metabolism mentioned above, the mechanism by which TH deficiency promotes other NDDs also includes its role in fine-tuning the central nervous immune microenvironment. Additionally, TH is involved in maintaining the homeostasis of trace elements (such as zinc), and zinc deficiency can disrupt the balance between Th1/Th2/Th17 cells, which is believed to contribute to the pathogenesis of MS [97].
Based on this knowledge, research has attempted to mimic this molecular event by applying T3 in combination with apo-transferrin and found that this combination has synergistic effects on oligodendrocyte maturation and remyelination in vivo. The beneficial effects of this combination were markedly reduced by administration of TH receptor antagonists, which significantly promote oligodendrocyte maturation and in vivo remyelination [100]. Selective TRβ agonist Sob-AM2 promoted remyelination in oligodendrocytes with little or no peripheral side effects attributable to TH, as assessed by enhanced myelin regeneration in demyelinated murine models [16]. Clinically, from a preclinical standpoint, and even from initial clinical findings, there is reason to be optimistic that targeting TRs may be a viable approach to treat demyelinating diseases. Success in large animal models of disease has shown thyromimetic agents to promote remyelination and help recover function in the setting of significant CNS demyelination, opening up a promising opportunity to translate these findings into treatment for human MS [18]. Overall, these observations have set the stage for success with TR agonists. While these represent significant opportunities, there is a clear gap in the clinical trials space that highlights the need for careful assessment of the safety profiles of TR agonists, given the varied systemic effects of TH, including on the cardiovascular system, metabolic effects, and brain physiology [98]. Initial clinical findings have shown some degree of efficacy and tolerability, but larger and more integrated studies are needed to validate these results. Nonetheless, the overall body of work has provided strong evidence that TH signaling, through nuclear receptors, plays an essential role in oligodendrocyte differentiation, synthesis of myelin proteins, and remyelination, thereby positioning TRs as promising therapeutic targets for demyelinating diseases Investigations on modulation of THs and its effects on NDDs have gained considerable interest. At present, investigators are evaluating the effects of TRH analogs with improved pharmacokinetic properties to determine whether they can improve cognitive function, slow down the progression of NDDs and reduce significant fluctuations in the systemic TH levels [94]. Furthermore, thyromimetic agents such as sobetirome and new diphenyl-methane derivatives have been shown to be effective in stabilizing transthyretin amyloidosis, a pathologic process involved in neurodegeneration, highlighting the potential of TH analogs and their substantial therapeutic benefit [108]. Therefore, novel therapies targeting the TH pathway, such as centrally selective TH receptor β agonists (e.g., sobetirome and its prodrug Sob-AM2), which have shown significant myelin repair potential in preclinical models [16,106], have become promising therapeutic strategies.
6. The Cellular and Molecular Signalling Mechanisms of TH and HPT in Neuroprotection and Anti-Neuroinflammatory Effects
6.1. Neuroprotective Mechanisms of TRH
TRH has been widely studied as an important hormone existing in the HPT axis, which can promote TSH and prolactin secretion. In addition to the endocrine function, TRH has been reported to be neuroprotective in NDDs and brain injuries (traumatic brain injury, TBI). This neuroprotective effect of TRH may be associated with the PI3K/AKT signaling pathway, which mediates the suppression of glutamate-induced excitotoxicity [28,114]. In addition, the neuroprotective effect of TRH analogs may be related to the protection against oxidative stress. However, TRH analogs cannot be widely used in clinic because of the limited penetration of TRH analogs into the brain via the blood–brain barrier [115,116]. Thus, it is essential to study TRH analogs and corresponding delivery systems for the treatment of NDDs and brain injuries. This highlights the importance of studying receptor signaling in clinical neurology [117,118] (Figure 3).
Figure 3.
Thyroid hormones (THs) are key neuroprotective and anti-neuroinflammatory signaling mechanisms.
6.2. TH and Neural Stem Cells (NSCs) Function Regulation
Thyroid hormones (THs), either T3 or T4, play a positive modulatory role in the regulation of NSCs that give rise to the brain and are involved in brain repair. THs are mainly present in the neurogenic areas of the brain such as the SVZ and the SGZ. In these regions, T3 promotes the commitment of NSCs to neuronal fates and modulates the differentiation of OPCs, which are important for oligodendrocyte myelination [119,120]. The molecular mechanisms underlying these actions are partly mediated through genomic pathways, such as the translocation of TH receptors into the nucleus, and partly through non-genomic pathways that regulate mitochondrial activities [121], which affect the self-organization of progenitor cells at different developmental stages. Transcriptomic analysis in Xenopus laevis has shown that signaling through the TH pathway is essential for regulating gene expression in NSCs and progenitor cells. T3 exposure results in the upregulation of genes involved in the biogenesis and functions of ribosomes, translation, mitochondria, and proteasomes, which are important for the activation of NSCs and neurogenesis [122].
In TBI, MS, and other NDDs, NSCs provide valuable insights into repair processes. Data support the notion that THs induce the proliferation and differentiation of NSCs toward neurons and oligodendrocytes to promote remyelination and neuronal regeneration [123]. T3 attenuates neuronal mortality after TBI through mitophagy and enhances neurogenesis, suggesting that T3 has dual protective and regenerative effects [124]. The transport and localized activation of THs within neurogenic niches are regulated by MCT8 and DIO2, which are involved in NSC signaling. Knockout of these proteins results in defects in neurogliogenesis and olfactory functions, highlighting the importance of TH metabolism during brain repair [125,126]. Ratios of TH concentrations at critical periods of development, such as those caused by hypothyroidism or PFAS-induced disruption of TH signaling, can inhibit NSC growth and differentiation, leading to lifelong impairments in neurogenesis and oligodendrogenesis. Specifically, PFAS disrupts oligodendrogenesis and remyelination. T3 may rescue these effects, suggesting that modulation of TH signaling could provide protection against the environmental toxin PFAS [119,127,128]. THs regulate NSCs, specifically tanycytes, which display stem cell-like properties. Decreases in the expression of neural cell adhesion molecules such as NrCAM, are associated with decreased tanycyte populations and related markers, suggesting that TH signaling regulates the maintenance and differentiation of NSCs [129]. In addition to the mechanisms described above, THs exert a large degree of control over NSCs through interactions with other signaling pathways, such as Sonic Hedgehog, The TRIP6-YAP-SHH axis is particularly important for the maintenance and differentiation of NSCs in the postnatal SVZ [130]. Synthetic agonists modulating TRβ1 can increase the differentiation of OPCs in inflammatory contexts, suggesting new potential therapies for demyelinating diseases [131]. We identified TH transporters and receptors within human neural progenitor cells and neurons using human cerebral organoid models. These data support the idea that TH signaling plays a role in cortical development and neurogenesis, which is useful for understanding the mechanisms underlying TH-related neurodevelopmental disorders [132,133,134].
Despite achieving biochemical euthyroidism, many patients still experience lingering symptoms like cognitive impairment and fatigue. This finding implies a potential shortcoming in TH signaling within the CNS [135,136]. Levothyroxine monotherapy results in an increase in serum free T4; however, it may cause a decrease in serum free T3 due to impaired conversion function, which may be detrimental to neuropsychiatric symptoms [137,138]. For some patients, a combination approach with liothyronine (LT3) in conjunction with LT4 may improve quality of life and reduce symptoms, despite a paucity of information regarding the long-term safety of this combination therapy [135,139]. Variability in genetic polymorphisms of deiodinase enzymes may benefit from individualized consideration regarding TH replacement therapies [137]. Hypothyroidism worsens cognitive decline and neuropsychiatric symptoms in patients with NDDs, TH replacement therapy (THRT) partially eliminates these problems, but cannot eliminate them altogether, highlighting the shortcomings of our treatment modalities [136]. The use of extended LT4 therapy risks subclinical hyperthyroidism, which increases cardiovascular risks in the elderly population and complicates management regimens [140,141]. Both under- and over-treatment are detrimental to patient outcomes, and careful consideration of THRT dosage and monitoring is imperative [141,142]. In special populations, like pregnant women, careful titration of THRT is necessary to maximize neurodevelopmental outcomes for both mother and child [142,143]. Novel treatment modalities utilizing thyroid extracellular matrix hydrogels are being investigated to overcome the limitations of hormone replacement therapy and restore thyroid function, with potential advantages for the treatment of NDDs [144,145]. TH replacement therapy successfully normalizes TH levels but struggles to restore tissue function, particularly in the brain. Patient variability in response highlights an opportunity for improvement and calls for further research and advanced treatment strategies for NDDs associated with hypothyroidism.
Thyroid hormones (THs) are closely related to the pathological processes of various NDDs, and their changes are associated with key pathological markers. They participate in disease progression by affecting specific neural pathways [146,147]. Abnormal thyroid function can alter the processing of β-amyloid precursor protein [146], and the neurotoxicity mediated by thyroid hormone response proteins suggests that TH signaling may intersect with amyloid pathology [146]. In PD, TH levels are significantly associated with cognitive dysfunction1; the increased co-expression of dopamine transporters and tyrosine hydroxylase in peripheral immune cells suggests a common regulatory abnormality [148]. In animal models, promoting TH signaling can increase the number of dopaminergic neurons in the substantia nigra and dopamine levels, improving motor function [149], indicating that TH supports the survival and function of dopaminergic neurons, and its dysregulation may participate in pathology by affecting dopamine synthesis and transmission. In MS, the role of TH focuses on myelination and oligodendrocyte function, and its promotion of oligodendrocyte maturation and myelination depends on the activation of transcription and metabolic pathways within the CNS [150]. The metabolic dysfunction of oligodendrocytes and the dysregulation of TH-dependent pathways in MS constitute one of the key mechanisms driving demyelination and neurodegeneration; thus, TH dysregulation is mainly associated with myelin pathology. In addition, the frequency of Eomesodermin-expressing Th cells is increased in MS patients, and these cells may also play a role in other NDDs [151].
6.3. The Expression of TH in the Brain Region of NDDs
The expression of TH in the CNS and metabolic alterations are important components of the pathophysiological mechanisms of various NDDs, showing significant regional specificity in different diseases. In AD, pathological changes exceed the variations in serum TH profiles [90]. Studies have found that local hypothyroidism occurs in the hippocampus (a key brain region related to memory) of AD model mice, with the mechanism being the specific downregulation of deiodinase type 2 that converts thyroxine to active triiodothyronine. This local hormone deficiency in brain tissue can occur earlier than changes in peripheral blood indicators. It can also inhibit the innate immune response of microglia, thereby exacerbating disease progression [97].
In PD research, clinical observations suggest that TH levels are related to the degree of cognitive impairment in PD patients [146]. More notably, studies have found that the expression of dopamine transporters and tyrosine hydroxylase is significantly upregulated in peripheral blood mononuclear cells of PD patients, and this phenomenon is replicated in PD animal models, suggesting that central lesions in the nigrostriatal dopaminergic pathway may trigger compensatory changes in peripheral immune markers [148].
For MS, the role of TH signaling in promoting myelin regeneration is a research focus. TH and CNS-selective agonists can drive oligodendrocyte precursor cell differentiation and effectively promote remyelination in MS animal models [152,153]. In experimental autoimmune encephalomyelitis models, supplementation with triiodothyronine has been confirmed to protect myelin, maintain nerve conduction, and preserve axonal integrity [154]. However, systemic administration of TH in chronic demyelination models may inhibit endogenous repair, while central selective TH receptor agonists show better therapeutic potential [153].
In HD, lesions are highly concentrated in the striatum. Research reveals that the expression of a key TH binding protein—μ-crystallin—is downregulated in the striatum of HD animal models [155]. This protein is specifically highly expressed in the striatum, and its absence enhances the susceptibility of striatal neurons to the toxicity of mutant huntingtin protein, indicating that TH-related local metabolic dysregulation may be one of the core factors leading to the selective vulnerability of this brain region [156].
7. Research and Application of Thyroid Hormones and Related Derivative Drugs
7.1. Therapeutic Perspectives and Clinical Potential
Thyroid hormone(TH) analogs, like sobetirome, which are selective agonists of TRβ, possess a remarkable potential for the treatment of neurodegenerative disorders due to their ability to promote neuronal wellbeing and myelin repair with a better safety profile than natural thyronines [16]. Interestingly, recent studies have revealed that TH analogs can stabilize transthyretin (TTR), a protein essential for TH transport and responsible for neurodegenerative amyloidosis, by preventing TTR aggregation, making them promising multi-target drugs for the treatment of the hereditary amyloidosis, familial amyloid polyneuropathy and even AD. In addition, sobetirome analogs are expected to provide therapeutic benefits for genetic diseases, such as Allan–Herndon–Dudley syndrome, which is caused by mutations in the MCT8 gene that lead to defective TH transport to the brain and neurological deficits by accumulating thyroid signaling in the CNS (e.g., Sob-AM2 can be used for brain accumulation and myelin repair in NDDs) [157]. In addition, sobetirome displays certain anti-inflammatory activities that may be beneficial for neurodegenerative disorders. For instance, TH analogs can modulate macrophage polarization and suppress M1 phenotype, an activated macrophage state that is involved in inflammation (TRβ1-activated macrophages), which may represent a potential mechanism for immunomodulation in neuroinflammation [158]. With the development of molecular biology, receptor-selective compounds are being developed to treat CNS disorders while alleviating side effects in distant organs. Recently, TH analog, resmetirom, approved for metabolic disorders, is an example [159]. Innovative TH analogs like sobetirome may represent novel therapeutic approaches for the treatment of NDDs by regulating metabolic process, preventing amyloid aggregation, promoting remyelination and reducing inflammation while bypassing defective transport system and activating beneficial receptors. However, the in vivo effectiveness and safety of TH analogs should still be further investigated [157].
Thyrotropin-releasing hormone (TRH), being a tripeptide, plays a key role in regulating the HPT axis and also exhibits neuroprotective properties; however, its clinical use is limited due to poor absorption and rapid degradation [160]. Therefore, these characteristics have motivated numerous studies on novel strategies for avoiding the above-mentioned delivery approaches and the formulation of TRH analogs that retain biological activity but overcome these limitations. It has been reported that TRH could be effectively used to bypass the blood–brain barrier, which improves the CNS accessibility [161]. Meanwhile, the application of biodegradable polymer-based nanoparticles can provide high drug loading and controlled release, which are critical for the above-mentioned therapeutic effect. Subsequently, by employing intranasal refillable atomizers, these nanoparticles were effectively delivered to the olfactory neuroepithelium, which improved the cerebral delivery while reducing the systemic degradation. For the above-mentioned TRH-loaded nanoparticles, in vivo safety evaluations using cynomolgus monkeys and rats demonstrated that there was no obvious systemic adverse reaction and no apparent endocrine disturbance, and the TSH and prolactin levels were well maintained. There was slight damage to the nasal tissue. Overall, these results demonstrated the safety and biocompatibility of the above-mentioned nanoparticles [162]. No apparent endocrine disturbance was noteworthy, given that TRH is involved in the HPT axis and there is a potential risk of inducing unexpected hormonal effects. Sophisticated delivery system: lipid-core polymeric nanocapsules: improve the bioavailability and effectiveness of TRH by enhancing the encapsulation and delaying the release rate of TRH to achieve the best pharmacodynamics [163]. Chemical permeation enhancers such as carveol and borneol promote the diffusion of peptides into the dermis. However, the CNS is still favored for intranasal administration because it is directly accessible and has low systemic exposure [164]. The analogs of TRH such as taltirelin have good pharmacokinetics and enhance receptor affinity. The neuronal activation is enhanced, and new possibilities for the pharmaceutical use of taltirelin for OB APA have been shown [165]. AAV vectors expressing TRH-related peptides were transfected into the brain, and the expression and secretion of peptides in the CNS were increased, and the problems related to effective and targeted delivery were solved [166]. TRH can activate the PI3K/AKT signaling pathway for neuroprotection. Therefore, accurate administration of TRH is necessary for neuroprotective agents [28]. TRH is an important neuropeptide with a wide range of physiological activities. Many advances have been made in the development of TRH analogs and means of enhancing the blood–brain barrier permeability and resisting degradation, which enhance the neuroprotective effect by improving therapeutic efficacy and maintaining therapeutic time. Therefore, TRH is expected to play a more important role in amplifying therapeutic efficacy and reducing side effects by developing selective TRH analogs involving β-arrestin2 in TRH receptor signaling [167]. The recent progress in administering TRH via the intranasal biodegradable nanoparticles system has enhanced its safety and bioavailability within the CNS. The new TRH-based therapy for neurodegenerative and neuropsychiatric disorders will be realized based on the ongoing investigations in the delivery system and TRH receptor signaling.
Search strategies for therapeutic approaches against neurodegenerative disorders are increasingly embracing the concept of combinatorial therapies. However, THs are not able to resolve the neuropsychiatric or cognitive impairments present in hypothyroidism or NDDs [20,104]. Magnesium threonate (MgT) readily crosses the blood–brain barrier, increases brain magnesium content, and exhibits neuroprotective properties in AD through the reduction in Ab accumulation and increase in BDNF levels [104]. MgT reduces Ab concentrations in hypothyroid models lacking TH, suggesting that it may improve the efficacy of combination therapy with THs [104]. The use of combined treatment strategies combining THs and MgT may provide neuroprotective advantages owing to their respective hormonal and neuroprotective deficiencies, as well as those resulting from neuroinflammation. Furthermore, TRH has been shown to be effective against glutamate-induced neurotoxicity and may also provide neuroprotective advantages when combined with THs [28,160]. Combinations of THs and agents such as MgT or TRH analogs hold promise for the treatment of NDDs; however, the pharmacokinetics and interactions of these substances should be carefully investigated to ensure treatment safety and efficacy. Future clinical trials targeting TH treatments for NDDs should utilize advanced study designs that take into account the complexities of these diseases, and participants should be stratified according to thyroid function, genetics, and other relevant biomarkers [20,168]. Precision medicine strategies using omics approaches can help identify patients who may benefit from TH treatments or other integrative therapies involving neuroprotective agents, such as magnesium L-threonate or TRH analogs [168,169]. Neuroimaging and thyroid–liver axis-related biomarkers, which reflect the complex regulatory network involved in TH metabolism and systemic homeostasis, can provide more accurate therapeutic evaluations and assessments of disease progression [168,169]. Novel drug formulations, such as intranasal administration of TRH analogs, may enhance therapeutic efficacy by addressing issues related to blood–brain barrier permeability and agent degradation [160]. The design of trials should include assessments of cognitive, motor, and neuropsychiatric parameters, as well as the use of biomarkers for evaluating treatments. Furthermore, adaptive approaches may facilitate the rapid identification of effective therapies. The synthesis of knowledge regarding TH and neuroprotective approaches may eventually lead to personalized treatments for NDDs.
7.2. Comprehensive Strategies to Improve TRH Delivery Systems, Including Targeted Delivery and Safety Considerations
In conclusion, the clinical efficacy of TRH and its analogs depends on the effectiveness of the delivery system, and the core challenge is overcoming biological barriers to achieve effective delivery to the target site (Table S1). The enhancement strategies mainly include: overcoming the blood–brain barrier through chemical modification or RNA interference to enhance delivery to the CNS [155,170]; achieving direct and sustained drug delivery to the brain through local implantation [171]; utilizing nanocarriers to improve the physicochemical properties and pharmacokinetics of drugs for controlled release [163], and improving oral bioavailability via formulation design [172]. However, safety evaluation is crucial, and any delivery system must be rigorously evaluated for long-term safety [173]. In the future, it is necessary to combine multiple strategies to improve delivery efficiency while deeply understanding the therapeutic mechanisms and ensuring safety to maximize the clinical potential of TRH.
8. Conclusions
Thyroid hormones (THs) are essential for normal development of the nervous system and have also been demonstrated to be intimately involved in the pathology of neurodegenerative disorders. The level of active TH T3/FT3 is reduced, and this hormone plays an important role in the pathophysiology and clinical progression of PD [146,174]. Monitoring these hormone levels is useful for assessing patients’ prognosis. Future treatment strategies may include developing TH analogs specific to the CNS [175], regulating hormone pathways in specific populations (such as RTHβ patients) [176], and targeting downstream pathogenic pathways related to TH (such as oxidative stress) [177]. Thyroid hormone analogs have entered clinical applications, such as Resmetirom, which has been approved for the treatment of MASH, providing a precedent for neurological applications [175]. Treatments for genetic disorders, such as Triac, have shown benefits in RTHβ patients, demonstrating the feasibility of targeting abnormal pathways to treat neurological symptoms [175,176]. Basic research has revealed new targets, such as YOD1, which exacerbate dopamine neuron damage via the PKM2-Nrf2 axis, potentially providing neuroprotective strategies for PD [177]. However, several unresolved issues remain: the specific mechanisms of thyroid hormone neurotoxicity, particularly the interactions of THRP with proteins like c-Abl, are still unclear [146]; differences in sensitivity to hormonal fluctuations among different populations pose challenges for personalized treatment [174]; and there is a lack of systematic research on how to integrate upstream hormone regulation with downstream pathway therapies. Several limitations also exist: most evidence comes from observational studies [174], making it difficult to establish causality; some findings, such as specific gene mutations, are based solely on case reports [176], requiring validation of their generalizability; many targets and mechanisms are derived from model studies, necessitating experimental evaluation for clinical translation [177]; and the development of centrally selective analogs faces challenges in delivery and tissue selectivity.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/brainsci16020229/s1, Table S1: TH-related therapeutic agents and their applications in NDDs.
Author Contributions
X.L. and Z.L. designed and wrote the draft, M.S., Y.D. and H.B. prepared figures; X.C. extensively edited the manuscript, J.W. conceptualize and edit the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
Data sharing not applicable to this article as no datasets were generated or analyzed during the current study.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Okabe, N.; Goto, K. Physicochemical properties of 57 kDa thyroid hormone binding protein from rat liver nuclei. J. Biochem. 1989, 106, 1064–1067. [Google Scholar] [CrossRef] [Scilit]
- McKinney, J.D.; Waller, C.L. Polychlorinated biphenyls as hormonally active structural analogues. Environ. Health Perspect. 1994, 102, 290–297. [Google Scholar] [CrossRef] [Scilit]
- Mazák, K.; Noszál, B. Physicochemical Properties of Zwitterionic Drugs in Therapy. ChemMedChem 2020, 15, 1102–1110. [Google Scholar] [CrossRef] [Scilit]
- Dietrich, S.W.; Bolger, M.B.; Kollman, P.A.; Jorgensen, E.C. Thyroxine analogues. 23. Quantitative structure-activity correlation studies of in vivo and in vitro thyromimetic activities. J. Med. Chem. 1977, 20, 863–880. [Google Scholar] [CrossRef] [Scilit]
- Fame, R.M.; Ali, I.; Lehtinen, M.K.; Kanarek, N.; Petrova, B. Optimized Mass Spectrometry Detection of Thyroid Hormones and Polar Metabolites in Rodent Cerebrospinal Fluid. Metabolites 2024, 14, 79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Filfilan, W.M. Thyroid Hormones Regulate the Thermoregulatory Mechanisms of the Body: Review. Pak. J. Biol. Sci. 2023, 26, 453–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, X.; Zhang, H.; Guan, S.; Zhao, Q.; Shan, Y. Receptor modulators associated with the hypothalamus -pituitary-thyroid axis. Front. Pharmacol. 2023, 14, 1291856. [Google Scholar] [CrossRef] [Scilit]
- Friesema, E.C.; Visser, T.J.; Borgers, A.J.; Kalsbeek, A.; Swaab, D.F.; Fliers, E.; Alkemade, A. Thyroid hormone transporters and deiodinases in the developing human hypothalamus. Eur. J. Endocrinol. 2012, 167, 379–386. [Google Scholar] [CrossRef] [Scilit]
- Groeneweg, S.; Peeters, R.P.; Visser, T.J.; Visser, W.E. Therapeutic applications of thyroid hormone analogues in resistance to thyroid hormone (RTH) syndromes. Mol. Cell. Endocrinol. 2017, 458, 82–90. [Google Scholar] [CrossRef] [Scilit]
- Bianco, A.C.; Dumitrescu, A.; Gereben, B.; Ribeiro, M.O.; Fonseca, T.L.; Fernandes, G.W.; Bocco, B. Paradigms of Dynamic Control of Thyroid Hormone Signaling. Endocr. Rev. 2019, 40, 1000–1047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, T.K.T.; Townsend, L.K.; Smiles, W.J.; Oakhill, J.S.; Fullerton, M.D.; Steinberg, G.R. AMPK at the interface of nutrient sensing, metabolic flux and energy homeostasis. Nat. Metab. 2026, 8, 27–51. [Google Scholar] [CrossRef] [Scilit]
- Sheng, Z.; Luo, Q.; Liu, X.; Yang, X. Bioactives and exercise synergize to modulate AMPK and inflammation. Front. Immunol. 2025, 16, 1670379. [Google Scholar] [CrossRef] [Scilit]
- Wang, W.; Zhu, H.; Jiang, Q.; Shi, Y.; Wang, X. FOXO: A key target in regulating aging and age-related diseases. Biogerontology 2026, 27, 38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forrest, D. The erbA/thyroid hormone receptor genes in development of the central nervous system. Semin. Cancer Biol. 1994, 5, 167–176. [Google Scholar] [PubMed]
- Mendoza, A.; Hollenberg, A.N. New insights into thyroid hormone action. Pharmacol. Ther. 2017, 173, 135–145. [Google Scholar] [CrossRef] [Scilit]
- Saponaro, F.; Sestito, S.; Runfola, M.; Rapposelli, S.; Chiellini, G. Selective Thyroid Hormone Receptor-Beta (TRβ) Agonists: New Perspectives for the Treatment of Metabolic and Neurodegenerative Disorders. Front. Med. 2020, 7, 331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hartley, M.D.; Kirkemo, L.L.; Banerji, T.; Scanlan, T.S. A Thyroid Hormone-Based Strategy for Correcting the Biochemical Abnormality in X-Linked Adrenoleukodystrophy. Endocrinology 2017, 158, 1328–1338. [Google Scholar] [CrossRef] [Scilit]
- Duncan, I.D.; Vivian, J.A.; August, B.K.; Keuler, N.S.; Komro, A.; Radecki, D.; Kiland, J.A.; Gandhi, R.; Reilly, M.; Cameron, S.; et al. Promotion of remyelination by a thyromimetic drug leading to functional recovery. Exp. Neurol. 2025, 389, 115227. [Google Scholar] [CrossRef] [Scilit]
- Głombik, K.; Detka, J.; Budziszewska, B. Hormonal Regulation of Oxidative Phosphorylation in the Brain in Health and Disease. Cells 2021, 10, 2937. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Hao, M.; Li, Y.; Cheng, K.; Zhang, C. The Role of Thyroid Hormones in Neurodegenerative Disorders: Opportunities and Challenges. Mol. Neurobiol. 2025, 63, 217. [Google Scholar] [CrossRef] [Scilit]
- Zorrilla Veloz, R.I.; McKenzie, T.; Palacios, B.E.; Hu, J. Nuclear hormone receptors in demyelinating diseases. J. Neuroendocrinol. 2022, 34, e13171. [Google Scholar] [CrossRef] [Scilit]
- Przybylak, M.; Grabowski, J.; Bidzan, L. Cognitive functions and thyroid hormones secretion disorders. Psychiatr. Pol. 2021, 55, 309–321. [Google Scholar] [CrossRef] [Scilit]
- Li, Z.; Liu, J. Thyroid dysfunction and Alzheimer’s disease, a vicious circle. Front. Endocrinol. 2024, 15, 1354372. [Google Scholar] [CrossRef] [Scilit]
- Mohammadi, S.; Dolatshahi, M.; Rahmani, F. Shedding light on thyroid hormone disorders and Parkinson disease pathology: Mechanisms and risk factors. J. Endocrinol. Investig. 2021, 44, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Ma, Y.; Erb, M.L.; Moore, D.J. Aging, cellular senescence and Parkinson’s disease. J. Park. Dis. 2025, 15, 239–254. [Google Scholar] [CrossRef] [Scilit]
- Chen, L.; Wang, C.; Qin, L.; Zhang, H. Parkinson’s disease and glucose metabolism impairment. Transl. Neurodegener. 2025, 14, 10. [Google Scholar] [CrossRef] [Scilit]
- Mark, J.R.; Tansey, M.G. Immune cell metabolic dysfunction in Parkinson’s disease. Mol. Neurodegener. 2025, 20, 36. [Google Scholar] [CrossRef] [Scilit]
- Dong, Y.; Watson, D.J. Thyrotropin-releasing hormone protects hippocampal neurons against glutamate toxicity via phosphatidylinositol 3-kinase/AKT pathway and new protein synthesis. bioRxiv 2025. [Google Scholar] [CrossRef] [Scilit]
- Graceffo, E.; Opitz, R.; Megges, M.; Krude, H.; Schuelke, M. RNA Sequencing Reveals a Strong Predominance of THRA Splicing Isoform 2 in the Developing and Adult Human Brain. Int. J. Mol. Sci. 2024, 25, 9883. [Google Scholar] [CrossRef] [Scilit]
- Alamara, D.O.; Sadeghi, L.; Dehghan, G. The relationship between thyroid deficiency and blood-based biomarkers of cognitive disorders. Neuro Endocrinol. Lett. 2023, 44, 216–222. [Google Scholar]
- Vancamp, P.; Le Blay, K.; Butruille, L.; Sébillot, A.; Boelen, A.; Demeneix, B.A.; Remaud, S. Developmental thyroid disruption permanently affects the neuroglial output in the murine subventricular zone. Stem Cell Rep. 2022, 17, 459–474. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Minakhina, S.; Bansal, S.; Zhang, A.; Brotherton, M.; Janodia, R.; De Oliveira, V.; Tadepalli, S.; Wondisford, F.E. A Direct Comparison of Thyroid Hormone Receptor Protein Levels in Mice Provides Unexpected Insights into Thyroid Hormone Action. Thyroid 2020, 30, 1193–1204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, Y.; Song, Z.; Huang, M.; Li, C.; Nong, C.; Jiang, T.; Li, Z.; Yi, Z. Elucidating thyroid hormone transport proteins disruption by nitrophenols through computational and spectroscopic analysis. Biophys. Chem. 2025, 320–321, 107415. [Google Scholar] [CrossRef] [Scilit]
- Rochtus, A.M.; Herijgers, D.; Jansen, K.; Decallonne, B. Antiseizure medications and thyroid hormone homeostasis: Literature review and practical recommendations. Epilepsia 2022, 63, 259–270. [Google Scholar] [CrossRef] [Scilit]
- Dong, X.; Dong, J.; Zhao, Y.; Guo, J.; Wang, Z.; Liu, M.; Zhang, Y.; Na, X. Effects of Long-Term In Vivo Exposure to Di-2-Ethylhexylphthalate on Thyroid Hormones and the TSH/TSHR Signaling Pathways in Wistar Rats. Int. J. Environ. Res. Public Health 2017, 14, 44. [Google Scholar] [CrossRef] [Scilit]
- Vincenzi, M.; Camilot, M.; Ferrarini, E.; Teofoli, F.; Venturi, G.; Gaudino, R.; Cavarzere, P.; De Marco, G.; Agretti, P.; Dimida, A.; et al. Identification of a novel pax8 gene sequence variant in four members of the same family: From congenital hypothyroidism with thyroid hypoplasia to mild subclinical hypothyroidism. BMC Endocr. Disord. 2014, 14, 69. [Google Scholar] [CrossRef] [Scilit]
- Ortiga-Carvalho, T.M.; Chiamolera, M.I.; Pazos-Moura, C.C.; Wondisford, F.E. Hypothalamus-Pituitary-Thyroid Axis. Compr. Physiol. 2016, 6, 1387–1428. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, X.; Cao, Y.; Jin, H.; Wang, X.; Zhang, L.; Zhang, Y.; Yu, Y.; Huang, Y.; Gao, Y.; Zhang, J. Hydrogen Sulfide Promotes Thyroid Hormone Synthesis and Secretion by Upregulating Sirtuin-1. Front. Pharmacol. 2022, 13, 838248. [Google Scholar] [CrossRef] [Scilit]
- Yu, J.; Shen, S.; Yan, Y.; Liu, L.; Luo, R.; Liu, S.; Wu, Y.; Li, Y.; Jiang, J.; Ying, H. Iodide Excess Inhibits Thyroid Hormone Synthesis Pathway Involving XBP1-Mediated Regulation. Nutrients 2023, 15, 887. [Google Scholar] [CrossRef] [Scilit]
- McLanahan, E.D.; Andersen, M.E.; Fisher, J.W. A biologically based dose-response model for dietary iodide and the hypothalamic-pituitary-thyroid axis in the adult rat: Evaluation of iodide deficiency. Toxicol. Sci. 2008, 102, 241–253. [Google Scholar] [CrossRef] [Scilit]
- Chartoumpekis, D.V.; Ziros, P.G.; Habeos, I.G.; Sykiotis, G.P. Emerging roles of Keap1/Nrf2 signaling in the thyroid gland and perspectives for bench-to-bedside translation. Free Radic. Biol. Med. 2022, 190, 276–283. [Google Scholar] [CrossRef] [Scilit]
- Köhrle, J. Selenium, Iodine and Iron-Essential Trace Elements for Thyroid Hormone Synthesis and Metabolism. Int. J. Mol. Sci. 2023, 24, 3393. [Google Scholar] [CrossRef] [Scilit]
- Sinha, R.A.; Bruinstroop, E.; Yen, P.M. Actions of thyroid hormones and thyromimetics on the liver. Nat. Rev. Gastroenterol. Hepatol. 2025, 22, 9–22. [Google Scholar] [CrossRef] [Scilit]
- Emrich, F.; Gomes, B.H.; Selvatici-Tolentino, L.; Lopes, R.A.; Secio-Silva, A.; Carvalho-Moreira, J.P.; Bittencourt-Silva, P.G.; Guarnieri, L.O.; Silva, A.B.P.; Drummond, L.R.; et al. Hypothyroidism alters the rhythmicity of the central clock, body temperature and metabolism: Evidence of Bmal1 transcriptional regulation by T3. J. Physiol. 2024, 602, 4865–4887. [Google Scholar] [CrossRef] [Scilit]
- Horn, S.; Heuer, H. Thyroid hormone action during brain development: More questions than answers. Mol. Cell. Endocrinol. 2010, 315, 19–26. [Google Scholar] [CrossRef] [Scilit]
- de Souza, J.S. Thyroid hormone biosynthesis and its role in brain development and maintenance. Adv. Protein Chem. Struct. Biol. 2024, 142, 329–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bunevicius, R. Thyroid disorders in mental patients. Curr. Opin. Psychiatry 2009, 22, 391–395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aranda, A. Thyroid Hormone Action by Genomic and Nongenomic Molecular Mechanisms. Methods Mol. Biol. 2025, 2876, 17–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tedeschi, L.; Vassalle, C.; Iervasi, G.; Sabatino, L. Main Factors Involved in Thyroid Hormone Action. Molecules 2021, 26, 7337. [Google Scholar] [CrossRef] [Scilit]
- Davis, P.J.; Leonard, J.L.; Davis, F.B. Mechanisms of nongenomic actions of thyroid hormone. Front. Neuroendocrinol. 2008, 29, 211–218. [Google Scholar] [CrossRef] [Scilit]
- Alcaide Martin, A.; Mayerl, S. Local Thyroid Hormone Action in Brain Development. Int. J. Mol. Sci. 2023, 24, 12352. [Google Scholar] [CrossRef] [Scilit]
- Valcárcel-Hernández, V.; López-Espíndola, D.; Guillén-Yunta, M.; García-Aldea, Á.; López de Toledo Soler, I.; Bárez-López, S.; Guadaño-Ferraz, A. Deficient thyroid hormone transport to the brain leads to impairments in axonal caliber and oligodendroglial development. Neurobiol. Dis. 2022, 162, 105567. [Google Scholar] [CrossRef] [Scilit]
- Niu, Y.; Zhu, M.; Dong, M.; Li, J.; Li, Y.; Xiong, Y.; Liu, P.; Qin, Z. Bisphenols disrupt thyroid hormone (TH) signaling in the brain and affect TH-dependent brain development in Xenopus laevis. Aquat. Toxicol. 2021, 237, 105902. [Google Scholar] [CrossRef] [Scilit]
- Dong, M.; Li, Y.; Zhu, M.; Li, J.; Qin, Z. Tetrabromobisphenol A Disturbs Brain Development in Both Thyroid Hormone-Dependent and -Independent Manners in Xenopus laevis. Molecules 2021, 27, 249. [Google Scholar] [CrossRef] [Scilit]
- Gilbert, M.E.; Hassan, I.; Wood, C.; O’Shaughnessy, K.L.; Spring, S.; Thomas, S.; Ford, J. Gestational Exposure to Perchlorate in the Rat: Thyroid Hormones in Fetal Thyroid Gland, Serum, and Brain. Toxicol. Sci. 2022, 188, 117–130. [Google Scholar] [CrossRef] [Scilit]
- Spirhanzlova, P.; Couderq, S.; Le Mével, S.; Leemans, M.; Krief, S.; Mughal, B.B.; Demeneix, B.A.; Fini, J.B. Short- and Long-Term Effects of Chlorpyrifos on Thyroid Hormone Axis and Brain Development in Xenopus laevis. Neuroendocrinology 2023, 113, 1298–1311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hochbaum, D.R.; Hulshof, L.; Urke, A.; Wang, W.; Dubinsky, A.C.; Farnsworth, H.C.; Hakim, R.; Lin, S.; Kleinberg, G.; Robertson, K.; et al. Thyroid hormone remodels cortex to coordinate body-wide metabolism and exploration. Cell 2024, 187, 5679–5697.e5623. [Google Scholar] [CrossRef] [Scilit]
- Hochbaum, D.R.; Dubinsky, A.C.; Farnsworth, H.C.; Hulshof, L.; Kleinberg, G.; Urke, A.; Wang, W.; Hakim, R.; Robertson, K.; Park, C.; et al. Thyroid hormone rewires cortical circuits to coordinate body-wide metabolism and exploratory drive. bioRxiv 2023. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flamant, F.; Richard, S. Thyroid Hormone Receptors Function in GABAergic Neurons During Development and in Adults. Endocrinology 2024, 165, bqae101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Madhusudhan, U.; M, K.; Singaravelu, V.; Ganji, V.; John, N.; Gaur, A. Brain-Derived Neurotrophic Factor-Mediated Cognitive Impairment in Hypothyroidism. Cureus 2022, 14, e23722. [Google Scholar] [CrossRef] [Scilit]
- Monko, T.R.; Tripp, E.H.; Burr, S.E.; Gunderson, K.N.; Lanier, L.M.; Georgieff, M.K.; Bastian, T.W. Cellular Iron Deficiency Disrupts Thyroid Hormone Regulated Gene Expression in Developing Hippocampal Neurons. J. Nutr. 2024, 154, 49–59. [Google Scholar] [CrossRef] [Scilit]
- Wasserman-Bartov, T.; Admati, I.; Lebenthal-Loinger, I.; Sharabany, J.; Lerer-Goldshtein, T.; Appelbaum, L. Tsh Induces Agrp1 Neuron Proliferation in Oatp1c1-Deficient Zebrafish. J. Neurosci. 2022, 42, 8214–8224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tambones, I.; le Maire, A. Structural Insights Into Thyroid Hormone Receptors. Endocrinology 2024, 166, bqae154. [Google Scholar] [CrossRef] [Scilit]
- Brtko, J. Thyroid hormone and thyroid hormone nuclear receptors: History and present state of art. Endocr. Regul. 2021, 55, 103–119. [Google Scholar] [CrossRef] [Scilit]
- Ritter, M.J.; Amano, I.; Hollenberg, A.N. Transcriptional Cofactors for Thyroid Hormone Receptors. Endocrinology 2025, 166, bqae164. [Google Scholar] [CrossRef] [Scilit]
- Del Prete, M.; Muratori, F.; Campi, I.; Di Sacco, G.; Vignati, F.; Pellegrino, D.; Persani, L. A rare mutation of thyroid hormone receptor beta gene in thyroid hormone resistance syndrome. Endocrinol. Diabetes Metab. Case Rep. 2021, 1, 1–5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamagami, K.; Kanamoto, N.; Yamashita, Y.; Sasai, Y.; Tagami, T. Novel Thyroid Hormone Receptor β Gene Variant (F245L) Causing Mild Resistance to Thyroid Hormone. JCEM Case Rep. 2025, 3, luaf267. [Google Scholar] [CrossRef] [Scilit]
- Cayrol, F.; Díaz Flaqué, M.C.; Fernando, T.; Yang, S.N.; Sterle, H.A.; Bolontrade, M.; Amorós, M.; Isse, B.; Farías, R.N.; Ahn, H.; et al. Integrin αvβ3 acting as membrane receptor for thyroid hormones mediates angiogenesis in malignant T cells. Blood 2015, 125, 841–851. [Google Scholar] [CrossRef] [Scilit]
- Ariyani, W.; Miyazaki, W.; Amano, I.; Koibuchi, N. Involvement of integrin αvβ3 in thyroid hormone-induced dendritogenesis. Front. Endocrinol. 2022, 13, 938596. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.; Sjölinder, M.; Wang, X.; Altenbacher, G.; Hagner, M.; Berglund, P.; Gao, Y.; Lu, T.; Jonsson, A.B.; Sjölinder, H. Thyroid hormone enhances nitric oxide-mediated bacterial clearance and promotes survival after meningococcal infection. PLoS ONE 2012, 7, e41445. [Google Scholar] [CrossRef] [Scilit]
- Selivanova, E.K.; Gaynullina, D.K.; Tarasova, O.S. Thyroxine Induces Acute Relaxation of Rat Skeletal Muscle Arteries via Integrin αvβ3, ERK1/2 and Integrin-Linked Kinase. Front. Physiol. 2021, 12, 726354. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, M.T.; Wang, L.M.; Changou, C.A.; Chin, Y.T.; Yang, Y.S.H.; Lai, H.Y.; Lee, S.Y.; Yang, Y.N.; Whang-Peng, J.; Liu, L.F.; et al. Crosstalk between integrin αvβ3 and ERα contributes to thyroid hormone-induced proliferation of ovarian cancer cells. Oncotarget 2017, 8, 24237–24249. [Google Scholar] [CrossRef] [Scilit]
- Tieman, K.; Heyland, A. Developmental effects of sulfated thyroid hormones in sea urchin skeletogenesis suggest activation of non-canonical thyroid hormone signaling pathway. Front. Endocrinol. 2025, 16, 1648899. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Liu, H.; Li, N.; Wang, J.; Song, L. TDCPP mimics thyroid hormones associated with the activation of integrin αvβ3 and ERK1/2. Chemosphere 2020, 256, 127066. [Google Scholar] [CrossRef] [Scilit]
- Xu, Y.; Yang, L.; Teng, Y.; Li, J.; Li, N. Exploring the underlying molecular mechanism of tri(1,3-dichloropropyl) phosphate-induced neurodevelopmental toxicity via thyroid hormone disruption in zebrafish by multi-omics analysis. Aquat. Toxicol. 2023, 258, 106510. [Google Scholar] [CrossRef] [Scilit]
- Kleinau, G.; Neumann, S.; Grüters, A.; Krude, H.; Biebermann, H. Novel insights on thyroid-stimulating hormone receptor signal transduction. Endocr. Rev. 2013, 34, 691–724. [Google Scholar] [CrossRef] [Scilit]
- Kleinau, G.; Worth, C.L.; Kreuchwig, A.; Biebermann, H.; Marcinkowski, P.; Scheerer, P.; Krause, G. Structural-Functional Features of the Thyrotropin Receptor: A Class A G-Protein-Coupled Receptor at Work. Front. Endocrinol. 2017, 8, 86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luan, S.; Bi, W.; Shi, S.; Peng, L.; Li, Z.; Jiang, J.; Gao, L.; Du, Y.; Hou, X.; He, Z.; et al. Thyrotropin receptor signaling deficiency impairs spatial learning and memory in mice. J. Endocrinol. 2020, 246, 41–55. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Luan, S.; Ruan, C.; Li, W.; Zhang, X.; Ran, Z.; Bi, W.; Tong, Y.; Gao, L.; Zhao, J.; et al. TSHR signaling promotes hippocampal dependent memory formation through modulating Wnt5a/β-catenin mediated neurogenesis. Biochem. Biophys. Res. Commun. 2024, 704, 149723. [Google Scholar] [CrossRef] [Scilit]
- Crilly, S.E.; Puthenveedu, M.A. Compartmentalized GPCR Signaling from Intracellular Membranes. J. Membr. Biol. 2021, 254, 259–271. [Google Scholar] [CrossRef] [Scilit]
- Ricci, G.; Volpi, L.; Pasquali, L.; Petrozzi, L.; Siciliano, G. Astrocyte-neuron interactions in neurological disorders. J. Biol. Phys. 2009, 35, 317–336. [Google Scholar] [CrossRef] [Scilit]
- Fellin, T.; Carmignoto, G. Neurone-to-astrocyte signalling in the brain represents a distinct multifunctional unit. J. Physiol. 2004, 559, 3–15. [Google Scholar] [CrossRef] [Scilit]
- Lindsey, R.C.; Godwin, C.; Mohan, S. Skeletal effects of nongenomic thyroid hormone receptor beta signaling. J. Endocrinol. 2019, 242, 173–183. [Google Scholar] [CrossRef] [Scilit]
- Barrera-Hernandez, G.; Zhan, Q.; Wong, R.; Cheng, S.Y. Thyroid hormone receptor is a negative regulator in p53-mediated signaling pathways. DNA Cell Biol. 1998, 17, 743–750. [Google Scholar] [CrossRef] [Scilit]
- Lin, K.H.; Chen, C.Y.; Chen, S.L.; Yen, C.C.; Huang, Y.H.; Shih, C.H.; Shen, J.J.; Yang, R.C.; Wang, C.S. Regulation of fibronectin by thyroid hormone receptors. J. Mol. Endocrinol. 2004, 33, 445–458. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.H.; Lee, H.S.; Kim, Y.H.; Kwon, M.J.; Kim, J.H.; Min, C.Y.; Yoo, D.M.; Choi, H.G. The Association Between Thyroid Diseases and Alzheimer’s Disease in a National Health Screening Cohort in Korea. Front. Endocrinol. 2022, 13, 815063. [Google Scholar] [CrossRef] [Scilit]
- Ye, J.; Huang, Z.; Liang, C.; Yun, Z.; Huang, L.; Liu, Y.; Luo, Z. Thyroid dysfunction and risk of different types of dementia: A systematic review and meta-analysis. Medicine 2024, 103, e39394. [Google Scholar] [CrossRef] [Scilit]
- Lopez, O.; Huff, F.J.; Martinez, A.J.; Bedetti, C.D. Prevalence of thyroid abnormalities is not increased in Alzheimer’s disease. Neurobiol. Aging 1989, 10, 247–251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoshimasu, F.; Kokmen, E.; Hay, I.D.; Beard, C.M.; Offord, K.P.; Kurland, L.T. The association between Alzheimer’s disease and thyroid disease in Rochester, Minnesota. Neurology 1991, 41, 1745–1747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quinlan, P.; Horvath, A.; Eckerström, C.; Wallin, A.; Svensson, J. Altered thyroid hormone profile in patients with Alzheimer’s disease. Psychoneuroendocrinology 2020, 121, 104844. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, B.W.; Kim, S.; Kang, S.; Won, K.S.; Yi, H.A.; Kim, H.W. Relationship Between Thyroid Hormone Levels and the Pathology of Alzheimer’s Disease in Euthyroid Subjects. Thyroid 2020, 30, 1547–1555. [Google Scholar] [CrossRef] [Scilit]
- Ge, F.; Dong, L.; Zhu, D.; Lin, X.; Shi, J.; Xiao, M. Comparison of Serum Triiodothyronine with Biomarkers for Alzheimer’s Disease Continuum in Euthyroid Subjects. J. Alzheimers Dis. 2022, 85, 605–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salehipour, A.; Dolatshahi, M.; Haghshomar, M.; Amin, J. The Role of Thyroid Dysfunction in Alzheimer’s Disease: A Systematic Review and Meta-Analysis. J. Prev. Alzheimers Dis. 2023, 10, 276–286. [Google Scholar] [CrossRef] [Scilit]
- Ge, F.; Song, B.; Wang, X.; Tian, M.; Lin, X.; Shi, J.; Ye, X. Association of thyroid autoimmune status with Alzheimer’s disease biomarkers in euthyroid subjects. J. Neuroimmunol. 2025, 409, 578780. [Google Scholar] [CrossRef] [Scilit]
- AlAnazi, F.H.; Al-Kuraishy, H.M.; Alexiou, A.; Papadakis, M.; Ashour, M.H.M.; Alnaaim, S.A.; Elhussieny, O.; Saad, H.M.; Batiha, G.E. Primary Hypothyroidism and Alzheimer’s Disease: A Tale of Two. Cell. Mol. Neurobiol. 2023, 43, 3405–3416. [Google Scholar] [CrossRef] [Scilit]
- Chaalal, A.; Poirier, R.; Blum, D.; Gillet, B.; Le Blanc, P.; Basquin, M.; Buée, L.; Laroche, S.; Enderlin, V. PTU-induced hypothyroidism in rats leads to several early neuropathological signs of Alzheimer’s disease in the hippocampus and spatial memory impairments. Hippocampus 2014, 24, 1381–1393. [Google Scholar] [CrossRef] [Scilit]
- Kim, D.K.; Choi, H.; Lee, W.; Choi, H.; Hong, S.B.; Jeong, J.H.; Han, J.; Han, J.W.; Ryu, H.; Kim, J.I.; et al. Brain hypothyroidism silences the immune response of microglia in Alzheimer’s disease animal model. Sci. Adv. 2024, 10, eadi1863. [Google Scholar] [CrossRef] [Scilit]
- Byeon, J.H.; Byun, M.S.; Yi, D.; Jung, J.H.; Sohn, B.K.; Chang, Y.Y.; Kong, N.; Jung, G.; Ahn, H.; Lee, J.Y.; et al. Moderation of thyroid hormones for the relationship between amyloid and tau pathology. Alzheimers Res. Ther. 2024, 16, 164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Accorroni, A.; Rutigliano, G.; Sabatini, M.; Frascarelli, S.; Borsò, M.; Novelli, E.; Bandini, L.; Ghelardoni, S.; Saba, A.; Zucchi, R.; et al. Exogenous 3-Iodothyronamine Rescues the Entorhinal Cortex from β-Amyloid Toxicity. Thyroid 2020, 30, 147–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tozzi, F.; Rutigliano, G.; Borsò, M.; Falcicchia, C.; Zucchi, R.; Origlia, N. T(1)AM-TAAR1 signalling protects against OGD-induced synaptic dysfunction in the entorhinal cortex. Neurobiol. Dis. 2021, 151, 105271. [Google Scholar] [CrossRef] [Scilit]
- Sepúlveda, P.; Ferreira, A.F.F.; Sandoval, C.; Bergoc, G.; Moreno, A.C.R.; Nunes, M.T.; Torrão, A.D.S. Thyroid Hormone Supplementation Restores Cognitive Deficit, Insulin Signaling, and Neuroinflammation in the Hippocampus of a Sporadic Alzheimer’s-like Disease Rat Model. Cells 2024, 13, 1793. [Google Scholar] [CrossRef] [Scilit]
- Escamilla, S.; Salas-Lucia, F. Thyroid Hormone and Alzheimer Disease: Bridging Epidemiology to Mechanism. Endocrinology 2024, 165, bqae124. [Google Scholar] [CrossRef] [Scilit]
- Bhuiyan, P.; Zhang, W.; Liang, G.; Jiang, B.; Vera, R.; Chae, R.; Kim, K.; Louis, L.S.; Wang, Y.; Liu, J.; et al. Intranasal Delivery of Lithium Salt Suppresses Inflammatory Pyroptosis in the Brain and Ameliorates Memory Loss and Depression-like Behavior in 5XFAD Mice. J. Neuroimmune Pharmacol. 2025, 20, 26. [Google Scholar] [CrossRef] [Scilit]
- Zhou, C.; You, J.; Guan, X.; Guo, T.; Wu, J.; Wu, H.; Wu, C.; Chen, J.; Wen, J.; Tan, S.; et al. Microstructural alterations of the hypothalamus in Parkinson’s disease and probable REM sleep behavior disorder. Neurobiol. Dis. 2024, 194, 106472. [Google Scholar] [CrossRef] [Scilit]
- Peng, Y.; Zhu, L.; Bai, Q.; Wang, L.; Li, Q. Associations between Thyroid Hormones and Cognitive Impairment in Patients with Parkinson’s Disease. eNeuro 2024, 11, ENEURO.0239-24.2024. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.H.; Lee, H.S.; Ahn, J.H.; Oh, J.K.; Chang, I.B.; Song, J.H.; Wee, J.H.; Min, C.Y.; Yoo, D.M.; Choi, H.G. Association Between Thyroid Diseases and Parkinson’s Disease: A Nested Case-Control Study Using a National Health Screening Cohort. J. Parkinsons Dis. 2021, 11, 211–220. [Google Scholar] [CrossRef] [Scilit]
- Gabaldon-Albero, A.; Mayo, S.; Martinez, F. NR4A2 as a Novel Target Gene for Developmental and Epileptic Encephalopathy: A Systematic Review of Related Disorders and Therapeutic Strategies. Int. J. Mol. Sci. 2024, 25, 5198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, M.; Wu, T.; Chen, N. Bridging neurotrophic factors and bioactive peptides to Alzheimer’s disease. Ageing Res. Rev. 2024, 94, 102177. [Google Scholar] [CrossRef] [Scilit]
- Schneider, S.A.; Tschaidse, L.; Reisch, N. Thyroid Disorders and Movement Disorders-A Systematic Review. Mov. Disord. Clin. Pract. 2023, 10, 360–368. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miyamoto, K.; Saiki, S.; Matsumoto, H.; Suzuki, A.; Yamashita, Y.; Iseki, T.; Ueno, S.I.; Shiina, K.; Kataura, T.; Kamagata, K.; et al. Systemic Metabolic Alteration Dependent on the Thyroid-Liver Axis in Early PD. Ann. Neurol. 2023, 93, 303–316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saiki, S. Association of Pathological Progression of Parkinson’s Disease and the Thyroid Gland. Brain Nerve 2023, 75, 965–970. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rozo-Paz, G.; Ruiz-Forero, C.M.; Suárez-Mera, J.D.; Monsalve Duarte, G.; Kattah Calderón, W. Levodopa induces thyroid function regulation in a patient with thyroid hormone resistance and Parkinson’s disease: A case report. Front. Endocrinol. 2025, 16, 1536372. [Google Scholar] [CrossRef] [Scilit]
- Zeng, Y.; Cao, S.; Yang, H. No causal relationship between thyroid function and Parkinson’s disease: A bidirectional Mendelian randomization study. Neurol. Sci. 2024, 45, 1481–1487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kondo, Y.; Ozawa, A.; Kohno, D.; Saito, K.; Buyandalai, B.; Yamada, S.; Horiguchi, K.; Nakajima, Y.; Shibusawa, N.; Harada, A.; et al. The Hypothalamic Paraventricular Nucleus Is the Center of the Hypothalamic-Pituitary-Thyroid Axis for Regulating Thyroid Hormone Levels. Thyroidr 2022, 32, 105–114. [Google Scholar] [CrossRef] [Scilit]
- Daimon, C.M.; Chirdon, P.; Maudsley, S.; Martin, B. The role of Thyrotropin Releasing Hormone in aging and neurodegenerative diseases. Am. J. Alzheimers Dis. 2013, 1, 29–59. [Google Scholar] [CrossRef] [Scilit]
- Meisenberg, G.; Simmons, W.H. Minireview. Peptides and the blood-brain barrier. Life Sci. 1983, 32, 2611–2623. [Google Scholar] [CrossRef] [Scilit]
- Xiang, W.; Chao, Z.Y.; Feng, D.Y. Role of Toll-like receptor/MYD88 signaling in neurodegenerative diseases. Rev. Neurosci. 2015, 26, 407–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ryskamp, D.A.; Korban, S.; Zhemkov, V.; Kraskovskaya, N.; Bezprozvanny, I. Neuronal Sigma-1 Receptors: Signaling Functions and Protective Roles in Neurodegenerative Diseases. Front. Neurosci. 2019, 13, 862. [Google Scholar] [CrossRef] [Scilit]
- Valcarcel-Hernandez, V.; Butruille, L.; Remaud, S. Effects of thyroid disruption on neural cells stem fate in the mouse brain. Presse Med. 2025, 54, 104312. [Google Scholar] [CrossRef] [Scilit]
- Butruille, L.; Vancamp, P.; Demeneix, B.A.; Remaud, S. Thyroid hormone regulation of adult neural stem cell fate: A comparative analysis between rodents and primates. Vitam. Horm. 2021, 116, 133–192. [Google Scholar] [CrossRef] [Scilit]
- Vujovic, F.; Farahani, R.M. Thyroid Hormones and Brain Development: A Focus on the Role of Mitochondria as Regulators of Developmental Time. Cells 2025, 14, 150. [Google Scholar] [CrossRef] [Scilit]
- Cordero-Véliz, C.; Larraín, J.; Faunes, F. Transcriptome analysis of the response to thyroid hormone in Xenopus neural stem and progenitor cells. Dev. Dyn. 2023, 252, 294–304. [Google Scholar] [CrossRef] [Scilit]
- Vancamp, P.; Butruille, L.; Demeneix, B.A.; Remaud, S. Thyroid Hormone and Neural Stem Cells: Repair Potential Following Brain and Spinal Cord Injury. Front. Neurosci. 2020, 14, 875. [Google Scholar] [CrossRef] [Scilit]
- Lin, C.; Li, N.; Chang, H.; Shen, Y.; Li, Z.; Wei, W.; Chen, H.; Lu, H.; Ji, J.; Liu, N. Dual effects of thyroid hormone on neurons and neurogenesis in traumatic brain injury. Cell Death Dis. 2020, 11, 671. [Google Scholar] [CrossRef] [Scilit]
- Valcárcel-Hernández, V.; Vancamp, P.; Butruille, L.; Remaud, S.; Guadaño-Ferraz, A. Combined deletion of Mct8 and Dio2 impairs SVZ neurogliogenesis and olfactory function in adult mice. Neurobiol. Dis. 2024, 199, 106572. [Google Scholar] [CrossRef] [Scilit]
- Luongo, C.; Butruille, L.; Sébillot, A.; Le Blay, K.; Schwaninger, M.; Heuer, H.; Demeneix, B.A.; Remaud, S. Absence of Both Thyroid Hormone Transporters MCT8 and OATP1C1 Impairs Neural Stem Cell Fate in the Adult Mouse Subventricular Zone. Stem Cell Rep. 2021, 16, 337–353. [Google Scholar] [CrossRef] [Scilit]
- Butruille, L.; Jubin, P.; Martin, E.; Aigrot, M.S.; Lhomme, M.; Fini, J.B.; Demeneix, B.; Stankoff, B.; Lubetzki, C.; Zalc, B.; et al. Deleterious functional consequences of perfluoroalkyl substances accumulation into the myelin sheath. Environ. Int. 2023, 180, 108211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vancamp, P.; Spirhanzlova, P.; Sébillot, A.; Butruille, L.; Gothié, J.D.; Le Mével, S.; Leemans, M.; Wejaphikul, K.; Meima, M.; Mughal, B.B.; et al. The pyriproxyfen metabolite, 4′-OH-PPF, disrupts thyroid hormone signaling in neural stem cells, modifying neurodevelopmental genes affected by ZIKA virus infection. Environ. Pollut. 2021, 285, 117654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moore, A.; Chinnaiya, K.; Kim, D.W.; Brown, S.; Stewart, I.; Robins, S.; Dowsett, G.K.C.; Muir, C.; Travaglio, M.; Lewis, J.E.; et al. Loss of Function of the Neural Cell Adhesion Molecule NrCAM Regulates Differentiation, Proliferation and Neurogenesis in Early Postnatal Hypothalamic Tanycytes. Front. Neurosci. 2022, 16, 832961. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, M.Y.; Yang, X.L.; Chung, C.C.; Lai, Y.J.; Tsai, J.C.; Kuo, Y.L.; Yu, J.Y.; Wang, T.W. TRIP6 promotes neural stem cell maintenance through YAP-mediated Sonic Hedgehog activation. FASEB J. 2024, 38, e23501. [Google Scholar] [CrossRef] [Scilit]
- Baldassarro, V.A.; Quadalti, C.; Runfola, M.; Manera, C.; Rapposelli, S.; Calzà, L. Synthetic Thyroid Hormone Receptor-β Agonists Promote Oligodendrocyte Precursor Cell Differentiation in the Presence of Inflammatory Challenges. Pharmaceuticals 2023, 16, 1207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Graffunder, A.S.; Bresser, A.A.J.; Fernandez Vallone, V.; Megges, M.; Stachelscheid, H.; Kühnen, P.; Opitz, R. Spatiotemporal expression of thyroid hormone transporter MCT8 and THRA mRNA in human cerebral organoids recapitulating first trimester cortex development. Sci. Rep. 2024, 14, 9355. [Google Scholar] [CrossRef] [Scilit]
- McDermott, M.T. Hypothyroidism. Ann. Intern. Med. 2020, 173, Itc1–Itc16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barranco, H.; Fazendin, J.; Lindeman, B.; Chen, H.; Ramonell, K.M. Thyroid hormone replacement following lobectomy: Long-term institutional analysis 15 years after surgery. Surgery 2023, 173, 189–192. [Google Scholar] [CrossRef] [Scilit]
- Mazza, A.D. Personalized Approaches to Hypothyroidism: The Role of Triiodothyronine (T3) in Thyroid Hormone Replacement. Cureus 2025, 17, e90685. [Google Scholar] [CrossRef] [Scilit]
- Akkaya, E.C.; Ilgin, R.; Adil, H.; Çelik, A. Magnesium L-Threonate Reduces Hippocampal Amyloid-β Load without Cognitive Improvement in a PTU-induced Hypothyroidism Model in Young Rats. Mol. Neurobiol. 2025, 63, 8. [Google Scholar] [CrossRef] [Scilit]
- Wolff, T.M.; Dietrich, J.W.; Müller, M.A. Optimal Hormone Replacement Therapy in Hypothyroidism—A Model Predictive Control Approach. Front. Endocrinol. 2022, 13, 884018. [Google Scholar] [CrossRef] [Scilit]
- Wilson, J.B.; Hoang, T.D.; Lee, M.L.; Epstein, M.; Friedman, T.C. Reverse T3 in patients with hypothyroidism on different thyroid hormone replacement. PLoS ONE 2025, 20, e0325046. [Google Scholar] [CrossRef] [Scilit]
- Azizi, F.; Amouzegar, A.; Mehran, L.; Abdi, H. LT4 and Slow Release T3 Combination: Optimum Therapy for Hypothyroidism? Int. J. Endocrinol. Metab. 2020, 18, e100870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rossi, L.; Paternoster, M.; Cammarata, M.; Bakkar, S.; Miccoli, P. Levothyroxine therapy in thyroidectomized patients: Ongoing challenges and controversies. Front. Endocrinol. 2025, 16, 1582734. [Google Scholar] [CrossRef] [Scilit]
- Efthymiadis, A.; Henry, M.; Spinos, D.; Bourlaki, M.; Tsikopoulos, A.; Bourazana, A.; Bastounis, A.; Tsikopoulos, K. Adequacy of thyroid hormone replacement for people with hypothyroidism in real-world settings: A systematic review and meta-analysis of observational studies. Clin. Endocrinol. 2024, 100, 488–501. [Google Scholar] [CrossRef] [Scilit]
- Peng, C.C.; Maraka, S.; Pearce, E.N. Under and overtreatment with thyroid hormone replacement during pregnancy. Curr. Opin. Endocrinol. Diabetes Obes. 2022, 29, 474–482. [Google Scholar] [CrossRef] [Scilit]
- Kanazawa, K.; Inaba, T.; Koga, S.; Kuwabara, K. Clinical insights of pregnancy management, adrenal insufficiency as a possible cause of elevated TSH: A pilot study of case series. BMC Pregnancy Childbirth 2023, 23, 711. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Long, H.; Zhang, P.; Liu, B.; Li, S.; Sun, R.; Diao, T.; Li, F. Development and characterization of a novel injectable thyroid extracellular matrix hydrogel for enhanced thyroid tissue engineering applications. Front. Bioeng. Biotechnol. 2024, 12, 1481295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heim, M.; Nixon, I.J.; Emmerson, E.; Callanan, A. From hormone replacement therapy to regenerative scaffolds: A review of current and novel primary hypothyroidism therapeutics. Front. Endocrinol. 2022, 13, 997288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mooradian, A.D.; Haas, M.J. Role of Thyroid Hormone in Neurodegenerative Disorders of Older People. Cells 2025, 14, 140. [Google Scholar] [CrossRef] [Scilit]
- Baksi, S.; Pradhan, A. Thyroid hormone: Sex-dependent role in nervous system regulation and disease. Biol. Sex. Differ. 2021, 12, 25. [Google Scholar] [CrossRef] [Scilit]
- Gopinath, A.; Mackie, P.; Hashimi, B.; Buchanan, A.M.; Smith, A.R.; Bouchard, R.; Shaw, G.; Badov, M.; Saadatpour, L.; Gittis, A.; et al. DAT and TH expression marks human Parkinson’s disease in peripheral immune cells. npj Park. Dis. 2022, 8, 72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, S.S.; Wu, Z.; Liu, X.; Edgington-Mitchell, L.; Ye, K. Treating Parkinson’s Disease via Activation of BDNF/TrkB Signaling Pathways and Inhibition of Delta-Secretase. Neurotherapeutics 2022, 19, 1283–1297. [Google Scholar] [CrossRef] [Scilit]
- Emamnejad, R.; Pagnin, M.; Petratos, S. The iron maiden: Oligodendroglial metabolic dysfunction in multiple sclerosis and mitochondrial signaling. Neurosci. Biobehav. Rev. 2024, 164, 105788. [Google Scholar] [CrossRef] [Scilit]
- Kanazawa, T.; Sato, W.; Raveney, B.J.E.; Takewaki, D.; Kimura, A.; Yamaguchi, H.; Yokoi, Y.; Saika, R.; Takahashi, Y.; Fujita, T.; et al. Pathogenic Potential of Eomesodermin-Expressing T-Helper Cells in Neurodegenerative Diseases. Ann. Neurol. 2024, 95, 1093–1098. [Google Scholar] [CrossRef] [Scilit]
- Zhang, M.; Ma, Z.; Qin, H.; Yao, Z. Thyroid Hormone Potentially Benefits Multiple Sclerosis via Facilitating Remyelination. Mol. Neurobiol. 2016, 53, 4406–4416. [Google Scholar] [CrossRef] [Scilit]
- Hartley, M.D.; Banerji, T.; Tagge, I.J.; Kirkemo, L.L.; Chaudhary, P.; Calkins, E.; Galipeau, D.; Shokat, M.D.; DeBell, M.J.; Van Leuven, S.; et al. Myelin repair stimulated by CNS-selective thyroid hormone action. JCI Insight 2019, 4, e126329. [Google Scholar] [CrossRef] [Scilit]
- Dell’Acqua, M.L.; Lorenzini, L.; D’Intino, G.; Sivilia, S.; Pasqualetti, P.; Panetta, V.; Paradisi, M.; Filippi, M.M.; Baiguera, C.; Pizzi, M.; et al. Functional and molecular evidence of myelin- and neuroprotection by thyroid hormone administration in experimental allergic encephalomyelitis. Neuropathol. Appl. Neurobiol. 2012, 38, 454–470. [Google Scholar] [CrossRef] [Scilit]
- Francelle, L.; Galvan, L.; Gaillard, M.C.; Guillermier, M.; Houitte, D.; Bonvento, G.; Petit, F.; Jan, C.; Dufour, N.; Hantraye, P.; et al. Loss of the thyroid hormone-binding protein Crym renders striatal neurons more vulnerable to mutant huntingtin in Huntington’s disease. Hum. Mol. Genet. 2015, 24, 1563–1573. [Google Scholar] [CrossRef] [Scilit]
- Aurich, M.; Schliebs, R.; Stewart, M.G.; Rudolph, E.; Fischer, H.D.; Bigl, V. Adaptive changes in the central noradrenergic system in monocular deprived rats. Brain Res. Bull. 1989, 22, 173–180. [Google Scholar] [CrossRef] [Scilit]
- Marziali, L.N.; Garcia, C.I.; Pasquini, J.M. Transferrin and thyroid hormone converge in the control of myelinogenesis. Exp. Neurol. 2015, 265, 129–141. [Google Scholar] [CrossRef] [Scilit]
- Bernal, J. Thyroid hormones and brain development. Vitam. Horm. 2005, 71, 95–122. [Google Scholar] [CrossRef] [Scilit]
- Vose, L.R.; Vinukonda, G.; Jo, S.; Miry, O.; Diamond, D.; Korumilli, R.; Arshad, A.; Zia, M.T.; Hu, F.; Kayton, R.J.; et al. Treatment with thyroxine restores myelination and clinical recovery after intraventricular hemorrhage. J. Neurosci. 2013, 33, 17232–17246. [Google Scholar] [CrossRef] [Scilit]
- Farías-Serratos, B.M.; Lazcano, I.; Villalobos, P.; Darras, V.M.; Orozco, A. Thyroid hormone deficiency during zebrafish development impairs central nervous system myelination. PLoS ONE 2021, 16, e0256207. [Google Scholar] [CrossRef] [Scilit]
- Fernandez, M.; Giuliani, A.; Pirondi, S.; D’Intino, G.; Giardino, L.; Aloe, L.; Levi-Montalcini, R.; Calzà, L. Thyroid hormone administration enhances remyelination in chronic demyelinating inflammatory disease. Proc. Natl. Acad. Sci. USA 2004, 101, 16363–16368. [Google Scholar] [CrossRef] [Scilit]
- Franco, P.G.; Silvestroff, L.; Soto, E.F.; Pasquini, J.M. Thyroid hormones promote differentiation of oligodendrocyte progenitor cells and improve remyelination after cuprizone-induced demyelination. Exp. Neurol. 2008, 212, 458–467. [Google Scholar] [CrossRef] [Scilit]
- D’Intino, G.; Lorenzini, L.; Fernandez, M.; Taglioni, A.; Perretta, G.; Del Vecchio, G.; Villoslada, P.; Giardino, L.; Calzà, L. Triiodothyronine administration ameliorates the demyelination/remyelination ratio in a non-human primate model of multiple sclerosis by correcting tissue hypothyroidism. J. Neuroendocrinol. 2011, 23, 778–790. [Google Scholar] [CrossRef] [Scilit]
- Brenta, G.; Danzi, S.; Klein, I. Potential therapeutic applications of thyroid hormone analogs. Nat. Clin. Pract. Endocrinol. Metab. 2007, 3, 632–640. [Google Scholar] [CrossRef] [Scilit]
- Emamnejad, R.; Dass, M.; Mahlis, M.; Bozkurt, S.; Ye, S.; Pagnin, M.; Theotokis, P.; Grigoriadis, N.; Petratos, S. Thyroid hormone-dependent oligodendroglial cell lineage genomic and non-genomic signaling through integrin receptors. Front. Pharmacol. 2022, 13, 934971. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, S.J.; Chaudhary, P.; DeBell, M.J.; Marracci, G.; Miller, H.; Calkins, E.; Pocius, E.; Napier, B.A.; Emery, B.; Bourdette, D.; et al. TREM2 is thyroid hormone regulated making the TREM2 pathway druggable with ligands for thyroid hormone receptor. Cell Chem. Biol. 2022, 29, 239–248.e234. [Google Scholar] [CrossRef] [Scilit]
- Bongert, M.; Schönauer, E.; Trendelenburg, P.; Ceylan, U.; Ladopoulos, T.; Vohl, K.; Bratek, D.; Mattukat, A.; Beyer, L.; Gerwert, K.; et al. Eomesodermin-expressing CD4 Th cells and association with multiple sclerosis progression and brain atrophy. Brain Commun. 2025, 7, fcaf415. [Google Scholar] [CrossRef] [Scilit]
- Mezzaroba, L.; Alfieri, D.F.; Colado Simão, A.N.; Vissoci Reiche, E.M. The role of zinc, copper, manganese and iron in neurodegenerative diseases. Neurotoxicology 2019, 74, 230–241. [Google Scholar] [CrossRef] [Scilit]
- Zucchi, R. Thyroid Hormone Analogues: An Update. Thyroid 2020, 30, 1099–1105. [Google Scholar] [CrossRef] [Scilit]
- Kim, M.J.; Petratos, S. Oligodendroglial Lineage Cells in Thyroid Hormone-Deprived Conditions. Stem Cells Int. 2019, 2019, 5496891. [Google Scholar] [CrossRef] [Scilit]
- Singh, B.K.; Sinha, R.A.; Ohba, K.; Yen, P.M. Role of thyroid hormone in hepatic gene regulation, chromatin remodeling, and autophagy. Mol. Cell. Endocrinol. 2017, 458, 160–168. [Google Scholar] [CrossRef] [Scilit]
- Al-Suhaimi, E.; AlQuwaie, R.; AlSaqabi, R.; Winarni, D.; Dewi, F.R.P.; AlRubaish, A.A.; Shehzad, A.; Elaissari, A. Hormonal orchestra: Mastering mitochondria’s role in health and disease. Endocrine 2024, 86, 903–929. [Google Scholar] [CrossRef] [Scilit]
- Alvarez-Salas, E.; García-Luna, C.; de Gortari, P. New Efforts to Demonstrate the Successful Use of TRH as a Therapeutic Agent. Int. J. Mol. Sci. 2023, 24, 11047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, F.; Zhao, J.; Du, J.; Li, J.; Wang, P.; Yi, Z.; Feng, T.; Wan, Z. Exploring the relationships between clinical manifestations and sex hormones, thyroid hormones, and menstrual factors in female Parkinson’s disease patients. Front. Med. 2025, 12, 1573768. [Google Scholar] [CrossRef] [Scilit]
- Freund, M.E.T.; van der Most, F.; Groeneweg, S.; van Geest, F.S.; Visser, W.E. Thyroid Hormone Analogs: Recent Developments. Thyroid 2025, 35, 990–1002. [Google Scholar] [CrossRef] [Scilit]
- van Geest, F.S.; Liao, W.; Voorhoeve, P.G.; Leen, W.G.; Zwaveling-Soonawala, N.; Chatterjee, V.K.; Van den Berg, S.A.A.; Verburg, F.A.; Meima, M.E.; van den Akker, E.L.T.; et al. Extreme resistance to thyroid hormone caused by a novel mosaic thyroid hormone receptor beta mutation. Eur. Thyroid. J. 2025, 14, e250092. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, X.; Sun, J.; Chen, F.; Tang, H.; Zeng, Y.; Li, L.; Yu, Q.; Chen, L.; Hammad, M.; Xu, X.; et al. YOD1 regulates oxidative damage of dopamine neurons in Parkinson’s disease by deubiquitinating PKM2. Clin. Transl. Med. 2025, 15, e70420. [Google Scholar] [CrossRef] [Scilit]
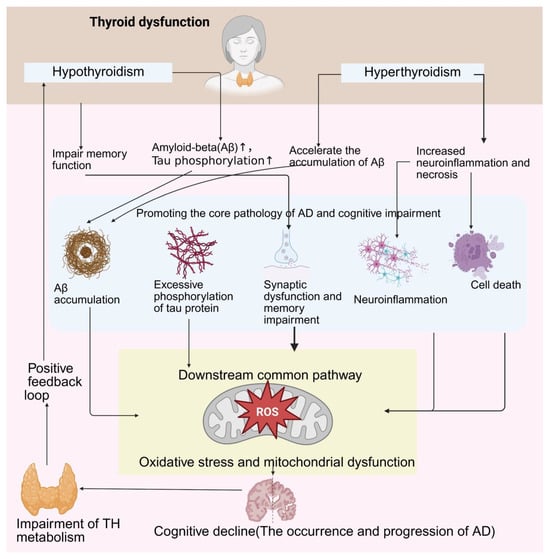
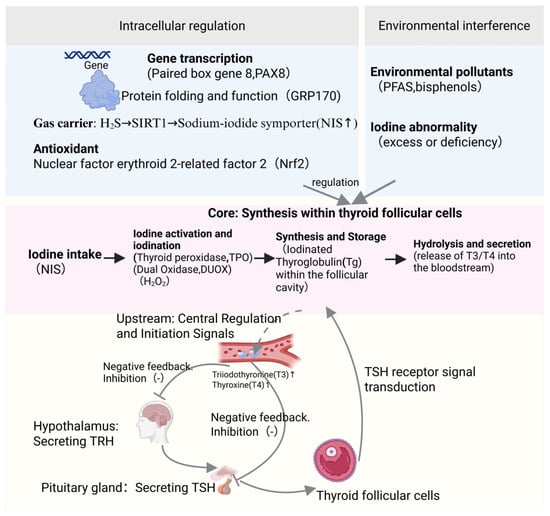
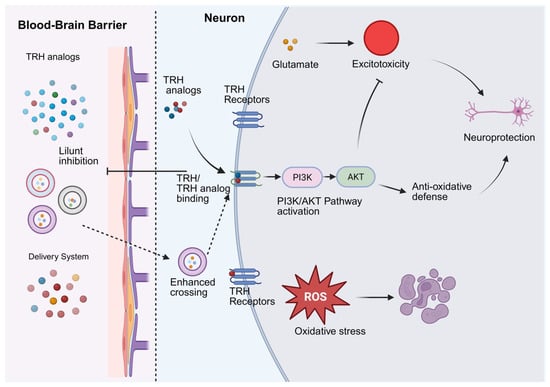
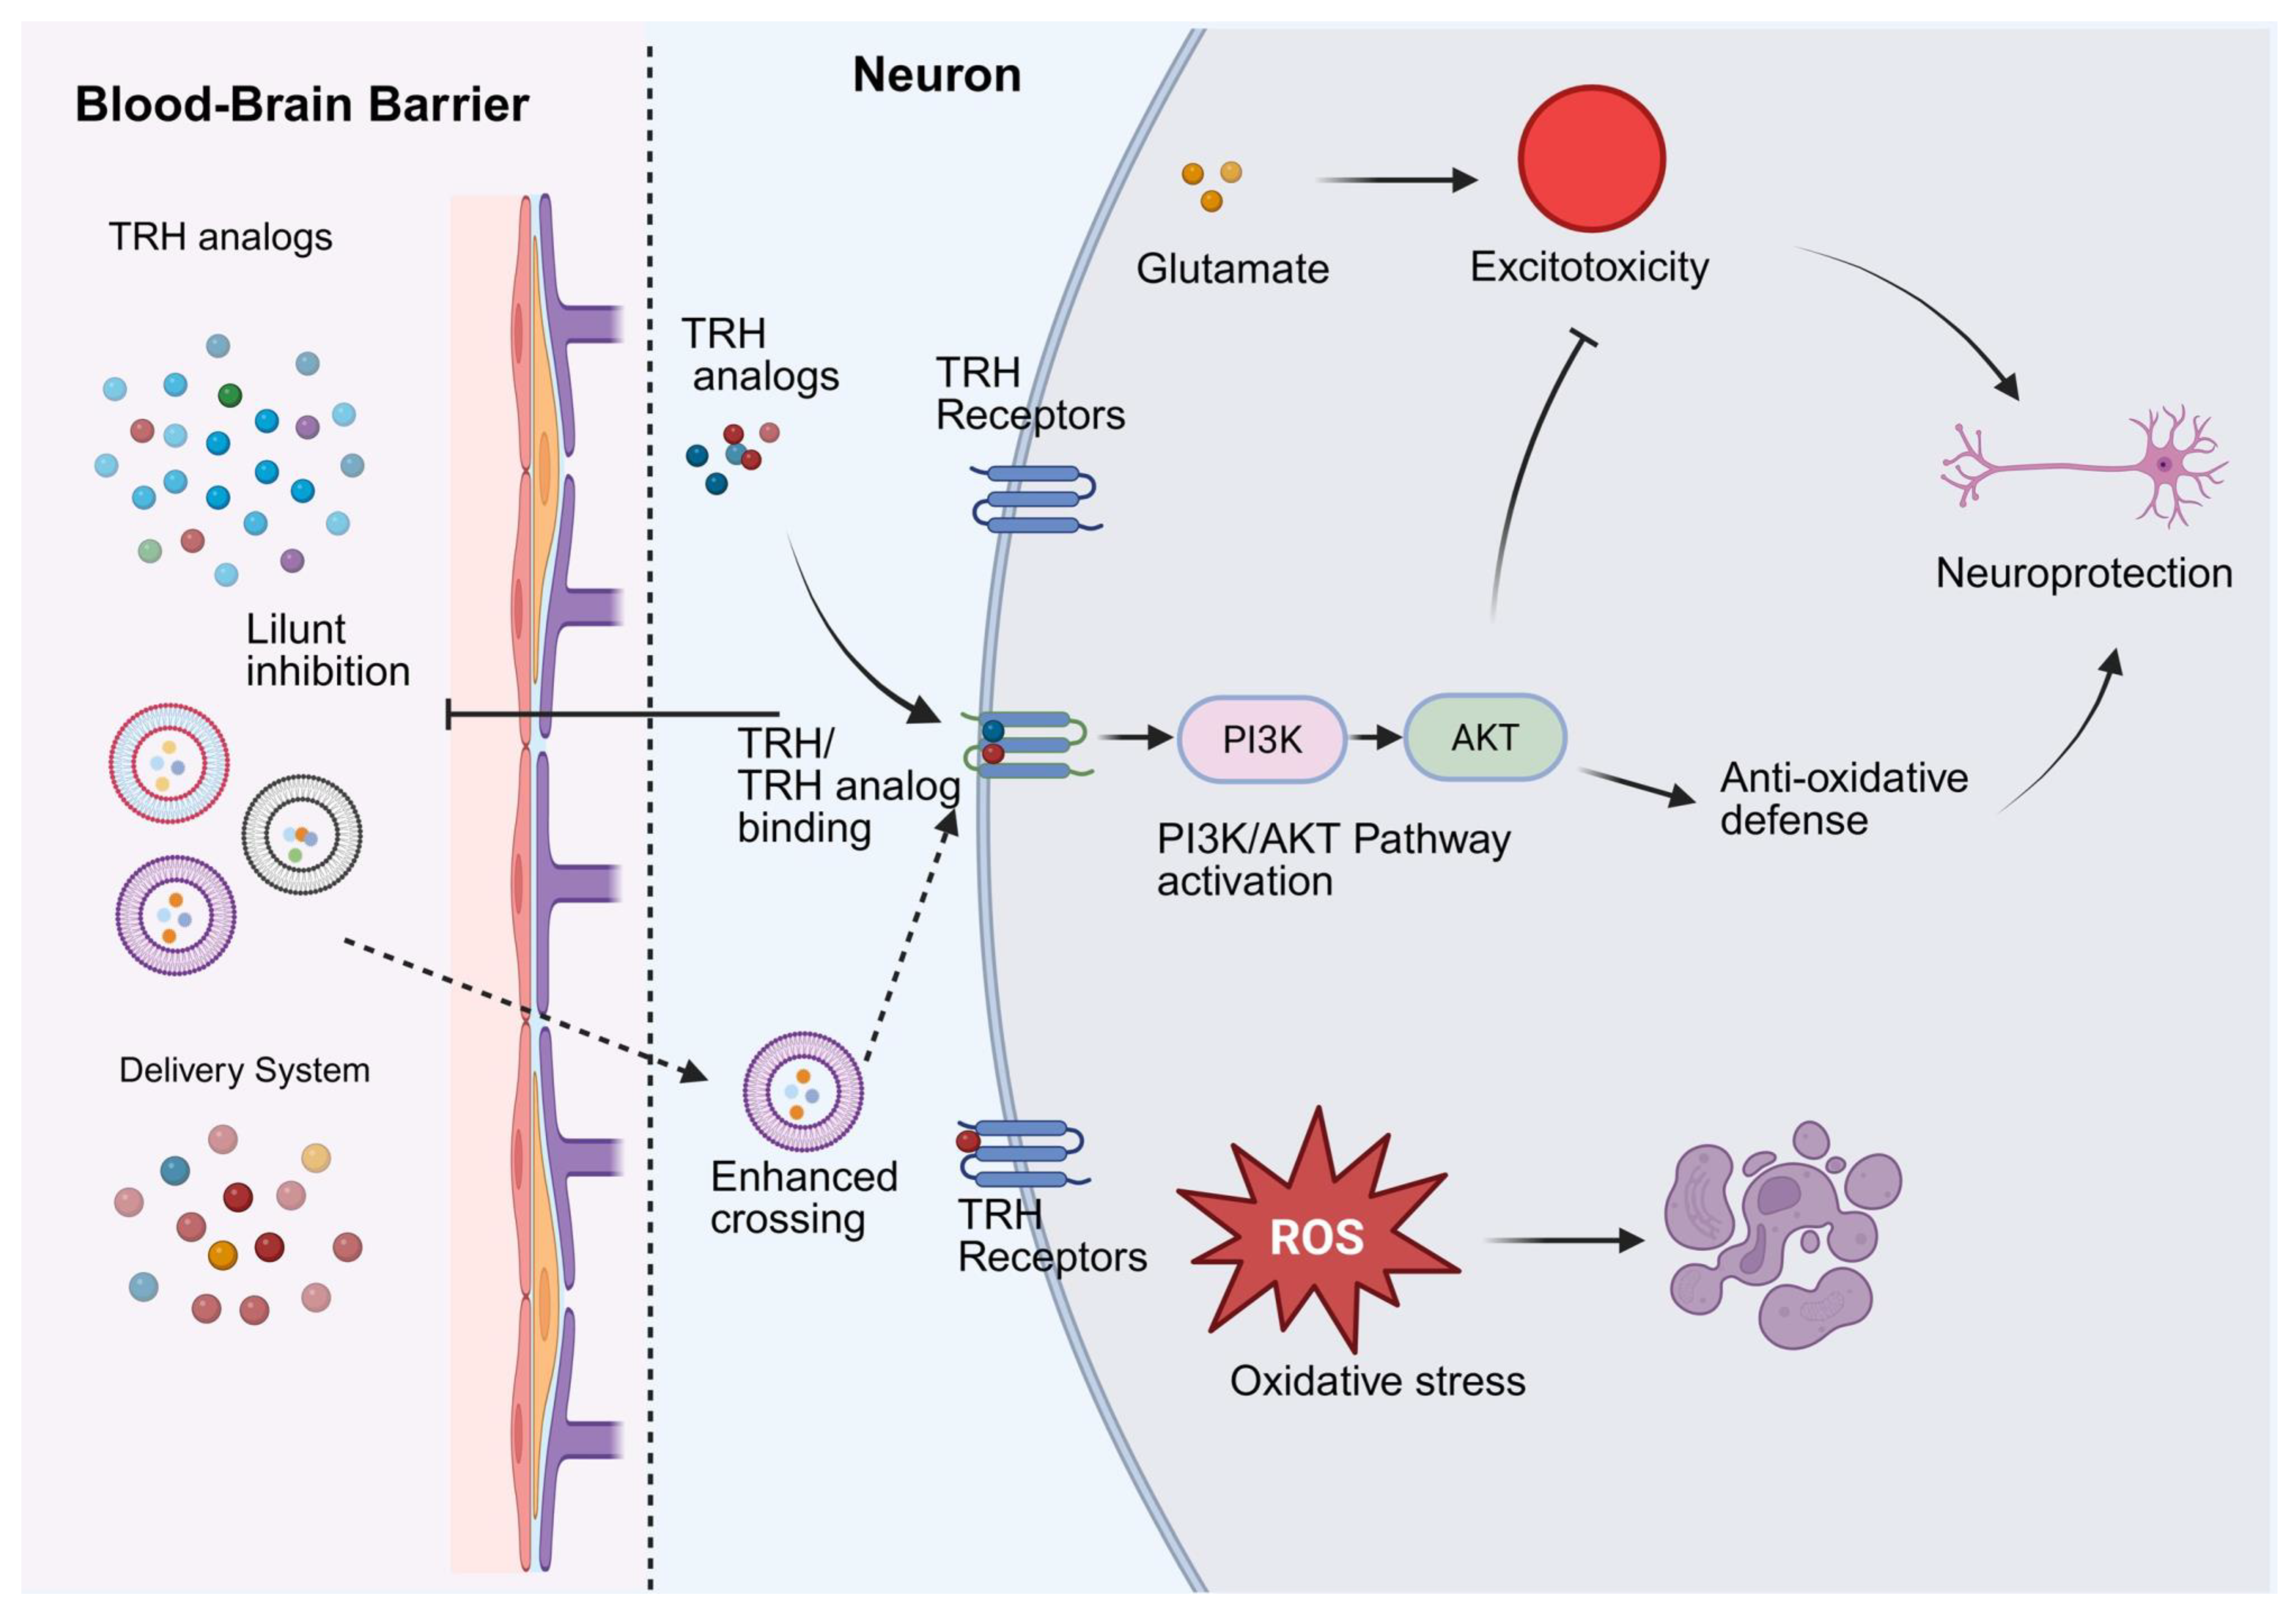
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.