


Abstract
Introduction: Outcome measures using telerehabilitation (TR) in the context of post-stroke rehabilitation are an area of emerging research. The current review assesses the literature related to TR for patients requiring post-stroke rehabilitation. The purpose of this study is to survey the outcome measures used in TR studies and to define which parts of the International Organization of Functioning are measured in trials. Methods: TR studies were searched in Cochrane Central Register of Controlled Trials, PubMed, Embase, Scopus, Google Scholar, and Web of Science, The Cochrane Central Register of Controlled Trials (Cochrane Library), the Cumulative Index to Nursing and Allied Health Literature (CINAHL), and the Physiotherapy Evidence Database (PEDro) from 2016 to June 2023. Two reviewers individually assessed the full text. Discrepancies regarding inclusion or exclusion were resolved by an additional reviewer. Results: A total of 24 studies were included in the current review. The findings were synthesized and presented taking into account their implications within clinical practice, areas of investigation, and strategic implementation. Conclusions: The scoping review has recognized a broad range of outcome measures utilized in TR studies, shedding light on gaps in the current literature. Furthermore, this review serves as a valuable resource for researchers and end users (such as clinicians and policymakers), providing insights into the most appropriate outcome measures for TR. There is a lack of studies examining the required follow-up after TR, emphasizing the need for future research in this area.
1. Introduction
The use of innovative technology for the treatment of cognitive and motor impairments in stroke during the critical golden hour is of paramount importance [1]. Recently, the use of telerehabilitation (TR), which we define as the ability to provide assessment and intervention to people who require rehabilitative services via telecommunication, has emerged as a substitute for in-person therapy [2]. Recent studies have shown that TR can positively affect motor functions such as balance, mobility, and postural control [1,3].
TR offers a potential solution to some of the accessibility challenges faced by individuals living with stroke [2,4]. A study found that TR interventions for stroke found no change between telehealth and face-to-face interventions for activities of daily living, balance, and upper extremity involvement [5]. Within TR, communication between patients and qualified rehabilitation professionals is facilitated via technologies like telephones and internet-based videoconferencing. Analyzing the efficacy of these interventions is pivotal for advancing the field of TR [1]. Numerous tools have been developed to assess both the outcomes and the effectiveness of post-stroke interventions [6].
There is a growing need for improvements in stroke care [7]. The latter study provides strong evidence supporting the effectiveness of both virtual reality (VR) and TR in enhancing stroke care, offering valuable guidance on selecting appropriate outcome measures for assessing the effect of these interventions on survivors of stroke and their families [7]. A recent literature review recognized numerous assessment tools utilized in stroke therapy [8]. Another review of outcome measures utilized in randomized controlled trials (RCTs) identified 30 distinct measures documented in RCTs, which gauged the efficacy of interventions in stroke therapy [9]. The adequacy of TR relative to the status quo is confirmed when outcome measures demonstrate no significant decline in performance compared to traditional treatment [5]. Thus, choice of an appropriate outcome metric to utilize in research and in clinical practice is imperative.
It is important to note that when selecting outcome measures for clinical observation for patient improvement, the consideration should assess not just impairments in motor function, but also encompass various factors such as the patient’s lifestyle and daily preferences [9]. There are numerous advantages to employing standardized outcome measures, which include the ability to identify patients at risk of experiencing adverse or unfavorable outcomes, identifying the most effective interventions tailored to specific contexts, and analyzing organizational metrics [2]. Clinicians have supported the utilization of standardized tools in therapy for several years. A study by Diana et al. in 2017 emphasized the importance of clear outcome measurements with a focus on TR and VR [10]. However, there remains a lack of consensus regarding the utilization of outcome measures to enable meaningful appraisals across interventions and studies [4]. This gap in consensus has persisted from January 2015 until the present day, especially within the realm of TR. Considering the COVID-19 pandemic, during which the healthcare industry relied heavily on telerehabilitation interventions, there is a pressing need for establishing a consistent approach in this regard [11]. In addition, using telerehabilitation is beneficial for patients who cannot commute to clinical settings, particularly in rural and isolated areas [12]. Telerehabilitation also has the potential to reduce the costs of hospitalization for some patients [13]. Peretee et al. in 2017 found that telerehabilitation is effective in caring for patients with severe pathologies, such as serious cognitive deficits, enabling them to undergo physiotherapy at home without the need for exhausting transportation [13]. TR is also well-suited for patients residing in rural areas, distant from urban clinical centers, who need rehabilitation during the critical golden hour [13]. Virtual reality serves as a technology for home-based rehabilitation, providing a safe environment for patients to engage in conventional exercises, even though some studies explore the application of TR in virtual environments [14].
The current review is the first to our knowledge that attempts to elucidate the outcome measures employed in the rapidly evolving field of TR. The most recent telerehabilitation technologies include exergames (e.g., the XR-MoBI technology), digital applications, digital health technologies, telecommunication methods, and mobile applications used as treatments for patients [15].
With the aim of establishing comprehensive guidelines for the utilization of outcome measures in TR, particularly within the realm of stroke rehabilitation, we have conducted a scoping review that systematically synthesizes the prevalent outcome measurement practices. Thus, the present study aims to delineate the findings from this scoping review.
2. Methods
The Arksey and O’Malley framework from the University of York was used as guidance for a methodologically rigorous approach to systematically review the outcome metrics utilized to evaluate the efficacy of TR [16]. The York framework has been used broadly in knowledge synthesis trials and consists of the following five stages: (1) classifying the research question; (2) recognizing pertinent studies based on the research question; (3) trial selection; (4) charting the information within the selected trials; and (5) organizing, summarizing, and reporting the findings of the scoping review. The research questions for the current review were as follows: which outcome measures are used in TR stroke therapy trials and at what time points are they controlled (admission, discharge, and follow-up of the patient) subsequent to a stroke? Which functions from the International Classification of Functioning (ICF) are assessed in the outcome measures? This study was carried out in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines [17].
2.1. Eligibility Criteria
The inclusion criteria for this scoping review consisted of trials: (1) including patients that had sustained a stroke, (2) recounting a rehabilitation protocol utilizing TR, (3) written in English, and (4) published after January 2015. The exclusion criteria included: (1) non-English manuscripts, (2) papers omitting outcome measures, (3) papers only reporting laboratory measures, (4) discussion and protocol papers or commentary and qualitative studies, (5) poster presentations, abstracts, or papers lacking information about the treatment, and (6) papers only reporting the change and development of the technology. The search was completed using study design or publication date.
2.2. Search Strategy
The literature search was done by a librarian in the field of therapy. The search included PubMed, Embase, Scopus, Google Scholar, Web of Science, The Cochrane Central Register of Controlled Trials (Cochrane Library), the Cumulative Index to Nursing and Allied Health Literature (CINAHL), and the Physiotherapy Evidence Database (PEDro) (until July 2023) to classify potentially related studies.
2.3. Data Collection Process
Two of the reviewers (MGN and MF) independently investigated the titles and abstracts extracted from the database searches to determine if they fit the inclusion criteria. Disagreements regarding the inclusion or exclusion of a particular manuscript based on the appraisal of its abstract were determined by reaching an agreement or consulting an additional reviewer (AS). Data extraction arrangements were established based on the current literature in the field and on the questions of the research. Extraction of the data was based on essential information according to questions of the current review such as (a) the study’s authors, (b) the publication date, (c) the objective(s) of the trial, (d) the design of the trial, (e) country, (f) outcome measures reported, (g) patient characteristics (e.g., age, sex, socioeconomic status, level of education, motor functional level, the phase of the stroke, type of the stroke), (h) related ICF domains, (i) period of time at which the assessment was taken (e.g., admission, discharge, follow-up), (j) technology used for TR, and (k) details on the TR intervention. The outcome measures were categorized based on the ICF domains [16].
2.4. Critical Appraisal of the Included Articles
The modified Critical Appraisal Skills Programme (CASP) tool [18,19] was used for assessing the quality of each of the included studies by the three reviewers (MGN, MF, and AS). The CASP tool is an instrument used for evaluating the strengths and limitations of any qualitative research approach [19]. The tool has 10 questions that each emphasizes different methodological domains of a qualitative study: the identification of the research questions, the relevance of the methodology (including study design), description of the population and sample size, outcomes, suitability of analysis methodologies, relevance, and clarification of results. Information was obtained from studies achieving scores greater than 50% based on the CASP scoring system.
2.5. Quality Assessment
We used the CASP tools for assessing the quality of studies, primarily case-control studies and clinical trials. The CASP RCT checklist evaluates 11 critical criteria:
- (1)
- Did the study address a clearly focused research question?
- (2)
- Was the assignment of participants to interventions randomized?
- (3)
- Were all participants who entered the study accounted for at its conclusion?
- (4)
- Was blinding appropriately addressed for participants, assessors, and therapists?
- (5)
- Were the study groups similar at the start of the randomized controlled trial?
- (6)
- Apart from the experimental intervention, did each study group receive the same level of care (i.e., were they treated equally)?
- (7)
- Were the effects of intervention reported comprehensively?
- (8)
- Was the precision of the estimate of the intervention or treatment effect reported?
- (9)
- Did the benefits of the experimental intervention outweigh the harms and costs?
- (10)
- Could the results be applied to your local population/in your context?
- (11)
- Would the experimental intervention provide greater value to the people in your care than any of the existing interventions?
The CASP case-control study checklist also consists of 11 questions:
- (1)
- Did the study address a clearly focused issue?
- (2)
- Did the authors use an appropriate method to answer their question?
- (3)
- Were the cases recruited appropriately?
- (4)
- Were the controls selected appropriately?
- (5)
- Was the exposure accurately measured to minimize bias?
- (6)
- Aside from the experimental intervention, were the groups treated equally, and did the authors account for the potential confounding factors in the design and/or in their analysis?
- (7)
- How large was the treatment effect?
- (8)
- How precise was the estimate of the treatment effect?
- (9)
- Are the results credible?
- (10)
- Can the results be applied to the local population?
- (11)
- Do the results of this study fit with other available evidence?
Responses to these questions were recorded as ‘‘Yes”, “No”, or “Can’t tell”. In the current review, seven studies were evaluated using the CASP RCT checklist [20,21,22,23,24,25,26] (Table 1).
Table 1.
The characteristics of the included studies.
In addition, when appraising other studies using the CASP case-control study checklist, questions 4 (Were the controls selected appropriately?) and 6 (Aside from the experimental intervention, were the groups treated equally, and did the authors account for the potential confounding factors in the design and/or in their analysis?) were deemed not applicable since the reported trials were uncontrolled trials. Thus, the total number of questions for the latter studies was nine rather than 11. Sixteen out of the 23 trials had scores between 7 and 9 out of 9, with only two studies scoring 7. Six of the included trials had a score between 8 and 9 out of 11, whereas only four studies scored 7.
3. Results
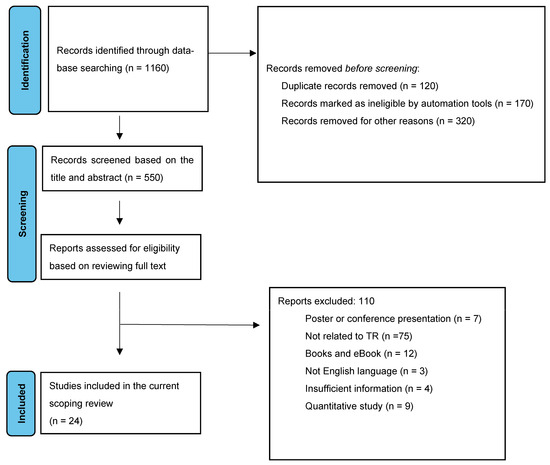
The exploration of the electronic databases recognized 550 manuscripts after duplicate studies were removed. After screening of the titles and abstracts, 136 studies remained. After a full-text review process, 110 articles were excluded, leaving a total of 24 included studies. Reasons for exclusion of studies are depicted in Figure 1.
Figure 1.
PRISMA 2023 flow diagram for the scoping review about TR and stroke as rehabilitation.
3.1. Included Studies
The current scoping review encompassed a comprehensive analysis of 24 studies. This review is organized into three key sections: (a) essential characteristics of the trials, which include details about the authors, location, publication year, study design, subject characteristics, type of stroke, TR explanation, and the numerical score of the quality of the studies above 7 from 9 related to pooled studies, (b) TR outcome measures used in assessing post-stroke patients, and (c) areas of the ICF covered by these outcome measures. The included trials were published between 2015 and 2023, and most of the trials were conducted in the USA and Canada. The most common study designs were quantitative approaches such as RCTs, CTs, case studies with one group and two groups with pre- and post-test intervention (Table 1).
3.2. Participant Characteristics
The study participants primarily consisted of males (335) who had experienced various stroke conditions, including ischemic, subacute, and chronic stroke with symptoms such as hemiparesis, aphasia, and other neurological disorders. These individuals were willing and consenting to begin a rehabilitation protocol. All studies provided detailed information on age, gender distribution, and the total number of participants. Two of the studies included a single case study involving post-stroke patients (Table 1). All the studies used TR intervention and two studies used TR with VR. The TR interventions were provided via various modalities, including video games, an internet-connected computer and laptop, TR application, serious games, and robot-based TR (Table 1)
3.3. Frequently Used Outcome Measures
A total of 20 outcomes were used in the scoping review (15 outcomes in TR studies and 5 outcomes in TR studies with VR). The most used outcomes were the Fugel–Meyer assessment of the recovery of patients with stroke (FMA) [20,24,35,42], balance, and motor function in the upper limb function. All outcome measures were used pre- and post-protocol based on TR (Table 2).
Table 2.
Frequency of used outcome measures in TR intervention studies.
3.4. ICF, Disability, and Health Domain
The ICF serves as a framework comprising domains or categories, offering valuable guidelines for reporting functioning, performance, and health in clinical assessments. In the current study, none of the trials employed the ICF guidelines for outcome measurement encompassing aspects of both upper and lower limb function, structural aspects, and physical activity. The majority of the pooled studies focused on upper limb function (trunk mobility and functional recovery) [21,23,28,32,35,42] and some studies focused on lower limb function (balance and gait) [25,26,30,32,34,38].
4. Discussion
In recent years, TR has emerged as a new technology for treating and rehabilitating stroke patients [34]. In the current review, we identified more than 20 outcome measures (Table 2) that illustrate a broad range of assessments utilized in trials focused on stroke rehabilitation with interventions provided through TR. Among these measures, the most used was the FMA. FMA is a performance-based deficiency index and is designed to measure motor function, balance, awareness, and joint functioning in stroke patients. It serves multiple purposes, including measuring motor recovery, assessing disease severity, and aiding in treatment planning and evaluation.
In contrast, other studies have employed various other tools to assess a common outcome such as balance [7]. These tools encompass diverse measurements, including gait speed, Barthel Index (BI), Berg Balance Scale (BBS), Stroke Impact Scale (SIS), and quality of life (QOL) metrics. Importantly, the FMA has demonstrated outstanding reliability in both inter-rater and intra-rater assessments, exhibits strong construct validity, and is highly responsive to detecting changes in patient’s conditions. The intraclass correlation coefficient (ICC) for both the intra- and inter-rater reliability of the FMA both had values above 0.90, consistent with the reliability of this tool for stroke in the chronic and subacute phases. For validation of measuring the strength of association, the ICC and other correlation methods are necessary.
The BBS is another reliable tool, but it is not sensitive enough to detect subtle yet clinically significant changes in balance in individual subjects, particularly those recovering from stroke [15]. It is a relatively inexpensive test and can be used with a wide range of populations, including healthy individuals and patients. It evaluates balance through a comprehensive assessment that encompasses two distinct dimensions, static and dynamic, via a structured questionnaire [43,44].
Gait analysis is another valuable measurement that was utilized in five of the included studies to meticulously assess details of step and gait speed in stroke patients [34]. In addition, the Stroke Impact Scale (SIS) is a widely used measure due to its reliability, validity, and sensitivity to change [45]. The SIS contains a question to evaluate the patient’s global perception of their percentage of recovery [46]. Another frequently utilized measure that was used in studies is the Barthel Index (BI). However, there is a strong need for greater consistency in methods, content, and scoring across studies, given that the “BI” acronym is associated with various assessment methodologies. For example, some studies have adopted a 10-item scale, scoring on a range of 0 to 100 with 5-point increments [47]. This approach has been used in several multicenter stroke trials, and we call for more uniform application of this tool for stroke trials. Consistency in result reporting will allow for more appropriate pooling of data for literature review and meta-analysis.
In general, all the aforementioned outcome measures aim to capture important changes in patients who are undergoing stroke rehabilitation, whether by TR or more traditional means. Importantly, most studies have highlighted that patient satisfaction plays a pivotal role in their recovery and motivation to continue with rehabilitation to regain function. Surprisingly, only two studies incorporated a thorough assessment of patient satisfaction and motivation, using tools including the Client Satisfaction Scale (CSS) and the Canadian Occupational Performance Measure (COPM). Upon examining the satisfaction levels of patients who underwent TR following a stroke, the results unequivocally indicate that TR can be a highly effective intervention in the realm of rehabilitation. A study even mentioned maintenance of long exercises in telerehabilitation as feasible; ultimately telerehabilitation can prevent deterioration, improve physical performance, health status, and quality of life [41].
Our scoping review identified various evaluation questions that pertained to changes in health service utilization, intervention costs, and the utilization of comprehensive assessment tools to gauge aspects of patient safety, comfort, ease of use, and the efficiency-related consequences resulting from interactions with the technology [48]. This scoping review focused on motor functions such as upper-extremity function, balance, and postural control, yielding outcomes similar to those observed in previous research, such as the study conducted in 2017 [7]. Notably, the trial of Tate et al. found a limited number of studies (8.8%) that assessed specific motor, sensory, and other bodily functions [47]. It is worth mentioning that most of the studies reviewed in this study predominantly evaluated domains related to mental function [47]. In contrast, our scoping review identified only two studies that used the Mini Mental State Examination (MMSE). Future studies should prioritize outcome measures that support ICF domains using TR. Adhering to the Canadian Best Practice Recommendations for Stroke Care can comprehensively cover the various aspects of the ICF framework during both the short- and long-term recovery in stroke patients.
5. Conclusions
Our review included quantitative studies such as RCTs, CTs, case studies that provided essential information regarding participant demographics, including age and sex, as well as details about the interventions and the specific type of TR employed for rehabilitation. Most of these studies assessed outcomes related to motor function, consistently reporting improvements in this domain. However, it is important to note that most studies did not include information about the cost implications of the interventions, which could provide valuable insights for healthcare providers, clinicians, patients, and their families when making decisions based on using new technology with TR. Future studies should emphasize measuring the utilization and feasibility of these outcomes within the context of TR while also providing detailed cost-related information. Furthermore, future studies should investigate the standards that guide the selection of outcomes by clinicians and investigators. Furthermore, incorporating standard exercises can facilitate the learning and correction of general motor patterns, leading to noticeable improvements. It is crucial to explore the reasons behind the exclusion of certain outcomes, such as the need to establish new protocols for professionals, ensuring the availability of assessment tools in the same language as the patients, managing the time required for assessments, and addressing equipment-related prerequisites for the utilization of specific tools. Understanding and addressing these factors will contribute to the improvement of outcome selection processes in TR and related research. Exploring comprehensive methods to assess intervention costs and investigating potential variation in TR acceptance among different demographic groups could be impactful. The development of an application for assessment based on standardized measurements is essential for telerehabilitation, as physiotherapists can monitor activation and compare movement patterns. On the other hand, future studies must further assess follow-up outcomes for TR and characterize the effect size over the long term.
Funding
This study received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Vellata, C.; Belli, S.; Balsamo, F.; Giordano, A.; Colombo, R.; Maggioni, G. Effectiveness of telerehabilitation on motor impairments, non-motor symptoms and compliance in patients with Parkinson’s disease: A systematic review. Front. Neurol. 2021, 12, 627999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, F.; Zhang, D.; Chen, J.; Tang, K.; Li, X.; Hou, Z. Research hotspots and trends of brain-computer interface technology in stroke: A bibliometric study and visualization analysis. Front. Neurol. 2023, 17, 1243151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, J.; Zhang, X.; Lian, Z. Impact of wooden versus nonwooden interior designs on office workers’ cognitive performance. Percept. Mot. Ski. 2020, 127, 36–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakhostin Ansari, N.; Bahramnezhad, F.; Anastasio, A.T.; Hassanzadeh, G.; Shariat, A. Telestroke: A Novel Approach for Post-Stroke Rehabilitation. Brain Sci. 2023, 13, 1186. [Google Scholar] [CrossRef] [Scilit]
- Laver, K.E.; Adey-Wakeling, Z.; Crotty, M.; Lannin, N.A.; George, S.; Sherrington, C. Telerehabilitation services for stroke. Cochrane Database Syst. Rev. 2020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scuteri, D.; Mantovani, E.; Tamburin, S.; Sandrini, G.; Corasaniti, M.T.; Bagetta, G. Opioids in post-stroke pain: A systematic review and meta-analysis. Front. Pharmacol. 2020, 11, 587050. [Google Scholar] [CrossRef] [Scilit]
- Veras, M.; Kairy, D.; Rogante, M.; Giacomozzi, C.; Saraiva, S. Scoping review of outcome measures used in telerehabilitation and virtual reality for post-stroke rehabilitation. J. Telemed. Telecare 2017, 23, 567–587. [Google Scholar] [CrossRef] [Scilit]
- Zeng, X.; Zhang, Y.; Kwong, J.S.; Zhang, C.; Li, S.; Sun, F. The methodological quality assessment tools for preclinical and clinical studies, systematic review and meta-analysis, and clinical practice guideline: A systematic review. J. Evid. Based Med. 2015, 8, 2–10. [Google Scholar] [CrossRef] [Scilit]
- Gold, D.A. An examination of instrumental activities of daily living assessment in older adults and mild cognitive impairment. J. Clin. Exp. Neuropsychol. 2012, 34, 11–34. [Google Scholar] [CrossRef] [Scilit]
- Diana, C.; Mirela, I.; Sorin, M. Approaches on the relationship between competitive strategies and organizational performance through the Total Quality Management (TQM). Qual. Access Success 2017, 18, 328–333. [Google Scholar]
- Edwards, D.; Kumar, S.; Brinkman, L.; Ferreira, I.C.; Esquenazi, A.; Nguyen, T. Telerehabilitation Initiated Early in Post-Stroke Recovery: A Feasibility Study. Neurorehabil. Neural Repair. 2023, 37, 131–141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huzmeli, E.D.; Duman, T.; Yildirim, H. Efficacy of Telerehabilitation in patients with stroke in turkey: A pilot Study/Turkiye’de Inmeli Hastalarda Telerehabilitasyonun Etkinligi: Pilot Calisma. Turk. J. Neurol. 2017, 23, 21–26. [Google Scholar] [CrossRef] [Scilit]
- Peretti, A.; Amenta, F.; Tayebati, S.K.; Nittari, G.; Mahdi, S.S. Telerehabilitation: Review of the state-of-the-art and areas of application. JMIR Rehabil. Assist. Technol. 2017, 4, e7511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rutkowski, S.; Kiper, P.; Cacciante, L.; Mazurek, J.; Turolla, A. Use of virtual reality-based training in different fields of rehabilitation: A systematic review and meta-analysis. J. Phys. Med. Rehabil. 2020, 52, 1–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arntz, A.; Weber, F.; Handgraaf, M.; Lällä, K.; Korniloff, K.; Murtonen, K.-P. Technologies in Home-Based Digital Rehabilitation: Scoping Review. JMIR Rehabil. Assist. Technol. 2023, 10, e43615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Tam, W.W.; Tang, A.; Woo, B.; Goh, S.Y. Perception of the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) statement of authors publishing reviews in nursing journals: A cross-sectional online survey. BMJ Open 2019, 9, e026271. [Google Scholar] [CrossRef] [Scilit]
- Stucki, G.; Cieza, A.; Ewert, T.; Kostanjsek, N.; Chatterji, T.B. Application of the International Classification of Functioning, Disability and Health (ICF) in clinical practice. Disabil. Rehabil. 2002, 24, 281–282. [Google Scholar] [CrossRef] [Scilit]
- Long, H.A.; French, D.P.; Brooks, J.M. Optimising the value of the critical appraisal skills programme (CASP) tool for quality appraisal in qualitative evidence synthesis. Res. Methods Med. Health Sci. 2020, 1, 31–42. [Google Scholar] [CrossRef] [Scilit]
- Cramer, S.C.; Young, B.M.; Schwarz, A.; Chang, T.Y.; Su, M. Telerehabilitation Following Stroke. Phys. Med. Rehabil. Clin. N. Am. 2023. [Google Scholar] [CrossRef] [Scilit]
- Uswatte, G.; Taub, E.; Lum, P.; Brennan, D.; Barman, J.; Bowman, M.H. Tele-rehabilitation of upper-extremity hemiparesis after stroke: Proof-of-concept randomized controlled trial of in-home constraint-induced movement therapy. Restor. Neurol. Neurosci. 2021, 39, 303–318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Øra, H.P.; Kirmess, M.; Brady, M.C.; Sørli, H.; Becker, F. Technical features, feasibility, and acceptability of augmented telerehabilitation in post-stroke aphasia—Experiences from a randomized controlled trial. Front. Neurol. 2020, 11, 671. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rozevink, S.G.; van der Sluis, C.K.; Hijmans, J.M. HoMEcare aRm rehabiLItatioN (MERLIN): Preliminary evidence of long term effects of telerehabilitation using an unactuated training device on upper limb function after stroke. J. Neuroeng. Rehabil. 2021, 18, 141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rozevink, S.G.; Van der Sluis, C.K.; Garzo, A.; Keller, T.; Hijmans, J.M. HoMEcare aRm rehabiLItatioN (MERLIN): Telerehabilitation using an unactuated device based on serious games improves the upper limb function in chronic stroke. J. Neuroeng. Rehabil. 2021, 18, 48. [Google Scholar] [CrossRef] [Scilit]
- Saywell, N.L.; Mudge, S.; Kayes, N.M.; Stavric, V.; Taylor, D. A six-month telerehabilitation programme delivered via readily accessible technology is acceptable to people following stroke: A qualitative study. Physiotherapy 2023, 120, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.J.; Lee, E.C.; Kim, M.; Ko, S.-H.; Huh, S.; Choi, W. Feasibility of dance therapy using telerehabilitation on trunk control and balance training in patients with stroke: A pilot study. Medicine 2022, 101, e30286. [Google Scholar] [CrossRef] [Scilit]
- Toh, S.F.M.; Gonzalez, P.C.; Fong, K.N. Usability of a wearable device for home-based upper limb telerehabilitation in persons with stroke: A mixed-methods study. Digit. Health 2023, 9, 20552076231153737. [Google Scholar] [CrossRef] [Scilit]
- Marianna, C.; Francesco, A.; Paolo, T.; Loris, P.; Tiziana, M.; Giuseppe, N. Stroke Telerehabilitation in Calabria: A Health Technology Assessment. Front. Neurol. 2022, 12, 777608. [Google Scholar]
- Allegue, D.R.; Higgins, J.; Sweet, S.N.; Archambault, P.S.; Michaud, F.; Miller, W. Rehabilitation of upper extremity by telerehabilitation combined with exergames in survivors of chronic stroke: Preliminary findings from a feasibility clinical trial. JMIR Rehabil. Assist. Technol. 2022, 9, e33745. [Google Scholar] [CrossRef] [Scilit]
- Salgueiro, C.; Urrútia, G.; Cabanas-Valdés, R. Telerehabilitation for balance rehabilitation in the subacute stage of stroke: A pilot controlled trial. Neurorehabilitation 2022, 51, 91–99. [Google Scholar] [CrossRef] [Scilit]
- Salgueiro, C.; Urrútia, G.; Cabanas-Valdés, R. Influence of core-stability exercises guided by a telerehabilitation app on trunk performance, balance and gait performance in chronic stroke survivors: A preliminary randomized controlled trial. Int. J. Environ. Res. Public Health 2022, 19, 5689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, M.; Dexter, B.; Hancock, A.; Hoffman, N.; Kerschke, S.; Hux, K. Implementing Team-Based Post-Stroke Telerehabilitation: A Case Example. Int. J. Telerehabili. 2022, 14, e6438. [Google Scholar] [CrossRef] [Scilit]
- Dawson, D.R.; Anderson, N.D.; Binns, M.; Bar, Y.; Chui, A.; Gill, N. Strategy-training post-stroke via tele-rehabilitation: A pilot randomized controlled trial. Disabil. Rehabil. 2022, 5, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, S.-C.; Lin, C.-H.; Su, S.-W.; Chang, Y.-T.; Lai, C.-H. Feasibility and effect of interactive telerehabilitation on balance in individuals with chronic stroke: A pilot study. J. Neuroeng. Rehabil. 2021, 18, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nam, C.; Zhang, B.; Chow, T.; Ye, F.; Huang, Y.; Guo, Z. Home-based self-help telerehabilitation of the upper limb assisted by an electromyography-driven wrist/hand exoneuromusculoskeleton after stroke. J. Neuroeng. Rehabil. 2021, 18, 1–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marin-Pardo, O.; Donnelly, M.R.; Phanord, C.S.; Wong, K.; Pan, J.; Liew, S.-L. Functional and neuromuscular changes induced via a low-cost, muscle-computer interface for telerehabilitation: A feasibility study in chronic stroke. Front. Neuroergono 2022, 3, 33. [Google Scholar] [CrossRef] [Scilit]
- Kessler, D.; Anderson, N.D.; Dawson, D.R. Occupational performance coaching for stroke survivors delivered via telerehabilitation using a single-case experimental design. Br. Assoc. Occup. Ther. 2021, 84, 488–496. [Google Scholar] [CrossRef] [Scilit]
- Burgos, P.I.; Lara, O.; Lavado, A.; Rojas-Sepúlveda, I.; Delgado, C.; Bravo, E. Exergames and telerehabilitation on smartphones to improve balance in stroke patients. Brain Sci. 2020, 10, 773. [Google Scholar] [CrossRef] [Scilit]
- Ivanova, E.; Lorenz, K.; Schrader, M.; Minge, M. Developing motivational visual feedback for a new telerehabilitation system for motor relearning after stroke. In Proceedings of the 31st International BCS Human Computer Interaction Conference (HCI 2017), Sunderland, UK, 3–6 July 2017; Volume 31. [Google Scholar] [CrossRef] [Scilit]
- Dodakian, L.; McKenzie, A.L.; Le, V.; See, J.; Pearson-Fuhrhop, K.; Burke Quinlan, E. A home-based telerehabilitation program for patients with stroke. Neurorehabil. Neural Repair. 2017, 31, 923–933. [Google Scholar] [CrossRef] [Scilit]
- Zanaboni, P.; Hoaas, H.; Aarøen Lien, L.; Hjalmarsen, A.; Wootton, R. Long-term exercise maintenance in COPD via telerehabilitation: A two-year pilot study. J. Telemed. Telecare 2017, 23, 74–82. [Google Scholar] [CrossRef] [Scilit]
- Cramer, S.C.; Dodakian, L.; Le, V.; McKenzie, A.; See, J.; Augsburger, R. A feasibility study of expanded home-based telerehabilitation after stroke. Front. Neurol. 2021, 11, 611453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anwer, S.; Waris, A.; Gilani, S.O.; Iqbal, J.; Shaikh, N.; Pujari, A.N. Rehabilitation of upper limb motor impairment in stroke: A narrative review on the prevalence, risk factors, and economic statistics of stroke and state of the art therapies. Healthcare 2022, 10, 190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rossetti, G.; Cazabet, R. Community discovery in dynamic networks: A survey. ACM Comput. Surv. (CSUR) 2018, 51, 1–37. [Google Scholar] [CrossRef] [Scilit]
- Chen, S.; Lach, J.; Lo, B.; Yang, G.-Z. Toward pervasive gait analysis with wearable sensors: A systematic review. J. Biomed. Inform. X 2016, 20, 1521–1537. [Google Scholar] [CrossRef] [Scilit]
- Hauer, K.A.; Kempen, G.I.; Schwenk, M.; Yardley, L.; Beyer, N.; Todd, C. Validity and sensitivity to change of the falls efficacy scales international to assess fear of falling in older adults with and without cognitive impairment. Gerontology 2011, 57, 462–472. [Google Scholar] [CrossRef] [Scilit]
- Quinn, T.J.; Langhorne, P.; Stott, D.J. Barthel index for stroke trials: Development, properties, and application. Stroke 2011, 42, 1146–1151. [Google Scholar] [CrossRef] [Scilit]
- Tate, R.L.; Godbee, K.; Sigmundsdottir, L. A systematic review of assessment tools for adults used in traumatic brain injury research and their relationship to the ICF. Neurorehabilitation 2013, 32, 729–750. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).