Review

Beyond Risk Prediction: Considering Upstream Universal Suicide Prevention to Decrease Risk and Increase Resilience

Department of Psychological Services, Texas Tech University, Lubbock, TX 79409-2051, USA
*
Author to whom correspondence should be addressed.
Behav. Sci. 2026, 16(2), 243; https://doi.org/10.3390/bs16020243
Submission received: 29 December 2025 / Revised: 29 January 2026 / Accepted: 3 February 2026 / Published: 9 February 2026

Abstract

Despite decades of research, suicide risk factors predict outcomes at chance levels, and there is a dearth of protective factor and resilience research, which limits the utility of risk-based approaches. Further, suicide prevention interventions primarily consist of individual psychotherapies and treating individuals after suicide-related outcomes occur. Unfortunately, there is a lack of upstream suicide prevention interventions targeting known suicide risk factors and aiming to increase well-being and resilience in the U.S. Thus, we discuss these problems in the field and the U.S. health care system and provide a possible solution. We propose using low-intensity, universal, and upstream prevention interventions, such as Stress Control. Stress Control is a classroom-style, Cognitive Behavior Therapy-based program shown to reduce “risk,” stress, anxiety, and depression and boost well-being and resilience as part of a stepped-care model. Although Stress Control’s suicide prevention effectiveness has not yet been directly assessed, we discuss how it could be a promising suicide prevention strategy with additional testing. A proposed mechanism for this reduction is building resilience to common risk factors and suicide ideation via evidence-based coping skills, thereby decreasing future suicide risk. We review current limitations and discuss how upstream, scalable, universal prevention interventions can help improve psychological resilience and reduce suicidal thoughts and behaviors, lowering the U.S. suicide rate. Implications and recommendations are discussed.

1. Introduction

Despite over 50 years of suicide prevention research (Fox et al., 2020; Franklin et al., 2017), suicide rates in the United States (U.S.) increased by 36% from 2000 to 2021, while worldwide suicide rates decreased (Centers for Disease Control and Prevention [CDC], 2023a; Martínez-Alés et al., 2022; Naghavi, 2019). In the U.S., suicide is a leading cause of death, with over 45,000 deaths in 2020 (National Institute of Mental Health [NIMH], 2022). Further, among U.S. adults, there are approximately 1.4 million suicide attempts per year, with over 710,000 individuals receiving medical attention following a suicide attempt (Centers for Disease Control and Prevention [CDC], 2020; World Health Organization [WHO], 2023). Rates of suicide ideation (SI) are even greater, with about 14 million U.S. adults reporting SI in the previous year (Centers for Disease Control and Prevention [CDC], 2023a). These statistics demonstrate the importance of continuing to focus on suicide prevention efforts.
Suicide prevention is best conceptualized as a public health problem, with multiple contextual factors impacting the development of SI and attempts. Overlapping social determinants of health, including legislation policies and commercial determinants, and individual risk factors, such as socioeconomic position or demographics, may increase poor mental health and suicide risk (Pirkis et al., 2024). For example, several social determinants of health have been associated with increased risk of psychiatric disorders and SI and suicidal behaviors (Na et al., 2025). Living and working in difficult, stressful, and unequitable circumstances can increase an individual’s stress, anxiety, and depression, which are suicide risk factors (Alegría et al., 2018; Alon et al., 2024; Howarth et al., 2020; Orsolini et al., 2020; Sareen et al., 2005). Public health suicide prevention programs are often focused on greater societal factors rather than clinical prevention interventions (e.g., Caine et al., 2018; Decker et al., 2018). For example, mental health suicide prevention interventions primarily include individual psychotherapy implemented after a point of crisis or suicide attempt (Brown & Jager-Hyman, 2014; D’Anci et al., 2019). Despite this, there is a gap in evidence-based public health interventions focused on universal mental health, suicide risk, and protective factors to improve well-being and resilience and decrease suicide-related outcomes for adults.
Another factor that complicates suicide prevention is that current methods of predicting suicidal thoughts and behaviors remain only slightly better than chance (Franklin et al., 2017). Furthermore, the low base rate of suicidal thoughts and behaviors places mathematical constraints on positive predictive value (i.e., the likelihood that a model-identified positive case truly represents the phenomenon of interest) of tested models (Mitchell et al., 2021). This makes accurate prediction at the individual level very difficult, even with highly sensitive screening, stratification, and assessment strategies (Carter & Spittal, 2018). Even modern machine learning and health-system stratification models produce large area-under-the-curve statistics values but low positive predictive values (Belsher et al., 2019; Mitchell et al., 2021). Relying on risk prediction may miss suicide deaths or attempts and increase the burden on healthcare systems via false positive cases.
There are also concerns about current interventions for suicidal thoughts and behaviors, specifically the uniformly small intervention effect sizes (Fox et al., 2020). Suicide interventions are limited in their reliability and ability to reduce suicide attempts or deaths (Fox et al., 2020). No treatment modality meaningfully outperforms another, and the modest effect sizes appear insufficient to counteract the limitations of prediction-based care (Fox et al., 2020). These converging limitations indicate that prediction-based methods do not reliably guide suicide-related clinical decision-making as a stand-alone strategy. Therefore, suicide prevention cannot hinge solely on identifying and treating a narrow “high-risk” group.
Protective factors may also offer insight into how to further bolster suicide prevention efforts (Sher, 2019). Network analyses have revealed that self-esteem and social support had moderate strength centrality, while resilience, self-esteem, access to mental health services, and a positive attitude toward mental health services were inversely related to SI (Holman & Williams, 2022). Additionally, social support was associated with a decreased lifetime suicide attempt within U.S. and United Kingdom (U.K.) samples (Kleiman & Liu, 2013). Although limited, research consistently demonstrates that increasing protective factors may play a key role in suicide prevention efforts.
More specifically, resilience may serve as a protective factor against suicide (Jeong & Noh, 2023; Roy et al., 2007). Resilience can be defined as the process of adapting well in the face of adversity, trauma, tragedy, threats, or significant life stressors (American Psychological Association, 2018). Individuals with high resilience possess several supportive factors and characteristics that reduce the risk of suicidal thoughts and behaviors, including engagement in activities and behaviors that strengthen social support, promote physical health, facilitate awareness of when external support is needed, and foster a sense of meaning in life (Levine, 2003; Sher, 2019). For example, integrating resilience into an intervention group for older adults significantly reduced SI and depressive symptoms compared to a control group (Zhang et al., 2022). However, there has been a lack of suicide prevention research focusing on resilience.
There is also a lack of upstream suicide prevention interventions to decrease psychological suicide risk factors and increase protective factors and resilience (McMahon, 2022). This is despite evidence that reducing psychological risk factors and increasing protective factors and resilience reduce SI and attempts (Elbogen et al., 2020; Sher, 2019; Turecki et al., 2019). Current suicide prevention efforts are disproportionately focused on treatment-oriented approaches, primarily individual psychotherapies delivered after suicide-related outcomes have occurred (Hofstra et al., 2020), rather than on prevention strategies aimed at enhancing well-being and resilience earlier in the risk trajectory (Centers for Disease Control and Prevention [CDC], 2022). This treatment-centric model is constrained by substantial barriers, including limited scalability amid global mental health treatment gaps of approximately 60–80%, poor access to services, clinician burnout, and a limited impact on population-level suicide rates in the United States (Alonso et al., 2018; Coombs et al., 2021; Fox et al., 2020; Hedegaard et al., 2020; McCormack et al., 2018; Thornicroft et al., 2017). Thus, implementing upstream suicide prevention interventions focused on increasing resilience, well-being, and protective factors prior to SI (i.e., prevention interventions) and interventions aimed at reducing the occurrence or reoccurrence of SI and attempts (i.e., treatment interventions; Centers for Disease Control and Prevention [CDC], 2022; Hofstra et al., 2020) may aid in a more holistic approach to suicide prevention.

2. A Stepped Care Approach

One solution to the imbalance between need and available care is to implement stepped care that emphasizes true prevention interventions. Stepped care includes offering different types of interventions based on patients’ needs and preferences (Richards et al., 2012). In addition, stepped care can help address the current disparities in access to care for mental health and suicide prevention (Alvarez et al., 2022; Cook et al., 2019; Mohatt et al., 2021). This could be accomplished by incorporating evidence-based interventions that are easily disseminated to large numbers of people with minimal specialist services (Bower & Gilbody, 2005). Additionally, within this framework, there is greater capacity to provide early intervention and to triage patients to increasingly intensive interventions as needed, thereby facilitating timely, appropriate patient care (Bower et al., 2006). Evidence-based, low-intensity, suicide prevention interventions can also be utilized to target and reduce clinical risk factors for suicide and to increase protective factors and resilience, ultimately reducing SI and suicide attempts across a wider margin of the populace (Ki et al., 2024; Turecki et al., 2019).
Unfortunately, a major barrier to the effective implementation of prevention interventions within a stepped care framework is the lack of easily implementable suicide prevention interventions. One evidence-based, universal intervention that has been implemented in the U.K. to reduce depression, anxiety, and stress, and increase mental well-being and resilience for adults is Stress Control. Thus, we aim to reframe suicide prevention through a stepped-care lens, discussing Stress Control as a low-intensity, scalable, universal prevention intervention to enhance well-being and resilience and reduce suicide risk in the U.S.

3. What Is Prevention?

Prevention interventions for mental health aim to prevent the occurrence or development of disorders by promoting wellness, teaching coping skills, and providing psychoeducation through inclusive, wide-reaching programs (Goldsmith et al., 2002). Specifically, upstream prevention interventions focus on reducing factors that contribute to ill health and aim to prevent the onset of a disorder (McMahon, 2022). At the other end of the intervention spectrum, downstream interventions focus on individual behavioral change and treatments for established disorders (National Collaborating Centre for Determinants of Health, 2014). Although there are examples of upstream suicide prevention intervention efforts (e.g., peer support and group skill-building prevention interventions among United States Air Force [USAF] airmen; Wyman et al., 2020), most suicide prevention interventions focus on downstream interventions (e.g., treatment after suicide-related outcomes; Hofstra et al., 2020).
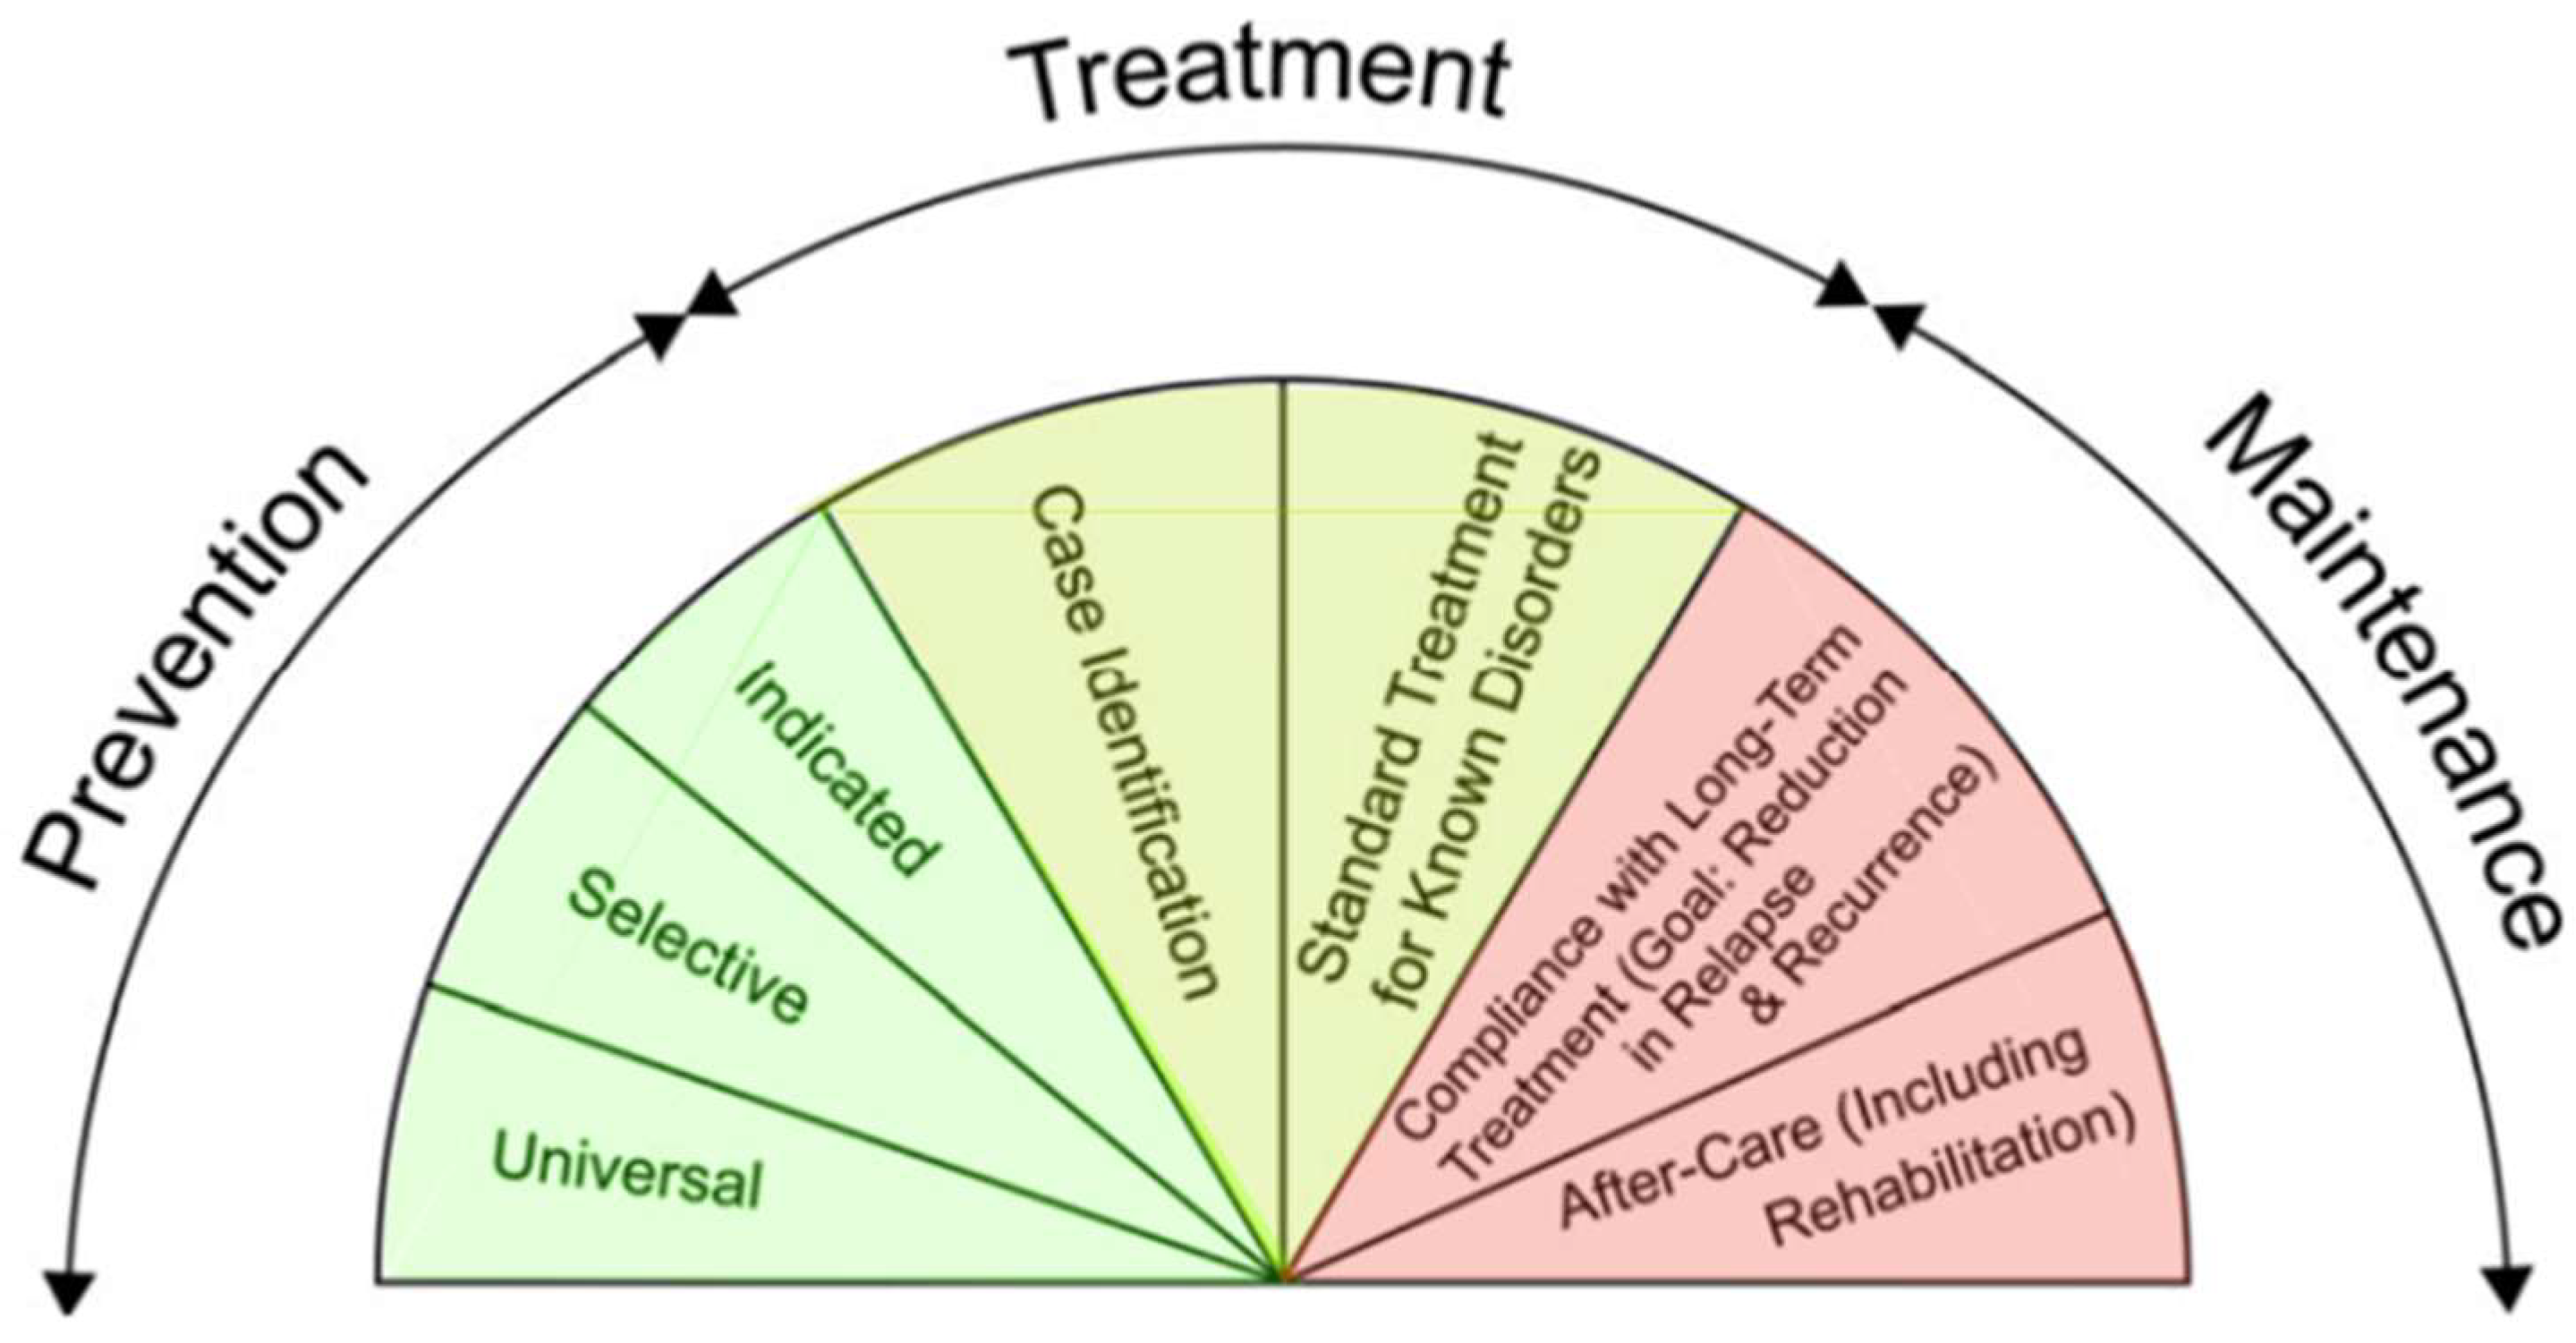
In addition to upstream and downstream interventions, the U.S. Institute of Medicine (IOM, 1994) further defines a spectrum of prevention, treatment, and maintenance interventions (see Figure 1). Prevention is subdivided into universal interventions, selective interventions, and indicated interventions. Treatment includes two subcategories: case identification and standard treatment for the known disorder (i.e., also includes interventions poised to reduce the likelihood of future co-occurring disorders). Maintenance includes compliance with long-term treatment (i.e., reducing relapse and recurrence of disorder) and after-care (i.e., rehabilitation services for the patient).
An example of a similar, successful paradigm shift is evident in cardiovascular disease prevention (Knox et al., 2004; Ramôa-Castro et al., 2017). Cardiovascular research was focused on the prediction of patients with cardiovascular disease who would go on to experience myocardial infarctions and related deaths. Prediction rates mirrored current suicide prediction rates with a stagnation in patient outcomes despite substantial funds dedicated to cardiovascular disease research (Knox et al., 2004). However, a shift from treatment to prevention was key, including upstream and universal prevention interventions that encouraged physical activity, smoking cessation, and healthy diets among healthy individuals (Vogel et al., 2021). These universal prevention efforts successfully reduced myocardial infarction-related deaths and prevented cardiovascular disease in healthy individuals, resulting in a decrease in mortality between 1970 and 1990 (Knox et al., 2004). Following this example, expanding universal and upstream suicide prevention intervention efforts to include individuals who have not yet developed SI is one solution to deficits in risk identification, outcome prediction, and limited access to effective treatments (Coombs et al., 2021; Fox et al., 2020; Franklin et al., 2017).

3.1. Stratified Suicide Screening and Interventions

The Limitations of Screening and Risk Stratification as a Path to Suicide Prevention. Within healthcare settings, identification of suicide risk factors and risk stratification are primary methods for allocating suicide prevention treatment interventions to patients (Large et al., 2017; Large & Ryan, 2014). However, suicide risk screenings often result in clinicians designating patients as “high, medium, or low” risk for suicide, despite screening measures having poor prediction validity of future suicide (e.g., Carter & Spittal, 2018; Large et al., 2017). Targeted (i.e., also indicated/selective) screening serves a purpose like case identification in suicide prevention. Targeted screening is conducted after a patient discloses clinical markers that warrant further evaluation (e.g., SI disclosure; Bryan et al., 2023a). The U.S. Preventive Services Task Force (2023) and current evidence-based suicide prevention recommendations support targeted screening in settings with low base rates of suicide-related outcomes, such as primary care (Bryan et al., 2009, 2022).
Universal screening assesses all patients for SI at every healthcare visit (Goldstein-Grumet & Boudreaux, 2023). A benefit of this approach is the potential to identify individuals at risk who might not be identified through targeted screening (Boudreaux et al., 2016; Cui & Fiske, 2021; De Vylder et al., 2019; Raue et al., 2014). Recent evidence supports the use of universal screening and outreach in higher-risk settings, such as emergency departments and specialty mental health services (Mann et al., 2021). However, there is insufficient evidence to support universal suicide risk screening in low-risk settings (Bryan et al., 2023b; Nestadt et al., 2020; O’Connor et al., 2013). In low-risk settings, universal screening may increase the risk of false positives among patients who are screened as high risk (Bryan et al., 2023b).
Importantly, neither targeted nor universal screenings will increase the identification of suicide risk among patients who do not wish to disclose risk. Up to 50% of patients may choose not to disclose SI or suicide attempts for various reasons, including stigma, potential repercussions (e.g., negative impacts on careers), or confidentiality concerns (Bryan & Morrow, 2011; Calear & Batterham, 2019; Husky et al., 2016; McGillivray et al., 2022; Sheehan et al., 2019).
Finally, suicide risk screenings are only able to identify patients who are already involved in the healthcare system. More than 12% of U.S. residents lack health insurance, and 44% of U.S. adults report difficulty paying for health care (Centers for Disease Control and Prevention [CDC], 2023b; West Health, 2022). Thus, a significant number of individuals may not regularly attend healthcare appointments or engage in indicated treatments due to financial and other barriers (Horwitz et al., 2020; Snow et al., 2019). Although research supports implementing both targeted and universal suicide risk screenings within healthcare systems, a more pressing concern is whether adequate services exist for those at risk (Mongelli et al., 2020). Upstream and universal prevention interventions may address these concerns.
Standard Downstream Treatments for Identified Suicide Risk. Current suicide prevention efforts exist within a stratified model and rely heavily on identification via screening measures and subsequent high-intensity treatment interventions, targeting individual factors (Fox et al., 2020). A significant limitation of psychotherapy treatments is reduced availability or access to mental health services (Coombs et al., 2021; David-Ferdon et al., 2016). Due to limited scalability (i.e., individual- or small-group formats), the number of patients that licensed providers can treat is severely restricted (David-Ferdon et al., 2016). Clinicians (e.g., psychologists, psychiatrists) who are appropriately trained in evidence-based suicide prevention treatments and best practices are even fewer, with wide variability in comfort, avoidance, and perceived self-efficacy amongst providers engaging in evidence-based practices with patients at elevated risk for suicide (Mitchell et al., 2020; Roush et al., 2018; Silva et al., 2016). Moreover, access to treatments is curtailed by barriers, such as stigma, discrimination, distrust of mental health providers, geographic locations (e.g., rural populations), and increasing financial costs for patients (David-Ferdon et al., 2016; Drapalski et al., 2008; Jensen et al., 2020; Rowan et al., 2013; Thornicroft, 2008).
Ultimately, a predominantly downstream, stratified treatment model results in poor access overall, where only a minority of patients receive psychotherapy, and most receive no treatment (Bebbington et al., 2000; Lovell & Richards, 2000). This approach may explain, in part, why suicide prevention has fallen behind other public health problems and evidence-based, downstream treatment interventions, which have had a limited impact on suicide-related outcomes (David-Ferdon et al., 2016; Klonsky et al., 2020).

3.2. Applying a Prevention Framework to Suicide-Related Outcomes: Indicated, Selective, and Universal Prevention Interventions

Indicated prevention interventions for suicide prevention would be designed to target specific individuals who are exhibiting early signs of suicide potential but have not yet experienced SI within the population, enhancing protective psychological factors (e.g., coping and belonging) and resilience, as opposed to reactionary processes (Goldsmith et al., 2002; Pietrzak et al., 2011). In prior prevention interventions, such as the Prevention of Suicide in Primary Elderly Collaborative Trial (PROSPECT), depression care managers acted as a liaison between patients and primary care physicians, monitored treatment adherence, provided psychotherapy for depression when requested, and coordinated specialist referrals (Bruce & Pearson, 1999). This indicated that the prevention intervention was more effective than treatment as usual at preventing SI and reducing hopelessness (Reynolds et al., 2001). Similarly, recent reviews have confirmed the continued benefit of indicated prevention interventions, such as antidepressants, problem-solving-focused interventions, community support initiatives, or interdisciplinary care collaboration, to manage present mental health symptoms before they progress to SI in populations at elevated risk (e.g., adolescents and older adults; Sakashita & Oyama, 2019; Xavier et al., 2019).
Selective prevention interventions would target at-risk groups regardless of their current mental health status, focusing on groups that have a higher likelihood of developing SI and aiming to prevent the onset of suicide-related outcomes among specific subpopulations (e.g., military members; IOM, 1994; Pruitt et al., 2019). Such interventions, such as gatekeeper trainings for community members (i.e., Question, Persuade, Refer [QPR]), emphasize the identification and referral of at-risk individuals to higher levels of care dependent on need, and have shown to minimize subsequent hopelessness and pessimism leading to escalation to suicidal behavior (Sakashita & Oyama, 2019). Another example is the USAF Suicide Prevention Program (AFSPP) delivered to USAF members. AFSPP is a multi-level suicide prevention program (e.g., involves leadership, education, and community preventive services; Knox et al., 2003). Data from 1990 to 2002 showed a reduction in the proportion of suicides each year across the decade, with rate reductions beginning when AFSPP was first fully implemented (Knox et al., 2003). Despite these promising decreases in suicide rates, the Air Force has experienced a recent increase in suicide rates (U.S. Department of Defense, 2020), suggesting that multi-level suicide prevention programs, although efficacious, address suicide risk better for some individuals than others.
Universal suicide prevention interventions would address an entire population (e.g., nation, state, local community) regardless of individual symptoms or risk (IOM, 1994). These prevention programs would be designed to influence everyone, reducing suicide risk by removing barriers to care, enhancing knowledge of suicide prevention techniques, increasing access to help, and strengthening protective processes like social support, resilience, and coping skills (Goldsmith et al., 2002; Sakashita & Oyama, 2019). Importantly, preliminary studies have emphasized protective factors (e.g., social support, resilience) in intervention research aimed at preventing SI and related behaviors by enhancing coping skills for daily stressors (Allen et al., 2022; Antonio et al., 2020). Furthermore, increased social support, adaptive responses to fear, physical fitness, cognitive flexibility, and living in accordance with one’s values are associated with greater resilience, which reduces stress-related disorders and, in turn, suicide risk (Sher, 2019). The Wingman-Connect Program (W-CP), also implemented by the U.S. Air Force, is an example of a universal prevention intervention designed to address the needs of healthy and vulnerable service members simultaneously (Wyman et al., 2022). W-CP provided group trainings focused on protective factors against suicide, including social connectedness, social support, and effective stress management (de Aguiar et al., 2022; Dempsey et al., 2021; Leahy, 2017; Pickering et al., 2018; Rugo et al., 2020; Wyman et al., 2019). Despite its success in decreasing suicide deaths among military personnel, very few contemporary universal suicide prevention interventions designed for a general adult population have been widely implemented or empirically investigated.
Increasing resilience is a proposed mechanism for suicide prevention among those experiencing heightened risk factors to reduce subsequent suicide risk. Resilience-targeted interventions have shown reduced SI and depressive symptoms among older adults compared to a control sample (Zhang et al., 2022). A systematic review found that among 70 studies, resilience was one of the most valuable protective factors for reducing suicidal thoughts and behaviors among older adults (Ki et al., 2024). Introducing resilience-focused interventions throughout community care settings that both reduce risk factors and focus on maintaining well-being throughout life changes has the potential to mitigate the overall frequency of suicidal crises. In principle, any prevention intervention that targets known suicide risk factors, bolsters protective factors, increases suicide resilience, and promotes well-being could be considered a cog in the machine of universal prevention intervention for suicide prevention.
A comprehensive approach to suicide prevention must combine upstream, universal prevention strategies to promote adaptive decision-making, wellness, and resilience among the entire population regardless of risk, selective and indicated prevention strategies supporting those at an increased risk, and treatment strategies designed to support individuals currently in crisis or at high-risk (e.g., active SI, recent attempt; Turecki et al., 2019). By expanding the conceptualization of suicide prevention to include upstream universal interventions, suicide prevention may experience a similar success in patient outcomes that has been seen in cardiovascular disease prevention and other public health efforts. One potential solution is an easily disseminable, pre-packaged, evidence-based program, such as Stress Control.

4. Stress Control

Stress Control was developed as a low-intensity, high-volume intervention to increase access to mental health services in primary care without requiring a provider referral (e.g., J. White, 1995, 1997; J. White & Keenan, 1990). It has been embedded within the U.K.’s National Health Service (NHS) for over 40 years as part of a broader stepped-care model, functioning primarily as a guided self-help intervention that bridges the gap between individual psychotherapy and brief, single-session interventions, thereby reducing strain on the mental healthcare system while still addressing common mental health problems (J. White, 2022; J. White et al., 2008). Stress Control has been adapted for use by students, teachers, and parents in school settings, for online implementation, and has shown to function well within a community-based setting (K. White & White, 2021; J. White, 2017). It is a self-referral, didactic, psychoeducational program designed to be “low contact-high volume” (i.e., one professional to many attendees) to help alleviate provider shortages resulting from the proliferation of individual psychotherapies (David-Ferdon et al., 2016). Specifically, the use of psychoeducation, shown to be an effective evidence-based practice across mental health disorders; (Lukens & McFarlane, 2004) and coping techniques (e.g., diaphragmatic breathing; Hopper et al., 2019) for comorbid common mental health problems mirrors current transdiagnostic treatment models, like the Unified Protocol (UP; Barlow et al., 2016). For example, interventions targeting affective factors rather than disorder-specific symptoms have been effective in individual treatment and group settings, while seamlessly tying into stepped care approaches (Bullis et al., 2015; Ellard et al., 2010; J. White et al., 2008).
Stress Control itself comprises 6 distinct yet interrelated, weekly, 90 min cognitive–behavioral therapy (CBT)-based psychoeducation classes (see the Online Supplementary Materials document and Table 1 for descriptions of each class; J. White, 1997; J. White et al., 2010b). Class sizes can be adjusted to accommodate a wide range of attendees (e.g., 6–160 individuals; Dolan et al., 2021; J. White et al., 2010b), increasing timely access to care and reducing service waitlists. Ideally, classes are offered on a cyclical basis throughout the year (e.g., session 6 is followed by session 1, repeating every 6 weeks); however, this schedule is flexible and dependent on local resources. The program is designed for attendees to complete classes sequentially, but this is not required (J. White et al., 2010b). For example, attendees can join Stress Control at any point in the program sequence, attend missed classes in a subsequent offering of the course, or repeat classes to reinforce their skills.
Given the didactic nature of Stress Control, trainers are not required to be licensed mental health practitioners. For instance, Stress Control has been delivered by nurses (J. White et al., 2010a) and community members (J. White, 2022, personal communication) following a two-day in-person or virtual training provided by Dr. White and his team. This helps alleviate mental health provider shortages and burdens and provides a much-needed influx of evidence-based services in areas with such shortages (Mills et al., 2016).
Stress Control aims to prevent anxiety, depression, and stress, and enhance mental well-being (e.g., coping skills, promoting resilience) in at-risk populations, to decrease symptoms of mild to moderate “emotional disorders”, and to prevent symptom relapse through teaching attendees how to “be their own therapists”. Importantly, Stress Control is not a group therapy as individual care is not provided, and personal disclosure is not as highly emphasized. Furthermore, it is not intended to replace individual psychotherapy. Instead, it is designed as a low-intensity, CBT-based psychoeducation intervention that can be attended alongside other interventions.
In Stress Control, stress is described as a common experience, with a focus on effective coping rather than “curing” stress (e.g., J. White et al., 2010a, 2010b), emphasizing the importance of cultivating resilience-focused strategies rather than eliminating stress altogether. The use of lay terminology is deliberate, aiming to reduce stigma (i.e., a barrier to mental health care) and increase help-seeking (P. W. Corrigan et al., 2014; P. Corrigan, 2004). The use of normalizing language extends throughout the program, with attendees referred to as “students” rather than patients, and “trainers” or “coaches” rather than “therapists” or “clinicians”. This approach has increased attendance and reduced attrition in populations that typically underutilize services and is unique to Stress Control compared to other similar didactic stress-reduction interventions (Hayes et al., 2020).
The acceptability and feasibility of Stress Control have been demonstrated in multiple practice-based studies and a meta-analysis (e.g., Burns et al., 2016; Dolan et al., 2021; Mills et al., 2016). Indeed, Stress Control is typically the sole intervention for approximately 98% of attendees in the U.K., and 66% of attendees preferred Stress Control to individual therapy (J. White et al., 2010b). From 2013 to 2020, 7793 U.K. residents participated in practice-based research for Stress Control (Dolan et al., 2021). Furthermore, a multi-site evaluation of practice data revealed that 4451 individuals attended Stress Control over a 2-year period (2013–2015) across 5 rural health services (Delgadillo et al., 2016). Within this broader sample, 96% of participants highly recommended the treatment, showed a 50% reduction in anxiety and depression, and maintained an attrition rate average of 31% (Burns et al., 2016). These findings demonstrate the broad appeal of Stress Control, supporting its potential in suicide prevention.

5. Stress Control as a Suicide Prevention Intervention

Within a suicide prevention stepped-care framework, Stress Control simultaneously follows the U.S. IOM (1994) framework of prevention, treatment, and maintenance. Specifically, Stress Control would be considered a prevention intervention for someone interested in learning more about mental health and wellness overall (i.e., universal prevention), someone who was experiencing elevated stress (i.e., selective prevention), and someone experiencing SI but before any suicidal behaviors (i.e., indicated prevention). Prevention of an individual transitioning from SI to suicidal behaviors would occur through the reduction in known clinical risk factors for SI and the implementation of known protective factors. Early prevention is especially important, given that greater treatment effectiveness is observed when the disorder is detected early (Chan et al., 2018; Colizzi et al., 2020).
Importantly, Stress Control aims to increase resilience by equipping attendees with knowledge (e.g., definitions of stress, anxiety, and depression) and coping skills (e.g., practices related to mindfulness, physical fitness, sleep hygiene), allowing individuals more effective ways of navigating future stressful life events, thereby reducing suicide risk overall. Reviews of comparable stress-reduction prevention interventions suggest that improvements in common mental health problems and subsequent downstream effects on suicide risk may operate through strengthening said coping resources and shifting cognitive reappraisal about one’s environment away from ruminative processes toward more effective problem-solving styles, both risk factors for suicidal thoughts and behaviors (Brosschot et al., 2006; Franz et al., 2021). Notably, the final Stress Control session explicitly focuses on maintaining gains in well-being and resilience beyond program completion.
Although direct treatment for suicide-related outcomes is the best practice for suicide prevention, timely access to evidence-based care remains a barrier to effective suicide-specific treatment interventions (Labouliere et al., 2021; Mental Health America, 2023; Turpin et al., 2008). Therefore, for individuals with co-morbid SI and depression, for example, without access to suicide-specific treatment interventions, Stress Control would be considered both a proximal treatment for anxiety, depression, and stress and a distal treatment for SI.
There are no studies that directly assess Stress Control’s impact on SI or other suicide-related outcomes. However, Stress Control has been shown to reduce risk (i.e., violence toward self and others), as measured by the 34-item CORE Risk Outcomes Measure (CORE-OM; Evans et al., 2002), a widely used indicator of mental health treatment outcomes in U.K. populations. The CORE-OM risk domain includes items assessing self-directed harm and suicidal cognition (e.g., thoughts of self-harm or being better off dead), as well as harm toward others (e.g., physical violence or intimidation), with studies demonstrating significant pre–post reductions following the 6-week program in community (Cohen’s d = 0.38, p < 0.001) and vulnerable incarcerated samples (Cohen’s d = 0.66, p < 0.001; Evans et al., 2002). Although the evidence base remains limited, these findings suggest that Stress Control may be relevant for suicide prevention while simultaneously addressing common treatment barriers.

6. Current Limitations to Prevention Interventions

Although Stress Control offers considerable scalability and flexibility as a proposed universal upstream suicide prevention intervention, these advantages, like those of other preventive approaches, are accompanied by inherent practical tradeoffs. Stress Control is currently implemented primarily as a universal community-based intervention in the U.K. Such interventions require unique funding sources, infrastructure, and personnel support, which are not often observed in fragmented healthcare delivery systems such as those currently observed in the U.S. Typically, prevention interventions are most successful when implemented within large, organized systems with considerable oversight, heightened compliance among community members, and centralized funding mechanisms. More specifically, the logistics (e.g., setup and operation) of community-based prevention interventions within an inconsistent, limited, and chaotic referral system pose unique obstacles for patients, particularly because the system relies heavily on patients finding and enrolling in programs on their own. Further compounding these challenges, Stress Control and similar programs, despite their broad preventive reach, are not designed to replace clinical treatment pathways; thus, referral to higher levels of stepped care remains necessary. For this reason, in addition to the obstacles mentioned previously, community prevention intervention programs would, at least initially, rely on mental health professionals to implement them, increasing the potential burden on an already overstretched workforce.
Despite the widespread use of Stress Control in the NHS, research examining its effectiveness is somewhat limited and varies in study quality (Burns et al., 2016; Delgadillo et al., 2016; Dolan et al., 2021; Van Daele et al., 2013). For example, Stress Control has primarily been evaluated in practice-based studies, with only two randomized control trials (RCTs) evaluating its effectiveness (i.e., Hayes et al., 2020; Kitchiner et al., 2009; Mills et al., 2016; Wong et al., 2016). Another limitation and area for future direction is the lack of longitudinal studies that assess the effectiveness of regular or multiple-session attendance over months or years (Dolan et al., 2021). Moreover, most studies have been conducted with British patients, limiting generalizability. Although one RCT was conducted in Hong Kong, given the U.K.’s strong influence there until 1997, even this study’s participants may be less representative of a Chinese sample overall (Wong et al., 2016). Given these limitations, it is paramount to increase the number of RCTs on Stress Control and to evaluate its effectiveness across a more diverse range of populations.
Looking at examples from other prevention intervention-based programs, the US AFSPP provides limited insight into potential issues in implementing universal prevention interventions, given its implementation within an organization with clearly defined cultural boundaries, expectations, and a strongly reinforced command hierarchy (Knox et al., 2003). Perhaps the largest limitations in translating results from these examples are a lack of generalizability to the U.S. populace, including how universal upstream approaches will be funded in a healthcare system based in the profitability of targeted intervention. This is made worse, in part, by a lack of prioritization of such research at the federal level.

7. Ways Forward and Proposed Solutions

Overall, expanding suicide prevention research to include healthy and at-risk populations will help to identify and address upstream factors that influence the development of suicide risk, as well as advance suicide prevention research. Although a focus on symptomatic individuals is necessary for acute crisis resolution and stabilization, it is clearly not sufficient given the rise in suicide-related outcomes despite increases in suicide prevention research and funding (Fox et al., 2020; Franklin et al., 2017). Evidence-based treatments are vital for suicide prevention; however, a greater number of evidence-based universal prevention interventions are needed to address mental health suicide risk factors before SI develops.
Further, given that Stress Control is an evidence-based low-intensity intervention shown to effectively reduce common mental health problems, incorporating Stress Control as part of stepped care for suicide prevention could help inform the understanding of a progressive model of healthcare and low-intensity interventions for suicide prevention simultaneously. These results could help to fill a significant gap in the suicide prevention literature and inform later RCTs for low-intensity interventions for suicide prevention. Indeed, experimental comparison of Stress Control to other universal prevention interventions, particularly for adults in a community setting, in decreasing suicide risk factors and increasing resilience could be particularly helpful and fruitful. Thus, research evaluating Stress Control as a universal prevention intervention has the potential to greatly increase understanding in suicide prevention research.
The implementation of Stress Control could help to address barriers to mental health services and greatly reduce the number of treatment-seeking individuals who are currently unable to receive mental health healthcare. Additionally, because Stress Control can simultaneously serve as a prevention, treatment, and maintenance intervention, there is a greater opportunity to intervene at all stages of suicide risk and to extend intervention to individuals in prodromal or nascent states. This alleviates an overreliance on clinical treatment models and greatly expands the margins for successful intervention time points, which could aid suicide prevention overall (David-Ferdon et al., 2016).
Research is needed to examine the direct impact of Stress Control on reducing the development of SI, as well as its impact on suicide-related outcomes and resilience. For our current American Foundation for Suicide Prevention research grant, we are implementing a Stress Control RCT within a U.S. urban community among individuals with SI during the prior month to identify if this upstream, prevention intervention is effective in reducing clinical and psychological risk factors and suicide-related outcomes and bolstering resilience and well-being. We hope to gain a greater understanding of the feasibility of implementing an evidence-based low-intensity intervention within the U.S. Additionally, we hope this project will inform needed solutions to the steady rise in suicide risk factors, suicide-related outcomes, and the lack of available effective mental healthcare services. Additional work in this area will be key to understanding effective community-based suicide prevention interventions.

8. Conclusions

A greater emphasis on earlier, scalable prevention interventions that strengthen resilience to known risk factors may help mitigate risk trajectories, reduce the likelihood of crisis escalation “downstream,” and increase overall well-being. Shifting to “true prevention” interventions could reduce reliance on suicide risk identification and prediction. This remains necessary when providers are placed in a position of determining who is in greater need of services, a symptom of a fragmented U.S. healthcare system.
Further, universal prevention interventions offer a unique advantage in that they can be delivered broadly across populations, engaging individuals at varying levels of suicide risk (e.g., no SI to elevated risk, current SI, or prior attempts) within a single framework, while still engaging in stepped care and traditional intervention treatment pathways when imminent risk is identified. By providing earlier upstream access to evidence-based support, such prevention interventions may also enhance resilience and well-being, shifting the primary intervention target from safety to bettering individual lives (Goldsmith et al., 2002). This is especially salient when considering inequities in current approaches (e.g., cost and availability of individual psychotherapy) in suicide prevention and proactively considering how to address additional risk burden (e.g., stress, anxiety, depression) due to social determinants of mental health (Kirkbride et al., 2024; Na et al., 2025; Pirkis et al., 2024).
Substantial change is still required to realistically implement universal upstream prevention interventions in the U.S. Indeed, more research is needed on the effectiveness of such interventions, aiming to not only reduce suicide but also identify mechanisms to enhance resilience. To mitigate the rising suicide rates in the U.S., we need a paradigm shift, changing how evidence-based low-intensity interventions are delivered to individuals who would otherwise not have access to mental health care services or suicide prevention interventions, as well as expanding the use of upstream, universal suicide prevention interventions.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/bs16020243/s1, We provide descriptions of each Stress Control class in the Online Supplementary Materials document.

Author Contributions

Conceptualization, S.S. and S.M.M.; Methodology, S.S. and S.M.M.; Resources, S.S. and S.M.M. Writing—Original Draft Preparation, S.S., S.M.M., C.M., R.S., and D.R.; Writing—Review & Editing, S.M.M., C.M., S.S., R.S., and D.R.; Supervision, S.S. and S.M.M.; Project Administration, S.S., S.M.M., R.S., and D.R.; Funding Acquisition, S.S. and S.M.M. All authors have read and agreed to the published version of the manuscript.

Funding

Time for this research was supported, in part, by funding from the National Institute of Mental Health (L30 MH120575) and the American Foundation for Suicide Prevention (PRG-1-108-23).

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

No new data were created or analyzed in this study. Data sharing is not applicable to this article.

Acknowledgments

During the preparation of this work, the authors utilized an AI grammar service to provide grammatical guidance for the manuscript. After using this tool/service, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.

Conflicts of Interest

The sponsors had no role in the design, execution, interpretation, or writing of the study. The content is solely the responsibility of the authors and does not necessarily represent the official views of any agency below.

References

  1. Alegría, M., NeMoyer, A., Falgàs Bagué, I., Wang, Y., & Alvarez, K. (2018). Social determinants of mental health: Where we are and where we need to go. Current Psychiatry Reports, 20(11), 95. [Google Scholar] [CrossRef] [Scilit]
  2. Allen, J., Wexler, L., & Rasmus, S. (2022). Protective factors as a unifying framework for strength-based intervention and culturally responsive American Indian and Alaska native suicide prevention. Prevention Science, 23(1), 59–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Alon, N., Macrynikola, N., Jester, D. J., Keshavan, M., Reynolds, C. F., III, Saxena, S., Thomas, M. L., Torous, J., & Jeste, D. V. (2024). Social determinants of mental health in major depressive disorder: Umbrella review of 26 meta-analyses and systematic reviews. Psychiatry Research, 335, 115854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Alonso, J., Liu, Z., Evans-Lacko, S., Sadikova, E., Sampson, N., Chatterji, S., Abdulmalik, J., Aguilar-Gaxiola, S., Al-Hamzawi, A., Andrade, L. H., Bruffaerts, R., Cardoso, G., Cia, A., Florescu, S., de Girolamo, G., Gureje, O., Haro, J. M., He, Y., de Jonge, P., … WHO World Mental Health Survey Collaborators. (2018). Treatment gap for anxiety disorders is global: Results of the world mental health surveys in 21 countries. Depression and Anxiety, 35(3), 195–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Alvarez, K., Polanco-Roman, L., Samuel Breslow, A., & Molock, S. (2022). Structural racism and suicide prevention for ethnoracially minoritized youth: A conceptual framework and illustration across systems. The American Journal of Psychiatry, 179(6), 422–433. [Google Scholar] [CrossRef] [Scilit]
  6. American Psychological Association. (2018). Building your resilience. Available online: https://www.apa.org/topics/resilience (accessed on 28 December 2025).
  7. Antonio, M. C. K., Chung-Do, J. J., Goebert, D. A., Bifulco, K., & Alvarez, A. R. G. (2020). A qualitative evaluation of the impacts of a strength-based and youth-driven approach to suicide prevention in rural and minority communities in Hawai’i. Hawai’i Journal of Health & Social Welfare, 79(Suppl. S1), 96–100. [Google Scholar]
  8. Barlow, D. H., Allen, L. B., & Choate, M. L. (2016). Toward a unified treatment for emotional disorders—Republished article. Behavior Therapy, 47(6), 838–853. [Google Scholar] [CrossRef] [Scilit]
  9. Bebbington, P. E., Meltzer, H., Brugha, T. S., Farrell, M., Jenkins, R., Ceresa, C., & Lewis, G. (2000). Unequal access and unmet need: Neurotic disorders and the use of primary care services. Psychological Medicine, 30(6), 1359–1367. [Google Scholar] [CrossRef] [Scilit]
  10. Belsher, B. E., Smolenski, D. J., Pruitt, L. D., Bush, N. E., Beech, E. H., Workman, D. E., Morgan, R. L., Evatt, D. P., Tucker, J., & Skopp, N. A. (2019). Prediction models for suicide attempts and deaths: A systematic review and simulation. JAMA Psychiatry, 76(6), 642–651. [Google Scholar] [CrossRef] [Scilit]
  11. Boudreaux, E. D., Camargo, C. A., Jr., Arias, S. A., Sullivan, A. F., Allen, M. H., Goldstein, A. B., Manton, A. P., Espinola, J. A., & Miller, I. W. (2016). Improving suicide risk screening and detection in the emergency department. American Journal of Preventive Medicine, 50(4), 445–453. [Google Scholar] [CrossRef] [Scilit]
  12. Bower, P., & Gilbody, S. (2005). Stepped care in psychological therapies: Access, effectiveness and efficiency: Narrative literature review. British Journal of Psychiatry, 186(1), 11–17. [Google Scholar] [CrossRef] [Scilit]
  13. Bower, P., Gilbody, S., & Barkham, M. (2006). Making decisions about patient progress: The application of routine outcome measurement in stepped care psychological therapy services. Primary Care Mental Health, 4(1), 21–28. [Google Scholar]
  14. Brosschot, J. F., Gerin, W., & Thayer, J. F. (2006). The perseverative cognition hypothesis: A review of worry, prolonged stress-related physiological activation, and health. Journal of Psychosomatic Research, 60(2), 113–124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Brown, G. K., & Jager-Hyman, S. (2014). Evidence-based psychotherapies for suicide prevention. American Journal of Preventive Medicine, 47(3), S186–S194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Bruce, M. L., & Pearson, J. L. (1999). Designing an intervention to prevent suicide: PROSPECT (Prevention of Suicide in Primary Care Elderly: Collaborative Trial). Dialogues in Clinical Neuroscience, 1(2), 100–112. [Google Scholar] [CrossRef] [Scilit]
  17. Bryan, C. J., Allen, M. H., Bryan, A. O., Thomsen, C. J., Baker, J. C., & May, A. M. (2023a). Does suicide risk screening improve the identification of primary care patients who will attempt suicide versus depression screening alone? Joint Commission Journal on Quality and Patient Safety, 49(12), 680–688. [Google Scholar] [CrossRef] [Scilit]
  18. Bryan, C. J., Allen, M. H., & Hoge, C. W. (2023b). Weighing the costs and benefits of universal suicide risk screening in primary care: An evidence-based approach. Psychiatric Services, 74(1), 79–81. [Google Scholar] [CrossRef] [Scilit]
  19. Bryan, C. J., Corso, K. A., Neal-Walden, T. A., & Rudd, M. D. (2009). Managing suicide risk in primary care: Practice recommendations for behavioral health consultants. Professional Psychology: Research and Practice, 40(2), 148–155. [Google Scholar] [CrossRef] [Scilit]
  20. Bryan, C. J., & Morrow, C. E. (2011). Circumventing mental health stigma by embracing the warrior culture: Lessons learned from the defender’s edge program. Professional Psychology: Research and Practice, 42(1), 16. [Google Scholar] [CrossRef] [Scilit]
  21. Bryan, C. J., Thomsen, C. J., Bryan, A. O., Baker, J. C., May, A. M., & Allen, M. H. (2022). Scores on the suicide cognitions scale-revised (SCS-R) predict future suicide attempts among primary care patients denying suicide ideation and prior attempts. Journal of Affective Disorders, 313, 21–26. [Google Scholar]
  22. Bullis, J. R., Sauer-Zavala, S., Bentley, K. H., Thompson-Hollands, J., Carl, J. R., & Barlow, D. H. (2015). The unified protocol for transdiagnostic treatment of emotional disorders: Preliminary exploration of effectiveness for group delivery. Behavior Modification, 39(2), 295–321. [Google Scholar] [CrossRef] [Scilit]
  23. Burns, P., Kellett, S., & Donohoe, G. (2016). “Stress Control” as a large group psychoeducational intervention at step 2 of IAPT services: Acceptability of the approach and moderators of effectiveness. Behavioural and Cognitive Psychotherapy, 44(4), 431–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Caine, E. D., Reed, J., Hindman, J., & Quinlan, K. (2018). Comprehensive, integrated approaches to suicide prevention: Practical guidance. Injury Prevention, 24(1), 38–45. [Google Scholar] [CrossRef] [Scilit]
  25. Calear, A. L., & Batterham, P. J. (2019). Suicidal ideation disclosure: Patterns, correlates and outcome. Psychiatry Research, 278, 1–6. [Google Scholar] [CrossRef] [Scilit]
  26. Carter, G., & Spittal, M. J. (2018). Suicide risk assessment: Risk stratification is not accurate enough to be clinically useful and alternative approaches are needed. Crisis: The Journal of Crisis Intervention and Suicide Prevention, 39(4), 229–234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Centers for Disease Control and Prevention [CDC]. (2020). 1999–2018 Wide Ranging Online Data for Epidemiological Research (WONDER), multiple cause of death files [Fact sheet]. National Center for Health Statistics. Available online: http://wonder.cdc.gov/ucd-icd10.html (accessed on 28 December 2025).
  28. Centers for Disease Control and Prevention [CDC]. (2022). Prevalence of depression among adults aged 20 and over: United States, 2013–2016. Available online: https://www.cdc.gov/nchs/products/databriefs/db303.htm (accessed on 28 December 2025).
  29. Centers for Disease Control and Prevention [CDC]. (2023a). Suicide data and statistics [Fact sheet]. National Center for Health Statistics. Available online: https://www.cdc.gov/suicide/facts/data.html?CDC_AAref_Val=https://www.cdc.gov/suicide/suicide-data-statistics.html (accessed on 28 December 2025).
  30. Centers for Disease Control and Prevention [CDC]. (2023b). U.S. uninsured rate dropped 18% during the pandemic [Fact sheet]. Available online: https://www.cdc.gov/nchs/pressroom/releases/20230516.html?CDC_AAref_Val=https://www.cdc.gov/nchs/pressroom/nchs_press_releases/2023/202305.htm (accessed on 28 December 2025).
  31. Chan, S. K. W., Chan, S. W. Y., Pang, H. H., Yan, K. K., Hui, C. L. M., Chang, W. C., Lee, E. H. M., & Chen, E. Y. H. (2018). Association of an early intervention service for psychosis with suicide rate among patients with first-episode schizophrenia-spectrum disorders. JAMA Psychiatry, 75(5), 458–464. [Google Scholar] [CrossRef] [Scilit]
  32. Colizzi, M., Lasalvia, A., & Ruggeri, M. (2020). Prevention and early intervention in youth mental health: Is it time for a multidisciplinary and trans-diagnostic model for care? International Journal of Mental Health Systems, 14(1), 23. [Google Scholar] [CrossRef] [Scilit]
  33. Cook, B. L., Hou, S. S.-Y., Lee-Tauler, S. Y., Progovac, A. M., Samson, F., & Sanchez, M. J. (2019). A review of mental health and mental health care disparities research: 2011–2014. Medical Care Research and Review, 76(6), 683–710. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Coombs, N. C., Meriwether, W. E., Caringi, J., & Newcomer, S. R. (2021). Barriers to healthcare access among U.S. adults with mental health challenges: A population-based study. SSM—Population Health, 15, 100847. [Google Scholar] [CrossRef] [Scilit]
  35. Corrigan, P. (2004). How stigma interferes with mental health care. American Psychologist, 59(7), 614–625. [Google Scholar] [CrossRef] [Scilit]
  36. Corrigan, P. W., Druss, B. G., & Perlick, D. A. (2014). The impact of mental illness stigma on seeking and participating in mental health care. Psychological Science in the Public Interest, 15(2), 37–70. [Google Scholar] [CrossRef] [Scilit]
  37. Cui, R., & Fiske, A. (2021). Gender differences in male depression and suicide risk. Violence and Gender, 8(2), 80–84. [Google Scholar] [CrossRef] [Scilit]
  38. D’Anci, K. E., Uhl, S., Giradi, G., & Martin, C. (2019). Treatments for the prevention and management of suicide. Annals of Internal Medicine, 171(5), 334–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. David-Ferdon, C., Crosby, A. E., Caine, E. D., Hindman, J., Reed, J., & Iskander, J. (2016). CDC grand rounds: Preventing suicide through a comprehensive public health approach. Morbidity and Mortality Weekly Report, 65(34), 894–897. [Google Scholar] [CrossRef] [Scilit]
  40. de Aguiar, K. R., Bilhalva, J. B., Cabelleira, M. D., Guimarães, G. O., Madureira, T., Agako, A., de Souza, M. S., & Souza, L. D. (2022). The impact of mindfulness on suicidal behavior: A systematic review. Trends in Psychiatry and Psychotherapy, 44, e20210316. [Google Scholar] [CrossRef] [Scilit]
  41. Decker, M. R., Wilcox, H. C., Holliday, C. N., & Webster, D. W. (2018). An integrated public health approach to interpersonal violence and suicide prevention and response. Public Health Reports®, 133(Suppl. S1), 65S–79S. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Delgadillo, J., Kellett, S., Ali, S., McMillan, D., Barkham, M., Saxon, D., Donohoe, G., Stonebank, H., Mullaney, S., & Eschoe, P. (2016). A multi-service practice research network study of large group psychoeducational cognitive behavioral therapy. Behaviour Research and Therapy, 87, 155–161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Dempsey, C. L., Benedek, D. M., Nock, M. K., Zuromski, K. L., Brent, D. A., Ao, J., Aliaga, P. A., Heeringa, S. G., Kessler, R. C., Stein, M. B., & Ursano, R. J. (2021). Social closeness and support are associated with lower risk of suicide among U.S. Army Soldiers. Suicide and Life-Threatening Behavior, 51(5), 940–954. [Google Scholar] [CrossRef] [Scilit]
  44. De Vylder, J. E., Ryan, T. C., Cwik, M., Wilson, M. E., Jay, S., Nestadt, P. S., Goldstein, M., & Wilcox, H. C. (2019). Assessment of selective and universal screening for suicide risk in a pediatric emergency department. JAMA Network Open, 2(10), e2014070. [Google Scholar] [CrossRef] [Scilit]
  45. Dolan, N., Simmonds-Buckley, M., Kellett, S., Siddell, E., & Delgadillo, J. (2021). Effectiveness of stress control large group psychoeducation for anxiety and depression: Systematic review and meta-analysis. British Journal of Clinical Psychology, 60(3), 375–399. [Google Scholar] [CrossRef] [Scilit]
  46. Drapalski, A. L., Milford, J., Goldberg, R. W., Brown, C. H., & Dixon, L. B. (2008). Perceived barriers to medical care and mental health care among veterans with serious mental illness. Psychiatric Services, 59(8), 921–924. [Google Scholar] [CrossRef]
  47. Elbogen, E. B., Molloy, K., Wagner, H. R., Kimbrel, N. A., Beckham, J. C., Van Male, L., Leinbach, J., & Bradford, D. W. (2020). Psychosocial protective factors and suicidal ideation: Results from a national longitudinal study of veterans. Journal of Affective Disorders, 260, 703–709. [Google Scholar] [CrossRef] [Scilit]
  48. Ellard, K. K., Fairholme, C. P., Boisseau, C. L., Farchione, T. J., & Barlow, D. H. (2010). Unified protocol for the transdiagnostic treatment of emotional disorders: Protocol development and initial outcome data. Cognitive and Behavioral Practice, 17(1), 88–101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Evans, C., Connell, J., Barkham, M., Margison, F., McGrath, G., Mellor-Clark, J., & Audin, K. (2002). Towards a standardised brief outcome measure: Psychometric properties and utility of the CORE-OM. British Journal of Psychiatry, 180(1), 51–60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Fox, K. R., Huang, X., Guzmán, E. M., Funsch, K. M., Cha, C. B., Ribeiro, J. D., & Franklin, J. C. (2020). Interventions for suicide and self-injury: A meta-analysis of randomized controlled trials across nearly 50 years of research. Psychological Bulletin, 146(12), 1117–1145. [Google Scholar] [CrossRef] [Scilit]
  51. Franklin, J. C., Ribeiro, J. D., Fox, K. R., Bentley, K. H., Kleiman, E. M., Huang, X., Musacchio, K. M., Jaroszewski, A. C., Chang, B. P., & Nock, M. K. (2017). Risk factors for suicidal thoughts and behaviors: A meta-analysis of 50 years of research. Psychological Bulletin, 143(2), 187–232. [Google Scholar] [CrossRef] [Scilit]
  52. Franz, P. J., Kleiman, E. M., & Nock, M. K. (2021). Reappraisal and suppression each moderate the association between stress and suicidal ideation: Preliminary evidence from a daily diary study. Cognitive Therapy and Research, 45, 1120–1127. [Google Scholar] [CrossRef] [Scilit]
  53. Goldsmith, S. K., Pellmar, T. C., Kleinman, A. M., & Bunney, W. E. (Eds.). (2002). Reducing suicide: A national imperative. In Institute of Medicine (US) Committee on pathophysiology and prevention of adolescent and adult suicide. National Academies Press (US). [Google Scholar]
  54. Goldstein-Grumet, J., & Boudreaux, E. D. (2023). Universal suicide screening is feasible and necessary to reduce suicide. Psychiatric Services, 74(1), 81–83. [Google Scholar] [CrossRef]
  55. Hayes, J., Crowley, R., O’Brien, Y., Hannon, G., Hennessey, E., O’Connell, L., Twomey, D., Berry, D., Harrington, J., & McCarthy, P. (2020). The impact of a Stress Control course delivered in partnership with a sports organisation on mental health outcomes in a general population. The Cognitive Behaviour Therapist, 13, 47. [Google Scholar] [CrossRef] [Scilit]
  56. Hedegaard, H., Curtin, S. C., & Warner, M. (2020). Increase in suicide mortality in the United States, 1999–2018 (pp. 1–8), NCHS Data Brief No. 362. CDC. [CrossRef] [Scilit]
  57. Hofstra, E., Van Nieuwenhuizen, C., Bakker, M., Özgül, D., Elfeddali, I., de Jong, S. J., & van der Feltz-Cornelis, C. M. (2020). Effectiveness of suicide prevention interventions: A systematic review and meta-analysis. General Hospital Psychiatry, 63, 127–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Holman, M. S., & Williams, M. N. (2022). Suicide risk and protective factors: A network approach. Archives of Suicide Research, 26(1), 137–154. [Google Scholar] [CrossRef] [Scilit]
  59. Hopper, S. I., Murray, S. L., Ferrara, L. R., & Singleton, J. K. (2019). Effectiveness of diaphragmatic breathing for reducing physiological and psychological stress in adults: A quantitative systematic review. JBI Database of Systematic Reviews and Implementation Reports, 17(9), 1855–1876. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  60. Horwitz, A. G., McGuire, T., Busby, D. R., Eisenberg, D., Zheng, K., Pistorello, J., Albucher, R., Coryell, W., & King, C. A. (2020). Sociodemographic differences in barriers to mental health care among college students at elevated suicide risk. Journal of Affective Disorders, 271, 123–130. [Google Scholar] [CrossRef] [Scilit]
  61. Howarth, E. J., O’Connor, D. B., Panagioti, M., Hodkinson, A., Wilding, S., & Johnson, J. (2020). Are stressful life events prospectively associated with increased suicidal ideation and behaviour? A systematic review and meta-analysis. Journal of Affective Disorders, 266, 731–742. [Google Scholar] [CrossRef] [Scilit]
  62. Husky, M. M., Zablith, I., Alvarez Fernandez, V., & Kovess-Masfety, V. (2016). Factors associated with suicidal ideation disclosure: Results from a large population-based study. Journal of Affective Disorders, 205, 36–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Institute of Medicine [IOM] Committee on Prevention of Mental Disorders. (1994). Reducing risks for mental disorders: Frontiers for preventive intervention research (P. J. Mrazek, & R. J. Haggerty, Eds.). National Academies Press. [Google Scholar]
  64. Jensen, E. J., Wieling, E., & Mendenhall, T. (2020). A phenomenological study of clinicians’ perspectives on barriers to rural mental health care. Journal of Rural Mental Health, 44(1), 51–61. [Google Scholar] [CrossRef] [Scilit]
  65. Jeong, H., & Noh, H. (2023). Resilience as a protective factor in older adult suicide: A rapid review. Journal of Gerontological Social Work, 66(8), 1005–1018. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Ki, M., Lapierre, S., Gim, B., Hwang, M., Kang, M., Dargis, L., Jung, M., Koh, E. J., & Mishara, B. (2024). A systematic review of psychosocial protective factors against suicide and suicidality among older adults. International Psychogeriatrics, 36(5), 346–370. [Google Scholar] [CrossRef] [Scilit]
  67. Kirkbride, J. B., Anglin, D. M., Colman, I., Dykxhoorn, J., Jones, P. B., Patalay, P., Pitman, A., Soneson, E., Steare, T., Wright, T., & Griffiths, S. L. (2024). The social determinants of mental health and disorder: Evidence, prevention and recommendations. World Psychiatry, 23(1), 58–90. [Google Scholar] [CrossRef] [Scilit]
  68. Kitchiner, N. J., Edwards, D., Wood, S., Sainsbury, S., Hewin, P., Burnard, P., & Bisson, J. I. (2009). A randomized controlled trial comparing an adult education class using cognitive behavioural therapy (“stress control”), anxiety management group treatment and a waiting list for anxiety disorders. Journal of Mental Health, 18, 307–315. [Google Scholar] [CrossRef] [Scilit]
  69. Kleiman, E. M., & Liu, R. T. (2013). Social support as a protective factor in suicide: Findings from two nationally representative samples. Journal of Affective Disorders, 150(2), 540–545. [Google Scholar] [CrossRef] [Scilit]
  70. Klonsky, E. D., Pachkowski, M. C., & Shahnaz, A. (2020). Understanding suicide to prevent suicide. The Behavior Therapist, 43, 339–343. [Google Scholar]
  71. Knox, K. L., Conwell, Y., & Caine, E. D. (2004). If suicide is a public health problem, what are we doing to prevent it? American Journal of Public Health, 94(1), 37–45. [Google Scholar] [CrossRef] [Scilit]
  72. Knox, K. L., Litts, D. A., Talcott, G. W., Feig, J. C., & Caine, E. D. (2003). Risk of suicide and related adverse outcomes after exposure to a suicide prevention programme in the US Air Force: Cohort study. BMJ (Clinical Research Edition), 327(7428), 1376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  73. Labouliere, C. D., Green, K. L., Vasan, P., Cummings, A., Layman, D., Kammer, J., Rahman, M., Brown, G. K., Finnerty, M., & Stanley, B. (2021). Is the outpatient mental health workforce ready to save lives? Suicide prevention training, knowledge, self-efficacy, and clinical practices prior to the implementation of a statewide suicide prevention initiative. Suicide & Life-Threatening Behavior, 51(2), 325–333. [Google Scholar] [CrossRef] [Scilit]
  74. Large, M. M., & Ryan, C. J. (2014). Suicide risk categorisation of psychiatric inpatients: What it might mean and why it is of no use. Australasian Psychiatry, 22(4), 390–392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  75. Large, M. M., Ryan, C. J., Carter, G., & Kapur, N. (2017). Can we usefully stratify patients according to suicide risk? BMJ, 359, j4627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  76. Leahy, R. L. (2017). Cognitive therapy techniques: A practitioner’s guide. Guilford Publications. [Google Scholar]
  77. Levine, S. (2003). Psychological and social aspects of resilience: A synthesis of risks and resources. Dialogues in Clinical Neuroscience, 5(3), 273–280. [Google Scholar] [CrossRef] [Scilit]
  78. Lovell, K., & Richards, D. (2000). Multiple access points and levels of entry (MAPLE): Ensuring choice, accessibility and equity for CBT services. Behavioural and Cognitive Psychotherapy, 28(4), 379–391. [Google Scholar] [CrossRef] [Scilit]
  79. Lukens, E. P., & McFarlane, W. R. (2004). Psychoeducation as evidence-based practice: Considerations for practice, research, and policy. Brief Treatment and Crisis Intervention, 4(3), 205–225. [Google Scholar] [CrossRef] [Scilit]
  80. Mann, J. J., Michel, C. A., & Auerbach, R. P. (2021). Improving suicide prevention through evidence-based strategies: A systematic review. American Journal of Psychiatry, 178(7), 611–624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  81. Martínez-Alés, G., Jiang, T., Keyes, K. M., & Gradus, J. L. (2022). The recent rise of suicide mortality in the United States. Annual Review of Public Health, 43(1), 99–116. [Google Scholar] [CrossRef] [Scilit]
  82. McCormack, H. M., MacIntyre, T. E., O’Shea, D., Herring, M. P., & Campbell, M. J. (2018). The prevalence and cause(s) of burnout among applied psychologists: A systematic review. Frontiers in Psychology, 9, 1897. [Google Scholar] [CrossRef] [Scilit]
  83. McGillivray, L., Rheinberger, D., Wang, J., Burnett, A., & Torok, M. (2022). Non-disclosing youth: A cross sectional study to understand why young people do not disclose suicidal thoughts to their mental health professional. BMC Psychiatry, 22(1), 3. [Google Scholar] [CrossRef] [Scilit]
  84. McMahon, N. E. (2022). Framing action to reduce health inequalities: What is argued for through use of the ‘upstream–downstream’ metaphor? Journal of Public Health, 44(3), 671–678. [Google Scholar] [CrossRef] [Scilit]
  85. Mental Health America. (2023). 2022 key findings [Fact sheet]. Available online: https://www.mhanational.org/issues/state-mental-health-america (accessed on 28 December 2025).
  86. Mills, R., Mowlds, W., Dyer, K., Corr, P., & Kavanagh, M. (2016). Responding to mental health statutory drivers: Experience of a low intensity cognitive behavioural therapy programme. Irish Journal of Psychological Medicine, 33(4), 217–224. [Google Scholar] [CrossRef] [Scilit]
  87. Mitchell, S. M., Cero, I., Littlefield, A. K., & Brown, S. L. (2021). Using categorical data analyses in suicide research: Considering clinical utility and practicality. Suicide & Life-Threatening Behavior, 51(1), 76–87. [Google Scholar] [CrossRef] [Scilit]
  88. Mitchell, S. M., Taylor, N. J., Jahn, D. R., Roush, J. F., Brown, S. L., Quinnett, P., & Ries, R. (2020). Suicide-related training, self-efficacy, and mental health care providers’ reactions toward suicidal individuals. Crisis: The Journal of Crisis Intervention and Suicide Prevention, 41(5), 359–366. [Google Scholar] [CrossRef] [Scilit]
  89. Mohatt, N. V., Kreisel, C. J., Hoffberg, A. S., & Beehler, S. J. (2021). A systematic review of factors impacting suicide risk among rural adults in the United States. The Journal of Rural Health: Official Journal of the American Rural Health Association and the National Rural Health Care Association, 37(3), 565–575. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  90. Mongelli, F., Georgakopoulos, P., & Pato, M. T. (2020). Challenges and opportunities to meet the mental health needs of underserved and disenfranchised populations in the United States. Focus, 18(1), 16–24. [Google Scholar] [CrossRef] [Scilit]
  91. Na, P. J., Shin, J., Kwak, H. R., Lee, J., Jester, D. J., Bandara, P., Kim, J. Y., Moutier, C. Y., Pietrzak, R. H., Oquendo, M. A., & Jeste, D. V. (2025). Social determinants of health and suicide-related outcomes: A review of meta-analyses. JAMA Psychiatry, 82(4), 337–346. [Google Scholar] [CrossRef] [Scilit]
  92. Naghavi, M. (2019). Global, regional, and national burden of suicide mortality 1990 to 2016: Systematic analysis for the Global Burden of Disease Study 2016. BMJ, 364, l94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  93. National Collaborating Centre for Determinants of Health. (2014). Let’s talk: Moving upstream. National Collaborating Centre for Determinants of Health, St. Francis Xavier University. Available online: https://nccdh.ca/resources/entry/lets-talk-moving-upstream (accessed on 28 December 2025).
  94. National Institute of Mental Health [NIMH]. (2022). Suicide. Available online: https://www.nimh.nih.gov/health/statistics/suicide (accessed on 28 December 2025).
  95. Nestadt, P. S., Triplett, P., Mojtabai, R., & Berman, A. L. (2020). Universal screening may not prevent suicide. General Hospital Psychiatry, 63, 14–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  96. O’Connor, E., Gaynes, B. N., Burda, B. U., Soh, C., & Whitlock, E. P. (2013). Screening for and treatment of suicide risk relevant to primary care: A systematic review for the US Preventive Services Task Force. Annals of Internal Medicine, 158(10), 741–754. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  97. Orsolini, L., Latini, R., Pompili, M., Serafini, G., Volpe, U., Vellante, F., Fornaro, M., Valchera, A., Tomasetti, C., Fraticelli, S., Alessandrini, M., La Rovere, R., Trotta, S., Martinotti, G., Di Giannantonio, M., & De Berardis, D. (2020). Understanding the complex of suicide in depression: From research to clinics. Psychiatry Investigation, 17(3), 207–221. [Google Scholar] [CrossRef] [Scilit]
  98. Pickering, T. A., Wyman, P. A., Schmeelk-Cone, K., Hartley, C., Valente, T. W., Pisani, A. R., Rulison, K. L., Brown, C. H., & LoMurray, M. (2018). Diffusion of a peer-led suicide preventive intervention through school-based student peer and adult networks. Frontiers in Psychiatry, 9, 598. [Google Scholar] [CrossRef] [Scilit]
  99. Pietrzak, R. H., Russo, A. R., Ling, Q., & Southwick, S. M. (2011). Suicidal ideation in treatment-seeking veterans of operations enduring freedom and Iraqi freedom: The role of coping strategies, resilience, and social support. Journal of Psychiatric Research, 45(6), 720–726. [Google Scholar] [CrossRef] [Scilit]
  100. Pirkis, J., Dandona, R., Silverman, M., Khan, M., & Hawton, K. (2024). Preventing suicide: A public health approach to a global problem. The Lancet Public Health, 9(10), e787–e795. [Google Scholar] [CrossRef] [Scilit]
  101. Pruitt, L. D., Smolenski, D. J., Bush, N. E., Tucker, J., Issa, F., Hoyt, T. V., & Reger, M. A. (2019). Suicide in the military: Understanding rates and risk factors across the United States’ Armed Forces. Military Medicine, 184(Suppl. S1), 432–437. [Google Scholar] [CrossRef] [Scilit]
  102. Ramôa-Castro, A., Oliveira, N. L., Ribeiro, F., & Oliveira, J. (2017). Impact of educational interventions on primary prevention of cardiovascular disease: A systematic review with a focus on physical activity. European Journal of General Practice, 23(1), 59–68. [Google Scholar] [CrossRef] [Scilit]
  103. Raue, P. J., Ghesquiere, A. R., & Bruce, M. L. (2014). Suicide risk in primary care: Identification and management in older adults. Current Psychiatry Reports, 16(9), 466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  104. Reynolds, C. F., III, Degenholtz, H., Parker, L. S., Schulberg, H. C., Mulsant, B. H., Post, E., & Rollman, B. (2001). Treatment as usual (TAU) control practices in the PROSPECT study: Managing the interaction and tension between research design and ethics. International Journal of Geriatric Psychiatry, 16(6), 602–608. [Google Scholar] [CrossRef] [Scilit]
  105. Richards, D. A., Bower, P., Pagel, C., Weaver, A., Utley, M., Cape, J., Pilling, S., Lovell, K., Gilbody, S., Leibowitz, J., Owens, L., Paxton, R., Hennessy, S., Simpson, A., Gallivan, S., Tomson, D., & Vasilakis, C. (2012). Delivering stepped care: An analysis of implementation in routine practice. Implementation Science, 7(1), 3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  106. Roush, J. F., Brown, S. L., Jahn, D. R., Mitchell, S. M., Taylor, N. J., Quinnett, P., & Ries, R. (2018). Mental health professionals’ suicide risk assessment and management practices: The impact of fear of suicide-related outcomes and comfort working with suicidal individuals. Crisis: The Journal of Crisis Intervention and Suicide Prevention, 39, 55–64. [Google Scholar] [CrossRef] [Scilit]
  107. Rowan, K., McAlpine, D. D., & Blewett, L. A. (2013). Access and cost barriers to mental health care, by insurance status, 1999–2010. Health Affairs, 32(10), 1723–1730. [Google Scholar] [CrossRef] [Scilit]
  108. Roy, A., Sarchiapone, M., & Carli, V. (2007). Low resilience in suicide attempters. Archives of Suicide Research, 11(3), 265–269. [Google Scholar] [CrossRef] [Scilit]
  109. Rugo, K. F., Leifker, F. R., Drake-Brooks, M. M., Snell, M. B., Bryan, C. J., & Bryan, A. O. (2020). Unit cohesion and social support as protective factors against suicide risk and depression among National Guard Service members. Journal of Social and Clinical Psychology, 39(3), 214–228. [Google Scholar] [CrossRef] [Scilit]
  110. Sakashita, T., & Oyama, H. (2019). Developing a hypothetical model for suicide progression in older adults with universal, selective, and indicated prevention strategies. Frontiers in Psychiatry, 10, 161. [Google Scholar] [CrossRef] [Scilit]
  111. Sareen, J., Cox, B. J., Afifi, T. O., De Graaf, R., Asmundson, G. J., Ten Have, M., & Stein, M. B. (2005). Anxiety disorders and risk for suicidal ideation and suicide attempts: A population-based longitudinal study of adults. Archives of General Psychiatry, 62(11), 1249–1257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  112. Sheehan, L., Oexle, N., Armas, S. A., Wan, H. T., Bushman, M., Glover, L., & Lewy, S. A. (2019). Benefits and risks of suicide disclosure. Social Science & Medicine, 223, 16–23. [Google Scholar] [CrossRef] [Scilit]
  113. Sher, L. (2019). Resilience as a focus of suicide research and prevention. Acta Psychiatrica Scandinavica, 140(2), 169–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  114. Silva, C., Smith, A. R., Dodd, D. R., Covington, D. W., & Joiner, T. E. (2016). Suicide-related knowledge and confidence among behavioral health care staff in seven states. Psychiatric Services, 67(11), 1240–1245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  115. Snow, A., Cerel, J., Loeffler, D. N., & Flaherty, C. (2019). Barriers to mental health care for transgender and gender-nonconforming adults: A systematic literature review. Health & Social Work, 44(3), 149–155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  116. Thornicroft, G. (2008). Stigma and discrimination limit access to mental health care. Epidemiology and Psychiatric Sciences, 17(1), 14–19. [Google Scholar] [CrossRef] [Scilit]
  117. Thornicroft, G., Chatterji, S., Evans-Lacko, S., Gruber, M., Sampson, N., Aguilar-Gaxiola, S., Al-Hamzawi, A., Alonso, J., Andrade, L., Borges, G., Bruffaerts, R., Bunting, B., de Almeida, J. M., Florescu, S., de Girolamo, G., Gureje, O., Haro, J. M., He, Y., Hinkov, H., … Kessler, R. C. (2017). Undertreatment of people with major depressive disorderin 21 countries. The British Journal of Psychiatry, 210(2), 119–124. [Google Scholar] [CrossRef] [Scilit]
  118. Turecki, G., Brent, D. A., Gunnell, D., O’Connor, R. C., Oquendo, M. A., Pirkis, J., & Stanley, B. H. (2019). Suicide and suicide risk. Nature Reviews Disease Primers, 5(1), 74. [Google Scholar] [CrossRef] [Scilit]
  119. Turpin, G., Richards, D., Hope, R., & Duffy, R. (2008). Improving access to psychological therapies: A national initiative to ensure the delivery of high quality evidence-based therapies. Papeles del Psicólogo, 29(3), 271–280. [Google Scholar]
  120. U.S. Department of Defense. (2020). Annual suicide report. Available online: https://www.dspo.mil/Portals/113/Documents/CY20%20Suicide%20Report/CY%202020%20Annual%20Suicide%20Report.pdf?ver=0OwlvDd-PJuA-igow5fBFA%3D%3D (accessed on 28 December 2025).
  121. U.S. Preventive Services Task Force. (2023). Final recommendation statement: Screening for depression and suicide risk in adults. USPSTF. Available online: https://www.uspreventiveservicestaskforce.org/uspstf/recommendation/screening-depression-suicide-risk-adults (accessed on 28 December 2025).
  122. Van Daele, T., Van Audenhove, C., Vansteenwegen, D., Hermans, D., & Van den Bergh, O. (2013). Effectiveness of a six-session stress reduction program for groups. Mental Health & Prevention, 1(1), 19–25. [Google Scholar]
  123. Vogel, B., Acevedo, M., Appelman, Y., Bairey Merz, C. N., Chieffo, A., Figtree, G. A., Guerrero, M., Kunadian, V., Lam, C. S. P., Maas, A. H. E. M., Mihailidou, A. S., Olszanecka, A., Poole, J. E., Saldarriaga, C., Saw, J., Zühlke, L., & Mehran, R. (2021). The Lancet women and cardiovascular disease commission: Reducing the global burden by 2030. Lancet, 397(10292), 2385–2438. [Google Scholar] [CrossRef] [Scilit]
  124. West Health. (2022). 112 million Americans struggle to afford healthcare [Fact sheet]. Available online: https://www.westhealth.org/press-release/112-million-americans-struggle-to-afford-healthcare/#:~:text=WASHINGTON%2C%20D.C.%20%E2%80%94%20Mar.,is%20not%20worth%20the%20cost (accessed on 28 December 2025).
  125. White, J. (1995). An analysis of components in large group didactic therapy: “Stress Control”. Clinical Psychology Forum, 76, 11–13. [Google Scholar] [CrossRef] [Scilit]
  126. White, J. (1997). “Stress control” large group therapy: Implications for managed care systems. Depression and Anxiety, 5, 43–45. [Google Scholar] [CrossRef] [Scilit]
  127. White, J. (2017). Stress control: A mind, body, life approach to boosting your well-being. Hachette UK. [Google Scholar]
  128. White, J. (2022). Personal communication.
  129. White, J., Bennett-Levy, J., Christensen, H., & Farrand, P. (2010a). The STEPS model: A high-volume, multi-level, multi-purpose approach to address common mental health problems. In J. Bennett-Levy, D. Richards, P. Farrand, H. Christensen, K. Griffiths, D. Kavanagh, B. Klein, M. A. Lau, J. Proudfoot, L. Ritterband, J. White, & C. Williams (Eds.), Oxford guide to low intensity CBT interventions (pp. 35–52). Oxford University Press. [Google Scholar]
  130. White, J., Bennett-Levy, J., Richards, D., Farrand, P., Christensen, H., Griffiths, K., Kavanagh, D., Klein, B., Lau, M., & Proudfoot, J. (2010b). Large group didactic CBT classes for common mental health problems. In J. Bennett-Levy, D. Richards, P. Farrand, H. Christensen, K. Griffiths, D. Kavanagh, B. Klein, M. A. Lau, J. Proudfoot, L. Ritterband, J. White, & C. Williams (Eds.), Oxford guide to low intensity CBT interventions (pp. 313–321). Oxford University Press. [Google Scholar]
  131. White, J., Joice, A., Petrie, S., Johnston, S., Gilroy, D., Hutton, P., & Hynes, N. (2008). STEPS: Going beyond the tip of the iceberg. A multi-level, multipurpose approach to common mental health problems. Journal of Public Mental Health, 7(1), 42–50. [Google Scholar] [CrossRef] [Scilit]
  132. White, J., & Keenan, M. (1990). Stress control: A pilot study of large group therapy for generalized anxiety disorder. Behavioural and Cognitive Psychotherapy, 18, 143–146. [Google Scholar] [CrossRef] [Scilit]
  133. White, K., & White, J. (2021). Getting online quickly in the first COVID-19 lockdown: ‘Stress Control at Home’. Clinical Psychology Forum, 1, 48–52. [Google Scholar] [CrossRef] [Scilit]
  134. Wong, S. Y. S., Yip, B. H. K., Mak, W. W. S., Mercer, S., Cheung, E. Y. L., Ling, C. Y. M., Lui, W. W. S., Tang, W. K., Lo, H. H. M., Wu, J. C. Y., Lee, T. M. C., Gao, T., Griffiths, S. M., Chan, P. H. S., & Ma, H. S. W. (2016). Mindfulness-based cognitive therapy v. group psychoeducation for people with generalised anxiety disorder: Randomised controlled trial. The British Journal of Psychiatry, 209(1), 68–75. [Google Scholar] [CrossRef] [Scilit]
  135. World Health Organization [WHO]. (2023). Suicide prevention [Fact sheet]. Available online: https://www.who.int/health-topics/suicide#tab=tab_1 (accessed on 28 December 2025).
  136. Wyman, P. A., Pickering, T. A., Pisani, A. R., Cero, I., Yates, B., Schmeelk-Cone, K., Hendricks Brown, C., Gibbons, R. D., Simonson, J., & Pflanz, S. E. (2022). Wingman-connect program increases social integration for air force personnel at elevated suicide risk: Social network analysis of a cluster RCT. Social Science & Medicine, 296, 114737. [Google Scholar] [CrossRef] [Scilit]
  137. Wyman, P. A., Pickering, T. A., Pisani, A. R., Rulison, K., Schmeelk-Cone, K., Hartley, C., Gould, M., Caine, E. D., LoMurray, M., Brown, C. H., & Valente, T. W. (2019). Peer-adult network structure and suicide attempts in 38 high schools: Implications for network-informed suicide prevention. Journal of Child Psychology and Psychiatry, and Allied Disciplines, 60(10), 1065–1075. [Google Scholar] [CrossRef] [Scilit]
  138. Wyman, P. A., Pisani, A. R., Brown, C. H., Yates, B., Morgan-DeVelder, L., Schmeelk-Cone, K., Gibbons, R. D., Caine, E. D., Petrova, M., Neal-Walden, T., Linkh, D. J., Matteson, A., Simonson, J., & Pflanz, S. E. (2020). Effect of the wingman-connect upstream suicide prevention program for Air Force personnel in training: A cluster randomized clinical trial. JAMA Network Open, 3(10), e2022532. [Google Scholar] [CrossRef] [Scilit]
  139. Xavier, A., Otero, P., Blanco, V., & Vázquez, F. L. (2019). Efficacy of a problem-solving intervention for the indicated prevention of suicidal risk in young Brazilians: Randomized controlled trial. Suicide and Life-Threatening Behavior, 49(6), 1746–1761. [Google Scholar] [CrossRef] [Scilit]
  140. Zhang, D., Tian, Y., Wang, R., Wang, L., Wang, P., & Su, Y. (2022). Effectiveness of a resilience-targeted intervention based on “I have, I am, I can” strategy on nursing home older adults’ suicidal ideation: A randomized controlled trial. Journal of Affective Disorders, 308, 172–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. U.S. Institute of Medicine (IOM, 1994) Intervention Continuum. Note. A schematic of the U.S. Institute of Medicine’s intervention, or continuum of care, classification system. Highlighted in green are prevention interventions that primarily focus on equipping individuals with the skills and knowledge needed to reduce the likelihood of negative health behaviors. Highlighted in yellow are treatment interventions that provide individuals with clinical and supportive services, traditionally including inpatient, residential, intensive outpatient, or outpatient services. Maintenance, highlighted in red, provides individuals with a comprehensive long-term support network to prevent re-engagement in negative behavioral health outcomes. Used with permission from the National Academy of Sciences.
Behavsci 16 00243 g001
Table 1. Stress Control Class Descriptions.
Class NumberClass TopicKey LessonsActions Taught
Class 1 What is Stress?Functions of the class, how Stress Control worksThink of ways to weaken mechanisms of stress
Class 2Controlling Your BodyHow our body affects our feeling, fight/flightLimiting caffeine, increasing exercise, belly breathing, progressive relaxation
Class 3Controlling Your ThoughtsHow our thoughts affect our feelingsChallenging unhelpful thoughts, breaking stress up
Class 4Controlling Your ActionsHow our actions affect our feelingsFacing fears, stepping out of your comfort zone, problem-solving skills
Class 5Controlling Panicky Feelings & Getting a Good Night’s SleepHow our breathing affects stress, how our sleep affects our stressControlling breathing, combining prevention skills, sleeping tips
Class 6Boosting Your WellbeingUnderstanding existing compared to thriving, value alignmentSteps towards wellbeing, increasing mindfulness, compassion, gratitude
Note. “Stress” is used as a broad term for distress, including mental health distress, when presenting this information to participants.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.