


Simple Summary
For many people, a companion animal is a treasured family member, and its death can cause deep and lasting grief. Yet this grief is often dismissed by others as an overreaction, leaving bereaved owners feeling alone and unsupported. Surprisingly little is known about what actually happens in the body and brain when a beloved pet dies. This review brings together findings from two fields that have rarely been connected. One is research on how humans and animals form close bonds, and the other is research on how people grieve the loss of other humans. We describe how the same biological systems that build the bond with a pet, including hormones, stress responses, and reward pathways, may also drive the pain of losing one. We find that although these connections are biologically plausible, they have rarely been tested directly in grieving pet owners. We therefore identify priorities for future studies, including biological measures that could be tracked over time, and highlight how cultural attitudes may shape grief across countries. This work aims to help society recognize pet loss as genuine grief and to guide better support for those affected.
Abstract
The loss of a companion animal can provoke grief whose intensity rivals human bereavement, yet its biological basis remains largely uncharted. This structured narrative review synthesizes neurobiological, endocrinological, immunological, and psychosocial evidence into a mechanistic framework offered not as established fact but as a source of testable hypotheses. We trace the substrates of the human–animal bond across six interacting systems and propose how disruption of each upon an animal’s death may drive grief. Three carry comparatively robust analogical support (oxytocinergic signaling, hypothalamic–pituitary–adrenal [HPA] axis regulation, and neuroinflammatory activation) and three are more exploratory (dopaminergic, serotonergic, and endocannabinoid pathways). Integrating extracted study-level data into transparent prioritization heuristics, we identify the HPA axis, assessed with its coupled oxytocinergic partner, as the most defensible first target for a direct biomarker study, a conclusion robust across three methodologically independent analyses. No direct pet-loss evidence yet supports any proposal, and this gap is the review’s central motivation. As applied context, we address euthanasia-related guilt, disenfranchised grief under East Asian norms (a tentative “double disenfranchisement” hypothesis that we put forward for testing), assessment instruments, evidence-graded therapies, priorities for developing Korean-language tools, and One Health research priorities.
1. Introduction
When a companion animal dies, the owner’s world can come apart in ways that few anticipate, the owner included. Months of sadness, intrusive memories, and broken sleep are among the reactions that bereaved owners commonly describe. These reactions are neither rare nor confined to a sentimental minority. They are well documented and clinically relevant [1,2,3]. The literature on pet loss grief, though growing, is scattered across disciplines that have seldom looked at one another’s work, and it has almost nothing to say about bereaved owners in East Asian societies. The present review was undertaken to bridge that gap, and evidence that has until now remained dispersed across veterinary science, psychology, neuroscience, and public health is drawn together here.
The scale of companion animal ownership alone demands attention. In South Korea, the Animal and Plant Quarantine Agency under the Ministry of Agriculture, Food and Rural Affairs recorded roughly 3.29 million registered dogs and cats as of 2023, a figure that has risen each year [4]. Survey-based estimates of the total companion animal population run higher, but the registration data provide the most reliable lower bound. Worldwide, an estimated 57% of consumers reported owning a pet in the mid-2010s [5]. These animals are now commonly treated as family. The language of “fur baby” and “pet parent” is not mere affectation. It reflects a genuine psychological reorganization whose clinical implications medicine has been slow to absorb [6,7,8]. When such animals die, the grief response can mirror human bereavement in symptom profile and sometimes exceed it in severity [1,3]. A meaningful proportion of bereaved owners may satisfy DSM-5 criteria for persistent complex bereavement disorder [2], while depressive symptoms have been associated with heightened stress-induced inflammatory responses in humans [9]. This finding provides indirect context for the proposed pet loss mechanisms; it does not establish inflammatory or immune changes following pet loss. In a large UK study using quota-based sampling, 7.5% of pet-bereaved individuals met ICD-11 criteria for prolonged grief disorder, with the symptom structure showing full measurement invariance relative to human loss [10]. Taken together, these figures indicate that clinically significant distress occurs in a substantial minority of bereaved owners. The relationship also has deep roots. Dogs were the first species to be domesticated, and the many thousands of years since have involved coevolution rather than simple cohabitation, with consequences that are biological, behavioral, and social at once. Selection favored animals able to read human social signals and humans disposed to respond to them, so that the affiliative systems described in Section 3, which include the oxytocinergic, dopaminergic, and stress-regulatory circuits conserved across mammals, are engaged by a companion animal much as they are by a human companion. An attachment formed with an animal is therefore not a metaphorical version of a human attachment but a use of the same machinery, and that is the biological reason its rupture can produce a comparable response. This coevolutionary history is the theoretical foundation on which the rest of the review rests.
Yet this grief routinely goes unrecognized, and the obstacle to recognition is social rather than clinical. Doka’s [11] concept of disenfranchised grief, bereavement that society neither acknowledges nor sanctions, fits pet loss almost perfectly. In Korean clinical and social settings, the problem may run deeper. Cultural norms favoring emotional restraint create what we later describe as a potential double burden, in which owners grieve intensely but feel doubly prohibited from showing it [12,13]. Few healthcare professionals receive any training to recognize or respond to this particular form of loss [14].
A substantial neurobiological gap sits at the center of these observations. We have extensive data on oxytocinergic and HPA-axis correlates of human social bonding. We know almost nothing about what happens biologically when someone loses an animal with whom they have shared daily oxytocin-mediated interactions for a decade or more. Closing this gap requires the kind of cross-disciplinary thinking that the One Health paradigm was designed to support (Figure 1) [15,16]. Veterinary medicine, psychology, neuroscience, and public health all need to be brought into the same analysis.
Figure 1.
The One Health framework of companion-animal bereavement. Human caregivers and companion animals are joined through shared neurobiological substrates, oxytocinergic signaling, hypothalamic–pituitary–adrenal (HPA) + autonomic axis regulation, endocannabinoid tone, dopaminergic reward, serotonergic response, and neuroinflammatory balance. They are coupled through a shared oxytocinergic loop and mutual stress buffering, so that rupture of the attachment bond by death carries bidirectional consequences: prolonged grief with cardiovascular and immune dysregulation in humans, disenfranchised social recognition of the loss, and stress behaviors in surviving animals. Epidemiological anchors come from a UK quota sample [10] (N = 975), in which 32.6% had experienced the death of a pet, 7.5% met criteria for prolonged grief disorder, the relative risk of prolonged grief after pet loss was 1.27 versus non-bereaved, and pet loss accounted for 8.1% of all prolonged-grief cases. Each of the six neurobiological systems is assigned a color, and the same color is used for that system in every figure of this review. Data sources: the epidemiological values shown are taken from [10], and the neurobiological substrates summarized here are documented with citations in Section 3.
This review examines the neurobiological architecture of the human–animal bond and proposes how each system may become disrupted when that bond is severed by death. We also consider clinical phenomenology, epidemiology, and psychosocial context. We review assessment instruments and therapeutic approaches graded by evidence quality, discuss priorities for culturally adapted tool development in Korea, and discuss educational implications and future research directions.
Several prior reviews have addressed adjacent terrain, and two of them bear directly on the present one. Cleary and colleagues offered a systematic review focused on the clinical phenomenology of pet bereavement [17], and Packman and colleagues advanced the disenfranchised grief framework as it applies to animal loss [18]. Our contribution differs from these in both scope and integration, in that we synthesize neurobiological mechanisms across six interacting systems, extend the analysis to East Asian cultural contexts, and identify priorities for culturally adapted instrument development. To our knowledge, no prior review has combined these three elements—mechanistic framework, cultural extension, and instrument-development priorities—within a single One Health framing. It also differs in orientation from social-neuroscience reviews of human grief, which characterize bereavement-related brain circuitry in people but do not engage the companion-animal bond or the cross-species neurobiology that a One Health account requires. We regard this neurobiological framework and its data-driven prioritization as the primary contribution of the present review. The assessment instruments, therapeutic grading, cultural analysis, and educational recommendations that follow are developed as the applied context for which this framework is intended, rather than as independent aims.
2. Review Methodology
This structured narrative review follows the Scale for the Assessment of Narrative Review Articles (SANRA) quality criteria [19]. It is not a PRISMA-compliant systematic review, though we applied independent dual screening of titles and abstracts to reduce selection bias, as noted in the Limitations. A narrative synthesis is the appropriate design for this review because it aims to integrate mechanistically heterogeneous evidence, namely animal models, human bereavement studies, and human–animal-bond research, into a single hypothesis-generating framework, an objective that a PRISMA-style systematic review, which presumes a homogeneous body of studies with groupable outcomes, is not designed to serve.
Search strategy. We searched PubMed/MEDLINE, PsycINFO, Web of Science, Scopus, and Google Scholar from January 1980 to April 2026, without language restrictions. Search strings combined three conceptual blocks: (i) bereavement (“pet loss,” “companion animal bereavement,” “disenfranchised grief,” “complicated grief”); (ii) human–animal relationship (“human–animal bond,” “attachment to pet”); and (iii) neurobiology (“oxytocin,” “HPA axis,” “cortisol,” “dopamine,” “neuroinflammation,” “endocannabinoid”). For cultural-context searches, we added “Korea,” “Japan,” “China,” “Confucian,” and “East Asia” to the bereavement block.
Inclusion criteria. Original research, systematic reviews, meta-analyses, and narrative reviews addressing neurobiological, psychological, or cultural dimensions of pet loss grief or human–animal bonding were eligible. Book chapters were included where they represent seminal conceptualizations, for example, Doka’s disenfranchised grief framework [11].
Exclusion criteria. Conference abstracts without full text, editorial commentaries lacking original data, and articles dealing exclusively with animal welfare without reference to human bereavement were excluded.
Limitations of methodology. Titles and abstracts from database searches were independently screened by two reviewers (J.O. and H.J.K.) against the inclusion and exclusion criteria. Disagreements were resolved through discussion, and any case that remained unresolved was adjudicated by the corresponding author (W.L.). Full-text articles passing screening were assessed for relevance by all authors. Because this is a structured narrative review rather than a systematic one, selection bias cannot be fully ruled out. We attempted to mitigate this by conducting comprehensive multi-database searches. All neurobiological propositions in Section 3 are explicitly framed as hypotheses that require prospective empirical validation. All figures in this review are original works prepared by the authors from the data described in the text and in Supplementary Methods S1. No figure has been reproduced or adapted from a previously published article, website, or other external source, so no reproduction permission is required. The data underlying each figure are attributed in the corresponding legend and itemized in Supplementary Methods S1, Table S3.
Claude (Opus 4.8, Anthropic) was used for limited language editing, initial literature and reference searches, and initial diagram generation through author-written Python (Matplotlib) and HTML/CSS; all data and scientific interpretations were provided and verified by the authors, and each figure was subsequently reviewed and modified individually by the authors.
3. The Human–Animal Bond: Neurobiological Foundations and What Happens When It Breaks
Most reviews treat the neuroscience of bonding and the neuroscience of grief as separate topics. We regard this separation as a conceptual shortcoming. The very systems that sustain the bond are the ones whose disruption drives the grief. In the subsections that follow, we therefore pair each neurobiological substrate with the hypothesized consequences of its loss.
One point governs the interpretation of everything that follows in this section. With the single exception of explicitly labeled predictions, all evidence cited below comes from human social bonding, human bereavement after human loss, or animal models. None of it comes from bereaved pet owners. The human and animal findings serve as scaffolding for hypotheses, not as confirmation of them. We organize the six systems into two tiers. Three carry comparatively strong analogical support and are ready for first-generation biomarker testing, namely the oxytocinergic system, the HPA axis with its autonomic partners, and the neuroinflammatory response. Three are more exploratory and rest on thinner evidence, namely dopaminergic reward circuitry and the serotonergic and endocannabinoid pathways. (Figure 2) Because no direct pet-loss biomarker data yet exist, every index value reported below is derived from analogical human and animal evidence, and the indices themselves are proposed heuristics rather than validated psychometric instruments.
Figure 2.
Mechanism map of the six candidate neurobiological systems whose disruption is hypothesized to drive pet loss grief, ranked by the First-Study Priority Index (FSPI). Systems are organized into a primary tier (oxytocinergic system, HPA axis, neuroinflammatory response), ready for first-generation biomarker testing, and an exploratory tier (dopaminergic, serotonergic, and endocannabinoid pathways), with the tier marked on each row. Each row summarizes the system’s role during the bond and its predicted change upon loss, and reports the analogical readiness index (TRI, 0–100), the citation-consensus ratio (0–1, from Scite Smart Citations), the median empirical sample size of the primary studies (N, shown as a dash where review-only), and the composite FSPI (=TRI × consensus × sample-adequacy). The color assigned to each system is the same as in Figure 1. Definitions, weights, and sensitivity analyses for the TRI and the FSPI are given in Supplementary Methods S1. Data sources: all index values are derived from the studies listed in Appendix A, Table A1, with the derivation of each value itemized in Supplementary Methods S1, Table S3.
3.1. The Oxytocinergic System (Primary)
Of all the neurobiological substrates of the human–animal bond, oxytocin has attracted the most sustained research attention. This nine-amino-acid neuropeptide is synthesized in the paraventricular and supraoptic nuclei, released from the posterior pituitary, and sits at the intersection of maternal behavior, pair bonding, social recognition, trust, and stress regulation [20]. Its deep evolutionary conservation across mammals indicates that social attachment is better understood as a biological necessity than as a sentimental luxury [21]. The broader psychosocial and psychophysiological effects of human–animal interaction, with oxytocin as a probable mediator, have been reviewed in detail [22].
The signature finding in this literature is bidirectional oxytocinergic activation. Early work showed that a dog’s gaze at its owner raises the owner’s urinary oxytocin [23]. Nagasawa and colleagues [24] went further, demonstrating in 2015 that mutual gaze between dogs and owners elevates urinary oxytocin in both species, an interspecific positive feedback loop without clear precedent. Oxytocin concentrations correlated with gaze duration and self-reported attachment, consistent with a dose–response relationship. Later studies confirmed that exogenous oxytocin enhances canine bonding behavior [25] and that tactile contact with a companion dog raises salivary oxytocin while lowering cortisol, blood pressure, and heart rate [26]. Oxytocin also modulates stress reactivity through direct inhibitory projections to the HPA axis, attenuating corticotropin-releasing hormone secretion from the paraventricular nucleus and suppressing adrenocorticotropic hormone release [27], and it facilitates fear extinction through actions on the amygdala [28].
A methodological caveat is warranted before these findings are extended to the pet loss context. Studies of human-dog oxytocin relationships have used heterogeneous biological matrices, namely urine, saliva, and plasma, and the correlations between matrices are weak [29]. The claim that companion-animal interaction sustains tonic oxytocin signaling therefore rests on convergent rather than directly comparable evidence. Future prospective studies should standardize the measurement modality and, where feasible, favor central over peripheral indices.
OXTR gene polymorphisms, particularly rs53576, have been proposed as moderators of social bonding and affiliative behavior [30]. A word of caution is in order before these polymorphisms are carried into the pet loss context. The candidate gene literature for rs53576 suffers from inconsistent replication, small effect sizes, and what appears to be substantial publication bias [31]. Treating these associations as straightforwardly applicable to pet loss grief without genome-wide approaches would be premature. The OXTR locus remains a biologically plausible exploratory target, but candidate-gene-era findings alone cannot support strong claims.
Hypothesized consequences of bond disruption, and the studies that would test them. During an active relationship, daily touch, eye contact, and olfactory exposure likely sustain elevated baseline oxytocin tone, which, in turn, inhibits HPA activity and supports autonomic homeostasis [26,32]. When the animal dies, the sudden and permanent removal of these oxytocin-stimulating interactions may precipitate an acute drop in oxytocinergic signaling, a collapse analogous to what happens when a rodent pair bond is experimentally disrupted. In prairie voles, breaking established bonds reduces oxytocin receptor binding in limbic structures and produces anxiety-like behavior and HPA hyperactivity [33]. Bereaved individuals show dysregulated diurnal cortisol patterns, flattened slopes, and altered awakening responses that persist for weeks to months [34]. From this reasoning, we derive a specific and testable prediction, namely that bereaved pet owners should show reduced oxytocin concentrations in acute bereavement and that these reductions should track grief severity and pre-loss attachment strength. This prediction has not yet been tested in bereaved pet owners.
3.2. The HPA Axis and Autonomic Nervous System (Primary)
Interaction with companion animals consistently down-regulates the stress axis. Pet owners show lower cortisol responses to psychosocial stressors than non-owners [35] and a systematic review encompassing 129 human–dog interaction studies confirmed cortisol reduction as one of the most robust findings in the field [36]. In certain experimental paradigms, the animal buffered stress more effectively than a spouse [37], a result that invites reflection on whether the non-evaluative, unconditional character of the human–animal relationship may offer stress-regulatory benefits that even close human relationships cannot fully replicate.
Heart rate variability, a reliable index of parasympathetic tone, increases during and after human-dog interaction [36,38]. Polyvagal theory [39] offers a complementary view, in which a trusted attachment figure activates the ventral vagal complex and promotes calm engagement. At the population level, pet ownership is associated with lower cardiovascular morbidity and mortality [40], likely reflecting sustained autonomic adaptation.
Hypothesized consequences of bond disruption, and the studies that would test them. With the stress buffer removed, the HPA axis loses its principal brake, so glucocorticoid hyperexposure is the predicted consequence. Here too the supporting evidence comes from human loss rather than from pet loss. Chronic grief after human bereavement is associated with sustained HPA activation and a dysregulated cortisol diurnal rhythm [41]. Elevated glucocorticoids suppress lymphocyte proliferation and natural killer cell cytotoxicity, impair hippocampal neurogenesis through reduced brain-derived neurotrophic factor, fragment sleep architecture, and promote systemic inflammation through NF-κB pathway interactions [42]. McEwen’s concept of allostatic overload [43] is useful here. Owners who have relied chronically on the bond’s stress-buffering effects may accumulate allostatic burden quickly when that resource disappears overnight. Whether any of this holds for pet loss specifically is unknown, and serial cortisol sampling in bereaved owners is the obvious first test.
3.3. Dopaminergic Reward Circuitry (Exploratory)
Social bonds engage the mesolimbic dopamine system, the circuitry responsible for reward prediction, motivational salience, and incentive learning. Bond dissolution lowers dopamine signaling in reward-related regions [44]. In a small human neuroimaging study, women with complicated grief showed greater nucleus accumbens activation in response to cues of the deceased than women with noncomplicated grief; activation was positively associated with yearning [45]. A separate study identified a distributed neural network involved in grief, including regions associated with affect processing, memory, and autonomic regulation [46]. These findings concern human bereavement and do not directly measure dopamine signaling after pet loss. Oxytocin and dopamine interact in the nucleus accumbens during bond formation [47], creating self-reinforcing loops that may heighten grief vulnerability when the bonded partner dies. Whether analogous dopaminergic changes occur in pet loss grief is unknown, and this gap is addressable.
Hypothesized consequences of bond disruption, and the studies that would test them. By analogy with human neuroimaging, pet loss may involve disruption of dopaminergic reward circuitry. Grief regulation engages prefrontal and limbic circuits [48], and the deceased animal may continue to act as a conditioned reward stimulus that drives the yearning and searching of acute grief. When these reward-seeking behaviors persistently go unreinforced, the plausible outcome is reward-system hypoactivity, expressed as anhedonia and social withdrawal [49]. Direct neuroimaging is needed before any of this can be asserted.
3.4. Serotonergic and Endocannabinoid Systems (Exploratory)
Serotonin contributes to affiliative behavior and social reward processing [50]. Endogenous opioids modulate social bonding as well, and on this point the animal evidence is direct. Panksepp and colleagues [51] showed that endorphins mediate the rewarding aspects of social contact and that disrupting opioidergic signaling produces separation distress in animal models. Central serotonergic activity falls in bereaved individuals with complicated grief and major depression [52].
The endocannabinoid system modulates social bonding, fear extinction, and stress resilience [53]. Anandamide and 2-arachidonoylglycerol act on CB1 and CB2 receptors to attenuate HPA responses, reduce amygdala-mediated fear, and support hedonic tone. In animal models, social separation lowers anandamide in the prefrontal cortex and amygdala and produces anxiety-like and depressive-like behaviors that pharmacological enhancement of the system can reverse [54].
Hypothesized consequences of bond disruption, and the studies that would test them. Neither serotonergic nor endocannabinoid changes have been investigated in pet loss grief, and the indirect evidence is thinner than for the primary systems. Serotonergic deficits are well established in complicated human grief and concurrent depression [52], and it would be surprising if pet loss grief of comparable severity did not involve similar disruption. The endocannabinoid data are thinner still, resting almost entirely on rodent separation paradigms. If social separation lowers prefrontal and amygdalar anandamide in rodents [54], prolonged absence of a bonded companion could plausibly produce analogous effects in humans, but this is conjecture. We place both systems in the exploratory tier and recommend that serotonergic and endocannabinoid assays be included as secondary measures in the biomarker panels of Section 8, valuable for hypothesis generation rather than confirmation.
3.5. Neuroinflammatory Cascades (Primary)
Social loss activates microglia and upregulates pro-inflammatory cytokines, including interleukin-1β, interleukin-6, and tumor necrosis factor-α, in limbic and prefrontal regions in animal models [55]. In humans, bereavement raises circulating inflammatory markers that predict grief severity and subsequent depression [56]. Some of this response may reflect withdrawal of the anti-inflammatory signaling normally provided by oxytocin [57].
Hypothesized consequences of bond disruption, and the studies that would test them. Neuroinflammation may drive depressive symptoms indirectly through tryptophan catabolism along the kynurenine pathway [58]. The proposed sequence begins when bereavement triggers a peripheral and central inflammatory response. Pro-inflammatory cytokines activate indoleamine 2,3-dioxygenase, which shunts tryptophan away from serotonin synthesis and toward neurotoxic kynurenine metabolites (Figure 3). The resulting serotonergic deficit and accumulation of quinolinic acid could sustain depressive and anxiety symptoms beyond what the psychological loss alone would predict. None of these pathways has been examined in bereaved pet owners. Given the robust association between human bereavement and inflammatory markers [56], and the plausible withdrawal of oxytocin-mediated anti-inflammatory protection upon pet death [57], inflammatory profiling of bereaved owners is a tractable and high-priority target. On the readiness dimension, the neuroinflammatory system ranks in the primary tier, but the data-driven robustness analyses in Section 3.7 identify it as the most fragile of the primary mechanisms. Its high readiness should therefore be read together with that qualification. A first direct test would pair serial inflammatory markers with grief severity in the same bereaved owners over the first months after loss, and the panel we would prioritize for that purpose is set out in Section 8.
Figure 3.
Putative kynurenine-pathway bridge linking peripheral inflammation to serotonergic deficit. Pro-inflammatory signaling induces indoleamine 2,3-dioxygenase (IDO), which shunts tryptophan away from serotonin synthesis and toward kynurenine and its neuroactive metabolite quinolinic acid. Link-level citation-consensus ratios (inflammation → kynurenine, 0.76, Dantzer et al. [59]; kynurenine → serotonin, 0.94, Cervenka et al. [60]) yield a serial-chain confidence of 0.72 (0.76 × 0.94). Data sources: the two link-level ratios are those of Dantzer et al. [59] and Cervenka et al. [60] as cited above, with derivations itemized in Supplementary Methods S1, Table S3.
3.6. Summary of Evidence and Critical Research Gaps
Table 1 maps each proposed mechanism against its evidence base and the studies needed to test it. The pattern is consistent across all six systems. Indirect or analogical evidence is available, but direct pet-loss-specific evidence is absent.
Table 1.
Evidence base, tier, and required empirical studies. None of the six neurobiological mechanisms has yet been examined directly in pet-bereaved populations. Every entry rests on analogical evidence and requires prospective validation, the gap this review addresses. The tier of each mechanism is also marked, so the strength of the underlying analogical case is visible at a glance.
Specificity of the proposed markers and the problem of psychiatric comorbidity. None of the six markers considered above is specific to bereavement, still less to the loss of a companion animal. Altered diurnal cortisol rhythms, reduced oxytocinergic tone, blunted striatal reward signaling, and raised interleukin-6 and C-reactive protein are reported in major depressive disorder, in anxiety and post-traumatic stress disorders, and in chronic psychosocial stress of many kinds, and they accompany human bereavement in general rather than pet bereavement in particular. Two consequences follow for interpreting future studies. The first is inferential, in that a biomarker profile obtained after the death of a companion animal cannot by itself show that the death produced it, which is why the prospective pre-loss to post-loss design described in Section 8, in which each participant serves as their own baseline, is preferred to cross-sectional comparison. The second concerns concurrent psychiatric morbidity and is the more difficult of the two. A substantial proportion of bereaved owners will carry a pre-existing or emergent depressive or anxiety disorder, and the biological signature of such a disorder overlaps almost entirely with the signature predicted here for grief itself. To our knowledge, no study has characterized these systems in individuals experiencing pet loss grief together with a diagnosed mental disorder, and this is an informative gap rather than a peripheral one, because it is precisely in the comorbid group that clinical need is greatest. We therefore recommend that future studies screen for depressive and anxiety disorders at every time point, treat symptom severity as a covariate and as a candidate moderator rather than as an exclusion criterion, and, where sample size permits, stratify the analysis into bereaved owners without a concurrent diagnosis, bereaved owners with one, and non-bereaved individuals carrying the same diagnosis. Only a design of this kind can separate what is attributable to the loss from what is attributable to the disorder that accompanies it.
3.7. A Data-Driven Prioritization of Mechanisms
The six systems reviewed above differ not only in their proposed relevance to pet loss but also in the maturity, reliability, and structure of the evidence supporting them. To move beyond a descriptive account and compare the evidence supporting potential first studies, we integrated the quantitative evidence assembled for this review (79 extracted evidence records, corresponding to 75 unique publications, with extractable design, sample size, and citation data). Four of the 79 records were subsequently identified as duplicate entries for the same publication, which is why Appendix A lists 75 studies, and the index values reported below were computed on the full 79-record set. We report both counts so that the difference is not mistaken for an inconsistency. We then used the extracted data to construct a small set of transparent prioritization metrics. The full evidence base is reproduced in Appendix A, Table A1. These metrics are proposed heuristics rather than established psychometrics, and we report them together with their limitations. Full definitions, scoring rules, weighting, and sensitivity analyses for these metrics are provided in Supplementary Methods S1. We aim to identify, based on current evidence, which mechanism is the most defensible first target for a direct biomarker study of pet loss grief.
We first defined a First-Study Priority Index (FSPI) that combines three independent dimensions of evidential strength. The first is analogical readiness, reflecting how well a mechanism is supported by human bereavement and human–animal bond research that can be extended to pet loss. The second is citation consensus, computed for each mechanism as the ratio of supporting to supporting-plus-contrasting Smart Citations aggregated across its key papers. The third is sample adequacy, indexed by the median empirical sample size of the primary studies underlying the mechanism. Because these three dimensions are drawn from methodologically distinct sources, namely literature synthesis, a citation-classification database, and per-study sample extraction, their combination is informative rather than redundant. The composite is a product of these three inputs, and the readiness index itself weights its evidence dimensions according to the review’s priorities, namely human-bereavement support, human–animal-bond support, and quantified effect size. Because these choices are analytic rather than empirically derived, the resulting order should be read as a directional guide to which mechanism to test first, not as a precise or validated ranking, and its robustness to alternative weightings and to expansion of the evidence base is examined in Supplementary Methods S1.
The resulting ranking placed the hypothalamic–pituitary–adrenal (HPA) axis first, followed by the neuroinflammatory, oxytocinergic, dopaminergic, serotonergic, and endocannabinoid systems. This ordering is notable because it differs from what analogical readiness alone would suggest. On readiness alone, the neuroinflammatory system ranks highest, but when reliability and statistical power are incorporated, the HPA axis overtakes it. As a worked illustration, drawn from Table S1 of the Supplementary Materials, the HPA axis scores 85 × 1.00 × 1.00 = 85.0, whereas the neuroinflammatory system scores 92 × 0.71 × 1.00 = 65.1, so the stronger raw readiness of the neuroinflammatory system is outweighed once its lower citation consensus enters the product. The reordering proved stable across four sequential expansions of the evidence base (from 33 to 46 to 58 to 79 studies), and the HPA advantage widened rather than narrowed as evidence accumulated, because the neuroinflammatory literature acquired additional contrasting citations while the HPA literature did not. The HPA axis was ranked first in four of five alternative weighting schemes, indicating the result is not an artifact of a particular weighting choice (Figure 4).
Figure 4.
Data-driven prioritization of the six mechanisms by the First-Study Priority Index (FSPI). (A) Bubble plot showing analogical readiness (TRI), citation consensus, and sample adequacy for the six mechanisms. Bubble position encodes analogical readiness (x-axis, TRI) and citation consensus (y-axis). Bubble area encodes sample adequacy. (B) Bar chart showing the composite FSPI for the six mechanisms. Bars show the composite FSPI (HPA axis 85, neuroinflammatory 65, oxytocinergic 57, dopaminergic 36, serotonergic 35, endocannabinoid 30), each computed as TRI × consensus × sample-adequacy. The color assigned to each system is the same as in Figure 1 and Figure 2. Derivations are fully specified and reproducible in Supplementary Methods S1. Data sources: all index values are derived from the studies listed in Appendix A, Table A1, with the derivation of each value itemized in Supplementary Methods S1, Table S3.
Two further analyses, each methodologically independent of the FSPI and of the other, converged on the same conclusion. An evidence-triangulation analysis counted the number of distinct study designs supporting each mechanism (causal animal-loss model, human longitudinal, human experimental, cross-sectional, and synthesis review). The HPA axis was the only mechanism spanning four independent designs (Figure S1, Supplementary Materials), uniquely combining a causal animal-loss model (early maternal loss in wild chimpanzees) with human longitudinal and experimental evidence. By contrast, the neuroinflammatory and dopaminergic systems lacked a causal animal-loss anchor, resting solely on human observational and review evidence, which limits direct causal testing. A concentration analysis then quantified (Table S2 of the Supplementary Materials) how much of each mechanism’s citation weight rested on a single dominant paper. The neuroinflammatory system was the most concentrated, with roughly three-quarters of its citation weight attributable to one general review of relationships and inflammation that is not specific to bereavement. In contrast, the HPA and oxytocinergic systems drew on a more evenly distributed base of primary loss studies and therefore present no single point of failure.
The agreement of three independent analyses is the central result (Figure 5). The FSPI, the triangulation-breadth analysis, and the concentration analysis use different inputs yet all favor the HPA axis and all identify the neuroinflammatory system as comparatively fragile, since it is contested in its citation record, lacks a causal loss model, and is heavily dependent on a single non-specific review. The robustness of the HPA-first conclusion across these lenses gives us more confidence in it than any single metric would justify.
Figure 5.
Robustness of the HPA-first ranking across independent lenses. (A) Citation-concentration analysis, using top-paper share and the Herfindahl index (HHI), identifies the neuroinflammatory system as the most single-source dependent (top-paper share ≈ 74%, HHI 0.57), whereas the HPA and oxytocinergic systems rest on a more evenly distributed base of primary loss studies. (B) Rank matrix showing the rank of each mechanism under the three methodologically independent analyses (FSPI, evidence triangulation, and citation concentration; 1 = best). See Supplementary Methods S1 for all derivations. Data sources: the concentration and triangulation analyses are computed from the citation records of the studies listed in Appendix A, Table A1. The color assigned to each system is the same as in Figure 1, Figure 2 and Figure 4.
A complementary network analysis of how the six systems interconnect refines this recommendation. Mapping the mechanistic links reported across the extracted studies, the oxytocinergic and HPA systems emerged as the most integrative hubs (Figure S2, Supplementary Materials), while the neuroinflammatory system was the most peripheral, connected to the wider network only through the kynurenine pathway to serotonin. The single strongest link in the network was the coupling between oxytocin and cortisol. This suggests that an optimal first study should not measure the HPA axis in isolation but should assess the coupled HPA-oxytocin axis, since these two primary-tier systems are both individually robust and, mechanistically, most tightly linked.
Three boundary conditions must be stated plainly before these indices are put to use. First, a study-level analysis found that how contested a finding is could not be predicted from either its frequency of citation or its sample size, with both relationships statistically indistinguishable from zero. Citation consensus is therefore orthogonal to citation volume and statistical power, meaning popularity and sample size cannot substitute for direct evidence of agreement. Consensus is derived from automated Smart Citation classifications, which carry a nonzero misclassification rate, so we treat it as an approximate signal and rely on the agreement of independent analyses rather than on any single value. Second, and most importantly, every metric above is built on human bereavement and human–animal bond data, because direct biomarker studies of pet loss do not yet exist. These indices are intended to compare candidate mechanisms for an initial direct biomarker study and indicate where empirical testing might begin. They do not establish that any mechanism has been demonstrated in pet loss itself. Third, the dimension weights are the authors’ analytic choice rather than empirically derived. Although the ranking held under four of the five alternative weighting schemes tested and across successive expansions of the evidence base (Section S1.3 of the Supplementary Materials), the index should be interpreted as a directional priority rather than a precise ordinal scale. The prioritization is thus a hypothesis-generating tool, and the gap it addresses remains the central justification for the research priorities discussed in Section 8.
5. Assessment Instruments
5.1. Existing Validated Instruments
Systematic assessment of pet loss grief requires validated, standardized instruments. Table 2 summarizes the principal measures currently available. One limitation applies across the board, in that none of these instruments has been formally validated in Korean-speaking populations. This is more than a methodological inconvenience, since it constitutes a substantial barrier to research in the region. A Chinese-language adaptation of the Pet Bereavement Questionnaire was validated in a Hong Kong Chinese sample in 2024 [79], but no Korean-language version exists.
Table 2.
Principal instruments for pet loss grief assessment with East Asian validation status.
5.2. Priorities for Culturally Adapted Tool Development in Korea
Korean-language instruments are necessary to examine the questions raised here empirically in Korean populations. Table S4 in the Supplementary Materials presents an illustrative sequence based on methodological dependencies.
6. Therapeutic Approaches
6.1. Evidence Classification Framework
A basic limitation of the therapeutic literature must be stated at the outset. No randomized controlled trial (RCT) has specifically targeted companion animal bereavement. Every psychotherapeutic recommendation, therefore, rests on evidence extrapolated from human bereavement research. Table 3 grades available approaches using a modified classification adapted from the Oxford Centre for Evidence-Based Medicine (CEBM) Levels of Evidence, with asterisked levels (e.g., Level II*) denoting extrapolated evidence derived from studies in analogous populations (e.g., human bereavement) rather than the target population (pet loss bereavement).
Table 3.
Therapeutic approaches for pet loss grief graded by evidence level.
One entry in Table 3 warrants an added note. Intranasal oxytocin is rated Level V for its mechanistic plausibility from animal models and early human social-cognition studies. Yet, recent meta-analyses and methodological reviews have raised serious concerns about the reproducibility of intranasal oxytocin effects on human social and emotional outcomes [93,94]. The current evidence does not support clinical use. We include it only as a target for hypothesis-driven research, contingent on resolution of these methodological concerns.
6.2. The Role of Veterinarians
Veterinarians are often the first professionals a bereaved owner encounters after an animal’s death, and the quality of that encounter matters a great deal. Best-practice guidance stresses structured, empathic communication throughout end-of-life decision-making [95]. Empathic communication and collaborative decision-making reduce grief severity, lower decisional regret, and increase client satisfaction [68,96]. Communication failures predict worse grief outcomes, whether through rushed consultations, failure to acknowledge distress, or euphemistic language that obscures the reality of euthanasia [97].
This places veterinarians in an untenable position when they are not supported. Repeated exposure to animal death and owner grief drives compassion fatigue, and the profession faces elevated suicide risk [98]. Institutional support remains inadequate in most health systems, Korea included. From a One Health perspective, veterinary well-being is not a separate issue from owner bereavement, and the two are better regarded as different aspects of a single problem.
6.3. Interdisciplinary One Health Approaches
Full-scale integration across veterinary and mental health systems is logistically complex and unlikely to materialize as a single coordinated reform. Achievable near-term steps include standardized pet loss screening questions in primary care intake assessments; referral cards linking bereaved owners to grief support resources in veterinary clinic waiting rooms; shared continuing education that brings veterinary and mental health professionals into structured dialogue; and, where feasible, co-located or tele-linked counseling services accessible through veterinary clinics. A One Health framework does not require that every discipline solve every problem. It requires that each discipline recognize where its boundaries intersect with those of another and act accordingly.
7. Educational Implications for Healthcare Professionals
Pet loss grief is currently absent from veterinary, medical, and nursing curricula. This reflects an assumption, largely unexamined, that human–animal relationships are emotional rather than clinical concerns. We therefore propose a tiered interprofessional educational framework, addressed in turn to veterinarians, to physicians and psychiatrists, and to nurses.
Veterinarians need to recognize signs of grief, practice empathetic end-of-life communication, know how to use grief assessment tools, maintain current referral lists, and learn strategies to manage their own compassion fatigue. Veterinary schools should integrate these competencies into clinical rotations rather than relegating them to elective seminars.
Physicians and psychiatrists should be aware of DSM-5 diagnostic correlates, competent in screening for pet-loss-related depression and anxiety, and familiar with evidence-based therapeutic options. A patient who presents with depression after a pet’s death deserves the same diagnostic rigor as one who presents after any other significant loss.
Nurses are well-positioned to integrate companion animal ownership and pet loss history into routine assessments. An empathic, validating response from a nurse can be the first signal a bereaved patient receives that their grief is legitimate.
In Korea specifically, educational content must address the cultural norms around emotional restraint and the “double disenfranchisement” dynamic described in Section 4.3. Standardized patient simulations portraying bereaved Korean owners, with culturally authentic emotional restraint rather than open Western-style expressions of grief, would provide a valuable pedagogical tool for training Korean healthcare professionals. The goal is not to impose a Western grief model but to equip clinicians to recognize culturally encoded grief that manifests in indirect, somatized, or restrained forms.
8. Future Research Directions
The most pressing need is direct empirical testing of the neurobiological mechanisms proposed in Section 3. The priorities below are organized by methodological domain. The design features are illustrative and should be adapted to the study setting.
Biomarker studies. Prospective longitudinal studies could enroll participants before an anticipated loss and continue follow-up through bereavement. The coupled HPA-oxytocin axis is the primary candidate, assessed through concurrent diurnal cortisol and salivary oxytocin sampling. Inflammatory, endocannabinoid, and tryptophan/kynurenine measures could provide secondary outcomes. Studies should also assess attachment, grief severity, disenfranchisement, depressive and anxiety symptoms, and psychiatric comorbidity. Participants with concurrent diagnoses should be analyzed as clinically relevant subgroups rather than excluded.
Genetic moderators. Candidate gene approaches to OXTR rs53576 and 5-HTTLPR should be interpreted with extreme caution given the replication crisis in this literature [31]. Future genetic studies will require adequate statistical power and, where feasible, genome-wide approaches. Epigenetic analyses, including OXTR and NR3C1 methylation, offer a complementary and potentially more informative window into how bond disruption alters gene regulation.
Cross-cultural and qualitative research. Mixed-methods studies combining Korean-language qualitative interviews, validated Korean instruments, and cross-cultural comparisons could determine whether “double disenfranchisement” is specific to Korea or reflects a broader East Asian pattern.
Intervention trials. No intervention for pet loss grief has been evaluated in a randomized controlled trial. A pet-loss-adapted complicated grief treatment that addresses euthanasia-related guilt represents a logical initial test.
Pet loss grief research in East Asian populations remains limited. The Korean-language measures discussed in Section 5.2 would support biomarker, cross-cultural, and intervention studies in this population.
9. Conclusions
Pet loss grief deserves greater recognition from the biomedical and psychological research communities than it has received to date. The neurobiological framework we have proposed brings together oxytocinergic disruption, HPA dysregulation, dopaminergic reward-system hypoactivity, and neuroinflammation, but each piece is offered as a testable hypothesis rather than an established mechanism. The framework becomes actionable in its prioritization, since integrating analogical readiness, citation consensus, and sample adequacy identifies the HPA axis, assessed together with its coupled oxytocinergic partner, as the most defensible first target for a direct biomarker study. This ranking remained first under four of the five alternative weighting schemes tested, as the evidence base expanded from 33 to 79 studies. This ordering is a directional research priority, not a validated metric, and no mechanism has yet been measured directly in bereaved pet owners. We have been deliberate about several caveats throughout. Direct pet-loss-specific neurobiological evidence does not yet exist. The therapeutic recommendations rest on extrapolation from human bereavement research, and culturally adapted assessment instruments for East Asian populations still need to be built. One further limitation should be stated plainly, because no amount of hedging removes it. The case assembled here is analogical throughout, and analogical support, however internally consistent, cannot establish that the same biology operates when the deceased is a companion animal rather than a person. The proposed markers are moreover not specific to bereavement, let alone to pet bereavement, so any change observed in a bereaved owner will have to be distinguished from the effects of concurrent depressive and anxiety disorders. The framework should accordingly be judged by whether it generates studies capable of refuting it rather than by the strength of the analogies on which it currently rests.
With its growing companion animal population and distinctive cultural context, South Korea provides an important setting for research on culturally adapted assessment, neurobiology, and intervention.
Direct empirical studies are now needed to test the proposed framework. Prospective cohorts that begin before an anticipated pet loss could examine changes in oxytocin, diurnal cortisol, inflammatory markers, and endocannabinoids across bereavement. Pet-loss-specific intervention trials are also needed, with adapted complicated grief treatment addressing euthanasia-related guilt as one candidate. Testing the “double disenfranchisement” hypothesis will first require validated Korean-language assessment tools. These priorities define the main next steps without prescribing a fixed research program.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/ani16193129/s1. Supplementary Methods S1, index definitions, scoring rules, weighting, and sensitivity and robustness analyses for the Translational Readiness Index and the First-Study Priority Index, together with the supporting tables (Table S1, base-scheme inputs and index ranking; Table S2, triangulation breadth and concentration risk; Table S3, figure-value provenance index) and a supplementary reference list; Figure S1, evidence triangulation architecture across the six mechanisms; Figure S2, mechanism co-occurrence network and centrality; Table S4, illustrative sequence for culturally adapted pet loss grief assessment in Korean and East Asian populations.
Author Contributions
Conceptualization, W.L.; methodology, W.L.; literature screening, J.O., H.J.K. and T.H.P.N.; data extraction and table verification, T.H.P.N.; writing of the original draft, W.L. and T.H.P.N.; writing, review, and editing, all authors; supervision, W.L. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data supporting the findings of this review are contained within the article, including the complete quantitative evidence base presented in Appendix A (Table A1). The full evidence database, comprising the extracted studies and the derived analytic sheets, is available from the corresponding author upon reasonable request.
Acknowledgments
The authors used Claude (Opus 4.8, Anthropic) to assist with limited language editing, initial literature and reference searches, and initial diagram generation through author-written Python (Matplotlib) and HTML/CSS. All data and scientific interpretations were provided and verified by the authors. Each figure was subsequently reviewed and modified individually by the authors in Microsoft PowerPoint (365). The authors take full responsibility for all content in this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| 2-AG | 2-arachidonoylglycerol |
| 5-HT | 5-hydroxytryptamine (serotonin) |
| 5-HTTLPR | serotonin-transporter-linked polymorphic region |
| AEA | anandamide (N-arachidonoylethanolamine) |
| CABS | Companion Animal Bonding Scale |
| CBT | cognitive behavioral therapy |
| CEBM | Centre for Evidence-Based Medicine |
| CGT | complicated grief treatment |
| CRP | C-reactive protein |
| DSM-5 | Diagnostic and Statistical Manual of Mental Disorders, 5th Edition |
| ECS | endocannabinoid system |
| FSPI | First-Study Priority Index |
| GAD-7 | Generalized Anxiety Disorder 7-item scale |
| HHI | Herfindahl-Hirschman Index |
| HPA | hypothalamic–pituitary–adrenal (axis) |
| HRV | heart rate variability |
| ICD-11 | International Classification of Diseases, 11th Revision |
| ICG | Inventory of Complicated Grief |
| ICG-K | Inventory of Complicated Grief, Korean version |
| IDO | indoleamine 2,3-dioxygenase |
| IL-6 | interleukin-6 |
| OT | oxytocin |
| OXTR | oxytocin receptor gene |
| PAS | Pet Attitude Scale |
| PBQ | Pet Bereavement Questionnaire |
| PGD | prolonged grief disorder |
| PHQ-9 | Patient Health Questionnaire-9 |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| RCT | randomized controlled trial |
| SANRA | Scale for the Assessment of Narrative Review Articles |
| TNF | tumor necrosis factor |
| TRI | Translational Readiness Index |
Appendix A
Table A1.
Quantitative evidence base: the 75 unique studies extracted for the mechanism-prioritization analysis. N denotes sample size (“review” or “—” where not applicable); S/C/M denotes Scite Smart Citation tallies (Supporting/Contrasting/Mentioning), with “—” where not tallied.
References
- Archer, J.; Winchester, G. Bereavement following death of a pet. Br. J. Psychol. 1994, 85, 259–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.A. Does the DSM-5 grief disorder apply to owners of deceased pets? A psychometric study of impairment during pet loss. Psychiatry Res. 2020, 285, 112800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wrobel, T.A.; Dye, A.L. Grieving pet death: Normative, gender, and attachment issues. OMEGA-J. Death Dying 2003, 47, 385–393. [Google Scholar] [CrossRef] [Scilit]
- Ministry of Agriculture Food and Rural Affairs (MAFRA). Survey on the Current Status of Animal Protection; MAFRA: Sejong, Republic of Korea, 2023. [Google Scholar]
- Growth from Knowledge (GfK). GfK Global Pet Ownership Survey; GfK: London, UK, 2016. [Google Scholar]
- Cohen, S.P. Can pets function as family members? West. J. Nurs. Res. 2002, 24, 621–638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blouin, D.D. Understanding relations between people and their pets. Sociol. Compass 2012, 6, 856–869. [Google Scholar] [CrossRef] [Scilit]
- Irvine, L. If You Tame Me: Understanding Our Connection with Animals; Temple University Press: Philadelphia, PA, USA, 2004. [Google Scholar]
- Fagundes, C.P.; Glaser, R.; Hwang, B.S.; Malarkey, W.B.; Kiecolt-Glaser, J.K. Depressive symptoms enhance stress-induced inflammatory responses. Brain Behav. Immun. 2013, 31, 172–176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hyland, P. No pets allowed: Evidence that prolonged grief disorder can occur following the death of a pet. PLoS ONE 2026, 21, e0339213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doka, K.J. Disenfranchised Grief: Recognizing Hidden Sorrow; Lexington Books: Lexington, MA, USA, 1989. [Google Scholar]
- Bonanno, G.A.; Papa, A.; Lalande, K.; Zhang, N.; Noll, J.G. Grief processing and deliberate grief avoidance: A prospective comparison of bereaved spouses and parents in the United States and the People’s Republic of China. J. Consult. Clin. Psychol. 2005, 73, 86–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chentsova-Dutton, Y.E.; Tsai, J.L. Self-focused attention and emotional reactivity: The role of culture. J. Personal. Soc. Psychol. 2010, 98, 507–519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chur-Hansen, A. Grief and bereavement issues and the loss of a companion animal: People living with a companion animal, owners of livestock, and animal support workers. Clin. Psychol. 2010, 14, 14–21. [Google Scholar] [CrossRef] [Scilit]
- One Health Commission. What Is One Health? Available online: https://www.onehealthcommission.org (accessed on 29 September 2026).
- Gibbs, E.P.J. The evolution of One Health: A decade of progress and challenges for the future. Vet. Rec. 2014, 174, 85–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cleary, M.; West, S.; Thapa, D.K.; Westman, M.; Vesk, K.; Kornhaber, R. Grieving the loss of a pet: A qualitative systematic review. Death Stud. 2022, 46, 2167–2178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Packman, W.; Carmack, B.J.; Katz, R.; Carlos, F.; Field, N.P.; Landers, C. Online survey as empathic bridging for the disenfranchised grief of pet loss. Omega 2014, 69, 333–356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baethge, C.; Goldbeck-Wood, S.; Mertens, S. SANRA—A scale for the quality assessment of narrative review articles. Res. Integr. Peer Rev. 2019, 4, 5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, H.J.; Macbeth, A.H.; Pagani, J.H.; Young, W.S. Oxytocin: The great facilitator of life. Prog. Neurobiol. 2009, 88, 127–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Donaldson, Z.R.; Young, L.J. Oxytocin, vasopressin, and the neurogenetics of sociality. Science 2008, 322, 900–904. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beetz, A.; Uvnäs-Moberg, K.; Julius, H.; Kotrschal, K. Psychosocial and psychophysiological effects of human–animal interactions: The possible role of oxytocin. Front. Psychol. 2012, 3, 234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nagasawa, M.; Kikusui, T.; Onaka, T.; Ohta, M. Dog’s gaze at its owner increases owner’s urinary oxytocin during social interaction. Horm. Behav. 2009, 55, 434–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nagasawa, M.; Mitsui, S.; En, S.; Ohtani, N.; Ohta, M.; Sakuma, Y.; Onaka, T.; Mogi, K.; Kikusui, T. Oxytocin-gaze positive loop and the coevolution of human-dog bonds. Science 2015, 348, 333–336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romero, T.; Nagasawa, M.; Mogi, K.; Hasegawa, T.; Kikusui, T. Oxytocin promotes social bonding in dogs. Proc. Natl. Acad. Sci. USA 2014, 111, 9085–9090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Handlin, L.; Hydbring-Sandberg, E.; Nilsson, A.; Ejdebäck, M.; Jansson, A.; Uvnäs-Moberg, K. Short-term interaction between dogs and their owners: Effects on oxytocin, cortisol, insulin and heart rate—An exploratory study. Anthrozoös 2011, 24, 301–315. [Google Scholar] [CrossRef] [Scilit]
- Neumann, I.D. Brain oxytocin: A key regulator of emotional and social behaviours in both females and males. J. Neuroendocrinol. 2008, 20, 858–865. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viviani, D.; Charlet, A.; van den Burg, E.; Robinet, C.; Hurni, N.; Abatis, M.; Magara, F.; Stoop, R. Oxytocin selectively gates fear responses through distinct outputs from the central amygdala. Science 2011, 333, 104–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCullough, M.E.; Churchland, P.S.; Mendez, A.J. Problems with measuring peripheral oxytocin: Can the data on oxytocin and human behavior be trusted? Neurosci. Biobehav. Rev. 2013, 37, 1485–1492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feldman, R.; Monakhov, M.; Pratt, M.; Ebstein, R.P. Oxytocin pathway genes: Evolutionary ancient system impacting on human affiliation, sociality, and psychopathology. Biol. Psychiatry 2016, 79, 174–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Border, R.; Johnson, E.C.; Evans, L.M.; Smolen, A.; Berley, N.; Sullivan, P.F.; Keller, M.C. No support for historical candidate gene or candidate gene-by-interaction hypotheses for major depression across multiple large samples. Am. J. Psychiatry 2019, 176, 376–387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beetz, A.; Julius, H.; Turner, D.; Kotrschal, K. Effects of social support by a dog on stress modulation in male children with insecure attachment. Front. Psychol. 2012, 3, 352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Young, L.J.; Wang, Z. The neurobiology of pair bonding. Nat. Neurosci. 2004, 7, 1048–1054. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ong, A.D.; Fuller-Rowell, T.E.; Bonanno, G.A.; Almeida, D.M. Spousal loss predicts alterations in diurnal cortisol activity through prospective changes in positive emotion. Health Psychol. 2011, 30, 220–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, K.; Blascovich, J.; Mendes, W.B. Cardiovascular reactivity and the presence of pets, friends, and spouses: The truth about cats and dogs. Psychosom. Med. 2002, 64, 727–739. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teo, J.T.; Johnstone, S.J.; Römer, S.S.; Thomas, S.J. Psychophysiological mechanisms underlying the potential health benefits of human-dog interactions: A systematic literature review. Int. J. Psychophysiol. 2022, 180, 27–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, K.M.; Blascovich, J.; Tomaka, J.; Kelsey, R.M. Presence of human friends and pet dogs as moderators of autonomic responses to stress in women. J. Personal. Soc. Psychol. 1991, 61, 582–589. [Google Scholar] [CrossRef] [PubMed]
- Friedmann, E.; Son, H. The human-companion animal bond: How humans benefit. Vet. Clin. N. Am. Small Anim. Pract. 2009, 39, 293–326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Porges, S.W. The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-Regulation; W.W. Norton: New York, NY, USA, 2011. [Google Scholar]
- Mubanga, M.; Byberg, L.; Nowak, C.; Egenvall, A.; Magnusson, P.K.; Ingelsson, E.; Fall, T. Dog ownership and the risk of cardiovascular disease and death—A nationwide cohort study. Sci. Rep. 2017, 7, 15821. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buckley, T.; McKinley, S.; Tofler, G.; Bartrop, R. Cardiovascular risk in early bereavement: A literature review and proposed mechanisms. Int. J. Nurs. Stud. 2010, 47, 229–238. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miller, G.E.; Cohen, S.; Ritchey, A.K. Chronic psychological stress and the regulation of pro-inflammatory cytokines: A glucocorticoid-resistance model. Health Psychol. 2002, 21, 531–541. [Google Scholar] [CrossRef] [PubMed]
- McEwen, B.S. Stressed or stressed out: What is the difference? J. Psychiatry Neurosci. 2005, 30, 315–318. [Google Scholar] [CrossRef] [Scilit]
- Berridge, K.C.; Robinson, T.E. What is the role of dopamine in reward: Hedonic impact, reward learning, or incentive salience? Brain Res. Rev. 1998, 28, 309–369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Connor, M.F.; Wellisch, D.K.; Stanton, A.L.; Eisenberger, N.I.; Irwin, M.R.; Lieberman, M.D. Craving love? Enduring grief activates brain’s reward center. NeuroImage 2008, 42, 969–972. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gündel, H.; O’Connor, M.F.; Littrell, L.; Fort, C.; Lane, R.D. Functional neuroanatomy of grief: An fMRI study. Am. J. Psychiatry 2003, 160, 1946–1953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feldman, R. The neurobiology of human attachments. Trends Cogn. Sci. 2017, 21, 80–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Freed, P.J.; Yanagihara, T.K.; Hirsch, J.; Mann, J.J. Neural mechanisms of grief regulation. Biol. Psychiatry 2009, 66, 33–40. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shear, M.K. Complicated grief. N. Engl. J. Med. 2015, 372, 153–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tops, M.; Russo, S.; Boksem, M.A.; Tucker, D.M. Serotonin: Modulator of a drive to withdraw. Brain Cogn. 2009, 71, 427–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Panksepp, J.; Herman, B.; Conner, R.; Bishop, P.; Scott, J.P. The biology of social attachments: Opiates alleviate separation distress. Biol. Psychiatry 1978, 13, 607–618. [Google Scholar] [PubMed]
- Zisook, S.; Shear, K. Grief and bereavement: What psychiatrists need to know. World Psychiatry 2009, 8, 67–74. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hill, M.N.; McLaughlin, R.J.; Bingham, B.; Shrestha, L.; Lee, T.T.Y.; Gray, J.M.; Hillard, C.J.; Gorzalka, B.B.; Viau, V. Endogenous cannabinoid signaling is essential for stress adaptation. Proc. Natl. Acad. Sci. USA 2010, 107, 9406–9411. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bluett, R.J.; Gamble-George, J.C.; Hermanson, D.J.; Hartley, N.D.; Marnett, L.J.; Patel, S. Central anandamide deficiency predicts stress-induced anxiety: Behavioral reversal through endocannabinoid augmentation. Transl. Psychiatry 2014, 4, e408. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Frank, M.G.; Watkins, L.R.; Maier, S.F. Stress-induced neuroinflammatory priming: A liability factor in the etiology of psychiatric disorders. Neurobiol. Stress 2016, 4, 62–70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kiecolt-Glaser, J.K.; Derry, H.M.; Fagundes, C.P. Inflammation: Depression fans the flames and feasts on the heat. Am. J. Psychiatry 2015, 172, 1075–1091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szeto, A.; Nation, D.A.; Mendez, A.J.; Dominguez-Bendala, J.; Brooks, L.G.; Schneiderman, N.; McCabe, P.M. Oxytocin attenuates NADPH-dependent superoxide activity and IL-6 secretion in macrophages and vascular cells. Am. J. Physiol.-Endocrinol. Metab. 2008, 295, E1495–E1501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myint, A.M.; Kim, Y.K. Network beyond IDO in psychiatric disorders: Revisiting neurodegeneration hypothesis. Prog. Neuro-Psychopharmacol. Biol. Psychiatry 2014, 48, 304–313. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dantzer, R.; O’Connor, J.C.; Lawson, M.A.; Kelley, K.W. Inflammation-associated depression: From serotonin to kynurenine. Psychoneuroendocrinology 2011, 36, 426–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cervenka, I.; Agudelo, L.Z.; Ruas, J.L. Kynurenines: Tryptophan’s metabolites in exercise, inflammation, and mental health. Science 2017, 357, eaaf9794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Field, N.P.; Orsini, L.; Gavish, R.; Packman, W. Role of attachment in response to pet loss. Death Stud. 2009, 33, 334–355. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cordaro, M. Pet loss and disenfranchised grief: Implications for mental health counseling practice. J. Ment. Health Couns. 2012, 34, 283–294. [Google Scholar] [CrossRef] [Scilit]
- Park, R.M.; Royal, K.D.; Gruen, M.E. A literature review: Pet bereavement and coping mechanisms. J. Appl. Anim. Welf. Sci. 2023, 26, 285–299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lundorff, M.; Holmgren, H.; Zachariae, R.; Farver-Vestergaard, I.; O’Connor, M. Prevalence of prolonged grief disorder in adult bereavement: A systematic review and meta-analysis. J. Affect. Disord. 2017, 212, 138–149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, S.; Xiang, Z. Who suffered most after deaths due to COVID-19? Prevalence and correlates of prolonged grief disorder in COVID-19 related bereaved adults. Glob. Health 2021, 17, 19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, B.H.; Richards, H.C.; Wilson, C.A. Pet bonding and pet bereavement among adolescents. J. Couns. Dev. 1996, 74, 505–509. [Google Scholar] [CrossRef] [Scilit]
- Tzivian, L.; Friger, M.; Kushnir, T. Associations between stress and quality of life: Differences between owners keeping a living dog or losing a dog by euthanasia. PLoS ONE 2015, 10, e0121081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adams, C.L.; Bonnett, B.N.; Meek, A.H. Predictors of owner response to companion animal death in 177 clients from 14 practices in Ontario. J. Am. Vet. Med. Assoc. 2000, 217, 1303–1309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharkin, B.S.; Knox, D. Pet loss: Issues and implications for the psychologist. Prof. Psychol. Res. Pract. 2003, 34, 414–421. [Google Scholar] [CrossRef] [Scilit]
- Doka, K.J. Disenfranchised Grief: New Directions, Challenges, and Strategies for Practice; Research Press: Champaign, IL, USA, 2002. [Google Scholar]
- Gross, J.J.; Levenson, R.W. Hiding feelings: The acute effects of inhibiting negative and positive emotion. J. Abnorm. Psychol. 1997, 106, 95–103. [Google Scholar] [CrossRef] [PubMed]
- Wu, Y.; Song, J. The relationship between pet attachment and pet loss grief in Chinese undergraduates. Behav. Sci. 2025, 15, 431. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doka, K.J.; Martin, T.L. Grieving Beyond Gender: Understanding the Ways Men and Women Mourn; Routledge: New York, NY, USA, 2010. [Google Scholar]
- Stroebe, M.; Schut, H. The Dual Process Model of coping with bereavement: Rationale and description. Death Stud. 1999, 23, 197–224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neimeyer, R.A. Meaning Reconstruction and the Experience of Loss; American Psychological Association: Washington, DC, USA, 2001. [Google Scholar]
- Worden, J.W. Grief Counseling and Grief Therapy: A Handbook for the Mental Health Practitioner; Springer: New York, NY, USA, 2009. [Google Scholar]
- Kübler-Ross, E. On Death and Dying; Macmillan: New York, NY, USA, 1969. [Google Scholar]
- Packman, W.; Field, N.P.; Carmack, B.J.; Ronen, R. Continuing Bonds and Psychosocial Adjustment in Pet Loss. J. Loss Trauma 2011, 16, 341–357. [Google Scholar] [CrossRef] [Scilit]
- Yiu, W.W.Y.; Cheung, H.N.; Wong, P.W.C. Adaptation and Validation of the Pet Bereavement Questionnaire (PBQ) for Chinese Population. Animals 2024, 14, 2845. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunt, M.; Padilla, Y. Development of the Pet Bereavement Questionnaire. Anthrozoös 2006, 19, 308–324. [Google Scholar] [CrossRef] [Scilit]
- Poresky, R.H.; Hendrix, C.; Mosier, J.E.; Samuelson, M.L. The Companion Animal Bonding Scale: Internal Reliability and Construct Validity. Psychol. Rep. 1987, 60, 743–746. [Google Scholar] [CrossRef] [Scilit]
- Templer, D.I.; Salter, C.A.; Dickey, S.; Baldwin, R.; Veleber, D.M. The construction of a pet attitude scale. Psychol. Rec. 1981, 31, 343–348. [Google Scholar] [CrossRef] [Scilit]
- Prigerson, H.G.; Maciejewski, P.K.; Reynolds, C.F., 3rd; Bierhals, A.J.; Newsom, J.T.; Fasiczka, A.; Frank, E.; Doman, J.; Miller, M. Inventory of Complicated Grief: A scale to measure maladaptive symptoms of loss. Psychiatry Res. 1995, 59, 65–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kroenke, K.; Spitzer, R.L.; Williams, J.B. The PHQ-9: Validity of a brief depression severity measure. J. Gen. Intern. Med. 2001, 16, 606–613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spitzer, R.L.; Kroenke, K.; Williams, J.B.; Löwe, B. A brief measure for assessing generalized anxiety disorder. Arch. Intern. Med. 2006, 166, 1092–1097. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shiozaki, M.; Hirai, K.; Dohke, R.; Morita, T.; Miyashita, M.; Sato, K.; Tsuneto, S.; Shima, Y.; Uchitomi, Y. Measuring the regret of bereaved family members regarding the decision to admit cancer patients to palliative care units. Psychooncology 2008, 17, 926–931. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mercer, S.W.; Maxwell, M.; Heaney, D.; Watt, G.C. The consultation and relational empathy (CARE) measure: Development and preliminary validation and reliability of an empathy-based consultation process measure. Fam. Pract. 2004, 21, 699–705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, D.H.; Lee, J.J.; Moon, D.-S.; Cha, M.-J.; Kim, M.A.; Min, S.; Yang, J.H.; Lee, E.J.; Yoo, S.K.; Chung, U.-S. Korean Version of Inventory of Complicated Grief Scale: Psychometric Properties in Korean Adolescents. J. Korean Med. Sci. 2016, 31, 114–119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shear, M.K.; Frank, E.; Houck, P.R.; Reynolds, C.F. Treatment of complicated grief: A randomised controlled trial. JAMA 2005, 293, 2601–2608. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wagner, B.; Knaevelsrud, C.; Maercker, A. Internet-based cognitive-behavioral therapy for complicated grief: A randomized controlled trial. Death Stud. 2006, 30, 429–453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Frankl, V.E. Man’s Search for Meaning; Beacon Press: Boston, MA, USA, 1959. [Google Scholar]
- MacDonald, K.; MacDonald, T.M. The peptide that binds: A systematic review of oxytocin and its prosocial effects in humans. Harv. Rev. Psychiatry 2010, 18, 1–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mierop, A.; Mikolajczak, M.; Stahl, C.; Béna, J.; Luminet, O.; Lane, A.; Corneille, O. How Can Intranasal Oxytocin Research Be Trusted? A Systematic Review of the Interactive Effects of Intranasal Oxytocin on Psychosocial Outcomes. Perspect. Psychol. Sci. 2020, 15, 1228–1242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quintana, D.S.; Lischke, A.; Grace, S.; Scheele, D.; Ma, Y.; Becker, B. Advances in the field of intranasal oxytocin research: Lessons learned and future directions for clinical research. Mol. Psychiatry 2021, 26, 80–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaw, J.R.; Lagoni, L. End-of-life communication in veterinary medicine: Delivering bad news and euthanasia decision making. Vet. Clin. N. Am. Small Anim. Pract. 2007, 37, 95–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lagoni, L.; Butler, C.; Hetts, S. The Human-Animal Bond and Grief; W.B. Saunders: Philadelphia, PA, USA, 1994. [Google Scholar]
- Stoewen, D.L.; Coe, J.B.; MacMartin, C.; Stone, E.A.; Dewey, C.E. Qualitative study of the communication expectations of clients accessing oncology care at a tertiary referral centre for dogs with life-limiting cancer. J. Am. Vet. Med. Assoc. 2014, 245, 785–795. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nett, R.J.; Witte, T.K.; Holzbauer, S.M.; Elchos, B.L.; Campagnolo, E.R.; Musgrave, K.J.; Carter, K.K.; Kurkjian, K.M.; Vanicek, C.F.; O’Leary, D.R.; et al. Risk factors for suicide, attitudes toward mental illness, and practice-related stressors among US veterinarians. J. Am. Vet. Med. Assoc. 2015, 247, 945–955. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, R.; Royal, K. A National Survey of Companion Animal Owners’ Self-Reported Methods of Coping Following Euthanasia. Vet. Sci. 2020, 7, 89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Testoni, I.; De Cataldo, L.; Ronconi, L.; Zamperini, A. Pet Loss and Representations of Death, Attachment, Depression, and Euthanasia. Anthrozoös 2017, 30, 135–148. [Google Scholar] [CrossRef] [Scilit]
- Ogi, A.; Mariti, C.; Baragli, P.; Sergi, V.; Gazzano, A. Effects of Stroking on Salivary Oxytocin and Cortisol in Guide Dogs: Preliminary Results. Animals 2020, 10, 708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nagasawa, M.; Ogawa, M.; Mogi, K.; Kikusui, T. Intranasal Oxytocin Treatment Increases Eye-Gaze Behavior toward the Owner in Ancient Japanese Dog Breeds. Front. Psychol. 2017, 8, 1624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simpson, E.A.; Sclafani, V.; Paukner, A.; Hamel, A.F.; Novak, M.A.; Meyer, J.S.; Suomi, S.J.; Ferrari, P.F. Inhaled oxytocin increases positive social behaviors in newborn macaques. Proc. Natl. Acad. Sci. USA 2014, 111, 6922–6927. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miller, S.L.; Serpell, J.A.; Dalton, K.R.; Waite, K.B.; Morris, D.O.; Redding, L.E.; Dreschel, N.A.; Davis, M.F. The Importance of Evaluating Positive Welfare Characteristics and Temperament in Working Therapy Dogs. Front. Vet. Sci. 2022, 9, 844252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedrinelli, V.; Rimoldi, B.; Conti, L.; Bordacchini, A.; Parrini, L.; Betti, L.; Giannaccini, G.; Dell’Oste, V.; Carmassi, C. Grief-Related Psychopathology from Complicated Grief to DSM-5-TR Prolonged Grief Disorder: A Systematic Review of Biochemical Findings. Int. J. Mol. Sci. 2025, 26, 11835. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, R.L.; LeRoy, A.S.; Chen, M.A.; Suchting, R.; Jaremka, L.M.; Liu, J.; Heijnen, C.; Fagundes, C.P. Grief Symptoms Promote Inflammation During Acute Stress Among Bereaved Spouses. Psychol. Sci. 2022, 33, 859–873. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zuelke, A.E.; Luppa, M.; Löbner, M.; Pabst, A.; Schlapke, C.; Stein, J.; Riedel-Heller, S.G. Effectiveness and Feasibility of Internet-Based Interventions for Grief After Bereavement: Systematic Review and Meta-analysis. JMIR Ment. Health 2021, 8, e29661. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hopf, D.; Eckstein, M.; Aguilar-Raab, C.; Warth, M.; Ditzen, B. Neuroendocrine mechanisms of grief and bereavement: A systematic review and implications for future interventions. J. Neuroendocrinol. 2020, 32, e12887. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seiler, A.; von Känel, R.; Slavich, G.M. The Psychobiology of Bereavement and Health: A Conceptual Review From the Perspective of Social Signal Transduction Theory of Depression. Front. Psychiatry 2020, 11, 565239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Girard-Buttoz, C.; Tkaczynski, P.J.; Samuni, L.; Fedurek, P.; Gomes, C.; Löhrich, T.; Manin, V.; Preis, A.; Valé, P.F.; Deschner, T.; et al. Early maternal loss leads to short- but not long-term effects on diurnal cortisol slopes in wild chimpanzees. eLife 2021, 10, e64134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kakarala, S.E.; Roberts, K.E.; Rogers, M.; Coats, T.; Falzarano, F.; Gang, J.; Chilov, M.; Avery, J.; Maciejewski, P.K.; Lichtenthal, W.G.; et al. The neurobiological reward system in Prolonged Grief Disorder (PGD): A systematic review. Psychiatry Res. Neuroimaging 2020, 303, 111135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bryant, R.A.; Andrew, E.; Korgaonkar, M.S. Distinct neural mechanisms of emotional processing in prolonged grief disorder. Psychol. Med. 2021, 51, 587–595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McConnell, M.H.; Killgore, W.D.S.; O’Connor, M.-F. Yearning predicts subgenual anterior cingulate activity in bereaved individuals. Heliyon 2018, 4, e00852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bui, E.; Hellberg, S.N.; Hoeppner, S.S.; Rosencrans, P.; Young, A.; Ross, R.A.; Hoge, E.; Simon, N.M. Circulating levels of oxytocin may be elevated in complicated grief: A pilot study. Eur. J. Psychotraumatol. 2019, 10, 1646603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Correia, A.S.; Vale, N. Tryptophan Metabolism in Depression: A Narrative Review with a Focus on Serotonin and Kynurenine Pathways. Int. J. Mol. Sci. 2022, 23, 8493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, D.; Dinh, D.; Lee, D.; Li, D.; Anguren, A.; Moreno-Sanz, G.; Gall, C.M.; Piomelli, D. Enhancement of Anandamide-Mediated Endocannabinoid Signaling Corrects Autism-Related Social Impairment. Cannabis Cannabinoid Res. 2016, 1, 81–89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, F.S.; Kumsta, R.; von Dawans, B.; Monakhov, M.; Ebstein, R.P.; Heinrichs, M. Common oxytocin receptor gene ( OXTR ) polymorphism and social support interact to reduce stress in humans. Proc. Natl. Acad. Sci. USA 2011, 108, 19937–19942. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onaka, T.; Takayanagi, Y. The oxytocin system and early-life experience-dependent plastic changes. J. Neuroendocrinol. 2021, 33, e13049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wirobski, G.; Range, F.; Schaebs, F.S.; Palme, R.; Deschner, T.; Marshall-Pescini, S. Life experience rather than domestication accounts for dogs’ increased oxytocin release during social contact with humans. Sci. Rep. 2021, 11, 14423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Payne, E.; Bennett, P.C.; McGreevy, P.D. Current perspectives on attachment and bonding in the dog–human dyad. Psychol. Res. Behav. Manag. 2015, 8, 71–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thielke, L.E.; Udell, M.A.R. The role of oxytocin in relationships between dogs and humans and potential applications for the treatment of separation anxiety in dogs. Biol. Rev. 2017, 92, 378–388. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oliva, J.L.; Rault, J.-L.; Appleton, B.; Lill, A. Oxytocin blocks pet dog (Canis familiaris) object choice task performance being predicted by owner-perceived intelligence and owner attachment. Pet. Behav. Sci. 2016, 1, 31–46. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Hattori, M.; Kinoshita, K.; Saito, A.; Yamamoto, S. Exogenous oxytocin increases gaze to humans in male cats. Sci. Rep. 2024, 14, 8953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Aniello, B.; Scandurra, A.; Pinelli, C.; Marinelli, L.; Mongillo, P. Is this love? Sex differences in dog-owner attachment behavior suggest similarities with adult human bonds. Anim. Cogn. 2022, 25, 137–148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Connor, M.-F.; Wellisch, D.K.; Stanton, A.L.; Olmstead, R.; Irwin, M.R. Diurnal cortisol in Complicated and Non-Complicated Grief: Slope differences across the day. Psychoneuroendocrinology 2012, 37, 725–728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mason, T.M.; Duffy, A.R. Complicated Grief and Cortisol Response: An Integrative Review of the Literature. J. Am. Psychiatr. Nurses Assoc. 2019, 25, 181–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guldin, M.-B.; O’Connor, M.; Sokolowski, I.; Jensen, A.B.; Vedsted, P. Identifying bereaved subjects at risk of complicated grief: Predictive value of questionnaire items in a cohort study. BMC Palliat. Care 2011, 10, 9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Breen, L.J.; Aoun, S.M.; O’Connor, M.; Johnson, A.R.; Howting, D. Effect of caregiving at end of life on grief, quality of life and general health: A prospective, longitudinal, comparative study. Palliat. Med. 2020, 34, 145–154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mah, K.; Swami, N.; Pope, A.; Earle, C.C.; Krzyzanowska, M.K.; Nissim, R.; Hales, S.; Rodin, G.; Hannon, B.; Zimmermann, C. Caregiver bereavement outcomes in advanced cancer: Associations with quality of death and patient age. Support. Care Cancer 2022, 30, 1343–1353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peak, A.; Martin, L.; Post, K.M.; Hua, W. Maladaptive Personality Characteristics, Coping and Situational Factors Predict Symptoms of Complicated Grief and Health Difficulties. OMEGA-J. Death Dying 2026, 93, 2119–2142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fagundes, C.P.; Brown, R.L.; Chen, M.A.; Murdock, K.W.; Saucedo, L.; LeRoy, A.; Wu, E.L.; Garcini, L.M.; Shahane, A.D.; Baameur, F.; et al. Grief, depressive symptoms, and inflammation in the spousally bereaved. Psychoneuroendocrinology 2019, 100, 190–197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schultze-Florey, C.R.; Martínez-Maza, O.; Magpantay, L.; Breen, E.C.; Irwin, M.R.; Gündel, H.; O’Connor, M.-F. When grief makes you sick: Bereavement induced systemic inflammation is a question of genotype. Brain Behav. Immun. 2012, 26, 1066–1071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- LeRoy, A.S.; Gabert, T.; Garcini, L.; Murdock, K.W.; Heijnen, C.; Fagundes, C.P. Attachment orientations and loss adjustment among bereaved spouses. Psychoneuroendocrinology 2020, 112, 104401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kiecolt-Glaser, J.K.; Gouin, J.-P.; Hantsoo, L. Close relationships, inflammation, and health. Neurosci. Biobehav. Rev. 2010, 35, 33–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mann, J.J. The serotonergic system in mood disorders and suicidal behaviour. Philos. Trans. R. Soc. B 2013, 368, 20120537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mann, J.J.; Currier, D.M. Stress, genetics and epigenetic effects on the neurobiology of suicidal behavior and depression. Eur. Psychiatry 2010, 25, 268–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gibson, E.L. Tryptophan supplementation and serotonin function: Genetic variations in behavioural effects. Proc. Nutr. Soc. 2018, 77, 174–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lamontagne, S.J.; Ballard, E.D.; Zarate, C.A. Effects of stress on endophenotypes of suicide across species: A role for ketamine in risk mitigation. Neurobiol. Stress 2022, 18, 100450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fitzgerald, J.M.; Chesney, S.A.; Lee, T.S.; Brasel, K.; Larson, C.L.; Hillard, C.J.; deRoon-Cassini, T.A. Circulating endocannabinoids and prospective risk for depression in trauma-injury survivors. Neurobiol. Stress 2021, 14, 100304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karhson, D.S.; Hardan, A.Y.; Parker, K.J. Endocannabinoid signaling in social functioning: An RDoC perspective. Transl. Psychiatry 2016, 6, e905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bassir Nia, A.; Bender, R.; Harpaz-Rotem, I. Endocannabinoid System Alterations in Posttraumatic Stress Disorder: A Review of Developmental and Accumulative Effects of Trauma. Chronic Stress 2019, 3, 2470547019864096. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maldonado, R.; Cabañero, D.; Martín-García, E. The endocannabinoid system in modulating fear, anxiety, and stress. Dialogues Clin. Neurosci. 2020, 22, 229–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, P.; Smith, A.S.; Lei, K.; Liu, Y.; Wang, Z. Breaking bonds in male prairie vole: Long-term effects on emotional and social behavior, physiology, and neurochemistry. Behav. Brain Res. 2014, 265, 22–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Love, T.M. Oxytocin, motivation and the role of dopamine. Pharmacol. Biochem. Behav. 2014, 119, 49–60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vitale, E.M.; Smith, A.S. Neurobiology of Loneliness, Isolation, and Loss: Integrating Human and Animal Perspectives. Front. Behav. Neurosci. 2022, 16, 846315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luyten, P.; Fonagy, P. The stress–reward–mentalizing model of depression: An integrative developmental cascade approach to child and adolescent depressive disorder based on the Research Domain Criteria (RDoC) approach. Clin. Psychol. Rev. 2018, 64, 87–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedersen, C.A. Biological Aspects of Social Bonding and the Roots of Human Violence. Ann. N. Y. Acad. Sci. 2004, 1036, 106–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaplow, J.B.; Shapiro, D.N.; Wardecker, B.M.; Howell, K.H.; Abelson, J.L.; Worthman, C.M.; Prossin, A.R. Psychological and environmental correlates of HPA axis functioning in parentally bereaved children: Preliminary findings. J. Trauma. Stress 2013, 26, 233–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Debbané, M.; Salaminios, G.; Luyten, P.; Badoud, D.; Armando, M.; Solida Tozzi, A.; Fonagy, P.; Brent, B.K. Attachment, Neurobiology, and Mentalizing along the Psychosis Continuum. Front. Hum. Neurosci. 2016, 10, 406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonanno, G.A.; Wortman, C.B.; Nesse, R.M. Prospective Patterns of Resilience and Maladjustment During Widowhood. Psychol. Aging 2004, 19, 260–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vable, A.M.; Subramanian, S.V.; Rist, P.M.; Glymour, M.M. Does the “Widowhood Effect” Precede Spousal Bereavement? Results from a Nationally Representative Sample of Older Adults. Am. J. Geriatr. Psychiatry 2015, 23, 283–292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ong, A.D.; Fuller-Rowell, T.E.; Bonanno, G.A. Prospective predictors of positive emotions following spousal loss. Psychol. Aging 2010, 25, 653–660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stroebe, W.; Schut, H. Risk factors in bereavement outcome: A methodological and empirical review. In Handbook of Bereavement Research: Consequences, Coping, and Care; Stroebe, M.S., Hansson, R.O., Stroebe, W., Schut, H.A.W., Eds.; American Psychological Association: Washington, DC, USA, 2001; pp. 349–372. [Google Scholar] [CrossRef] [Scilit]
- Palitsky, R.; Wilson, D.T.; Friedman, S.E.; Ruiz, J.M.; Sullivan, D.; O’Connor, M.-F. The Relationship of Prolonged Grief Disorder Symptoms With Hemodynamic Response to Grief Recall Among Bereaved Adults. Psychosom. Med. 2023, 85, 545–550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jadhav, A.; Weir, D. Widowhood and Depression in a Cross-National Perspective: Evidence from the United States, Europe, Korea, and China. J. Gerontol. B Psychol. Sci. Soc. Sci. 2018, 73, e143–e153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szabó, Á.; Kok, A.A.L.; Beekman, A.T.F.; Huisman, M. Longitudinal Examination of Emotional Functioning in Older Adults After Spousal Bereavement. J. Gerontol. B Psychol. Sci. Soc. Sci. 2020, 75, 1668–1678. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kamp, K.S.; O’Connor, M.; Spindler, H.; Moskowitz, A. Bereavement hallucinations after the loss of a spouse: Associations with psychopathological measures, personality and coping style. Death Stud. 2019, 43, 260–269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guiaux, M.; Van Tilburg, T.; Broese Van Groenou, M. Changes in contact and support exchange in personal networks after widowhood. Pers. Relatsh. 2007, 14, 457–473. [Google Scholar] [CrossRef] [Scilit]
- Cohen-Mansfield, J.; Shmotkin, D.; Malkinson, R.; Bartur, L.; Hazan, H. Parental bereavement increases mortality in older persons. Psychol. Trauma 2013, 5, 84–92. [Google Scholar] [CrossRef] [Scilit]
- Shear, M.K.; Mulhare, E. Complicated Grief. Psychiatr. Ann. 2008, 38, 662–670. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Z.; Li, L.W.; Xu, H.; Liu, J. Does widowhood affect cognitive function among Chinese older adults? SSM Popul. Health 2019, 7, 100329. [Google Scholar] [CrossRef] [Scilit] [PubMed]
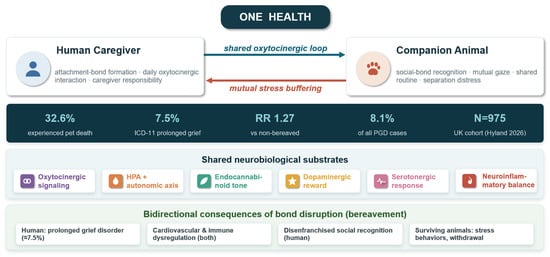
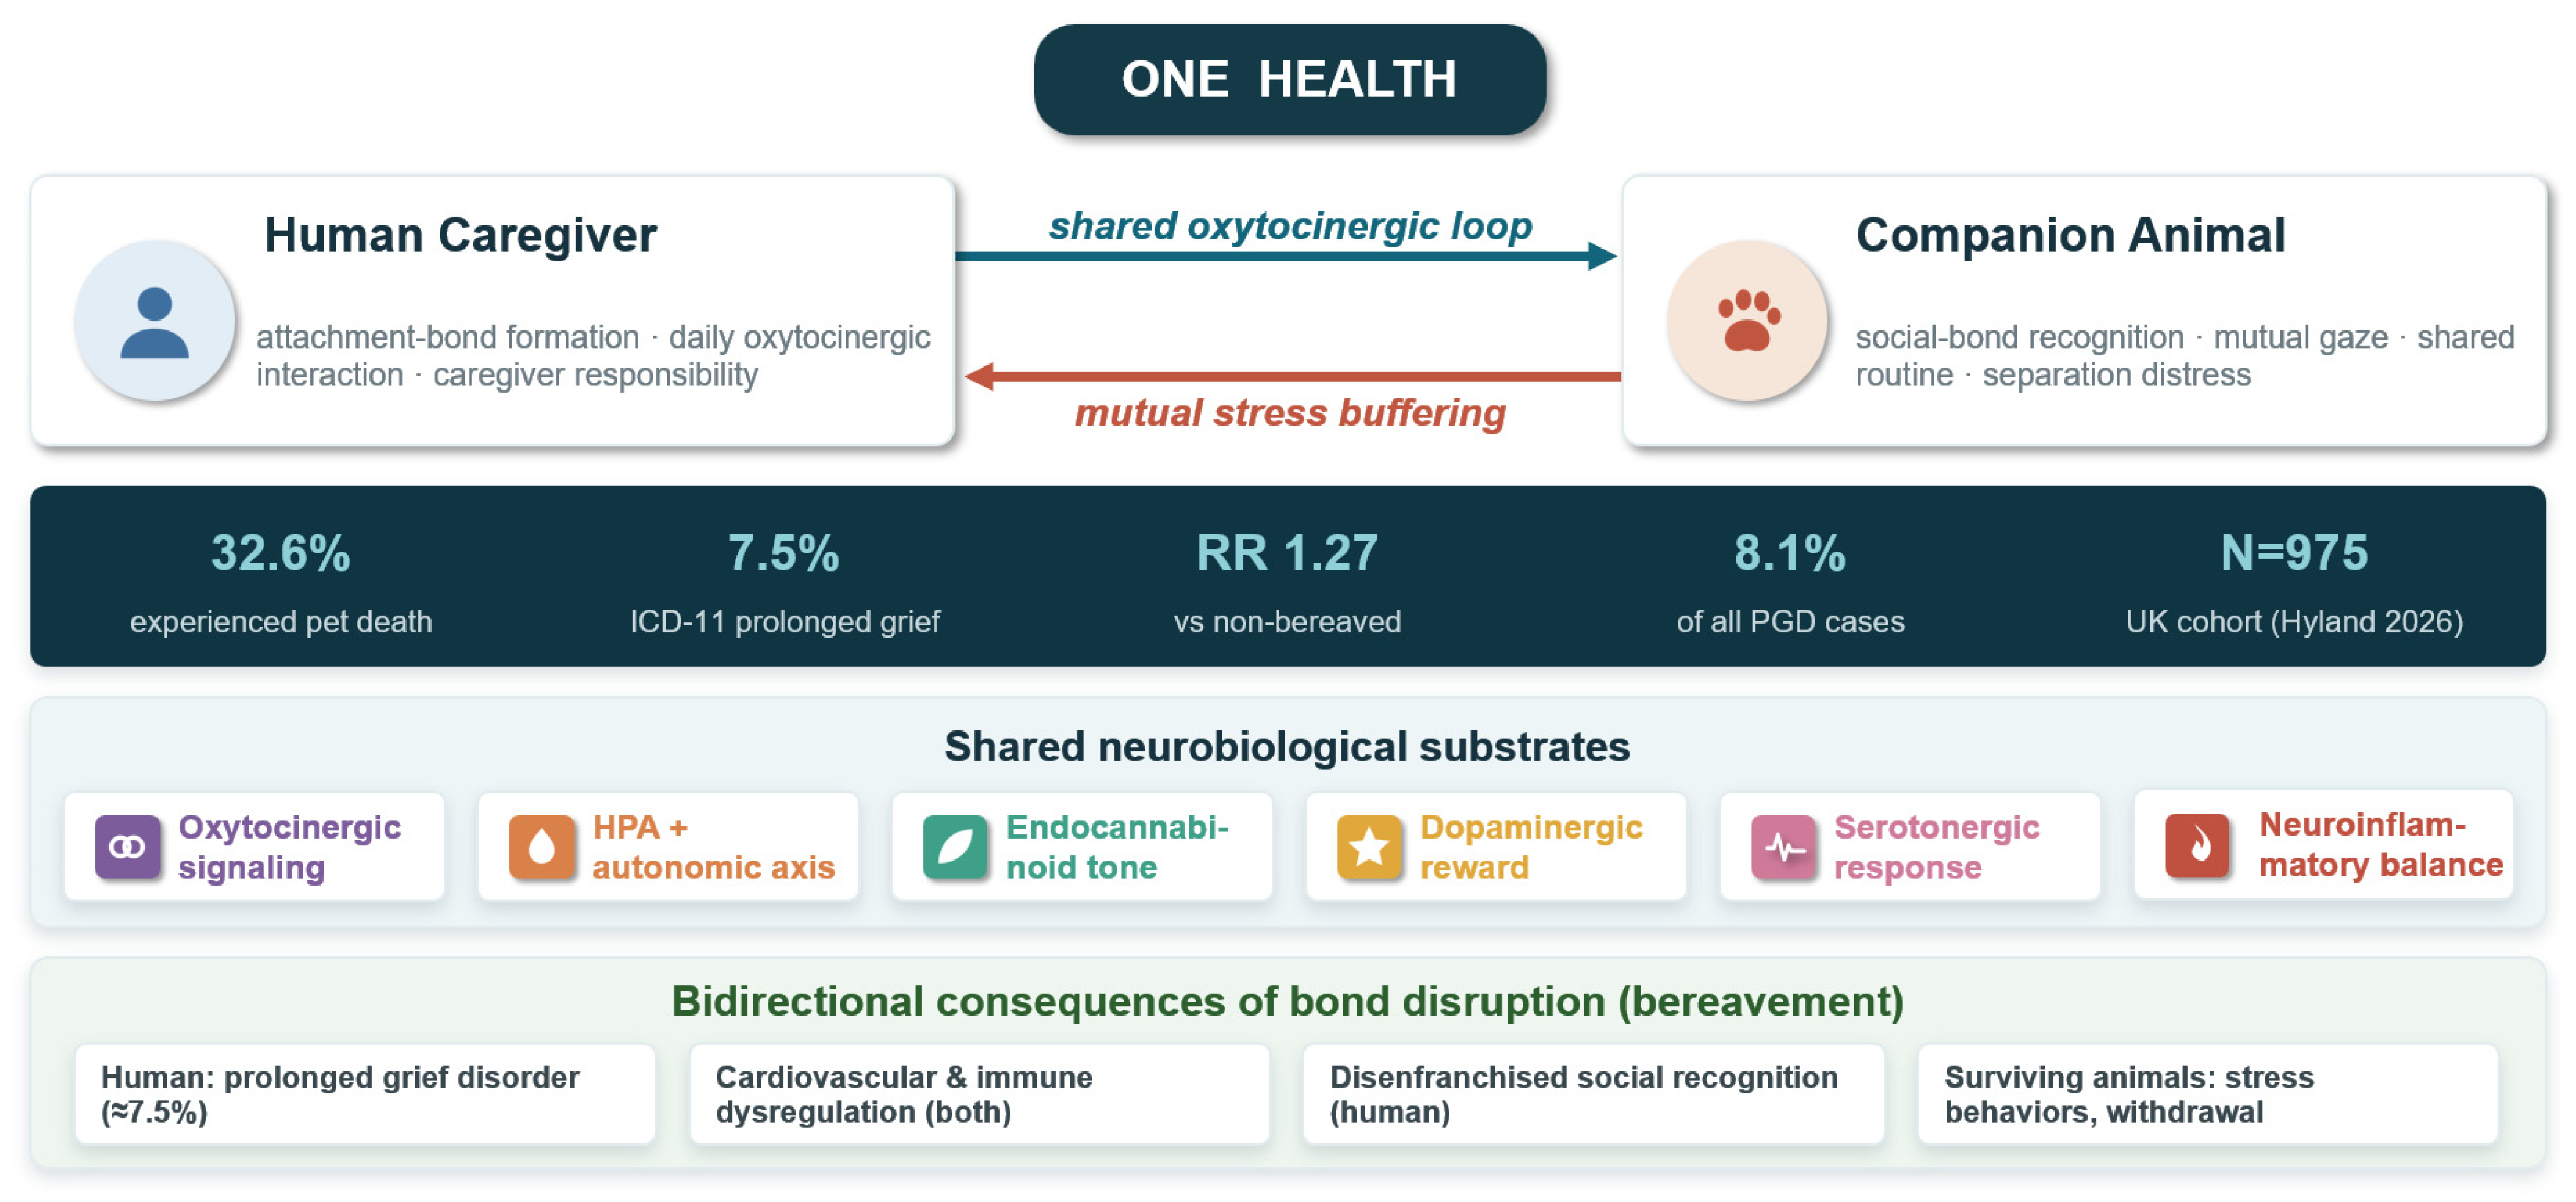

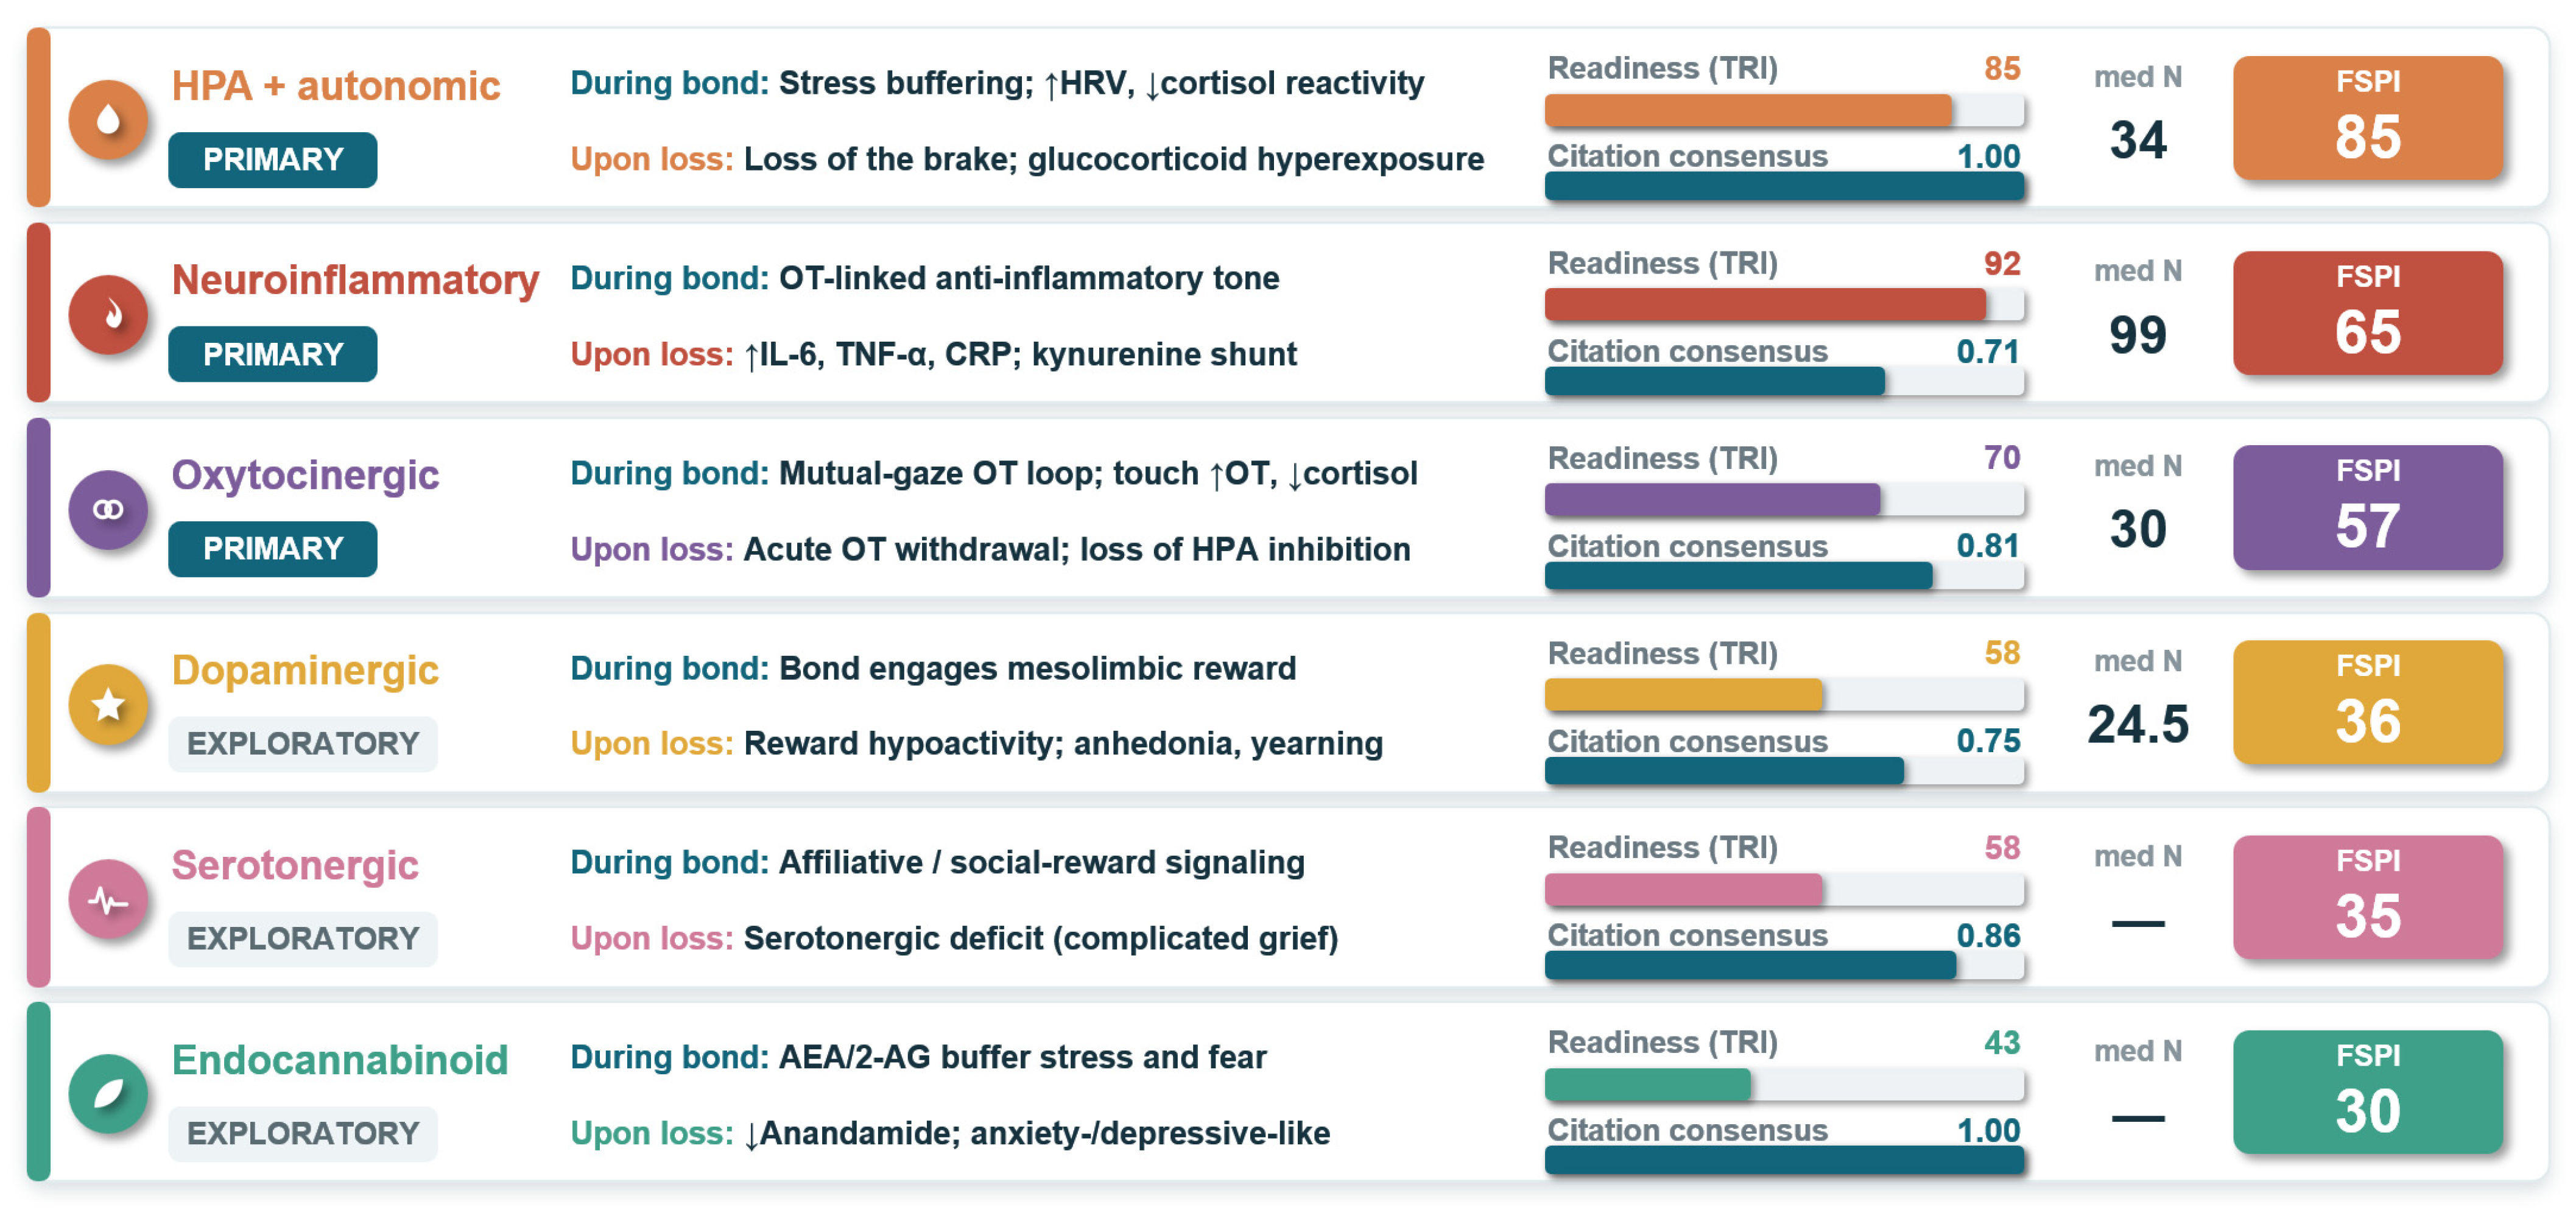
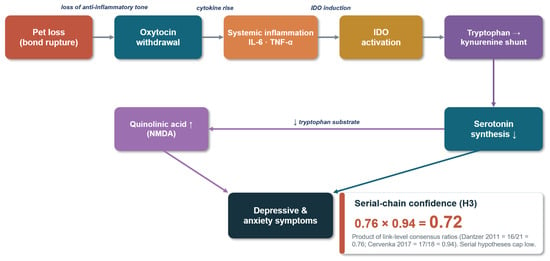
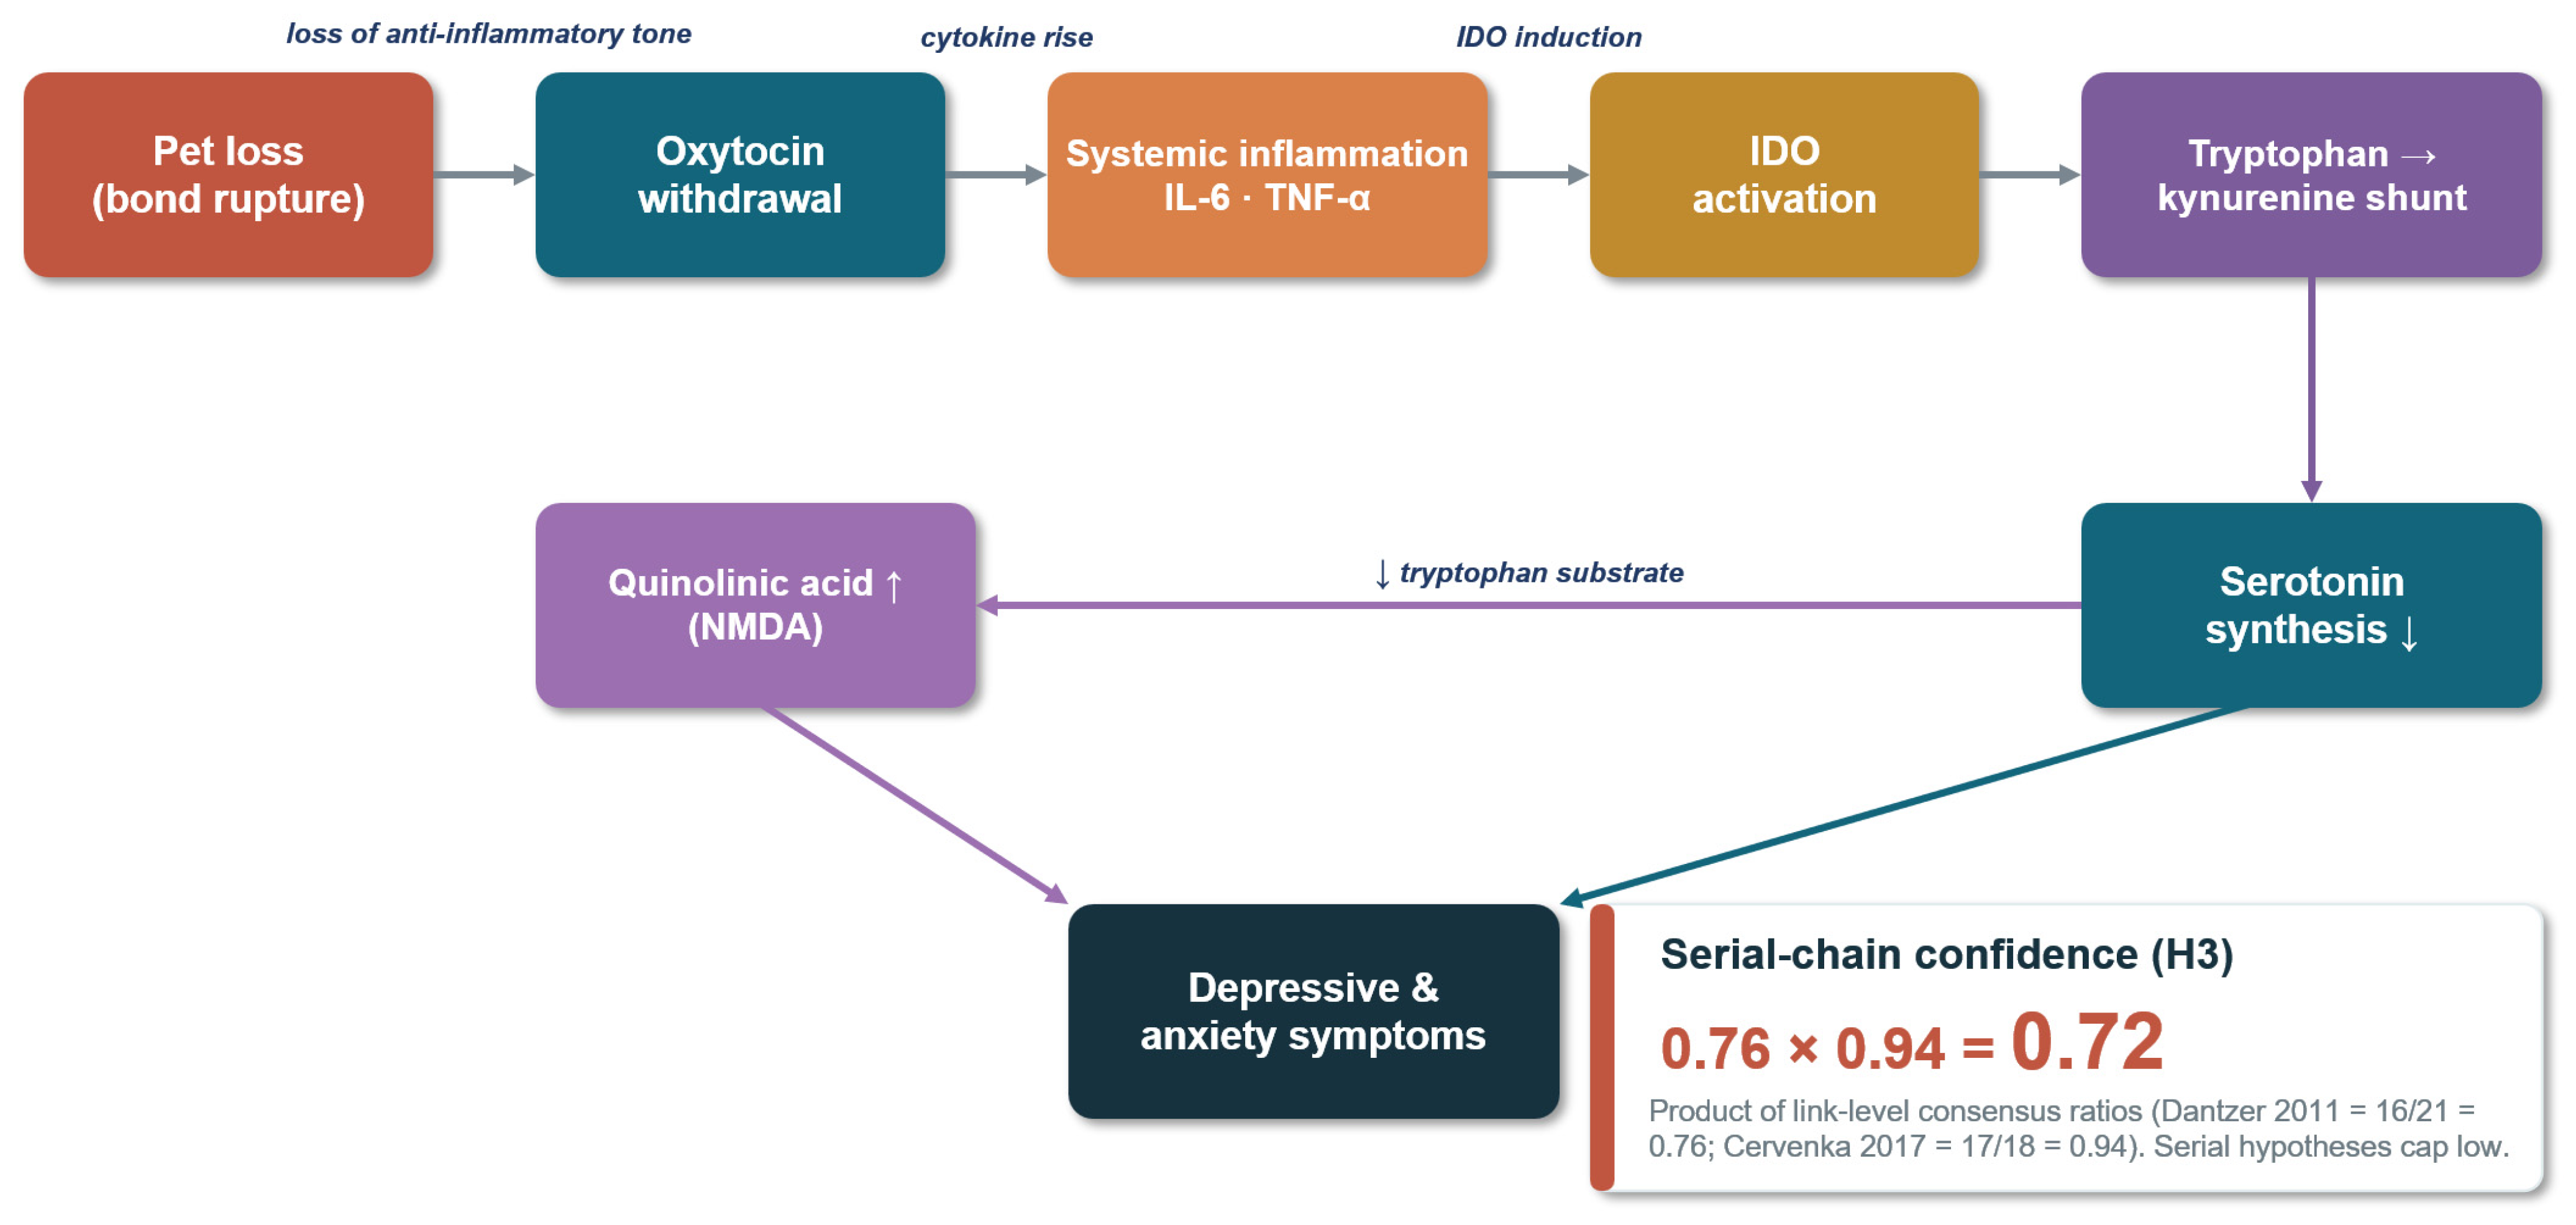
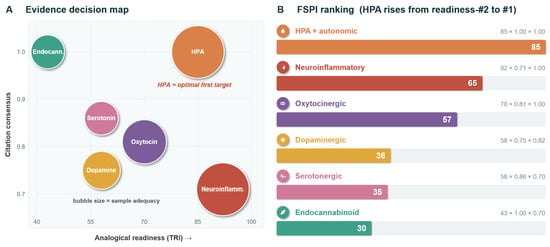
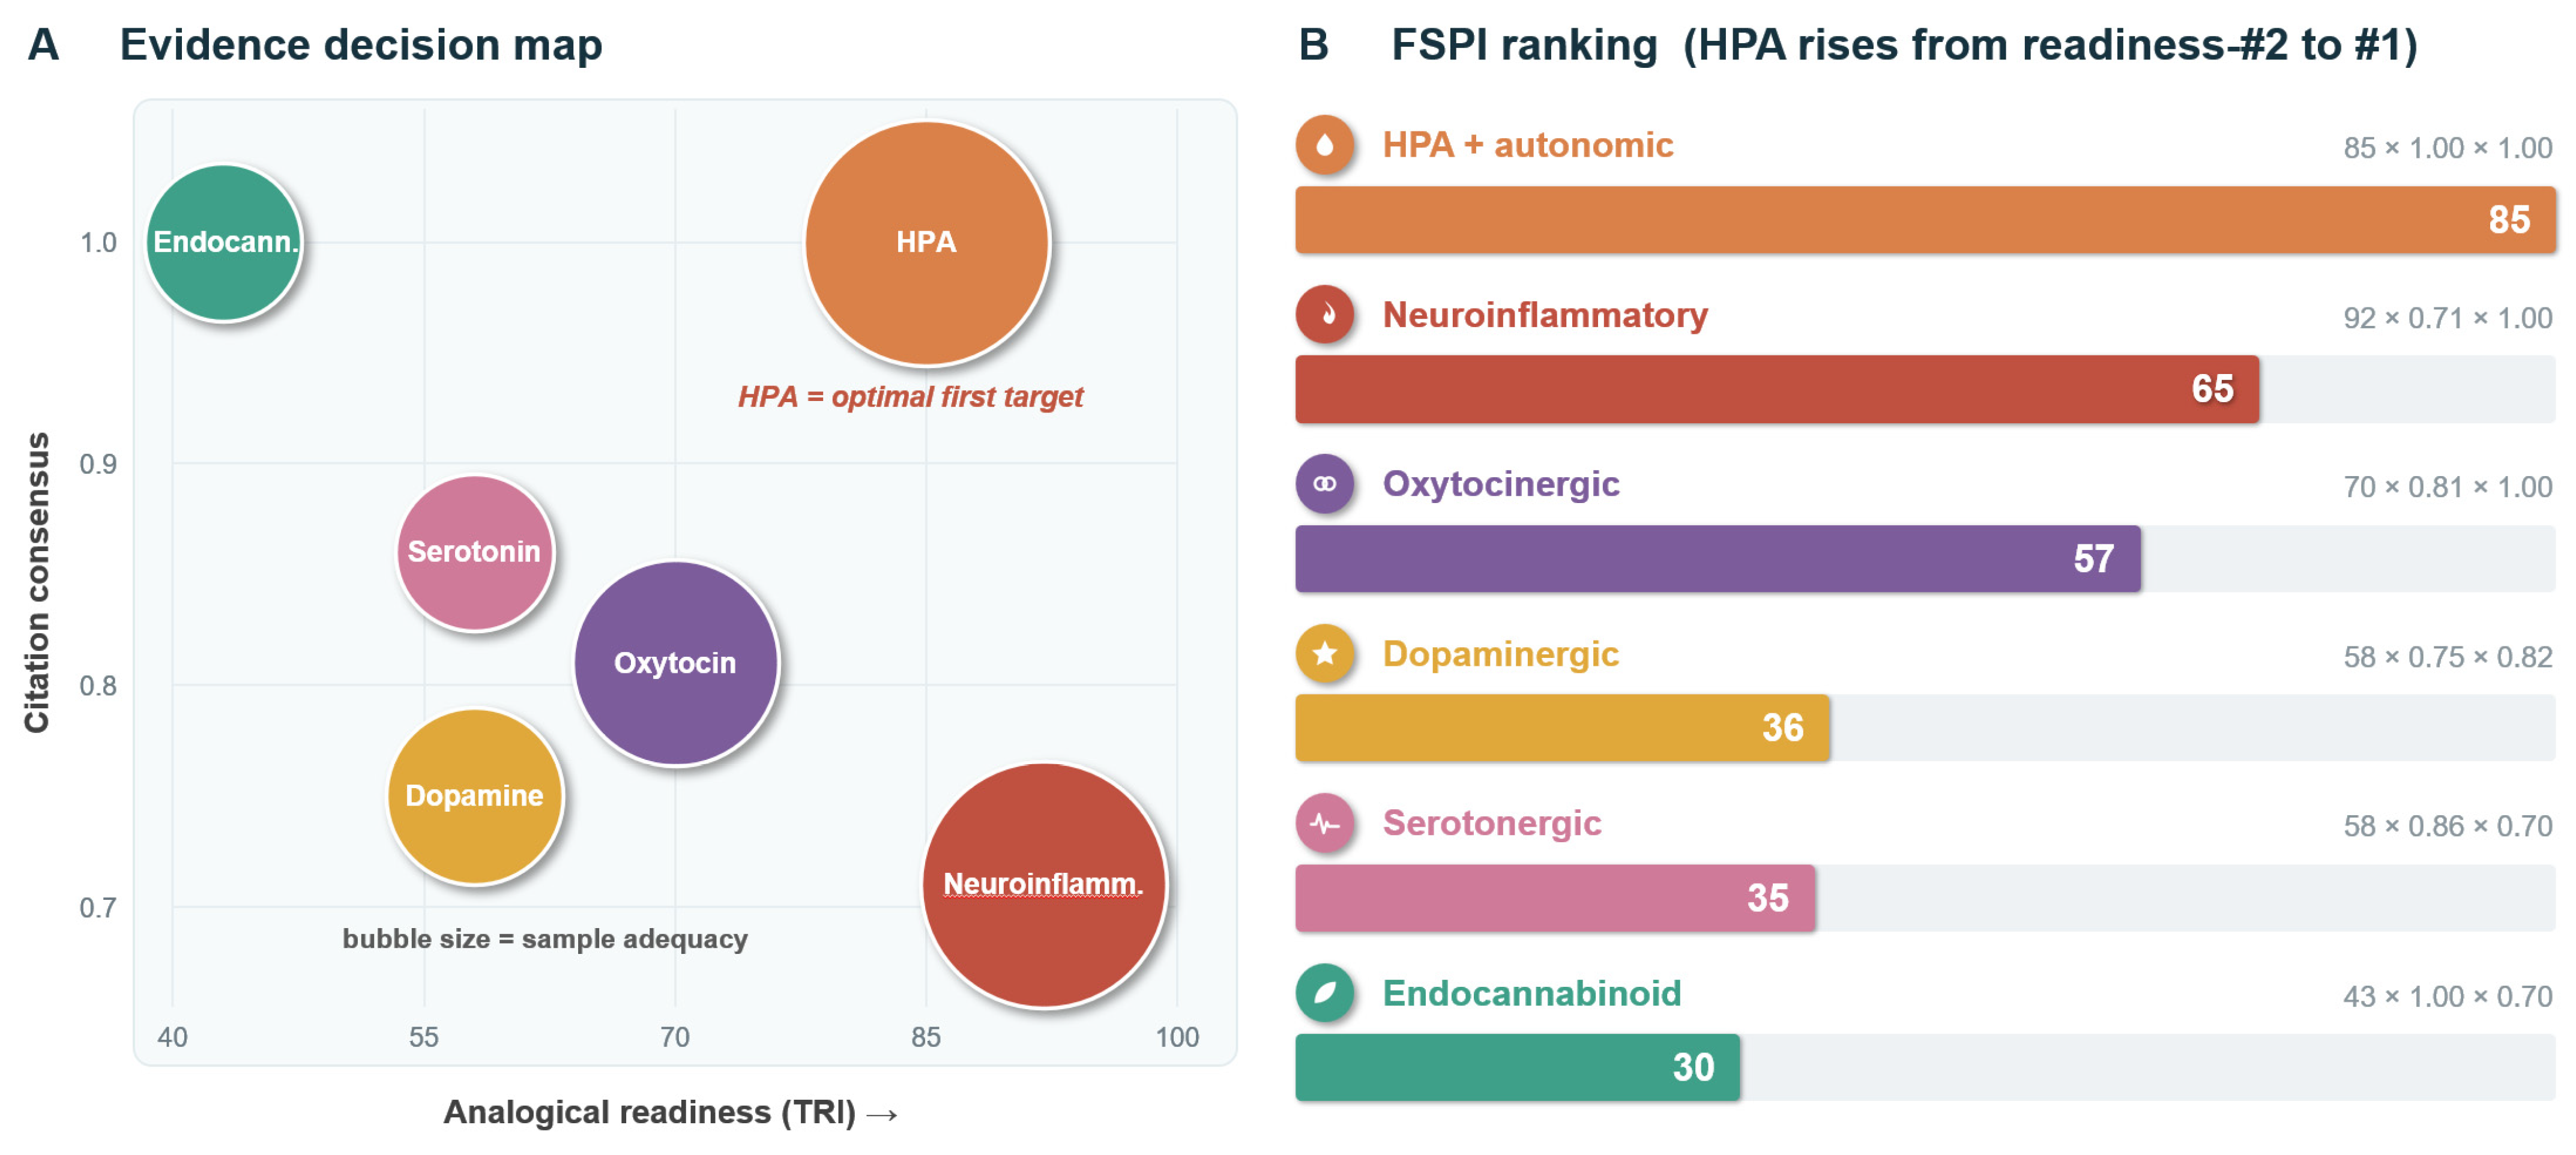
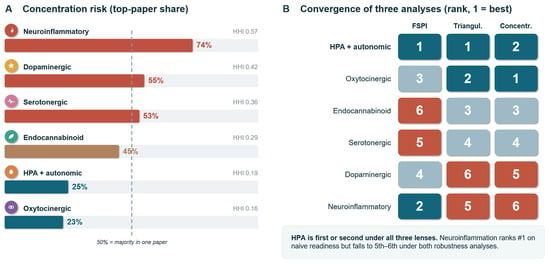
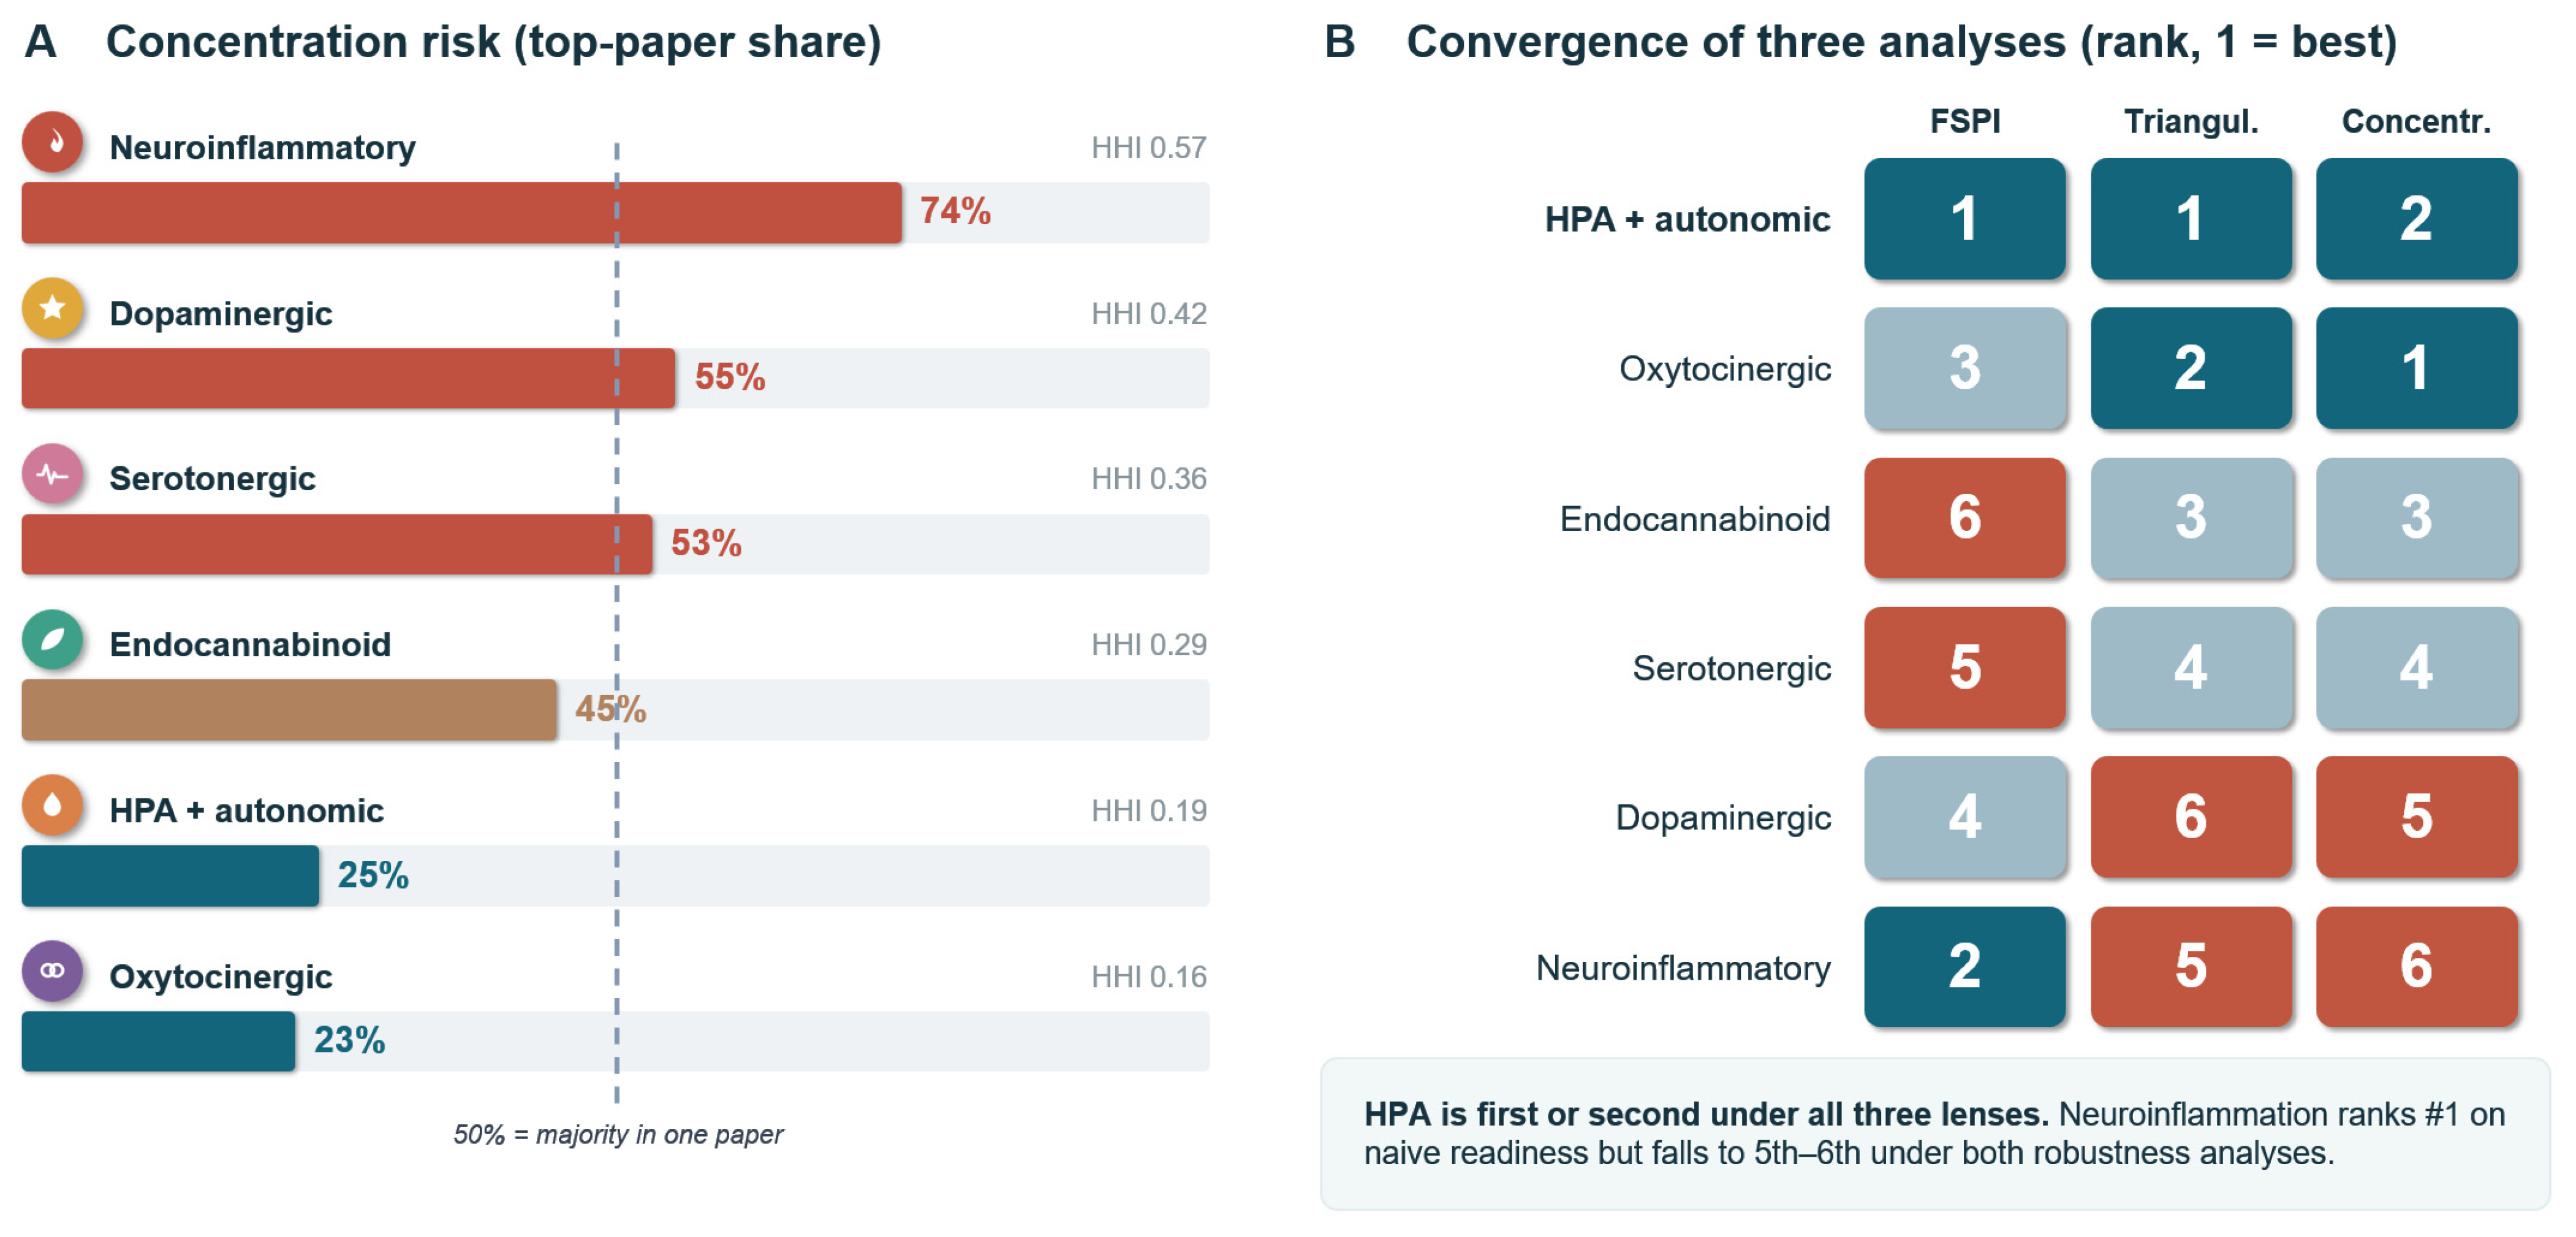
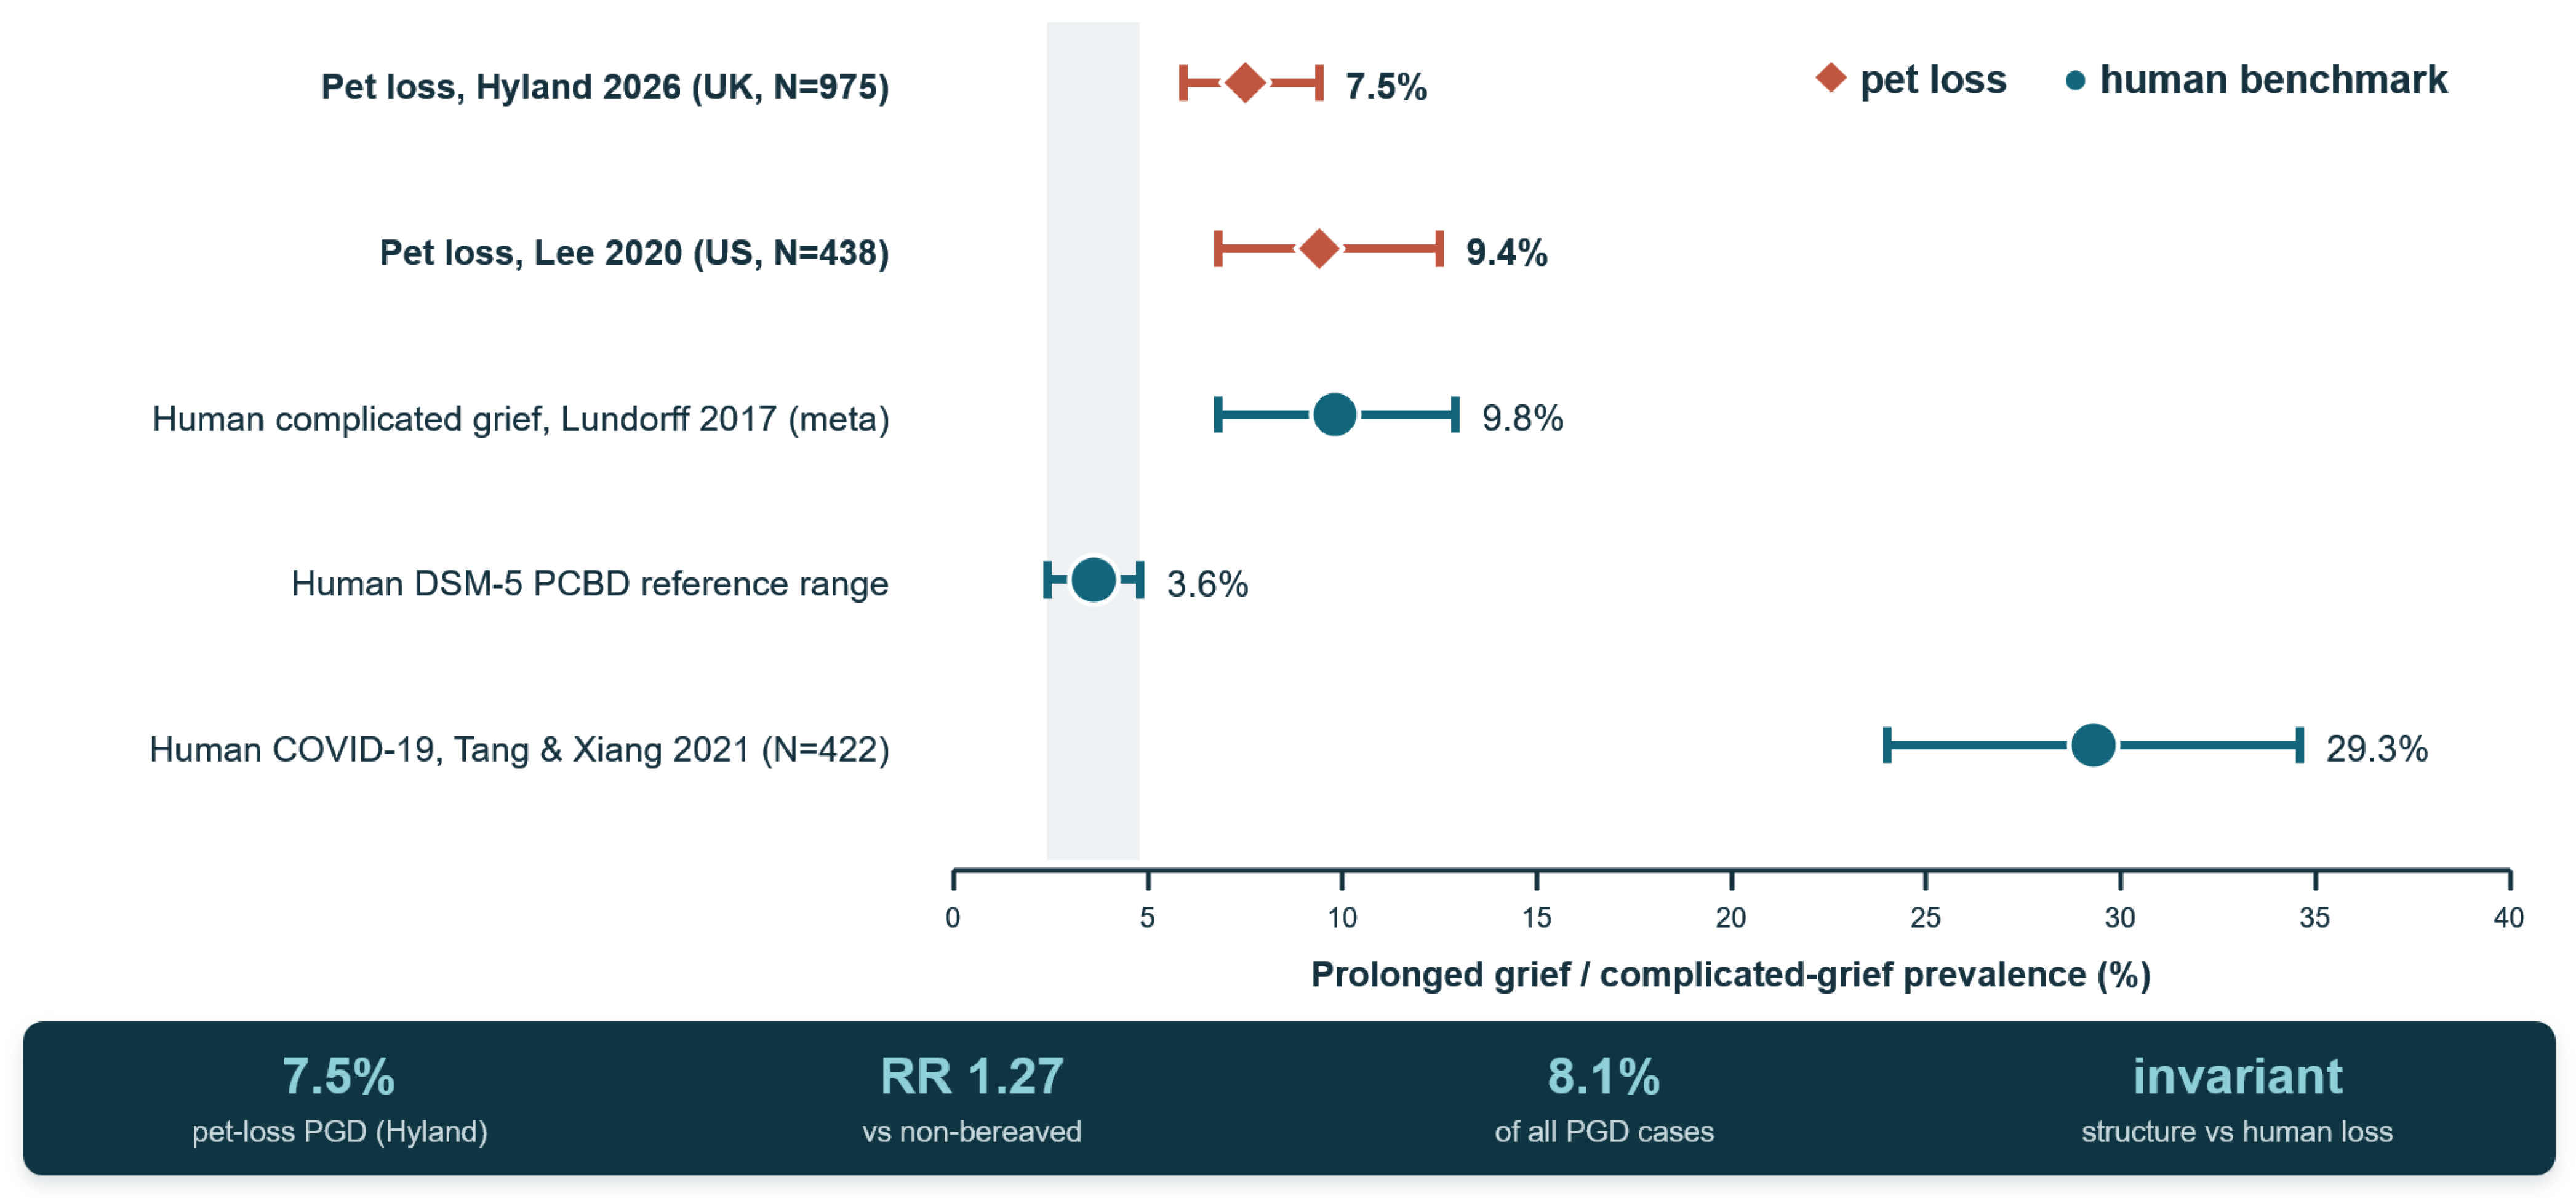

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.