


Abstract
Bacterial endophthalmitis is an intraocular infection that causes rapid vison loss. Pathogens can infect the intraocular space directly (exogenous endophthalmitis (ExE)) or indirectly (endogenous endophthalmitis (EnE)). To identify predictive factors for the visual prognosis of Japanese patients with bacterial endophthalmitis, we retrospectively examined the bacterial endophthalmitis characteristics of 314 Japanese patients and performed statistics using these clinical data. Older patients, with significantly more severe clinical symptoms, were prevalent in the ExE group compared with the EnE group. However, the final best-corrected visual acuity (BCVA) was not significantly different between the ExE and EnE groups. Bacteria isolated from patients were not associated with age, sex, or presence of eye symptoms. Genus Streptococcus, Streptococcus pneumoniae, and Enterococcus were more prevalent in ExE patients than EnE patients and contributed to poor final BCVA. The presence of eye pain, bacterial identification, and poor BCVA at baseline were risk factors for final visual impairment.
1. Introduction
Bacterial endophthalmitis is a purulent inflammation of the intraocular fluids, i.e., the vitreous and the aqueous humor that leads to significant visual loss with progression in hours to days. The foundation of the treatment for bacterial endophthalmitis is focal and systemic administration of antibiotics; vitrectomy is performed if the endophthalmitis is severe. Unless the patient receives appropriate treatment early in the disease, it causes irreversible damage to the retina, which results in a high probability of vision loss [1,2,3,4,5,6,7,8].
Bacterial endophthalmitis is classified into two groups on the basis of the infection route (exogenous or endogenous). Exogenous endophthalmitis (ExE) is mainly caused by eye surgery [9,10,11,12,13,14,15,16,17,18,19,20,21,22,23] and trauma [24,25,26] due to the direct infection of pathogens into the eye from outside. Acute endophthalmitis appears as a postoperative complication within 1–2 weeks after the surgical intervention, most commonly on the third to fifth postoperative day [1,2]. In endogenous endophthalmitis (EnE), there is an infection focus (or foci) somewhere else in the body, and then the pathogens are transferred to the eye [27,28,29,30,31,32,33,34].
Several types of causative pathogens have been reported, with a trend to different types of causative pathogens for ExE and EnE. In eyes with ExE, the normal conjunctival florae are the typical causative pathogens [35,36,37,38]. Conversely, bacteremia can cause EnE.
Despite recent advances in the science and technology for the identification of pathogens using polymerase chain reaction (PCR) [39,40] and matrix-assisted laser desorption/ionization time-of-flight mass spectrometry [41,42], new antibiotics, and minimally invasive vitrectomy, bacterial endophthalmitis remains a severe intraocular infection that causes a high risk of vision loss. Recently, a large cohort study in Japanese patients with postoperative endophthalmitis after cataract surgery showed that the incidence of endophthalmitis was 0.025% [12]. In the present study, we retrospectively examined the characteristics of 314 bacterial endophthalmitis cases seen in multiple institutions of the Japan Clinical REtina STudy group (J-CREST) in a 10-year span and performed statistics to identify predictive factors for visual prognosis using these clinical data.
2. Results
2.1. Patients’ Characteristics
The patients’ characteristics are shown in Table 1. Briefly, 278 patients (88.5%) developed infection unilaterally, and 242 eyes (69.1%) developed ExE. Additionally, in 84.2% and 15.8% of unilateral cases, the patients developed ExE and EnE, respectively. Bacteria were identified in 117 eyes (37.7%). Vitrectomy was performed in 276 eyes (79.1%) as a primary treatment. Overall, BCVA had significantly improved 3 months after treatment (p < 0.0001).
Table 1.
Patients’ characteristics.
2.2. Better Vision Group versus Legal Blindness Group
We performed univariate and multivariate analyses for contributions of nine factors: age, sex, right or left eye, ExE or EnE, duration from the onset (days), presence of eye symptoms (eye pain and ciliary injection), bacterial identification, and initial BCVA (Table 2).
Table 2.
Characteristics of patients in the “better vision” and “legal blindness” groups.
Univariate analysis showed that four factors, presence of eye pain (p < 0.0001), presence of ciliary injection (p = 0.01), bacterial identification (p < 0.0001), and poor initial BCVA (p < 0.0001), significantly contributed to legal blindness. Multivariate analysis of these four factors showed that three factors (presence of eye pain, bacterial identification, and poor BCVA at the baseline) significantly contributed to the legal blindness group (Table 2).
2.3. Primary Endpoint: Contribution of Initial BCVA to Visual Prognosis
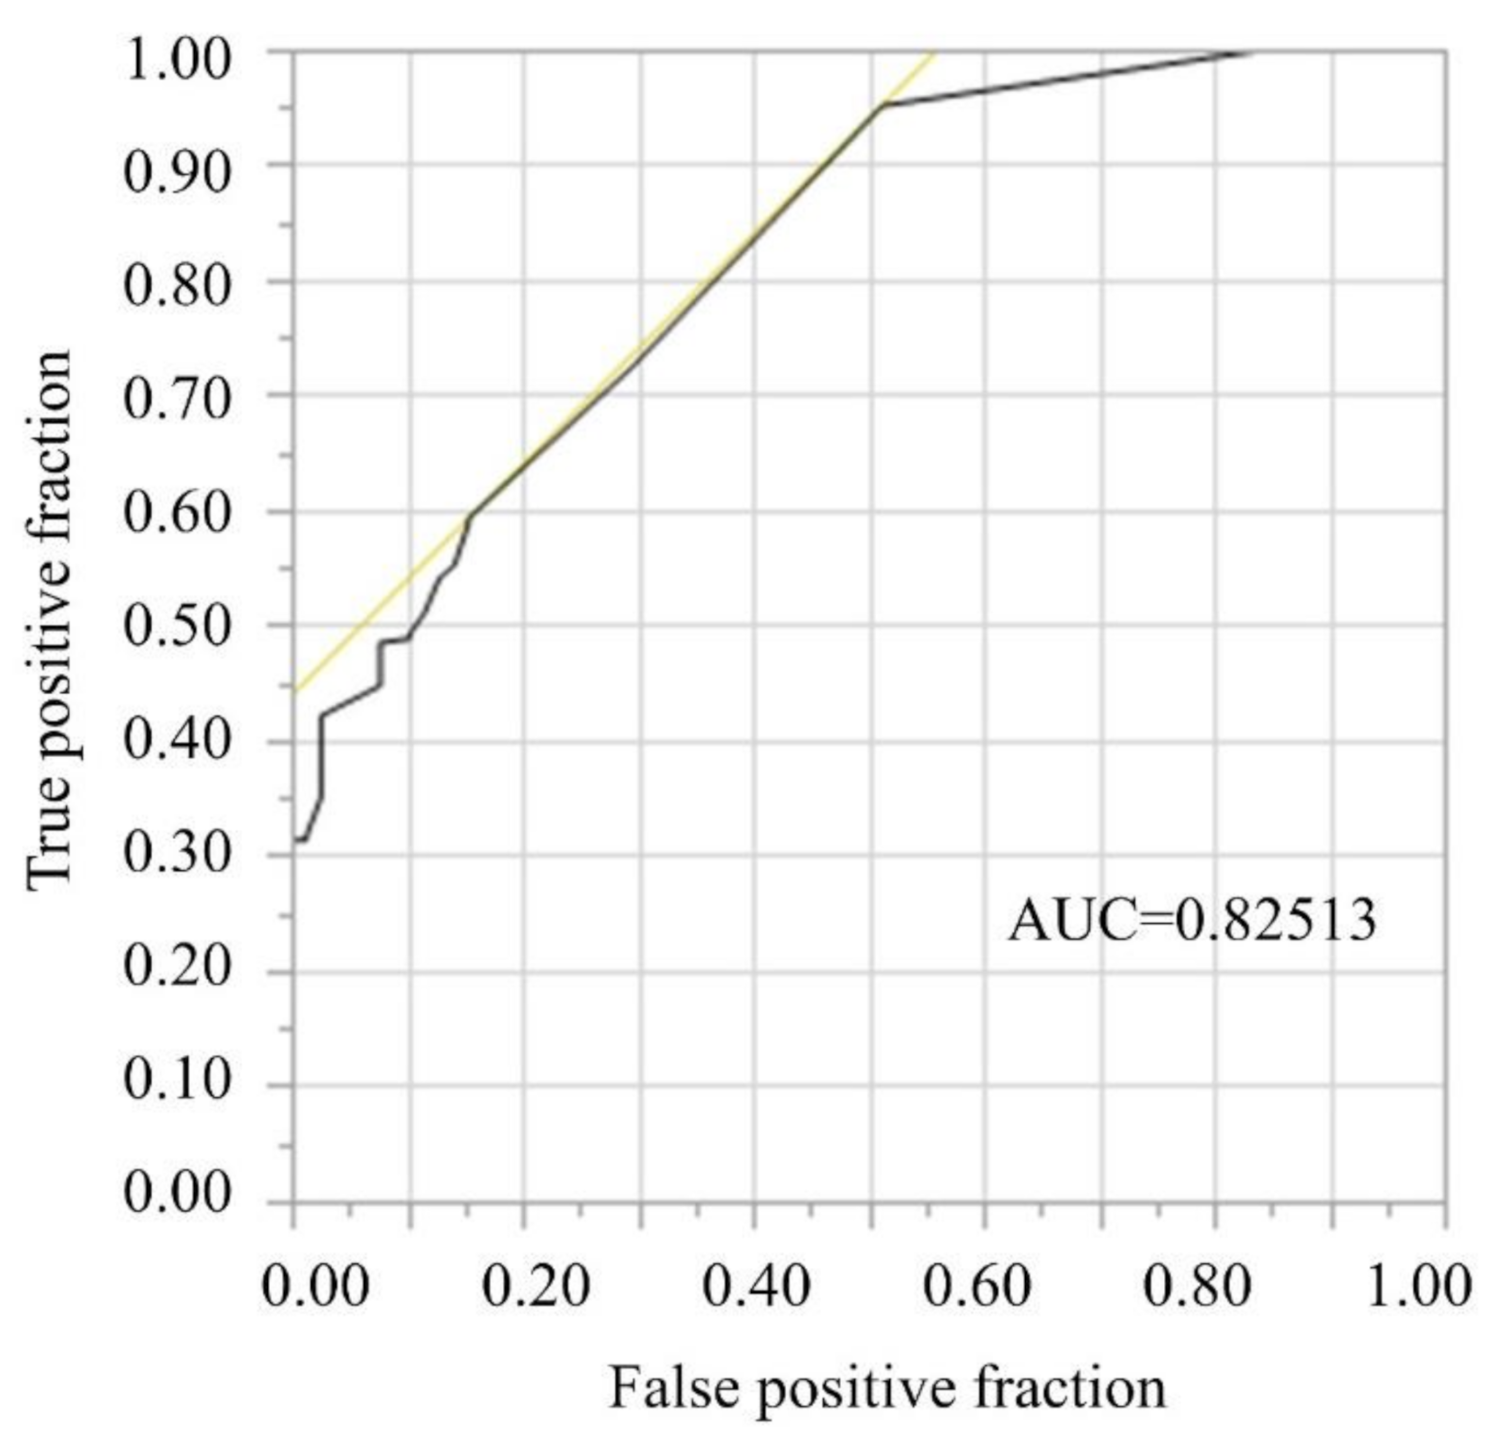
The receiver operating characteristic (ROC) curve of the better vison group, as shown in Figure 1, suggests that the area under the curve (AUC) for the ROC curve was 0.83. The cut-off value was 1.7 logMAR (Snellen ≥ 6/300).
Figure 1.
The receiver operating characteristic (ROC) curve of the better vison group. The area under the curve (AUC) for the ROC curve was 0.83. The cut-off value was 1.7 logMAR (Snellen ≥ 6/300).
2.4. Secondary Endpoints: Exogenous versus Endogenous Endophthalmitis
To investigate the difference between ExE and EnE, we compared the characteristics in the two groups (Table 3). Briefly, the ExE patients were older than the EnE patients (p = 0.0004). Significantly more of the ExE patients presented with severe clinical symptoms, including eye symptoms (eye pain and ciliary injection), and the ExE patients had worse initial BCVA than did the EnE patients (p < 0.0001, p = 0.0001, respectively). However, the final BCVAs between the two groups did not differ significantly.
Table 3.
Characteristics of patients in the exogenous endophthalmitis (ExE) and endogenous endophthalmitis (EnE) groups.
2.5. Secondary Endpoints: Analyses of pathogens
We classified the pathogens into eight types: coagulase-negative staphylococci (CoNS), Staphylococcus aureus, Genus Streptococcus, Streptococcus pneumoniae, Enterobacteriaceae, Enterococcus, other bacteria, and fungus. Characteristic associated with the eight types are shown in Table 4. Briefly, age, sex and presence of eye symptoms (eye pain and ciliary injection) did not show any significant differences between the eight types. CoNS, Streptococcus pneumoniae, Enterococcus, and other bacteria were detected at significantly higher rates in patients with ExE than in those with EnE. The best initial BCVAs were seen in patients with fungus, and the worst final BCVAs were seen in patients with Genus Streptococcus, Streptococcus pneumoniae, or Enterococcus.
Table 4.
Characteristics of patients grouped by bacterial types.
2.6. Secondary Endpoints: Analyses of Selected Treatments
To investigate the differences between the therapy types, we determined the characteristics in three groups, as shown in Table 5. Briefly, vitrectomy was performed in older patients, and in eyes with ExE, shorter duration from the onset, eye pain, ciliary injection, bacterial identification, and poor initial BCVA, which is consistent with the consensuses of retinal surgeons in J-CREST. Eyes that needed only antibiotic eye drops and/or intravitreal antibiotics and/or systemic antibiotics had a very good chance of achieving good final vision.
Table 5.
Patients’ characteristics according to therapy types.
3. Discussion
We showed here the characteristics of 314 Japanese patients (350 eyes) with bacterial endophthalmitis. Ocular pain, bacterial identification, and poor BCVA at baseline contributed to the final visual impairment. In particular, if the initial BCVA was under 1.7 logMAR (Snellen ≥ 6/300), the final BCVA was likely to stay below 1.0 logMAR (Snellen 6/60 or better).
Our results were similar to several reports in the literature from other countries regarding the rate of bacterial identification (our results: 37.7% by culturing and PCR, 39.7% by culturing [7], 43.4% by culturing [23], 23% by culturing [31], 28.6% by culturing [33], 38.6% by PCR [39], 30% by culturing [40], and 45.5% by culturing [42]). PCR has become a commonly used tool for the identification of ocular pathogens [39,40], but the identification of bacteria is still difficult. However, we showed that the presence of identifiable bacteria is one of the risk factors for final visual impairment, which suggests that substantial amounts of intraocular pathogens are needed for bacterial detection. As PCR technology progresses, the rate of bacterial identification becomes much higher; with further progress, bacterial identification, which the present study showed was a risk factor for final visual impairment, will no longer be a risk factor.
BCVA in patients with endophthalmitis improved significantly after treatment, and the percentage of patients with final BCVA ≤ 1.0 logMAR was 76.6%, which suggests that our treatments for endophthalmitis in J-CREST were not inferior to those in other reports (33.3% (Snellen 20/31 or better) [5], 28% (Snellen 20/120 or better) [6], 44% (Snellen 20/40 or better) [18], 32.7% (Snellen 20/40 or better) [22], 71% (Snellen 5/200 or better) [43], 34.5% (Snellen 20/400 or better) [44], and 34.5% (Snellen 20/60 or better) [45]). Additionally, the ophthalmologists in J-CREST (all are retina specialists) tended to perform a vitrectomy as a primary treatment for endophthalmitis, which is likely a worldwide trend [4,24,46,47].
In the present analyses, three factors (presence of eye pain, bacterial identification, and poor initial BCVA) significantly contributed to legal blindness, which suggests that a severe condition at baseline is a risk factor for later visual impairment. This is not very surprising, as the same findings appear in the literature: eye pain [11], bacterial identification [29,48,49], and poor initial BCVA [11,25,26,29,30,33,50]. Other factors that have been reported as risk factors include: younger age (<85 years) [21], female sex [30], presence of an intraocular foreign body [25], a higher number of intravitreal injections [25,30], the type of injury (rupture) [26], retinal detachment [26,48], and proliferative vitreoretinopathy [26]. The most important risk factor for visual impairment at 12 weeks was poor initial BCVA. The present study showed that the final BCVA could remain under 1.0 logMAR when the baseline BCVA was under 1.7 logMAR (Snellen 6/300 or better). This cut-off value is suggested to be a good parameter for informed consent and for prognosis of final BCVA in patients with endophthalmitis.
In this study, there were 242 eyes (69.1%) with ExE and 108 eyes (30.9%) with EnE. From the literature, the rates of ExE are 85.0% [5], 92.2% [7], 82.8% (Enterococcus endophthalmitis) [44], and 78.4% [46]. Thus, the present study showed an EnE rate that was higher than the results in the literature. ExE was observed in older patients and was significantly associated with presentation of severe clinical symptoms. However, the final BCVAs between the two groups were not significantly different. In developing countries, ocular trauma is the main cause of ExE [7]. Conversely, in the developed countries, ExE is mainly caused by ocular surgeries, such as cataract surgery, so there are much older patients with ExE than with EnE.
Patients with ExE after ocular surgeries or trauma showed rapid worsening of eye conditions, due to the direct invasion of pathogens. Therefore, the infection speed in the eyeball can be faster than it is with EnE. The bacterial growth corresponds with the severe clinical symptoms. Although the final BCVA was not significantly different between the ExE and EnE groups, patients with EnE often have poor general health condition, e.g., immunosuppressive state, a terminal stage of cancer, and cannot communicate well with medical staff, so the clinical symptoms may simply appear milder than in ExE. Additionally, because of the rapid worsening of eye conditions in eyes with ExE, patients with ExE may consult a doctor sooner than do patients with EnE, which suggests one possible reason for the lack of difference in final BCVA between ExE and EnE patients. Moreover, we sometimes had cases in which it was difficult to distinguish between noninfectious uveitis and EnE. We, as ophthalmologists, should keep the possibility of EnE in mind.
In eyes with EnE, the pathogens are carried by the blood stream transarterially. Therefore, we think that infection is more common in the left eye than in the right eye, but the present study did not prove that.
Regarding the types of pathogens observed, CoNS, Enterococcus, Streptococcus pneumoniae, and other bacteria were detected significantly more commonly in patients with ExE than EnE. CoNS, Enterococcus, and Streptococcus pneumoniae are normal conjunctival florae, and their detection rate increases with patient age [35,36,37,38]. The best baseline BCVA was seen in patients with fungal infection, and poorest final BCVA was seen in patients with Genus Streptococcus, Streptococcus pneumoniae, and Enterococcus. Fungal endophthalmitis is usually detectable at an early stage in hospitals, so the clinical symptoms at baseline may be mild. Conversely, Enterococcus, Streptococcus pneumoniae, and Genus Streptococcus are highly virulent, which suggests that the ocular tissue is easily harmed. Therefore, we must rapidly make these diagnoses.
Vitrectomy was performed in eyes with severe infection. It is reasonable for any ophthalmologist to treat endophthalmitis. Studies have concluded that vitrectomy is effective for the initial treatment of endophthalmitis; early vitrectomy (i.e., within 24 h) might be helpful in achieving a better visual outcome [2,4,46,51], and a primary vitrectomy demonstrated greater visual improvement [2,18,47]. However, the European Vitreo-Retinal Society Endophthalmitis Study showed similar outcomes after treatment with intravitreal antibiotics alone compared with intravitreal antibiotics and vitrectomy within 1 week of presentation [45]. Interestingly, the present study showed that 94% of eyes without intravitreal antibiotics or vitrectomy had final BCVA under 1.0 logMAR, which suggests that J-CREST retina specialists were able to decide the appropriate treatments, depending on the disease severity.
We acknowledge several limitations to the present study. First, the bacterial identification rates may have differed between centers because the companies that performed the tests were not standardized, i.e., different laboratories were used by the different hospitals in this multicenter retrospective study. Second, the follow-up duration was only 3 months, so the results may change when we examine data for longer follow-up periods.
In summary, we retrospectively examined the characteristics of Japanese patients with endophthalmitis and showed that eye pain, bacterial identification, and poor BCVA at baseline were the three risk factors for visual impairment at 12 weeks. Notably, the final BCVA could remain under 1.0 logMAR when the baseline BCVA was under 1.7 logMAR (Snellen ≥ 6/300). Endophthalmitis remains a severe ocular infection, but we can challenge it with rapid and bold treatments, with advances in medical knowledge and technology.
4. Materials and Methods
4.1. Study Design and Eligibility
This was a multicenter, retrospective study of consecutive patients with bacterial endophthalmitis in the following 13 J-CREST institutions: Hyogo College of Medicine, Sapporo City General Hospital, the University of Tsukuba, Shiga University of Medical Science, the National Defense Medical College, Kobe University Graduate School of Medicine, Nara Medical University School of Medicine, Mie University, Kurume University School of Medicine, Yamaguchi University, Tokushima University, St. Marianna University School of Medicine, and Kagoshima University Graduate School of Medical and Dental Sciences, between January 2010 and November 2019, inclusive. The data, analytic methods, and study materials will be made available to other researchers for purposes of reproducing the results.
4.2. Patients
At each hospital in the J-CREST group, data from patients with bacterial endophthalmitis were analyzed using medical records. The bacterial endophthalmitis was judged by a retinal specialist in each hospital to have a “definite” diagnosis (could prove pathogens) or “a strong suspicion” (could not prove pathogens). The observation period was >12 weeks for all analyzed subjects. Among the 325 Japanese patients (364 eyes) with bacterial endophthalmitis initially enrolled in the present study, data from 11 patients were excluded from the analysis because of a lack of follow-up at 12 weeks. Therefore, a total of 350 eyes in 314 patients were analyzed.
4.3. Protocol
Data were extracted from medical records in the various hospitals and sent to the data center in the Department of Ophthalmology, Hyogo College of Medicine. We analyzed patient age, sex, type of bacterial endophthalmitis, duration from the onset of symptoms to the initial treatment, main complaint (presence of ocular pain and ciliary injection), whether bacteria were identified, details of identified bacteria, and best-corrected visual acuity (BCVA) at baseline and 4 and 12 weeks after treatment started. BCVA was measured on a Japanese Snellen chart, with values converted to log minimum angle of resolution (logMAR). For analysis, patients were grouped on the basis of BCVA at 12 weeks. Those with BCVA ≤ 1.0 logMAR (Snellen 6/60 or better) are referred to as the “better vision group” versus those with BCVA > 1.0 logMAR (Snellen < 6/60) are the “legal blindness” group [52].
4.4. Endpoints
The primary endpoint was to assess the contribution of initial BCVA to visual prognosis. Therefore, we examined the difference between the patients in the better vision and legal blindness group at 12 weeks. We also examined the difference between ExE and EnE and determined pathogens that contributed to poor BCVA. Additionally, this study compared between patients in the better vision and legal blindness groups. Risk factors for the legal blindness group were investigated based on the patients’ characteristics, eye symptoms, and initial BCVA.4.5. Statistical Analyses
Categorical variables are presented as numbers and percentages and compared using the Chi-square test. Continuous variables are expressed as the mean ± standard deviation (SD), or the median and interquartile range, and compared using a t-test or the Wilcoxon rank-sum test. We constructed a multivariable logistic model to explore the variables associated with BCVA at 12 weeks. Logistic regression analysis was performed to identify potential risk factors underlying BCVA at 12 weeks, incorporating all variables with a p-value < 0.01 in the univariate analysis. Uncertain or undetectable data were considered null, and missing values for laboratory data were eliminated from the analyses. All statistical analyses were conducted using JMP 14.2.0 (SAS Institute Inc., Cary, NC). All reported p-values were two-tailed, and the statistical significance level was set at p < 0.05.
Supplementary Materials
The following are available online at https://www.mdpi.com/article/10.3390/pathogens10040390/s1, Table S1: original data of cases, Table S2: original data of eyes.
Author Contributions
Conceptualization, H.I. and K.U.; methodology, H.I., K.U., and Y.T.; validation, K.U., Y.T., S.K., H.T. (Hiroto Terasaki), and F.G.; formal analysis, H.I. and K.U.; investigation, H.I., J.M., S.M., T.S. (Tomoko Sawada), T.K. (Takayuki Kanda), A.M., T.U., M.S., S.Y., T.O., Y.M., T.J., H.T. (Hiroto Terasaki), T.S. (Takaaki Sugisawa), and Y.K.; data curation, H.I.; writing—original draft preparation, H.I. and K.U.; writing—review and editing, K.U., Y.T., T.K. (Takamasa Kinoshita), F.O., M.O., M.T., S.K., N.O., M.K., S.Y., K.K., Y.M., H.T. (Hitoshi Takagi), T.S. (Taiji Sakamoto), and F.G.; supervision, T.S. (Taiji Sakamoto) and F.G.; project administration, H.I.; All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The current study was performed in accordance with the Declaration of Helsinki and with approval from the ethics committee of Hyogo College of Medicine (3380) and the ethics committees of the other participating hospitals.
Informed Consent Statement
This study is retrospective study. Patients were not required to give informed consent to the study because the analysis used anonymous clinical data that were obtained after each patient agreed to treatment by written consent. In addition, we applied Opt-out method to obtain consent on this study using the home page of Hyogo College of Medicine described later. The Opt-out method was approved by the ethics committee of Hyogo College of Medicine (3380).
Data Availability Statement
The data presented in this study are available in supplementary Tables S1 and S2.
Acknowledgments
We thank Claire Barnes, PhD, from Edanz Group (https://en-author-services.edanz.com/ac, accessed on 1 November 2020) for editing a draft of this manuscript.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Lalwani, G.A.; Flynn, H.W., Jr.; Scott, I.U.; Quinn, C.M.; Berrocal, A.M.; Davis, J.L.; Murray, T.G.; Smiddy, W.E.; Miller, D. Acute-onset endophthalmitis after clear corneal cataract surgery (1996–2005). Clinical features, causative organisms, and visual acuity outcomes. Ophthalmology 2008, 115, 473–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pietras-Baczewska, A.; Jasińska, E.; Toro, M.D.; Bonfiglio, V.; Reibaldi, M.; Avitabile, T.; Nowomiejska, K.; Rejdak, R. Urgent Vitrectomy with Vancomycin Infusion, Silicone Oil Endotamponade, and General Antibiotic Treatment in Multiple Cases of Endophthalmitis from a Single Day of Intravitreal Injections—Case Series. J. Clin Med. 2021, 10, 1059. [Google Scholar] [CrossRef] [Scilit]
- Ben Artsi, E.; Katz, G.; Kinori, M.; Moisseiev, J. Endophthalmitis today: A multispecialty ophthalmology department perspective. Eur. J. Ophthalmol. 2016, 26, 71–77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kitsche, M.; Herber, R.; Pillunat, L.E.; Terai, N. Clinical and visual outcome of endophthalmitis patients: A single-center experience. Graef. Arch. Clin. Exp. 2020, 258, 183–189. [Google Scholar] [CrossRef] [Scilit]
- Malmin, A.; Syre, H.; Ushakova, A.; Utheim, T.P.; Forsaa, V.A. Twenty years of endophthalmitis: Incidence, aetiology and clinical outcome. Acta Ophthalmol. 2021, 99, e62–e69. [Google Scholar] [CrossRef] [Scilit]
- Wong, J.S.; Chan, T.K.; Lee, H.M.; Chee, S.P. Endogenous bacterial endophthalmitis: An east Asian experience and a reappraisal of a severe ocular affliction. Ophthalmology. 2000, 107, 1483–1491. [Google Scholar] [CrossRef] [Scilit]
- Yang, X.B.; Liu, Y.Y.; Huang, Z.X.; Mao, Y.; Zhao, L.; Xu, Z.P. Clinical analysis of 1593 patients with infectious endophthalmitis: A 12-year study at a tertiary referral center in western China. Chin. Med. J. 2018, 131, 1658–1665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.; Lin, L.; Li, Y.; Jiang, Z.; Li, C.; Liu, M.; Duan, F.; Lin, X. Etiology, microbiological isolates, and antibiotic susceptibilities in culture-proven pediatric endophthalmitis: A 9-year review. Graef. Arch. Clin. Exp. 2021, 259, 197–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ben Ghezala, I.; Mariet, A.S.; Benzenine, E.; Bron, A.M.; Baudin, F.; Daien, V.; Korobelnik, J.F.; Quantin, C.; Creuzot-Garcher, C. Incidence of acute postoperative endophthalmitis following macular surgery in France between 2006 and 2016. Acta Ophthalmol. 2020, 98, e333–e338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Campbell, R.J.; El-Defrawy, S.R.; Gill, S.S.; Whitehead, M.; Campbell, E.; Hooper, P.L.; Bell, C.M.; Ten Hove, M.W. Association of cataract surgical outcomes with late surgeon career stages: A population-based cohort study. JAMA Ophthalmol. 2019, 137, 58–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Y.H.; Li, Y.H.; Lin, Y.J.; Chen, Y.P.; Wang, N.K.; Chao, A.N.; Liu, L.; Wu, W.C.; Lai, C.C.; Chen, T.L.; et al. Prognostic factors and visual outcomes of pyogenic liver abscess-related endogenous Klebsiella pneumoniae endophthalmitis: A 20-year retrospective review. Sci. Rep. 2019, 9, 1071. [Google Scholar] [CrossRef] [Scilit]
- Inoue, T.; Uno, T.; Usui, N.; Kobayakawa, S.; Ichihara, K.; Ohashi, Y.; Japanese Prospective Multicenter Study Group for Postoperative Endophthalmitis after Cataract Surgery. Incidence of endophthalmitis and the perioperative practices of cataract surgery in Japan: Japanese Prospective Multicenter Study for Postoperative Endophthalmitis after Cataract Surgery. Jpn. J. Ophthalmol. 2018, 62, 24–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kannan, N.B.; Sen, S.; Mishra, C.; Lalitha, P.; Rameshkumar, G.; Rajan, R.P.; Arumugam, K.K.; Ramasamy, K. Comparative study of microbiological profile and management outcomes of acute endophthalmitis after microincision vitrectomy surgery versus intravitreal injections. Ocul. Immunol. Inflamm. 2020, 3, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lai, H.C.; Tseng, W.C.; Pao, S.I.; Wong, C.S.; Huang, R.C.; Chan, W.H.; Wu, Z.F. Relationship between anesthesia and postoperative endophthalmitis: A retrospective study. Medicine. 2017, 96, e6455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Madan, S.; Kapoor, M.; Pal, H.; Singh, P. Delayed-onset postoperative endophthalmitis. J. Cataract Refract. Surg. 2020, 46, 1064–1065. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morioka, M.; Takamura, Y.; Nagai, K.; Yoshida, S.; Mori, J.; Takeuchi, M.; Sawada, T.; Sone, K.; Fukuyama, H.; Kusuhara, S.; et al. Incidence of endophthalmitis after intravitreal injection of an anti-VEGF agent with or without topical antibiotics. Sci. Rep. 2020, 10, 22122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oshima, Y.; Kadonosono, K.; Yamaji, H.; Inoue, M.; Yoshida, M.; Kimura, H.; Ohji, M.; Shiraga, F.; Hamasaki, T.; Japan Microincision Vitrectomy Surgery Study Group. Multicenter survey with a systematic overview of acute-onset endophthalmitis after transconjunctival microincision vitrectomy surgery. Am. J. Ophthalmol. 2010, 150, 716–725.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pershing, S.; Lum, F.; Hsu, S.; Kelly, S.; Chiang, M.F.; Rich, W.L., 3rd; Parke, D.W., 2nd. Endophthalmitis after cataract surgery in the United States: A report from the Intelligent Research in Sight Registry, 2013–2017. Ophthalmology 2020, 127, 151–158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simonsz, H.J.; Rutar, T.; Kraft, S.; Thiadens, A.; Batstra, M.R.; Verdijk, R.M.; Loeffler, K.U.; Kommerell, G.; Endophthalmitis-after-Strabismus-Surgery Reporting Group. Endophthalmitis after strabismus surgery: Incidence and outcome in relation to age, operated eye muscle, surgical technique, scleral perforation and immune state. Acta Ophthalmol. 2021, 99, 37–51. [Google Scholar] [CrossRef] [Scilit]
- Stem, M.S.; Rao, P.; Lee, I.J.; Woodward, M.A.; Faia, L.J.; Wolfe, J.D.; Capone, A., Jr.; Covert, D.; Dass, A.B.; Drenser, K.A.; et al. Predictors of endophthalmitis after intravitreal injection: A multivariable analysis based on injection protocol and povidone iodine strength. Ophthalmol. Retina 2019, 3, 3–7. [Google Scholar] [CrossRef] [Scilit]
- Xu, K.; Chin, E.K.; Bennett, S.R.; Williams, D.F.; Ryan, E.H.; Dev, S.; Mittra, R.A.; Quiram, P.A.; Davies, J.B.; Parke, D.W., 3rd; et al. Endophthalmitis after intravitreal injection of vascular endothelial growth factor inhibitors: Management and visual outcomes. Ophthalmology 2018, 125, 1279–1286. [Google Scholar] [PubMed]
- Zhu, Y.; Chen, X.; Chen, P.; Wu, J.; Hua, H.; Yao, K. The occurrence rate of acute-onset postoperative endophthalmitis after cataract surgery in Chinese small- and medium-scale departments of ophthalmology. Sci. Rep. 2017, 7, 40776. [Google Scholar] [CrossRef] [Scilit]
- Dossarps, D.; Bron, A.M.; Koehrer, P.; Aho-Glele, L.S.; Creuzot-Garcher, C. FRCR net (FRenCh Retina specialists net). Endophthalmitis after intravitreal injections: Incidence, presentation, management, and visual outcome. Am. J. Ophthalmol. 2015, 160, 17–25.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Danielescu, C.; Anton, N.; Stanca, H.T.; Munteanu, M. Endogenous endophthalmitis: A review of case series published between 2011 and 2020. J. Ophthalmol. 2020, 2020, 8869590. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, X.; Xia, H.; Jin, C.; Chen, W.; Siu-Chun Ng, D.; Yan, H.; Chen, H. Prognostic factors associated with visual outcome of salvageable eyes with posttraumatic endophthalmitis. Sci. Rep. 2019, 9, 12678. [Google Scholar] [PubMed]
- Okamoto, Y.; Morikawa, S.; Okamoto, F.; Inomoto, N.; Ishikawa, H.; Ueda, T.; Sakamoto, T.; Sugitani, K.; Oshika, T. Clinical characteristics and outcomes of open globe injuries in Japan. Jpn. J. Ophthalmol. 2019, 63, 109–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bjerrum, S.S.; la Cour, M. 59 eyes with endogenous endophthalmitis- causes, outcomes and mortality in a Danish population between 2000 and 2016. Graef. Arch. Clin. Exp. 2017, 255, 2023–2027. [Google Scholar] [CrossRef] [Scilit]
- Cunningham, E.T.; Flynn, H.W.; Relhan, N.; Zierhut, M. Endogenous endophthalmitis. Ocul. Immunol. Inflamm. 2018, 26, 491–495. [Google Scholar] [PubMed]
- Gounder, P.A.; Hille, D.M.; Khoo, Y.J.; Phagura, R.S.; Chen, F.K. Endogenous endophthalmitis in western Australia: A sixteen-year retrospective study. Retina 2020, 40, 908–918. [Google Scholar] [CrossRef] [Scilit]
- Hsieh, M.C.; Chen, S.N.; Cheng, C.Y.; Li, K.H.; Chuang, C.C.; Wu, J.S.; Lee, S.T.; Chiu, S.L. Clinicomicrobiological profile, visual outcome and mortality of culture-proven endogenous endophthalmitis in Taiwan. Sci. Rep. 2020, 10, 12481. [Google Scholar] [CrossRef] [Scilit]
- Maling, S.; King, C.; Davies, N. A British Ophthalmological Surveillance Unit Study on metastatic endogenous endophthalmitis. Eye. 2018, 32, 743–748. [Google Scholar] [PubMed]
- Silpa-Archa, S.; Ponwong, A.; Preble, J.M.; Foster, C.S. Culture-positive endogenous endophthalmitis: An eleven-year retrospective study in the central region of Thailand. Ocul. Immunol. Inflamm. 2018, 26, 533–542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Todokoro, D.; Mochizuki, K.; Nishida, T.; Eguchi, H.; Miyamoto, T.; Hattori, T.; Suzuki, T.; Inoue, T.; Nejima, R.; Hoshi, S.; et al. Isolates and antibiotic susceptibilities of endogenous bacterial endophthalmitis: A retrospective multicenter study in Japan. J. Infect. Chemother. 2018, 24, 458–462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uppuluri, A.; Zarbin, M.A.; Budoff, G.; Bhagat, N. Risk factors for endogenous endophthalmitis in hospitalized patients with Candida Fungemia. Ophthalmol. Retina 2020. S2468-6530(20)30412-7. Advance online publication. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mamah, C.C.; Anyalebechi, O.C.; Onwubiko, S.N.; Okoloagu, M.N.; Maduka-Okafor, F.C.; Ebede, S.O.; Umeh, R.E. Conjunctival bacterial flora and their antibiotic sensitivity among patients scheduled for cataract surgery in a tertiary hospital in south-east Nigeria. Graef. Arch. Clin. Exp. 2021, 259, 443–448. [Google Scholar] [CrossRef] [Scilit]
- Bruttini, C.; Pallone, C.; Verticchio Vercellin, A.; Acerbi, G.; Baschetti, S.; Bruttini, P.; Riva, I.; Quaranta, L. Pre-operative conjunctival flora in patients with local and/or systemic risk factors for post cataract surgery infection in Northern Italy. Eur. J. Ophthalmol. 2020, 1120672120934991, Advance online publication. [Google Scholar] [CrossRef] [Scilit]
- Reibaldi, M.; Avitabile, T.; Bandello, F.; Longo, A.; Bonfiglio, V.; Russo, A.; Castellino, N.; Rejdak, R.; Nowomiejska, K.; Toro, M.; et al. The effectiveness of 0.6% povidone iodine eye drops in reducing the conjunctival bacterial load and needle contamination in patients undergoing anti-VEGF intravitreal injection: A prospective, randomized study. J. Clin. Med. 2019, 8, 1031. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chiquet, C.; Musson, C.; Aptel, F.; Boisset, S.; Maurin, M. Genetic and phenotypic traits of Staphylococcus epidermidis strains causing postcataract endophthalmitis compared to commensal conjunctival flora. Am. J. Ophthalmol. 2018, 191, 76–82. [Google Scholar] [CrossRef] [Scilit]
- Selva Pandiyan, A.; Siva Ganesa Karthikeyan, R.; Rameshkumar, G.; Sen, S.; Lalitha, P. Identification of bacterial and fungal pathogens by rDNA gene barcoding in vitreous fluids of endophthalmitis patients. Semin. Ophthalmol. 2021, 3, 1–7. [Google Scholar]
- Kosacki, J.; Boisset, S.; Maurin, M.; Cornut, P.L.; Thuret, G.; Hubanova, R.; Vandenesch, F.; Carricajo, A.; Aptel, F.; Chiquet, C.; et al. Specific PCR and quantitative real-time PCR in ocular samples from acute and delayed-onset postoperative endophthalmitis. Am. J. Ophthalmol. 2020, 212, 34–42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chun, L.Y.; Dolle-Molle, L.; Bethel, C.; Dimitroyannis, R.C.; Williams, B.L.; Schechet, S.A.; Hariprasad, S.M.; Missiakas, D.; Schneewind, O.; Beavis, K.G.; et al. Rapid pathogen identification and antimicrobial susceptibility testing in in vitro endophthalmitis with matrix assisted laser desorption-ionization Time-of-Flight Mass Spectrometry and VITEK 2 without prior culture. PLoS ONE 2019, 14, e0227071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, S.; Zhou, C.; Zhang, P.; Feng, C.; Zhang, T.; Sun, Z.; Zhuang, H.; Chen, H.; Chang, Q.; Jiang, R.; et al. Diagnostic performance of MALDI-TOF MS compared to conventional microbiological cultures in patients with suspected endophthalmitis. Ocul. Immunol. Inflamm. 2020, 28, 483–490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yannuzzi, N.A.; Patel, N.A.; Relhan, N.; Tran, K.D.; Si, N.; Albini, T.A.; Berrocal, A.M.; Davis, J.L.; Smiddy, W.E.; Townsend, J.; et al. Clinical features, antibiotic susceptibilities, and treatment outcomes of endophthalmitis caused by Staphylococcus epidermidis. Ophthalmol. Retina 2018, 2, 396–400. [Google Scholar] [CrossRef] [Scilit]
- Dave, V.P.; Pathengay, A.; Braimah, I.Z.; Panchal, B.; Sharma, S.; Pappuru, R.R.; Mathai, A.; Tyagi, M.; Narayanan, R.; Jalali, S.; et al. ENTEROCOCCUS ENDOPHTHALMITIS: Clinical settings, antimicrobial susceptibility, and management outcomes. Retina 2020, 40, 898–902. [Google Scholar] [CrossRef] [Scilit]
- Soliman, M.K.; Gini, G.; Kuhn, F.; Parolini, B.; Ozdek, S.; Adelman, R.A.; Sallam, A.B.; European Vitreo-Retinal Society (EVRS) Endophthalmitis Study Group. Visual outcome of early vitrectomy and intravitreal antibiotics in acute postsurgical and postintravitreal injection endophthalmitis: European Vitreo-Retinal Society Endophthalmitis Study Report Two. Retina 2021, 41, 423–430. [Google Scholar] [CrossRef] [Scilit]
- Choi, E.Y.; Han, J.Y.; Lee, H.; Lee, S.C.; Koh, H.J.; Kim, S.S.; Kim, M. Impact of antibiotic resistance of pathogens and early vitrectomy on the prognosis of infectious endophthalmitis: A 10-year retrospective study. Graef. Arch. Clin. Exp. 2019, 257, 805–813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crosby, N.J.; Westcott, M.; Michael, E.; Cunningham, W.J.; Welch, S.; Polkinghorne, P.J. Comparative outcomes of primary vitrectomy versus tap and inject for endophthalmitis following phacoemulsification cataract surgery. Ocul. Immunol. Inflamm. 2020, 15, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, C.S.; Khan, M.; Patrie, J.; Bajwa, A.; Shildkrot, Y.E. Pars plana vitrectomy for endophthalmitis: Microbiologic spectrum and clinical outcomes. Ocul. Immunol. Inflamm. 2020, 6, 1–6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stevenson, L.J.; Dawkins, R.C.H.; Sheorey, H.; McGuinness, M.B.; Hurley, A.H.; Allen, P.J. Gram-negative endophthalmitis: A prospective study examining the microbiology, clinical associations and visual outcomes following infection. Clin. Exper. Ophthalmol. 2020, 48, 813–820. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoshida, M.; Yokokura, S.; Nishida, T.; Mochizuki, K.; Suzuki, T.; Maruyama, K.; Otomo, T.; Nishiguchi, K.M.; Kunikata, H.; Nakazawa, T. Endogenous endophthalmitis caused by group B streptococcus; case reports and review of 35 reported cases. BMC Ophthalmol. 2020, 20, 126. [Google Scholar] [CrossRef] [Scilit]
- Mochizuki, Y.; Ishikawa, H.; Sato, A.; Yamada, K.; Takesue, Y.; Gomi, F. Pasteurella multocida-induced endophthalmitis after a cat scratch. Am. J. Ophthalmol. Case Rep. 2020, 18, 100711. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Congdon, N.; O’Colmain, B.; Klaver, C.C.; Klein, R.; Muñoz, B.; Friedman, D.S.; Kempen, J.; Taylor, H.R.; Mitchell, P.; Eye Diseases Prevalence Research Group. Causes and prevalence of visual impairment among adults in the United States. Arch. Ophthalmol. 2004, 122, 477–485. [Google Scholar] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).