


Abstract
Background and Clinical Significance: Plasmablastic lymphoma (PBL) is a rare and highly aggressive B-cell neoplasm most often associated with immunodeficiency. Transformation of chronic lymphocytic leukemia/small lymphocytic lymphoma (CLL/SLL) into PBL is exceptionally uncommon, particularly in immunocompetent individuals. This paper describes a rare synchronous SLL-to-PBL transformation and summarizes current knowledge on synchronous and metachronous cases reported in the literature. Case Presentation A midle-aged immunocompetent patent presented with generalized lymphadenopathy and lumbar pain. Concurrent biopsies of an axillary lymph node and a retroperitoneal mass were obtained. Diagnostic evaluation included immunohistochemistry; fluorescent in situ hybridization (FISH); PCR-based assessment of IGH, IGK, and IGL loci; and next-generation sequencing (NGS) of IGHV to assess clonal relatedness. The patient was treated with six cycles of Dara-CHOP, followed by autologous stem cell transplantation and maintenance therapy with daratumumab and ibrutinib. The axillary node showed SLL (CD20+, CD5+, CD23+), while the retroperitoneal mass demonstrated classic features of PBL (CD138+, MUM1+, MYC+, Ki-67 ~100%, CD20−). FISH detected MYC rearrangement in the PBL component. PCR and NGS confirmed identical IGHV1-69 rearrangements, establishing clonal relatedness and Richter transformation. A review of published cases shows that both synchronous and metachronous CLL/SLL-to-PBL transformations are exceedingly rare. The patient achieved partial metabolic remission after treatment and remains in sustained metabolic response 24 months after diagnosis. Conclusions: This case highlights a rare example of synchronous CLL/SLL-to-PBL transformation in an immunocompetent patient. Integration of detailed molecular diagnostics enabled early recognition and guided a personalized treatment approach incorporating CD38-targeted therapy and BTK inhibition, resulting in an excellent long-term clinical outcome.
1. Introduction
Chronic lymphocytic leukemia (CLL) is the most common leukemia in Western countries, accounting for approximately 25–30% of adult leukemias. Richter’s transformation (RT) refers to the progression of CLL/small lymphocytic lymphoma (SLL) into a more aggressive lymphoma, most commonly diffuse large B-cell lymphoma (DLBCL), the most frequent subtype of non-Hodgkin lymphoma worldwide. This transformation occurs in approximately 2–10% of patients during the course of the disease and represents a clinically significant event [1,2]. Plasmablastic lymphoma (PBL) is a rare and aggressive transformation, especially uncommon in immunocompetent individuals [2]. It is most often seen in the context of immunodeficiency, such as HIV infection or prior exposure to chemotherapy [3,4,5]. We report a rare synchronous SLL and PBL case in an immunocompetent patient, and we additionally analyzed published cases of CLL/SLL-to-PBL transformations, focusing on their clinical presentation, diagnostic features, and therapeutic approaches, highlighting patterns relevant for early recognition and management.
2. Case Report
We report a rare case of synchronous SLL and PBL in a middle-aged patient, who presented in late 2023 with lower back pain, highlighting both diagnostic challenges and histopathological features.
18F-FDG PET/CT revealed intensely hypermetabolic retroperitoneal masses compressing the right ureter without evidence of renal impairment, along with bilateral pelvic lymph node involvement, with SUVmax values reaching up to 18.6. Shortly thereafter, biopsies of an axillary lymph node—selected for accessibility despite unreported SUVmax values—and a retroperitoneal lymph node were performed in the setting of significant lymphadenopathy on imaging. The complete blood count was normal, with an absolute lymphocyte count of 1.9 G/L. Examination of the blood smear revealed no cytological abnormalities. Immunophenotyping of peripheral blood by flow cytometry revealed a monoclonal B-cell population expressing CD5, CD23, and FMC7, with low expression of CD20 and λ light chain, and negative for CD79b. This population accounted for less 0.5 G/L of circulating B cells, consistent with a diagnosis of small lymphocytic leukemia.
Biopsy specimens were analyzed histologically and immunohistochemically.
Axillary and retroperitoneal lymph nodes were examined for morphology and immunophenotype using standard immunohistochemical panels. The antibody panel was designed to assess mature B-cell lineage, plasma cell differentiation, germinal center derivation, and relevant differential diagnostic entities, in accordance with current WHO recommendations for the diagnosis of plasmablastic lymphoma [3], and included CD20, CD5, CD23, CD10, BCL6, cyclin D1, CD138, CD38, MUM1, c-MYC, Ki-67, and immunoglobulin light chains.
FISH analysis was performed to detect MYC, BCL2, and BCL6 rearrangements. Clonal relatedness between SLL and PBL components was assessed by PCR-based analysis of IGH, IGK, and IGL loci, complemented by next-generation sequencing (NGS) of IGHV. In situ hybridization for EBV (EBER) and HHV8 (LANA1) was also performed. The patient was treated with Dara-CHOP chemotherapy (daratumumab, cyclophosphamide, doxorubicin, vincristine, and prednisone) followed by autologous hematopoietic stem cell transplantation (AHSCT). Maintenance therapy consisted of monthly daratumumab and ibrutinib.
Clinical and pathological features of reported transformation cases from CLL/SLL to PBL were analyzed separately for synchronous and metachronous transformations. Synchronous cases were defined as those in which CLL/SLL and PBL were diagnosed simultaneously or within a 6-month interval, while metachronous cases were defined as those in which transformation occurred more than 6 months after the initial CLL/SLL diagnosis. This distinction was made because synchronous transformations, occurring within a short temporal window, are more likely to originate from the same precursor clone, whereas metachronous cases may develop through later genetic divergence or therapy-driven clonal evolution, making their clonal relationship less predictable unless formally confirmed by molecular testing. For both groups, we collected and compared available clinical characteristics, pathological findings, immunophenotypic profiles, molecular data, treatment approaches, and patient outcomes, as reported in the literature.
3. Results
3.1. Morphological and Immunohistochemical Evaluation
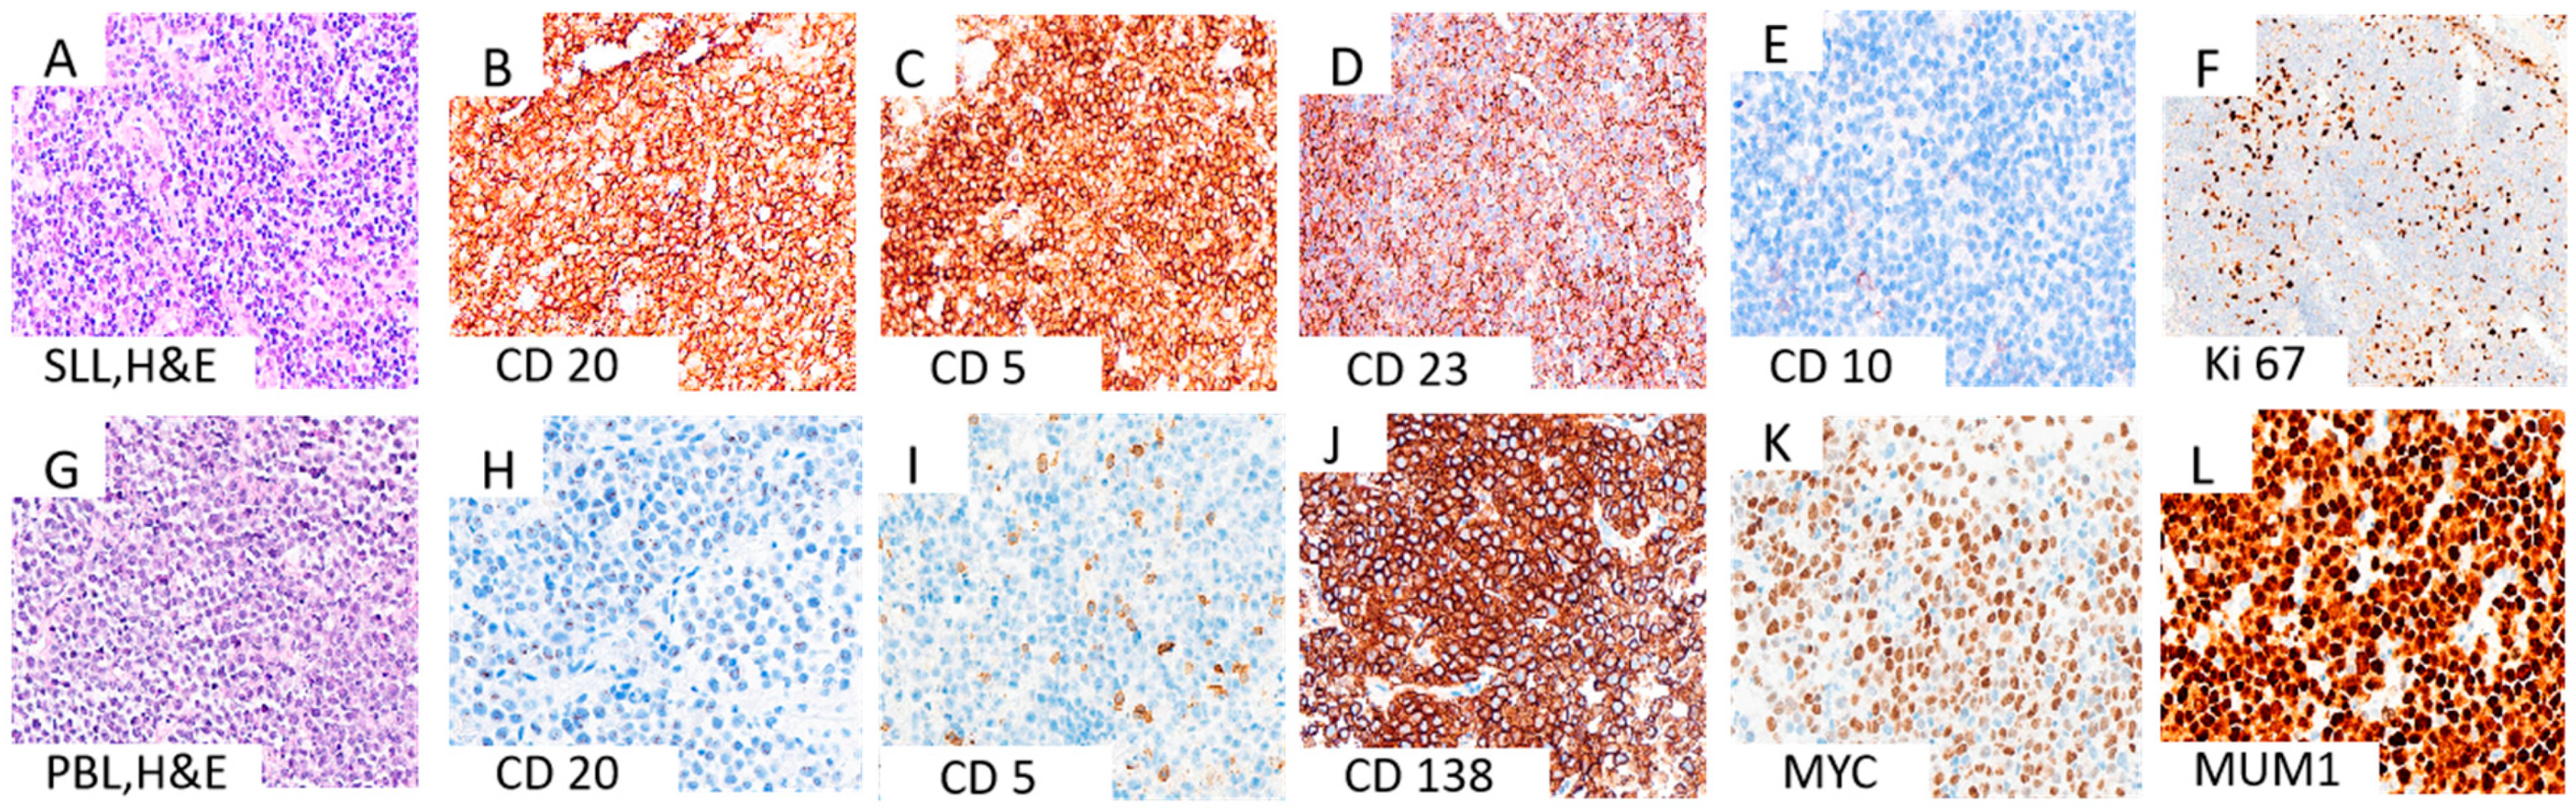
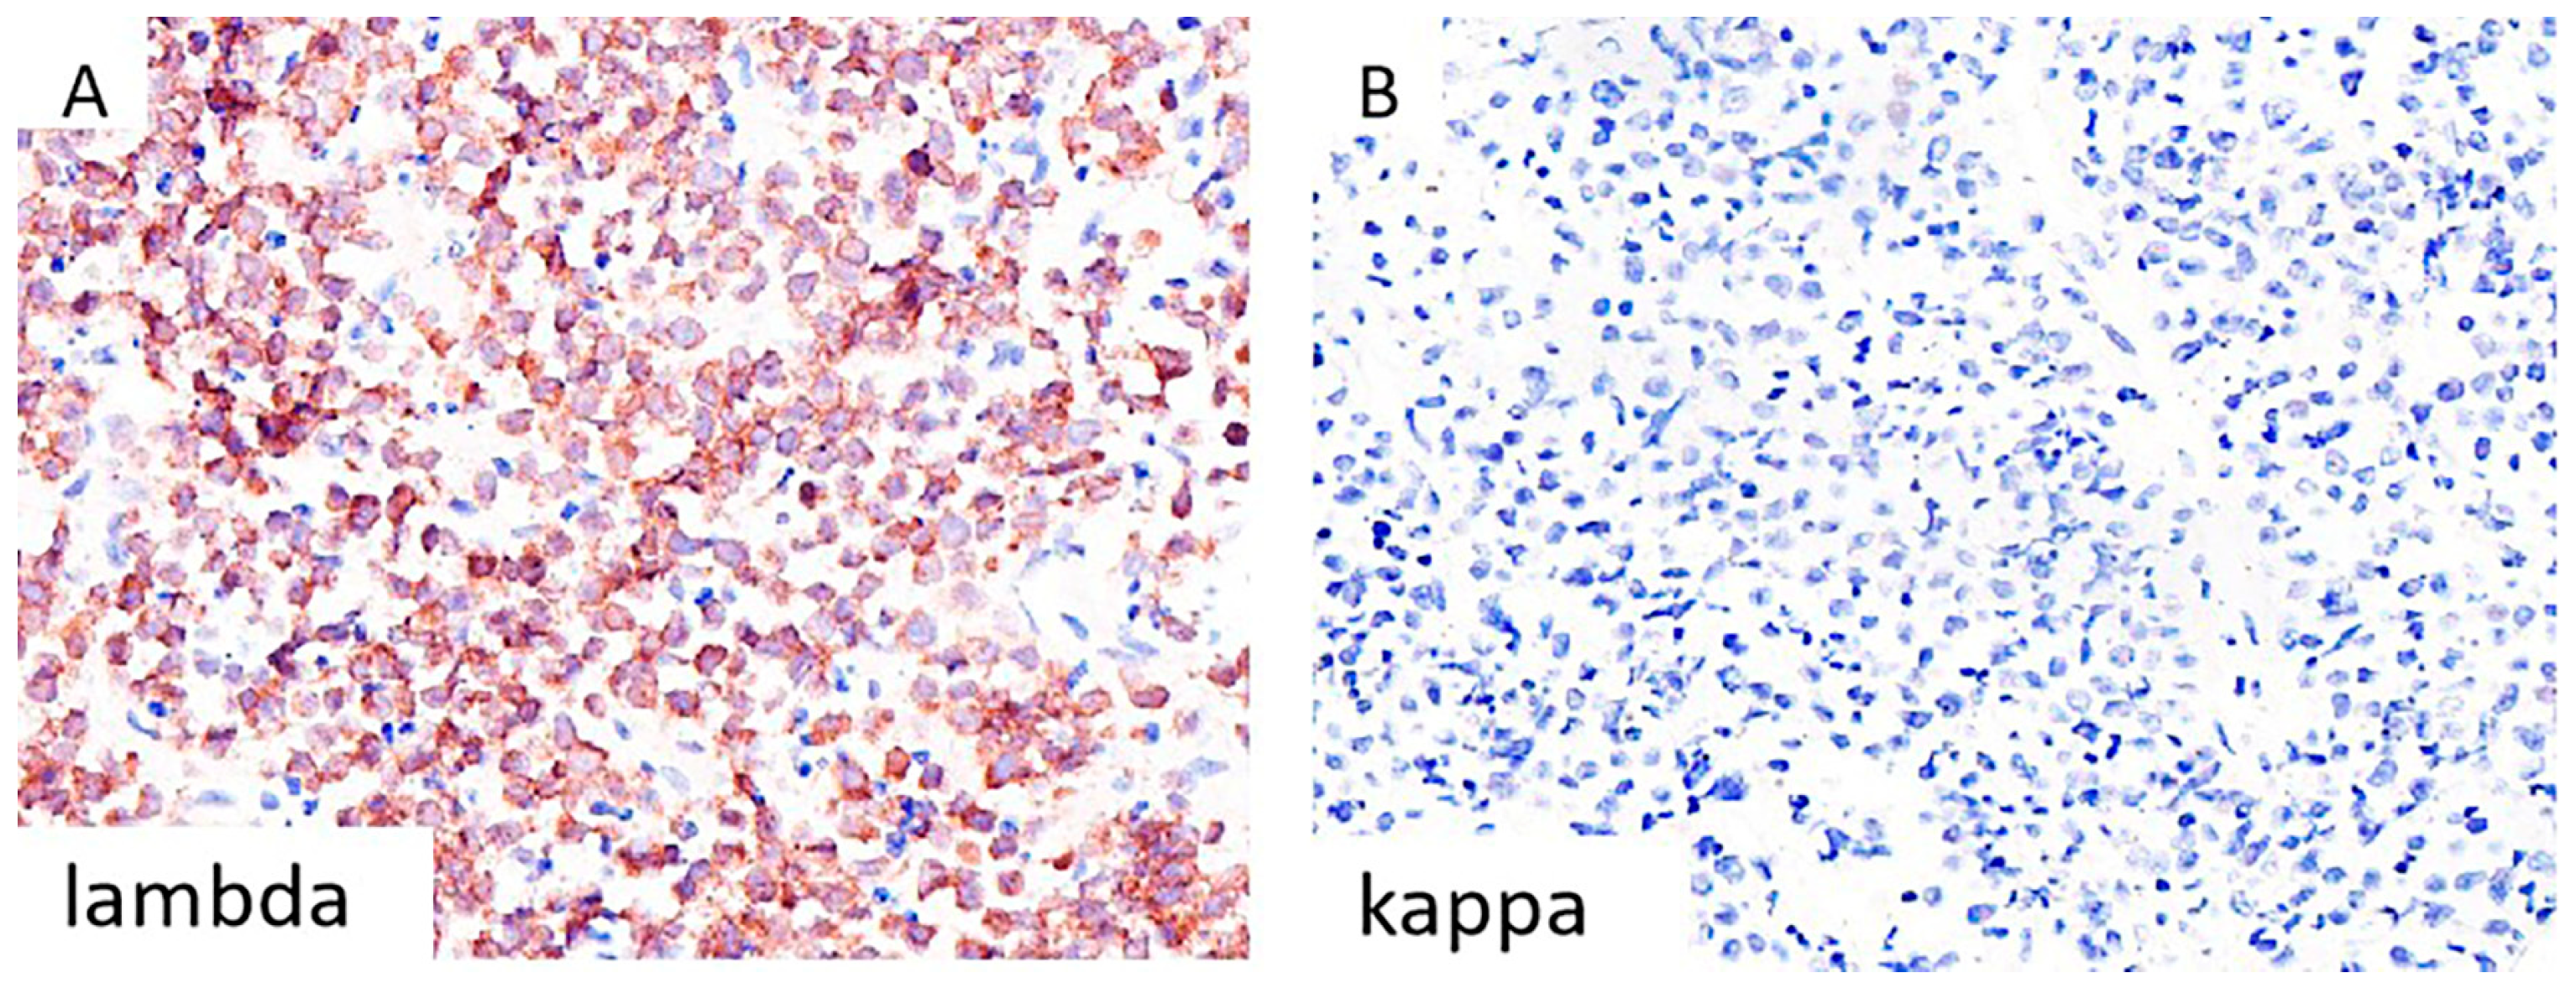
An axillary lymph node biopsy revealed diffuse infiltration by small neoplastic cells with round-to-slightly-irregular nuclei, condensed chromatin, and scant cytoplasm (Figure 1A). Immunohistochemistry confirmed SLL/CLL phenotype: CD20+, CD5+, CD23+, CD10−, BCL6−, cyclin D1−. The Ki67 proliferation index was low (20–30%), with focal enhancement in proliferative centers (Figure 1B–F). Retroperitoneal lymph node histology showed a compact lymphoid proliferation of medium-to-large plasmacytoid cells with rounded/angular nuclei, decondensed chromatin, and prominent nucleoli. Apoptotic debris and mitoses were observed. Tumor cells were CD138+, CD38+, MUM1+, c-myc+, CD5−, CD10−, CD19−, CD20−, CD23−, CD45−, BCL2−, BCL6−, EMA−, cyclin D1−, ALK1−, IgA−, OCT2−, LANA1−. The Ki67 index was nearly 100% (Figure 1G–L). Tumor cells expressed lambda light chains, but were negative for kappa (Figure 2A,B). EBV and HHV8 were negative. In situ hybridization for Epstein–Barr virus-encoded RNA (EBER) was negative in the plasmablastic lymphoma component, and immunohistochemistry showed complete loss of PAX5 expression (Supplementary Figure S1).
Figure 1.
Histopathological and immunophenotypic features of SLL and its transformation into PBL. (A–F) Representative images of SLL showing: (A) diffuse infiltrate of small mature lymphocytes with clumped chromatin (H&E); (B) diffuse CD20 positivity; (C) co-expression of CD5; (D) CD23 positivity; (E) absence of CD10 expression; (F) low Ki-67 proliferation index exceeded in proliferative centers. (G–L) Corresponding images of the transformed PBL showing: (G) diffuse sheets of large atypical cells with plasmablastic morphology (H&E); (H) loss of CD20 expression; (I) partial expression of CD5; (J) strong expression of plasma cell marker CD138; (K) diffuse and strong nuclear expression of MYC; (L) diffuse nuclear positivity for MUM1. Abbreviations: SLL, small lymphocytic lymphoma; PBL, plasmablastic lymphoma; H&E, hematoxylin and eosin; magnification, 40×.
Figure 2.
A supportive finding for the diagnosis of PBL with lambda light chain restriction. Immunohistochemically, diffuse cytoplasmic staining for lambda light chain is observed in the majority of neoplastic cells (A), while no kappa expression is detected (B). Abbreviations: PBL, plasmablastic lymphoma; magnification, 40×.
3.2. Molecular Analysis
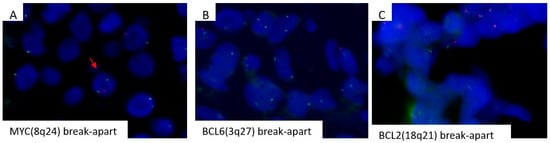
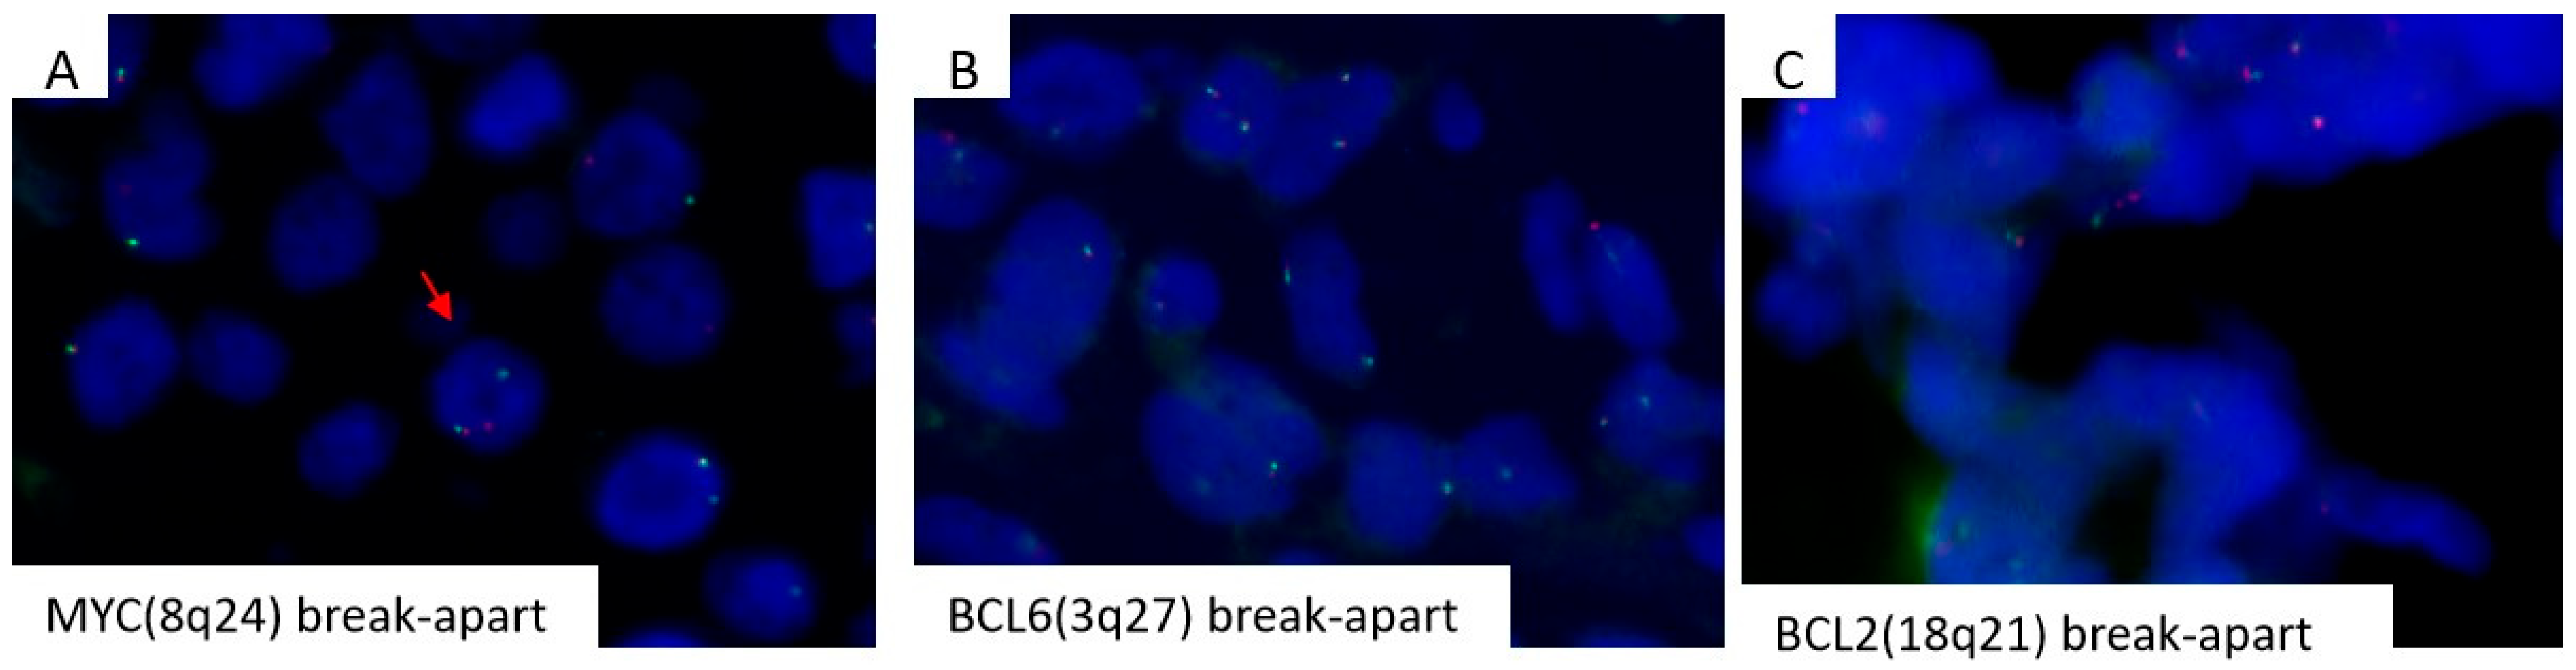
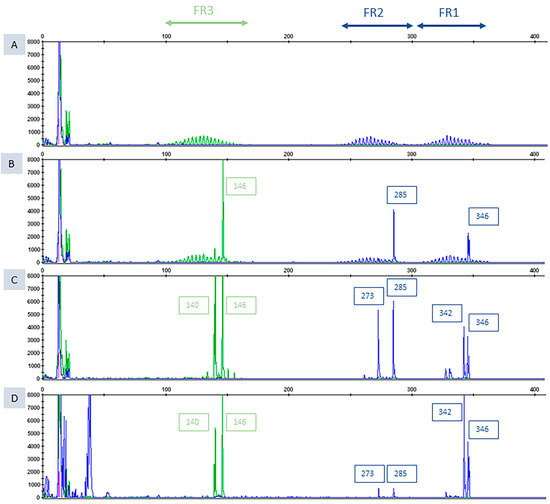
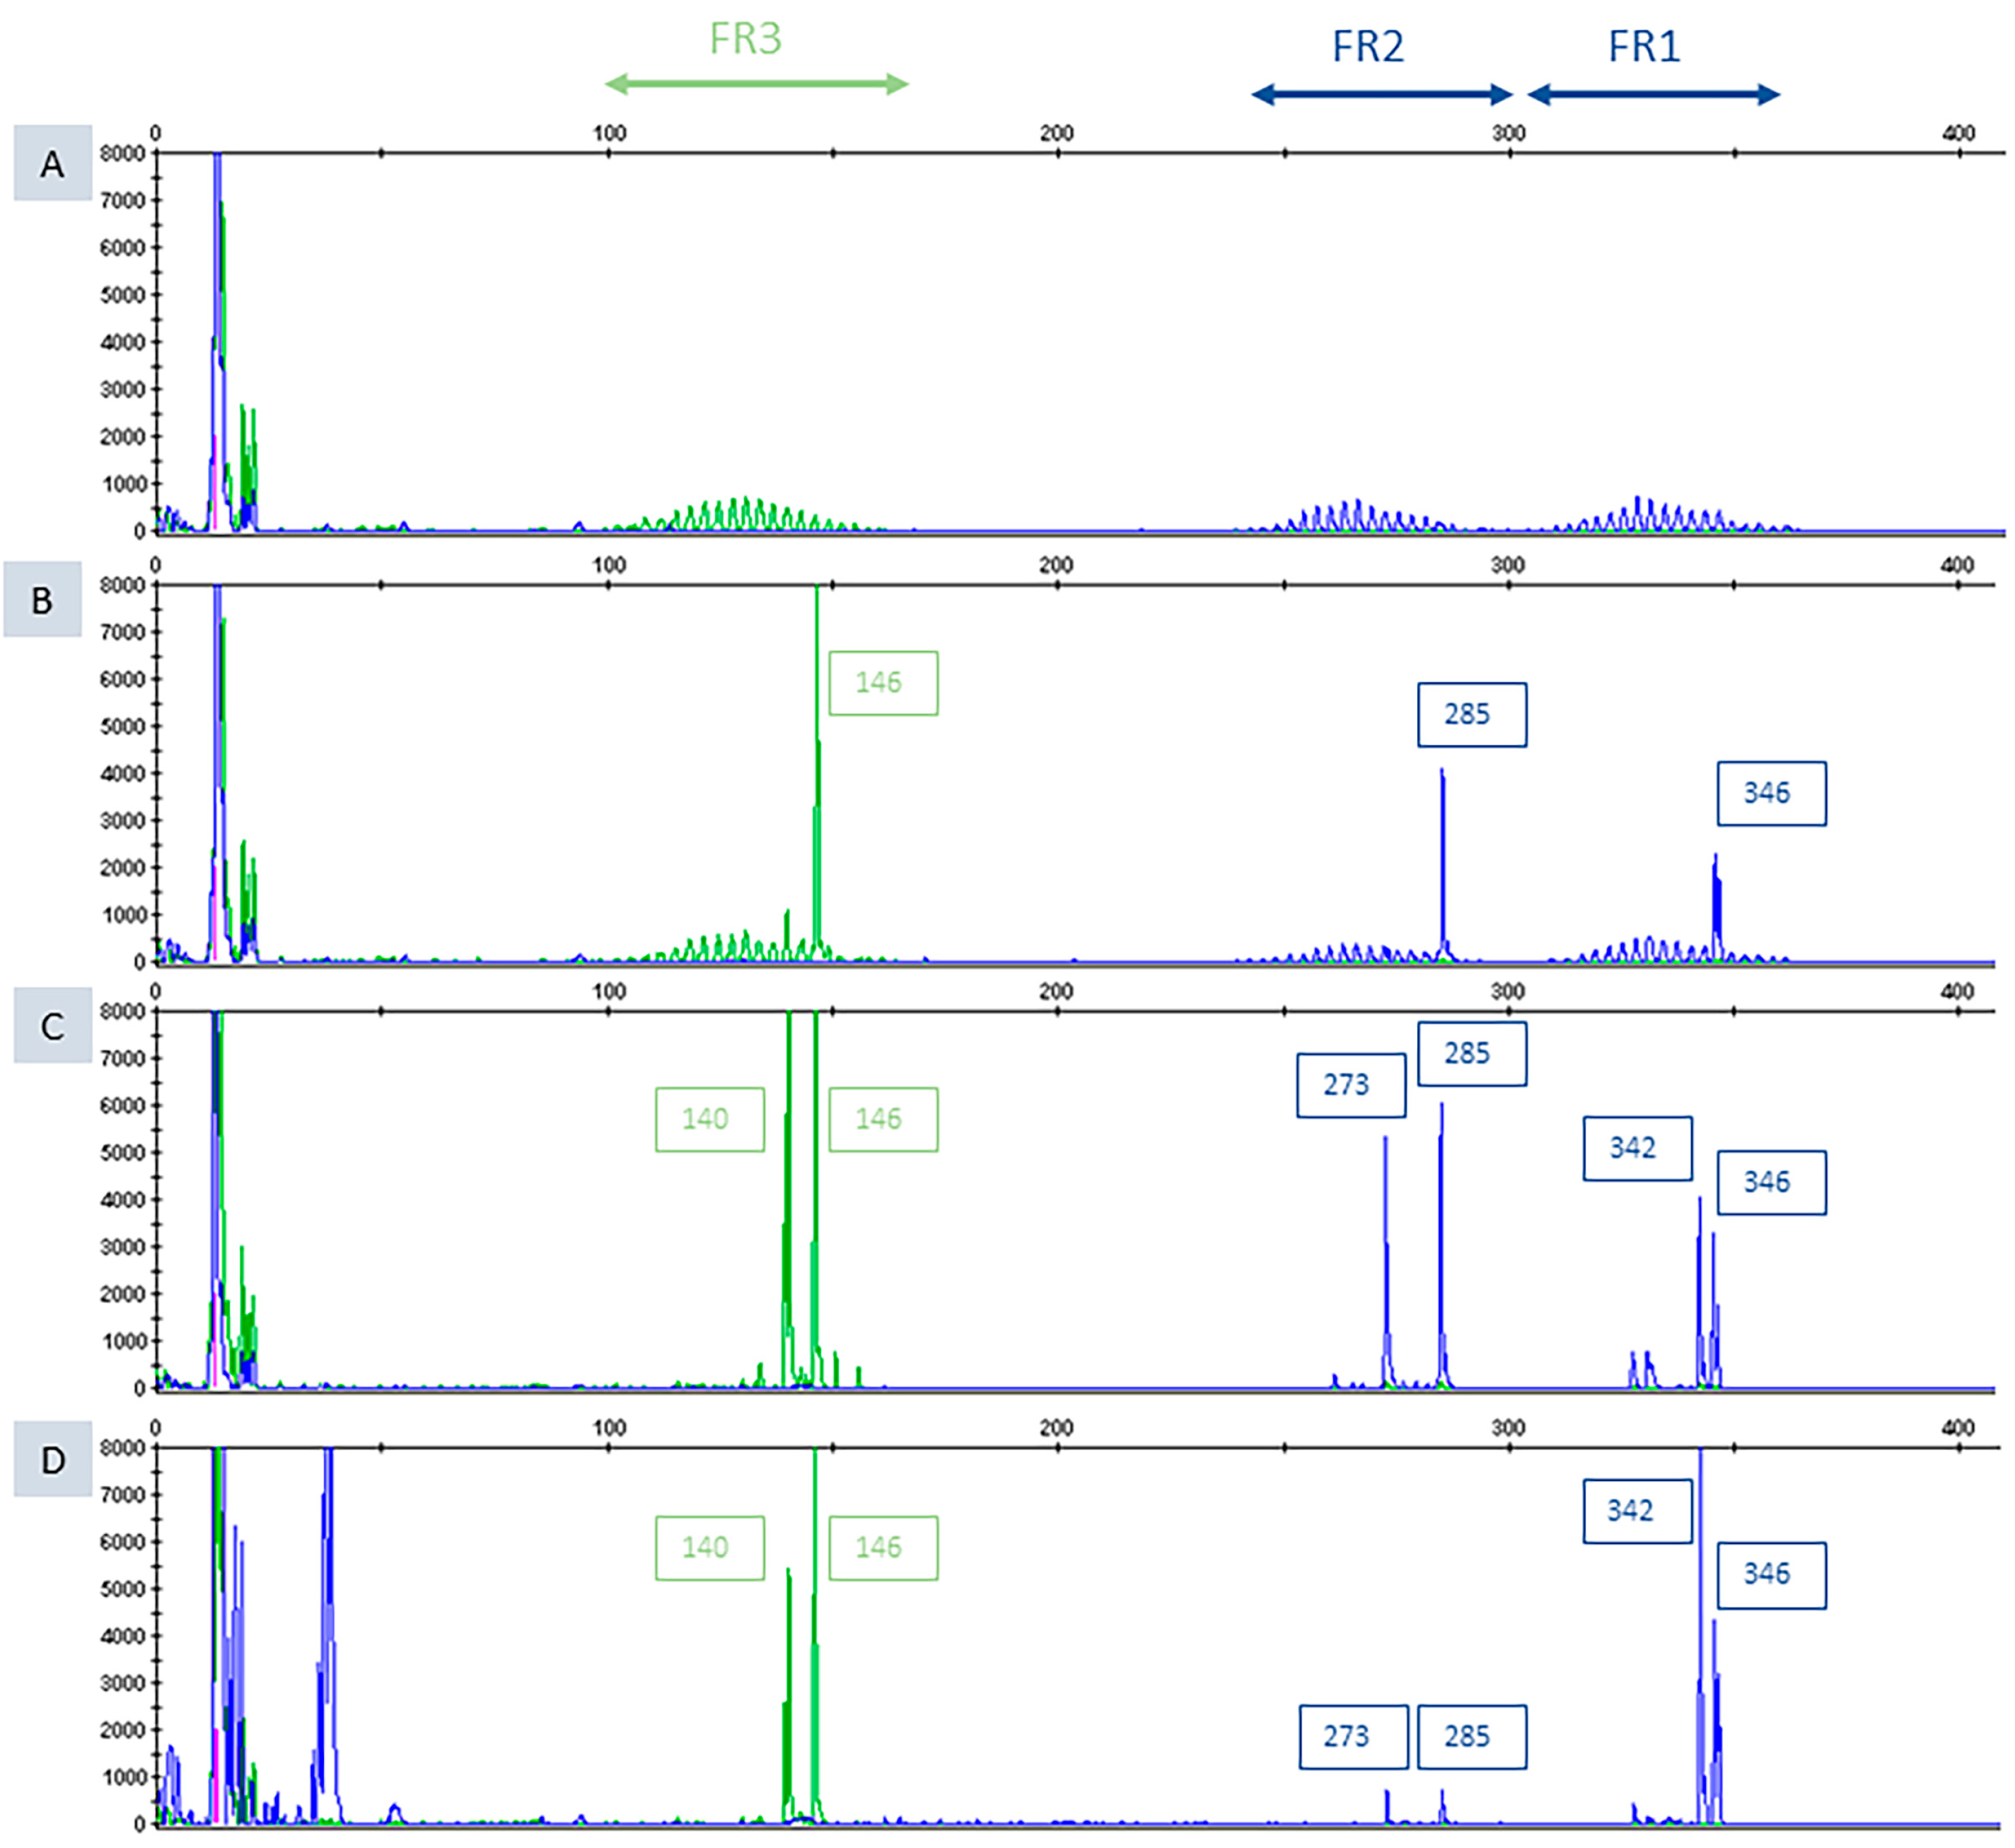
FISH analysis detected MYC rearrangement in PBL; BCL2 and BCL6 translocations were absent (Figure 3A–C). PCR analysis demonstrated an identical IGHV1-69/IGHD3/IGHJ6 rearrangement in both SLL and PBL (Figure 4). This finding was further confirmed by NGS analysis, establishing clonal relatedness and supporting the diagnosis of Richter transformation.
Figure 3.
Representative FISH images using break-apart probes (MetaSystems) for MYC (8q24), BCL6 (3q27), and BCL2 (18q21). (A) The MYC probe demonstrates a break-apart signal pattern indicative of an MYC rearrangement (arrow). In contrast, (B) the BCL6 and (C) BCL2 probes show fused signals, consistent with the absence of BCL6 and BCL2 gene rearrangements; Abbreviation: FISH, fluorescence in situ hybridization.
Figure 4.
Graphical representation of B clonality (IgH locus) results. Y axis: fragments height in fluorescence intensity; X axis: fragments size in base pairs (size of the expected fragments: VH-FR1-JH 310-360; VH-FR2-JH 250-295; VH-FR3-JH 100-170). Peak sizes are shown in boxes. (A) Polyclonal control (Gaussian distribution of the size of the fragments amplified), (B) positive control (presence of a clonal rearrangement (1 peak) in the FR1, FR2 and FR3 region), (C) lymph-node biopsy (presence of a clonal rearrangement (2 peaks) in the FR1, FR2 and FR3 region), (D) retro-peritoneal biopsy (presence of the same clonal rearrangement (2 peaks of the same size) as in the lymph-node biopsy). Abbreviations: IgH, immunoglobulin heavy chain; VH, variable region of heavy chain; FR, framework region; JH, joining region of heavy chain.
3.3. Therapy
After two cycles of Dara-CHOP, follow-up PET showed no progression but did show persistent hypermetabolic lesions, prompting four additional cycles. Several months later, a complete metabolic response was observed in the abdominal mass, though pelvic lymphadenopathy remained metabolically active. Subsequently, the patient underwent AHSCT. Chemotherapy was well tolerated; aplasia occurred on day + 2, and G-CSF started on day + 7, with uneventful recovery. In July 2024, the patient underwent AHSCT as consolidation therapy. Maintenance therapy for residual SLL/CLL was subsequently initiated with daratumumab and ibrutinib.
3.4. Brief Review of Synchronous Versus Metachronous Transformations Reported in the Literature
The results of our literature review are presented in Table 1 and Table 2. In summary, we identified four simultaneously diagnosed transformation cases within less than six months and ten non-simultaneously diagnosed cases. In both groups, patients were predominantly elderly males, with heterogeneous clinical presentations, diagnostic approaches, and treatment modalities. CHOP-based regimens were the most frequently applied therapy. In the synchronous group, only our patient achieved clinical stability with a daratumumab-based regimen targeting CD38 in addition to prior CHOP therapy, whereas in the metachronous group, one patient responded to combined localized therapy and chemotherapy.
Table 1.
Overview of clinical and pathological features of reported transformation cases from CLL/SLL to PBL that were diagnosed simultaneously (under 6 months between diagnosis).
Table 2.
Overview of clinical and pathological features of reported transformation cases from CLL/SLL to PBL that were not diagnosed simultaneously (more than 6 months between diagnosis).
4. Discussion
PBL is a rare and aggressive B-cell neoplasm first described by Delecluse et al. in 1997, predominantly affecting older male patients and immunocompromised individuals such as those with HIV, EBV infection, or post-transplant immunosuppression [3,4,14,15]. Extranodal involvement is common, while purely nodal PBL in immunocompetent patients remains exceedingly rare [3,13,16]. Transformation of CLL/SLL into PBL is particularly uncommon. The first reported case was described by Robak et al. in 2001 in an HIV- and EBV-negative woman [17].
Early (≤6 months) versus late (>6 months) transformations may reflect distinct biological mechanisms: early transformation could result from a pre-existing aggressive sub-clone or a common progenitor at the time of CLL diagnosis, whereas late transformation may arise from clonal evolution under therapeutic or micro-environmental pressure [4,15]. Based on this hypothesis, we reviewed the published cases and stratified synchronous and metachronous transformations in Table 1 and Table 2 to highlight potential differences in pathogenesis and clinical behavior.
Precise diagnosis typically involves a lymph node biopsy, supported by ancillary studies such as IHC, FISH, PCR, and NGS to confirm clonality [2,7,11]. We report a rare case in an immunocompetent middle-aged patien, who presented with lumbar pain, bilateral renal obstruction, and generalized lymphadenopathy. SLL and PBL were diagnosed simultaneously from axillary and retroperitoneal lymph nodes. While most reported patients are older males, only a few female cases—including ours—have been described [6,12,18,19]. The clinical presentation in our patient, with generalized lymphadenopathy and lumbar pain, aligns with the most commonly reported manifestations in the literature, which often also include B symptoms and pain associated with retroperitoneal or skeletal involvement [20,21]. Unlike most reported cases, the transformation in our patient was confined to lymph nodes, with no bone marrow involvement. This localized presentation may indicate an early stage of transformation or a nodal form of PBL with distinct biological behavior, and it may also reflect the benefit of rapid and accurate diagnostic evaluation. The diagnosis was established using a complete diagnostic workup—including imaging, IHC, and FISH—with clonal relatedness confirmed by PCR and NGS, representing, to our knowledge, the first such comprehensive approach reported in the literature. Histologically, the axillary lymph node showed classic SLL features with CD20 and CD5 expression. In contrast, the retroperitoneal lymph node demonstrated a diffuse proliferation of large plasmablast- and immunoblast-like cells with high mitotic activity and necrosis. These cells expressed plasma cell markers CD38, CD138, and MUM1; had a high Ki-67 index; and lacked B-cell markers such as CD20 and PAX5, consistent with typical PBL [3,4,15]. The complete loss of PAX5 expression in the plasmablastic component represents an essential diagnostic criterion for plasmablastic lymphoma and supports its distinction from immunoblastic diffuse large B-cell lymphoma, in accordance with the WHO’s 5th edition classification [22]. Because PBL can overlap morphologically and immunophenotypically with other entities—including immunoblastic DLBCL, plasmablastic myeloma, ALK-positive large B-cell lymphoma, and HHV-8-associated DLBCL—these diagnoses were carefully excluded. In our case, ALK positivity and paraproteinemia were absent, and Burkitt lymphoma was ruled out based on characteristic morphology and immunophenotype, while the lack of BCL2 and BCL6 expression helped exclude DLBCL. Positivity for MYC and plasma cell markers supported the diagnosis of PBL [3,23].
Consistent with other reports, our patient tested negative for HIV, EBV, and HHV-8. Although HIV status is often negative or unreported in the literature, EBV positivity has been described by Khanna et al. and Martinez et al. ([2,7]; Table 1 and Table 2). These observations suggest that some cases of plasmablastic lymphoma arise independently of viral infection and instead represent clonal evolution of the original CLL/SLL clone rather than a de novo secondary lymphoma. NGS studies demonstrating identical immunoglobulin gene rearrangements in CLL and PBL components support a common clonal origin with acquisition of additional late genetic events. Central to this process is MYC deregulation, often through chromosomal rearrangements, driving high proliferative activity and transcriptional reprogramming toward terminal plasmablastic differentiation with loss of the mature B-cell phenotype, while the frequent absence of EBV in RT–PBL further supports a mechanism driven by somatic genetic alterations rather than viral oncogenesis.
Using FISH, we confirmed an MYC rearrangement, in line with the majority of previously reported cases ([2,6,9,17]). In contrast, Gasljevic et al. described a case without MYC rearrangement, highlighting potential diagnostic challenges, particularly as the antecedent disease was classical Hodgkin lymphoma rather than CLL/SLL ([11]; Table 2).
Confirming clonal relatedness through PCR and NGS was essential to establish this case as a true Richter transformation rather than two unrelated neoplasms ([2,6,12]). While Ramsay et al. and Chan et al. previously applied NGS, their analyses were limited to metachronous cases ([9,12]; Table 2). NGS is particularly valuable in synchronous transformations, where histopathological and immunophenotypic overlap can obscure disease evolution and where molecular confirmation is necessary to distinguish true transformation from the coexistence of two independent lymphoid neoplasms. In these instances, high-resolution genomic analysis provides definitive evidence of clonal relatedness, improves understanding of pathogenesis, and informs more tailored therapeutic strategies ([18]). Although additional synchronous transformation cases have been reported ([8,10,16,24,25]), they were excluded from our review due to a lack of clonality confirmation, limiting their interpretive value.
Therapeutic management of PBL remains challenging due to its intrinsic chemo-resistance, MYC rearrangements, plasmacytic phenotype, and often low CD20 expression, which reduces rituximab efficacy [12,17]. In most reported cases, patients received R-CHOP or CHOP-like regimens and succumbed within six months, with only two exceptions: one patient survived 24 months, and another remained stable at the time of publication ([7,13]; Table 2). A particularly unusual case, reported by Mazumder et al. but not included in our review due to unconfirmed clonality, involved spontaneous regression of a gingival mass following a biopsy [24]. However, the diagnostic workup was limited to histology and EBV positivity, without molecular or phenotypic profiling, leaving its classification uncertain. In contrast to most reviewed cases, particularly synchronous transformations, our patient was diagnosed approximately 24 months ago and remains clinically stable after completing eight cycles of chemotherapy. She was treated with a daratumumab-based regimen targeting CD38, a marker highly expressed in PBL, which led to rapid resolution of lymphadenopathy, hepatosplenomegaly, and systemic symptoms. The patient subsequently underwent ASCT and is maintained on daratumumab and ibrutinib. This multimodal approach appears effective in controlling both plasmablastic and residual B-cell components. These observations emphasize the importance of tailoring treatment to the plasmablastic phenotype, particularly through the use of CD38-targeted therapy, BTK inhibitors, and stem cell transplantation.
5. Conclusions
This report describes a rare synchronous transformation of CLL/SLL into PBL in an immunocompetent woman, with nodal disease and clonal relatedness confirmed by PCR and NGS. Early molecular confirmation allowed a prompt initiation of targeted multimodal therapy, resulting in a favorable outcome. These findings underscore the value of precise molecular diagnostics in synchronous transformations and the potential efficacy of CD38- and BTK-directed treatments in plasmablastic disease.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/diagnostics16050702/s1, Figure S1: Representative immunohistochemical and in situ hybridization findings in the plasmablastic lymphoma component. Immunohistochemistry shows complete absence of PAX5 expression in tumor cells, confirming loss of B-cell lineage markers. In situ hybridization for Epstein–Barr virus-encoded RNA (EBER) demonstrates absence of EBV-positive tumor cells.
Author Contributions
Conceptualization: J.F. and A.M.; Methodology: J.F. and A.M.; Formal analysis and investigation: J.F., S.M., T.T., R.R., T.B. (Thorsten Braun), G.L., T.B. (Thami Benboubker), M.S. and A.M.; Writing—original draft preparation: J.F. and S.M.; Writing—review and editing: J.F., A.M. and T.T.; Supervision: A.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Ethical review and approval were waived for this study, as it involved a fully anonymized retrospective case report conducted in accordance with French data protection regulations (CNIL MR-004).
Informed Consent Statement
The manuscript has been fully anonymized, and no identifying patient information is included. In accordance with French regulations on retrospective anonymized data (CNIL MR-004), individual informed consent was not required.
Data Availability Statement
The data presented in this study are available on request from the corresponding author due to privacy.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| RT | Richter’s transformation |
| CLL/SLL | Chronic lymphocytic leukemia/Small lymphocytic lymphoma |
| DLBCL | Diffuse large B-cell lymphoma |
| PBL | Plasmablastic lymphoma |
| HIV | Human immunodeficiency virus |
| EBV | Epstein–Barr virus |
| HHV-8 | Human herpesvirus 8 |
| SLL | Small lymphocytic lymphoma |
| CD | Cluster of differentiation |
| MUM1 | Multiple myeloma oncogene 1 |
| MYC | MYC proto-oncogene |
| Ki-67 | Marker of proliferation |
| FISH | Fluorescent in situ hybridization |
| PCR | Polymerase chain reaction |
| IGH | Immunoglobulin heavy chain |
| IGK | Immunoglobulin kappa light chain |
| IGL | Immunoglobulin lambda light chain |
| NGS | Next-generation sequencing |
| PET | Positron emission tomography |
| HE | Hematoxylin and eosin |
| EMA | Epithelial membrane antigen |
| ALK1 | Anaplastic lymphoma kinase 1 |
| LANA1 | Latency-associated nuclear antigen 1 (HHV8) |
| Dara-CHOP | Daratumumab + cyclophosphamide + doxorubicin + vincristine + prednisone |
| AHSCT | Autologous hematopoietic stem cell transplantation |
| BTK | Bruton tyrosine kinase |
References
- Petrackova, A.; Turcsanyi, P.; Papajik, T.; Kriegova, E. Revisiting Richter transformation in the era of novel CLL agents. Blood Rev. 2021, 49, 100824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khanna, A.; Drumheller, B.R.; Deeb, G.; Tolbert, E.W.; Asakrah, S. Plasmablastic transformation of chronic lymphocytic leukemia: A review of literature and report on 2 cases. Lab. Med. 2023, 54, e177–e185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bailly, J.; Jenkins, N.; Chetty, D.; Mohamed, Z.; Verburgh, E.R.; Opie, J.J. Plasmablastic lymphoma: An update. Int. J. Lab. Hematol. 2022, 44, 1121, Correction in Int. J. Lab. Hematol. 2022, 44, 54–63. https://doi.org/10.1111/ijlh.13863. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teruya-Feldstein, J. Diffuse Large B-Cell Lymphomas with Plasmablastic Differentiation. Curr. Oncol. Rep. 2005, 7, 357–363. [Google Scholar] [CrossRef] [Scilit]
- Bhatt, R.; Naha, K.; Desai, D.S. Plasmablastic Lymphoma. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2024. [Google Scholar]
- Ronchi, A.; Marra, L.; Frigeri, F.; Botti, G.; Franco, R.; De Chiara, A. Richter Syndrome with Plasmablastic Lymphoma at Primary Diagnosis: A Case Report with a Review of the Literature. Appl. Immunohistochem. Mol. Morphol. 2017, 25, e40–e45. [Google Scholar] [CrossRef] [Scilit]
- Martinez, D.; Valera, A.; Perez, N.S.; Villegas, L.F.S.; Gonzalez-Farre, B.; Sole, C.; Gine, E.; Lopez-Guillermo, A.; Roue, G.; Martinez, S.; et al. Plasmablastic transformation of low-grade B-cell lymphomas: Report on 6 cases. Am. J. Surg. Pathol. 2013, 37, 272–281. [Google Scholar] [CrossRef] [Scilit]
- Ramalingam, P.; Nayak-Kapoor, A.; Reid-Nicholson, M.; Jones-Crawford, J.; Ustun, C. Plasmablastic lymphoma with small lymphocytic lymphoma: Clinico-pathologic features, and review of the literature. Leuk. Lymphoma 2008, 49, 1999–2002. [Google Scholar] [CrossRef] [Scilit]
- Ramsey, M.C.; Sabatini, P.J.B.; Smith, A.C.; Sakhdari, A. Molecular characterization and clonal evolution in Richter transformation: Insights from a case of plasmablastic lymphoma (RT-PBL) arising from chronic lymphocytic leukaemia (CLL) and review of the literature. EJHaem 2023, 4, 1203–1207. [Google Scholar] [CrossRef] [Scilit]
- Marvyin, K.; Tjønnfjord, E.B.; Breland, U.M.; Tjønnfjord, G.E. Transformation to plasmablastic lymphoma in CLL upon ibrutinib treatment. BMJ Case Rep. 2020, 13, e235816. [Google Scholar] [CrossRef] [Scilit]
- Gasljevic, G.; Grat, M.; Prevodnik, V.K.; Kuzmanov, B.G.; Gazic, B.; Lovrecic, L.; Podgornik, H. Chronic Lymphocytic Leukemia with Divergent Richter’s Transformation into a Clonally Related Classical Hodgkin’s and Plasmablastic Lymphoma: A Case Report. Case Rep. Oncol. 2020, 13, 120–129. [Google Scholar] [CrossRef] [Scilit]
- Chan, K.L.; Blombery, P.; Jones, K.; Lade, S.; Carney, D.; Tran, H.; Seymour, J.F.; Tam, C.S. Plasmablastic Richter transformation as a resistance mechanism for chronic lymphocytic leukaemia treated with BCR signalling inhibitors. Br. J. Haematol. 2017, 177, 324–328. [Google Scholar] [CrossRef] [Scilit]
- Pan, Z.; Xie, Q.; Repertinger, S.; Richendollar, B.G.; Chan, W.C.; Huang, Q. Plasmablastic transformation of low-grade CD5+ B-cell lymphoproliferative disorder with MYC gene rearrangements. Hum. Pathol. 2013, 44, 2139–2148. [Google Scholar] [CrossRef] [Scilit]
- Delecluse, H.J.; Anagnostopoulos, I.; Dallenbach, F.; Hummel, M.; Marafioti, T.; Schneider, U.; Huhn, D.; Schmidt-Westhausen, A.; Reichart, P.; Gross, U.; et al. Plasmablastic lymphomas of the oral cavity: A new entity associated with the human immunodeficiency virus infection. Blood 1997, 89, 1413–1420. [Google Scholar] [CrossRef] [Scilit]
- Chen, B.J.; Chuang, S.S. Lymphoid Neoplasms with Plasmablastic Differentiation: A Comprehensive Review and Diagnostic Approaches. Adv. Anat. Pathol. 2020, 27, 61–74. [Google Scholar] [CrossRef] [Scilit]
- Hatzimichael, E.; Papathanasiou, K.; Zerdes, I.; Flindris, S.; Papoudou-Bai, A.; Kapsali, E. Plasmablastic Lymphoma with Coexistence of Chronic Lymphocytic Leukemia in an Immunocompetent Patient: A Case Report and Mini-Review. Case Rep. Hematol. 2017, 2017, 2861596. [Google Scholar] [CrossRef] [Scilit]
- Robak, T.; Urbańska-Ryś, H.; Strzelecka, B.; Krykowski, E.; Bartkowiak, J.; Bĺoński, J.Z.; Kordek, R.; Warzocha, K. Plasmablastic lymphoma in a patient with chronic lymphocytic leukemia heavily pretreated with cladribine (2-CdA): An unusual variant of Richter’s syndrome. Eur. J. Haematol. 2001, 67, 322–327. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Reyero, J.; Magunacelaya, N.M.; de Villambrosia, S.G.; Loghavi, S.; Mediavilla, A.G.; Tonda, R.; Beltran, S.; Gut, M.; Gonzalez, A.P.; D’ámore, E.; et al. Genetic lesions in MYC and STAT3 drive oncogenic transcription factor overexpression in plasmablastic lymphoma. Haematologica 2021, 106, 1120–1128. [Google Scholar] [CrossRef] [Scilit]
- van den Brand, M.; Möbs, M.; Otto, F.; Kroeze, L.I.; de Castro, D.G.; Stamatopoulos, K.; Davi, F.; Bravetti, C.; Kolijn, P.M.; Vlachonikola, E.; et al. EuroClonality-NGS Recommendations for Evaluation of B-Cell Clonality Analysis by Next-Generation Sequencing. J. Mol. Diagn. 2023, 25, 729–739. [Google Scholar]
- Loghavi, S.; Alayed, K.; Aladily, T.N.; Zuo, Z.; Ng, S.B.; Tang, G.; Hu, S.; Yin, C.C.; Miranda, R.N.; Medeiros, L.J.; et al. Stage, age, and EBV status impact outcomes of plasmablastic lymphoma patients: A clinicopathologic analysis of 61 patients. J. Hematol. Oncol. 2015, 8, 65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Castillo, J.J.; Guerrero-Garcia, T.; Baldini, F.; Tchernonog, E.; Cartron, G.; Ninkovic, S.; Cwynarski, K.; Dierickx, D.; Tousseyn, T.; Lansigan, F.; et al. Bortezomib plus EPOCH is effective as frontline treatment in patients with plasmablastic lymphoma. Br. J. Haematol. 2019, 184, 679–682. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- WHO Classification of Tumours Editorial Board. Haematolymphoid tumours. In WHO Classification of Tumours, 5th ed.; International Agency for Research on Cancer: Lyon, France, 2022; Volume 11. [Google Scholar]
- Grimm, K.E.; O’Malley, D.P. Aggressive B cell lymphomas in the 2017 revised WHO classification of tumors of hematopoietic and lymphoid tissues. Ann. Diagn. Pathol. 2019, 38, 6–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazumder, S.; Jinkala, S.; Gochhait, D.; Manivannan, P.; Amalnath, D. Concomitant diagnosis of plasmablastic lymphoma and chronic lymphocytic leukemia: A rare phenomenon. Int. J. Appl. Basic Med. Res. 2021, 11, 201. [Google Scholar] [CrossRef] [Scilit]
- Holderness, B.M.; Malhotra, S.; Levy, N.B.; Danilov, A.V. Brentuximab vedotin demonstrates activity in a patient with plasmablastic lymphoma arising from a background of chronic lymphocytic leukemia. J. Clin. Oncol. 2013, 31, e197–e199. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.