


Abstract
Background: Peritonitis remains a major complication of peritoneal dialysis (PD), and most previous studies have focused little on the recurrent burden of peritonitis. We investigated the associations of longitudinal complete blood count (CBC)-derived biomarkers with first and subsequent qualifying peritonitis episodes using a recurrent-event framework. Methods: Incident PD patients enrolled between 28 December 2011 and 3 November 2021 were followed through 31 December 2022. Each CBC-derived biomarker was modeled separately as a time-varying exposure in an event-order-stratified Prentice, Williams and Peterson total time (PWP-TT) model of 30-day-separated qualifying peritonitis episodes, adjusted for confounding factors. Restricted cubic splines (RCS) revealed the true shape of the relationship. Biomarkers were assessed separately with Benjamini–Hochberg false discovery rate (BH-FDR) correction for multiple comparisons. Sensitivity analyses included a common complete-case analysis, PWP gap time (PWP-GT), and patient-level shared frailty models. Results: A total of 374 incident PD patients, 10,057 lab records and 179 peritonitis episodes were included in the analysis. Higher neutrophil-to-lymphocyte ratio (NLR) was associated with increased risk of qualifying peritonitis episodes in the multivariate PWP-TT analysis (HR 1.073, 95% CI 1.025–1.123, BH-FDR-adjusted p = 0.018). RCS analysis showed a nonlinear association for NLR (p overall < 0.001, p nonlinearity = 0.022), with risk increasing at higher NLR levels. Systemic inflammation response index (SIRI) showed a similar association (HR 1.099, 95% CI 1.021–1.184, BH-FDR-adjusted p = 0.050) with no evidence of nonlinearity (p nonlinearity = 0.112). Findings were unchanged in the common complete-case analysis and directionally consistent in PWP-GT and shared frailty models. Conclusions: Higher NLR was robustly associated with an increased risk of first and subsequent qualifying peritonitis episodes, with a nonlinear pattern. Whereas SIRI showed a similar but less robust association. These findings support the potential utility of NLR for longitudinal peritonitis risk assessment in PD.
1. Introduction
Peritoneal dialysis-associated peritonitis (PDAP) remains a serious complication of peritoneal dialysis (PD) and may result in catheter removal, transfer to hemodialysis, and death [1]. The 2022 International Society for Peritoneal Dialysis (ISPD) guideline continues to regard peritonitis frequency as a key quality indicator, recommending an overall rate of no more than 0.40 episodes per patient-year and that more than 80% of patients remain peritonitis-free each year [1]. Beyond peritonitis frequency itself, the outcome was affected by prior peritonitis history. In the multinational Peritoneal Dialysis Outcomes and Practice Patterns Study, the probability of cure declined with an increasing number of prior peritonitis episodes [2], suggesting that the clinical course of a peritonitis episode depends, at least in part, on the patient’s preceding peritonitis history. Collectively, it is important to consider prior peritonitis history when evaluating PDAP outcomes, rather than treating each episode as an isolated event.
Complete blood count (CBC)-derived biomarkers are inexpensive and readily available biomarkers of systemic inflammation. Several CBC-derived biomarkers have been associated with PDAP. Higher neutrophil-to-lymphocyte ratio (NLR), platelet-to-lymphocyte ratio (PLR), and systemic inflammation response index (SIRI) have been reported for the occurrence of PDAP [3]. An elevated monocyte-to-lymphocyte ratio (MLR) and PLR at PD initiation were associated with the risk of first peritonitis [4,5] and systemic immune-inflammation index (SII) has been associated with frequent PDAP [6]. More recently, a multicenter cohort of 2036 PD patients showed that elevated pan-immune inflammatory value (PIV), SII, and PLR were associated with higher risk of first peritonitis [7]. However, the available longitudinal studies have largely focused on the first peritonitis episode [4,5,7], while studies addressing multiple episodes have classified patients according to peritonitis frequency rather than explicitly modeling recurrent events [6]. Patients may experience multiple episodes during longitudinal follow-up, and the clinical course of subsequent episodes [2,8], and peritoneal membrane function [9,10] may be influenced by previous peritonitis. Accordingly, restricting analysis to the first episode omits information contained in subsequent events [11] and may incompletely characterize the overall longitudinal burden of PDAP. Furthermore, CBC-derived biomarkers may change during longitudinal follow-up; serial NLR measurements have demonstrated distinct longitudinal patterns during follow-up [12], whereas most available studies have relied on measurements obtained at a single time point.
To address this gap, we conducted a long-term follow-up study to investigate the associations between CBC-derived biomarkers and first and subsequent qualifying peritonitis episodes using a recurrent-event framework. By incorporating multiple episodes and their event order within the same patient and treating biomarkers as time-varying exposures, this approach enabled a more comprehensive assessment of peritonitis risk over time. In this study, we further explored the potential utility of CBC-derived biomarkers for longitudinal risk stratification in PD patients.
2. Methods
2.1. Population and Data Collection
In this retrospective cohort study, all incident patients who started PD therapy from 28 December 2011 to 3 November 2021 at Peking University Third Hospital and were followed up regularly were included. Patients were excluded if they lacked baseline information, had no follow-up data during the observation period, had received any form of dialysis except for peritoneal dialysis for more than 1 month, or had received previous kidney transplantation. Patients who started PD in other centers and transferred to our center midway were also excluded because we were unable to get their complete clinical laboratory data information.
In our center, patients’ clinical history, demographics, and clinical lab assays were detailed recorded when following up. All parameters were measured in the clinical laboratory of Peking University Third Hospital. In this study, the complete blood cell counts were performed using the Sysmex automatic blood analyzer XN-10 [B4]. In addition, after PD initiation, all patients were closed and followed by dedicated nurses. In our center, patient education and staff education are in line with ISPD recommendations. All the new incidents of complications during the follow-up were recorded in our center. The study protocol was approved by the Peking University Third Hospital Medical Science Research Ethics Committee, M20241122. Waiver of informed consent and use of data by this study was permitted by the Peking University Third Hospital Medical Science Research Ethics Committee due to the retrospective design of the present study. Patients were followed until death, cessation of PD, failure to follow up, or 31 December 2022.
2.2. Study Outcome and Peritonitis Definition
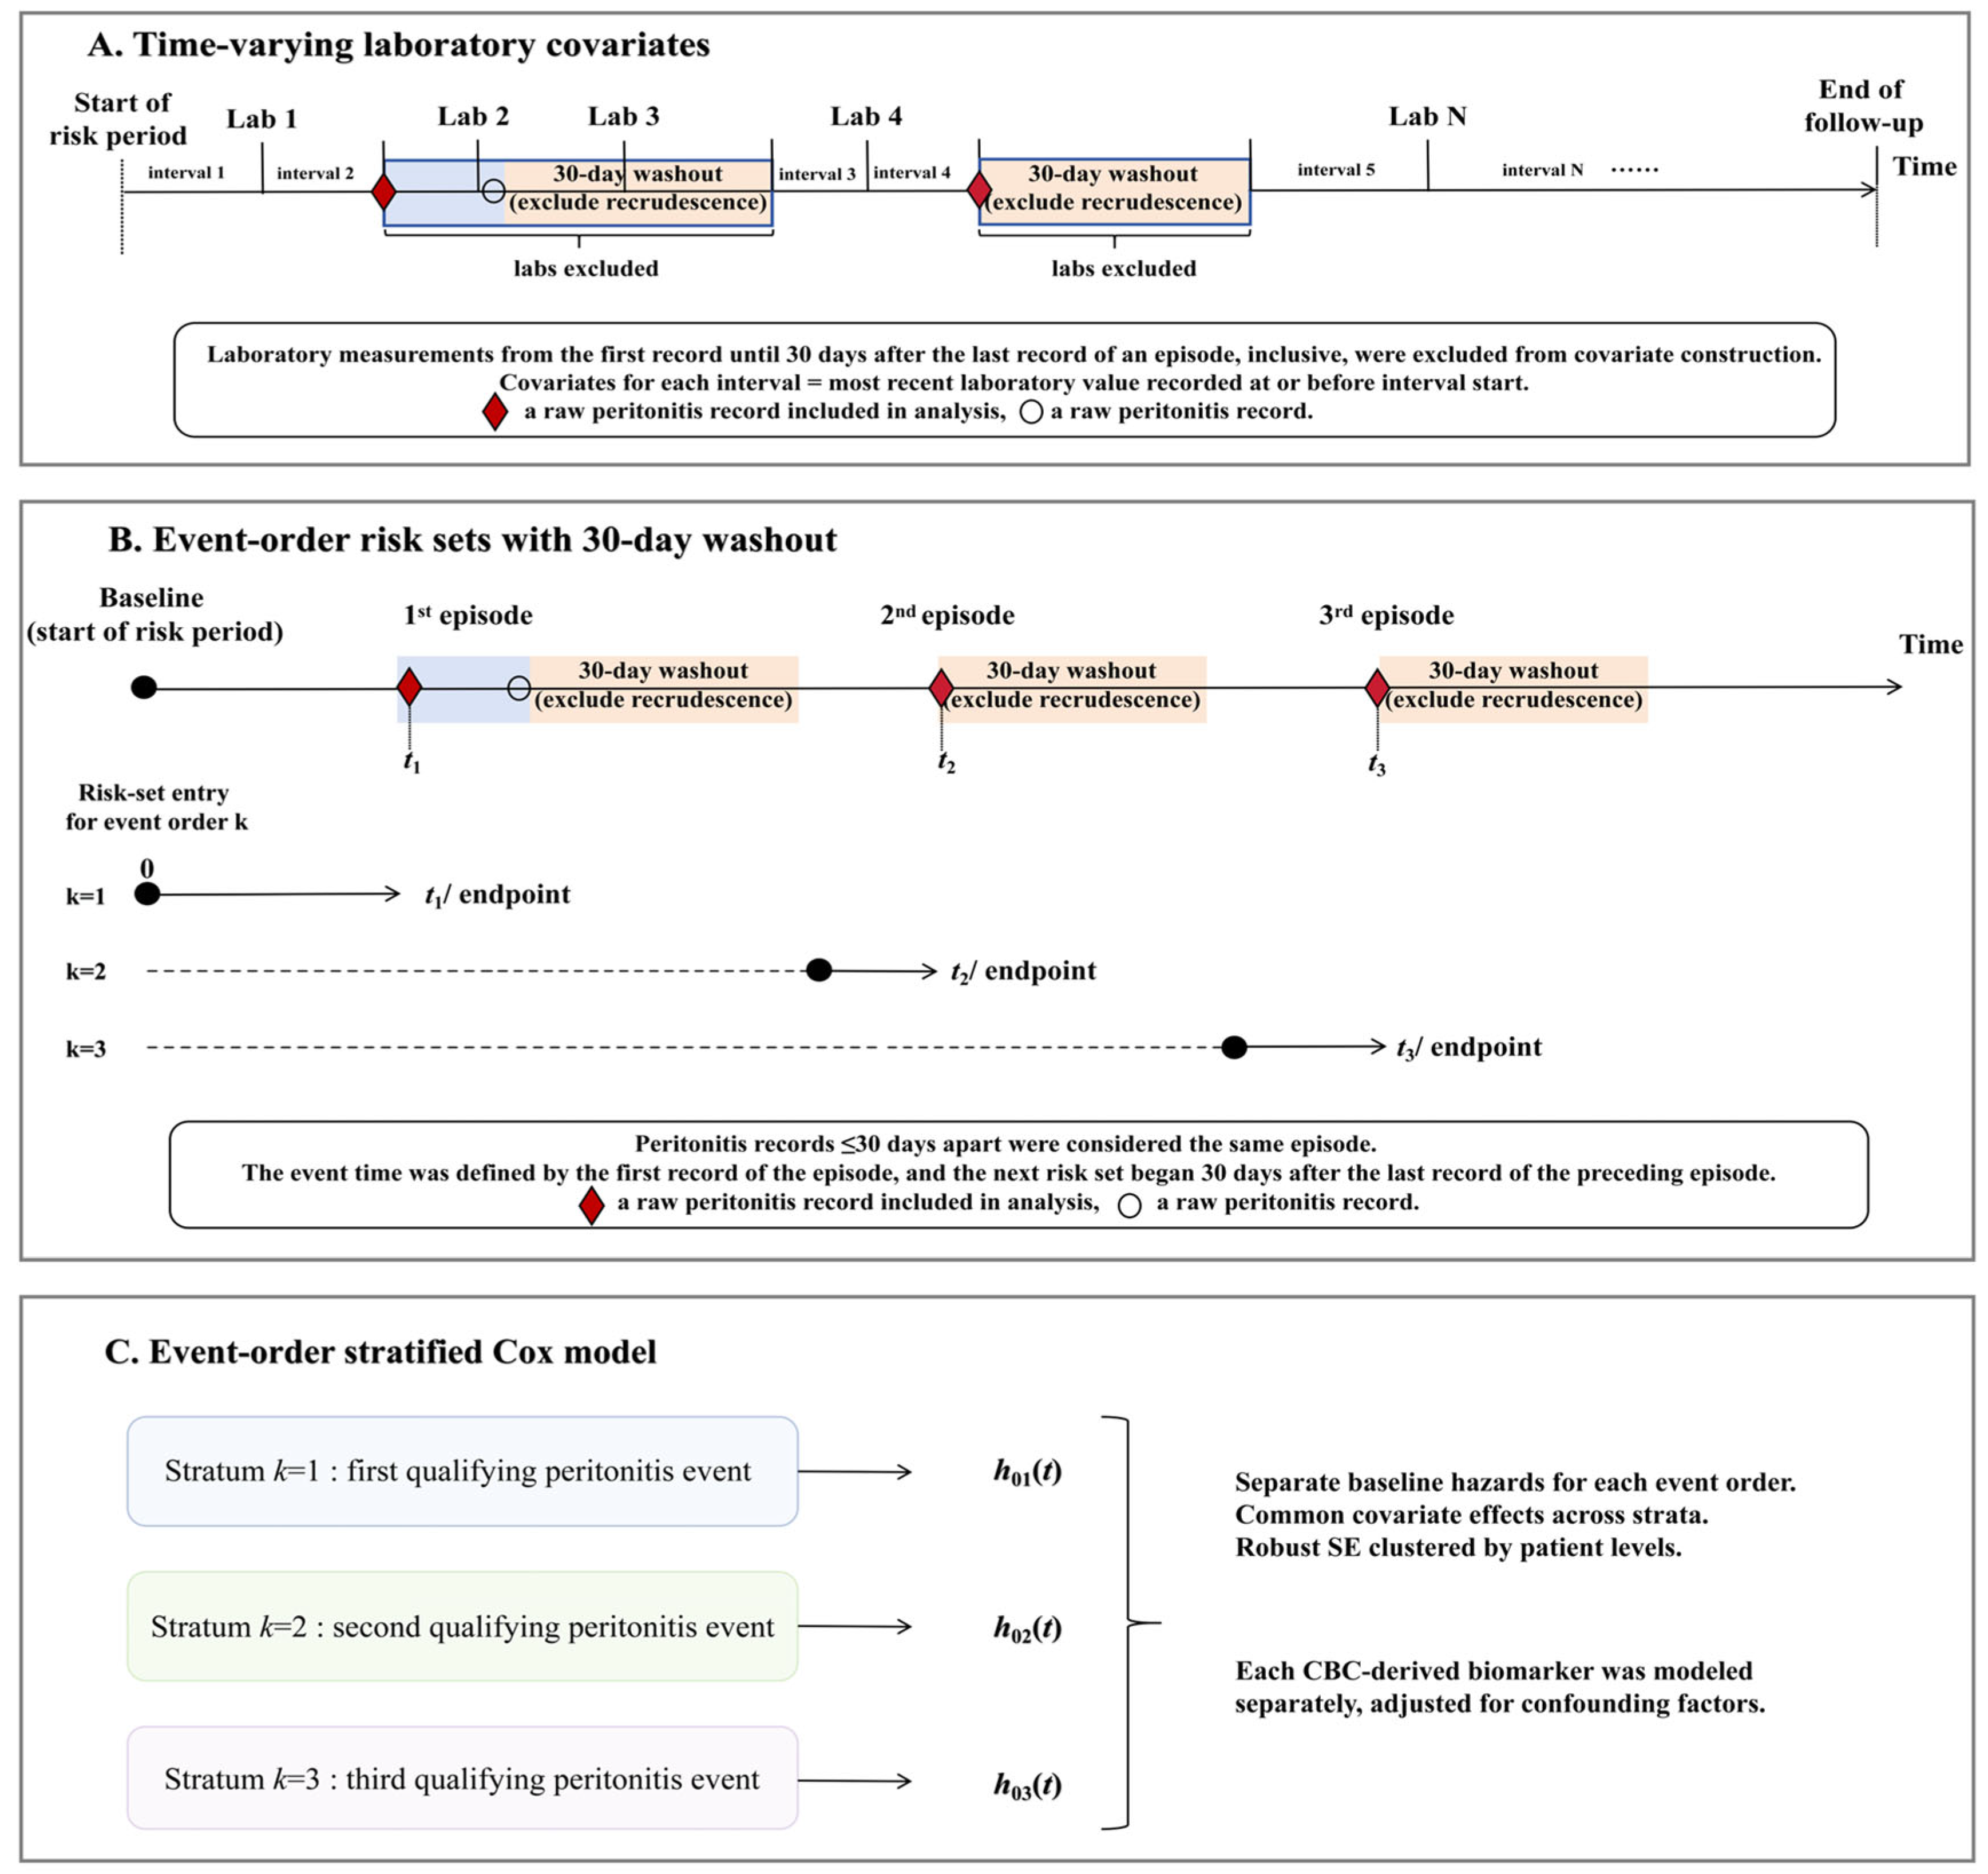
PDAP was diagnosed according to the ISPD guidelines applicable at the time [1,13]. The diagnosis required at least two of the following criteria: (1) Clinical features of abdominal pain and/or cloudy peritoneal effluent; (2) Dialysate white cell count > 100 cells/µL after a dwell time of at least 2 h with >50% polymorphonuclear leukocytes; and (3) Positive dialysate effluent culture. The outcome was the first and subsequent qualifying peritonitis episodes after PD catheter insertion. The first peritonitis episode after catheter insertion was counted as an event. For each patient, consecutive raw peritonitis records were considered to belong to the same clinical episode if they were within 30 days of each other (Figure 1).
Figure 1.
PWP-TT recurrent-event Cox model for first and subsequent qualifying peritonitis episodes. Abbreviations: PWP-TT: Prentice, Williams and Peterson total time.
2.3. The Formula Calculation for CBC-Derived Biomarkers
mean platelet volume to platelet count ratio (MPV/PC) = mean platelet volume/platelet count × 100
NLR = neutrophil count/lymphocyte count
MLR = monocyte count/lymphocyte count × 10
PLR = platelet count/lymphocyte count/100
SIRI = neutrophil count × monocyte count/lymphocyte count
PIV = (neutrophil count × platelet count × monocyte count)/lymphocyte count/100
SII = (neutrophil count × platelet count)/lymphocyte count/100
2.4. Statistical Analysis
All data were obtained from routine clinical records at Peking University Third Hospital, encompassing baseline data at dialysis initiation, follow-up data, and outcome data. Clinical laboratory parameters, such as albumin, blood phosphorus, and more, were collected during each patient visit. Results of clinical and laboratory characteristics were expressed as frequencies and percentages for categorical variables, mean ± standard deviation for continuous normally distributed variables, and median (interquartile range, IQR) for continuous variables that were not normally distributed. Comparison for patients in different groups was performed using chi-square tests, two-tailed unpaired t-tests, or Mann–Whitney’s tests, depending on data distribution.
2.5. Peritonitis Episode Definition and Laboratory Record Selection
In the analysis, consecutive raw peritonitis records separated by ≤30 days were merged into one episode. Episode onset, as well as event time, was the date of its first record, and the 30-day washout period began after its last record. A new episode required >30 days since the last record of the preceding episode. Laboratory measurements were restricted to the period from PD catheter insertion to the end of follow-up. Measurements from the onset of each peritonitis episode through 30 days after its last raw record, inclusive, were excluded before last-observation-carried-forward (LOCF) imputation and time-varying covariates construction.
2.6. Handling of Missing Data and Time-Varying Covariates
Laboratory variables were measured repeatedly at irregular intervals and were incorporated into the survival analyses as time-varying covariates. To preserve temporal ordering and prevent the use of future information, laboratory records were chronologically ordered within each patient, and a history-restricted LOCF approach was applied [14]. For each laboratory parameter, a missing observation was replaced by the most recent available historical value. Values preceding the first available measurement of a given parameter were left missing, and no backward filling or other imputation using subsequent measurements was allowed.
Within each event-specific risk period, follow-up was divided into contiguous start-stop intervals at laboratory measurement times, with the risk-set entry time and event, or censoring time defining the boundaries of the risk period. Time-varying covariate value was assigned using the most recent laboratory measurement recorded at or before the beginning of each interval. After LOCF, if any variable required for a given model remained missing, the corresponding risk intervals were excluded from that model.
2.7. Prentice, Williams and Peterson Total Time (PWP-TT) Model
First and subsequent qualifying peritonitis episodes were analyzed using Cox proportional hazards regression under the PWP-TT model conditional risk-set framework [15,16]. Follow-up time was measured from the date of PD catheter insertion. Analyses were restricted to the first three qualifying peritonitis episodes because relatively few patients remained at risk for higher-order events [15]. For the first event, risk time began at catheter insertion. For higher-order events, patients became eligible for the next conditional risk set only after the washout period following the preceding episode had been completed, and they remained under observation.
Within each event-specific risk period, follow-up was represented in the counting process using start–stop intervals. Separate baseline hazard functions were allowed for the first, second, and third event orders by stratifying the Cox model by event order. Covariate effects were estimated as common effects across the event-order strata. Patient-level cluster-robust standard errors were used to account for correlation arising from repeated intervals and repeated qualifying peritonitis episodes within the same individual. Tied event times were handled using the Efron method [17] (Figure 1).
2.8. Associations with First and Subsequent Qualifying Peritonitis Episodes
Associations of the eight CBC-derived biomarkers, albumin and other clinical variables with the risk of first and subsequent qualifying peritonitis episodes were initially examined using univariable PWP-TT models. Effect estimates are presented as hazard ratios (HRs) with 95% confidence intervals (CIs). The proportional hazards assumption was assessed for each fitted PWP-TT model using tests based on Schoenfeld residuals. Both covariate-specific and global test results were examined, with a global p value > 0.05 interpreted as indicating no evidence against the proportional hazards assumption.
Each CBC-derived biomarker was subsequently evaluated in a separate multivariable PWP-TT model. Factors, which p value < 0.1 in univariable mode, as adjustment set were entered simultaneously. As in the univariable analyses, models were stratified by event order and patient-clustered robust standard errors were used.
Multicollinearity was evaluated separately for each adjusted model using variance inflation factors (VIFs). For each predictor, the VIF was derived from a linear regression of that predictor on the remaining covariates in the same model. A VIF > 5 was considered indicative of potentially important multicollinearity.
To account for multiple comparisons in the primary multivariable analyses, p value for the eight CBC-derived biomarkers were adjusted using the Benjamini–Hochberg false discovery rate (BH-FDR) procedure [18]. BH-FDR-adjusted p-values < 0.05 were considered statistically significant.
2.9. Assessment of Nonlinear Associations
Potential nonlinear associations between CBC-derived biomarkers and the risk of first and subsequent qualifying peritonitis episodes up to the third event order were examined using restricted cubic spline (RCS). Each spline model was fitted within the PWP-TT framework, using 4 knots, and was adjusted for confounding factors. Event-order-specific baseline hazards and patient-clustered robust variance estimation were retained as in the primary multivariable models.
Hazard-ratio curves were referenced to the median marker value in the corresponding analysis sample. The overall association of each marker and evidence of departure from linearity were evaluated using Wald χ2 tests for the complete spline term and its nonlinear component, respectively. p values < 0.05 for the nonlinear component were considered evidence of a nonlinear association. When nonlinearity was significant, the hazard ratio from the PWP-TT model was interpreted as an average overall trend and reported for reference only; the RCS curve was used to describe the shape of the association.
2.10. Sensitivity Analyses
As sensitivity analyses, the multivariable PWP-TT models were repeated in a common complete-case sample with complete data for all CBC-derived biomarkers and adjustment covariates. PWP gap time (PWP-GT) model [19] and a patient-level shared frailty model [20] were conducted, both of which were stratified by event order and adjusted for confounding factors.
The statistical analyses were performed using R version 4.5.2 and IBM SPSS Statistics 25.
3. Results
3.1. Patient Characteristics
A total of 374 incident PD patients were included in this study. The median follow-up duration was 2.38 years (interquartile range 1.35, 4.54). 10,057 lab records, 210 peritonitis records and 179 episodes were included in the analysis. Baseline Clinical and laboratory characteristics are depicted in Table 1. Of them, 108 PD patients experienced at least one episode of peritonitis, among whom 70 had one episode, 25 had two episodes, 6 had three episodes, and 7 had at least four episodes. Cultures negative for peritonitis were observed in 50 records. The most common pathogens were Staphylococcus epidermidis (28, 13.3%), Escherichia coli (16, 7.6%) and Klebsiella pneumoniae (12, 5.7%). Mixed infections (≥2 organisms) were observed in 10 records. In total, 155 records were treatment successes (defined as improvement or cure), while 47 records were treatment failures (defined as death, catheter removal, relapse, permanent transfer to hemodialysis). After applying the PWP risk-set rules, 158 event observations were included: 107 first events, 38 s events, and 13 third events. Interval-level comparison of laboratory parameters between PWP-TT risk intervals without a qualifying peritonitis episode and PWP-TT risk intervals ending in a qualifying peritonitis episode in the final PWP analysis cohort was depicted in Supplement Table S1.
Table 1.
Baseline clinical and laboratory characteristics of peritoneal dialysis patients according to the occurrence of peritonitis during follow-up.
3.2. The Relationship of CBC-Derived Biomarkers and First and Subsequent Qualifying Peritonitis Episodes by Univariate PWP-TT Analysis
We found that increased NLR, increased SIRI, increased MPV/PC, and increased PIV were associated with increased risk of peritonitis occurrence. However, we did not find a significant association between mean platelet volume (MPV), MLR, PLR, SII, and first and subsequent qualifying peritonitis episodes. (Table 2).
Table 2.
Univariable PWP-TT analysis of factors associated with first and subsequent qualifying peritonitis episodes in PD.
3.3. The Relationship of CBC-Derived Biomarkers and First and Subsequent Qualifying Peritonitis Episodes by Multivariate PWP-TT Analysis
After adjusting for age, albumin and phosphorus, multivariate PWP-TT analysis showed that NLR (HR 1.073, 95% CI 1.025–1.123, BH-FDR-adjusted p = 0.018) and SIRI (HR 1.099, 95% CI 1.021–1.184, BH-FDR-adjusted p = 0.050) were independently associated with increased risk of first and subsequent qualifying peritonitis episodes. However, we did not find a significant independent association between MPV/PC, PIV and first and subsequent qualifying peritonitis episodes (Table 3). In RCS analysis, we found that the associations between MPV/PC, MPV, PLR, SIRI, PIV, SII, and first and subsequent qualifying peritonitis episodes showed no evidence of nonlinearity after adjusting for age, phosphorus, and albumin (Figure 2). However, NLR showed a significant nonlinear association (p overall < 0.001, p nonlinearity = 0.022), with higher risk at higher NLR levels. MLR showed a nonlinear pattern (p overall = 0.057, p nonlinearity = 0.026) without a significant overall association. Given the significant nonlinearity for NLR, the linear HR was interpreted as an average effect across the exposure range and was presented for reference only; the RCS curve was used to describe the shape of the association.
Table 3.
Multivariable PWP-TT analysis of factors associated with first and subsequent qualifying peritonitis episodes in PD.
Figure 2.
Restricted cubic spline fitting for the association between each CBC-derived biomarker and first and subsequent qualifying peritonitis episodes, up to the third event order, adjusted for phosphorus, albumin, and age. Abbreviations: CBC: complete blood count; MPV/PC (a): mean platelet volume to platelet count ratio; MPV (b): mean platelet volume; NLR (c): neutrophil-to-lymphocyte ratio; MLR (d): monocyte-to-lymphocyte ratio; PLR (e): platelet-to-lymphocyte ratio; SIRI (f): systemic inflammation response index; PIV (g): pan-immune inflammation value; SII (h): systemic immune-inflammation index.
3.4. Sensitivity Results
The common complete-case analysis yielded results similar to those of the specific CBC-derived biomarker analyses. Associations for NLR (HR 1.080, 95% CI 1.034–1.127, p < 0.001) and SIRI (HR 1.098, 95% CI 1.027–1.174, p = 0.006) persisted in the PWP-GT models. Similar results were observed for NLR (HR 1.085, 95% CI 1.032–1.141, p = 0.001) and SIRI (HR 1.117, 95% CI 1.030–1.211, p = 0.008) in the shared frailty models (Supplement Table S2).
4. Discussion
In this study, we investigated the associations of longitudinal CBC-derived biomarkers with first and subsequent qualifying peritonitis episodes in PD patients using a recurrent-event framework. NLR showed the most robust association with peritonitis risk and remained statistically significant after BH-FDR correction. RCS analysis further revealed a significant nonlinear association for NLR, with higher risk at higher NLR levels. SIRI also showed a positive association, which was borderline after multiple-comparison correction. These findings were broadly consistent across common complete-case, PWP-GT, and patient-level shared frailty analyses, supporting a robust association between higher NLR levels and an increased risk of qualifying peritonitis episodes during PD.
Unlike conventional first-event analyses, the PWP-TT framework allowed us to account for multiple qualifying peritonitis episodes within the same patient while preserving event order and the total-time scale from PD initiation. Distinct episodes were defined using a prespecified 30-day separation rule, with patients re-entering the subsequent risk set only after completion of the washout period. The analysis was restricted to the first three-episode orders because higher-order risk sets were sparse. In addition, biomarkers and relevant laboratory covariates were updated using the most recent measurements available before each risk interval, thereby better reflecting patients’ evolving clinical status during follow-up.
Evidence from a meta-analysis of 11 studies suggested that NLR was associated with the occurrence of PDAP [21]. NLR has also been reported as an independent risk factor for treatment failure in PD-related peritonitis [22]. Extending these findings, our study showed that higher NLR remained significantly associated with the risk of qualifying peritonitis episodes after accounting for multiple events within the same patient using the PWP-TT model. In our study, NLR was measured before the onset of clinically apparent peritonitis; the observed association is unlikely to be explained solely by the inflammatory response accompanying a peritonitis episode. NLR integrates variations in circulating neutrophil and lymphocyte counts; it has been established as a parameter of systemic inflammation and physiological stress [23], reflecting the dynamic relationship between innate and adaptive cellular immune responses [24]. One possible explanation is that an elevated pre-event NLR reflects an underlying immune-inflammatory phenotype associated with greater susceptibility to infection. Uremia is characterized by disturbances of both innate and adaptive immunity, with immunoactivation contributing to chronic inflammation while immunodepression contributes to the increased susceptibility to infection [25]. Although neutrophils may exhibit chronic low-grade activation in CKD, the antibacterial capacity of innate immune effectors can be impaired, together with substantial alterations in adaptive immune responses [26]. Therefore, increased neutrophil predominance or activation in the uremic milieu does not necessarily indicate preserved or enhanced antimicrobial competence. Recent evidence indicates that CKD and ESKD are accompanied by adaptive immunosenescence, including reductions in naive lymphocyte populations, altered T-cell and B-cell responses, and a diminished capacity to respond to new infectious challenges, despite concomitant increases in pro-inflammatory mediators [27]. A higher NLR before peritonitis may reflect an underlying state of immune-inflammatory dysregulation rather than indicating enhanced antimicrobial defense. Such underlying immune-inflammatory dysregulation could also provide a plausible biological explanation for the association between higher NLR and qualifying peritonitis during follow-up.
Another explanation is that an elevated NLR measured shortly before peritonitis captures an early inflammatory response during an evolving but not clinically apparent infectious process. Neutrophil mobilization can occur rapidly after an inflammatory stimulus; in a murine model of acute peritonitis, intraperitoneal thioglycollate administration produced a 4.5-fold increase in circulating neutrophils within 2 h [28]. Lymphopenia can be a feature of infections [29]. Therefore, when the interval between NLR measurement and peritonitis onset is short, an elevated NLR could represent an early marker of incipient inflammation following microbial exposure before overt clinical manifestations develop.
Taken together, elevated pre-event NLR may reflect either a pre-existing immune-inflammatory state linked to increased susceptibility to peritonitis, or an early systemic response to a developing infectious process. These two mechanisms are not mutually exclusive, and cannot be differentiated based on the current observational data. Future research including serial NLR measurements and evaluating the interval between NLR assessment and peritonitis onset may help clarify whether NLR predominantly reflects a relatively persistent host susceptibility phenotype or short-term preclinical inflammatory changes.
SIRI integrates neutrophil, monocyte, and lymphocyte counts and may therefore capture a broader systemic inflammatory profile than NLR by incorporating the monocyte component. Liu et al. reported that SIRI was independently associated with the occurrence of PDAP [3], which is consistent with the direction of our findings, although the association in our primary analysis was attenuated after correction for multiple comparisons. The additional monocyte component may provide information on the early systemic cellular response to inflammation. During inflammation, monocytes can be mobilized from the bone marrow into the circulation and subsequently recruited to inflamed tissues [30], including the peritoneal cavity, where monocyte-derived macrophages contribute to help eliminate infection and to clear apoptotic debris and resolve inflammation [31]. By incorporating circulating monocytes in addition to neutrophils and lymphocytes, SIRI may capture an additional dimension of the systemic inflammatory response that is relevant to evolving peritoneal inflammation.
Unlike NLR and SIRI, MPV/PC, PLR, PIV and SII incorporate platelet-related information. MPV reflects platelet size and is commonly used as a marker of platelet activation [32]. Previous studies have suggested that MPV may reflect systemic inflammation during acute peritonitis in PD patients [33]. In addition, lower MPV/PC has been associated with time to the first new-onset infection event in PD patients [34], while PLR [5] and SII [6] have been linked to incident or frequent PDAP. However, most of these findings were derived from first-event, single-event or composite-outcome analyses rather than recurrent models.
In the present study, MPV, MPV/PC, PLR, PIV and SII were not independently associated with qualifying peritonitis episodes in the multivariable PWP-TT analyses. Several factors may contribute to these differences from previous reports. First, compared with logistic regression or conventional Cox models, the PWP-TT framework explicitly conditions subsequent risk sets on preceding events, incorporates time-varying covariates, and accounts for within-patient correlation, thereby providing a more structured assessment of subsequent peritonitis. Second, platelet-related indices may be influenced by multiple factors unrelated to peritonitis. Chronic kidney disease is characterized by complex and sometimes opposing alterations in platelet function, including both impaired and enhanced platelet reactivity, which may weaken the specificity of platelet-derived biomarkers [35]. In addition, patients with renal failure requiring maintenance dialysis have a high cardiovascular risk and may require antithrombotic therapies [36], which can affect platelet count and function. Third, MPV is also susceptible to pre-analytical variation, including the type of anticoagulant used and the time interval between venipuncture and measurement [37]. Collectively, these biological and analytical factors may contribute to the variability of MPV, MPV/PC, PLR, PIV and SII and limit their specificity for peritonitis risk.
MLR was not significantly associated with qualifying peritonitis episodes in our study. In contrast, a recent study reported that a higher MLR at PD initiation was independently associated with subsequent peritonitis risk, although that analysis was based on a baseline measurement and conventional time-to-first-event Cox regression [4]. This difference may partly reflect the longitudinal design of our study and its ability to capture multiple events over time. MLR captures the balance between monocytes and lymphocytes, whereas SIRI additionally incorporates neutrophils and may provide a more integrated representation of systemic inflammatory and immune status [38,39]. Given the rapid mobilization and key role in antimicrobial defense during infection [40], the additional neutrophil component of SIRI may partly explain its stronger association with qualifying peritonitis episodes in our analysis. However, this interpretation remains hypothesis-generating and requires further validation.
According to the ISPD guidelines, the diagnosis of PDAP relies on clinical manifestations, dialysate leukocyte count and differential, and microbiological culture. CBC-derived biomarkers reflect systemic inflammatory and immune responses and are not specific to peritoneal infection. Although several observational studies have demonstrated associations between these biomarkers and the occurrence or outcomes of PDAP [3,4,7,41], evidence directly comparing CBC-derived biomarkers with dialysate inflammatory parameters remains limited. A recent study reported only weak correlations between hematologic inflammatory indices and dialysate leukocyte counts, without significant associations with clinical outcomes [42]. Therefore, these CBC-derived biomarkers should not be regarded as diagnostic biomarkers for PD peritonitis. Peritoneal dialysate analysis remains the cornerstone of diagnosis, and blood biomarkers may only serve as potential tools for risk stratification.
Several additional biomarkers have been investigated in PDAP, including dialysate IL-6, matrix metalloproteinase-8, and neutrophil gelatinase-associated lipocalin [43], as well as serum CRP [44]. A previous study has demonstrated that IL-6/MMP-8-based point-of-care testing has high sensitivity and predictive values for diagnosing PDAP, supporting its potential as a screening tool that may facilitate early diagnosis [45]. Nevertheless, the ISPD guidelines do not currently recommend novel biomarker-based diagnostic methods for routine clinical use, as their ability to replace conventional diagnostic criteria has not been established [1]. Further prospective, multicenter studies are needed to determine clinically meaningful thresholds, validate incremental predictive value, and clarify whether these biomarkers can improve clinical decision-making.
This study has several limitations. First, although the data were prospectively collected, the present analysis was retrospective and therefore remains susceptible to potential bias; prospective studies are needed to further validate these findings. Second, the single-center study may limit the generalizability of the results. Third, residual confounding cannot be excluded because potentially relevant factors, such as the use of antiplatelet or other medications affecting platelet function, were not fully controlled for. Fourth, competing events were not explicitly modeled. Fifth, the 10-year study period spanned several updates in PD management guidelines; although the diagnostic criteria of PDAP remained consistent throughout the study period, temporal changes in treatment strategies and other clinical practices may have influenced patient outcomes. Therefore, time-period bias cannot be fully excluded. Sixth, we cannot entirely exclude the possibility that peritonitis was already present but remained undiagnosed at the time of CBC-derived measurement, although such cases are uncommon in our routine clinical practice. Beyond these limitations, this study has several strengths. The availability of longitudinal follow-up data allowed CBC-derived biomarkers and relevant laboratory variables to be evaluated dynamically over time. Moreover, the PWP-TT framework enabled the analysis of first and subsequent qualifying peritonitis episodes while preserving event order and accounting for within-patient dependence. The consistency of the findings across alternative analytical approaches further supports the robustness of the observed associations.
5. Conclusions
Higher NLR was robustly associated with an increased risk of first and subsequent qualifying peritonitis episodes with evidence of nonlinearity, while the association observed for SIRI was less robust. These findings suggest that NLR may serve as a useful marker for longitudinal risk assessment of peritonitis in PD patients. In clinical practice, NLR may help identify higher-risk PD patients who could benefit from closer follow-up and reinforcement of preventive measures, including reassessment of PD exchange techniques and infection-prevention education. Further external validation is needed before its routine clinical implementation.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/life16111831/s1, Table S1: Interval-level comparison of laboratory parameters between PWP-TT risk intervals without a qualifying peritonitis episode and PWP-TT risk intervals ending in a qualifying peritonitis episode in the final PWP analysis cohort; Table S2: Sensitivity analyses of the associations between CBC-derived biomarkers and first and subsequent qualifying peritonitis episodes.
Author Contributions
Conceptualization, W.T.; methodology, W.T.; formal analysis, X.-Q.Z.; writing—original draft preparation, X.-Q.Z.; writing—review and editing, W.T.; funding acquisition, W.T. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by the National Natural Science Foundation of China [grant number 82470774].
Institutional Review Board Statement
This study was conducted according to the guidelines of the Helsinki Declaration. The study protocol was approved by the Peking University Third Hospital Medical Science Research Ethics Committee, M20241122, approval date: 6 January 2025.
Informed Consent Statement
Waiver of informed consent and use of data by this study was permitted by the Peking University Third Hospital Medical Science Research Ethics Committee due to the retrospective design of the present study.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Acknowledgments
AI tool usage declaration: To enhance efficiency, we utilized the ChatGPT 5.6 Sol assistant (accessed June to August 2026) for initial code generation and debugging assistance. AI-assisted outputs were reviewed and validated by the authors. This tool was only used to accelerate the implementation process, while the design of the study, core ideas, and result analyses were independently completed by the authors. The authors took full responsibility for the content of the publication.
Conflicts of Interest
The authors declare that there is no conflict of interest regarding the publication of this article.
References
- Li, P.K.; Chow, K.M.; Cho, Y.; Fan, S.; Figueiredo, A.E.; Harris, T.; Kanjanabuch, T.; Kim, Y.L.; Madero, M.; Malyszko, J.; et al. ISPD peritonitis guideline recommendations: 2022 update on prevention and treatment. Perit. Dial. Int. 2022, 42, 110–153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Sahlawi, M.; Zhao, J.; Mccullough, K.; Fuller, D.S.; Boudville, N.; Ito, Y.; Kanjanabuch, T.; Nessim, S.J.; Piraino, B.M.; Pisoni, R.L.; et al. Variation in Peritoneal Dialysis-Related Peritonitis Outcomes in the Peritoneal Dialysis Outcomes and Practice Patterns Study (PDOPPS). Am. J. Kidney Dis. 2022, 79, 45–55.e41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Y.; Zhang, L.; Tian, T.; Guo, Z.; Shao, Y.; Ma, X.; Sheng, Y.; Sun, F. Diagnostic value of NLR, PLR and SIRI in peritoneal dialysis-associated peritonitis. Am. J. Transl. Res. 2025, 17, 2250–2257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, L.; Wang, L.; Jiang, X.; Yang, X.; Yu, X.; Ji, J.; Jiang, W.; Ding, X. Elevated Monocyte-to-Lymphocyte Ratio at Peritoneal Dialysis Initiation Predicts Long-Term Peritonitis Risk: A Retrospective Cohort Study. Blood Purif. 2025, 54, 554–564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Su, N.; Zheng, Y.; Zhang, X.; Tang, X.; Tang, L.W.; Wang, Q.; Chen, X.; Wang, X.; Wen, Y.; Feng, X.; et al. Platelet-to-lymphocyte ratio and the first occurrence of peritonitis in peritoneal dialysis patients. BMC Nephrol. 2022, 23, 415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, J.; Wang, D.; Chen, Y.; Feng, J. The association between new inflammation markers and frequent peritoneal dialysis-associated peritonitis. BMC Nephrol. 2024, 25, 81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, X.; Qiu, W.; Xu, Q.; Wen, Y.; Wu, X.; Zhan, X.; Peng, F.; Wang, X.; Wu, J.; Su, N.; et al. Predictive value of complete blood cell count-based inflammatory markers for peritonitis risk in peritoneal dialysis patients: A multicenter cohort study. PLoS ONE 2026, 21, e0354120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ljungquist, O.; Tobijaszewska, M.; Torisson, G.; Martus, G.; Segelmark, M.; Tverring, J. Modifiable risk factors for peritoneal dialysis-related infections–A population-based cohort study on risk factors and outcomes in South Sweden. Front. Nephrol. 2025, 5, 1583675. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Esch, S.; Struijk, D.G.; Krediet, R.T. The Natural Time Course of Membrane Alterations during Peritoneal Dialysis is Partly Altered by Peritonitis. Peritoneal. Dial. Int. J. Int. Soc. Perit. Dial. 2016, 36, 448–456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ito, Y.; Sun, T.; Tawada, M.; Kinashi, H.; Yamaguchi, M.; Katsuno, T.; Kim, H.; Mizuno, M.; Ishimoto, T. Pathophysiological Mechanisms of Peritoneal Fibrosis and Peritoneal Membrane Dysfunction in Peritoneal Dialysis. Int. J. Mol. Sci. 2024, 25, 8607. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Watson, V.; Smith, C.T.; Bonnett, L.J. Systematic review of methods used in prediction models with recurrent event data. Diagn. Progn. Res. 2024, 8, 13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lau, L.F.; Ng, J.K.; Fung, W.W.; Chan, G.C.; Cheng, P.M.; Chow, K.M.; Leung, C.B.; Li, P.K.; Szeto, C.C. Relationship between Serial Serum Neutrophil-Lymphocyte Ratio, Cardiovascular Mortality, and All-Cause Mortality in Chinese Peritoneal Dialysis Patients. Kidney Blood Press. Res. 2023, 48, 414–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, P.K.; Szeto, C.C.; Piraino, B.; Bernardini, J.; Figueiredo, A.E.; Gupta, A.; Johnson, D.W.; Kuijper, E.J.; Lye, W.C.; Salzer, W.; et al. Peritoneal dialysis-related infections recommendations: 2010 update. Perit. Dial. Int. 2010, 30, 393–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Digitale, J.; Franzon, D.; Pletcher, M.J.; McCulloch, C.E.; Gennatas, E.D. Methods for Addressing Missingness in Electronic Health Record Data for Clinical Prediction Models: Comparative Evaluation. JMIR Med. Inform. 2025, 13, e79307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amorim, L.D.; Cai, J. Modelling recurrent events: A tutorial for analysis in epidemiology. Int. J. Epidemiol. 2015, 44, 324–333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, Z.; Gill, T.M.; Allore, H.G. Modeling repeated time-to-event health conditions with discontinuous risk intervals. An example of a longitudinal study of functional disability among older persons. Methods Inf. Med. 2008, 47, 107–116. [Google Scholar] [PubMed]
- Efron, B. The Efficiency of Cox’s Likelihood Function for Censored Data. J. Am. Stat. Assoc. 1977, 72, 557–565. [Google Scholar] [CrossRef] [Scilit]
- Guo, B.; Liu, X.; Si, Q.; Zhang, D.; Li, M.; Li, X.; Zhao, Y.; Hu, F.; Zhang, M.; Liu, Y.; et al. Associations of CBC-Derived inflammatory indicators with sarcopenia and mortality in adults: Evidence from Nhanes 1999∼2006. BMC Geriatr. 2024, 24, 432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oyamada, S.; Chiu, S.-W.; Yamaguchi, T. Comparison of statistical models for estimating intervention effects based on time-to-recurrent-event in stepped wedge cluster randomized trial using open cohort design. BMC Med. Res. Methodol. 2022, 22, 123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gorfine, M.; Zucker, D.M. Shared Frailty Methods for Complex Survival Data: A Review of Recent Advances. Annu. Rev. Stat. Its Appl. 2023, 10, 51–73. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Z.; Li, Y.; Quan, Q.; Wang, H.; Zhang, W.; Zhang, X. Risk prediction models for peritoneal dialysis-associated peritonitis: A systematic review and meta-analysis. Int. Urol. Nephrol. 2026, 58, 967–979. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, J.; Zhu, L.; Ni, J.; Tong, M.; Wang, H. Technique failure in peritoneal dialysis-related peritonitis: Risk factors and patient survival. Ren. Fail. 2023, 45, 2205536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Islam, M.M.; Satici, M.O.; Eroglu, S.E. Unraveling the clinical significance and prognostic value of the neutrophil-to-lymphocyte ratio, platelet-to-lymphocyte ratio, systemic immune-inflammation index, systemic inflammation response index, and delta neutrophil index. Turk. J. Emerg. Med. 2024, 24, 8–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zahorec, R. Neutrophil-to-lymphocyte ratio, past, present and future perspectives. Bratisl. Lek. Listy 2021, 122, 474–488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kato, S.; Chmielewski, M.; Honda, H.; Pecoits-Filho, R.; Matsuo, S.; Yuzawa, Y.; Tranaeus, A.; Stenvinkel, P.; Lindholm, B. Aspects of immune dysfunction in end-stage renal disease. Clin. J. Am. Soc. Nephrol. 2008, 3, 1526–1533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Espi, M.; Koppe, L.; Fouque, D.; Thaunat, O. Chronic Kidney Disease-Associated Immune Dysfunctions: Impact of Protein-Bound Uremic Retention Solutes on Immune Cells. Toxins 2020, 12, 300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, T.H.; Chen, J.J.; Wu, C.Y.; Lin, T.Y.; Hung, S.C.; Yang, H.Y. Immunosenescence, gut dysbiosis, and chronic kidney disease: Interplay and implications for clinical management. Biomed. J. 2024, 47, 100638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wengner, A.M.; Pitchford, S.C.; Furze, R.C.; Rankin, S.M. The coordinated action of G-CSF and ELR + CXC chemokines in neutrophil mobilization during acute inflammation. Blood 2008, 111, 42–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Finfer, S.; Venkatesh, B.; Hotchkiss, R.S.; Sasson, S.C. Lymphopenia in sepsis—An acquired immunodeficiency? Immunol. Cell Biol. 2022, 101, 535–544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patel, A.A.; Ginhoux, F.; Yona, S. Monocytes, macrophages, dendritic cells and neutrophils: An update on lifespan kinetics in health and disease. Immunology 2021, 163, 250–261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, M.; Silva-Sanchez, A.; Randall, T.D.; Meza-Perez, S. Specialized immune responses in the peritoneal cavity and omentum. J. Leukoc. Biol. 2021, 109, 717–729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Korniluk, A.; Koper-Lenkiewicz, O.M.; Kamińska, J.; Kemona, H.; Dymicka-Piekarska, V. Mean Platelet Volume (MPV): New Perspectives for an Old Marker in the Course and Prognosis of Inflammatory Conditions. Mediat. Inflamm. 2019, 2019, 9213074. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ulu, S.; Asik, G.; Acay, A.; Ahsen, A.; Altug, A.; Yaman, G.; Yüksel, Ş. Is Mean Platelet Volume a Possible Marker in Acute Peritonitis? Electron. J. Gen. Med. 2015, 12, 13–17. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.Q.; Tian, X.K.; Wang, L.; Tang, W. Effect of platelet indices on mortality and comorbidity in peritoneal dialysis: A cohort study. BMC Nephrol. 2024, 25, 278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baaten, C.C.; Sternkopf, M.; Henning, T.; Marx, N.; Jankowski, J.; Noels, H. Platelet Function in CKD: A Systematic Review and Meta-Analysis. J. Am. Soc. Nephrol. 2021, 32, 1583–1598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guedes, M.; Andrews, C.; Zhao, J.; Atkins, G.B.; Barash, I.; Bash, L.D.; Coyle, C.R.; Ke, X.; Ramey, D.R.; Johnson, D.W.; et al. Multinational Real-World Practice Patterns in the Use of Antithrombotic Therapy Among Patients on Hemodialysis and Peritoneal Dialysis. Kidney Med. 2026, 8, 101211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hardy, M.; Lessire, S.; Kasikci, S.; Baudar, J.; Guldenpfennig, M.; Collard, A.; Dogné, J.M.; Chatelain, B.; Jacqmin, H.; Lecompte, T.; et al. Effects of Time-Interval since Blood Draw and of Anticoagulation on Platelet Testing (Count, Indices and Impedance Aggregometry): A Systematic Study with Blood from Healthy Volunteers. J. Clin. Med. 2020, 9, 2515. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marchi, F.; Pylypiv, N.; Parlanti, A.; Storti, S.; Gaggini, M.; Paradossi, U.; Berti, S.; Vassalle, C. Systemic Immune-Inflammation Index and Systemic Inflammatory Response Index as Predictors of Mortality in ST-Elevation Myocardial Infarction. J. Clin. Med. 2024, 13, 1256. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayama, T.; Ochiai, H.; Ozawa, T.; Miyata, T.; Asako, K.; Fukushima, Y.; Kaneko, K.; Nozawa, K.; Fujii, S.; Misawa, T.; et al. High systemic inflammation response index (SIRI) level as a prognostic factor for colorectal cancer patients after curative surgery: A single-center retrospective analysis. Sci. Rep. 2025, 15, 1008. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, F.; Xia, Y.; Su, J.; Quan, F.; Zhou, H.; Li, Q.; Feng, Q.; Lin, C.; Wang, D.; Jiang, Z. Neutrophil diversity and function in health and disease. Signal Transduct. Target. Ther. 2024, 9, 343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, P.; He, L.-J.; Huang, C.; Hu, J.; Sun, S. Neutrophil-to-Lymphocyte Ratio and Treatment Failure in Peritoneal Dialysis-Associated Peritonitis. Front. Med. 2021, 8, 699502. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gibyeli Genek, D.; Yeşil, C.; Arslan Yeşil, C.; Terzioğlu Yazıcı, G.C.; Alp, A.; Huddam, B. Clinical outcomes in peritoneal dialysis–related peritonitis: Association with biochemical but not hematologic inflammatory indices. Int. J. Artif. Organs 2026, 49, 765–773. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fung, W.W.-S.; Li, P.K.-T. Recent advances in novel diagnostic testing for peritoneal dialysis-related peritonitis. Kidney Res. Clin. Pract. 2022, 41, 156–164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zalunardo, N.Y.; Rose, C.L.; Ma, I.W.Y.; Altmann, P. Higher serum C-reactive protein predicts short and long-term outcomes in peritoneal dialysis-associated peritonitis. Kidney Int. 2007, 71, 687–692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Htay, H.; Choo, J.C.; Huang, D.H.; Jayaballa, M.; Johnson, D.W.; Koniman, R.; Oei, E.L.; Suai, T.C.; Wu, S.Y.; Foo, M.W. Rapid point-of-care test for diagnosis of peritonitis in peritoneal dialysis patients. Perit. Dial. Int. J. Int. Soc. Perit. Dial. 2024, 44, 413–418. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.