


Abstract
Understanding the genetic architecture of metabolic epilepsies is of paramount importance, both to current clinical practice and for the identification of further research directions. The main goals of our study were to identify the scope of metabolic epilepsies and to investigate their clinical presentation, diagnostic approaches and treatments. The International Classification of Inherited Metabolic Disorders and IEMbase were used as a basis for the identification and classification of metabolic epilepsies. Six hundred metabolic epilepsies have been identified, accounting for as much as 37% of all currently described inherited metabolic diseases (IMD). Epilepsy is a particularly common symptom in disorders of energy metabolism, congenital disorders of glycosylation, neurotransmitter disorders, disorders of the synaptic vesicle cycle and some other IMDs. Seizures in metabolic epilepsies may present variably, and most of these disorders are complex and multisystem. Abnormalities in routine laboratory tests and/or metabolic testing may be identified in 70% of all metabolic epilepsies, but in many cases they are non-specific. In total, 111 metabolic epilepsies (18% of all) have specific treatments that may significantly change health outcomes if diagnosed in time. Although metabolic epilepsies comprise an important and significant group of disorders, their real scope and frequency may have been underestimated.
1. Introduction
Understanding the genetic architecture of metabolic epilepsies is of paramount importance, both to current clinical practice and for the identification of further research directions. Metabolic epilepsy, defined as epilepsy that results directly from an inherited metabolic disorder (IMD) in which seizures are a core symptom of the disorder [1], are at the intersection of the disciplines of biochemical and molecular genetics and epileptology. In the last decade, high-throughput gene-sequencing studies have yielded an abundance of discoveries that change the paradigms in both epilepsy genetics [2] and IMDs [3]. The International Classification of Inherited Metabolic Disorders (ICIMD), which was recently adopted and endorsed by the international metabolic community, expands the definition of IMDs according to the current understanding of molecular and cell biology and encompasses more than 1500 IMDs. This classification includes all conditions where the impairment of biochemical pathways is intrinsic to the disorder‘s pathomechanism, while the presence of a diagnostic metabolic biomarker is no longer a prerequisite [4]. In this ever-growing classification, vastly expanded conventional IMD categories such as congenital disorders of glycosylation can be found, as well as recently defined IMD groups such as congenital disorders of autophagy [5], disorders of metabolite repair/proofreading [6], and disorders of the synaptic vesicle cycle [7]. Metabolic epilepsies belong to various IMD groups [8,9]. A significant number of these diseases have specific treatments that may significantly change health outcomes if diagnosed in time. This treatment not only replaces or complements conventional treatment with antiseizure drugs (ASD), but also targets the pathophysiology of the disorder and other systemic symptoms besides seizures. In recent years, the number of treatable metabolic epilepsies has increased significantly due to major breakthroughs in treatment strategies, elucidation and targeting of diseases’ molecular mechanisms and the application of new methodologies for clinical trials in small populations, which are applicable to rare diseases [8,10].
Although the International League Against Epilepsies (ILAE) Commission for Classification and Terminology states in its Position Paper that “An etiologic diagnosis should be considered from when the patient first presents, and at each step along the diagnostic pathway” [1], there is a lack of any classification of monogenic epilepsies, and ILAE recommendations for genetic testing in epilepsy were developed in the pre-genomic era [11]. The ILAE on-line diagnostic manual only provides information on 59 epilepsy genes and 8 IMDs or IMD groups and does not reflect the real scope of monogenic epilepsies [12]. Meanwhile, more than 1000 human genes have been associated with monogenic disorders that involve epilepsy or seizures and a considerable portion of them (373 genes out of a list of 880 genes (42%) in our previous study) are IMDs [13]. Metabolic epilepsies comprise a significant part of the etiologies in certain groups of epilepsy patients, such as neonatal epilepsy [14], refractory epilepsy [15], status epilepticus [16] and progressive myoclonus epilepsies [17], among others. Besides, although it is generally perceived that metabolic epilepsies account for a very small proportion of all patients with epilepsy [1,18], IMDs are frequently diagnosed through genomic testing in various cohorts of patients with epilepsy, including unselected cohorts of patients with variable epilepsy phenotypes, early-onset epilepsy, progressive myoclonic epilepsy and even adult or elderly patients with epilepsy (Table 1).
Table 1.
Percentage of diagnosed IMDs in various cohorts of epilepsy patients.
The main goals of our study were to identify the scope of metabolic epilepsies ac-cording to the current classification of IMDs (ICIMD), and to investigate the clinical presentation, diagnostic approaches and treatments of these metabolic epilepsies.
2. Materials and Methods
The International Classification of Inherited Metabolic Disorders (ICIMD) and IEMbase were used as a basis for the identification and classification of metabolic epilepsies [4,23]. All IMDs including epilepsy or seizures as a clinical symptom were included in the list. Information on the clinical presentation and diagnostics of every IMD listed in the ICIMD was obtained mainly from the database, Online Mendelian Inheritance in Man (OMIM; https://www.ncbi.nlm.nih.gov/omim (accessed on 10 December 2021) [23], and missing information was supplemented by literature searches. Clinical synopses of metabolic epilepsies are included in the Supplementary Table S1. Information on the treatment of diseases was mostly based on our previous studies [8,24,25] and supplemented by literature searches as required. For the literature search, we used a targeted approach to identify missing information on specific IMD’s clinical presentation, diagnostics and/or treatment. We searched PubMed (http://www.ncbi.nlm.nih.gov/pubmed (accessed on 10 December 2021), restricted searches to English language and publications in peer-reviewed journals, encompassing a period up to December 2021.
The definitions and terms relevant to this study are presented in Table 2.
Table 2.
Terms and definitions.
3. Results
3.1. The Scope of Metabolic Epilepsies
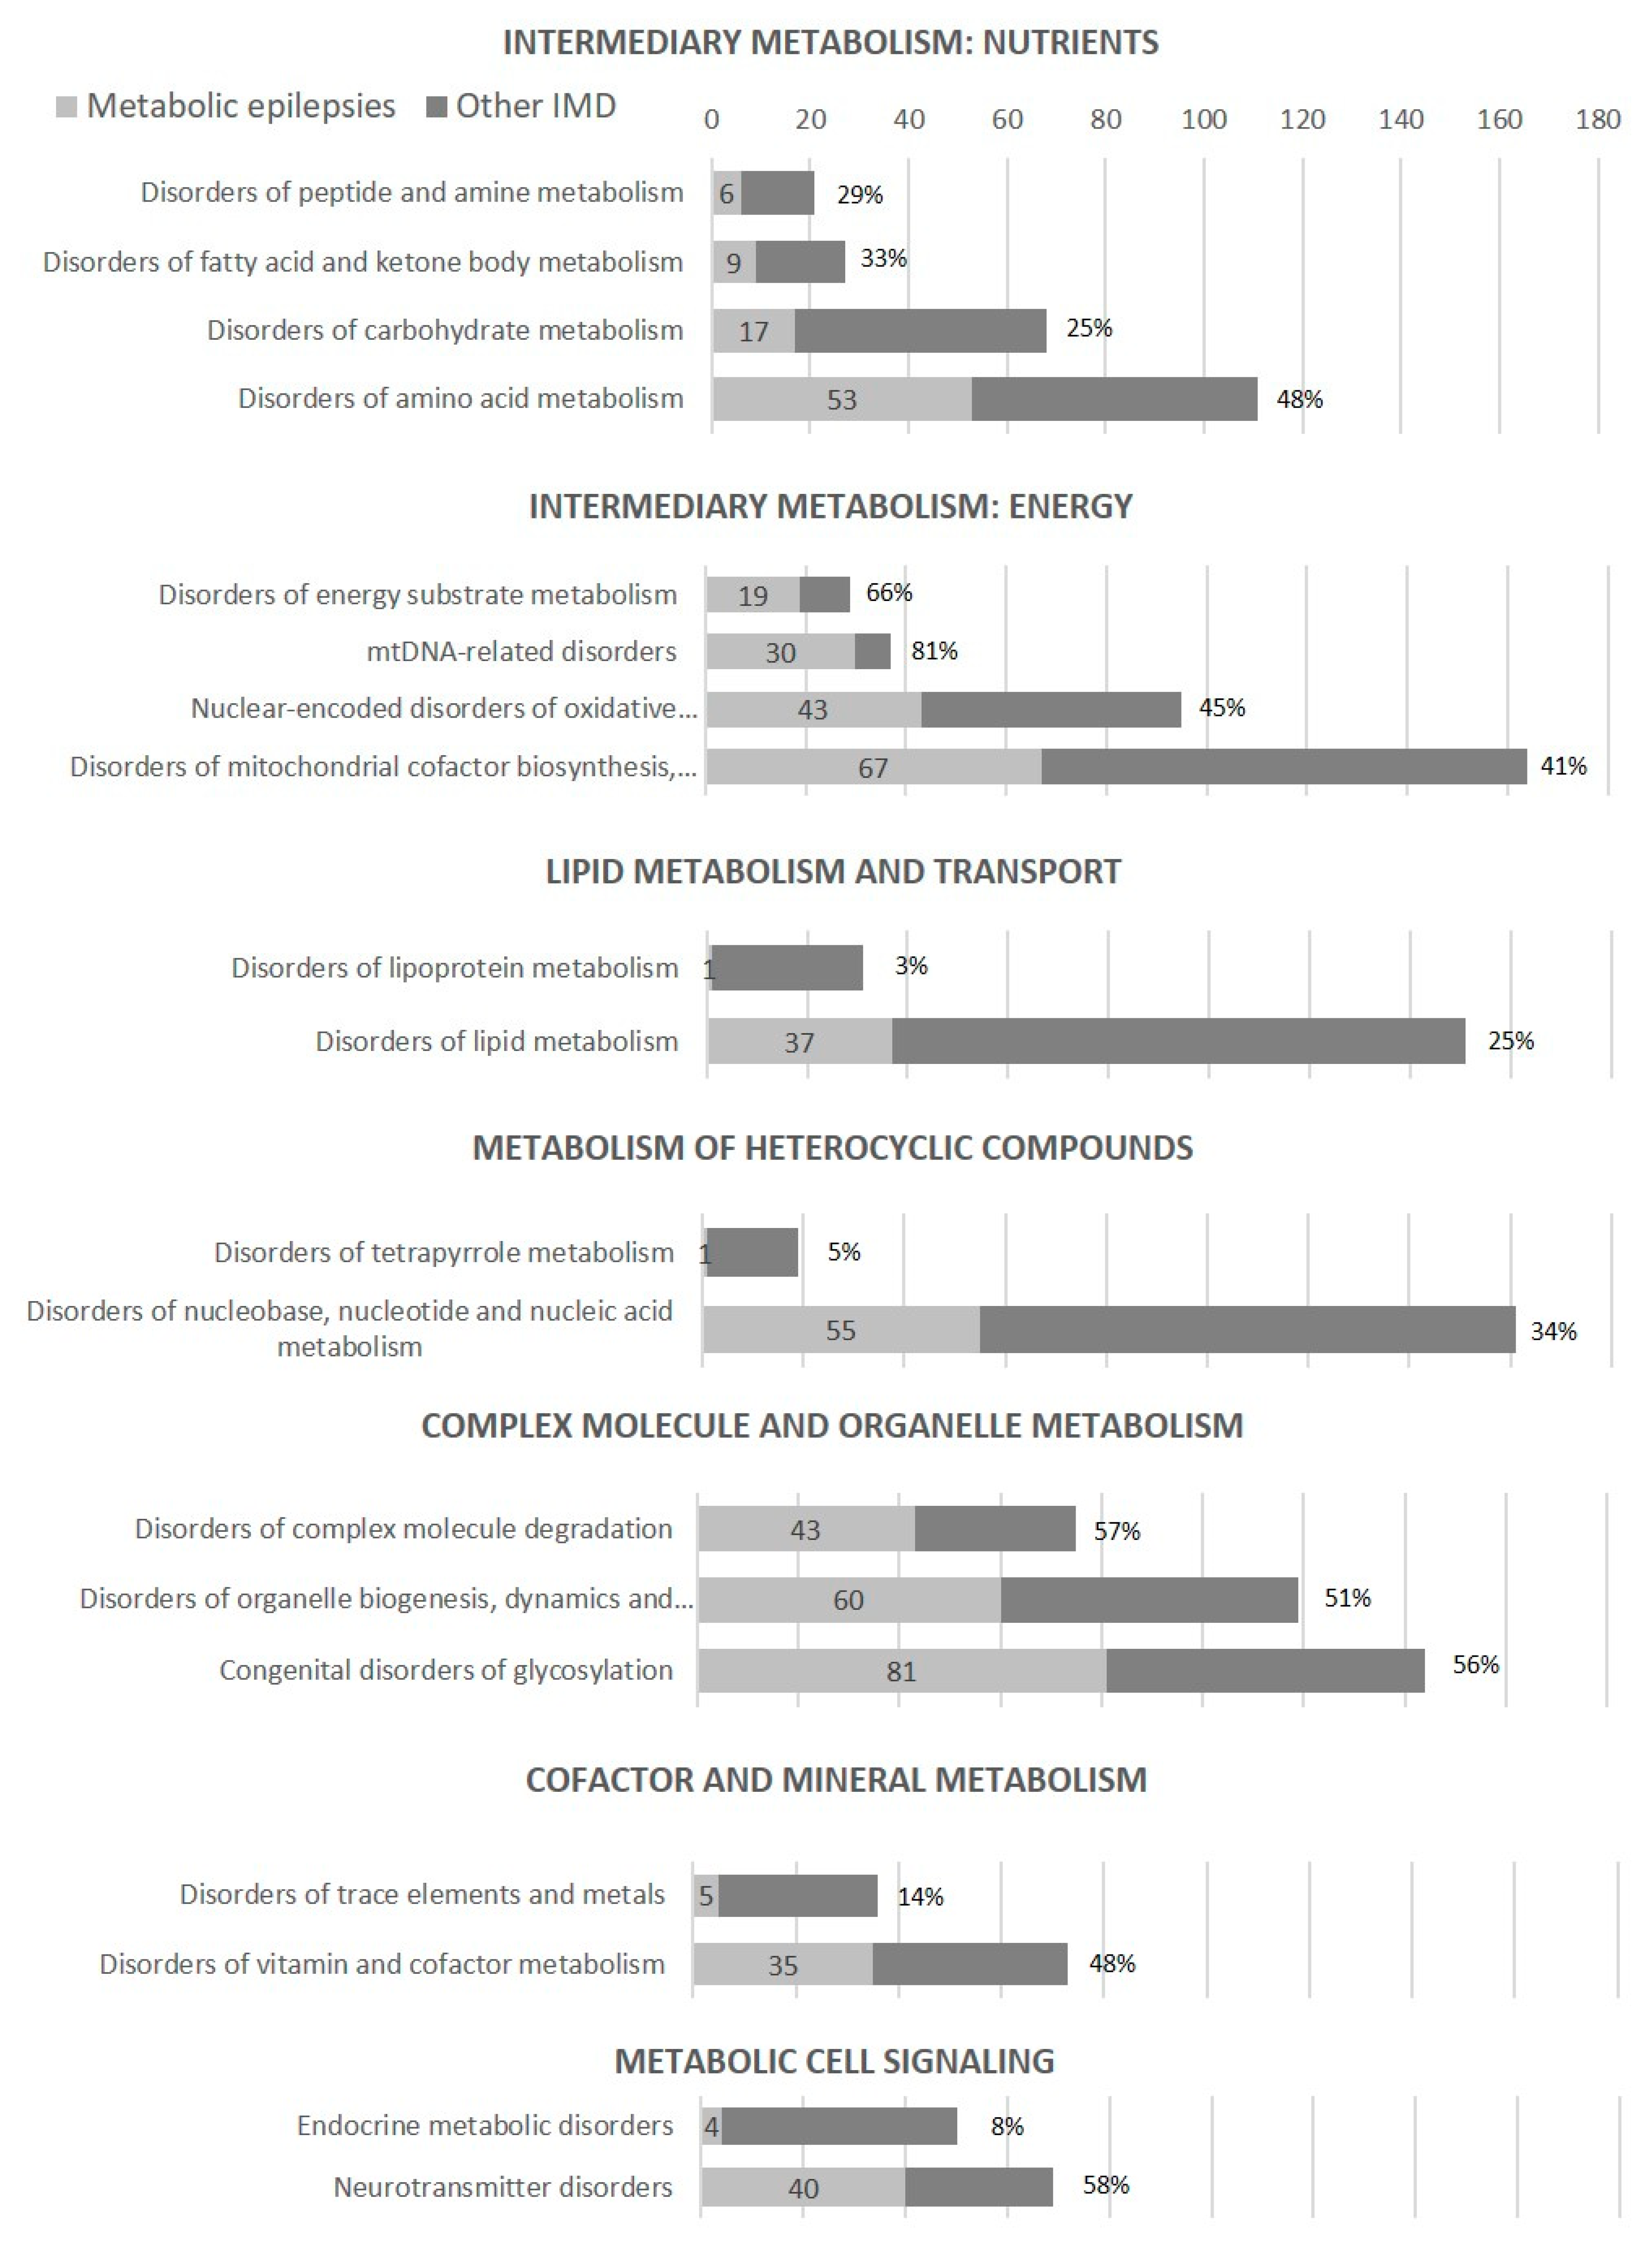
In this study, 600 metabolic epilepsies have been identified, accounting for as much as 37% of all currently described IMDs (1625 IMDs in the ICIMD and IEMbase, as of 10 December 2021), i.e., epilepsy or seizures are common manifestations of IMDs (Table 3, Figure 1). Epilepsy or seizures are particularly common symptoms in some groups of IMDs:
Table 3.
Metabolic epilepsies according to the International Classification of Inherited Metabolic Disorders (ICIMD).
Figure 1.
Number and percentage of metabolic epilepsies in ICIMD groups.
- Energy metabolism defects, especially mtDNA-related disorders (30/37 disorders, 81%) and disorders of energy substrate metabolism (19/29, 66%);
- Some disorders of amino acid metabolism, such as urea cycle disorders and inherited hyperammonemia, organic acidurias and disorders of branched-chain amino acid metabolism (24/33 disorders, 73%) and disorders of glycine and serine metabolism, glutamate/glutamine and aspartate/asparagine metabolism (13/15 disorders, 87%);
- Complex molecule and organelle metabolism defects, including all three groups—congenital disorders of glycosylation (81/144 disorders, 56%), disorders of organelle biogenesis, dynamics and interactions (60/119 disorders, 51%) and disorders of complex molecule degradation (43/75 disorders, 57%);
- Neurotransmitter disorders (40/69 disorders, 58%).
Like other IMDs, the majority of metabolic epilepsies are inherited as autosomal recessive (497 diseases, 83% of all metabolic epilepsies), 68 diseases are autosomal dominant (11% of all metabolic epilepsies), 34 metabolic epilepsies are X-linked (6% of all metabolic epilepsies), and 1 metabolic epilepsy (catalytic phosphatidylinositol 3-kinase subunit α superactivity) is caused by a somatic mutation of PIK3CA (Supplementary Table S1).
3.2. Clinical Presentation of Metabolic Epilepsies
Seizures in metabolic epilepsies may present variably. In some diseases, seizures occur in a subset of patients only (e.g., epilepsy is present in about half of individuals affected with SSADH deficiency [26]); in other cases, epilepsy is a constant symptom (e.g., GABA-transaminase deficiency [27]). The age of presentation can be a diagnostic indication in some metabolic epilepsies [8,28]; however, it must be emphasized that there can be a considerable overlap among age groups, many disorders (e.g., mitochondriopathies) may present at any age and there is a general trend for the expansion of the clinical spectrum of many IMDs towards adolescent or adult-onset phenotypes with improved diagnostics [29,30].
Although seizure semiology can be highly variable, the presence of certain types of seizures such as progressive myoclonic seizures [17], infantile spasms [31], epilepsia partialis continua [8] or refractory myoclonic or tonic seizures in the context of a burst suppression pattern on electroencephalogram (EEG) in the neonatal period [14] should raise the suspicion of metabolic epilepsy. Besides, although metabolic epilepsies are more frequently associated with generalized seizures, focal epilepsy may be a symptom in a number of IMDs, especially those associated with cortical malformations (e.g., peroxisomal disorders or congenital disorders of glycosylation) [32]. Encephalopathy is characteristic of 112 IMDs (19%) that are often classified as developmental and epileptic encephalopathies (DEE) (e.g., early infantile epileptic encephalopathies due to GABRA1, GABRB1, GABRB2 or GABRB3 pathogenic variants; Supplementary Table S1). The effects of treatment with antiseizure drugs (ASD) vary widely; some diseases readily respond to ASD, but at least 91 IMDs (15%) may cause refractory or intractable seizures and status epilepticus. Many disorders of intermediary metabolism present with symptomatic seizures during metabolic crises—at least 40 disorders (7%) may lead to metabolic coma—and persistent seizures may develop as a consequence of these crises.
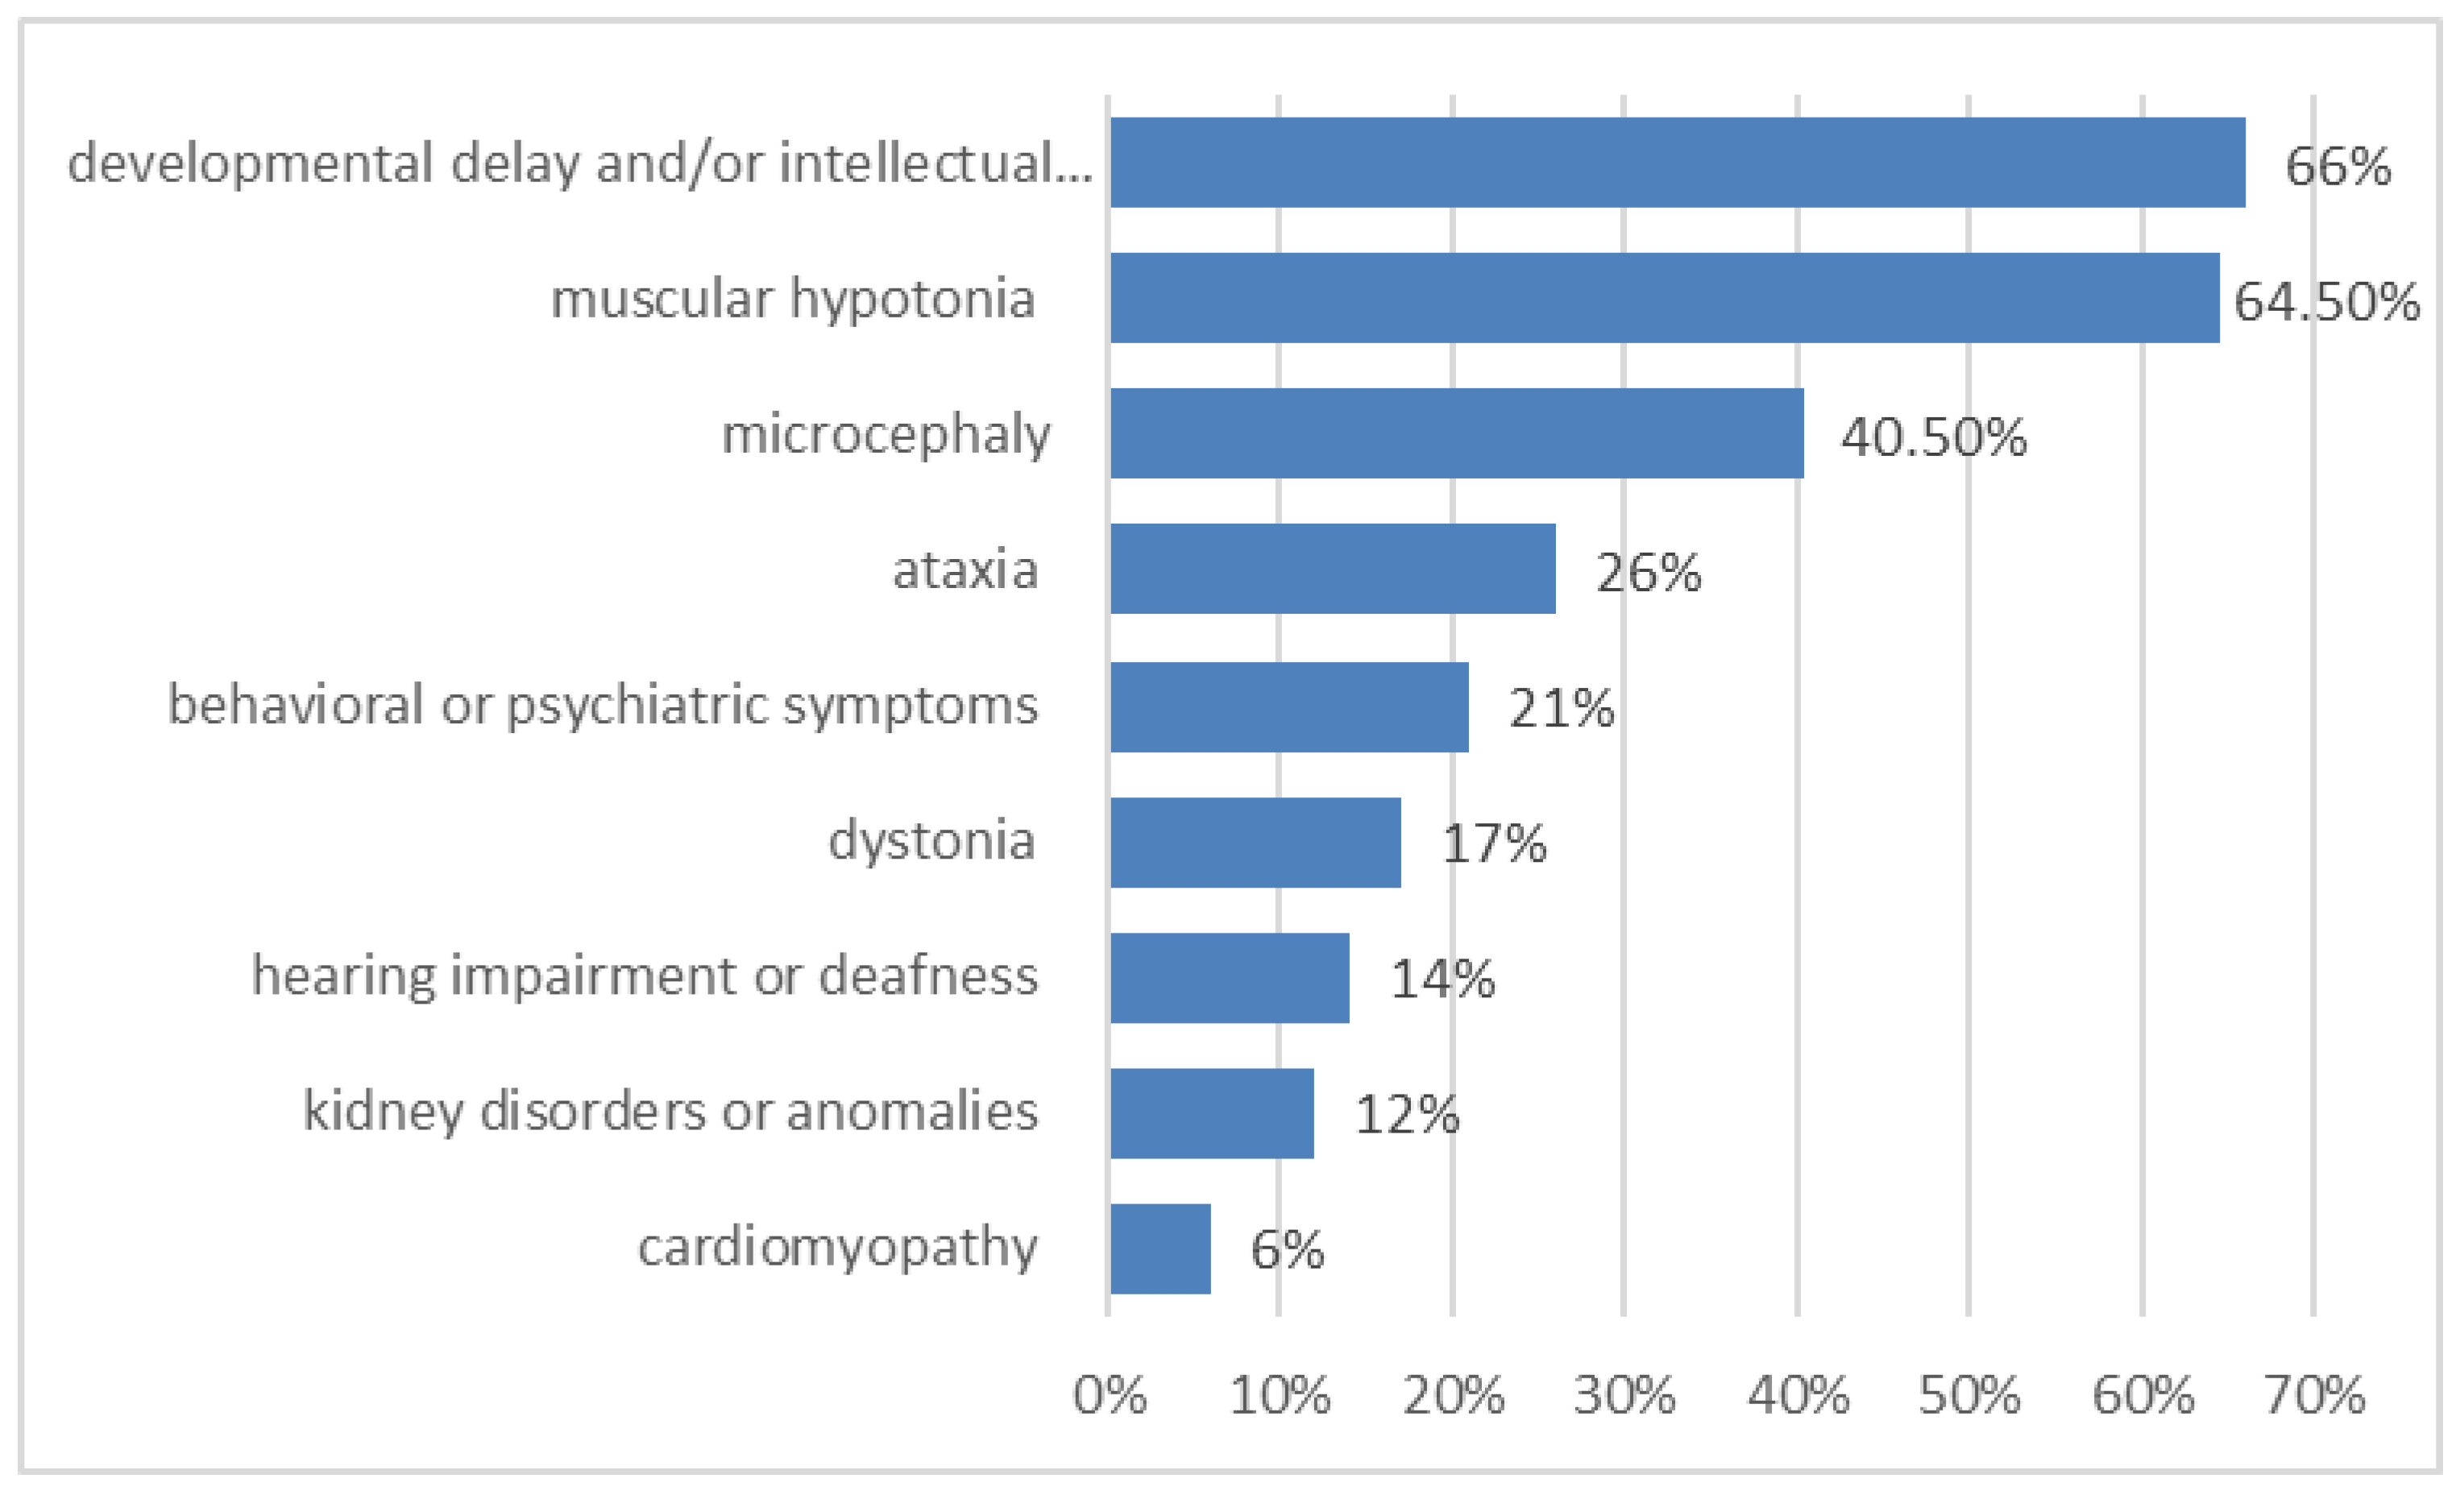
Most of these metabolic epilepsies are complex disorders and encompass not only seizures but also other symptoms, i.e., the presentation is often multisystemic (Figure 2). Epilepsy is usually accompanied by developmental delay and/or intellectual disability (400 metabolic epilepsies, 66% of all metabolic epilepsies) that may develop after a period of normal development (e.g., in neurodegenerative diseases as disorders of glycosaminoglycan degradation). Other frequent symptoms are muscular hypotonia (387 diseases, 64.5% of all metabolic epilepsies), microcephaly (40.5% of all metabolic epilepsies) and ataxia (155 disorders, 26% of all metabolic epilepsies). Behavioral or psychiatric symptoms occur in at least 126 metabolic epilepsies (21% of all metabolic epilepsies), and dystonia occurs in 100 (17%) of all metabolic epilepsies. Other systems and organs may also be affected, e.g., cardiomyopathy is a symptom of 35 metabolic epilepsies (6% of all metabolic epilepsies), kidney disorders or anomalies are a symptom of 74 metabolic epilepsies (12% of all metabolic epilepsies), hearing impairment or deafness are a symptom of 84 (14% of all metabolic epilepsies). Clinical synopses of metabolic epilepsies are presented in Supplementary Table S1.
Figure 2.
Some of the most frequent accompanying symptoms in metabolic epilepsies (in %).
3.3. Diagnostics of Metabolic Epilepsies
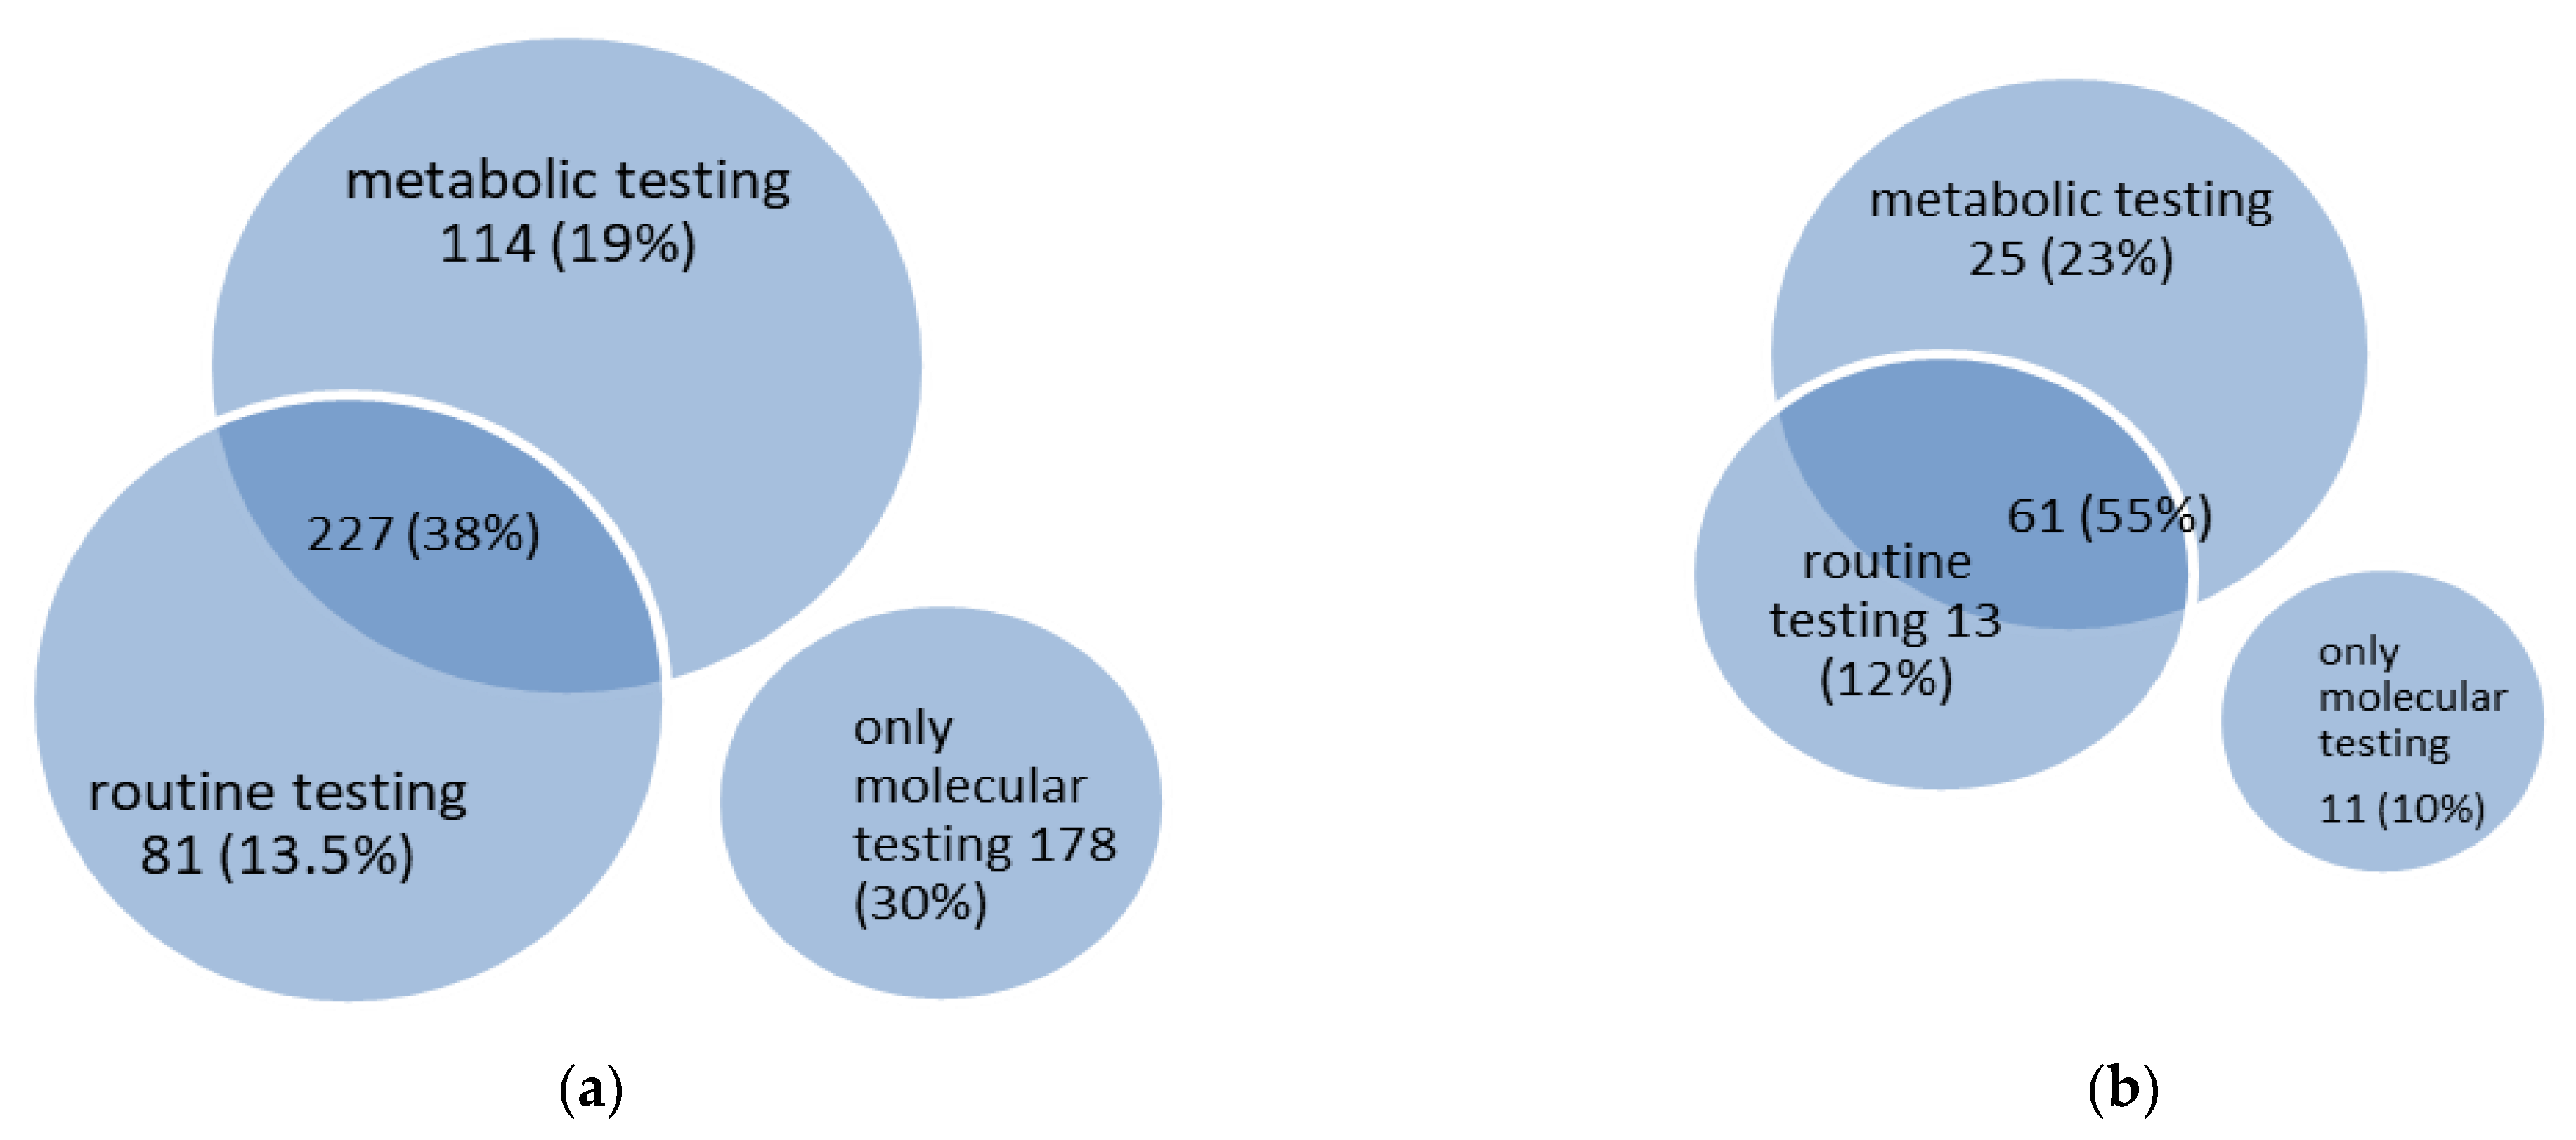
In 422 diseases (70% of all metabolic epilepsies), abnormalities can be identified by using routine laboratory tests and/or metabolic testing (Figure 3). Metabolic testing includes a wide range of investigations from conventional tests available in almost every metabolic laboratory (e.g., plasma amino acids, acylcarnitines or urinary organic acids) to highly-specialized (e.g., analysis of plasma sphingolipids for the diagnosis of sphingolipidoses) or invasive investigations (e.g., biopsies of various tissues). In some cases, these abnormalities are not disease-specific (e.g., an increase in plasma alanine concentration in patients with hyperlactacidemia). Abnormalities identified by routine laboratory tests include changes in blood ammonia, acid-base, ketones, lactate or glucose concentrations, changes in complete blood count, among others. One hundred and fourteen diseases (19% of all metabolic epilepsies) are characterized by abnormalities found in metabolic testing only, and 227 diseases (38% of all metabolic epilepsies) are characterized by abnormalities found in both routine and metabolic testing; hence, more or less specific metabolic biomarkers may be identified in 341 metabolic epilepsies (57% of all metabolic epilepsies). In 81 diseases (13.5% of all metabolic epilepsies), only abnormalities in routine laboratory tests are detected.
Figure 3.
Venn diagram of diagnostic testing in 600 metabolic epilepsies (a) and 111 treatable metabolic epilepsies (b).
Of the 110 treatable metabolic epilepsies (Section 3.4. Treatable metabolic epilepsies, below), 61 diseases (55% of treatable metabolic epilepsies) are characterized by changes in both routine and metabolic studies, and 25 diseases (23% of treatable metabolic epilepsies) are characterized by abnormalities in metabolic testing only; thus, more or less specific metabolic biomarkers are characteristic of 86 treatable metabolic epilepsies (78% of treatable metabolic epilepsies) (Figure 3). Abnormalities in routine laboratory tests only are identified in 13 treatable metabolic epilepsies (12% of treatable metabolic epilepsies), and 11 treatable metabolic epilepsies (10% of treatable metabolic epilepsies) do not present any changes in routine laboratory or metabolic tests and can only be diagnosed through molecular genetic testing.
3.4. Treatable Metabolic Epilepsies
In this study, 111 metabolic epilepsies (18% of all) are treatable. These diseases have specific treatments that target the pathophysiology of the disease and usually affect not only seizures but also other neurologic and/or systemic symptoms (Table 4). The majority of treatable metabolic epilepsies are amenable to nutritional therapy (65 IMDs, 59% of all treatable metabolic epilepsies), followed by pharmacological therapy (37 IMDs, 34%), vitamin and trace element substitution (36 IMDs, 32%), hemodialysis/peritoneal dialysis (13 IMDs, 12%), solid organ transplantation (12 IMDs, 11%), hematopoietic stem cell transplantation (5 IMDs, 4.5%), gene-based therapy (3 IMDs, 3%), and enzyme replacement therapy (2 IMDs, 2%). In some treatable metabolic epilepsies, more than one treatment strategy is applied. Relatively simple, inexpensive and (often) quite effective nutritional and vitamin/trace element substitution therapies [33] are effective in 59% and 32% of treatable metabolic epilepsies in this study.
Table 4.
Treatable metabolic epilepsies.
The majority of treatable metabolic epilepsies are related to the following three groups of IMDs: defects of intermediary metabolism of nutrients and energy, and cofactor/mineral metabolism defects. Nutritional and vitamin/trace element substitution therapies are mostly applied in these diseases. The list of treatable metabolic epilepsies also includes six congenital disorders of glycosylation (which are amenable to various treatment strategies including nutritional, pharmacological and vitamin/trace element substitution) and seven lysosomal storage diseases that are mostly amenable to the more sophisticated stem cell or gene-based therapies (defects of complex molecule and organelle metabolism). Finally, defects of metabolic cell signaling encompass ten treatable metabolic epilepsies that are mostly amenable to pharmacological treatments, e.g., memantine and/or intravenous immunoglobulins for ionotropic glutamate receptor NMDA-type defects [24].
4. Discussion
Although it is commonly thought that metabolic epilepsies account for only a small fraction of all monogenic epilepsies and of all patients with epilepsy, the real scope and frequency of metabolic epilepsies remain underestimated. As many as 600 metabolic epilepsies have been identified in this study, which represent 37% of all currently known IMDs. The number of metabolic epilepsies is likely to increase still further; as human metabolic pathways involve more than 3200 genes, many potential future IMDs remain to be discovered [34]. Recently, several novel categories of IMDs such as congenital disorders of autophagy, disorders of the synaptic vesicle and disorders of metabolite repair/proofreading have been defined. These groups of IMDs may also expand in the future, e.g., the ICIMD currently includes 12 congenital disorders of autophagy [35], while a database of autophagy-associated human genes currently includes 679 genes, http://www.tanpaku.org/autophagy (accessed on 10 December 2020); 163 of these genes are associated with monogenic diseases, while 65 diseases (40%, 65/163) may present with epilepsy or seizures, including many of the so-called mTORopathies where defects of autophagy and mitophagy comprise some of the main pathogenetic mechanisms [36,37]. Autophagy is a fundamental and conserved catabolic pathway that is particularly important to post-mitotic and metabolically active cells such as neurons; hence, the prominent involvement of the central nervous system, including seizures, is a characteristic of congenital disorders of autophagy [38].
The identification and characterization of the genetic landscape of metabolic epilepsies is highly important for several reasons: this knowledge can help achieve the “triple aim” of healthcare organizations, i.e., improvement of patient experiences with care, improvement of health outcomes, and better management of health system impacts through better organization of healthcare services (including diagnostics, treatment and multidisciplinary care) [39]. In addition, research into the molecular mechanisms of metabolic epilepsies may pave the way towards new areas of research and ultimately lead to the discovery of new treatments in both rare and common epilepsies [10,40].
The first steps towards further progress represent well-established principles of effective diagnostics. The establishment of the precise etiology is highly beneficial to patients, families and societies: this not only allows for specific, prognosis-altering treatments, but also has implications for prognosis, a family’s reproductive and life plans, provides guidance for further patient management, allows for engagement with peer-support groups, and halts the diagnostic odyssey, including invasive and expensive testing. Besides, it may provide the means for further investigation of the disease’s molecular mechanisms and the inclusion of patients into clinical trials [41]. Metabolic epilepsies are at the intersection of the disciplines of epileptology, IMDs and genetics, and the referring physician will most often be a metabolic pediatrician/internist, neurologist/epileptologist or geneticist. Conventional investigations used for the diagnosis of epilepsy by epileptologists or neurologists (such as seizure semiology, electrophysiological, or imaging investigations) only rarely provide diagnostic clues for the etiological diagnosis of IMD [13]. Clinical “red flags” for IMD include parental consanguinity or family history for a similar condition, multisystem involvement, abnormalities in routine laboratory testing, fluctuating course of illness, seizures related to fasting, food intake or catabolic stress, unexplained neonatal seizures, refractory seizures or myoclonic seizures, encephalopathic episodes, and neuro-regression [8,42,43]. At least two thirds of metabolic epilepsies result in developmental delay and/or intellectual disability, which is much more common than in the general population of patients with epilepsy (25% of all children with epilepsy experience neurocognitive deficits [44]). However, the whole range of symptoms and signs in metabolic epilepsies is highly diverse, and the symptoms are frequently non-specific and overlapping with non-IMDs (Supplementary Table S1). Therefore, IMDs may be diagnosed “unexpectedly” in patients with previously unsuspected IMD [45,46], whereas other genetic or non-genetic diseases can be identified in patients suspected of suffering from IMDs [47]. Moreover, 18% of all metabolic epilepsies are treatable, but early diagnosis is a mandatory prerequisite for successful treatment, and the whole clinical spectrum of the disease may still not be fully developed at the time of diagnosis.
Metabolic epilepsies are diagnosed through metabolic and/or genetic testing methods. Unfortunately, there is no established “gold standard” for one or another testing modality in every clinical situation, and both methods have their own pros and cons. In some cases, metabolic testing has higher specificity and sensitivity and shorter turnaround time, but only non-specific metabolic biomarkers are identified in many IMDs, with the further need for diagnostic confirmation through genetic testing. The non-specificity of metabolic biomarkers may even be misleading (e.g., patients with pyridoxine-dependent epilepsy due to PLPBP gene mutations were misdiagnosed with mitochondrial or glycine encephalopathies due to non-specific abnormalities in metabolic testing) [48]. Another drawback of metabolic testing is the need for a diverse spectrum of targeted biochemical assays that analyze a limited number of metabolites each; some of these tests are very rare, highly-specialized and have limited availability [49]. Indeed, when only conventional, more widely available metabolic testing is used for IMD diagnostics, diagnostic yields are usually very low; e.g., the diagnostic yield in a neonatal intensive care unit (190 neonates tested) was only 5.6% [50], even though many IMDs that are not diagnosed through conventional metabolic testing may present in the neonatal period [14]. Similarly, the diagnostic yield of metabolic testing in epileptic encephalopathies (110 patients tested) was only 7% [51]. Some recently developed metabolomic methods provide opportunities for wider and untargeted diagnostics; however, their application in clinical practice is still limited [49,52]. In recent years, genomic testing is replacing single-gene sequencing in clinical practice and provides opportunities for more or less untargeted diagnostics, especially in patients with non-specific symptoms where the probability of diagnosing IMD is lower. However, the specificity and sensitivity may be lower and the turnaround time may be longer for genetic testing, which may result in missed diagnoses [53]. Moreover, there is great variability in genomic testing and in many cases gene panels are used instead of exome or genome sequencing to avoid incidental findings, variants of unknown significance and the burden of the interpretative workload for identified variants. Unfortunately, gene panels differ greatly in both the number and composition of genes, even when used for similar groups of patients with epilepsy, with a high chance of missing diagnoses, especially in non-specific phenotypes with a vast genetic architecture, such as epilepsy [13,54]. Indeed, bearing in mind the wide genetic heterogeneity of metabolic epilepsies that currently encompass at least 600 nosologies, and the heterogeneity and non-specificity of the clinical presentation, omics methods may provide the optimal way to identify the diagnosis in every patient. “Multi-omics” may be the best strategy for the diagnostics of metabolic epilepsies, especially in unsolved cases; however, the price and availability of such testing are still prohibitive.
In day-to-day clinical practice, the choice of diagnostic strategy may depend on several other factors. (1) The availability of highly-specialized clinical and laboratory expertise and diagnostic methods within the healthcare system. Metabolic tests are usually performed in specialized metabolic-testing laboratories and their availability, especially for less frequently used highly-specialized metabolic tests, varies across countries and regions. Metabolic physicians usually have direct contact with metabolic laboratories, while other professionals may not. Besides, there is a lack of adult metabolic specialists in many countries, whereas in some countries the specialty of metabolician does not exist at all [55]. Genetic testing is performed in both clinical and commercial laboratories and is usually more widely available. (2) The clinical presentation and age of a given patient and index of suspicion for IMDs; e.g., metabolicians are more likely to diagnose inherited disorders of intermediary metabolism, epileptologists are more likely to diagnose neurotransmitter disorders, and geneticists are more likely to diagnose syndromic metabolic epilepsies accompanied by intellectual disability and/or malformations. Importantly, the attitudes of different professionals towards the diagnostics of IMD may vary. For example, a recent study found that epileptologists caring for mostly adult patients were significantly less likely to order genetic testing than were physicians caring for mostly pediatric patients (33% vs. 80%) [56]. (3) The acuity and treatability of illness, where timely diagnosis is essential. Many IMDs, especially those of intermediary metabolism, may present with metabolic crises, and many metabolic epilepsies evoke refractory seizures or status epilepticus [15,16]. In many cases, the turn-around time of metabolic testing, especially for conventional metabolic tests, is better; however, accelerated protocols for genomic testing in the intensive care setting (e.g., genome sequencing) are becoming more widely available [57]. (4) The cost-effectiveness and reimbursement of diagnostic tests. In some healthcare systems, even those of developed countries, genomic testing may be underutilized due to limited reimbursement or perceived costliness despite the established fact that comprehensive and more or less untargeted testing modalities, such as exome sequencing, eventually provide overall cost-effectiveness in larger patient populations [58,59,60].
The development of specific treatments for metabolic epilepsies has prospered in recent years. Potentially prognosis-altering specific treatments that are personalized and targeted to the disease pathophysiological mechanisms are becoming available for an increasing number of metabolic epilepsies. In many cases the treatment consists of relatively simple, inexpensive and (often) quite effective nutritional and vitamin/trace element substitution therapies [33] that comprised 59% and 32% of available specific treatments for metabolic epilepsies in this study. Unfortunately, this success has not been accompanied by similar success in the development of therapies for common epilepsies. Despite the advent of many ASDs over the past 50 years and decades of research into the neurobiology of epilepsy, ASDs remain ineffective in 30 to 40% of epilepsy patients and this proportion has remained essentially unchanged over the years [61]. The development of currently used ASDs is mostly based on ictogenesis models, targets either ion channels or neurotransmitter receptors but not epileptogenesis processes, and does not have disease-modifying properties [62,63]. Indeed, the concept of epilepsy as exclusively a channelopathy that has prevailed for many decades may preclude further progress in the study of epileptogenesis [61,64]. Deeper insights into the molecular mechanisms of metabolic epilepsies may pave the way towards novel or more personalized approaches of epileptogenesis-targeted treatments in both rare and common multifactorial epilepsies. The main groups of metabolic epilepsies identified in this study, including defects of energy metabolism, defects of complex molecule and organelle metabolism, and neurotransmitter disorders, may provide insights into future directions for investigation. As metabolic disturbances play a highly important role in epileptogenesis, various metabolic-targeting models have been developed recently for these purposes, including those for the investigation of various bioenergetic processes [61,65,66], mitochondrial functions [67], autophagy [68] and lipid metabolism [69], among others. As autophagy and mitophagy impairments are implicated in the epileptogenesis mechanisms downstream of mTOR hyperactivation in mTORopathies and malformations of cortical development, these processes provide promising novel therapeutic targets [36,37].
Study Limitations
Although already quite extensive, this study presents an overview of metabolic epilepsies as of 2022 and is based on the recently-established ICIMD classification, which has been widely endorsed by the IMD community. Therefore, IMDs that are currently unacknowledged in the ICIMD nosology or entirely novel groups of IMDs may not be represented in this list of metabolic epilepsies. Indeed, several novel IMD groups have emerged in recent years (e.g., congenital disorders of autophagy and disorders of the synaptic vesicle) and we foresee the further appearance of such novel groups as we gain deeper insights into the pathomechanisms of many rare and common epilepsies. Constant revision and improvement are intrinsic to the ICIMD and we encourage further studies and revisions in the field of metabolic epilepsies in the coming years.
5. Conclusions
Characterization of the genetic architecture of metabolic epilepsies is of paramount importance, both to current clinical practice and for the identification of further research directions.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/genes13030508/s1, Table S1: Metabolic epilepsies according to the ICIMD.
Author Contributions
Conceptualization, B.T., C.R.F., C.D.M.v.K.; methodology, B.T., C.R.F., C.D.M.v.K.; investigation, B.T., C.R.F., C.D.M.v.K.; data curation, B.T.; writing—original draft preparation, B.T.; writing—review and editing, B.T., C.R.F., C.D.M.v.K. All authors have read and agreed to the published version of the manuscript.
Funding
This work was financially supported by the European Reference Network on hereditary metabolic disorders (MetabERN). This ERN is co-funded by the European Union with-in the framework of the Third Health Program “ERN-2016—Framework Partnership Agreement 2017–2021”.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Acknowledgments
This work was supported by the European Reference Network on hereditary metabolic disorders (MetabERN).
Conflicts of Interest
The authors declare no conflict of interest.
References
- Scheffer, I.E.; Berkovic, S.; Capovilla, G.; Connolly, M.B.; French, J.; Guilhoto, L.; Hirsch, E.; Jain, S.; Mathern, G.W.; Moshé, S.L.; et al. ILAE classification of the epilepsies: Position paper of the ILAE Commission for Classification and Terminology. Epilepsia 2017, 58, 512–521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thomas, R.H.; Berkovic, S.F. The hidden genetics of epilepsy—A clinically important new paradigm. Nat. Rev. Neurol. 2014, 10, 283–292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morava, E.; Rahman, S.; Peters, V.; Baumgartner, M.R.; Patterson, M.; Zschocke, J. Quo vadis: The re-definition of “inborn metabolic diseases”. J. Inherit. Metab. Dis. 2015, 38, 1003–1006. [Google Scholar] [CrossRef] [Scilit]
- Ferreira, C.R.; Rahman, S.; Keller, M.; Zschocke, J. ICIMD Advisory Group. An international classification of inherited metabolic disorders (ICIMD). J. Inherit. Metab. Dis. 2021, 44, 164–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ebrahimi-Fakhari, D.; Saffari, A.; Wahlster, L.; Lu, J.; Byrne, S.; Hoffmann, G.F.; Jungbluth, H.; Sahin, M. Congenital disorders of autophagy: An emerging novel class of inborn errors of neuro-metabolism. Brain 2016, 139 Pt 2, 317–337. [Google Scholar] [CrossRef] [Scilit]
- Veiga-da-Cunha, M.; Van Schaftingen, E.; Bommer, G.T. Inborn errors of metabolite repair. J. Inherit. Metab. Dis. 2020, 43, 14–24. [Google Scholar] [CrossRef] [Scilit]
- Tristán-Noguero, A.; García-Cazorla, À. Synaptic metabolism: A new approach to inborn errors of neurotransmission. J. Inherit. Metab. Dis. 2018, 41, 1065–1075. [Google Scholar] [CrossRef] [Scilit]
- Van Karnebeek, C.D.M.; Sayson, B.; Lee, J.J.Y.; Tseng, L.A.; Blau, N.; Horvath, G.A.; Ferreira, C.R. Metabolic Evaluation of Epilepsy: A Diagnostic Algorithm with Focus on Treatable Conditions. Front. Neurol. 2018, 9, 1016. [Google Scholar] [CrossRef] [Scilit]
- Tumienė, B.; Peterlin, B.; Maver, A.; Utkus, A. Contemporary scope of inborn errors of metabolism involving epilepsy or seizures. Metab. Brain Dis. 2018, 33, 1781–1786. [Google Scholar] [CrossRef] [Scilit]
- Stockler-Ipsiroglu, S.; Potter, B.K.; Yuskiv, N.; Tingley, K.; Patterson, M.; van Karnebeek, C. Developments in evidence creation for treatments of inborn errors of metabolism. J. Inherit. Metab. Dis. 2021, 44, 88–98. [Google Scholar] [CrossRef] [Scilit]
- Ottman, R.; Hirose, S.; Jain, S.; Lerche, H.; Lopes-Cendes, I.; Noebels, J.L.; Serratosa, J.; Zara, F.; Scheffer, I.E. Genetic testing in the epilepsies--report of the ILAE Genetics Commission. Epilepsia 2010, 51, 655–670. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- International League against Epilepsies, Diagnostic Manual of the Epilepsies. Available online: https://www.epilepsydiagnosis.org/ (accessed on 10 December 2021).
- Tumienė, B.; Maver, A.; Writzl, K.; Hodžić, A.; Čuturilo, G.; Kuzmanić-Šamija, R.; Čulić, V.; Peterlin, B. Diagnostic exome sequencing of syndromic epilepsy patients in clinical practice. Clin. Genet. 2018, 93, 1057–1062. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brimble, E.; Ruzhnikov, M.R.Z. Metabolic Disorders Presenting with Seizures in the Neonatal Period. Semin. Neurol. 2020, 40, 219–235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhatnagar, M.; Shorvon, S. Genetic mutations associated with status epilepticus. Epilepsy Behav. 2015, 49, 104–110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guerrini, R.; Parrini, E.; Marini, C.; Mei, D. What is the role of next generation sequencing in status epilepticus? Epilepsy Behav. 2019, 101 Pt B, 106373. [Google Scholar] [CrossRef] [Scilit]
- Canafoglia, L.; Franceschetti, S.; Gambardella, A.; Striano, P.; Giallonardo, A.T.; Tinuper, P.; Di Bonaventura, C.; Michelucci, R.; Ferlazzo, E.; Granata, T.; et al. Progressive Myoclonus Epilepsies: Diagnostic Yield With Next-Generation Sequencing in Previously Unsolved Cases. Neurol. Genet. 2021, 7, e641. [Google Scholar] [CrossRef] [Scilit]
- Perucca, P.; Bahlo, M.; Berkovic, S.F. The Genetics of Epilepsy. Annu Rev. Genom. Hum. Genet. 2020, 21, 205–230. [Google Scholar] [CrossRef] [Scilit]
- Costain, G.; Cordeiro, D.; Matviychuk, D.; Mercimek-Andrews, S. Clinical Application of Targeted Next-Generation Sequencing Panels and Whole Exome Sequencing in Childhood Epilepsy. Neuroscience 2019, 418, 291–310. [Google Scholar] [CrossRef] [Scilit]
- Helbig, K.L.; Farwell Hagman, K.D.; Shinde, D.N.; Mroske, C.; Powis, Z.; Li, S.; Tang, S.; Helbig, I. Diagnostic exome sequencing provides a molecular diagnosis for a significant proportion of patients with epilepsy. Genet. Med. 2016, 18, 898–905. [Google Scholar] [CrossRef] [Scilit]
- Demos, M.; Guella, I.; DeGuzman, C.; McKenzie, M.B.; Buerki, S.E.; Evans, D.M.; Toyota, E.B.; Boelman, C.; Huh, L.L.; Datta, A.; et al. Diagnostic Yield and Treatment Impact of Targeted Exome Sequencing in Early-Onset Epilepsy. Front. Neurol. 2019, 10, 434. [Google Scholar] [CrossRef] [Scilit]
- Zacher, P.; Mayer, T.; Brandhoff, F.; Bartolomaeus, T.; Le Duc, D.; Finzel, M.; Heinze, A.; Horn, S.; Klöckner, C.; Körber, G.; et al. The genetic landscape of intellectual disability and epilepsy in adults and the elderly: A systematic genetic work-up of 150 individuals. Genet. Med. 2021, 23, 1492–1497. [Google Scholar] [CrossRef] [Scilit]
- Online Mendelian Inheritance in Man (OMIM). Available online: https://www.ncbi.nlm.nih.gov/omim (accessed on 10 December 2021).
- Hoytema van Konijnenburg, E.M.M.; Wortmann, S.B.; Koelewijn, M.J.; Tseng, L.A.; Houben, R.; Stöckler-Ipsiroglu, S.; Ferreira, C.R.; van Karnebeek, C.D.M. Treatable inherited metabolic disorders causing intellectual disability: 2021 review and digital app. Orphanet. J. Rare Dis. 2021, 16, 170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Warmerdam, H.A.G.; Termeulen-Ferreira, E.A.; Tseng, L.A.; Lee, J.Y.; van Eeghen, A.M.; Ferreira, C.R.; van Karnebeek, C.D.M. A Scoping Review of Inborn Errors of Metabolism Causing Progressive Intellectual and Neurologic Deterioration (PIND). Front. Neurol. 2020, 10, 1369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pearl, P.L.; DiBacco, M.L.; Papadelis, C.; Opladen, T.; Hanson, E.; Roullet, J.B.; Gibson, K.M. Succinic Semialdehyde Dehydrogenase Deficiency: Review of the Natural History Study. J. Child. Neurol. 2021, 36, 1153–1161. [Google Scholar] [CrossRef] [Scilit]
- Koenig, M.K.; Hodgeman, R.; Riviello, J.J.; Chung, W.; Bain, J.; Chiriboga, C.A.; Ichikawa, K.; Osaka, H.; Tsuji, M.; Gibson, K.M.; et al. Phenotype of GABA-transaminase deficiency. Neurology 2017, 88, 1919–1924. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, S.; Prasad, A.N. Inborn Errors of Metabolism and Epilepsy: Current Understanding, Diagnosis, and Treatment Approaches. Int. J. Mol. Sci. 2017, 18, 1384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saudubray, J.M.; Mochel, F. The phenotype of adult versus pediatric patients with inborn errors of metabolism. J. Inherit. Metab. Dis. 2018, 41, 753–756. [Google Scholar] [CrossRef] [Scilit]
- Sirrs, S.M.; Lehman, A.; Stockler, S.; van Karnebeek, C.D. Treatable inborn errors of metabolism causing neurological symptoms in adults. Mol. Genet. Metab. 2013, 110, 431–438. [Google Scholar] [CrossRef] [Scilit]
- Gkampeta, A.; Pavlou, E. Infantile spasms (West syndrome) in children with inborn errors of metabolism: A review of the literature. J. Child. Neurol. 2012, 27, 1295–1301. [Google Scholar] [CrossRef] [Scilit]
- Schiller, S.; Rosewich, H.; Grünewald, S.; Gärtner, J. Inborn errors of metabolism leading to neuronal migration defects. J. Inherit. Metab. Dis. 2020, 43, 145–155. [Google Scholar] [CrossRef] [Scilit]
- Tseng, L.A.; Sowerbutt, C.; Lee, J.J.Y.; van Karnebeek, C.D.M. P4 medicine for epilepsy and intellectual disability: Nutritional therapy for inherited metabolic disease. Emerg. Top. Life Sci. 2019, 3, 75–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brunk, E.; Sahoo, S.; Zielinski, D.C.; Altunkaya, A.; Dräger, A.; Mih, N.; Gatto, F.; Nilsson, A.; Preciat Gonzalez, G.A.; Aurich, M.K.; et al. Recon3D enables a three-dimensional view of gene variation in human metabolism. Nat. Biotechnol. 2018, 36, 272–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Inborn Errors of Metabolism Knowledgebase (IEMbase). Available online: www.IEMbase.org (accessed on 10 December 2021).
- Limanaqi, F.; Biagioni, F.; Busceti, C.L.; Fabrizi, C.; Frati, A.; Fornai, F. mTOR-Related Cell-Clearing Systems in Epileptic Seizures, an Update. Int. J. Mol. Sci. 2020, 21, 1642. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ebrahimi-Fakhari, D.; Saffari, A.; Wahlster, L.; Sahin, M. Using tuberous sclerosis complex to understand the impact of MTORC1 signaling on mitochondrial dynamics and mitophagy in neurons. Autophagy 2017, 13, 754–756. [Google Scholar] [CrossRef] [Scilit]
- Teinert, J.; Behne, R.; Wimmer, M.; Ebrahimi-Fakhari, D. Novel insights into the clinical and molecular spectrum of congenital disorders of autophagy. J. Inherit. Metab. Dis. 2020, 43, 51–62. [Google Scholar] [CrossRef] [Scilit]
- Potter, B.K.; Chakraborty, P.; Kronick, J.B.; Wilson, K.; Coyle, D.; Feigenbaum, A.; Geraghty, M.T.; Karaceper, M.D.; Little, J.; Mhanni, A.; et al. Canadian Inherited Metabolic Diseases Research Network. Achieving the “triple aim” for inborn errors of metabolism: A review of challenges to outcomes research and presentation of a new practice-based evidence framework. Genet. Med. 2013, 15, 415–422. [Google Scholar] [CrossRef] [Scilit]
- Bauer, S.; van Alphen, N.; Becker, A.; Chiocchetti, A.; Deichmann, R.; Deller, T.; Freiman, T.; Freitag, C.M.; Gehrig, J.; Hermsen, A.M.; et al. Personalized translational epilepsy research—Novel approaches and future perspectives: Part II: Experimental and translational approaches. Epilepsy Behav. 2017, 76, 7–12. [Google Scholar] [CrossRef] [Scilit]
- ACMG Board of Directors. Clinical utility of genetic and genomic services: A position statement of the American College of Medical Genetics and Genomics. Genet. Med. 2015, 17, 505–507. [Google Scholar] [CrossRef] [Scilit]
- Almannai, M.; Al Mahmoud, R.A.; Mekki, M.; El-Hattab, A.W. Metabolic Seizures. Front. Neurol. 2021, 12, 640371. [Google Scholar] [CrossRef] [Scilit]
- Wilmshurst, J.M.; Gaillard, W.D.; Vinayan, K.P.; Tsuchida, T.N.; Plouin, P.; Van Bogaert, P.; Carrizosa, J.; Elia, M.; Craiu, D.; Jovic, N.J.; et al. Summary of recommendations for the management of infantile seizures: Task Force Report for the ILAE Commission of Pediatrics. Epilepsia 2015, 56, 1185–1197. [Google Scholar] [CrossRef] [Scilit]
- Tolchin, B.; Hirsch, L.J.; LaFrance, W.C., Jr. Neuropsychiatric Aspects of Epilepsy. Psychiatr. Clin. N. Am. 2020, 43, 275–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pronicka, E.; Piekutowska-Abramczuk, D.; Ciara, E.; Trubicka, J.; Rokicki, D.; Karkucińska-Więckowska, A.; Pajdowska, M.; Jurkiewicz, E.; Halat, P.; Kosińska, J.; et al. New perspective in diagnostics of mitochondrial disorders: Two years’ experience with whole-exome sequencing at a national paediatric centre. J. Transl. Med. 2016, 14, 174. [Google Scholar] [CrossRef] [Scilit]
- Wortmann, S.B.; Koolen, D.A.; Smeitink, J.A.; van den Heuvel, L.; Rodenburg, R.J. Whole exome sequencing of suspected mitochondrial patients in clinical practice. J. Inherit. Metab. Dis. 2015, 38, 437–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riley, L.G.; Cowley, M.J.; Gayevskiy, V.; Minoche, A.E.; Puttick, C.; Thorburn, D.R.; Rius, R.; Compton, A.G.; Menezes, M.J.; Bhattacharya, K.; et al. The diagnostic utility of genome sequencing in a pediatric cohort with suspected mitochondrial disease. Genet. Med. 2020, 22, 1254–1261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jensen, K.V.; Frid, M.; Stödberg, T.; Barbaro, M.; Wedell, A.; Christensen, M.; Bak, M.; Ek, J.; Madsen, C.G.; Darin, N.; et al. Diagnostic pitfalls in vitamin B6-dependent epilepsy caused by mutations in the PLPBP gene. JIMD Rep. 2019, 50, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Coene, K.L.M.; Kluijtmans, L.A.J.; van der Heeft, E.; Engelke, U.F.H.; de Boer, S.; Hoegen, B.; Kwast, H.J.T.; van de Vorst, M.; Huigen, M.C.D.G.; Keularts, I.M.L.W.; et al. Next-generation metabolic screening: Targeted and untargeted metabolomics for the diagnosis of inborn errors of metabolism in individual patients. J. Inherit. Metab. Dis. 2018, 41, 337–353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bower, A.; Imbard, A.; Benoist, J.F.; Pichard, S.; Rigal, O.; Baud, O.; Schiff, M. Diagnostic contribution of metabolic workup for neonatal inherited metabolic disorders in the absence of expanded newborn screening. Sci. Rep. 2019, 9, 14098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mercimek-Mahmutoglu, S.; Patel, J.; Cordeiro, D.; Hewson, S.; Callen, D.; Donner, E.J.; Hahn, C.D.; Kannu, P.; Kobayashi, J.; Minassian, B.A.; et al. Diagnostic yield of genetic testing in epileptic encephalopathy in childhood. Epilepsia 2015, 56, 707–716. [Google Scholar] [CrossRef] [Scilit]
- Wanders, R.J.A.; Vaz, F.M.; Ferdinandusse, S.; van Kuilenburg, A.B.P.; Kemp, S.; van Karnebeek, C.D.; Waterham, H.R.; Houtkooper, R.H. Translational Metabolism: A multidisciplinary approach towards precision diagnosis of inborn errors of metabolism in the omics era. J. Inherit. Metab. Dis. 2019, 42, 197–208. [Google Scholar] [CrossRef] [Scilit]
- Adhikari, A.N.; Gallagher, R.C.; Wang, Y.; Currier, R.J.; Amatuni, G.; Bassaganyas, L.; Chen, F.; Kundu, K.; Kvale, M.; Mooney, S.D.; et al. The role of exome sequencing in newborn screening for inborn errors of metabolism. Nat. Med. 2020, 26, 1392–1397. [Google Scholar] [CrossRef] [Scilit]
- Chambers, C.; Jansen, L.A.; Dhamija, R. Review of Commercially Available Epilepsy Genetic Panels. J. Genet. Couns. 2016, 25, 213–217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sechi, A.; Fabbro, E.; Langeveld, M.; Tullio, A.; Lachmann, R.; Mochel, F. SSIEM Adult Physicians Metabolic Group. Education and training in adult metabolic medicine: Results of an international survey. JIMD Rep. 2019, 49, 63–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferraro, L.; Pollard, J.R.; Helbig, I. Attitudes toward Epilepsy Genetics Testing among Adult and Pediatric Epileptologists-Results of a Q-PULSE Survey. Epilepsy Curr. 2016, 16, 46–47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soden, S.E.; Saunders, C.J.; Willig, L.K.; Farrow, E.G.; Smith, L.D.; Petrikin, J.E.; LePichon, J.B.; Miller, N.A.; Thiffault, I.; Dinwiddie, D.L.; et al. Effectiveness of exome and genome sequencing guided by acuity of illness for diagnosis of neurodevelopmental disorders. Sci. Transl. Med. 2014, 6, 265ra168. [Google Scholar] [CrossRef] [Scilit]
- Joshi, C.; Kolbe, D.L.; Mansilla, M.A.; Mason, S.O.; Smith, R.J.; Campbell, C.A. Reducing the Cost of the Diagnostic Odyssey in Early Onset Epileptic Encephalopathies. Biomed. Res. Int. 2016, 2016, 6421039. [Google Scholar] [CrossRef] [Scilit]
- Stark, Z.; Schofield, D.; Martyn, M.; Rynehart, L.; Shrestha, R.; Alam, K.; Lunke, S.; Tan, T.Y.; Gaff, C.L.; White, S.M. Does genomic sequencing early in the diagnostic trajectory make a difference? A follow-up study of clinical outcomes and cost-effectiveness. Genet. Med. 2019, 21, 173–180. [Google Scholar] [CrossRef] [Scilit]
- Alam, K.; Schofield, D. Economic evaluation of genomic sequencing in the paediatric population: A critical review. Eur. J. Hum. Genet. 2018, 26, 1241–1247. [Google Scholar] [CrossRef] [Scilit]
- Ibhazehiebo, K.; Gavrilovici, C.; de la Hoz, C.L.; Ma, S.C.; Rehak, R.; Kaushik, G.; Meza Santoscoy, P.L.; Scott, L.; Nath, N.; Kim, D.Y.; et al. A novel metabolism-based phenotypic drug discovery platform in zebrafish uncovers HDACs 1 and 3 as a potential combined anti-seizure drug target. Brain 2018, 141, 744–761. [Google Scholar] [CrossRef] [Scilit]
- Galanopoulou, A.S.; Buckmaster, P.S.; Staley, K.J.; Moshé, S.L.; Perucca, E.; Engel, J., Jr.; Löscher, W.; Noebels, J.L.; Pitkänen, A.; Stables, J.; et al. American Epilepsy Society Basic Science Committee and The International League Against Epilepsy Working Group On Recommendations For Preclinical Epilepsy Drug Discovery. Identification of new epilepsy treatments: Issues in preclinical methodology. Epilepsia 2012, 53, 571–582. [Google Scholar] [CrossRef] [Scilit]
- Sills, G.J.; Rogawski, M.A. Mechanisms of action of currently used antiseizure drugs. Neuropharmacology 2020, 168, 107966. [Google Scholar] [CrossRef] [Scilit]
- Greenberg, D.A.; Subaran, R. Blinders, phenotype, and fashionable genetic analysis: A critical examination of the current state of epilepsy genetic studies. Epilepsia 2011, 52, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, M.G.; Rowley, S.; Fulton, R.; Dinday, M.T.; Baraban, S.C.; Patel, M. Altered Glycolysis and Mitochondrial Respiration in a Zebrafish Model of Dravet Syndrome. eNeuro 2016, 3, ENEURO.0008-16.2016. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jakkamsetti, V.; Marin-Valencia, I.; Ma, Q.; Good, L.B.; Terrill, T.; Rajasekaran, K.; Pichumani, K.; Khemtong, C.; Hooshyar, M.A.; Sundarrajan, C.; et al. Brain metabolism modulates neuronal excitability in a mouse model of pyruvate dehydrogenase deficiency. Sci. Transl. Med. 2019, 11, eaan0457. [Google Scholar] [CrossRef] [Scilit]
- Rowley, S.; Liang, L.P.; Fulton, R.; Shimizu, T.; Day, B.; Patel, M. Mitochondrial respiration deficits driven by reactive oxygen species in experimental temporal lobe epilepsy. Neurobiol. Dis. 2015, 75, 151–158. [Google Scholar] [CrossRef] [Scilit]
- Kuijpers, M.; Kochlamazashvili, G.; Stumpf, A.; Puchkov, D.; Swaminathan, A.; Lucht, M.T.; Krause, E.; Maritzen, T.; Schmitz, D.; Haucke, V. Neuronal Autophagy Regulates Presynaptic Neurotransmission by Controlling the Axonal Endoplasmic Reticulum. Neuron 2021, 109, 299–313.e9. [Google Scholar] [CrossRef] [Scilit]
- Srivastava, N.K.; Mukherjee, S.; Sharma, R.; Das, J.; Sharma, R.; Kumar, V.; Sinha, N.; Sharma, D. Altered lipid metabolism in post-traumatic epileptic rat model: One proposed pathway. Mol. Biol. Rep. 2019, 46, 1757–1773. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).