


Abstract
Background/Objectives: Although the exact etiology of Inflammatory Bowel Diseases (IBD) is not yet fully understood, recent evidence suggests that both genetic and dietary factors are involved in their pathogenesis. The aim of the present exploratory study was to investigate how first-degree relatives (FDRs) of individuals with IBD perceive familial risk and the role of diet in IBD onset and prevention. Methods: A mixed methods approach was followed. A total of 103 unaffected FDRs of individuals living with IBD in Greece participated in an online questionnaire examining demographic characteristics, disease-related knowledge, risk perception, and beliefs about the role of diet in IBD. In parallel, 16 semi-structured interviews explored participants’ beliefs, self-reported dietary practices, and the factors shaping them using a framework analysis guided by the Health Belief Model. Results: Exploratory quantitative findings indicated that belief in the role of diet was associated with higher odds of self-reported family dietary changes, while belief in genetic risk was associated with lower odds of self-reported family dietary changes. The findings did not characterize the nature, maintenance, or motivation of these changes. Qualitative findings provided a deeper understanding of participants’ beliefs, highlighting that diet was mainly viewed as relevant to IBD management rather than prevention. Fear of disease onset and healthcare professional guidance were perceived as key facilitators of dietary changes. Conclusions: Our findings highlight heterogeneous beliefs regarding familial IBD risk and self-reported family diet changes, and support future research addressing balanced familial-risk communication for unaffected FDRs.
1. Introduction
Inflammatory Bowel Disease (IBD) is a general term that encompasses a group of chronic diseases characterized by relapsing and remitting inflammation of the intestine. The two main IBD types are Crohn’s Disease (CD) and Ulcerative Colitis (UC) [1]. IBD is estimated to affect more than three million people in the United States and approximately 2.5 to 3 million in Europe [2]. To date, there is no definitive treatment for IBD, and available therapeutic approaches focus on achieving remission and preventing relapse [3]. IBD patients are often required to manage serious physical symptoms (e.g., pain, discomfort, and surgical interventions), psychological burdens (e.g., depression and anxiety) [4], and social challenges (e.g., professional problems and social isolation) [5]. IBD, thus, can significantly affect both the physical and mental health of patients, as well as their overall quality of life [6].
Although the exact etiology of IBD is still not completely known, recent studies have indicated that both genetic susceptibility and diet are involved in IBD pathogenesis [7,8,9,10].
In particular, population studies have provided compelling evidence that genetic factors play a vital role in the pathogenesis of IBD. Both UC and CD often occur in more than one member of the same family, with family studies showing that a child has a 26-fold increased risk of developing CD when a sibling has already been diagnosed with the disease; in the case of UC the corresponding increase in risk is nine-fold [11]. On a similar note, the risk of developing IBD is eight to ten times higher among first-degree relatives (FDRs) of individuals with UC or CD, implying a strong genetic predisposition to IBD. Of note, twin studies have also provided evidence of genetic predisposition for IBD, with stronger evidence for CD compared to UC [12]. A recent genetic association study collected data from more than 75,000 adolescent and adult IBD patients and controls and conducted various genome-wide analyses [13]. The study identified 163 genetic regions associated with IBD susceptibility, and approximately 300 potential candidate genes. Of these 163 loci, 110 were associated with increased risk for both subtypes of IBD, while 30 were specific for CD and 23 were exclusive to UC [13]. Likewise, a multinational study involving over 20,000 individuals of European and non-European descent, identified 38 new genetic loci associated with IBD, highlighting shared genetic risk across different populations and increasing the total number of known risk loci for IBD to 200 [14,15].
Past research has explored the role of specific dietary components on IBD development and identified several dietary practices related to a decreased IBD risk [7,8]. For instance, increased intake of the omega-6 arachidonic acid has been associated with an elevated risk of developing UC [16]. Conversely, an increased intake of omega-3 fatty acids, such as docosahexaenoic acid (DHA), and a high ratio of omega-3 to omega-6 fatty acids, may lower the UC and CD risk [17]. Plant fibers may reduce the risk of IBD onset, with fiber from fruits and whole-grain breads protecting against CD and fiber from whole grains reducing UC risk [18]. Increased vitamin D intake may reduce the risk of UC whereas high zinc intake is associated with a lower likelihood of CD. In contrast, intake of iron; folate; vitamin B12; vitamins A, C, and E; and polyphenols have not been associated with IBD risk [19].
In addition to studying individual dietary components, there is growing research on overall dietary patterns and their potential impact on the risk of an IBD diagnosis. Dietary patterns characterized by high consumption of fruits, whole grains, nuts and seeds, alongside a limited intake of red and processed meats and foods high in sugars, have been linked to lower risk of developing IBD. On the contrary, high consumption of ultra-processed foods has been associated with a greater likelihood of developing CD [7].
Although the role of dietary factors and genetic predisposition in the pathogenesis of IBD has been extensively investigated, the interplay between these two determinants remains poorly understood. Increasing evidence supports that gene–environment interactions, diet-induced changes in the gut microbiota, and epigenetic modifications collectively influence immune dysfunction and intestinal inflammation [20]. However, the mechanistic pathways through which dietary exposures interact with the host genetic background to lead to disease development have not yet been elucidated.
Furthermore, existing research has focused predominantly on biomedical, molecular, and epidemiological factors, with comparatively limited attention to the experiences of individuals at elevated genetic risk of developing IBD. In particular, the beliefs, perceptions, and attitudes of unaffected FDRs of individuals living with IBD towards the role of diet in IBD onset, alongside their current dietary practices, remain underexplored [21]. Examining these perspectives would enhance our understanding of how families interpret and respond to perceived IBD risk, thereby informing family-centered risk communication and dietary guidance tailored to the information needs of this population [22].
A mixed methods approach that centers the perspectives of unaffected FDRs of individuals living with IBD may provide a more holistic understanding of the cognitive and behavioral dimensions of dietary decision-making within these families. Such an approach could clarify whether dietary changes are reported within families following an IBD diagnosis, what beliefs underlie them, and where those beliefs diverge from current evidence. These insights could inform family-centered risk communication and dietary guidance.
Hence, following a mixed methods approach, the aim of the present study was to examine dietary beliefs and reported family dietary changes among unaffected FDRs of individuals with IBD, including parents, siblings, and offspring. Specifically, the study examined how unaffected FDRs perceive their familial IBD risk, what they believe about the role of diet in IBD onset, what information they report needing, and whether dietary changes were implemented within the family following the diagnosis of a relative. The study was not designed to evaluate whether such changes reduce the risk of developing IBD.
2. Materials and Methods
2.1. Study Design
A convergent parallel (concurrent) mixed methods design was employed, and qualitative and quantitative studies were concurrently conducted between October 2025 and March 2026.
An online questionnaire survey was administered to 103 unaffected FDRs of individuals living with IBD in Greece. All 103 participants completed all survey items included in the analyses, resulting in no missing responses. The online survey aimed at investigating knowledge, perceptions and attitudes regarding the role of diet in the occurrence and prevention of IBD in unaffected FDRs of individuals living with IBD. At the same time, the perception of familial predisposition was examined, as well as possible dietary practices or changes adopted to reduce the relative risk.
The qualitative study included semi-structured interviews with unaffected FDRs of individuals living with IBD. The interviews explored in-depth the perceptions, experiences, and dietary practices of the participants.
No formal integration between the qualitative and quantitative components (e.g., triangulation or use of an integration matrix) was performed at the analysis level but findings are discussed together. The rationale for mixing was complementarity and expansion: the quantitative study estimates how frequently particular perceptions and self-reported family dietary changes occur in this population, while the qualitative study explains the reasoning, motivations and constraints that a close ended response format could not capture.
2.2. Inclusion/Exclusion Criteria
In both studies, eligibility criteria included adult age (18 or above years), ability to communicate in the Greek language and residency in Greece. Additionally, participants were required to self-report no personal diagnosis of IBD and to be an FDR of an individual living with IBD (i.e., parent, sibling, or offspring). No further inclusion criteria were applied.
2.3. Procedure & Ethical Approval
The current study obtained ethical approval from the Ethics Committee of the Department of Nutrition & Dietetics, University of Thessaly (approval no: 57/1.10.2025) and was completed in accordance with the code of conduct, legal regulations, and ethical guidelines defined by the University Ethics Committee. Participants were informed that they could pause or withdraw from the studies at any point without giving a reason. Moreover, during interviews, researchers were instructed to pause or terminate an interview if participants showed signs of distress; no participant withdrew, paused, or requested termination.
Participants were invited to take part in the online survey through social media platforms and organizations that provide support to people with IBD. Before giving their consent, participants were fully informed about the study’s objectives and procedures. The online questionnaire included closed-ended questions regarding demographic characteristics, as well as knowledge, perceptions and attitudes regarding the role of diet in the occurrence and prevention of IBD. It is worth noting that data collection was conducted anonymously, without recording any information that could reveal the participants’ identities, ensuring that responses could not be linked to specific individuals.
For the qualitative study, interviewees were invited to take part in two different ways. Initially, as in the quantitative phase, interested individuals were informed about both studies through social media platforms and IBD patient support organizations, and could contact the research team directly. In addition, participants who expressed interest in receiving more information about the interview study while completing the online questionnaire were given the opportunity to provide their contact information. The research team then contacted them, providing detailed information about the subject and scope of the qualitative study. Sampling for the qualitative component was by convenience and self-selection through the same channels as the survey.
Next, for both recruitment methods, the study information sheet, which outlined the purpose of the research, the potential risks and benefits for participants, voluntary participation, and confidentiality issues, was emailed to those who expressed interest in participating in the interviews.
Recruitment was conducted through social media and patient-support organizations, and the survey platform recorded only submitted questionnaires. Therefore, the number of individuals who saw the invitation, and the number of individuals who opened the survey link without submitting a response cannot be calculated. No partial or incomplete questionnaires were received.
For the qualitative study, individual interviews were scheduled and conducted on dates that were convenient for both the participants and the researcher(s). Every individual who was approached consented to participate, and all 16 scheduled interviews were conducted and completed. Before the process began, participants were asked to sign the consent form electronically. All interviews were conducted online. On the day of the interview, researchers D.E.S. (female, PhD), who has a background in psychology and specifically health psychology, and G.C. (male, BSc), who has a background in nutrition and dietetics, provided a detailed explanation of the study’s purpose and gave participants ample time to ask any questions. Each interview lasted approximately one hour. Participants had the option to withdraw at any time, either to ask questions or to leave early in case of psychological distress.
Both researchers conducting the interviews had received training in qualitative research methods, covering semi-structured interviewing and framework-based and thematic analysis, before data collection began, and both had prior experience of conducting and analyzing qualitative interviews.
Neither interviewer had any prior relationship with the participants nor was involved in the clinical care of the affected relative. Reflexivity was addressed through discussion between the two researchers during coding, in which interpretations were compared and the potential influence of the researchers’ background on their questioning and interpretation was examined.
All data and information generated by the two studies were stored electronically and handled with the greatest confidentiality. Specifically, in the context of the quantitative study, no personal data, such as names, were collected, with the sole exception of the email addresses of those who wished to participate in the qualitative phase as well. Participants’ data were stored on computers at the Laboratory of Nutrition and Clinical Dietetics, after first being coded with numerical identifiers to ensure their confidentiality. The interview recordings were securely stored on an encrypted drive, accessible exclusively to the researchers of the studies. Prior to analysis, the interviews were transcribed verbatim, the data were then anonymized and imported into NVivo (version 14) for further processing.
2.4. Materials
An online questionnaire (see Supplementary Materials, Questionnaire S1) was developed by the research team for the purpose of the present study, and its content was informed by previously published literature on IBD regarding disease-related knowledge, risk perception, and beliefs about the role of diet in disease onset and prevention [23,24]. The questionnaire consisted mainly of closed-ended questions.
The initial draft was reviewed by two members of the research team with expertise in nutrition, dietetics and public health. No quantitative content validity index was computed, no cognitive interviewing was conducted with members of the target population, and no formal pilot test was performed. The clarity and readability of the questions were checked to ensure their suitability for use in the target population. The questionnaire was designed as a set of descriptive indicators of perception and self-reported behavior rather than as a psychometric scale.
The questionnaire collected information on the demographic characteristics of the participants, including gender, age, education level, employment status, marital status and place of residence. In addition, the presence of IBD in the family environment of the participants was investigated. At the same time, participants’ perceptions regarding the likelihood of IBD occurrence in FDRs (including parents, siblings, and children) were assessed. Participants’ attitudes towards this statement were recorded using a five-point Likert scale (1 = “Strongly disagree” to 5 = “Strongly agree”). In addition, it was investigated whether participants had discussed with a healthcare professional the likelihood of IBD occurrence or the role of diet in its occurrence and/or prevention. In the case of a positive response, participants were asked to identify the specialty of the healthcare professional. Finally, the questionnaire assessed participants’ beliefs about the role of diet in IBD onset or prevention and whether they reported that dietary changes had been implemented within the family to reduce disease risk. The latter item did not identify which family members changed their diet, the specific nature or maintenance of these changes, or the underlying motivation for them.
With regards to the qualitative study, a semi-structured topic guide entailing ten open questions was used for all interviews (Table 1). Questions explored the perceptions, beliefs and behavioral intentions of FDRs of individuals with IBD regarding perceived susceptibility, perceived severity of the disease, perceived benefits of nutrition and perceived barriers of dietary changes, cues to action, self-efficacy and dietary changes that were finally made, within the context of a cognitive-behavioral model, the Health Belief Model (HBM). Probing and follow-up questions were used where appropriate to encourage deeper reflection and to clarify emerging topics. A consent form was also administered to the participants prior to the start of the interviews.
Table 1.
Topic guide for semi-structured interviews with FDRs of individuals with IBD.
2.5. Analyses
2.5.1. Statistical Analysis
Quantitative data on demographic characteristics, participants’ relationship with IBD, professional consultations and perceptions of FDRs were presented as absolute (n) and relative (%) frequencies. To explore factors associated with self-reported family dietary changes, an exploratory, post hoc parsimonious logistic regression analysis was performed. The binary outcome was self-reported implementation of dietary changes within the family to reduce disease risk, as assessed by the corresponding questionnaire item. The initial model included demographic variables (age, gender, education level, employment status) and perceptions regarding the disease (belief in genetic risk, consultation with a healthcare professional regarding risk, belief in the role of diet). Given the limited number of outcome events, the initial model was simplified post hoc by sequentially removing non-significant and redundant variables and variables contributing to data separation. Gender, education level and employment status were removed at this stage and are therefore not included in the reduced model reported in the Results section, which retains age, belief in genetic risk, consultation with a healthcare professional regarding risk, and belief in the role of diet. This simplification was not pre-specified, and the resulting estimates are therefore considered exploratory and hypothesis-generating. Odds Ratios (OR) with their corresponding 95% Confidence Intervals (CI) were calculated to estimate the strength of the associations. Statistical significance was set at p < 0.05. All statistical analyses were conducted using Jamovi (Version 2.6.44).
2.5.2. Framework Analysis
A deductive analysis method was used in this study to identify, analyze and interpret the meanings from the interviews. In this approach, the analysis starts from the theory which acts as a guide for the identification of the initial codes [25]. The present study was based on the theoretical framework of HBM, which was developed in the 1950s. This model is widely used in health behavior research and allows the understanding of the processes that support both the adoption and maintenance of health behaviors but also offers a theoretical basis for the development of health interventions.
HBM predicts the likelihood that an individual will engage in behaviors that aim to prevent, detect, or control health problems. For this purpose, specific concepts are used, such as perceived vulnerability, perceived severity, perceived benefits and barriers, cues to action, and more recently the addition of self-efficacy [26]. Since specific categories had been predefined based on the model, the data were analyzed in the following way. First, the specific thematic units were identified and the basic elements of HBM were recorded and served as initial codes. The data were then analyzed to identify and classify the corresponding meanings, and the predefined thematic categories were used as a basis for the meanings that emerged from the data (deductive analysis). The third and final step included the agreement between the researchers on both issues that concern the research questions, the codes and the basic thematic areas [27] as well as the saturation of the data. Since the analysis was framework-based, saturation refers to no additional codes within the predefined categories, indicating that sufficient data had been obtained to fully populate the framework.
Interviews were conducted, audio-recorded and transcribed verbatim in Greek, and all coding was performed on the Greek transcripts in NVivo (version 14). Only the quotations included in the manuscript were translated into English, by a bilingual member of the research team. A second bilingual researcher member independently back translated the quotations, and any discrepancies were resolved through discussion to ensure conceptual rather than literal equivalence.
3. Results
3.1. Quantitative Results
The demographic characteristics of the 103 unaffected study participants are presented in Table 2. The median age of the sample was 43.0 years (Q1, Q3: 34.0, 51.5). Most were females (61.2%), resided in urban areas (85.4%) and had completed higher education or above (72.8%). Regarding marital and employment status, the majority of the respondents were married (62.1%) and in full-time employment (61.2%). FDRs’ IBD diagnoses included CD (63.1%) and UC (36.9%). Participants’ relationships with the individual with IBD included being a parent (53.4%), sibling (13.6%), or offspring (33.0%).
Table 2.
Demographic characteristics of participants (N = 103).
Less than half of the participants (42.7%) agreed or strongly agreed that FDRs of IBD patients face a higher risk of developing the disease compared to the general population (Table 3). A similar proportion (39.8%) remained neutral whereas 17.5% disagreed.
Table 3.
Participants’ perceptions regarding the familial risk of IBD (N = 103).
According to Table 4, 58.3% discussed the possibility of disease onset among FDRs with a healthcare professional, while the vast majority (93.2%) had discussed the preventive role of diet in lowering IBD risk. Fewer than half of the participants (43.7%) agreed that diet plays a role in the onset or prevention of IBD in FDRs. Likewise, only 28.2% reported having implemented dietary changes within their family to reduce IBD risk. The survey did not assess which family members made these changes, their specific content or maintenance, or the motivation underlying them.
Table 4.
Participants’ perceptions, consultations and dietary practices regarding IBD (N = 103).
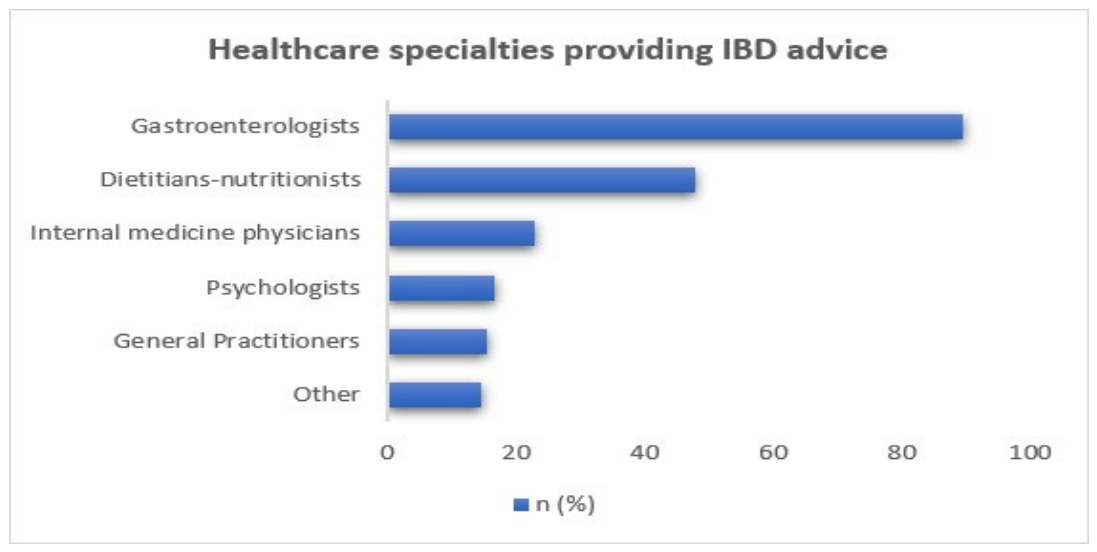
The different specialties of healthcare professionals providing advice on the role of diet in IBD prevention are shown in Figure 1. Among participants who reported consulting a healthcare professional (n = 96), the total number of reported consultations exceeds the sub-sample size as participants were able to select more than one specialty (multiple response question). Gastroenterologists were selected by the vast majority (89.6%) as the primary source of dietary advice, followed by dietitians-nutritionists (47.9%). Other professionals involved in patient consultation included internal medicine physicians (22.9%), psychologists (16.7%), and general practitioners (15.6%). A smaller proportion (14.6%) reported seeking advice from other specialties, such as nursing staff or pediatricians.
Figure 1.
Healthcare professionals’ specialties providing IBD advice (N = 96).
An exploratory, post hoc parsimonious logistic regression analysis was performed to assess factors associated with self-reported dietary changes among participants (n = 103 with n = 29 events) (see Table 5). To address potential overfitting and sparse-data bias associated with the limited number of events, a revised, parsimonious model was fitted by removing non-significant and redundant variables that caused data separation. The overall model demonstrated a satisfactory fit and was statistically significant (χ2 = 16.67, df = 7, p = 0.020, Nagelkerke R2 = 0.214). Belief that diet plays a role in the onset or prevention of IBD among FDRs was associated with higher odds of self-reported family dietary changes (OR = 3.916, 95% CI: 1.444–10.620, p = 0.007), indicating that individuals holding this belief were nearly four times more likely to self-report family dietary modifications. Conversely, strong agreement that FDRs are at higher genetic risk was inversely associated with self-reported family dietary modifications (Category 5 vs. 1: OR = 0.061, 95% CI: 0.004–0.894, p = 0.041); this estimate is imprecise and no causal or mechanistic interpretation is implied. Other factors included in the adjusted model, such as age (OR = 0.989, p = 0.581) and prior discussions with healthcare professionals regarding genetic risk (OR = 2.401, p = 0.097), did not show statistically significant associations with dietary changes.
Table 5.
Exploratory, post hoc parsimonious logistic regression of factors associated with self-reported family dietary changes (N = 103, n = 29 events).
3.2. Qualitative Results
As Table 6 illustrates, 16 unaffected FDRs of individuals living with IBD participated in the study. The associated IBD diagnoses of the FDR were evenly distributed between CD (n = 8) and UC (n = 8). Regarding disease status, most of the participants reported that their affected relative diagnosis was made 1–6 years ago.
Table 6.
Demographic characteristics of unaffected FDRs of individuals with IBD, who participated in individual interviews (N = 16).
Most interviewees were women (n = 9) and lived in urban areas (n = 14). All participants completed at least junior high school or high school education level, and most were employed full-time. The median age of the interviewees was 37 years. Of the participants, six were parents of children with IBD, five were siblings of individuals with IBD, and five were offspring of individuals with IBD.
Sub-analyses by the aforementioned demographic characteristics are presented, where relevant, within each theme.
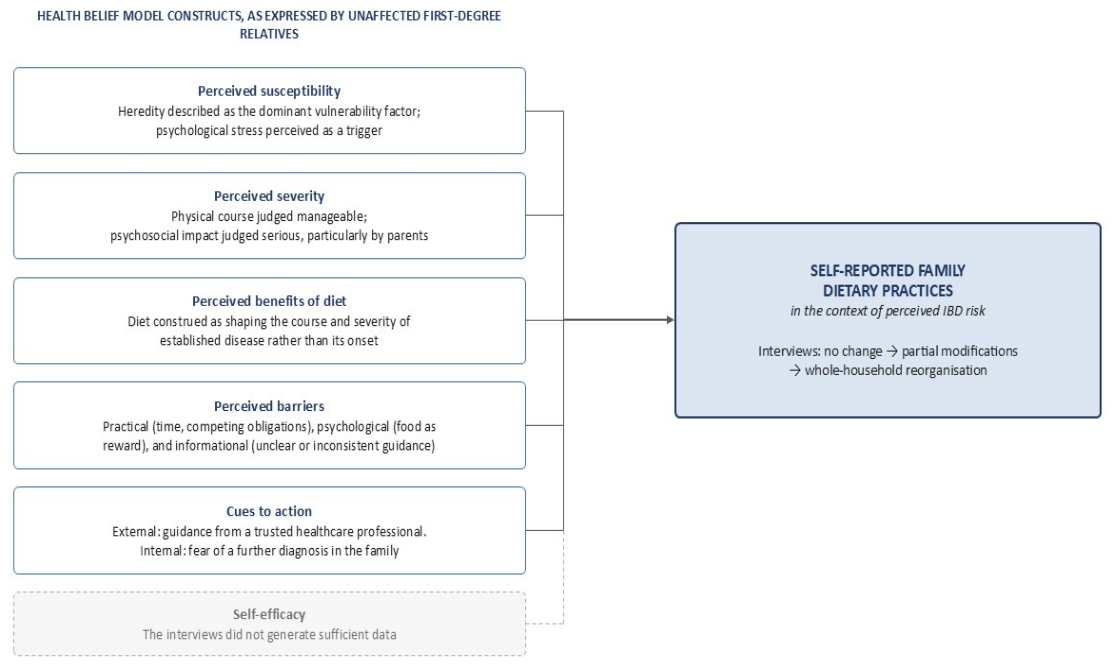
At a high level, two overarching themes emerged from the analysis. The first theme, namely “reported family dietary changes in the context of IBD”, highlighted substantial variability in whether and how participants adapted their diets following an IBD diagnosis within the family, ranging from no changes to more structured modifications. The second theme, “factors affecting dietary practices as reflected in the HBM”, reflected key constructs of the HBM, showing that perceptions of susceptibility, severity, benefits, barriers, and cues to action collectively shaped participants’ decisions regarding dietary change (Figure 2). Both themes are presented in detail below.
Figure 2.
Studied HBM constructs influencing dietary practices among families with an IBD diagnosis.
3.2.1. Theme 1—Reported Family Dietary Changes in the Context of IBD
Reported family dietary changes following an IBD diagnosis in the family varied considerably across interviewees. Most interviewees reported that they had not changed anything in their diet after the diagnosis of their relative.
“We did not make any major changes to our diet after the diagnosis.”(PART7, Male, 50 years old)
Among those reporting dietary changes, some mentioned partial dietary modifications, such as a decrease in the consumption of fried foods, junk foods, sugar, and salt, as these participants themselves perceived these modifications as a way to prevent the disease. Others described increased consumption of fruits, vegetables, and fatty fish; reduced consumption of red meat; and elevated use of olive oil.
“We’ve been avoiding fried foods for a very long time, anyway. We got an air fryer right after the diagnosis. We eat very often, like I said four times a week, vegetables, beans, peas and a spinach-rice dish.”(PART2, Female, 35 years old)
Only a few participants described systematic dietary changes after the IBD diagnosis of their relative. These participants regarded diet as something they could use actively in the hope of avoiding the disease; this preventive intent is reported here as their own understanding of what they were doing, rather than as a classification of the dietary changes themselves. In most of these families the modifications were implemented collectively, affecting the entire household.
“We are more careful now, especially regarding food and food combinations—not only for my brother, but for all of us in general. If something seems to bother us, we pay more attention to it. Overall, our eating habits and lifestyle have changed somewhat, and we have definitely become more mindful about our diet.”(PART9, Female, 24 years old)
3.2.2. Theme 2—Factors Affecting Dietary Practices as Reflected in the HBM
According to HBM, the adoption of preventive behaviors and dietary changes is influenced by the interaction of perceived vulnerability, perceived severity, perceived benefits and barriers, cues to action, and self-efficacy. The analysis of the present data revealed that participants acknowledged the existence of genetic vulnerability in IBD onset. Regarding perceived severity, participants who focused on physical symptoms of IBD had a sense of reduced perceived severity, while those who focused on psychosocial symptoms of IBD showed a stronger perception of severity. Most participants said that diet mainly affects the progression and flare ups of IBD rather than its onset. Perceived barriers were either practical, such as cost and time for food preparation, or psychological, such as habits. Cues to action were both internal and external, including reliable guidance from healthcare professionals and the fear of a new IBD diagnosis. These factors are described in more detail below.
Perceived Susceptibility to IBD Onset
Perceived susceptibility to the occurrence of IBD emerged as a multidimensional concept, which was expressed with different intensity and emotional load among the participants. About half recognized the possibility of the disease occurring in family members with IBD history, which indicates an increased level of risk awareness.
“…because this seems to be related to a genetic predisposition, I already consider it a possibility and would not be entirely surprised if it were confirmed.”(PART1, Male, 37 years old)
Heredity was systematically reported as the most important vulnerability factor for most interviewees. Genetic predisposition was described either as a “latent” condition that can be “activated” under specific conditions or, in some cases, as an almost inevitable development. For some participants, the coexistence of other autoimmune diseases in the family history such as Hashimoto disease and autoimmune rheumatic diseases, further strengthened the perception of risk, as IBD was associated with a broader autoimmune susceptibility.
“I have Hashimoto’s, I have a thyroid condition…Among my relatives, my brother has vitiligo. That is, as the doctors explained to me as well, they’re like “cousins” that run around within the family.”(PART12, Female, 41 years old)
Most interviewees stated that anxiety and psychological stress could increase IBD susceptibility. These participants often attributed a triggering role to prolonged emotional distress; IBD diagnosis was perceived as a consequence of severe psychosomatic stress rather than a random occurrence.
“I believe that the primary factor that influences is stress…I think that stress triggers many different health-related issues.”(PART4, Female, 28 years old)
Perceived Severity of an IBD Diagnosis
Many interviewees perceived the disease as relatively manageable, largely due to confidence in current treatments and the belief that early diagnosis and appropriate management could reduce disease burden. As one relative explained:
“It doesn’t worry me much because I understand that, unless something very severe develops, it may remain mild. And even if it becomes more serious, I will know ways to manage it, so I feel at ease about it.”(PART3, Female, 29 years old)
Among FDRs without IBD who were parents, the possibility of the disease affecting their children was perceived as particularly concerning, placing greater emphasis on its psychosocial impact. Their concerns focused on emotional distress, quality of life, and the broader effects on family functioning, particularly when children were involved. This heightened emotional frame is reflected in statements such as:
“I don’t want my children to go through anything that affects their daily lives or their psychological well-being, like IBD did to my brother. I know it’s not a fatal disease and that there are stages where you can manage it, but I still wouldn’t want them to have it…”.(PART12, Female, 41 years old)
Perceived Benefits of a Healthy Diet
Most participants expressed uncertainty about the beneficial role of diet in IBD prevention implying that diet cannot cause the disease. Nevertheless, most suggested that diet plays a crucial role in shaping severity, intensity, and progression of symptoms once IBD appears.
“I can’t say I’m convinced that diet causes the disease, but I do believe it strongly influences how it presents—particularly in terms of severity”.(PART5, Male, 47 years old)
At the same time, participants emphasized that diet alone is not sufficient for prevention, highlighting its synergistic interaction with other factors, most notably stress. Several described IBD as the result of a broader lifestyle context, where multiple influences act together.
“I think it’s a combination of factors—it’s not just about diet. You might be eating well, but if you’re also stressed, smoking, or have other habits… everything works together. You need to look at the bigger picture”.(PART2, Female, 35 years old)
In fact, adverse psychological factors were perceived as having a more crucial role in IBD onset than diet, as reflected in the words of one interviewee:
“I’m not sure, but I feel that the onset is influenced more by stress and psychological factors than by diet.”.(PART1, Male, 37 years old)
Perceived Barriers to Adopting a Healthy Diet
According to the interviewees, perceived barriers against healthier dietary changes were practical, psychological, and social. Limited time, work and family obligations, and the convenience of quick meals were frequently reported by participants as practical barriers to changing diet to prevent the disease.
“Unfortunately, due to the demands of everyday life—balancing office work, professional responsibilities, and childcare—we often resort to ordering takeout meals because of time constraints.”(PART2, Female, 35 years old)
At a psychological level, as most participants explained, the consumption of un-healthy food was associated with emotional reward and stress relief, posing significant challenges to behavior change.
“Psychology may also play a role, as many people—myself included in the past—tend to view junk food as a form of reward or entertainment. It is often perceived as more enjoyable, while at the same time being less healthy, so this factor may contribute as well.”(PART1, Male, 37 years old)
At a social level, lack of clear dietary information and guidance from healthcare professionals increased confusion among interviewees and discouraged the adoption of healthier dietary choices.
“It stems from a lack of information, as people are often unaware of what drives the eating habits that they should adopt.”(PART15, Female, 52 years old)
Cues to Action Promoting Dietary Changes
Cues to action are triggers—both internal and external—that motivate individuals to adopt or maintain health-related dietary behaviors. In this study, participants described a range of such cues that could motivate them to make dietary changes to prevent IBD.
In particular, internal cues included personal experiences that heightened awareness or concern about health. These encompassed the fear prompted by a potential new IBD diagnosis or the appearance of physical symptoms in the unaffected family members. As a participant mentioned:
“It could certainly be the fear of developing such a disease (that could motivate me to implement dietary changes)…”(PART6, Male, 31 years old)
On the other hand, external cues involved influences from the social and healthcare environment. According to almost all interviewees, reliable guidance from healthcare professionals, regular monitoring by a dietitian-nutritionist, and family support would reinforce participants’ commitment to behavior change and maintenance of healthier dietary habits.
“The guidance of a gastroenterologist, internal medicine physician, dietitian, or another appropriate healthcare professional is of great importance, depending on the individual’s needs.”(PART8, Male, 26 years old)
4. Discussion
To our knowledge, this is the first mixed methods study conducted in Greece to examine how unaffected FDRs of individuals living with IBD understand their familial risk and explore their beliefs about the role of diet in IBD onset. The qualitative and quantitative data reveal a complex interplay between the perceived disease severity and vulnerability and dietary perceptions and self-reported modifications within the study population. To facilitate interpretation of the findings from the two components, Table 7 presents a joint display highlighting areas of convergence, divergence, and complementarity between the quantitative and qualitative findings.
Table 7.
Joint display of quantitative and qualitative findings.
Quantitative findings showed that fewer than half of the participants recognized the increased IBD risk among FDRs, with many remaining uncertain. This aligns with previous research indicating that although familial predisposition is well established in IBD, health literacy may influence the interpretation of genetic susceptibility information [28]. In contrast, qualitative data indicated greater awareness of genetic susceptibility, often framing IBD as an almost “inevitable” but manageable health condition. This discrepancy may reflect the explanatory depth of the qualitative methods and participation bias, since individuals who participate in interviews are often more interested or informed about the topic. As such, this may have contributed to the higher expressed awareness of genetic susceptibility observed in the qualitative findings.
Interviewees emphasized that genetic risk does not act alone and frequently identified psychological stress as a trigger for IBD. This perception among study’s participants is consistent with previous studies showing that individuals with IBD similarly identify stress as a key contributor to disease onset and exacerbation [4,29]. Such perceptions are supported by evidence highlighting the substantial psychological burden of IBD, with anxiety, depression, and impaired quality of life frequently reported among patients and often persisting despite clinical remission [29,30,31,32].
Notably, perceptions of severity, which were assessed in the qualitative study, among many FDRs, did not solely focus on physical symptoms; several participants highlighted the psychological impact of the disease. While these perspectives reflect the experiences and concerns of relatives at risk rather than individuals living with IBD themselves, they do align with the priorities reported by patients with IBD, for whom disease burden during remission extends beyond symptom control to include psychological well-being and quality of life [33,34]. This overlap implies that FDRs may have a broader understanding of IBD severity, similar to that described by IBD patients [33,34].
Quantitative analyses revealed skepticism about diet in prevention; more than half of the participants did not believe that diet plays a role in IBD onset and prevention. However, belief in the role of diet emerged as a significant factor associated with self-reported family dietary changes within our sample. Past literature also suggests that individuals’ dietary beliefs significantly influence their behavior, as many modify their diet based on their personal perceptions of the role of diet in IBD [35]. Further to this quantitative finding, qualitative results illustrated how such beliefs may be shaped, influenced and sometimes constrained. Many interviewees perceived diet as more beneficial regarding IBD management rather than its onset. This perception seemed to weaken motivation for self-reported dietary changes, especially when compared to the relatively strong recognition of genetic susceptibility. Contrary to the perceptions of our study population, emerging evidence recognizes diet as a modifiable risk factor in IBD prevention [8,36,37,38,39]; specific dietary patterns such as Mediterranean-like, high fiber and low ultra-processed lower the risk of IBD onset [7]. In addition, current clinical guidelines from the European Society for Clinical Nutrition and Metabolism and the European Crohn’s and Colitis Organisation consensus primarily address nutritional management and dietary considerations in established IBD rather than primary prevention among unaffected FDRs [7,40]. However, emerging observational evidence suggests that a dietary pattern rich in fruits, vegetables, fibers, and omega-3 fatty acids, and low in omega-6 fatty acids and ultra-processed foods, may be associated with a reduced risk of developing IBD [8,36,37,38,39]. The low perceived benefit of diet in IBD prevention as captured in the present interviews in combination with emerging evidence suggesting a potential role of dietary patterns in IBD onset highlights the importance of balanced communication regarding the current evidence on diet and IBD risk. Since no dietary intervention has been shown to reduce IBD incidence in FDRs, the emphasis should remain on balanced risk communication and general healthy-eating guidance rather than IBD-specific preventive dietary prescription.
A striking finding across both study components was the gap between participants’ awareness about the role of diet and the self-reported family dietary changes. Interviews revealed multiple barriers to dietary change, including practical constraints such as time and cost, psychological factors such as emotional attachment to unhealthy foods, and social barriers such as unclear or inconsistent dietary guidance. Our findings are in line with behavioral studies which show that when many barriers are identified, the likelihood of behavior change and, in particular, the adoption of health behaviors may be reduced [41].
Both internal and external cues were identified by our qualitative findings, as key determinants of adopting and maintaining healthier dietary practices. Healthcare professionals were identified in the qualitative findings as an important external cue to action, with participants emphasizing that guidance from trusted experts could motivate and support dietary behavior change. This may be read alongside the quantitative results, where gastroenterologists (89.6%) were reported as the primary source of advice, followed by dietitians-nutritionists (47.9%), highlighting the central role of medical professionals in shaping FDRs’ understanding of IBD and the role of diet. This finding is consistent with past research highlighting the central role of healthcare professionals in improving IBD outcomes through effective communication and provision of evidence-based support. Use of patient decision aids and reliable dietary guidance may, thus, help reduce uncertainty, counter misinformation, and support informed decision-making among individuals living with or being at risk of IBD [42,43,44].
Finally, our qualitative results offer valuable context for interpreting the lack of significant associations between sociodemographic factors and dietary changes in our quantitative model. Sociodemographic characteristics were not associated with reported dietary change in this sample, although the limited number of outcome events restricts the precision of these estimates; the qualitative findings point to beliefs, motivations and perceived barriers as priorities for future work. This finding underscores the importance of moving toward a more cognitive and emotional based informed approach, integrating clear risk information and psychological support.
The present study presents several strengths alongside limitations. The mixed method design is a significant advantage, as it combines quantitative and qualitative approaches, preserving the strengths of each method, while limiting the respective limitations. This approach allows for a more comprehensive understanding of the phenomenon under study, which would not be possible with the implementation of an exclusively quantitative or qualitative method [45,46]. In the qualitative study, strengths include the satisfactory number of participants and the use of semi-structured interviews, offering flexibility and the possibility of listening to the FDRs’ voices. The quantitative findings provide interesting exploratory evidence regarding factors that may be associated with self-reported family dietary changes in this sample. The exploratory, post hoc parsimonious multivariable logistic regression identified an association between belief in the role of diet and reported family dietary changes. Given the limited number of outcome events and the exploratory nature of the analysis, these findings should be interpreted cautiously but may contribute to hypothesis generation and inform the design of future, adequately powered studies examining factors associated with dietary change among unaffected FDRs of individuals with IBD.
However, the study also has some limitations, including the use of convenience sampling and online recruitment. These may introduce selection bias, potentially leading to an overrepresentation of participants from urban areas and of those who are more engaged with digital platforms. Several limitations follow from the reliance on self-reported data rather than objective measurements. Moreover, recall bias and social desirability bias may have influenced participants’ responses.
For the quantitative study, while online data collection allowed for geographical expansion, the sample size is relatively small, especially when using logistic regression. In combination with the absence of a priori sample size calculation, the statistical power and the stability of the estimated associations may have been affected. Furthermore, due to the cross-sectional nature of the study, it is not possible to establish causality regarding the factors associated with dietary changes. In addition, the item assessing the role of diet combined IBD onset and prevention into a single question, preventing differentiation between these concepts. The questionnaire recorded whether participants reported that dietary changes had been implemented within the family but did not identify which family members made these changes, the specific nature of the changes, whether they were maintained over time, or their underlying motivation. Such changes may have reflected general health considerations, management of the affected relative’s condition, perceived personal or familial IBD risk, or a combination of these factors. Accordingly, the survey outcome should not be interpreted as a direct measure of preventive dietary behavior among unaffected FDRs. Similarly, the consultation item did not specify whether discussions with healthcare professionals concerned the affected relative’s care or the respondent’s own risk. Reported consultations suggest that healthcare professionals were an important source of information in this sample; however, the content and behavioral consequences of these discussions were not assessed.
Regarding the qualitative study one limitation concerns the inherent susceptibility of qualitative methods to interpretive bias. To address this issue, two researchers (D.E.S., G.C.) independently coded the data and discussed differences until a consensus was reached, ensuring the reliability of the present analysis. An additional limitation relates to the self-efficacy dimension of HBM. Although self-efficacy is a key factor in adopting and maintaining dietary changes, participants in our study did not provide sufficient data to adequately assess this dimension. As a result, the analysis could not provide conclusions about self-efficacy and its possible influence on dietary practices. Future studies could further investigate this dimension of HBM. Also, the experiences of FDRs’ living in small or remote areas have not been adequately recorded, limiting the applicability of the results to all of Greece.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/gastroent17030046/s1, Questionnaire S1: Online questionnaire—“Perceived Familial Risk, Dietary Beliefs, and Self-Reported Family Dietary Changes among Unaffected First-Degree Relatives of Individuals with Inflammatory Bowel Disease: A Mixed Methods Study in Greece”.
Author Contributions
V.S., D.E.S. and O.A. conceptualized and designed the current study. G.C. and D.E.S. performed interviews. D.E.S., E.Z., G.C., M.M. (Maria Misiou), M.M. (Maria Metallinou), I.D. and A.V. performed transcriptions and thematic analysis. A.T., D.E.S. and V.S. performed statistical analysis. V.S., D.E.S., E.Z., A.T., A.S., M.M. (Maria Misiou), G.C., A.V., M.M. (Maria Metallinou), I.D., A.K., K.A. and O.A. prepared the original draft and have responsibility for the final content. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was conducted in accordance with the principles of the Declaration of Helsinki. Ethical approval was obtained from the Ethics Committee of the Department of Nutrition & Dietetics, University of Thessaly and was conducted in line with the code of conduct, legal regulations, and ethical guidelines defined by the University Ethics Committee (approval no: 57, approval date: 1 October 2025).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request. The following email address will be monitored for requests: oandroutsos@uth.gr.
Acknowledgments
The authors would like to thank Anna Maria Pentzeretzi and Maria Delliou for their valuable assistance and support during the preparation of this manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| CD | Crohn’s Disease |
| CI | Confidence Intervals |
| FDRs | First-Degree Relatives |
| HBM | Health Belief Model |
| IBD | Inflammatory Bowel Disease |
| OR | Odds Ratios |
| UC | Ulcerative Colitis |
References
- Tomasello, G.; Abruzzo, A.; Sinagra, E.; Damiani, P.; Damiani, F.; Traina, G.; Campanella, C.; Rappa, F.; Marino Gammazza, A.; Noto, M.; et al. Nutrition in IBD patient’s. What are the prospects? Prog. Nutr. 2015, 17, 79–86. [Google Scholar] [CrossRef] [Scilit]
- Dubinsky, M.C.; Dotan, I.; Rubin, D.T.; Bernauer, M.; Patel, D.; Cheung, R.; Modesto, I.; Latymer, M.; Keefer, L. Burden of comorbid anxiety and depression in patients with inflammatory bowel disease: A systematic literature review. Expert Rev. Gastroenterol. Hepatol. 2021, 15, 985–997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Talley, N.J.; Abreu, M.T.; Achkar, J.-P.; Bernstein, C.N.; Dubinsky, M.C.; Hanauer, S.B.; Kane, S.V.; Sandborn, W.J.; Ullman, T.A.; Moayyedi, P. An Evidence-Based Systematic Review on Medical Therapies for Inflammatory Bowel Disease. Am. J. Gastroenterol. 2011, 106, S2–S25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strongylou, D.E.; Svolos, V.; Vlachou, A.; Zoupa, E.; Vakouftsi, V.-R.; Ntanou, A.; Argyriou, K.; Kapsoritakis, A.; Bonoti, F.; Androutsos, O. Understanding the Tripartite Relationship Between Dietary Practices, Psychological Well-Being, and Disease Experience in Greek Patients with IBD: A Mixed-Methods Exploration. Nutrients 2026, 18, 1439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lopez-Cortes, R.; Hueso-Montoro, C.; Garcia-Caro, M.P.; Montoya-Juarez, R.; Schmidt-Riovalle, J.; Marti-Garcia, C.; Marin-Fernandez, B. Factors Influencing the Life Experiences of Individuals with Inflammatory Bowel Disease. Gastroenterol. Nurs. 2018, 41, 120–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdulla, M.; Hallak, Y.; Sawaf, B.; Abbarh, S.; Abdalkarim, M.; Battikh, E.; Naga, Y.; Rakab, A. Impact of inflammatory bowel disease on quality of life and fatigue: A systematic review and meta-analysis. Inflamm. Bowel Dis. 2025, 31, S66. [Google Scholar] [CrossRef] [Scilit]
- Svolos, V.; Gordon, H.; Lomer, M.C.E.; Aloi, M.; Bancil, A.; Day, A.S.; Day, A.S.; Fitzpatrick, J.A.; Gerasimidis, K.; Gkikas, K.; et al. European Crohn’s and Colitis Organisation consensus on dietary management of inflammatory bowel disease. J. Crohn’s Colitis 2025, 19, jjaf122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Halmos, E.P.; Godny, L.; Vanderstappen, J.; Sarbagili-Shabat, C.; Svolos, V. Role of diet in prevention versus treatment of Crohn’s disease and ulcerative colitis. Frontline Gastroenterol. 2024, 15, 247–257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gkikas, K.; Svolos, V.; Hansen, R.; Russell, R.K.; Gerasimidis, K. Take-Home Messages from 20 Years of Progress in Dietary Therapy of Inflammatory Bowel Disease. Ann. Nutr. Metab. 2023, 79, 476–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gerasimidis, K.; Godny, L.; Sigall-Boneh, R.; Svolos, V.; Wall, C.; Halmos, E. Current recommendations on the role of diet in the aetiology and management of IBD. Frontline Gastroenterol. 2022, 13, 160–167. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uhlig, H.H.; Schwerd, T.; Koletzko, S.; Shah, N.; Kammermeier, J.; Elkadri, A.; Ouahed, J.; Wilson, D.C.; Travis, S.P.; Turner, D.; et al. The Diagnostic Approach to Monogenic Very Early Onset Inflammatory Bowel Disease. Gastroenterology 2014, 147, 990–1007.e1003. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, J.H.; Brant, S.R. Recent insights into the genetics of inflammatory bowel disease. Gastroenterology 2011, 140, 1704–1712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loddo, I.; Romano, C. Inflammatory Bowel Disease: Genetics, Epigenetics, and Pathogenesis. Front. Immunol. 2015, 6, 551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, J.Z.; van Sommeren, S.; Huang, H.; Ng, S.C.; Alberts, R.; Takahashi, A.; Ripke, S.; Lee, J.C.; Jostins, L.; Shah, T.; et al. Association analyses identify 38 susceptibility loci for inflammatory bowel disease and highlight shared genetic risk across populations. Nat. Genet. 2015, 47, 979–986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGovern, D.P.; Kugathasan, S.; Cho, J.H. Genetics of Inflammatory Bowel Diseases. Gastroenterology 2015, 149, 1163–1176.e1162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- IBD in EPIC Study Investigators; Tjonneland, A.; Overvad, K.; Bergmann, M.M.; Nagel, G.; Linseisen, J.; Hallmans, G.; Palmqvist, R.; Sjodin, H.; Hagglund, G.; et al. Linoleic acid, a dietary n-6 polyunsaturated fatty acid, and the aetiology of ulcerative colitis: A nested case–control study within a European prospective cohort study. Gut 2009, 58, 1606–1611. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barbalho, S.M.; Goulart Rde, A.; Quesada, K.; Bechara, M.D.; de Carvalho Ade, C. Inflammatory bowel disease: Can omega-3 fatty acids really help? Ann. Gastroenterol. 2016, 29, 37–43. [Google Scholar] [PubMed]
- John, S.; Luben, R.; Shrestha, S.S.; Welch, A.; Khaw, K.-T.; Hart, A.R. Dietary n-3 polyunsaturated fatty acids and the aetiology of ulcerative colitis: A UK prospective cohort study. Eur. J. Gastroenterol. Hepatol. 2010, 22, 602–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ananthakrishnan, A.N.; Khalili, H.; Konijeti, G.G.; Higuchi, L.M.; de Silva, P.; Korzenik, J.R.; Fuchs, C.S.; Willett, W.C.; Richter, J.M.; Chan, A.T. A Prospective Study of Long-term Intake of Dietary Fiber and Risk of Crohn’s Disease and Ulcerative Colitis. Gastroenterology 2013, 145, 970–977. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sugihara, K.; Kamada, N. Diet–Microbiota Interactions in Inflammatory Bowel Disease. Nutrients 2021, 13, 1533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moller, F.T.; Andersen, V.; Wohlfahrt, J.; Jess, T. Familial risk of inflammatory bowel disease: A population-based cohort study 1977–2011. Off. J. Am. Coll. Gastroenterol. 2015, 110, 564–571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santos, M.P.C.; Gomes, C.; Torres, J. Familial and ethnic risk in inflammatory bowel disease. Ann. Gastroenterol. 2018, 31, 14–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zallot, C.; Quilliot, D.; Chevaux, J.-B.; Peyrin-Biroulet, C.; Guéant-Rodriguez, R.M.; Freling, E.; Collet-Fenetrier, B.; Williet, N.; Ziegler, O.; Bigard, M.-A.; et al. Dietary Beliefs and Behavior Among Inflammatory Bowel Disease Patients. Inflamm. Bowel Dis. 2013, 19, 66–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Vries, J.H.; Dijkhuizen, M.; Tap, P.; Witteman, B.J. Patient’s Dietary Beliefs and Behaviours in Inflammatory Bowel Disease. Dig. Dis. 2018, 37, 131–139. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, H.F.; Shannon, S.E. Three approaches to qualitative content analysis. Qual. Health Res. 2005, 15, 1277–1288. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Janz, N.K.; Becker, M.H. The Health Belief Model: A decade later. Health Educ. Q. 1984, 11, 1–47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bingham, A.J.; Witkowsky, P. Deductive and inductive approaches to qualitative data analysis. Anal. Interpret. Qual. Data After Interview 2021, 1, 133–146. [Google Scholar]
- Hooker, G.W.; Peay, H.; Erby, L.; Bayless, T.; Biesecker, B.B.; Roter, D.L. Genetic literacy and patient perceptions of IBD testing utility and disease control: A randomized vignette study of genetic testing. Inflamm. Bowel Dis. 2014, 20, 901–908. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wintjens, D.S.J.; de Jong, M.J.; van der Meulen-de Jong, A.E.; Romberg-Camps, M.J.; Becx, M.C.; Maljaars, J.P.; van Bodegraven, A.A.; Mahmmod, N.; Markus, T.; Haans, J.; et al. Novel Perceived Stress and Life Events Precede Flares of Inflammatory Bowel Disease: A Prospective 12-Month Follow-Up Study. J. Crohn’s Colitis 2019, 13, 410–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knowles, S.R.; Graff, L.A.; Wilding, H.; Hewitt, C.; Keefer, L.; Mikocka-Walus, A. Quality of Life in Inflammatory Bowel Disease: A Systematic Review and Meta-analyses-Part I. Inflamm. Bowel Dis. 2018, 24, 742–751. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riggott, C.; Ford, A.C.; Gracie, D.J. Review article: The role of the gut–brain axis in inflammatory bowel disease and its therapeutic implications. Aliment. Pharmacol. Ther. 2024, 60, 1200–1214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Y.; Chen, X.; Lin, S.; Huang, S.; Li, L.; Hong, M.; Li, J.; Ma, L.; Ma, J. Effects of psychological stress on inflammatory bowel disease via affecting the microbiota-gut-brain axis. Chin. Med. J. 2025, 138, 664–677. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viazis, N.; Mantzaris, G.; Karmiris, K.; Polymeros, D.; Kouklakis, G.; Maris, T.; Karagiannis, J.; Karamanolis, D.G. Inflammatory bowel disease: Greek patients’ perspective on quality of life, information on the disease, work productivity and family support. Ann. Gastroenterol. 2013, 26, 52–58. [Google Scholar] [PubMed]
- Popov, J.; Farbod, Y.; Chauhan, U.; Kalantar, M.; Hill, L.; Armstrong, D.; Halder, S.; Marshall, J.K.; Moayyedi, P.; Kaasalainen, S. Patients’ Experiences and Challenges in Living with Inflammatory Bowel Disease: A Qualitative Approach. Clin. Exp. Gastroenterol. 2021, 14, 123–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guida, L.; Di Giorgio, F.M.; Busacca, A.; Carrozza, L.; Ciminnisi, S.; Almasio, P.L.; Di Marco, V.; Cappello, M. Perception of the Role of Food and Dietary Modifications in Patients with Inflammatory Bowel Disease: Impact on Lifestyle. Nutrients 2021, 13, 759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hou, J.K.; Abraham, B.; El-Serag, H. Dietary Intake and Risk of Developing Inflammatory Bowel Disease: A Systematic Review of the Literature. Am. J. Gastroenterol. 2011, 106, 563–573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tayyem, R.F.; Qalqili, T.R.; Ajeen, R.; Rayyan, Y.M. Dietary Patterns and the Risk of Inflammatory Bowel Disease: Findings from a Case-Control Study. Nutrients 2021, 13, 1889. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meyer, A.; Agrawal, M.; Savin-Shalom, E.; Wong, E.C.L.; Levinson, C.; Gold, S.; Narula, N.; Colombel, J.-F.; Carbonnel, F. Impact of diet on inflammatory bowel disease risk: Systematic review, meta-analyses and implications for prevention. eClinicalMedicine 2025, 86, 103353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khalili, H.; Håkansson, N.; Chan, S.S.; Chen, Y.; Lochhead, P.; Ludvigsson, J.F.; Chan, A.T.; Hart, A.R.; Olén, O.; Wolk, A. Adherence to a Mediterranean diet is associated with a lower risk of later-onset Crohn’s disease: Results from two large prospective cohort studies. Gut 2020, 69, 1637–1644. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bischoff, S.C.; Bager, P.; Escher, J.; Forbes, A.; Hébuterne, X.; Hvas, C.L.; Joly, F.; Klek, S.; Krznaric, Z.; Ockenga, J.; et al. ESPEN guideline on Clinical Nutrition in inflammatory bowel disease. Clin. Nutr. 2023, 42, 352–379. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Champion, V.L.; Skinner, C.S. The health belief model. In Health Behavior and Health Education: Theory, Research, and Practice, 4th ed.; Glanz, K., Rimer, B.K., Viswanath, K., Eds.; Jossey-Bass/Wiley: San Francisko, CA, USA, 2008; pp. 45–65. [Google Scholar]
- Schoefs, E.; Vermeire, S.; Ferrante, M.; Sabino, J.; Lambrechts, T.; Avedano, L.; Haaf, I.; De Rocchis, M.S.; Broggi, A.; Sajak-Szczerba, M.; et al. What are the Unmet Needs and Most Relevant Treatment Outcomes According to Patients with Inflammatory Bowel Disease? A Qualitative Patient Preference Study. J. Crohn’s Colitis 2023, 17, 379–388. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Day, A.S.; Vanderstappen, J.; Sandall, A.; Svolos, V.; Shabat, C.S. From Kitchen to Inflammatory Bowel Disease (IBD) Clinic: Transforming the Role of Dietitians in IBD Care. A Narrative Review by Dietitians with Expertise in IBD. JCC Plus 2026, 1, e70007. [Google Scholar] [CrossRef] [Scilit]
- Gkikas, K.; Wan, M.; Svolos, V.; Nichols, B.; Hansen, R.; Russell, R.K.; Gerasimidis, K. YouTube as a Source of Information for Food, Diet-Related Items, and Advisory Comments for the Management of Inflammatory Bowel Disease. Inflamm. Bowel Dis. 2024, 30, 347–356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Creswell, J.W.; Plano Clark, V.L. Designing and Conducting Mixed Methods Research, 2nd ed.; SAGE: Los Angeles, CA, USA, 2011. [Google Scholar]
- Morse, J.M.; Niehaus, L. Mixed Method Design: Principles and Procedures; Left Coast Press: Walnut Creek, CA, USA, 2009. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.