


Abstract
Background and Aim: Exportin 1 (XPO1) is the principal nuclear export receptor for numerous tumor-suppressor proteins, regulatory factors, and selected oncogenic mRNAs, and it has emerged as a therapeutically relevant vulnerability in multiple myeloma (MM). Selinexor, a first-in-class oral selective inhibitor of nuclear export (SINE), targets XPO1 and has demonstrated antimyeloma activity both as a doublet and in combination with established therapeutic agents. This review summarizes the biological rationale and molecular mechanisms of XPO1 inhibition, the pharmacological basis of dose and schedule optimization, the clinical evidence supporting selinexor-based therapy, the positioning of XPO1 inhibition relative to BCMA-directed and T-cell-redirecting therapies, mechanisms of resistance and candidate predictive biomarkers, emerging next-generation XPO1 inhibitors, and practical considerations regarding toxicity management. Materials and Methods: A narrative review of the published literature on XPO1 biology and selinexor in MM was performed, with emphasis on preclinical mechanistic studies, prospective clinical trials, and studies addressing resistance, biomarkers, pharmacokinetics, pharmacodynamics, and treatment-related toxicity. Particular attention was given to pivotal and clinically relevant studies evaluating selinexor-based regimens, including Selinexor Treatment of Refractory Myeloma (STORM), BOSTON, and combination cohorts from the STOMP program, together with recent translational studies expanding the molecular framework of XPO1 inhibition. Results: XPO1 inhibition exerts pleiotropic antimyeloma effects through nuclear retention and reactivation of tumor-suppressor proteins, suppression of NF-κB-dependent signaling and oncogenic mRNA translation, enhancement of glucocorticoid signaling, and disruption of cellular protein homeostasis. More recent findings implicate treatment-induced XPO1 degradation through ubiquitin-regulatory mechanisms and suppression of lipid biosynthesis through the Lipin1–SREBP axis. Clinically, selinexor demonstrated activity in heavily pretreated triple-class refractory MM and subsequently showed improved efficacy when incorporated into once-weekly combination regimens, particularly with bortezomib and dexamethasone. Additional combinations with carfilzomib, pomalidomide, lenalidomide, and daratumumab have demonstrated clinically meaningful activity in selected relapsed/refractory multiple myeloma (RRMM) populations. The clinical pharmacology of selinexor—a short plasma half-life of 6–8 h, dose-proportional exposure, and pharmacodynamic effects that outlast plasma concentrations—provides the rationale for intermittent once-weekly dosing, and clinical development has progressively shifted from twice-weekly 80 mg schedules toward lower-dose once-weekly regimens (40–100 mg) supported by proactive toxicity management. In the current treatment landscape, selinexor-based regimens are unlikely to displace BCMA-directed chimeric antigen receptor (CAR) T-cell therapies or bispecific antibodies in eligible patients, but they retain a distinct role for patients who cannot access, are ineligible for, or progress after T-cell-redirecting therapy. However, prospective data in the post-BCMA setting are still lacking. Candidate determinants of response and resistance include XPO1 Cys528 alterations, hnRNPU, USP7-dependent regulation of XPO1 stability, and Lipin1–SREBP signaling; these differ substantially in the strength of the supporting evidence, and none is currently prospectively validated for patient selection. Beyond selinexor, second-generation and non-SINE XPO1 inhibitors such as eltanexor and SL-801 remain in early clinical development. Preclinical findings suggest that selinexor may favorably modulate T-cell and natural killer cell function, while limited clinical observations support further investigation of its use as holding or bridging therapy before CAR T-cell therapy. Preservation of T-cell fitness and improvement in subsequent clinical outcomes remain unproven. Treatment-related cytopenias, gastrointestinal toxicity, fatigue, and hyponatremia remain important but can frequently be addressed through proactive supportive care and dose optimization. Conclusions: XPO1 inhibition represents a mechanistically distinct therapeutic strategy in MM, and selinexor has established clinical activity across multiple relapsed/refractory settings. Increasing use of lower-dose, once-weekly combination strategies has improved its therapeutic feasibility, while emerging insights into XPO1 degradation, metabolic regulation, and molecular determinants of response are broadening the biological framework of this drug class. Within an increasingly crowded therapeutic landscape, the most plausible current role of selinexor-based therapy is as an oral, immediately available option for patients who are ineligible for, cannot access, or have progressed after BCMA-directed and T-cell-redirecting treatments. Prospective biomarker validation, randomized dose optimization, and clarification of treatment sequencing will be important for defining the future role of XPO1-directed therapy in MM.
Keywords:
multiple myeloma; selinexor; XPO1; exportin 1; nuclear export; SINE; biomarkers; drug resistance 1. Biology of XPO1 and the Nuclear Export Mechanism
Macromolecular transport between the nucleus and cytoplasm in eukaryotic cells plays a fundamental role in the regulation of gene expression, the cell cycle, the DNA damage response, apoptosis, and cellular homeostasis. This molecular trafficking occurs through nuclear pore complexes, whereas the regulated transport of proteins and large macromolecular complexes is largely mediated by nuclear transport receptors belonging to the karyopherin family. XPO1, also known as chromosome region maintenance 1, is the major nuclear export receptor in the cell and controls the transport of numerous proteins as well as various RNA species from the nucleus to the cytoplasm [1].
1.1. XPO1 Structure and Cargo Recognition
XPO1 is an evolutionarily conserved protein with a molecular weight of approximately 120 kDa. Structurally, it consists of 21 consecutive Huntingtin, elongation factor 3, A subunit of protein phosphatase 2A, and TOR1 repeats. The superhelical architecture formed by these Huntingtin, elongation factor 3, A subunit of protein phosphatase 2A, and TOR1 repeats enables XPO1 to interact with cargo proteins, Ran-GTP, and other components of the nuclear transport machinery [1]. A substantial proportion of proteins transported by XPO1 contain short amino acid sequences termed nuclear export signals (NES). Classical NES motifs are enriched in hydrophobic amino acids, particularly leucine, as well as isoleucine, valine, phenylalanine, and methionine. NES-containing cargos bind to the hydrophobic NES-binding groove located on the outer convex surface of XPO1 [2].
Crystallographic studies have demonstrated that NES motifs with different amino acid sequences and secondary structures can engage the same hydrophobic binding region on XPO1. Five hydrophobic pockets within this region accommodate the hydrophobic side chains of the NES. The ability of different NES motifs to adopt distinct backbone conformations while engaging the same hydrophobic pockets explains how XPO1 can recognize highly diverse NES sequences [1,3,4]. Cys528, located within the NES-binding groove, is a critical residue for the pharmacological targeting of XPO1. SINE compounds target Cys528 within the cargo-binding pocket of XPO1, thereby preventing the binding and nuclear export of NES-containing cargos. The demonstration that the XPO1 C528S mutation confers resistance to selinexor further confirms the critical role of Cys528 in the selinexor–XPO1 interaction [5].
1.2. Ran-GTP-Dependent Nuclear Export Cycle
XPO1-mediated nuclear export depends on the Ran-GTP/Ran-GDP gradient generated by the small GTPase Ran (Ras-related nuclear protein). In the nucleus, the chromatin-associated guanine nucleotide exchange factor regulator of chromosome condensation 1 maintains a high concentration of GTP-bound Ran. Within the nucleus, XPO1 binds cooperatively to Ran-GTP and an NES-containing cargo to form the XPO1–Ran-GTP–cargo ternary complex [1]. This export complex traverses the nuclear pore complex and reaches the cytoplasm. In the cytoplasm, Ran GTPase-activating protein 1 and Ran-binding protein 1 facilitate Ran-GTP hydrolysis and disassembly of the export complex. Consequently, the cargo is released into the cytoplasm, whereas XPO1 returns to the nucleus to participate in another transport cycle. Thus, the high Ran-GTP concentration in the nucleus and low concentration in the cytoplasm provide directionality to XPO1-mediated nuclear transport [1] (Figure 1).
Figure 1.
XPO1-mediated Ran-GTP-dependent nuclear export cycle and the mechanism of XPO1 inhibition by selinexor. The figure is original and was prepared by the authors.
1.3. Biological Significance of XPO1-Mediated Nuclear Export
The biological significance of XPO1 extends beyond the physical translocation of macromolecules from the nucleus to the cytoplasm. By controlling the subcellular localization of numerous regulatory proteins and RNA species, XPO1 influences multiple cellular processes, including cell-cycle progression, DNA-damage responses, transcriptional regulation, apoptosis, and cellular survival [1]. Dysregulation of XPO1-mediated nuclear export has been increasingly implicated in malignant transformation and tumor progression. XPO1 is overexpressed in a variety of hematologic and solid malignancies, where excessive nuclear export can result in the aberrant cytoplasmic localization and functional inactivation of tumor-suppressor and growth-regulatory proteins. Because the biological activity of many of these proteins depends on their nuclear localization, their inappropriate export may simultaneously impair cell-cycle checkpoints, apoptotic signaling, and cellular responses to genomic stress [6,7]. Importantly, XPO1 functions as a central regulatory node rather than as a component of a single oncogenic signaling pathway. Consequently, pharmacologic disruption of XPO1-mediated export has the potential to restore the nuclear localization and activity of multiple tumor-suppressive cargos while concurrently interfering with survival-promoting mechanisms. This pleiotropic biological effect provides a strong rationale for targeting XPO1 in malignancies characterized by dependence on dysregulated nuclear export [7].
1.4. Pharmacologic Targetability of XPO1
The structural and functional features of the NES-binding groove described above establish XPO1 as a druggable component of the nuclear transport machinery. Because substitution of Cys528 with serine (C528S) markedly reduces sensitivity to SINE compounds, the antitumor activity of these agents can be attributed to direct engagement of XPO1 rather than to off-target effects, and this genetic evidence provided the molecular foundation for SINE development [8]. Among these agents, selinexor (KPT-330) became the first XPO1 inhibitor to achieve clinical implementation. Its pharmacologic characteristics and the downstream molecular consequences of XPO1 inhibition are discussed in detail in the subsequent sections [9].
1.5. Scope, Novelty, and Added Value of This Review
Several reviews on XPO1 inhibition and on selinexor in multiple myeloma have been published, and the present article is intended to complement rather than duplicate them. Gandhi et al. provided the first comprehensive synthesis of the biological rationale for targeting XPO1-mediated nuclear export in myeloma [10], whereas Podar et al. focused on the pharmacology and the early clinical development of selinexor [11]. Balasubramanian et al. reviewed selective inhibitors of nuclear export across hematological neoplasms [12], Huang et al. summarized the clinical trials conducted in relapsed/refractory and newly diagnosed disease [13], and Gay et al. have recently discussed the strategic use of selinexor in an evolving treatment landscape [14].
The added value of the present review can be defined in seven points. First, it integrates structural biology, nucleocytoplasmic transport physiology and plasma-cell biology into a single mechanistic argument for XPO1 dependency in myeloma (Section 1 and Section 2 and Table 1), rather than presenting the mechanism of action as background information. Second, it adopts a pharmacology-first perspective: exposure–response relationships, the dissociation between plasma exposure and the duration of functional target inhibition, dose and schedule optimization across the 40–100 mg once-weekly range, and the resulting widening of the therapeutic window are discussed explicitly (Section 3 and Table 2). Third, it compiles the clinical evidence trial by trial, presenting the treated population, the exact regimen and schedule, the reported efficacy and the principal grade ≥ 3 toxicities side by side (Table 3). Fourth, it grades the proposed mechanisms of resistance and the candidate biomarkers of response according to the strength of the supporting evidence and states what would be required for clinical qualification. Fifth, it provides a practice-oriented account of supportive care, including nutritional and metabolic management (Section 7.2, Section 7.3, Section 7.4, Section 7.5, Section 7.6, Section 7.7 and Section 7.8), which is usually absent from molecularly oriented reviews. Sixth, it positions XPO1 inhibition explicitly against BCMA-directed and T-cell-redirecting therapies, defines the patient populations most likely to benefit (Section 5.7 and Table 4), and, separately, examines the evidence that selinexor spares T-cell fitness and may therefore be used as holding or bridging therapy around those treatments rather than only as an alternative to them (Section 5.8). Seventh, it compares the clinically evaluated and emerging XPO1 inhibitors in a structured manner (Section 8) and formulates a pharmacology- and biomarker-guided development agenda (Section 9).
To distinguish clinical observations from experimental mechanisms and candidate biomarkers, this review uses three descriptive evidence categories. Tier A denotes clinical evidence of therapeutic activity or pharmacodynamic effects directly documented in treated patients. Clinical efficacy does not, by itself, validate a proposed molecular mechanism or establish pharmacological synergy. Tier B denotes experimental mechanistic evidence from cell lines, animal models, or patient-derived cells studied ex vivo; the use of patient-derived material alone does not constitute clinical validation. Tier C denotes exploratory associations and candidate predictive biomarkers derived from correlative analyses that have not established clinical utility for treatment selection. These categories describe the nature of the evidence rather than a formal hierarchy of study quality. Where a finding has support from more than one category, the experimental and clinical components are described separately. All figures and tables in this review are original and were prepared by the authors from the cited sources; no material has been reproduced from copyrighted publications.
2. Biological and Therapeutic Significance of XPO1 in Multiple Myeloma
In MM, the proliferation and survival of malignant plasma cells are supported not only by alterations in intracellular signaling pathways but also by complex interactions with the bone marrow microenvironment. Because inhibition of XPO1-mediated nuclear export can simultaneously alter the intracellular localization of multiple tumor suppressor and survival-regulatory proteins, it has emerged as a potential therapeutic strategy in MM [7].
2.1. XPO1 Expression and Its Clinical and Biological Relevance in MM
Evidence from patient-derived material supports a biologically relevant role for XPO1 in plasma-cell malignancies. Tai et al. found elevated XPO1/CRM1 expression in MM and plasma cell leukemia samples, with particularly high levels in bortezomib-resistant cells [7]. Higher expression was also linked to a greater burden of lytic bone disease and inferior survival. Consistent with these clinical associations, experimental depletion of XPO1 reduced MM-cell viability, indicating that XPO1 contributes functionally to malignant plasma-cell survival [7]. XPO1 blockade exerts antimyeloma activity through several convergent mechanisms. In preclinical models, SINE compounds retain XPO1 cargo proteins, including tumor suppressors, within the nucleus, a change associated with cell-cycle arrest and apoptosis. XPO1 inhibition also reduces c-MYC and MCL-1 expression and attenuates nuclear factor kappa B (NF-κB) activity. Consequently, XPO1 represents a distinct therapeutic node through which several pathways supporting MM-cell growth and survival can be disrupted simultaneously [7,15].
2.2. Plasma-Cell Biology and the Biological Basis of XPO1 Dependency in Multiple Myeloma
The pronounced sensitivity of malignant plasma cells to XPO1 inhibition is unlikely to be explained by target expression alone and is better understood in the context of plasma-cell biology. Plasma cells are terminally differentiated, professional secretory cells that devote a large proportion of their transcriptional and translational output to the synthesis, assembly, and secretion of immunoglobulins. This secretory program imposes a continuous burden on the endoplasmic reticulum and requires constitutive engagement of the unfolded protein response, which is coordinated by the IRE1α–XBP1, PERK–ATF4, and ATF6 branches [16,17]. XBP1 is both a driver of plasma-cell differentiation and a dependency in MM cells, and its activity is required to sustain the expanded secretory apparatus [17]. Because immunoglobulin assembly and sustained unfolded protein response signaling depend on efficient proteasomal clearance of misfolded proteins, plasma cells operate close to the threshold of proteotoxic stress, which underlies their exceptional sensitivity to proteasome inhibition [18]. XPO1 inhibition converges on the same vulnerability: it limits the cytoplasmic availability of transcripts encoding survival and secretory-pathway proteins, promotes the nuclear retention of stress-responsive transcription factors, and, in combination with proteasome inhibition, exacerbates the accumulation of misfolded protein [7,15].
Plasma-cell identity is maintained by a highly interconnected transcriptional network in which IRF4, PRDM1/BLIMP1, XBP1, and MYC occupy central positions [17,19]. Several components of this network are short-lived and depend on continuous nucleocytoplasmic trafficking. The mRNA encoding c-MYC, for example, is exported through the XPO1–eIF4E pathway, so that XPO1 blockade reduces MYC translation at the same time as it retains MYC-antagonizing tumor suppressors in the nucleus [7,9,15]. IRF4 expression is likewise maintained by autoregulatory loops that are sensitive to perturbation of MYC- and NF-κB-dependent signaling [19]. Consequently, XPO1 inhibition does not merely add a second insult to an already stressed cell; it interferes with the transcriptional circuitry that sustains the malignant plasma-cell phenotype.
Plasma cells also place an unusually high demand on nucleocytoplasmic transport. Ribosome biogenesis requires the export of pre-60S and pre-40S subunits through the XPO1-dependent adaptors NMD3 and LTV1, and the RNA-binding protein hnRNPU, which regulates the localization of these factors and the translation of RAN and MDM2 mRNAs, determines the sensitivity of MM cells to selinexor [20]. In parallel, the large volume of immunoglobulin transcripts that must reach the cytoplasm makes plasma cells particularly dependent on mRNA export pathways. This combination of a high transport burden and a limited capacity to compensate for its interruption may explain why XPO1 inhibition produces a more pronounced effect in plasma-cell malignancies than in many other tumor types [7,20].
The tumor-suppressor barriers that would normally limit the consequences of oncogenic signaling are also frequently compromised in MM. Deletion of 17p and TP53 alterations define high-risk disease, and gain of 1q21, t(4;14), and t(14;16) identify additional adverse subgroups [21]. Because XPO1 inhibition restores the nuclear localization of p53, p21, p27, FOXO-family proteins, and IκBα, its activity does not depend on intact p53 signaling; instead, it re-engages several partially redundant growth-suppressive and apoptotic programs simultaneously [7,9,15].
The bone marrow microenvironment reinforces this dependency. Adhesion of MM cells to bone marrow stromal cells activates NF-κB-dependent survival signaling and confers adhesion-mediated drug resistance, and the same niche supports MM-cell growth through interleukin-6, insulin-like growth factor 1, and BAFF/APRIL signaling [22,23]. SINE compounds retain cytotoxicity in coculture models with stromal cells and osteoclasts and suppress RANKL-induced NF-κB and NFATc1 activation in osteoclast precursors, indicating that XPO1 inhibition acts on both tumor cells and the cellular components of the bone marrow niche [7].
Taken together, these observations indicate that the dependence of MM cells on XPO1 reflects the convergence of four features: an exceptionally high requirement for mRNA and ribosomal subunit export imposed by immunoglobulin secretion; a transcriptional program that relies on short-lived, transport-sensitive regulators; a proteotoxic and endoplasmic reticulum stress load that is already close to the threshold of tolerance; and frequent loss of tumor-suppressor checkpoints. This framework also implies that the magnitude of “transport dependency” may differ between patients, providing a conceptual basis for the biomarker strategies discussed in Section 6.
2.3. Tumor-Suppressor Retention and MM Cell Survival
A central consequence of XPO1 inhibition in MM is the restoration of nuclear localization of tumor-suppressor and growth-regulatory proteins. Preclinical studies have demonstrated that selective inhibitors of nuclear export retain XPO1 cargo proteins within the nucleus, thereby restoring tumor-suppressive functions that are compromised by excessive nuclear export. This redistribution is associated with cell-cycle arrest and induction of apoptosis in malignant plasma cells [7]. The antimyeloma effects of XPO1 inhibition are therefore intrinsically pleiotropic. Rather than targeting a single oncogenic driver, inhibition of nuclear export simultaneously alters the intracellular localization and functional activity of multiple proteins involved in proliferation, survival, and apoptosis. In parallel, XPO1 inhibition reduces the expression of key survival-associated proteins, including c-MYC and MCL-1, further contributing to suppression of myeloma-cell viability. These observations provide a mechanistic link between increased XPO1 activity in MM and the survival advantage of malignant plasma cells, while supporting nuclear export as a therapeutically actionable vulnerability [7].
2.4. XPO1–IκBα–NF-κB Axis and PI Resistance
NF-κB signaling contributes to myeloma-cell survival and resistance to proteasome inhibitors. Preclinical studies indicate that XPO1 inhibition can restore sensitivity to bortezomib and carfilzomib, in part through nuclear retention of IκBα and suppression of NF-κB activity [15]. The experimental evidence and implications for combination therapy are discussed in Section 4.1.
2.5. Bone Marrow Microenvironment and Myeloma Bone Disease
The effects of XPO1 inhibition are not restricted to malignant plasma cells. SINE compounds retain cytotoxic activity when MM cells are cocultured with bone marrow stromal cells or osteoclasts. This suggests that the antimyeloma activity of XPO1 inhibition can persist despite protective signals provided by the bone marrow microenvironment. XPO1 inhibition also has biological effects relevant to myeloma bone disease. SINE compounds suppress receptor activator of nuclear factor κB ligand (RANKL)-induced NF-κB and nuclear factor of activated T cells 1 (NFATc1) activation, thereby inhibiting osteoclastogenesis and bone resorption, while exerting more limited effects on osteoblasts and bone marrow stromal cells. In in vivo models of MM-associated bone lesions, XPO1 inhibition reduced tumor burden and bone lysis and prolonged survival. These findings suggest that targeting XPO1 may simultaneously affect both malignant plasma cells and microenvironmental mechanisms contributing to MM bone disease [7].
2.6. GR–REDD1–mTORC1 Axis and Synergy with Dexamethasone
Preclinical studies indicate that selinexor enhances glucocorticoid receptor (GR) expression and potentiates dexamethasone-induced antimyeloma activity through GR-dependent REDD1 induction and suppression of mTORC1 signaling [24]. This interaction provides a biological rationale for incorporating dexamethasone into selinexor-containing regimens. The supporting experimental evidence is discussed in Section 4.2. The major biological effects of XPO1 inhibition in MM are illustrated in Figure 2.
Figure 2.
Major biological effects of XPO1 inhibition in multiple myeloma. The figure is original and was prepared by the authors. Abbreviations: XPO1, exportin 1; GR, glucocorticoid receptor; REDD1, regulated in development and DNA damage responses 1; mTORC1, mechanistic target of rapamycin complex 1; IκBα, inhibitor of nuclear factor kappa B alpha; NF-κB, nuclear factor kappa B; PI, proteasome inhibitor; RANKL, receptor activator of nuclear factor κB ligand; NFATc1, nuclear factor of activated T cells 1; MM, multiple myeloma.
2.7. Positioning XPO1 as a Therapeutic Target
Taken together, the biological and preclinical evidence summarized above positions XPO1 as a therapeutically relevant vulnerability in MM. Increased XPO1 expression and its association with adverse disease characteristics, together with the reduction in myeloma-cell viability following XPO1 suppression, support a functional dependence of malignant plasma cells on dysregulated nuclear export [7]. The therapeutic rationale for XPO1 inhibition is further strengthened by its ability to simultaneously restore the nuclear localization of tumor-suppressor proteins, suppress survival-associated mechanisms including c-MYC, MCL-1, and NF-κB signaling, and interfere with protective interactions within the bone marrow microenvironment. In addition, inhibition of osteoclastogenic signaling provides a potential biological link between XPO1 targeting and myeloma-associated bone disease. The ability of XPO1 inhibition to restore sensitivity to proteasome inhibitors (PIs) through the IκBα–NF-κB axis and to enhance dexamethasone-induced cell death through GR–REDD1–mTORC1 signaling further provides a mechanistic rationale for combination-based therapeutic strategies [7,15,24]. Collectively, these observations established the biological foundation for the clinical development of selective inhibitors of nuclear export in MM. Selinexor, the first-in-class clinically implemented XPO1 inhibitor, represents the principal translation of this therapeutic concept and is discussed in detail in the following section [9].
Table 1.
Major XPO1-Related Biological Mechanisms in MM and Effects of XPO1 Inhibition.
3. Selinexor: Pharmacology and Molecular Mechanisms of Action
3.1. Pharmacological and Pharmacokinetic Profile
Selinexor (KPT-330) is an orally bioavailable, small-molecule SINE and the first agent of this class to achieve clinical implementation. Its principal pharmacologic target is XPO1, the major nuclear export receptor responsible for the transport of numerous proteins and RNA species from the nucleus to the cytoplasm [9,25]. Following oral administration, selinexor reaches maximum plasma concentrations within approximately 2–4 h and has a terminal elimination half-life of approximately 6–8 h. Pharmacokinetic analyses indicate a generally predictable exposure profile across clinically relevant dosing schedules. Selinexor is widely distributed and highly bound to plasma proteins. These pharmacokinetic properties, together with the persistence of its downstream pharmacodynamic effects on nuclear export, have supported the development of intermittent dosing schedules, including once- and twice-weekly administration [25].
3.2. Pharmacokinetic–Pharmacodynamic Relationships and the Rationale for Intermittent Dosing
The clinical pharmacology of selinexor has been characterized in detail and provides the basis for its current dosing strategies. After oral administration, selinexor is absorbed relatively rapidly, with a time to maximum plasma concentration of approximately 2–4 h, and it has a terminal elimination half-life of approximately 6–8 h. Exposure is dose proportional across the clinically relevant dose range and does not accumulate appreciably at steady state [25]. After a single 80 mg dose, the mean maximum plasma concentration is approximately 680 ng/mL and the mean area under the concentration–time curve is approximately 5400 ng·h/mL; plasma protein binding is approximately 95%, the apparent volume of distribution is approximately 133 L, and apparent clearance is approximately 18.6 L/h [26]. Population pharmacokinetic analyses identified body weight and sex as covariates, although their effects on selinexor exposure were not considered clinically meaningful [25]. No clinically significant pharmacokinetic differences have been observed in patients with mild or moderate hepatic impairment or with renal impairment corresponding to a creatinine clearance of 15–89 mL/min. However, severe hepatic impairment increases total and free selinexor exposure by approximately 32%, and a reduced starting dose is recommended. The effects of end-stage renal disease (creatinine clearance < 15 mL/min) and hemodialysis on selinexor pharmacokinetics remain unknown [26]. Complementary clinical evidence from the BOSTON renal impairment subgroup analysis supports the feasibility of selinexor–bortezomib–dexamethasone in appropriately selected patients with renal impairment [27].
The pharmacodynamic behavior of selinexor differs substantially from its pharmacokinetic profile. Target engagement can be assessed by measuring the binding of SINE compounds to XPO1 in cell lysates with fluorescent probes, but the low XPO1 expression in peripheral blood mononuclear cells limits their usefulness as a surrogate tissue for clinical pharmacodynamic monitoring, and no XPO1 occupancy threshold has been prospectively linked to clinical response [28]. Functional inhibition of nuclear export nevertheless persists well beyond the decline in plasma concentrations, because drug-bound XPO1 recovers slowly [25,28]. This dissociation between exposure and effect is the principal pharmacological rationale for intermittent dosing: schedules that generate high peak exposure followed by a drug-free interval can sustain target inhibition while allowing the bone marrow and gastrointestinal epithelium to recover [25,29].
Exposure–toxicity relationships are consistent with this model. Regulatory analyses found that higher selinexor exposure was associated with a higher overall incidence of adverse events, and, in the twice-weekly STORM schedule, almost all patients required dose modification (99.1%) and the median duration of treatment at the 80 mg twice-weekly dose was only 3.5 weeks [30]. An integrated safety analysis of 437 patients treated across phase 1 and phase 2/3 studies characterized nausea, vomiting, diarrhea, fatigue, decreased appetite, cytopenias, and hyponatremia as dose- and schedule-dependent and generally reversible [31]. Thrombocytopenia, hyponatremia, nausea, anorexia, and fatigue therefore represent the toxicities that most directly limit dose intensity, and they are managed through dose reduction, schedule modification, and proactive supportive care rather than through pharmacokinetic monitoring [29,32,33].
Because exposure varies only modestly with patient characteristics, and because the pharmacodynamic effect outlasts the pharmacokinetic profile, dose individualization in practice is driven by tolerability and by the observed depth of response rather than by measured drug concentrations [25,29]. This has practical implications: the starting dose, the dosing interval, and the intensity of supportive care should be selected according to baseline thrombocytopenia, nutritional and performance status, and the anticipated toxicity of the combination partner, and dose reductions should be applied early rather than after the emergence of severe toxicity [29,33].
3.3. Dose Optimization, Schedule Refinement, and the Therapeutic Window
The clinical development of selinexor illustrates a progressive widening of its therapeutic window through schedule refinement rather than dose escalation. The initial phase 1 evaluation used doses up to 60 mg/m2 (approximately 80 mg) twice weekly together with dexamethasone 20 mg twice weekly, a schedule associated with substantial gastrointestinal and hematologic toxicity [34,35]. The pivotal STORM study retained twice-weekly selinexor 80 mg because it was the highest dose considered tolerable in a triple-class refractory population; however, the median duration of response was 4.4 months and Grade ≥ 3 thrombocytopenia occurred in 58% of patients, indicating that this schedule operated close to the limit of tolerability [32].
The transition to once-weekly dosing was therefore driven by the pharmacology of the drug rather than by dose escalation. BOSTON established once-weekly selinexor 100 mg with once-weekly bortezomib and dexamethasone as an effective regimen in patients who had received one to three prior lines of therapy, with a median progression-free survival of 13.9 months [36]. Even with this schedule, however, dose reductions were required in 65% of patients, and the median final selinexor dose was 71.4 mg per week, indicating that the starting dose frequently exceeds the dose that can be sustained during long-term treatment [29].
Subsequent studies examined whether lower once-weekly doses could further improve the therapeutic index. In a pooled analysis of the SPd cohorts of the STOMP program and a companion study, once-weekly selinexor 40 mg with pomalidomide and dexamethasone produced a numerically longer median progression-free survival than the 60 mg schedule (18.4 versus 9.5 months) despite a lower objective response rate (50% versus 65%), and it was associated with a higher relative dose intensity (94.3% versus 77.6%) and a longer median duration of exposure (28 versus 22 weeks) [37]. Although these cohorts were small, non-randomized, and analyzed descriptively, the observation that a lower dose can be accompanied by more durable disease control supports the concept that treatment continuity and cumulative dose intensity over time may matter more than the immediate depth of response, and it has contributed to the increasing use of 40–60 mg once-weekly schedules in combination regimens [29,37].
Additional schedule modifications have been developed to improve early tolerability. Step-up dosing, in which selinexor is initiated at 60 mg weekly and increased by 20 mg per week to a target dose of 100 mg with prophylactic antiemetic therapy, was associated with a low rate of grade ≥ 2 gastrointestinal toxicity in a small retrospective series [38]. In routine practice, planned omission of the dose scheduled for the final week of a 35-day cycle (Day 29) provides an additional recovery interval and is consistent with the general trend toward lower-dose, intermittent schedules, although this approach has not been compared prospectively with the BOSTON schedule [29]. Patient-related factors such as baseline thrombocytopenia, nutritional status, performance status, and renal function should inform the starting dose and the intensity of supportive care, because they influence both tolerability and the likelihood of maintaining an effective dose over time [29,33].
In summary, the therapeutic window of selinexor has been widened primarily by reducing dose frequency and by integrating proactive supportive care, and the available evidence supports once-weekly dosing as the preferred schedule for combination regimens. Important pharmacological questions remain: the optimal once-weekly dose has not been defined prospectively for each combination partner; no validated measure of XPO1 occupancy is available for clinical use; and predictors of exposure-related toxicity have not been identified. Prospective studies incorporating pharmacodynamic sampling and randomized dose comparison would therefore be of considerable value [25,28,29].
3.4. Direct Target Engagement: Cys528 and XPO1 Inhibition
The primary molecular event underlying selinexor activity is direct engagement of XPO1 within its hydrophobic NES-binding groove. Selinexor interacts with the critical Cys528 residue within the cargo-binding pocket, thereby preventing productive binding of NES-containing cargos and disrupting XPO1-mediated nuclear export [1,28]. Unlike irreversible XPO1 inhibitors such as leptomycin B, selinexor forms a slowly reversible covalent interaction with Cys528. Functional blockade of the NES-binding groove consequently alters the intracellular distribution of a broad spectrum of XPO1 cargos, resulting in their nuclear retention and initiating multiple downstream antitumor effects. The central importance of Cys528 for SINE activity is further supported by experimental models in which substitution of this residue confers marked resistance to XPO1 inhibition [1,8].
3.5. Nuclear Retention of Tumor-Suppressor Proteins
A major downstream consequence of XPO1 inhibition is the nuclear retention and functional reactivation of tumor-suppressor and cell-cycle regulatory proteins. Selinexor prevents the XPO1-mediated export of cargos including p53, p21, p27, FOXO-family proteins, and retinoblastoma protein (Rb), thereby increasing their nuclear availability. Restoration of these nuclear tumor-suppressive functions can activate complementary antineoplastic programs. Increased p53 activity promotes pro-apoptotic signaling, including induction of PUMA and BAX, whereas restoration of p21- and p27-dependent cell-cycle control contributes to inhibition of cyclin-dependent kinase activity and G1/S cell-cycle arrest. Through simultaneous modulation of multiple XPO1 cargos, selinexor therefore produces a broader tumor-suppressive response than would be expected from inhibition of a single signaling pathway [7,9,15]. Selinexor also promotes nuclear retention of IκBα, resulting in suppression of NF-κB transcriptional activity. The biological relevance of this pathway in MM, particularly its contribution to proteasome-inhibitor resistance and combination therapy, is discussed in Section 2.
3.6. Suppression of Oncogenic mRNA Export and Translation
The mRNAs encoding several pro-survival proteins, including c-Myc, Cyclin D1, MCL-1, and cIAP, depend on the XPO1–eIF4E complex for their export from the nucleus to the cytoplasm. By inhibiting XPO1-mediated nuclear export, selinexor promotes the nuclear retention of these transcripts and consequently reduces their cytoplasmic translation and downstream oncoprotein expression. Because c-MYC and MCL-1 are among the shortest-lived of these proteins, their levels fall rapidly after XPO1 blockade, which contributes to the early onset of apoptosis observed in myeloma cells. The parallel suppression of NF-κB-dependent transcription through nuclear retention of IκBα is described in Section 2.4 and Section 3.5 and is not repeated here [7,9,15].
3.7. XPO1 Degradation Through the ASB8–USP7 Axis
Exposure to selinexor also promotes the proteasomal degradation of its molecular target, XPO1. Using cryo-electron microscopy, Wing et al. (2025) demonstrated that SINE compounds, including selinexor, expose a cryptic site on XPO1 that enables recruitment of ASB8, a substrate receptor of a Cullin-RING E3 ubiquitin ligase complex [39]. This allosteric, “molecular glue-like” mechanism promotes XPO1 ubiquitination and subsequent proteasomal degradation. This mechanism is complemented by an additional regulatory layer described by Wang et al. (2025): under physiological conditions, the deubiquitinase USP7 stabilizes XPO1 through deubiquitination, whereas selinexor disrupts the USP7–XPO1 interaction, thereby impairing XPO1 stabilization and facilitating its degradation [40]. Thus, the activity of selinexor extends beyond functional inhibition of XPO1-mediated nuclear export to include active depletion of the cellular XPO1 protein pool [39,40].
3.8. Lipin1–SREBP Axis and Metabolic Reprogramming
Recent evidence suggests that the antimyeloma activity of selinexor extends beyond the regulation of nuclear transport and classical survival pathways to include alterations in cellular lipid metabolism. Lipin1 has been identified as an XPO1-dependent nuclear export cargo, and inhibition of XPO1 by selinexor promotes the nuclear accumulation of Lipin1. Nuclear Lipin1 suppresses the transcriptional activity of sterol regulatory element-binding proteins (SREBPs), leading to reduced expression of key genes involved in lipid and cholesterol biosynthesis, including FASN, SCD, DHCR24, and FDPS. Consistent with these transcriptional changes, selinexor treatment reduces fatty-acid and cholesterol synthesis in MM cell lines and primary CD138+ myeloma cells. Genetic suppression experiments further support a functional role for Lipin1 in the inhibition of SREBP signaling and in determining sensitivity to selinexor, both in vitro and in murine xenograft models. Collectively, these findings identify the Lipin1–SREBP axis as an additional metabolic component of selinexor activity, expanding its mechanism of action beyond nuclear retention of tumor-suppressor proteins and suppression of classical oncogenic survival pathways [41].
3.9. Immunomodulatory Effects on the Tumor Microenvironment
Evidence has accumulated that the activity of selinexor is not confined to tumor cell-intrinsic mechanisms and extends to the cellular composition and functional state of the tumor immune microenvironment. In preclinical systems, XPO1 inhibition increases the activation of CD8+ T lymphocytes and natural killer cells, re-polarizes macrophages toward a less immunosuppressive phenotype, inhibits myeloid-derived suppressor cells, and lowers the concentration of pro-inflammatory cytokines; selinexor has additionally been reported to relieve inhibitory signaling in natural killer cells and to increase the immunogenicity of myeloma cells, including upregulation of BCMA [42,43]. Importantly, part of this evidence derives from patient material rather than from cell lines alone: in bone marrow samples obtained during clinical studies, selinexor treatment was associated with increased CD8 and granzyme B expression in T cells [43]. These observations are mechanistically relevant because they predict that XPO1 inhibition should preserve, rather than deplete, the endogenous T-cell compartment on which CAR T-cell therapy and bispecific antibodies depend. The direction of this effect distinguishes selinexor from alkylating agents and, to a lesser extent, from proteasome inhibitors, which have been associated with impaired T-cell fitness. Applying the evidence classification of Section 1.5, the cellular effects observed in preclinical models remain Tier B, whereas the pharmacodynamic changes documented in patient bone marrow approach Tier A; the clinical consequences of these immunomodulatory effects are considered in Section 5.8.
3.10. Integrated Mechanistic Model
The antimyeloma activity of selinexor reflects the coordinated disruption of multiple cellular processes rather than inhibition of a single oncogenic pathway. Direct engagement of XPO1 at Cys528 inhibits XPO1-mediated nuclear export, resulting in the nuclear retention and functional reactivation of tumor-suppressor and cell-cycle regulatory proteins. In parallel, nuclear retention of IκBα suppresses NF-κB transcriptional activity, while impaired export of oncogenic mRNAs reduces the translation of key survival-associated proteins, including c-Myc, Cyclin D1, MCL-1, and cIAP [44]. More recent findings have further expanded this mechanistic framework. Selinexor not only functionally inhibits XPO1 but also promotes depletion of the XPO1 protein pool through ubiquitin–proteasome-dependent mechanisms involving the USP7–XPO1 and CRL5–ASB8 regulatory axes. In addition, nuclear accumulation of Lipin1 suppresses SREBP-dependent transcription and lipid and cholesterol biosynthesis, revealing a metabolic component of XPO1 inhibition. Emerging evidence also suggests that selinexor may influence the tumor microenvironment through modulation of NK- and T-cell function and immune checkpoint expression, although the clinical relevance of these immunomodulatory effects remains to be established [39,42]. Collectively, these complementary mechanisms integrate alterations in nuclear transport, transcriptional regulation, apoptotic and cell-cycle control, oncogenic protein synthesis, protein homeostasis, and cellular metabolism. This pleiotropic mode of action provides a biological rationale for combining selinexor with agents targeting complementary vulnerabilities in MM and forms the mechanistic basis for the combination strategies discussed in the following section. Under the evidence framework defined in Section 1.5, experimental studies support Cys528-dependent target engagement [5,8], nuclear retention of tumor-suppressor proteins [7], inhibition of NF-κB signaling [15], XPO1 degradation through ASB8- and USP7-related mechanisms [39,40], and modulation of Lipin1–SREBP signaling [41]. These mechanistic findings are supported primarily by preclinical evidence (Tier B). Evidence obtained from patient-derived cells studied ex vivo remains experimental and should not be interpreted as clinical validation. Clinical trials establish the therapeutic activity of selinexor-containing regimens (Tier A), but do not establish the relative contribution of each proposed mechanism to clinical response [32,36]. Immunomodulatory findings should likewise be distinguished according to whether they arise from experimental models or observations directly documented in treated patients.
Table 2.
Pharmacologic and Pharmacokinetic Characteristics of Selinexor.
4. Preclinical Rationale for Combination Therapy
4.1. Synergy with Proteasome Inhibitors
The combination of selinexor with PIs, particularly bortezomib and carfilzomib, is supported by a strong mechanistic rationale centered on complementary inhibition of the IκBα–NF-κB signaling axis. NF-κB is a major regulator of myeloma-cell survival, proliferation, and treatment resistance, and its activity is tightly controlled by the endogenous inhibitor IκBα. Proteasome inhibition prevents the proteasomal degradation of IκBα, whereas selinexor inhibits XPO1-mediated nuclear export and promotes its nuclear retention. The combination therefore increases both the abundance and nuclear localization of IκBα, resulting in enhanced formation of IκBα–NF-κB complexes and more profound suppression of NF-κB transcriptional activity [15].
Preclinical studies have demonstrated that this interaction is particularly relevant in the setting of acquired PI resistance. Selinexor restored sensitivity to both bortezomib and carfilzomib in PI-resistant MM cell lines and enhanced apoptosis when combined with either PI. Importantly, similar sensitization was observed in myeloma cells obtained from patients with PI-refractory disease, supporting the translational relevance of this mechanism. The functional importance of the IκBα–NF-κB axis was further demonstrated by IκBα knockdown experiments, in which depletion of IκBα markedly attenuated the cytotoxicity of the selinexor–bortezomib combination [15]. In addition to suppression of NF-κB signaling, combined XPO1 and proteasome inhibition enhances the nuclear accumulation of tumor-suppressor proteins and disrupts multiple survival pathways, resulting in synergistic antimyeloma activity in preclinical models. Collectively, these findings indicate that selinexor and PIs exert complementary effects on protein homeostasis and nuclear export and provide a biological rationale for combining selinexor with bortezomib or carfilzomib, including in PI-resistant disease. This preclinical framework subsequently supported the clinical development of PI-containing selinexor regimens [45].
4.2. Synergy with Dexamethasone
The combination of selinexor with dexamethasone is supported by a distinct mechanistic interaction involving glucocorticoid receptor signaling and suppression of the mTORC1 pathway. Selinexor increases GR expression in MM cells, thereby enhancing their responsiveness to dexamethasone. Upon dexamethasone-mediated GR activation, the combination markedly increases GR-dependent transcription and promotes the expression of downstream regulators of mTOR signaling, particularly regulated in development and DNA damage response 1 (REDD1) [24]. Enhanced REDD1 expression contributes to suppression of mTORC1 activity, a central regulator of cellular growth, metabolism, and survival in MM. Consistent with this mechanism, silencing of REDD1 attenuated the inhibitory effect of the selinexor–dexamethasone combination on mTOR signaling, supporting a functional role for the GR–REDD1–mTORC1 axis in the observed synergy. Importantly, although the direct antimyeloma activity of selinexor is largely independent of GR expression, its synergistic interaction with dexamethasone appears to be GR-dependent. These findings provide a biological rationale for incorporating dexamethasone into selinexor-based regimens and illustrate how XPO1 inhibition can enhance glucocorticoid-mediated antimyeloma activity through coordinated suppression of mTORC1 signaling [24].
4.3. Rationale for Combination with IMiDs
Preclinical studies have also demonstrated synergistic antimyeloma activity when XPO1 inhibition is combined with immunomodulatory drugs (IMiDs), providing a rationale for the clinical evaluation of selinexor with pomalidomide or lenalidomide. In experimental MM models, the addition of an IMiD to XPO1 inhibition enhanced cytotoxicity compared with either therapeutic approach alone, including activity observed with selinexor–pomalidomide combinations [9]. The biological basis for this interaction is likely multifactorial. Selinexor simultaneously promotes nuclear retention and reactivation of tumor-suppressor proteins, suppresses NF-κB signaling, and reduces the expression of survival-associated oncoproteins such as c-MYC and MCL-1. These effects may complement the direct antimyeloma and immunomodulatory activities of IMiDs, thereby increasing cellular susceptibility to treatment. Importantly, however, the molecular determinants of selinexor–IMiD synergy have not been defined as clearly as those underlying its interactions with PIs or dexamethasone [9]. The demonstration of synergistic activity in preclinical MM models provided the rationale for subsequent clinical investigation of selinexor–IMiD combinations, particularly selinexor plus pomalidomide and dexamethasone (SPd) and selinexor plus lenalidomide and dexamethasone (SRd). Their clinical efficacy and safety are discussed in the subsequent sections [9].
4.4. Rationale for Combination with Anti-CD38 Monoclonal Antibodies
The combination of selinexor with anti-CD38 monoclonal antibodies, particularly daratumumab, represents a mechanistically complementary therapeutic strategy in MM. Whereas selinexor exerts predominantly tumor cell-intrinsic effects through inhibition of XPO1-mediated nuclear export, reactivation of tumor-suppressor pathways, suppression of oncogenic signaling, and induction of apoptosis, daratumumab targets CD38-expressing plasma cells through immune-mediated mechanisms. The distinct mechanisms of action of these agents therefore provide a biological rationale for their combined use [46]. In addition, emerging evidence that selinexor may modulate NK- and T-cell function and immune checkpoint expression raises the possibility that XPO1 inhibition could influence the immune microenvironment in ways that complement antibody-based therapy. However, these immunomodulatory effects remain incompletely characterized, and a direct mechanistic basis for synergy between selinexor and anti-CD38 antibodies has not yet been established as clearly as that observed with PIs or dexamethasone [42]. Despite this mechanistic uncertainty, the non-overlapping modes of action and clinical activity of both therapeutic classes supported the evaluation of selinexor–daratumumab combinations in relapsed/refractory MM. Subsequent clinical studies have demonstrated activity of selinexor, daratumumab, and dexamethasone-containing regimens, including in heavily pretreated populations, and these clinical data are discussed in the following sections [46].
4.5. Translation of Preclinical Synergy into Clinical Combination Strategies
The pleiotropic effects of XPO1 inhibition provide a strong biological rationale for incorporating selinexor into combination-based treatment strategies in MM. Rather than relying on a single pathway, selinexor simultaneously restores tumor-suppressor activity, suppresses oncogenic and NF-κB-dependent survival signaling, alters protein homeostasis, and promotes apoptosis. These effects create multiple opportunities for complementary interactions with established antimyeloma agents [7,15]. Among these combinations, the mechanistic rationale is particularly well established for PIs and dexamethasone, through modulation of the IκBα–NF-κB and GR–REDD1–mTORC1 axes, respectively. Preclinical studies have also demonstrated enhanced antimyeloma activity when selinexor is combined with IMiDs, while combinations with anti-CD38 monoclonal antibodies are supported by complementary mechanisms of action and emerging preclinical and clinical evidence [9,15,24,42,46]. Collectively, these observations provided the foundation for the systematic clinical evaluation of selinexor-based doublet, triplet, and, more recently, quadruplet regimens. Importantly, the development of once-weekly selinexor-containing combinations has also sought to optimize the balance between antimyeloma activity and tolerability. The clinical translation of these strategies, including combinations with dexamethasone, bortezomib, carfilzomib, pomalidomide, lenalidomide, and daratumumab, is discussed in the following section [9,36]. The mechanistic rationale for these combinations is supported primarily by preclinical studies (Tier B). Clinical studies provide evidence of therapeutic activity for selinexor-containing regimens, including combinations evaluated in STOMP and the randomized SVd versus Vd comparison in BOSTON (Tier A) [36,37,46,47]. However, demonstration of clinical activity or superiority of a combination regimen does not, by itself, establish pharmacological synergy or validate the proposed molecular mechanism in patients.
5. Clinical Development of Selinexor in Multiple Myeloma
5.1. Early Clinical Development and Selinexor–Dexamethasone
Early clinical development of selinexor in MM established proof of concept for therapeutic XPO1 inhibition while also demonstrating the importance of combination therapy. In a multicenter phase I study, Chen et al. evaluated selinexor with or without dexamethasone in patients with heavily pretreated RRMM. Single-agent selinexor demonstrated modest activity, with an objective response rate (ORR) of 4% and a clinical benefit rate of 21%. In contrast, the addition of dexamethasone substantially enhanced antimyeloma activity; in the cohort receiving selinexor 45 mg/m2 (approximately 80 mg) plus dexamethasone 20 mg twice weekly, the ORR reached 50%. These findings provided early clinical support for the mechanistic synergy between XPO1 inhibition and glucocorticoid signaling and established selinexor plus dexamethasone as the backbone for subsequent clinical development [34].
The activity of this combination was subsequently evaluated by Vogl et al. in a phase II study involving 79 patients with highly refractory MM who had received a median of seven prior treatment regimens. Patients received selinexor 80 mg plus dexamethasone 20 mg twice weekly. Forty-eight patients had disease refractory to bortezomib, carfilzomib, lenalidomide, and pomalidomide, whereas 31 patients were additionally refractory to an anti-CD38 monoclonal antibody. The overall response rate was 21%, with comparable response rates in the quad-refractory (21%) and penta-refractory (20%) subgroups. Notably, an ORR of 35% was observed among patients with high-risk cytogenetic abnormalities, including t(4;14), t(14;16), and del(17p). The median duration of response was approximately 5 months [35]. Collectively, these early studies demonstrated that selinexor retained clinically meaningful activity in heavily pretreated and multidrug-refractory MM and that dexamethasone substantially enhanced its antimyeloma effect. These observations established the selinexor–dexamethasone backbone and provided the foundation for its subsequent evaluation in the larger STORM study.
5.2. The STORM Trial
The phase IIb STORM study represented a pivotal step in the clinical development of selinexor by evaluating its activity in a population with highly refractory MM and limited remaining therapeutic options. In Part 2 of the study, 122 patients with penta-exposed, triple-class refractory MM received oral selinexor 80 mg plus dexamethasone 20 mg twice weekly. Patients had previously been exposed to bortezomib, carfilzomib, lenalidomide, pomalidomide, and daratumumab and were required to have disease refractory to at least one proteasome inhibitor, one immunomodulatory drug, and daratumumab. The population was heavily pretreated, with a median of seven previous treatment regimens, and 53% of patients had high-risk cytogenetic abnormalities [32]. Selinexor plus dexamethasone achieved an ORR of 26% (95% CI, 19–35%), including two stringent complete responses, six very good partial responses, and 24 partial responses. An additional 13% of patients achieved a minimal response, resulting in a clinical benefit rate of 39%. Responses occurred rapidly, with a median time to response of approximately 4 weeks. The median duration of response was 4.4 months, while median progression-free survival (PFS) and overall survival (OS) were 3.7 and 8.6 months, respectively. Notably, among patients achieving at least a minimal response, median OS extended to 15.6 months [32]. The clinical relevance of these findings should be interpreted in the context of the highly treatment-refractory population enrolled in STORM. All patients had progressive disease at study entry, and most had exhausted the major therapeutic classes available at that time. Despite this adverse clinical profile, selinexor–dexamethasone produced clinically meaningful responses across several patient subgroups, providing proof that XPO1 remained a therapeutically actionable target even in advanced multidrug-refractory MM. The STORM results provided the pivotal efficacy evidence supporting the initial accelerated regulatory approval of selinexor in heavily pretreated RRMM and established XPO1 inhibition as a clinically validated therapeutic strategy. However, the toxicity profile and relatively limited durability of disease control observed with twice-weekly selinexor also highlighted the need for more tolerable dosing schedules and rational combination approaches. These considerations subsequently shaped the development of once-weekly selinexor-containing regimens, most notably the selinexor–bortezomib–dexamethasone combination evaluated in the phase III BOSTON trial.
5.3. The BOSTON Trial
The phase III BOSTON trial provided randomized evidence supporting the clinical efficacy of selinexor-based combination therapy in previously treated MM. In this multicenter, open-label study, 402 patients who had received one to three prior lines of therapy were randomly assigned to receive once-weekly selinexor, bortezomib, and dexamethasone (SVd; n = 195) or standard bortezomib and dexamethasone (Vd; n = 207). In the SVd arm, selinexor was administered at 100 mg once weekly together with once-weekly bortezomib, representing a substantially different treatment schedule from the twice-weekly selinexor–dexamethasone regimen used in STORM [36]. The study met its primary endpoint, demonstrating a significant improvement in PFS with SVd. Median PFS was 13.93 months with SVd compared with 9.46 months with Vd (HR, 0.70; 95% CI, 0.53–0.93; p = 0.0075), corresponding to a 30% reduction in the risk of disease progression or death. The overall response rate was also significantly higher with SVd than with Vd (76.4% vs. 62.3%; p = 0.0012), and responses were deeper, with very good partial response or better achieved in 44.6% and 32.4% of patients, respectively. An important feature of the BOSTON regimen was the use of once-weekly bortezomib in the SVd arm, compared with twice-weekly bortezomib in the control arm. Despite the addition of selinexor, clinically significant peripheral neuropathy was less frequent with SVd: grade ≥ 2 peripheral neuropathy occurred in 21% of patients receiving SVd compared with 34% receiving Vd (p = 0.0013). Conversely, selinexor-associated toxicities remained clinically relevant, particularly thrombocytopenia, fatigue, and anemia, emphasizing the importance of supportive care, dose modification, and toxicity monitoring during treatment [48]. The clinical benefit of SVd was also observed across biologically relevant subgroups. In a prespecified analysis of patients with high-risk cytogenetic abnormalities, the ORR was 78.6% with SVd compared with 57.7% with Vd, while median PFS was 12.91 versus 8.61 months, respectively. Although the PFS difference within the high-risk subgroup did not reach statistical significance, these findings suggested that the activity of selinexor-based therapy was maintained in patients with adverse cytogenetic features. BOSTON therefore marked an important transition in the clinical development of selinexor, from the twice-weekly selinexor–dexamethasone approach used in heavily pretreated triple-class refractory disease to a once-weekly, mechanism-based triplet regimen applicable earlier in the relapsed/refractory treatment course. The trial demonstrated the clinical efficacy of combining selinexor with bortezomib and dexamethasone, consistent with the preclinical rationale, but did not directly establish pharmacological synergy in patients [36]. On the basis of the BOSTON results, selinexor in combination with bortezomib and dexamethasone received regulatory approval for patients with MM who had received at least one prior therapy.
5.4. The STOMP Program and Other Selinexor-Based Triplets
The phase Ib/II STOMP (Selinexor and Backbone Treatments of Multiple Myeloma Patients) study provided a platform for the systematic evaluation of once-weekly selinexor in combination with several established antimyeloma agents. Multiple parallel cohorts investigated combinations with carfilzomib, pomalidomide, daratumumab, lenalidomide, and other therapeutic backbones. Collectively, these studies demonstrated that selinexor could be incorporated into diverse triplet regimens and supported the transition from the twice-weekly selinexor–dexamethasone schedule used in STORM toward lower-dose, once-weekly combination strategies. Selinexor, carfilzomib, and dexamethasone (SKd). The combination of selinexor with carfilzomib and dexamethasone was evaluated in patients with RRMM, based on the preclinical synergy between XPO1 and proteasome inhibition. In the STOMP SKd cohort, 32 patients with a median of four prior lines of therapy received once-weekly selinexor in combination with carfilzomib and dexamethasone. Among patients who were not refractory to carfilzomib, the overall response rate was 78%, with 44% achieving a very good partial response or better. Median PFS was approximately 15 months and median duration of response was 22.7 months. Importantly, activity was maintained in patients with high-risk cytogenetic features, supporting the potential utility of dual XPO1 and proteasome inhibition in biologically adverse disease [47].
Selinexor, pomalidomide, and dexamethasone (SPd). The all-oral SPd regimen has also demonstrated clinically meaningful activity in RRMM. Early STOMP experience showed responses in both pomalidomide-naïve and IMiD-refractory populations, supporting the feasibility of combining XPO1 inhibition with an IMiD backbone. Subsequent dose-optimization analyses evaluated once-weekly selinexor at 40 or 60 mg in combination with pomalidomide and dexamethasone. Although the 60 mg regimen produced a higher ORR (65% versus 50%), the 40 mg regimen was associated with a longer median PFS (18.4 versus 9.5 months) and a more favorable overall tolerability profile. These observations illustrate the importance of dose optimization when selinexor is incorporated into combination therapy and support the use of lower once-weekly doses to improve the therapeutic index [37]. The 40 mg schedule is now being tested prospectively: the randomized phase III XPORT-MM-031 (EMN29) study compares all-oral SPd40 with elotuzumab, pomalidomide and dexamethasone in patients who received an anti-CD38 monoclonal antibody as their immediate prior line of therapy. Enrolment of 117 patients was completed, and this event-driven trial is the first randomized test both of the lower once-weekly dose and of the “mechanism-switch” hypothesis immediately after anti-CD38 exposure [49].
Selinexor, daratumumab, and dexamethasone (SDd). In the STOMP SDd cohort, 34 patients with RRMM received selinexor in combination with daratumumab and dexamethasone. Patients had received a median of three prior treatment regimens and were frequently refractory to PIs and IMiDs. Among daratumumab-naïve patients, the ORR was 73% and median PFS was 12.5 months. Once-weekly selinexor at 100 mg was selected as the recommended phase II dose in combination with standard daratumumab and dexamethasone. In contrast, responses were not observed among the small number of patients with pre-existing daratumumab-refractory disease in this cohort [46]. This observation has since been qualified by a dedicated phase IIb study in which patients continued daratumumab after progression on a daratumumab-containing regimen, and selinexor was added as the only new agent. Among 10 heavily pretreated patients, all of whom were refractory to their last line of therapy and 70% had high-risk cytogenetics, the ORR was 50%, median PFS was 6.87 months, and median OS was 29.3 months [50]. Because the expected ORR to single-agent selinexor is below 30%, these data suggest that some interaction between the two agents may persist even in daratumumab-refractory disease; although the sample size is very small, the design was single-arm, and the result requires confirmation [50].
Selinexor, lenalidomide, and dexamethasone (SRd). An all-oral combination of selinexor, lenalidomide, and dexamethasone was also explored within STOMP. At the recommended phase II dose of once-weekly selinexor 60 mg, lenalidomide 25 mg on days 1–21, and weekly dexamethasone, particularly high response rates were observed in lenalidomide-naïve RRMM, with an ORR of approximately 92%. In contrast, substantially lower activity was observed among patients previously exposed to lenalidomide. These findings suggest that prior lenalidomide exposure and sensitivity to the lenalidomide backbone should be considered when selecting patients for SRd [13].
Taken together, the STOMP experience demonstrated that selinexor can be combined with multiple therapeutic classes and that once-weekly dosing can preserve substantial antimyeloma activity while facilitating combination treatment. The heterogeneity in efficacy across individual cohorts also highlights the importance of prior drug exposure, refractory status, partner-agent selection, and selinexor dose optimization when selecting a selinexor-based regimen.
5.5. Emerging Quadruplet Strategies
The clinical development of selinexor has increasingly expanded beyond doublet and triplet regimens toward quadruplet combinations designed to simultaneously target multiple therapeutic vulnerabilities in MM. These approaches remain less mature than the established selinexor-based triplets and should therefore be regarded as emerging strategies rather than standard treatment options. One of the most extensively evaluated quadruplet approaches combines selinexor with daratumumab, bortezomib, and dexamethasone (Dara-SVd). This strategy builds upon the established activity of SVd while incorporating CD38-directed immune therapy. In a phase II study, the combination was evaluated in patients with RRMM, demonstrating the feasibility of simultaneously targeting XPO1-mediated nuclear export, proteasome-dependent protein homeostasis, and CD38-expressing plasma cells. These findings provide clinical support for further investigation of selinexor-containing quadruplets, although longer follow-up and comparative studies are required to define their relative efficacy and tolerability [51].
Another emerging strategy combines selinexor with carfilzomib, pomalidomide, and dexamethasone (SKPd). This approach is supported by the independently demonstrated activity of both SKd and SPd and aims to exploit complementary effects of XPO1 inhibition, proteasome inhibition, and immunomodulation. A prospective multicenter study reported preliminary results of SKPd in 10 patients with extramedullary myeloma, comprising three newly diagnosed, four first-relapse, and three other relapsed/refractory cases. The overall response rate was 100%, including complete or stringent complete responses in 50%. These findings were reported in a conference abstract and should be interpreted cautiously because of the small, heterogeneous population and absence of a comparator group [52]. More broadly, the development of selinexor-containing quadruplets reflects a shift toward lower-dose, once-weekly selinexor schedules integrated into multidrug regimens. Such strategies may improve depth of response by targeting complementary biological pathways; however, this potential benefit must be balanced against cumulative hematologic, gastrointestinal, constitutional, and infectious toxicities. Careful dose optimization and patient selection are therefore likely to be particularly important when selinexor is incorporated into four drug combinations. At present, selinexor-based quadruplets remain investigational, and available data are substantially less mature than those supporting SVd or other established selinexor-containing triplets. Ongoing and randomized studies will be required to determine whether the addition of selinexor to contemporary three-drug backbones translates into clinically meaningful improvements in depth and durability of response without unacceptable toxicity.
5.6. Clinical Interpretation and Patient Selection
The clinical role of selinexor in MM should be considered within an increasingly complex treatment landscape that now includes PIs, IMiDs, anti-CD38 monoclonal antibodies, CAR T-cell therapies, bispecific antibodies, and other targeted approaches. Rather than representing a universally preferred option at relapse, selinexor may be particularly valuable in selected clinical scenarios in which its distinct mechanism of action, oral administration, and lack of cross-resistance with several established drug classes provide therapeutic advantages. One potentially relevant population comprises patients with high-risk cytogenetic disease. Subgroup analyses of the BOSTON trial demonstrated that the benefit of selinexor–bortezomib–dexamethasone was preserved in patients with high-risk abnormalities, including del(17p), t(4;14), t(14;16), and amplification of 1q21. These findings suggest that adverse cytogenetic features do not preclude responsiveness to XPO1 inhibition and support consideration of selinexor-containing combinations in biologically high-risk disease [48].
Renal impairment represents another clinically relevant setting. Because renal dysfunction is common in advanced MM and may restrict the use or dosing of several antimyeloma agents, treatments that can be administered without major renal dose adjustment are potentially advantageous. Subgroup analyses from BOSTON have demonstrated preserved efficacy of once-weekly selinexor–bortezomib–dexamethasone across patients with renal impairment, supporting the feasibility of this regimen in appropriately selected patients with compromised renal function [27].
The positioning of selinexor has also evolved with the introduction of T-cell-redirecting therapies. CAR T-cell products and bispecific antibodies can achieve deep and durable responses in eligible patients; however, access, manufacturing time, infectious complications, immune fitness, comorbidities, and rapidly progressive disease may limit their applicability in individual patients. In this context, selinexor-based regimens may provide an alternative for patients who are unsuitable for or unable to access T-cell-redirecting therapy. More recently, selinexor has also been explored as a potential holding or bridging strategy before CAR T-cell therapy, although this application remains investigational and requires prospective validation.
Prior treatment exposure should substantially influence regimen selection. Patients with previous anti-CD38 monoclonal antibody exposure may retain sensitivity to selinexor-based combinations because XPO1 inhibition operates through a distinct therapeutic mechanism. Real-world analyses support this reasoning. In a nationwide electronic health record-derived cohort of patients treated with a selinexor-containing triplet, real-world overall survival was 14.7 months and derived progression-free survival 4.7 months overall, whereas patients who had received an anti-CD38 monoclonal antibody in the immediate prior line had numerically better outcomes (real-world overall survival 20.9 months; derived progression-free survival 8.7 months) [53]. Conversely, the efficacy of specific selinexor combinations depends partly on sensitivity to the partner agent. Lower activity of SRd was reported after prior lenalidomide exposure [13], whereas SDd demonstrated activity in both daratumumab-naïve and daratumumab-refractory cohorts, with outcomes requiring cautious interpretation because of differences between studies [46,50].
Patient selection must also account for the characteristic toxicity profile of selinexor. Baseline thrombocytopenia, poor nutritional status, significant fatigue, recurrent gastrointestinal symptoms, and susceptibility to electrolyte disturbances may adversely affect tolerability. In contrast, contemporary once-weekly schedules and proactive supportive care can substantially improve treatment feasibility compared with the higher-intensity twice-weekly dosing initially used in STORM. Therefore, the choice of selinexor dose, combination partner, and supportive-care strategy should be individualized according to prior therapy, disease biology, comorbidities, performance status, and anticipated treatment tolerance [33].
Overall, selinexor is best viewed as a mechanism-driven therapeutic option whose clinical value depends on appropriate patient and regimen selection. Its distinct XPO1-directed activity may be particularly useful in multidrug-exposed disease, selected high-risk subgroups, patients with renal impairment, and individuals for whom cellular or bispecific immunotherapies are unsuitable or temporarily inaccessible. Further prospective studies are needed to define its optimal sequencing relative to contemporary immunotherapies and to determine whether biomarker-guided patient selection can further improve its therapeutic index. The clinical development and regulatory milestones of selinexor in MM are outlined in Figure 3.
Figure 3.
Timeline of the clinical development and regulatory approval of selinexor in multiple myeloma, from the first characterization of XPO1 inhibitors to current mechanistic insights. Original figure prepared by the authors from the information in the cited publications; no copyrighted material has been reproduced.
Table 3.
Clinical Trials of Selinexor-Based Regimens in Multiple Myeloma: Populations, Regimens, Efficacy, and Major Toxicities.
5.7. Positioning of Selinexor Relative to BCMA-Directed and T-Cell-Redirecting Therapies
The therapeutic landscape of relapsed/refractory MM has changed substantially since the pivotal selinexor studies were conducted. BCMA-directed CAR T-cell therapies, bispecific antibodies, and BCMA-directed antibody–drug conjugates now achieve response rates and durability that exceed those reported for selinexor-based regimens in broadly comparable populations. In the CARTITUDE-1 study, ciltacabtagene autoleucel produced an objective response in 97% of infused patients, including a stringent complete response in 67%, with a 12-month progression-free survival of 77% [55]; idecabtagene vicleucel achieved an objective response rate of 73% with a median progression-free survival of 8.8 months in the KarMMa study [56]. Among bispecific antibodies, teclistamab produced an objective response in 63% of patients with a median progression-free survival of 11.3 months [57], elranatamab in 61% of BCMA-naive patients [58], and talquetamab in 64–70% with median durations of response of 7.8–10.2 months [59]. In earlier lines of therapy, belantamab mafodotin combined with bortezomib–dexamethasone or pomalidomide–dexamethasone significantly improved progression-free survival compared with the respective standard-of-care comparators, with a 12-month progression-free survival of 71% versus 51% in DREAMM-8 [60,61]. These results imply that selinexor-based therapy is unlikely to be selected as a first-choice option in patients who are eligible for, and able to access, T-cell-redirecting therapy. It should also be emphasized that these trials enrolled different populations, used different endpoints and follow-up durations, and were not designed for comparison with one another; the figures above therefore describe the contemporary standard rather than a formal ranking.
The clinical value of selinexor consequently lies in the settings in which these more intensive approaches cannot be applied. Selinexor is an oral agent that can be incorporated into regimens without the leukapheresis, cellular manufacturing, or lymphodepleting chemotherapy required for CAR T-cell therapy. However, the route of administration of the complete regimen depends on the combination partners: SPd is all-oral, whereas combinations containing bortezomib, carfilzomib, or daratumumab require parenteral administration [36,37,46,47]. Although selinexor-based regimens avoid the characteristic cytokine release syndrome and ICANS associated with T-cell-redirecting therapies, they can cause clinically significant cytopenias and other toxicities requiring close monitoring and dose modification [26,31]. These characteristics are relevant for patients with rapidly progressive disease in whom the interval required for CAR T-cell manufacturing or for step-up dosing of a bispecific antibody may be clinically prohibitive, for patients with substantial comorbidity or impaired performance status, for patients who are ineligible for or have exhausted BCMA-directed therapy, and for patients treated in settings where cellular therapies are not available [53]. In addition, selinexor-based regimens have been evaluated as a holding or bridging strategy before CAR T-cell therapy, an application discussed in Section 5.8 [43,54].
Several limitations should be acknowledged when selinexor is positioned against these newer modalities. First, the depth and durability of response achieved with selinexor-based regimens are generally lower than those reported for BCMA-directed T-cell-redirecting therapies, and the pivotal BOSTON study compared once-weekly selinexor–bortezomib–dexamethasone with twice-weekly bortezomib and dexamethasone rather than with a contemporary control regimen, so that its results cannot be extrapolated directly to current sequencing questions [36]. Second, no prospective study has compared a selinexor-based regimen with a bispecific antibody or a CAR T-cell product, and the evidence on selinexor in patients whose disease is refractory to BCMA-directed therapy is limited to a small retrospective series and to pooled data from heterogeneous salvage cohorts [9,62,63]; the activity of XPO1 inhibition after BCMA-directed treatment therefore remains an important evidence gap. Third, the toxicity profile of selinexor, particularly cytopenias, gastrointestinal symptoms, and hyponatremia, requires active management and constrains combination with myelosuppressive agents [32,33]. Fourth, no randomized trial has yet demonstrated an overall survival benefit for a selinexor-based regimen; in BOSTON, overall survival data were immature at the primary analysis [36].
In the absence of randomized comparisons with contemporary therapies, the position of selinexor is best described as complementary rather than competing. Its principal role is likely to be that of a mechanism-driven, orally available option for patients who cannot receive, do not respond to, or relapse after BCMA-directed and T-cell-redirecting therapies, and prospective studies are needed to define its optimal sequencing in this context, including its use before and after bispecific antibodies and CAR T-cell products [9,64].
Contemporary treatment options for RRMM include CAR T-cell therapies, bispecific antibodies, antibody–drug conjugates, and combinations incorporating established antimyeloma agents [55,56,57,58,59,60,61]. Selinexor-containing regimens provide an additional option with a distinct mechanism of action. Their clinical positioning should consider prior treatment exposure and refractoriness, disease tempo, comorbidities, anticipated toxicity, access, and patient preferences. Response rates from separate trials should not be used to establish a definitive treatment ranking. The oral administration of selinexor may offer practical advantages, although whether the complete regimen is all-oral depends on its combination partners [36,37,46,47].
On this basis, the patient populations most likely to benefit from selinexor-based therapy can be defined as follows: (1) patients who are not candidates for, or who have progressed after, CAR T-cell therapy and bispecific antibodies, or for whom these treatments are not immediately available, including those with rapidly progressive disease in whom the interval required for manufacturing, bridging and lymphodepletion is prohibitive; (2) patients with impaired T-cell fitness or extensive prior T-cell-directed and immunomodulatory treatment, in whom T-cell-dependent approaches are less likely to be effective; (3) patients with renal impairment, in whom selinexor requires no dose adjustment and the oral route avoids an additional infusion-related burden; (4) selected older or frail patients for whom T-cell-redirecting therapies are unsuitable, provided that bone marrow reserve, nutritional status, performance status, and the anticipated tolerability of the selinexor-containing regimen are carefully assessed [26,31,33]; (5) patients with triple-class refractory MM who may benefit from an agent with a mechanism of action distinct from those of proteasome inhibitors, IMiDs, and anti-CD38 antibodies, as supported by the clinical activity observed in STORM [32]; (6) selected patients with disease progression after BCMA-directed therapy, in whom selinexor-containing regimens may be considered according to prior treatment, sensitivity to combination partners, and tolerability. Evidence in this setting remains limited to small retrospective series and heterogeneous pooled analyses, which do not establish superiority over bispecific antibodies or other salvage options [62,63]; and (7) patients for whom the oral route, the absence of a manufacturing delay and the avoidance of cytokine release syndrome are important determinants of quality of life or adherence. Conversely, a selinexor-containing regimen may be unsuitable when resistance to its combination partners, limited bone marrow reserve, or anticipated toxicity makes adequate treatment delivery unlikely. In rapidly progressive disease, the choice should be guided by the expected speed and depth of response, prior drug sensitivity, and the immediate availability of alternative treatments.
Table 4.
Comparative Positioning of Selinexor-Based Regimens and Contemporary Immunotherapies in Relapsed/Refractory Multiple Myeloma.
5.8. Selinexor, T-Cell Fitness, and Sequencing Around T-Cell-Redirecting Therapies
The efficacy of BCMA-directed CAR T-cell therapy and of bispecific antibodies depends on the functional capacity of the patient’s own T cells. Treatment administered before apheresis (holding therapy) and between apheresis and infusion (bridging therapy) must therefore achieve disease control without compromising T-cell fitness. This requirement is not trivial: in retrospective analyses, alkylating agents and, to a lesser extent, proteasome inhibitors have been associated with inferior outcomes after subsequent CAR T-cell therapy [54]. Selinexor is of interest in this context because its mechanism of action is tumor cell-intrinsic and because the immunological effects summarized in Section 3.9 point, if anything, in the opposite direction.
The preclinical rationale rests on three observations. First, XPO1 inhibition enhances CD8+ T-cell and natural killer cell activation, re-polarizes macrophages, inhibits myeloid-derived suppressor cells and reduces pro-inflammatory cytokine levels, changes that are compatible with an improved rather than a depleted effector compartment [42,43]. Second, selinexor may increase the immunogenicity of myeloma cells and upregulate BCMA, the antigen targeted by most available T-cell-redirecting products [43,65]. Third, in a CD19-directed CAR T-cell model, administration of selinexor before, rather than concurrently with, CAR T cells produced a greater reduction in tumor burden, which provides a specific argument for sequential use as holding therapy rather than for simultaneous administration [54].
Clinical evidence remains limited, consisting mainly of retrospective observations and a small early-phase clinical experience. In an exploratory analysis of 45 heavily pretreated patients from two academic centers who received a selinexor-containing regimen before BCMA-directed CAR T-cell therapy—selinexor at a median of the seventh line and CAR T-cell therapy at a median of the ninth, with 24.4% receiving selinexor as part of bridging—the overall response rate to CAR T-cell therapy was 89%, with a median duration of response of 8.1 months, a median progression-free survival of 8.0 months and a median overall survival of 35.9 months. In a multivariable model, use of a selinexor-based regimen in the line immediately preceding CAR T-cell therapy was associated with a trend toward reduced risk of progression (HR 0.40; 95% CI 0.14–1.09) and with a reduced risk of death (HR 0.08; 95% CI 0.02–0.46) [54]. These estimates should be interpreted cautiously because the study was small and retrospective, and the observed associations may be affected by patient selection, treatment sequencing, and residual confounding. The findings indicate that responses to CAR T-cell therapy can occur after selinexor exposure, but they do not establish that prior selinexor improves subsequent CAR T-cell outcomes or preserves T-cell fitness. Prospective studies with appropriate comparator groups and direct assessments of T-cell function are needed to evaluate these hypotheses [54]. In a separate phase I experience, selinexor was combined with the BCMA-directed CAR T-cell product CT103A using a two-step schedule during bridging and maintenance; the first two patients with extramedullary disease achieved stringent complete remission without immune effector cell-associated neurotoxicity syndrome or cytokine release syndrome above grade 2 [65].
Evidence for bispecific antibodies is weaker still. In a pooled analysis of patients treated in the STORM, STOMP, BOSTON and XPORT-MM-028 studies, outcomes with subsequent anti-BCMA therapy were not adversely affected by prior selinexor exposure; however, the great majority of those patients received belantamab mafodotin rather than a bispecific antibody, so the question of whether selinexor influences subsequent bispecific antibody efficacy is effectively unanswered [43]. Prospective evaluation is under way: a phase II study is adding selinexor to commercially available teclistamab, elranatamab or talquetamab [66], and a phase I study is testing selinexor as maintenance after CAR T-cell therapy [67].
Two practical considerations qualify this strategy. The cytopenias, fatigue and hyponatremia characteristic of selinexor may interfere with the timing of apheresis and with fitness for lymphodepletion, so once-weekly, lower-dose schedules with proactive supportive care (Section 7) are preferable when selinexor is used in this setting. In addition, no prospective data define the interval that should separate the last selinexor dose from apheresis or infusion, and this should currently be determined by institutional protocol. Applying the evidence classification of Section 1.5, the mechanistic basis for T-cell sparing is Tier B with supporting patient-derived pharmacodynamic data, whereas the clinical claim that selinexor does not compromise subsequent T-cell-redirecting therapy is Tier C. The stronger claim—that selinexor enhances the efficacy of CAR T-cell therapy or bispecific antibodies—remains a hypothesis and should not at present guide treatment selection outside a clinical trial.
6. Mechanisms of Resistance and Biomarkers of Response to Selinexor
6.1. Target-Based Resistance: XPO1 Cys528 Alterations
A direct mechanism of resistance to selective inhibitors of nuclear export involves alteration of the drug-binding site within XPO1. Selinexor interacts with Cys528 located in the NES-binding groove of XPO1, and substitution of this residue can markedly reduce sensitivity to SINE compounds. CRISPR/Cas9-based studies demonstrated that replacement of cysteine with serine (C528S) is sufficient to confer profound resistance to selinexor, even in the heterozygous state, confirming the critical importance of Cys528 for target engagement. Despite the strength of this experimental evidence, XPO1 C528S has not been established as a common mechanism of acquired selinexor resistance in patients with MM. Thus, although alteration of the XPO1 drug-binding site provides a proof-of-principle mechanism of target-based resistance, clinical resistance to selinexor appears to be substantially more complex and is likely driven predominantly by adaptive and non-mutational mechanisms [5,8]. From an evidence perspective, Cys528 alteration is a mechanistically definitive but preclinical model of target-based resistance: it has been demonstrated in genome-edited cell lines, but it has not been documented as a recurrent mechanism of acquired resistance in patients with MM [5,8].
6.2. Adaptive and Non-Mutational Resistance Mechanisms
Resistance to selinexor does not appear to depend exclusively on mutations affecting XPO1. Experimental models generated through prolonged drug exposure demonstrate that resistant MM cells can develop broad adaptive changes that attenuate the cellular consequences of XPO1 inhibition. These changes include reduced nuclear accumulation of tumor-suppressor proteins, impaired induction of apoptosis, and transcriptional alterations involving apoptotic signaling, inflammatory pathways, cellular adhesion, and stress-response mechanisms. Adaptive remodeling of nucleocytoplasmic transport may represent an additional mechanism of resistance. Molecular profiling of selinexor-refractory disease has identified enrichment of pathways involved in mRNA processing, splicing, and nucleocytoplasmic transport, together with alterations in alternative nuclear transport components. These observations raise the possibility that malignant plasma cells may partially compensate for XPO1 blockade by increasing their dependence on alternative transport pathways, thereby reducing the biological consequences of XPO1 inhibition. Collectively, these findings support a model in which selinexor resistance frequently reflects cellular adaptation to sustained disruption of nuclear export rather than the emergence of a single dominant escape mutation. Such plasticity may also explain the heterogeneity of clinical responses to selinexor and highlights the need for biomarkers capable of identifying tumors that remain dependent on XPO1-mediated transport [20]. This adaptive phenotype has been characterized in patient-derived material and translational profiling studies and therefore represents the resistance mechanism with the strongest clinical anchoring among those discussed in this section [20].
6.3. hnRNPU and Nuclear Transport and RNA Metabolism
The RNA-binding protein heterogeneous nuclear ribonucleoprotein U (hnRNPU) has emerged as a potential determinant of selinexor sensitivity in MM. hnRNPU participates in several aspects of RNA metabolism and is closely linked to the nuclear transport machinery. Experimental studies demonstrated that MM cells with reduced hnRNPU expression were more susceptible to selinexor-induced apoptosis, whereas high hnRNPU expression was associated with a more resistant phenotype. Consistent with these findings, patients who responded to selinexor exhibited relatively lower hnRNPU expression, suggesting its potential relevance as a predictive biomarker. Mechanistically, hnRNPU influences XPO1-dependent nuclear transport through several complementary processes. It regulates the intracellular localization of LTV1 and NMD3, proteins involved in the nuclear export of ribosomal subunits, and also binds to RAN and MDM2 mRNAs, thereby modulating their translation. Reduction in hnRNPU consequently alters both ribosomal transport and the broader RNA–protein network supporting XPO1-mediated nuclear export. These observations suggest that the response to selinexor is determined not only by XPO1 itself but also by the broader regulatory machinery controlling nuclear transport and RNA metabolism. Although hnRNPU remains an investigational biomarker and requires prospective clinical validation, its association with selinexor sensitivity provides a potential framework for biomarker-guided selection of patients most likely to benefit from XPO1 inhibition [20]. Evidence supporting hnRNPU as a candidate biomarker includes preclinical mechanistic studies (Tier B) and exploratory associations with treatment response in patient samples (Tier C). Its potential utility for patient selection requires prospective validation using a standardized assay and predefined expression cut-offs [20].
6.4. XPO1 Degradation and the USP7 Axis
The extent of XPO1 degradation following selinexor exposure may represent an additional determinant of treatment sensitivity. Beyond functional inhibition of XPO1-mediated nuclear export, selinexor promotes ubiquitin–proteasome-dependent depletion of the XPO1 protein pool. Experimental studies have demonstrated a positive association between the extent of XPO1 degradation and cellular sensitivity to selinexor, suggesting that efficient target depletion may contribute to the depth of the antimyeloma response. The deubiquitinase USP7 has emerged as an important regulator of this process. Under basal conditions, USP7 interacts with XPO1 and promotes its stabilization through deubiquitination. Selinexor disrupts the USP7–XPO1 interaction, thereby increasing XPO1 ubiquitination and facilitating its subsequent proteasomal degradation. Conversely, preservation of XPO1 stability may attenuate the functional consequences of selinexor exposure. Consistent with this model, USP7 expression has been reported to correlate negatively with selinexor sensitivity in MM cells, whereas genetic or pharmacologic suppression of USP7 enhances the antimyeloma activity of selinexor in both in vitro and in vivo models. These findings suggest that the balance between XPO1 ubiquitination and deubiquitination may influence therapeutic response and raise the possibility that USP7 expression or the extent of treatment-induced XPO1 degradation could serve as biomarkers of selinexor sensitivity. However, their predictive value has not yet been prospectively validated in patients [40]. The evidence supporting this mechanism is preclinical (Tier B), including experiments in MM cell lines, murine xenograft models, and primary CD138+ cells obtained from patients and studied ex vivo. These findings do not establish USP7 expression or treatment-induced XPO1 degradation as clinically validated predictive biomarkers [40].
6.5. Lipin1–SREBP as a Metabolic Determinant
Emerging evidence suggests that metabolic dependencies may also influence sensitivity to XPO1 inhibition. Lipin1, recently identified as an XPO1-dependent nuclear export cargo, provides a mechanistic link between selinexor activity and lipid metabolism in malignant plasma cells. Following XPO1 inhibition, nuclear accumulation of Lipin1 suppresses SREBP-dependent transcription, leading to reduced expression of genes involved in fatty-acid and cholesterol biosynthesis, including FASN, SCD, DHCR24, and FDPS. Importantly, experimental manipulation of Lipin1 expression has demonstrated that this pathway is not merely a downstream pharmacodynamic consequence of XPO1 inhibition. Suppression of Lipin1 attenuates the inhibitory effect of selinexor on SREBP signaling and reduces sensitivity to treatment, whereas preserved Lipin1-dependent signaling contributes to the metabolic and antimyeloma effects of selinexor in vitro and in murine xenograft models. These findings identify the Lipin1–SREBP axis as a potential metabolic determinant of selinexor response and suggest that variability in lipid-metabolic dependencies may contribute to heterogeneous treatment sensitivity among MM cells. Nevertheless, the clinical utility of Lipin1 or SREBP-related signatures as predictive biomarkers remains investigational and requires validation in prospectively characterized patient cohorts [41]. Evidence for this axis derives from preclinical models, including murine xenografts; no patient-level validation is currently available [41].
6.6. Resistance in Triple-Class Refractory Multiple Myeloma
Triple-class refractory disease, defined by refractoriness to a proteasome inhibitor, an immunomodulatory agent and an anti-CD38 monoclonal antibody, is associated with a median overall survival of less than one year under conventional regimens and represents the setting in which new mechanisms of action are most urgently needed. Selinexor was developed in precisely this population: the pivotal STORM trial enrolled 122 patients with triple-class refractory myeloma, most of whom were refractory to five agents [32]. Clinical resistance in this context is best understood as the combined result of disease-intrinsic and host-related factors rather than as a single molecular event.
Four aspects deserve emphasis. First, mutation of Cys528 has been reproducibly generated in preclinical models under selective pressure but has not been documented as a recurrent mechanism of acquired resistance in patients with myeloma; clinical resistance therefore appears to be driven predominantly by non-mutational processes, and mutation screening is unlikely to be informative in this setting [5]. Second, adaptive mechanisms predominate. Sustained nuclear factor-κB signaling, altered transport of specific cargoes, compensatory changes in ribosomal biogenesis and protein homeostasis, and a shift toward dependence on autophagy and metabolic adaptation have all been shown to attenuate the response to selinexor in preclinical models (Tier B). Third, resistance to prior therapies should be distinguished from resistance to selinexor itself. Although IMiDs and selinexor both interact with cellular protein-regulatory pathways, this does not establish that IMiD-associated changes in cereblon signaling confer resistance to XPO1 inhibition. Such a relationship requires direct experimental and clinical investigation. Prior treatment exposure and refractoriness should therefore inform the selection of combination partners without being presented as established molecular mechanisms of selinexor resistance. Fourth, patient selection remains the principal unmet need in this population. A three-gene expression signature associated with response to selinexor has been reported but has not been prospectively validated [68], and XPO1 abundance alone does not reliably predict benefit. Consequently, in triple-class refractory myeloma, selinexor should be regarded as an active but not uniformly effective option, and the identification of a validated predictor of response would add more clinical value in this setting than in earlier lines of therapy.
6.7. Emerging Predictive Biomarkers and Future Perspectives
At present, no prospectively validated biomarker is available for selecting patients with MM for selinexor-based therapy. Although XPO1 expression provides a biological rationale for therapeutic targeting, XPO1 abundance alone is unlikely to fully account for the substantial heterogeneity in clinical response. Emerging evidence instead supports a multidimensional model in which target engagement, nuclear transport dependency, protein homeostasis, RNA metabolism, and metabolic state collectively influence sensitivity to XPO1 inhibition. Several candidate biomarkers have emerged from preclinical and translational studies. Alterations at the XPO1 Cys528 binding site provide a mechanistically definitive but apparently uncommon model of target-based resistance. In contrast, hnRNPU expression may reflect dependence on nuclear transport and RNA-regulatory networks, whereas USP7 activity and the efficiency of treatment-induced XPO1 degradation may influence the extent of target depletion. The Lipin1–SREBP axis further suggests that metabolic characteristics of MM cells may contribute to selinexor responsiveness [8,20,40,41]. Rather than relying on a single molecular marker, future biomarker strategies may therefore require integrated signatures incorporating nuclear transport, XPO1 turnover, RNA-processing pathways, and cellular metabolism. Prospective correlative studies embedded within clinical trials will be essential to determine whether these candidate biomarkers can predict response independently of established clinical and disease-related factors. Such approaches may ultimately enable biomarker-guided selection of patients most likely to benefit from XPO1 inhibition while avoiding unnecessary toxicity in those with intrinsically resistant disease.
Candidate determinants of selinexor sensitivity and resistance, together with their mechanistic context and supporting evidence, are summarized in Table 5 and Figure 4. XPO1 Cys528 alterations, USP7-dependent regulation of XPO1 stability, and Lipin1–SREBP signaling are supported primarily by preclinical studies (Tier B) [8,40,41]. hnRNPU has both experimental mechanistic support (Tier B) and exploratory associations with treatment response in patient samples (Tier C) [20]. The WNT10A–DUSP1–ETV7 expression signature has been evaluated in independent clinical cohorts, but its utility for prospectively guiding treatment selection remains unestablished (Tier C) [68]. Prognostic associations, including those reported for XPO1 expression, should not be interpreted as evidence of predictive benefit from selinexor [7]. None of these candidates is currently established for routine biomarker-guided selection. Further development requires standardized assays, predefined cut-offs, and prospective evaluation of whether biomarker-guided treatment improves clinical outcomes.
Table 5.
Candidate Determinants of Selinexor Sensitivity and Resistance: Mechanisms, Evidence Level, and Readiness for Clinical Use.
Figure 4.
Integrated overview of proposed mechanisms of action, resistance pathways, and candidate biomarkers associated with XPO1 inhibition in multiple myeloma. Mechanistic findings arise predominantly from preclinical studies, including experiments using patient-derived cells ex vivo. Clinical associations do not, by themselves, establish causal mechanisms or predictive utility for treatment selection. The nature of the supporting evidence and the validation status of candidate biomarkers are summarized in Table 5. Original figure prepared by the authors.
7. Selinexor Toxicity and Practical Management
7.1. Overall Safety Profile
Selinexor is associated with a characteristic and generally predictable toxicity profile comprising hematologic, gastrointestinal, metabolic, and constitutional adverse events. The most commonly reported toxicities include thrombocytopenia, anemia, neutropenia, fatigue, nausea, decreased appetite, weight loss, diarrhea, vomiting, and hyponatremia. The incidence and severity of these adverse events may vary according to selinexor dose and schedule, combination partners, baseline patient characteristics, and prior treatment exposure. Early clinical experience with twice-weekly selinexor highlighted the clinical impact of cytopenias, gastrointestinal symptoms, fatigue, and nutritional deterioration. More recent treatment strategies have increasingly adopted lower-dose, once-weekly selinexor schedules, together with proactive supportive care and early dose modification, to improve tolerability while maintaining antimyeloma activity. Accordingly, careful monitoring and early management of treatment-related adverse events are essential for maintaining treatment adherence and optimizing the therapeutic benefit of selinexor-based regimens [32,33,36].
7.2. Hematologic Toxicities and Their Management
Hematologic toxicity represents an important component of the safety profile of selinexor, particularly in heavily pretreated patients with limited bone marrow reserve. Thrombocytopenia is among the most clinically relevant adverse events, while anemia and neutropenia are also frequently observed during treatment. Regular complete blood count monitoring is therefore essential, particularly during the early treatment period and in patients with baseline cytopenias. Management is based on the severity of cytopenia and associated clinical complications and may include temporary treatment interruption, dose reduction, transfusion support, growth-factor administration, and antimicrobial therapy when indicated. Severe thrombocytopenia or clinically significant bleeding generally requires treatment interruption and supportive care, whereas severe anemia may require red blood cell transfusion. For clinically significant neutropenia or febrile neutropenia, temporary treatment interruption and granulocyte colony-stimulating factor support may be considered. Once adequate hematologic recovery is achieved, selinexor can generally be resumed at a reduced dose according to the applicable dose-modification recommendations [32,33]. In patients with chemotherapy-associated anemia whose cancer treatment is not curative in intent, erythropoiesis-stimulating agents (ESAs) may be considered when hemoglobin declines below 10 g/dL, in accordance with ASCO/ASH guideline recommendations, with iron replacement used as appropriate to improve the hemoglobin response and reduce transfusion requirements; thrombotic risk and other contraindications should be assessed before initiating ESA therapy [69].
7.3. Gastrointestinal Toxicity, Anorexia, and Weight Loss
Gastrointestinal adverse events are common during selinexor-based therapy and include nausea, vomiting, diarrhea, decreased appetite, and weight loss. These toxicities may negatively affect oral intake, hydration, nutritional status, and overall treatment tolerance, particularly during the early phases of therapy. Proactive supportive care is therefore important and should include preventive antiemetic therapy, together with close monitoring of body weight, nutritional intake, hydration status, and serum electrolytes. Patients who develop persistent gastrointestinal symptoms or clinically significant anorexia and weight loss may require additional antiemetic therapy, nutritional support, hydration, appetite-stimulating interventions, and temporary selinexor dose interruption or reduction according to toxicity severity. Early recognition and management are particularly important to prevent progressive nutritional deterioration and to maintain treatment adherence.
A step-up dosing strategy may represent an additional approach to improve early gastrointestinal tolerability. In a small single-center retrospective series of eight patients, selinexor was initiated at 60 mg weekly and increased by 20 mg each week to a target dose of 100 mg, together with prophylactic aprepitant, a 5-HT3 antagonist, and dexamethasone. No grade ≥ 2 nausea/vomiting or diarrhea was observed, while five of eight patients achieved at least a partial response. Although limited by the small sample size and retrospective design, these findings suggest that gradual dose escalation may warrant further evaluation as a strategy to mitigate early gastrointestinal toxicity [32,33,38].
7.4. Hyponatremia and Metabolic Abnormalities
Hyponatremia is a characteristic metabolic adverse event associated with selinexor therapy and may occur in the context of reduced oral intake, gastrointestinal toxicity, dehydration, or other treatment-related factors. Serum sodium levels should therefore be assessed at baseline and monitored regularly during treatment, with particular attention to patients experiencing persistent nausea, vomiting, anorexia, or weight loss. Management should include evaluation and correction of potentially contributing factors, optimization of hydration and nutritional status, and appropriate electrolyte replacement. Clinically significant or severe hyponatremia may require temporary interruption of selinexor, with treatment resumed at a reduced dose following adequate correction [33].
7.5. Fatigue and Constitutional Toxicity
Fatigue is a common and clinically relevant adverse event during selinexor-based therapy and may adversely affect functional status, quality of life, and treatment adherence. Because fatigue is frequently multifactorial, potentially contributing factors such as anemia, dehydration, nutritional impairment, electrolyte abnormalities, infection, sleep disturbance, and concomitant medications should be assessed and corrected whenever possible. Management is primarily supportive and includes optimization of hydration and nutritional status, activity and energy-conservation strategies, and treatment of reversible contributing factors. Persistent or severe fatigue may require temporary treatment interruption or selinexor dose reduction to improve tolerability and maintain long-term treatment adherence [33].
7.6. Neurologic and Ocular Adverse Events
Neurologic and ocular adverse events have been reported less frequently during selinexor-based therapy. Neurologic manifestations may include dizziness, confusion, cognitive disturbances, or other changes in mental status, whereas ocular events may include blurred vision and, less commonly, cataract-related changes. Patients who develop new or worsening neurologic or visual symptoms should undergo appropriate clinical evaluation to exclude alternative causes, including metabolic abnormalities, concomitant medications, infection, or underlying comorbidities. Persistent or clinically significant toxicity may require treatment interruption or dose modification, with specialist evaluation when appropriate [32,33].
7.7. Supportive Care and Dose Optimization
Optimal use of selinexor requires a proactive rather than reactive approach to supportive care. Before treatment initiation, baseline blood counts, serum electrolytes, hydration and nutritional status, body weight, and relevant comorbidities should be assessed. During therapy, regular monitoring allows early recognition of cytopenias, gastrointestinal toxicity, electrolyte disturbances, nutritional deterioration, and other treatment-related adverse events. Preventive antiemetic therapy, adequate hydration, and nutritional support are particularly important during the early treatment period. Dose and schedule optimization are also central to improving tolerability. Contemporary selinexor-based regimens increasingly favor once-weekly dosing, while temporary treatment interruption and stepwise dose reduction can be used to manage clinically significant or persistent toxicities. Supportive measures, including transfusion support, growth factors, antiemetics, electrolyte replacement, and nutritional interventions, should be individualized according to the toxicity profile and clinical condition of the patient. Importantly, early toxicity management may help prevent treatment discontinuation and preserve exposure to an otherwise active therapy. Therefore, appropriate patient selection, anticipatory supportive care, close monitoring, and timely dose modification should be considered integral components of selinexor-based treatment. Practical recommendations for the use of selinexor in routine practice—including pre-emptive supportive care, proactive monitoring, and adaptation of dose and schedule to the individual toxicity profile—have recently been summarized for the Canadian treatment landscape [70]. More recently, tolerability-driven dose-optimization strategies have incorporated planned treatment-free intervals into once-weekly selinexor schedules. In clinical practice, omission of the late-cycle dose (e.g., Day 29 in a 35-day schedule) may provide an additional recovery period before the subsequent cycle, potentially facilitating hematologic, nutritional, and constitutional recovery. This approach is consistent with the broader trend toward lower-dose and intermittent selinexor schedules, although specific Day-29 omission has not been prospectively validated as an alternative to the original BOSTON regimen and should therefore be individualized according to treatment tolerance [29,32,33].
7.8. Nutritional and Metabolic Support
Given the high frequency of anorexia, nausea, reduced oral intake, and weight loss during selinexor therapy, nutritional status should be assessed at baseline and monitored throughout treatment. In patients at nutritional risk, an energy intake of approximately 25–30 kcal/kg/day and a protein intake of 1.0–1.5 g/kg/day may be considered, with requirements individualized according to nutritional status, age, comorbidities, renal function, and degree of catabolic stress. Small, frequent, energy- and protein-dense meals and early use of oral nutritional supplements may be helpful when adequate intake cannot be achieved with the usual diet. Adequate hydration should also be maintained, with approximately 2 L/day of fluid encouraged when clinically appropriate and in the absence of contraindications such as significant cardiac or renal dysfunction. These targets follow the general ESPEN recommendations for clinical nutrition in patients with cancer and are not specific to selinexor; they should therefore be adapted to the individual patient [71]. Practical management strategies for common selinexor-associated adverse events are summarized in Table 6.
Table 6.
Practical Management of Common Selinexor-Associated Adverse Events.
8. Next-Generation and Emerging XPO1 Inhibitors
8.1. Eltanexor (KPT-8602)
Eltanexor (KPT-8602) is a second-generation SINE developed to preserve XPO1-directed antitumor activity while improving the tolerability limitations associated with selinexor. Like selinexor, eltanexor occupies the NES-binding groove of XPO1, but it penetrates the blood–brain barrier substantially less. In preclinical models of hematologic malignancy, this property was associated with reduced anorexia, weight loss, and constitutional toxicity, allowing more frequent dosing while maintaining XPO1 inhibition, and with greater prolongation of survival than selinexor at tolerable doses [72]. In MM, preclinical studies demonstrated antimyeloma activity of eltanexor and synergistic effects in combination with established agents, including proteasome inhibitors. In a phase I study of eltanexor with or without dexamethasone in heavily pretreated RRMM, the overall response rate among 35 efficacy-evaluable patients was 20% (7/35), comprising one very good partial response and six partial responses; nine additional patients achieved a minimal response [73]. Eltanexor has not undergone clinical development in MM comparable to that of selinexor, and its therapeutic role therefore remains undefined. Nevertheless, its reduced central nervous system penetration and improved preclinical tolerability provide proof of concept that pharmacological refinement of XPO1 inhibition can broaden the therapeutic window of this drug class [72,73].
8.2. Other Selective Inhibitors of Nuclear Export
Several additional SINE compounds have been characterized. Verdinexor (KPT-335) is an orally available SINE that has been developed primarily in veterinary oncology, where a phase II study in dogs with lymphoma demonstrated single-agent clinical activity at a dosing schedule of 1.5 mg/kg three times weekly; this program illustrates that XPO1 inhibition is a tractable target outside human medicine but does not provide direct evidence for human use [74]. KPT-185, KPT-251, and KPT-350 are earlier-generation SINE compounds that were instrumental in establishing the pharmacology of this drug class, including the demonstration that XPO1 is a valid target in chronic lymphocytic leukemia [75]. KPT-350 was designed with increased central nervous system penetration, the opposite of the design goal pursued with eltanexor. None of these compounds has entered clinical development in MM.
8.3. Non-SINE XPO1 Inhibitors
XPO1 can also be inhibited by compounds that are structurally unrelated to the SINE series. Leptomycin B, the prototypical natural-product XPO1 inhibitor, was limited by severe toxicity in early clinical testing and is now used mainly as a laboratory tool. Felezonexor (SL-801, formerly CBS9106) is an orally available, reversible, non-SINE XPO1 inhibitor. Preclinical studies demonstrated XPO1 protein degradation, inhibition of nuclear export, cell-cycle arrest, and apoptosis in hematologic cancer models, including myeloma [76]. The same compound subsequently entered phase I evaluation as SL-801 in advanced solid tumors. An interim analysis reported stable disease in 27% of 45 patients, with vomiting, nausea, and fatigue among the most frequent adverse events [77]. These findings establish early clinical experience outside MM but do not demonstrate clinical efficacy in MM.
8.4. Comparative Perspective and Open Questions
Table 7 summarizes the principal characteristics of the XPO1 inhibitors discussed above. Several conclusions can be drawn. First, all clinically evaluated agents in this class act by occupying the NES-binding groove; resistance mediated by alteration of Cys528 would therefore be expected to affect the class as a whole rather than individual compounds, and the same consideration applies to therapeutic strategies designed to overcome it. Second, the differences between agents relate mainly to pharmacokinetics, tissue distribution, and dosing schedule rather than to a fundamentally different mechanism of action; reduced central nervous system penetration, for example, appears to translate into improved tolerability rather than greater efficacy. Third, the clinical development of next-generation agents in MM remains far behind that of selinexor, and no comparative trial has been performed; as a result, the therapeutic value of these compounds is currently uncertain, and their most plausible contribution may be to permit more continuous dosing or combination with myelosuppressive agents if a tolerability advantage is confirmed in randomized studies [72,73]. Finally, because the clinical experience with these agents is limited, the biomarker considerations discussed in Section 6 apply to the class as a whole and will need to be re-evaluated as additional agents enter clinical testing.
Table 7.
Comparative Overview of Clinically Evaluated and Emerging XPO1 Inhibitors.
9. Future Directions
Future research on XPO1 inhibition in multiple myeloma should address three priorities. First, randomized dose-comparison studies should define the optimal once-weekly selinexor dose for each combination partner and determine whether planned treatment-free intervals or step-up schedules improve tolerability without compromising efficacy [29]. Second, candidate biomarkers—including hnRNPU, the USP7–XPO1 axis, and Lipin1–SREBP signaling—require prospective evaluation using standardized assays and predefined cut-offs before they can guide treatment selection [20,40,41]. Third, prospective studies should clarify the sequencing of selinexor relative to anti-CD38 antibodies and T-cell-redirecting therapies, including its potential roles as holding, bridging, or maintenance treatment and its activity after BCMA-directed therapy [9,43].
Ongoing studies address several of these questions. XPORT-MM-031 (EMN29) compares selinexor–pomalidomide–dexamethasone with elotuzumab–pomalidomide–dexamethasone following anti-CD38 treatment [49]; a phase II study is evaluating selinexor with commercially available bispecific antibodies [66]; and an early-phase study is investigating selinexor maintenance after CAR T-cell therapy [67]. These studies should help establish whether the proposed sequencing strategies translate into clinical benefit. Further development of next-generation XPO1 inhibitors should also determine whether their pharmacological differences offer meaningful improvements in tolerability and treatment delivery [72,73].
Treatment Alternatives and Sequencing in Lenalidomide-Refractory Relapse
For patients with lenalidomide-refractory relapsed multiple myeloma who cannot access CAR-T-cell therapy or bispecific antibodies, treatment selection among available combinations remains an important clinical consideration. Several analyses of selected anti-CD38-based regimens have reported median progression-free survival ranging from approximately 8 to 14 months in lenalidomide-refractory populations: 9.9 months with daratumumab–pomalidomide–dexamethasone (DPd) in APOLLO [78], 7.8 months with daratumumab–bortezomib–dexamethasone (DVd) in CASTOR [79], and 11.4 months with isatuximab–pomalidomide–dexamethasone (Isa-Pd) in ICARIA-MM [80]. In a small post hoc analysis of DREAMM-7 specifically involving lenalidomide-refractory patients at first relapse, median progression-free survival was 13.5 months in the DVd arm (n = 27) [81]. These estimates are specific to the regimens and populations studied and should not be generalized to all anti-CD38-based combinations.
In the extended follow-up analysis of BOSTON, median progression-free survival with selinexor–bortezomib–dexamethasone (SVd) was 10.2 months in the lenalidomide-refractory subgroup [82]. Although these studies differ in prior treatment exposure, treatment schedules, and patient characteristics, their findings provide context for considering SVd among available alternatives. At first relapse, SVd may therefore be considered for selected patients without access to T-cell-redirecting therapies, taking into account bortezomib sensitivity, prior anti-CD38 exposure, comorbidities, tolerability, and patient preference. This represents an individualized treatment option rather than evidence that SVd is equivalent or superior to an anti-CD38-based regimen.
An additional, hypothesis-generating consideration concerns the potential influence of selinexor on subsequent antibody therapy. Preclinical studies demonstrated that selinexor downregulated HLA-E on myeloma cells and enhanced daratumumab-mediated antibody-dependent cellular cytotoxicity, with greater activity following selinexor pretreatment than simultaneous administration [83]. These observations raise the possibility that selinexor exposure could enhance susceptibility to subsequent daratumumab-based treatment and provide a rationale for prospective sequencing studies. However, short-term experimental pretreatment does not establish a sustained effect across separate treatment lines. Whether an SVd-to-daratumumab sequence improves clinical outcomes remains unknown; the current evidence does not justify deferring an otherwise appropriate daratumumab-based regimen solely to achieve this proposed sensitization.
10. Conclusions
XPO1 has emerged as a biologically and therapeutically relevant target in MM, where dysregulated nuclear export contributes to tumor-cell survival, treatment resistance, and disruption of tumor-suppressor function. Selinexor, the first-in-class SINE, exerts pleiotropic antimyeloma effects through inhibition of XPO1-mediated nuclear export, restoration of nuclear tumor-suppressor activity, suppression of oncogenic signaling and protein synthesis, and modulation of XPO1 protein stability and cellular metabolism. Recent mechanistic findings involving the USP7–XPO1 axis, CRL5–ASB8-mediated XPO1 degradation, and Lipin1–SREBP signaling have further expanded the biological framework of XPO1 inhibition beyond conventional nuclear cargo retention, and the pronounced dependence of malignant plasma cells on nucleocytoplasmic transport provides a coherent biological explanation for the activity of this drug class. Clinical development has established selinexor as an active component of combination therapy in relapsed/refractory MM, and the progressive shift from twice-weekly to lower-dose once-weekly schedules, guided by the pharmacokinetic–pharmacodynamic profile of the drug and supported by proactive toxicity management, has substantially improved its therapeutic feasibility. In contemporary practice, selinexor is best regarded as complementary to, rather than competitive with, BCMA-directed and T-cell-redirecting therapies, with its clearest role in patients who cannot receive, do not respond to, or progress after such treatments. Nevertheless, treatment-related toxicity, heterogeneous sensitivity, the absence of prospectively validated predictive biomarkers, and uncertainty regarding optimal sequencing remain important challenges. Future progress will depend on randomized dose-optimization studies, prospective qualification of biomarkers, and clarification of the role of XPO1 inhibition before and after cellular and bispecific immunotherapy. In practice, selinexor-containing regimens may be considered for selected patients with RRMM according to prior treatment exposure, sensitivity to combination partners, access to alternative therapies, and anticipated tolerability. Their role after BCMA-directed or other T-cell-redirecting therapies remains incompletely defined and requires prospective evaluation.
Author Contributions
Conceptualization: S.K., H.E., B.N.A., T.Z., B.A.C., T.U., M.S.D.; Methodology: S.K., H.E., B.N.A., T.Z., B.A.C., T.U., M.S.D.; Writing—original draft preparation, S.K., H.E., B.N.A., T.Z., B.A.C., T.U., M.S.D.; writing—review and editing, S.K., H.E., B.N.A., T.Z., B.A.C., T.U., M.S.D. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Fung, H.Y.J.; Chook, Y.M. Atomic basis of CRM1-cargo recognition, release and inhibition. Semin. Cancer Biol. 2014, 27, 52–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, X.; Biswas, A.; Süel, K.E.; Jackson, L.K.; Martinez, R.; Gu, H.; Chook, Y.M. Structural basis for leucine-rich nuclear export signal recognition by CRM1. Nature 2009, 458, 1136–1141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Güttler, T.; Madl, T.; Neumann, P.; Deichsel, D.; Corsini, L.; Monecke, T.; Ficner, R.; Sattler, M.; Görlich, D. NES consensus redefined by structures of PKI-type and Rev-type nuclear export signals bound to CRM1. Nat. Struct. Mol. Biol. 2010, 17, 1367–1376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fung, H.Y.J.; Fu, S.C.; Chook, Y.M. Nuclear export receptor CRM1 recognizes diverse conformations in nuclear export signals. eLife 2017, 6, e23961. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neggers, J.E.; Vercruysse, T.; Jacquemyn, M.; Vanstreels, E.; Baloglu, E.; Shacham, S.; Crochiere, M.; Landesman, Y.; Daelemans, D. Identifying drug-target selectivity of small-molecule CRM1/XPO1 inhibitors by CRISPR/Cas9 genome editing. Chem. Biol. 2015, 22, 107–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Turner, J.G.; Dawson, J.; Cubitt, C.L.; Baz, R.; Sullivan, D.M. Inhibition of CRM1-dependent nuclear export sensitizes malignant cells to cytotoxic and targeted agents. Semin. Cancer Biol. 2014, 27, 62–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tai, Y.T.; Landesman, Y.; Acharya, C.; Calle, Y.; Zhong, M.Y.; Cea, M.; Tannenbaum, D.; Cagnetta, A.; Reagan, M.; A Munshi, A.; et al. CRM1 inhibition induces tumor cell cytotoxicity and impairs osteoclastogenesis in multiple myeloma: Molecular mechanisms and therapeutic implications. Leukemia 2014, 28, 155–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neggers, J.E.; Vanstreels, E.; Baloglu, E.; Shacham, S.; Landesman, Y.; Daelemans, D. Heterozygous mutation of cysteine 528 in XPO1 is sufficient for resistance to selective inhibitors of nuclear export. Oncotarget 2016, 7, 68842–68850. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mo, C.C.; Yee, A.J.; Midha, S.; Hartley-Brown, M.A.; Nadeem, O.; O’Donnell, E.K.; Bianchi, G.; Sperling, A.S.; Laubach, J.P.; Richardson, P.G. Selinexor: Targeting a novel pathway in multiple myeloma. EJHaem 2023, 4, 792–810. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gandhi, U.H.; Senapedis, W.; Baloglu, E.; Unger, T.J.; Chari, A.; Vogl, D.; Cornell, R.F. Clinical Implications of Targeting XPO1-Mediated Nuclear Export in Multiple Myeloma. Clin. Lymphoma Myeloma Leuk. 2018, 18, 335–345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Podar, K.; Shah, J.; Chari, A.; Richardson, P.G.; Jagannath, S. Selinexor for the treatment of multiple myeloma. Expert Opin. Pharmacother. 2020, 21, 399–408. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balasubramanian, S.K.; Azmi, A.S.; Maciejewski, J. Selective inhibition of nuclear export: A promising approach in the shifting treatment paradigms for hematological neoplasms. Leukemia 2022, 36, 601–612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Q.; Zhao, R.; Xu, L.; Hao, X.; Tao, S. Treatment of multiple myeloma with selinexor: A review. Ther. Adv. Hematol. 2024, 15, 20406207231219442. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gay, F.; Buda, G.; Petrucci, M.T.; Bolli, N.; Cea, M.; Derudas, D.; Mangiacavallicc, S.; Montefusco, V.; Antonioli, E.; Barilà, G.; et al. Refining the role of selinexor in multiple myeloma: Strategic use in a shifting treatment landscape. ESMO Open 2026, 11, 106054. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Turner, J.G.; Kashyap, T.; Dawson, J.L.; Gomez, J.; Bauer, A.A.; Grant, S.; Dai, Y.; Shain, K.H.; Meads, M.; Landesman, Y.; et al. XPO1 inhibitor combination therapy with bortezomib or carfilzomib induces nuclear localization of IκBα and overcomes acquired proteasome inhibitor resistance in human multiple myeloma. Oncotarget 2016, 7, 78896–78909. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tellier, J.; Nutt, S.L. Plasma Cells: The Programming of an Antibody-Secreting Machine. Eur. J. Immunol. 2019, 49, 30–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carrasco, D.R.; Sukhdeo, K.; Protopopova, M.; Sinha, R.; Enos, M.; Carrasco, D.E.; Zheng, M.; Mani, M.; Henderson, J.; Pinkus, G.S.; et al. The Differentiation and Stress Response Factor XBP-1 Drives Multiple Myeloma Pathogenesis. Cancer Cell 2007, 11, 349–360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obeng, E.A.; Carlson, L.M.; Gutman, D.M.; Harrington, W.J.; Lee, K.P.; Boise, L.H. Proteasome Inhibitors Induce a Terminal Unfolded Protein Response in Multiple Myeloma Cells. Blood 2006, 107, 4907–4916. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaffer, A.L.; Emre, N.C.T.; Lamy, L.; Ngo, V.N.; Wright, G.; Xiao, W.; Powell, J.; Dave, S.; Yu, X.; Zhao, H.; et al. IRF4 Addiction in Multiple Myeloma. Nature 2008, 454, 226–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Xu, J.; Li, Q.; Zhang, Y.; Lin, Z.; Zhai, X.; Wang, F.; Huang, J.; Gao, Q.; Wen, J.; et al. RNA-binding protein hnRNPU regulates multiple myeloma resistance to selinexor. Cancer Lett. 2024, 580, 216486. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van de Donk, N.W.C.J.; Pawlyn, C.; Yong, K.L. Multiple Myeloma. Lancet 2021, 397, 410–427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hideshima, T.; Mitsiades, C.; Tonon, G.; Richardson, P.G.; Anderson, K.C. Understanding Multiple Myeloma Pathogenesis in the Bone Marrow to Identify New Therapeutic Targets. Nat. Rev. Cancer 2007, 7, 585–598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bianchi, G.; Anderson, K.C. Understanding Biology to Tackle the Disease: Multiple Myeloma from Bench to Bedside, and Back. CA Cancer J. Clin. 2014, 64, 422–444. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Argueta, C.; Kashyap, T.; Klebanov, B.; Unger, T.J.; Guo, C.; Harrington, S.; Baloglu, E.; Lee, M.; Senapedis, W.; Shacham, S.; et al. Selinexor synergizes with dexamethasone to repress mTORC1 signaling and induce multiple myeloma cell death. Oncotarget 2018, 9, 25529–25544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bader, J.C.; Abdul Razak, A.R.; Shacham, S.; Xu, H. Pharmacokinetics of selinexor: The first-in-class selective inhibitor of nuclear export. Clin. Pharmacokinet. 2021, 60, 957–969. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karyopharm Therapeutics Inc. XPOVIO (Selinexor) Tablets, for Oral Use: Full Prescribing Information; Karyopharm Therapeutics Inc.: Newton, MA, USA, 2026. [Google Scholar]
- Delimpasi, S.; Mateos, M.V.; Auner, H.W.; Gavriatopoulou, M.; Dimopoulos, M.A.; Quach, H.; Pylypenko, H.; Hájek, R.; Leleu, X.; Dolai, T.K.; et al. Efficacy and tolerability of once-weekly selinexor, bortezomib, and dexamethasone in comparison with standard twice-weekly bortezomib and dexamethasone in previously treated multiple myeloma with renal impairment: Subgroup analysis from the BOSTON study. Am. J. Hematol. 2022, 97, E83–E86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crochiere, M.L.; Baloglu, E.; Klebanov, B.; Donovan, S.; Del Alamo, D.; Lee, M.; Kauffman, M.; Shacham, S.; Landesman, Y. A method for quantification of exportin-1 (XPO1) occupancy by selective inhibitor of nuclear export (SINE) compounds. Oncotarget 2016, 7, 1863–1877. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baljevic, M.; Schiller, G.; Mark, T.M.; Van Domelen, D.R.; Gasparetto, C. Lower dose and weekly schedules of selinexor in multiple myeloma—Updated evidence on safety and efficacy. Front. Oncol. 2025, 15, 1649493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Multidiscipline Review: XPOVIO (Selinexor) NDA 212306; Center for Drug Evaluation and Research: Silver Spring, MD, USA, 2019.
- Gavriatopoulou, M.; Chari, A.; Chen, C.; Bahlis, N.; Vogl, D.T.; Jakubowiak, A.; Dingli, D.; Cornell, R.F.; Hofmeister, C.C.; Siegel, D.; et al. Integrated Safety Profile of Selinexor in Multiple Myeloma: Experience from 437 Patients Enrolled in Clinical Trials. Leukemia 2020, 34, 2190–2200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chari, A.; Vogl, D.T.; Gavriatopoulou, M.; Nooka, A.K.; Yee, A.J.; Huff, C.A.; Moreau, P.; Dingli, D.; Cole, C.; Lonial, S.; et al. Oral selinexor–dexamethasone for triple-class refractory multiple myeloma. N. Engl. J. Med. 2019, 381, 727–738. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mikhael, J.; Noonan, K.R.; Faiman, B.; Gleason, C.; Nooka, A.K.; Costa, L.J.; Jagannath, S.; Richardson, P.G.; Siegel, D.; Chari, A.; et al. Consensus recommendations for the clinical management of patients with multiple myeloma treated with selinexor. Clin. Lymphoma Myeloma Leuk. 2020, 20, 351–357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, C.; Siegel, D.; Gutierrez, M.; Jacoby, M.; Hofmeister, C.C.; Gabrail, N.; Baz, R.; Mau-Sorensen, M.; Berdeja, J.G.; Savona, M.; et al. Safety and efficacy of selinexor in relapsed or refractory multiple myeloma and Waldenström macroglobulinemia. Blood 2018, 131, 855–863. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vogl, D.T.; Dingli, D.; Cornell, R.F.; Huff, C.A.; Jagannath, S.; Bhutani, D.; Zonder, J.; Baz, R.; Nooka, A.; Richter, J.; et al. Selective inhibition of nuclear export with oral selinexor for treatment of relapsed or refractory multiple myeloma. J. Clin. Oncol. 2018, 36, 859–866. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grosicki, S.; Simonova, M.; Spicka, I.; Pour, L.; Kriachok, I.; Gavriatopoulou, M.; Pylypenko, H.; Auner, H.W.; Leleu, X.; Doronin, V.; et al. Once-per-week selinexor, bortezomib, and dexamethasone versus twice-per-week bortezomib and dexamethasone in patients with multiple myeloma (BOSTON): A randomised, open-label, phase 3 trial. Lancet 2020, 396, 1563–1573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, D.; Schiller, G.J.; Madan, S.; Lentzsch, S.; Chubar, E.; Lavi, N.; Van Domelen, D.R.; Bentur, O.S.; Baljevic, M. Efficacy and safety of once-weekly selinexor 40 mg versus 60 mg with pomalidomide and dexamethasone in relapsed and/or refractory multiple myeloma. Front. Oncol. 2024, 14, 1352281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zorlu, T.; Aslan Candir, B.; Uncu Ulu, B.; Iskender, D.; Yigenoglu, T.N.; Ulas, T.; Dal, M.S.; Altuntas, F. Prevention of selinexor-induced nausea/vomiting and diarrhea in the first month of therapy: A novel step-up dosing approach. In Proceedings of the 12th World Congress on Controversies in Multiple Myeloma (COMy), Paris, France, 14–17 May 2026. [Google Scholar]
- Wing, C.E.; Fung, H.Y.J.; Kwanten, B.; Cagatay, T.; Niesman, A.B.; Jacquemyn, M.; Gharghabi, M.; Permentier, B.; Shakya, B.; Nandi, R.; et al. SINE compounds activate exportin 1 degradation through an allosteric mechanism. Nat. Chem. Biol. 2025, 21, 2002–2013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Chen, M.; Jiang, J.; Wan, Y.; Li, X.; Zhang, M.; Xiao, F.; Zhong, L.; Zhong, H.; Qin, Z.; et al. Targeting deubiquitinase USP7-mediated stabilization of XPO1 contributes to the anti-myeloma effects of selinexor. J. Transl. Med. 2025, 23, 62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.Y.; Chen, M.P.; Jiang, J.X.; Wan, Y.K.; Li, X.; Zhang, Y.W.; Fang, Y.; Huang, H.-H.; Qin, Z.-Y.; Hou, J. Lipin1-dependent transcriptional inactivation of SREBPs contributes to selinexor sensitivity in multiple myeloma. Acta Pharmacol. Sin. 2025, 46, 2496–2508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tasbihi, K.; Bruns, H. Selinexor’s immunomodulatory impact in advancing multiple myeloma treatment. Cells 2025, 14, 430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khouri, J.; Sborov, D.; Rossi, A.; Martin, T.; Kashyap, T.; Mark, T.; Baljevic, M. Focusing on selinexor for holding and bridging prior to CAR-T in relapsed/refractory multiple myeloma. J. Clin. Med. 2025, 14, 4071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, S.; Fu, J.; Walker, C.J.; Yang, J.; Bhutani, D.; Chakraborty, R.; Mamillapalli, N.; Mapara, M.Y.; Landesman, Y.; Lentzsch, S. Dual targeting of protein translation and nuclear protein export results in enhanced antimyeloma effects. Blood Adv. 2023, 7, 2926–2937. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kashyap, T.; Argueta, C.; Aboukameel, A.; Unger, T.J.; Klebanov, B.; Mohammad, R.M.; Muqbil, I.; Azmi, A.S.; Drolen, C.; Senapedis, W.; et al. Selinexor, a selective inhibitor of nuclear export (SINE) compound, acts through NF-κB deactivation and combines with proteasome inhibitors to synergistically induce tumor cell death. Oncotarget 2016, 7, 78883–78895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gasparetto, C.; Lentzsch, S.; Schiller, G.; Callander, N.; Tuchman, S.; Chen, C.; White, D.; Kotb, R.; Sutherland, H.; Sebag, M.; et al. Selinexor, daratumumab, and dexamethasone in patients with relapsed or refractory multiple myeloma. EJHaem 2021, 2, 56–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gasparetto, C.; Schiller, G.J.; Tuchman, S.A.; Callander, N.S.; Baljevic, M.; Lentzsch, S.; Rossi, A.C.; Kotb, R.; White, D.; Bahlis, N.J.; et al. Once-weekly selinexor, carfilzomib, and dexamethasone in carfilzomib non-refractory multiple myeloma patients. Br. J. Cancer 2022, 126, 718–725. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Richard, S.; Chari, A.; Delimpasi, S.; Simonova, M.; Spicka, I.; Pour, L.; Kriachok, I.; Dimopoulos, M.A.; Pylypenko, H.; Auner, H.W.; et al. Selinexor, bortezomib, and dexamethasone versus bortezomib and dexamethasone in previously treated multiple myeloma: Outcomes by cytogenetic risk. Am. J. Hematol. 2021, 96, 1120–1130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ClinicalTrials.gov. Study of Selinexor, Pomalidomide and Dexamethasone (SPd) Versus Elotuzumab, Pomalidomide and Dexamethasone (EPd) in Participants with Relapsed or Refractory Multiple Myeloma (XPORT-MM-031/EMN29); Identifier NCT05028348. Available online: https://clinicaltrials.gov/study/NCT05028348 (accessed on 23 October 2026).
- Biran, N.; Zolotov, E.; Vesole, D.; Parmar, H.; Phull, P.; Doucette, K.; Roney, P.; Ahn, J.; Feinman, R.; Zenreich, J.; et al. A phase IIb study of selinexor in combination with daratumumab in patients with daratumumab-refractory multiple myeloma. Haematologica 2025, 110, 2493–2497. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- González-Calle, V.; Rodríguez-Otero, P.; Sureda, A.; De Arriba, F.; Reinoso, M.; Ribas, P.; González-Rodríguez, A.P.; González, Y.; Oriol, A.; Martínez-López, J.; et al. Selinexor, daratumumab, bortezomib, and dexamethasone for the treatment of patients with relapsed or refractory multiple myeloma: Results of the phase II, non-randomized, multicenter GEM-SELIBORDARA study. Haematologica 2024, 109, 2219–2229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, H.; Wang, L.; Chu, X.; Wang, W.J.; Wang, L. Efficacy and safety of selinexor, carfilzomib, pomalidomide and dexamethasone in the treatment of MM with extramedullary disease: A prospective multi-center study. Hematol. Oncol. 2025, 43, e773_70096. [Google Scholar] [CrossRef] [Scilit]
- Whiteley, A.; Ijioma, S.C.; Ray, D.; Langerman, S.S.; Hu, E.; Pierre, A.; Mark, T.; Yimer, H. Real-world treatment patterns and survival outcomes of patients with relapsed/refractory multiple myeloma treated with a selinexor-containing triplet-based regimen. Curr. Oncol. 2025, 32, 268. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costa, B.A.; Dima, D.; Mark, T.; Sadek, N.L.; Ijioma, S.; Ray, D.; Goel, U.; Dranitsaris, G.; Sheng, T.; Moshier, E.; et al. Impact of prior selinexor exposure on outcomes of chimeric antigen receptor T-cell therapy for relapsed/refractory multiple myeloma: An exploratory analysis. J. Clin. Med. 2025, 14, 1316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berdeja, J.G.; Madduri, D.; Usmani, S.Z.; Jakubowiak, A.; Agha, M.; Cohen, A.D.; Stewart, A.K.; Hari, P.; Htut, M.; Lesokhin, A.; et al. Ciltacabtagene Autoleucel, a B-Cell Maturation Antigen-Directed Chimeric Antigen Receptor T-Cell Therapy in Patients with Relapsed or Refractory Multiple Myeloma (CARTITUDE-1): A Phase 1b/2 Open-Label Study. Lancet 2021, 398, 314–324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Munshi, N.C.; Anderson, L.D.; Shah, N.; Madduri, D.; Berdeja, J.; Lonial, S.; Raje, N.; Lin, Y.; Siegel, D.; Oriol, A.; et al. Idecabtagene Vicleucel in Relapsed and Refractory Multiple Myeloma. N. Engl. J. Med. 2021, 384, 705–716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moreau, P.; Garfall, A.L.; van de Donk, N.W.C.J.; Nahi, H.; San-Miguel, J.F.; Oriol, A.; Nooka, A.K.; Martin, T.; Rosinol, L.; Chari, A.; et al. Teclistamab in Relapsed or Refractory Multiple Myeloma. N. Engl. J. Med. 2022, 387, 495–505. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lesokhin, A.M.; Tomasson, M.H.; Arnulf, B.; Bahlis, N.J.; Miles Prince, H.; Niesvizky, R.; Rodríguez-Otero, P.; Martinez-Lopez, J.; Korde, N.; Martin, T.; et al. Elranatamab in Relapsed or Refractory Multiple Myeloma: Phase 2 MagnetisMM-3 Trial Results. Nat. Med. 2023, 29, 2259–2267. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chari, A.; Minnema, M.C.; Berdeja, J.G.; Oriol, A.; van de Donk, N.W.; Rodríguez-Otero, P.; Askari, E.; Mateos, M.-V.; Costa, L.J.; Caers, J.; et al. Talquetamab, a T-Cell-Redirecting GPRC5D Bispecific Antibody for Multiple Myeloma. N. Engl. J. Med. 2022, 387, 2232–2244. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hungria, V.; Robak, P.; Hus, M.; Zherebtsova, V.; Ward, C.; Ho, P.J.; Ribas de Almeida, A.C.; Hajek, R.; Kim, K.; Grosicki, S.; et al. Belantamab Mafodotin, Bortezomib, and Dexamethasone for Multiple Myeloma. N. Engl. J. Med. 2024, 391, 393–407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dimopoulos, M.A.; Beksac, M.; Pour, L.; Delimpasi, S.; Vorobyev, V.; Quach, H.; Spicka, I.; Radocha, J.; Robak, P.; Kim, K.; et al. Belantamab Mafodotin, Pomalidomide, and Dexamethasone in Multiple Myeloma. N. Engl. J. Med. 2024, 391, 408–421. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chari, A.; Vogl, D.T.; Jagannath, S.; Jasielec, J.; Unger, T.J.; DeCastro, A.; Shah, J.; Kauffman, M.; Shacham, S.; Jakubowiak, A. Selinexor-based regimens for the treatment of myeloma refractory to chimeric antigen receptor T cell therapy. Br. J. Haematol. 2020, 189, e126–e130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tomasik, J.; Shouval, R.; Gafter-Gvili, A.; Topiłko, J.; Bilicki, D.; Basak, G.W. Salvage therapies after anti-BCMA CAR-T failure in patients with multiple myeloma: A meta-analysis of response rates. Eur. J. Haematol. 2026, 116, 663–673. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Afrough, A.; Hashmi, H.; Hansen, D.K.; Sidana, S.; Ahn, C.; Peres, L.C.; Dima, D.; Freeman, C.L.; Puglianini, O.C.; Kocoglu, M.H.; et al. Real-world impact of bridging therapy on outcomes of ide-cel for myeloma in the US Myeloma Immunotherapy Consortium. Blood Cancer J. 2024, 14, 63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, D.; Fu, H.; Que, Y.; Ruan, H.; Xu, M.; Long, X.; Yu, Q.; Li, C.; Li, Z.; Cai, S.; et al. A novel two-step administration of XPO-1 inhibitor may enhance the effect of anti-BCMA CAR-T in relapsed/refractory extramedullary multiple myeloma. J. Transl. Med. 2023, 21, 812. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ClinicalTrials.gov. A Phase II Safety and Efficacy Study of Selinexor in Combination with Bispecific Antibody in Patients with Relapsed/Refractory Multiple Myeloma; Identifier NCT06822972. Available online: https://clinicaltrials.gov/study/NCT06822972 (accessed on 23 October 2026).
- ClinicalTrials.gov. Selinexor Maintenance Post CAR-T Cell Therapy for Multiple Myeloma; Identifier NCT07200102. Available online: https://clinicaltrials.gov/study/NCT07200102 (accessed on 23 October 2026).
- Restrepo, P.; Bhalla, S.; Ghodke-Puranik, Y.; Aleman, A.; Leshchenko, V.; Melnekoff, D.T.; Agte, S.; Jiang, J.; Madduri, D.; Richter, J.; et al. A three-gene signature predicts response to selinexor in multiple myeloma. JCO Precis. Oncol. 2022, 6, e2200147. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bohlius, J.; Bohlke, K.; Castelli, R.; Djulbegovic, B.; Lustberg, M.B.; Martino, M.; Mountzios, G.; Peswani, N.; Porter, L.; Tanaka, T.N.; et al. Management of Cancer-Associated Anemia with Erythropoiesis-Stimulating Agents: ASCO/ASH Clinical Practice Guideline Update. J. Clin. Oncol. 2019, 37, 1336–1351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, R.; Kotchetkov, R.; Lancman, G.; White, D. Selinexor for Multiple Myeloma in the Canadian Landscape: Where Are We Today? In Dialogues in Multiple Myeloma; Catalytic Health: Toronto, ON, Canada, 2025. [Google Scholar]
- Muscaritoli, M.; Arends, J.; Bachmann, P.; Baracos, V.; Barthelemy, N.; Bertz, H.; Bozzetti, F.; Hütterer, E.; Isenring, E.; Kaasa, S.; et al. ESPEN practical guideline: Clinical nutrition in cancer. Clin. Nutr. 2021, 40, 2898–2913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hing, Z.A.; Fung, H.Y.J.; Ranganathan, P.; Mitchell, S.; El-Gamal, D.; Woyach, J.A.; Williams, K.; Goettl, V.M.; Smith, J.; Yu, X.; et al. Next-generation XPO1 inhibitor shows improved efficacy and in vivo tolerability in hematological malignancies. Leukemia 2016, 30, 2364–2372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cornell, R.F.; Baz, R.; Richter, J.R.; Rossi, A.; Vogl, D.T.; Chen, C.; Shustik, C.; Alvarez, M.J.; Shen, Y.; Unger, T.J.; et al. A phase 1 clinical trial of oral eltanexor in patients with relapsed or refractory multiple myeloma. Am. J. Hematol. 2022, 97, E54–E58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sadowski, A.R.; Gardner, H.L.; Borgatti, A.; Wilson, H.; Vail, D.M.; Lachowicz, J.; Manley, C.; Turner, A.; Klein, M.K.; Waite, A. Phase II Study of the Oral Selective Inhibitor of Nuclear Export (SINE) KPT-335 (Verdinexor) in Dogs with Lymphoma. BMC Vet. Res. 2018, 14, 250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lapalombella, R.; Sun, Q.; Williams, K.; Tangeman, L.; Jha, S.; Zhong, Y.; Goettl, V.; Mahoney, E.; Berglund, C.; Gupta, S.; et al. Selective Inhibitors of Nuclear Export Show That CRM1/XPO1 Is a Target in Chronic Lymphocytic Leukemia. Blood 2012, 120, 4621–4634. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sakakibara, K.; Saito, N.; Sato, T.; Suzuki, A.; Hasegawa, Y.; Friedman, J.M.; Kufe, D.W.; VonHoff, D.D.; Iwami, T.; Kawabe, T. CBS9106 Is a Novel Reversible Oral CRM1 Inhibitor with CRM1 Degrading Activity. Blood 2011, 118, 3922–3931. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Barve, M.; Chiorean, E.; LoRusso, P.; Courtney, K.; Qi, D.; Bullington, J.; Sardone, M.; Chen, J.; Brooks, C. Interim Results from a Trial of SL-801, a Novel XPO-1 Inhibitor, in Patients with Advanced Solid Tumors. Ann. Oncol. 2019, 30, v175. [Google Scholar] [CrossRef] [Scilit]
- Sonneveld, P.; Terpos, E.; Boccadoro, M.; Delimpasi, S.; Beksac, M.; Katodritou, E.; Moreau, P.; Baldini, L.; Symeonidis, A.; Bila, J.; et al. Pomalidomide and Dexamethasone with or without Subcutaneous Daratumumab in Patients with Relapsed or Refractory Multiple Myeloma: Updated Analysis of the Phase 3 Apollo Study. Blood 2021, 138, 2747. [Google Scholar] [CrossRef] [Scilit]
- Mateos, M.V.; Sonneveld, P.; Hungria, V.; Nooka, A.K.; Estell, J.A.; Barreto, W.; Corradini, P.; Min, C.-K.; Medvedova, E.; Weisel, K.; et al. Daratumumab, Bortezomib, and Dexamethasone Versus Bortezomib and Dexamethasone in Patients with Previously Treated Multiple Myeloma: Three-year Follow-up of CASTOR. Clin. Lymphoma Myeloma Leuk. 2020, 20, 509–518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bringhen, S.; Pour, L.; Vorobyev, V.; Vural, F.; Warzocha, K.; Benboubker, L.; Koh, Y.; Maisnar, V.; Karlin, L.; Pavic, M.; et al. Isatuximab plus pomalidomide and dexamethasone in patients with relapsed/refractory multiple myeloma according to prior lines of treatment and refractory status: ICARIA-MM subgroup analysis. Leuk. Res. 2021, 104, 106576. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hungria, V.; Robak, P.; Hus, M.; Zherebtsova, V.; Ward, C.; Ho, P.J.; de Almeida, A.C.; Hájek, R.; Kim, K.; Grosicki, S.; et al. Outcomes in Second-Line Lenalidomide-Refractory Patients in the Phase 3 DREAMM-7 Study of Belantamab Mafodotin, Bortezomib (V), and Dexamethasone (d) vs Daratumumab-Vd in RRMM. Clin. Lymphoma Myeloma Leuk. 2025, 25, S333–S334. [Google Scholar] [CrossRef] [Scilit]
- Mateos, M.V.; Engelhardt, M.; Leleu, X.; Mesa, M.G.; Cavo, M.; Dimopoulos, M.; Bianco, M.; Merlo, G.M.; la Porte, C.; Richardson, P.G.; et al. Impact of prior treatment on selinexor, bortezomib, dexamethasone outcomes in patients with relapsed/refractory multiple myeloma: Extended follow-up subgroup analysis of the BOSTON trial. Eur. J. Haematol. 2024, 113, 242–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harding, D.T.; Graham, L.V.; Bartlett, L.G.; Gudgeon, N.; Fisher, J.G.; Walker, C.J.; Kashyap, T.; E Brookes, C.; Haslam, A.; McIlroy, G.; et al. Selinexor potentiates NK cell activation against multiple myeloma. Clin. Exp. Immunol. 2026, 220, uxag059. [Google Scholar] [CrossRef] [Scilit] [PubMed]
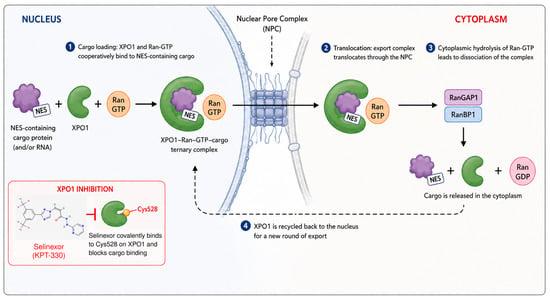
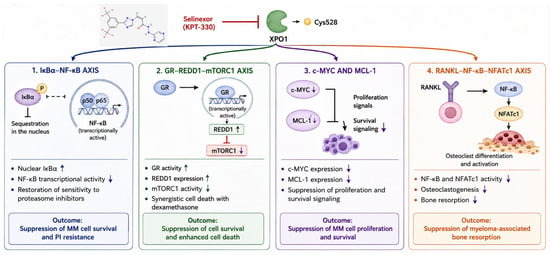
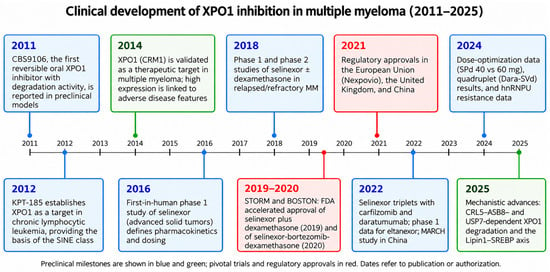
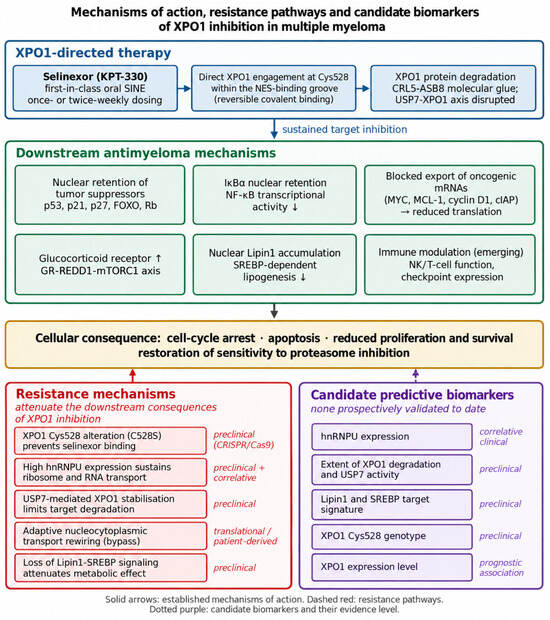

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.