


Abstract
Malignant fibrous histiocytoma of bone is the osseous counterpart of the tumor in soft tissue. It is a rare primary bone tumor, and there have been conflicting reports on its grades of malignancy. The appendicular skeleton, especially the femur, is the most common site of involvement, whereas the calcaneus is rarely involved. We describe a primary malignant fibrous histiocytoma of the calcaneal bone in a 21-year-old man. The patient underwent neoadjuvant and adjuvant chemotherapy and below-the-knee amputation, and no local recurrence or metastasis was noted after 2 years of follow-up. (J Am Podiatr Med Assoc 97(3): 218–222, 2007)
Malignant fibrous histiocytoma of bone is the osseous counterpart of the tumor in soft tissue. It is a rare primary bone tumor, and there have been conflicting reports on its grades of malignancy. A typical neoplasm is one that shows fibrogenic differentiation, often in a storiform pattern, alternating with regions of cells that appear histiocytic. [1,2] In recent years, increasing numbers of patients with primary or secondary malignant bone tumors with histologic characteristics identical to those of malignant fibrous histiocytoma originating in soft tissues have been reported. [3] The appendicular skeleton, especially the femur, was the most common site of involvement, whereas the calcaneus was rarely involved. [4] We describe a primary malignant fibrous histiocytoma of the calcaneal bone.
Case Report
A 21-year-old man complained of progressively worsening pain and a mass on the left foot and ankle (especially on the heel) of 6 months’ duration. He was otherwise healthy. The patient was evaluated by means of detailed clinical and laboratory examination that included history, standard radiographs of the calcaneus, total-body bone scintigraphy, chest tomography, and foot and ankle magnetic resonance imaging. Physical examination of the left ankle and foot revealed moderate effusion and tenderness of the foot. Results of routine laboratory studies were normal.
Standard radiographs showed an osteolytic and eccentric lesion in the body of the calcaneus (Figure 1). Computed tomography revealed a purely lytic and poorly marginated lesion with cortical destruction. Periosteal reactions and endosteal scalloping with medial and lateral cortical bone destruction were present (Figure 2). Chest tomography findings were normal.
Scintigraphic examination revealed increased uptake in and around the os calcis. After injection of radiotracer, there was linear reserve of radiotracer at the border of the articular surface of the talus with the calcaneus (Figure 3). The scan was otherwise normal.
Magnetic resonance imaging demonstrated a tumoral mass that showed destruction and extension through the calcaneus, displacing the cuboid bone anteriorly. The inferolateral aspect of the talus and cuboid bones was hypointense on T1-weighted series (Figure 4A ) and hyperintense on T2-weighted series with fat suppression (Figure 4B). Signal records were more compatible with edema and inactivation osteoporosis. After paramagnetic contrast fluid injection, there was a contrast view of the lesion measuring 5 × 6.5 × 8 cm (Figure 4C ). According to the Enneking staging system, it was a stage IIB lesion. Open biopsy of the lytic lesion revealed a malignant spindle cell tumor with morphological features compatible with malignant fibrous histiocytoma (Figure 5).
We applied three cycles of neoadjuvant chemotherapy with doxorubicin (35 mg/day), cisplatin (50 mg/day), and ifosfamide (4 g/day). After neoadjuvant chemotherapy, the patient underwent below-the-knee amputation. Because there were no tumor cells in the vicinity of the surgical margins after histologic examination, it was considered a radical amputation (Figure 6 ). On pathologic examination, response to chemotherapy as an indicator of the tumor necrosis ratio was reported as 50%. Therefore, doxorubicin was replaced with etoposide (185 mg/day) for an additional six cycles of adjuvant chemotherapy. The patient was followed up for 2 years. Chest radiographs were taken every 2 months, and the lungs were examined using computed tomography every 6 months. At the end of 2 years of follow-up, no local recurrence or metastasis was noted.
Discussion
Although malignant fibrous histiocytoma is well known as a tumor of the soft tissues, it also occurs rarely as a primary tumor in bone. [5] As a soft-tissue tumor, it occurs predominantly in the extremities. Spanier et al [6] reported 11 cases; Huvos, [7] 18 cases; Feldman and Lattes, [8] 23 cases; Dahlin et al, [9] 35 cases; and Kahn et al, [10] 7 cases of an identical tumor in bone.
Malignant fibrous histiocytoma of bone occurs predominantly in middle-aged individuals and is frequently associated with other underlying bone lesions. [3] Histologically, malignant fibrous histiocytoma of bone should be differentiated from other sarcomas. This differentiation may be difficult in biopsy material because many other malignant bone tumors, most notably osteosarcomas, may contain areas indistinguishable morphologically from a malignant fibrous histiocytoma with a storiform pattern. Lack of immature bone and cartilage production in malignant fibrous histiocytoma helps differentiate it from osteosarcomas. Histologic differentiation from benign fibrous histiocytoma rests on evaluation of cytologic detail. Also, most benign fibrous histiocytomas have a characteristically benign radiologic appearance. Giant cell tumor of bone may contain fibrous histiocytoma–like components histologically, and one should consider the characteristic radiology of this tumor. [2]
Huvos et al [4] reported that most patients were middle-aged or older adults with a mean age of 40.5 years; only 21.5% of the patients were 21 years or younger. The ages of the 11 patients reported by Spanier et al [6] varied from 18 to 68 years. The age range of the 23 patients reported by Feldman and Lattes [8] was 9 to 79 years. Malignant fibrous histiocytoma associated with other lesions occurs predominantly in men older than 40 years. Huvos et al [4] reported that a survival difference related to age was found; those who were 21 years or younger had a statistically significantly better prognosis compared with those who were older. Our patient was 21 years old and had a primary malignant fibrous histiocytoma of bone at the calcaneal region.
Malignant fibrous histiocytoma shows a propensity to involve the lower extremities. Although various bones are affected, the long bones of the knee region are the most common site. [4,11,12] Huvos et al [4] reported that the femur was the most frequently affected site, accounting for almost one-third of all cases; the lower extremity was the most common region affected in more than half of the patients. Bacci et al [1] reported that the tumor site was around the knee in 68% of the cases. Kahn et al [10] reported that all of the tumors were localized at the femur and the tibia. Only one patient was reported with malignant fibrous histiocytoma at the calcaneal region. [1,10] These reports indicate that the tumor location in the present case is a rare one.
The Enneking staging system has been shown to be of prognostic value. Low-grade intracompartmental tumors (stage IA) have the best prognosis, and high-grade extracompartmental tumors (stage IIB) have the worst prognosis. [13] Bacci et al [1] reported that five tumors in their series did not show a soft-tissue component (stage II), whereas 25 tumors extended extraosseously (stage IIB), and 61% of patients had been treated by amputation. In the patient described here, the tumor stage was IIB, and we also performed a below-the-knee amputation. High-grade malignant fibrous histiocytoma of bone should be treated by radical surgery even if metastases were detected at the time of diagnosis. The lung is the most common site for metastases. Rooser et al [14] reported that metastases were present in the lungs in 25% of patients at the time of diagnosis. Many previous studies [7,8,15-17] of patients with malignant fibrous histiocytoma of bone reported that most patients had subclinical pulmonary micrometastases. For this reason, we performed three cycles of neoadjuvant chemotherapy with a combination of doxorubicin, cisplatin, and ifosfamide.
The use of neoadjuvant chemotherapy and delayed surgery has been proved to be a successful model for the treatment of osteogenic sarcoma. This model of treatment also seems to be useful for evaluating the clinical and histologic responses to chemotherapy in other malignant tumors, especially malignant fibrous histiocytoma. [3,18]
Several authors [2,3] reported a correlation between local recurrence and tumor-related death, and some reports showed that the prognosis in malignant fibrous histiocytoma was similar to that in high-grade osteosarcomas and fibrosarcomas. Bielack et al [19] reported that the prognosis for 23 patients whose malignant fibrous histiocytoma responded well to preoperative chemotherapy was excellent, with only one of them developing metastases and none with local recurrence. Urban et al [3] observed good clinical responses in all patients. No local recurrence or metastasis was observed in our patient in 2 years of follow-up.
Conclusion
Although malignant fibrous histiocytoma is well known as a tumor of the soft tissues, it may also occur as a primary tumor in bone. The appendicular skeleton, especially the femur, is the most common site of involvement, whereas the calcaneus is rarely involved. Malignant fibrous histiocytoma of bone should be differentiated histologically from other sarcomas, most notably osteosarcomas, which may contain areas indistinguishable morphologically from a malignant fibrous histiocytoma with a storiform pattern.
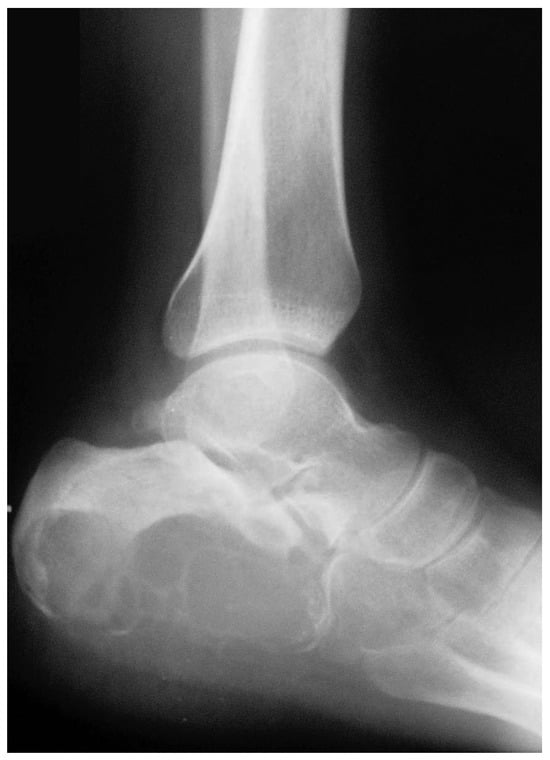
Figure 1.
Lateral radiograph illustrating the osteolytic lesion of the calcaneus.
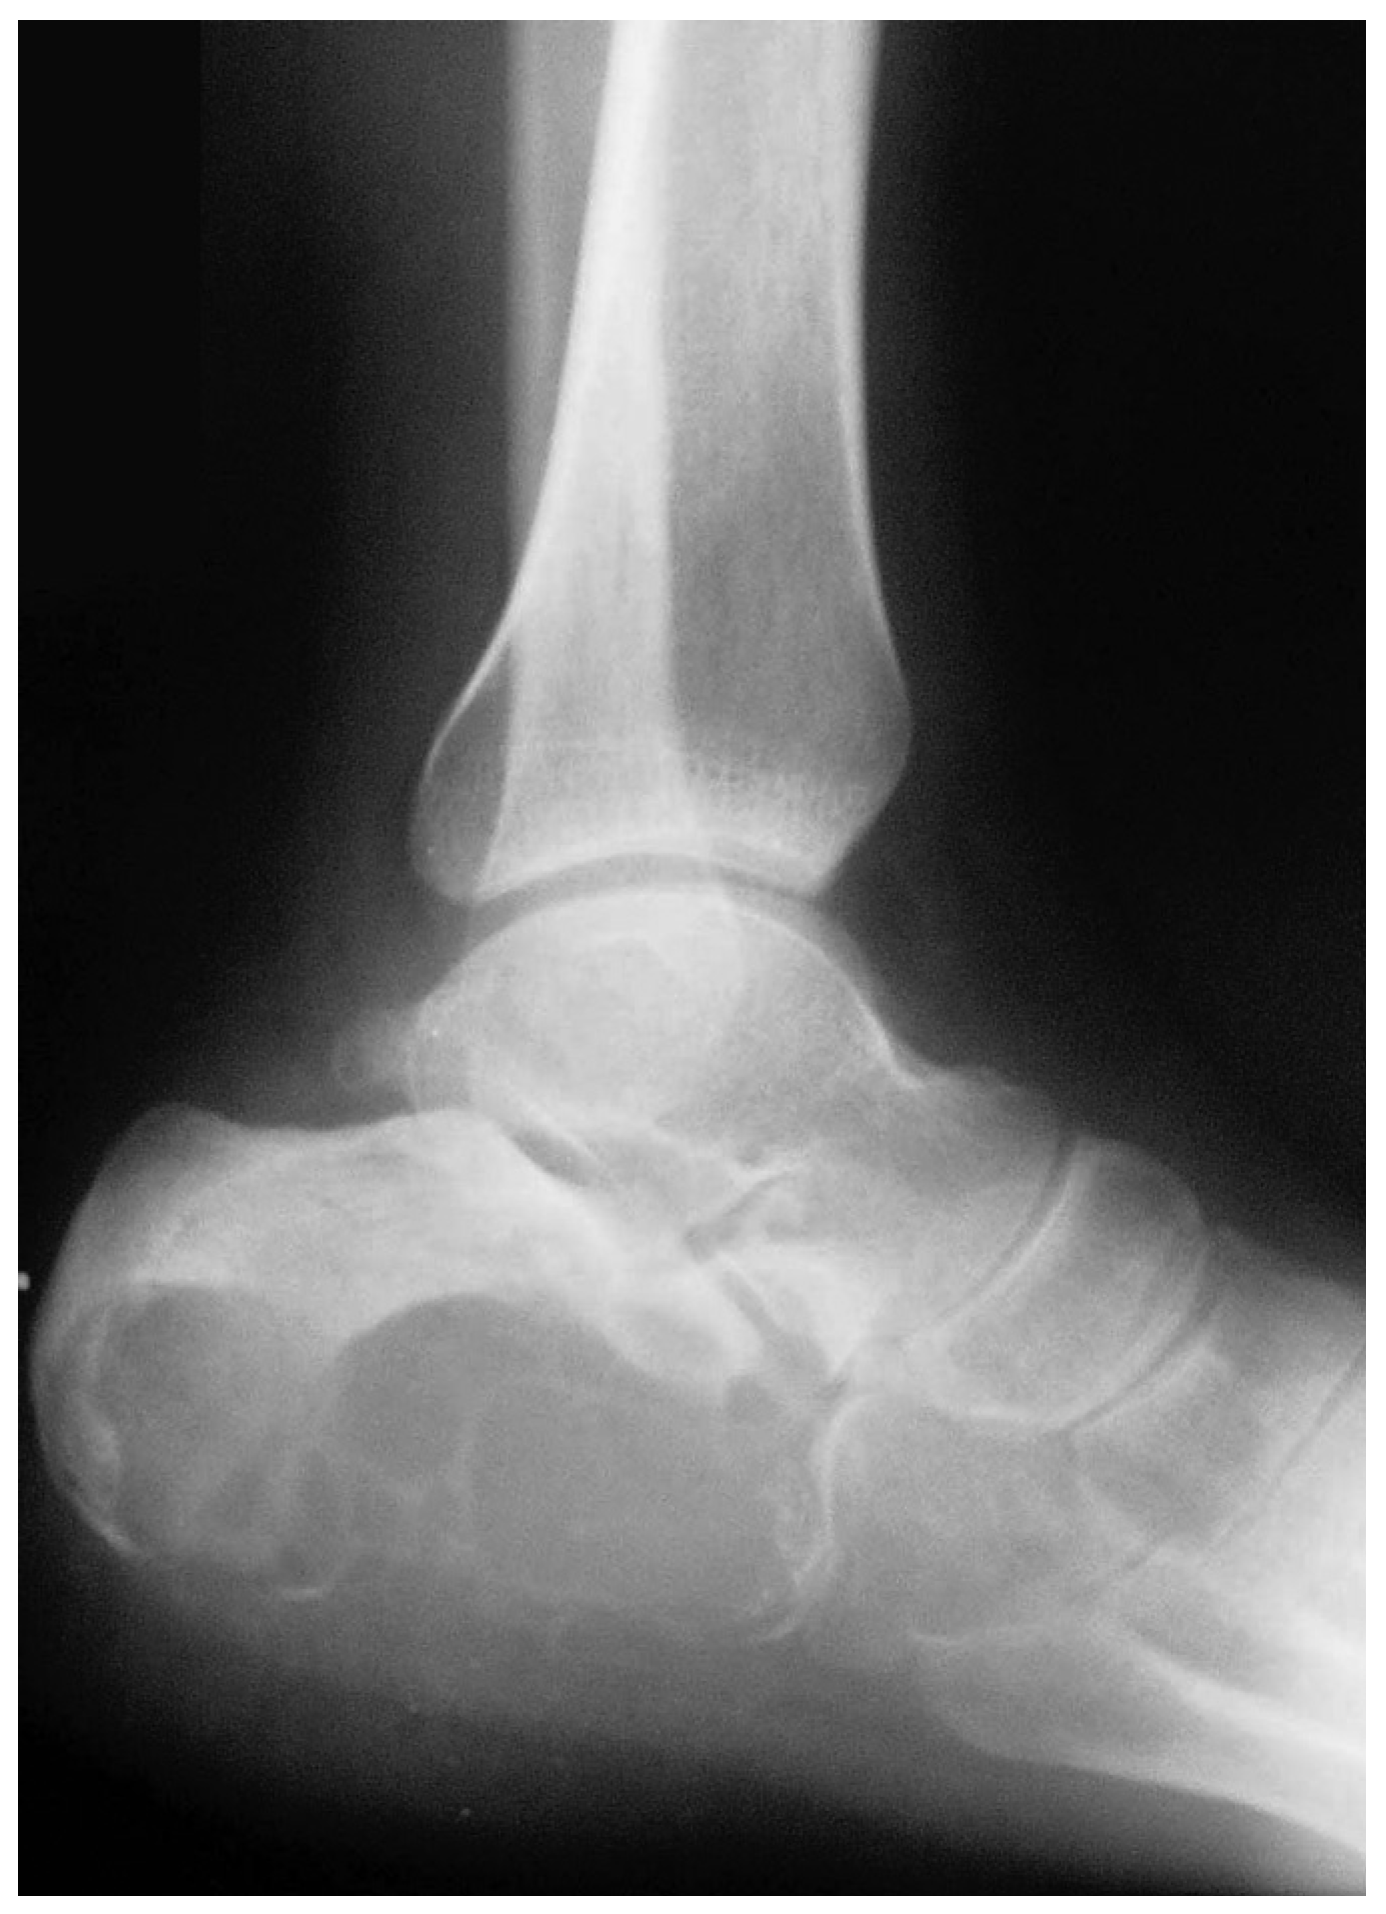
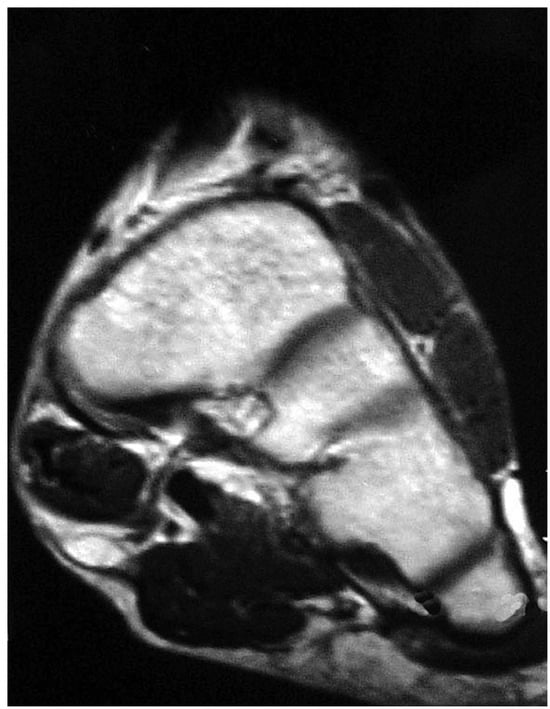
Figure 2.
Axial computed tomogram of the calcaneus with 3-mm sections demonstrated an osteolytic lesion eroding cortical bone.
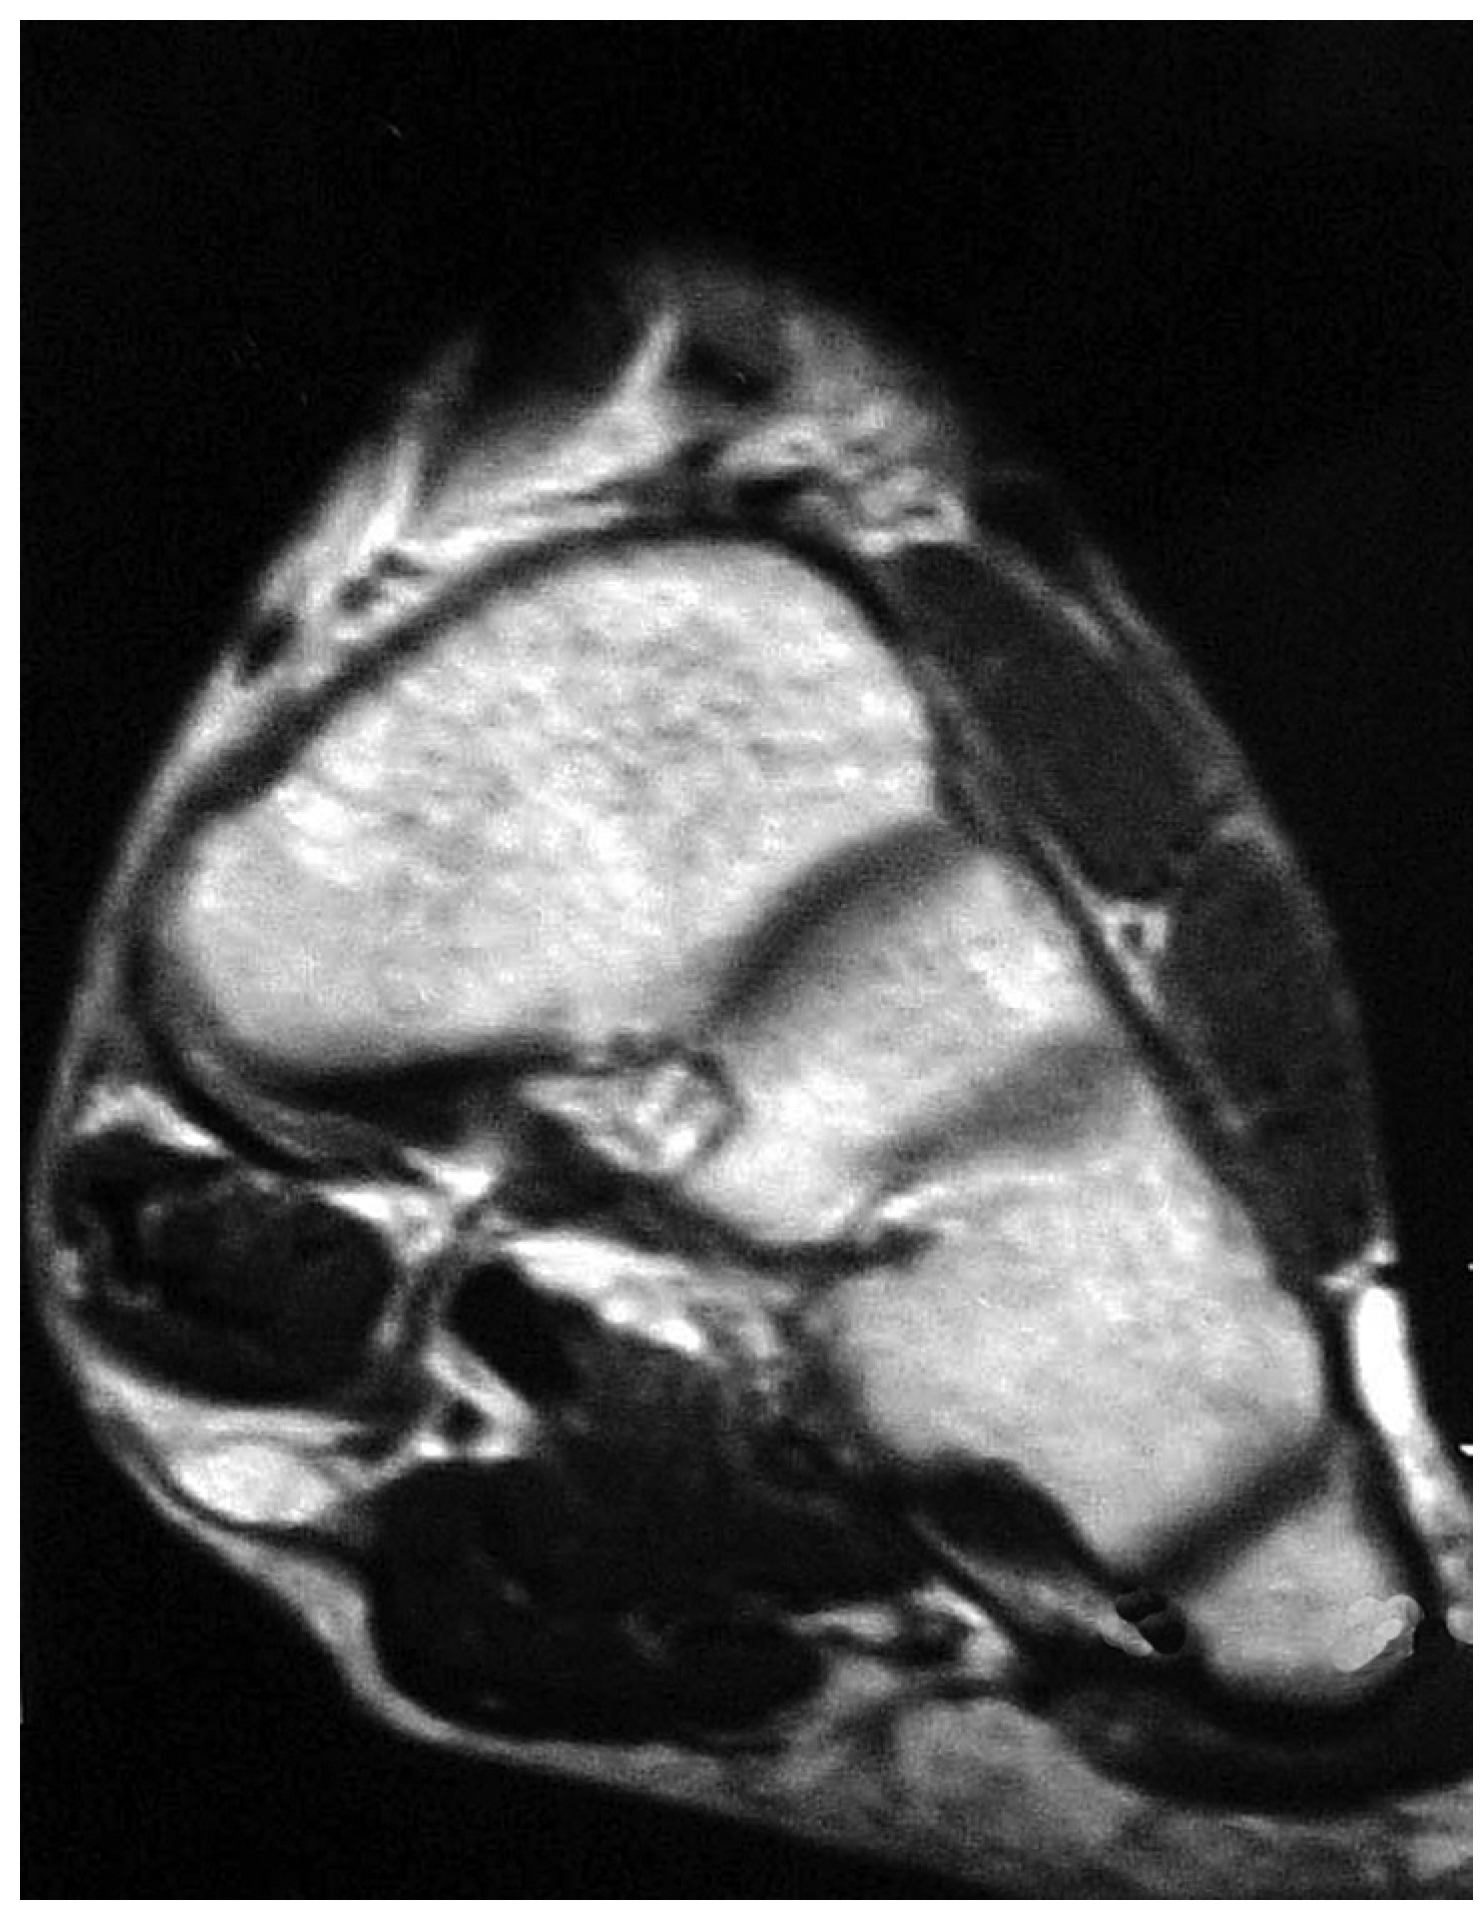
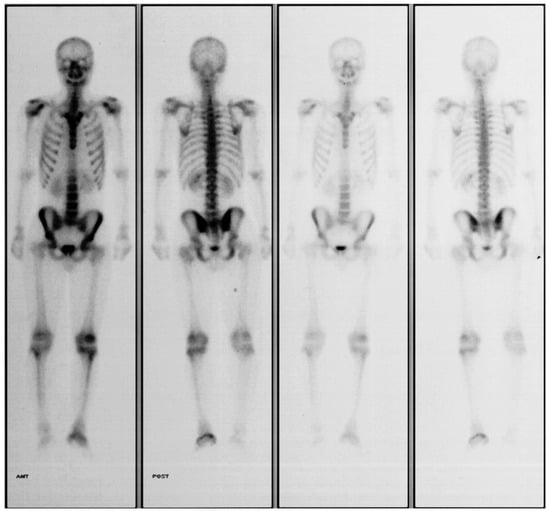
Figure 3.
Scintigraphic examination showed a linear reserve of radiotracer at the border of the articular surface of the talus with the calcaneus.
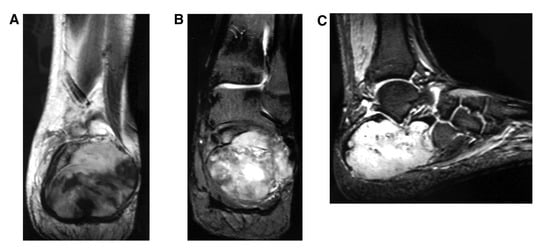
Figure 4.
A, The inferolateral aspect of the talus and cuboid bones was hypointense on T1-weighted magnetic resonance images. B, The talus and cuboid bones were hyperintense on T2-weighted images with fat suppression. C, After paramagnetic contrast fluid injection, there was a contrast view of the lesion.
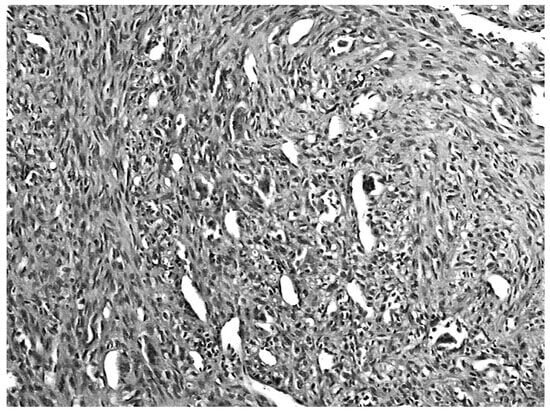
Figure 5.
Histologically, the lesion consisted of atypical cells with a fibroblastic or histiocytic appearance. The dominating pattern was storiform. Atypical osteoid or tumoral bone production was not seen (H&E, ×100).
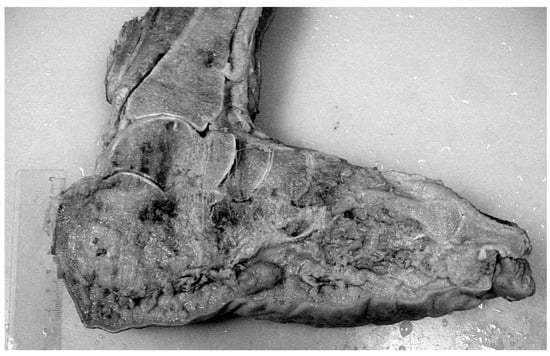
Figure 6.
Bisected calcaneal bone from the below-the-knee amputation specimen. The tumor infiltrates the medullary bone and the cortex to invade adjacent soft tissues.
Financial Disclosures: None reported. | |
Conflict of Interest: None reported. |
References
- Bacci G, Springfield D, Capanna R, et al: Adjuvant chemotherapy for malignant fibrous histiocytoma in the femur and tibia.J Bone Joint Surg Am67:620,1985.
- Unni KK: “Malignant (Fibrous) Histiocytoma,” in Dahlin’s Bone Tumors, 5th Ed, p 217, Lippincott-Raven, Philadelphia,1996.
- Urban C, Rosen G, Huvos AG, et al: Chemotherapy of malignant fibrous histiocytoma of bone: a report of five cases.Cancer51:795,1983.
- Huvos AG, Heilweil M, Bretsky SS: The pathology of malignant fibrous histiocytoma of bone: a study of 130 patients.Am J Surg Pathol9:853,1985.
- Gaucher AA, Regent DM, Gillet PM, et al: Case report 656.Skeletal Radiol20:137,1991.
- Spanier SS, Enneking WF, Enriques P: Primary malignant fibrous histiocytoma of bone.Cancer36:2084,1975.
- Huvos AG: Primary malignant fibrous histiocytoma of bone: clinicopathologic study of 18 patients.N Y State J Med76:552,1976.
- Feldman F, Lattes R: Primary malignant fibrous histiocytoma (fibrous xanthoma) of bone.Skeletal Radiol1:145,1977.
- Dahlin DC, Krishnan KU, Matsuno T: Malignant (fibrous) histiocytoma of bone: fact or fancy? Cancer 39: 1508,1977.
- Kahn LB, Webber B, Mills E, et al: Malignant fibrous histiocytoma (malignant fibrous xanthoma; xanthosarcoma) of bone.Cancer42:640,1978.
- Galli SJ, Weintraub HP, Proppe KH: Malignant fibrous histiocytoma and pleomorphic sarcoma in association with medullary bone infarcts.Cancer41:607,1978.
- Yuen WWH, Saw D: Malignant fibrous histiocytoma of bone.J Bone Joint Surg Am67:482,1985.
- Enneking WF, Spanier SS, Goodman MA: A system for the surgical staging of musculoskeletal sarcoma.Clin Orthop153:106,1980.
- Rooser B, Willen H, Gustafson P, et al: Malignant fibrous histiocytoma of soft tissue.Cancer67:499,1991.
- Dunham WK, Wilborn WH: Malignant fibrous histiocytoma of bone: report of two cases and review of the literature.J Bone Joint Surg Am61:939,1979.
- McCarthey EF, Matsuno T, Dorfman HD: Malignant fibrous histiocytoma of bone: a study of 35 cases.Hum Pathol10:57,1979.
- Spanier SS: Malignant fibrous histiocytoma of bone.Orthop Clin North Am8:947,1977.
- Rosen G, Marcove R, Caparros B, et al: Primary osteogenic sarcoma: the rationale for preoperative chemotherapy and delayed surgery.Cancer43:2163,1979.
- Bielack SS, Schroeders A, Fuchs N, et al: Malignant fibrous histiocytoma of bone: a retrospective EMSOS study of 125 cases.Acta Orthop Scand70:353,1999.
© 2007 American Podiatric Medical Association