


Abstract
One hundred fifty-three subjects between the ages of 18 and 41 years (mean age, 26.2 years) with no history of congenital or traumatic deformity or foot problems walked along a 6-m walkway while the angular and linear displacement of the tibia, calcaneus, navicular, and first metatarsal was measured by means of an electromagnetic motion analysis system. Three-dimensional movement of the calcaneus relative to the tibia, of the navicular relative to the calcaneus, and of the first metatarsal relative to the navicular during the stance phase of gait was calculated. The results of this study provide information on, and an understanding of, how the calcaneus, navicular, and first metatarsal function during the stance phase of normal human walking.
The treatment of mechanically related foot disorders is often a challenge to clinicians. Sometimes this is due to the lack of information about how various segments of the foot move in relation to one another, especially during activities such as walking. The foot may be divided into three functional units: the rearfoot, the midfoot, and the first ray. Each of these units is a component of the medial longitudinal arch, which plays an important role in how the foot functions during weightbearing activities. [1]
Of these three functional units, the rearfoot has been studied the most. The vast majority of these investigations have focused on the calcaneus, probably because of its close relationship with the subtalar joint and the relative ease with which it can be measured during walking. [2-5] Almost exclusively, its movement has been referenced to that of the tibia. The frontal plane motion between the calcaneus and the tibia has been referred to in the medical literature as the rearfoot angle. [6-9] Although significant research attention has been directed at the calcaneus, information on the movement of more distal segments of the foot during walking is relatively sparse.
The midfoot consists of the navicular and cuboid bones. The articulation of these bones with the talus and calcaneus constitutes what is generally termed the midtarsal joint. [10] Although the midtarsal joint is composed of two separate anatomic articulations, the transverse tarsal region is often described as a single functional unit with two distinct axes: the longitudinal and the oblique. [10,11] With the early work of Manter [11] and Hicks [12] as a basis, a theoretical model for motion at the midtarsal joint has been proposed. Motion about the longitudinal axis is considered to be primarily in the frontal plane and consists of inversion and eversion. [11,13-15] During normal walking, the midtarsal joint is said to invert about its longitudinal axis during the loading response and then evert during the midstance and propulsion phases. [10,14] These motions are opposite to those attributed to the subtalar joint during normal walking and are considered to be the direct result of the interdependence of the two joints. Such interdependence is necessary to maintain a plantigrade foot during stance. [11] Motion about the oblique axis of the midtarsal joint is considered to be primarily dorsiflexion coupled with abduction, and plantarflexion coupled with adduction. [11,15-17] During the stance phase, motion about the oblique axis is theorized to consist of dorsiflexion and abduction during the loading response and midstance phases. It switches to plantarflexion and adduction during the propulsion phase. [10,14] Unfortunately, no data have been presented in the literature to verify these proposed movements. In addition, no functional range of motion of the midtarsal joint during gait has been reported. Root et al, [14] however, did suggest that 4° to 6° of inversion about the longitudinal axis is necessary to counteract a similar amount of eversion at the subtalar joint.
The midfoot has frequently been represented by tracking the movement of the navicular bone. [18,19] Clinical tests such as “navicular drop” have been proposed and used as a method of estimating midfoot position and movement. [20,21] Research documenting the dynamic movement of the midfoot through the navicular bone during walking, however, is relatively scarce.
In 1999, the authors of the current study measured the vertical and horizontal linear displacement of the navicular bone during the stance phase of walking. [19] They reported a mean displacement of 7.9 mm between the positions of foot flat and heel-off. That same year, the authors also reported on angular movement of the navicular bone relative to the tibia during walking. [18] That study demonstrated a very similar pattern of movement compared with the rearfoot. Leardini et al [22] also published a study on the angular displacement of the midfoot during walking. Using rigid markers placed on the posterior calcaneus and dorsum of the foot of nine individuals, they recorded the movement of the midfoot relative to the rearfoot. Unfortunately, the attachment of the rigid marker on the dorsum of the foot to measure midfoot motion is extremely susceptible to error caused by muscle contraction.
The first metatarsal and medial cuneiform bones are frequently considered a functional unit because of the extremely small amount of movement between the two bones. [12] Together, these are referred to as the first ray. The first ray is thought to have a single, tri-planar axis with an orientation of approximately 45° to the longitudinal reference of the foot. [12,14,23] Because of the orientation of this tri-planar axis, the amount of movement in the frontal plane is approximately equal to that in the sagittal plane. [14] The majority of authors agree that first ray dorsiflexion is accompanied by inversion. [10,12,14,24-26] Other authors, however, have described dorsiflexion and eversion. [27-30] Using cadavers, several investigators have shown that as the rearfoot pronates, the first ray dorsiflexes. [29] These studies and the general consensus regarding the first ray’s tri-plane movement pattern have led authors to deduce how the first ray moves during closed kinetic chain activities such as walking. During the loading response of normal gait, the first ray is thought to dorsiflex and invert. During the propulsion phase, it plantarflexes and everts. [10,23,31] Wernick and Volpe [10] described the motion of the first ray during gait to be maximally dorsiflexed at heel strike, progressing to maximal plantarflexion after heel-off. In addition to the theoretical pattern of movement of the first ray during walking, its functional range of motion has not been well documented. Root et al [14] suggested that approximately 10° of plantarflexion was needed during the propulsion phase of gait to allow for full extension of the hallux. Unfortunately, none of these authors investigated dynamic in vivo movement of the first ray during activities such as walking. Despite the lack of information on the actual movement of the first ray during walking, numerous theories exist about its dysfunction and the possible consequences of that dysfunction. [14,32,33]
Mechanical dysfunction of the first ray involves the presence of either hypomobility or hypermobility in the sagittal plane. First ray hypomobility has been linked to high plantar pressures beneath the first metatarsal head, [34] impaired shock attenuation through the medial longitudinal arch, [35] and a variety of mechanical overuse injuries of the foot and lower extremity. [36] Conversely, hypermobility of the first ray has been hypothesized as contributing to such conditions as acquired flatfoot, posterior tibialis tendinitis, plantar fasciitis, and shin splints. [35] Hypermobility of the first ray is also considered a causal factor in the development of bunions. [35,37]
As was mentioned previously, effective treatment of mechanical foot problems is often a significant challenge. There is a large body of theoretical writings concerning how the functional units of the foot work and interact with each other. Unfortunately, with the exception of the rearfoot, very little is known about the dynamic movement of the midfoot and first ray during walking. The purpose of this study was to record three-dimensional motion of the rearfoot (calcaneus), midfoot (navicular), and first ray (first metatarsal) during the stance phase of normal walking. Such information should dramatically improve basic knowledge of foot function and shed light on the etiology and management of pathological conditions such as acquired flatfoot, plantar fasciitis, tendinitis, metatarsalgia, and hallux abducto valgus.
Materials and Methods
Subjects
The subjects for this study were 153 individuals (55 men, 98 women) between the ages of 18 and 41 years (mean, 26.2 years). Subjects were chosen from a larger pool of volunteers because they had no history of congenital deformity, pain, or traumatic injury to either of their lower extremities at least 6 months prior to the start of the study. Table 1 shows the demographics for the subjects who participated in the study. The Institutional Review Board at Northern Arizona University approved the study prior to the start of data collection, and all subjects provided informed written consent.

Table 1.
Demographic Information of Subjects.
Instrumentation
Movement of the tibia, calcaneus, navicular, and first metatarsal of each subject’s right extremity was measured by means of the 6D-Research electromagnetic motion analysis system (Skill Technologies Inc, Phoenix, Arizona). This system is based upon the Fastrak tracking device (Polhemus, Colchester, Vermont) and uses an electromagnetic transmitter with up to four electromagnetic sensors. The sensors measure 2.8 × 2.3 cm and weigh 17 g. The signals from each sensor are input to a digital signal processor that computes the sensor’s position and orientation relative to a transmitter. It has an effective accurate range of a 76-cm radius from the transmitter. Within this range, it has an accuracy of 0.8 mm and 0.15° RMS (root mean square). [38] Although a 76-cm radius is typically too small for recording a full walking stride, it is sufficient for analyzing the stance phase of a single limb. [39] For the present study, the electromagnetic transmitter was positioned at a height of 96 cm, at the midway point of a 6-m raised walkway. The walkway was raised to a height of 76 cm to avoid any possible distortion of the electromagnetic fields caused by metal reinforcement in the laboratory’s concrete floor. Figure 1 shows the experimental setup used for this study. Four electromagnetic sensors were used to collect the angular position data of the tibia, calcaneus, navicular, and first metatarsal during walking. Joint coordinate system angles for the ankle, as defined by Allard et al, [40] were calculated by means of the calcaneal and tibial sensors. Adaptation of this definition was used to calculate joint coordinate system angles between the navicular and the calcaneus sensors, and between the first metatarsal and navicular sensors. Movement about a mediolateral axis (X) was defined as dorsiflexion/plantarflexion while motion about an anterior-posterior axis (Y) was inversion/eversion. Finally, movement about a vertical (Z) or longitudinal axis of the proximal segment (either tibia, calcaneus, or navicular) was defined as internal/external rotation for the calcaneus relative to the tibia, but abduction/adduction for the navicular relative to the calcaneus and the first metatarsal relative to the navicular. The sampling rate for each sensor was 60 Hz, and the resulting angles and linear displacements were smoothed by means of a 6-Hz low-pass digital Butterworth filter.
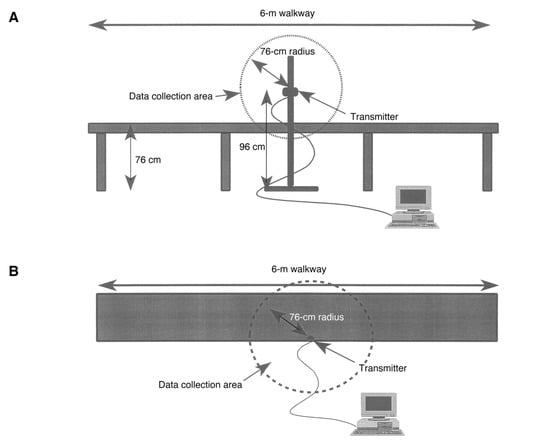
Figure 1.
Schematic representation of the experimental setup used for data collection with the 6D-Research electromagnetic motion analysis system. A, Sagittal plane view; B, transverse plane view.
The temporal occurrences of heel strike, foot flat, heel-off and toe-off were recorded by means of four force-sensing switches (Interlink Electronics, Camarillo, California). The switches were secured to the plantar surface of the subject’s right heel, first metatarsal head, fifth metatarsal head, and hallux with adhesive tape. The signal produced by each switch was recorded and synchronized with the kinematic data.
Procedure
Following the recording of the subject’s height and body mass, the four electromagnetic sensors were attached to the subject’s right lower extremity with double-sided adhesive tape. A sensor was placed on the tibial tubercle; the posterior calcaneus, just proximal to the calcaneal fat pad; the navicular tubercle; and the distal medial first metatarsal shaft (Fig. 2). These locations were selected because the minimal presence of soft tissue reduced the possibility of sensor-skin movement during walking. Particular care was taken with the navicular and first metatarsal sensors to ensure that they were not influenced by contraction of the adjacent tendons of the extensor digitorum, extensor hallucis longus, and posterior tibialis. The sensors were connected to a microcomputer for data collection by means of a 30-foot serial cable. The subject then stood relaxed with knees extended, feet parallel to the line of progression, and heels centered with the second metatarsals. While the subject was in this position, each sensor’s orientation was initialized relative to the laboratory reference. This position was used as the zero reference point for all angular measurements. After the sensors were initialized, each subject walked along the walkway at a self-selected speed. The subject’s stance phase duration for each trial was monitored to ensure the consistency of his or her walking speed. Any trial in which the stance phase duration deviated more than 10% from the mean of all other trials was deleted, and another trial was collected. This process was repeated until five walking trials were recorded for each subject. Angular movement of the calcaneus relative to the tibia, the navicular relative to the calcaneus, and the first metatarsal relative to the navicular was then calculated and stored for later analysis.
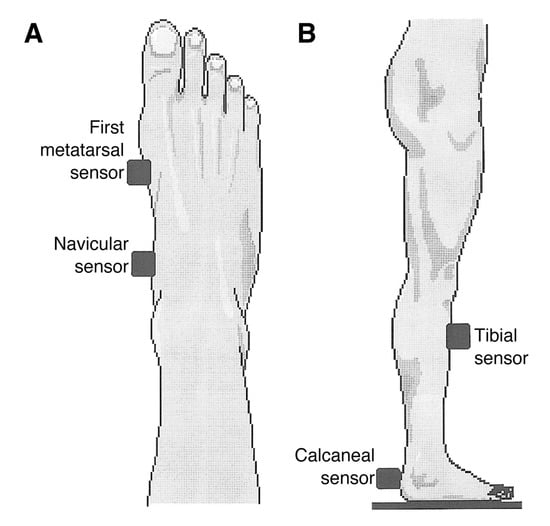
Figure 2.
A, Diagram of sensor placement on the right foot; B, definition of kinematic data on the right lower extremity.
Data Analysis
Intraclass correlation coefficients (2,1) were used to assess between-trial reliability of each subject’s stance phase duration. [41] Consistency of the motion patterns obtained by the electromagnetic system was estimated by means of the coefficient of multiple correlation described by Kadaba et al. [42]
The five walking trials were first normalized to each subject’s stance phase duration to allow comparison across trials and groups of subjects. Next, the mean of all 153 subjects was calculated to provide an average pattern for all subjects. The resulting average motion pattern of the calcaneus, navicular, and first metatarsal about the three principle axes for all subjects was then plotted to display the typical movement pattern of each bone.
Results
By means of the force-sensitive foot switches attached to the plantar surface of the subject’s right foot, mean (± SD) stance phase duration was calculated to be 679 (± 48) msec. The instant of foot flat, defined as when the first metatarsal head contacted the ground, was found to be at 15.0% (± 3.1°) of the stance phase. Heel-off was determined to be at 55.1% (± 7.8°) of stance. With regard to between-trial reliability of the stance phase duration, the calculated intraclass correlation coefficient value was .969. The mean coefficient of multiple correlation values for the motion patterns of all segments are presented in Table 2. All mean coefficients of multiple correlation were found to exceed .800 except for internal/external rotation of the first metatarsal. This motion pattern had a coefficient of .648, indicating moderate between-trial variability. The between-subject coefficients of multiple correlation for each motion pattern are also shown in Table 2 and provide information on the similarity of one subject to the next. Each of the motion patterns had from moderate to good between-subject consistency, with the exception of navicular inversion/eversion, navicular abduction/adduction, and first metatarsal abduction/adduction. The coefficient of multiple correlation values for these would be classified as poor.
Table 2.
Mean Coefficient of Multiple Correlation Values for Dynamic Motion Pattern of the Calcaneus, Navicular, and First Metatarsal.
Calcaneus
The movement of the calcaneus relative to the tibia about a mediolateral axis (dorsiflexion/plantarflexion) is shown in Figure 3 A. As can be seen, the rearfoot is very close to its zero position (resting standing position) at heel strike. It then rapidly plantarflexes to –10.3° (± 3.2°) by 14% of the stance phase. At this point, it reverses direction and dorsiflexes to 6.5° (± 3.6°) by 73% of the stance phase. The calcaneus then plantarflexes again until toe-off.
Figure 3.
Joint angles of the calcaneus about each of the principle axes during the stance phase of walking: A, mediolateral axis (dorsiflexion/plantarflexion); B, anterior-posterior axis (inversion/eversion); and C, vertical axis (internal/external rotation). The broken lines represent ± 1SD from the mean motion pattern calculated from the average of 153 subjects.
Figure 3 B shows the movement of the calcaneus about an anterior-posterior axis (inversion/eversion). At heel strike, it is inverted 3.0° (± 2.7°) relative to the tibia and then gradually everts to –2.2° (± 2.4°) by 55% of the stance phase. Following this prolonged period of eversion, the motion is reversed and quickly inverts to its maximum value of 5.5° (± 3.2°) just prior to the foot leaving the ground.
Finally, the movement of the calcaneus relative to the tibia about the longitudinal or vertical axis of the tibia (internal/external rotation) is shown in Figure 3 C. Because the calcaneus is fixed to the supporting surface by body weight during the stance phase, motion of the calcaneus relative to the tibia can be interpreted as being internal/external rotation of the tibia on the calcaneus. [8,9,43] Thus, at the instant of heel strike, the tibia is essentially at its zero position of internal/external rotation, but quickly internally rotates to its maximum value of –3.8° (± 3.5°) at 21% of the stance phase. It then reverses direction and externally rotates for the remainder of the stance phase. Its maximum external rotation value is 6.2° (± 4.6°) and occurs at the instant of toe-off.
Navicular
The angular movement of the navicular relative to the calcaneus about the mediolateral axis (dorsiflexion/plantarflexion) is shown in Figure 4 A. As can be seen, the navicular is plantarflexed –2.4° (± 2.6°) at heel strike and rapidly dorsiflexes to its maximum value of 3.2° (± 2.4°) at foot flat. It then reverses direction and gradually plantarflexes to –5.9° (± 4.0°) at toe-off.
Figure 4.
Joint angles of the navicular relative to the calcaneus about each of the principle axes during the stance phase of walking: A, mediolateral axis (dorsiflexion/plantarflexion); B, anterior-posterior axis (inversion/eversion); and C, vertical axis (abduction/adduction). The broken lines represent ± 1SD from the mean motion pattern calculated from the average of 153 subjects.
Figure 4 B shows the angular movement of the navicular relative to the calcaneus about the anterior-posterior axis (inversion/eversion) during the stance phase of walking. At the instant of heel strike, it is everted –2.2° (± 2.9°), but rapidly inverts toward zero until 24% of the stance phase. Its angle at this point is –0.3° (± 2.4°). At this point, the navicular reverses direction and everts for the remainder of the stance phase, reaching its maximum value of –3.3° (± 3.5°) at toe-off. Although the navicular approaches a position of inversion relative to the resting standing position, it is never actually inverted during the stance phase of walking.
The angular movement of the navicular relative to the calcaneus about the longitudinal or vertical axis of the calcaneus (abduction/adduction) is shown in Figure 4 C. As can be seen, it is in the defined zero position at heel strike and adducts only 1.5° (± 3.0°) during the initial 75% of the stance phase. Throughout the final 25% of stance, the navicular rapidly abducts to 2.7° (± 3.5°).
First Metatarsal
The movement of the first metatarsal relative to the navicular about a mediolateral axis (dorsiflexion/plantarflexion) is shown in Figure 5 A. As can be seen, the first metatarsal is plantarflexed –1.3° (± 3.0°) at heel strike and gradually dorsiflexes to its maximum value of 3.8° (± 2.4°) at 70% of the stance phase. It then reverses direction and rapidly plantarflexes to –6.4° (± 4.6°) at toe-off.
Figure 5.
Joint angles of the first metatarsal relative to the navicular about each of the principle axes during the stance phase of walking: A, mediolateral axis (dorsiflexion/plantarflexion); B, anterior-posterior axis (inversion/eversion); and C, vertical axis (abduction/adduction). The broken lines represent ± 1SD from the mean motion pattern calculated from the average of 153 subjects.
Figure 5 B shows the movement of the first metatarsal relative to the navicular about an anterior-posterior axis (inversion/eversion). At heel strike, the first metatarsal is at its resting standing position, but then everts to –2.6° (± 2.4°) by 26% of the stance phase. The first metatarsal then reverses direction and assumes a position of inversion at 77% of the stance phase. It continues to invert to its maximum value of 2.0° (± 3.9°) at toe-off.
The movement of the first metatarsal relative to the navicular about the longitudinal or vertical axis of the navicular (abduction/adduction) is shown in Figure 5 C. As the graph indicates, there is a general pattern of abduction followed by adduction. The first metatarsal is adducted 0.7° (± 3.3°) at heel strike, but abducts to its maximum amount of abduction of –0.8° (± 2.5°) by 52% of the stance phase. Its maximum adduction of 1.8° (± 3.2°) is not obtained until late in the stance phase (88% of stance phase duration).
Discussion
Intraclass Correlation Coefficients
With the use of the criteria for ICC classification suggested by Landis and Koch, [44] stance phase duration for this study was determined to be “almost perfect.” In this study, the average between-trial motion pattern repeatability as measured by the coefficient of multiple correlation was considered to be excellent for all patterns except for first metatarsal abduction/adduction, which was considered good (Table 2). In comparison with other published reports, these measurements of reliability and consistency are slightly larger than those reported by Liu et al [8] and Moseley et al. [9] The higher values reported in the current study may be related to the larger sample size compared with Liu and Moseley. Liu et al [8] and Moseley et al [9] studied 10 and 14 subjects, respectively.
The coefficients of multiple correlation calculated as indicators of between-subject consistency indicate that the results of the current study represent movement patterns that are fairly common in the sagittal and frontal planes, but less so in the transverse plane (Table 2). The lower levels of between-subject consistency of the navicular and first metatarsal in the transverse plane therefore make it difficult to know what is the most typical pattern of movement. Further research may help to determine if these low between-subject coefficients of multiple correlation are due simply to inherent subject variability, the presence of subpopulations within this average motion pattern, or skin-sensor artifact. Although significant care was taken to minimize skin-sensor movement, it could not be eliminated completely. Further research therefore needs to focus on the validity of using sensors on the skin over the navicular and first metatarsal bones to measure osseous motion during walking.
Joint Angles
Calcaneus. Sagittal motion of the calcaneus relative to the tibia is very similar to that reported previously in the literature. [8,9,43,45] Frontal plane motion of the calcaneus, sometimes called rearfoot motion, is also comparable to that found by previous investigators. [6-9,43] The differences observed between this study and the others involve the initial value at heel strike and are directly related to the different “zero” positions used by the various investigators. The results obtained for the internal/external rotation of the tibia upon the calcaneus are also consistent with previous research. [8,9,43,45-47] The significance of these results is therefore not the new information it provides, but the labeling of what should be termed normal or typical motion because of the fairly large sample size used in the present study. As can be seen, most individuals do not evert quickly during the loading response of the gait cycle. Instead, subjects demonstrate a more gradual pattern of eversion compared with previous reports in the literature (Fig. 3 B). [3,14,31,48]
Navicular. Because the navicular is frequently used as a clinical indicator of medial longitudinal arch height, the results of this study on the movement of the navicular relative to the calcaneus can be extrapolated to be somewhat representative of the midfoot region and thus the midtarsal joint. [20,21,49,50] The findings of the current study, for the most part, substantiate the theoretical statements by previous authors. It has been proposed that motion about the longitudinal axis of the midfoot will be opposite to that of the rearfoot. [10,11,51] As can be seen in Figure 4 B, the navicular does indeed invert during the loading response and evert for the remainder of the stance phase. This is essentially opposite from what has been shown to occur in the frontal plane (inversion/eversion) for the rearfoot. [8,9,43] The magnitude of motion about the longitudinal axis of the midfoot relative to that of the rearfoot, however, does not appear to be equal as proposed by Root et al, [51] who suggested that the magnitude of midfoot motion will be roughly equivalent to that of the rearfoot. Lundberg et al, [52] on the other hand, found that the majority of foot motion occurred in the midfoot. The magnitude of navicular inversion/eversion relative to the calcaneus was found to be 1.9° in the current study compared with 5.2° for the calcaneus relative to the tibia (Figs. 3 B and 4 B). The smaller magnitude of midfoot motion obtained in the present study compared with Lundberg et al [52] may be the result of several factors. For example, the current study recorded motion of a single bone (navicular) relative to the calcaneus during walking while Lundberg et al [52] measured movement between several bones in a quasi-static condition.
With respect to the oblique axis of the midfoot, the literature indicates that during the loading response of gait, the midfoot will dorsiflex and abduct and then during the propulsive phase it will plantarflex and adduct. [11,15-17,53] The current study essentially substantiates these statements. As is shown in Figure 4 A, the navicular dorsiflexes and then plantarflexes during the stance phase of walking. The navicular adducts in conjunction with plantarflexion, as seen in the later portion of the stance phase. Abduction and dorsiflexion, however, do not occur during the loading response. Instead, the navicular remains essentially in a zero position for the first 10% of the stance phase.
First metatarsal. The results of the current investigation reveal that movement of the first metatarsal (first ray), although consistent, is small. Total average excursion of the first metatarsal relative to the navicular is 10.2° in the sagittal plane, 4.5° in the frontal plane, and only 2.5° in the transverse plane. Although no previous research could be found on this topic, it appears that the requirement of 10° first-ray plantarflexion during the propulsion phase of gait previously cited by Root et al [14] may be excessive. Subjects in the current study had an average of only 6.4° of plantarflexion (Fig. 5 A). One reason for such a discrepancy might be the reference point used for defining dorsiflexion/plantarflexion of the first ray. Root et al [14] defined dorsiflexion/plantarflexion of the first ray relative to the rest of the foot proximal to the medial cuneiform. The current study instead used the navicular as its reference for movement. Of interest, an additional 3.6° of plantarflexion is seen in the present study between the navicular and the calcaneus (Fig. 4 A). If this 3.6° is added to the 6.4° observed between the first metatarsal and the navicular (Fig. 5 A), the 10° range motion of the first ray proposed by Root et al [14] appears to be valid. Further research would certainly help to clarify this issue.
In other respects, however, the results of this study do not substantiate the generally accepted movement pattern of the first ray during walking. Previous authors have suggested that the first ray is dorsiflexed and inverted during the loading response of gait. It should then plantarflex and evert during the propulsion phase of walking. [10,14] Instead, the current study found the first metatarsal to be slightly plantarflexed and everted during the loading phase of walking (Figs. 5 A and B). From heel-off to toe-off, instead of plantarflexion, the first metatarsal continues to dorsiflex until 70% of the stance phase before it begins to plantarflex (Fig. 5 A). It does not assume a position of plantarflexion until 88% of the stance phase. At heel-off, the first metatarsal is slightly everted and doesn’t become inverted until 77% of the stance phase. This pattern of movement is consistent with that proposed by D’Amico and Schuster [27] in 1979. They demonstrated dorsiflexion and eversion of the first metatarsal in cadavers when the rearfoot was pronated. Using a cadaver model, Oldenbrook and Smith [28] also demonstrated that all five metatarsals evert and dorsiflex with internal rotation of the leg (pronation of the subtalar joint). They also demonstrated abduction of the metatarsals with internal rotation of the leg. This second finding by Oldenbrook and Smith [28] is also supported by the results of the current study (Fig. 5 C).
Conclusion
Three-dimensional kinematic analysis of the calcaneus relative to the tibia, the navicular relative to the calcaneus, and the first metatarsal relative to the navicular was undertaken in 153 healthy individuals during the stance phase of normal walking. Mean motion patterns of the resulting data were presented. The results of this study provide additional information on, and an understanding of, the typical movement of the calcaneus (rearfoot), navicular (midfoot), and first metatarsal (first ray) during normal gait.
The results of this study certainly support the theory of tri-planar motion traditionally ascribed to the rearfoot, midfoot, and first ray. The complexity of the dynamic weightbearing foot is also illustrated by the results of this study. Treatment and clinical management of the foot, especially of the first ray, should therefore seek to augment or control these motions without preventing their natural occurrence. Further research needs to be done to better understand the action of the first ray relative to proximal segments, such as the rearfoot or lower leg. Despite the need for further research, the results of this study clearly show that some of the current ideas about the kinematics of the foot during normal walking should be reexamined. This information should therefore help to reevaluate current strategies and define future approaches for the clinical management of injuries and dysfunction in these regions. The kinematics of the functional units of the foot in individuals with injury, pathology, or deformity also needs to be studied. The results of those studies could then be compared with the current investigation.
References
- SALTZMAN, C.L.; NAWOCZENSKI, D.A. TALBOT KD: Measurement of the medial longitudinal arch. Arch Phys Med Rehabil 1995, 76, 45. [Google Scholar] [CrossRef] [Scilit]
- SOUTAS-LITTLE, R.W.; BEAVIS, G.C.; VERSTRAETE, M.C. ET AL: Analysis of foot motion during running using a joint co-ordinate system. Med Sci Sports Exerc 1987, 19, 285. [Google Scholar] [CrossRef] [Scilit]
- WRIGHT, D.G.; DESAI, S.M.; HENDERSON, W.H. Action of the subtalar and ankle-joint complex during the stance phase of walking. J Bone Joint Surg Am 1964, 46, 361. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- AREBLAD, M.; NIGG, B.M.; EKSTRAND, J.; et al. Three-dimensional measurement of rearfoot motion during running. J Biomech 1990, 23, 933. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- HAMILL, J.; BATES, B.T.; KNUTZEN, K.M.; et al. Relationship between selected static and dynamic lower extremity measures. Clin Biomech 1989, 4, 217. [Google Scholar] [CrossRef] [Scilit]
- MCPOIL, T.G.; CORNWALL, M.W. Relationship between neutral subtalar joint position and pattern of rearfoot motion during walking. Foot Ankle 1994, 15, 141. [Google Scholar] [CrossRef] [Scilit]
- MCPOIL, T.G.; CORNWALL, M.W. Relationship between three static angles of the rearfoot and the pattern of rearfoot motion during walking. J Orthop Sports Phys Ther 1996, 23, 370. [Google Scholar] [CrossRef] [Scilit]
- LIU, W.; SIEGLER, S.; HILLSTROM, H.; et al. Three-dimensional, six-degrees-of-freedom kinematics of the human hindfoot during the stance phase of level walking. Hum Movement Sci 1997, 16, 283. [Google Scholar] [CrossRef] [Scilit]
- MOSELEY, L.; SMITH, R.; HUNT, A.; et al. Three-dimensional kinematics of the rearfoot during the stance phase of walking in normal adult males. Clin Biomech 1996, 11, 39. [Google Scholar] [CrossRef] [Scilit]
- WERNICK, J.; VOLPE, R.G. Lower Extremity Function and Normal Mechanics. In Clinical Biomechanics of the Lower Extremities; Valmassy, R.L., Ed.; CV Mosby: St Louis, 1996; p. 1. [Google Scholar]
- MANTER JT: Movements of the subtalar joint and transverse tarsal joints. Anat Rec 1941, 80, 397. [CrossRef] [Scilit]
- HICKS JH: The mechanics of the foot. Part I: the joints. J Anat 1953, 87, 345.
- ELFTMAN H: The transverse tarsal joint and its control. Clin Orthop 1960, 16, 41.
- ROOT, M.L.; ORIEN, W.P.; WEED, J.H. Clinical Biomechanics: Normal and Abnormal Function of the Foot; Clinical Biomechanics Corp: Los Angeles, 1977; Vol 2, p. 175. [Google Scholar]
- OATIS CA: Biomechanics of the foot and ankle under static conditions. Phys Ther 1988, 68, 1815. [CrossRef] [Scilit] [PubMed]
- NOVICK, A. Anatomy and Biomechanics. In Physical Therapy of the Foot and Ankle; Hunt, G.C., McPoil, T.G., Eds.; Churchill Livingstone: New York, 1995; p. 11. [Google Scholar]
- DONATELLI, R.A. Normal Anatomy and Biomechanics. In The Biomechanics of the Foot and Ankle; Donatelli, R.A., Ed.; FA Davis Co: Philadelphia, 1996; p. 3. [Google Scholar]
- CORNWALL, M.W. MCPOIL TG: Three-dimensional movement of the foot during the stance phase of walking. JAPMA 1999, 89, 56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- CORNWALL, M.W. MCPOIL TG: Relative movement of the navicular bone during normal walking. Foot Ankle Int 1999, 20, 507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- BRODY DM: Techniques in the evaluation and treatment of the injured runner. Orthop Clin North Am 1982, 13, 541. [CrossRef] [Scilit]
- PICCIANO, A.M.; ROWLANDS, M.S.; WORRELL, T. Reliability of open and closed kinetic chain subtalar joint neutral positions and navicular drop test. J Orthop Sports Phys Ther 1993, 18, 553. [Google Scholar] [CrossRef] [Scilit]
- LEARDINI, A.; BENEDETTI, M.G.; CATANI, F.; et al. An anatomically based protocol for the description of foot segment kinematics during gait. Clin Biomech 1999, 14, 528. [Google Scholar] [CrossRef] [Scilit]
- NORKIN, C.C.; LEVANGIE, P.K. The Ankle-Foot Complex. In Joint Structure and Function: A Comprehensive Analysis; Norkin, C.C., Levangie, P.K., Eds.; FA Davis Co: Philadelphia, 1992; p. 379. [Google Scholar]
- KELSO, S.F.; RICHIE, D.H.; COHEN, I.R.; et al. Direction and range of motion of the first ray. JAPA 1982, 72, 600. [Google Scholar] [CrossRef] [Scilit]
- EBISUI JM: The first ray axis and the first metatarsophalangeal joint: an anatomical and pathomechanical study. JAPA 1968, 58, 160.
- SGARLATO, T.E. A Compendium of Podiatric Biomechanics; California College of Podiatric Medicine: San Francisco, 1971. [Google Scholar]
- D’AMICO, J.C. SCHUSTER RO: Motion of the first ray: clarification through investigation. JAPA 1979, 69, 17. [Google Scholar]
- OLDENBROOK, L.L.; SMITH, C.E. Metatarsal head motion secondary to rearfoot pronation and supination: an anatomical investigation. JAPA 1979, 69, 24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DUVRIES, H.L. Surgery of the Foot; CV Mosby: St Louis, 1965. [Google Scholar]
- GRODE, S.E.; MCCARTHY, D.J. The anatomical implications of hallux abducto valgus: a cryomicrotomy study. JAPA 1980, 70, 539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DONATELLI, R.A. Abnormal Biomechanics. In The Biomechanics of the Foot and Ankle; Donatelli, R.A., Ed.; FA Davis Co: Philadelphia, 1996; p. 34. [Google Scholar]
- ROUKIS, T.S.; SCHERER, P.R.; ANDERSON, C.F. Position of the first ray and motion of the first metatarsophalangeal joint. JAPMA 1996, 86, 538. [Google Scholar] [CrossRef] [Scilit]
- DANANBERG HJ: Gait style as an etiology to chronic postural pain. Part I: functional hallux limitus. JAPMA 1993, 83, 433. [CrossRef] [Scilit]
- BIRKE, J.A.; FRANKS, B.D.; FOTO, J.G. First ray joint limitation, pressure, and ulceration of the first metatarsal head in diabetes mellitus. Foot Ankle Int 1995, 16, 277. [Google Scholar] [CrossRef] [Scilit]
- GLASOE, W.M.; YACK, H.J.; SALTZMAN, C.L. Anatomy and biomechanics of the first ray. Phys Ther 1999, 79, 854. [Google Scholar] [CrossRef] [Scilit]
- MILCHAUD, T.M. Foot Orthoses and Other Forms of Conservative Foot Care; Williams & Wilkins: Baltimore, 1993. [Google Scholar]
- SHEREFF MJ: Pathophysiology, anatomy, and biomechanics of hallux valgus. Orthop 1990, 13, 939. [CrossRef] [Scilit]
- Fastrak User’s Manual; Polhemus, Inc: Colchester, VT, 1993.
- MANNON, K.; ANDERSON, T.; CHEETHAM, P.; et al. A comparison of two motion analysis systems for the measurement of two-dimensional rearfoot motion during walking. Foot Ankle 1997, 18, 427. [Google Scholar] [CrossRef] [Scilit]
- ALLARD, P.; KIRTLEY, C.; ROSENBAUM, D.; et al. A joint coordinate system for the ankle complex. Int Soc Biomechanics 1995, 59, 6. [Google Scholar]
- SHROUT, P.E.; FLEISS, J.L. Intraclass correlations: uses in assessing rater reliability. Psychol Bull 1979, 86, 420. [Google Scholar] [CrossRef]
- KADABA, M.P.; RAMAKRISHNAN, H.K.; WOOTTEN, M.E.; et al. Repeatability of kinematic, kinetic, and electromyographic data in normal adult gait. J Orthop Res 1989, 7, 849. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- PIERRYNOWSKI, M.R.; SMITH, S.B. Rear foot inversion/eversion during gait relative to the subtalar joint neutral position. Foot Ankle Int 1996, 17, 406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- LANDIS, J.R. KOCH GG: The measurement of observer agreement for categorical data. Biometrics 1977, 33, 159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- INMAN, V.T.; RALSTON, H.J. TODD F: Human Walking; Williams & Wilkins: Baltimore, 1981. [Google Scholar]
- CORNWALL, M.W. MCPOIL TG: Footwear and foot orthotic effectiveness research: a new approach. J Orthop Sports Phys Ther 1995, 21, 337. [Google Scholar] [CrossRef] [Scilit]
- SAWERT, M.K.; CORNWALL, M.W.; MCPOIL, T.G. The validation of two-dimensional measurement of transverse tibial rotation during walking. Lower Extremity 1995, 2, 285. [Google Scholar]
- SAMMARCO, G.J. Biomechanics of the Foot. In Basic Biomechanics of the Skeletal System; Nordin, M., Frankel, V.H., Eds.; Lea & Febiger: Philadelphia, 1989; p. 163. [Google Scholar]
- BECKETT, M.E.; MASSIE, D.L.; BOWERS, K.D.; et al. Incidence of hyperpronation in the ACL injured knee: a clinical perspective. Athletic Training 1992, 27, 58. [Google Scholar]
- CORNWALL, M.W.; MCPOIL, T.G.; HAYNES, J. Relationship between rearfoot and midfoot motion during walking [abstract]. Phys Ther 1996, 76, S75. [Google Scholar]
- ROOT, M.L.; ORIEN, W.P.; WEED, J.H.; et al. Biomechanical Evaluation of the Foot; Clinical Biomechanics Corp: Los Angeles, 1971; Vol 1. [Google Scholar]
- LUNDBERG, A.; SVENSSON, O.K.; BYLUND, C.; et al. Kinematics of the ankle/foot complex. Part 2: pronation and supination. Foot Ankle 1989, 9, 248. [Google Scholar] [CrossRef] [Scilit]
- SCOTT, S.H.; WINTER, D.A. Biomechanical model of the human foot: kinematics and kinetics during the stance phase of walking. J Biomech 1993, 26, 1091. [Google Scholar] [CrossRef] [Scilit]
© 2002 American Podiatric Medical Association