Article

To Evaluate Efficacy of Intralesional Platelet-Rich Plasma in Patients with Plantar Fasciitis

by
Sanjiv Kumar
1,
Chethan Channaveera
1,
Satyaranjan Sethi
1,
Ranjan Kumar Wadhwa
1 and
Vijender Anand
2,*
1
Department of Physical Medicine and Rehabilitation, VMMC and Safdarjung Hospital, New Delhi 110029, India
2
Department of Physical Medicine and Rehabilitation, Employee’s State Insurance Corporation Medical College and Hospital, Faridabad 121001, Haryana, India
*
Author to whom correspondence should be addressed.
J. Am. Podiatr. Med. Assoc. 2026, 116(4), 24161; https://doi.org/10.7547/24-161
Submission received: 3 September 2024 / Revised: 13 December 2024 / Accepted: 31 December 2024 / Published: 14 August 2026

Abstract

Background: Plantar fasciitis (PF) is one of the most common causes of heel pain, affecting 10% of the general population. Platelet-rich plasma (PRP) has been demonstrated to be helpful in managing PF and reducing plantar facia thickness (PFT). This study objective was to know the effect and efficacy of ultrasound (USG)-guided intralesional PRP in PF in relation to pain, PFT and foot function index (FFI). Methods: A prospective interventional study was conducted in a tertiary care hospital on eighty-five diagnosed cases of unilateral PF. All patients had undergone pain intensity assessment by visual analogue scale (VAS) and FFI, and USG examination of PFT after USG-guided intralesional PRP injection was assessed at baseline (0 weeks), 2 weeks and 6 weeks. Results: Following USG-guided intralesional PRP injection, a statistically significant decrease was noted in plantar fascia thickness (PFT) from baseline 0 (week) 6.592 mm ± 0.51 mm to 5.169 mm ± 0.39 mm and reduced to 4.07 mm ± 0.39 mm at the 2nd week and 6th week, respectively (p value < 0.001). A statistically significant reduction in VAS score was noted which reduced from 8.647 ± 0.55 to 5.588 ± 1.13 (2nd week) and further reduced to 1.21 ± 1.06 at the end of the 6 weeks (p value < 0.001). Mean FFI in our study at baseline was 85.494 ± 6.55, at 2 weeks the mean FFI was 49.341 ± 7.277 and at the end of the 6 weeks it reduced to 24.235 ± 1.608; a statistically significant decrease was noted (p value < 0.001). Conclusions: PRP injection helps in the reduction in heel pain (VAS), reduction in PFT, and improvement in all domains of FFI, leading to enhancement of quality of life.

1. Introduction

The plantar fascia (PF) is crucial in supporting the plantar arch and is a vital component of the heel pad [1]. Plantar fasciitis is one of the most common causes of heel pain. Excessive straining of the plantar fascia can cause microtrauma, resulting in the formation of microtears along its path or at the point where it attaches to the medial calcaneal tuberosity. This process ultimately leads to the chronic degeneration of the plantar fascia fibres [2].
Plantar fasciitis accounts for about 10% of runner-related injuries and 11–15% of all foot symptoms requiring professional care. It is common in middle-aged obese females and young athletes [3]. The prevalence of plantar fasciitis is 59% in India among the age group of 40 to 50 years [4]. Patients feel pain on the first step out of bed in the morning, which is relieved with increased activity, and pain elicited on palpation of the plantar calcaneal region [5]. On USG examination, there is a gross thickening and hypo echogenicity of the plantar fascia at its insertion at the calcaneal tuberosity [6].
Treatment of plantar fasciitis includes conservative methods by modalities, exercises, oral analgesics with or without injectables (steroids, platelet-rich plasma (PRP), local anesthetics, prolotherapy), and surgical interventions [7]. PRP is a platelet-rich concentrate with a platelet level higher than the baseline by several times [8]. It modulates collagen synthesis, decreases inflammation, promotes tissue healing, and stimulates fibroblast activity [9]. Platelet-rich plasma (PRP) treatment is characterized by its affordability, ease of administration, and minimally invasive nature.
This study aimed to evaluate how ultrasound-guided platelet-rich plasma injection affects the treatment of plantar fasciitis, particularly regarding pain relief, better function, and changes in the thickness of the plantar fascia.

2. Materials and Methods

2.1. Design and Procedure

The study was conducted in the Department of Physical Medicine and Rehabilitation in a tertiary care hospital between September 2019 and September 2021 after obtaining institutional ethics committee approval (IEC/VMMC/SJH/Thesis/2019-10/150) from VMMC & Safdarjung Hospital, New Delhi, on 30 October 2019, and confirming compliance with the Declaration of Helsinki.
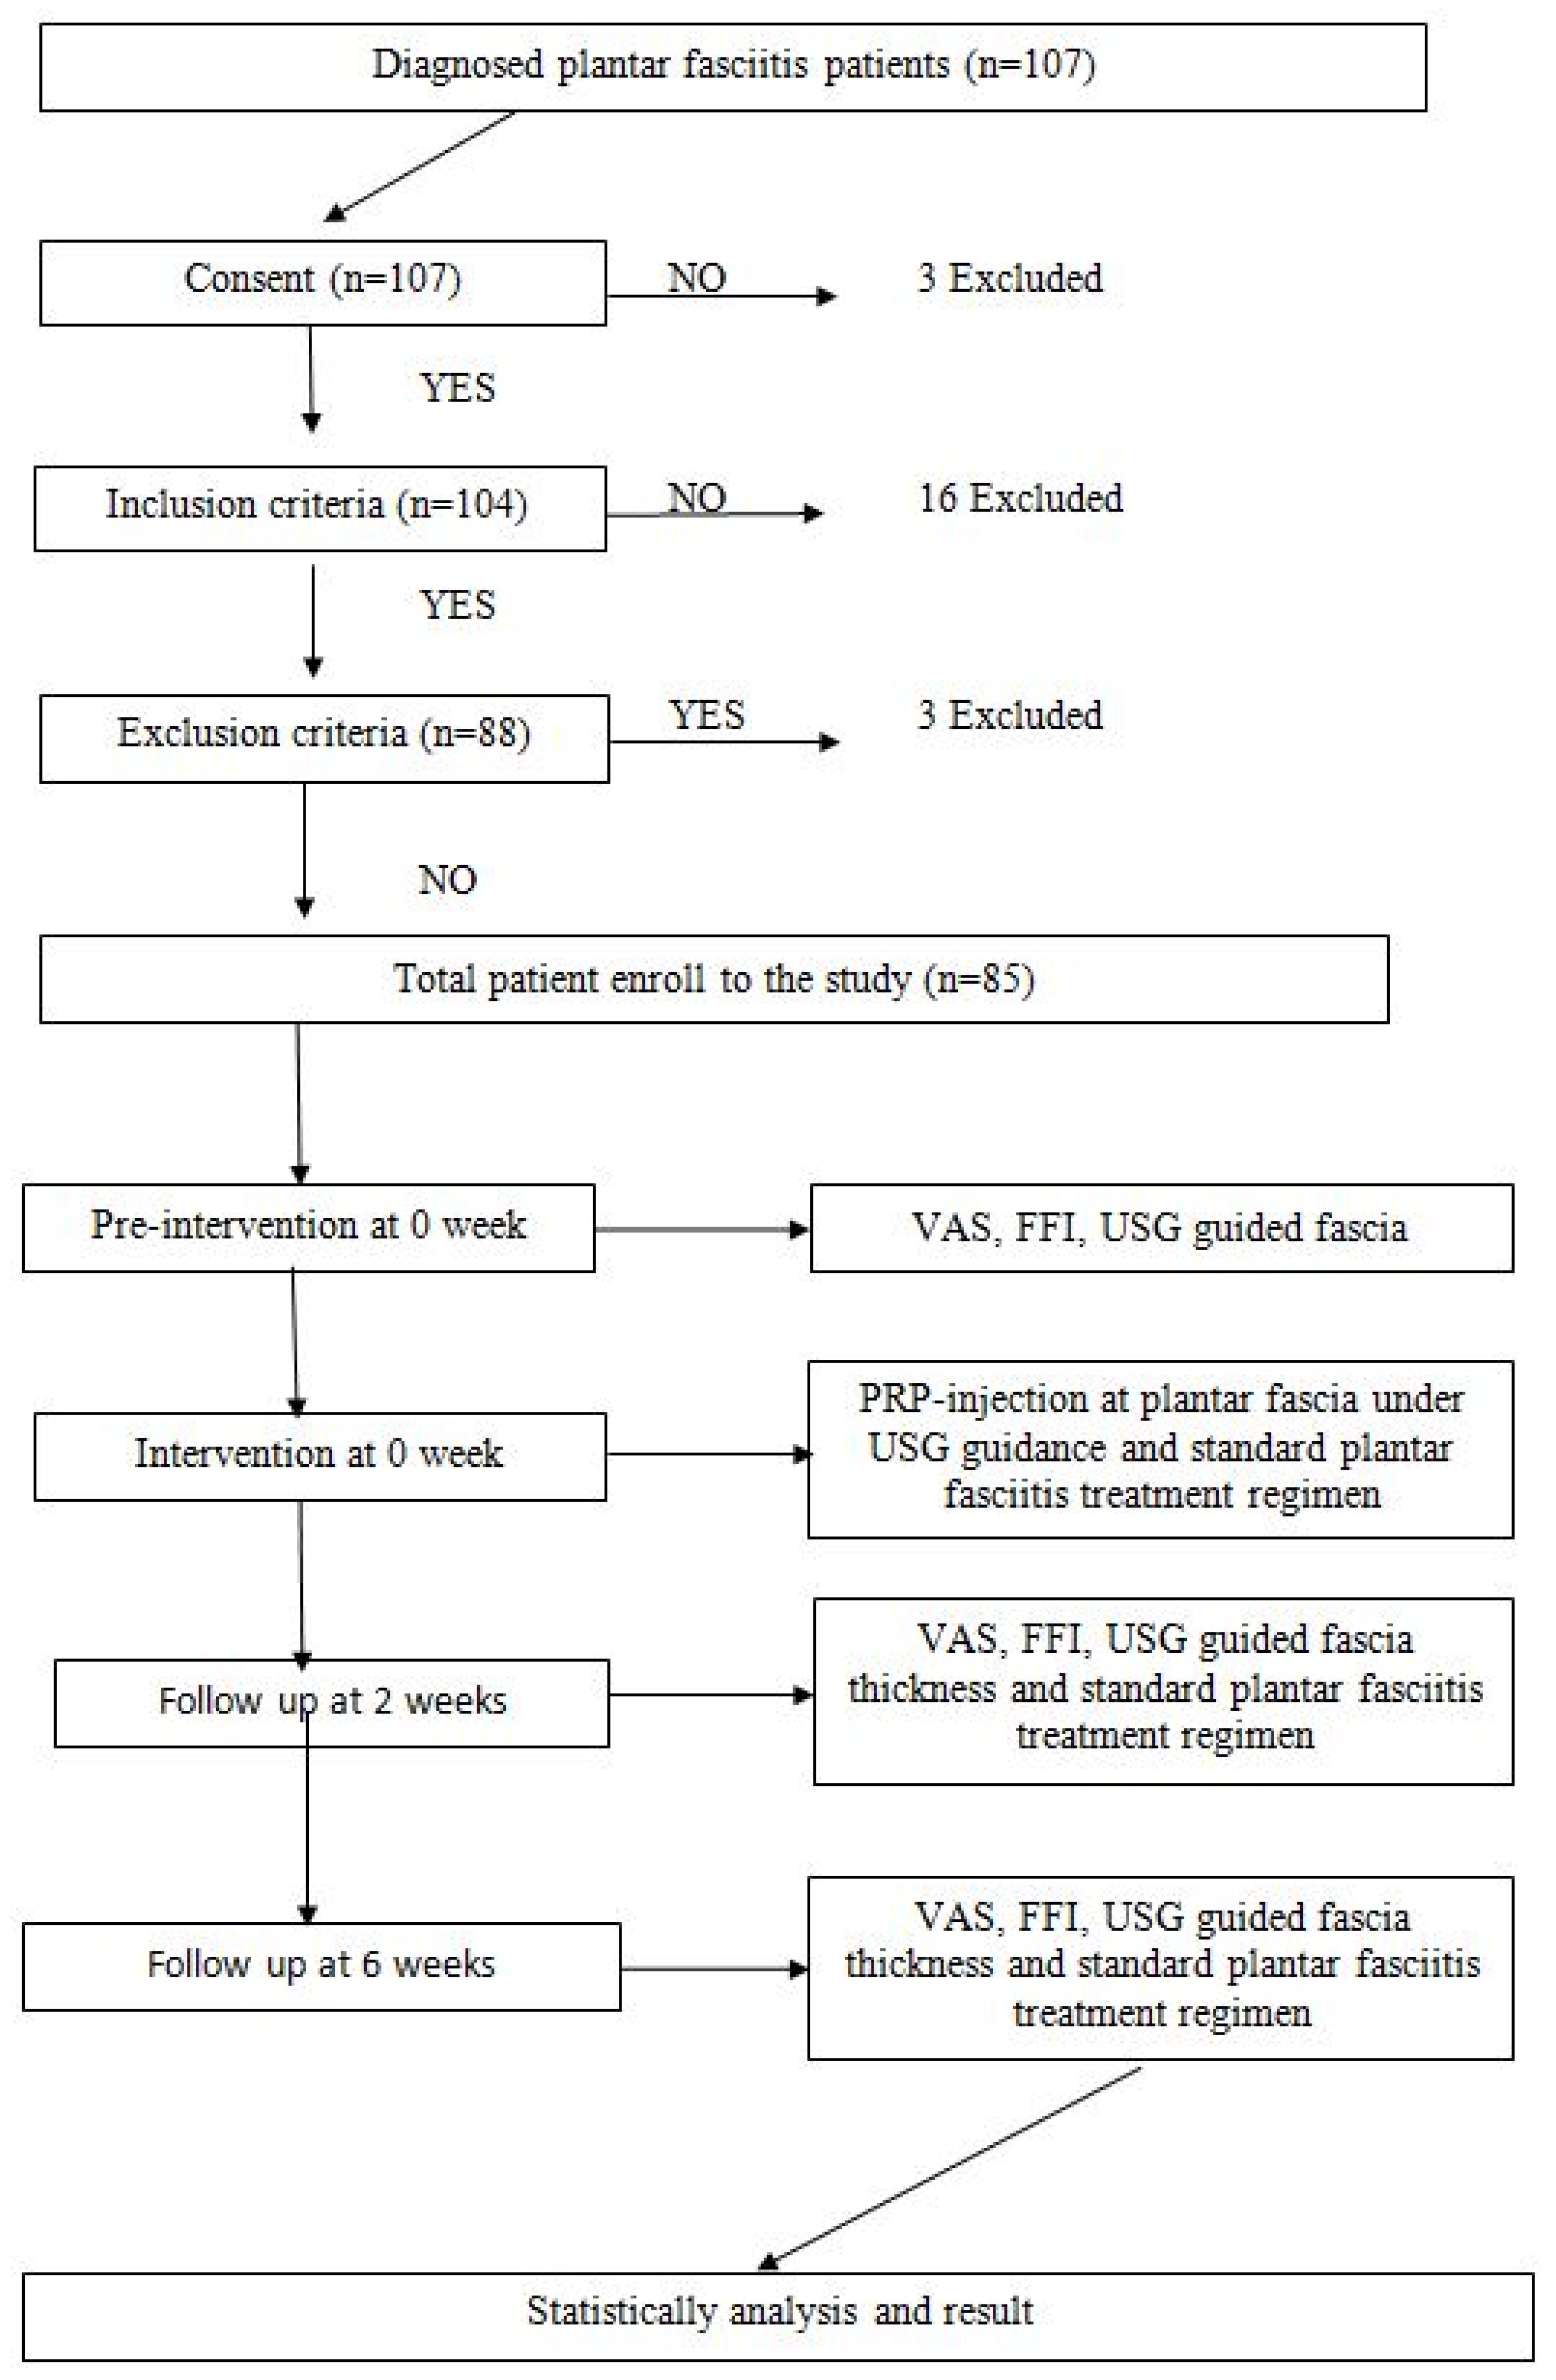
After obtaining informed consent, a total of 107 patients were subjected to screening. Eighty-five cases aged 18 years and older who had been diagnosed with unilateral plantar fasciitis and had not experienced any improvement in symptoms despite receiving conservative treatment for a period exceeding three months were included in the study. However, 22 patients were excluded from the study due to history of bleeding disorder and ongoing anticoagulation therapy, prior surgery on the plantar fascia, presence of local malignancy, pathology of the Achilles’ tendon, pregnancy, uncontrolled diabetes, and any local trauma or infection as shown in Figure 1.
A total of eighty-five individuals were evaluated to determine their pain levels using the visual pain scale (VAS), assess their functional score using the foot function index (FFI), and measure the thickness of the plantar fascia using ultrasound imaging (USG). These assessments were conducted at three different time points: baseline, the second week, and the sixth week. The patients were instructed to start gentle stretching exercises of plantar fascia and Achilles tendon, and exercises aimed at strengthening the foot and ankle musculature.
Following proper aseptic techniques, about 20 mL of autologous peripheral venous blood was obtained and collected in a vial coated with sodium citrate. The collected blood was then subjected to centrifugation at a speed of 2500 rpm for a duration of five minutes using a centrifugal machine to prepare platelet-rich plasma (PRP) as shown in Figure 2.
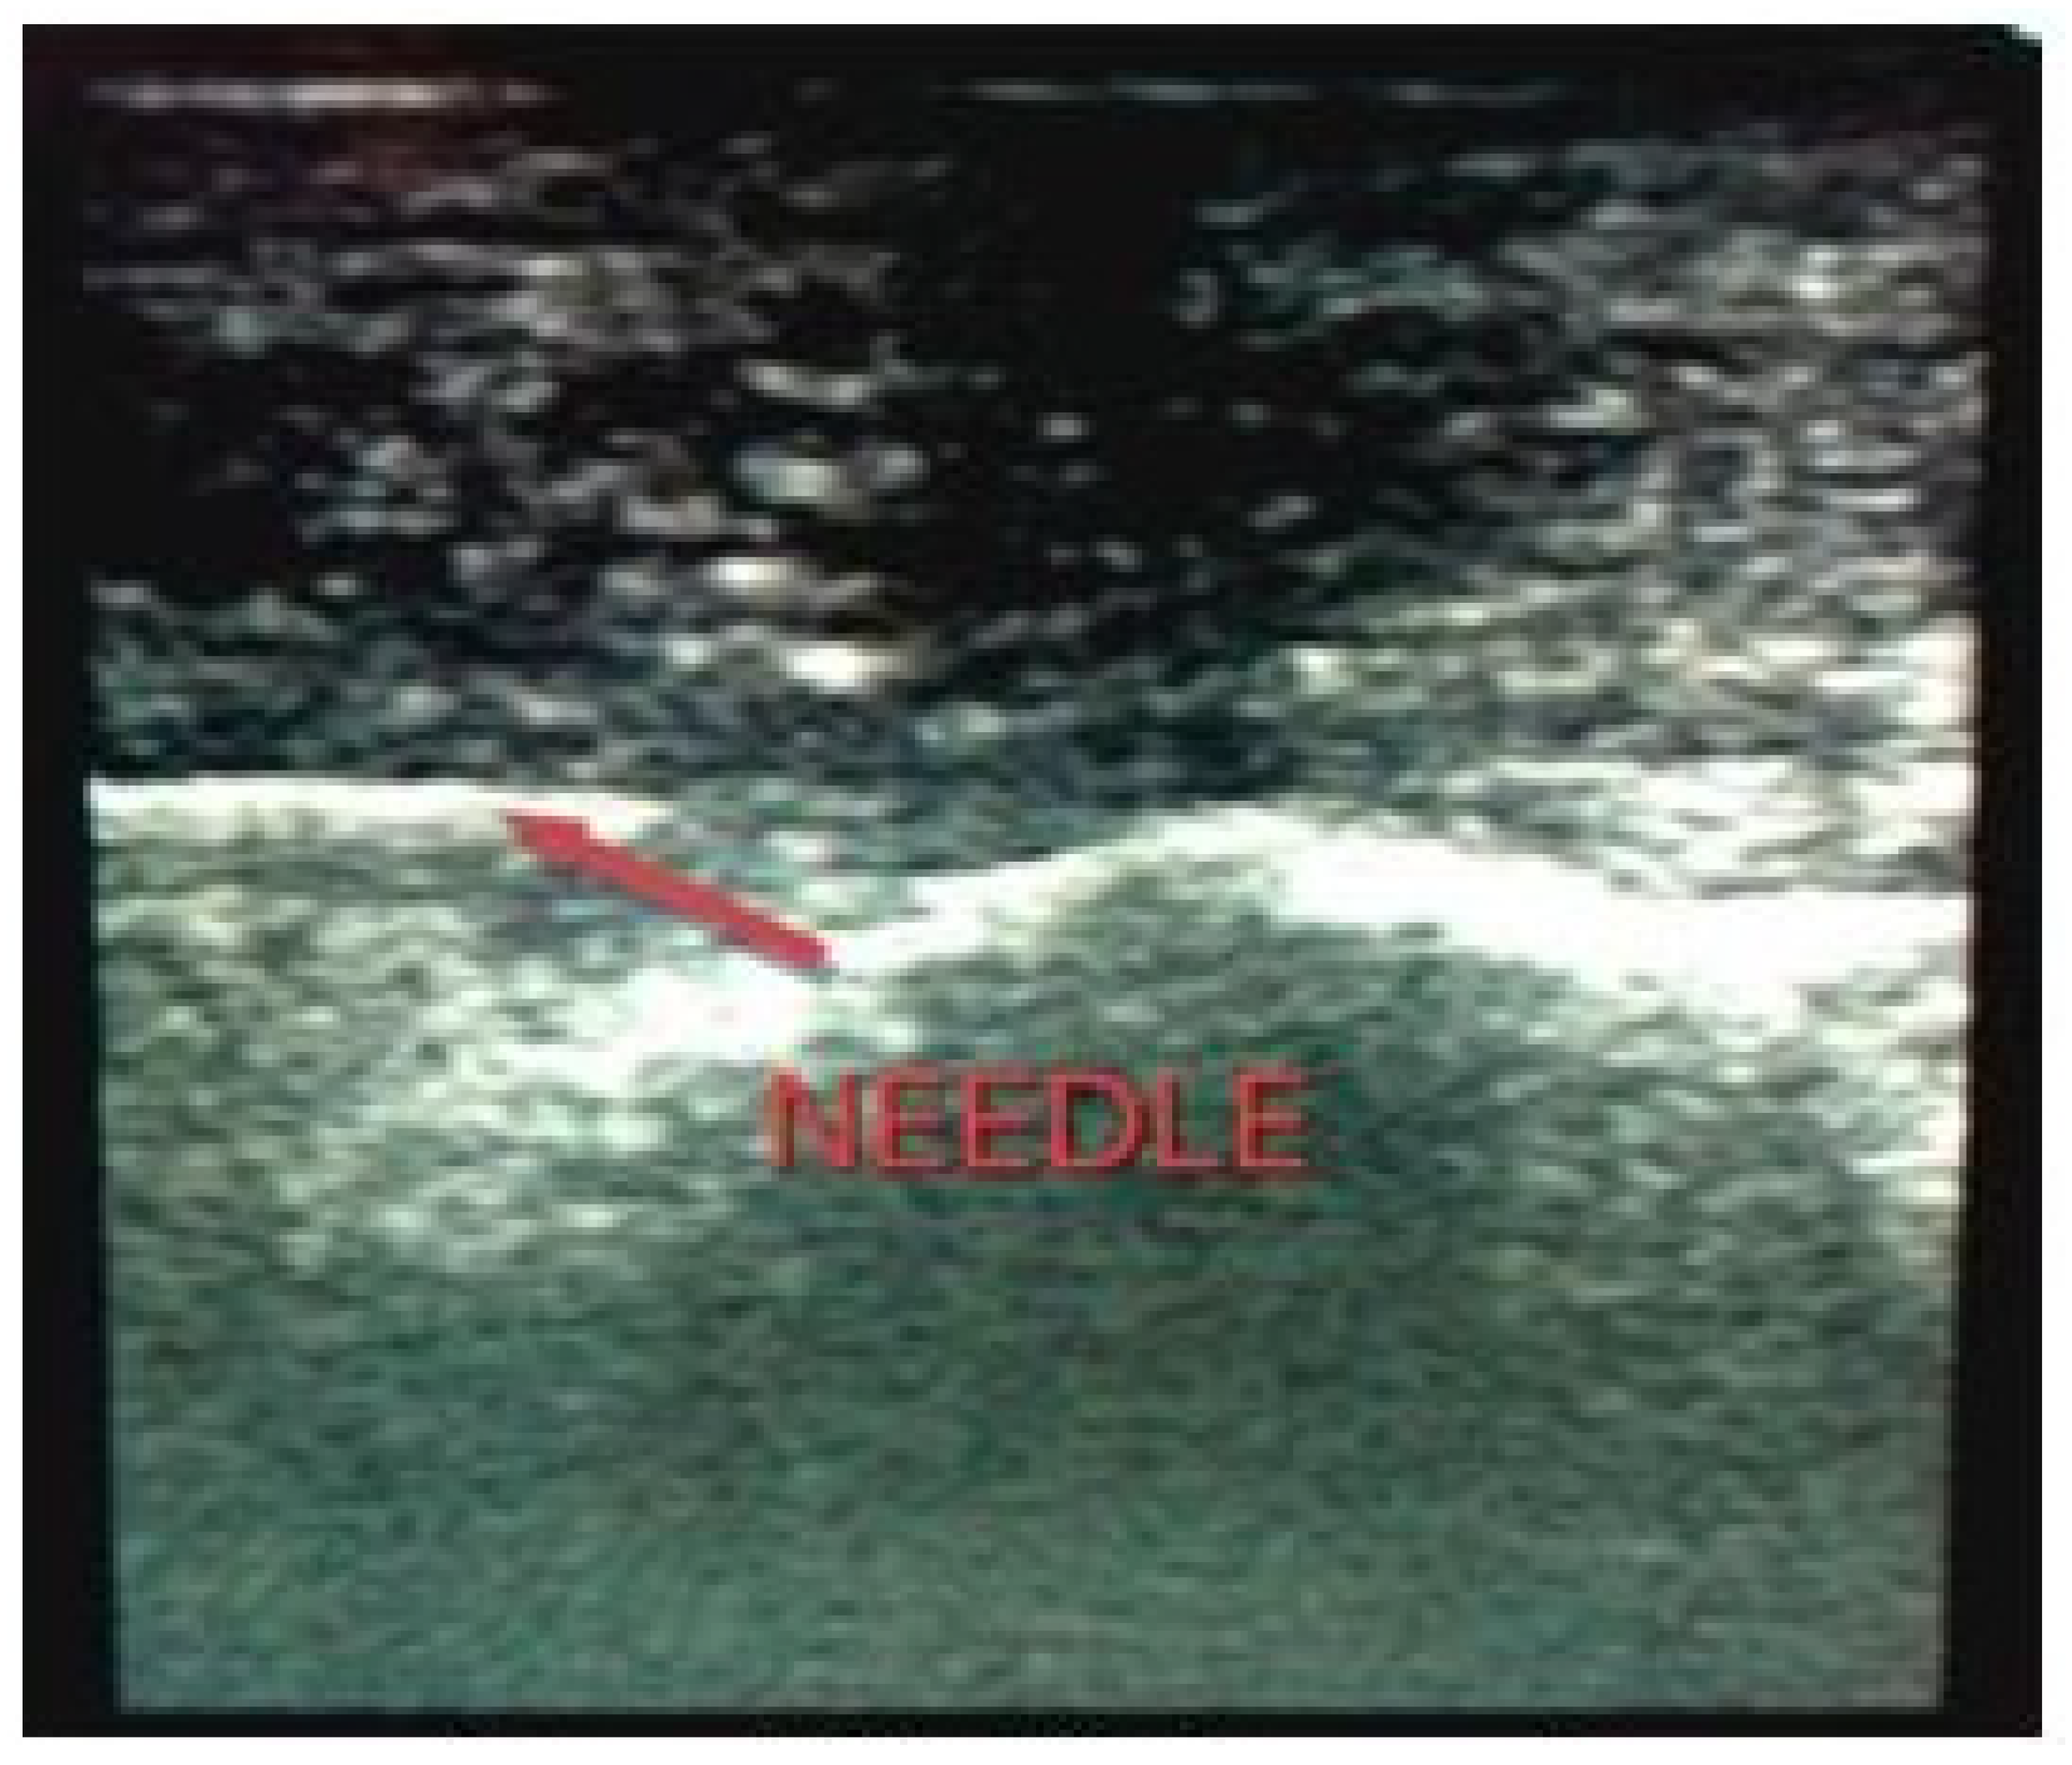
Under ultrasound guidance, 2 mL of freshly prepared PRP was injected immediately into the plantar fascia near the medial calcaneal tubercle at the point of maximum tenderness of the plantar fascia as shown in Figure 3. Following the administration of the injection, all patients were provided with a rescue drug of paracetamol 650 mg.

2.2. Statistical Analysis

Data were entered in MS Excel, and analysis was done using SPSS version 21.0. We presented the data as mean and standard deviation for continuous variables and as percentages for categorical variables. We performed repeated measures ANOVA to compare the means at three different time points. A post hoc Bonferroni test was done to compare paired means between two time points. A p-value of less than 0.05 was considered significant.

3. Result

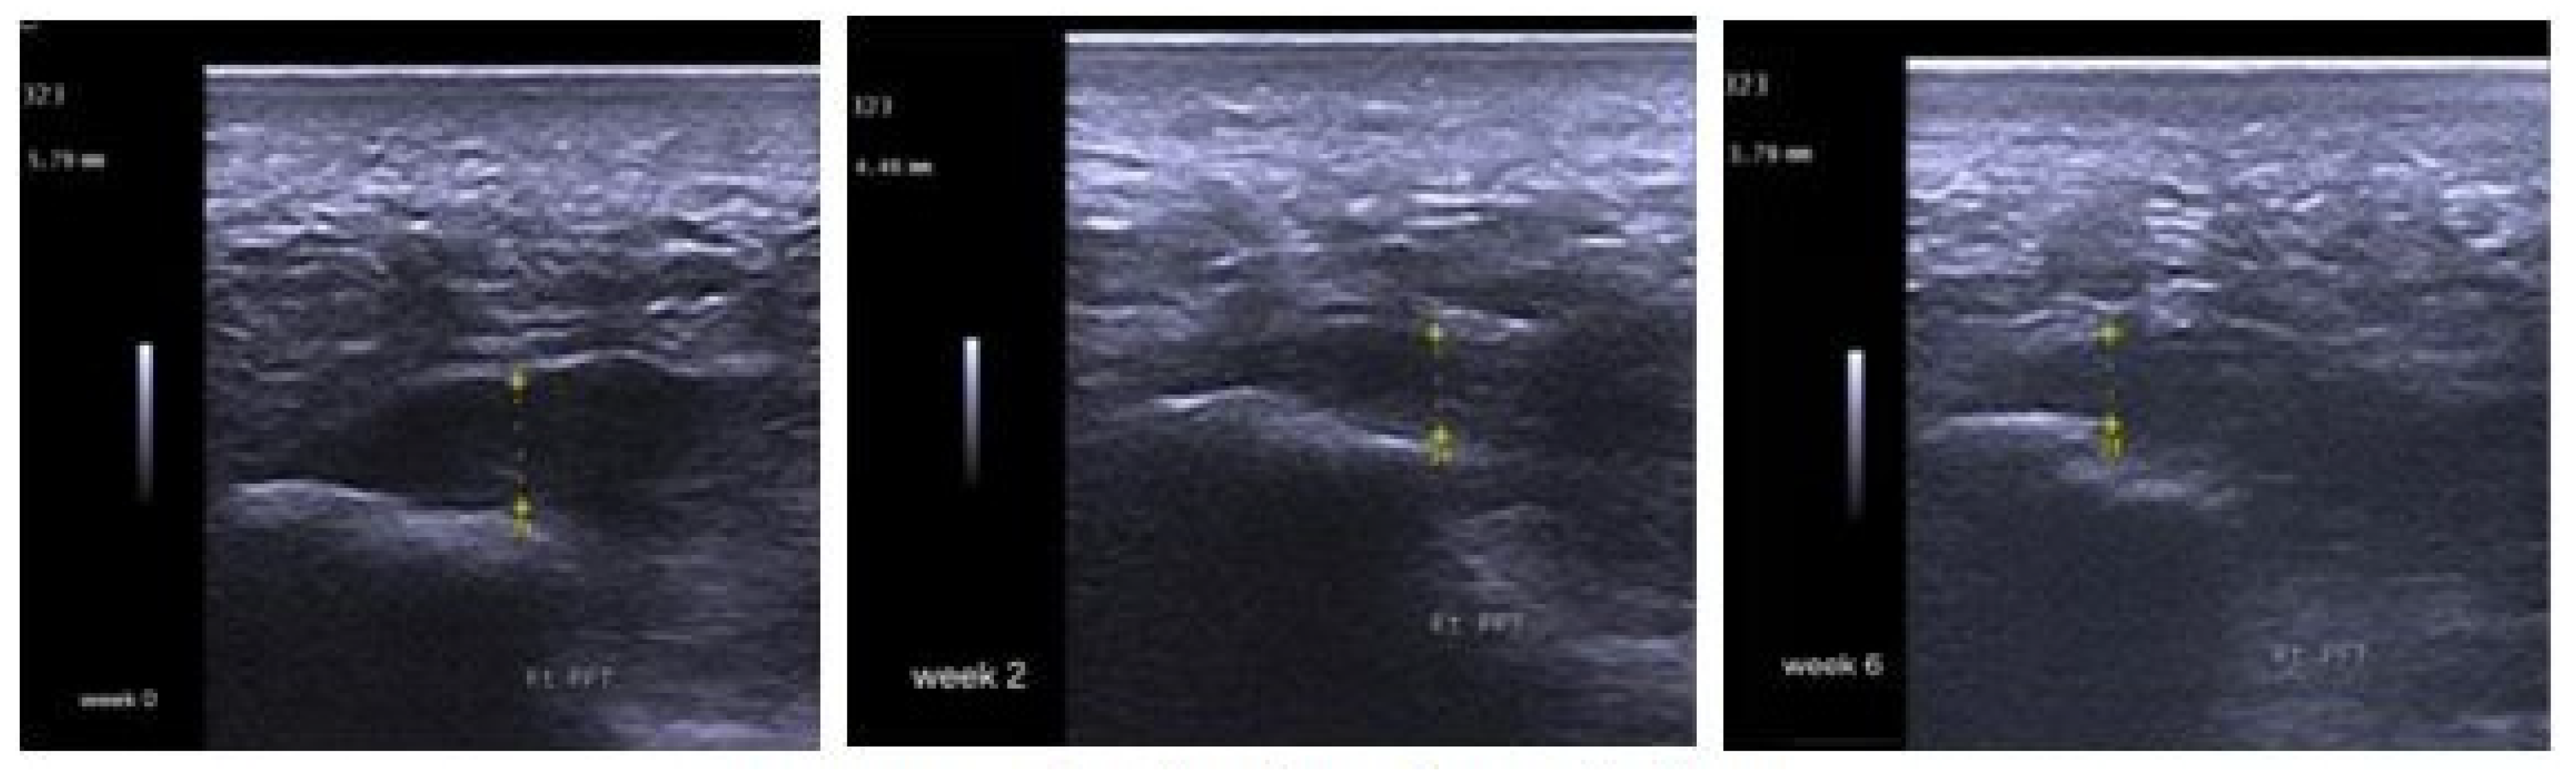
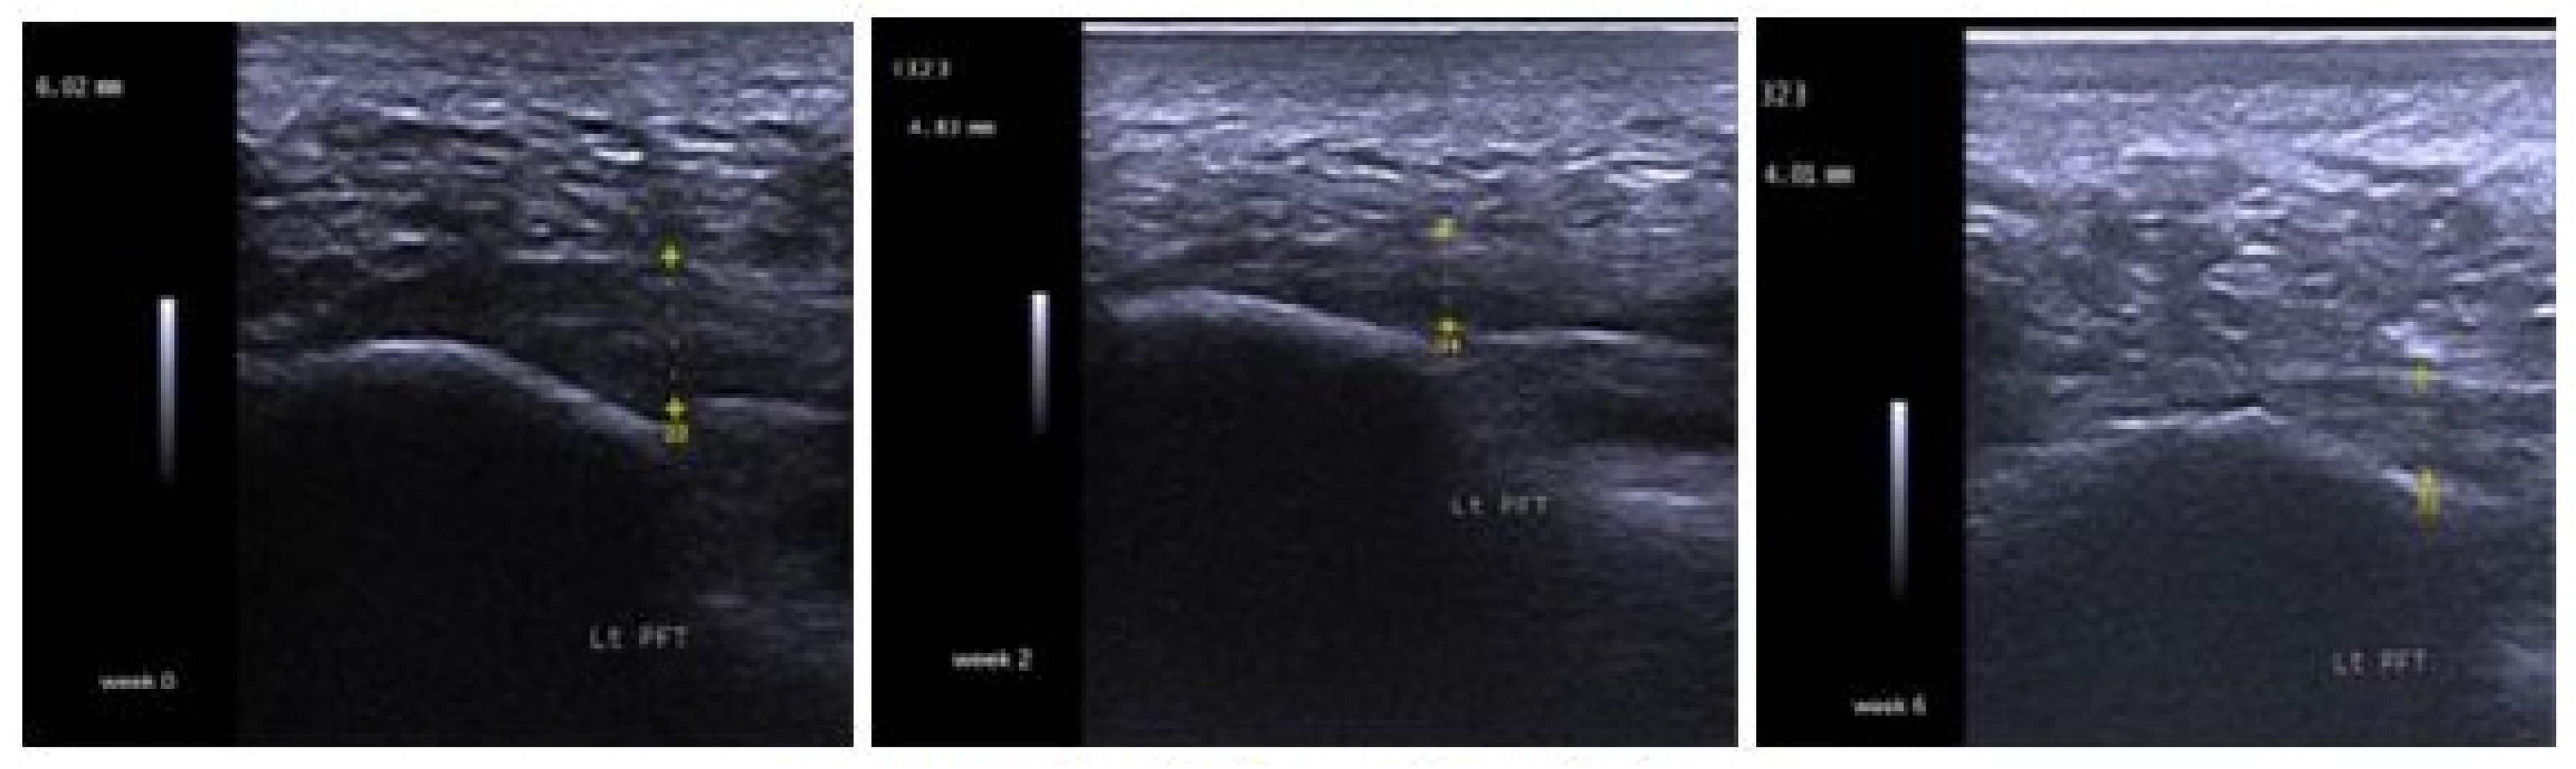
Eighty-five eligible patients were enrolled in the study; all patients received ultrasound-guided intralesional PRP injection. Most patients were over 40 years of age (75.3%), and the mean age group was 43.435 ± 5.35 years; 57 (67.1%) were females, and 44 (32.9%) were males. Homemakers were more affected than other occupations; 50.6% of patients had left side involvement compared to 49.4% with right side involvement as shown in Table 1. Figure 4 and Figure 5 show the progression of the decrease in PF thickness during follow-ups.
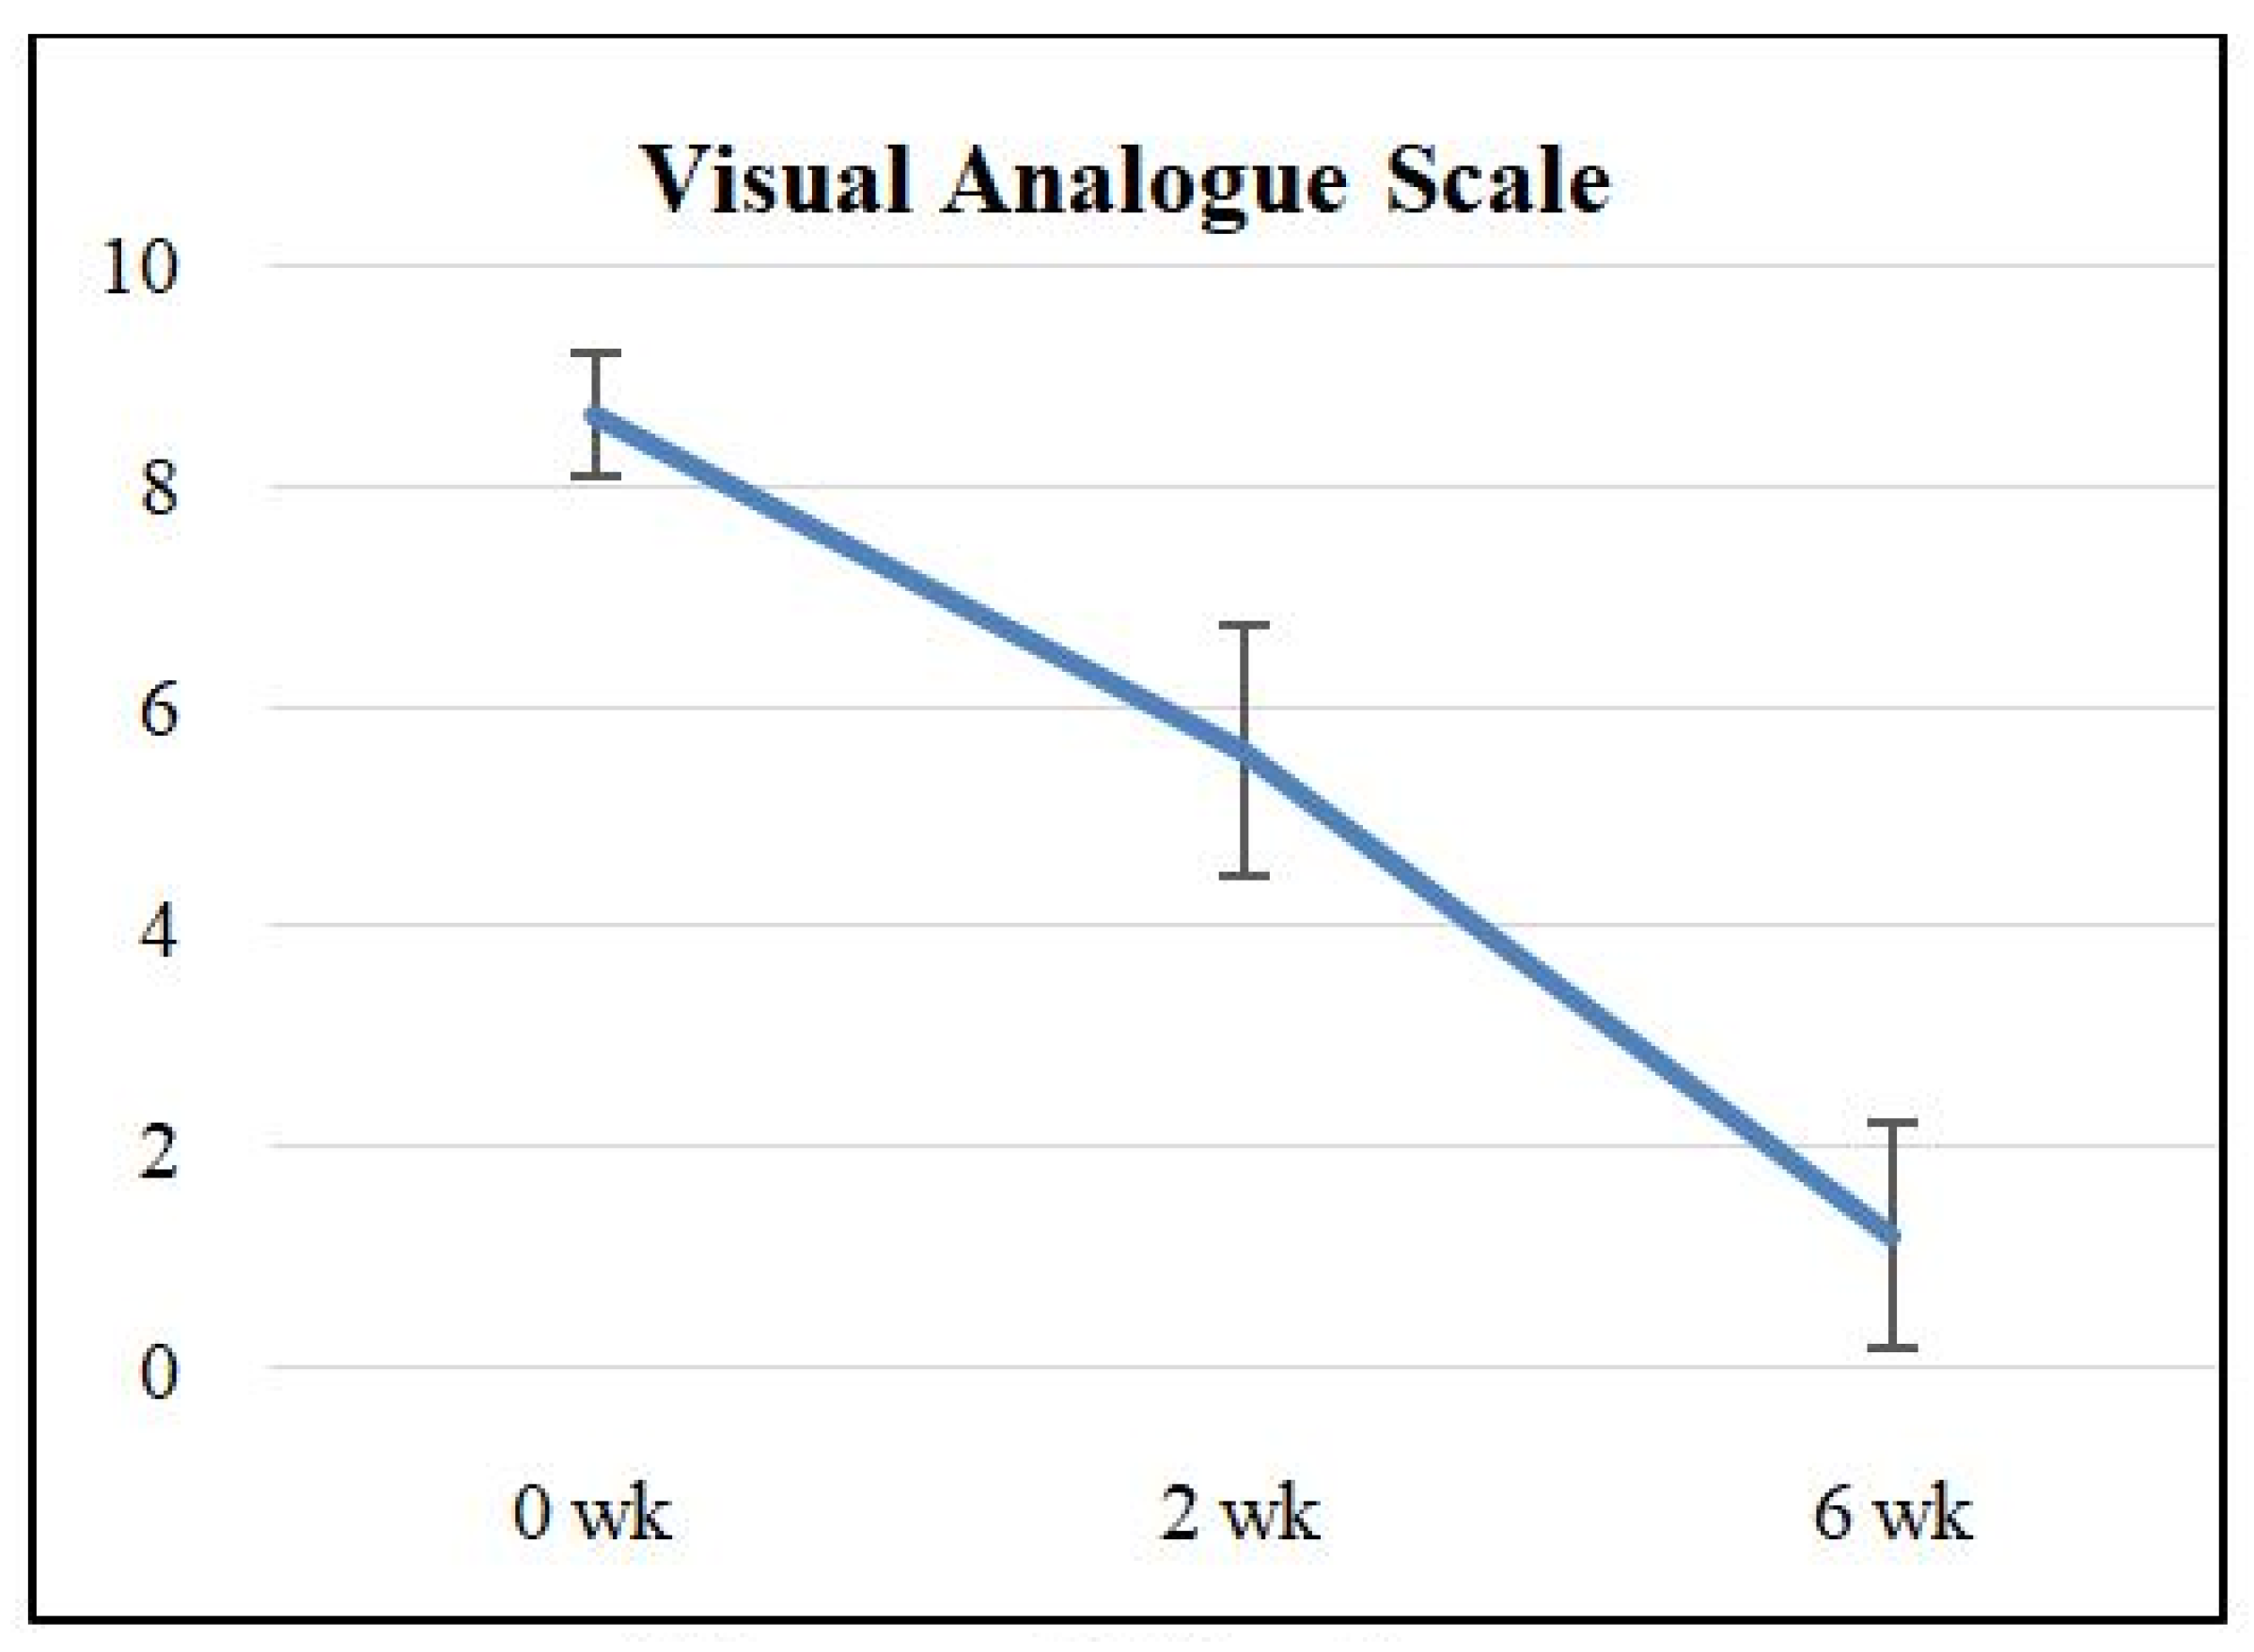
When comparing the visual analogue scale (VAS) scores between the baseline measurement of 8.647 ± 0.55 and the follow-up period, a significant decrease in VAS scores was observed among the patients at the two-week follow-up measurement of 5.588 ± 1.13 and the six-week follow-up measurement of 1.21 ± 1.01 (p < 0.05) as shown in Figure 6 and Table 2.
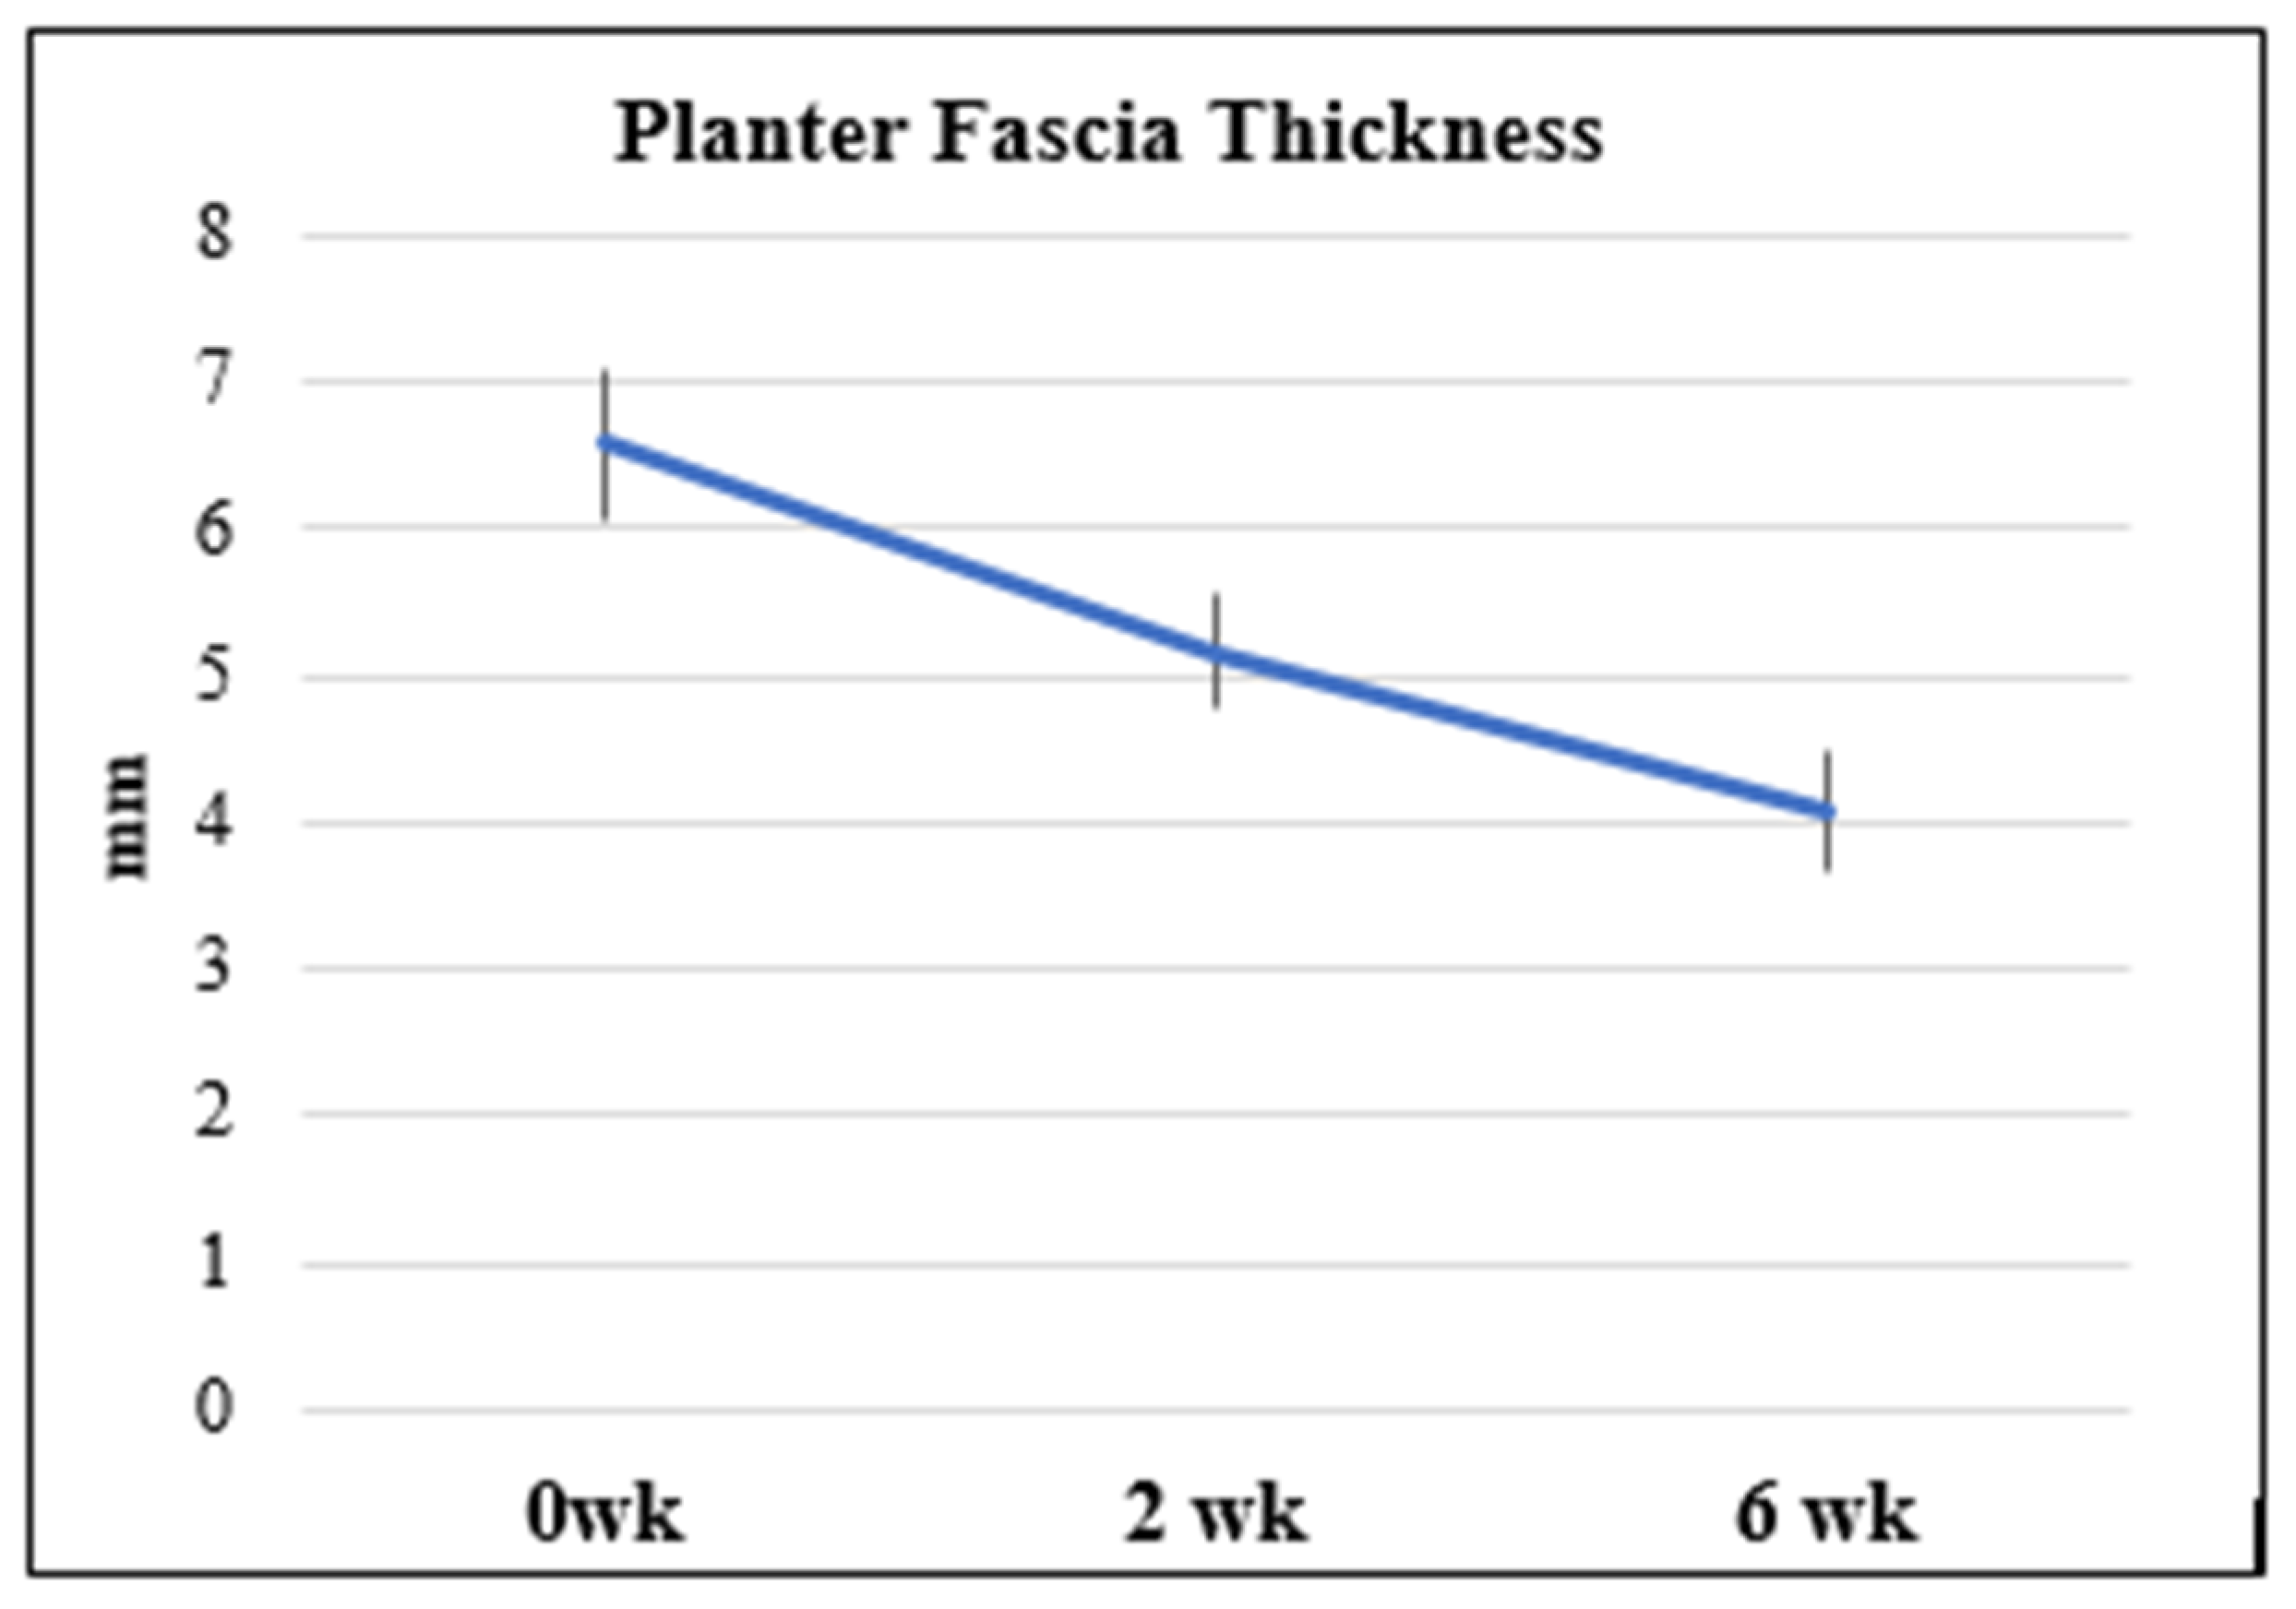
There was a statistically significant reduction in the thickness of the plantar fascia from the initial measurement of 6.59 ± 0.51 mm to 4.076 ± 0.399 mm after six weeks (p < 0.05) as shown in Figure 7 and Table 2.
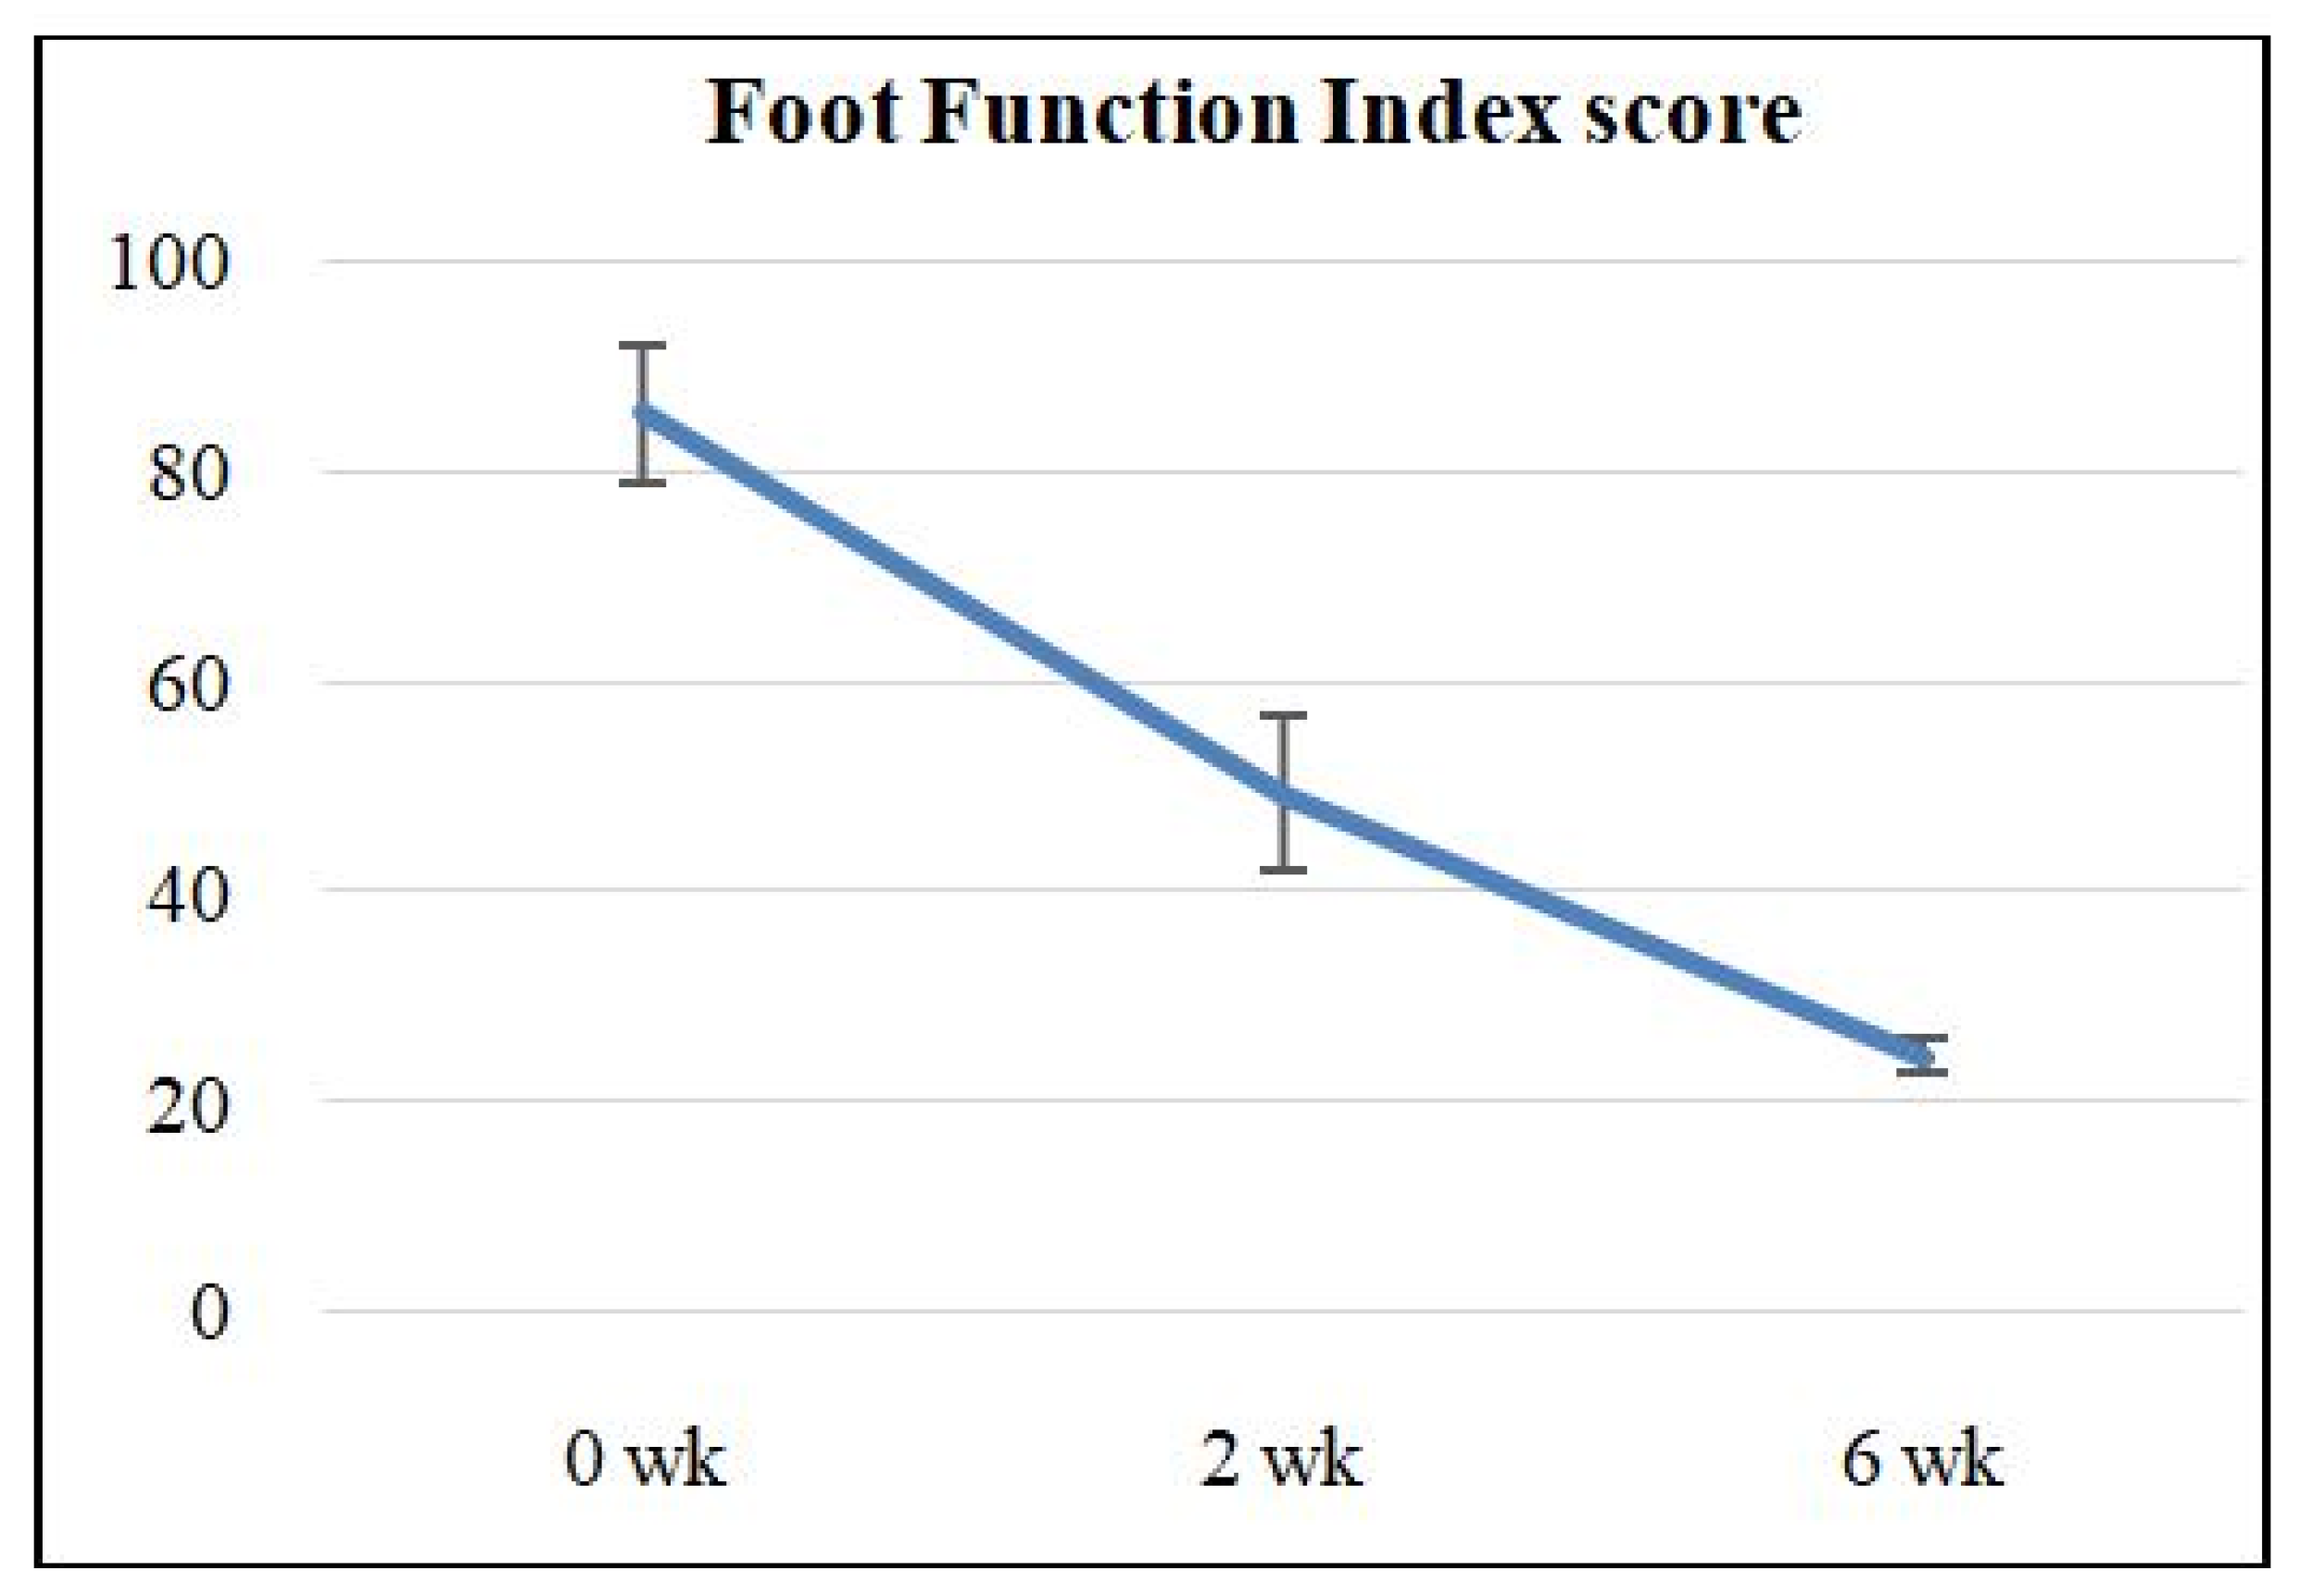
The study examined the overall foot function index (FFI) score changes over time. The baseline FFI score was recorded as 85.494 ± 6.55. After the intervention, there was a substantial decrease in the FFI score to 49.341 ± 7.27 at the end of the second week and a further decrease to 24.235 ± 1.60 at the six-week follow-up (p < 0.05) as shown in Figure 8 and Table 2.
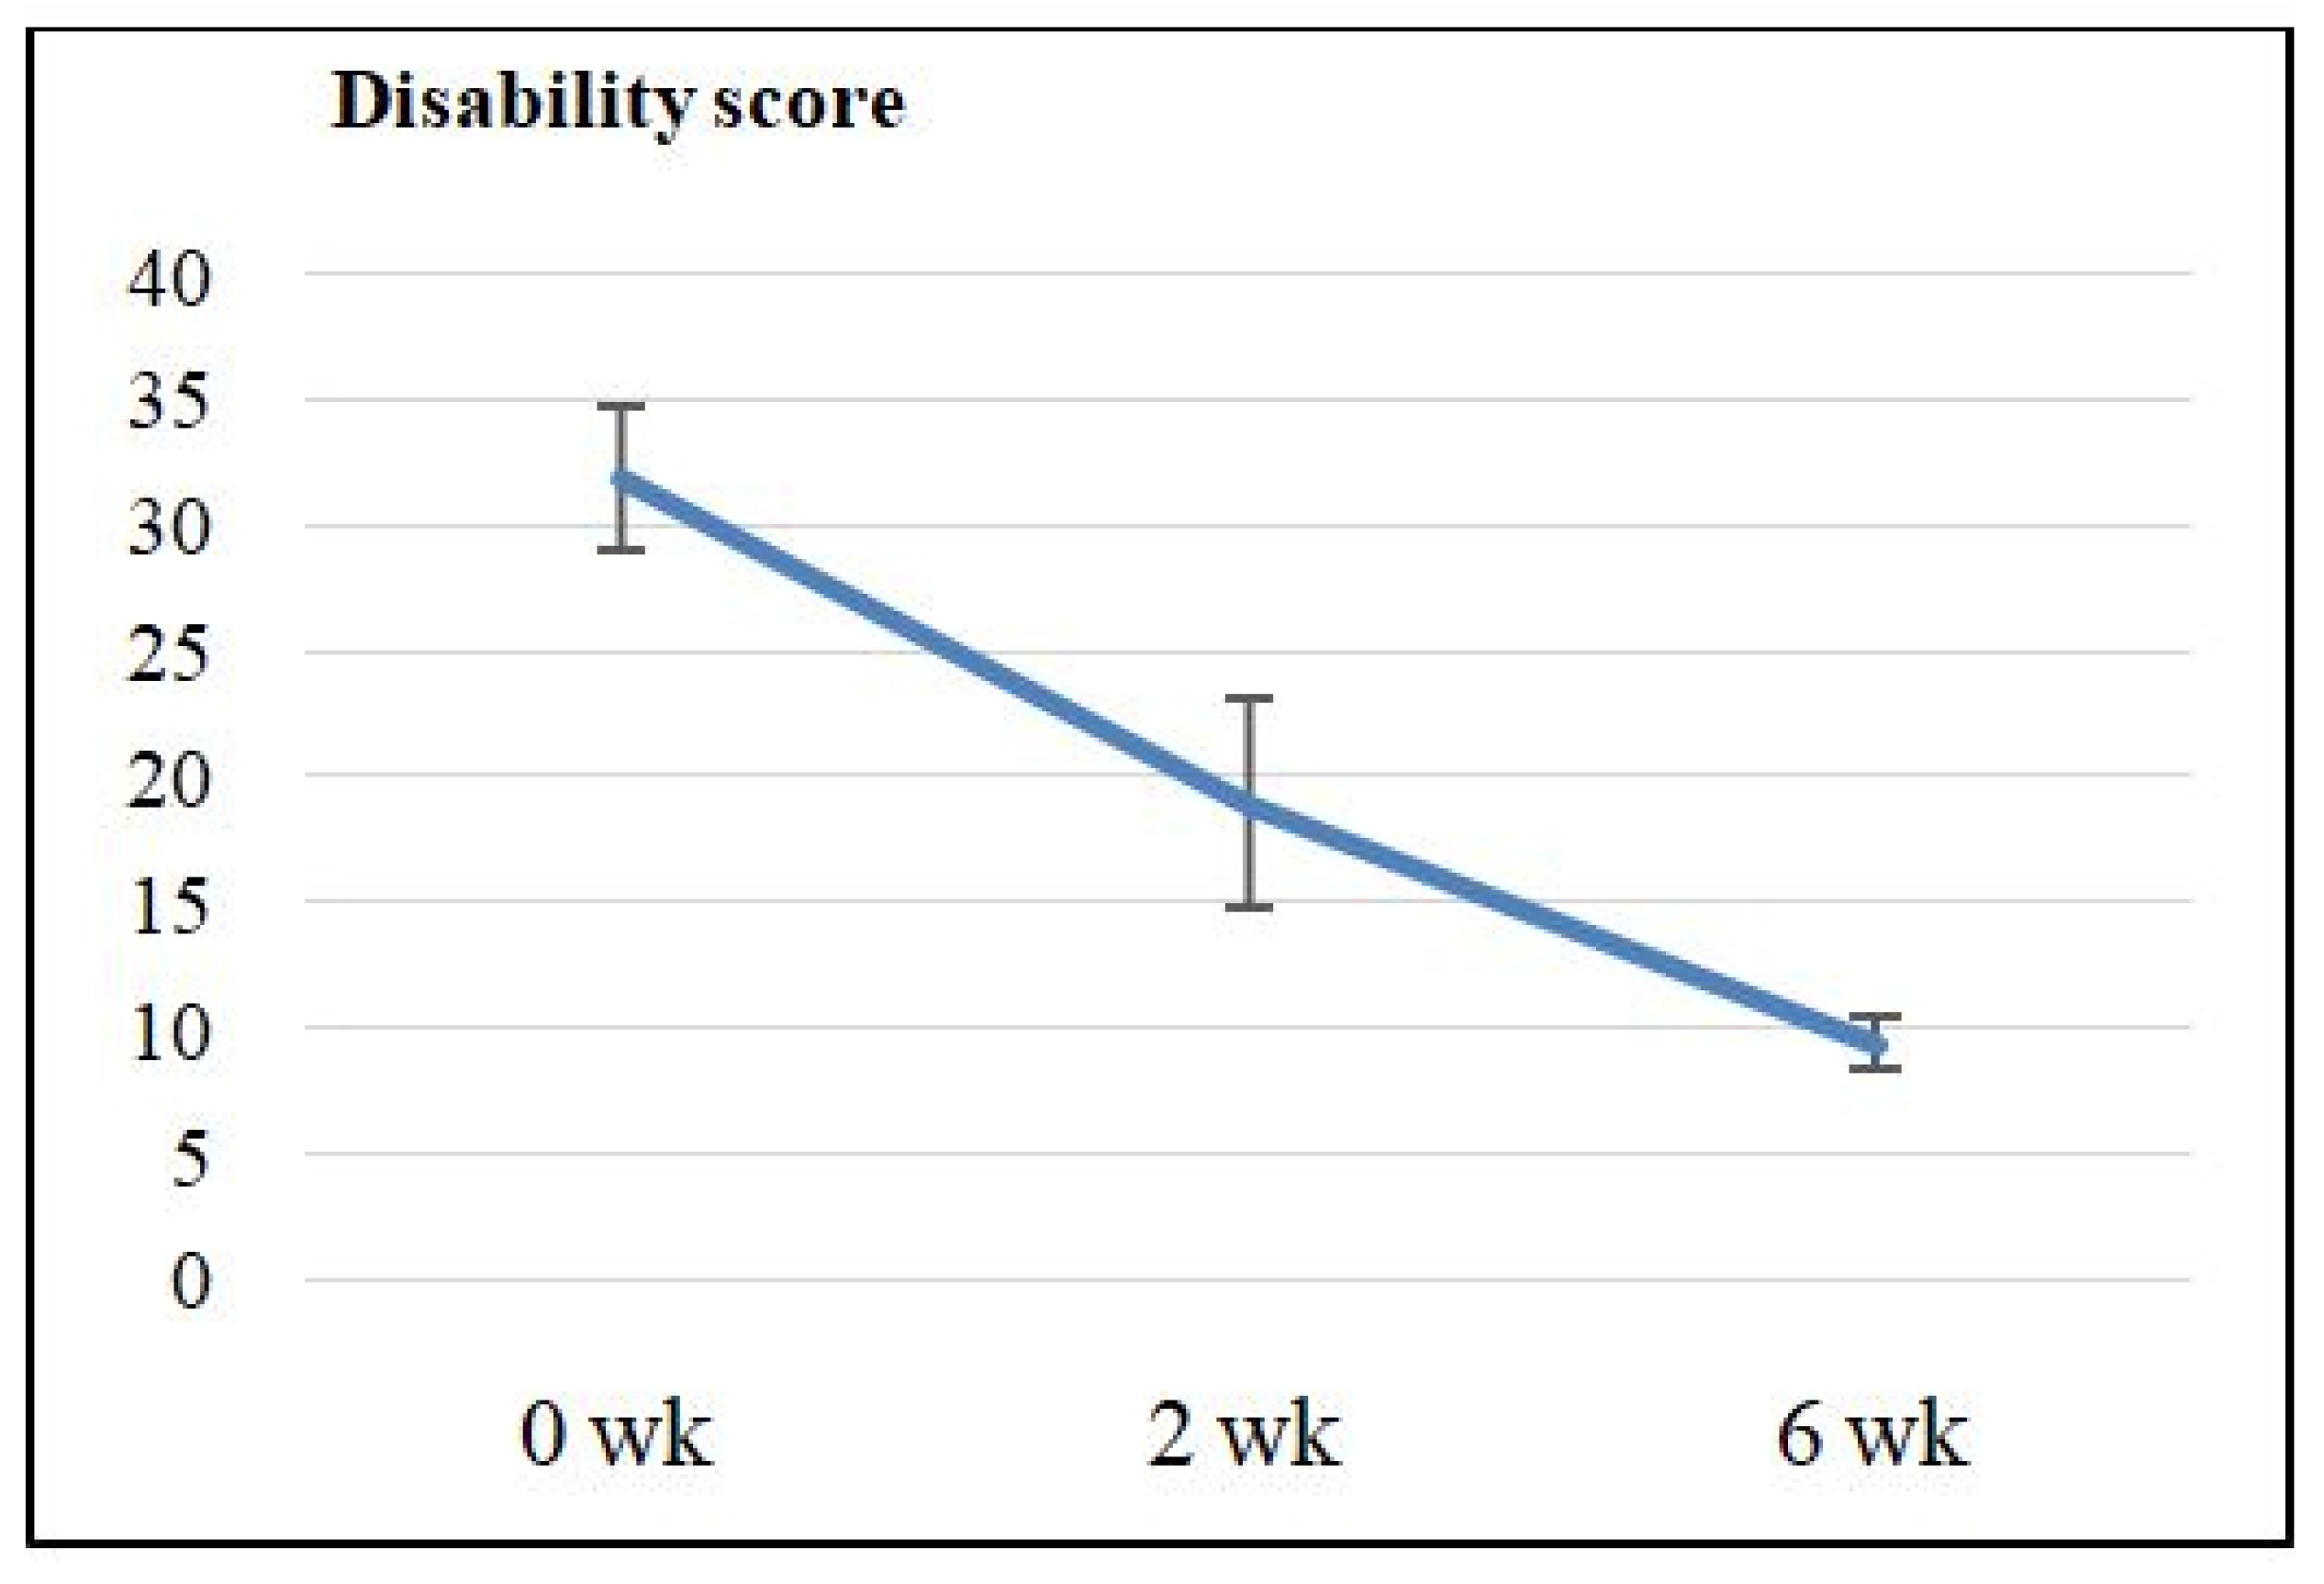
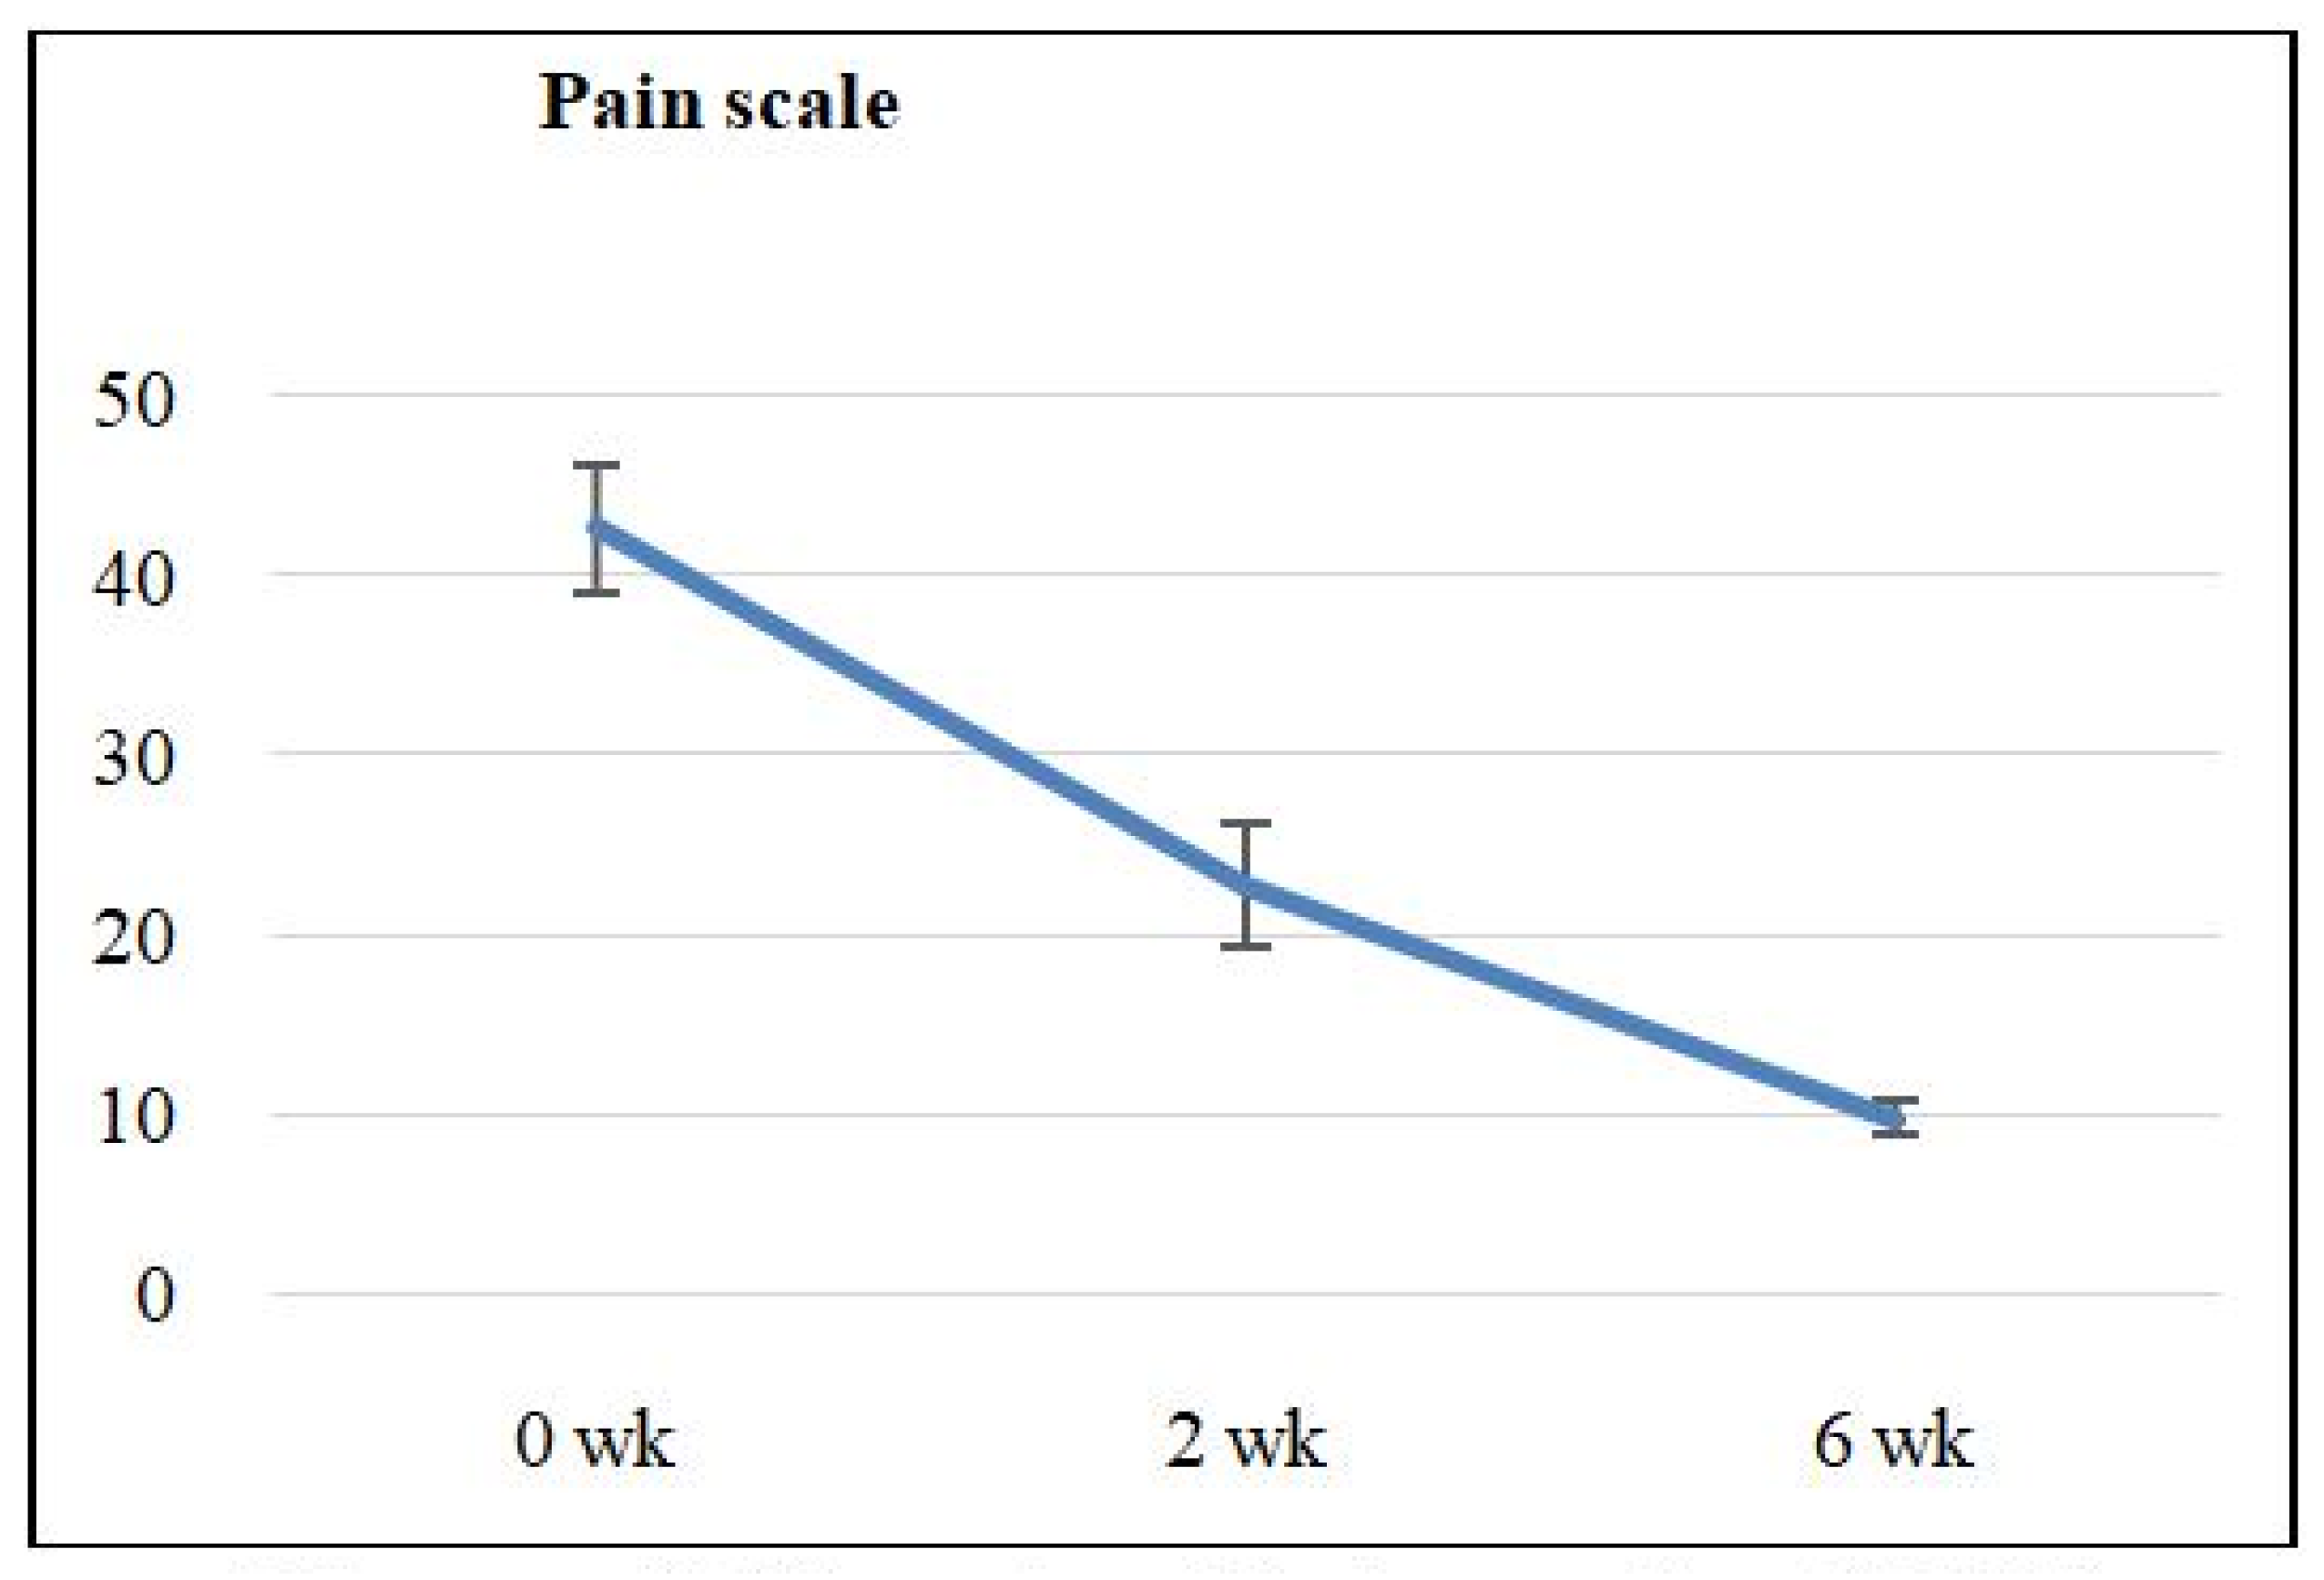
The pain domain scores in the foot function index were recorded as follows: at 0 weeks, the score was 42.58 ± 3.52; at two weeks, the score was 22.78 ± 3.48; and at six weeks, the score was 9.81 ± 1.052, as shown in Figure 9 and Table 2. The average disability score on the foot function index was 31.894 ± 2.78 at the baseline measurement (0 weeks), 19 ± 4.20 at the two-week follow-up, and 9.435 ± 1.09 at the six-week follow-up, as shown in Figure 10 and Table 2.
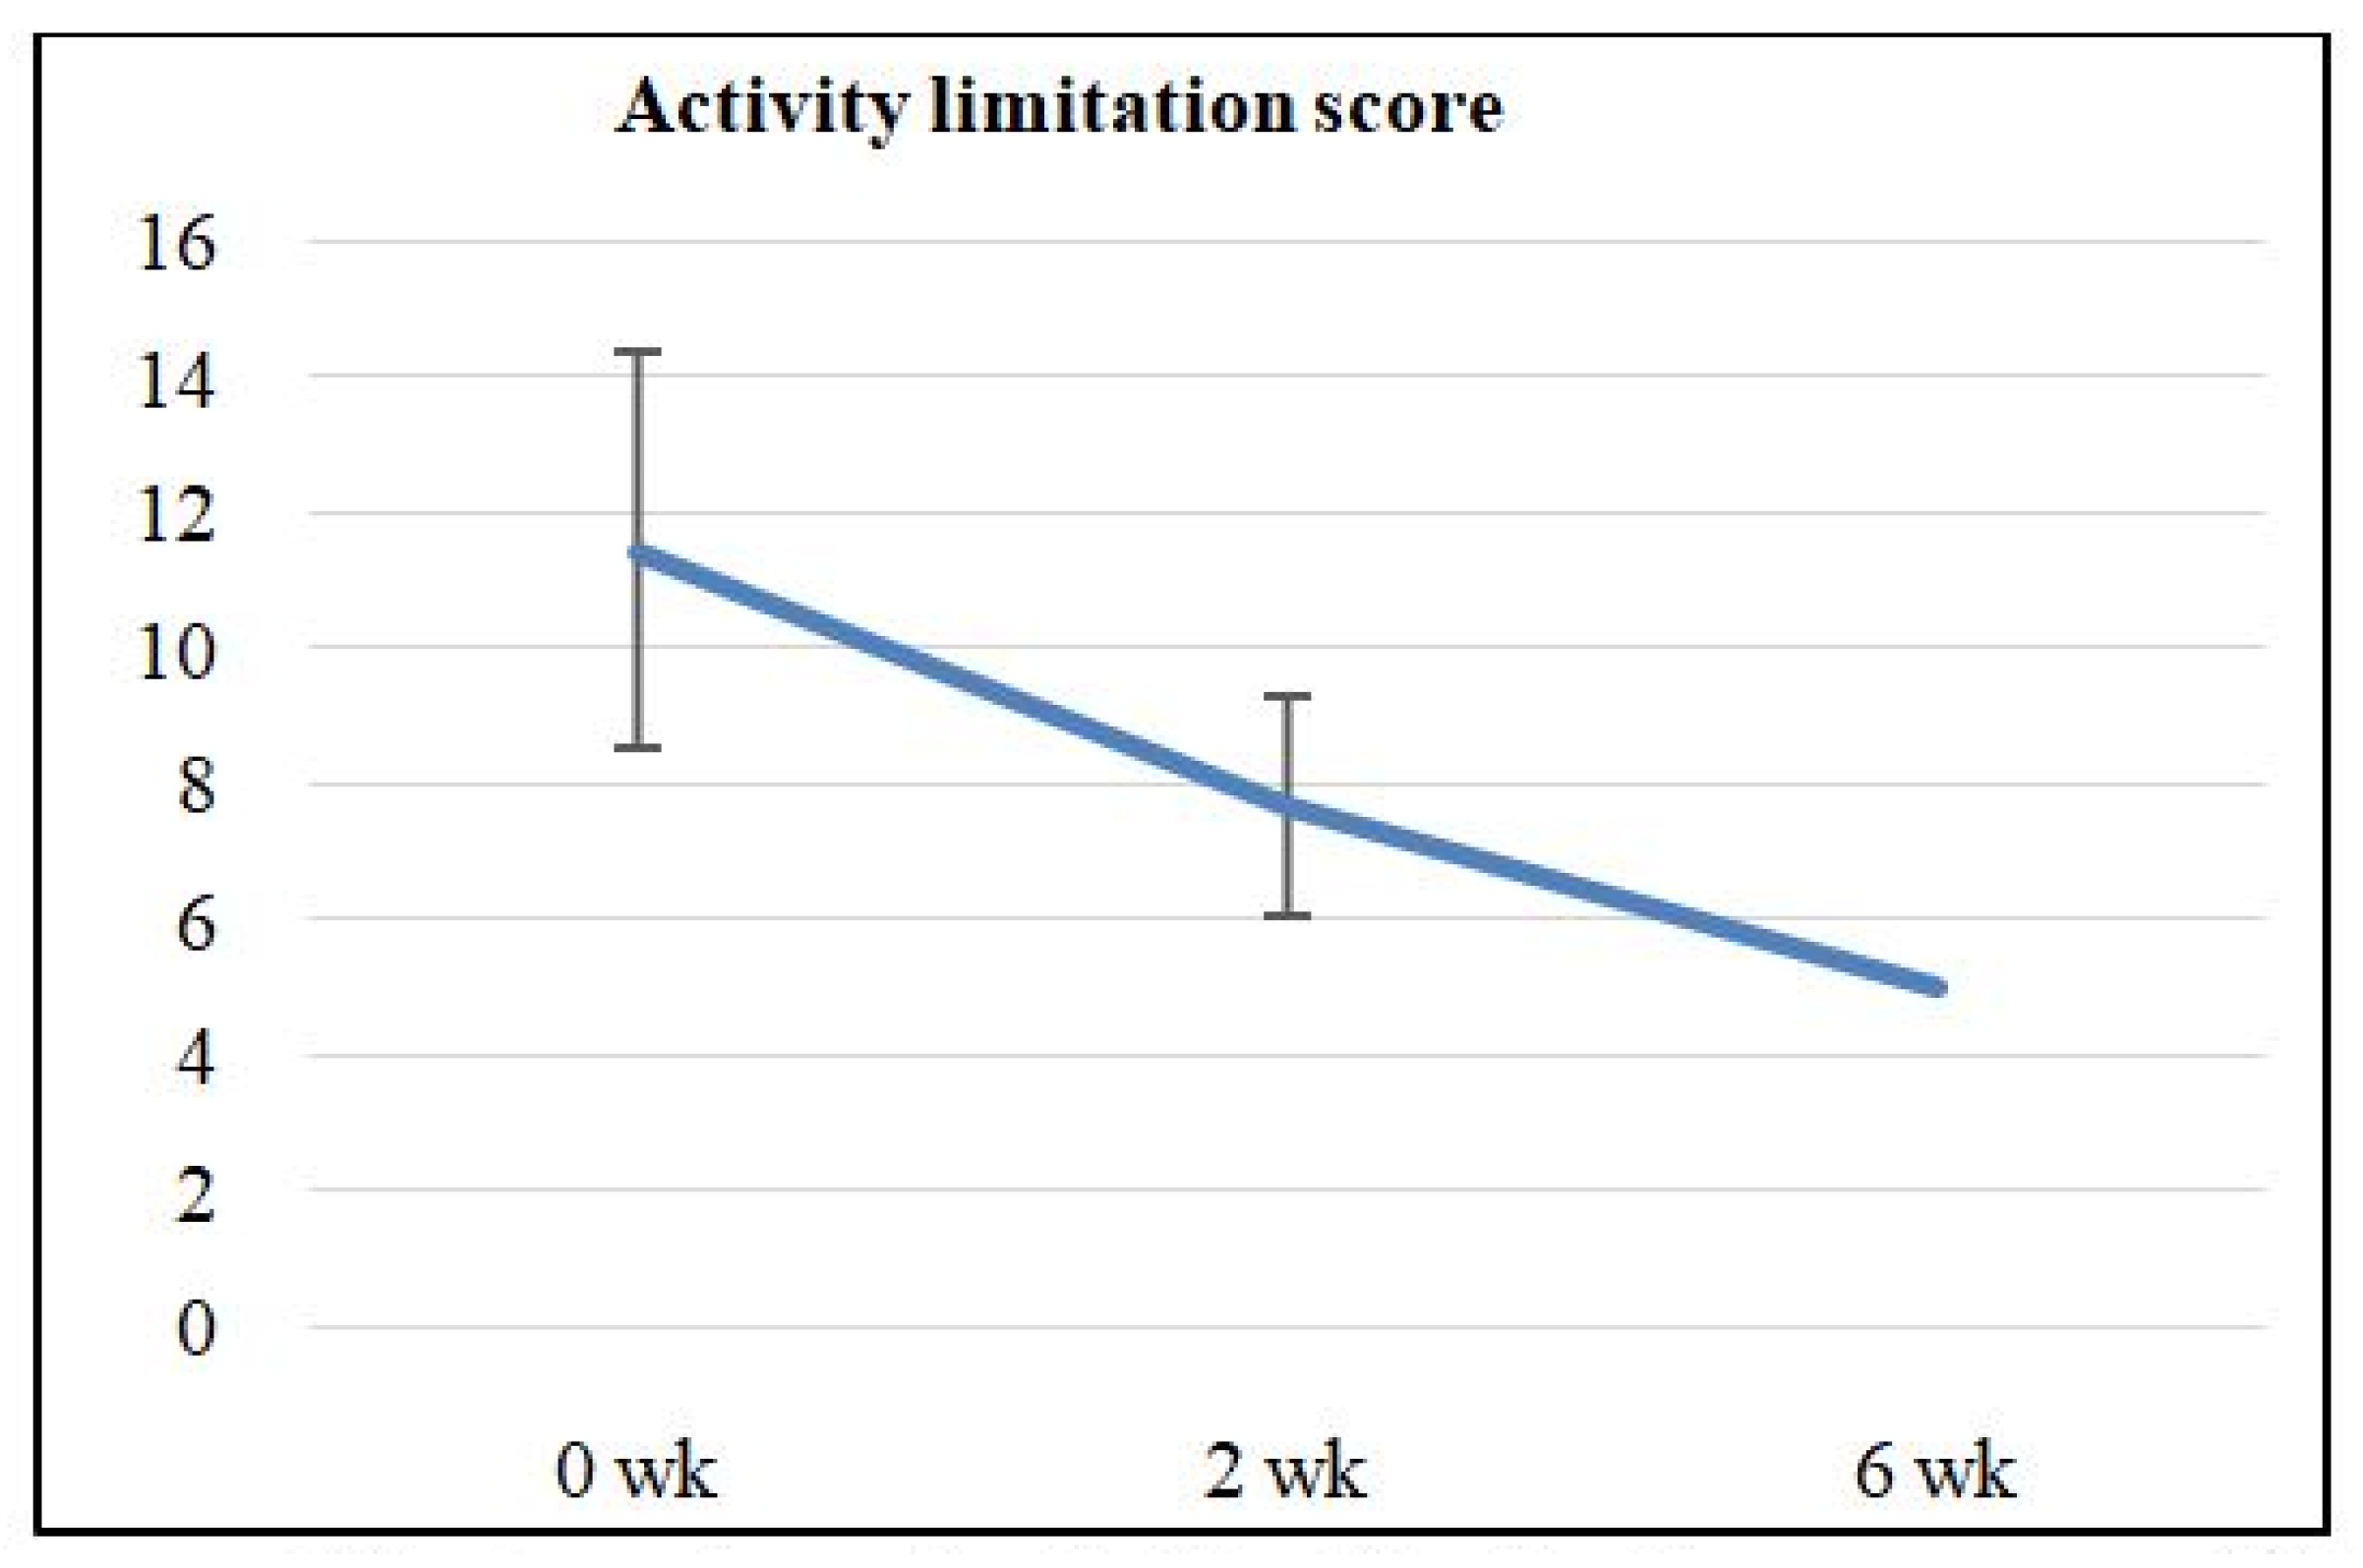
The mean activity limitation score in the foot function index was recorded at baseline (11.447 ± 2.913), two weeks (7.659 ± 1.62), and six weeks (5.0 ± 0.00) as shown in Figure 11 and Table 2.
Eighty-five patients reported complete compliance with the recommended post-procedure exercise programme. Until the end of the study period, no individual experienced any complications.

4. Discussion

In recent years, platelet-rich plasma (PRP) has been used to manage plantar fasciitis. The literature contains established evidence of its efficacy in alleviating pain and improving functional limitations associated with this condition [7]. The role of platelet-rich plasma (PRP) in regulating angiogenesis and promoting anabolic effects seems relevant in addressing the underlying pathophysiology of collagen matrix breakdown and disorganized vascularity observed in plantar fasciitis [8]. The combination of eccentric exercise, cyclic plantar fascia-specific stretching, and PRP injection can improve and expedite healing, leading to favourable long-term outcomes [10].
In our study most of our patients were aged above 40 years; the mean age of the patients was 43.43 ± 5.35 years, comparable to the study by Agyekum et al. [11] which reported the common age group presentation was 40–60 years [11]. The number of female patients (65.1%) outnumbered males (34.9%) in our study, which correlates with the study done by Nahin R. et al.: females (1.19%), males (0.47%) [12]. In our study, most of the patients were homemakers (52.4%) with a history of prolonged standing. This finding is comparable with the study of Lapidus PW and Guidotti FP which highlighted patients with occupations with continual standing or walking, such as homemakers, waiters, maids, and kitchen workers [3]. In our study, involvement of the left heel (50.2%) was slighty more as compared to the right heel (49.8%). However, in the literature reviewed, there was no study that reported side predominance in plantar fasciitis affliction.
The pain scores on the visual analogue scale (VAS) showed a significant decrease at 0 weeks, 2 weeks, and 6 weeks; the median pain scores decreased by 9, 6, and 1 respectively (p value < 0.001). This finding is consistent with the study conducted by Deghady et al. [13], who also reported a statistically significant improvement in median pain scores recorded on the VAS. In their study, the baseline pain score was 9, which decreased to 5 at 2 weeks and 4 at the end of 6 weeks (p value 0.001). There was a statistically significant reduction in pain scores observed in our study. The pain scores decreased from an average of 8.64 ± 0.55 at baseline to 5.58 ± 1.13 at the 2-week follow-up. Furthermore, the pain levels further decreased to 1.21 ± 1.01 at the end of the 6-week period. This finding is consistent with a previous study conducted by Puri V, specifically in reference to the baseline pain scores [14]. The visual analogue scale (VAS) at baseline was recorded as 8.47 ± 0.97, and it decreased to 1.7 ± 1.27 at the 6-month mark (Sahoo P K et al.) [15]. Similarly, Shetty VD et al. reported a baseline VAS of 8.1 ± 1.32, which decreased to 1.8 ± 1.12.
The diagnostic approach of using longitudinal sonographic imaging to assess the plantar fascia involved identifying certain indicators, such as plantar fascial thickening beyond the established cut-off value of 4 mm, fusiform thickening of the plantar fascia in proximity to the calcaneal enthesis, and the presence of an abnormal fascial echo texture. There was a statistically significant reduction in plantar fascia thickness (PFT) observed during the study. The mean values for PFT at baseline, two weeks, and six weeks were 6.592 ± 0.51, 5.169 ± 0.39, and 4.076 ± 0.39, respectively. The p-value associated with this drop was 0.0001. In our study we observed a decrease in the median value of PFT over time. The baseline median PFT value was 6.7 mm, which decreased to 5.1 mm at two weeks and further decreased to 4.1 mm at the end of six weeks. This finding aligns with a previous study conducted by Deghady et al. [13]; they also reported a significant reduction in PFT from 4.9 mm to 4 mm.
In the current study, the average mean ± SD value of the foot function index (FFI) at baseline (0 weeks) was 85.494 ± 6.55. This value decreased to 49.341 ± 7.27 at two weeks and decreased to 24.235 ± 1.60 at six weeks, with a statistically significant p-value of 0.0001. The findings mentioned above correlate with the research conducted by Deghady et al. The researchers determined that the median FFI (Foot Function Index) values at baseline and after six weeks were 73 and 34.12, respectively.
The findings of this study demonstrate notable clinical and sonographic improvements compared to the initial measurements (VAS, FFI, PFT), both during the 2-week and during the 6-week follow-up period, with no observed complications. These findings of our study are in agreement with the study by El Mallah et al.; they reported that PRP injection is a promising safe line of treatment for chronic plantar fasciitis carrying no complications, effective in relieving pain and improving function [16].
In summary, a significant reduction in plantar fascia thickness, pain (VAS), and function (FFI) was seen, indicating statistical significance when evaluating these parameters in comparison to the baseline after the administration of platelet-rich plasma (PRP) in patients with plantar fasciitis (PF). This finding is consistent with previous research. However, these studies exhibited variations in sample size, assessment methods, measurement of plantar fascia thickness, preparation of platelet-rich plasma (PRP), and duration of follow-up. The average duration of the procedure was approximately 30 min, and it did not incur any financial burden for the patients.
Our study has several limitations, notably a potentially short follow-up period, the absence of a control arm for comparison with other treatment modalities, and the absence of randomization.

5. Conclusions

USG-guided PRP injection helps in the precise placement of the needle for PRP injection, ensuring relief of pain (VAS), enhancing quality of life, and decreasing plantar fascia thickness. To generate robust evidence on a larger scale, multi-centre trials with a twelve-month follow-up period are recommended to provide substantial data about the efficacy of ultrasound-guided platelet-rich plasma (PRP) injections as a viable therapy option for plantar fasciitis.

Author Contributions

Conceptualization, S.K. and V.A.; methodology, S.K., C.C. and S.S.; formal analysis, R.K.W.; investigation, S.K., C.C. and S.S.; data curation, R.K.W.; writing—original draft preparation, S.K. and C.C.; writing—review and editing, V.A. and S.S.; supervision, V.A. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Ethics Committee of Vardhman Mahavir Medical College and Safdarjung Hospital, New Delhi, India (protocol code IEC/VMMC/SJH/Thesis/2019-10/150, approved October 2019).

Informed Consent Statement

Informed consent was obtained from all subjects involved in the study. Written informed consent has been obtained from the patients to publish this paper.

Data Availability Statement

The raw data supporting the conclusions of this article will be made available by the authors on request.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Draghi, F.; Gitto, S.; Bortolotto, C.; Draghi, A.G.; Belometti, G.O. Imaging of Plantar fascia disorder: Findings on plain radiography, ultrasound and magnetic resonance imaging. Insights Imaging 2017, 8, 69–78. [Google Scholar] [PubMed]
  2. Diamond, J.B. A Literature Review of Plantar Fasciitis; Boston University: Boston, MA, USA, 2017. [Google Scholar]
  3. Lapidus, P.W.; Guidotti, F.P. Painful heel: Report of 323 Patients with painful heels. Clin. Orthop. Relat. Res. 1965, 39, 178–186. [Google Scholar] [CrossRef] [Scilit]
  4. Lourdes, R.K.; Ram, G.G. Incidence of calcaneal spur in Indian population with heel pain. Int. J. Res. Orthop. 2016, 2, 174–176. [Google Scholar] [CrossRef] [Scilit]
  5. Gautham, P.; Nuhmani, S.; Kachanathu, S.J. Plantar fasciitis—An update. Bangladesh J. Med. Sci. 2015, 14, 3–8. [Google Scholar]
  6. McNally, E.; Shetty, S. Plantar Fascia: Imaging Diagnosis and Guided Treatment. In Seminars in Musculoskeletal Radiology; Thieme Medical Publishers: New York, NY, USA, 2010; Volume 14, pp. 334–343. [Google Scholar]
  7. Covey, C.J.; Malder, M.D. Plantar fasciitis: How best to treat? J. Pract. 2013, 62, 466–467. [Google Scholar]
  8. Fitzpatrick, J.; Bulsara, M.; Zheng, M.H. The effectiveness of platelet-rich plasma in the treatment of tendinopathy: A meta-analysis of randomized controlled clinical trials. Am. J. Sports Med. 2017, 45, 226–233. [Google Scholar] [PubMed]
  9. Monto, R.R. Platelet-rich plasma and plantar fasciitis. Sports Med. Arthrosc. Rev. 2013, 21, 220–224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Alsousou, J.; Thompson, M.; Hulley, P.; Noble, A.; Willett, K. The biology of platelet-rich plasma and its application in trauma and orthopaedic surgery: A review of the literature. J. Bone Joint. Surg. Br. 2009, 91, 987–996. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Agyekum, E.K.; Ma, K. Heel pain: A systematic review. Chin. J. Traumatol. 2015, 18, 164–169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Nahin, R.L. Prevalence and Pharmaceutical Treatment of Plantar Fasciitis in United States Adults. J. Pain 2018, 19, 885–896. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Deghady, A.A.M.; Hamid, M.M.A.; Helal, A.M.H.; El-Sherif, S.M.; Latief, H.A.S.A. Platelet-Rich Plasma in treatment of plantar fasciitis: Randomized double blinded placebo control study. J. Appl. Clin. Pathol. 2019, 2, 1. [Google Scholar] [CrossRef] [Scilit]
  14. Puri, V.P.; Gaur, A.K. A comparative study of effectiveness of local injection of autologous platelet rich plasma and injection corticosteroid solution in treatment of plantar fasciitis. Int. J. Res. Orthop. 2019, 5, 335–339. [Google Scholar] [CrossRef] [Scilit]
  15. Sahoo, P.; Ujade, N.; Das, S. Effectiveness of single injection of platelet-rich plasma over corticosteroid in the treatment of plantar fasciitis—A randomized, comparative study. J. Musculoskelete. Surg. Res. 2020, 4, 187–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Mallah, R.I.; Elatter, E.A.; Zidan, H.F. Platelet-rich plasma versus dry needling of myofascial meridian trigger points in the treatment of plantar fasciitis. Egypt. Rheumatol. Rehabil. 2017, 44, 58–68. [Google Scholar] [CrossRef] [Scilit]
Figure 1. Methodology flow chart.
Japma 116 24161 g001
Figure 2. Centrifugation and PRP.
Japma 116 24161 g002
Figure 3. Needle placement.
Japma 116 24161 g003
Figure 4. Right side plantar fascia thickness.
Japma 116 24161 g004
Figure 5. Left side plantar fascia thickness.
Japma 116 24161 g005
Figure 6. VAS score.
Japma 116 24161 g006
Figure 7. Plantar fascia thickness.
Japma 116 24161 g007
Figure 8. Foot function index.
Japma 116 24161 g008
Figure 9. Pain scale FFI.
Japma 116 24161 g009
Figure 10. Disability score of FFI.
Japma 116 24161 g010
Figure 11. Activity limitation score of FFI.
Japma 116 24161 g011
Table 1. Demographic data.
CharacteristicsN = 85
Age (mean ± SD [years])43.43 ± 5.35
Sex, M/F (No.)28/57 (32.9/67.1%)
Side of foot involved (left/right) (No.)43/42 (50.6/49.4%)
VAS8.647 ± 0.55
Plantar fascia thickness (mm)6.59 ± 0.51
Foot function index85.49 ± 6.55
Pain scale score42.58 ± 3.52
Disability score31.89 ± 2.78
Activity limitation score11.44 ± 2.91
Table 2. Study outcomes over various time periods with statistical significance.
Mean ± SDVisual Analogue ScalePlantar Fascia Thickness (mm)Pain ScoreDisability ScoreActivity LimitationFoot Function Index
0 wk8.64 ± 0.556.59 ± 0.5142.58 ± 3.5231.894 ± 2.7811.44 ± 2.9185.49 ± 6.55
2 wk5.58 ± 1.135.16 ± 0.3922.78 ± 3.4819.000 ± 4.207.65 ± 1.6249.34 ± 7.27
6 wk1.21 ± 1.014.07 ± 0.399.81 ± 1.059.435 ± 1.0965.00 ± 0.0024.23 ± 1.60
p value<0.001<0.001<0.001<0.001<0.001<0.001
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.