Article

Correlation Analysis Between Hip Internal Rotation Range and Plantar Pressure During Standing And Walking

1
Graduate School, Harbin Sport University, Harbin 150008, China
2
College of Sports and Human Sciences, Harbin Sport University, Harbin 150008, China
*
Author to whom correspondence should be addressed.
These authors contributed equally to this work.
These authors also contributed equally to this work.
J. Am. Podiatr. Med. Assoc. 2026, 116(4), 24144; https://doi.org/10.7547/24-144
Submission received: 20 August 2024 / Revised: 17 January 2025 / Accepted: 28 January 2025 / Published: 14 August 2026

Abstract

Background: Different studies on football players with fifth metatarsal stress fractures have found that hip internal rotation (HIR) range of motion is significantly reduced, while lateral forefoot pressure is significantly increased; therefore, the purpose of this study was to determine whether HIR range of motion is related to lateral plantar pressure. Methods: The study included 120 college students (60 males and 60 females). HIR was measured using a smartphone inclinometer app in the prone position and a compass app in the supine position. Plantar pressure was assessed using the Gaitview® AFA-50 system during standing and walking. Correlation analysis was performed using SPSS 27.0. Results: Among all subjects, HIR activity in the prone position was significantly negatively correlated with standing second through fourth metatarsophalangeal joints (MTPJ2–4), fifth metatarsophalangeal joint (MTPJ5), and midfoot (MF) pressures, and significantly positively correlated with standing first toe (T1) pressure. During walking, there is a significant negative correlation between HIR in the prone position and MTPJ2–4, MTPJ5, MF, and lateral heel (LH). Similarly, in the supine position, HIR is significantly negatively corelated with MTPJ2–4, MTPJ5, MF, medial heel (MH), and LH. Conclusions: There is a significant negative correlation between HIR and lateral plantar pressure, indicating that reduced HIR is associated with increased lateral plantar pressure. Improving HIR through targeted rehabilitation may reduce lateral plantar pressure, offering new approaches for non-surgical treatment of little toe capsulitis and reducing the risk of fifth metatarsal stress fractures.

1. Introduction

The hip joint is a ball-and-socket joint formed by the femoral head and acetabulum and has a wide range of motion. Hip range of motion is an important clinical parameter for identifying hip problems and monitoring progression after clinical treatment [1,2,3,4,5,6]. During physical examination, six common hip motions are typically assessed in three planes: flexion, extension, abduction, adduction, internal rotation, and external rotation. Among them, reduced hip internal rotation (HIR) range of motion has been associated with fifth metatarsal stress fracture [2], shin splints [3], anterior cruciate ligament injury [4], hip impingement syndrome [1,5] and non-specific low back pain [5]. The normal value of passive HIR activity is 45° [7], although some studies have defined it as 35° [8]. Cook classified HIR activity below 30° as dysfunction [9]. According to the Joint-by-Joint Approach [9], insufficient flexibility of the hip joint induces compensation from adjacent joints, which increases the risk of injuries to the lumbar spine, knee joints, and ankles.
Patients with foot diseases such as tailor’s bunion and fifth metatarsal stress fractures have significantly increased lateral plantar pressure [10,11], and A study has shown that patients with fifth metatarsal stress fractures have reduced HIR activity [2]. However, HIR activity can be modified [12,13,14,15]. To improve lateral plantar pressure by increasing HIR activity, whether the reduction in HIR activity is related to increased lateral plantar pressure must be clarified. Therefore, this study measured and analyzed the HIR activity and plantar pressure of college students to explain the relationship between hip internal rotation activity and plantar pressure.

2. Method

2.1. Design

We followed the methodological framework for developing reporting guidelines recommended by the Enhancing the QUAlity and Transparency Of health Research (EQUATOR) Network (http://www.equator-network.org). The CERT was registered on the Equator Network as a reporting guideline under development.

2.2. Participants—Selection and Recruitment

In total, 120 healthy college students were enrolled in this study, including 240 hip joints and 240 feet: 60 males and 60 females. The basic information of the subjects is shown in (Table 1). In this study, all of the participants were informed verbally and in writing about the purpose, nature, and procedures of the study. The experimental protocol was approved by the Ethics Committee (2024001). Our study was conducted in accordance with the principles of the Declaration of Helsinki. All of the subjects were informed of the experimental procedures and signed written informed consent one day before testing.
The data collection time was from December 2023 to January 2024. The inclusion criteria were as follows: ① college student; ② age 18–26 years; ③ ability to walk independently and smoothly in daily life without movement limitations. The exclusion criteria were as follows: ① lower limb fracture; ② self-reported pregnancy; ③ paralysis.

2.3. Joint Range of Motion Measurement

This study used an iPhone X smartphone with an iOS 16.1 operating system, an XW-W01 phone holder, a treatment bed, the “Bubble Level and Clinometer” smartphone application (Peter Breitling) [16,17], and a compass application (Apple, United States) [16,18] to assess HIR range of motion. To ensure the accuracy of the data, the examiner was a rehabilitation therapist with professional qualification certificates and clinical experience. The examiner passively internally rotated the participant’s hip joint until the end point was reached. Each operation and related measurements were repeated 3 times, and the average was taken. The end point of each measurement was defined by detection of a firm end feel [19] or observation of compensatory movements of the pelvis and/or trunk.
Prone position: The subject was prone on the treatment bed. The posterior superior iliac spine was palpated to ensure that the pelvis had not experienced lateral tilt or rotation, and the subject’s pelvis was firmly fixed to the treatment bed with a strap. The smartphone was securely fixed at the level of the tibial tubercle and parallel to the axis of the anterior tibial crest using the smartphone armband. The knee joint of the test leg was flexed at 90 degrees, and the non-test leg was placed flat on the treatment bed. The examiner held the subject’s ankle with one hand and fixed the subject’s pelvis with the other hand to rotate the hip joint inward (Figure 1). The angle difference between the starting position and the ending position was recorded by the Clinometer mobile app, which represented the internal rotation angle of the hip joint.
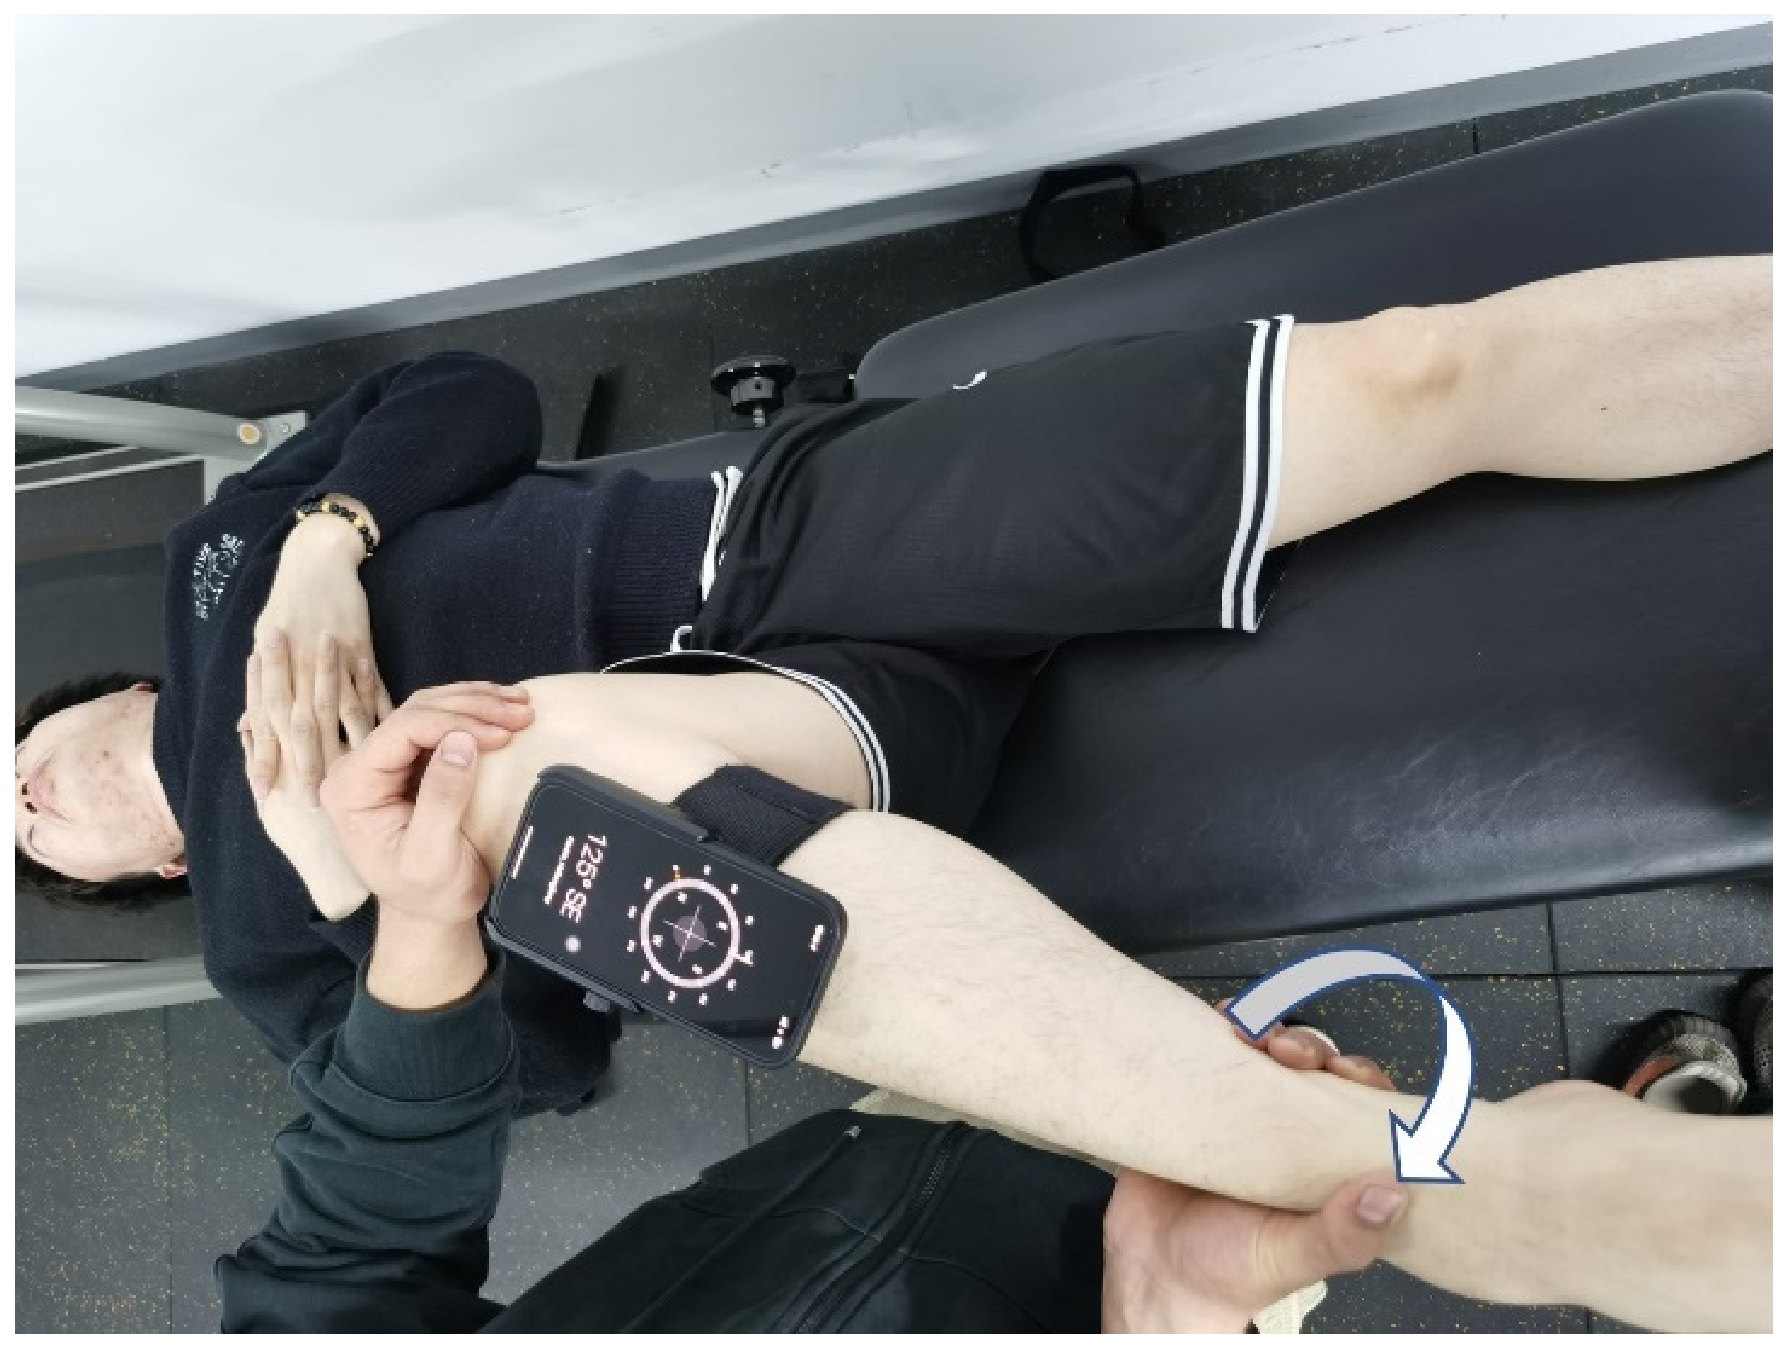
Supine position: The subject was supine on the treatment bed. The anterior superior iliac spine was palpated to ensure that the pelvis had not experienced lateral tilt or rotation, and the smartphone was securely fixed at the level of the tibial tubercle and parallel to the axis of the anterior tibial crest using the smartphone arm strap. The subject’s hips and knees were measured with passive flexion at 90 degrees. The examiner held the participant’s right ankle with one hand, fixed the participant’s right knee with the other hand, and rotated the hip joint inward (Figure 2). The angle difference between the starting position and the ending position, which represented the internal rotation angle of the hip joint, was recorded via the compass mobile app.

2.4. Plantar Pressure Measurement

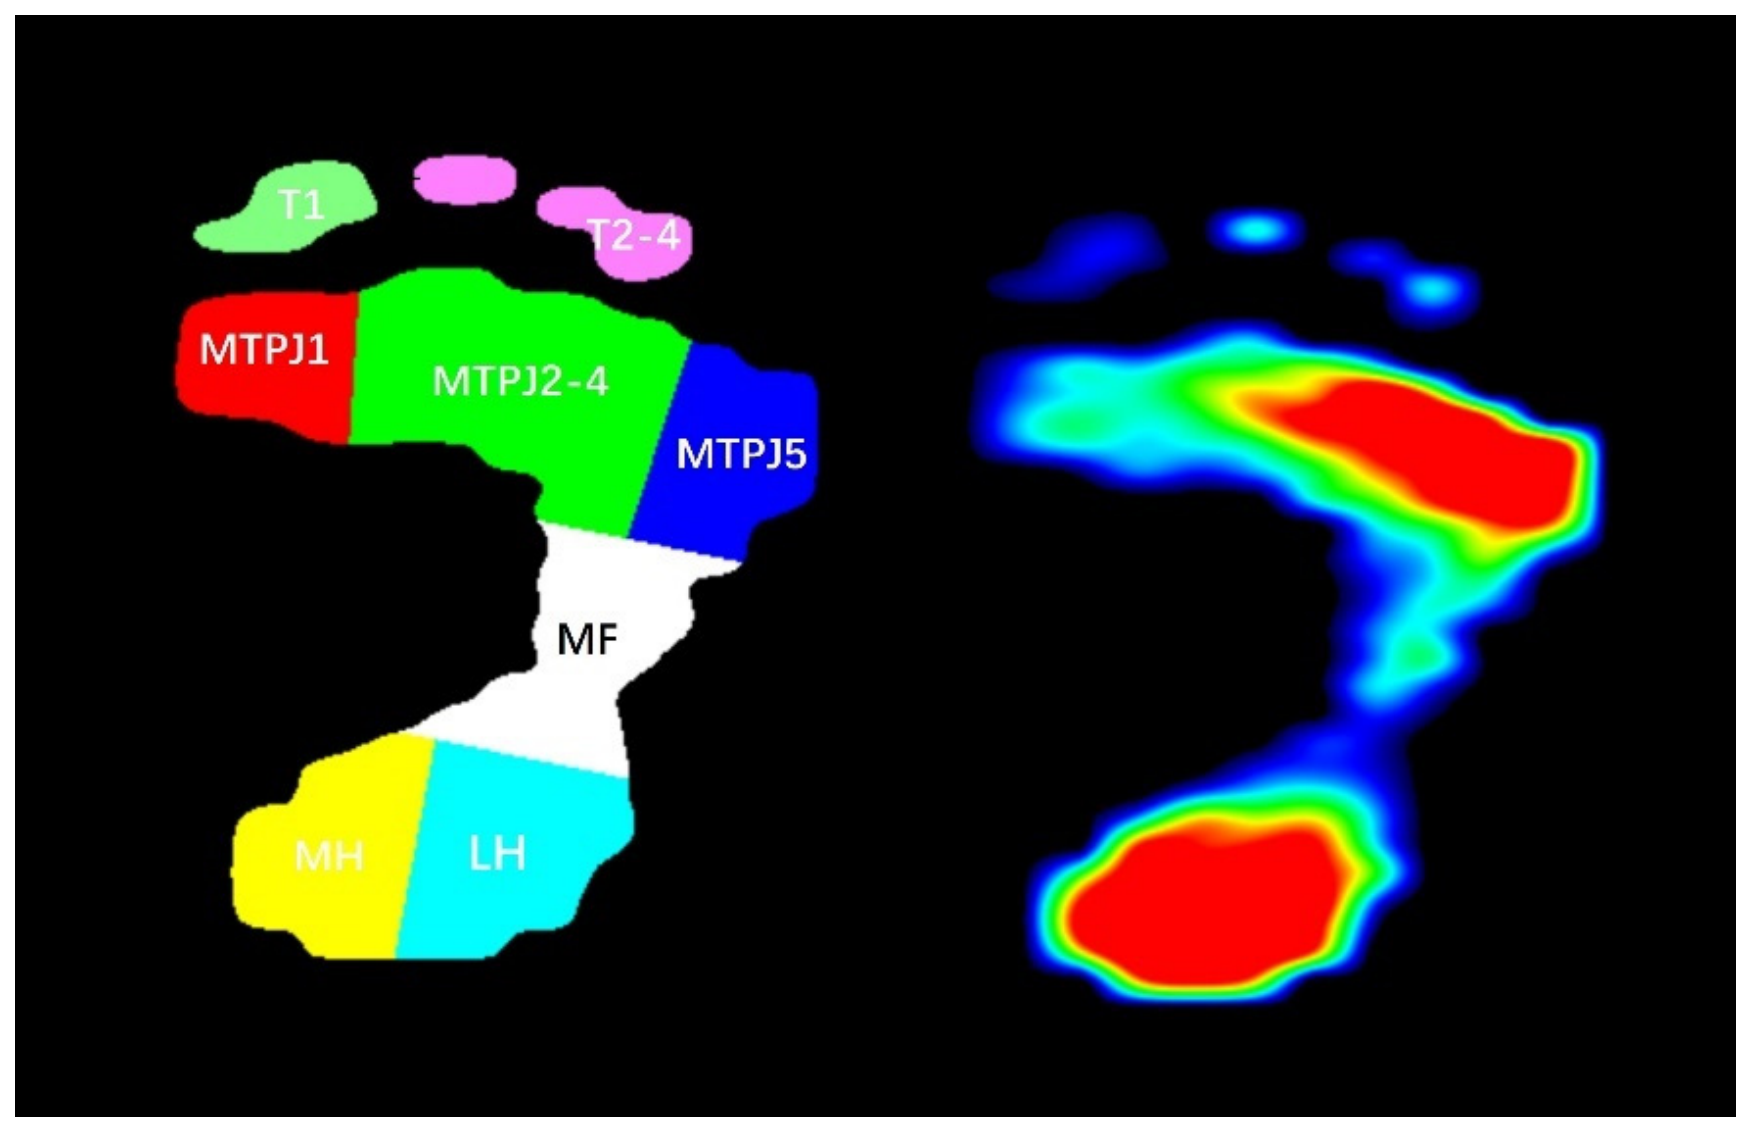
In this study, subjects were evaluated for plantar pressure while standing and walking using the Gaitview® AFA-50 system (alFOOTs, Republic of Korea) [20]. The system includes an effective area of 410 mm × 410 mm × 3 mm containing 2304 (48 × 48) force-sensitive resistor sensors, and the sampling rate is 17 Hz. The specific method for collecting plantar pressure in the standing position: the subject was barefoot, with both feet naturally standing above the plantar pressure collection plate, eyes looking straight ahead, arms hanging down naturally, and keeping the body stable throughout the process. The test time was 10 s, and the system automatically recorded the relevant plantar pressure indicator. The specific method for collecting plantar pressure during walking: The subject was instructed to choose a starting position and walk at their own comfortable pace and step length and then to step on the pressure plate when taking the second step. During the test, the subjects were all barefoot and walking with their eyes looking straight ahead. Each subject walked back and forth three times to become familiar with the test process. During the formal collection of data, if the subject’s feet were not placed in the correct area, then the subject paused on the mat while walking, or the subject did not continue walking across the mat for more than two steps; subsequently, the test was excluded and rerun. After data collection, Gaitview Pro® version 2.0 was used to determine the time-integrated average pressure value (1 kPa = 1.98 kg/cm2) in eight areas of the foot. The eight areas included: first toe (T1), second through fifth toes (T2–5), first metatarsophalangeal joints (MTPJ1), second through fourth metatarsophalangeal joints (MTPJ2–4), fifth metatarsophalangeal joints (MTPJ5), midfoot (MF), medial heel (MH), and lateral heel (LH) (Figure 3).

2.5. Statistical Analysis

This study used SPSS 27.0 software for statistical analysis. Measurement data conforming to a normal distribution are expressed as ( x ¯ ± s) by Pearson correlation analysis; for data not conforming to a normal distribution, the median (M) and interquartile range (P25, P75) were determined by Spearman correlation analysis. In all analyses, P < 0.05 was considered indicative of a statistically significant difference.

3. Results

3.1. Relationship Between HIR Range of Motion in the Prone Position and Plantar Pressure in Standing Position

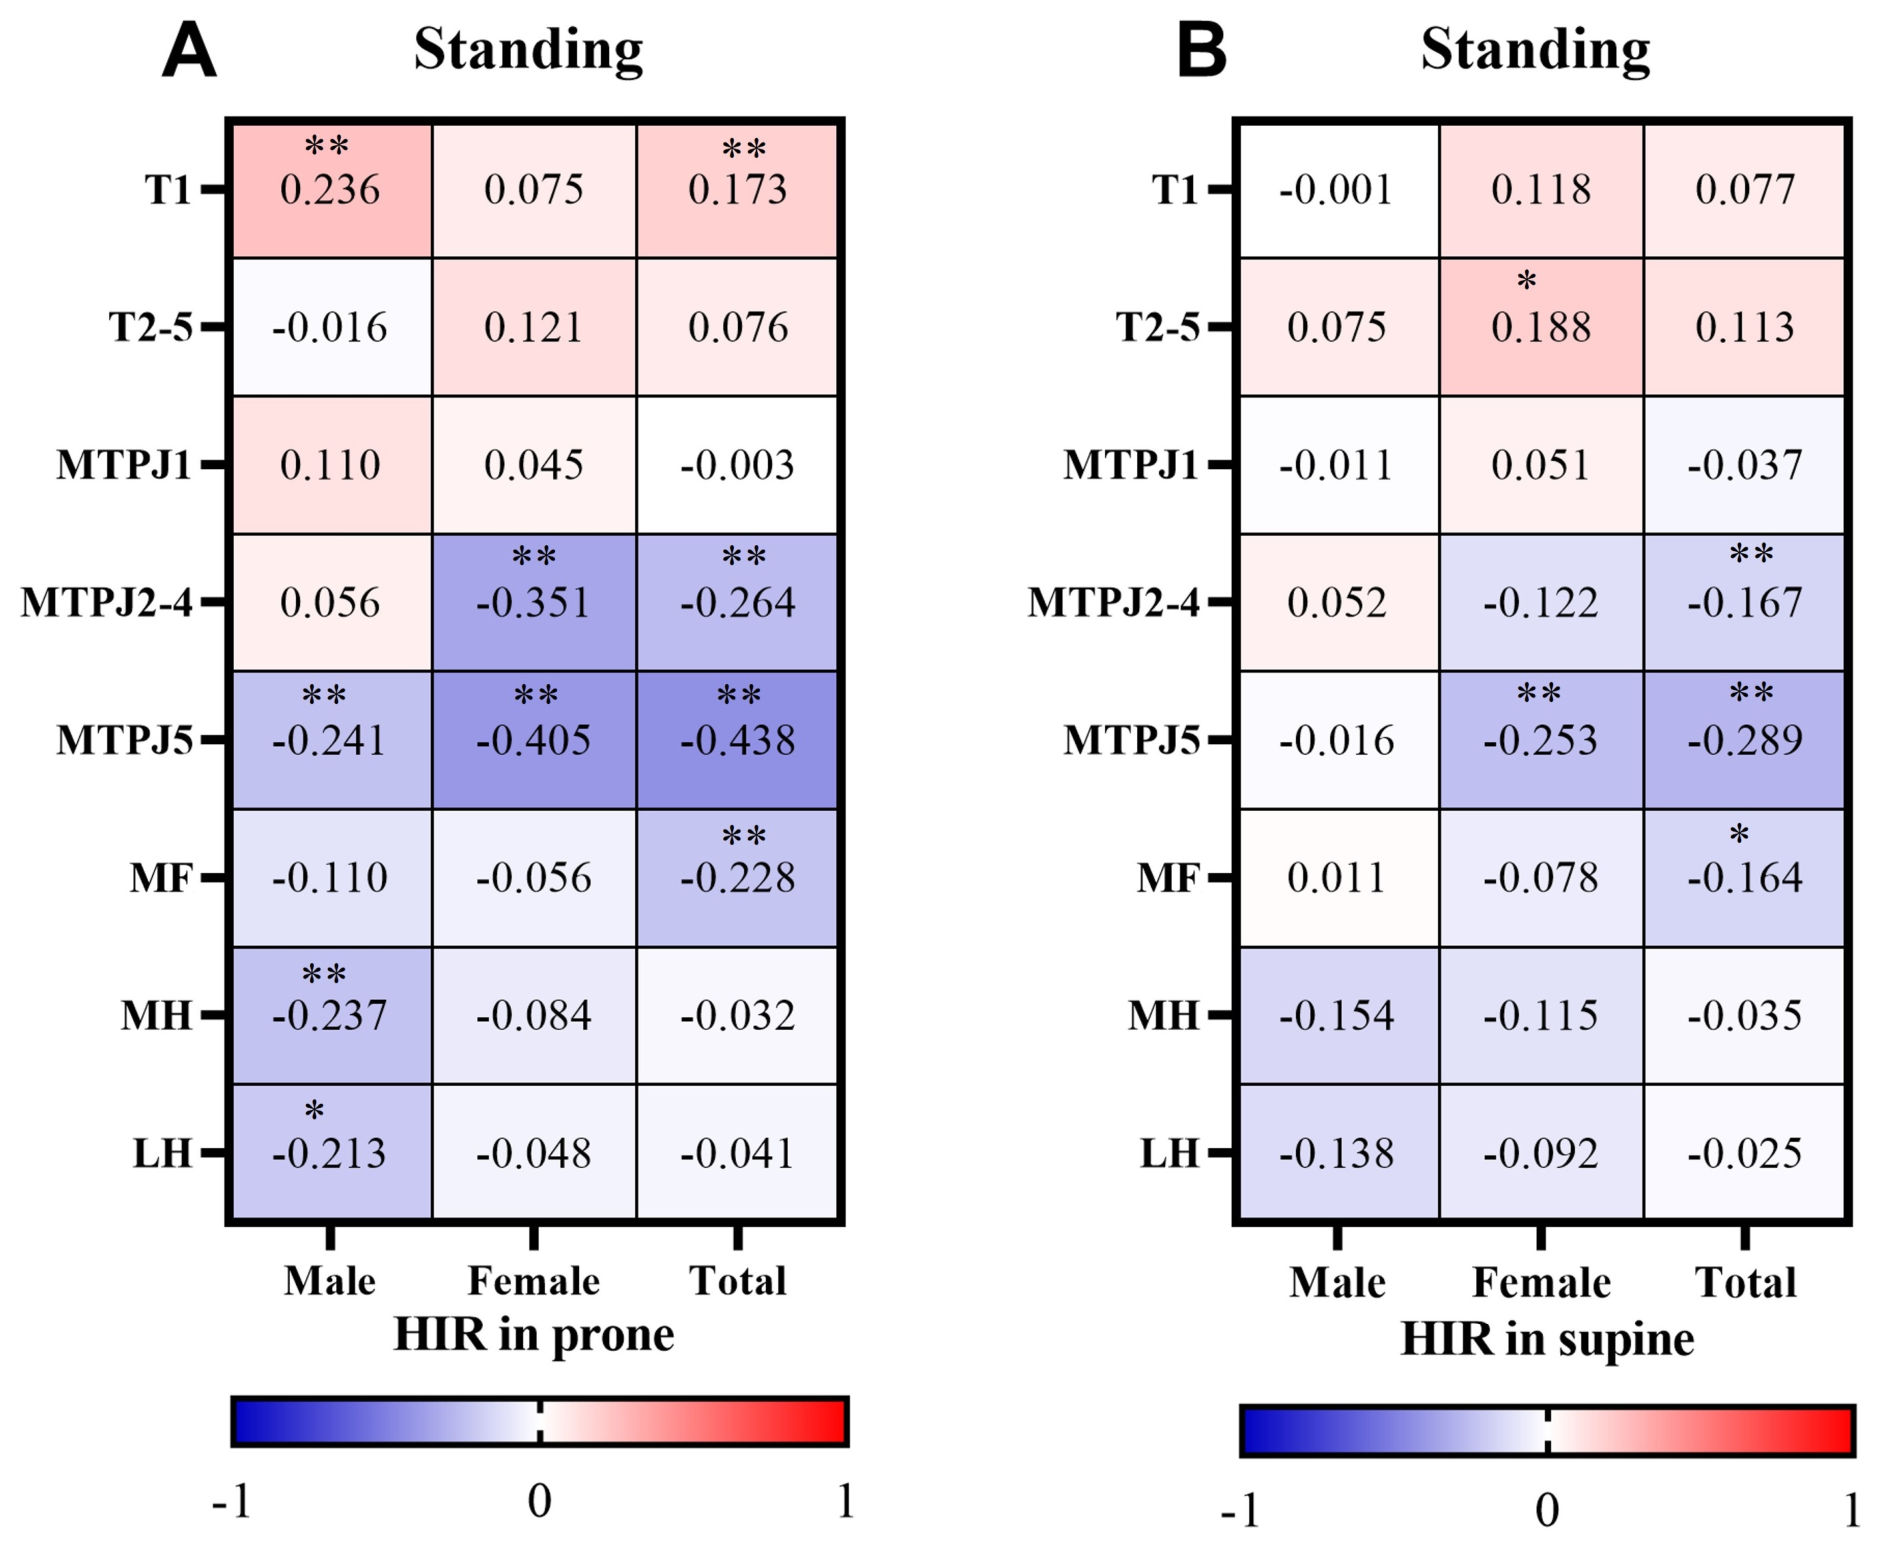
HIR activity in the prone position among men was significantly negatively correlated with MTPJ5 (r = −0.241, P < 0.01), MH (r = −0.237, P < 0.01) and LH (r = −0.213, P < 0.05) pressures in the standing position and significantly positively correlated with T1 pressure in the standing position (r = 0.236, P < 0.01). No correlations were found between HIR activity in the prone position among men and T2–5, MTPJ1, MTPJ2–4 and MF pressures in the standing position.
Significant negative correlations were found between the female prone position HIR activity and standing position MTPJ2–4 (r = −0.351, P < 0.01) and MTPJ5 (r = −0.405, P < 0.01) pressures. No correlations were noted between standing position T1, T2–5, MTPJ1, MF, MH and LH pressures.
Significant negative correlations with standing MTPJ2–4 (r = −0.264, P < 0.01), MTPJ5 (r = −0.438, P < 0.01) and MF (r = −0.228, P < 0.01) pressures were identified, and prone HIR activity was significantly positively correlated with standing T1 pressure (r = 0.173, P < 0.01). No correlations were found between prone HIR activity and standing T2–5, MTPJ1, MH and LH pressures (Figure 4A).

3.2. Relationship Between HIR Range of Motion in the Supine Position and Plantar Pressure in the Standing Position

No correlations were found between HIR range of motion in the supine position and T1, T2–5, MTPJ1, MTPJ2–4, MTPJ5, MF, MH and LH pressures in the standing position among men.
A significant negative correlation was noted between HIR activity in the supine position among women and MTPJ5 pressure in the standing position (r = −0.253, P < 0.01) and a significant positive correlation was found for T2–5 in the standing position (r = 0.188, P < 0.05). No correlations were found between HIR activity in the supine position and T1, MTPJ1, MTPJ2–4, MF, MH and LH pressures in the standing position among women.
Among all subjects, MTPJ2–4 (r = −0.167, P < 0.01), MTPJ5 (r = −0.289, P < 0.01) and MF (r = −0.164, P < 0.05) showed significant negative correlations, and no correlation was found between HIR activity in the supine position and T1, T2–5, MTPJ1, MH and LH pressures in the standing position (Figure 4B).

3.3. Relationship Between HIR Range of Motion in the Prone Position and Plantar Pressure During Walking

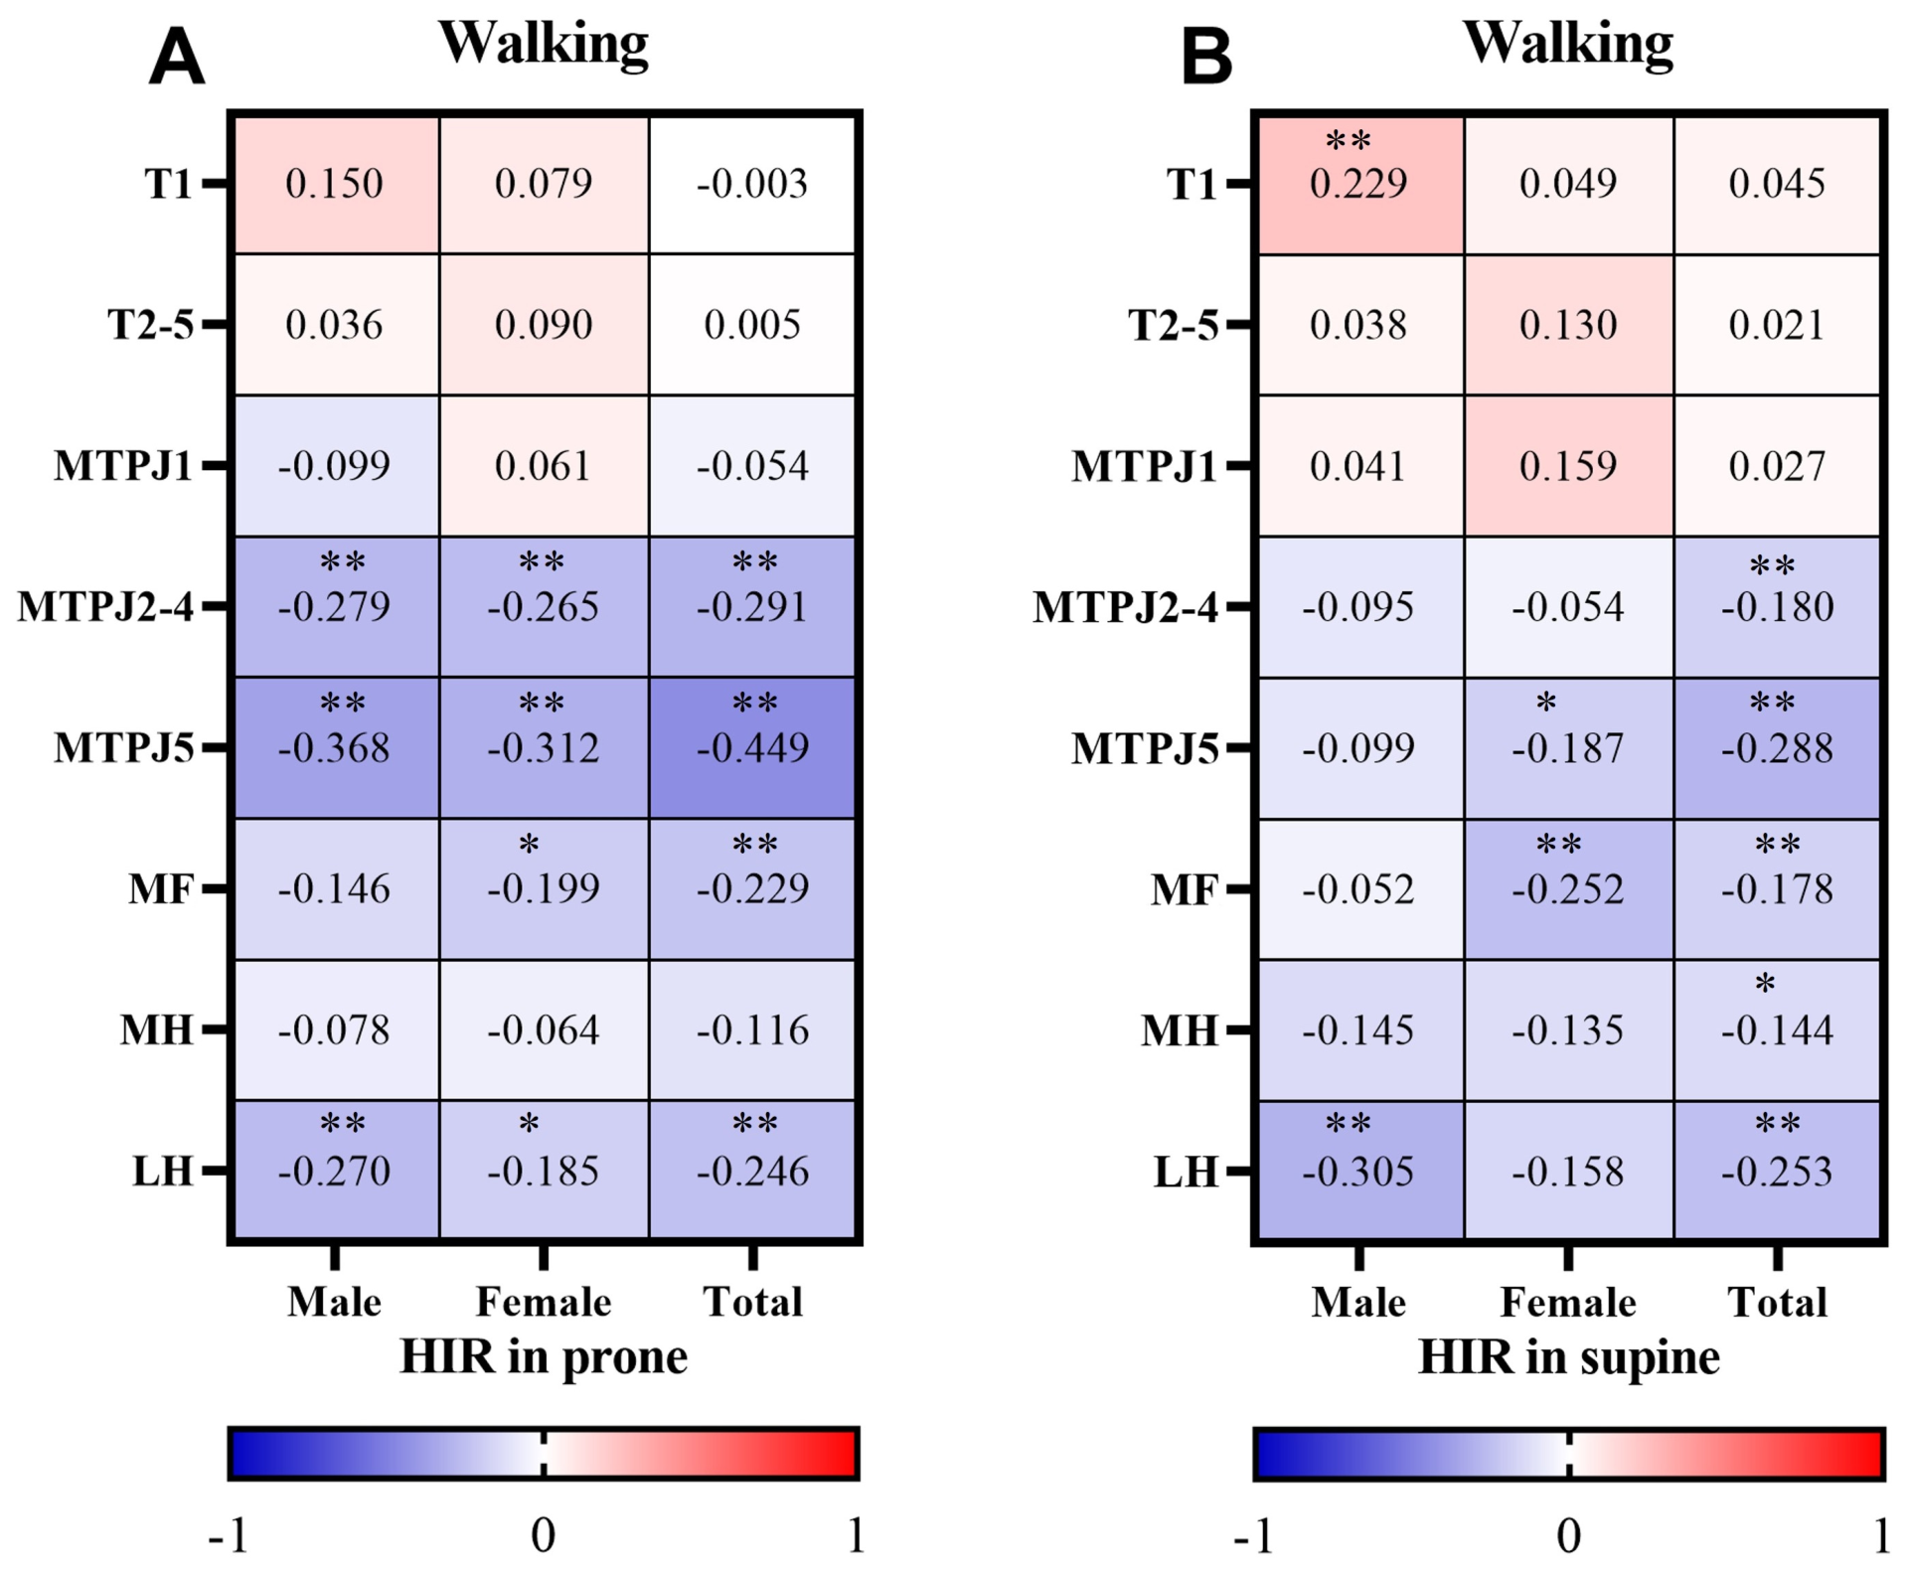
The results showed that male prone position HIR activity was related to MTPJ2–4 (r = −0.279, P < 0.01), MTPJ5 (r = −0.368, P < 0.01) and LH (r = −0.270, P < 0.01), showing significant negative correlations. No correlation was found between HIR activity in male prone position and T1, T2–5, MTPJ1, MF and MH during walking.
MTPJ2–4 (r = −0.265, P < 0.01), MTPJ5 (r = −0.312, P < 0.01), MF (r = −0.199, P < 0.05) and LH (r = −0.185, P < 0.05) while walking were significantly negatively correlated with prone HIR activity in women. There was no correlation between female prone position HIR activity and T1, T2–5, MTPJ1 and MH pressures during walking.
Among all subjects, HIR activity in the prone position was significantly negatively correlated with MTPJ2–4 (r = −0.291, P < 0.01), MTPJ5 (r = −0.449, P < 0.01), MF (r = −0.229, P < 0.01) and LH (r = −0.246, P < 0.01) while walking. There was no correlation between HIR activity in the prone position and T1, T2–5, MTPJ1 and MH during walking (Figure 5A).

3.4. Relationship Between HIR Range of Motion in the Supine Position and Plantar Pressure During Walking

Male supine HIR activity was correlated with LH during walking (r = −0.305, P < 0.01), and there was a significant positive correlation between male supine HIR activity and T1 during walking (r = 0.229, P < 0.05). There was no correlation between supine HIR activity and T2–5, MTPJ1, MTPJ2–4, MTPJ5, MF and MH during walking.
There was a significant negative correlation between the HIR activity in the supine position of women and MTPJ5 (r = −0.187, P < 0.05) and MF (r = −0.252, P < 0.01) during walking. There was no correlation between T1, T2–5, MTPJ1, MTPJ2–4, MH and LH during walking.
Among all subjects, the activity range of HIR in the supine position showed significant negative correlations with MTPJ2–4 (r = −0.180, P < 0.01), MTPJ5 (r = −0.288, P < 0.01), MF (r = −0.178, P < 0.01), MH (r = −0.144, P < 0.05) and LH (r = −0.253, P < 0.01) during walking. No correlation was found between T1, T2–5 and MTPJ1 (Figure 5B).

4. Discussion

4.1. HIR Activity Is Inversely Related to Lateral Plantar Pressure

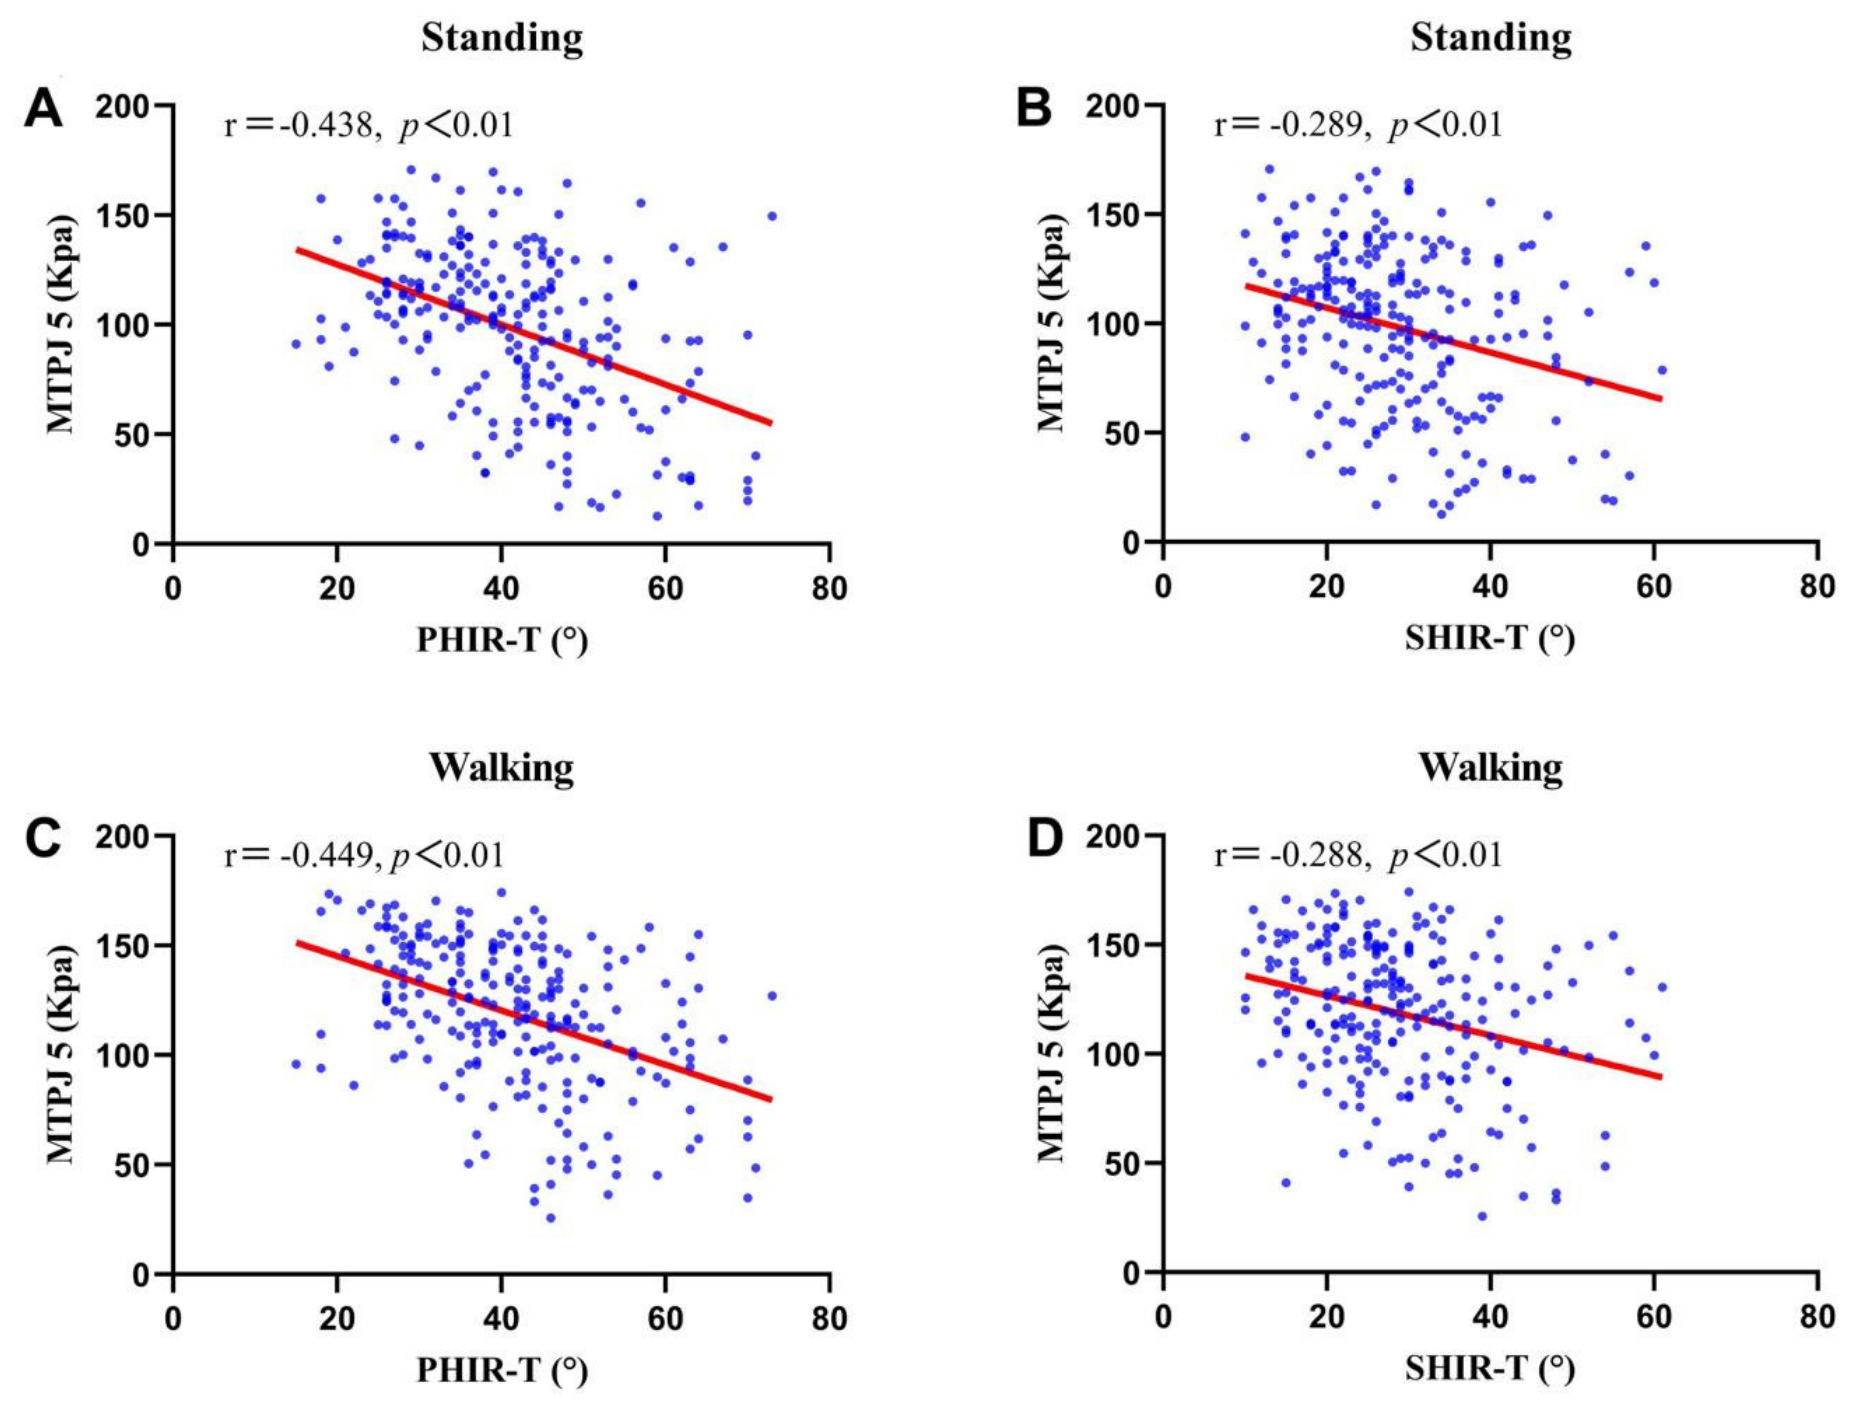
This study found that when sex was not distinguished, HIR activity was significantly negatively correlated with pressure values in the four regions of MTPJ2–4, MTPJ5, MF and LH, whether standing or walking, with MTPJ5 regions showing the highest negative correlation (Figure 6). This indicates that reduced HIR activity is related to increased pressure on the lateral plantar surface, especially in the MTPJ5 area on the lateral forefoot. In addition, there was a positive correlation between HIR and T1 in the supine position while standing, indicating that increased HIR activity may be related to increased pressure on the medial side of the foot. Regarding the lower limb kinetic chain, internal/external rotation of the hip is related to supination/pronation of the foot [21]. The typical dynamic knee valgus pattern is characterized by excessive femoral adduction and internal rotation, knee abduction, tibial internal rotation, and foot pronation [22], increasing pressure on the medial side of the foot. In contrast, limited HIR mobility results in external rotation of the femur and knee joint and supination of the foot, which increases lateral pressure on the foot.
This study found that HIR activity in the prone position was more negatively correlated with MTPJ5, MTPJ2–4, and MF than HIR activity in the supine position. Because the hip joints are in different positions in these two positions, the prone HIR range of motion test hip joint is at 0 degrees, while the supine HIR range of motion test hip joint is at 90 degrees of flexion. When the hip joint is at 90 degrees of flexion, the piriformis muscle is the internal rotator of the hip joint [8], and the influence on the mobility of the internal rotation of the hip joint is weakened [23]. In addition, the test with the hip joint at 0 degrees of flexion is closer to the biomechanics of the hip joint during standing and walking.

4.2. Interfering Factors in the Correlation Between HIR Activity and Lateral Plantar Pressure

People with reduced HIR activity may not necessarily show increased lateral plantar pressure when standing and walking. This is because the foot deviation is an important influencing factor. According to functional anatomy, when the foot deviation of people with limited HIR is large, the tension of the external rotator muscles will be reduced, which will reduce the force of the external rotator muscles to pull the femur externally, causing tibial internal rotation and foot pronation, and reducing the pressure on the lateral side of the foot. In the experiment, we also found that when the subjects with increased lateral plantar pressure reduced the foot deviation angle, the plantar pressure in the MTPJ5 area increased significantly—the reason for this was just explained. This also explains why men may compensate with a larger foot deviation angle, reducing the correlation between HIR activity and lateral plantar pressure compared to women. In addition, the ankle is also an important influencing factor of plantar pressure. For example, even if the HIR activity is reduced, the excessive pronation of the foot caused by flatness increases the pressure on the medial side of the foot instead of the MTPJ5 area [24]. Meanwhile, walking speed can also affect plantar pressure; a faster walking speed can cause plantar pressure to concentrate on the medial side of the foot [25].
People with elevated HIR activity may not necessarily show reduced lateral plantar pressure when standing and walking. The measurement position of HIR activity is an important factor. Although HIR mobility is normal in supine and prone positions, it does not mean that good HIR mobility can be maintained during standing and walking. Because standing and walking are weight-bearing positions, this can significantly reduce HIR mobility [12,26]. Walking requires good internal rotation of the hip in the extension position, so HIR range of motion may be smaller in weight-bearing and extension positions. In addition, the ankle joint can also affect plantar pressure. A laterally deviating Subtalar Joint axis, which is commonly seen in high arches, can lead to supination [27].

4.3. Practical Significance

Foot diseases associated with increased pressure on the lateral side of the plantar include fifth metatarsal stress fractures and tailor’s bunion, demonstrating their association, which may help with conservative treatment of tailor’s bunion and reduce the incidence of fifth metatarsal stress fractures. Tailor’s bunion and fifth metatarsal stress fractures have similar biomechanical characteristics, with excessive external rotation of the hip joint during soccer kicking [28] and the habit of tailors sitting with their hips in an abducted and externally rotated cross-legged position [10], leading to a decrease in the hip internal rotation range of motion [29]. Therefore, reducing excessive external rotation of the hip joint (sitting with legs crossed, sitting with legs crossed, sleeping with the hips in abducted and externally rotated positions, etc.) or relaxing and stretching the hip external rotators is beneficial for improving the HIR range of motion, which may reduce pressure on the lateral side of the plantar, help with conservative treatment of tailor’s bunion and reduce the incidence of fifth metatarsal stress fractures.

4.4. Study Limitations

This study found a correlation between HIR activity and plantar pressure but did not demonstrate causality. In future studies, limited HIR range of motion can be improved through methods such as joint mobilization and stretching [12,13,14,15], and changes in foot pressure before and after the intervention could be compared to clarify the causal relationship. Additionally, this study only measured HIR activity; future studies should consider hip external rotation activity as well as the ratio of hip internal and external rotation.
There are certain limitations in the assessment methods and equipment used in this study. The HIR activity test utilized in this research is not the optimal method. In subsequent studies, assessment tests designed to evaluate HIR activity in the hip’s posterior extension under weight-bearing positions can be developed and their validity and reliability examined. Furthermore, although the pressure plate system provides valuable information, its limitation lies in its inability to fully simulate pressure changes during actual movements. In contrast, an in-shoe pressure system can overcome this limitation and provide more comprehensive data.
It is necessary to comprehensively consider factors related to plantar pressure, not limited to the hip joint. For example, future studies should use methods such as various foot posture indexes to assess the inversion and eversion status of the foot and analyze the characteristics of plantar pressure. Additionally, walking speed, foot deviation angle, and walking load conditions should also be considered, as these factors may influence plantar pressure.

5. Conclusions

During standing and walking, the HIR range of motion was negatively correlated with pressure on the lateral side of the foot, especially in the MTPJ 5 region. Considering that the range of HIR is a modifiable factor, this finding suggests that increasing hip internal rotation range of motion can improve plantar pressure distribution, which may facilitate conservative treatment of tailor’s bunion and reduce the incidence of fifth metatarsal stress fractures.

Author Contributions

Conceptualization, Z.Y. and C.Y.; methodology, Z.Y.; software, X.Y.; validation, Z.Y., C.Y. and Z.X.; formal analysis, X.Y.; investigation, C.G.; resources, D.J. and Y.Q.; data curation, N.H.; writing—original draft preparation, Z.Y.; writing—review and editing, C.Y., Z.X. and Y.Q.; visualization, Z.X. and Y.Q.; project administration, Y.Q.; funding acquisition, Y.Q. All authors have read and agreed to the published version of the manuscript.

Funding

This research was sponsored by the Natural Science Foundation of Heilongjiang Province (Grant Number: LH2024C063).

Institutional Review Board Statement

All participants were informed verbally and in writing about the purpose, nature, and procedures of the study. Written informed consent was obtained from all participants prior to participation. The study protocol was approved by the Ethics Committee of Harbin Sport University (Approval No.: 2024001, approved on 3 January 2024). The study was conducted in accordance with the principles of the Declaration of Helsinki.

Informed Consent Statement

Informed consent was obtained from all subjects involved in the study.

Data Availability Statement

The raw data supporting the conclusions of this article will be made available by the authors on request, without undue reservation.

Acknowledgments

The authors would like to thank the Exercise Capacity Development and Evaluation Laboratory of Harbin Sport University and all of the volunteers for participating in this study.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Wong, S.E.; Cogan, C.J.; Zhang, A.L. Physical examination of the hip: Assessment of femoroacetabular impingement, labral pathology, and microinstability. Curr. Rev. Musculoskelet. Med. 2022, 15, 38–52. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Saita, Y. Range limitation in hip internal rotation and fifth metatarsal stress fractures (jones fracture) in professional football players. Knee Surg. Sports Traumatol. Arthrosc. 2018, 26, 1943–1949. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Lilletvedt, J.; Kreighbaum, E.; Phillips, R. Analysis of selected alignment of the lower extremity related to the shin splint syndrome. J. Am. Podiatr. Med. Assoc. 1979, 69, 211–217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Beaulieu, M.L.; Wojtys, E.M.; Ashton-Miller, J.A. Risk of anterior cruciate ligament fatigue failure is increased by limited internal femoral rotation during In vitro repeated pivot landings. Am. J. Sports Med. 2015, 43, 2233–2241. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Frasson, V.B.; Vaz, M.A.; Morales, A.B.; Torresan, A.; Telöken, M.A.; Gusmão, P.D.F.; Crestani, M.V.; Baroni, B.M. Hip muscle weakness and reduced joint range of motion in patients with femoroacetabular impingement syndrome: A case-control study. Braz. J. Phys. Ther. 2020, 24, 39–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Avman, M.A.; Osmotherly, P.G.; Snodgrass, S.; Rivett, D.A. Is there an association between hip range of motion and nonspecific low back pain? A systematic review. Musculoskelet. Sci. Pract. 2019, 42, 38–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Han, H.; Kubo, A.; Kurosawa, K.; Maruichi, S.; Maruyama, H. Hip rotation range of motion in sitting and prone positions in healthy Japanese adults. J. Phys. Ther. Sci. 2015, 27, 441–445. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
  8. Mansfield, P.J.; Neumann, D.A. Chapter 9—Structure and function of the hip. In Essentials of Kinesiology for the Physical Therapist Assistant; Mansfield, P.J., Ed.; Mosby: Philadelphia, PA, USA, 2019; p. 272. [Google Scholar]
  9. Cook, G.; Burton, L. Sfma assessment breakout descriptions and—flowcharts. In Movement: Functional Movement Systems; Screening, Assessment and Corrective Strategies; Cook, G., Ed.; On Target Publications: Aptos, CA, USA, 2010; p. 172. [Google Scholar]
  10. Shi, G.G.; Humayun, A.; Whalen, J.L.; Kitaoka, H.B. Management of bunionette deformity. J. Am. Acad. Orthop. Surg. 2018, 26, e396–e404. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Thomson, A.; Akenhead, R.; Whiteley, R.; D’Hooghe, P.; Van Alsenoy, K.; Bleakley, C. Fifth metatarsal stress fracture in elite male football players: An on-field analysis of plantar loading. BMJ Open Sport Exerc. Med. 2018, 4, e000377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Walsh, R.; Kinsella, S. The effects of caudal mobilisation with movement (MWM) and caudal self-mobilisation with movement (SMWM) in relation to restricted internal rotation in the hip: A randomised control pilot study. Man. Ther. 2016, 22, 9–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Beselga, C.; Neto, F.; Alburquerque-Sendín, F.; Hall, T.; Oliveira-Campelo, N. Immediate effects of hip mobilization with movement in patients with hip osteoarthritis: A randomised controlled trial. Man. Ther. 2016, 22, 80–85. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Torres, D.; Hanney, W.J.; Velazquez, L.; Pabian, P.S.; Pilkington, C. The effect of mobilization with movement and passive stretching on hip range of motion: A randomized controlled trial. Orthop. Pract. 2021, 33, 150–154. [Google Scholar]
  15. Bremner, C.B.; Girouard, T.J.; Samuel, M.N.; Turner, C.L.; Santo, A.S.; Mercer, J.A. The acute effect of hip external rotator stretches on hip internal rotation range of motion. Int. J. Exerc. Sci. 2015, 8, 75–84. [Google Scholar] [CrossRef] [Scilit]
  16. Ganokroj, P.; Sompornpanich, N.; Kerdsomnuek, P.; Vanadurongwan, B.; Lertwanich, P. Validity and reliability of smartphone applications for measurement of hip rotation, compared with three-dimensional motion analysis. BMC Musculoskelet. Disord. 2021, 22, 166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Whyte, E.; Ó Doinn, T.; Downey, M.; O’Connor, S. Reliability of a smartphone goniometric application in the measurement of hip range of motion among experienced and novice clinicians. J. Sport Rehabil. 2021, 30, 969–972. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. St-Pierre, M.O.; Sobczak, S.; Fontaine, N.; Saadé, N.; Boivin, K. Quantification and reliability of hip internal rotation and the FADIR test in supine position using a smartphone application in an asymptomatic population. J. Manip. Physiol. Ther. 2020, 43, 620–626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Clarkson, H.M. Hip. In Musculoskeletal Assessment; Clarkson, H.M., Ed.; Wolters Kluwer: Philadelphia, PA, USA, 2021; p. 867. [Google Scholar]
  20. Kim, Y.T.; Lee, J.S. Normal pressures and reliability of the gaitview® system in healthy adults. Prosthet. Orthot. Int. 2012, 36, 159–164. [Google Scholar] [CrossRef] [Scilit] [PubMed][Green Version]
  21. Duval, K.; Lam, T.; Sanderson, D. The mechanical relationship between the rearfoot, pelvis and low-back. Gait Posture 2010, 32, 637–640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Willson, J.D.; Davis, I.S. Utility of the frontal plane projection angle in females with patellofemoral pain. J. Orthop. Sports Phys. Ther. 2008, 38, 606–615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Baba, K.; Chiba, D.; Mori, Y.; Kuwahara, Y.; Kogure, A.; Sugaya, T.; Kamata, K.; Oizumi, I.; Suzuki, T.; Kurishima, H.; et al. Impacts of external rotators and the ischiofemoral ligament on preventing excessive internal hip rotation: A cadaveric study. J. Orthop. Surg. 2022, 17, 4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Buldt, A.K.; Forghany, S.; Landorf, K.B.; Levinger, P.; Murley, G.S.; Menz, H.B. Foot posture is associated with plantar pressure during gait: A comparison of normal, planus and cavus feet. Gait Posture 2018, 62, 235–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Wu, F.L.; Lung, C.W.; Wang, W.T.J.; Elliott, J.; Jain, S.; Jan, Y.K. Effects of walking speeds and durations on peak plantar pressures. J. Am. Podiatr. Med. Assoc. 2022, 112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Aefsky, B.; Fleet, N.; Myers, H.; Butler, R.J. Reliability and validity of a novel approach to measure hip rotation. J. Sport Rehabil. 2016, 25, 330–337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Simsek, D.; Yildizer, G.; Gungor, E.O.; Ors, B.S.; Harput, G. Does foot posture influence plantar pressure? South. Afr. J. Res. Sport. Phys. Educ. Recreat. 2021, 43, 111–122. [Google Scholar]
  28. De-la-Cruz-Torres, B.; Abuín-Porras, V.; Blanco-Morales, M.; De-La-Cueva-Reguera, M.; Calvo-Lobo, C.; López-López, D.; Romero-Morales, C. Acute effects of a single football training or match on passive hip rotation range of motion in semi-professional football players: A pilot study. Medicina 2020, 56, 228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Nagamoto, H.; Abe, M.; Konashi, Y.; Kimura, R.; Takahashi, M.; Oizumi, A. Rotation-related sports players demonstrate rotation-type lumbar spondylolysis fracture angle and decreased hip internal rotation range of motion. J. Orthop. 2021, 28, 101–106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
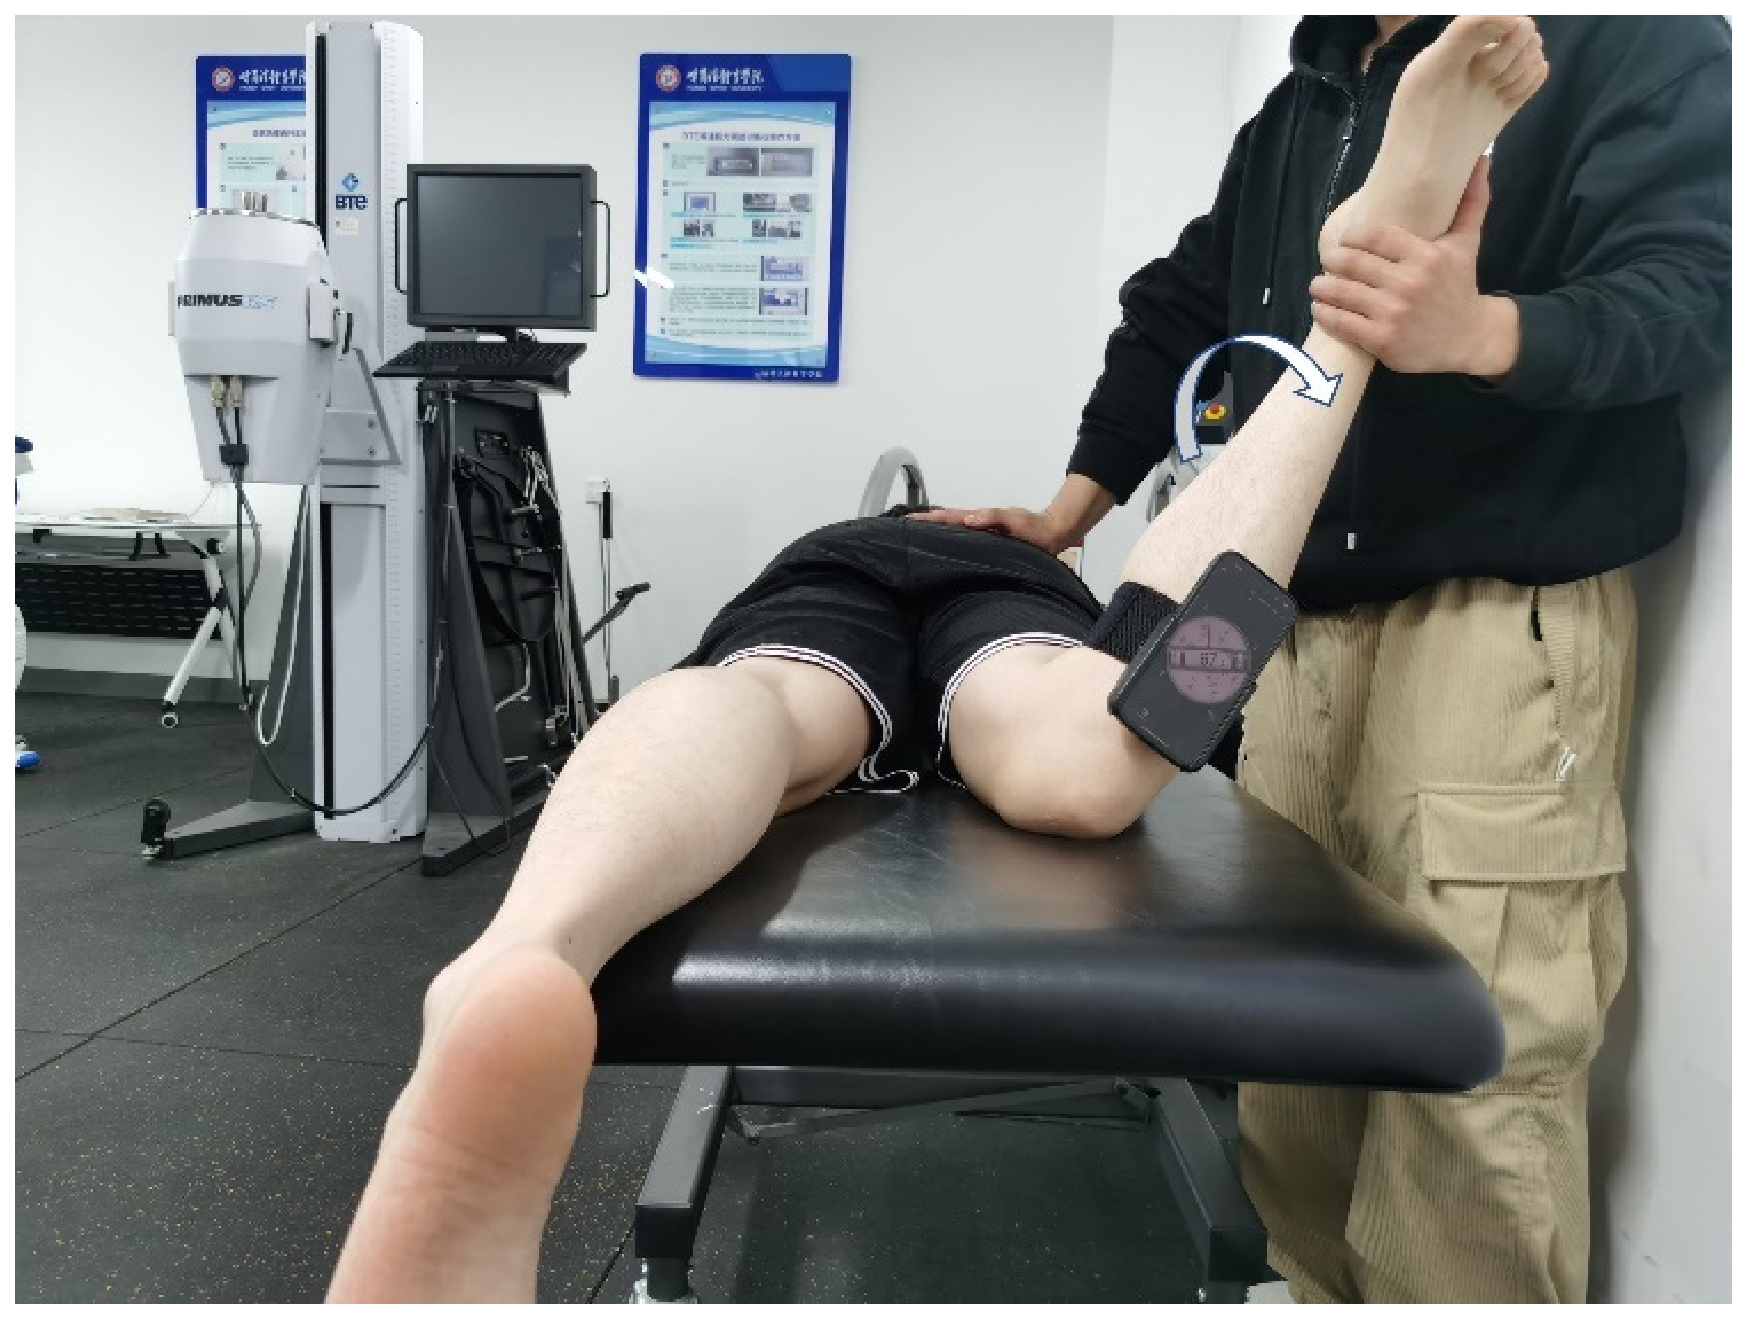
Figure 1. HIR range of motion test in the prone position.
Japma 116 24144 g001
Figure 2. HIR range of motion test in the supine position.
Japma 116 24144 g002
Figure 3. Plantar pressure zones. First toe (T1), second through fifth toes (T2–5), first metatarsophalangeal joints (MTPJ1), second through fourth metatarsophalangeal joints (MTPJ2–4), fifth metatarsophalangeal joints (MTPJ5), midfoot (MF), medial heel (MH), and lateral heel (LH).
Japma 116 24144 g003
Figure 4. Correlation analysis between hip internal rotation (HIR) range of motion and standing plantar pressure. (A) Correlation analysis between standing plantar pressure and HIR measured in the prone position. (B) Correlation analysis between standing plantar pressure and HIR measured in the supine position. Plantar pressure zone, T1 represents the 1st toe area; T2–5 represents the 2–5 toes; MTPJ1 represents the 1st metatarsophalangeal joint; MTPJ2–4 represents the 2–4 metatarsophalangeal joints; MTPJ5 represents the 5th metatarsophalangeal joint; MF represents midfoot; MH stands for medial heel; LH stands for lateral heel. * significant correlation at the 5% level, ** significant correlation at 1% level.
Japma 116 24144 g004
Figure 5. Correlation analysis between hip internal rotation (HIR) range of motion and plantar pressure during walking. (A) Correlation analysis between plantar pressure during walking and HIR measured in the prone position. (B) Correlation analysis between plantar pressure during walking and HIR measured in the supine position. Plantar pressure zone, T1 represents the 1st toe area; T2–5 represents the 2–5 toes; MTPJ1 represents the 1st metatarsophalangeal joint; MTPJ2–4 represents the 2–4 metatarsophalangeal joints; MTPJ5 represents the 5th metatarsophalangeal joint; MF represents midfoot; MH stands for medial heel; LH stands for lateral heel. * significant correlation at the 5% level, ** significant correlation at 1% level.
Japma 116 24144 g005
Figure 6. Correlation analysis between hip internal (HIR) rotation range of motion and plantar pressure in the fifth metatarsophalangeal joint (MTPJ5). (A) Correlation between MTPJ5 plantar pressure during standing and hip internal rotation range of motion measured in the prone position (PHIR-T). (B) Correlation between MTPJ5 plantar pressure during standing and hip internal rotation range of motion measured in the supine position (SHIR-T). (C) Correlation between MTPJ5 plantar pressure during walking and hip internal rotation range of motion measured in the prone position (PHIR-T). (D) Correlation between MTPJ5 plantar pressure during walking and hip internal rotation range of motion measured in the supine position (SHIR-T).
Japma 116 24144 g006
Table 1. Basic information of the subjects.
Total (n = 120)Males (n = 60)Females (n = 60)
Age20.08 ± 2.1319.78 ± 1.8420.37 ± 2.37
Height/m1.71 ± 0.091.78 ± 0.061.64 ± 0.05 **
Weight/kg63.65 ± 11.4170.87 ± 7.9856.44 ± 9.64 **
Body mass index/(kg·m−2)21.59 ± 2.7922.34 ± 2.1420.84 ± 3.16 **
Shoe size/size39.83 ± 2.5742.03 ± 1.3737.62 ± 1.24 **
*: indicates a significant correlation at the 5% level, **: indicates a significant correlation at the 1% level.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.