


Abstract
Background: Patient complaints of excessively warm or cold feet are common in medical practice. Such symptoms can be caused by underlying vascular or neurologic disease, and measurement of foot temperature during daily activity and sleep could provide a deeper understanding of their actual thermal basis. Methods: We used a Thermochron iButton to assess surface foot temperature variation and its relationship to ambient temperature during the day with activity and at night during sleep in 39 healthy individuals aged 18 to 65 years in a temperate region of the United States. We simultaneously used actigraphy to record leg movement. Results: We identified a mean ± SD awake temperature of 30.6° ± 2.6° C and asleep temperature of 34.0° ± 1.8° C, with values reaching as low as 15.9°C in the winter and as high as 37.5°C in the summer. Foot temperature was found to be independent of foot movement or sex; however, there was, as expected, a strong association between foot temperature and ambient temperature (r = .59, P < .001). Several measures of foot temperature variation demonstrated a significant or near-significant reduction with increasing age, including the Euclidean distance (r = −.38, P = .02) for awake periods and the variance (r = −.30, P = .06) during sleep. Conclusions: These results provide data on the normal variation of foot temperature in individuals living in a temperate climate and demonstrate the potential use of Thermochron iButton technology in clinical contexts, including the evaluation of patients with excessively warm or cold feet.
In podiatric medical and general medical practice, patients may occasionally voice complaints about their feet feeling excessively cold or warm. Such complaints can have a variety of causes, including vascular insufficiency [1], the presence of polyneuropathy [2], or the use of antihypertensive medications [3]. Whereas these symptoms may be acknowledged by the treating physician, they are not routinely pursued, in part owing to the lack of a straightforward approach for measuring foot temperature during normal daily activity and the absence of any associated normative data. In addition to assessing such patient complaints, a method for measuring ambulatory foot temperature could have other potential applications, including the monitoring of individuals with occupational exposure to excessively cold environments. Indeed, most clinical studies that evaluate foot temperature have focused on measurements only at discrete time points, either at home or in the clinic, where factors such as ambient temperature, body position, and clothing can be standardized. Unfortunately, this type of data provides little information regarding foot temperature variation in the real world.
For some time, we have been interested in using measures of ambulatory foot temperature as potential indicators of neuropathic disease. In 2003, Kang et al [4] reported early foot temperature data from a small group of individuals with polyneuropathy using a datalogger recording device in which a matchbook-sized device was worn at the waist and a wire lead was extended down to the dorsum of the foot and real-time temperature measurements were made and recorded. These results suggested that patients with polyneuropathy might have distinct temperature profiles from healthy individuals. More recently, dime-sized devices for temperature measurement and recording, Thermochron iButtons (Maxim Integrated Products Inc, Sunnyvale, California), have become widely available. These inexpensive devices, which similarly provide a point-based measure of temperature, can be placed on the dorsum of the foot itself and are entirely self-contained, able to measure and record temperature at frequent intervals throughout the day. Although not developed specifically for medical use and providing temperature monitoring at only one location, they have been studied by other researchers in a clinical setting [5]. Following up on this work, we [6] also reported their safety and tolerability for use on the feet. Most recently, we [7] completed a study demonstrating differences in foot thermoregulation between diabetic patients with and without polyneuropathy. In that study, we also obtained foot temperature data on a group of 39 nondiabetic control participants. Herein, we expand on that normative data, detailing the reference range and variability of surface foot temperature during wakefulness and sleep, the effect of environmental temperature extremes on foot temperature, and the impact of age. The hope is that the availability of such normative data will spur others in podiatric medicine and beyond to consider using these measurements in research and in clinical practice.
Materials and Methods
Participants
Healthy individuals without a history of neurologic disease or podiatric medical problems were recruited for this study through advertisements. Individuals were excluded if they 1) were currently smoking regularly, 2) had a medical disorder or drug therapy known to be associated with neuropathy (eg, a history of diabetes mellitus or exposure to chemotherapy for neoplastic disease), 3) had any active podiatric medical problems, or 4) had any other factors that limited physical activity or that could create artifacts such as using a cane or walker.
On the day of study, after signing the informed consent form approved by the institutional review board of Beth Israel Deaconess Medical Center, all of the patients underwent an additional brief review of their medical history, social history, and medications (if any); any individual identified as meeting at least one of the exclusion criteria was excluded.
All of the participants then underwent a standard directed neurologic examination, including assessment of distal strength and muscle bulk in the legs and feet, deep tendon reflexes at the knees and ankles, and lower-extremity sensory perception, including assessment of sharp-dull discrimination, light touch, vibration perception, and joint position sense. A standard 10-g monofilament test was also performed on both feet. The dorsalis pedis and tibialis posterior pulses were palpated. Anyone identified as having abnormal examination findings was excluded from further participation in the study. Unless the participant expressed a preference or there was a history of mild trauma or other potential confounding problems, the side to undergo long-term temperature monitoring was chosen arbitrarily.
Time of Study
Given that we were interested in assessing the variability of ambulatory foot temperature in different environments, we specifically enrolled people throughout the year. However, we also made the greatest effort to enroll people during the winter months in Boston to effectively assess the extremes of cooling on foot temperature.
Temperature Measurement
Ongoing temperature measurement was performed using Thermochron iButton temperature monitors. Initially, two different models of iButton were used: model DS1921H-F5#, with a range of 15° to 46° C and a resolution of ±0.125°C, was used to measure foot temperature and model DS1921G-F5#, with a range of −40° to 85° C and a resolution of ±0.125°C from −30° to 70° C, was used to measure ambient temperature. Later, a more accurate iButton device became available and was used to measure foot and ambient temperature because it had a wider range of function and higher accuracy (model DS1922L#F50, with a range of −40° to 85° C and a resolution of ±0.0625°C). All of the devices were preset using a computer interface, allowing for an interval and number of recordings to be made. Although the newer devices can record considerably more data points than the first, we used only data obtained every 2 min across a 32-hour period (approximately 960 points) to remain consistent with the older device data. The exact time at which measurements should commence and terminate can also be programmed into each device. The device was set to not overwrite measurements, thus stopping after all the data points are obtained.
The foot iButton was affixed to the web space between the first and second toes using medical-grade adhesive tape (3M Transpore Surgical Tape, No. 1527-1; 3M Health Care, St Paul, Minnesota) (Figure 1). The ambient iButton was affixed via a key ring apparatus to external clothing (Figure 1). Participants were instructed to keep the device attached to the foot throughout the study period except while bathing. Additional tape was supplied so that participants could reattach the device after its removal. During sleep, we requested that the ambient temperature device be placed by the bed but not worn or placed under the blankets.
Footwear
We provided all of the individuals with identical socks (Banda Men’s/Women’s No-Elastic Acrylic Crew Socks, No. 99158; FootSmart, Norcross, Georgia) and requested that during the study they wear simple, noninsulated footwear while going about their normal daily outdoor activities and indoors as well. During sleep, we requested that they continue to wear the socks.
Monitoring Foot Movement
We also monitored foot movement to determine how foot activity affected thermoregulation and as an additional marker for sleep onset and activity level during the day. We, thus, used a commercially available actigraphy monitor (Actiwatch 16, No. 198-0101-02; Mini Mitter/Respironics, Bend, Oregon). The device is loosely affixed to the ankle (Figure 1). It works by measuring movement via an accelerometer and can perform “counts” of leg movements within a certain preset period. We chose a short 15-sec period because it gave us more flexibility and we could always combine values from adjacent periods if needed later. The internal chronometer on the actigraphy device was synchronized with the two iButtons.
Diaries
In addition to wearing the measurement devices, participants were requested to maintain simple paper diaries for the entire 32-hour period. Individuals recorded the date, general activity (examples include “at work,” “sitting at desk,” “going to lunch,” “showering,” and “sleeping”), start and end time of the activity, and whether they were outside, inside, or both during the particular activity. Participants also were asked to identify the exact time that the devices were removed for bathing and replaced. Individuals were provided a digital watch synchronized with both iButtons and the actigraphy device so that all of the recorded times would be internally consistent. At completion of the study, individuals were requested to return all of the devices and the diary in a preaddressed, prepaid envelope to eliminate the need for a return visit.
Data Analysis
After downloading the data from the devices into a spreadsheet, the individual measures (foot temperature, ambient temperature, and actigraphy counts) were plotted against time. The graph was then annotated with information provided from the diary, including times of sleeping, removal of the device for bathing, and outside activity. These times were confirmed by assessing changes in actigraphy counts and on the ambient temperature monitor (eg, sleep was confirmed by the stabilization of ambient temperatures and a marked reduction in actigraphy counts).
The sleep and awake data were then analyzed separately. In sleep, because the iButton was outside the covers, the measured ambient temperature does not directly reflect the ambient temperature experienced by the foot. The sleep data were, thus, analyzed in a variety of ways that did not rely on the ambient temperature measurements, including summary statistics (mean temperature, SD, and average rate of positive and negative change per 2-min measuring interval). Summary statistics were also obtained for the awake data, but here the efforts were to determine the relationship between ambient and foot temperatures and between foot movement and foot temperature. For awake and asleep data, the relationship between these measures and participant age was also assessed. Parametric and nonparametric tests were used where appropriate, and, for simplicity, all relationships sought were assumed to be linear. Data processing was performed with Matlab (The Math-Works Inc, Natick, Massachusetts) and SPSS (SPSS Inc, Chicago, Illinois).
Results
Forty-six healthy individuals were enrolled in this study. Four individuals were excluded during screening; in another, the device malfunctioned, and only minimal data were recorded; another individual did not have an examination completed (owing to an error in scheduling the appointment); and another did not return the devices, leaving a total of 39 individuals (19 men and 20 women; mean age, 43 years; age range, 18–65 years) on whom a complete data set was obtained. The technique was well tolerated, with no complaints of foot irritation or other problems. Ten participants were studied in the spring (March 21–June 20), seven in the summer (June 21–September 20), four in the fall (September 21–December 20), and 18 in the winter (December 21–March 20).
Temporal Presentation of Data
Figure 2 shows a typical recording from a 53-year-old woman. In addition to foot and ambient temperatures, the bottom points show the actigraphy data as a series of counts per minute. These temperature measurements were made in early March. The sleep periods are easily identified by a relatively stable foot temperature and near-steady ambient temperature. In addition, foot movement activity dropped dramatically during sleep, as was anticipated.
Summary Measures
Table 1 provides the basic summary data for the 39 participants separated into awake and asleep measurements. No relationship between foot temperature and sex was identified (r = .032, P = .93). Without removing ambient temperature, foot temperature and foot movement were very strongly correlated (r = .59, P < .001). However, with ambient temperature as a covariate, there was no significant relationship between foot movement and foot temperature (r = .20, P = .23). On the other hand, foot temperature was strongly correlated with ambient temperature, controlling for age and movement (r = .59, P < .001). A moderate association between awake and asleep foot temperature for each individual was also identified (r = .39, P = .02). This relationship became slightly stronger when controlling for age and mean ambient temperature (r = .42, P < .001).
Temperature Extremes
The mean minimum ambient temperature experienced was 12.1°C, with the lowest for any individual reaching −4.5°C. The mean of the lowest foot temperatures recorded during outdoor activity was 23.5°C, with the lowest value for any individual being 15.9°C (occurring at the same time as the −4.5°C reading noted for ambient temperature). The mean maximum ambient temperature experienced was 33.9°C, with the highest for any individual reaching 40.0°C. The mean of the highest foot temperatures recorded during outdoor activity was 35.5°C, with the highest value for any individual being 37.5°C.
Relationship of Foot Temperature with Age
Awake.
A significant direct relationship between awake foot temperature and age was identified (r = .39, P = .01), but this did not hold when ambient temperature and foot movement were used as covariates (r = .26, P = .11). One possible explanation for this finding is that older participants are less likely to perform sustained outdoor activities in colder weather. Accordingly, other measures were sought that would be less subject to variation based on the type of ambient exposure. One metric is the Euclidean distance, a measurement that can be used for capturing the actual difference or “distance” between the points in two time series. A weak inverse trend (r =−.27, P = .10) was noted in the Euclidean distance between foot and ambient trace and age. When ambient and foot temperatures were normalized to fluctuate around the same mean value, thus removing any constant offset effects in the distance measurement, Euclidean distance between the two traces showed a stronger and significant inverse correlation with age (r = −.38, P = .02). This suggests that younger individuals experience greater variation in foot temperatures due to homeostatic mechanisms, whereas older individuals experience variation induced by ambient temperature effects. A second measure of variance was determined by analyzing histograms of the derivatives of the foot and ambient traces. A wider histogram suggests greater variance. The width of each histogram was defined as the width of the histogram encompassing 95% of the temperature data. Using this measure, there was again a significant reduction in variability with age (r = −.37, P = .04). Although this could be attributed in part to the effect of variance in ambient temperature on that of foot temperature, no significant relationship was found between age and ambient temperature variance itself (r = −.246, P = .13).
Asleep.
No significant relationship between age and mean asleep foot temperature was identified (r = .23, P = .16). However, a moderate inverse relationship between the SD of the foot temperature and age during sleep was found (r = −.45, P = .005), suggesting that foot temperature becomes less variable with increasing age. Similarly, an inverse relationship was identified between positive rate of change (ie, warming) and age (r = −.54, P = .001); likewise, an inverse relationship between negative rate of change (cooling) and age (r = −.367, P = .03) was also found. This finding of decreased variability with increasing age was supported by a trend in the variance computed by histogram analysis (r = −.30, P = .06).
Discussion
Using Thermochron iButton technology, we documented the normal variation of foot temperature in a variety of environments during daily activity and during sleep. These results demonstrate that foot temperature can vary considerably during the day and that it can reach relatively low values in cold environmental conditions. Although the participants in this study were not equipped with any specific insulation, foot temperature in the winter months was commonly observed below 25°C and as low as 15.9°C. Of interest is the fact that foot temperature did not seem to rely substantially on foot activity and that there was apparently a tendency for people to have peripheral thermoregulation set slightly differently, with some individuals having warmer feet during the day and at night.
Perhaps the most interesting effects were those associated with age. As with most other biological parameters, such as heart rate, the inherent variation and complexity of the physiologic signal decreases with increasing age [8]. Although we intentionally avoided studying a very old cohort of individuals, these effects in this group of people aged only up to 65 years were evident during sleep, when variation due to changes in ambient exposure should be at a minimum, but also in some of the awake data analyses.
To date, there has been relatively little study of the daily variation in normal foot temperature and its relationship with ambient temperature. Our interest in this stems from a basic hypothesis that foot thermoregulation will be impaired in diseases such as polyneuropathy and venous stasis [9,10] Indeed, older and more recent works [4,7] suggest this to be the case. Despite many studies evaluating foot temperature or thermography in different clinical contexts, almost all of this work was performed in a laboratory setting or by patients at home using single measurements at discrete time points. One such study [11] has demonstrated the value of intermittent temperature measurements to help in the early identification of foot ulcerations in diabetes. Another obvious difference between the technique presented herein and more standard approaches, such as thermography, is that the present method is point based, providing data from only one small region of the foot. Given the small size of the iButton, it would be possible to place several on the foot to obtain a more complete assessment of real-time foot temperature, if desired.
Several limitations of this study should be noted. First, the diaries that were kept were limited to the basic daily activities and provided only modest information, and it is likely that the recorded times were not always accurate. For example, sleep onset could be established only by a reduction in actigraphy counts in conjunction with patients’ recording of their bedtime in the diary, although actigraphy by itself has been shown to be accurate in this regard [12]. Second, the iButton device, although a well-crafted and accurate device [5], has limitations. It can retain only so much data, and we chose to record at 2-min intervals because this would provide us with sufficiently frequent measurements to record changes in temperature and yet still allow for approximately 32 hours of recording. Obviously, one could choose to study shorter periods with more frequent measurement intervals. Third, we did not obtain data from the contralateral extremity. Although we considered this idea, the main goal of this study was to assess normal fluctuations in foot temperature and their relationship with ambient temperature and not to identify between-foot differences in temperature.
Another important limitation of this study is that we evaluated the temperature on the dorsum of the foot rather than on the plantar surface because the iButton fits neatly into the web space between digits 1 and 2 and, we believed, would least likely injure the surrounding tissues while the patient performed normal daily activities. However, measuring plantar surfaces may be especially valuable because skin breakdown in this region, especially in diabetes, can produce changes in foot temperature before an ulcer actually forms [11]. For iButtons to be applied successfully to the plantar surface, however, they would probably need to be effectively embedded in the sock or the insole of the shoe rather than simply being placed on the skin, where they could lead to additional injury.
The approach to measurement and data analysis used herein may be helpful in the clinical care and research of individuals who present to medical providers with the primary complaint of excessively cold or warm feet to determine whether these complaints can be tied to a measurable physical parameter. Ultimately, with further study, it is possible that foot temperature measurement and analysis using Thermochron iButton technology will provide a simple tool that will answer a variety of interesting and useful clinical and research questions relevant to podiatric medical care.

Table 1.
Summary of Foot Temperature Data for All 39 of the Study Participants.
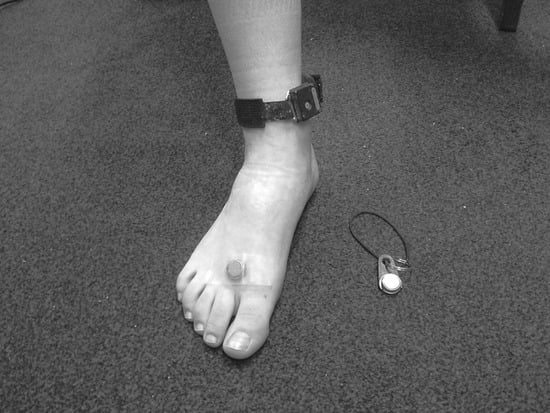
Figure 1.
Setup for foot temperature monitoring. The Thermochron iButton is attached to the foot in the web space between digits 1 and 2. The actigraphy monitor is attached to the ankle. To the right is the ambient temperature monitor on a key chain clip, which allows it to be affixed easily to external clothing or to an elastic band around the wrist.
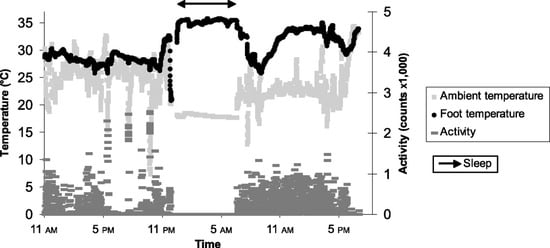
Figure 2.
Example of foot temperature, ambient temperature, and actigraphy count data obtained from a healthy 53-year-old woman in a 32-hour period. Note the near cessation of foot movement during sleep. Participants were asked to remove the ambient temperature monitor during sleep and to place it by the bedside.
Acknowledgment
Theophano Mitsa, PhD, Ary Goldberger, MD, Madelena Costa, PhD, and Caterina Stamoulis, PhD, for the helpful discussions about data analysis.
Financial Disclosure
This work was funded, in part, by grant R21-DK071178 from the National Institutes of Health.
Conflict of Interest
None reported.
References
- Stoffers HE, Kester AD, Kaiser V, et al: Diagnostic value of signs and symptoms associated with peripheral arterial occlusive disease seen in general practice: a multivariable approach. Med Decis Making17:61, 1997.
- Gorson KC, Ropper AH: Idiopathic distal small fiber neuropathy. Acta Neurol Scand92:376, 1995.
- Feleke E, Lyngstam O, Rastam L, et al: Complaints of cold extremities among patients on antihypertensive treatment. Acta Med Scand213:381, 1983.
- Kang P, Hoffman S, Krismitsos E, et al: Ambulatory foot temperature measurement: a new technique in polyneuropathy evaluation. Muscle Nerve27:737, 2003.
- van Marken Lichtenbelt WD, Daanen HA, Wouters L, et al: Evaluation of wireless determination of skin temperature using iButtons. Physiol Behav88:489, 2006.
- Rutkove SB, Nie R, Mitsa T, et al: A methodology for the real-time measurement of distal extremity temperature. Physiol Meas28:1421, 2007.
- Rutkove SB, Veves A, Mitsa T, et al: Impaired distal thermoregulation in diabetes and diabetic polyneuropathy. Diabetes Care32:671, 2009.
- Ziegler D, Piolot R, Strassburger K, et al: Normal ranges and reproducibility of statistical, geometric, frequency domain, and non-linear measures of 24-hour heart rate variability. Horm Metab Res31:672, 1999.
- Bharara M, Cobb JE, Claremont DJ: Thermography and thermometry in the neuropathic assessment of the diabetic foot: a case for furthering the role of thermal technique. Int J Low Extrem Wounds5:250, 2006.
- Kelechi TJ, Michel Y: A descriptive study of skin temperature, tissue perfusion, and tissue oxygen in patients with chronic venous disease. Biol Res Nurs9:70, 2008.
- Lavery LA, Higgins KR, Lanctot DR, et al: Home monitoring of foot skin temperatures to prevent ulceration. Diabetes Care27:2642, 2004.
- Lichstein KL, Stone KC, Donaldson J, et al: Actigraphy validation with insomnia. Sleep29:232, 2006.
© 2010 American Podiatric Medical Association