


Simple Summary
Life after cancer brings ongoing challenges related to nutrition, wellbeing, and long-term health. Many people living with and beyond cancer find it difficult to follow recommended healthy eating habits and need practical, supportive dietary guidance. Culinary nutrition interventions may offer a useful solution, as they combine nutrition knowledge with hands-on cooking skills, sensory experiences, behaviour change strategies, and social support. Previous studies suggest that cooking skill interventions can improve food literacy, build confidence around food choices, reduce food-related anxiety, and strengthen social connections and family involvement. This review examined the current scientific literature to assess the effects of culinary nutrition interventions on health-related outcomes for people living with and beyond cancer, as well as for their support networks. Overall, the findings show that these interventions, whether delivered alone or combined with physical activity or mental health components, are generally beneficial. Improvements were seen across most outcome areas, particularly those valued by the cancer community, such as dietary intake and quality of life. Although the exact size of these effects cannot be determined, this review highlights their potential and identifies priorities for future research.
Abstract
People living with and beyond cancer often face ongoing challenges related to nutrition, wellbeing, and long-term health. Many individuals express a need for evidence-based, tailored dietary support, yet practical approaches to sustaining healthy eating behaviours remain limited. Culinary nutrition interventions, which integrate nutrition education with hands-on culinary skills, may help address these needs; however, their effects have not been systematically synthesised. This systematic review evaluates the impact of culinary nutrition interventions, delivered alone or in combination with physical activity or mental health components, on dietary intake, psychosocial and health-related outcomes, anthropometric measures, clinical and metabolic markers, and feasibility among individuals living with or beyond cancer. Following PRISMA guidelines, 18 studies were identified across PubMed, Scopus, EMBASE, CINAHL, and Web of Science (last searched in April 2025) and narratively synthesised. A total of 1173 participants were included, with sample sizes ranging from 4 to 190 participants per intervention. Interventions were well received and rated as highly acceptable, with strong engagement and minimal adverse effects. Across studies, statistically significant improvements were reported in dietary intake (7/13 studies), quality of life (4/5), mental health (5/6), self-efficacy (2/3), symptom management (3/4), self-reported cognitive health (1/1), food-related behaviours (2/2), selected anthropometric measures (4/8), and selected metabolic biomarkers (4/6). The evidence suggests that culinary nutrition interventions hold promise as supportive, behaviour-focused strategies aligned with oncology nutrition guidelines and responsive to patient needs. However, due to heterogeneity across interventions and outcomes, and variability in methodological quality as assessed using the Cochrane risk of bias tool, quantification of effects was not possible, limiting interpretation of the evidence. Further high-quality studies using comparable outcome measures and longer-term follow-up are needed to quantify the magnitude of effects, assess their durability over time, and inform the integration of culinary nutrition programmes into cancer care. This systematic review is registered under the PROSPERO ID CRD42024567041 and was funded by the RCSI Research Summer School Fund.
1. Introduction
Global cancer rates are increasing, with an estimated 10 million cancer deaths in 2022 [1,2], though advances in screening and treatment have led to better survival rates [3]. According to the World Health Organisation (WHO) and the International Agency for Research on Cancer (IARC), there were approximately 53.5 million people worldwide who were alive within five years of a cancer diagnosis in the same year, 2022 [4]. Life after cancer comes with its own mental and physical health challenges; cancer treatments and their associated long-term effects can cause major changes in people’s lives, significantly increasing the likelihood of developing comorbidities such as cardiovascular disease, diabetes, and osteoporosis, affecting the quality of life and wellbeing of those affected by cancer and their close relatives [5].
Nutrition plays a central role in life after cancer. Evidence supports an increased risk of all-cause mortality with unhealthy dietary patterns and a reduced risk with healthier patterns among individuals affected by breast and colorectal cancer [6,7]. For breast cancer specifically, a meta-analysis of cohort studies provides strong evidence of an inverse association between high adherence to the Mediterranean diet and all-cause mortality [8]. Yet, people with a history of cancer often report the need for reliable food and nutrition information and resources to support their ongoing recovery and wellbeing [9,10]. Although nutrition and physical activity guidelines exist for individuals living with and beyond a cancer diagnosis, these recommendations are broad, not cancer-specific, and are largely adapted from general cancer prevention guidelines [6]. Moreover, a recent cross-sectional study by the American Cancer Society (n = 10,020) reported that 88% of respondents living with and beyond cancer did not adhere to the recommended healthy eating habits [11]. Establishing and sustaining healthy eating behaviours is often challenging after treatment; factors such as fatigue, stress, depression, limited knowledge and resources, unsupportive food environments, and changes in taste and appetite have been identified as the main barriers to maintaining healthy dietary behaviours [10,12,13]. Furthermore, many people affected by cancer report seeking nutrition information from external sources due to the lack of accessible dietary support within healthcare system settings, despite uncertainty about the reliability of these sources [9,14,15,16,17]. When advice is received, it is not always perceived as relevant to needs and preferences, and individuals frequently express a desire to receive evidence-based, tailored dietary support [9,14,15,17]. Together, these findings underscore a critical gap in post-treatment care and highlight the need for structured, accessible, and personalised nutrition resources and services for people living with and beyond cancer.
Nutrition education programmes for individuals living with and beyond cancer have demonstrated beneficial impacts. A recent systematic review of nutrition-related care in primary care settings found that nutrition interventions delivered by dietitians to people living with and beyond cancer produced meaningful changes in outcomes such as intentional weight loss and improved body composition [18]. Participants have reported improved nutrition knowledge, reduced obstacles to adopting healthier eating patterns, and greater confidence in implementing dietary advice [7,18,19,20]. Within nutrition programmes, culinary nutrition interventions combine nutrition education with hands-on cooking instruction to improve dietary behaviours and health outcomes [21]. Culinary nutrition interventions may be more effective than education alone because they merge nutrition knowledge with practical cooking skills, sensory experiences, behavioural strategies, and social support [21,22,23]. Both adult and child participants show improved dietary quality, greater fruit and vegetable intake, and healthier eating habits [22,23,24,25]. Cooking skill interventions have positive effects on food literacy, particularly improving confidence in healthy cooking with vulnerable, low-socioeconomic groups gaining more benefits [25,26]. Beyond dietary change and healthy cooking, culinary nutrition programmes build long-term skills fostering confidence, reducing food anxiety and strengthening social connections and family engagement [27].
Culinary interventions may be a promising approach to promote healthy eating behaviours and improve health outcomes for people living with and beyond cancer; however, evidence regarding their specific content, structure, and effectiveness remains limited. In particular, there is a lack of comprehensive synthesis on how culinary interventions influence health-related outcomes among people affected by cancer, a population with unique nutritional needs and behavioural challenges. While a scoping review has previously mapped existing studies, their content, and delivery methods, no systematic review yet has critically evaluated the quality and impact of these interventions [28]. This systematic review therefore aims to address this gap by providing an in-depth analysis of culinary intervention quality and their associated health outcomes in cancer survivorship.
The main aim of this study was to conduct a systematic review to answer the following research question: “What is the impact on health-related outcomes of culinary nutrition interventions for people living with and beyond cancer, as well as their support networks?”
2. Materials and Methods
This systematic review was carried out according to the Cochrane Handbook [29] and Preferred Reporting Items for Systematic reviews and Meta-Analyses (PRISMA) guidelines [30]. It is registered under the PROSPERO ID CRD42024567041.
2.1. Eligibility Criteria
2.1.1. Inclusion and Exclusion Criteria
Quantitative and qualitative evaluations of randomised and non-randomised controlled culinary nutrition education interventions were reviewed,, including interventions with other components such as physical activity or mental health. As a prerequisite for inclusion, only studies targeting people of all ages affected by any type of cancer, as well as their support networks and carers, were included. The programmes could be group-based or individual, but must include a culinary component (at least one session) which could be delivered in real-time, through pre-recorded videos, or via written materials. Interventions could be delivered in person, over the phone, or online. The review included studies with or without a control or comparator. In terms of outcome measures, preferred outcomes identified by those living with and beyond cancer, such as diet quality and quality of life, were considered [31], along with other outcomes including dietary, psychosocial, clinical, metabolic, anthropometric, and feasibility. Culinary nutrition interventions that were not targeted at people living with and beyond cancer or their support networks were not included.
2.1.2. Search Criteria
The online databases PubMed, Scopus, Excerpta Medica Database (EMBASE), Cumulative Index to Nursing and Allied Health Literature (CINAHL), and Web of Science were used to search the literature. The literature search was carried out by KW between January and April 2025. Only peer-reviewed articles written in the English language and published in the last 10 years were included. The search terms were refined several times to optimise article selection while maintaining search sensitivity, given the large volume of literature published on the topic of nutrition and cancer. The full search strategy for each database is presented in Supplementary Figure S1.
2.2. Study Selection
Titles and abstracts retrieved from the search were imported into Covidence systematic review software (Veritas Health Innovation, Melbourne, VIC, Australia). Two authors (MIC and LA) independently reviewed the search results and screened all publications. Initially, titles and abstracts were screened, and any conflicts were resolved through group discussion. Similarly, the full texts of selected articles were reviewed independently by the same authors, with disagreements also resolved through discussion. The selection process followed the established inclusion criteria. Protocol papers, reviews, editorial letters, and conference abstracts were excluded, as well as records for which neither the abstract nor full text could be accessed.
2.3. Data Extraction
A standardised data extraction format was followed for the extraction process, created in Microsoft Excel (Microsoft Office LTSC Professional Plus 2021, Version 2108) and presented here in table form. To gather the studies’ characteristics, the extracted data included author and programme name; place; participants, ethnicity, cancer type, timepoint (before, during, or after treatment), sample size, gender, and age; study design; main nutrition intervention components and specific culinary-related content; delivery, length, and frequency; intervention design, resources, theoretical frameworks, and co-design; and data collection timepoints and health-related outcome measures, including any quantitative non-significant and significant between- and within-group results reported. Two reviewers (MS and MIC) independently extracted data from the included studies. Any disagreement was settled via discussion with a third reviewer (LK).
2.4. Data Analysis
Since a meta-analysis was not possible due to the high diversity of interventions and outcome measures, studies’ results were narratively synthesised following the Cochrane Handbook and Synthesis Without Meta-analysis (SWiM) guidelines [29,32]. This method is intended to examine trends among studies and does not provide information about effect size or evaluate statistical significance; the summary results presented across the studies require careful interpretation.
2.5. Study Risk of Bias Assessment
The Risk of Bias 2.0 (RoB 2) tool for randomised studies [33] and the Risk of Bias in Non-randomised Studies of Interventions (ROBINS-1 V2) tool for non-randomised studies [34] were used to conduct a risk of bias assessment for the included studies in this review. The RoB 2 tool assessed randomised studies under five domains: bias arising from the randomisation process, bias due to deviations from intended interventions, bias due to missing outcome data, bias in the measurement of the outcome, and bias in the selection of the reported result. For each domain, and for the overall risk of bias of each study, the results were on a scale of low risk, some concern, or high risk of bias. The ROBINS-1 V2 tool assessed non-randomised studies under seven domains: risk of bias due to confounding, risk of bias in the classification of interventions, risk of bias in the selection of participants into the study, risk of bias due to deviations from intended interventions, risk of bias due to missing data, risk of bias arising from measurement of the outcome, and risk of bias in the selection of the reported result. For each domain, and for the overall risk of bias of each study, the results were on a scale of low, moderate, serious, or critical risk of bias. The risk of bias was independently assessed by two reviewers (MS and MIC). Any disagreement was settled via discussion with a third reviewer (LK).
3. Results
3.1. Characteristics of the Studies
A total of 8283 records were retrieved from five databases, with 4265 of those titles included in the screening after duplicates were removed by the software. An additional 256 duplicates were manually removed by the reviewers, leaving 4008 for screening. Of these, 19 articles (reporting on 18 studies) were selected and included in the systematic review; a study flow diagram is presented in Figure 1. A total of 1173 participants were included, with sample sizes ranging from 4 to 190 participants per intervention.
Figure 1.
Flowchart detailing the study selection.
The characteristics of the studies and their interventions are described in Table 1 for both non-randomised and randomised controlled studies. Nine articles (44%) reported on 8 randomised controlled trials (RCTs) (mean sample size = 31.8, SD = ±14.0; range 15–60) [35,36,37,38,39,40,41,42,43], and 10 studies (56%) were non-randomised controlled trials (non-RCSTs) (mean sample size 46.3, SD ±33.5; range 4–102) [44,45,46,47,48,49,50,51,52,53]. Only two non-RCT studies included a control group [48,52]. Of the 19 articles, 13 were quantitative (68%) [35,37,39,40,41,42,43,45,48,49,50,51,53] and 6 were mixed-methods (32%) studies [36,38,44,46,47,52]. The majority of the studies were conducted in the USA (n = 14, 78%) [35,36,37,38,40,41,42,43,44,45,49,50,51,53], followed by Canada (n = 2, 11%) [46,47], Israel (n = 1, 5%) [52], Japan (n = 1, 5%) [48], and Spain (n = 1, 5%) [39]. All studies were conducted in adult populations. Ten studies (56%) focused on female participants [35,36,37,38,39,41,42,43,46,50]. Eight studies included both men and women; however, in six of these studies, women constituted 75% or more of the sample [40,44,47,48,49,51,52]. The average sample age ranged between 50 and 64 years old. One study did not report the gender and age of its participants [45]. Nine studies (50%) involved participants with a history of breast cancer [35,36,37,38,39,41,42,43,50], seven (39%) included participants with any cancer type [40,44,45,47,49,51,52], one (6%) head and neck cancer [53], one (6%) digestive cancer [48], and one (6%) gynaecological cancers [46]. Three studies (17%) allowed caregiver participation in the programme [46,47,53]. Fifteen studies (83%) did not target any specific ethnicity [35,37,38,39,40,41,44,45,46,47,48,49,50,51,52], one study (6%) was conducted in Hispanic populations [42,43], one (6%) in African American populations [36], and one (6%) in Caucasian adults [53]. The majority of the studies (n = 15, 83%) were conducted post-treatment [35,36,38,40,41,42,43,44,45,46,47,48,49,50,51,53], two interventions (11%) took place during treatment [37,39], and one (6%) during and post-treatment [52].
Table 1.
Summary characteristics of each study.
3.2. Characteristics of Interventions
Half of the interventions (n = 9) included only a single culinary/nutrition-related component [35,40,42,43,45,46,47,48,49,53], and the other half were multicomponent. Eight interventions (44%) included a physical activity element [36,37,38,39,41,44,50,51], and four (22%) had a psychosocial aspect [36,50,51,52]. Kondo et al. (2023) was the only intervention that did not report including nutrition education alongside the culinary cooking component [48]. Fourteen studies (77%) were conducted in-person in group settings [35,36,37,38,39,40,42,43,44,45,46,47,51,52,53]. Of these, five interventions included a hybrid format and followed participants up with phone calls and/or emails [35,36,37,47,51], and one included online coaching [44]. Three interventions were delivered fully online [41,49,50], and one intervention was one-to-one, in-person [48]. Fifteen interventions (83%) included registered dietitians or nutritionists as part of the delivery team [36,38,39,40,41,42,43,46,47,48,49,50,51,52,90], while 14 studies (77%) included chefs and culinary professionals [35,38,40,41,42,43,44,46,47,50,51,53]. Raber’s programme “Cooking after cancer” was delivered by trained peer facilitators with a personal connection to cancer [45], while Sheean’s RCT “Everyday counts” was delivered by both health and athletic coaches [37]. Other programme facilitators included mental health professionals, physiotherapists, behavioural health specialists, physicians, social workers, and occupational therapists. Interventions ranged from one-off 30 min sessions to 24 week programmes; see Table 1 for details.
All interventions, except for one [48], reported basing their educational content on specific nutrition guidelines and recommendations: the American Institute for Cancer Research (AICR) guidelines [38,40,41,42,43,44,45,49,50,52], the American Cancer Society (ACS) guidelines [36,37,38,41,42,43], the Mediterranean diet guidelines [35,50,51], the American Heart Association and American College of Cardiology (AHA/ACC) Guidelines [44], the Spanish Society of Community Nutrition Guidelines [39], the World Health Organisation’s Nutrient Intake Goal [53], guidelines for fatigue reduction through diet for people affected by cancer [47], nutrition, cancer, and gastrointestinal (GI) complication guidelines [46], garden-based lifestyle interventions [44], and the World Health Organisation physical activity guidelines [39]. Fifteen studies based their interventions’ format and delivery on established behaviour change techniques, such as social learning theory and social cognitive theory [36,37,38,40,41,42,43,46,47], the transtheoretical model of health behaviour change [40,42,43,53], experiential learning theory [46,47,48], self-determination theory [41,44], Contento’s model [42,43], the theory of planned behaviour [36], stages of change [35], lifestyle behaviour change frameworks [51], and other behaviour change techniques [40,46,47,50,52]. Three programmes did not base their interventions on health behavioural theories [39,45,49]. Finally, seven interventions engaged multiple stakeholders through co-design and community-based participatory research methods: community-led co-design [37,42,43], stakeholder-led co-design [40], and participant-led co-design [48,50,52,53].
3.3. Nutrition Component of the Interventions
The nutrition education content of most interventions included a combination of nutrition education sessions [35,36,37,38,39,40,41,42,43,44,45,46,47,49,50,51,52,53] alongside either cooking demonstrations [35,36,39,40,42,43,44,49,50,51,53], hands-on cooking lessons [37,41,46,47,52], or both [38,45]. Kondo et al. (2023) delivered hands-on cooking lessons and did not report a nutrition education component, even though the intervention was facilitated by a dietitian and an occupational therapist [48].
The main topics addressed general healthy eating, food groups, and nutrients [35,36,37,38,39,40,41,42,43,44,45,46,47,49,50,51,52,53]; meal planning, recipes, portion size, and meal preparation [35,36,37,38,39,40,41,42,43,45,46,47,49,50,52,53,60,90]; food shopping, food labels, and eating out [35,38,39,40,41,42,43,45,46,48,50,51,52,53]; psychosocial aspects of food such as mindful eating, food anxiety, emotional wellbeing, meal sharing, and eating together [39,40,41,42,43,48,50,52,53]; barriers to healthy eating, goal setting, coaching, and behaviour change strategies [35,36,37,40,44,47,50,51,52,53]; cancer-related food taste changes [35,40,42,43,51,52,53], and other nutrition-related modifiable risk factors for cancer [36,38,44,45,46,47,48,50]. Several interventions focused on specific dietary approaches, including whole food plant-based diets [37,40,44,45], Mediterranean-style diets [35,50,51], and anti-inflammatory diets [35,49], as well as diets addressing cancer-related fatigue [47] and cancer-related GI issues [46,48].
With regard to the culinary nutrition component of the interventions, in most studies, the cooking sessions complemented the nutrition education content delivered. Cooking demonstrations and hands-on sessions were facilitated by chefs (n = 8, 44%) [35,38,42,43,44,46,47,51], culinary specialists (n = 2, 11%) [40,50], or both (n = 2, 11%) [41,53]. Six studies did not include a culinary or chef professional in their delivery team (33%) [36,37,39,45,48,49,52]. In four studies, participants were invited to select the recipes to prepare [48,50,52,53], while three studies culturally tailored the cooking sessions to align with participants’ dietary traditions [36,42,43,52]. The culinary sessions typically involved recipe preparation, ingredient selection, increasing the inclusion of healthier options such as fruits, vegetables, herbs, and spices, and the development of practical cooking skills (e.g., knife skills and equipment use) [35,36,37,38,40,41,42,43,44,46,47,48,49,50,51,52,53]. Five interventions focused on Mediterranean-style cooking (28%) [35,49,50,51,52], six on preparing and sharing meals together (33%) [35,38,40,41,42,43,45,51,52,53], and six on introducing healthier alternatives (for example, enhancing sweetness without added sugar, or flavour without added salt, or increasing the fibre content) (33%) [42,43,47,49,50,51]. Other sessions emphasised cooking methods that promote convenience and taste (50%) [35,38,40,42,43,45,47,51,52,53], have anti-inflammatory properties (17%) [35,47,49], address cancer-related dietary challenges (39%) [35,38,39,44,45,46,47], utilise garden produce (6%) [44], or incorporate friendly cooking competitions (6%) [38]. The culinary content was only briefly described with little detail in four interventions (22%) [36,38,39,48].
3.4. Outcome Measures
Table 2 describes a summary of the outcome measures and results for each study. Across the studies included, outcome measures spanned across seven key areas: dietary intake, anthropometric measures, psychosocial wellbeing, health-related outcomes, clinical and metabolic measures, feasibility, and qualitative outcomes. Dietary intake was assessed in 13 studies (72%) using self-reported tools, including dietary recall [35,36,37,39] and questionnaires [35,38,40,44,45,49,52,53]. Psychosocial and behavioural outcomes were assessed in 12 studies (67%) and included quality of life (n = 5, 28%) [37,40,44,51,52]; perceived stress, anxiety, depression, and subjective wellbeing (n = 6, 33%) [37,40,41,48,51,52]; self-efficacy and confidence in symptom management (n = 6, 28%) [36,40,44,46,47]; food-related behaviours (n = 2, 11%) [50,52]; lifestyle behaviours and risks factors (n = 2, 11%) [37,44]; emotional support (n = 1, 6%) [40]; and health literacy (n = 1, 6%) [38]. Eight studies additionally assessed health-related outcomes such as fatigue and energy levels (n = 3, 17%) [37,40,47], physical functioning (n = 3, 17%) [39,47,48], physical activity (n = 2, 11%) [36,44], and cognitive function (n = 1, 6%) [49]. Eight studies measured anthropometric outcomes; these were typically measured via weight and body mass index (BMI) (n = 8, 39%) [37,38,39,41,42,43,44,51] and waist circumference (n = 6, 33%) [37,39,41,42,43,44,51]. Clinical and metabolic outcome measures were included in six studies [36,37,39,42,44,51]; clinical measures included resting heart rate (n = 1, 6%) [39] and blood pressure (n = 3, 17%) [39,44,51], while metabolic outcomes comprising cardiometabolic fitness—VO2 max (n = 1, 6%) [36], lipid markers (n = 3, 17%) [39,44,51], glycaemic markers (n = 2, 11%) [44,51], inflammatory markers (n = 3, 17%) [42,44,51], nutrient/antioxidant markers (n = 2, 11%) [42,44], cellular energetics (n = 1, 6%) [37], and epigenetic markers (n = 1, 6%) [42]. Five studies evaluated the feasibility of the intervention alongside its effectiveness (28%) [38,39,44,46,47]. Qualitative outcomes were reported in six studies using focus groups, interviews, or questionnaires (33%) [36,37,38,44,46,47].
Table 2.
Outcomes measured, summary of results and risk of bias of each study.
3.4.1. Dietary Intake
Thirteen studies reported dietary intake outcomes; however, outcome measures were heterogeneous. Fruit and vegetable (F/V) intake was assessed in six studies. Greenlee et al. (2015, 2016) reported significant increases in F/V intake in the intervention arm versus control, maintained at 6- and 12-month follow-up (+2 and +2.3 F/V servings, respectively) [42,43]. Similarly, Greenlee et al. (2024) observed an increase in daily servings of F/V after the intervention (+1.5) [41]. In contrast, Miller et al. (2020), Morato-Martínez et al. (2021), Sheean et al. (2021), and Parekh et al. (2018) found no significant between-group differences in F/V intake [37,38,39,40]. Miller et al. (2020) and Parekh et al. (2018) also assessed nutrition knowledge, skills, and confidence. In the first study, nutrition knowledge improved significantly at both week 9 and 15 (+0.8 and +0.6), while nutrition confidence (+0.7) and skills (+0.4) showed significant improvement by week 15 [40]. Fat intake was assessed in three studies; Greenlee et al. (2015, 2016) observed a significant reduction in percent calories from total fat (−7.1%) and saturated fat (−3.8%) at 3 months, and non-significant changes at follow-up [42,43]. Similarly, Greenlee et al. (2024) recorded a reduction in fat intake post-intervention (−10 g of total fat and −4.6 of saturated fat) [41]; and Sheppard et al. (2016) observed non-significant changes in total fat, % energy from fat, and fibre intake [36].
Zuniga et al. (2019) assessed adherence to a Mediterranean diet using three-day food records and observed a significant increase in adherence to Mediterranean diet guidelines in the intervention arm (22.5% improvement). Improved adherence was noted for three specific guideline components: consuming ≥3 servings of fish or shellfish per week, reducing red meat intake to <1 serving per day, and limiting consumption of commercial sweets and baked goods to <3 times per week [35]; moreover, use of spices/herbs increased by 146.2%. Both Zuniga et al. (2019) and Greenlee et al. (2024) reported a significant reduction in total calorie intake in the intervention group (+195.5 kCal and −170 kCal, respectively) [35,41]. Jackson et al. (2024) further evaluated dietary intake using the Dietary Inflammatory Index (DII) and found a significant decrease (−2.7) in the inflammatory potential of the intervention group’s diet [49]. Barak-Nahum et al. (2016) also reported significant improvements, as measured by the Intuitive Eating Scale and Food Choice questionnaires (+13.5) [52]. Spees et al. (2019) observed significant improvements in dietary intake using the Healthy Eating Index (HEI) (+5.2) [44]. Parekh’s and Sheean’s studies achieved high dietary intake scores at baseline with limited potential for further improvement after the intervention [37,38]. Raber et al. (2022) [45] and Allen-Winters et al. (2020) [53] also evaluated dietary intake and found no significant changes. Overall, findings were mixed across single-component and multicomponent interventions, as well as between randomised and non-randomised controlled trials, with both study designs demonstrating significant and non-significant results.
3.4.2. Quality of Life
Barak-Nahum et al. (2016) [52], Golubić et al. (2018) [51], Miller et al. (2020) [40], Sheean et al. (2021) [37], and Spees et al. (2019) [44] reported on quality of life, although different validated instruments were used. Sheean et al. (2021) reported statistically significant pre–post improvements in physical (+1.6), emotional (+1.4), and functional wellbeing (+1.2) measured using the FACT instrument [37]. Using the QOL-CSV, Spees et al. (2019) observed statistically significant improvements across physical, psychological, and spiritual quality-of-life domains (+16) [44]. Barak-Nahum et al. (2016) reported significantly higher health-related quality of life and affective wellbeing in the intervention group assessed using the SF-12 (+13.23), higher subjective positive affect (+40.6), and lower negative affect (−28) [52]. Golubić et al. (2018) identified statistically significant improvements in physical (+62%), mental (+51%), and overall health-related quality of life (+54%), measured using the VR-12 [51]. In contrast, Miller et al. (2020) found no statistically significant changes in quality of life when assessed using the FACT-G7 [40].
3.4.3. Other Psychosocial Outcomes and Health-Related Outcomes
Six studies assessed mental health outcomes such as perceived stress, anxiety, depression, and subjective wellbeing. Miller et al. (2020) reported no significant improvements in psychological distress [40]. Golubić et al. (2018) found significant improvements in perceived stress (−20%), assessed using the Perceived Stress Scale (PSS) [51]. Greenlee et al. (2024) noted no significant changes in anxiety scores assessed via the Patient-Reported Outcomes Measurement Information System (PROMIS) questionnaire [41]. Sheean et al. (2021) reported mixed results with the Hospital Anxiety and Depression Scale (HADS): significant reductions in depression were observed in the intervention group compared with the control (−0.9), anxiety decreased significantly in the control group (−1.2), and perceived stress decreased significantly for participants in both groups, with a higher decrease for the intervention group (−2.8) [37]. Kondo et al. (2023) also assessed anxiety and depression using the HADS and reported significant improvements only in the intervention group, with intergroup comparisons indicating additional gains for both anxiety (−4) and depression (−6) [48]. Barak-Nahum et al. (2016) found significant improvements in subjective wellbeing, lower subjective wellbeing’s negative affect (+28), and positive affect (+41), measured using the Subjective Wellbeing Scale [52].
Regarding food-related behaviours, Huang et al. (2023) assessed mindfulness while eating via the Mindful Eating Questionnaire (MEQ) and found a significant increase in all MEQ subscale scores except for the distraction subscale (scale mean change 0.12) [50]. Similarly, Barak-Nahum et al. (2016) [52] reported a positive effect of the culinary intervention on intuitive eating and food choices, as measured by the Intuitive Eating Scale. Participants in the intervention group showed that intuitive eating, in general, increased over time: unconditional permission to eat (+25.1), eating for physical rather than emotional reasons (+22.9), and reliance on hunger and satiety cues (+37.3). Moreover, higher healthy food choice scores were associated with better health-related quality of life and positive affect, and with lower negative affect, independent of intervention group [52].
Pritlove et al. (2024) [46], Sheppard et al. (2016) [36], and Spees et al. (2019) [44] assessed the self-efficacy of participants, with Pritlove et al. (2024) [46] finding significant improvement in self-efficacy with regard to managing GI side effects. Qualitative findings also supported this result, with the improvements in knowledge and confidence providing an increase in empowerment and self-efficacy for some participants [46]. Sheppard et al. (2016) found that participants had high perceived control in achieving and maintaining their dietary and physical activity goals (overall satisfaction, 86%) [36], while Spees et al. (2019) noted non-significant changes for self-efficacy [44].
Symptom management was assessed by Miller et al. (2020) [40], Sheean et al. (2021) [37], Pritlove et al. (2020) [47], and Pritlove et al. (2024) [46]. Pritlove et al. (2020) found that fatigue scores significantly improved and were maintained across the full follow-up period (from baseline to week 9 and week 12, +5 and +7.75) [47]. Sheean et al. (2021) found that fatigue improved for the intervention group (+1.6) [37], and Miller et al. (2020) found no significant changes in fatigue symptoms [40]. Miller et al. (2020) observed that perceived control over the cancer trajectory remained relatively stable in both groups [40]. Pritlove et al. (2024) reported statistically significant improvements in bowel-related and GI symptoms post-intervention [46], while Sheean et al. (2021) observed that participants in the intervention group experienced meaningful improvements in both breast cancer-related symptoms (+6.8) and endocrine symptoms (+8.7) [37]. Jackson et al. (2024) [49] assessed cognitive function using the Functional Assessment of Cancer Therapy–Cognitive Function (FACT-Cog) tool and reported significant improvements in FACT-Cog subscores following the intervention: perceived cognitive impairment (Δmedian −38), comments from others (Δmedian −16), and quality of life (Δmedian −10).
3.4.4. Anthropometric Measures
Eight studies reported anthropometric outcomes, assessed using BMI, body weight, or waist circumference [36,37,38,39,41,42,43,44,51]. Findings varied across studies. Morato-Martínez et al. (2021) observed significant decreases in body weight (−1.87 kg) and BMI (−0.61 kg/m2) in the intervention group [39], while Parekh et al. (2018) also reported a significant reduction in age-adjusted BMI (−0.69 kg/m2) [38]. Golubić et al. (2018) found significant reductions in BMI (−2.4 kg/m2), weight (−7%), and waist circumference (−6.6 cm) in the intervention arm [51]. Similarly, Spees et al. (2019) observed significant reductions in body weight (3.9 kg), BMI (−1.5 kg/m2), and waist circumference (−5.5 cm) [44]. In contrast, Greenlee et al. (2015, 2016), Greenlee et al. (2024), Sheppard et al. (2016), and Sheean et al. (2021) reported no significant changes in anthropometric measures [36,37,41,42,43,72]. The results differed across randomised and non-randomised controlled trials; significant improvements in anthropometric outcomes were observed in four multicomponent interventions that combined a physical activity component with a culinary or nutrition element [38,39,44,51]. Three other multicomponent interventions showed no significant changes [36,37,41], and one single-component intervention likewise reported no significant differences [42,43].
3.4.5. Clinical and Metabolic Outcomes
Six studies reported on clinical and metabolic measures [36,37,39,42,44,51]. Golubić et al. (2018) [51], Spees et al. (2019) [44], and Morato-Martínez et al. (2021) [39] reported on blood pressure changes; Spees et al. (2019) observed a significant improvement in systolic blood pressure (−9.5 mmHg) [44], while Morato-Martínez et al. (2021) and Golubić et al. (2018) found no significant changes [39,51]; even though systolic and diastolic blood pressure did not reach statistical significance in Golubić’s Lifestyle180® study, participants reported an overall decrease in their use of blood pressure medications, 30% of participants reduced BP medications, while 15% increased their medication [51]. Morato-Martínez et al. also found no changes in heart rate [39]. Regarding cardiometabolic fitness, Sheppard et al. (2016) examined changes in VO2 max and observed non-significant changes [36]. Morato-Martínez et al. (2021) [39], Golubić et al. (2018) [51], and Spees et al. (2019) [44] examined lipid profiles. Morato-Martínez et al. (2021) observed a significant reduction in LDL cholesterol in the intervention group at month 6 and 12 (−35.29 mg/dL and −12.5 mg/dL), as well as total cholesterol (−29.29 mg/dL and −32.92 mg/dL) with non-significant changes for triglycerides and HDL cholesterol [39]. Golubić et al. (2018) reported significant improvements in triglycerides (−23.0 mg/dL) and HDL-C (+3.3 mg/dL) and non-significant changes in LDL cholesterol; some participants decreased the use of lipid-lowering medication (12% reduced vs. 3% increased) [51], whereas Spees et al. (2019) found significant reductions in total cholesterol (−6%) and triglycerides (−14%) [44].
Greenlee et al. (2016), Morato-Martínez et al. (2021), Golubić et al. (2018), and Spees et al. (2019) assessed glycaemic markers [39,42,44,51]. Golubić et al. (2018) reported significant improvements in fasting insulin (−4.2 mU/mL) and insulin sensitivity (−1.5), and non-significant changes were observed in fasting plasma glucose [51]. In contrast, Spees et al. (2019), Greenlee et al. (2016), and Morato-Martínez et al. (2021) found no significant changes in insulin or fasting plasma glucose [39,42,44]. Golubić et al. (2018), Greenlee et al. (2016), and Spees et al. (2019) examined inflammatory markers [42,44,51]. Greenlee et al. (2016) examined inflammatory markers including interleukin-1 alpha (IL-1α), interleukin-10 (IL-10), tumour necrosis factor-alpha (TNF-α), and high-sensitivity C-reactive protein (hs-CRP), and found no significant changes [42]. In contrast, Spees et al. (2019) reported a significant decrease in hs-CRP levels (−28%) in the intervention group, as well as a reduction in Insulin-like Growth Factor Binding Protein 3 (IGFBP-3) (−5%) [44]. Golubić et al. (2018) also observed significant reductions in c-CRP (−1.3 mg/L) [51]. Greenlee et al. (2016) [42] assessed antioxidant status by measuring plasma carotenoids and found that participants in the intervention group achieved a significantly greater percent decrease in plasma lutein at both month 6 and 12 (+13.8% and +20.4%, respectively); no significant changes were observed in blood levels of lycopene, α-carotene, β-carotene, β-cryptoxanthin, and retinol [42]. Spees et al. (2019) reported significant increases in plasma carotenoid concentrations in the intervention group with total dietary carotenoids increasing by 66% and total plasma carotenoids by 35% [44]. Sheean et al. (2021) observed no changes in spare respiratory capacity [37], a measure of mitochondrial function and the cell’s ability to respond to increased energy demand [92]. Greenlee et al. (2016) observed no significant changes in DNA methylation [42]. Five out of the six studies reporting on clinical and metabolic measures were multicomponent [36,37,39,44,51], and no differences were present between RCTs [36,37,39,42] versus nRCTs [44,51] in terms of achieving significant results.
3.4.6. Feasibility and Qualitative Outcomes
Spees et al. (2019) [44], Pritlove et al. (2020) [47], Pritlove et al. (2024) [46], and Parekh et al. (2018) [38] looked at the feasibility of interventions. Spees et al. (2019) [44] found that attendance and engagement were strong; participants attended 90% of education sessions and 59% of harvest weeks, with most completing at least 80% of intervention weeks. Use of the web portal (90%) and tele-motivational interviewing (59%) was high, and email was the preferred communication mode. Acceptability was excellent, with 93% rating the programme very positively. Participants valued the group education sessions most, reported meaningful health benefits and community support, and overwhelmingly indicated improvements in diet and physical activity, with nearly all planning to apply what they learned [44]. Pritlove et al. (2020) [47] assessed feasibility via qualitative interviews. Common themes regarding the feasibility of the intervention included that most participants found the programme length and frequency to be appropriate, that recipes and culinary strategies were easy to understand and implement, and that the programme was flexible regarding scheduling [47]. Pritlove et al. (2024) [46] also found similar themes; qualitative interviews reflected strong perceptions of feasibility, with modest recruitment (32%) but optimal retention (72%), suggesting a need to explore alternative formats. Participants reported high satisfaction and perceived utility of the program. Common recommendations included offering more in-class sessions and expanding the programme to enhance engagement and sustain participation over time [46]. Recruitment targets were achieved within six months in Parekh’s study (2018) [38] and session attendance was strong, with over half of participants attending all sessions. Qualitative feedback indicated high acceptability, with participants valuing the hands-on cooking activities and overall programme structure.
Six studies explored qualitative outcomes. Across these studies, key themes included participant satisfaction with the sessions, perceived benefits, and suggestions for programme enhancement. Parekh et al. (2018) reported that participants viewed the sessions as valuable and appreciated the supportive group environment [38]. In Spees et al. (2019), participants described reductions in medication use and reported experiencing fewer challenges with healthy eating following the intervention [44]. Both Sheppard et al. (2016) and Pritlove et al. (2020, 2024) noted high levels of satisfaction among participants [36,46,47]. Regarding recommendations for improvement, participants in Parekh et al. (2018) suggested incorporating booster sessions and providing information on tailored diets [38]. Those in Sheppard et al. (2016) proposed more opportunities for interaction with peers and facilitators, along with greater contextual tailoring of the programme [36]. Participants in Pritlove et al. (2020) recommended a multi-tiered structure based on participants’ skill levels and more one-to-one consultations [47], while those in Pritlove et al. (2024) expressed interest in additional in-person sessions and programme expansion [46]. Similarly, participants in Sheean et al. (2021) highlighted the value of expanding the intervention and offering more ongoing support [37]. No consistent differences in qualitative outcomes were observed between single- and multicomponent interventions or between randomised and non-randomised study designs.
3.5. Risk of Bias
For the nine RCTs included in this study, the overall risk of bias was high in three studies [37,38,40], and the remaining six studies had some concerns [35,36,39,41,42,43]. Risk of bias arising from the randomisation process was low in three studies [37,42,43], and of some concern in six studies [35,36,38,39,40,41]. Bias due to deviations from intended interventions was of some concern in all nine studies [35,36,37,38,39,40,41,42,43]. Bias due to missing outcome data was low risk in four studies [37,41,42,43], of some concern in three studies [35,39,40], and high in two studies [36,38]. Risk of bias in the measurement of outcome was low in one study [42], of some concern in six studies [35,36,38,39,41,43], and high in two studies [37,40]. Risk of bias in the selection of reported results was low in one study [41], and of some concern in the remaining eight studies [35,36,37,38,39,40,42,43]. For the 10 non-RCTs, the overall risk of bias was critical in eight studies [44,45,46,47,49,50,51,53] and moderate in two studies [48,52]. The risk of bias was critical in eight studies due to failure to control for confounding. Further details of the risk of bias assessments are provided in the Supplementary Materials.
4. Discussion
To our knowledge, this is the first systematic review to present a consolidated summary of the effects of culinary nutrition interventions on the health and wellbeing of people living with and beyond cancer. Eighteen programmes published in the literature within the past 10 years were deemed eligible. Despite considerable heterogenicity in intervention content and outcome measures, a consistent pattern emerged across interventions indicating generally positive effects on participants’ health and wellbeing. Our findings indicate that both culinary nutrition-only interventions and those combining nutrition with physical activity and/or mental health components have a positive impact on dietary intake, psychosocial and health outcomes, anthropometric measures, some clinical and metabolic indicators, and feasibility-related outcomes among people living with or beyond cancer.
In terms of the preferred nutrition-related outcome measures of those living with and beyond cancer, dietary intake and quality of life [31], in this review, dietary intake was assessed in 13 studies, with approximately 70% reporting positive changes following the intervention. Similarly, quality of life outcomes were evaluated in five studies, four of which reported significant improvements. These findings suggest that culinary nutrition interventions most consistently benefit outcomes that matter most to cancer survivors, indicating strong alignment with patient-identified needs and meaningful impact.
Overall, the reviewed evidence suggests that culinary nutrition interventions hold meaningful promise for supporting the health and wellbeing of people living with and beyond cancer [6,93,94,95]. Importantly, all studies were well-received, with high satisfaction, strong engagement, and few adverse effects, indicating that nutrition education programmes are both feasible and acceptable in survivorship care. The findings of this systematic review also reflect the broader needs of this population, emphasising the importance of supportive systems that facilitate sustainable dietary and lifestyle changes [9,10,13,14,96]. There is growing evidence that a healthy diet is linked to lower all-cause mortality in cancer survivors [6]; while many individuals understand healthy eating principles, making and maintaining meaningful changes, particularly after a cancer diagnosis, requires practical guidance, tailored support, and a structured environment to build skills. Culinary nutrition interventions address these needs by providing reliable, hands-on education that empowers individuals to apply recommendations in their daily lives [22,23]. This is especially relevant given that 88% of cancer survivors do not adhere to recommended healthy eating guidelines, highlighting a critical gap in post-treatment care [11]. Together, these findings highlight the need to integrate accessible, personalised, and supportive nutrition programmes into oncology care, recognising that sustained lifestyle change rarely happens in isolation—it requires coordinated support, community, and ongoing guidance.
Forty percent of the included studies incorporated elements of community-based participatory research (CBPR) [37,40,42,43,48,50,52,53]. Although it was not possible to quantify the level or impact of public and patient involvement (PPI) due to heterogeneity in both intervention design and participatory approaches, the inclusion of CBPR remains an important strength. People living with and beyond cancer have consistently highlighted the need for nutrition information and programmes to be tailored to their specific needs and lived experiences [9,14,15,17]. CBPR places community stakeholders at the centre of the research process and integrates experiential knowledge into the co-creation of health interventions alongside researchers and health professionals [97,98]. This collaborative approach enables the design of health promotion and prevention interventions that are responsive to the population’s context, preferences, and priorities. Importantly, CBPR facilitates the identification of both community-wide and subgroup-specific needs and supports a deeper understanding of how social, economic, and environmental determinants shape health behaviours and outcomes [97,98]. As such, CBPR-informed approaches may enhance the relevance, acceptability, and sustainability of culinary nutrition interventions in cancer care.
4.1. Quality of the Evidence
A key strength of the studies included in this review is that 88% of them drew on evidence-based nutrition recommendations and guidelines [35,36,37,38,39,40,41,42,43,44,46,47,49,50,51,52,53], and an equal proportion incorporated established behaviour-change theoretical frameworks to inform intervention design and content [35,36,37,38,40,41,42,43,44,46,47,48,50,51,52,53]. On the other hand, across the included studies, the overall risk of bias was substantial. Among the RCTs, most were rated as having some concerns [35,36,39,41,42,43], and three were rated as high risk [37,38,40]. Common issues included deviations from intended interventions, missing outcome data, and concerns regarding outcome measurement and selective reporting. The non-randomised studies demonstrated greater methodological limitations, with the majority, except for two studies [48,52], classified as having a critical risk of bias, primarily due to inadequate control of confounding [44,45,46,47,49,50,51,53].
4.2. Strengths and Limitations
One strength of the present review is that it is the first to comprehensively examine nutrition education interventions that include a culinary component for people living with and beyond cancer. While previous systematic reviews have evaluated the impact of nutrition education programmes [7,8,99,100,101,102], this is the first to focus specifically on culinary nutrition education interventions. This distinction is important, as cooking skills and practical culinary knowledge can enhance confidence, autonomy, and the capacity to adopt and sustain healthy eating behaviours [25]. This systematic review has several limitations that should be considered when interpreting the findings. Substantial heterogeneity across studies, including differences in sample size, intervention length, content and delivery format, and the range of outcomes assessed, limited the ability to compare results directly and quantify intervention effects or pool results in a meta-analysis. As described previously, the overall risk of bias was high, particularly among non-randomised studies, where inadequate control for confounding was common. Fifty percent of the selected studies targeted people with breast cancer [35,36,37,38,39,41,42,43,50], while 39% included participants with any cancer type [40,44,45,47,49,51,52]. Although this reflects the prevalence of breast cancer within the population [2], it nonetheless limits the generalisability of the findings to individuals with other cancer diagnoses. On the other hand, 15 studies (83%) were conducted in the post-treatment phase [35,36,38,40,41,42,43,44,45,46,47,48,49,50,51,52], which strengthens the relevance of the findings for individuals living beyond active cancer treatment.
4.3. Implications for Research and Practice
Although nutrition recommendations exist for people living with and beyond cancer, adapted and more practical strategies are needed to embed nutrition within oncology care and to support individuals in sustaining meaningful lifestyle changes over time [6]. This is particularly relevant given that the reviewed interventions were generally well tolerated and well accepted, with minimal reported adverse effects. At the same time, the limitations identified in this review emphasise the need for further high-quality research to better understand the role and effectiveness of these programmes, whether delivered alone or in combination with components such as physical activity or mental health support. Future research should extend beyond breast cancer to include a wider range of cancer types and more diverse populations. Greater inclusion of male participants, younger populations, and underrepresented groups is needed to improve the equity, relevance, and applicability of findings. A critical gap identified in this review is the lack of sustainability and long-term follow-up data. Future studies should evaluate the durability of dietary and health outcomes over time and assess whether culinary nutrition interventions support sustained long-term behaviour change.
5. Conclusions
This review summarises the effects of nutrition education programmes incorporating a culinary component in people living with and beyond cancer. The findings indicate that culinary nutrition interventions, both standalone and those combined with physical activity or mental health components, are generally beneficial, demonstrating improvements across most outcome areas, especially outcomes preferred by the cancer community—dietary intake and quality of life [31]. While the review cannot determine the precise magnitude of these effects, our findings summarise the ongoing research in this field and help understand their potential, direction, and scope, highlighting important areas for further investigation. The emerging evidence aligns with current oncology nutrition guidelines and highlights the potential of culinary nutrition programmes as supportive, behaviour-focused strategies that can complement clinical care and improve survivorship outcomes.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/curroncol33020076/s1, Figure S1: Search criteria. Supplementary Data: RoB Assessment.
Author Contributions
Conceptualization, M.I.-C. and L.K.; methodology, M.I.-C., M.S., L.A., K.W. and L.K.; validation, M.I.-C., M.S., L.A., K.W. and L.K.; formal analysis, M.I.-C., M.S. and L.A.; investigation, M.I.-C., M.S., L.A. and L.K.; resources, M.I.-C. and L.K.; data curation, M.I.-C. and M.S.; writing—original draft preparation, M.I.-C. and M.S.; writing—review and editing, M.I.-C. and L.K.; visualisation, M.I.-C. and M.S.; supervision, M.I.-C. and L.K.; project administration, M.I.-C. and L.K.; and funding acquisition, M.I.-C. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Research Summer School Fund, RCSI University of Medicine and Health Sciences, Dublin, Ireland.
Data Availability Statement
All data supporting the findings of this study are contained within the article and its Supplementary Materials.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Zhao, J.; Xu, L.; Sun, J.; Song, M.; Wang, L.; Yuan, S.; Zhu, Y.; Wan, Z.; Larsson, S.; Tsilidis, K.; et al. Global Trends in Incidence, Death, Burden and Risk Factors of Early-Onset Cancer from 1990 to 2019. BMJ Oncol. 2023, 2, e000049. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Cancer. Available online: https://www.who.int/news-room/fact-sheets/detail/cancer (accessed on 18 November 2025).
- Allemani, C.; Matsuda, T.; Di Carlo, V.; Harewood, R.; Matz, M.; Niksic, M.; Bonaventure, A.; Valkov, M.; Johnson, C.J.; Esteve, J.; et al. Global Surveillance of Trends in Cancer Survival 2000-14 (Concord-3): Analysis of Individual Records for 37,513,025 Patients Diagnosed with One of 18 Cancers from 322 Population-Based Registries in 71 Countries. Lancet 2018, 391, 1023–1075. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Global Cancer Burden Growing, Amidst Mounting Need for Services. Available online: https://www.who.int/news/item/01-02-2024-global-cancer-burden-growing--amidst-mounting-need-for-services (accessed on 18 November 2025).
- Wagle, N.S.; Nogueira, L.; Devasia, T.P.; Mariotto, A.B.; Yabroff, K.R.; Islami, F.; Jemal, A.; Alteri, R.; Ganz, P.A.; Siegel, R.L. Cancer Treatment and Survivorship Statistics, 2025. CA Cancer J. Clin. 2025, 75, 308–340. [Google Scholar] [CrossRef] [Scilit]
- Li, Z.; Ding, X.; Chen, Y.; Keaver, L.; Champ, C.E.; Fink, C.L.; Lebovits, S.C.; Corroto, M.; Zhang, F.F. Review of Nutrition Guidelines and Evidence on Diet and Survival Outcomes for Cancer Survivors: Call for Integrating Nutrition into Oncology Care. J. Nutr. 2024, 154, 2346–2362. [Google Scholar] [CrossRef] [Scilit]
- Castro-Espin, C.; Agudo, A. The Role of Diet in Prognosis among Cancer Survivors: A Systematic Review and Meta-Analysis of Dietary Patterns and Diet Interventions. Nutrients 2022, 14, 348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, G.; Leary, S.; Niu, J.; Perry, R.; Papadaki, A. The Role of the Mediterranean Diet in Breast Cancer Survivorship: A Systematic Review and Meta-Analysis of Observational Studies and Randomised Controlled Trials. Nutrients 2023, 15, 2099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Keaver, L.; O’Callaghan, N.; Douglas, P. Nutrition Support and Intervention Preferences of Cancer Survivors. J. Hum. Nutr. Diet. 2023, 36, 526–539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Keaver, L.; Douglas, P.; O’Callaghan, N. Perceived Barriers and Facilitators to a Healthy Diet among Cancer Survivors: A Qualitative Exploration Using the Tdf and Com-B. Dietetics 2023, 2, 123–139. [Google Scholar] [CrossRef] [Scilit]
- Baughman, C.; Norman, K.; Mukamal, K. Adherence to American Cancer Society Nutrition and Physical Activity Guidelines among Cancer Survivors. JAMA Oncol. 2024, 10, 789–792. [Google Scholar] [CrossRef] [Scilit]
- Wu, Y.P.; Yi, J.; McClellan, J.; Kim, J.; Tian, T.; Grahmann, B.; Kirchhoff, A.C.; Holton, A.; Wright, J. Barriers and Facilitators of Healthy Diet and Exercise among Adolescent and Young Adult Cancer Survivors: Implications for Behavioral Interventions. J. Adolesc. Young Adult Oncol. 2015, 4, 184–191. [Google Scholar] [CrossRef] [Scilit]
- Keaver, L.; McGough, A.M.; Du, M.; Chang, W.; Chomitz, V.; Allen, J.D.; Attai, D.J.; Gualtieri, L.; Zhang, F.F. Self-Reported Changes and Perceived Barriers to Healthy Eating and Physical Activity among Global Breast Cancer Survivors: Results from an Exploratory Online Novel Survey. J. Acad. Nutr. Diet. 2021, 121, 233–241.e8. [Google Scholar] [CrossRef] [Scilit]
- Keaver, L.; Richmond, J.; Rafferty, F.; Douglas, P. Sources of Nutrition Advice and Desired Nutrition Guidance in Oncology Care: Patient’s Perspectives. J. Hum. Nutr. Diet. 2023, 36, 434–442. [Google Scholar] [CrossRef] [Scilit]
- Johnston, E.A.; van der Pols, J.C.; Ekberg, S. Needs, Preferences, and Experiences of Adult Cancer Survivors in Accessing Dietary Information Post-Treatment: A Scoping Review. Eur. J. Cancer Care 2021, 30, e13381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beeken, R.J.; Williams, K.; Wardle, J.; Croker, H. “What About Diet?” A Qualitative Study of Cancer Survivors’ Views on Diet and Cancer and Their Sources of Information. Eur. J. Cancer Care 2016, 25, 774–783. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baguley, B.J.; Benna-Doyle, S.; Drake, S.; Curtis, A.; Stewart, J.; Loeliger, J. Access to Nutrition Services and Information after Active Cancer Treatment: A Mixed Methods Study. J. Cancer Surviv. 2024, 18, 176–185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ryding, H.G.; Mitchell, L.J.; Rigby, R.R.; Ball, L.; Hobby, J.; Williams, L.T. Effectiveness of Dietetic Care for Cancer Survivors in the Primary Care Setting: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J. Cancer Surviv. 2025, 19, 1694–1725. [Google Scholar] [CrossRef] [Scilit]
- Wu, L.M.; Chen, C.M.; Hsu, H.T.; Liu, Y.; Su, H.L. Tailored Education Enhances Healthy Behaviour Self-Efficacy in Childhood Cancer Survivors: A Randomised Controlled Study with a 4-Month Follow-Up. Eur. J. Cancer Care 2019, 28, e13063. [Google Scholar] [CrossRef] [Scilit]
- Thompson, J.; Silliman, K.; Clifford, D.E. Impact of an Early Education Multimedia Intervention in Managing Nutrition-Related Chemotherapy Side Effects: A Pilot Study. Springerplus 2013, 2, 179. [Google Scholar] [CrossRef] [Scilit]
- Croxford, S.; Stirling, E.; MacLaren, J.; McWhorter, J.W.; Frederick, L.; Thomas, O.W. Culinary Medicine or Culinary Nutrition? Defining Terms for Use in Education and Practice. Nutrients 2024, 16, 603. [Google Scholar] [CrossRef] [Scilit]
- Lang, R.D.; Jennings, M.C.; Lam, C.; Yeh, H.C.; Zhu, C.; Kumra, T. Community Culinary Workshops as a Nutrition Curriculum in a Preventive Medicine Residency Program. Med. Ed. Portal 2019, 15, 10859. [Google Scholar] [CrossRef] [Scilit]
- Hasan, B.; Thompson, W.G.; Almasri, J.; Wang, Z.; Lakis, S.; Prokop, L.J.; Hensrud, D.D.; Frie, K.S.; Wirtz, M.J.; Murad, A.L.; et al. The Effect of Culinary Interventions (Cooking Classes) on Dietary Intake and Behavioral Change: A Systematic Review and Evidence Map. BMC Nutr. 2019, 5, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marshall, H.; Albin, J. Food as Medicine: A Pilot Nutrition and Cooking Curriculum for Children of Participants in a Community-Based Culinary Medicine Class. Matern. Child Health J. 2021, 25, 54–58. [Google Scholar] [CrossRef] [Scilit]
- Garcia, A.L.; Reardon, R.; McDonald, M.; Vargas-Garcia, E.J. Community Interventions to Improve Cooking Skills and Their Effects on Confidence and Eating Behaviour. Curr. Nutr. Rep. 2016, 5, 315–322. [Google Scholar] [CrossRef] [Scilit]
- Muzaffar, H.; Guenther, E.; Bosse, O.; Nii-Aponsah, H. Effectiveness of Gardening-Only, Cooking-Only and Combined Cooking and Gardening Programs in Elementary Schools to Improve Fruit and Vegetable Intake: A Systematic Review. Nutrients 2023, 15, 3008. [Google Scholar] [CrossRef] [Scilit]
- Farmer, N.; Touchton-Leonard, K.; Ross, A. Psychosocial Benefits of Cooking Interventions: A Systematic Review. Health Educ. Behav. 2018, 45, 167–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Johnston, E.A.; Ayre, S.K.; Au-Yeung, Y.T.; Goodwin, B.C. A Scoping Review of Group Nutrition Education and Cooking Programs for People Affected by Cancer. J. Acad. Nutr. Diet. 2024, 124, 1302–1327. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Thomas, J.; Chandler, J.; Cumpston, M.; Li, T.; Page, M.J.; Welch, V.A. (Eds.) Cochrane Handbook for Systematic Reviews of Interventions; John Wiley & Sons: Hoboken, NJ, USA, 2024. [Google Scholar]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The Prisma 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Foecke Munden, E.; Kemp, M.; Guth, A.; Chang, A.M.; Worster, B.; Olarewaju, I.; Denton, M.; Rising, K.L. Patient-Important Needs and Goals Related to Nutrition Interventions During Cancer Treatment. Nutr. Cancer 2023, 75, 1143–1150. [Google Scholar] [CrossRef] [Scilit]
- Campbell, M.; McKenzie, J.E.; Sowden, A.; Katikireddi, S.V.; Brennan, S.E.; Ellis, S.; Hartmann-Boyce, J.; Ryan, R.; Shepperd, S.; Thomas, J.; et al. Synthesis without Meta-Analysis (Swim) in Systematic Reviews: Reporting Guideline. BMJ 2020, 368, l6890. [Google Scholar] [CrossRef] [Scilit]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. Rob 2: A Revised Tool for Assessing Risk of Bias in Randomised Trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.; Hernán, M.A.; Reeves, B.C.; Savović, J.; Berkman, N.D.; Viswanathan, M.; Henry, D.; Altman, D.G.; Ansari, M.T.; Boutron, I.; et al. Robins-I: A Tool for Assessing Risk of Bias in Non-Randomised Studies of Interventions. BMJ 2016, 355, i4919. [Google Scholar] [CrossRef] [Scilit]
- Zuniga, K.E.; Parma, D.L.; Muñoz, E.; Spaniol, M.; Wargovich, M.; Ramirez, A.G. Dietary Intervention among Breast Cancer Survivors Increased Adherence to a Mediterranean-Style, Anti-Inflammatory Dietary Pattern: The Rx for Better Breast Health Randomized Controlled Trial. Breast Cancer Res. Treat. 2019, 173, 145–154. [Google Scholar] [CrossRef] [Scilit]
- Sheppard, V.B.; Hicks, J.; Makambi, K.; Hurtado-de-Mendoza, A.; Demark-Wahnefried, W.; Adams-Campbell, L. The Feasibility and Acceptability of a Diet and Exercise Trial in Overweight and Obese Black Breast Cancer Survivors: The Stepping Stone Study. Contemp. Clin. Trials 2016, 46, 106–113. [Google Scholar] [CrossRef] [Scilit]
- Sheean, P.; Matthews, L.; Visotcky, A.; Banerjee, A.; Moosreiner, A.; Kelley, K.; Chitambar, C.R.; Papanek, P.E.; Stolley, M. Every Day Counts: A Randomized Pilot Lifestyle Intervention for Women with Metastatic Breast Cancer. Breast Cancer Res. Treat. 2021, 187, 729–741. [Google Scholar] [CrossRef] [Scilit]
- Parekh, N.; Jiang, J.; Buchan, M.; Meyers, M.; Gibbs, H.; Krebs, P. Nutrition Literacy among Cancer Survivors: Feasibility Results from the Healthy Eating and Living against Breast Cancer (Heal-Bca) Study: A Pilot Randomized Controlled Trial. J. Cancer Educ. 2018, 33, 1239–1249. [Google Scholar] [CrossRef] [Scilit]
- Morato-Martínez, M.; Santurino, C.; López-Plaza, B.; Arcos-Castellanos, L.; Clavero-Fraile, M.; Valero-Pérez, M.; Palma Milla, S.; Valero, M.; Gómez Candela, C. A Standardized, Integral Nutritional Intervention and Physical Activity Program Reduces Body Weight in Women Newly Diagnosed with Breast Cancer. Nutr. Hosp. 2021, 38, 575–584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miller, M.F.; Li, Z.; Habedank, M. A Randomized Controlled Trial Testing the Effectiveness of Coping with Cancer in the Kitchen, a Nutrition Education Program for Cancer Survivors. Nutrients 2020, 12, 3144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenlee, H.; Rillamas-Sun, E.; Yung, R.L.; Cobos, S.; Donzella, S.M.; Huang, Y.; Schattenkerk, L.; Ueland, K.; VanDoren, M.; Myers, S.A.; et al. Cook and Move for Your Life, an Ehealth Intervention for Women with Breast Cancer. NPJ Breast Cancer 2024, 10, 62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenlee, H.; Ogden Gaffney, A.; Aycinena, A.C.; Koch, P.; Contento, I.; Karmally, W.; Richardson, J.M.; Shi, Z.; Lim, E.; Tsai, W.Y.; et al. Long-Term Diet and Biomarker Changes after a Short-Term Intervention among Hispanic Breast Cancer Survivors: The ¡Cocinar Para Su Salud! Randomized Controlled Trial. Cancer Epidemiol. Biomark. Prev. 2016, 25, 1491–1502. [Google Scholar] [CrossRef] [Scilit]
- Greenlee, H.; Gaffney, A.O.; Aycinena, A.C.; Koch, P.; Contento, I.; Karmally, W.; Richardson, J.M.; Lim, E.; Tsai, W.Y.; Crew, K.; et al. ¡Cocinar Para Su Salud!: Randomized Controlled Trial of a Culturally Based Dietary Intervention among Hispanic Breast Cancer Survivors. J. Acad. Nutr. Diet. 2015, 115, 709–723.e3. [Google Scholar] [CrossRef] [Scilit]
- Spees, C.K.; Braun, A.C.; Hill, E.B.; Grainger, E.M.; Portner, J.; Young, G.S.; Kleinhenz, M.D.; Chitchumroonchokchai, C.; Clinton, S.K. Impact of a Tailored Nutrition and Lifestyle Intervention for Overweight Cancer Survivors on Dietary Patterns, Physical Activity, Quality of Life, and Cardiometabolic Profiles. J. Oncol. 2019, 2019, 1503195. [Google Scholar] [CrossRef] [Scilit]
- Raber, M.; Costigan, M.; Chandra, J.; Basen-Engquist, K. Cooking after Cancer: The Structure and Implementation of a Community-Based Cooking Program for Cancer Survivors. J. Cancer Educ. 2022, 37, 539–545. [Google Scholar] [CrossRef] [Scilit]
- Pritlove, C.; Capone, G.; Ramasamy, M.; Avery, L.; Fierini, D.; Ferguson, S.E.; Han, K.; Jones, J.M. Eliminating Digestive Irregularities Caused by Late Effects: A Pilot Study of an Innovative Culinary Nutrition Intervention for Reducing Gastrointestinal Toxicity in Gynecologic Cancer Patients Who Have Undergone Pelvic Radiotherapy. Nutrients 2024, 16, 4227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pritlove, C.; Capone, G.; Kita, H.; Gladman, S.; Maganti, M.; Jones, J.M. Cooking for Vitality: Pilot Study of an Innovative Culinary Nutrition Intervention for Cancer-Related Fatigue in Cancer Survivors. Nutrients 2020, 12, 2760. [Google Scholar] [CrossRef] [Scilit]
- Kondo, K.; Kim, S.; Noguchi, N.; Akiyama, R.; Murata, W.; Lee, B. Improvements in Psychological Distress in Patients Participating in a Cooking Programme Following Digestive Cancer Surgery: A Retrospective, Propensity Score-Matched Pilot Study. Br. J. Occup. Ther. 2023, 86, 615–621. [Google Scholar] [CrossRef] [Scilit]
- Jackson, M.K.; Ehlers, D.K.; Bilek, L.D.; Graeff-Armas, L.; Acquazzino, M.; Hébert, J.R.; Price, S.; Beaudoin, R.; Hanson, C.K. The Impact of a Virtual Educational Cooking Class on the Inflammatory Potential of Diet in Cancer Survivors. Appl. Sci. 2024, 14, 5332. [Google Scholar] [CrossRef] [Scilit]
- Huang, S.; Riccardi, D.; Pflanzer, S.; Redwine, L.S.; Gray, H.L.; Carson, T.L.; McDowell, M.; Thompson, Z.; Hubbard, J.J.; Pabbathi, S. Survivors Overcoming and Achieving Resiliency (Soar): Mindful Eating Practice for Breast Cancer Survivors in a Virtual Teaching Kitchen. Nutrients 2023, 15, 4205. [Google Scholar] [CrossRef] [Scilit]
- Golubić, M.; Schneeberger, D.; Kirkpatrick, K.; Bar, J.; Bernstein, A.; Weems, F.; Ehrman, J.; Perko, J.; Doyle, J.; Roizen, M. Comprehensive Lifestyle Modification Intervention to Improve Chronic Disease Risk Factors and Quality of Life in Cancer Survivors. J. Altern. Complement. Med. 2018, 24, 1085–1091. [Google Scholar] [CrossRef] [Scilit]
- Barak-Nahum, A.; Haim, L.B.; Ginzburg, K. When Life Gives You Lemons: The Effectiveness of Culinary Group Intervention among Cancer Patients. Soc. Sci. Med. 2016, 166, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Allen-Winters, S.; Wakefield, D.; Gaudio, E.; Moore, S.; Boone, K.; Morris, S.; Schwartz, D.L. “Eat to Live”-Piloting a Culinary Medicine Program for Head & Neck Radiotherapy Patients. Support. Care Cancer 2020, 28, 2949–2957. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rock, C.L.; Thomson, C.A.; Sullivan, K.R.; Howe, C.L.; Kushi, L.H.; Caan, B.J.; Neuhouser, M.L.; Bandera, E.V.; Wang, Y.; Robien, K.; et al. American Cancer Society Nutrition and Physical Activity Guideline for Cancer Survivors. CA Cancer J. Clin. 2022, 72, 230–262. [Google Scholar] [CrossRef] [Scilit]
- American Institute for Cancer Research. Cancer Prevention. Available online: https://www.aicr.org/cancer-prevention/ (accessed on 23 October 2025).
- Contento, I.R. Nutrition Education: Linking Research, Theory, and Practice; Jones & Barlett Learning: Burlington, MA, USA, 2007. [Google Scholar]
- Bandura, A. Human Agency in Social Cognitive Theory. Am. Psychol. 1989, 44, 1175–1184. [Google Scholar] [CrossRef]
- Prochaska, J.O.; Velicer, W.F. The Transtheoretical Model of Health Behavior Change. Am. J. Health Promot. 1997, 12, 38–48. [Google Scholar] [CrossRef] [Scilit]
- Aycinena, A.C.; Jennings, K.A.; Gaffney, A.O.; Koch, P.A.; Contento, I.R.; Gonzalez, M.; Guidon, E.; Karmally, W.; Hershman, D.; Greenlee, H. Cocinar Para Su Salud! Development of a Culturally Based Nutrition Education Curriculum for Hispanic Breast Cancer Survivors Using a Theory-Driven Procedural Model. Health Educ. Behav. 2017, 44, 13–22. [Google Scholar] [CrossRef] [Scilit]
- Ueland, K.; Sanchez, S.C.; Rillamas-Sun, E.; Shen, H.; Schattenkerk, L.; Garcia, G.; VanDoren, M.; Myers, S.A.; Santiago-Torres, M.; Di, C.; et al. A Digital Health Intervention to Improve Nutrition and Physical Activity in Breast Cancer Survivors: Rationale and Design of the Cook and Move for Your Life Pilot and Feasibility Randomized Controlled Trial. Contemp. Clin. Trials 2022, 123, 106993. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stacey, F.G.; James, E.L.; Chapman, K.; Courneya, K.S.; Lubans, D.R. A Systematic Review and Meta-Analysis of Social Cognitive Theory-Based Physical Activity and/or Nutrition Behavior Change Interventions for Cancer Survivors. J. Cancer Surviv. 2015, 9, 305–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spark, L.C.; Reeves, M.M.; Fjeldsoe, B.S.; Eakin, E.G. Physical Activity and/or Dietary Interventions in Breast Cancer Survivors: A Systematic Review of the Maintenance of Outcomes. J. Cancer Surviv. 2013, 7, 74–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flannery, M. Self-Determination Theory: Intrinsic Motivation and Behavioral Change. Oncol. Nurs. Forum 2017, 44, 155–156. [Google Scholar] [CrossRef] [Scilit]
- Bandura, A. Self-Efficacy: Toward a Unifying Theory of Behavioral Change. Psychol. Rev. 1977, 84, 191–215. [Google Scholar] [CrossRef]
- Graffigna, G.; Barello, S. Spotlight on the Patient Health Engagement Model (Phe Model): A Psychosocial Theory to Understand People’s Meaningful Engagement in Their Own Health Care. Patient Prefer. Adherence 2018, 12, 1261–1271. [Google Scholar] [CrossRef] [Scilit]
- Borek, A.J.; Abraham, C. How Do Small Groups Promote Behaviour Change? An Integrative Conceptual Review of Explanatory Mechanisms. Appl. Psychol. Health Wellbeing 2018, 10, 30–61. [Google Scholar] [CrossRef] [Scilit]
- Golant, M.; Thiboldeaux, K. The Wellness Community’s Integrative Model of Evidence-Based Psychosocial Programs, Services, and Interventions. In Psychooncology; Oxford University Press: Oxford, UK, 2010. [Google Scholar] [CrossRef] [Scilit]
- Leszcz, M.; Goodwin, P.J. The Rationale and Foundations of Group Psychotherapy for Women with Metastatic Breast Cancer. Int. J. Group Psychother. 1998, 48, 245–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aranceta Bartrina, J.; Grupo Colaborativo de la Sociedad Espanola de Nutricion, C.; Arija Val, V.V.; Maiz Aldalur, E.; Martinez de Victoria Munoz, E.; Ortega Anta, R.M.; Perez-Rodrigo, C.; Quiles Izquierdo, J.; Rodriguez Martin, A.; Roman Vinas, B.; et al. Dietary Guidelines for the Spanish Population (Senc, Diciembre 2016); the New Graphic Icon of Healthy Food. Nutr. Hosp. 2016, 33, 1–48. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. WHO Guidelines on Physical Activity and Sedentary Behaviour; World Health Organization: Geneva, Switzerland, 2020. [Google Scholar]
- Pinto, B.M.; Floyd, A. Theories Underlying Health Promotion Interventions among Cancer Survivors. Semin. Oncol. Nurs. 2008, 24, 153–163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ajzen, I. The Theory of Planned Behavior. Organ. Behav. Hum. Decis. Process 1991, 50, 179–211. [Google Scholar] [CrossRef] [Scilit]
- Bandura, A. Health Promotion by Social Cognitive Means. Health Educ. Behav. 2004, 31, 143–164. [Google Scholar] [CrossRef] [Scilit]
- Ramirez, A.G.; Parma, D.L.; Munoz, E.; Mendoza, K.D.; Harb, C.; Holden, A.E.C.; Wargovich, M. An Anti-Inflammatory Dietary Intervention to Reduce Breast Cancer Recurrence Risk: Study Design and Baseline Data. Contemp. Clin. Trials 2017, 57, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Skouroliakou, M.; Grosomanidis, D.; Massara, P.; Kostara, C.; Papandreou, P.; Ntountaniotis, D.; Xepapadakis, G. Serum Antioxidant Capacity, Biochemical Profile and Body Composition of Breast Cancer Survivors in a Randomized Mediterranean Dietary Intervention Study. Eur. J. Nutr. 2018, 57, 2133–2145. [Google Scholar] [CrossRef] [Scilit]
- Sureda, A.; Bibiloni, M.D.M.; Julibert, A.; Bouzas, C.; Argelich, E.; Llompart, I.; Pons, A.; Tur, J.A. Adherence to the Mediterranean Diet and Inflammatory Markers. Nutrients 2018, 10, 62. [Google Scholar] [CrossRef] [Scilit]
- Mazzocchi, M.; Brasili, C.; Sandri, E. Trends in Dietary Patterns and Compliance with World Health Organization Recommendations: A Cross-Country Analysis. Public Health Nutr. 2008, 11, 535–540. [Google Scholar] [CrossRef] [Scilit]
- Michie, S.; Richardson, M.; Johnston, M.; Abraham, C.; Francis, J.; Hardeman, W.; Eccles, M.P.; Cane, J.; Wood, C.E. The Behavior Change Technique Taxonomy (V1) of 93 Hierarchically Clustered Techniques: Building an International Consensus for the Reporting of Behavior Change Interventions. Ann. Behav. Med. 2013, 46, 81–95. [Google Scholar] [CrossRef] [Scilit]
- Serra-Majem, L.; Roman, B.; Estruch, R. Scientific Evidence of Interventions Using the Mediterranean Diet: A Systematic Review. Nutr. Rev. 2006, 64, S27–S47. [Google Scholar] [CrossRef] [Scilit]
- Harris, M.A.; Oelbaum, R.; Flomo, D. State of the Art Reviews: Changing and Adhering to Lifestyle Changes: What Are the Keys? Am. J. Lifestyle Med. 2007, 1, 214–219. [Google Scholar] [CrossRef] [Scilit]
- Porciello, G.; Montagnese, C.; Crispo, A.; Grimaldi, M.; Libra, M.; Vitale, S.; Palumbo, E.; Pica, R.; Calabrese, I.; Cubisino, S.; et al. Mediterranean Diet and Quality of Life in Women Treated for Breast Cancer: A Baseline Analysis of Dedica Multicentre Trial. PLoS ONE 2020, 15, e0239803. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Warren, J.M.; Smith, N.; Ashwell, M. A Structured Literature Review on the Role of Mindfulness, Mindful Eating and Intuitive Eating in Changing Eating Behaviours: Effectiveness and Associated Potential Mechanisms. Nutr. Res. Rev. 2017, 30, 272–283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morris, M.C.; Tangney, C.C.; Wang, Y.; Sacks, F.M.; Barnes, L.L.; Bennett, D.A.; Aggarwal, N.T. Mind Diet Slows Cognitive Decline with Aging. Alzheimers Dement. 2015, 11, 1015–1022. [Google Scholar] [CrossRef] [Scilit]
- van den Brink, A.C.; Brouwer-Brolsma, E.M.; Berendsen, A.A.M.; van de Rest, O. The Mediterranean, Dietary Approaches to Stop Hypertension (Dash), and Mediterranean-Dash Intervention for Neurodegenerative Delay (Mind) Diets Are Associated with Less Cognitive Decline and a Lower Risk of Alzheimer’s Disease—A Review. Adv. Nutr. 2019, 10, 1040–1065. [Google Scholar] [CrossRef] [Scilit]
- Morris, T.H. Experiential Learning—A Systematic Review and Revision of Kolb’s Model. Interact. Learn. Environ. 2020, 28, 1064–1077. [Google Scholar] [CrossRef] [Scilit]
- Zick, S.M.; Colacino, J.; Cornellier, M.; Khabir, T.; Surnow, K.; Djuric, Z. Fatigue Reduction Diet in Breast Cancer Survivors: A Pilot Randomized Clinical Trial. Breast Cancer Res. Treat. 2017, 161, 299–310. [Google Scholar] [CrossRef] [Scilit]
- Michie, S.; Ashford, S.; Sniehotta, F.F.; Dombrowski, S.U.; Bishop, A.; French, D.P. A Refined Taxonomy of Behaviour Change Techniques to Help People Change Their Physical Activity and Healthy Eating Behaviours: The Calo-Re Taxonomy. Psychol. Health 2011, 26, 1479–1498. [Google Scholar] [CrossRef] [Scilit]
- Hollywood, L.; Surgenor, D.; Reicks, M.; McGowan, L.; Lavelle, F.; Spence, M.; Raats, M.; McCloat, A.; Mooney, E.; Caraher, M.; et al. Critical Review of Behaviour Change Techniques Applied in Intervention Studies to Improve Cooking Skills and Food Skills among Adults. Crit. Rev. Food Sci. Nutr. 2018, 58, 2882–2895. [Google Scholar] [CrossRef] [Scilit]
- Eckel, R.H.; Jakicic, J.M.; Ard, J.D.; de Jesus, J.M.; Houston Miller, N.; Hubbard, V.S.; Lee, I.M.; Lichtenstein, A.H.; Loria, C.M.; Millen, B.E.; et al. 2013 Aha/Acc Guideline on Lifestyle Management to Reduce Cardiovascular Risk: A Report of the American College of Cardiology/American Heart Association Task Force on Practice Guidelines. J. Am. Coll. Cardiol. 2014, 63, 2960–2984. [Google Scholar] [CrossRef] [Scilit]
- Spees, C.K.; Hill, E.B.; Grainger, E.M.; Buell, J.L.; White, S.E.; Kleinhenz, M.D.; Clinton, S.K. Feasibility, Preliminary Efficacy, and Lessons Learned from a Garden-Based Lifestyle Intervention for Cancer Survivors. Cancer Control 2016, 23, 302–310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hartmann, C.; Dohle, S.; Siegrist, M. A Self-Determination Theory Approach to Adults’ Healthy Body Weight Motivation: A Longitudinal Study Focussing on Food Choices and Recreational Physical Activity. Psychol. Health 2015, 30, 924–948. [Google Scholar] [CrossRef] [Scilit]
- Marchetti, P.; Fovez, Q.; Germain, N.; Khamari, R.; Kluza, J. Mitochondrial Spare Respiratory Capacity: Mechanisms, Regulation, and Significance in Non-Transformed and Cancer Cells. FASEB J. 2020, 34, 13106–13124. [Google Scholar] [CrossRef] [Scilit]
- Terranova, C.O.; Protani, M.M.; Reeves, M.M. Overall Dietary Intake and Prognosis after Breast Cancer: A Systematic Review. Nutr. Cancer 2018, 70, 153–163. [Google Scholar] [CrossRef] [Scilit]
- Raji Lahiji, M.; Vafa, S.; de Souza, R.J.; Zarrati, M.; Sajadian, A.; Razmpoosh, E.; Jaberzadeh, S. Effect of Dietary-Based Lifestyle Modification Approaches on Anthropometric Indices and Dietary Intake Parameters in Women with Breast Cancer: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Adv. Nutr. 2022, 13, 1974–1988. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Micek, A.; Godos, J.; Brzostek, T.; Gniadek, A.; Favari, C.; Mena, P.; Libra, M.; Del Rio, D.; Galvano, F.; Grosso, G. Dietary Phytoestrogens and Biomarkers of Their Intake in Relation to Cancer Survival and Recurrence: A Comprehensive Systematic Review with Meta-Analysis. Nutr. Rev. 2021, 79, 42–65. [Google Scholar] [CrossRef] [Scilit]
- O’Callaghan, N.; Douglas, P.; Keaver, L. A Qualitative Study into Cancer Survivors’ Relationship with Nutrition Post-Cancer Treatment. J. Hum. Nutr. Diet. 2023, 36, 406–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leung, M.W.; Yen, I.H.; Minkler, M. Community Based Participatory Research: A Promising Approach for Increasing Epidemiology’s Relevance in the 21st Century. Int. J. Epidemiol. 2004, 33, 499–506. [Google Scholar] [CrossRef] [Scilit]
- Collins, S.E.; Clifasefi, S.L.; Stanton, J.; The Leap Advisory Board; Straits, K.J.E.; Gil-Kashiwabara, E.; Rodriguez Espinosa, P.; Nicasio, A.V.; Andrasik, M.P.; Hawes, S.M.; et al. Community-Based Participatory Research (Cbpr): Towards Equitable Involvement of Community in Psychology Research. Am. Psychol. 2018, 73, 884–898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Monllor-Tormos, A.; Garcia-Vigara, A.; Morgan, O.; Garcia-Perez, M.A.; Mendoza, N.; Tarin, J.J.; Cano, A. Mediterranean Diet for Cancer Prevention and Survivorship. Maturitas 2023, 178, 107841. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khalifa, A.; Guijarro, A.; Nencioni, A. Advances in Diet and Physical Activity in Breast Cancer Prevention and Treatment. Nutrients 2024, 16, 2262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dinas, P.C.; On Behalf of the Students of Module Introduction to Systematic Reviews; Karaventza, M.; Liakou, C.; Georgakouli, K.; Bogdanos, D.; Metsios, G.S. Combined Effects of Physical Activity and Diet on Cancer Patients: A Systematic Review and Meta-Analysis. Nutrients 2024, 16, 1749. [Google Scholar] [CrossRef] [Scilit]
- Bye, A.; Sandmael, J.A.; Stene, G.B.; Thorsen, L.; Balstad, T.R.; Solheim, T.S.; Pripp, A.H.; Oldervoll, L.M. Exercise and Nutrition Interventions in Patients with Head and Neck Cancer During Curative Treatment: A Systematic Review and Meta-Analysis. Nutrients 2020, 12, 3233. [Google Scholar] [CrossRef] [Scilit]
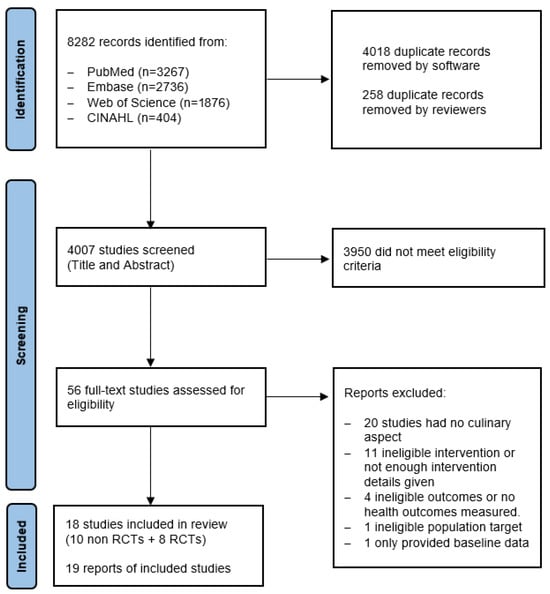
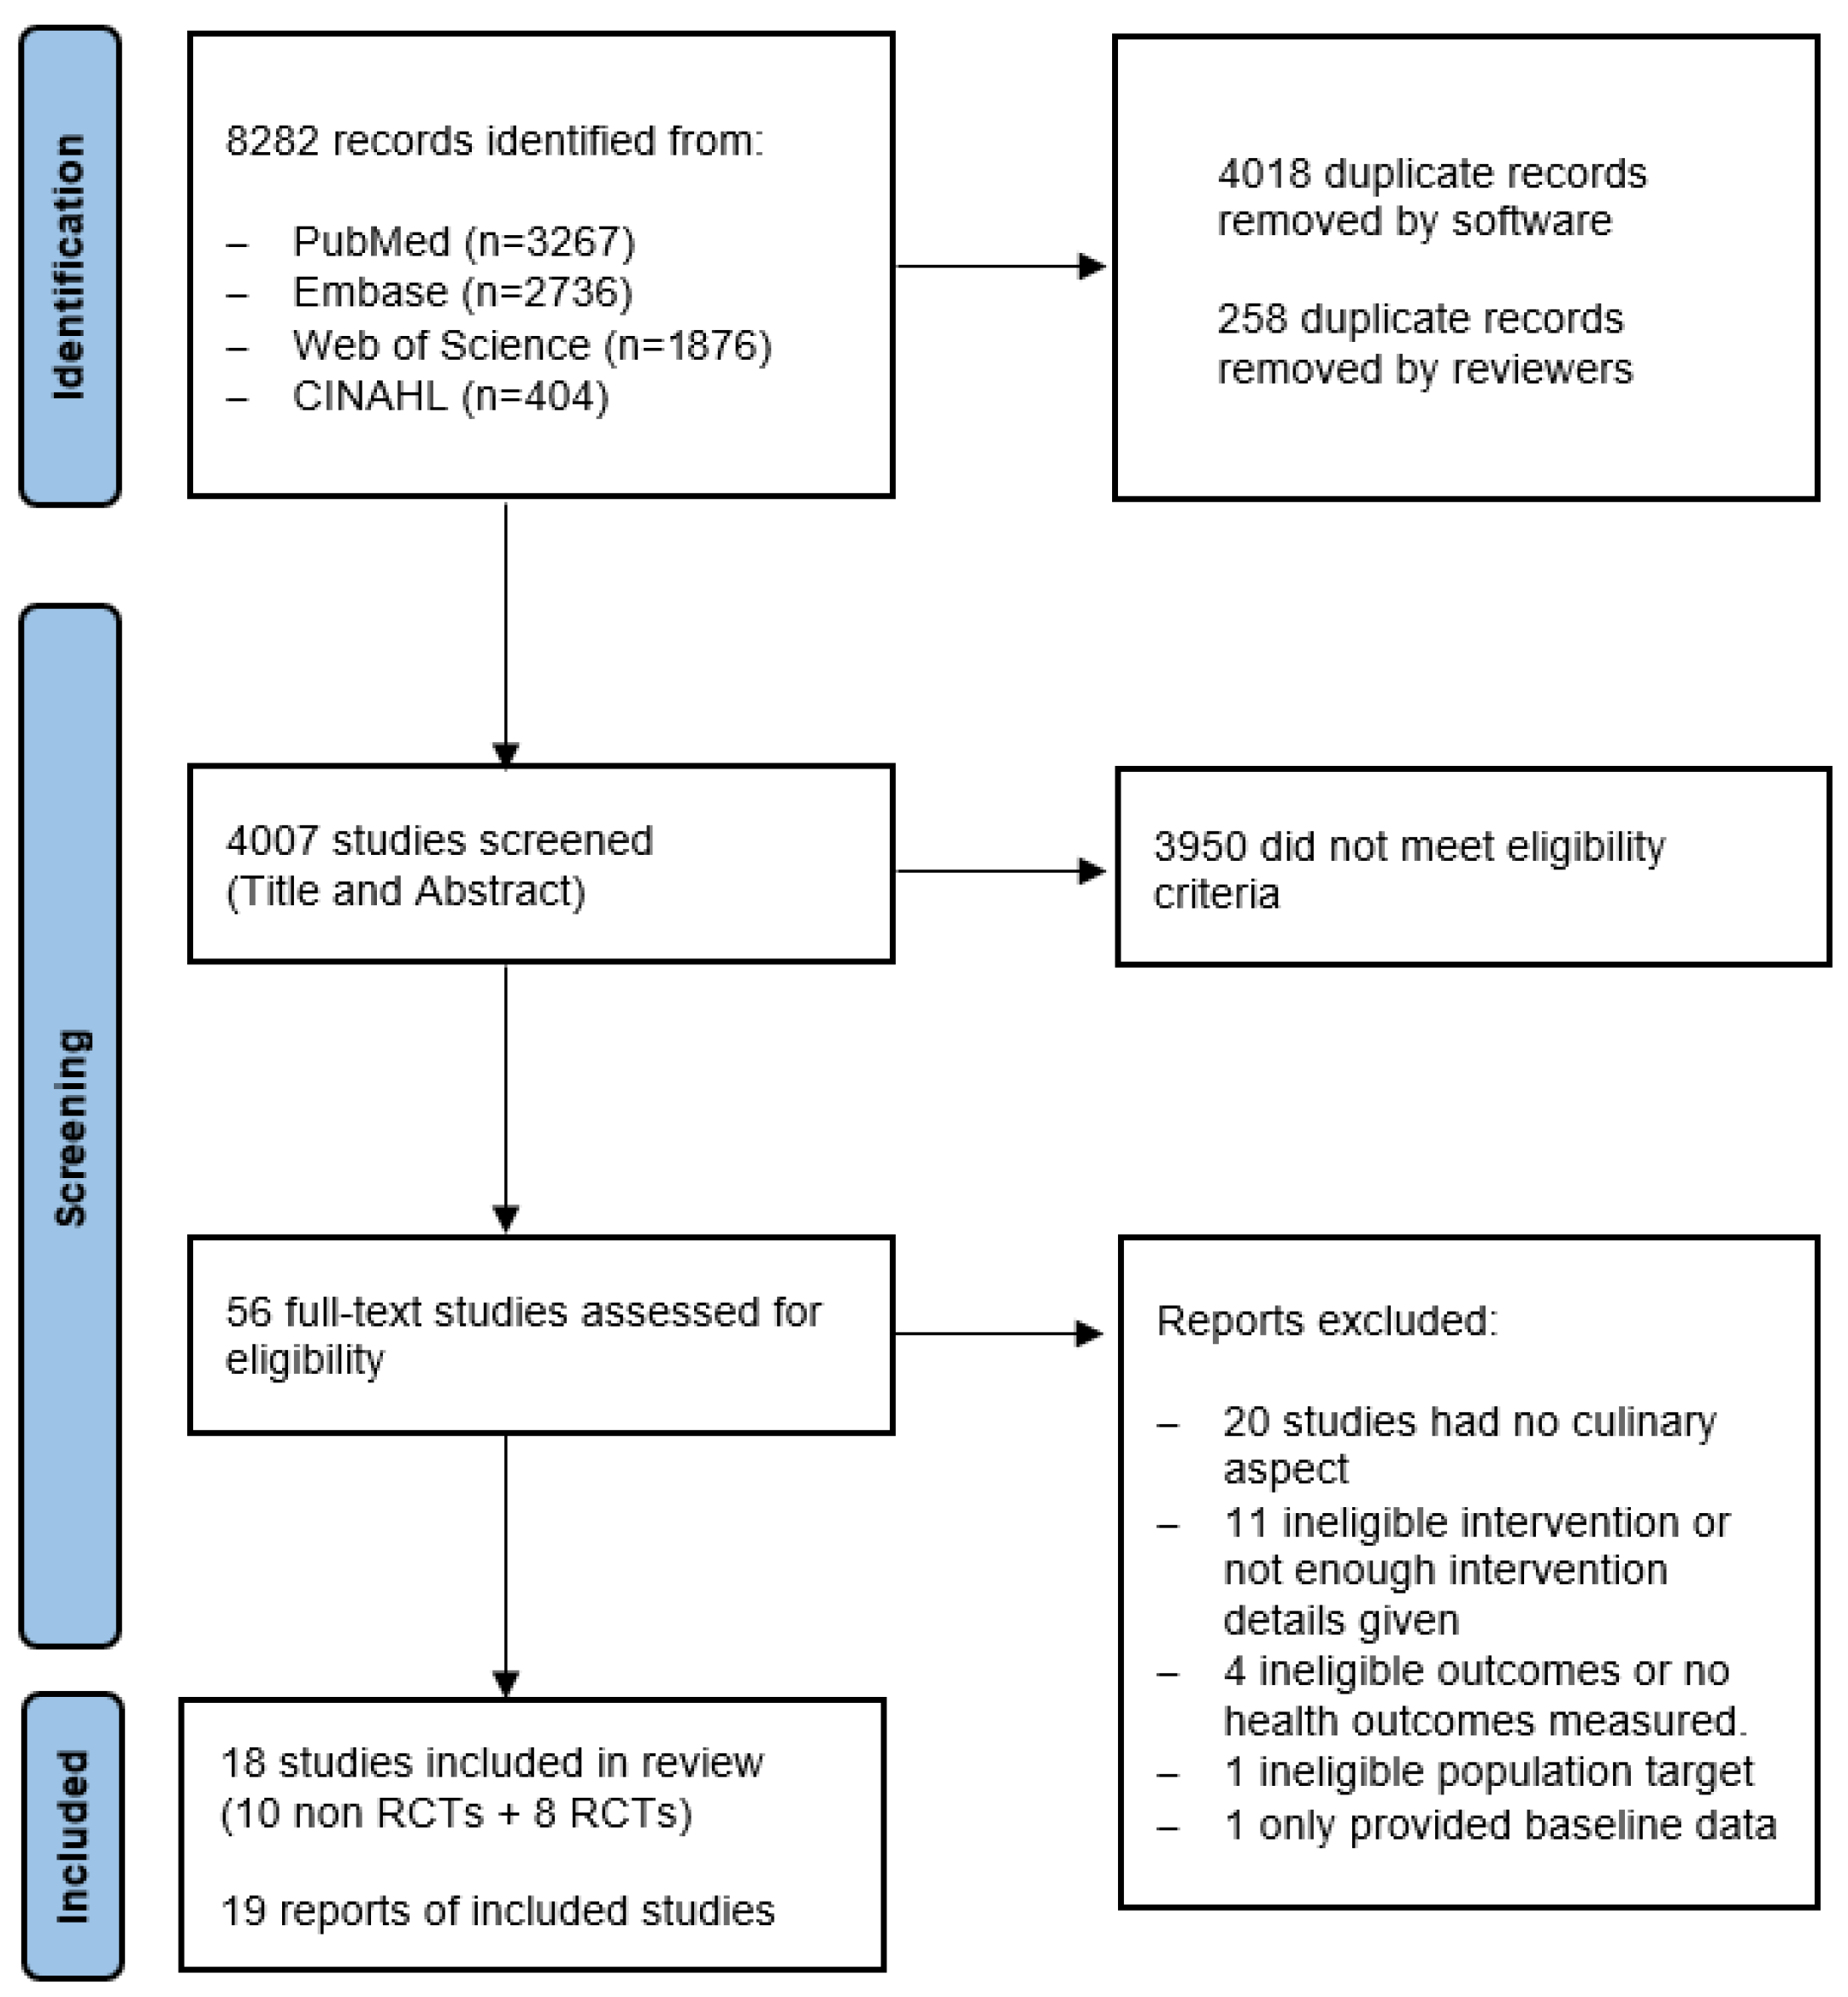

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.