


Abstract
Adolescents and young adults (AYA) with acute lymphoblastic leukemia (ALL) have significantly worse outcomes than their younger counterparts. Current treatment guidelines rely mostly on non-randomized retrospective studies. We performed a systematic review of studies published within the last 15 years comparing pediatric-inspired regimens (PIR) versus adult-type regimens or performing an age-stratified analysis of outcomes in the AYA population. Due to the heterogeneity of data, a meta-analysis was not possible. However, the gathered data show a trend toward improvement in outcomes and an acceptable toxicity profile in patients treated with PIRs compared to conventional adult-type regimens. There is still room for further improvement, as older patients within the AYA population tend to perform poorly with PIR or conventional adult-type chemotherapy. Further randomized studies are needed to develop an optimal treatment strategy for AYA with ALL.
1. Introduction
While the long-term prognosis of children with acute lymphoblastic leukemia (ALL) has improved in recent decades, the outcome of adolescents and young adults (AYA) patients aged from 15 to 39 years remains markedly worse than that of their younger counterparts [1]. Based on population-based data from the EUROCARE-5 study, which monitors the survival of cancer patients in Europe, the 5-year relative survival of children aged 0–14 years is 85.8%. In comparison, the relative survival rates in the adolescent (15–19 years) and young adult (20–39 years) age groups were 62.2% and 52.8%, respectively [2].
Due to the broad age range of the AYA population, these patients are treated in pediatric as well as adult settings with a myriad of different protocols. However, treating ALL in this age group is a challenge not only due to an increased incidence of unfavorable cytogenetic aberrations but also due to unique psychosocial circumstances as well as higher treatment-related toxicity compared to younger children [3]. Based on the current data and expert opinion guidelines, the best therapeutic approach for an AYA patient with ALL is to use a pediatric-inspired regimen (PIR) [3,4,5,6,7]. Compared to conventional adult-type protocols, PIRs tend to have more therapy elements and encompass higher cumulative doses of asparaginase, vincristine, and steroids, in addition to a generally longer maintenance phase [5]. The most prominent examples of PIR are protocols incorporating a Dana–Faber Cancer Institute (DFCI) or Berlin–Frankfurt–Münster (BFM) study group backbone. However, data on treatment strategies in AYA and ALL are limited due to the lack of randomized comparative studies and thus prone to bias, making interpretation and comparison difficult.
The purpose of this systematic review is to provide a comprehensive synthesis of published comparative studies examining the outcomes and toxicity of AYA patients treated for ALL with PIR versus conventional adult regimens. Furthermore, we would like to summarize the available data on age-stratified outcomes and adverse events (AE) in AYA patients receiving PIR treatment.
2. Materials and Methods
We conducted the systematic literature search according to the PRISMA guidelines in PubMed in November 2022 [8]. The search strategy was built around the following three concepts: “acute lymphoblastic leukemia”, “adolescents and young adults”, and “treatment protocol/strategy” (Supplementary Data). Publications on myeloid leukemia and those with animal models were omitted through the search strategy. We restricted the search to studies published between November 2007 and November 2022. The inclusion criteria were given through the PICO framework [8]. The population included AYA cancer patients diagnosed with ALL. The AYA population was defined as patients diagnosed between the ages of 15 and 39 years, or at least 75% of the study population had to be within this range. The intervention corresponded to the treatment protocol, either a pediatric, pediatric-inspired, or adult protocol. Depending on the data provided in the eligible publications, we aimed to compare either adult-type versus pediatric/pediatric-inspired protocols or pediatric/pediatric-inspired protocols stratified by different age categories. The envisaged outcomes included survival (e.g., overall (OS) or event-free survival (EFS)), toxicity (e.g., toxic death, admission to the ICU), or reasons for the protocols used. However, the final reporting of these outcomes depended on whether the data were provided in the eligible publications or not.
Two authors performed the title and abstract screening (MO, AZ) and full-text screening (AZ, PF) each. Discrepancies between reviewers one and two were solved by a third reviewer (KS) using the same criteria. We extracted the data from the eligible studies onto a standard sheet, including the first author, year of publication, study design, patients’ characteristics, information on the treatment protocol, and the outcomes assessed. We assessed the quality, relevance, and reliability of each included study by using the appropriate critical appraisal tool from the Joanna Briggs Institute (JBI) (https://jbi.global/critical-appraisal-tools) (accessed on 15 October 2022), including the checklists for cohort studies. Since the tools from the Joanna Briggs Institute do not have predefined categorizations, we defined a classification with three categories. If all criteria of the respective checklist were fulfilled, we assigned the study “Quality 1”. If one or two criteria were not fulfilled, we assigned the study to “Quality 2”. If three or more criteria were not fulfilled, the study was assigned “Quality 3”.
The protocol for this review was published on Prospero (https://www.crd.york.ac.uk/prospero; ID: CRD42022384667) (accessed on 27 December 2022).
3. Results
3.1. Description of Studies and Regimens
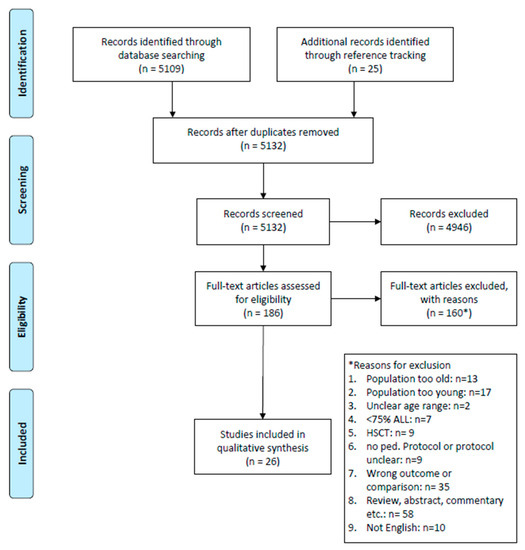
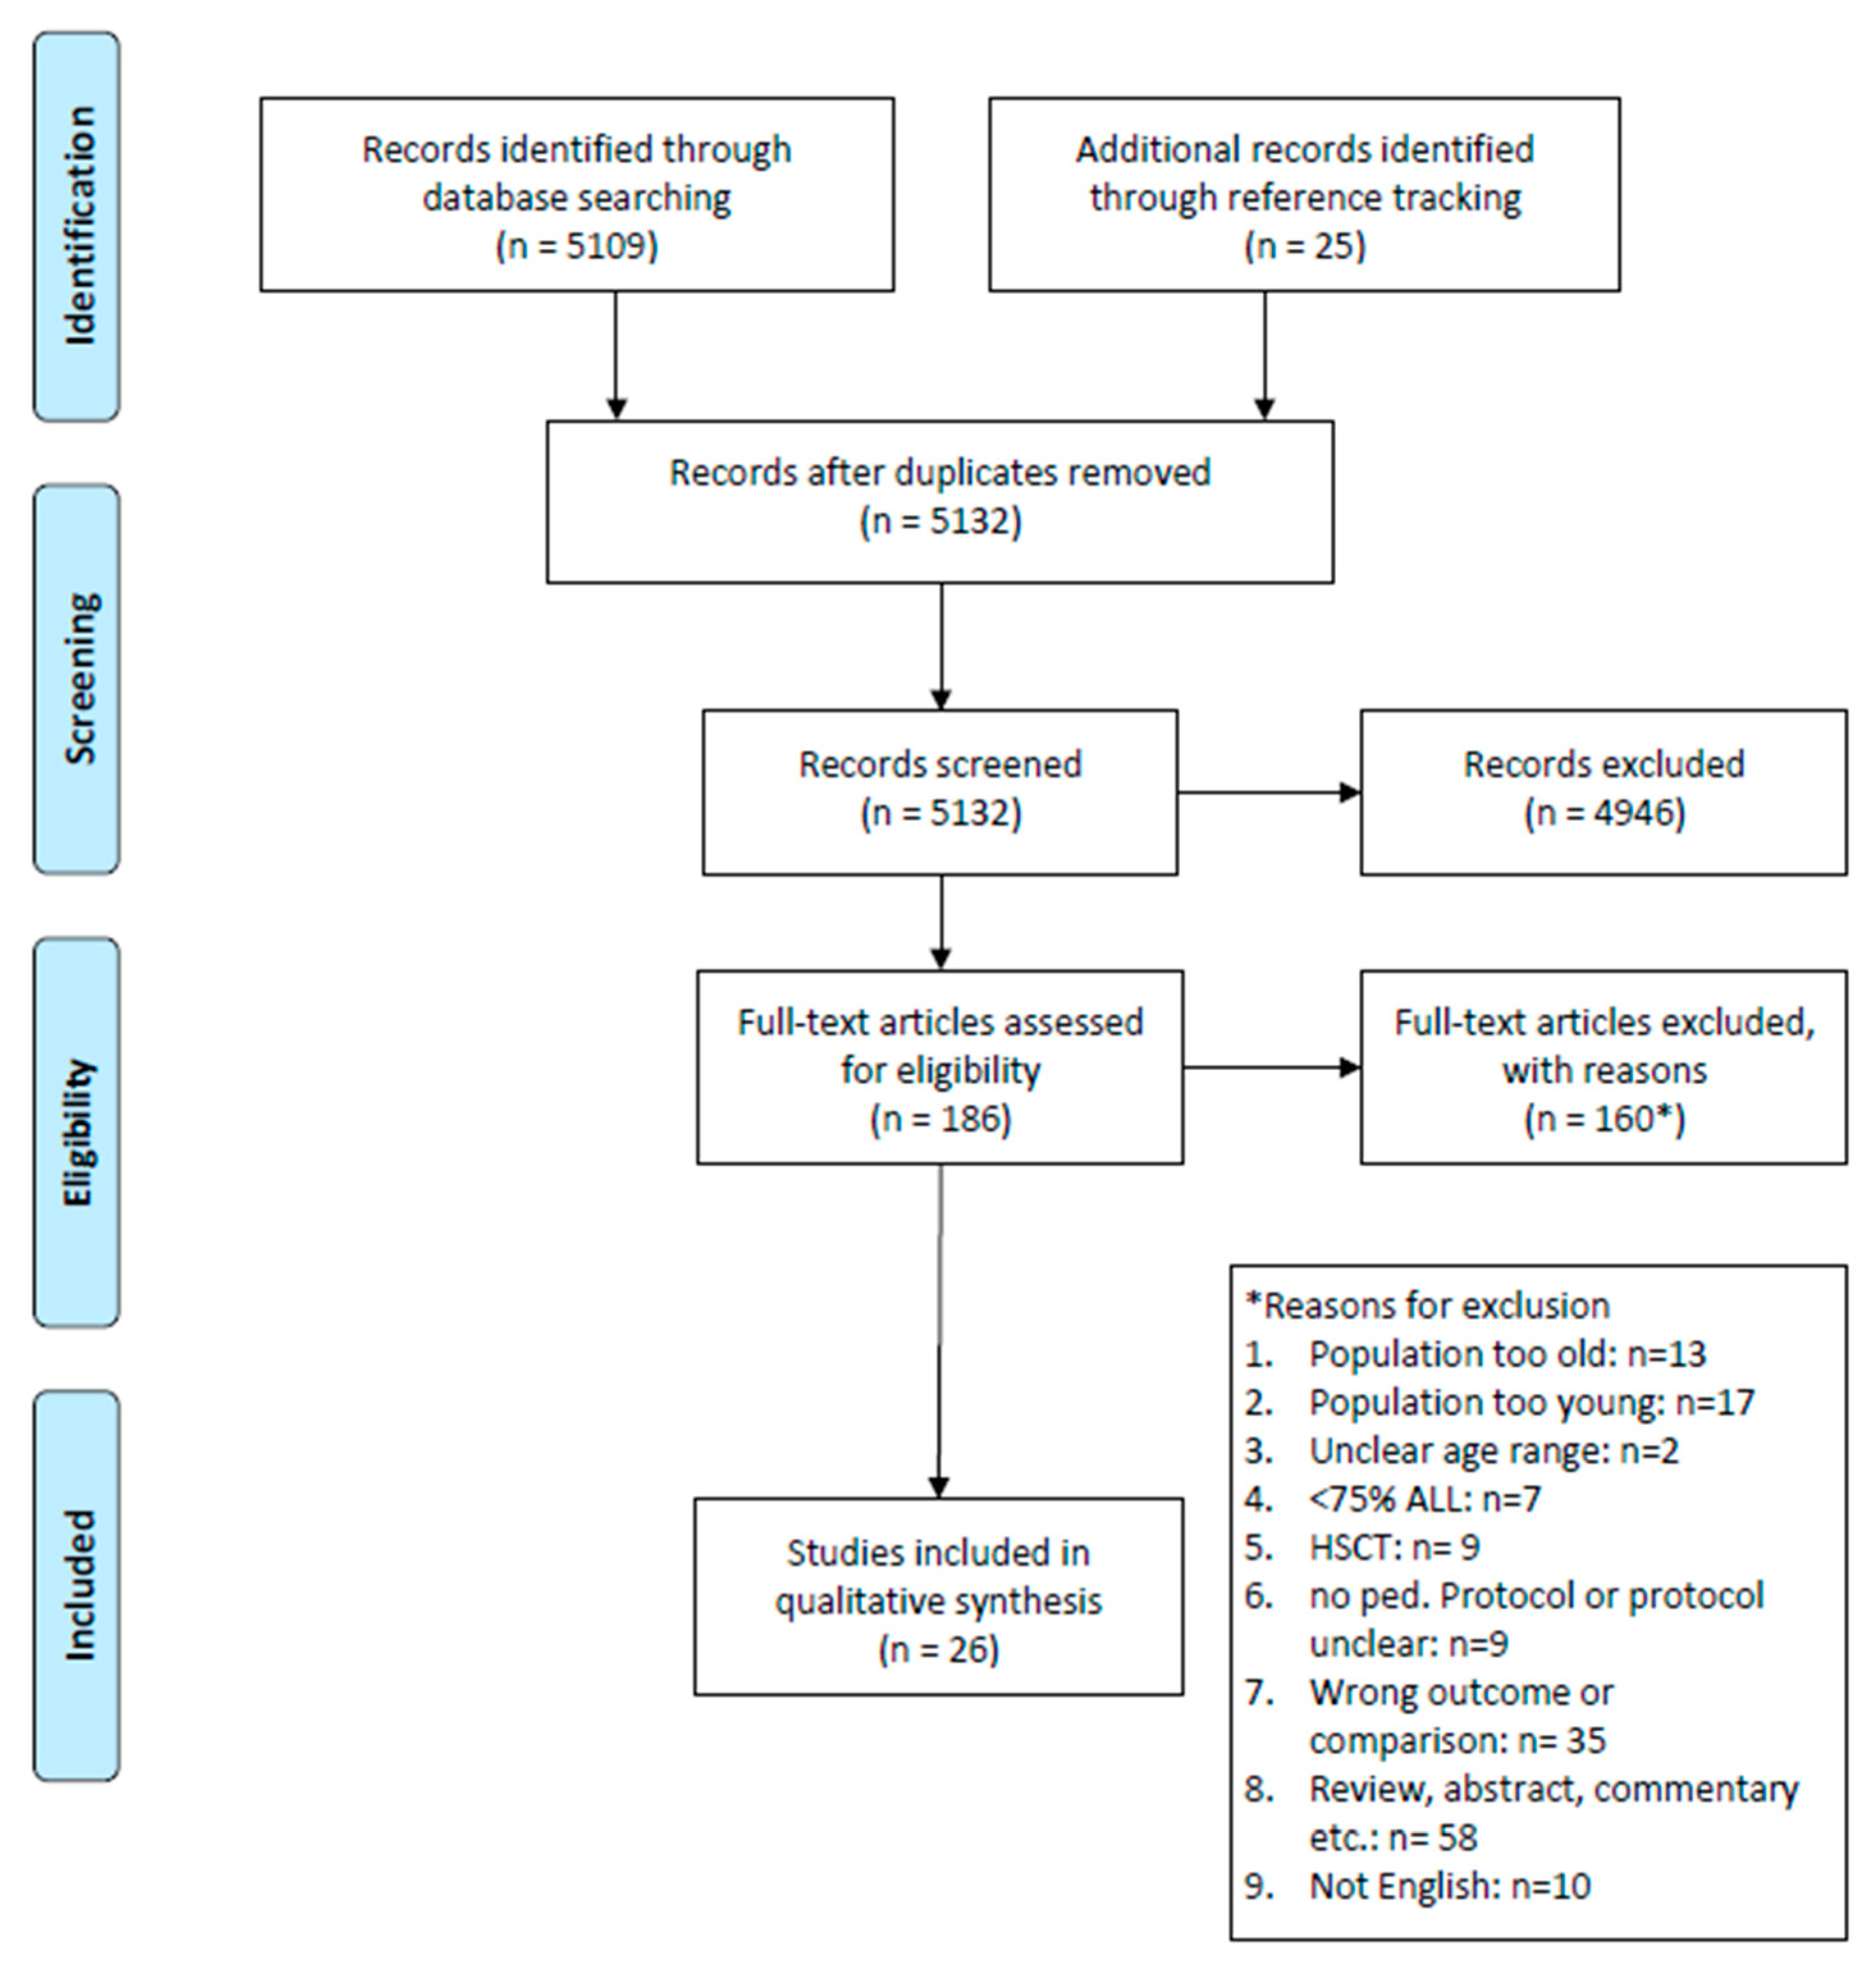
The literature search identified 5132 publications. A total of 168 potentially relevant full-text articles were retrieved for further evaluation. Among these, 26 met the inclusion criteria for our systematic review (Figure 1, Table 1, Supplementary Data) [9,10,11,12,13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34]. Fifteen of the included studies (57%) had a prospective design [9,14,16,19,20,22,23,25,26,27,28,29,30,32,33].
Figure 1.
PRISMA flow diagram.
Table 1.
Characteristics of the studies included in this review.
Twelve studies comparing the outcomes and/or toxicity of PIR vs. conventional adult-type regimens are summarized in Table 2 [10,11,12,15,17,18,21,22,24,29,30,31]. None of the studies were randomized controlled trials. Four studies included patients given PIR that were compared with historical controls receiving conventional adult regimens [12,24,29,30]. Others compared patients treated with PIR and adult protocols during approximately the same time periods. One study did not use any risk-adapted treatment for PIR; the others used some sort of risk stratification of patients [18].
Table 2.
Main findings of studies comparing outcomes and toxicity in adolescents and young adult patients receiving a pediatric/pediatric-inspired (PIR) or adult regimen.
Five studies had a median follow-up shorter than two years for at least one analyzed group [12,15,17,18,31], and one study did not specify the duration of follow-up [21]. Additionally, two studies had significantly longer follow-ups for the patients treated with conventional adult protocols [12,24], whereas another had significantly longer follow-ups for the patients treated with PIR [15]. In most studies, the compared groups had well-matched age distributions. However, in two studies, the group receiving the conventional adult treatment was slightly older than the PIR group [21,31], whereas the opposite was true for one study [12].
Nineteen studies, summarized in Table 3, describe the treatment outcomes or toxicities in different age groups, either within the defined AYA range or as a comparison to younger or older patients. Three studies have a shorter follow-up than 2 years [12,17,19], while one has a significantly shorter follow-up for the oldest analyzed age group [32]. Two studies contain data gathered during two different periods [9,12].
Table 3.
Main results of studies comparing age-stratified outcomes and toxicity in adolescents and young adult patients receiving a pediatric-inspired (PIR) or adult regimen.
The regimens of both PIR and conventional adult protocols were different between the studies. The dosing regimens are described in detail in the corresponding articles. However, in general, PIR had higher cumulative dosages of chemotherapeutic agents such as corticosteroids, vincristine, and methotrexate and incorporated more asparaginase. Regarding the studied populations, the type of ALL (B-ALL, T-ALL, or BCR–ABL positive ALL) differed between the studies but was consistent within each study (Table 1). Quality appraisal according to the JBI quality assessment scale for cohort studies is shown in Table 1.
3.2. Treatment Outcomes and Toxicity in AYA Patients When Treated with PIR versus Conventional Adult Regimens
A statistically significant improvement in OS in patients given PIR compared to conventional adult protocols was reported in 6 out of 11 studies (Table 2) [10,11,12,17,21,22]. Even in the five studies that found that OS did not statistically significantly differ between the two types of treatment strategies, the reported OS for PIR tended to be higher than in the adult-type regimens [18,24,29,30,31].
The limited data and their accuracy did not allow us to perform a meta-analysis to assess the impact of the treatment strategy used. Even the consultation with the guidance of Tierney JF et al. did not allow a calculation of the hazard ratios (HR) [35]. Only three studies report HRs, but the HRs were given for different time points (2 years, 3 years, and 5 years), which further impeded performing a meta-analysis [17,21,31].
The clinical endpoints other than OS were very heterogeneous among the studies (Table 2). Nevertheless, a similar trend can be seen with the reported relapse rates, event-free survival (EFS), relapse-free survival (RFS), and disease-free survival (DFS), which were described in 10/12 studies. Three studies demonstrate an improvement in EFS, two in RFS, and two in DFS for the entire analyzed group [10,11,12,18,21,22,24,31]. Additionally, Cheng et al. report a significant improvement in 5-year EFS for a sub-group of untransplanted patients, and Ganesan et al. report, in addition to the improvement in the relapse rate and RFS, a trend toward improvement of EFS (p = 0.054) in the analyzed ALL patients [15,18].
Altogether, nine out of twelve studies report an improvement in either OS or EFS/RFS/relapse rate or both, while three studies found equivalent results. No study reported statistically significant superior outcomes with conventional adult-type chemotherapy.
The results are less impressive for post-induction complete remission rate (CR), reported by nine studies, with only two showing a statistically significant increase in CR rate in patients given PIR compared to patients given conventional adult protocols (Table 2) [10,11,12,18,22,24,29,30,31].
Regarding toxicity, the studies show increased toxicity with PIR compared to conventional adult protocols. Most commonly, an increased incidence of pancreatitis, hypofibrinogenemia, neuropathy, hepatic toxicity, and infections was reported by the studies [10,22,24,29] (Table 2). However, most toxicities were described as mild and manageable with supportive care [10,24]. Most importantly, except for one study from India, no other studies reported significantly increased induction-related mortality (IRM) or treatment-related deaths [15,17,24,29,31]. Almanza-Huante et al. report a decrease in IRM and TRD with a modified pediatric protocol [12].
3.3. Age-Stratified Analysis of Outcomes and Toxicities in AYA Patients Treated with PIR
Nineteen studies were included in this section. These studies examine outcomes between different age groups of AYA ALL patients treated with PIR (Table 1 and Table 3). For two studies, an age-stratified PIR vs. adult-type protocol comparison is available. Almanza-Huante et al. found a significant increase in CR at the end of induction and OS in patients aged 21–43 years treated with PIR as opposed to an adult-type protocol, with no increase in IRM. However, the follow-up duration was significantly shorter in patients who were treated with PIR, which might impact the reported OS. Conversely, Rytting et al. found no difference in OS between patients aged ≥21 and <21 years treated with PIR versus an adult-type protocol.
The remaining studies examined age-stratified outcomes or toxicity in patients treated exclusively with PIR (Table 3). Six of these studies report a significantly superior OS in younger age groups [13,14,23,25,27], with two additional studies also showing a trend towards inferior OS with increasing age (p = 0.057 and p = 0.055) [17,30]. On the contrary, four studies found no significant difference in OS between different age groups [16,19,20,28]. Similarly, heterogeneous results can be found for EFS, with four studies showing better outcomes for younger age groups [14,23,25,32] and five studies showing no significant difference between the age groups [15,16,17,27,28]. However, the studies identifying age as a significant predictor of EFS belong to those with the largest number of enrolled patients and thus the largest statistical power [14,23,25,32].
Furthermore, there are several adverse events (AE) whose incidence seems to be increasing with age (Table 3). Hough et al. report an overall increased cumulative incidence of AEs for patients aged >10 years and a significantly shorter time to the first AE after the start of treatment [23]. The AEs most commonly reported with increasing age are thrombosis, hypofibrinogenemia, hepatic injury, and infectious complications [9,14,26,28,30,32,33]. The risk of ICU admission and IRM does not seem to increase with age [14,32,33]. However, two studies report an increased incidence of toxic deaths in remission in older age groups [14,23]. Several studies show that the incidence of avascular osteonecrosis (ON) reaches its peak in the AYA age group, with a decrease in frequency in younger children and adults [32,33,34]. Furthermore, Valtis et al. show an increased risk for ON with the use of pegylated asparaginase, which is used with increasing frequency in new generations of PIR [34].
4. Discussion
This systematic review of 26 published comparative studies reporting outcomes of AYA patients with ALL shows a trend towards improvement in outcomes and an acceptable toxicity profile in patients treated with PIRs, compared to conventional adult-type regimens. While direct comparison and analysis were difficult due to heterogeneous study populations, treatment settings, treatment eras, and treatment protocols, most of the included studies nevertheless reported an increase in survival with the use of PIR.
Despite PIRs quickly becoming the standard of care for ALL treatment in the AYA population, further improvements are necessary. Our systematic review demonstrates a clear trend towards poorer survival with increasing age, even when using PIRs [13,14,23,25,27]. This is most likely due to a combination of higher therapy-related toxicity, requiring dose reductions and protocol adjustments and causing treatment delays, as well as disease biology [14,23].
Since PIRs are expected to be more intensive than adult-type regimens, an increase in treatment-related toxicity and adverse events is expected. However, our data show that while certain AEs increase with age, their toxicity is mostly manageable. Furthermore, PIRs also showed good results even in lower- and middle-income countries [10,12,17,18,19,31]. Yet, setting the age limit for the feasibility of these protocols is crucial so that the added toxicity and mortality do not surpass the positive effect of PIR on survival. With our analysis of age-stratified outcomes, we were unable to identify the optimal upper age limit for PIR.
Some of the included studies report low completion rates, high treatment abandonment rates, and large proportions of patients requiring dose reductions and treatment delays with increasing age [9,19,22,28]. In the study by Ribera et al., there were significantly more delays during reinductions and dose modifications for vincristine or asparaginase in young adults than in adolescents (p = 0.04 and p = 0.03, respectively). Adjustments to the protocol or alterations in the treatment strategy are more likely if the physician is unfamiliar with the protocol [9]. This is highlighted by the study by Gupta et al., which found a trend towards inferior EFS in patients treated with PIR in adult centers versus pediatric centers (HR 1.92, 95% CI 0.99–3.75, p = 0.06). The magnitude of the disparity between the two types of treatment centers persisted over time and even after adjusting for sociodemographic factors. This may be partially explained by a larger proportion of AYA patients treated in pediatric centers being registered on clinical trials (86/123 (69.9%) vs. 7/152 (4.6%), p < 0.001) or by better psychosocial support [21].
However, it is also well documented that treatment completion in the AYA age group is often low despite the physicians’ familiarity with the protocol. In the study by Advani et al., 57% of the AYA patients completed all therapy according to the COG AALL0232 PIR protocol versus 74% of the patients below 18 years of age [9]. Furthermore, Hayakawa et al. also report frequent terminations due to AEs or patients’ wishes. The latter happened predominantly during maintenance therapy [22]. This is presumably due to long, arduous PIR treatment programs resulting in low motivation. An alternative explanation for treatment termination in some low- and middle-income countries is socioeconomic factors, such as needing to pay for treatment out of pocket [19].
All these factors make translating the conclusions of this systematic review into clinical practice a precarious endeavor. The main limitations of our systematic review are based on the limited available data, including the lack of randomized studies and the heterogeneity in reporting the outcomes.
Randomized studies are needed to establish international treatment standards for AYA patients with ALL, improve risk stratification, and evaluate treatment response assessment using minimal disease measurements. Such studies would also ensure better data collection, adherence to the treatment dosing and schedule, integrated management of the most common AEs, and better support for physicians unfamiliar with the pediatric-inspired treatment protocols. Without them, we may not be able to definitively elucidate the magnitude of the influence of various treatment elements on improved outcomes (the prescribed regimen, locus of care, physicians´ experience with the protocol, compliance, socioeconomic and psychosocial factors, etc.).
5. Conclusions
Unfortunately, the gathered data do not allow for clear conclusions about the best treatment protocols to use in the AYA population. The trend towards improved outcomes with PIR must be viewed with caution, as non-randomized trials are prone to bias and difficult to compare and interpret. We should strive to enroll AYAs with ALL in randomized controlled trials of PIR vs. conventional adult-type protocols to definitively elucidate the best treatment strategy.
Supplementary Materials
The supporting information about our search strategy and extracted data from each article can be downloaded at: https://www.mdpi.com/article/10.3390/curroncol30090625/s1. Supplementary S1: Search strategy; Supplementary S2: Extracted data of each included study.
Author Contributions
Conceptualization, M.O. and K.S.; methodology, M.O. and K.S.; formal analysis, P.H.; title and abstract screening, A.Z. and M.O.; full-text screening and data extraction, A.Z. and P.F.; data curation, A.Z., P.F. and M.O.; writing—original draft preparation, A.Z.; writing—review and editing, P.F., P.H., N.B., M.O. and K.S.; supervision, N.B. and K.S.; project administration, M.O.; funding acquisition, N.B. and K.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by Swiss Cancer Research Foundation, Grant Number: HSR-5219-11-2020 and Palatin Stiftung 0069/2021.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Ferrari, A.; Stark, D.; Peccatori, F.A.; Fern, L.; Laurence, V.; Gaspar, N.; Bozovic-Spasojevic, I.; Smith, O.; De Munter, J.; Derwich, K.; et al. Adolescents and young adults (AYA) with cancer: A position paper from the AYA Working Group of the European Society for Medical Oncology (ESMO) and the European Society for Paediatric Oncology (SIOPE). ESMO Open 2021, 6, 100096. [Google Scholar] [CrossRef] [Scilit]
- Trama, A.; Botta, L.; Foschi, R.; Ferrari, A.; Stiller, C.; Desandes, E.; Maule, M.M.; Merletti, F.; Gatta, G. Survival of European adolescents and young adults diagnosed with cancer in 2000-07: Population-based data from EUROCARE-5. Lancet Oncol. 2016, 17, 896–906. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohan, S.R.; Advani, A.S. Treatment of Acute Lymphoblastic Leukemia in Adolescents and Young Adults. J. Adolesc. Young Adult Oncol. 2011, 1, 19–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ram, R.; Wolach, O.; Vidal, L.; Gafter-Gvili, A.; Shpilberg, O.; Raanani, P. Adolescents and young adults with acute lymphoblastic leukemia have a better outcome when treated with pediatric-inspired regimens: Systematic review and meta-analysis. Am. J. Hematol. 2012, 87, 472–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boissel, N.A.-O.; Baruchel, A.A.-O. Acute lymphoblastic leukemia in adolescent and young adults: Treat as adults or as children? Blood 2018, 132, 351–361. [Google Scholar] [CrossRef] [Scilit]
- Rizzari, C.; Putti, M.C.; Colombini, A.; Casagranda, S.; Ferrari, G.M.; Papayannidis, C.; Iacobucci, I.; Abbenante, M.C.; Sartor, C.; Martinelli, G. Rationale for a pediatric-inspired approach in the adolescent and young adult population with acute lymphoblastic leukemia, with a focus on asparaginase treatment. Hematol. Rep. 2014, 6, 5554. [Google Scholar] [CrossRef] [Scilit]
- Schafer, E.S.; Hunger, S.P. Optimal therapy for acute lymphoblastic leukemia in adolescents and young adults. Nat. Rev. Clin. Oncol. 2011, 8, 417–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liberati, A.; Altman, D.G.; Tetzlaff, J.; Mulrow, C.; Gøtzsche, P.C.; Ioannidis, J.P.A.; Clarke, M.; Devereaux, P.J.; Kleijnen, J.; Moher, D. The PRISMA statement for reporting systematic reviews and meta-analyses of studies that evaluate health care interventions: Explanation and elaboration. PLoS Med. 2009, 6, e1000100. [Google Scholar] [CrossRef] [Scilit]
- Advani, A.S.; Larsen, E.; Laumann, K.; Luger, S.M.; Liedtke, M.; Devidas, M.; Chen, Z.; Yin, J.; Foster, M.C.; Claxton, D.; et al. Comparison of CALGB 10403 (Alliance) and COG AALL0232 toxicity results in young adults with acute lymphoblastic leukemia. Blood Adv. 2021, 5, 504–512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alacacioglu, I.; Medeni, S.S.; Ozsan, G.H.; Payzin, B.; Sevindik, O.G.; Acar, C.; Katgi, A.; Ozdemirkan, F.; Piskin, O.; Ozcan, M.A.; et al. Is the BFM Regimen Feasible for the Treatment of Adult Acute Lymphoblastic Leukemia? A Retrospective Analysis of the Outcomes of BFM and Hyper-CVAD Chemotherapy in Two Centers. Chemotherapy 2014, 60, 219–223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al-Khabori, M.; Minden, M.D.; Yee, K.W.L.; Gupta, V.; Schimmer, A.D.; Schuh, A.C.; Xu, W.; Brandwein, J.M. Improved survival using an intensive, pediatric-based chemotherapy regimen in adults with T-cell acute lymphoblastic leukemia. Leuk. Lymphoma 2010, 21, 61–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almanza-Huante, E.; Espinosa-Bautista, K.; Rangel-Patiño, J.; Demichelis-Gómez, R. Comparison of Two Pediatric-Inspired Regimens to Hyper-CVAD in Hispanic Adolescents and Young Adults With Acute Lymphoblastic Leukemia. Clin. Lymphoma Myeloma Leuk. 2021, 21, 55–62. [Google Scholar] [CrossRef] [Scilit]
- Brandwein, J.M.; Atenafu, E.G.; Schuh, A.C.; Yee, K.W.; Schimmer, A.D.; Gupta, V.; Minden, M.D. Predictors of outcome in adults with BCR-ABL negative acute lymphoblastic leukemia treated with a pediatric-based regimen. Leuk. Res. 2014, 38, 532–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burke, M.A.-O.; Devidas, M.; Chen, Z.; Salzer, W.L.; Raetz, E.A.; Rabin, K.R.; Heerema, N.A.; Carroll, A.A.-O.X.; Gastier-Foster, J.M.; Borowitz, M.J.; et al. Outcomes in adolescent and young adult patients (16 to 30 years) compared to younger patients treated for high-risk B-lymphoblastic leukemia: Report from Children’s Oncology Group Study AALL0232. Leukemia 2022, 36, 648–655. [Google Scholar] [CrossRef] [Scilit]
- Cheng, C.N.; Li, S.S.; Hsu, Y.T.; Chen, Y.P.; Chen, T.Y.; Chen, J.S. Outcome of young adult patients with very-high-risk acute lymphoblastic leukemia treated with pediatric-type chemotherapy—A single institute experience. J. Formos. Med. Assoc. 2022, 121, 694–702. [Google Scholar] [CrossRef] [Scilit]
- DeAngelo, D.J.; Stevenson, K.E.; Dahlberg, S.E.; Silverman, L.B.; Couban, S.; Supko, J.G.; Amrein, P.C.; Ballen, K.K.; Seftel, M.D.; Turner, A.R.; et al. Long-term outcome of a pediatric-inspired regimen used for adults aged 18–50 years with newly diagnosed acute lymphoblastic leukemia. Leukemia 2015, 29, 526–534. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ganesan, P.A.-O.; Jain, H.A.-O.; Bagal, B.; Subramanian, P.G.; George, B.A.-O.; Korula, A.A.-O.; Mehra, N.; Kalaiyarasi, J.P.; Bhurani, D.A.-O.; Agrawal, N.A.-O.; et al. Outcomes in adolescent and young adult acute lymphoblastic leukaemia: A report from the Indian Acute Leukaemia Research Database (INwARD) of the Hematology Cancer Consortium (HCC). Br. J. Haematol. 2021, 193, e1. [Google Scholar] [CrossRef] [Scilit]
- Ganesan, P.A.-O.; Sagar, T.G.; Kannan, K.; Radhakrishnan, V.; Dhanushkodi, M.; Swaminathan, R.; Sundersingh, S.; Ganesan, T.S. Acute Lymphoblastic Leukemia in Young Adults Treated with Intensive “Pediatric” Type Protocol. Indian J. Hematol. Blood Transfus. 2018, 34, 422–429. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gómez-De León, A.; Varela-Constantino, A.L.; Colunga-Pedraza, P.R.; Sánchez-Arteaga, A.; García-Zárate, V.; Rodríguez-Zúñiga, A.C.; Méndez-Ramírez, N.; Cantú-Rodríguez, O.G.; Gutiérrez-Aguirre, C.H.; Tarín-Arzaga, L.; et al. Treatment of Ph-Negative Acute Lymphoblastic Leukemia in Adolescents and Young Adults with an Affordable Outpatient Pediatric Regimen. Clin. Lymphoma Myeloma Leuk. 2022, 22, 883–893. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenwood, M.A.-O.; Trahair, T.A.-O.X.; Sutton, R.A.-O.; Osborn, M.A.-O.; Kwan, J.; Mapp, S.; Howman, R.; Anazodo, A.A.-O.; Wylie, B.; D’Rozario, J.; et al. An MRD-stratified pediatric protocol is as deliverable in adolescents and young adults as in children with ALL. Blood Adv. 2021, 5, 5574–5583. [Google Scholar] [CrossRef] [Scilit]
- Gupta, S.A.-O.; Pole, J.D.; Baxter, N.A.-O.; Sutradhar, R.A.-O.; Lau, C.; Nagamuthu, C.; Nathan, P.C. The effect of adopting pediatric protocols in adolescents and young adults with acute lymphoblastic leukemia in pediatric vs adult centers: An IMPACT Cohort study. Cancer Med. 2019, 8, 2095–2103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayakawa, F.; Sakura, T.; Yujiri, T.; Kondo, E.; Fujimaki, K.; Sasaki, O.; Miyatake, J.; Handa, H.; Ueda, Y.; Aoyama, Y.; et al. Markedly improved outcomes and acceptable toxicity in adolescents and young adults with acute lymphoblastic leukemia following treatment with a pediatric protocol: A phase II study by the Japan Adult Leukemia Study Group. Blood Cancer J. 2014, 4, e252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hough, R.; Rowntree, C.; Goulden, N.; Mitchell, C.; Moorman, A.; Wade, R.; Vora, A. Efficacy and toxicity of a paediatric protocol in teenagers and young adults with Philadelphia chromosome negative acute lymphoblastic leukaemia: Results from UKALL 2003. Br. J. Haematol. 2016, 172, 439–451. [Google Scholar] [CrossRef] [Scilit]
- Kliman, D.; Barnett, M.; Broady, R.; Forrest, D.; Gerrie, A.; Hogge, D.; Nantel, S.; Narayanan, S.; Nevill, T.; Power, M.; et al. Comparison of a pediatric-inspired treatment protocol versus standard-intensity chemotherapy for young adults with standard-risk BCR-ABL negative acute lymphoblastic leukemia. Leuk. Lymphoma 2017, 58, 909–915. [Google Scholar] [CrossRef] [Scilit]
- Quist-Paulsen, P.; Toft, N.; Heyman, M.; Abrahamsson, J.; Griškevičius, L.; Hallböök, H.; Jónsson, Ó.G.; Palk, K.; Vaitkeviciene, G.; Vettenranta, K.; et al. T-cell acute lymphoblastic leukemia in patients 1–45 years treated with the pediatric NOPHO ALL2008 protocol. Leukemia 2020, 34, 347–357. [Google Scholar] [CrossRef] [Scilit]
- Rank, C.A.-O.; Toft, N.; Tuckuviene, R.; Grell, K.; Nielsen, O.J.; Frandsen, T.L.; Marquart, H.V.H.; Albertsen, B.K.; Tedgård, U.; Hallböök, H.; et al. Thromboembolism in acute lymphoblastic leukemia: Results of NOPHO ALL2008 protocol treatment in patients aged 1 to 45 years. Blood 2018, 131, 2475–2484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ribera, J.A.-O.; Morgades, M.; Montesinos, P.A.-O.; Tormo, M.; Martínez-Carballeira, D.; González-Campos, J.; Gil, C.; Barba, P.; García-Boyero, R.; Coll, R.; et al. A pediatric regimen for adolescents and young adults with Philadelphia chromosome-negative acute lymphoblastic leukemia: Results of the ALLRE08 PETHEMA trial. Cancer Med. 2020, 9, 2317–2329. [Google Scholar] [CrossRef] [Scilit]
- Ribera, J.M.; Oriol, A.; Sanz, M.-A.; Tormo, M.; Fernández-Abellán, P.; del Potro, E.; Abella, E.; Bueno, J.; Parody, R.; Bastida, P.; et al. Comparison of the results of the treatment of adolescents and young adults with standard-risk acute lymphoblastic leukemia with the Programa Español de Tratamiento en Hematología pediatric-based protocol ALL-96. J. Clin. Oncol. 2008, 26, 1843–1849. [Google Scholar] [CrossRef] [Scilit]
- Rytting, M.E.; Jabbour, E.J.; Jorgensen, J.L.; Ravandi, F.; Franklin, A.R.; Kadia, T.M.; Pemmaraju, N.; Daver, N.G.; Ferrajoli, A.; Garcia-Manero, G.; et al. Final results of a single institution experience with a pediatric-based regimen, the augmented Berlin-Frankfurt-Münster, in adolescents and young adults with acute lymphoblastic leukemia, and comparison to the hyper-CVAD regimen. Am. J. Hematol. 2016, 91, 819–823. [Google Scholar] [CrossRef] [Scilit]
- Rytting, M.E.; Thomas, D.A.; O’Brien, S.M.; Ravandi-Kashani, F.; Jabbour, E.J.; Franklin, A.R.; Kadia, T.M.; Pemmaraju, N.; Daver, N.G.; Ferrajoli, A.; et al. Augmented Berlin-Frankfurt-Münster therapy in adolescents and young adults (AYAs) with acute lymphoblastic leukemia (ALL). Cancer 2014, 120, 3660–3668. [Google Scholar] [CrossRef] [Scilit]
- Tantiworawit, A.; Rattanathammethee, T.A.-O.; Chai-Adisaksopha, C.; Rattarittamrong, E.; Norasetthada, L. Outcomes of adult acute lymphoblastic leukemia in the era of pediatric-inspired regimens: A single-center experience. Int. J. Hematol. 2019, 110, 295–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toft, N.; Birgens, H.; Abrahamsson, J.; Griškevičius, L.; Hallböök, H.; Heyman, M.; Klausen, T.W.; Jónsson, Ó.G.; Palk, K.; Pruunsild, K.; et al. Results of NOPHO ALL2008 treatment for patients aged 1–45 years with acute lymphoblastic leukemia. Leukemia 2018, 32, 606–615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toft, N.; Birgens, H.; Abrahamsson, J.; Griškevičius, L.; Hallböök, H.; Heyman, M.; Klausen, T.W.; Jónsson, Ó.G.; Palk, K.; Pruunsild, K.; et al. Toxicity profile and treatment delays in NOPHO ALL2008-comparing adults and children with Philadelphia chromosome-negative acute lymphoblastic leukemia. Eur. J. Haematol. 2016, 96, 160–169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valtis, Y.A.-O.; Stevenson, K.E.; Place, A.A.-O.; Silverman, L.B.; Vrooman, L.M.; Gotti, G.A.-O.; Brunner, A.M.; Nauffal, M.; DeAngelo, D.A.-O.; Luskin, M.A.-O. Orthopedic toxicities among adolescents and young adults treated in DFCI ALL Consortium Trials. Blood Adv. 2022, 6, 72–81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tierney, J.F.; Stewart, L.A.; Ghersi, D.; Burdett, S.; Sydes, M.R. Practical methods for incorporating summary time-to-event data into meta-analysis. Trials 2007, 8, 16. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).