


Case description
We report the case of a 79-year-old lady with severe symptomatic mitral regurgitation who successfully underwent a novel technique of percutaneous edge-to-edge valve reconstruction using a metallic clip.
The patient, with a history of aortic valve replacement 4 years prior and known mitral regurgitation for the last 2 years, was referred to us due to worsening symp-toms of heart failure over the 3 months prior. She presented with dyspnoea NYHA class III, despite medical treatment with an ACE-inhibitor, a thiazide and a loop diuretic. The patients’ history was also characterised by an ischemic stroke with partial right leg hemiparesis, osteoarthritis and renal function impairment (creatinin clearance 36 ml/min).
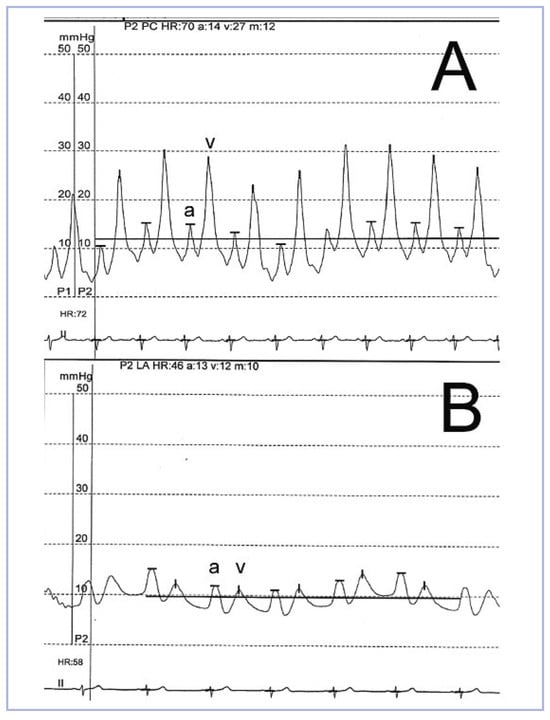
The ECG demonstrated sinus rhythm with left anterior hemiblock. Laboratory examination showed mild anaemia (haemoglobin of 11.5 g/dl) and an increased NT-proBNP (784 ng/l). The transthoracic and transesophageal (TEE) echocardiogram confirmed the diagnosis of severe mitral regurgitation with a posterior flail leaflet by ruptured cordae. The left atrium was dilated with a maximal diameter of 4.7 cm. The left ventricle was hypertrophic with a normal ejection fraction of 60%. Coronary artery disease could be excluded with angiography while the right heart catheter showed a prominent v-wave as a sign of severe mitral regurgitation and absence of pulmonary hypertension (fig. 1A).
Figure 1.
A Pulmonary wedge pressure showing prominent v-wave during right heart catheterisation. B The same patient after the intervention.
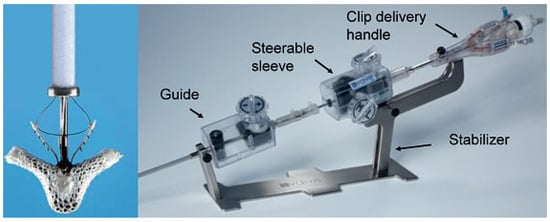
Due to her co-morbidities and the advanced age of the patient, the calculated surgical risk scores were greatly elevated (Morbidity or Mortality according to the Society of Thoracic Surgeons Score was 27.8% and the EuroSCORE 30-day-mortality was 33.8%). Therefore, we opted for a percutaneous mitral valve reconstruction using the MitraClip® system (fig. 2).
Figure 2.
Open MitraClip® mounted on the delivery system.
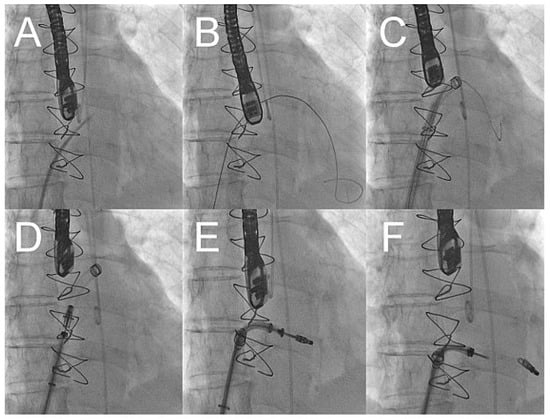
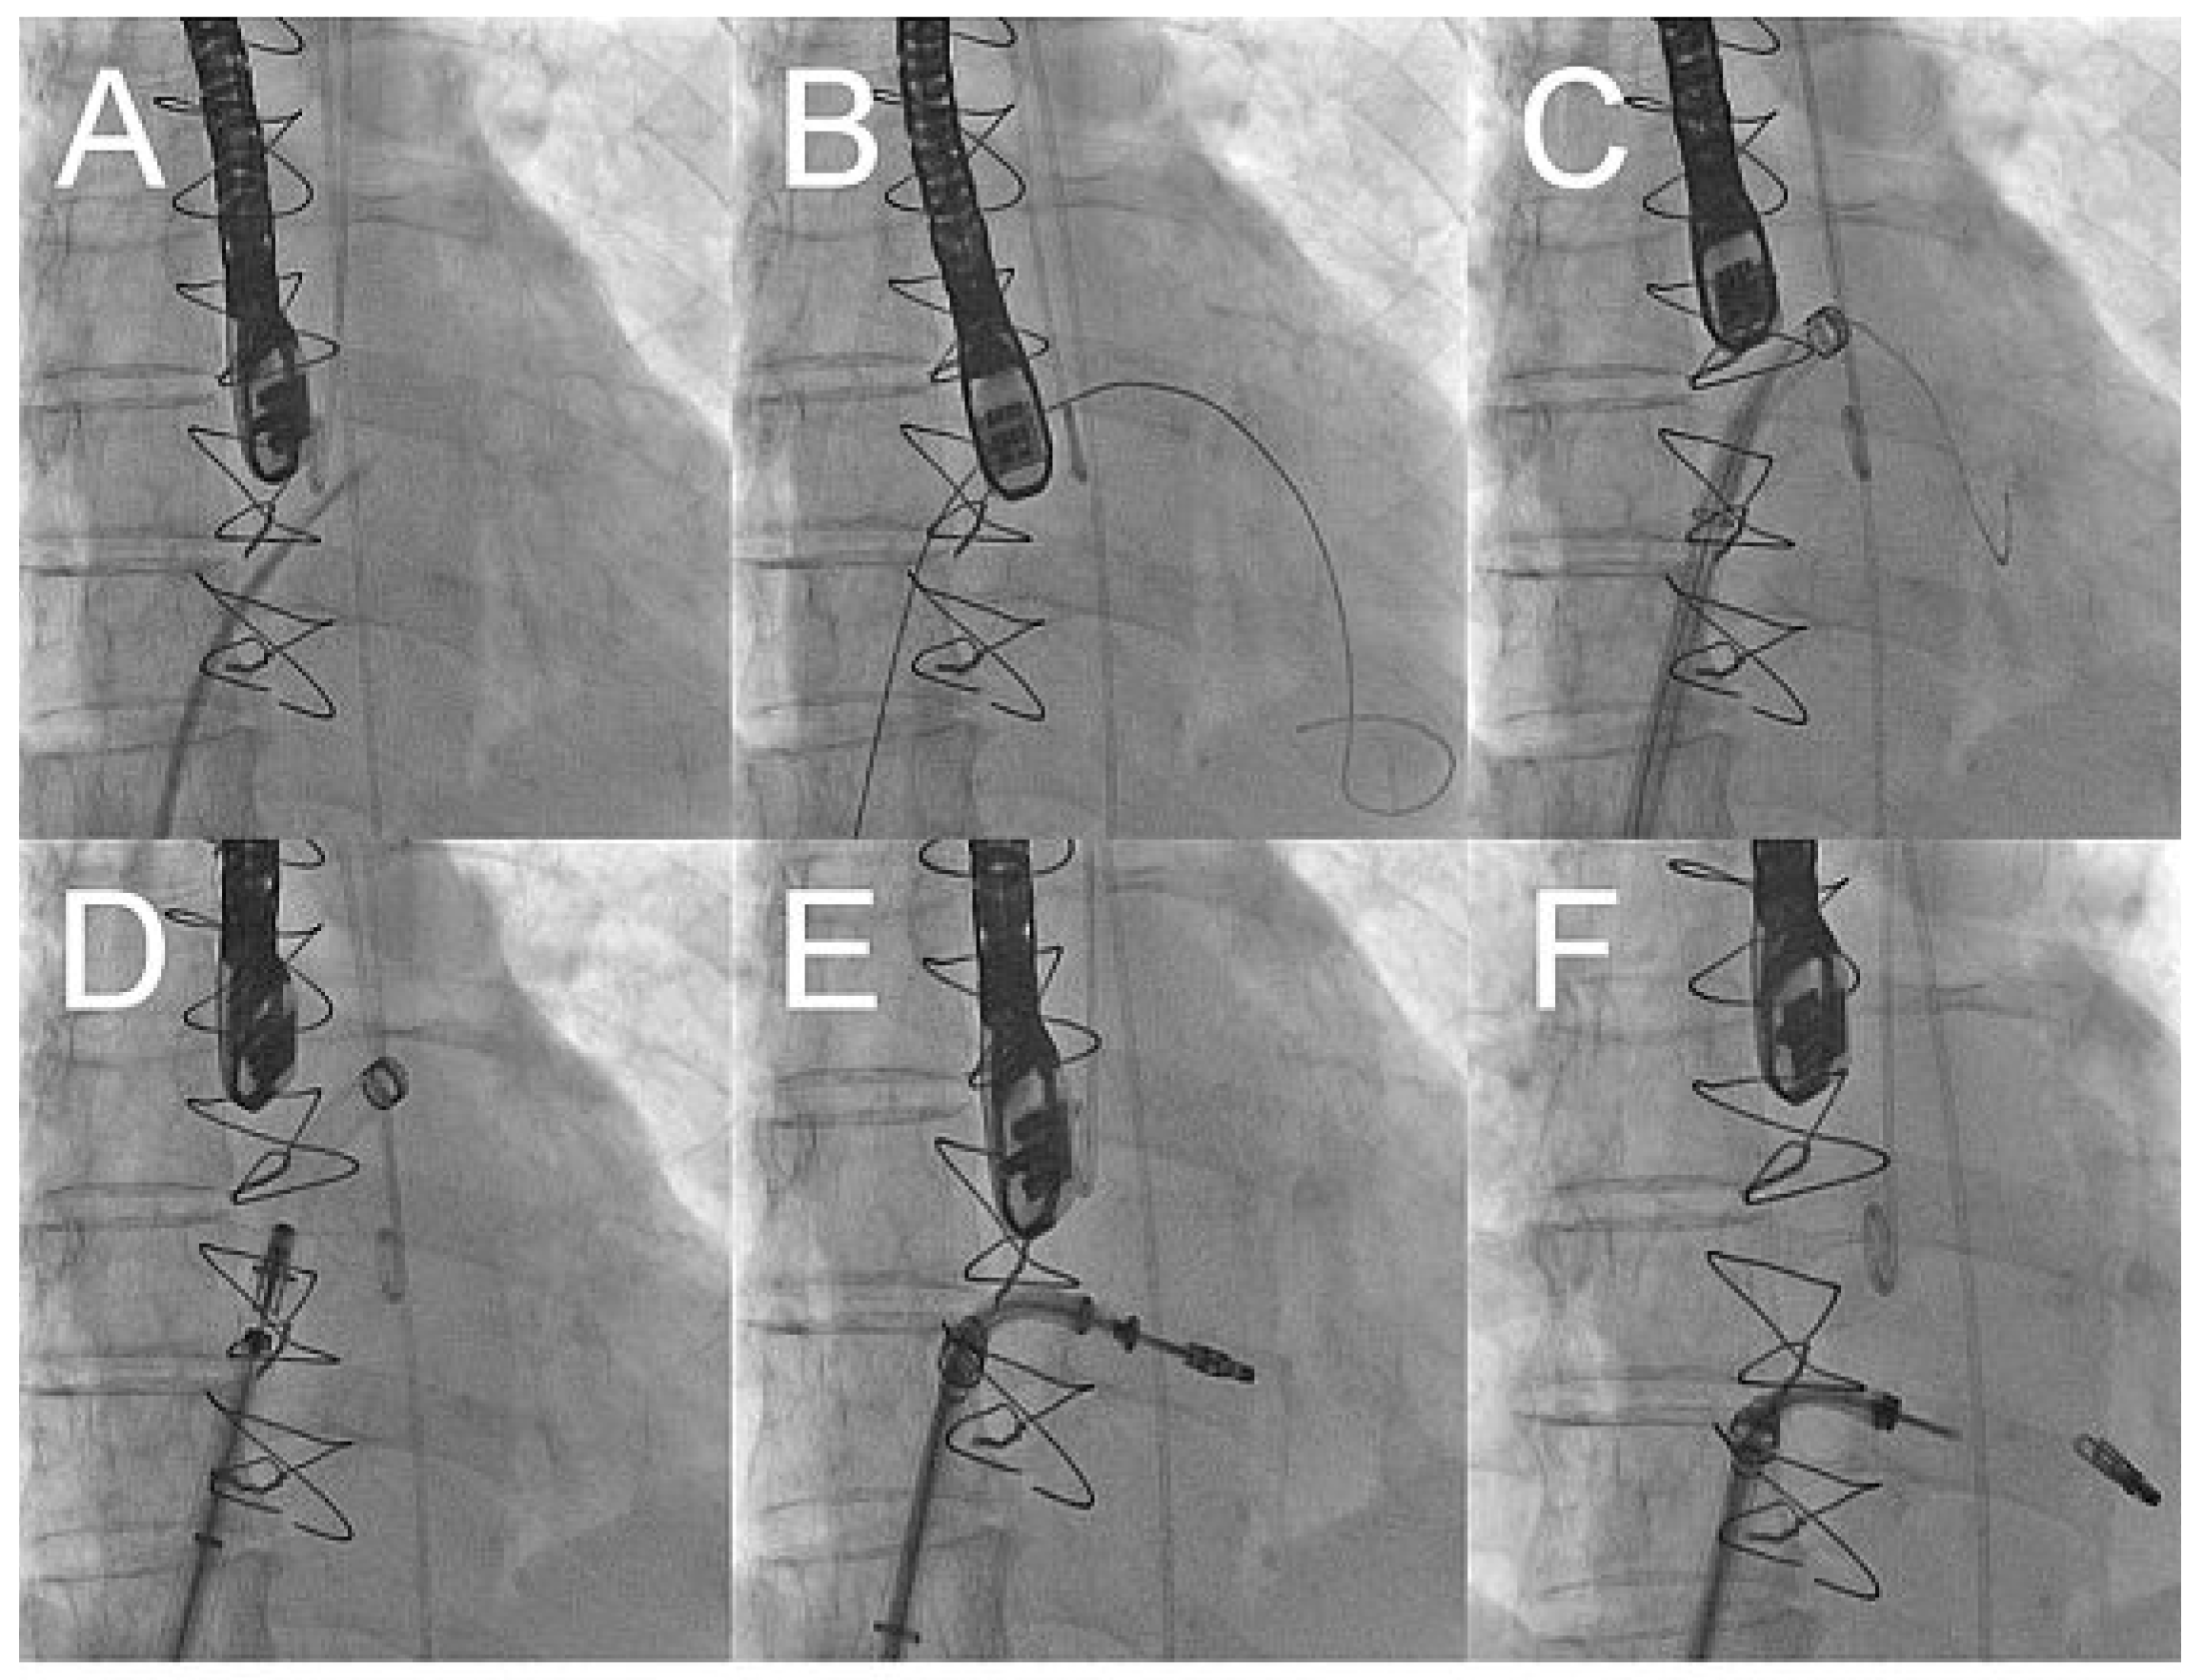
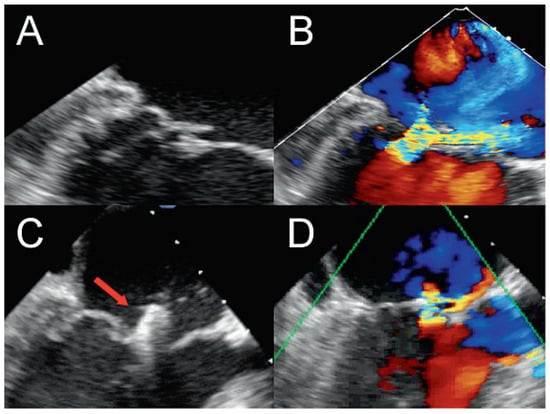
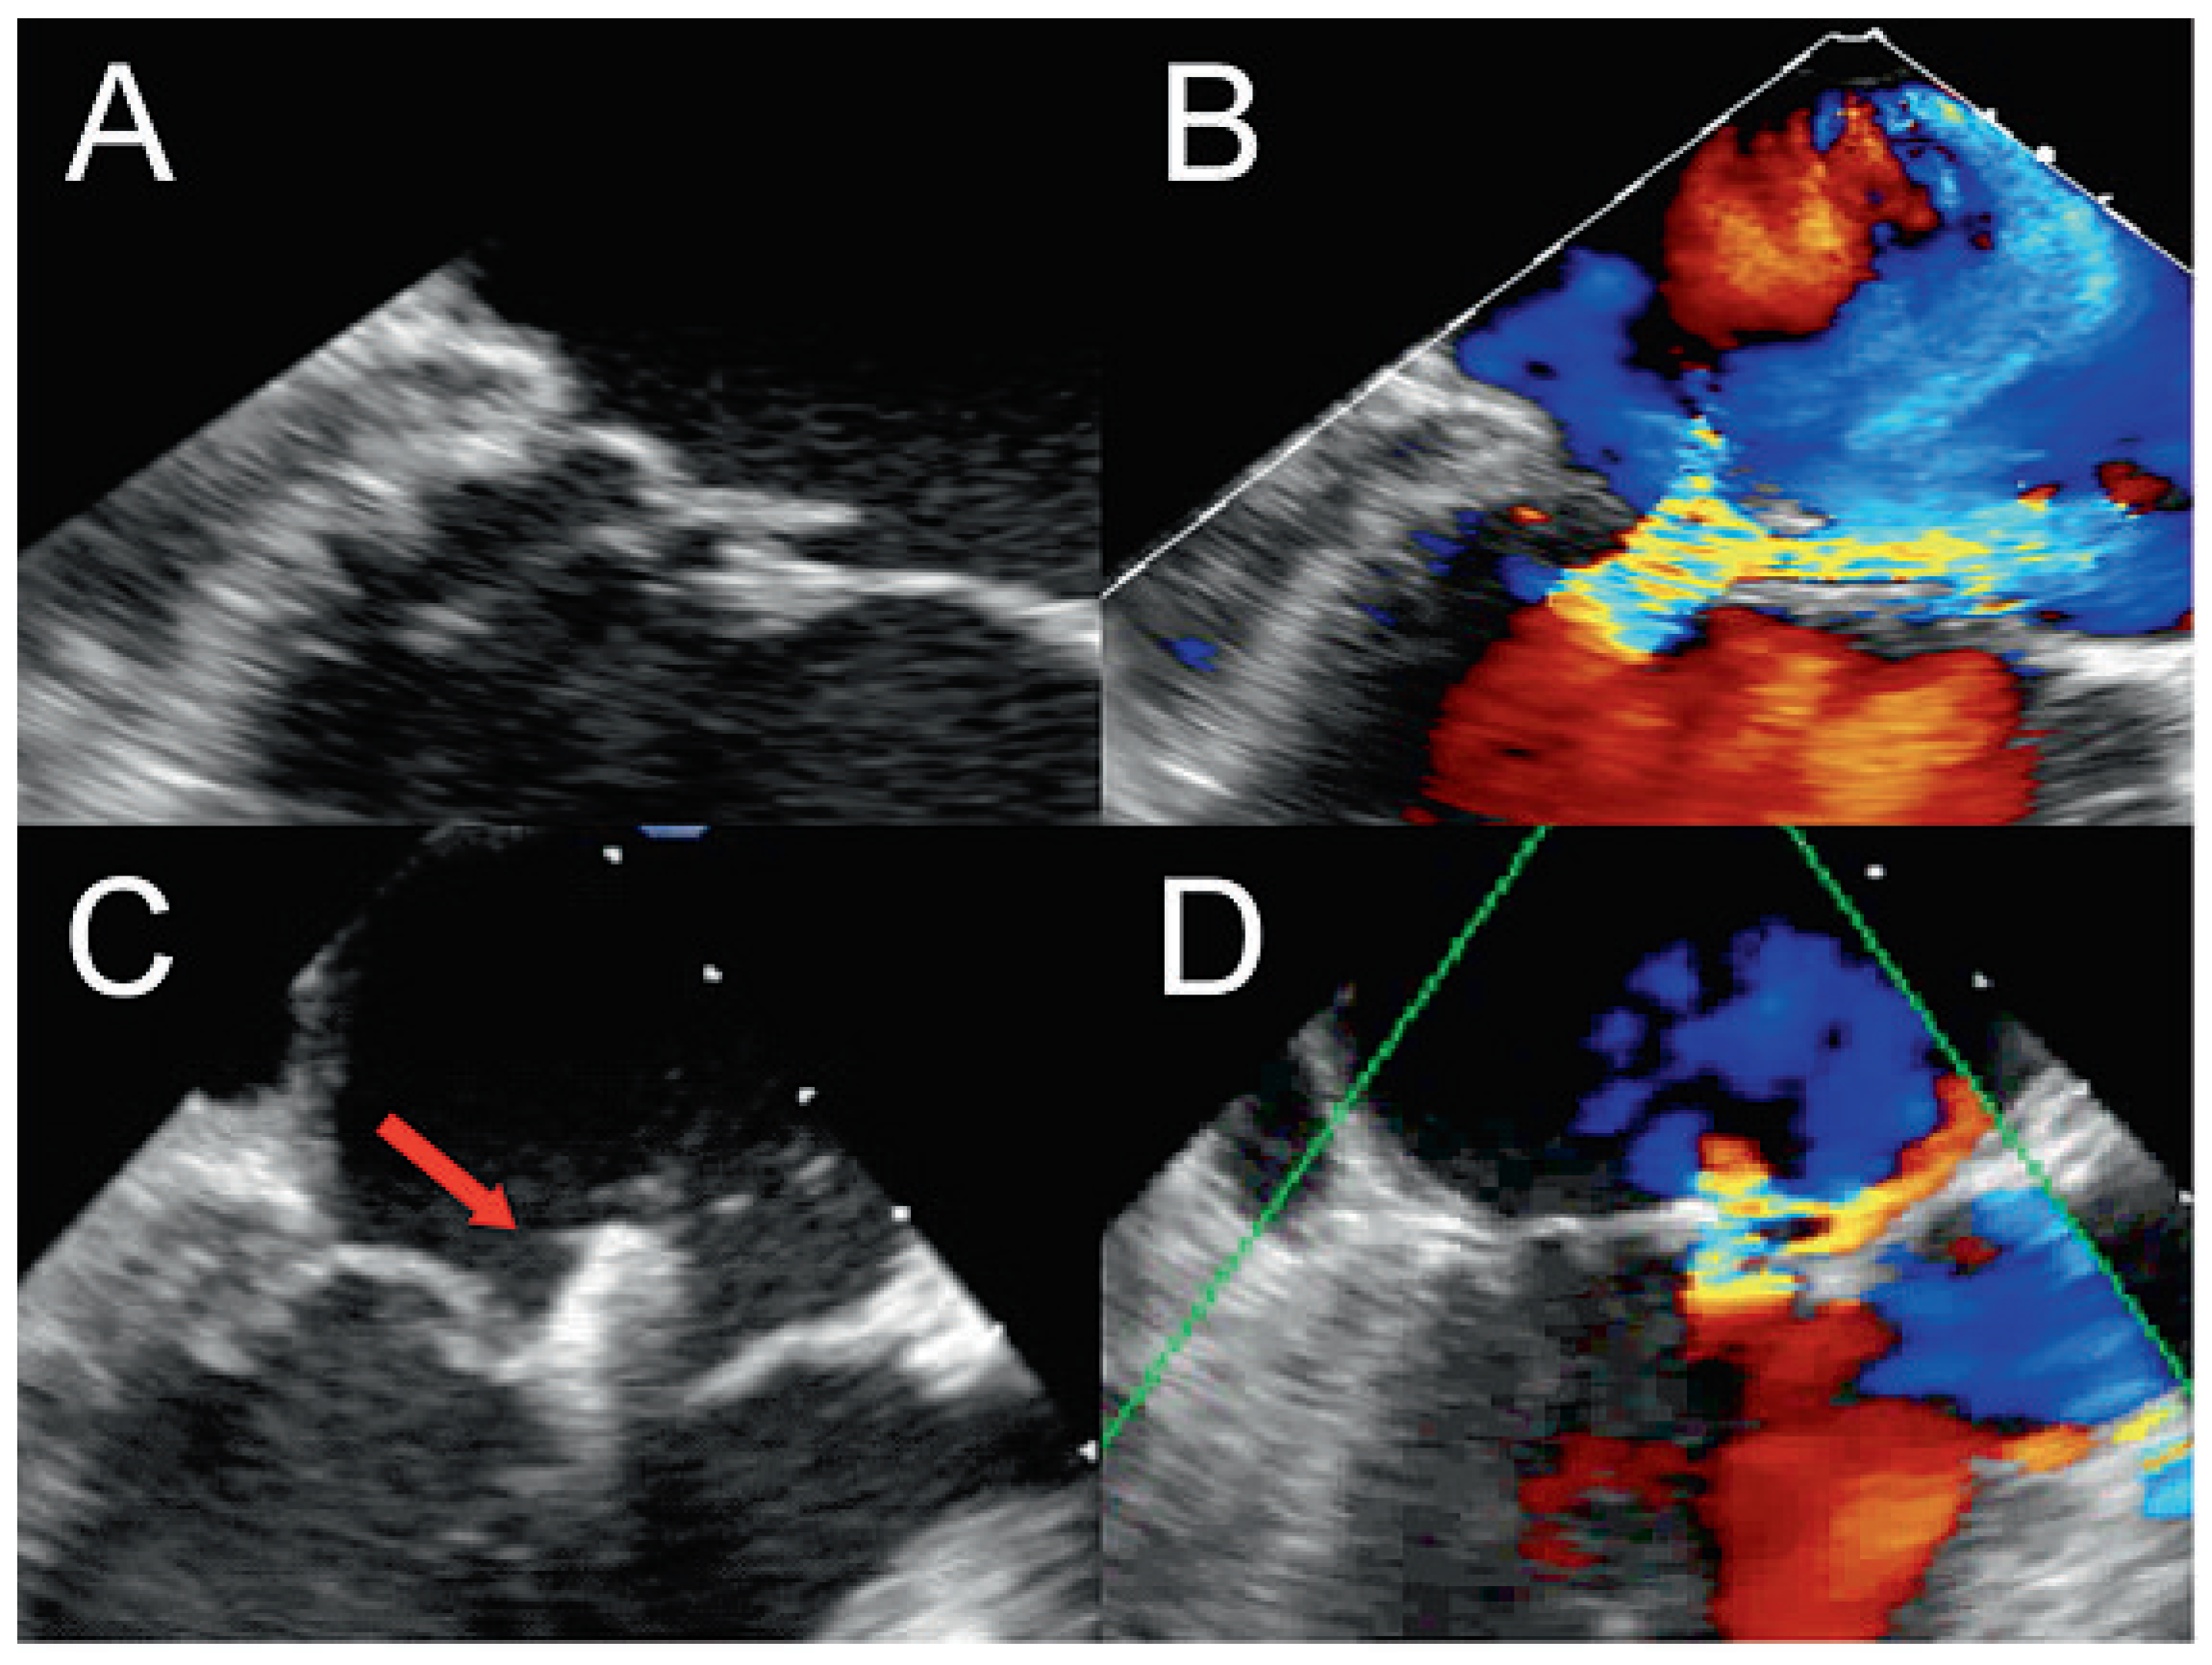
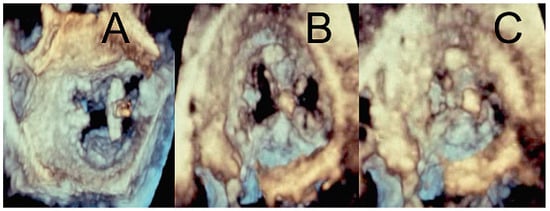
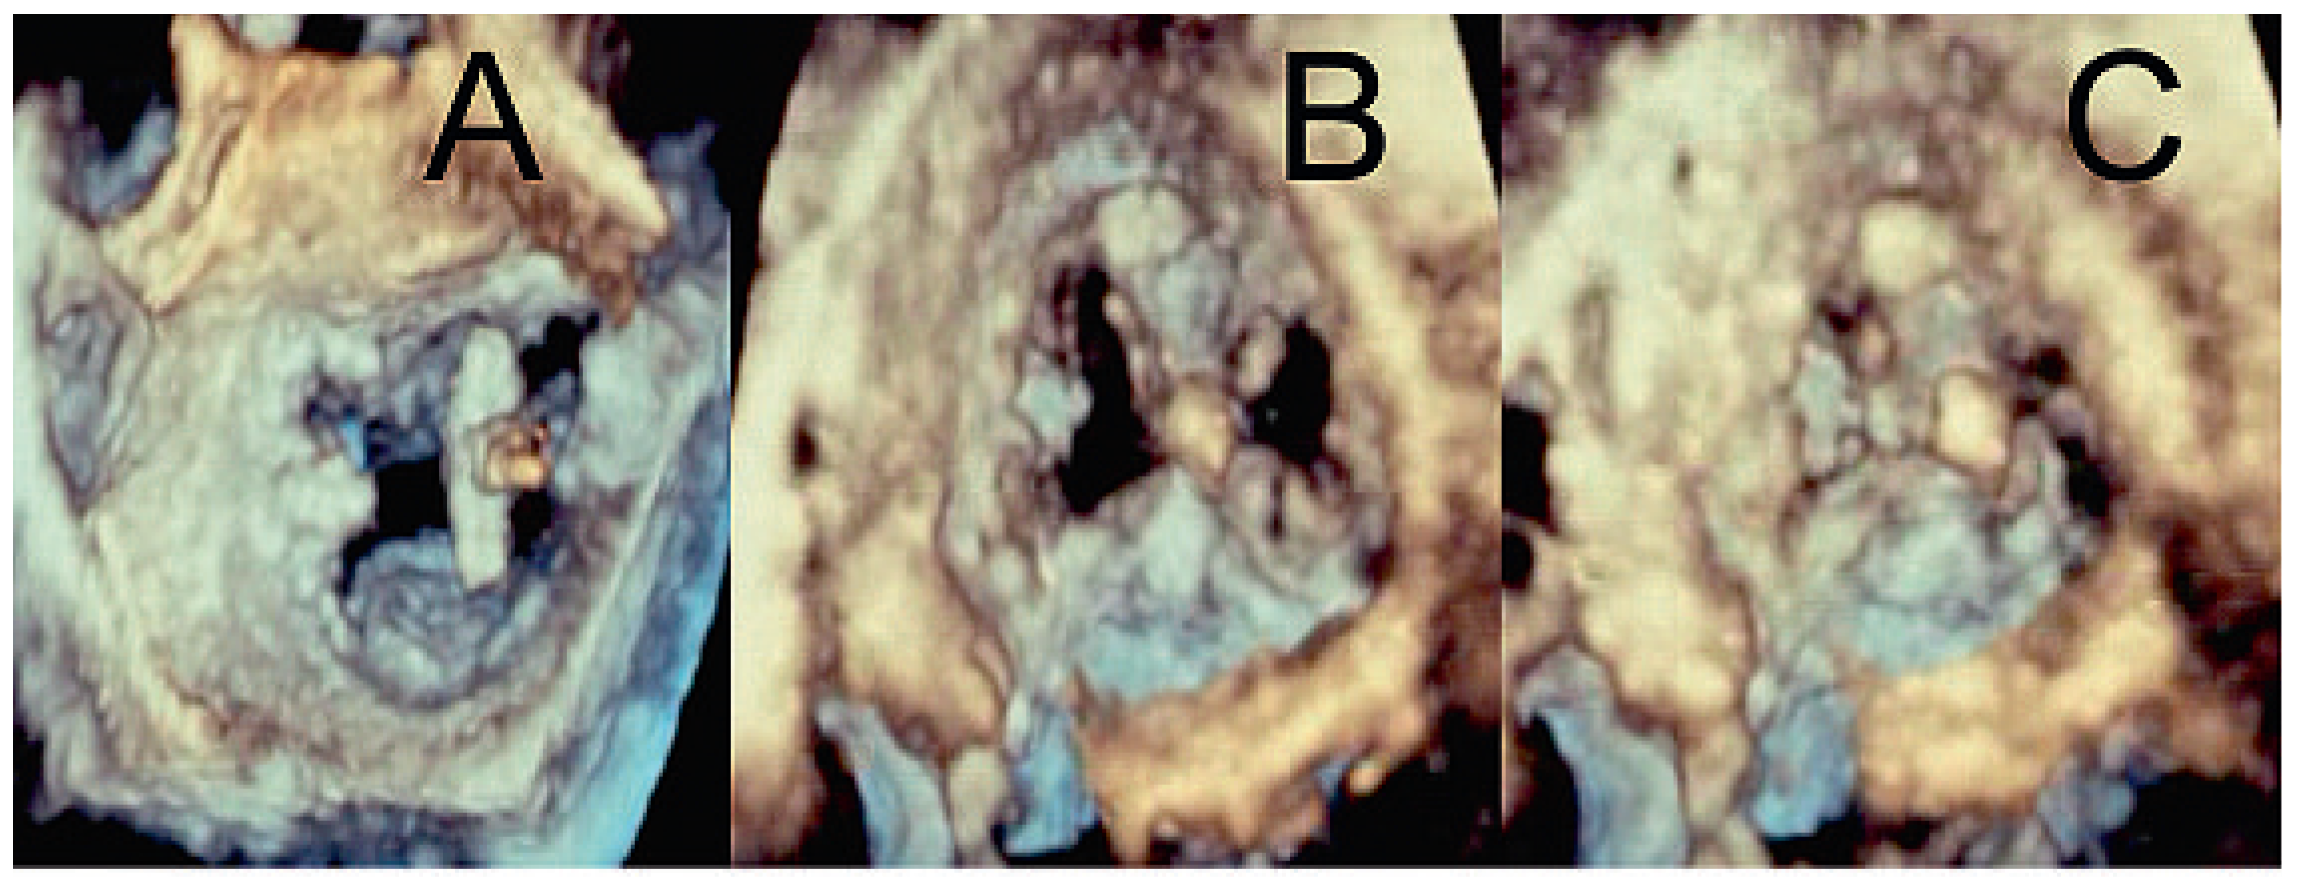
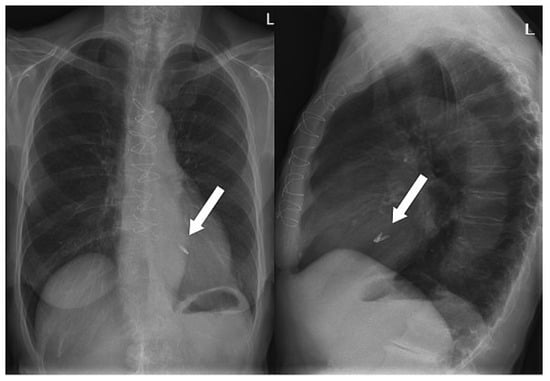
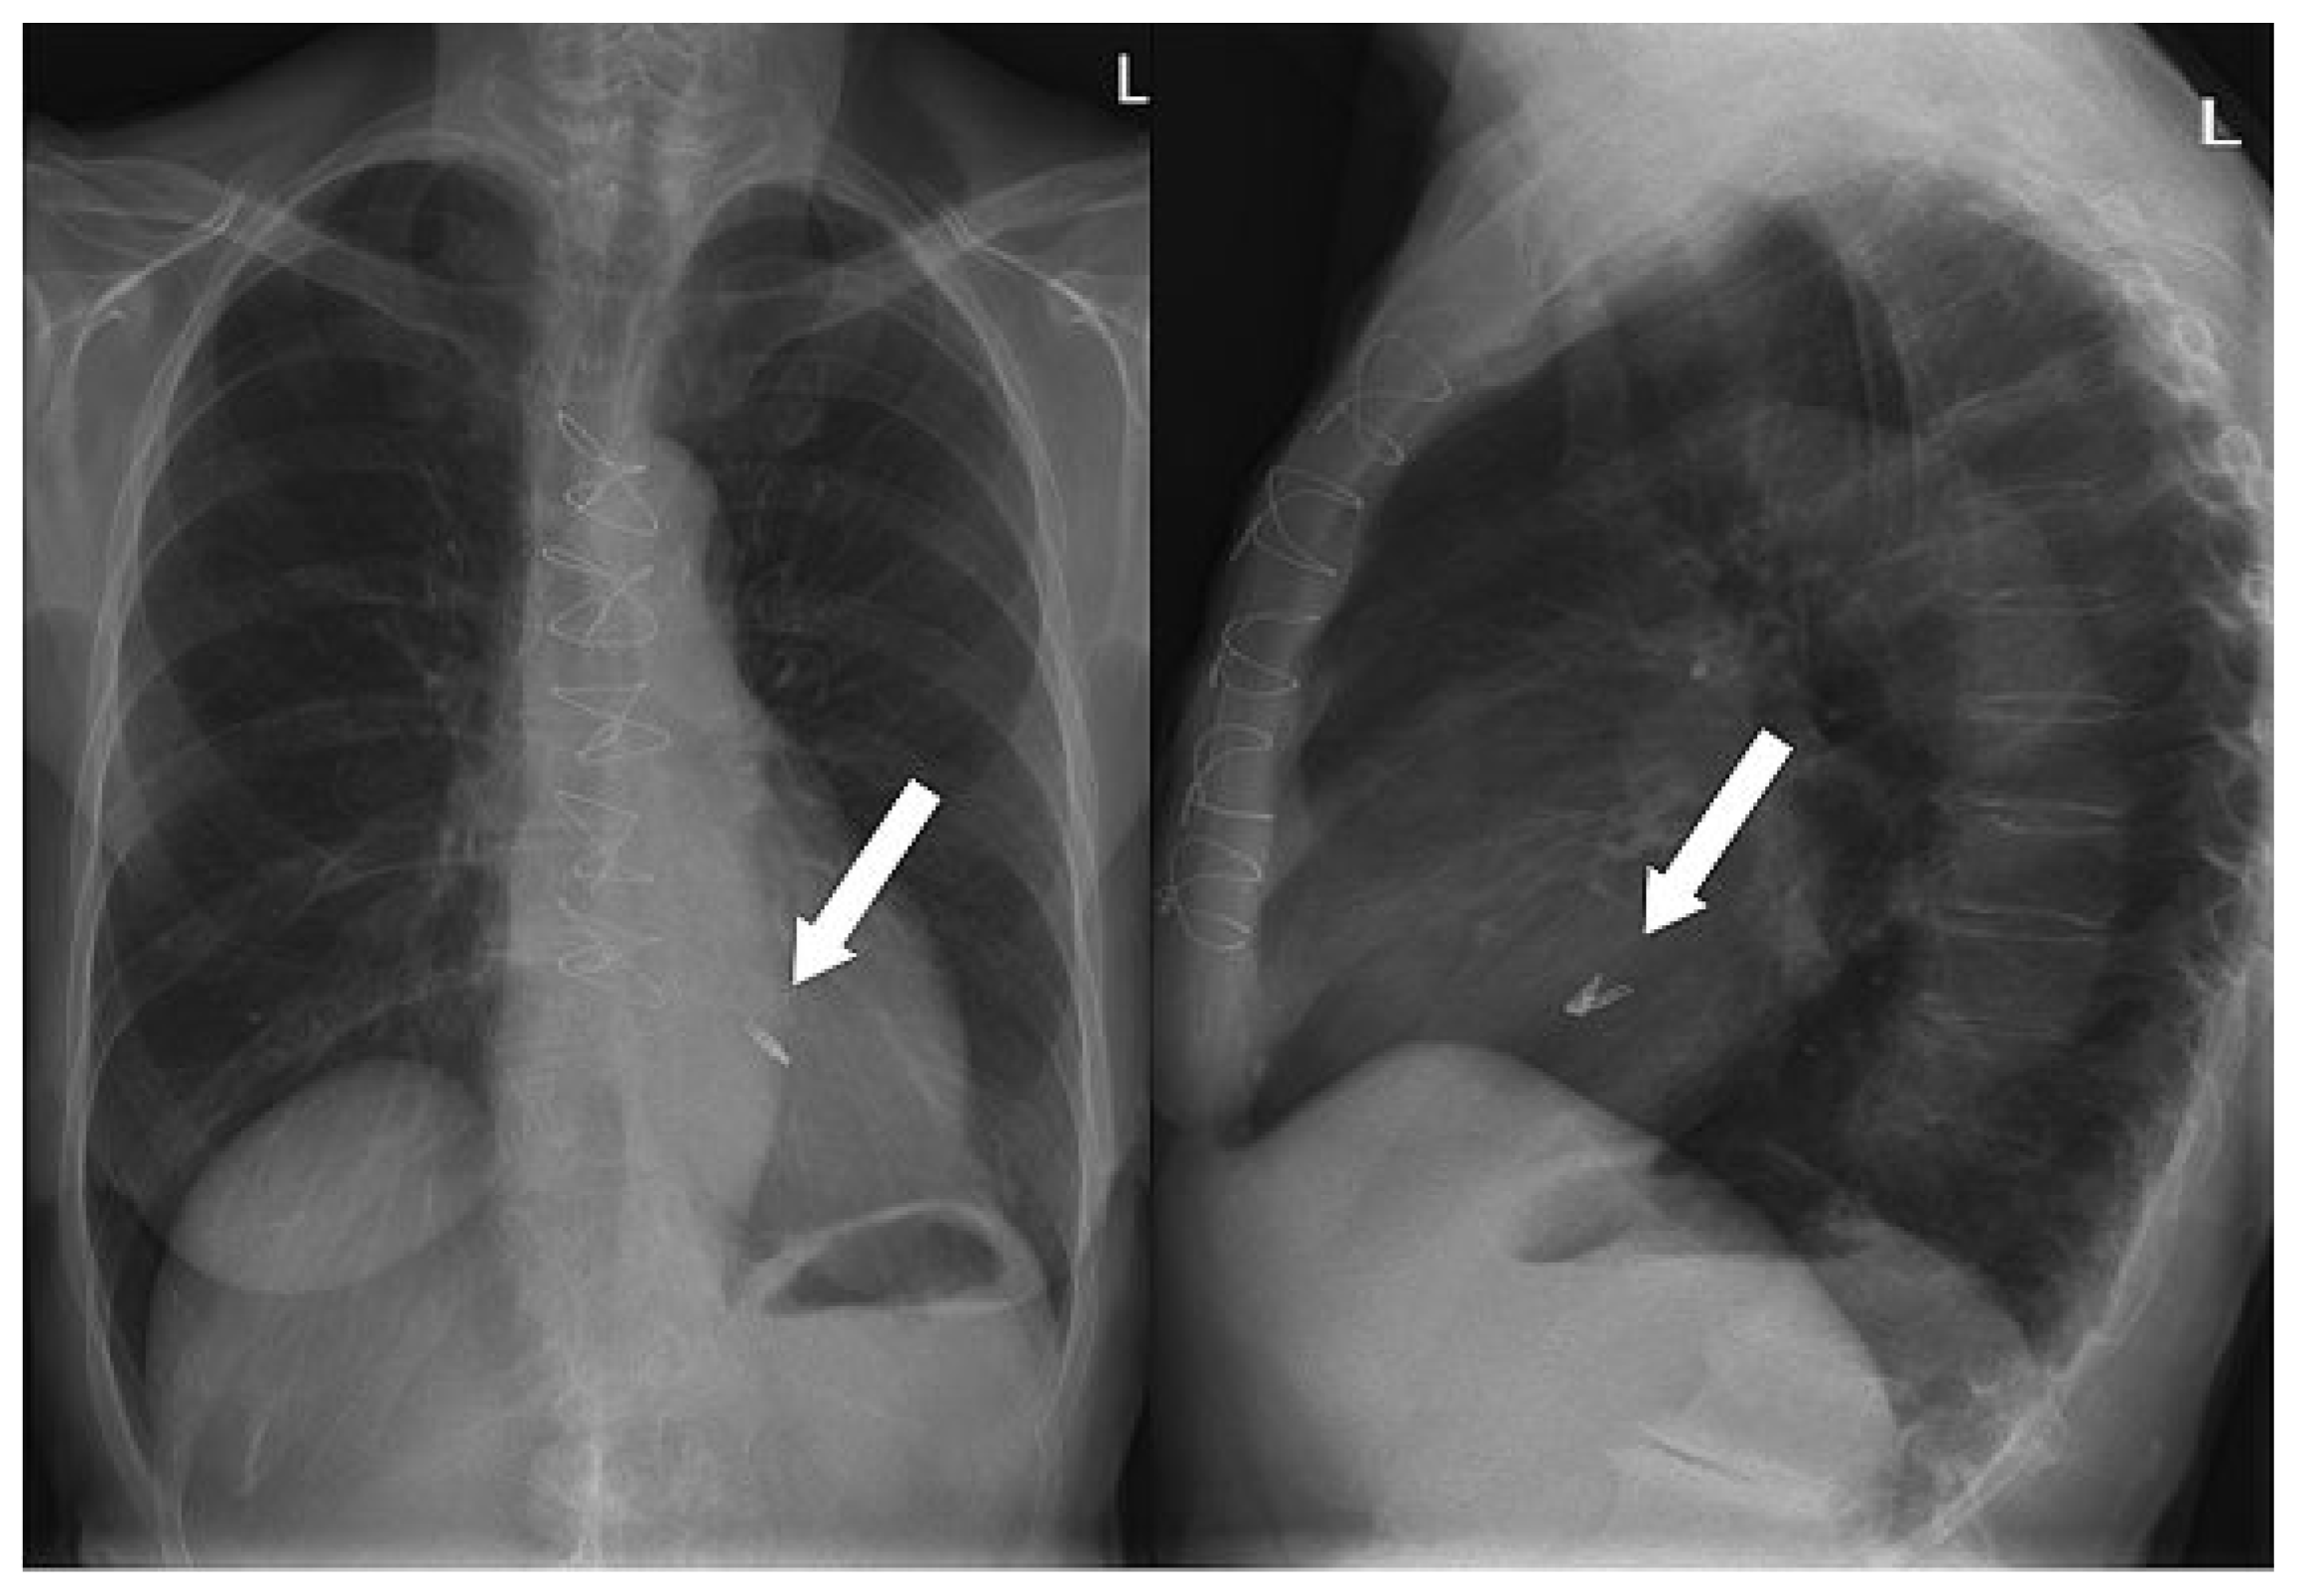
After gaining access through an 8 french sheath via the right femoral vein, transseptal puncture was performed under TEE and fluoroscopic-guidance, and an Amplatz-Super-Stiff® catheter was advanced into the left atrium (fig. 3A–C). Changing to a MitraClip-guide catheter, the clip delivery system was advanced via the left atrium (fig. 3D) into mitral position (fig. 3E). The system allows repositioning of the device under echocardiographic control until optimal placement has been found. This meant, before releasing the Clip (fig. 3F), that it could be repositioned until echocardiographic control showed the correct position of the device with mild residual regurgitation (fig. 4). 3-dimensional echocardiographic reconstruction images allowed the positioning and adjusting of the clip (fig. 5A) and the open and closed mitral valve after MitraClip® placement (fig. 5B and 5C) to be seen. The patient could be extubated in the catheter lab directly after clip implantation. The in-hospital recovery was uneventful and the patient could be discharged home three days after the intervention. During her four-week follow-up, the patient was in excellent health and reported a substantial improvement of her symptoms, reducing her exertional dyspnoea symptoms down to NYHA I–II. Echocardiographic control showed the MitraClip® in an optimal place with a residual mild-moderate regurgitation jet. On the chest x-ray film, the metallic clip can easily be identified (fig. 6).
Figure 3.
X-ray pictures showing the procedure of MitraClip® placement.
Figure 4.
Two-dimensional echocardiogram showing the flail posterior leaflet (A) with severe mitral regurgitation on colour Doppler (B). MitraClip® (red arrow) with mild residual regurgitation after placement (C) and as seen with colour Doppler (D).
Figure 5.
Three-dimensional echocardiogram showing the MitraClip® from the left atrium (A). Open (B) and closed (C) mitral valve after release of the device.
Figure 6.
Chest x-ray showing the position of the MitraClip®.
Discussion
Percutaneous mitral valve reconstruction with MitraClip® is a novel technique to treat patients with severe mitral regurgitation, for whom conventional mitral valve surgery is considered to be of too great a risk due to comorbidities and/or advanced age. Long-term follow-up data have yet to be gained, but it is already clear that this new and innovative approach, which follows the general trend for more minimal invasive treatment, shows interesting potential for the future.
Conflicts of Interest
The authors have no conflict of interest to disclose.
© 2010 by the authors. Attribution - Non-Commercial - NoDerivatives 4.0.