


Abstract
Background: Beta-blockers are widely prescribed across cardiovascular indications, yet their real-world cardiovascular adverse-event profiles across drug generations remain incompletely characterised in large pharmacovigilance datasets. Objective: The objective was to describe and compare cardiovascular adverse-event reporting patterns for atenolol, bisoprolol and nebivolol in the FDA Adverse Event Reporting System (FAERS). Methods: We performed a retrospective disproportionality analysis of FAERS reports using OpenVigil 2.1, covering each drug’s available reporting history from the first quarter of 2004 (2007 for nebivolol) through the third quarter of 2025 (FAERS 2025 Q3). Cardiovascular events were defined as individual MedDRA Preferred Terms; signals were assessed with the Reporting Odds Ratio (ROR, 95% CI) and Information Component (IC) under Evans’ criteria. Individual case safety reports were also analysed for demographics, seriousness and outcomes. Results: Atenolol was most strongly associated with bradycardia (ROR = 10.513), followed by pericardial haemorrhage (ROR = 7.067) and ventricular hypertrophy (ROR = 6.999). Bisoprolol showed the highest signals for diastolic dysfunction (ROR = 24.875), atrial tachycardia (ROR = 23.283) and chronic cardiac failure (ROR = 23.222). Nebivolol had the lowest overall reporting volume, although counts were not adjusted for exposure; its strongest signals were bradycardia (ROR = 9.619) and coronary artery stenosis (ROR = 9.351). Paediatric reports (0–17 years) were uncommon for atenolol and bisoprolol and nearly absent for nebivolol; none of the three is FDA-approved in this group. Reports mainly involved older adults (60–89 years), and a substantial proportion were classified as serious. Conclusions: All three agents generated significant signals across a broad range of cardiovascular events. Nebivolol had the lowest reporting volume, but this should not be interpreted as evidence of a safer profile. Because FAERS disproportionality cannot establish causality, these findings are hypothesis-generating and require prospective confirmation before they can inform beta-blocker selection.
1. Introduction
Cardiovascular disease (CVD) remains the leading cause of death worldwide. CVD includes a range of conditions such as coronary artery disease (CAD), stroke, hypertension, angina pectoris, myocardial infarction, and rheumatic heart disease [1]. Despite considerable therapeutic advances, the global burden has not abated: CVD deaths rose from 12.1 million in 1990 to 18.6 million in 2019 [1], and the burden has continued to grow [2]. The COVID-19 pandemic compounded this burden by disrupting healthcare delivery and worsening cardiovascular risk factors in vulnerable populations [3].
This burden has driven sustained efforts to develop, repurpose, and optimise cardiovascular treatments. Among currently available agents, beta-blockers have held a central place in cardiovascular medicine for decades, valued for their efficacy across a range of cardiac conditions [4]. Beyond their cardioprotective role, beta-blockers are also used in the management of anxiety, migraines, and certain tumours [5].
These agents act by competitively inhibiting catecholamine binding at β-adrenoceptors. Their primary cardiovascular effects (reduced heart rate, lower blood pressure and decreased myocardial workload) are mediated chiefly through β1-adrenoceptors in cardiac tissue, with β2-adrenoceptor antagonism in vascular and bronchial smooth muscle contributing to peripheral side effects in less selective agents [5,6].
Atenolol and bisoprolol are second-generation β1-selective agents and nebivolol is a third-generation vasodilatory β-blocker, so the three span two pharmacological generations within this drug class; all are among the most widely prescribed beta-blockers worldwide. Atenolol and bisoprolol are selective beta-1 adrenergic antagonists that reduce heart rate, blood pressure, and myocardial oxygen demand [7,8,9]. Nebivolol is a third-generation agent that combines beta-1 cardioselectivity with nitric oxide-mediated vasodilation [10]. Their labelled indications differ. In the United States, atenolol is indicated for hypertension, angina pectoris and acute myocardial infarction; bisoprolol for hypertension; and nebivolol for hypertension only. The heart-failure indication for bisoprolol derives from European approval following CIBIS-II. Comparative real-world cardiovascular adverse event profiles remain incompletely characterised. These three agents were selected because they are among the most widely prescribed beta-blockers globally, have well-characterised pharmacological profiles, and carry sufficient reporting volumes in the FDA Adverse Event Reporting System (FAERS) to support stable disproportionality estimates. Known adverse effects include bradycardia, hypotension, heart block, bronchospasm, and fatigue, with severity influenced by patient comorbidities, dosing, and concomitant medications [11]. Despite widespread use of all three agents, systematic pharmacovigilance comparisons across generations in large spontaneous reporting datasets are lacking.
This gap is especially relevant in patients with coexisting conditions such as asthma, diabetes, or peripheral vascular disease, in whom adverse event risk may be considerably higher.
This study compares the most frequently reported cardiovascular adverse events associated with atenolol (Tenormin), bisoprolol (Cardicor or Emcor), and nebivolol (Bystolic), using data from the FAERS database, building on prior FAERS-based disproportionality analyses in cardiovascular pharmacovigilance [12,13].
2. Methods
2.1. Study Design and Data Source
This retrospective pharmacovigilance study queried the FDA Adverse Event Reporting System (FAERS) to evaluate cardiovascular adverse-event reporting patterns associated with three β1-selective adrenergic receptor antagonists: atenolol, bisoprolol, and nebivolol. Individual case safety reports (ICSRs) were retrieved using OpenVigil 2.1, a validated pharmacovigilance data-mining platform that provides structured access to FAERS data [14]. OpenVigil 2.1 processes cleaned FAERS data and supports complete-case extraction, drug-name mapping, duplicate checking, data filtering, and disproportionality analysis [14]. The extracted ICSRs contained information regarding the suspected drug, indication, reported adverse events, seriousness and clinical outcomes, reporter country, reporter type, patient sex, and patient age, when available [13,15]. The publicly available data did not contain directly identifying patient information. Reports with missing demographic information were retained for the primary disproportionality analysis but were categorised as unknown or missing in descriptive analyses. Atenolol, bisoprolol, and nebivolol received initial FDA approval on 19 August 1981, 31 July 1992 and 17 December 2007, respectively [16]. The analysis included the full post-approval reporting period available in OpenVigil 2.1 for each drug. Queries were run with the latest report-submission date set to 1 January 2026, which returned all data then loaded in OpenVigil 2.1 (through FAERS 2025 Q3). Because OpenVigil 2.1 contains FDA AERS/FAERS data beginning in the first quarter of 2004, the effective observation periods began in 2004 for atenolol and bisoprolol and on 17 December 2007 for nebivolol. Because each drug was analysed against the FAERS reports available within its own observation window, the background against which disproportionality was computed differed by drug: approximately 16.32 million reports for atenolol and for bisoprolol and 15.44 million for nebivolol.
2.2. Procedure
The primary aim of this study was to assess cardiac safety, with particular attention to cardiovascular adverse events (CV-AEs). Adverse events were identified using the Medical Dictionary for Regulatory Activities (MedDRA), a standardised international terminology used across the regulatory lifecycle from clinical trials to post-marketing surveillance. MedDRA is structured hierarchically, and adverse events in this study were specified at the Preferred Term (PT) level, the level at which individual clinical events are coded, rather than through Standardised MedDRA Queries. Cardiovascular PTs were queried first for atenolol (Tenormin), followed by those for bisoprolol (Cardicor or Emcor) and nebivolol (Bystolic), covering each drug’s available FAERS reporting history through FAERS 2025 Q3 (see Section 2.1). Queries used MedDRA version 24 as implemented in OpenVigil 2.1. Reports were included regardless of the role recorded for the drug (primary suspect, secondary suspect, concomitant or interacting), which maximised sensitivity but also captured reports in which the β-blocker was not the suspected cause. Records were counted as unique individual safety reports using the OpenVigil 2.1 “ISR (unique reports)” setting. Each PT was queried individually against the drug of interest to obtain its own 2 × 2 contingency table, so the unit of analysis was the drug–PT pair. Cardiovascular events were chosen because they are the pharmacologically expected and most clinically consequential harms of β-blockade. Only drug–PT pairs that met the signal criteria in Section 2.3 are reported (for example, cardiac failure was excluded for atenolol with a reporting odds ratio (ROR) of 1.529), so the results tables list only positive signals rather than every cardiovascular term screened. Case-level characteristics (sex, age group, reporter country, drug role and serious outcomes) were counted for each drug–PT pair from the OpenVigil 2.1 case listings of unique reports (Supplementary Tables S1–S3); these counts can differ slightly from the report counts used for the disproportionality analysis. An outcome was counted whenever it was among the outcomes coded for a report, so outcome categories are not mutually exclusive. The reported fatal-outcome proportion is the number of these reports with an outcome coded as death divided by the number of unique reports for the same drug–PT pair (for example, 118 of 1796 atenolol bradycardia reports, 6.6%); because FAERS records outcomes at the report level, a coded death is not necessarily attributable to the event or the drug, and the proportion is neither a mortality nor a case-fatality rate.
2.3. Statistical Analysis
Signal detection used a case/non-case design, in which CV-AE reports for each beta-blocker were compared with those for all other drugs in the FAERS database. Disproportionality was quantified using the ROR, calculated from a 2 × 2 contingency table for each drug–event pair, in which A is the number of reports of the event of interest with the test drug, B the number of reports of that event with all other drugs in FAERS, C the number of reports of all other events with the test drug, and D the number of reports of all other events with all other drugs:
ROR = (A × D)/(B × C), 95% CI = eln(ROR)±1.96√(1/A+1/B+1/C+1/D)
The ROR compares the odds of a CV-AE being reported for a specific drug (e.g., atenolol) with the odds of the same event being reported for all other drugs in the database. A higher ROR indicates stronger disproportionate reporting of the event with the drug. An ROR above 1 means the event is reported more often with the drug than with all other drugs, an ROR below 1 means it is reported less often, and an ROR of 1 suggests no disproportionality [17]. A positive ROR signal was defined according to Evans’ criteria, which require at least three cases, a chi-square value above 4 and an ROR above 2.0; we also required the lower limit of the 95% confidence interval (CI) to exceed 1.0. These thresholds were originally proposed by Evans et al. for the proportional reporting ratio (PRR) and are applied here to the ROR, a common practice because the two measures converge for rare events [17]. Chi-square statistics were computed with Yates’ continuity correction, as implemented in OpenVigil 2.1. No correction for multiple comparisons was applied across the drug–event pairs tested; Evans’ criteria act as a screening threshold rather than as multiplicity control, and the signals reported are therefore hypothesis-generating. RORs, 95% CIs and chi-square values were taken from OpenVigil 2.1 and checked by recomputing them from each 2 × 2 table; the Information Component and its 95% credibility interval were computed from the same tables in Python (version 3.11; Python Software Foundation, Wilmington, DE, USA), following the Bayesian confidence propagation neural network (BCPNN) method of Bate et al. [15,18] with the shrinkage estimator of Norén et al. [19].
2.4. Information Component (IC) Analysis
Disproportionality was further evaluated using the Information Component (IC), a Bayesian signal detection method commonly applied in spontaneous reporting systems [15]. The IC compares the observed number of reports for a given drug–event pair with the number expected under the assumption of statistical independence, and was calculated as follows:
where NObs denotes the observed number of reports for the drug–event pair and NExp represents the expected number based on marginal totals. NExp was calculated as (A + B)(A + C)/N from the 2 × 2 table. A shrinkage factor of 0.5 was applied to stabilise estimates for rare events [19]. Statistical significance was assessed using the lower bound of the 95% Bayesian credibility interval (IC025), obtained as the base-2 logarithm of the 2.5th percentile of the posterior gamma distribution with shape NObs + 0.5 and rate NExp + 0.5 [19], with IC025 > 0 considered indicative of a positive disproportionality signal. Throughout the text and in the results tables, drug–event pairs are ranked by ROR; the figures show twelve of the strongest pairs for each drug, ranked by IC, so the order in the figures can differ from the order in the text.
IC = log2 [(NObs + 0.5)/(NExp + 0.5)]
3. Results
3.1. Atenolol
3.1.1. Cardiovascular Adverse Events Identified for Atenolol in FAERS
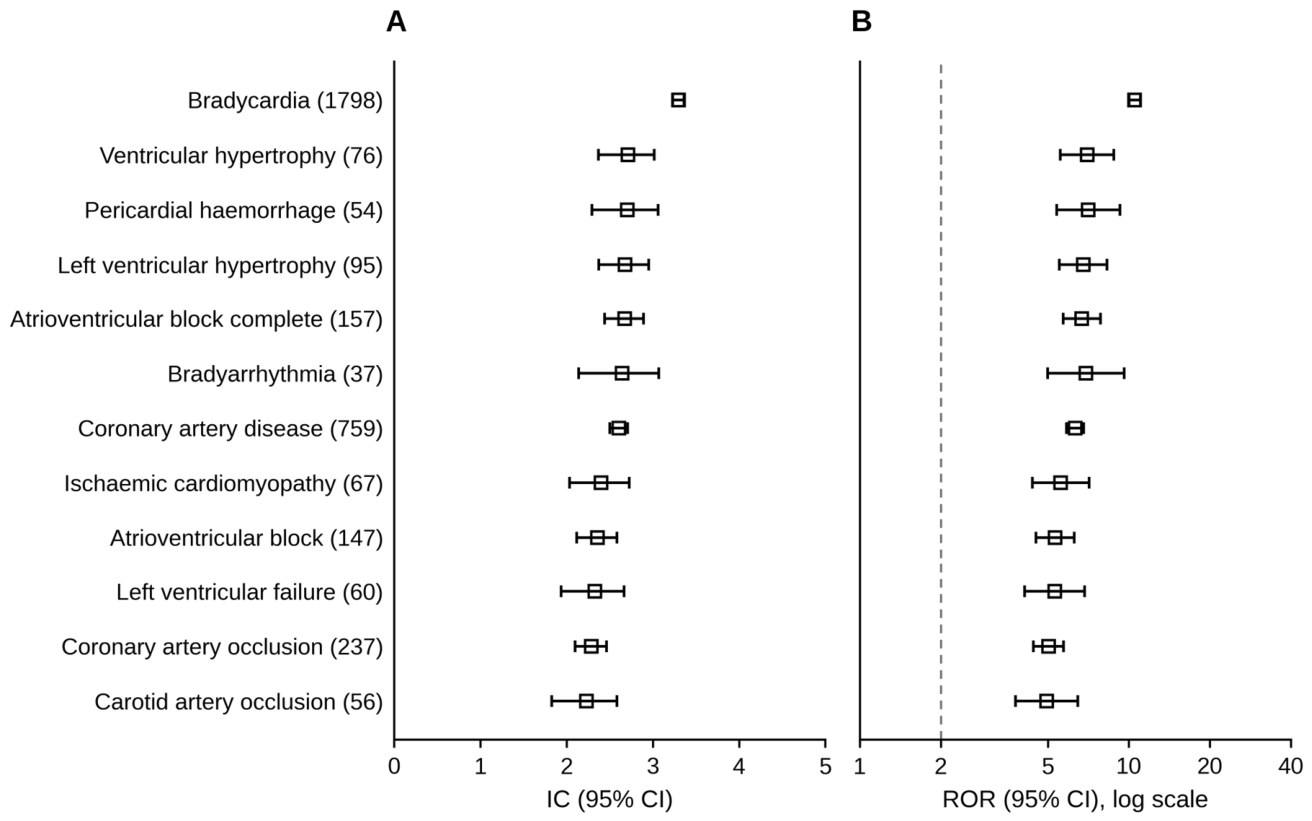
Disproportionality analysis identified significant cardiovascular pharmacovigilance signals for atenolol. The strongest signal was bradycardia (ROR = 10.513; 95% CI: 10.021–11.028), followed by pericardial haemorrhage (ROR = 7.067; 95% CI: 5.388–9.271), ventricular hypertrophy (ROR = 6.999; 95% CI: 5.568–8.798), bradyarrhythmia (ROR = 6.917), left ventricular hypertrophy (ROR = 6.765), and complete atrioventricular block (ROR = 6.686). Thirty-eight atenolol cardiovascular drug–event pairs met the signal criteria (Table 1); report counts ranged from 15 to 2625, and the twelve events with the highest Information Component are shown in Figure 1.
Table 1.
Cardiovascular Adverse Events Associated with Atenolol: A Pharmacovigilance Analysis of the FDA Adverse Event Reporting System (FAERS) Using Reporting Odds Ratio (ROR) and Information Component (IC).
Figure 1.
Atenolol: twelve highest-ranking cardiovascular adverse-event signals, ordered by information component (IC). (A) IC with its 95% credibility interval (CI); the lower bound (IC025) was above 0 for every event shown. (B) Reporting odds ratio (ROR) with its 95% confidence interval on a log scale; the dashed line marks ROR = 2 (Evans’ criteria). Report counts are shown in parentheses. Squares mark the point estimates and capped horizontal lines mark the intervals; for the events with the largest report counts the interval is narrower than the square. Results for all 38 atenolol drug–event pairs are listed in Table 1.
3.1.2. Characteristics of Atenolol Reports
Individual case safety reports for atenolol are summarised in Supplementary Table S1. Hypotension was the most frequently reported atenolol-associated adverse event (2625 reports; Table 1), followed by bradycardia (1798) and myocardial infarction (1675). The case-level characteristics below are based on the unique reports in Supplementary Table S1, whose totals are slightly lower than the report counts in Table 1. Among bradycardia reports (n = 1796), females and males were almost equally represented (46.7% and 46.0%). Hospitalisation was reported in 72.7% of bradycardia reports, life-threatening outcomes in 15.9% and death in 6.6%. Atenolol was recorded as the primary suspect drug in 46.7% of bradycardia reports. For left ventricular hypertrophy (n = 95), hospitalisation was recorded in 57.9% of reports, death in 14.7% and life-threatening outcomes in 15.8%.
Among bradycardia reports, the largest share came from the United States (33.2%; combining the “UNITED STATES” and “US” reporter-country entries), followed by the United Kingdom (14.9%), France (13.8%) and Italy (10.5%), with other countries accounting for most of the remainder. Bradycardia reports came from all age groups, with the largest proportions in patients aged 80–89 (21.6%), followed by those aged 70–79 (21.0%), 60–69 (15.1%) and 50–59 (11.3%); age was missing in 14.5%. These reports were therefore concentrated in older patients.
3.2. Bisoprolol
3.2.1. Cardiovascular Adverse Events Identified for Bisoprolol in FAERS
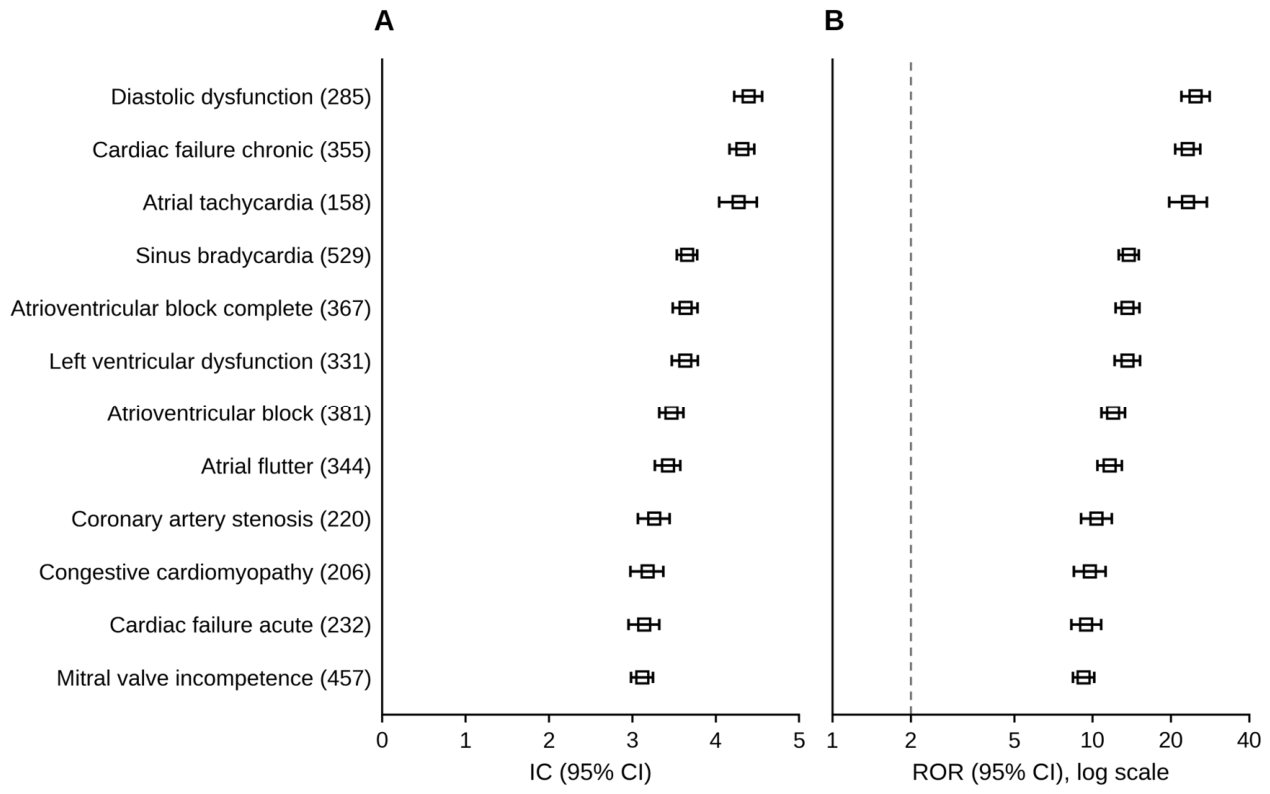
Disproportionality analysis identified significant cardiovascular pharmacovigilance signals for bisoprolol. The strongest signals were diastolic dysfunction (ROR = 24.875), atrial tachycardia (ROR = 23.283), and chronic cardiac failure (ROR = 23.222). Thirty-six bisoprolol cardiovascular drug–event pairs met the signal criteria (Table 2); report counts ranged from 150 to 4169, and twelve of the events with the highest Information Component are shown in Figure 2.
Table 2.
Cardiovascular Adverse Events Associated with Bisoprolol: A Pharmacovigilance Analysis of the FDA Adverse Event Reporting System (FAERS) Using Reporting Odds Ratio (ROR) and Information Component (IC).
Figure 2.
Bisoprolol: twelve highest-ranking cardiovascular adverse-event signals other than bradycardia (shown in Table 2), ordered by information component (IC). (A) IC with its 95% credibility interval (CI); the lower bound (IC025) was above 0 for every event shown. (B) Reporting odds ratio (ROR) with its 95% confidence interval on a log scale; the dashed line marks ROR = 2 (Evans’ criteria). Report counts are shown in parentheses. Squares mark the point estimates and capped horizontal lines mark the intervals; for the events with the largest report counts the interval is narrower than the square. Results for all 36 bisoprolol drug–event pairs are listed in Table 2.
3.2.2. Characteristics of Bisoprolol Reports
Individual case safety reports for bisoprolol are summarised in Supplementary Table S2. Hypotension was the most frequently reported bisoprolol-associated adverse event (4169 reports; Table 2), followed by atrial fibrillation (2862) and bradycardia (2770). Among hypotension reports (n = 4154), males comprised 46.6% and females 43.2%. Hospitalisation was reported in 70.8% of hypotension reports, death in 6.5% and life-threatening outcomes in 14.3%, and bisoprolol was the primary suspect drug in 16.4%. In contrast to the other two agents, few bisoprolol reports originated from the United States (2.8% of hypotension reports), compared with 19.8% from France, 17.6% from the United Kingdom and 12.0% from Italy. Hypotension reports were concentrated in patients aged 80–89 (25.0%), 70–79 (20.8%) and 60–69 (16.6%). Atrial fibrillation reports showed a similar profile (hospitalisation 68.5%, death 6.2%, United States 2.5%).
3.3. Nebivolol
3.3.1. Cardiovascular Adverse Events Identified for Nebivolol in FAERS
Disproportionality analysis identified significant cardiovascular pharmacovigilance signals for nebivolol. The strongest signals were bradycardia (ROR = 9.619) and coronary artery stenosis (ROR = 9.351), followed by chronic cardiac failure (ROR = 6.924) and sinus bradycardia (ROR = 6.464). Twenty-five nebivolol cardiovascular drug–event pairs met the signal criteria (Table 3); report counts ranged from 25 to 655, and the twelve events with the highest Information Component are shown in Figure 3.
Table 3.
Cardiovascular Adverse Events Associated with Nebivolol: A Pharmacovigilance Analysis of the FDA Adverse Event Reporting System (FAERS) Using Reporting Odds Ratio (ROR) and Information Component (IC).
Figure 3.
Nebivolol: twelve highest-ranking cardiovascular adverse-event signals, ordered by information component (IC). (A) IC with its 95% credibility interval (CI); the lower bound (IC025) was above 0 for every event shown. (B) Reporting odds ratio (ROR) with its 95% confidence interval on a log scale; the dashed line marks ROR = 2 (Evans’ criteria). Report counts are shown in parentheses. Squares mark the point estimates and capped horizontal lines mark the intervals; for the events with the largest report counts the interval is narrower than the square. Results for all 25 nebivolol drug–event pairs are listed in Table 3.
3.3.2. Characteristics of Nebivolol Reports
Individual case safety reports for nebivolol are summarised in Supplementary Table S3. Hypertension was the most frequently reported nebivolol-associated adverse event (655 reports; Table 3), followed by hypotension (639) and bradycardia (427). Among hypotension reports (n = 638), females comprised 46.1% and males 41.8%. Hospitalisation was reported in 65.8% of hypotension reports and 62.6% of bradycardia reports (n = 422), with death in 3.3% and 1.7%, respectively, and life-threatening outcomes in 13.2% and 15.2%. Nebivolol was identified as the primary suspect drug in 22.1% of hypotension reports and 39.1% of bradycardia reports. The United States contributed 30.9% of hypotension and 28.4% of bradycardia reports, followed by Italy and France for hypotension and by France and Italy for bradycardia. Only one hypotension report and no bradycardia report concerned a patient aged 0–17 years; the largest proportions were in patients aged 70–79 (19.0%) and 60–69 (18.3%) for hypotension and 70–79 (15.9%) and 80–89 (15.4%) for bradycardia; age was missing in 21.8% and 21.3% of these reports, respectively.
4. Discussion
Clinical trials establish the benefits of beta-blockers, but they enrol selected patients under controlled conditions. Patients who receive these drugs in routine practice are older, have more comorbidities and are often exposed to polypharmacy [1,2]. Their real-world adverse event experience across pharmacological generations remains poorly characterised [20]. Our analysis of FAERS reports for atenolol, bisoprolol, and nebivolol provides real-world evidence on 99 cardiovascular drug–event pairs (38 for atenolol, 36 for bisoprolol and 25 for nebivolol). Because a single report may be coded to more than one Preferred Term, case counts are not additive across events.
Atenolol showed the strongest association with bradycardia (ROR = 10.513; n = 1798), followed by pericardial haemorrhage (ROR = 7.067; n = 54) and ventricular hypertrophy (ROR = 6.999; n = 76). The bradycardia signal is mechanistically expected, since atenolol competitively blocks sinoatrial node β1 receptors and slows heart rate in a dose-dependent manner [11]. Many of the bradycardia reports described serious outcomes: 72.7% were associated with hospitalisation, 15.9% with a life-threatening outcome and 6.6% with a fatal outcome. The large share of reports from patients aged 70–79 (21.0%) and 80–89 (21.6%) is consistent with established prescribing patterns and is clinically relevant, as older patients are more susceptible to haemodynamic compromise from bradyarrhythmias [21]. There is no obvious β-blocker mechanism for pericardial haemorrhage; with only 54 reports, it may reflect concomitant anticoagulant or antiplatelet therapy or cardiac procedures in these patients and should be treated as a weak signal. The left ventricular hypertrophy (LVH) signal also requires comment. Although antihypertensive therapy is expected to attenuate LVH through blood pressure reduction, the LIFE trial demonstrated that atenolol was significantly inferior to losartan in reversing LVH despite equivalent blood pressure lowering, suggesting that atenolol does not confer comparable end-organ protection via non-haemodynamic pathways [22]. The other leading atenolol signals were bradyarrhythmia (ROR = 6.917; n = 37), left ventricular hypertrophy (ROR = 6.765; n = 95) and complete atrioventricular block (ROR = 6.686; n = 157). These signals include both conduction and structural terms, although the structural findings more likely reflect underlying hypertensive heart disease than a drug effect (see below). These estimates are based on one to two orders of magnitude fewer reports than the bradycardia signal (n = 1798) and are correspondingly less precise, as the wider credibility intervals in Figure 1 show.
For bisoprolol, the strongest disproportionality signals were observed for diastolic dysfunction (ROR = 24.875; n = 285), atrial tachycardia (ROR = 23.283; n = 158), and chronic cardiac failure (ROR = 23.222; n = 355). These highest-ROR signals were not those supported by the largest numbers of reports: bisoprolol’s most frequently reported events were hypotension (n = 4169), atrial fibrillation (n = 2862) and bradycardia (n = 2770), all with lower disproportionality (ROR = 5.617, 7.809 and 13.957, respectively). Signal magnitude and the volume of supporting evidence should therefore be considered together. The chronic cardiac failure signal must be interpreted in relation to the clinical use of bisoprolol. Bisoprolol is guideline-recommended for heart failure with reduced ejection fraction (HFrEF), as established by the CIBIS-II trial [23]. The pharmacovigilance signal probably reflects channelling bias: patients with pre-existing or progressive heart failure are disproportionately prescribed bisoprolol, and decompensation events are therefore more likely to be co-reported with this drug [24]. The diastolic dysfunction signal (ROR = 24.875) should be interpreted with caution. Slowing the heart rate lengthens rather than shortens diastolic filling time, so a direct mechanism is not straightforward; in heart failure with preserved ejection fraction (HFpEF), however, a stiff ventricle cannot raise stroke volume to offset a lower heart rate, so excessive bradycardia can reduce cardiac output and worsen symptoms [25]. Channelling of patients with pre-existing diastolic impairment toward bisoprolol is an equally likely explanation. Among bisoprolol-associated adverse events, hypotension (n = 4154) was associated with hospitalisation in 70.8% of reports, with death in 6.5% and life-threatening outcomes in 14.3%. Bisoprolol was the primary suspect drug in only 16.4% of these reports, so most of them described patients in whom bisoprolol was recorded as a secondary suspect or concomitant medication. Only 2.8% originated from the United States, compared with 30.9% to 37.2% for atenolol and nebivolol hypotension, so the bisoprolol reports largely reflect European practice.
Of the three agents, nebivolol had the lowest overall FAERS reporting volume. Bradycardia (ROR = 9.619; n = 427) and coronary artery stenosis (ROR = 9.351) were its strongest signals, although the absolute case counts were considerably lower than those for atenolol (n = 1798) and bisoprolol (n = 2770). This pattern could reflect nebivolol’s third-generation pharmacology, in which β1-selectivity combined with nitric oxide-mediated vasodilation attenuates the peripheral vasoconstriction and haemodynamic instability typical of earlier agents [10], but it is equally consistent with nebivolol’s later approval and lower prescription volume. Interest in nebivolol’s cardioprotective potential beyond hypertension is also growing, including possible applications in oncology [26]. The coronary artery stenosis signal is based on only 29 reports, and its wide confidence interval (95% CI: 6.482–13.490) reflects this limited evidence; it most plausibly reflects channelling toward patients with established coronary disease on guideline-directed therapy rather than a drug-attributable effect [27]. Moderately associated events, including sinus bradycardia (ROR = 6.464; n = 53), ischaemic stroke (ROR = 6.443; n = 98) and angina pectoris (ROR = 5.805; n = 129), are consistent with the cardiovascular comorbidity burden typical of patients receiving nebivolol. The reported fatal-outcome proportions for nebivolol were low (1.7% for bradycardia and 3.3% for hypotension), compared with 6.6% and 10.4% for atenolol and 6.5% for bisoprolol hypotension; because the reporting periods, countries and drug roles behind these figures differ, the differences cannot be attributed to the drugs. Paediatric reports (0–17 years) were uncommon, and none of the three agents carries FDA approval in this age group: there were 29 atenolol bradycardia reports (1.6%) and 50 atenolol hypotension reports (1.9%), 38 bisoprolol hypotension reports (0.9%) and 37 bisoprolol sinus bradycardia reports (7.0%), but only two nebivolol reports across all 25 events. FAERS does not distinguish direct paediatric treatment (for example, off-label use for hypertension or arrhythmia) from neonatal exposure through pregnancy or lactation, age was missing in 14% to 22% of the bradycardia and hypotension reports, and no denominator of paediatric use is available, so these reports show that paediatric exposure occurs with atenolol and bisoprolol but cannot establish a paediatric risk.
Several signals are better interpreted as markers of the treated disease than as adverse drug reactions. Atenolol is indicated for angina pectoris and acute myocardial infarction, so its signals for angina pectoris, myocardial infarction, acute myocardial infarction, coronary artery disease and myocardial ischaemia are expected among treated patients (confounding by indication). The same reasoning applies to bisoprolol’s heart-failure cluster (cardiac failure, chronic and acute cardiac failure, left ventricular dysfunction, diastolic dysfunction, congestive cardiomyopathy and cardiogenic shock), given its use in heart failure, and to the hypertension signal seen for bisoprolol and nebivolol, since hypertension is an indication for all three agents. Structural findings such as left ventricular and ventricular hypertrophy, valve incompetence and cardiomegaly are also more plausibly features of long-standing hypertensive or ischaemic heart disease than consequences of treatment. By contrast, bradycardia, sinus bradycardia, bradyarrhythmia, atrioventricular block and hypotension follow directly from β1-blockade and are the signals most likely to represent genuine adverse drug reactions. Indication-restricted analyses were not performed, so this classification is interpretive and should be tested in data that record indication reliably.
Pregnancy and lactation deserve separate consideration, as neither exposure group was captured in our FAERS stratification. Available evidence from systematic reviews indicates that beta-blockers cross the placenta and can cause neonatal bradycardia, hypoglycaemia, and respiratory depression; maternal use has also been associated with intrauterine growth restriction in some cohorts [28,29]. Atenolol in particular has been linked to significant intrauterine growth restriction and is generally avoided in pregnancy; labetalol is the preferred first-line beta-blocker in pregnancy, with bisoprolol or metoprolol as cardioselective alternatives when labetalol is not suitable, given comparatively lower rates of fetal growth restriction than atenolol [29]. During lactation, beta-blockers are excreted in breast milk to varying degrees depending on protein binding and renal elimination; atenolol accumulates more substantially than labetalol or propranolol and has been associated with neonatal bradycardia and cyanosis in breastfed infants, so guidance needs to be specific to each agent [30]. Our FAERS analysis could not stratify reports by pregnancy or lactation status; studies designed specifically for these populations are needed to fill this gap.
Across all three drugs, the demographic pattern was consistent: reports were concentrated in patients aged 60–89 (56% to 73% of bradycardia and hypotension reports with a recorded age), as expected given the prescribing context of these agents in hypertension, coronary disease, and heart failure. Age-related declines in baroreceptor sensitivity, autonomic reserve, and renal drug clearance each increase beta-blocker risk in this group [21], and clinicians should calibrate dosing and monitoring accordingly, particularly in patients with renal impairment or diabetes, where haemodynamic instability can escalate rapidly. The beta-blocker was recorded as the primary suspect drug in 46.7% of atenolol and 39.1% of nebivolol bradycardia reports, but in only 16.4% to 23.0% of hypotension reports across the three agents, so many hypotension reports concern patients in whom another drug was suspected. Primary-suspect designation reflects the reporting clinician’s judgement rather than an assessment of causality. Reports came from many countries, mainly in Europe and North America.
Among the three agents, nebivolol showed the lowest reporting volume, a pattern consistent with its dual β1-selective and nitric oxide-mediated vasodilatory mechanism [10,25] but equally with its later approval and lower prescription volume. Lower reporting volume also reduces precision: nebivolol’s most frequently reported event had 655 reports, compared with 2625 for atenolol and 4169 for bisoprolol, so its disproportionality estimates are the least precise of the three, and a genuinely lower risk cannot be distinguished from lower reporting volume on these data alone. These observations should not be interpreted as evidence of clinical superiority. They are hypothesis-generating signals from a voluntary reporting system, and prospective comparative studies are needed before they can inform clinical practice.
Limitations
This study has several limitations that are common to analyses of spontaneous reporting databases. First, FAERS data are subject to significant underreporting, as adverse events are submitted voluntarily by healthcare providers, patients, and manufacturers, and the true incidence of adverse events in the population cannot be derived from report counts alone. The ROR and IC are measures of disproportionate reporting, not measures of absolute risk or causality. Second, confounding by indication is an important consideration throughout this analysis: drugs are prescribed to patients with pre-existing cardiovascular disease, and many of the reported adverse events may reflect the underlying condition rather than a direct drug effect. This is especially relevant for bisoprolol, which is guideline-recommended for heart failure, so signals such as chronic cardiac failure and diastolic dysfunction are highly susceptible to channelling bias. Third, the analysis could not account for concomitant medications, polypharmacy, dose, or treatment duration, all of which may independently contribute to adverse event risk. Fourth, differences in market penetration, prescribing volume, and duration of clinical availability across the three agents influence both absolute report counts and the stability of disproportionality estimates, which limits direct cross-drug comparisons of reporting frequency and signal magnitude. Fifth, FAERS reports may contain duplicate entries despite OpenVigil 2.1’s deduplication procedures, and data quality is inherently dependent on the accuracy of voluntary submissions. Sixth, we did not have access to other large spontaneous reporting systems (e.g., VigiBase) or longitudinal cohort datasets for external validation, and our findings should therefore be regarded as hypothesis-generating pharmacovigilance signals requiring confirmation in independent data sources. Seventh, FAERS does not reliably capture patient ethnicity, so ethnicity-specific signal analyses were not possible; future studies using datasets with reliable ethnicity data are needed to explore potential ethnic differences in beta-blocker safety profiles. Eighth, adverse event reports were not stratified by pregnancy or lactation status; beta-blocker use in pregnant or breastfeeding patients needs dedicated pharmacoepidemiological study, as our FAERS analysis cannot characterise risks in these subpopulations. Ninth, five drug–event pairs met Evans’ criteria on the ROR point estimate while the lower limit of the 95% confidence interval was below 2.0 (cerebrovascular accident, tachycardia and atrial tachycardia for atenolol; cardio-respiratory arrest for bisoprolol; cardiomegaly for nebivolol), so the strength of these signals should be regarded as borderline. Tenth, because the ROR and IC for each drug were computed against the whole FAERS background rather than against the other two beta-blockers, and because the observation windows and background totals differ between drugs, the analysis characterises each agent’s reporting pattern and does not support a head-to-head ranking of the three agents. Despite these limitations, the use of dual signal detection methods (ROR and IC), adherence to Evans’ criteria, and the large sample size accrued over each drug’s full FAERS reporting history strengthen confidence in the pharmacovigilance signals identified.
5. Conclusions
This study identified significant cardiovascular pharmacovigilance signals for all three beta-blockers analysed, with differences between agents in signal magnitude, severity, and reported fatal-outcome proportions. Bisoprolol showed the highest disproportionality signals overall, especially for diastolic dysfunction and chronic cardiac failure; these signals should be interpreted in the light of channelling bias, given bisoprolol’s guideline-endorsed role in heart failure management. Atenolol’s strongest signal was bradycardia, reported mainly in older patients, consistent with its pharmacological profile as a non-vasodilatory beta-1 blocker. Nebivolol had the lowest overall reporting volume; this should not be equated with a safer profile, because counts were not adjusted for exposure and its observation window was the shortest of the three. Paediatric reports were uncommon for atenolol and bisoprolol and nearly absent for nebivolol; none of the three carries FDA approval in this age group, and these reports call for clinical awareness rather than regulatory action. The signal differences identified here are hypothesis-generating, cannot establish causality and should not be used as a basis for choosing between agents. Until confirmatory data are available, older patients receiving any of the three agents should be monitored closely for bradycardia and haemodynamic instability. More broadly, large-scale pharmacovigilance complements clinical trial evidence: it shows which events are reported disproportionately often for each agent in routine practice, in which patients and with what outcomes. Controlled trials are rarely designed or powered to answer these questions.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/cardiovascmed29040041/s1. Table S1: Characteristics of unique atenolol reports for each of the 38 cardiovascular adverse events in Table 1, by sex, drug role, age group, reporter country and serious outcome. Table S2: Characteristics of unique bisoprolol reports for each of the 36 cardiovascular adverse events in Table 2, by the same characteristics; for bradycardia only the report count is given (see table note). Table S3: Characteristics of unique nebivolol reports for each of the 25 cardiovascular adverse events in Table 3, by the same characteristics.
Author Contributions
Conceptualization: A.P.S., R.P., A.A.-L., V.K., and M.N.; Project administration: A.P.S.;., R.P., and A.A.-L.; Supervision: A.P.S., R.P., and A.A.-L.; Methodology: A.P.S., V.K., and M.N.; Formal analysis: V.K., H.V., and M.N.; Investigation: V.K. and H.V.; Data curation: V.K. and H.V.; Writing, original draft: V.K., H.V., and A.P.S.; Writing—review and editing: V.K., H.V., R.P., A.A.-L., and A.P.S. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by grants from the US National Institutes of Health (R01 HL185027) to A.P.S. and the VA Merit award (I01CX002684) to A.A.-L.
Institutional Review Board Statement
This study used de-identified, publicly available data from the FDA Adverse Event Reporting System (FAERS) database. As no human subjects were directly involved and all data are freely accessible without personal identifiers, institutional review board (IRB) approval was not required in accordance with applicable federal regulations (45 CFR 46.102(e)).
Informed Consent Statement
Not applicable. This study analysed de-identified, publicly available reports and did not involve human subjects.
Data Availability Statement
The data analysed in this study are publicly available from the FDA Adverse Event Reporting System (FAERS) and were accessed through OpenVigil 2.1 (https://openvigil.sourceforge.net; accessed on 27 September 2026). The query covered each drug’s available FAERS reporting history from the earliest records in OpenVigil 2.1 (first quarter 2004 for atenolol and bisoprolol; from initial FDA approval on 17 December 2007 for nebivolol) through the third quarter of 2025 (FAERS 2025 Q3). All disproportionality estimates are reported in Table 1, Table 2 and Table 3, and case-level characteristics are summarised in Supplementary Tables S1–S3.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| CVD | Cardiovascular Disease |
| AEs | Adverse Events |
| CV-AEs | Cardiovascular Adverse Events |
| FDA | Food and Drug Administration |
| FAERS | FDA Adverse Event Reporting System |
| ROR | Reporting Odds Ratio |
| CAD | Coronary Artery Disease |
| MedDRA | Medical Dictionary for Regulatory Activities |
| CI | Confidence Interval |
| IC | Information Component |
| ICSR | Individual Case Safety Report |
| PRR | Proportional Reporting Ratio |
| PT | Preferred Term |
| LVH | Left Ventricular Hypertrophy |
| HFrEF | Heart Failure with Reduced Ejection Fraction |
| HFpEF | Heart Failure with Preserved Ejection Fraction |
| BCPNN | Bayesian Confidence Propagation Neural Network |
References
- Roth, G.A.; Mensah, G.A.; Johnson, C.O.; Addolorato, G.; Ammirati, E.; Baddour, L.M.; Barengo, N.C.; Beaton, A.Z.; Benjamin, E.J.; Benziger, C.P.; et al. Global Burden of Cardiovascular Diseases and Risk Factors, 1990–2019: Update From the GBD 2019 Study. J. Am. Coll. Cardiol. 2020, 76, 2982–3021. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lindstrom, M.; DeCleene, N.; Dorsey, H.; Fuster, V.; Johnson, C.O.; LeGrand, K.E.; Mensah, G.A.; Razo, C.; Stark, B.; Turco, J.V.; et al. Global burden of cardiovascular diseases and risks collaboration, 1990–2021. J. Am. Coll. Cardiol. 2022, 80, 2372–2425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vosko, I.; Zirlik, A.; Bugger, H. Impact of COVID-19 on cardiovascular disease. Viruses 2023, 15, 508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eltabeeb, A.M.; Rabe Hamed, R.; El-Nabarawi, M.A.; Teaima, M.H.; Abdellatif, M.M. Recent Advances of β-blockers as drug repurposing approach: A systematic review. Bull. Pharm. Sci. Assiut Univ. 2024, 47, 681–698. [Google Scholar] [CrossRef] [Scilit]
- Diaconu, C.C.; Marcu, D.R.; Bratu, O.G.; Stanescu, A.M.A.; Gheorghe, G.; Hlescu, A.A.; Mischianu, D.L.; Manea, M. Beta-blockers in cardiovascular therapy: A review. J. Mind Med. Sci. 2019, 6, 216–223. [Google Scholar] [CrossRef] [Scilit]
- do Vale, G.T.; Ceron, C.S.; Gonzaga, N.A.; Simplicio, J.A.; Padovan, J.C. Three generations of β-blockers: History, class differences and clinical applicability. Curr. Hypertens. Rev. 2019, 15, 22–31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- James, P.A.; Oparil, S.; Carter, B.L.; Cushman, W.C.; Dennison-Himmelfarb, C.; Handler, J.; Lackland, D.T.; LeFevre, M.L.; MacKenzie, T.D.; Ogedegbe, O.; et al. 2014 Evidence-based guideline for the management of high blood pressure in adults: Report from the panel members appointed to the Eighth Joint National Committee (JNC 8). JAMA 2014, 311, 507–520. [Google Scholar] [PubMed]
- Heel, R.C.; Brogden, R.N.; Speight, T.M.; Avery, G.S. Atenolol: A review of its pharmacological properties and therapeutic efficacy in angina pectoris and hypertension. Drugs 1979, 17, 425–460. [Google Scholar] [PubMed]
- Johns, T.E.; Lopez, L.M., Jr. Bisoprolol: Is this just another beta-blocker for hypertension or angina? Ann. Pharmacother. 1995, 29, 403–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiss, R. Nebivolol: A novel beta-blocker with nitric oxide-induced vasodilatation. Vasc. Health Risk Manag. 2006, 2, 303–308. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Frishman, W.H. Beta-adrenergic receptor blockers. Adverse effects and drug interactions. Hypertension 1988, 11, II21–II29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meng, L.; Huang, J.; Jia, Y.; Huang, H.; Qiu, F.; Sun, S. Assessing fluoroquinolone-associated aortic aneurysm and dissection: Data mining of the public version of the FDA adverse event reporting system. Int. J. Clin. Pract. 2019, 73, e13331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, J.; Meng, L.; Yang, B.; Sun, S.; Luo, Z.; Chen, H. Safety profile of epidermal growth factor receptor tyrosine kinase inhibitors: A disproportionality analysis of FDA adverse event reporting system. Sci. Rep. 2020, 10, 4803. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Böhm, R.; von Hehn, L.; Herdegen, T.; Klein, H.J.; Bruhn, O.; Petri, H.; Höcker, J. OpenVigil FDA—Inspection of U.S. American Adverse Drug Events Pharmacovigilance Data and Novel Clinical Applications. PLoS ONE 2016, 11, e0157753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bate, A.; Evans, S.J.W. Quantitative signal detection using spontaneous ADR reporting. Pharmacoepidemiol. Drug Saf. 2009, 18, 427–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Drugs@FDA: FDA-Approved Drugs. Tenormin (Atenolol), NDA 018240; Zebeta (Bisoprolol Fumarate), NDA 019982; Bystolic (Nebivolol), NDA 021742. Available online: https://www.accessdata.fda.gov/scripts/cder/daf/ (accessed on 26 September 2026).
- Evans, S.J.; Waller, P.C.; Davis, S. Use of proportional reporting ratios (PRRs) for signal generation from spontaneous adverse drug reaction reports. Pharmacoepidemiol. Drug Saf. 2001, 10, 483–486. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bate, A.; Lindquist, M.; Edwards, I.R.; Olsson, S.; Orre, R.; Lansner, A.; De Freitas, R.M. A Bayesian neural network method for adverse drug reaction signal generation. Eur. J. Clin. Pharmacol. 1998, 54, 315–321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Norén, G.N.; Hopstadius, J.; Bate, A. Shrinkage observed-to-expected ratios for robust and transparent large-scale pattern discovery. Stat. Methods Med. Res. 2013, 22, 57–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ram, C.V.S. Beta-blockers in hypertension. Am. J. Cardiol. 2010, 106, 1819–1825. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chobanian, A.V.; Bakris, G.L.; Black, H.R.; Cushman, W.C.; Green, L.A.; Izzo, J.L., Jr.; Jones, D.W.; Materson, B.J.; Oparil, S.; Wright, J.T., Jr.; et al. Seventh report of the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure. Hypertension 2003, 42, 1206–1252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dahlöf, B.; Devereux, R.B.; Kjeldsen, S.E.; Julius, S.; Beevers, G.; de Faire, U.; Fyhrquist, F.; Ibsen, H.; Kristiansson, K.; Lederballe-Pedersen, O.; et al. LIFE Study Group. Cardiovascular morbidity and mortality in the Losartan Intervention For Endpoint reduction in hypertension study (LIFE): A randomised trial against atenolol. Lancet 2002, 359, 995–1003. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- The CIBIS-II Investigators and Committees. The Cardiac Insufficiency Bisoprolol Study II (CIBIS-II): A randomised trial. Lancet 1999, 353, 9–13. [PubMed]
- Ko, D.T.; Hebert, P.R.; Coffey, C.S.; Curtis, J.P.; Foody, J.M.; Sedrakyan, A.; Krumholz, H.M. Adverse effects of β-blocker therapy for patients with heart failure: A quantitative overview of randomized trials. Arch. Intern. Med. 2004, 164, 1389–1394. [Google Scholar] [PubMed]
- Dézsi, C.A.; Szentes, V. The real role of β-blockers in daily cardiovascular therapy. Am. J. Cardiovasc. Drugs 2017, 17, 361–373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cannata, F.; Stefanini, G.; Carlo-Stella, C.; Chiarito, M.; Figliozzi, S.; Novelli, L.; Lisi, C.; Bombace, S.; Panico, C.; Cosco, F.; et al. Nebivolol versus placebo in patients undergoing anthracyclines (CONTROL Trial): Rationale and study design. J. Cardiovasc. Med. 2023, 24, 469–474. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yancy, C.W.; Jessup, M.; Bozkurt, B.; Butler, J.; Casey, D.E., Jr.; Drazner, M.H.; Fonarow, G.C.; Geraci, S.A.; Horwich, T.; Januzzi, J.L.; et al. 2013 ACCF/AHA guideline for the management of heart failure: A report of the American College of Cardiology Foundation/American Heart Association Task Force on Practice Guidelines. J. Am. Coll. Cardiol. 2013, 62, e147–e239. [Google Scholar] [PubMed]
- de Bruin, R.; van Dalen, S.L.; Franx, S.J.; Ramaswamy, V.V.; Simons, S.H.P.; Flint, R.B.; van den Bosch, G.E. The Risk for Neonatal Hypoglycemia and Bradycardia after Beta-Blocker Use during Pregnancy or Lactation: A Systematic Review and Meta-Analysis. Int. J. Environ. Res. Public Health 2022, 19, 9616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katsi, V.; Papakonstantinou, I.P.; Papazachou, O.; Makris, T.; Tsioufis, K. Beta-Blockers in Pregnancy: Clinical Update. Curr. Hypertens. Rep. 2023, 25, 13–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van der Bijl, M.F.; Verdonk, K.; Roeters Van Lennep, J.E. Balancing health and safety: Cardiovascular medications during pregnancy and lactation. Case Rep. Womens Health 2024, 43, e00648. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.