


Abstract
A substantial number of survivors of disasters, pandemics, and other severe stressors develop persistent distress that impairs mental health and well-being. However, only a few brief psychological interventions target distress or subclinical symptoms. This systematic review aimed to identify and describe brief psychological interventions to reduce distress or subclinical symptoms in survivors of disasters, pandemics, and other severe stressors. Based on a systematic literature search (MEDLINE, PsycINFO, PSYNDEX, PTSDpubs, and Web of Science), we reviewed published studies and study protocols on self-help, psychosocial support, or brief psychotherapeutic interventions to reduce distress and/or subclinical symptoms following natural hazards and man-made disasters, pandemics, or other traumatic events. We included 27 published studies or study protocols (n = 15 RCTs, n = 3 controlled pre–post studies, and n = 9 uncontrolled pre–post studies) describing 22 interventions. We found evidence for reducing psychological distress and/or subclinical symptoms in 9 out of 15 RCTs, 2 out of 3 controlled pre–post studies, and 9 out of 9 uncontrolled pre–post studies. One RCT provided evidence of increasing well-being. Innovative brief interventions have been developed to reduce distress and/or subclinical symptoms that have an emerging evidence base.
1. Introduction
Natural hazards and man-made disasters (e.g., floods and mass violence; [1]), pandemics (e.g., the COVID-19 pandemic; [2]), but also other traumatic events (e.g., train accidents; [3]) can lead to psychological harm. Children are a group particularly vulnerable to suffering the consequences of crises [4]. Most mental health problems following such severe stressors are of a subclinical severity, e.g., [5]. Consequently, there is a strong need for interventions that focus on reducing subclinical symptoms in individuals who have been exposed to a particular stressor but lack a formal mental health diagnosis [6].
Brief evidence-based interventions might be useful to promote recovery and prevent mental disorders. For example, psychological first aid (PFA) is widely known as an evidence-based approach to help individuals and communities cope in the immediate aftermath of a traumatic event [7]. Furthermore, interventions based on cognitive behavioral therapy (CBT) have been found to be effective in reducing distress and subclinical symptoms in individuals who have experienced traumatic events, e.g., [8,9]. The COVID-19 pandemic, which is an acute global challenge and has been shown to have a major impact on psychological stress levels, e.g., [10,11], also highlights the need for mental health treatments. For example, a study conducted in China in 2020 found that 53.8% of respondents rated the psychological impact of the outbreak as moderate or severe [12]. Therefore, we chose to also include COVID-19-related studies within this systematic review.
However, developing and evaluating brief interventions to target subclinical distress after disaster and trauma is a relatively new research field. A couple of narrative or systematic reviews summarized brief interventions on the specific subtypes of disasters, e.g., mental health impacts in response to climate change [13] or the Indian Ocean Tsunami in 2004 [14], or were narrowed to particular age groups, e.g., children and adolescents [15]. There are also a number of reviews that summarize interventions for individuals with a diagnosed mental health disorder, such as PTSD, e.g., [16,17]. A comprehensive systematic review of studies describing or evaluating brief interventions to reduce psychological distress and/or subclinical symptoms in disaster-, pandemic-, or trauma-exposed individuals has not been conducted.
The aims of this systematic review were to (1) systematically identify brief interventions to reduce psychological distress and/or subclinical symptoms in survivors of disasters, pandemics, and other traumatic events and (2) describe their effectiveness.
2. Materials and Methods
Our report of this systematic review followed the ‘Preferred Reporting Items for Systematic Reviews and Meta-Analyses’ reporting guidelines, PRISMA; [18]. The review protocol was not published on PROSPERO.
2.1. Eligibility Criteria for Study Inclusion
We included published peer-reviewed studies or study protocols in the German or English language (1) that evaluated or planned to evaluate brief psychosocial support, self-help, or brief (≤12 sessions) psychotherapeutic interventions for survivors of disasters, pandemics, and other traumatic events (2) that described or examined interventions to reduce psychological distress, subclinical symptoms of any type of mental disorder, or symptoms of adjustment disorder. To provide an overview not only of completed studies but also of planned or ongoing studies of brief interventions, we included study protocols in this review.
We excluded studies or study protocols that (1) aimed to treat a mental disorder except for adjustment disorder, and studies (2) published before 2010.
2.2. Data Sources
We performed a systematic literature search in five databases (MEDLINE, PsycINFO, PSYNDEX, PTSDpubs, and Web of Science) from 1 January 2010 to 1 October 2021. Additionally, we identified studies by hand searching reference lists and contacting researchers.
2.3. Search Strategy
The search strategy was based on the PICOS (participants, interventions, comparisons, outcomes, and study design) approach [19]: Section S1 Populations: Disaster-, pandemic-, or trauma-exposed (e.g., term/pandemics); S2 Interventions: Brief interventions (e.g., indicated or low-intensity or brief or behavioral or short-term or low-threshold).mp. adj2 (therap* or treat* or intervention* or modification or train* or program*.ti,ab.); S3 Outcomes: Mental health outcomes relevant for disaster, pandemic, and trauma (e.g., psychological distress OR subclinical symptoms OR adjustment disorder* OR depress* or anxiet* or psychosocial dysfunction*.ti,ab.); S4 Study design: Feasibility or pilot studies, pre–post studies, controlled studies, randomized controlled trials (e.g., Clinical trials/).
2.4. Selection Process
Two reviewers (IL and AP) independently screened the titles and abstracts following the inclusion and exclusion criteria. The characteristics of the published studies or study protocols were extracted in an excel table (i.e., authors, year, title, journal, inclusion and exclusion criteria, and the final decision for eligibility). When disagreements occurred between the two reviewers, a third reviewer (AL) was consulted to decide together to include or exclude the study or protocol.
2.5. Data Collection Process and Synthesis
Data from the included studies were extracted independently by two reviewers (IL and AP) in an excel sheet. When disagreements in the extracted data occurred between the two reviewers, a third reviewer (AL) was consulted. The following data were extracted: study, intervention name and description, study design, timepoint of intervention after stressor exposure (e.g., 60 days or more), number of sessions, type of stressor, target population, delivery format, assessed outcomes, and results (see Appendix A).
3. Results
3.1. Study Selection
Database searches identified n = 319 records; 5 additional records were found through searching reference lists and contacting researchers (Figure 1). After removing 34 duplicates, screening abstracts, and reviewing full articles and study protocols, 21 studies and 6 study protocols were included that reported on brief interventions to reduce distress and/or subclinical symptoms in survivors of disasters, pandemics, or trauma.
Figure 1.
Flowchart of the review process.
3.2. Study Characteristics
The study characteristics are listed in Table 1. The 27 studies or study protocols were from 16 countries; most were from America or Asia. More than half of the described studies (n = 15; 55.6%) were RCTs; nine studies (33.3%) used an uncontrolled pre–post study design, and three studies (11.1%) were designed as a controlled pre–post study. Out of the 27 articles/study protocols, 11 articles/study protocols (40.7%) described studies on the survivors of natural hazards, 3 (11.1%) described studies on the survivors of man-made disasters, 8 (29.6%) described studies on the survivors of pandemics, and 5 (18.5%) described studies on survivors of other types of trauma. Twelve (44.4%) articles/protocols described studies examining the efficacy of psychosocial support interventions; nine (33.3%) articles/protocols described studies on the efficacy of brief psychotherapeutic treatments; and six (22.2%) articles/protocols reported on studies of self-help interventions.
Table 1.
Characteristics of the included published articles/protocols on brief interventions (n = 27).
4. Intervention Characteristics and Study Results
The characteristics of the brief interventions described in the included articles/protocols are summarized in Table A1 of Appendix A. More detailed information on intervention characteristics and results (e.g., effect sizes) of the included studies/protocols are provided in Table A2 of Appendix A.
4.1. Self-Help Programs
Five self-help programs targeted adults, and one intervention focused on adolescents and their parents. The interventions were mostly conducted online; only one intervention was designed in a hybrid format. Four of the six self-help interventions were developed in a pandemic context, and the remaining two interventions were designed to be applied after disasters. Three of the six interventions comprised additional psychotherapeutic or psychological support.
4.1.1. Pandemic-Focused Interventions
Computerized CBT (cCBT) [20] is a one-week online self-help intervention based on cognitive behavioral therapy (CBT). cCBT aims to reduce acute psychological distress and symptoms of depression, anxiety, and insomnia in adults during the COVID-19 pandemic. Three modules cover cognitive training, cognitive consolidation, and behavioral interventions. The intervention was tested in an RCT during the COVID-19 pandemic in China with N = 252 adult COVID-19-infected patients [20]. A significant decrease in depressive and anxiety symptoms was found at one-month follow-up in the cCBT + treatment as usual (TAU) group compared to a TAU-only group (psychological assessments, psychological support, consultations about well-being, and COVID-19).
The Individualized Short-term Training Program [21] is a self-help program that is combined with psychological support targeting depression and anxiety symptoms of emergency nurses during the COVID-19 pandemic. The program includes online and face-to-face elements. The length of the intervention and the number of sessions were not reported by the authors. The intervention covers knowledge about diagnosing COVID-19, handling and safety precautions with infected patients, and psychological support including mindfulness-based stress reduction. Psychologists provide online and practical face-to-face training and psychological support to nursing staff. The self-help online training is delivered asynchronously through videos, graphics, and texts. In an uncontrolled pre–post study, the authors of the intervention evaluated the Individualized Short-term Training Program in N = 71 female Chinese nurses working in an emergency isolation department during the COVID-19 pandemic [21]. A significant anxiety reduction but not in depression was found post-training.
Online Psychotherapy Tool (OPTT) [22] is a 9-week program to reduce mental health problems in adults during the COVID-19 pandemic. OPTT consists of a self-help module and psychotherapeutic support, with the main focus on self-help. The intervention combines CBT, mindfulness therapy, and problem-based therapy. Weekly 40 min self-guided web-based online modules are available, participants can interact with their therapist through a chat function within the online platform, and a therapist provides individual written feedback. The authors plan to conduct a nonrandomized controlled trial with N = 80 Canadian adults with anxiety symptoms during the COVID-19 pandemic [22]. The effects of the intervention on anxiety, depressive symptoms, resilience, and quality of life will be compared to a TAU control group. No study results have been reported yet.
“My Health too” [23] is a seven-session CBT-based online self-help program with an option for psychotherapeutic support (i.e., the possibility to call a CBT-trained psychologist). The program was designed for health care workers to reduce psychological distress during the COVID-19 pandemic and to prevent its long-term consequences. A total of 7 20 min asynchronous (i.e., the interaction does not happen in real time) video sessions cover psychoeducation on stressors, adaptive behavioral and cognitive coping strategies, mindfulness and acceptance of stressors, promoting action toward values, addressing barriers and motivation, and self-compassion. Weiner et al. [23] is currently investigating whether the intervention reduces distress in N = 120 French healthcare workers during the COVID-19 pandemic. In an RCT, the intervention group is compared to an active control group receiving bibliotherapy. No results have been published to date.
4.1.2. Disaster-Focused Interventions
The web-based Bounce Back Now (BBN) [24] is a four-session self-help program for disaster-affected adolescents and parents aiming to reduce post-disaster mental and behavioral problems. Four modules provide skills and strategies to cope with stress- and trauma-related symptoms, smoking, and alcohol use, and mood-related symptoms. The stress and trauma module provides education about PTSD symptoms and evidence-based trauma-focused interventions, a reduction in the avoidance of traumatic cues, coping strategies, and anxiety management. An additional self-help intervention for adults (Adult Self-Help, ASH) can be added to BBN, BBN + ASH [24]. A pre–post-test study with N = 979 US adolescents affected by tornadoes in Missouri and Alabama in 2011 [25] revealed a significant decline in PTSD symptoms in the BBN condition at 4- and 12-month follow-up compared to the control condition in which no education or recommendations were offered. Instead, participants were given quizzes and questions about myths and facts.
The Disaster Recovery Web (DRW) Project [26] is a self-help web-based program for adults affected by natural hazards to reduce symptoms of PTSD, depression, and anxiety. It is applied in the acute aftermath of a disaster and consists of four web modules educating about post-traumatic stress, depressed mood, generalized anxiety, and panic. There is no interaction with a therapist. A pre–post-test study without a control group conducted after Hurricane Ike in Texas with N = 1249 adult survivors [27] found no significant reduction in depressive symptoms or PTSD symptoms 4-months post-intervention.
4.2. Psychosocial Support Programs
Five psychosocial support programs targeted adults, and one intervention was developed for children and their parents. Two of the six psychosocial support programs were pandemic-focused, one intervention was disaster-focused, and three interventions targeted other types of trauma. Four interventions were designed as face-to-face interventions, although two of them could be applied either in a face-to-face or online format. The remaining two interventions were designed as online or phone-based interventions.
4.2.1. Pandemic-Focused Interventions
Grief Counseling for Adults [28] is a psychosocial support program to promote better life adaptation after loss. The program was developed to support bereaved Chinese people during COVID-19. A trained counselor delivers 8 to 10 online sessions lasting 1 h. Grief counseling for adults is based on current grief treatment approaches, including meaning reconstruction [29]; complicated grief treatment, CGT; [30], and cognitive behavioral therapy for complicated grief, CBT-CG; [31]. It covers understanding and managing grief reactions; managing painful emotions; learning self-care; increasing contact with others; coping with difficult days; and adapting to a new life. Grief counseling for adults will be evaluated in a single-blinded RCT among N = 160 bereaved Chinese adults who have lost their first-degree relative during the COVID-19 pandemic [28]. The researchers aim to evaluate the effects of the intervention on prolonged grief symptoms, PTSD, and depression at baseline, post-intervention, and at 3-month follow-up relative to a wait list control group. The results of this study have not yet been published.
Resiliency Engagement and Care in Health (REaCH) [32] is a 4-week psychosocial intervention for people with socioeconomic vulnerability during the COVID-19 pandemic. REaCH targets mental well-being, depressive symptoms, and perceived social support by providing proactive engagement and crisis intervention, problem-solving-oriented support therapy, and assertive linkage with community resources. It involves a synchronous telephonic befriending program consisting of 4 phone calls, each 0.5 to 1 h, delivered by lay workers and nonhealth professionals. The authors plan a cluster-randomized controlled trial (cRCT) to examine the REaCH intervention with N = 1440 economically disadvantaged and vulnerable Indian adults during the COVID-19 pandemic [32]. The intervention group will be compared with a control group receiving four phone calls informing about COVID-19.
4.2.2. Disaster-Focused Interventions
The Mental Health Integrated Disaster Preparedness (MHIDP) intervention [33] is aimed at improving disaster preparedness, reducing mental health symptoms, and fostering community cohesion in adults affected by natural hazards in Haiti. MHIDP includes establishing safety and practicing skills to cope with disaster-related distress, the provision of space for sharing personal experiences, and training in disaster preparedness (e.g., creating preparedness kits comprised of basic supplies). The content is provided within 3 sessions lasting 6 h. MHIDP intervention was evaluated in an RCT among N = 480 adults exposed to earthquakes and floods in Haiti [33]. The program was delivered by 2 trained lay mental health workers in groups of up to 20 participants. The intervention group was compared to a wait list control group across three timepoints (i.e., baseline, 3–4-month, and 7–8-month follow-up). Disaster preparedness behavior significantly increased among intervention participants, while depressive, anxiety, and PTSD symptoms significantly decreased at both follow-ups. A significant reduction in functional impairment was evident at 3–4-month follow-up but disappeared at 7–8-month follow-up.
4.2.3. Interventions Focusing on Other Severe Stressors
Problem Management Plus (PM+) [34] is a brief five-session program to reduce distress in adults living in communities affected by adversity or crises. PM+ includes managing stress, managing problems, behavioral activation (i.e., get going and keep doing), and strengthening social support. Trained nonspecialist lay providers deliver the intervention. PM+ was tested in a cRCT in N = 121 participants [35] in earthquake-affected communities in Nepal. Participants in the treatment group received five sessions of PM+ in a group setting, and participants in the control group received enhanced TAU (which entailed brief psychoeducation and the provision of referral options to primary care services). Depressive symptoms, daily functioning, psychological distress, PTSD symptoms, and psychosocial problems improved more in the PM+ arm than the enhanced TAU arm at 8 weeks post-intervention. A cRCT [36] investigated an adapted PM+ program with six to eight participants per group, which was compared to enhanced usual care (psychoeducation and a referral option to primary care providers trained in mental healthcare). N = 611 adults from disaster-prone regions in Nepal received 5 weekly sessions of approximately 2.5 h. The PM+ group showed lower psychological distress and depression symptoms, and had fewer “heart-mind” problems compared to the control group at 3-months post-treatment. However, the PM+ group did not show an improvement in functional impairment and PTSD symptoms. An adapted version of PM+ for participants living in conflict-affected Peshawar in Pakistan was tested in a pilot RCT [37] in N = 60 participants, compared to enhanced TAU (mental health care management by trained general care practitioners). Functioning and PTSD symptoms improved more in the PM+ group post-intervention, but no significant changes in psychological distress could be observed between the groups. The effects of PM+ were compared to facility-based enhanced TAU provided by community nurses in an RCT in N = 421 Kenyan women exposed to physical or sexual abuse [38]. The PM+ group showed significant improvements in psychological distress, daily functioning, PTSD symptoms, and personally identified problems in the change from baseline to 3-month follow-up. An RCT [39] is planned to examine an adapted version of videoconferencing PM+ in N = 240 adults in a group context of 3–4 participants in Sydney, Australia. The intervention will be delivered over 6 weekly 60 min sessions and will specifically target COVID-19-related distress. The control group will receive enhanced TAU (emailed handouts with PM+ strategies and no expert assistance). In addition to psychological distress, rumination, sleep problems, anhedonia, social support, and COVID-19-related stress will be examined.
The Skills fOr Life Adjustment and Resilience program (SOLAR) [6] is a brief five-session psychosocial support program to reduce persistent distress or subclinical symptoms in adults impacted by a disaster or trauma. It is delivered by trained coaches that can be non-mental-health professionals. SOLAR covers six modules: healthy living, managing strong emotions, getting back into life, coming to terms with the disaster, managing worry and rumination, and maintaining healthy relationships. An uncontrolled pre–post 3-month follow-up pilot study in N = 15 Australian bushfire survivors [6] demonstrated reductions in psychological distress, post-traumatic stress symptoms, and functional impairment at post-treatment. Another controlled pre–post pilot study [40] proved the acceptability, feasibility, and efficacy of a culturally adapted version of SOLAR with N = 99 Pacific Islanders that were exposed to Tropical Cyclone Pam in 2015. SOLAR was administered in a group format of up to 10 participants compared to a TAU control group, which included informal familial, community, and church-based support. Reductions in psychological distress, PTSD symptoms, and functional impairment were found in the intervention group relative to the control group from pre- to post-intervention. The SOLAR group program was evaluated in a randomized controlled feasibility study in N = 30 German survivors of different types of trauma [41]. Participants in the SOLAR group intervention showed a greater reduction in psychological distress, symptoms of insomnia, patient-centered outcomes, functional impairment, quality of life, and perceived social support post-intervention, compared to a wait list control group. Symptoms of PTSD did not decrease more greatly in the intervention group relative to the control group.
Listen Protect Connect (LPC) [42] is a school-based PFA program for children. LPC provides basic psychological support and aims to reduce the initial distress of students and parents following traumatic events, such as community disasters, emergencies, or personal trauma. LPC is delivered by non-mental-health professionals. It is based on the five-step crisis response strategy “Listen, Protect, Connect—Model & Teach” [42]. An adapted version of LPC (composed of three steps: listen, protect, and connect) was piloted in an uncontrolled pre–post study in N = 20 US-American children impacted by the Great Flood of Iowa in 2008 to reduce PTSD symptoms [43]. The school nurse provided 1 on average 25 min LPC session to each student. Depressive symptoms and felt connectedness to their school improved at 4 weeks post-intervention. Perceived social support increased at 8 weeks post-intervention. PTSD symptoms (i.e., re-experiencing, avoidance, and arousal) did not significantly decrease at 8 weeks post-intervention.
4.3. Brief Psychotherapeutic Programs
We identified ten brief psychotherapeutic interventions, of which four were developed for children or adolescents. Two brief psychotherapeutic interventions were disaster-focused; the remaining eight interventions addressed survivors of other types of trauma, although some of these interventions could also be applied in the aftermath of natural hazards and man-made disasters. There were no interventions specifically designed for use during a pandemic. All interventions were designed as face-to-face interventions.
4.3.1. Disaster-Focused Interventions
The Brief School-Based Cognitive Behavioral Intervention [44] is a one-session psychotherapeutic intervention for disaster-affected adolescents to reduce PTSD and depressive symptoms. The intervention is based on the cognitive behavioral model of post-traumatic stress disorder [45] and consists of a single 90 min session, delivered by trained CBT clinical psychologists. It involves four steps: the identification of problems, psychoeducation, decreasing negative appraisal, and the practice of relaxation breathing. A pilot study [44] examined the intervention in the context of pre-, post-, and follow-up measurements without a control group. N = 22 adolescents affected by the Great East Japan Earthquake in 2011 were divided into 2 groups, each with 11 adolescents. The results showed significant improvements in PTSD symptoms post-intervention which were maintained at a 4-month follow-up. There was no significant reduction in depressive symptoms.
Strength after Trauma (StArT) [46] is a brief manual-based trauma-focused CBT intervention for disaster-exposed adolescents to reduce PTSD symptoms. StArT compromises five modules: psychoeducation, cognitive restructuring, exposure, problem solving, and relapse prevention. It includes 10 sessions of 1 h and is delivered by a psychotherapist. StArT was piloted in an uncontrolled pre–post study in N = 6 American children exposed to Hurricane Katrina in 2005 [47]. The results suggest that the 10-session intervention was feasible when conducted in a school setting. Negative cognitions and PTSD symptoms significantly declined between pre- and post-treatment. No significant reduction in anxiety symptoms could be observed.
4.3.2. Interventions Focusing on Other Severe Stressors
Cognitive Behavioral Therapy for Post-disaster Distress (CBT-PD) [48] is an 8- to 12-session CBT intervention for adults impacted by major disasters, terrorism, or traumatic events to reduce post-disaster distress. The intervention is delivered by trained therapists. CBT-PD includes psychoeducation, coping skills, and cognitive restructuring. Coping skills include breathing retraining and behavioral activation. In an uncontrolled pre–post-test study, N = 342 adults from New York State, US, exposed to Hurricane Sandy in 2012 [49], were assessed at referral, baseline, intermediate treatment, as well as at post-treatment and 5-month follow-up. Significant reductions in distress throughout the intervention were found, with large improvements from pre- to post-treatment.
Exposure-based Cognitive Behavioral Therapy for children [50] aims to reduce PTSD symptoms in children in 4–8 60 min sessions with possible parent support. The intervention includes five elements: psychoeducation, repeated exposure to the trauma memory, cognitive restructuring, exploring and correcting undesired or unhelpful coping behavior, and relapse prevention. Eye Movement Desensitization and Reprocessing (EMDR) based on Shapiro [51] is typically delivered in 6–12 sessions to reduce PTSD symptoms in children, adolescents, and adults. EMDR applies an eight-phase approach: (phase 1) history taking, (phase 2) preparing the client, (phase 3) assessing the target memory, (phase 4–7) processing the memory to adaptive resolution, and (phase 8) evaluating treatment results. De Roos et al. [52] conducted an RCT comparing exposure-based CBT and EMDR in reducing disaster-related PTSD symptoms in N = 52 children and adolescents aged from 4 to 18, 6 months after the explosion of a fireworks company in Enschede, Netherlands. Participants with disaster-related clinical symptoms were included in the study. They received up to 4 individual sessions delivered by a clinical psychologist over 4–8 weeks along with up to 4 sessions of parental guidance. Both treatment approaches produced significant reductions in PTSD symptoms, anxiety symptoms, depressive symptoms, and behavioral problems post-intervention. The study did not find significant differences in the outcomes between the groups.
The Preventive Resilience Training for Unaccompanied Refugee Minors [53] is a CBT intervention consisting of 6 90 min sessions to reduce trauma-related symptoms such as PTSD, depression, and anxiety in adolescent refugees with trauma exposure. The resilience training includes psychoeducation, cultural resources, and emotion regulation strategies. The intervention is a group-based program delivered by clinical psychologists or social workers with training in trauma therapy. The authors conducted an RCT in N = 55 Australian male adolescent refugees from Afghanistan and Pakistan with flight experience [53]. The intervention group showed an increase in general well-being at 7 weeks post-intervention compared to the wait list control group. However, no reduction in anxiety, PTSD, and depressive symptoms could be found.
Mindfulness-Based Stress Reduction (MBSR) [54] is a transdiagnostic intervention to improve mindfulness. The intervention aims at developing four mindfulness practices (sitting meditation, walking meditation, mindful movement, and a body scan) to influence perceived distress, anxiety, depression, emotion dysregulation, and PTSD symptoms. It consists of 8 weekly 120 min sessions and one 240 min retreat session delivered face-to-face by an experienced MBSR teacher in groups of up to 30 participants [55]. Gallegos et al. [56] piloted MBSR in an uncontrolled pre–post study in N = 50 US-American adult women with a history of interpersonal childhood trauma. The results showed a significant reduction in perceived distress, depressive symptoms, anxiety, emotion dysregulation, and PTSD symptoms at post-intervention and 1-month follow-up compared to baseline. Mindfulness also significantly increased.
The Trauma Therapy Program [57] is an intervention comprising 6 sessions of 90 min to reduce work-related distress in health practitioners working in emergency services. The intervention aims to reduce symptoms of anxiety, depression, and PTSD. The program incorporates trauma-focused cognitive behavioral therapy, TF-CBT [58], and eye movement desensitization and reprocessing, EMDR [51]. The intervention is delivered by therapists trained in TF-CBT or EMDR. The program was tested in an uncontrolled pre–post-test study in N = 429 emergency service professionals from the UK [57]. The intervention effectively reduced anxiety, depression, and PTSD symptoms post-treatment compared to pre-treatment.
Emotional Freedom Techniques (EFT) [59] is a brief psychotherapeutic intervention to reduce psychological distress and symptoms of depression, anxiety, and PTSD. The intervention has a flexible number of sessions depending on the type and severity of the problems. EFT includes trauma exposure, cognitive, and somatic therapeutic components; it combines the exposure to traumatic memories with self-acceptance statements derived from cognitive therapy while applying psychological acupressure (i.e., tapping) as a stress relief technique. EFT is delivered by EFT-certified therapists. The effect of 6 EFT sessions 60 min was examined in an RCT with N = 55 US veterans from Iraq or Afghanistan war [60]. The EFT intervention focused on combat-related traumatic events and was delivered in combination with the TAU of a Veteran Administration (VA) hospital. The results showed significant reductions in PTSD, anxiety, depression, hostility, obsessive–compulsive behavior, paranoia, phobic anxiety, psychoticism, and somatization in the EFT group compared to the TAU group at post-intervention. Improvement in symptoms was maintained until the 3-month and 6-month follow-up. Interpersonal sensitivity did not significantly improve.
Solution Focused Brief Therapy (SFBT) [61] is a brief future- and goal-oriented psychotherapeutic intervention for adolescents and adults which can be applied to a wide range of issues. The intervention, comprising 5 sessions of 45 min., aims to explore current resources and future hopes [62]. An RCT assessed the effectiveness of SFBT in a group of N = 76 Chinese adolescents to reduce anxiety symptoms during the COVID-19 pandemic [63]. The intervention group received 2–4 sessions of SFBT via videoconferencing within 2 weeks, whereas the wait list control group received 2–4 sessions of counseling service. It was hypothesized that participants assigned to SFBT would have better clinical outcomes in terms of anxiety symptoms, depressive symptoms, and coping strategies than participants in the control group. The study results have not been published yet.
5. Discussion
This systematic review aimed to identify and synthesize brief interventions to reduce distress and/or subclinical symptoms in individuals exposed to disasters, pandemics, or other traumatic events. We considered 27 published articles or study protocols (including 15 RCTs) that reported on 22 different brief interventions to reduce distress and/or subclinical symptoms. Out of the 27 included articles or protocols, 10 were published articles describing intervention studies, and 5 were study protocols.
5.1. Self-Help Programs
Six published articles or study protocols described studies on the efficacy of brief self-help interventions. Two articles reported on an RCT or an uncontrolled pre–post study evaluating self-help programs for COVID-19 survivors (cCBT and the Individualized Short-term Training Program). Both studies reported significant reductions in anxiety at one-month follow-up after the application of cCBT [20] and post-training after the application of the Individualized Short-term Training Program [21]. Only the RCT on cCBT found reductions in depressive symptoms post-intervention [20]. Hence, there is the first evidence for two self-help interventions, namely cCBT and individualized short-term training, based on one RCT and one uncontrolled pre–post study, that these self-help programs may reduce anxiety in COVID-19 survivors in the short-term. Two additional study protocols on self-help programs for COVID-19 survivors were identified which might provide further evidence in the future [22,23].
Two published studies evaluated self-help programs (BBN and the DRW Project) for survivors of natural hazards (i.e., tornadoes and hurricanes). One article reported on a controlled pre–post study that found a significant decline in PTSD symptoms in adolescents and their parents at follow-up measurements after the application of BBN [25]; another article reported on an uncontrolled pre–post study that found no evidence for the efficacy of the DRW Project to reduce PTSD or depressive symptoms [27]. The lack of effectiveness of the DRW Project could be attributed to the fact that it was applied by the participants one year after the disaster. This may result in individuals being less motivated to engage with this intervention or having already recovered on their own.
We found no published articles or study protocols on studies evaluating a self-help program for survivors of other types of traumatic events.
5.2. Psychosocial Support Programs
Twelve published articles or study protocols described the evaluation of psychosocial support programs. We did not identify any evidence for the efficacy of psychosocial support programs for COVID-19 survivors. Two study protocols have been published [28,32] that describe evaluation studies on psychosocial support programs among COVID-19 survivors, but no results have been published yet.
We identified evidence for one psychosocial support program (MHIDP intervention) targeting survivors of natural hazards (i.e., earthquakes and floods) to improve depressive, anxiety, and PTSD symptoms at follow-up assessments [33].
Nine identified published articles or study protocols described psychosocial support programs originally developed for survivors of other severe stressors, e.g., exposure to community adversity, crises, or interpersonal abuse. However, most of these interventions could be applied to other types of stressors, such as natural hazards. An uncontrolled pre–post study [43] showed that the psychosocial support intervention LPC [42] for children after experiencing traumatic events, such as community disaster, emergency, or personal trauma, was successful in reducing PTSD and depressive symptoms at post-intervention.
We found five published articles or study protocols that described PM+ [34] for communities affected by adversity or crises. Two RCTs on PM+ [37,38] indicated a significant improvement in PTSD symptoms and daily functioning after the provision of PM+ using an individual format. Significant improvements in psychological distress at 3-month follow-up were only observed in the study of Bryant and colleagues [38]. The results of two cRCTs [35,36] indicated that PM+ applied in a group significantly reduced psychological distress and depressive symptoms post-intervention. However, only in the study of Sangraula and colleagues [35], were PTSD symptoms significantly reduced post-intervention. We found one study protocol [39] that has not yet published results. Overall, the results of a few studies indicate that PM+ leads to a significant decline in psychological distress and PTSD symptoms post-treatment. Our systematic literature search yielded three articles or study protocols reporting on studies on SOLAR [6]. A pilot RCT [41] reported significant reductions in psychological distress; PTSD symptoms did not significantly decrease in the SOLAR group relative to the control group, as PTSD symptoms declined in both groups. The results of one uncontrolled [6] and one controlled pre–post study [40] indicated significant reductions in psychological distress and PTSD symptoms. In sum, there is emerging evidence based on three studies that SOLAR leads to a significant decline in psychological distress, and evidence based on two (un)controlled pre–post studies that SOLAR effectively reduces PTSD symptoms.
Overall, in the field of psychosocial support programs, most evidence for their efficacy is currently available for PM+, for which some RCTs have been conducted. SOLAR is another promising psychosocial support program with an emerging evidence base.
5.3. Brief Psychotherapeutic Programs
Nine studies examined or planned to examine the efficacy of brief (i.e., max. 12 sessions) psychotherapeutic interventions. No studies described interventions designed for an application during a pandemic. Two articles [44,47] described uncontrolled pre–post studies that examined brief psychotherapeutic interventions (Brief School-based Cognitive Behavioral Intervention and StArT) for survivors of natural hazards (i.e., earthquakes and hurricanes). Both studies conducted with children and/or adolescents found that PTSD symptoms significantly decreased post-intervention.
Seven published articles or study protocols described brief psychotherapeutic interventions originally developed for survivors of other severe stressors, such as terrorism or traumatic events. Most of these interventions can also be applied to other types of stressors, such as disasters or pandemics. Overall, the results of five studies showed that the interventions EFT, exposure-based CBT, EMDR, MBSR, CBT-PD, and the Trauma Therapy Program were successful in reducing psychological distress and/or subclinical symptoms [49,52,56,57,60]. One RCT on the Preventive Resilience Training for Unaccompanied Refugee Minors reported no reduction in anxiety, PTSD, and depressive symptoms at a seven-week follow-up, although well-being significantly increased [53]. The reasons for the lack of effectiveness could be that the treatment dose was too low or the assessment of outcomes at only 7 weeks post-intervention might not be enough time to observe significant changes in symptoms. One study protocol described planning to examine the efficacy of SFBT on anxiety and depressive symptoms during the COVID-19 pandemic [63].
Overall, these findings suggest that there is the first evidence, especially on the efficacy of exposure-based CBT, EMDR, and EFT based on one RCT each. Additionally, there is a preliminary indication based on one uncontrolled pre–post study each that CBT-PD, MBSR, and Trauma Therapy Program may be effective in reducing psychological distress and/or subclinical symptoms.
5.4. Limitations
The interpretation of results synthesized in this systematic review should be interpreted considering the quality of the included studies. Thus, this systematic review is not without limitations. Several studies consisted of small sample sizes; more than half of the included studies considered fewer than 100 participants. Although a larger sample size would be desirable to achieve greater statistical power and generalizability in the results, there are challenges such as resource limitations and participant dropout making this difficult. In addition to 15 RCTs, 9 uncontrolled pre–post studies and 3 controlled pre–post studies were included in this review. Pre–post studies suffer from impaired internal validity and the associated limited interpretability of results. Furthermore, the long-term effectiveness of some interventions cannot be assessed because ten completed studies on these interventions did not report follow-up measurements [21,27,35,36,37,40,41,47,53,57]. One study lacked reporting on the length of the intervention [21]; ten studies did not report on the timepoint of intervention after stressor exposure [33,35,36,37,38,41,53,56,57,60], making it difficult to interpret the effectiveness of these interventions. Although we performed an extensive systematic review covering multiple established literature databases, we might have missed some additional studies describing effective interventions. We included six study protocols that described novel interventions for which evaluation was planned or ongoing and for which no evidence on their efficacy was available yet. Another drawback might arise from the nature of a systematic review to summarize and synthesize study results descriptively. Thus, it was not possible to directly compare the different interventions in terms of their efficacy, as could be performed in a meta-analysis. A strength of this review is the comprehensive reporting and discussion of the study’s findings; however, no quality assessment of the included studies was undertaken.
This systematic review extends previous research since, to our knowledge, no systematic review of studies describing or evaluating brief interventions aiming at reducing psychological distress and/or subclinical symptoms has been conducted before. We considered different types of stressors (i.e., natural hazards and man-made disasters, pandemics, and other severe stressors) as well as different types of interventions (i.e., self-help, psychosocial support, and psychotherapeutic) to provide a broad overview of brief interventions for reducing distress and/or subclinical symptoms. Therefore, some of the interventions and target groups might not be directly comparable.
6. Conclusions
This systematic review identified novel brief self-help programs, psychosocial support programs, or brief psychotherapeutic interventions that addressed distress and/or subclinical symptoms in survivors of disasters, pandemics, and other severe stressors. A few interventions showed the first evidence of being effective in reducing psychological distress and/or subclinical PTSD symptoms. Effective interventions mostly covered psychosocial support programs and brief psychotherapeutic interventions that focused on disasters or other severe stressors. Interventions that focused on the COVID-19 pandemic mainly involved self-help programs that showed limited evidence of effectiveness. Future research should further investigate the effectiveness of psychosocial support interventions and brief psychotherapeutic interventions for COVID-19 survivors.
Author Contributions
Conceptualization, A.L.; methodology, A.L.; title and abstract screening, I.L. and A.F.d.P.; data extraction, I.L. and A.F.d.P.; draft preparation, writing and editing, A.L., I.L. and A.F.d.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Available upon reasonable request to the corresponding author.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Characteristics of brief interventions described in the included articles/protocols (n = 27).
Table A2.
Detailed overview of intervention characteristics and results of the included studies/protocols (n = 27).
References
- North, C.S.; Pfefferbaum, B. Mental Health Response to Community Disasters: A Systematic Review. JAMA 2013, 310, 507–518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boden, M.; Zimmerman, L.; Azevedo, K.J.; Ruzek, J.I.; Gala, S.; Abdel Magid, H.S.; Cohen, N.; Walser, R.; Mahtani, N.D.; Hoggatt, K.J.; et al. Addressing the Mental Health Impact of COVID-19 through Population Health. Clin. Psychol. Rev. 2021, 85, 102006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ingram, L.A.; Tinago, C.B.; Cai, B.; Sanders, L.W.; Bevington, T.; Wilson, S.; Magruder, K.M.; Svendsen, E. Examining Long-Term Mental Health in a Rural Community Post-Disaster: A Mixed Methods Approach. J. Health Care Poor Underserved 2018, 29, 284–302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khorram-Manesh, A. The Impacts of Armed Conflicts and Civilian Uprisings on Children’s Health. Children 2022, 9, 1913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kessler, R.C.; Galea, S.; Gruber, M.J.; Sampson, N.A.; Ursano, R.J.; Wessely, S. Trends in Mental Illness and Suicidality after Hurricane Katrina. Mol. Psychiatry 2008, 13, 374–384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Donnell, M.L.; Lau, W.; Fredrickson, J.; Gibson, K.; Bryant, R.A.; Bisson, J.; Burke, S.; Busuttil, W.; Coghlan, A.; Creamer, M.; et al. An Open Label Pilot Study of a Brief Psychosocial Intervention for Disaster and Trauma Survivors. Front. Psychiatry 2020, 11, 483. [Google Scholar] [CrossRef] [Scilit]
- Snider, L.; Van Ommeren, M.; Schafer, A. Psychological First Aid: Guide for Field Workers; World Health Organization: Geneva, Switzerland, 2011; ISBN 978-92-4-154820-5. [Google Scholar]
- Qouta, S.R.; Palosaari, E.; Diab, M.; Punamäki, R.-L. Intervention Effectiveness among War-Affected Children: A Cluster Randomized Controlled Trial on Improving Mental Health. J. Trauma. Stress 2012, 25, 288–298. [Google Scholar] [CrossRef] [Scilit]
- Shooshtary, M.H.; Panaghi, L.; Moghadam, J.A. Outcome of Cognitive Behavioral Therapy in Adolescents After Natural Disaster. J. Adolesc. Health 2008, 42, 466–472. [Google Scholar] [CrossRef] [Scilit]
- Daly, M.; Robinson, E. Psychological Distress and Adaptation to the COVID-19 Crisis in the United States. J. Psychiatr. Res. 2021, 136, 603–609. [Google Scholar] [CrossRef] [Scilit]
- Glowacz, F.; Schmits, E. Psychological Distress during the COVID-19 Lockdown: The Young Adults Most at Risk. Psychiatry Res. 2020, 293, 113486. [Google Scholar] [CrossRef] [Scilit]
- Wang, C.; Pan, R.; Wan, X.; Tan, Y.; Xu, L.; Ho, C.S.; Ho, R.C. Immediate Psychological Responses and Associated Factors during the Initial Stage of the 2019 Coronavirus Disease (COVID-19) Epidemic among the General Population in China. Int. J. Environ. Res. Public Health 2020, 17, 1729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palinkas, L.A.; O’Donnell, M.L.; Lau, W.; Wong, M. Strategies for Delivering Mental Health Services in Response to Global Climate Change: A Narrative Review. J. Environ. Res. Public Health 2020, 17, 8562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lipinski, K.; Liu, L.L.; Wong, P.W. The Effectiveness of Psychosocial Interventions Implemented after the Indian Ocean Tsunami: A Systematic Review. Int. J. Soc. Psychiatry 2016, 62, 271–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, R.C.; Witt, A.; Fegert, J.M.; Keller, F.; Rassenhofer, M.; Plener, P.L. Psychosocial Interventions for Children and Adolescents after Man-Made and Natural Disasters: A Meta-Analysis and Systematic Review. Psychol. Med. 2017, 47, 1893–1905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roberts, N.P.; Kitchiner, N.J.; Kenardy, J.; Lewis, C.E.; Bisson, J.I. Early Psychological Intervention Following Recent Trauma: A Systematic Review and Meta-Analysis. Eur. J. Psychotraumatol. 2019, 10, 1695486. [Google Scholar] [CrossRef] [Scilit]
- Lopes, A.P.; Macedo, T.F.; Coutinho, E.S.F.; Figueira, I.; Ventura, P.R. Systematic Review of the Efficacy of Cognitive-Behavior Therapy Related Treatments for Victims of Natural Disasters: A Worldwide Problem. PLoS ONE 2014, 9, e109013. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Richardson, W.; Wilson, M.; Nishikawa, J.; Hayward, R. The Well-Built Clinical Question: A Key to Evidence-Based Decisions. ACP J. Club. 1995, 123, A12–A13. [Google Scholar] [CrossRef] [Scilit]
- Liu, Z.; Qiao, D.; Xu, Y.; Zhao, W.; Yang, Y.; Wen, D.; Li, X.; Nie, X.; Dong, Y.; Tang, S.; et al. The Efficacy of Computerized Cognitive Behavioral Therapy for Depressive and Anxiety Symptoms in Patients With COVID-19: Randomized Controlled Trial. J. Med. Internet Res. 2021, 23, e26883. [Google Scholar] [CrossRef] [Scilit]
- Zhou, M.; Yuan, F.; Zhao, X.; Xi, F.; Wen, X.; Zeng, L.; Zeng, W.; Wu, H.; Zeng, H.; Zhao, Z. Research on the Individualized Short-Term Training Model of Nurses in Emergency Isolation Wards during the Outbreak of COVID-19. Nurs. Open 2020, 7, 1902–1908. [Google Scholar] [CrossRef] [Scilit]
- Alavi, N.; Yang, M.; Stephenson, C.; Nikjoo, N.; Malakouti, N.; Layzell, G.; Jagayat, J.; Shirazi, A.; Groll, D.; Omrani, M.; et al. Using the Online Psychotherapy Tool to Address Mental Health Problems in the Context of the COVID-19 Pandemic: Protocol for an Electronically Delivered Cognitive Behavioral Therapy Program. JMIR Res. Protoc. 2020, 9, e24913. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiner, L.; Berna, F.; Nourry, N.; Severac, F.; Vidailhet, P.; Mengin, A.C. Efficacy of an Online Cognitive Behavioral Therapy Program Developed for Healthcare Workers during the COVID-19 Pandemic: The REduction of STress (REST) Study Protocol for a Randomized Controlled Trial. Trials 2020, 21, 870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruggiero, K.J.; Price, M.; Adams, Z.; Stauffacher, K.; McCauley, J.; Danielson, C.K.; Knapp, R.; Hanson, R.F.; Davidson, T.M.; Amstadter, A.B.; et al. Web Intervention for Adolescents Affected by Disaster: Population-Based Randomized Controlled Trial. J. Am. Acad. Child Adolesc. Psychiatry 2015, 54, 709–717. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gilmore, A.K.; Price, M.; Bountress, K.E.; Zuromski, K.L.; Ruggiero, K.; Resnick, H. A Longitudinal Examination of Interpersonal Violence Exposure, Concern for Loved Ones During a Disaster, and Web-Based Intervention Effects on Posttraumatic Stress Disorder Among Adolescent Victims of the Spring 2011 Tornadoes. J. Interpers. Violence 2021, 36, NP4611–NP4625. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruggiero, K.J.; Resnick, H.S.; Paul, L.A.; Gros, K.; McCauley, J.L.; Acierno, R.; Morgan, M.; Galea, S. Randomized Controlled Trial of an Internet-Based Intervention Using Random-Digit-Dial Recruitment: The Disaster Recovery Web Project. Contemp. Clin. Trials 2012, 33, 237–246. [Google Scholar] [CrossRef] [Scilit]
- Price, M.; Davidson, T.M.; Andrews, J.O.; Ruggiero, K.J. Access, Use and Completion of a Brief Disaster Mental Health Intervention among Hispanics, African-Americans and Whites Affected by Hurricane Ike. J. Telemed. Telecare 2013, 19, 70–74. [Google Scholar] [CrossRef] [Scilit]
- Tang, R.; Xie, T.; Jiao, K.; Xu, X.; Zou, X.; Qian, W.; Wang, J. Grief Reactions and Grief Counseling among Bereaved Chinese Individuals during COVID-19 Pandemic: Study Protocol for a Randomized Controlled Trial Combined with a Longitudinal Study. J. Environ. Res. Public Health 2021, 18, 9061. [Google Scholar] [CrossRef] [Scilit]
- Neimeyer, R.A. Meaning Reconstruction & the Experience of Loss, 1st ed.; American Psychological Association: Washington, DC, USA, 2001; ISBN 978-1-55798-742-6. [Google Scholar]
- Shear, M.K. Complicated Grief Treatment (CGT) for Prolonged Grief Disorder. In Evidence Based Treatments for Trauma-Related Psychological Disorders; Schnyder, U., Cloitre, M., Eds.; Springer International Publishing: Berlin/Heidelberg, Germany, 2015; pp. 299–314. ISBN 978-3-319-07108-4. [Google Scholar]
- Boelen, P.A. Cognitive-Behavioral Therapy for Complicated Grief: Theoretical Underpinnings and Case Descriptions. J. Loss Trauma 2006, 11, 1–30. [Google Scholar] [CrossRef] [Scilit]
- Devassy, S.M.; Allagh, K.P.; Benny, A.M.; Scaria, L.; Cheguvera, N.; Sunirose, I.P. Resiliency Engagement and Care in Health (REaCH): A Telephone Befriending Intervention for Upskilled Rural Youth in the Context of COVID-19 Pandemic—Study Protocol for a Multi-Centre Cluster Randomised Controlled Trial. Trials 2021, 22, 500. [Google Scholar] [CrossRef] [Scilit]
- James, L.E.; Welton-Mitchell, C.; Noel, J.R.; James, A.S. Integrating Mental Health and Disaster Preparedness in Intervention: A Randomized Controlled Trial with Earthquake and Flood-Affected Communities in Haiti. Psychol. Med. 2020, 50, 342–352. [Google Scholar] [CrossRef] [Scilit]
- Dawson, K.S.; Bryant, R.A.; Harper, M.; Kuowei Tay, A.; Rahman, A.; Schafer, A.; van Ommeren, M. Problem Management Plus (PM+): A WHO Transdiagnostic Psychological Intervention for Common Mental Health Problems. World Psychiatry 2015, 14, 354–357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sangraula, M.; Turner, E.L.; Luitel, N.P.; van ‘t Hof, E.; Shrestha, P.; Ghimire, R.; Bryant, R.; Marahatta, K.; van Ommeren, M.; Kohrt, B.A.; et al. Feasibility of Group Problem Management Plus (PM+) to Improve Mental Health and Functioning of Adults in Earthquake-Affected Communities in Nepal. Epidemiol. Psychiatr. Sci. 2020, 29, e130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jordans, M.J.D.; Kohrt, B.A.; Sangraula, M.; Turner, E.L.; Wang, X.; Shrestha, P.; Ghimire, R.; van’t Hof, E.; Bryant, R.A.; Dawson, K.S.; et al. Effectiveness of Group Problem Management Plus, a Brief Psychological Intervention for Adults Affected by Humanitarian Disasters in Nepal: A Cluster Randomized Controlled Trial. PLoS Med. 2021, 18, e1003621. [Google Scholar] [CrossRef] [Scilit]
- Rahman, A.; Riaz, N.; Dawson, K.S.; Usman Hamdani, S.; Chiumento, A.; Sijbrandij, M.; Minhas, F.; Bryant, R.A.; Saeed, K.; van Ommeren, M.; et al. Problem Management Plus (PM+): Pilot Trial of a WHO Transdiagnostic Psychological Intervention in Conflict-Affected Pakistan. World Psychiatry 2016, 15, 182–183. [Google Scholar] [CrossRef] [Scilit]
- Bryant, R.A.; Schafer, A.; Dawson, K.S.; Anjuri, D.; Mulili, C.; Ndogoni, L.; Koyiet, P.; Sijbrandij, M.; Ulate, J.; Shehadeh, M.H.; et al. Effectiveness of a Brief Behavioural Intervention on Psychological Distress among Women with a History of Gender-Based Violence in Urban Kenya: A Randomised Clinical Trial. PLoS Med. 2017, 14, e1002371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Keyan, D.; Dawson, K.; Azevado, S.; Yadav, S.; Tran, J.; Bryant, R.A. Brief Videoconferencing Psychological Intervention for Reducing COVID-19 Related Distress: Study Protocol for a Randomized Controlled Trial. BMC Public Health 2021, 21, 474. [Google Scholar] [CrossRef] [Scilit]
- Gibson, K.; Little, J.; Cowlishaw, S.; Ipitoa Toromon, T.; Forbes, D.; O’Donnell, M. Piloting a Scalable, Post-Trauma Psychosocial Intervention in Tuvalu: The Skills for Life Adjustment and Resilience (SOLAR) Program. Eur. J. Psychotraumatol. 2021, 12, 1948253. [Google Scholar] [CrossRef] [Scilit]
- Lotzin, A.; Hinrichsen, I.; Kenntemich, L.; Freyberg, R.-C.; Lau, W.; O’Donnell, M. The SOLAR Group Program to Promote Recovery after Disaster and Trauma-A Randomized Controlled Feasibility Trial among German Trauma Survivors. Psychol. Trauma. 2022, 14, 161–171. [Google Scholar] [CrossRef] [Scilit]
- Kataoka, S.; Langley, A.K.; Wong, M.; Baweja, S.; Stein, B.D. Responding to Students with Posttraumatic Stress Disorder in Schools. Child Adolesc. Psychiatr. Clin. North Am. 2012, 21, 119–133. [Google Scholar] [CrossRef] [Scilit]
- Ramirez, M.; Harland, K.; Frederick, M.; Shepherd, R.; Wong, M.; Cavanaugh, J.E. Listen Protect Connect for Traumatized Schoolchildren: A Pilot Study of Psychological First Aid. BMC Psychol. 2013, 1, 26. [Google Scholar] [CrossRef] [Scilit]
- Ito, D.; Koseki, S.; Ohtani, T. A Brief School-Based Cognitive-Behavioral Intervention for Japanese Adolescents With Severe Posttraumatic Stress. J. Trauma. Stress 2016, 29, 577–580. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ehlers, A.; Clark, D.M. A Cognitive Model of Posttraumatic Stress Disorder. Behav. Res. Ther. 2000, 38, 319–345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saltzman, W.R.; Silverman, W.K.; Brymer, M.J.; Allen, A.; Layne, C.; Pynoos, R.; Steinberg, A. StArT: Strength after Trauma: A Modular Intervention for Children and Adolescents Affected by Hurricanes. Natl. Child Trauma. Stress Netw. 2007, unpublished report. [Google Scholar]
- Taylor, L.K.; Weems, C.F. Cognitive-Behavior Therapy for Disaster-Exposed Youth with Posttraumatic Stress: Results from a Multiple-Baseline Examination. Behav. Ther. 2011, 42, 349–363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hamblen, J.L.; Gibson, L.E.; Mueser, K.T.; Norris, F.H. Cognitive Behavioral Therapy for Prolonged Postdisaster Distress. J. Clin. Psychol. 2006, 62, 1043–1052. [Google Scholar] [CrossRef] [Scilit]
- Hamblen, J.L.; Norris, F.H.; Symon, K.A.; Bow, T.E. Cognitive Behavioral Therapy for Postdisaster Distress: A Promising Transdiagnostic Approach to Treating Disaster Survivors. Psychol. Trauma Theory Res. Pract. Policy 2017, 9, 130–136. [Google Scholar] [CrossRef] [Scilit]
- Eland, J.; de Roos, C.; Kleber, R.J. Kind En Trauma: Een Opvangprogramma; Swets & Zeitlinger: Lisse, The Netherlands, 2000; ISBN 978-90-265-1611-5. [Google Scholar]
- Shapiro, F. Eye Movement Desensitization and Reprocessing (EMDR), Second Edition: Basic Principles, Protocols, and Procedures; Guilford Press: New York, NY, USA, 2001; ISBN 978-1-60623-796-0. [Google Scholar]
- de Roos, C.; Greenwald, R.; den Hollander-Gijsman, M.; Noorthoorn, E.; van Buuren, S.; de Jongh, A. A Randomised Comparison of Cognitive Behavioural Therapy (CBT) and Eye Movement Desensitisation and Reprocessing (EMDR) in Disaster-Exposed Children. Eur. J. Psychotraumatology 2011, 2, 5694. [Google Scholar] [CrossRef] [Scilit]
- Scheiber, B.; Greinz, G.; Hillebrand, J.B.; Wilhelm, F.H.; Blechert, J. Resilience training for unaccompanied refugee minors: A randomized controlled pilot study. Resilienztraining Fur Unbegleitete Minderjahrige Fluchtl. Eine Randomisiert-Kontrollierte Pilot. 2019, 28, 173–181. [Google Scholar] [CrossRef] [Scilit]
- Kabat-Zinn, J.; University of Massachusetts Medical Center/Worcester; Stress Reduction Clinic. Full Catastrophe Living: Using the Wisdom of Your Body and Mind to Face Stress, Pain, and Illness; Delacorte Press: New York, NY, USA, 1990; ISBN 978-0-385-29897-1. [Google Scholar]
- Frank, R. Therapieziel Wohlbefinden: Ressourcen Aktivieren in der Psychotherapie; Springer: Berlin/Heidelberg, Germany, 2017; ISBN 978-3-662-53470-0. [Google Scholar]
- Gallegos, A.M.; Lytle, M.C.; Moynihan, J.A.; Talbot, N.L. Mindfulness-Based Stress Reduction to Enhance Psychological Functioning and Improve Inflammatory Biomarkers in Trauma-Exposed Women: A Pilot Study. Psychol. Trauma Theory Res. Pract. Policy 2015, 7, 525–532. [Google Scholar] [CrossRef] [Scilit]
- Tehrani, N. Evaluation of a Trauma Therapy Programme within Emergency Service Organizations. Occup. Med. 2019, 69, 559–565. [Google Scholar] [CrossRef] [Scilit]
- Smith, P.; Perrin, S.; Dalgleish, T.; Meiser-Stedman, R.; Clark, D.M.; Yule, W. Treatment of Posttraumatic Stress Disorder in Children and Adolescents. Curr. Opin. Psychiatry 2013, 26, 66–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Craig, G. The EFT Manual, 2nd ed.; Energy Psychology Press: Santa Rosa, CA, USA, 2010. [Google Scholar]
- Church, D.; Hawk, C.; Brooks, A.J.; Toukolehto, O.; Wren, M.; Dinter, I.; Stein, P. Psychological Trauma Symptom Improvement in Veterans Using Emotional Freedom Techniques: A Randomized Controlled Trial. J. Nerv. Ment. Dis. 2013, 201, 153–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Shazer, S.; Berg, I.K.; Lipchik, E.; Nunnally, E.; Molnar, A.; Gingerich, W.; Weiner-Davis, M. Brief Therapy: Focused Solution Development. Fam. Process. 1986, 25, 207–221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iveson, C. Solution-Focused Brief Therapy. Adv. Psychiatr. Treat. 2002, 8, 149–156. [Google Scholar] [CrossRef] [Scilit]
- Chen, S. An Online Solution Focused Brief Therapy for Adolescent Anxiety during the Novel Coronavirus Disease (COVID-19) Pandemic: A Structured Summary of a Study Protocol for a Randomised Controlled Trial. Trials 2020, 21, 402. [Google Scholar] [CrossRef] [Scilit]
- Hamilton, M. A Rating Scale for Depression. J. Neurol. Neurosurg. Psychiatry 1960, 23, 56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hamilton, M. The Assessment of Anxiety States by Rating. Br. J. Med. Psychol. 1959, 32, 50–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zung, W.W.K. A Self-Rating Depression Scale. Arch. Gen. Psychiatry 1965, 12, 63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zung, W.W.K. A Rating Instrument For Anxiety Disorders. Psychosomatics 1971, 12, 371–379. [Google Scholar] [CrossRef] [Scilit]
- Soldatos, C.R.; Dikeos, D.G.; Paparrigopoulos, T.J. Athens Insomnia Scale: Validation of an Instrument Based on ICD-10 Criteria. J. Psychosom. Res. 2000, 48, 555–560. [Google Scholar] [CrossRef] [Scilit]
- Spitzer, R.L.; Kroenke, K.; Williams, J.B.W.; Löwe, B. A Brief Measure for Assessing Generalized Anxiety Disorder: The GAD-7. Arch. Intern. Med. 2006, 166, 1092–1097. [Google Scholar] [CrossRef] [Scilit]
- Kroenke, K.; Spitzer, R.L.; Williams, J.B.W. The PHQ-9: Validity of a Brief Depression Severity Measure. J. Gen. Intern Med. 2001, 16, 606–613. [Google Scholar] [CrossRef] [Scilit]
- Wagnild, G.M.; Young, H.M. Development and Psychometric Evaluation of the Resilience Scale. J. Nurs. Meas. 1993, 1, 165–178. [Google Scholar]
- Endicott, J.; Nee, J.; Harrison, W.; Blumenthal, R. Quality of Life Enjoyment and Satisfaction Questionnaire: A New Measure. Psychopharmacol. Bull. 1993, 29, 321–326. [Google Scholar]
- Cohen, S.; Kamarck, T.; Mermelstein, R. A Global Measure of Perceived Stress. J. Health Soc. Behav. 1983, 24, 385. [Google Scholar] [CrossRef] [Scilit]
- Arroll, B.; Goodyear-Smith, F.; Crengle, S.; Gunn, J.; Kerse, N.; Fishman, T.; Falloon, K.; Hatcher, S. Validation of PHQ-2 and PHQ-9 to Screen for Major Depression in the Primary Care Population. Ann. Fam. Med. 2010, 8, 348–353. [Google Scholar] [CrossRef] [Scilit]
- Zuromski, K.L.; Ustun, B.; Hwang, I.; Keane, T.M.; Marx, B.P.; Stein, M.B.; Ursano, R.J.; Kessler, R.C. Developing an Optimal Short-Form of the PTSD Checklist for DSM-5 (PCL-5). Depress Anxiety 2019, 36, 790–800. [Google Scholar] [CrossRef] [Scilit]
- Vaishnavi, S.; Connor, K.; Davidson, J.R.T. An Abbreviated Version of the Connor-Davidson Resilience Scale (CD-RISC), the CD-RISC2: Psychometric Properties and Applications in Psychopharmacological Trials. Psychiatry Res. 2007, 152, 293–297. [Google Scholar] [CrossRef] [Scilit]
- Bastien, C.H.; Vallières, A.; Morin, C.M. Validation of the Insomnia Severity Index as an Outcome Measure for Insomnia Research. Sleep Med. 2001, 2, 297–307. [Google Scholar] [CrossRef] [Scilit]
- Cropley, M.; Michalianou, G.; Pravettoni, G.; Millward, L.J. The Relation of Post-Work Ruminative Thinking with Eating Behaviour. Stress Health 2012, 28, 23–30. [Google Scholar] [CrossRef] [Scilit]
- Devilly, G.J.; Borkovec, T.D. Psychometric Properties of the Credibility/Expectancy Questionnaire. J. Behav. Exp. Psychiatry 2000, 31, 73–86. [Google Scholar] [CrossRef] [Scilit]
- Attkisson, C.C.; Zwick, R. The Client Satisfaction Questionnaire: Psychometric Properties and Correlations with Service Utilization and Psychotherapy Outcome. Eval. Program Plan. 1982, 5, 233–237. [Google Scholar] [CrossRef] [Scilit]
- Kilpatrick, D.G.; Ruggiero, K.J.; Acierno, R.; Saunders, B.E.; Resnick, H.S.; Best, C.L. Violence and Risk of PTSD, Major Depression, Substance Abuse/Dependence, and Comorbidity: Results from the National Survey of Adolescents. J. Consult. Clin. Psychol. 2003, 71, 692. [Google Scholar] [CrossRef] [Scilit]
- Weathers, F.W.; Litz, B.T.; Herman, D.; Huska, J.; Keane, T. The PTSD Checklist-Civilian Version (PCL-C). In NCfPBS; National Center for PTSD - Behavioral Science Division: Boston, MA, USA, 1994. [Google Scholar]
- Radloff, L.S. The CES-D Scale: A Self-Report Depression Scale for Research in the General Population. Appl. Psychol. Meas. 1977, 1, 385–401. [Google Scholar] [CrossRef] [Scilit]
- Blevins, C.A.; Weathers, F.W.; Davis, M.T.; Witte, T.K.; Domino, J.L. The Posttraumatic Stress Disorder Checklist for DSM-5 (PCL-5): Development and Initial Psychometric Evaluation. J. Trauma. Stress 2015, 28, 489–498. [Google Scholar] [CrossRef] [Scilit]
- Tedeschi, R.G.; Calhoun, L.G. The Posttraumatic Growth Inventory: Measuring the Positive Legacy of Trauma. J. Trauma. Stress 1996, 9, 455–471. [Google Scholar] [CrossRef]
- Lovibond, P.F.; Lovibond, S.H. The Structure of Negative Emotional States: Comparison of the Depression Anxiety Stress Scales (DASS) with the Beck Depression and Anxiety Inventories. Behav. Res. Ther. 1995, 33, 335–343. [Google Scholar] [CrossRef] [Scilit]
- Prigerson, H.; Horowitz, M.J.; Jacobs, S.C.; Parkes, C.M.; Aslan, M.; Goodkin, K.; Raphael, B.; Marwit, S.J.; Wortman, C.; Neimeyer, R.A.; et al. Prolonged Grief Disorder: Psychometric Validation of Criteria Proposed for DSM-V and ICD-11. PLoS Med. 2009, 6, e1000121. [Google Scholar] [CrossRef] [Scilit]
- Beck, A.T.; Kovacs, M.; Weissman, A. Assessment of Suicidal Intention: The Scale for Suicide Ideation. J. Consult. Clin. Psychol. 1979, 47, 343–352. [Google Scholar] [CrossRef]
- Skritskaya, N.A.; Mauro, C.; Olonoff, M.; Qiu, X.; Duncan, S.; Wang, Y.; Duan, N.; Lebowitz, B.; Reynolds, C.F.; Simon, N.M.; et al. Measuring Maladaptive Cognitions in Complicated Grief: Introducing the Typical Beliefs Questionnaire. Am. J. Geriatr. Psychiatry 2017, 25, 541–550. [Google Scholar] [CrossRef] [Scilit]
- Shear, K.; Monk, T.; Houck, P.; Melhem, N.; Frank, E.; Reynolds, C.; Sillowash, R. An Attachment-Based Model of Complicated Grief Including the Role of Avoidance. Eur. Arch. Psychiatry Clin. Neurosc. 2007, 257, 453–461. [Google Scholar] [CrossRef] [Scilit]
- Mundt, J.C.; Marks, I.M.; Shear, M.K.; Greist, J.M. The Work and Social Adjustment Scale: A Simple Measure of Impairment in Functioning. Br. J. Psychiatry 2002, 180, 461–464. [Google Scholar] [CrossRef] [Scilit]
- Topp, C.W.; Østergaard, S.D.; Søndergaard, S.; Bech, P. The WHO-5 Well-Being Index: A Systematic Review of the Literature. Psychother. Psychosom. 2015, 84, 167–176. [Google Scholar] [CrossRef] [Scilit]
- Zimet, G.D.; Dahlem, N.W.; Zimet, S.G.; Farley, G.K. The Multidimensional Scale of Perceived Social Support. J. Personal. Assess. 1988, 52, 30–41. [Google Scholar] [CrossRef] [Scilit]
- Falsetti, S.A.; Resnick, H.S.; Resick, P.A.; Kilpatrick, D.G. The Modified PTSD Symptom Scale: A Brief Self-Report Measure of Posttraumatic Stress Disorder. Behav. Ther. 1993, 16, 161–162. [Google Scholar]
- Rasmussen, A.; Eustache, E.; Raviola, G.; Kaiser, B.; Grelotti, D.J.; Belkin, G.S. Development and Validation of a Haitian Creole Screening Instrument for Depression. Transcult. Psychiatry 2015, 52, 33–57. [Google Scholar] [CrossRef] [Scilit]
- Kaiser, B.N.; Kohrt, B.A.; Keys, H.M.; Khoury, N.M.; Brewster, A.-R.T. Strategies for Assessing Mental Health in Haiti: Local Instrument Development and Transcultural Translation. Transcult. Psychiatry 2013, 50, 532–558. [Google Scholar] [CrossRef] [Scilit]
- Sampson, R.J.; Raudenbush, S.W.; Earls, F. Neighborhoods and Violent Crime: A Multilevel Study of Collective Efficacy. Science 1997, 277, 918–924. [Google Scholar] [CrossRef] [Scilit]
- Minhas, F.A.; Mubbashar, M.H. Validation of General Health Questionnaire in a Primary Care Setting of Pakistan. J. Coll. Physicians Surg. Pak. 1996, 6, 133–136. [Google Scholar]
- Zigmond, A.S.; Snaith, R.P. The Hospital Anxiety and Depression Scale. Acta Psychiatr. Scand. 1983, 67, 361–370. [Google Scholar] [CrossRef] [Scilit]
- Morin, C.; Stone, J.; Mcdonald, K.; Jones, S. Psychological Management of Insomnia: A Clinical Replication Series with 100 Patients. Behav. Ther. 1994, 25, 291–309. [Google Scholar] [CrossRef] [Scilit]
- Watson, D.; Clark, L.A.; Tellegen, A. Development and Validation of Brief Measures of Positive and Negative Affect: The PANAS Scales. J. Pers. Soc. Psychol. 1988, 54, 1063–1070. [Google Scholar] [CrossRef] [PubMed]
- Fawcett, J.; Clark, D.C.; Scheftner, W.A.; Gibbons, R.D. Assessing Anhedonia in Psychiatric Patients. Arch. Gen. Psychiatry 1983, 40, 79–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taylor, S.; Landry, C.A.; Paluszek, M.M.; Fergus, T.A.; McKay, D.; Asmundson, G.J.G. Development and Initial Validation of the COVID Stress Scales. J. Anxiety Disord. 2020, 72, 102232. [Google Scholar] [CrossRef] [Scilit]
- Kohrt, B.A.; Luitel, N.P.; Acharya, P.; Jordans, M.J.D. Detection of Depression in Low Resource Settings: Validation of the Patient Health Questionnaire (PHQ-9) and Cultural Concepts of Distress in Nepal. BMC Psychiatry 2016, 16, 58. [Google Scholar] [CrossRef] [Scilit]
- Üstün, T.B.; Chatterji, S.; Kostanjsek, N.; Rehm, J.; Kennedy, C.; Epping-Jordan, J.; Saxena, S.; von Korff, M.; Pull, C. Developing the World Health Organization Disability Assessment Schedule 2.0. Bull. World Health Organ 2010, 88, 815–823. [Google Scholar] [CrossRef] [Scilit]
- Luitel, N.P.; Jordans, M.J.D.; Sapkota, R.P.; Tol, W.A.; Kohrt, B.A.; Thapa, S.B.; Komproe, I.H.; Sharma, B. Conflict and Mental Health: A Cross-Sectional Epidemiological Study in Nepal. Soc. Psychiatry Psychiatr. Epidemiol. 2013, 48, 183–193. [Google Scholar] [CrossRef] [Scilit]
- Neacsiu, A.D.; Rizvi, S.L.; Vitaliano, P.P.; Lynch, T.R.; Linehan, M.M. The Dialectical Behavior Therapy Ways of Coping Checklist: Development and Psychometric Properties. J. Clin. Psychol. 2010, 66, 563–582. [Google Scholar] [CrossRef] [Scilit]
- Schwartz, A.C.; Bradley, R.L.; Sexton, M.; Sherry, A.; Ressler, K.J. Posttraumatic Stress Disorder among African Americans in an Inner City Mental Health Clinic. Psychiatr. Serv. 2005, 56, 212–215. [Google Scholar] [CrossRef] [Scilit]
- Ashworth, M.; Robinson, S.; Godfrey, E.; Shepherd, M.; Evans, C.; Seed, P.; Parmentier, H.; Tylee, A. Measuring Mental Health Outcomes in Primary Care: The Psychometric Properties of a New Patient-Generated Outcome Measure, ‘PSYCHLOPS’ (‘Psychological Outcome Profiles’). Prim. Care Ment. Health 2005, 3, 10. [Google Scholar]
- Gierk, B.; Kohlmann, S.; Kroenke, K.; Spangenberg, L.; Zenger, M.; Brähler, E.; Löwe, B. The Somatic Symptom Scale–8 (SSS-8): A Brief Measure of Somatic Symptom Burden. JAMA Intern. Med. 2014, 174, 399–407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Subba, P.; Luitel, N.P.; Kohrt, B.A.; Jordans, M.J.D. Improving Detection of Mental Health Problems in Community Settings in Nepal: Development and Pilot Testing of the Community Informant Detection Tool. Confl. Health 2017, 11, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gray, M.J.; Litz, B.T.; Hsu, J.L.; Lombardo, T.W. Psychometric Properties of the Life Events Checklist. Assessment 2004, 11, 330–341. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sampasa-Kanyinga, H.; Zamorski, M.A.; Colman, I. The Psychometric Properties of the 10-Item Kessler Psychological Distress Scale (K10) in Canadian Military Personnel. PLoS ONE 2018, 13, e0196562. [Google Scholar] [CrossRef] [Scilit]
- Gibson, K. The Relationship between Climate Change and Psychological Distress: A Case Study from Tuvalu. Ph.D. Thesis, University of Melbourne, Melbourne, Australia, 2018. [Google Scholar]
- Larsen, D.L.; Attkisson, C.C.; Hargreaves, W.A.; Nguyen, T.D. Assessment of Client/Patient Satisfaction: Development of a General Scale. Eval. Program Plan. 1979, 2, 197–207. [Google Scholar] [CrossRef] [Scilit]
- Schmidt, J.; Lamprecht, F.; Wittmann, W.W. Zufriedenheit Mit Der Stationären Versorgung. Entwicklung Eines Fragebogens Und Erste Validitätsuntersuchungen. [Satisfaction with Inpatient Care: Development of a Questionnaire and First Validity Assessments.]. PPmP Psychother. Psychosom. Med. Psychol. 1989, 39, 248–255. [Google Scholar]
- Richardson, J.R.J.; Peacock, S.J.; Hawthorne, G.; Iezzi, A.; Elsworth, G.; Day, N.A. Construction of the Descriptive System for the Assessment of Quality of Life AQoL-6D Utility Instrument. Health Qual. Life Outcomes 2012, 10, 38. [Google Scholar] [CrossRef] [Scilit]
- Cohen, S.; Mermelstein, R.; Kamarck, T.; Hoberman, H.M. Measuring the Functional Components of Social Support. In Social Support: Theory, Research and Applications; Springer: Den Haag, The Netherlands, 1985; pp. 73–94. ISBN 978-94-010-8761-2. [Google Scholar]
- Foa, E.B.; Johnson, K.M.; Feeny, N.C.; Treadwell, K.R. The Child PTSD Symptom Scale: A Preliminary Examination of Its Psychometric Properties. J. Clin. Child Psychol. 2001, 30, 376–384. [Google Scholar] [CrossRef] [Scilit]
- Constantine, N.A.; Benard, B.; Diaz, M. Measuring Protective Factors and Resilience Traits in Youth: The Healthy Kids Resilience Assessment. In Seventh Annual Meeting of the Society for Prevention Research; European Society for Prevention Research: New Orleans, LA, USA, 1999. [Google Scholar]
- Weiss, D.S.; Marmar, C.R. The Impact of Event Scale—Revised. In Assessing Psychological Trauma and PTSD; The Guilford Press: New York, NY, USA, 1997; pp. 399–411. ISBN 978-1-57230-162-7. [Google Scholar]
- Frederick, C.J.; Pynoos, R.S.; Nadar, K. Reaction Index to Psychic Trauma Form C (Child). Unpublished work, 1992.
- Lucas, C.P.; Zhang, H.; Fisher, P.W.; Shaffer, D.; Regier, D.A.; Narrow, W.E.; Bourdon, K.; Dulcan, M.K.; Canino, G.; Rubio-Stipec, M.; et al. The DISC Predictive Scales (DPS): Efficiently Screening for Diagnoses. J. Am. Acad. Child Adolesc. Psychiatry 2001, 40, 443–449. [Google Scholar] [CrossRef] [Scilit]
- Leitenberg, H.; Yost, L.W.; Carroll-Wilson, M. Negative Cognitive Errors in Children: Questionnaire Development, Normative Data, and Comparisons between Children with and without Self-Reported Symptoms of Depression, Low Self-Esteem, and Evaluation Anxiety. J. Consult. Clin. Psychol. 1986, 54, 528–536. [Google Scholar] [CrossRef]
- Silverman, W.K.; Fleisig, W.; Rabian, B.; Peterson, R.A. Childhood Anxiety Sensitivity Index. J. Clin. Child Psychol. 1991, 20, 162–168. [Google Scholar] [CrossRef] [Scilit]
- Taylor, L.K.; Costa, N.M.; Cannon, M.F.; Adams, C.S.; Weems, C.F. Developing the Anxiety Control Questionnaire for Children (ACQ-C) Short Form; Annual Convention of the American Psychological Association: New Orleans, LA, USA, 2006. [Google Scholar]
- Norris, F.H.; Hamblen, J.L.; Brown, L.M.; Schinka, J.A. Validation of the Short Posttraumatic Stress Disorder Rating Interview (Expanded Version, Sprint-E) as a Measure of Postdisaster Distress and Treatment Need. Am. J. Disaster. Med. 2008, 3, 201–212. [Google Scholar] [PubMed]
- Steinberg, A.M.; Brymer, M.J.; Decker, K.B.; Pynoos, R.S. The University of California at Los Angeles Post-Traumatic Stress Disorder Reaction Index. Curr. Psychiatry Rep. 2004, 6, 96–100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenwald, R.; Rubin, A.; Jurkovic, G.J.; Wiedemann, J.; Russell, A.M.; O’Connor, M.B. Psychometrics of the CROPS & PROPS in Multiple Cultures/Translations. In Proceedings of the 18th Annual Meeting of the International Society for Traumatic Stress Studies ISTSS, Baltimore, MD, USA, 7–10 November 2002. [Google Scholar]
- Birleson, P. The Validity of Depressive Disorder in Childhood and the Development of a Self-Rating Scale: A Research Report. J. Child Psychol. Psychiatry 1981, 22, 73–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- March, J.S.; Parker, J.D.; Sullivan, K.; Stallings, P.; Conners, C.K. The Multidimensional Anxiety Scale for Children (MASC): Factor Structure, Reliability, and Validity. J. Am. Acad. Child Adolesc. Psychiatry 1997, 36, 554–565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Achenbach, T.M. Manual for Child Behavior Checklist 4–18, 1991 Profile; Department of Psychiatry, University of Vermont: Burlington, VT, USA, 1991; ISBN 978-0-938565-08-6. [Google Scholar]
- Mewes, R.; Friele, B.; Bloemen, E. Validation of the Protect Questionnaire: A Tool to Detect Mental Health Problems in Asylum Seekers by Non-Health Professionals. Torture J. 2018, 28, 56–71. [Google Scholar] [CrossRef] [Scilit]
- Hollifield, M.; Verbillis-Kolp, S.; Farmer, B.; Toolson, E.C.; Woldehaimanot, T.; Yamazaki, J.; Holland, A.; St Clair, J.; SooHoo, J. The Refugee Health Screener-15 (RHS-15): Development and Validation of an Instrument for Anxiety, Depression, and PTSD in Refugees. Gen. Hosp. Psychiatry 2013, 35, 202–209. [Google Scholar] [CrossRef] [Scilit]
- Demir, S.; Reich, H.; Mewes, R.; Demir, S.; Reich, H.; Mewes, R. Psychologische Erstbetreuung Für Asylsuchende. Entwicklung Und Erste Erfahrungen Mit Einer Gruppenpsychoedukation Für Geflüchtete. Psychotherapeutenjournal 2016, 15, 124–131. [Google Scholar]
- Cohen, S. Perceived Stress in a Probability Sample of the United States. In The Social Psychology of Health; The Claremont Symposium on Applied Social Psychology; Sage Publications, Inc.: Thousand Oaks, CA, USA, 1988; pp. 31–67. ISBN 978-0-8039-3162-6. [Google Scholar]
- Spielberger, C.D.; Gorsuch, R.L.; Lushene, R.; Vagg, P.R.; Jacobs, G.A. Manual for the State-Trait Anxiety Inventory; Consulting Psychologists Press: Palo Alto, CA, USA, 1983. [Google Scholar] [CrossRef] [Scilit]
- Gratz, K.L.; Roemer, L. Multidimensional Assessment of Emotion Regulation and Dysregulation: Development, Factor Structure, and Initial Validation of the Difficulties in Emotion Regulation Scale. J. Psychopathol. Behav. Assess. 2004, 26, 41–54. [Google Scholar] [CrossRef] [Scilit]
- Baer, R.A.; Smith, G.T.; Hopkins, J.; Krietemeyer, J.; Toney, L. Using Self-Report Assessment Methods to Explore Facets of Mindfulness. Assessment 2006, 13, 27–45. [Google Scholar] [CrossRef] [Scilit]
- Goldberg, D.; Bridges, K.; Duncan-Jones, P.; Grayson, D. Detecting Anxiety and Depression in General Medical Settings. BMJ 1988, 297, 897–899. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tehrani, N.; Cox, S.J.; Cox, T. Assessing the Impact of Stressful Incidents in Organizations: The Development of an Extended Impact of Events Scale. Couns. Psychol. Q. 2002, 15, 191–200. [Google Scholar] [CrossRef] [Scilit]
- Antonovsky, A. The Salutogenic Model as a Theory to Guide Health Promotion. Health Promot Int. 1996, 11, 11–18. [Google Scholar] [CrossRef] [Scilit]
- Weathers, F.; Litz, B.; Herman, D.; Huska, J.A.; Keane, T. The PTSD Checklist (PCL): Reliability, Validity, and Diagnostic Utility. In Annual Convention of the International Society for Traumatic Stress; International Society of Traumatic Stress Studies: San Antonio, TX, USA, 1993. [Google Scholar]
- Davison, M.L.; Bershadsky, B.; Bieber, J.; Silversmith, D.; Maruish, M.E.; Kane, R.L. Development of a Brief, Multidimensional, Self-Report Instrument for Treatment Outcomes Assessment in Psychiatric Settings: Preliminary Findings. Assessment 1997, 4, 259–276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jitlina, K.; Zumbo, B.; Mirenda, P.; Ford, L.; Bennett, T.; Georgiades, S.; Waddell, C.; Smith, I.M.; Volden, J.; Duku, E.; et al. Psychometric Properties of the Spence Children’s Anxiety Scale: Parent Report in Children with Autism Spectrum Disorder. J. Autism. Dev. Disord. 2017, 47, 3847–3856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
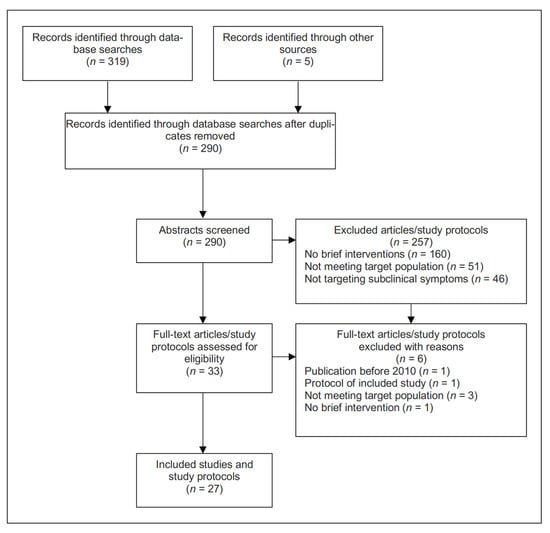
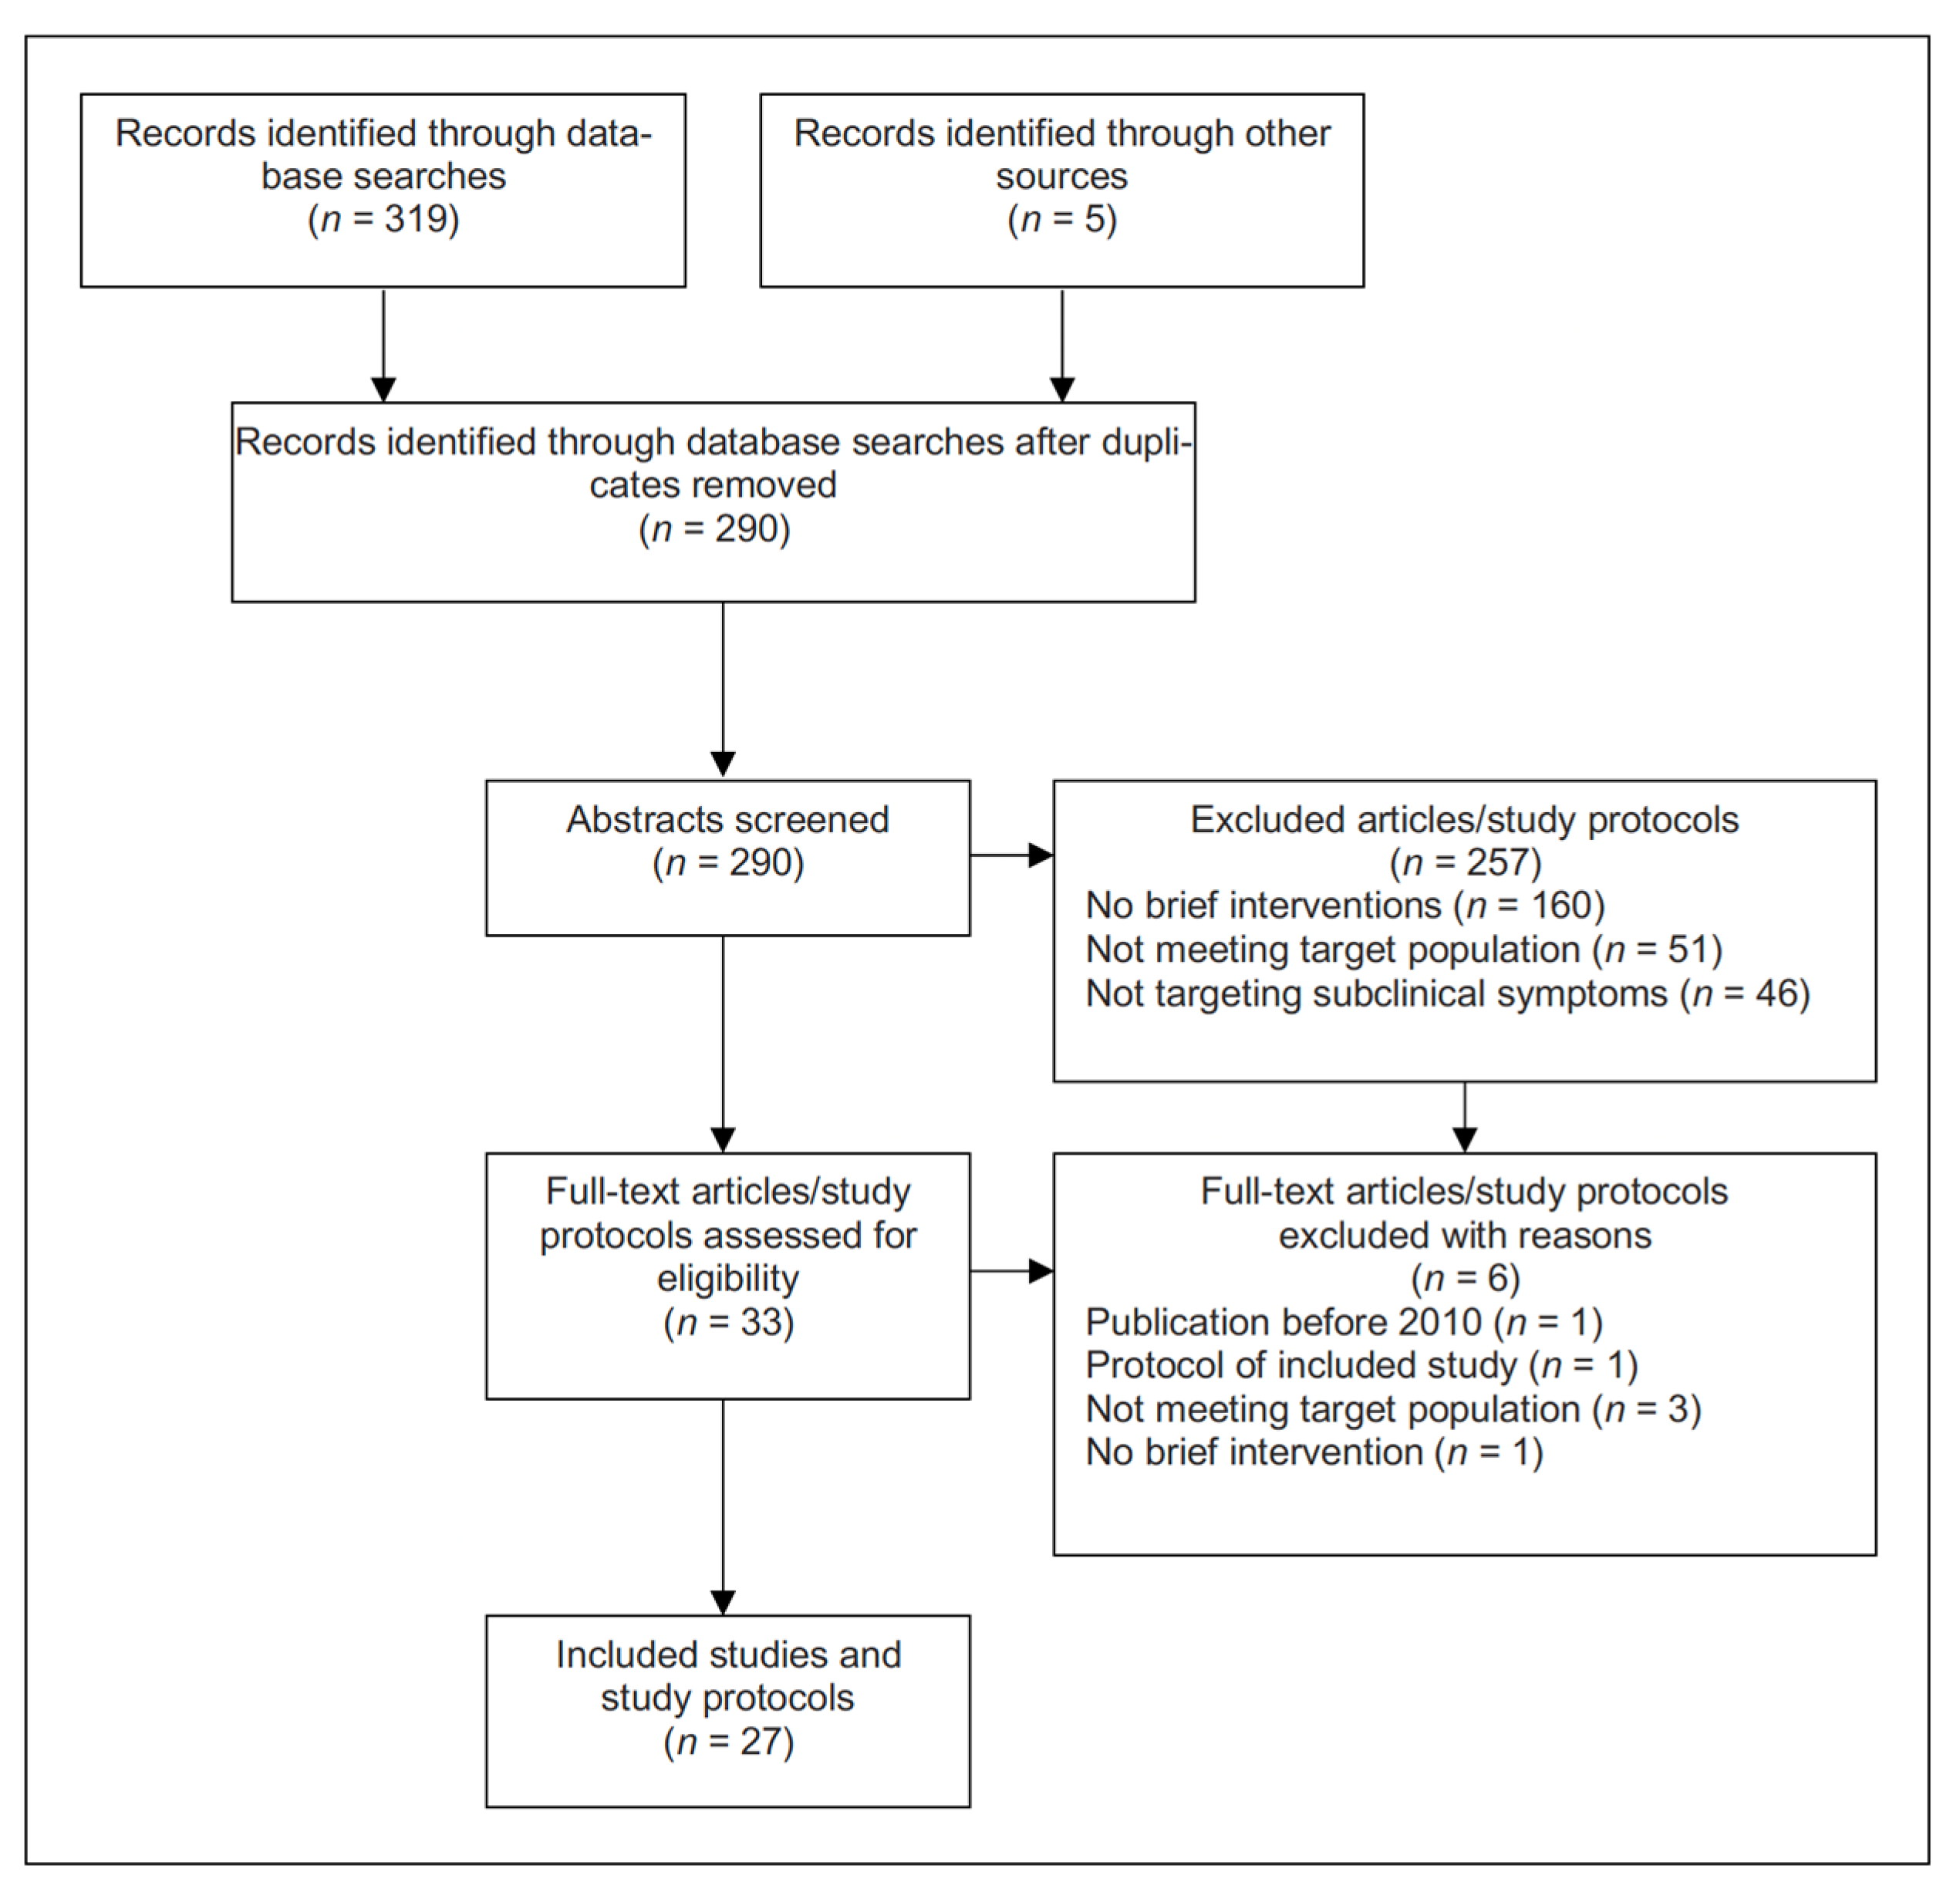

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).