


Abstract
Objective: To collect the available evidence about the effectiveness of pain neuroscience education (PNE) on pain, disability, and psychosocial factors in patients with chronic musculoskeletal (MSK) pain and central sensitization (CS). Methods: A systematic review was conducted. Searches were performed on Pubmed, PEDro, and CINAHL, and only randomized controlled trials (RCTs) enrolling patients ≥18 years of age with chronic MSK pain due to CS were included. No meta-analysis was conducted, and qualitative analysis was realized. Results: 15 RCTs were included. Findings were divided for diagnostic criteria (fibromyalgia—FM, chronic fatigue syndrome—CFS, low back pain—LBP, chronic spinal pain—CSP). PNE has been proposed as a single intervention or associated with other approaches, and different measures were used for the main outcomes considered. Conclusions, practice implication: PNE is effective in improving pain, disability, and psychosocial factors in patients with fibromyalgia, chronic low back pain (CLBP)—especially if associated with other therapeutic approaches—and also in patients with CFS and CSP. Overall, PNE seems to be more effective when proposed in one-to-one oral sessions and associated with reinforcement elements. However, specific eligibility criteria for chronic MSK pain due to CS are still lacking in most RCTs; therefore, for future research, it is mandatory to specify such criteria in primary studies.
1. Introduction
1.1. Background
Chronic musculoskeletal (MSK) disorders are one of the main health problems worldwide [1], with chronic low back pain (CLBP) still being the most common [2,3,4]. In detail, chronic pain can be defined as pain lasting beyond the normal healing time [5], beyond 3 months [6], or, lastly, beyond 3–6 months [7], according to different definitions and criteria arising from previous papers. Chronic MSK pain should also be divided into primary or secondary chronic MSK pain. Primary chronic MSK pain—the object of interest in this review—is considered the “chronic pain experienced in muscles, bones, joints, or tendons that (1) is characterized by significant emotional distress (such as anxiety, anger, frustration, or depressed mood) or functional disability (interference in daily life activities and reduced participation in social roles), and (2) cannot be attributed directly to a known disease or damage process” [8]. Despite the variability of chronic MSK disorders between countries, the estimated prevalence is still high ranging from 11.4% to 24% [9].
Interestingly, most of the patients suffering from MSK pain are unaware of the proper pathway of care to undertake. Therefore, there is a negative impact on pain, disability, and quality of life, with a direct increase in healthcare-related costs for these patients [10,11]. For these reasons, the importance of a biopsychosocial approach has progressively been highlighted for the management of persistent MSK pain, and the most recent approaches include therapeutic exercise, manual therapy associated with exercise, pharmacological pain management, and patient education [12,13,14,15,16,17].
Among the most widespread educational techniques, pain neuroscience education (PNE) has been recognized as an effective approach for the management of patients with persistent MSK disorders, showing clinically relevant results on pain, disability, and psychosocial factors—especially as an adjunct to exercise and/or manual therapy [18,19,20,21,22]. Several authors established that PNE is aimed at reconceptualizing pain perceptions, beliefs, and illness or avoidance behaviors through educational sessions such as one-to-one or collective oral sessions, phone calls, or written materials (booklets or email) [23,24]. However, PNE is not applicable to all patients, and some limits in clinical practice have already been previously highlighted [25]. In 2011, John Nijs and colleagues developed guidelines for the administration of PNE in MSK practice [24]. Specifically, they recommend PNE approaches in two cases: (1) patients with a medical diagnosis consistently related to a dominance of central sensitization (CS) or (2) patients with maladaptive coping strategies, illness perceptions or behaviors, and pain beliefs. Furthermore, to improve the specificity in the identification of patients who may benefit from PNE, the same authors have already provided detailed guidelines for the identification of those with a dominant CS pain mechanism [24,26].
Although PNE seems to be an effective intervention for patients with persistent MSK pain [19], data about the effectiveness of PNE in specific populations of patients with persistent MSK pain due to CS are sparse. In such a scenario, most of the inclusion criteria of published primary or secondary studies are limited to the general chronic MSK pain, but no specific eligibility criteria for CS have been addressed. Given that CS has clearly defined features [26], the effectiveness of PNE in patients with chronic MSK pain due to a dominant CS mechanism still remains a grey area of scientific literature [20,27,28].
1.2. Objectives
The primary aim of this systematic review is to collect the available evidence concerning the effectiveness of PNE, specifically in individuals suffering from chronic MSK pain and CS, on clinically relevant outcomes and to provide recommendations for clinicians and upcoming research.
2. Methods
This systematic review was conducted based on the PRISMA Statement 2020 [29]. The protocol was registered with PROSPERO [30] (CRD42022356005).
2.1. Eligibility Criteria
2.1.1. Study Design
Only randomized controlled trials (RCTs) published in Italian or in English were considered eligible. No further restrictions were applied.
2.1.2. Participants
Studies enrolling patients ≥18 years of age with persistent MSK pain for at least 3 months due to CS were included [6]. In detail, to increase the specificity of CS of the included patients, RCTs were included if their participants were in line with diagnostic criteria related to CS pain mechanism in the literature [24,26,31,32]. For this reason, the study selection used: central sensitization inventory (CSI) scores > 40 and quantitative sensory testing (QST) positive scores for CS or any other criteria [such as fibromyalgia or chronic fatigue syndrome (CFS), or psychosocial factors, maladaptive pain beliefs, illness behaviors]. Furthermore, if studies did not specify such aspects in their eligibility criteria (e.g., only patients with chronic MSK pain without any other information), an in-depth analysis was performed of the baseline characteristics of participants to identify any information that may be related to CS dominance. To make such screening, all questionnaires (such as the CSI itself or Pain Catastrophizing Scale—PCS, Fear-Avoidance Beliefs Questionnaire—FABQ, Tampa Scale of Kinesiophobia—TSK or other measures and questionnaires) were examined through a manual screening. Patients with scores in accordance with a dominance of CS pain mechanism diagnosis were included in the present study.
RCTs were excluded if they enrolled patients aged <18 years of age; or acute, subacute, or recurrent pain conditions or with pain of any duration caused by specific pathologies (pulmonary, cardiac, neurological, oncological, visceral, cognitive, psychiatric disorders) or patients who had surgical back procedures within a year.
No restrictions in terms of publication date have been implemented.
2.1.3. Interventions
RCTs were eligible if interventions were based on PNE proposed in any format. No restrictions were applied in terms of the combination of PNE with other interventions.
2.1.4. Comparisons
Educational interventions, waiting lists, placebo interventions, or other active (e.g., exercise) or passive (e.g., manual therapy) approaches were eligible for inclusion.
2.1.5. Outcome and Outcome Measures
To be included, RCTs had to assess at least 1 of the following outcomes: (1) pain, (2) disability, and (3) psychosocial factors. No restrictions were applied in terms of outcome measures.
2.2. Search Methods for Inclusion of Studies
Electronic Searches
An electronic search was conducted between May and September 2021 on the following databases: PubMed, PEDro, and CINAHL. Searches were set and managed according to the specific settings of each database. Search strings were composed using MESH (Medical Subject Headings)—where possible—or free terms and combined with Boolean operators (AND, OR, and NOT) in line with the PI(C)O model of clinical questions (participants, interventions, outcomes). An additional search on the main 3 databases was conducted between September and October 2022 to add also papers published after the first round of search. Furthermore, all bibliographies of the included studies and all other existing systematic reviews focused on PNE were manually screened to identify other potentially relevant papers.
The full search strategy for PubMed is available in Appendix A.
2.3. Study Selection and Data Extraction
After the removal of duplicates, all records were screened for title and abstract. Then, all full-text articles suitable for inclusion were screened according to the inclusion criteria of the present study through the independent analysis of the main two authors (B.L. and V.B.). A third author (L.S.) not involved in the screening process was involved in case of disagreements. The data extraction process was performed independently by the two main authors (B.L. and V.B.) Full-text papers were retrieved thanks to the Library Service of the University of Bologna and through direct e-mail contact with authors.
2.4. Inter-Rater Agreement
To quantify the inter-rater agreement between the two main authors for full-text selection, Cohen’s Kappa (K) was used. K value was calculated and interpreted according to Altman’s definition [33]: low (k < 0.2), fair (0.2 < k < 0.4), modest (0.41 < k < 0.61), good (0.61 < k < k0.80), excellent (x > 0.80).
2.5. Risk of Bias
The risk of bias in the included studies was independently assessed by the two main authors (B.L. and V.B.) through the Risk of Bias (RoB) assessment tool of the Cochrane Collaboration [34], and a third author (L.S.) was involved in case of disagreements.
2.6. Analysis
Due to the high heterogeneity across the included studies, no meta-analysis was performed, and a qualitative synthesis was conducted in a narrative and tabular format. All data from the included studies related to both between-groups and within-group differences were reported for each outcome. Where possible, punctual estimates, confidence intervals, standard deviation, effect size, statistical significance (p), and clinical relevance (minimal clinical important difference –MCID– or any other measure) were reported.
3. Results
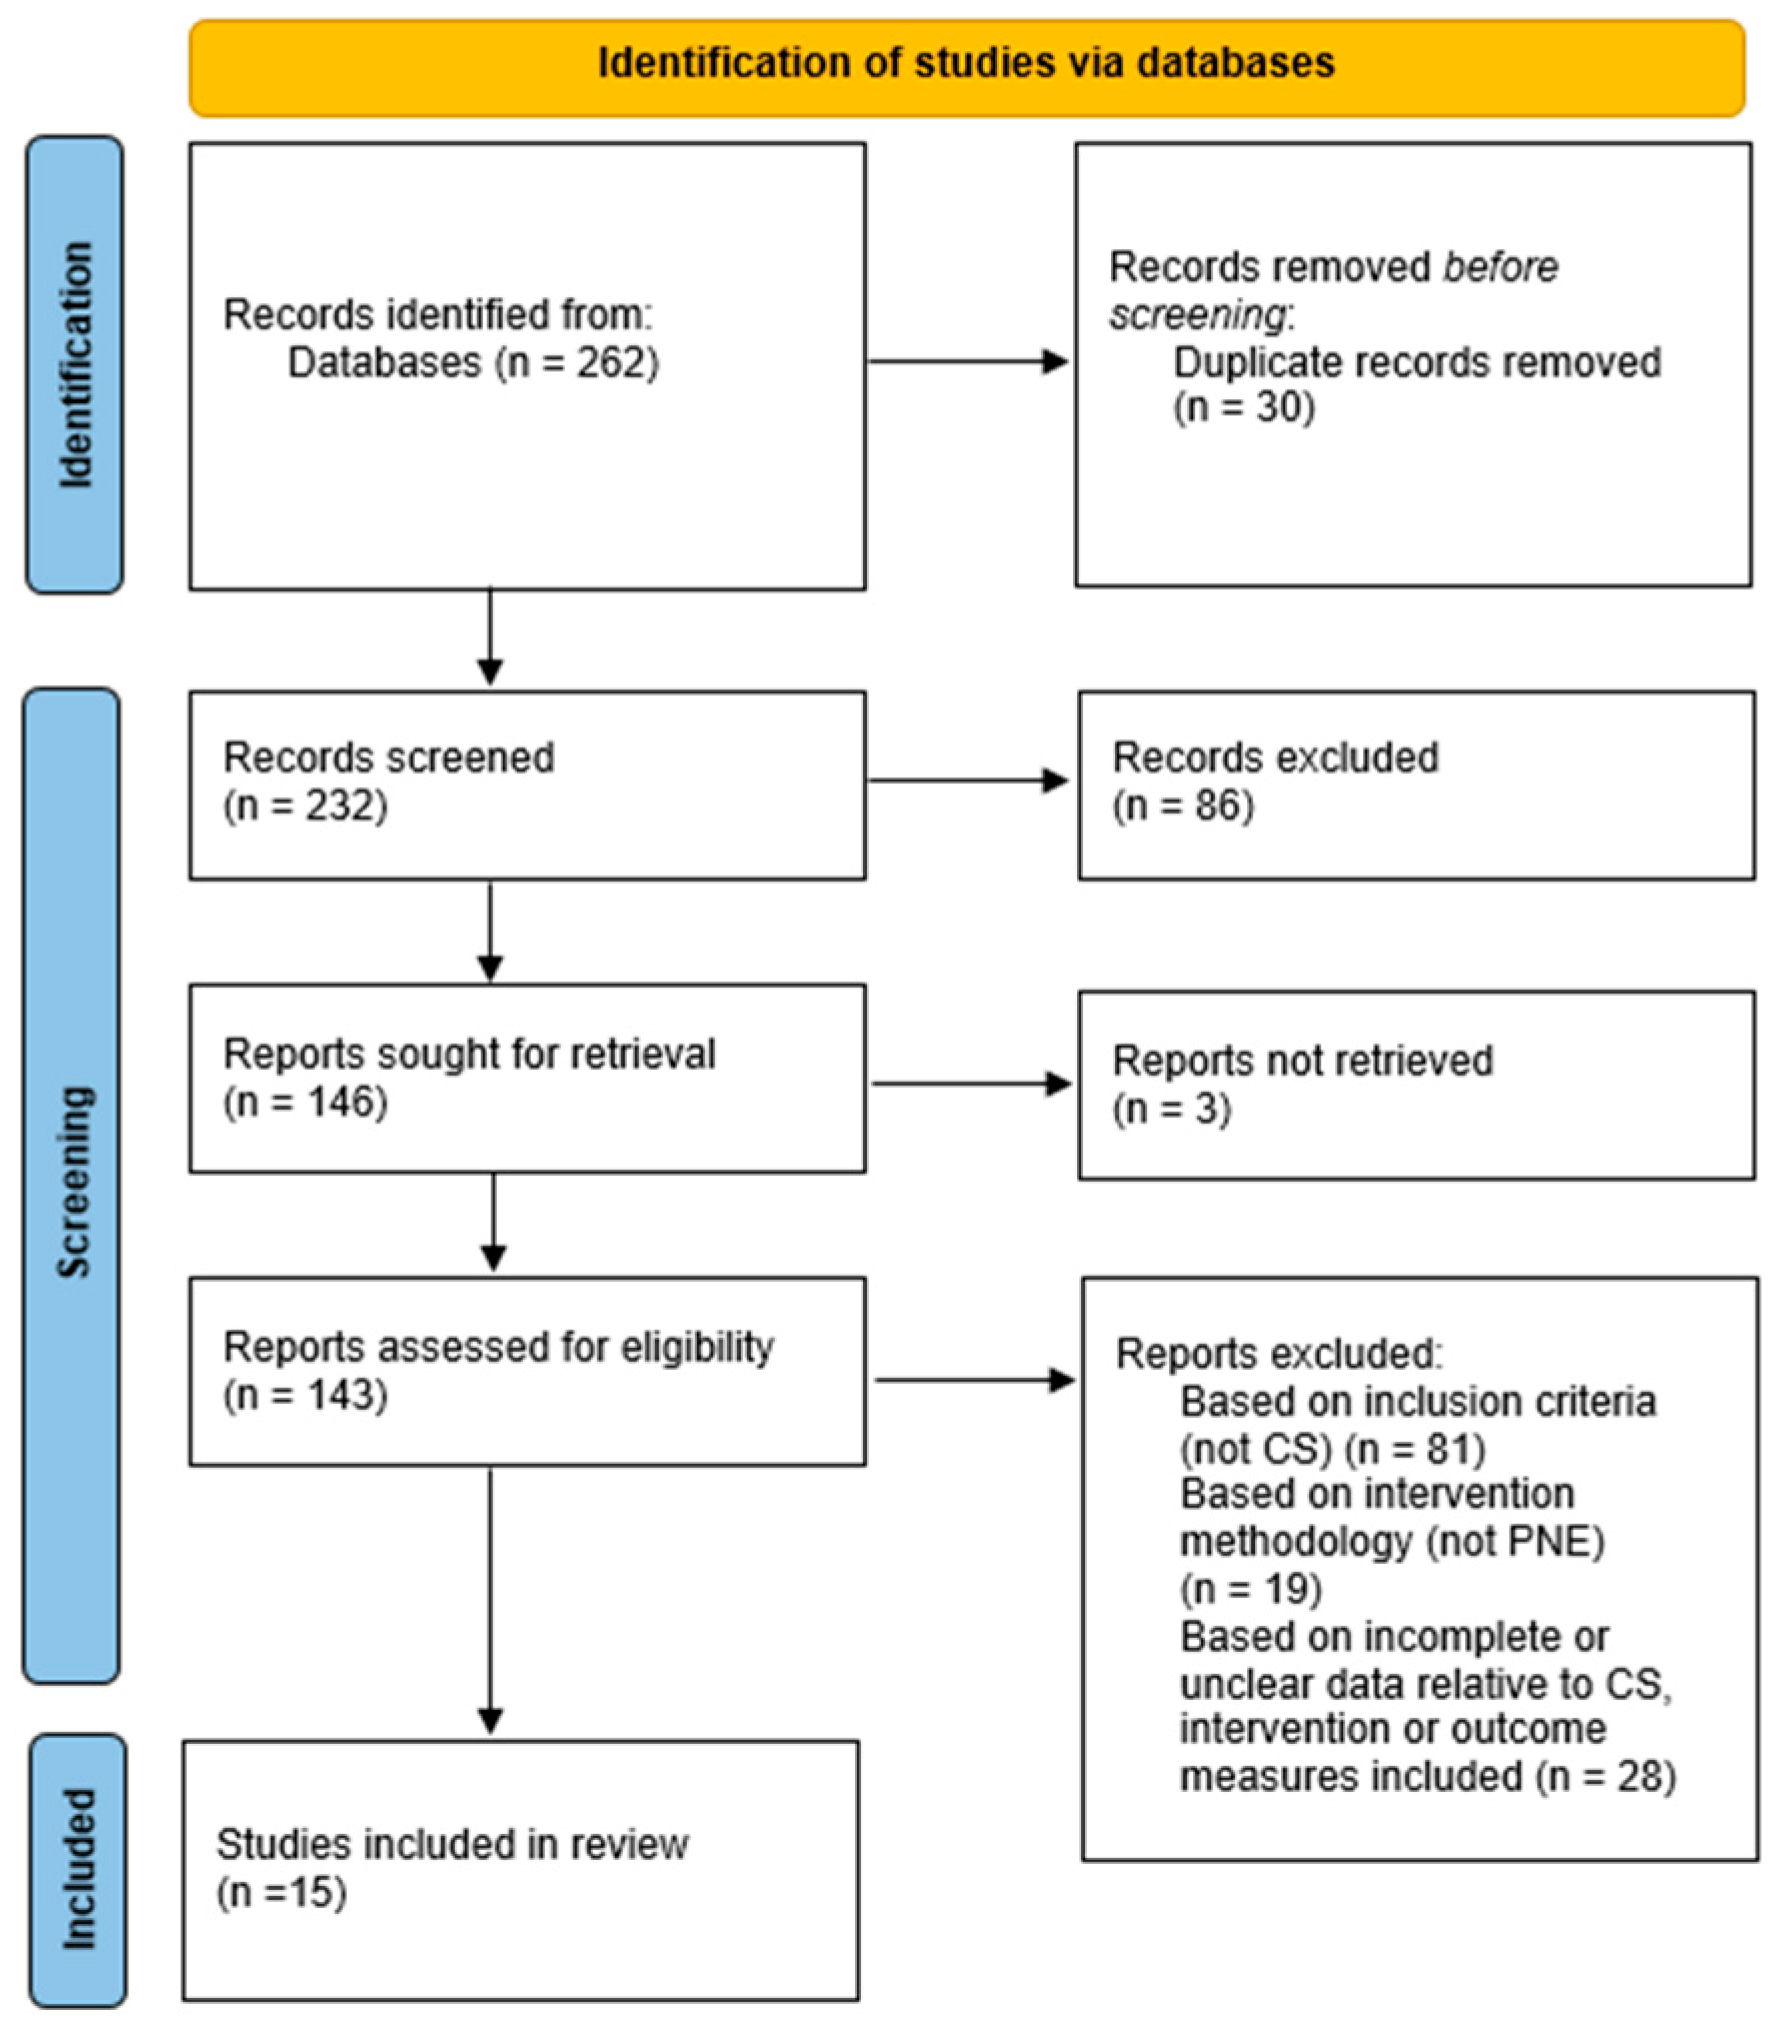
In total, 262 records were retrieved throughout the electronic searches. After the removal of duplicates, title, and abstracts screening led to 143 potentially relevant articles. Finally, a further 128 articles were excluded after the full-text screening, and 15 articles satisfied the inclusion criteria and were included in this systematic review.
The full selection process is reported in Figure 1.
Figure 1.
Flow chart and inclusion process of primary studies.
3.1. Study Characteristics
Overall, 15 RCTs were included [35,36,37,38,39,40,41,42,43,44,45,46,47,48,49]. All characteristics (study design, recruitment, age, sex, duration of pain, diagnostic criteria, and the number of participants) are described in detail in Table 1. Particularly, in 13 studies, participants were divided into 2 intervention groups [35,36,37,38,40,41,42,43,44,46,47,48,49], while 2 studies were multiple-arms RCTs [39,45]. Furthermore, three studies were multicenter trials [35,39,48].
Table 1.
Characteristics of the included studies.
3.1.1. Sample
In total, the participants included and randomized were 1085 (220 males, 863 females, and 2 others). Across all RCTs, the study of Téllez et al. [47] in 2015 had the smallest sample size (12), and the study of Serrat et al. [46] in 2020 had the largest sample size (169).
3.1.2. Drop-Out and Lost to Follow-Up
Out of 1085 patients recruited, there were 60 (5.53%) drop-outs, and 77 (7.10%) lost to follow-up. Details are specified in Table 2.
Table 2.
Drop-outs and lost to follow-up in the included studies.
3.1.3. Follow-Ups
The timing of re-assessment significantly varied across the included studies. Follow-ups ranged between a minimum of after-treatment follow-up [40] and a maximum of 12 weeks follow-up [35]. Details are reported in Table 1.
3.1.4. Adverse Effects
Only two studies [42,43] have specified the absence of adverse events, and one study [35] did not specify adverse events.
3.1.5. Type of Participants
The mean age of all participants was 45.92 years. Although all participants suffered from persistent MSK pain, diagnostic labels significantly differed. Six studies [37,41,42,43,44,47] included patients with CLBP lasting for more than 3 months; two studies [36,45] enrolled patients with CLBP lasting for more than 6 months; one study [38] included patients with fibromyalgia (FM) and CLBP; one study [39] enrolled patients with CSP; one study [40] included patients diagnosed with chronic CFS defined by the Centers for Disease Control and Prevention criteria [51], and four studies [35,46,48,49] included patients with fibromyalgia based on the American College of Rheumatology (ACR) criteria [50]. All specific characteristics are listed in Table 1.
3.1.6. Type of Interventions
PNE was proposed in different modalities in all experimental interventions both alone and in association with other therapeutic approaches. In particular, PNE was proposed as a single intervention [38,39,40,44,48,49], “sensitized” (culture-sensitive PNE approach, based on pain-related beliefs, cognitions, and behaviors of Turkish patients, adapted from rounds of a previous Delphi study) [41] or associated with other therapeutic approaches such as physiotherapy [37], therapeutic exercise [36,43], water-based exercises [42], manual therapy and home exercises [45], dry needling [47], usual care [35], other types of education with therapeutic exercise and outdoor activities associated with usual treatment [46]. Moreover, PNE administration modalities also differed in terms of duration and frequency of the treatment, assigned staff, topics treated, and instruments used. Details are specified in Table 1.
3.1.7. Type of Control Groups
Participants in the control group were subjected to different approaches such as self-management education [40,49], education and relaxation [48], neck/back school [39], usual care [35,46], health behavior control [38], dry needling [47], physiotherapy [37], therapeutic exercise [36], water exercises [42], group exercises [43], home exercises alone or in combination with manual therapy [45]. PNE is also administered in the control group in two studies: a standard approach [41] and PNE + aerobic exercises [44]. Specificities for each control group are expressed in Table 1.
3.1.8. Type of Outcome and Outcome Measures
Significant heterogeneity of outcome measures was found across the included studies for pain, disability, and psychosocial factors. Specifically, pain was assessed with NPRS in three studies [36,45,47], NRS in two studies [41,44], and VAS in three studies [38,43,46]. Disability was evaluated with RMDQ in six studies [36,37,41,43,44,47], QBPDS-PT in one study [42], ODI in two studies [45,47], FIQ in three studies [35,48,49], FIQR in one study [46]. Psychosocial factors were assessed with QBPDS-PT in 1 study [42], PCS in 9 studies [35,36,38,39,40,41,46,48,49], TSK in 12 studies [36,37,38,39,40,41,42,44,45,46,47,49], BPI in 2 studies [35,38], PCI in 2 studies [40,49], PBQ in 1 study [41], PVAQ in 2 studies [39,49], HADS in 2 studies [35,46], HAQ in 1 study [35], PDI in 1 study [39], in 2 studies IPQr [39] and IPQ-FM [48], RSES in 1 study [46], PROMIS in 1 study [38], FABQ in 1 study [43], PSEQ in 2 studies [43,44], PSCOQ in 1 study [38], SF-36 in 2 studies [46,49], and SWLS in 1 study [38]. All details are listed in Table 3.
Table 3.
Outcome and outcome measures in the included studies.
3.2. Risk of Bias
Selection bias was low across the included studies except for two RCTs [37,41] with unclear information about the randomization procedure. The performance bias was rated as high risk in all 15 studies included. Since seven studies [39,40,42,43,45,47,48] provided effective measures to ensure the blindness of assessors, a low risk for attrition bias was attributed. In contrast, in five articles [35,36,37,44,49], the blindness of the evaluators was not guaranteed, leading to a high risk of bias. Three studies [38,41,46] showed an unclear risk for detection bias. All studies were evaluated with a low bias risk for the incomplete reporting of data, except for three studies [37,39,46] that showed a lack of details. For reporting bias, only two studies [35,36] were at high risk, one study [37] was at unclear risk, and all the other studies were judged at low risk. In the evaluation of other biases, two studies [35,46] were labeled with low risk, three studies [44,46,47] with a high risk, and the remaining studies were at unclear risk. All details are listed in Table 4.
Table 4.
Risk of bias.
3.3. Agreement
The inter-rater agreement index (B.L. and V.B.) was good (K = 0.70) for full-text selection. Data are detailed in Table 5.
Table 5.
Agreement for full-text selection.
3.4. Effects of Interventions
The qualitative synthesis for the effectiveness of PNE was divided for the diagnostic label (fibromyalgia, CSP, CFS, fibromyalgia and/or CLBP and CLBP alone) and reported both in a narrative and a tabular format. Details are reported in Table 6.
Table 6.
Effectiveness of PNE based on between-group comparisons.
3.4.1. Fibromyalgia
In the treatment of patients with fibromyalgia, PNE had similar clinical results in improving all the considered outcomes if compared with education and relaxation techniques [48]. Similar conclusions were drawn for PNE when compared with education and self-management, except for the SF-36 questionnaire, where a significant improvement was observed in the intervention group with PNE [49]. When compared to usual treatment [35], PNE was more effective in improving outcome measures such as FIQ, BPI, HAQ, HADS, and PCS. When proposed in a multimodal program (TAU + NAT − FM), PNE was superior to usual care (TAU) for all outcome measures except for RSES [46]. Details are reported in Table 6.
3.4.2. Chronic Spinal Pain (CSP)
In the single RCT focused on CSP, PNE was more effective than education based on neck/back school in improving PCS values in participants with high CSI scores and improving PDI. In contrast, TSK-17 and IPQR values in both intervention groups, regardless of CSI level, were observed [39]. Details are reported in Table 6.
3.4.3. CFS
Compared with the self-management education of ADL [40], PNE was more effective in improving PCS “rumination,” PCI “distraction,” and PCI “worrying.” There were no significant differences between groups in the other PCI and PCS domains and in TSK scores. Details are reported in Table 6.
3.4.4. Fibromyalgia and/or CLBP
At the 1-month follow-up, PNE was significantly superior to the “Health Behavior Control” program on PSCOQ and BPI (severity and interference) scores [38]. However, the subsequent assessment at the 10-month follow-up showed no difference in all outcome measures. Details are reported in Table 6.
3.4.5. CLBP
In the study of Bodes et al. [36] in 2018, PNE associated with therapeutic exercise was more effective than therapeutic exercise alone in improving TSK-11 and PCS-13 at both follow-ups, NPRS and RMDQ at 3 months. Conversely, in the study by Pires et al. [42] in 2014, PNE associated with aquatic exercises showed similar results as aquatic exercises alone. There were no significant differences between the intervention group and the control group either between physiotherapy associated with PNE against physiotherapy alone [37] or between PNE sensitized against the standard PNE, although in the latter case, significant improvements over time in both groups with the two types of PNE were registered [41]. For VAS and RMDQ scores at the 8-week follow-up, a significant group difference was found in favor of the intervention group (PNE only) versus PNE associated with aerobic exercise [43]. At the same follow-up, PNE only associated with aerobic exercises was more effective in improving pain (NPRS) and psychosocial factors (PSEQ), losing significance values at the 3-month follow-up [44]. PNE combined with dry needling (DN) also was more effective than DN alone in improving TSK-17 scores, reaching the clinically significant difference (MCID > 8) [47]. In the study by Saracoglu et al. [45] in 2020, participants were divided into three groups, each with 23 participants. There was a significant improvement in TSK-17 scores at both follow-ups in the first group (PNE, manual therapy, and exercises at home) against the second group (manual therapy and exercises at home). In the first group compared with the third one (home exercises), there were significant improvements in TSK-17, NPRS, and ODI values at both follow-ups. Details are reported in Table 6.
4. Discussion
The objective of this SR was to collect the available evidence about the effectiveness of PNE in chronic MSK patients due to CS on pain, disability, and psychosocial factors.
The risk of bias in most of the studies was low, except the performance bias criterion rated as high risk in all studies. Nevertheless, since a low risk for performance bias may be hard to obtain in physical therapy trials, it does not seem to be a significant factor in downgrading the overall quality of evidence.
Overall, PNE seems to be effective both as a single intervention and more effective if proposed in a multidisciplinary program. Furthermore, only in two studies [37,48] was PNE not significantly superior to controls on all outcome measures. However, since most of the follow-ups were established in the short- or medium-term with few studies addressing long-term follow-ups, it is still unclear if such promising results supporting the effectiveness of PNE (or the combination of PNE with other effective therapeutic approaches) in chronic MSK patients with a dominant CS pain mechanism may also be maintained in the long-term.
4.1. Most Effective Strategies for Diagnostic Label
4.1.1. Fibromyalgia
In the context of FM, PNE proposed in combination with usual treatments for FM was more effective than usual treatments only, as appreciated in two studies with a low to moderate risk of bias [35,46]. However, in one RCT [35], the authors only provided p-values for FIQ scores (p < 0.001), and no data were specified for the remaining so-defined (in the results section) “significant” differences. At all follow-ups (1, 6, and 12 months), there were also improvements defined by authors as “clinically relevant,” but no data for clinical relevance were provided. The second study [46] supports such results revealing the superiority of PNE associated with usual treatments in all outcome measures except for RSES scores. Findings rising from the other 2 moderate to high-quality RCTs [48,49] do not support the effectiveness of PNE as a stand-alone intervention—if compared to education and relaxation [48] or self-management instruction [49]—both in the short- and medium-terms. The discrepancy in results of PNE in FM patients may be related to the necessity of such treatment to be involved in a more comprehensive approach for chronic MSK pain.
4.1.2. CSP
For CSP patients [39], results with a low risk of bias supporting the effectiveness of PNE over neck/back school education are limited to short-term follow-ups (2 weeks), and no long-term benefits were assessed. Although CSI scores were not assessed at the end of the study, it is noteworthy that there has been an improvement in outcomes closely related to CS, such as kinesiophobia and perception of disease, regardless of the level of CSI used to divide the participants in the baseline.
4.1.3. CFS
For CFS patients, conflicting results arising from the unique moderate-quality RCT [40] are strictly limited to the short-term (immediately post-session), and only psychosocial factors were evaluated. For the same outcome measures (e.g., PCS), different results were obtained (e.g., rumination and magnification or helplessness). Such contradictory results are far more reasonable since a single PNE session may not be effective enough (or more effective than other educational approaches) to modify beliefs, perceptions, and thoughts. The latter consideration is in line with Nijs and colleagues, who recommend at least two educational sessions: the first intended to explain CS and pain neurophysiology, and the second aimed at making sure patients understand previous pain [24,26].
4.1.4. Fibromyalgia and/or CLBP
When the participants are both FM and CLBP patients [38], PNE is an effective strategy to improve all psychosocial factors. Indeed, the only results supporting the effectiveness of PNE over a health behavior control approach are limited to the short-term (1 month). Such findings are not surprising since it is unlikely that a single PNE session lasting for 20–25 min with a 3-min instructional video (experimental intervention) will be more effective than the same procedure (control intervention) without significant differences in terms of educational contents.
4.1.5. CLBP
Overall, among the studies included with patients suffering from CLBP, findings from the included RCTs support the effectiveness of PNE, especially if associated with other therapeutic approaches. However, since results differed in terms of follow-up and outcome measures, further considerations are needed. Firstly, it seems that the PNE procedure does not affect outcomes, and both “culture-sensitive” and “standard” PNE are effective in the short term [41]. Significantly better short-term results were obtained if PNE was associated with exercise therapy [36] but not with usual physiotherapy [37]. This is in line with previous literature supporting the effectiveness of different forms of exercise in the management of CLBP patients [52,53,54,55]. However, the type of exercise therapy seems to be crucial. The combination of PNE and aquatic exercise did not add better results than aquatic exercise alone—except for VAS scores at 3 months [42]. The combination of PNE and dry needling (DN) compared to DN was more effective only on TSK scores but not on disability and pain measures. The latter aspect may be due to the reduction of fear of movement thanks to PNE concepts, which do not directly address pain or disability. Furthermore, such results must be interpreted with caution. Since DN is not a recommended procedure for CLBP patients, it does not represent a major comparator for the investigation of PNE effectiveness in CLBP. Surprisingly, previous findings are not in line with those rising from the comparison of PNE versus PNE + aerobic circuit-based exercise [44] and PNE + manual therapy (MT) and home-based exercise (HEX) versus two groups (MT + HEX and HEX only) [45]. In such a scenario, it is still unclear if the latter results are mainly related to the PNE concepts, administration modalities, type of MT approach, or exercise modalities.
4.2. Applicability of Results and Training for Health Professionals
RCTs included in this SR support the effectiveness of PNE in patients with chronic MSK pain due to CS, but the applicability of these results is questionable.
In terms of PNE administration, several modalities were proposed across the included RCTs. Furthermore, PNE was more effective throughout one-to-one oral sessions rather than the group- or online- or written-based approaches, and such findings are surely a major strength of PNE and its applicability in clinical practice. In terms of health professionals, PNE administration needs specific training to achieve enough knowledge of contents regarding neuroanatomy, neurophysiology, and pain mechanisms. Explanations proposed to patients must be proposed using understandable and simple language, metaphors, and examples—requiring, again, specific communicative- and educative-based training. Since not all clinicians are confident and trained in communicative skills and pain education, the latter aspect may limit the applicability of promising results of PNE in clinical practice. Moreover, PNE needs to be proposed only to selected patients; therefore, all clinicians should be able to screen patients in terms of pain mechanism and to recognize all the psychosocial factors related to CS—limiting the transferability of results of this systematic review only to those clinicians trained in these terms. Finally, nothing is known about the long-term effectiveness of PNE. The majority of follow-ups were set in the short- and medium-term. For this reason, the applicability of results in the long term is not possible.
Based on our findings, an urgent need for specific training in the context of pain education is needed, which should be gathered with other mandatory skills for clinicians in direct-access practice, such as screening for referral [56,57,58,59], knowledge in pain neuroscience [25], and other domains of rehabilitation such as exercise [60,61,62].
4.3. Consistency
Since our SR specifically addressed the effectiveness of PNE in patients with chronic MSK pain and CS, the consistency of our findings was limited to previous papers that investigated the overall effectiveness of PNE on MSK pain.
Overall, the results of this SR are consistent with other previous papers. Indeed, PNE already showed effective results in patients with chronic MSK pain, especially when included in multimodal programs [19]. Previous authors demonstrated that the combination of PNE and exercise, compared to exercise alone, leads to greater short-term improvements in pain, disability, and psychosocial factors [63]. Similar conclusions were drawn by Wood and colleagues, supporting the effectiveness of PNE on disability in the short term if combined with the usual-care physiotherapy treatments for CLBP [20]. Finally, Bülow and colleagues, in the first meta-analysis focused on the effectiveness of PNE, showed the promising effects of PNE on pain, disability, and physical, psychological, and social function [64], despite the low quality of included studies.
Therefore, all results gathered from previous papers are consistently in line with our findings. However, none of the previous SRs specifically focused on chronic MSK pain and CS; for this reason, consistency is still limited, and further research is needed.
4.4. Strengths and Limitations
The first limitation of this SR is the lack of specificity of inclusion criteria of primary studies related to the sample of participants with a dominant CS pain mechanism. Indeed, only two studies [36,39] clearly declared a sample of patients with chronic pain and CS using CSI scores. Although the main authors of this systematic review (B.L. and V.B.) screened all baselines characteristics of participants in all RCTs to improve the specificity of the participants with a dominant CS pain mechanism, the latter aspect must be intended as a significant limitation for both this work and current research in the field of PNE and CS. However, although studies enrolling patients with FM [35,38,46,48,49] or CFS [40] did not use specific inclusion criteria for CS, such conditions are currently considered pathologies with a dominant CS pain mechanism [26]. Therefore, such studies might extend the research focused on PNE and CS despite the lack of specific inclusion criteria.
To the best of the authors’ knowledge, this is the first systematic review focused on the effectiveness of PNE in patients with chronic MSK pain and CS; this is a major strength of this work. Furthermore, the accurate research screening process on databases, the manual searches, the double-blind assessment for the risk of bias across the studies, and the good Cohen’s K score for full-text selection are strengths of the methodological quality of this SR.
5. Conclusions
Overall, PNE effectively improves pain, disability, and psychosocial factors in patients with persistent MSK pain and CS. In particular, the one-to-one modality with medium- or long-term sessions with reinforcements (brochures and comprehension exercises) seems to be more effective than remote sessions (telephone and computer) or content-only reading.
In patients with FM, PNE showed promising results when included in a multidisciplinary program, compared with usual care, but not in comparison with other educational or self-management techniques. In patients with CSP and CFS, PNE seems reliable to improve clinical outcomes in the short term when proposed individually against other educational or self-management approaches. Moreover, in patients with CLBP, PNE appears to be effective in combination with other treatments, such as manual therapy and mostly therapeutic exercise.
5.1. Implications for Practice
PNE is a valuable and effective intervention for clinicians in the treatment of patients with persistent MSK pain and a dominant CS pain mechanism. Furthermore, the effectiveness of PNE is more evident if proposed in association with other therapeutic modalities such as manual therapy, therapeutic exercise, and self-management strategies.
5.2. Implications for Research
It is mandatory for future research to homogenize the inclusion criteria in RCTs in order to improve the specificity of sub-groups of participants with a dominance of the CS pain mechanism. Furthermore, longer follow-ups are needed to assess the long-term benefits of PNE, and more standardization of PNE procedures proposed for chronic MSK with CS is needed to summarize these results in a future meta-analysis quantitatively.
Author Contributions
Conceptualization, V.B. and B.L.; methodology, V.B.; investigation, V.B. and B.L.; data curation, V.B. and B.L.; writing—original draft preparation, V.B. and B.L.; writing—review and editing, V.B. and B.L.; supervision, L.S. and D.R. All authors have read and agreed to the published version of the manuscript.
Funding
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors. This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A. Supplementary Data
Search String PubMed: ((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((((“non specific neck pain”) OR (“neck pain syndrome”)) OR (“mechanical neck pain”)) OR (“mechanical low back pain”)) OR (“mechanical low back ache”)) OR (“mechanical back pain”)) OR (“mechanical shoulder pain”)) OR (“mechanical wrist pain”)) OR (“mechanical hip pain”)) OR (“mechanical knee pain”)) OR (“patellofemoral pain syndrome”)) OR (“chronic epicondylalgia”)) OR (“chronic musculoskeletal pain”)) OR (“chronic musculoskeletal disorder”)) OR (“chronic non-specific low back pain”)) OR (“chronic low back pain”)) OR (“chronic lower back pain”)) OR (“chronic back pain”)) OR (“chronic neck pain”)) OR (“chronic shoulder pain”)) OR (“chronic elbow pain”)) OR (“chronic tennis elbow”)) OR (“chronic epicondylitis”)) OR (“chronic wrist pain”)) OR (“chronic sacroiliac joint pain”)) OR (“chronic hip pain”)) OR (“chronic pelvic pain”)) OR (“chronic ankle pain”)) OR (“chronic knee pain”)) OR (“chronic arthritis pain”)) OR (“chronic osteoarthritis pain”)) OR (“chronic arthropathy”)) OR (“chronic tendinopathy”)) OR (“chronic plantar fasciitis”)) OR (“chronic carpal tunnel syndrome”)) OR (“chronic achilles tendinopathy”)) OR (“chronic rotator cuff tendinopathy”)) OR (“hamstring tendinopathy”)) OR (“chronic gluteal tendinopathy”)) OR (“tarsal tunnel syndrome”)) OR (“persistent musculoskeletal pain”)) OR (“persistent musculoskeletal disorders”)) OR (“persistent non-specific low back pain”)) OR (“persistent low back pain”)) OR (“persistent back pain”)) OR (“persistent neck pain”)) OR (“persistent shoulder pain”)) OR (“persistent elbow pain”)) OR (“persistent tennis elbow”)) OR (“persistent wrist pain”)) OR (“persistent hip pain”)) OR (“persistent pelvic pain”)) OR (“persistent ankle pain”)) OR (“persistent knee pain”)) OR (“persistent arthropathy”)) OR (“persistent carpal tunnel syndrome”)) OR (“persistent cubital tunnel syndrome”)) OR (“Low Back Pain” [MeSH Terms])) AND (“chronic pain” [MeSH Terms])) OR (“neck pain” [MeSH Terms])) AND (“chronic pain” [MeSH Terms])) OR (“back pain” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“shoulder pain” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“patellofemoral pain syndrome” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“musculoskeletal pain” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“musculoskeletal diseases” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“tennis elbow” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“elbow tendinopathy” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“pelvic pain” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“arthritis” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“osteoarthritis” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“tendinopathy” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“carpal tunnel syndrome” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) OR (“tarsal tunnel syndrome” [MeSH Terms])) AND (“Chronic Pain” [MeSH Terms])) AND (((((((((“pain neuroscience education”) OR (“neuroscience education”)) OR (“psychological education”)) OR (“neurophysiological pain education”)) OR (“neurobiology education”)) OR (“biology education”)) OR (PNE)) OR (“therapeutic neuroscience education”)) OR (psychoeducation))) AND ((((((((pain) OR (sore)) OR (ache)) OR (function)) OR (disability)) OR (“Psychological factors”)) OR (“Quality of life”)) OR (“Psychosocial factors”).
Search String CINAHL:
((MH “Fatigue Syndrome, Chronic”) OR (MH “Chronic Pain Control (Saba CCC)/ED”) OR (MH “Chronic Pain (NANDA)”) OR (MH “Chronic Pain/ED/RH”) OR (MH “Chronic Pain (Saba CCC)/ED”) OR (MH “Neck Pain/ED”)) AND (((((((((“pain neuroscience education”) OR (“neuroscience education”)) OR (“psychological education”)) OR (“neurophysiological pain education”)) OR (“neurobiology education”)) OR (“biology education”)) OR (PNE)) OR (“therapeutic neuroscience education”)) OR (psychoeducation)) AND ((((((((pain) OR (sore)) OR (ache)) OR (function)) OR (disability)) OR (“Psychological factors”)) OR (“Quality of life”)) OR (“Psychosocial factors”)).
PEDro Search:
We performed an advanced search by entering the words: Education (Therapy), Pain (Problem), Musculoskeletal (Subdiscipline), and Chronic pain (Topic). For the heading “Abstract and title” we performed all searches using the following words: pain neuroscience education, neuroscience education, psychological education, pain neurophysiological education, pain physiological education, neurobiology education, biology education, PNE, therapeutic neuroscience education.
References
- World Health Organization. Musculoskeletal Health. 2022. Available online: https://www.who.int/news-room/fact-sheets/detail/musculoskeletal-conditions (accessed on 12 August 2022).
- Maselli, F.; Storari, L.; Barbari, V.; Colombi, A.; Turolla, A.; Gianola, S.; Rossettini, G.; Testa, M. Prevalence and incidence of low back pain among runners: A systematic review. BMC Musculoskelet. Disord. 2020, 21, 343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, S.; Chen, M.; Wu, X.; Lin, S.; Tao, C.; Cao, H.; Shao, Z.; Xiao, G. Global, regional and national burden of low back pain 1990–2019: A systematic analysis of the Global Burden of Disease study 2019. J. Orthop. Transl. 2021, 32, 49–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, A.; March, L.; Zheng, X.; Huang, J.; Wang, X.; Zhao, J.; Blyth, F.M.; Smith, E.; Buchbinder, R.; Hoy, D. Global low back pain prevalence and years lived with disability from 1990 to 2017: Estimates from the Global Burden of Disease Study 2017. Ann. Transl. Med. 2020, 8, 299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonica, J.J. The Management of Pain, 2nd ed.; Lea & Febiger: Philadelphia, PA, USA, 1990. [Google Scholar]
- Treede, R.D.; Rief, W.; Barke, A.; Aziz, Q.; Bennett, M.I.; Benoliel, R.; Cohen, M.; Evers, S.; Finnerup, N.B.; First, M.B.; et al. A classification of chronic pain for ICD-11. Pain 2015, 156, 1003–1007. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Merskey, H.; Bogduk, N. Classification of Chronic Pain, 2nd ed.; IASP Task Force on Taxonomy; IASP Press: Seattle, WA, USA, 1994. [Google Scholar]
- Perrot, S.; Cohen, M.; Barke, A.; Korwisi, B.; Rief, W.; Treede, R.D.; IASP Taskforce for the Classification of Chronic Pain. The IASP classification of chronic pain for ICD-11: Chronic secondary musculoskeletal pain. Pain 2019, 160, 77–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cimmino, M.A.; Ferrone, C.; Cutolo, M. Epidemiology of chronic musculoskeletal pain. Best Pract. Res. Clin. Rheumatol. 2011, 25, 173–183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kinney, M.; Seider, J.; Beaty, A.F.; Coughlin, K.; Dyal, M.; Clewley, D. The impact of therapeutic alliance in physical therapy for chronic musculoskeletal pain: A systematic review of the literature. Physiother. Theory Pract. 2020, 36, 886–898. [Google Scholar] [CrossRef] [Scilit]
- McCarberg, B.H.; Nicholson, B.D.; Todd, K.H.; Palmer, T.; Penles, L. The impact of pain on quality of life and the unmet needs of pain management: Results from pain sufferers and physicians participating in an Internet survey. Am. J. Ther. 2008, 15, 312–320. [Google Scholar] [CrossRef] [Scilit]
- Barbari, V.; Storari, L.; Ciuro, A.; Testa, M. Effectiveness of communicative and educative strategies in chronic low back pain patients: A systematic review. Patient Educ. Couns. 2020, 103, 908–929. [Google Scholar] [CrossRef] [Scilit]
- George, S.Z.; Fritz, J.M.; Silfies, S.P.; Schneider, M.J.; Beneciuk, J.M.; Lentz, T.A.; Gilliam, J.R.; Hendren, S.; Norman, K.S. Interventions for the Management of Acute and Chronic Low Back Pain: Revision 2021. J. Orthop. Sports Phys. Ther. 2021, 51, CPG1–CPG60. [Google Scholar] [CrossRef] [Scilit]
- Booth, J.; Moseley, G.L.; Schiltenwolf, M.; Cashin, A.; Davies, M.; Hübscher, M. Exercise for chronic musculoskeletal pain: A biopsychosocial approach. Musculoskelet. Care 2017, 15, 413–421. [Google Scholar] [CrossRef] [Scilit]
- Sharma, L. Osteoarthritis of the Knee. N. Engl. J. Med. 2021, 384, 51–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knezevic, N.N.; Candido, K.D.; Vlaeyen, J.W.S.; Van Zundert, J.; Cohen, S.P. Low back pain. Lancet 2021, 398, 78–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chou, R.; Qaseem, A.; Snow, V.; Casey, D.; Cross, J.T., Jr.; Shekelle, P.; Owens, D.K.; Clinical Efficacy Assessment Subcommittee of the American College of Physicians; American College of Physicians; American Pain Society Low Back Pain Guidelines Panel. Diagnosis and treatment of low back pain: A joint clinical practice guideline from the American College of Physicians and the American Pain Society. Ann. Intern. Med. 2007, 47, 478–491. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Louw, A.; Diener, I.; Butler, D.S.; Puentedura, E.J. The effect of neuroscience education on pain, disability, anxiety, and stress in chronic musculoskeletal pain. Arch. Phys. Med. Rehabil. 2011, 92, 2041–2056. [Google Scholar] [CrossRef] [Scilit]
- Louw, A.; Zimney, K.; Puentedura, E.J.; Diener, I. The efficacy of pain neuroscience education on musculoskeletal pain: A systematic review of the literature. Physiother. Theory Pract. 2016, 32, 332–355. [Google Scholar] [CrossRef] [Scilit]
- Wood, L.; Hendrick, P.A. A systematic review and meta-analysis of pain neuroscience education for chronic low back pain: Short-and long-term outcomes of pain and disability. Eur. J. Pain 2019, 23, 234–249. [Google Scholar] [CrossRef] [Scilit]
- Watson, J.A.; Ryan, C.G.; Cooper, L.; Ellington, D.; Whittle, R.; Lavender, M.; Dixon, J.; Atkinson, G.; Cooper, K.; Martin, D.J. Pain Neuroscience Education for Adults With Chronic Musculoskeletal Pain: A Mixed-Methods Systematic Review and Meta-Analysis. J. Pain 2019, 20, 1140.e1–1140.e22. [Google Scholar] [CrossRef] [Scilit]
- Suso-Martí, L.; Cuenca-Martínez, F.; Alba-Quesada, P.; Muñoz-Alarcos, V.; Herranz-Gómez, A.; Varangot-Reille, C.; Domínguez-Navarro, F.; Casaña, J. Effectiveness of Pain Neuroscience Education in Patients with Fibromyalgia: A Systematic Review and Meta-Analysis. Pain Med. 2022, 23, 1837–1850. [Google Scholar] [CrossRef] [Scilit]
- Moseley, G.L. Reconceptualising pain according to modern pain science. Phys. Ther. Rev. 2007, 12, 169–178. [Google Scholar] [CrossRef] [Scilit]
- Nijs, J.; Paul van Wilgen, C.; Van Oosterwijck, J.; van Ittersum, M.; Meeus, M. How to explain central sensitization to patients with ‘unexplained’ chronic musculoskeletal pain: Practice guidelines. Man. Ther. 2011, 16, 413–418. [Google Scholar] [CrossRef] [Scilit]
- Barbari, V.; Storari, L.; Maselli, F.; Testa, M. Applicability of pain neuroscience education: Where are we now? J. Back Musculoskelet. Rehabil. 2021, 34, 511–520. [Google Scholar] [CrossRef] [Scilit]
- Nijs, J.; Van Houdenhove, B.; Oostendorp, R.A. Recognition of central sensitization in patients with musculoskeletal pain: Application of pain neurophysiology in manual therapy practice. Man. Ther. 2010, 15, 135–141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Puentedura, E.J.; Flynn, T. Combining manual therapy with pain neuroscience education in the treatment of chronic low back pain: A narrative review of the literature. Physiother. Theory Pract. 2016, 32, 408–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Louw, A.; Nijs, J.; Puentedura, E.J. A clinical perspective on a pain neuroscience education approach to manual therapy. J. Man. Manip. Ther. 2017, 25, 160–168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, 71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Booth, A.; Clarke, M.; Dooley, G.; Ghersi, D.; Moher, D.; Petticrew, M.; Stewart, L. The nuts and bolts of PROSPERO: An international prospective register of systematic reviews. Syst. Rev. 2012, 1, 2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kosek, E.; Cohen, M.; Baron, R.; Gebhart, G.F.; Mico, J.A.; Rice, A.S.C.; Rief, W.; Sluka, A.K. Do we need a third mechanistic descriptor for chronic pain states? Pain 2016, 157, 1382–1386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kosek, E.; Clauw, D.; Nijs, J.; Baron, R.; Gilron, I.; Harris, R.E.; Mico, J.A.; Rice, A.S.C.; Sterling, M. Chronic nociplastic pain affecting the musculoskeletal system: Clinical criteria and grading system. Pain 2021, 162, 2629–2634. [Google Scholar] [CrossRef] [Scilit]
- Altman, D.G. Practical Statistics for Medical Research, 1st ed.; Chapman and Hall: London, UK, 1990. [Google Scholar]
- Higgins, J.P.T.; Altman, D.G.; Gotzsche, P.C.; Juni, P.; Moher, D.; Oxman, A.D.; Savovic, J.; Schulz, K.F.; Weeks, L.; Sterne, J.A.C.; et al. The Cochrane Collaboration’s tool for assessing risk of bias in randomised trials. BMJ 2011, 343, d5928. [Google Scholar] [CrossRef] [Scilit]
- Barrenengoa-Cuadra, M.J.; Muñoa-Capron-Manieux, M.; Fernández-Luco, M.; Angón-Puras, L.Á.; Romón-Gómez, A.J.; Azkuenaga, M.; Etxebarria, A.; Orrantia, G.; Pikaza, A.; Uribe-Etxebarria, L.; et al. Effectiveness of a structured group intervention based on pain neuroscience education for patients with fibromyalgia in primary care: A multicentre randomized open-label controlled trial. Eur. J. Pain 2021, 25, 1137–1149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bodes Pardo, G.; Lluch Girbés, E.; Roussel, N.A.; Gallego Izquierdo, T.; Jiménez Penick, V.; Pecos Martín, D. Pain Neurophysiology Education and Therapeutic Exercise for Patients With Chronic Low Back Pain: A Single-Blind Randomized Controlled Trial. Arch. Phys. Med. Rehabil. 2018, 99, 338–347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gül, H.; Erel, S.; Toraman, N.F. Physiotherapy combined with therapeutic neuroscience education versus physiotherapy alone for patients with chronic low back pain: A pilot, randomized-controlled trial. Turk. J. Phys. Med. Rehabil. 2021, 67, 283–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kohns, D.J.; Urbanik, C.P.; Geisser, M.E.; Schubiner, H.; Lumley, M.A. The Effects of a Pain Psychology and Neuroscience Self-Evaluation Internet Intervention: A Randomized Controlled Trial. Clin. J. Pain 2020, 36, 683–692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malfliet, A.; Kregel, J.; Meeus, M.; Danneels, L.; Cagnie, B.; Roussel, N.; Nijs, J. Patients with Chronic Spinal Pain Benefit from Pain Neuroscience Education Regardless the Self-Reported Signs of Central Sensitization: Secondary Analysis of a Randomized Controlled Multicenter Trial. PM R 2018, 10, 1330–1343.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meeus, M.; Nijs, J.; Van Oosterwijck, J.; Van Alsenoy, V.; Truijen, S. Pain physiology education improves pain beliefs in patients with chronic fatigue syndrome compared with pacing and self-management education: A double-blind randomized controlled trial. Arch. Phys. Med. Rehabil. 2010, 91, 1153–1159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Orhan, C.; Lenoir, D.; Favoreel, A.; Van Looveren, E.; Yildiz Kabak, V.; Mukhtar, N.B.; Cagnie, B.; Meeus, M. Culture-sensitive and standard pain neuroscience education improves pain, disability, and pain cognitions in first-generation Turkish migrants with chronic low back pain: A pilot randomized controlled trial. Physiother. Theory Pract. 2021, 37, 633–645. [Google Scholar] [CrossRef] [Scilit]
- Pires, D.; Cruz, E.B.; Caeiro, C. Aquatic exercise and pain neurophysiology education versus aquatic exercise alone for patients with chronic low back pain: A randomized controlled trial. Clin. Rehabil. 2015, 29, 538–547. [Google Scholar] [CrossRef] [Scilit]
- Rabiei, P.; Sheikhi, B.; Letafatkar, A. Comparing Pain Neuroscience Education Followed by Motor Control Exercises With Group-Based Exercises for Chronic Low Back Pain: A Randomized Controlled Trial. Pain Pract. 2021, 21, 333–342. [Google Scholar] [CrossRef] [Scilit]
- Ryan, C.G.; Gray, H.G.; Newton, M.; Granat, M.H. Pain biology education and exercise classes compared to pain biology education alone for individuals with chronic low back pain: A pilot randomised controlled trial. Man. Ther. 2010, 15, 382–387. [Google Scholar] [CrossRef] [Scilit]
- Saracoglu, I.; Arik, M.I.; Afsar, E.; Gokpinar, H.H. The effectiveness of pain neuroscience education combined with manual therapy and home exercise for chronic low back pain: A single-blind randomized controlled trial. Physiother. Theory Pract. 2022, 38, 868–878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Serrat, M.; Almirall, M.; Musté, M.; Sanabria-Mazo, J.P.; Feliu-Soler, A.; Méndez-Ulrich, J.L.; Luciano, J.V.; Sanz, A. Effectiveness of a Multicomponent Treatment for Fibromyalgia Based on Pain Neuroscience Education, Exercise Therapy, Psychological Support, and Nature Exposure (NAT-FM): A Pragmatic Randomized Controlled Trial. J. Clin. Med. 2020, 9, 3348. [Google Scholar] [CrossRef] [Scilit]
- Téllez-García, M.; de-la-Llave-Rincón, A.I.; Salom-Moreno, J.; Palacios-Ceña, M.; Ortega-Santiago, R.; Fernández-de-Las-Peñas, C. Neuroscience education in addition to trigger point dry needling for the management of patients with mechanical chronic low back pain: A preliminary clinical trial. J. Bodyw. Mov. Ther. 2015, 19, 464–472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Ittersum, M.W.; van Wilgen, C.P.; van der Schans, C.P.; Lambrecht, L.; Groothoff, J.W.; Nijs, J. Written pain neuroscience education in fibromyalgia: A multicenter randomized controlled trial. Pain Pract. 2014, 14, 689–700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Oosterwijck, J.; Meeus, M.; Paul, L.; De Schryver, M.; Pascal, A.; Lambrecht, L.; Nijs, J. Pain physiology education improves health status and endogenous pain inhibition in fibromyalgia: A double-blind randomized controlled trial. Clin. J. Pain 2013, 29, 873–882. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fukuda, K.; Straus, S.E.; Hickie, I.; Sharpe, M.C.; Dobbins, J.G.; Komaroff, A. The chronic fatigue syndrome: A comprehensive approach to its definition and study. International Chronic Fatigue Syndrome Study Group. Ann. Intern. Med. 1994, 121, 953–959. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolfe, F.; Smythe, H.A.; Yunus, M.B.; Bennett, R.M.; Bombardier, C.; Goldenberg, D.L.; Tugwell, P.; Campbell, S.M.; Abeles, M.; Clark, P.; et al. The American College of Rheumatology 1990 Criteria for the Classification of Fibromyalgia. Report of the Multicenter Criteria Committee. Arthritis Rheum. 1990, 33, 160–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shiri, R.; Coggon, D.; Falah-Hassani, K. Exercise for the Prevention of Low Back Pain: Systematic Review and Meta-Analysis of Controlled Trials. Am. J. Epidemiol. 2018, 187, 1093–1101. [Google Scholar] [CrossRef] [Scilit]
- Gordon, R.; Bloxham, S. A Systematic Review of the Effects of Exercise and Physical Activity on Non-Specific Chronic Low Back Pain. Healthcare 2016, 4, 22. [Google Scholar] [CrossRef] [Scilit]
- Searle, A.; Spink, M.; Ho, A.; Chuter, V. Exercise interventions for the treatment of chronic low back pain: A systematic review and meta-analysis of randomised controlled trials. Clin. Rehabil. 2015, 29, 1155–1167. [Google Scholar] [CrossRef] [Scilit]
- Quentin, C.; Bagheri, R.; Ugbolue, U.C.; Coudeyre, E.; Pélissier, C.; Descatha, A.; Menini, T.; Bouillon-Minois, J.B.; Dutheil, F. Effect of Home Exercise Training in Patients with Nonspecific Low-Back Pain: A Systematic Review and Meta-Analysis. Int. J. Environ. Res. Public Health 2021, 18, 8430. [Google Scholar] [CrossRef] [Scilit]
- Maselli, F.; Palladino, M.; Barbari, V.; Storari, L.; Rossettini, G.; Testa, M. The diagnostic value of Red Flags in thoracolumbar pain: A systematic review. Disabil. Rehabil. 2022, 44, 1190–1206. [Google Scholar] [CrossRef] [Scilit]
- Andreoletti, F.; Maselli, F.; Storari, L.; Vongher, A.; Erbesato, M.; Testa, M.; Turolla, A. Screening for Referral of Serious Pathology by Physical Examination Tests in Patients with Back or Chest Pain: A Systematic Review. Int. J. Environ. Res. Public Health 2022, 19, 16418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pennella, D.; Giagio, S.; Maselli, F.; Giovannico, G.; Roncone, A.; Fiorentino, F.; Brindisino, F. Red flags useful to screen for gastrointestinal and hepatic diseases in patients with shoulder pain: A scoping review. Musculoskelet. Care 2022, 20, 721–730. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piano, L.; Maselli, F.; Viceconti, A.; Gianola, S.; Ciuro, A. Direct access to physical therapy for the patient with musculoskeletal disorders, a literature review. J. Phys. Ther. Sci. 2017, 29, 1463–1471. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hooker, S.P.; Buchner, D.M. Education and training in physical activity research and practice. Prev. Med. 2009, 49, 294–296. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coombes, J.S.; Williams, A.; Radford, J. Training health professionals to provide physical activity counselling. Prog. Cardiovasc. Dis. 2021, 64, 72–76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Netherway, J.; Smith, B.; Monforte, J. Training Healthcare Professionals on How to Promote Physical Activity in the UK: A Scoping Review of Current Trends and Future Opportunities. Int. J. Environ. Res. Public Health 2021, 18, 6701. [Google Scholar] [CrossRef] [Scilit]
- Siddall, B.; Ram, A.; Jones, M.D.; Booth, J.; Perriman, D.; Summers, S.J. Short-term impact of combining pain neuroscience education with exercise for chronic musculoskeletal pain: A systematic review and meta-analysis. Pain 2022, 163, e20–e30. [Google Scholar] [CrossRef] [Scilit]
- Bülow, K.; Lindberg, K.; Vaegter, H.B.; Juhl, C.B. Effectiveness of Pain Neurophysiology Education on Musculoskeletal Pain: A Systematic Review and Meta-Analysis. Pain Med. 2021, 22, 891–904. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).