


Abstract
Background: Virtual reality used for the treatment of mental health disorders is showing promising potential in clinical practice. Increasing self-compassion and self-protections and decreasing self-criticism have been identified as trans-diagnostic mechanisms helping to build a resilient self. The goal of this systematic review was to provide an overview of research studies about virtual reality while exploring its effectiveness in increasing self-compassion and self-protection and decreasing self-criticism. Methods: On 6 December 2022, titles, abstracts, and, where available, keywords were searched in the following databases: PubMed, Scopus, and Web of Science. The inclusion criteria were: empirical study; quantitative methodology; outcomes measured, including self-compassion and/or self-protection, and/or self-criticism; pre/post and/or control group intervention measures of selected outcomes; participants aged 18 and above; application of virtual reality technology as part of the intervention; full study availability; and English language. Exclusion criteria were: ruminations related only to physical pain; self-protection in the context of physical survival; VR used to increase ruminations. Results: Selection criteria were met by 19 studies (two randomized controlled trials, 16 longitudinal studies, and one case study) with an overall number of 672 participants. Results suggest that VR interventions targeting self-criticism, self-compassion, and self-protection might be effective for non-clinical (self-compassion) as well as clinical (self-criticism and self-protection) samples. Discussion: The present systematic review partially supports the effectiveness of VR interventions on self-criticism, self-protection, and self-compassion. To properly answer the question of its effectiveness, more randomized control trials with larger samples from different populations are needed. The results are also limited by the variability of intervention protocols and the amount of exposure to VR. Other: This work was supported by the Vedecká grantová agentúra VEGA under Grant 1/0075/19. This systematic review has not been pre-registered.
1. Introduction
Virtual reality (VR), as a facilitator of psychological interventions for the treatment of mental health disorders, is increasingly showing potential for clinical practice [1,2]. This has been particularly the case in the last few years, as it is only since 2016 that high-quality immersive VR technology has become affordable, making it accessible to wider audiences [3].
VR is defined as a technology that enables an advanced interaction between humans and computers and allows for humans to become immersed in a synthetic environment generated by the computer [4]. Although VR is meant to be an interactive and immersive system by design, the various existing forms of VR on the market can be divided into immersive and non-immersive, as well as interactive and non-interactive VR. Non-immersive VR is usually delivered through a computer screen and tends to come in the form of a three-dimensional computer game controlled via a keyboard, joystick, or some other type of interface [5]. Immersive VR, alternatively, can be described as a life-sized environment that evokes in the user the sensation of actually being part of it [6]. Immersion is usually achieved by blocking out sensory stimuli from the physical world and presenting an alternative three-dimensional digital world through a head-mounted display (HMD) or through an immersive room, such as Cave Automatic Virtual Environment (CAVE) [7]. Interactive VR is a system that is essentially sensitive and responsive to the user’s behavior, facilitating an interaction between the user and objects within this virtual world. Conversely, non-interactive VR does not allow for interaction; the user is more-or-less a passive viewer of a digitally generated environment. A 360-degree video would be considered non-interactive VR: although the user can exploit the full view through movements (e.g., head rotation while wearing a HMD), he or she cannot interact with the content of the presented environment.
VR has the capacity to provide a subjective and illusional experience, i.e., to (to some degree) simulate reality and real-world interactions, which indicates broad scientific and clinical implications. Moreover, VR offers tight control over simulation, reduces the inconsistency of interventions, and, most importantly, allows for the design of tailor-made therapeutically valuable situations that are otherwise (nearly) impossible to recreate in real life [6]. So far, research has been conducted on the clinical use of VR in the treatment of mental health disorders, showing promising results for depression (e.g., [8]), anxieties (e.g., [9]), post-traumatic stress disorder (e.g., [10]), eating disorders (e.g., [11]), pain management (e.g., [12]), autism (e.g., [13]), forensic psychiatry (e.g., [14]), and schizophrenia (e.g., [15]).
Depression and anxiety are two of the most common mental health disorders globally [16]. They frequently coexist—depressive people often have symptoms of anxiety, just as people with anxiety disorders often suffer from depression [17]. One of the main risk factors predicting both depression and anxiety has been identified as self-criticism [18]. Self-criticism can be conceptualized as an intense and persistent relationship one has with oneself, consisting of an unshakeable and increasing demand to constantly perform within the highest standards and an inwardly-directed hostility and depreciation when this unachievable demand is not met [19]. Self-criticism is often interchangeably used with or related to negative ruminations, self-judgement, self-hatred, self-contempt, self-attack, the inner critic, or self-shame. As the antidote to the pain that self-criticism (or negative self-treatment) causes, two adaptive processes were identified—self-compassion and self-protection—both within the framework of Emotion-focused Therapy [20]. In the therapeutic model of Emotion-focused Therapy [21], self-criticism, self-compassion, and self-protection are meaningfully tied together, and working with them is central to building one’s empowered and resilient self [20]. Emotion-focused Therapy’s efficiency for the treatment of self-criticism was supported, for example, by Shahar et al. [22,23], Thompson and Girz [24], and Timulak et al. [25].
Self-compassion is best understood as inwardly-directed compassion [26]. It can be conceptualized as an emotion [27,28], frame of mind [29], skills set [30], or process [31] that is associated with understanding the universality of human suffering, recognizing one’s own suffering, feeling for the suffering person, tolerating uncomfortable feelings, and acting on or having the motivation to act on that suffering in order to alleviate it. Interchangeably with self-compassion, scholars also use terms such as self-soothing or self-reassurance. Self-protection can be understood as assertiveness directed at one’s own inner critic. Also labelled as assertive anger [32] or protective anger [20], self-protection can be defined as a state or adaptive emotion that allows a person to stand up for their rights and needs, set boundaries against, and assertively engage in a fight with their own mistreatment they have internalized from the voices of important figures, mainly in childhood. More recently, Neff [33] introduced a similar concept of fierce self-compassion, which is defined as a united caring force against environmental pressures and injustices but also against one’s own habits. Interest in self-compassion has been growing significantly since the early 2000s [34], with the first few studies employing VR to enhance self-compassion appearing more recently (e.g., [35]). So far, it seems that a lot less has been published about self-protection in general. However, assertiveness most likely entered VR research at the turn of the millennium [11].
This systematic review focuses on VR interventions targeting the three abovementioned self-concepts: self-criticism, self-compassion, and self-protection. This systematic review summarizes the existing scientific literature on VR interventions applied to decrease self-criticism or increase self-compassion or self-protection, compared with control treatment, no treatment, or baseline scores in the clinical and non-clinical adult populations. The results of this systematic review may inform the development of effective VR interventions targeting not only these three self-concepts but ultimately may lead to new ways of addressing depression and anxiety. To our knowledge, this is the first systematic review focusing on self-compassion, self-criticism, and self-protection applied in virtual reality. As results of using virtual reality for mental health interventions are very promising, and these three concepts play a pivotal role in psychopathology as well as mental and physical health, we were particularly interested in how effective VR is for these particular three concepts.
2. Methods
This systematic review was directed according to the Preferred Reporting Items for Systematic Review and Meta-Analyses (PRISMA), using the 2020 updated guidelines [36].
2.1. Information Sources
This systematic review includes all literature written in English, published until 6th December 2022, and accessible through the PubMed, Scopus, and Web of Science databases. The main focus was on VR as a platform facilitating the increase of self-compassion and/or self-protection and/or the decrease of self-criticism. In all three databases, records (titles and abstracts) were searched, and where available, keywords were added to the search too.
2.2. Search Strategy
The searches were completed in three separate steps, depending on the search topic. The general search terms for all three searches were: (“virtual reality” OR “VR” OR “virtual environment*” OR “virtual world*” OR “avatar” OR “serious game*”). The topic-specific search terms for self-compassion were: (“compassion*” OR “self-compassion*” OR “self-sooth*” OR “self-reassur*”); for self-criticism: (“self-critic*” OR “inner critic*” OR “self-contempt*” OR “ “self-hat*” OR “self-attack*” OR “ruminat*” OR “self-judg*”); and for self-protection: (“self-protecti*” OR “protective anger” OR “assertive anger” OR “assertive*” OR “self-assert*” OR “fierce self-compassion”). See Appendix A for the full search syntax used in each of the databases.
2.3. Eligibility Criteria
The inclusion criteria were: empirical study; quantitative methodology; outcomes measured, including self-compassion and/or self-protection/assertiveness, and/or self-criticism/negative ruminations; pre/post and/or control group intervention measures of selected outcomes; participants aged 18 and above; application of VR technology as part of the intervention; full study availability; and English language. Exclusion criteria were: ruminations related only to physical pain; self-protection in the context of physical survival; and VR used to increase ruminations. When synthesizing the evidence, studies were grouped according to the main outcomes of this review: self-criticism, self-compassion, and self-protection.
2.4. Selection Process
The eligibility criteria were decided on by both authors. The database search was conducted by the first author (TŽ). The screening was completed by the first author under full supervision of the second author (JH). The first author justified all selected and rejected studies to the second author. The second author challenged the first author’s justifications. All decisions on inclusion and exclusion were made consensually by both authors.
2.5. Data Collection
All variables were agreed on by both authors. The data collection process was conducted by the first author and checked by the second author. The first author consulted the second author about any uncertainties or inconsistencies that arose from the data collection process. Only variables relevant to this systematic review were extracted. If other measurements had taken place in the selected studies, these were not included. In total, nine variables had been decided: one outcome domain (#8) and 8 additional variables (#1-#7, #9):
- Type of the study design; studies were defined according to the purpose of this systematic review (i.e., even though a study had a control group, if the control group was not used as a comparison for the intervention group in respect to our outcomes, we treated it as a within-group study).
- The components of each intervention and, where available, the duration of each component; and the total duration of VR exposure one participant in the intervention group received.
- Whether participants in the control group received VR exposure too or not.
- The content of each VR intervention.
- Immersion and interactivity of VR technology used.
- The type of sample used in the study and their age.
- The size of intervention and control group(s).
- What outcomes, according to the focus of this systematic review, were measured (self-compassion, self-protection, assertiveness, negative ruminations, or self-criticism) and how (names of relevant measuring tools used, if available).
- The results of relevant outcomes as measured in point #8.
Not all studies reported all variables in full detail. Where available, study investigators were contacted directly via email for any missing information. We define only immersive/non-immersive and interactive/non-interactive VR technology as, likely, this is the most straightforward way to understand VR technology from a non-technical user experience point of view. There are, of course, other parameters (e.g., display resolution, manufacturer, etc.) that could be looked at when classifying VR technology; however, this would perhaps make a lot more sense once there are more studies published.
2.6. Risk of Bias and Certainty Assessment
The risk of bias was assessed by the first author and checked and challenged by the second author. Discrepancies were discussed, clarified, and agreed upon together. As a framework, we followed the Cochrane Collaboration’s tool for assessing risk of bias in interventions [37], looking at selection, performance, detection, attrition, reporting, and other biases. We used this tool for both randomized and non-randomized studies. To assess attrition, we followed the five-and-20 rule of thumb used by some researchers, considering attrition of less than 5% as posing little threat and attrition greater than 20% as posing a potentially serious threat to the results’ validity [38].
Additionally, the certainty assessment for all outcomes was assessed by the first author and checked and challenged by the second author. Discrepancies were discussed, clarified, and agreed upon together. Certainty assessment was completed using the Grading of Recommendations Assessment, Development, and Evaluation (GRADE) framework [39], used for rating the quality of evidence in systematic reviews. The risk of bias due to missing results (publication bias) was assessed as part of the GRADE framework [39].
3. Results
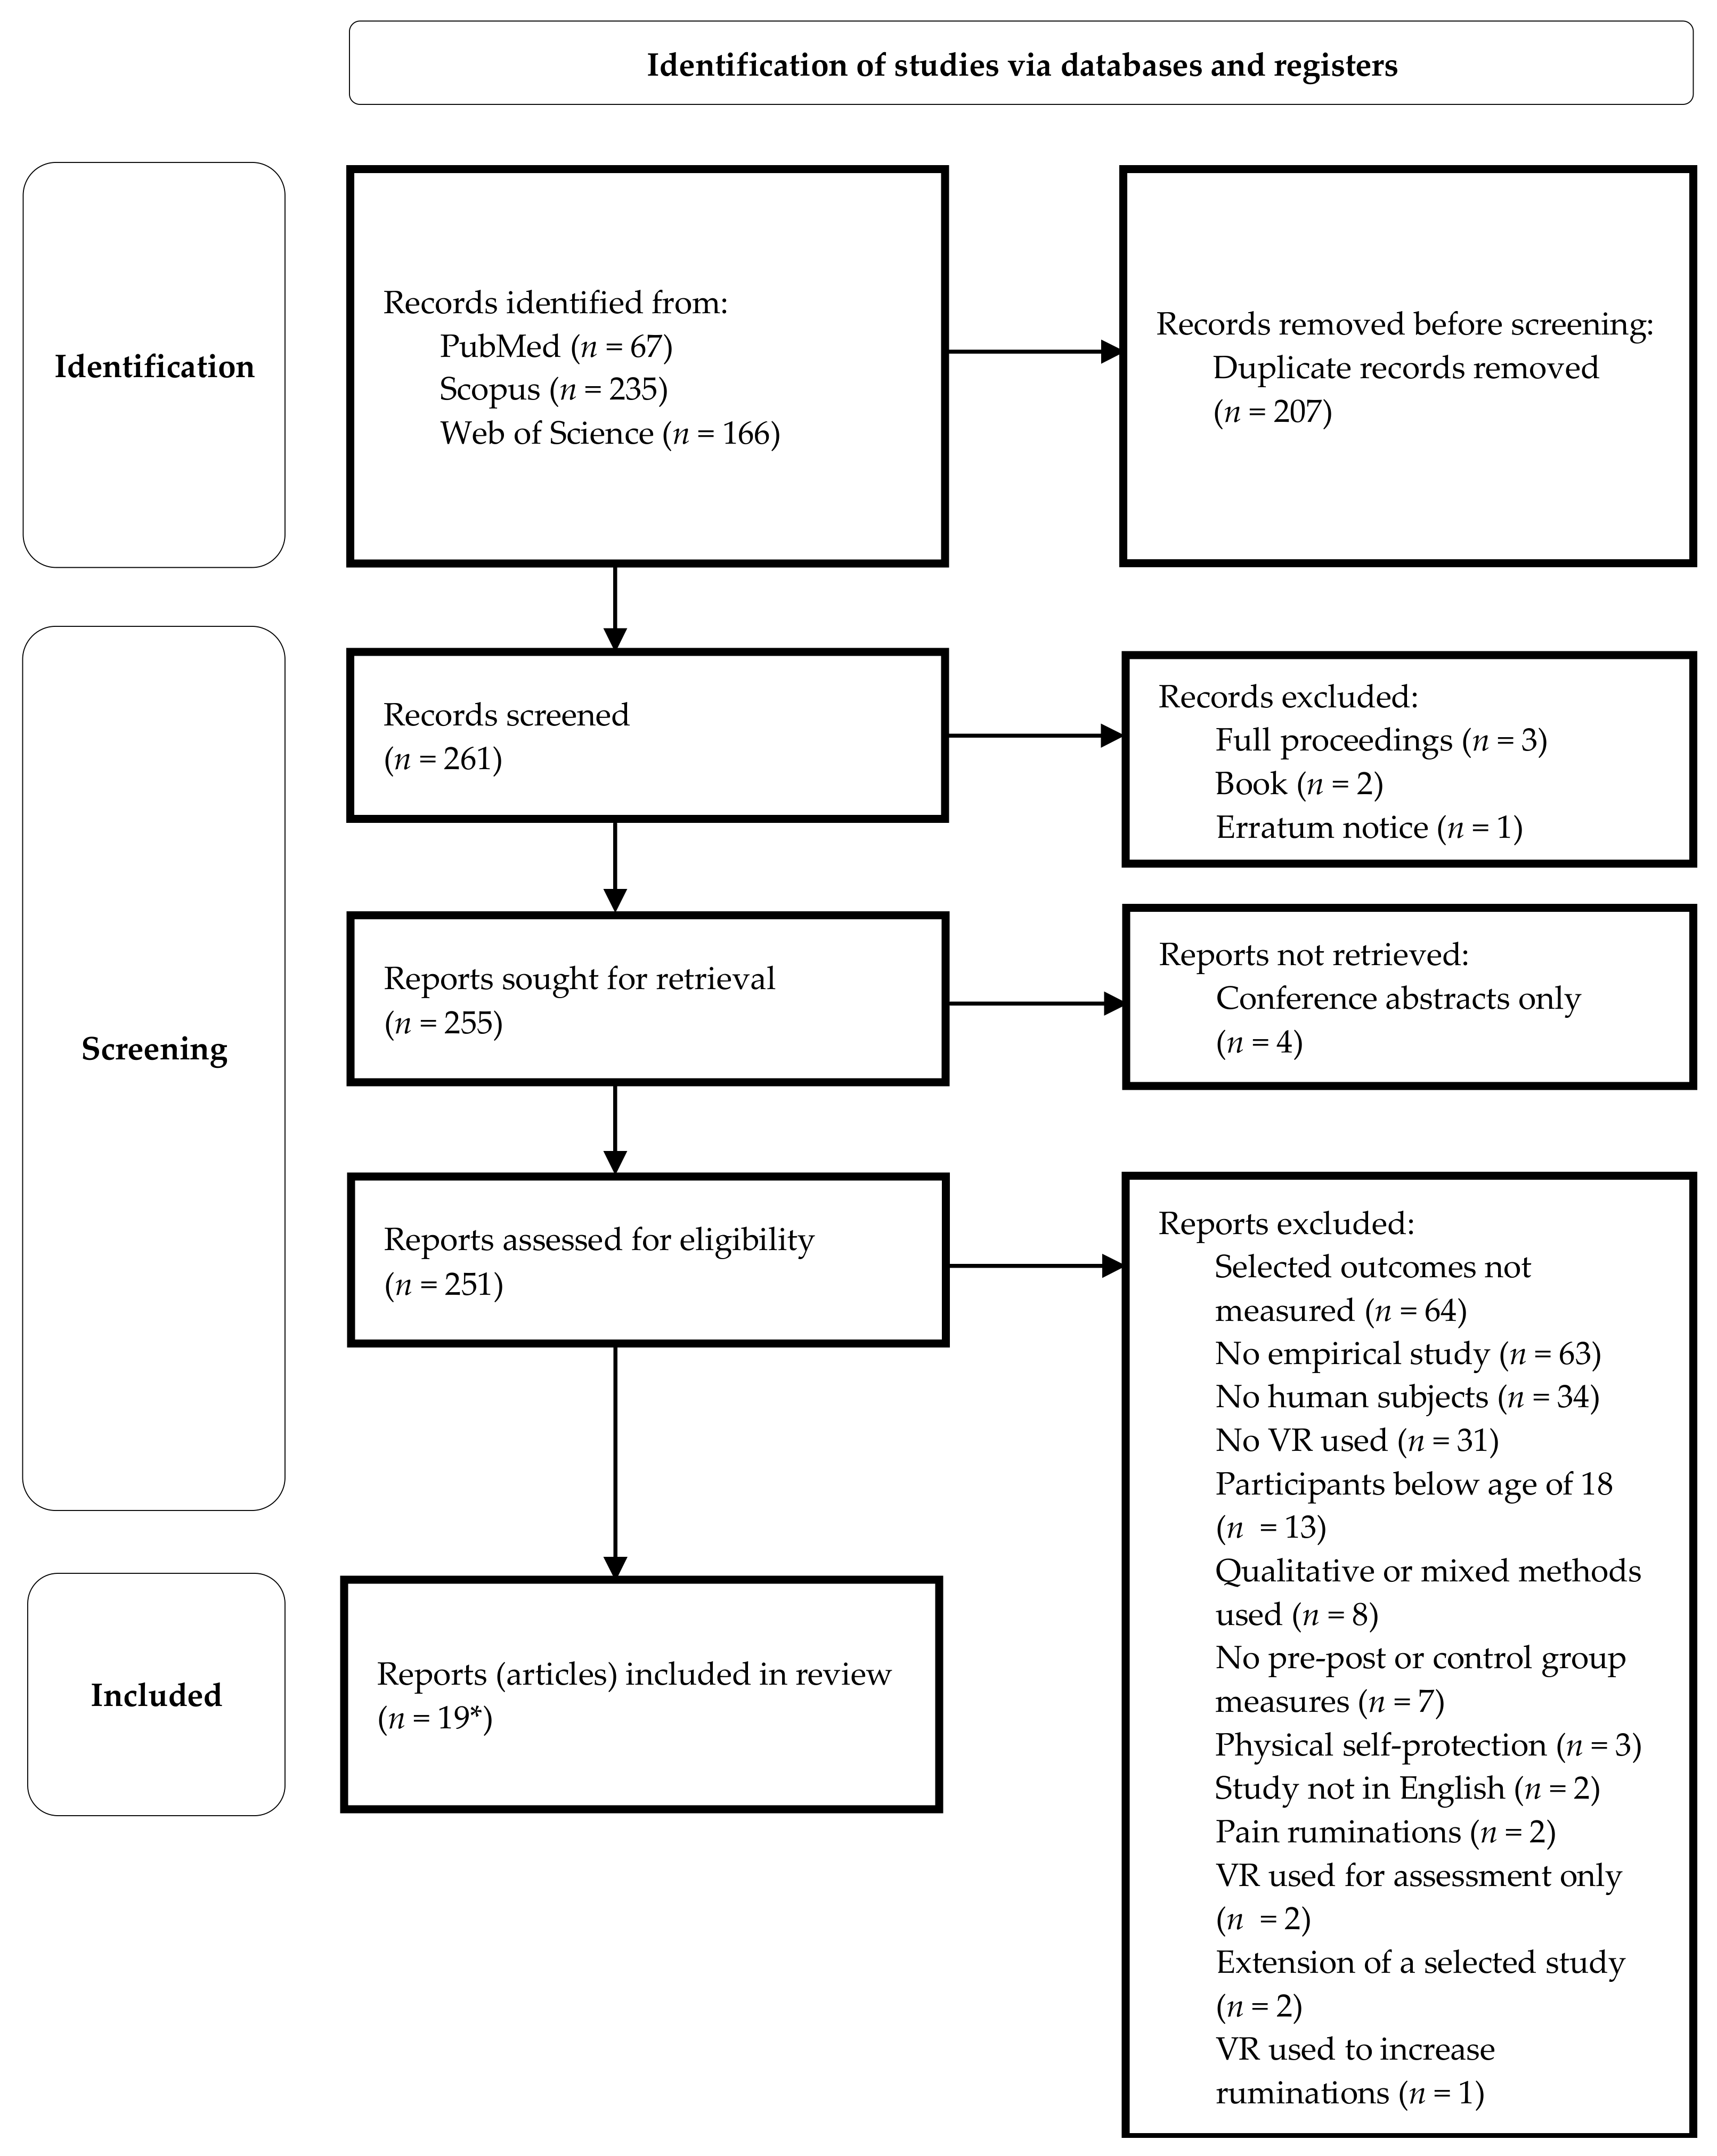
A total of 468 records were identified through our database searches. The exact search breakdown can be seen in Table 1. Selection criteria were met by 19 articles, of which two articles related to seemingly identical research [40,41]; hence, the final selection list is composed of 18 articles. However, one study [42] included different measurements of relevant variables at different time points: one measurement with one particular psychometric tool (MSCS; [43]) was taken at time points T1 and T4, and a different measurement using a different psychometric tool (SOFI; [44]) was taken at time points T2 and T3. In this case, we would treat them as two separate studies, making the final total of selected studies 19. See Table 2 for the complete list of studies in alphabetical order and the structured summaries for each variable.
Table 1.
Breakdown of search records according to topic and databases applied.
Table 2.
Final summary of selected studies.
The most common reasons for reports not to be selected for this review were: selected variables not measured; no empirical study; no human subjects involved; VR not used; participants below the age of 18; and no pre/post and/or control group intervention measures of selected outcomes. For details, see the PRISMA flow diagram in Figure 1.
Figure 1.
PRISMA 2020 flow diagram of selected reports. * Two articles on the final list had been identified as reports of the same research; therefore, the final number of selected reports is 18.
In terms of study designs, we looked at the studies from the perspective of our outcomes (self-compassion, self-protection, and self-criticism). If a study had a control group, but this control group was irrelevant to the outcome of our interest, we would treat it as a within-group study rather than a between-group study. Of the 19 selected studies, two were randomized controlled trials, 16 were longitudinal studies, and one was a case study. Of the 16 longitudinal studies, seven were randomized between-group studies, two were non-randomized between-group studies, one was a between-group study with randomization not specified, and six were within-group studies (see Table 2 for details).
Overall, in terms of bias, each of the included relevant studies shows between none and two low risks of bias, three to five high risks of bias, and one to three unclear risks of bias out of the six predefined categories of bias [37]. For self-criticism, three to five high risks of bias and one to three unclear risks of bias were identified amongst the respective studies. For the self-compassion domain, three to five high risks of bias and one to three unclear risks of bias were identified among the respective studies. Lastly, for the self-protection domain, three to four high risks of bias and one to two unclear risks of bias were identified amongst the respective studies. This indicates that some concern is certainly needed when interpreting results across each of the domains of this review (see Appendix B for details and Table 3 for a summary). In terms of certainty assessment, all three domains were rated as very low, mainly due to the dominance of small studies that have been conducted to date and the large variability amongst them (see Table 4 for details).
Table 3.
Risk of bias summary for the selected studies.
Table 4.
GRADE certainty assessment for measured outcomes.
Across all the studies, the overall number of participants taking part was 672, with 351 in the intervention and 321 in the control groups (these counts are only estimations as two studies did not provide the exact ratio between the intervention and the control group; [11,55]). Since some participants took part in two studies [42], we included them twice in our total count. Three studies [47,48,53] had a control group that was not relevant for measuring our outcomes; these participants were not included in the abovementioned counts. If a study had more than two groups, the group that received VR intervention was considered the intervention group, and the remaining groups were considered the control group. See Table 2 for details.
The final synthesis was grouped around each of the outcome domains: self-criticism, self-compassion, and self-protection. If a study measured two outcomes, e.g., self-criticism and self-compassion, the respective variables (as shown in Table 2) were synthesized for each outcome separately.
3.1. Self-Criticism
This systematic review identified six studies within the self-criticism outcome domain, with three of them measuring the impact of VR on self-criticism [8,35,50] and three on ruminations [47,48,54]. Of the six studies, four were published from 2016 onwards. Chronologically, the first study for this outcome looked at the application of VR to post-event processing in people with social anxiety disorder [54]. All six studies showed a decrease in self-criticism post-intervention; in five cases [8,35,47,48,54], this decrease was statistically significant. Additionally, four studies reported large effect sizes for self-criticism and ruminations decrease [8,35,47,50]; one study reported a large effect for ruminations decrease as part of a larger treatment group [54]; and one study did not report an effect size for ruminations at all [48].
All six studies used immersive head-mounted displays and interactive scenarios, and VR comprised the central part of all interventions. Four studies [8,35,47,48] used psychoeducation as part of the intervention, and three studies [8,35,50] applied embodied experience. On average, they had 24 (between 15 and 32) participants in the intervention groups. Four studies used clinical populations; in the remaining two cases [35,50], the populations were non-clinical. Three studies [8,47,48] did not have a control group, and one study [35] applied VR in the control group as well. The data on the number of completed VR sessions and overall durations spent in VR is not complete; from those reported, participants received between one and eight VR sessions with an overall VR exposure of 9.5 to 90 min. The scenarios involved either comforting a virtual child, embodying a patient with a severe anxiety disorder, or introducing oneself to or speaking to a virtual audience varying in size and level of disruption.
Results suggest that using immersive and interactive VR technology could be effective in targeting self-criticism. Additionally, psychoeducation may possibly play its part too as it was part of the intervention in four out of six studies; however, there is not enough evidence to either support or refute this observation. All studies with clinical samples showed significant results. All studies targeting the ruminations of participants suffering from social anxiety disorder (through virtual anxiety-provoking situations) reported significant reductions in ruminations. Where reported, studies with significant results delivered a minimum of three VR sessions with an overall VR exposure per participant of 24 min.
3.2. Self-Compassion
In terms of the outcome of self-compassion, nine studies were identified; eight of them measured self-compassion [8,35,42,45,49,50,51,53]; and one measured positive qualities towards self as a measure of self-compassion [42]. All studies, except for one [35], were published from 2016 onwards. Chronologically, the first study in this outcome domain applied VR embodiment experience to decrease self-criticism through self-compassion in women high in self-criticism [35]. Overall, of the nine studies, seven showed an increase in self-compassion [8,35,42,45,49,53]; for five of them, this increase was significant [8,35,45,49,53]. Of the remaining two studies, one showed a non-significant decrease in self-compassion [50] and one showed a non-significant change in self-compassion without reporting the direction of the effect [51]. Five studies [8,35,42,49] reported large effect sizes for self-compassion; one study [50] reported no effect for self-compassion; and three studies [45,51,53] did not report any effect size.
Of the nine studies in this domain, six [8,35,42,45,50] used immersive and interactive technology; two [49,51] used immersive head-mounted displays with non-interactive scenarios; and one [53] employed a non-immersive laptop with interactive content. In two studies, however, VR did not constitute a central part of the intervention [42,53]; in fact, it could be said that VR was marginal compared with the much larger proportion of other intervention parts. Embodied experience was part of the VR intervention in six studies [8,35,42,45,50]. Participants attended between one and six sessions, with all but three studies comprising only one VR session. Where reported, participants engaged in a minimum of 4 to 46 min of VR experience. The samples were, except for two studies [8,51], non-clinical, with an average intervention group size of 19 (between eight and 70). Three studies [8,51,53] had no control group, and two studies [35,45] had their control group also exposed to VR. Scenarios varied from an astronaut’s mission to the moon, observing people, avatars, objects, or nature, to embodying a child or an adult, healthy or with a mental condition.
Results suggest that VR could be effective in increasing self-compassion; looking at studies with significant results, this could be true even after just one 10 min, potentially even shorter, VR session. However, as all of the samples except for two were non-clinical, this can be concluded only for non-clinical adult samples. Technology, scenarios, and the structure of interventions varied across the studies.
3.3. Self-Protection
For this outcome domain, seven studies were identified; all of them measured the impact of VR on assertiveness [11,15,40,41,52,55,56,57]. All the studies were published before 2016. Chronologically, the first study in this outcome domain applied VR to treat body image disturbances in overweight women [11]. All seven studies showed a positive impact of VR on assertiveness; five studies [11,15,40,41,52,55] showed significant improvements; one study [57] fully reported only one measure, and it showed significant improvement for assertive behavior; and one study [56] did not report any inferential statistics. In terms of effect sizes, one study [57] reported a large effect for one of their assertiveness measures but did not report an effect for their second assertiveness measure; one study [40,41] reported a small and medium interaction effect between VR and CBT groups for their two assertiveness measures; another study [52] reported a large effect of time and a medium interaction effect between their VR and non-VR training groups; the remaining four studies did not report any effect sizes.
All seven studies employed interactive scenarios; however, only three of them [11,52,55] used head-mounted displays; the rest used personal computers, although in two cases [15,57] together with 3D glasses and headphones. In all studies, VR was a central part of the intervention. All participants attended between seven and 16 sessions, with each receiving approximately 220 to 480 min of VR experience in total; in one study [52] this information was not provided. VR was used only in intervention groups, which consisted solely of clinical samples averaging 13 participants (between one and 32). All studies but one [15] had a control group, and one study [57] was a case study of one patient. Scenarios included daily social situations and exposure to challenging stimuli.
Results suggest that VR could be effective in increasing self-protection/assertiveness, specifically when using VR technology with interactive scenarios that elicit challenging emotions in different virtual situations. However, based on this systematic review, this can be concluded only for clinical populations. Where reported, studies with significant results show a minimum of seven VR sessions with an overall VR exposure per participant of 220 min.
3.4. Adverse Effects
In addition to the analysis above, we also screened the studies in this review for any reports of adverse side effects as a result of taking part in VR, also known as cybersickness [70]. One study [51] reported adverse side effects (nausea and dizziness) in two participants; however, not necessarily attributable to VR intervention. Three studies [11,52,55] reported no cybersickness in any of their participants. The remaining studies did not address VR-related adverse side effects in their studies.
4. Discussion
This systematic review looked at the effectiveness of VR in decreasing self-criticism and increasing self-compassion and self-protection. Positive results have been identified across all three domains, adding to the encouragement of the application of VR for mental health purposes [5,6]. However, there are apparent differences (study design, number and duration of VR exposure, technology, scenarios, etc.) in the reviewed studies, and careful considerations need to be taken into account when interpreting these findings and offering any conclusions.
For decreasing self-criticism, immersive VR technology with interactive scenarios shows positive results after a relatively short-term intervention, specifically for adult clinical samples. This, or any other broader judgment, is however very limited, considering there were only six studies identified for this domain. It appears that this area has so far not received enough attention, considering the first study appeared in 2011. In addition, if there is a significant impact on clinical samples, it would be worth testing efficiency in non-clinical samples as well because the impact could be potentially even higher, as clinical samples may struggle more to overcome self-critical thoughts [71].
A brief VR intervention could be effective for increasing self-compassion in adult non-clinical samples. This conclusion comes from reviewing nine studies. These studies, however, varied greatly, indicating that more research is needed to better understand which features of VR intervention make it effective. An area to closely look at might be embodied experience, as already pointed out by Falconer et al. [35]. It seems promising that some of the studies with only one VR exposure made significant changes to self-compassion. If further elaborated, there is a big potential for improving the well-being of a greater non-clinical population. In addition, we suggest testing its potential with clinical samples as well.
For increasing self-protection/assertiveness, VR with interactive scenarios seems to have a positive effect, specifically in adult clinical samples. This, or any other conclusion, is again very limited, considering there were only seven studies identified for this domain. What stands out for this domain is that more repetitions and longer overall VR exposure took place compared with the other two domains. However, it is unclear whether fewer repetitions and a shorter overall exposure would have a different effect. With only seven studies to date, this area of research seems to have received very little attention since its onset in 2001, with the latest study to date published in 2014. It would be worth testing the impact of just one, or a shorter, VR exposure to develop more cost-effective interactions for increasing self-protection.
Interventions varied greatly across all the studies, and it remains unclear what is/are the key component(s) of effective VR interventions. Looking at the technology employed, the majority of the studies used immersive HMD, with only a few using a non-immersive computer screen. As none of the non-immersive studies provide information on the size of the effect, it is hard to judge what impact computer immersion plays on intervention effectiveness. Similarly, little can be concluded about interactivity, as only two studies provided non-interactive, passive content; the vast majority of the studies had their participants actively involved in the process of intervention. Additionally, the actual VR scenarios varied considerably in terms of content, number of exposures (repetition), and time spent in VR. This follows the observation of Rizzo and Koenig [5] that the identification of active ingredients in the use of clinical VR is still very much needed.
Another area of concern is the sample size. Small sample sizes can make statistical significance and effect size results unreliable. Field et al. [72] suggest a sample size of approximately 30 as a threshold for a reliable real-world population estimate. In our review, in all three domains, the average sample size was below this number, making any generalizations difficult. Additionally, more than a third of the studies were conducted on students, further adding to this issue. Larger sample studies with various population types are needed.
Furthermore, a great variety of self-report measures have been used across the selected studies, making a reliable synthesis difficult. Additionally, many of the selected studies show an overreliance on self-reported measures. Self-rated scales inevitably produce errors [72] and are confounded by bias, as reported by some of the authors in this review too (e.g., [48]). Therefore, the interpretation of results needs to take this point into account. Wider employment of other means of measurement (e.g., behavioral, vocal, or physiological markers) could prove beneficial for future research in this area. Additionally, reporting adverse effects, even with zero occurrence, should become more common for VR research, as it is unclear whether they appear only very rarely or they simply go unreported.
The results of this review predominantly focus on short-term change, with longer-term effects unknown. With only three studies employing follow-up measurements, the retention of positive changes beyond immediately after the intervention needs further research in order to establish the effectiveness of VR for our domains.
Since self-compassion and self-protection were identified as the antidotes to self-criticism within the latest research findings of Emotion-focused Therapy [20], we propose developing a novel VR intervention to decrease levels of self-criticism through evoking self-compassion and self-protection based on the two-chair technique [73,74].
Consistent with the wider affordability of VR as of 2016 [3], the number of studies looking at self-compassion and self-criticism has significantly grown this year. However, this is not the case for self-protection/assertiveness, as the latest study in this domain was published in 2014. This highlights a large research gap and an imminent need to expand on this area, especially if published studies suggest an existing potential. In fact, considering the low overall number of studies in this review, this statement can be applied to all three domains. More studies, especially randomized controlled trials (there were only two in this review), are needed to investigate the effect of VR on self-criticism, self-compassion and self-protection. Future trials should most importantly include larger samples, both clinical and non-clinical, and look at longer-term effects through follow-up periods; additionally, VR interventions need to be replicable and clearly embedded in theory to stimulate wider research; and finally, since age (e.g., [75]) and gender (e.g., [76]) may play a part in the way VR experience is processed, these should be investigated too.
5. Limitations
This systematic review has been conducted by only two reviewers. There is always a possibility that some studies may have been missed during the process. Limited published literature limits broader conclusions. It is difficult to estimate how many studies containing non-significant results may have gone unpublished or were published in different languages except for English. Not all studies reported all details, making a sound judgment difficult, and not all of the contacted authors responded to our questions to specify their research study. The selected studies varied greatly, leaving the final synthesis open to doubt. Finally, this study was not pre-registered. For future systematic reviews looking at this research area, we suggest more reviewers be involved and pre-register the protocol in order to mitigate any additional bias that may have arisen from these limitations.
6. Conclusions
A systematic review, guided by the PRISMA 2020 principles [36], has been conducted in order to provide an overview of the effectiveness of VR interventions aiming to increase self-compassion and self-protection and decrease self-criticism. In all three domains, positive results have been identified, supporting the notion that VR will become more established in mental health practice in the near future. However, any generalizations have to be inferred very carefully because the number of studies identified in this review is limited and they vary in design and application. Larger sample randomized controlled trials with a longer term follow-up period are required in order to establish robust evidence for VR interventions for all three outcome measures.
Author Contributions
J.H. and T.Ž. designed the research project. T.Ž. collected data. T.Ž. and J.H. conducted the systematic review. T.Ž. wrote the first draft of the article. Both authors, J.H. and T.Ž., interpreted the results, revised the manuscript and read and approved the final manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
The writing of this work was supported by the Vedecká grantová agentúra VEGA under Grant 1/0075/19.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Search syntax for selected databases.
Appendix B
Table A2.
Risk of bias analysis for the selected studies.
References
- Wiederhold, B.K. Lessons Learned as We Begin the Third Decade of Virtual Reality. Cyberpsychol. Behav. Soc. Netw. 2016, 19, 577–578. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wiederhold, B.K.; Riva, G. Virtual Reality Therapy: Emerging Topics and Future Challenges. Cyberpsychol. Behav. Soc. Netw. 2019, 22, 3–6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riva, G. Virtual Reality in Clinical Psychology. In Comprehensive Clinical Psychology; Elsevier: Amsterdam, The Netherlands, 2022; pp. 91–105. [Google Scholar] [CrossRef] [Scilit]
- Rizzo, A.A.; Buckwalter, J.G.; Neumann, U. Virtual Reality and Cognitive Rehabilitation: A Brief Review of the Future. J. Head Trauma Rehabil. 1997, 12, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Rizzo, A.; Koenig, S.T. Is clinical virtual reality ready for primetime? Neuropsychology 2017, 31, 877–899. [Google Scholar] [CrossRef] [Scilit]
- Freeman, D.; Reeve, S.; Robinson, A.; Ehlers, A.; Clark, D.; Spanlang, B.; Slater, M. Virtual reality in the assessment, understanding, and treatment of mental health disorders. Psychol. Med. 2017, 47, 2393–2400. [Google Scholar] [CrossRef] [Scilit]
- Cruz-Neira, C.; Sandin, D.J.; DeFanti, T.A. Surround-screen projection-based virtual reality: The design and implementation of the CAVE. In Proceedings of the SIGGRAPH ’93 20th Annual Conference on Computer Graphics and Interactive Techniques, Anaheim, CA, USA, 2–6 August 1993; Whitton, M.C., Ed.; Association for Computing Machinery: New York, NY, USA, 1993; pp. 135–142. [Google Scholar] [CrossRef] [Scilit]
- Falconer, C.; Rovira, A.; King, J.; Gilbert, P.; Antley, A.; Fearon, R.; Ralph, N.; Slater, M.; Brewin, C.R. Embodying self-compassion within virtual reality and its effects on patients with depression. BJPsych Open 2016, 2, 74–80. [Google Scholar] [CrossRef] [Scilit]
- Freeman, D.; Haselton, P.; Freeman, J.; Spanlang, B.; Kishore, S.; Albery, E.; Denne, M.; Brown, P.; Slater, M.; Nickless, A. Automated psychological therapy using immersive virtual reality for treatment of fear of heights: A single-blind, parallel-group, randomised controlled trial. Lancet Psychiatry 2018, 5, 625–632. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eshuis, L.; van Gelderen, M.; van Zuiden, M.; Nijdam, M.; Vermetten, E.; Olff, M.; Bakker, A. Efficacy of immersive PTSD treatments: A systematic review of virtual and augmented reality exposure therapy and a meta-analysis of virtual reality exposure therapy. J. Psychiatr. Res. 2020, 143, 516–527. [Google Scholar] [CrossRef] [Scilit]
- Riva, G.; Bacchetta, M.; Baruffi, M.; Molinari, E. Virtual Reality–Based Multidimensional Therapy for the Treatment of Body Image Disturbances in Obesity: A Controlled Study. CyberPsychol. Behav. 2001, 4, 511–526. [Google Scholar] [CrossRef] [Scilit]
- Ahmadpour, N.; Randall, H.; Choksi, H.; Gao, A.; Vaughan, C.; Poronnik, P. Virtual Reality interventions for acute and chronic pain management. Int. J. Biochem. Cell Biol. 2019, 114, 105568. [Google Scholar] [CrossRef] [Scilit]
- Qazi, S.; Raza, K. Towards a VIREAL Platform: Virtual Reality in Cognitive and Behavioural Training for Autistic Individuals. In Advanced Computational Intelligence Techniques for Virtual Reality in Healthcare; Gupta, D., Hassanien, A.E., Khanna, A., Eds.; Springer: Cham, Switzerland, 2020; pp. 25–47. [Google Scholar]
- Klein Tuente, S.; Bogaerts, S.; Bulten, E.; Vos, M.K.-D.; Vos, M.; Bokern, H.; Van Ijzendoorn, S.; Geraets, C.N.W.; Veling, W. Virtual Reality Aggression Prevention Therapy (VRAPT) versus Waiting List Control for Forensic Psychiatric Inpatients: A Multicenter Randomized Controlled Trial. J. Clin. Med. 2020, 9, 2258. [Google Scholar] [CrossRef] [Scilit]
- Rus-Calafell, M.; Gutiérrez-Maldonado, J.; Ribas-Sabaté, J. A virtual reality-integrated program for improving social skills in patients with schizophrenia: A pilot study. J. Behav. Ther. Exp. Psychiatry 2014, 45, 81–89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Depression and Other Common Mental Disorders: Global Health Estimates. 2017. Available online: https://www.who.int/publications/i/item/depression-global-health-estimates (accessed on 7 October 2021).
- Tiller, J.W.G. Depression and anxiety. Med. J. Aust. 2013, 199, S28–S31. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barcaccia, B.; Salvati, M.; Pallini, S.; Baiocco, R.; Curcio, G.; Mancini, F.; Vecchio, G.M. Interpersonal Forgiveness and Adolescent Depression. The Mediational Role of Self-reassurance and Self-criticism. J. Child Fam. Stud. 2020, 29, 462–470. [Google Scholar] [CrossRef] [Scilit]
- Shahar, G. Erosion: The Psychopathology of Self-Criticism; Oxford University Press: Oxford, UK, 2015. [Google Scholar]
- Timulak, L.; Pascual-Leone, A. New Developments for Case Conceptualization in Emotion-Focused Therapy. Clin. Psychol. Psychother. 2015, 22, 619–636. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greenberg, L. Emotion–focused therapy. Clin. Psychol. Psychother. Int. J. Theory Pract. 2004, 11, 3–16. [Google Scholar] [CrossRef] [Scilit]
- Shahar, B.; Bar-Kalifa, E.; Alon, E. Emotion-focused therapy for social anxiety disorder: Results from a multiple-baseline study. J. Consult. Clin. Psychol. 2017, 85, 238–249. [Google Scholar] [CrossRef] [Scilit]
- Shahar, B.; Carlin, E.R.; Engle, D.E.; Hegde, J.; Szepsenwol, O.; Arkowitz, H. A Pilot Investigation of Emotion-Focused Two-Chair Dialogue Intervention for Self-Criticism. Clin. Psychol. Psychother. 2012, 19, 496–507. [Google Scholar] [CrossRef] [Scilit]
- Thompson, S.; Girz, L. Overcoming shame and aloneness: Emotion-focused group therapy for self-criticism. Pers.-Cent. Exp. Psychother. 2020, 19, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Timulak, L.; Keogh, D.; Chigwedere, C.; Wilson, C.; Ward, F.; Hevey, D.; Griffin, P.; Jacobs, L.; Hughes, S.; Vaughan, C.; et al. A comparison of emotion-focused therapy and cognitive-behavioral therapy in the treatment of generalized anxiety disorder: Results of a feasibility randomized controlled trial. Psychotherapy 2022, 59, 84–95. [Google Scholar] [CrossRef] [Scilit]
- Neff, K.D.; Tirch, D. Self-compassion and ACT. In Mindfulness, Acceptance, and Positive Psychology: The Seven Foundations of Well-Being; Kashdan, T.B., Ciarrochi, J., Eds.; Context Press: Oakland, CA, USA, 2013; pp. 78–106. [Google Scholar]
- Lazarus, R.S. Progress on a cognitive-motivational-relational theory of emotion. Am. Psychol. 1991, 46, 819–834. [Google Scholar] [CrossRef]
- Goetz, J.L.; Keltner, D.; Simon-Thomas, E. Compassion: An evolutionary analysis and empirical review. Psychol. Bull. 2010, 136, 351–374. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neff, K. Self-Compassion: An Alternative Conceptualization of a Healthy Attitude Toward Oneself. Self Identity 2003, 2, 85–101. [Google Scholar] [CrossRef] [Scilit]
- Gilbert, P. An Introduction to Compassion Focused Therapy in Cognitive Behavior Therapy. Int. J. Cogn. Ther. 2010, 3, 97–112. [Google Scholar] [CrossRef] [Scilit]
- Strauss, C.; Taylor, B.L.; Gu, J.; Kuyken, W.; Baer, R.; Jones, F.; Cavanagh, K. What is compassion and how can we measure it? A review of definitions and measures. Clin. Psychol. Rev. 2016, 47, 15–27. [Google Scholar] [CrossRef] [Scilit]
- Pascual-Leone, A.; Greenberg, L.S. Emotional processing in experiential therapy: Why “the only way out is through”. J. Consult. Clin. Psychol. 2007, 75, 875–887. [Google Scholar] [CrossRef] [Scilit]
- Neff, K. Fierce Self-Compassion: How Women Can Harness Kindness to Speak Up, Claim Their Power, and Thrive; Penguin Life: London, UK, 2021. [Google Scholar]
- Neff, K.D.; Dahm, K.A. Self-compassion: What it is, what it does, and how it relates to mindfulness. In Handbook of Mindfulness and Self-Regulation; Ostafin, B., Robinson, M., Meier, B., Eds.; Springer: New York, NY, USA, 2015; pp. 121–137. [Google Scholar]
- Falconer, C.; Slater, M.; Rovira, A.; King, J.; Gilbert, P.; Antley, A.; Brewin, C.R. Embodying Compassion: A Virtual Reality Paradigm for Overcoming Excessive Self-Criticism. PLoS ONE 2014, 9, e111933. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. Syst. Rev. 2021, 89, 105906. [Google Scholar]
- Higgins, J.P.T.; Altman, D.G.; Gøtzsche, P.C.; Jüni, P.; Moher, D.; Oxman, A.D.; Savović, J.; Schulz, K.F.; Weeks, L.; Sterne, J.A.C.; et al. The Cochrane Collaboration’s tool for assessing risk of bias in randomised trials. BMJ 2011, 343, d5928. [Google Scholar] [CrossRef] [Scilit]
- Schulz, K.F.; Grimes, D.A. Sample size slippages in randomised trials: Exclusions and the lost and wayward. Lancet 2002, 359, 781–785. [Google Scholar] [CrossRef] [Scilit]
- Ryan, R.; Hill, S. How to GRADE the Quality of the Evidence; Cochrane Consumers and Communication Group: London, UK, 2016. [Google Scholar] [CrossRef] [Scilit]
- Klinger, E.; Bouchard, S.; Légeron, P.; Roy, S.; Lauer, F.; Chemin, I.; Nugues, P. Virtual Reality Therapy Versus Cognitive Behavior Therapy for Social Phobia: A Preliminary Controlled Study. Cyberpsychol. Behav. 2005, 8, 76–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Klinger, E.; Légeron, P.; Roy, S.; Chemin, I.; Lauer, F.; Nugues, P. Virtual reality exposure in the treatment of social phobia. In Cybertherapy: Internet and Virtual Reality as Assessment and Rehabilitation Tools for Clinical Psychology and Neuroscience; Riva, G., Botella, C., Légeron, P., Optale, G., Eds.; IOS Press: Amsterdam, The Netherlands, 2004; pp. 91–119. [Google Scholar]
- Cebolla, A.; Herrero, R.; Ventura, S.; Miragall, M.; Bellosta-Batalla, M.; Llorens, R.; Baños, R.M. Putting Oneself in the Body of Others: A Pilot Study on the Efficacy of an Embodied Virtual Reality System to Generate Self-Compassion. Front. Psychol. 2019, 10, 1521. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cook-Cottone, C.P.; Guyker, W.M. The Development and Validation of the Mindful Self-Care Scale (MSCS): An Assessment of Practices that Support Positive Embodiment. Mindfulness 2017, 9, 161–175. [Google Scholar] [CrossRef] [Scilit]
- Kraus, S.; Sears, S. Measuring the Immeasurables: Development and Initial Validation of the Self-Other Four Immeasurables (SOFI) Scale Based on Buddhist Teachings on Loving Kindness, Compassion, Joy, and Equanimity. Soc. Indic. Res. 2009, 92, 169–181. [Google Scholar] [CrossRef] [Scilit]
- Ascone, L.; Ney, K.; Mostajeran, F.; Steinicke, F.; Moritz, S.; Gallinat, J.; Kühn, S. Virtual Reality for Individuals with Occasional Paranoid Thoughts. In Proceedings of the CHI 2020: Extended Abstracts of the 2020 CHI Conference on Human Factors in Computing Systems, Honolulu, HI, USA, 25–30 April 2020. [Google Scholar] [CrossRef] [Scilit]
- Ascone, L.; Sundag, J.; Schlier, B.; Lincoln, T.M. Feasibility and Effects of a Brief Compassion-Focused Imagery Intervention in Psychotic Patients with Paranoid Ideation: A Randomized Experimental Pilot Study. Clin. Psychol. Psychother. 2017, 24, 348–358. [Google Scholar] [CrossRef] [Scilit]
- Hur, J.-W.; Shin, H.; Jung, D.; Lee, H.-J.; Lee, S.; Kim, G.J.; Cho, C.-Y.; Choi, S.; Lee, S.-M.; Cho, C.-H. Virtual Reality–Based Psychotherapy in Social Anxiety Disorder: fMRI Study Using a Self-Referential Task. JMIR Ment. Health 2021, 8, e25731. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.-J.; Lee, S.; Jung, D.; Hur, J.-W.; Lee, H.-J.; Lee, S.; Kim, G.J.; Cho, C.-Y.; Choi, S.; Lee, S.-M.; et al. Effectiveness of a Participatory and Interactive Virtual Reality Intervention in Patients with Social Anxiety Disorder: Longitudinal Questionnaire Study. J. Med. Internet Res. 2020, 22, e23024. [Google Scholar] [CrossRef] [Scilit]
- Modrego-Alarcón, M.; López-Del-Hoyo, Y.; García-Campayo, J.; Pérez-Aranda, A.; Navarro-Gil, M.; Beltrán-Ruiz, M.; Morillo, H.; Delgado-Suarez, I.; Oliván-Arévalo, R.; Montero-Marin, J. Efficacy of a mindfulness-based programme with and without virtual reality support to reduce stress in university students: A randomized controlled trial. Behav. Res. Ther. 2021, 142, 103866. [Google Scholar] [CrossRef] [Scilit]
- Navarrete, J.; Martínez-Sanchis, M.; Bellosta-Batalla, M.; Baños, R.; Cebolla, A.; Herrero, R. Compassionate Embodied Virtual Experience Increases the Adherence to Meditation Practice. Appl. Sci. 2021, 11, 1276. [Google Scholar] [CrossRef] [Scilit]
- O’Gara, G.; Murray, L.; Georgopoulou, S.; Anstiss, T.; Macquarrie, A.; Wheatstone, P.; Bellman, B.; Gilbert, P.; Steed, A.; Wiseman, T. SafeSpace: What Is the Feasibility and Acceptability of a Codesigned Virtual Reality Intervention, Incorporating Compassionate Mind Training, to Support People Undergoing Cancer Treatment in a Clinical Setting? BMJ Open 2022, 12, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Park, K.-M.; Ku, J.; Choi, S.-H.; Jang, H.-J.; Park, J.-Y.; Kim, S.I.; Kim, J.-J. A virtual reality application in role-plays of social skills training for schizophrenia: A randomized, controlled trial. Psychiatry Res. 2011, 189, 166–172. [Google Scholar] [CrossRef] [Scilit]
- Park, J.; Ogle, J.P. How virtual avatar experience interplays with self-concepts: The use of anthropometric 3D body models in the visual stimulation process. Fash. Text. 2021, 8, 28. [Google Scholar] [CrossRef] [Scilit]
- Price, M.; Anderson, P.L. The impact of cognitive behavioral therapy on post event processing among those with social anxiety disorder. Behav. Res. Ther. 2011, 49, 132–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riva, G.; Bacchetta, M.; Baruffi, M.; Molinari, E. Virtual-reality-based multidimensional therapy for the treatment of body image disturbances in binge eating disorders: A preliminary controlled study. IEEE Trans. Inf. Technol. Biomed. 2002, 6, 224–234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roy, S.; Klinger, E.; Légeron, P.; Lauer, F.; Chemin, I.; Nugues, P. Definition of a VR-Based Protocol to Treat Social Phobia. CyberPsychol. Behav. 2003, 6, 411–420. [Google Scholar] [CrossRef] [Scilit]
- Rus-Calafell, M.; Gutiérrez-Maldonado, J.; Ribas-Sabaté, J. Improving social behaviour in schizophrenia patients using an integrated virtual reality programme: A case study. In Annual Review of Cybertherapy and Telemedicine; Wiederhold, B.K., Riva, G., Eds.; IOS Press: Amsterdam, The Netherlands, 2012; Volume 181, pp. 283–286. [Google Scholar] [CrossRef] [Scilit]
- Gambrill, E.D.; Richey, C.A. An assertion inventory for use in assessment and research. Behav. Ther. 1975, 6, 550–561. [Google Scholar] [CrossRef] [Scilit]
- Gilbert, P.; Procter, S. Compassionate mind training for people with high shame and self-criticism: Overview and pilot study of a group therapy approach. Clin. Psychol. Psychother. 2006, 13, 353–379. [Google Scholar] [CrossRef] [Scilit]
- Abbott, M.J.; Rapee, R.M. Post-Event Rumination and Negative Self-Appraisal in Social Phobia Before and After Treatment. J. Abnorm. Psychol. 2004, 113, 136–144. [Google Scholar] [CrossRef] [Scilit]
- Edwards, S.L.; Rapee, R.; Franklin, J.A. Postevent Rumination and Recall Bias for a Social Performance Event in High and Low Socially Anxious Individuals. Cogn. Ther. Res. 2003, 27, 603–617. [Google Scholar] [CrossRef] [Scilit]
- Im, S.Y.; Choi, H.R.; Kwon, S.-M. The Influence of Post-Event Rumination on Social Self-Efficacy & Anticipatory Anxiety. Korean J. Clin. Psychol. 2007, 26, 39–56. [Google Scholar] [CrossRef]
- Rathus, S.A. A 30-item schedule for assessing assertive behavior. Behav. Ther. 1973, 4, 398–406. [Google Scholar] [CrossRef] [Scilit]
- Mellings, T.M.; Alden, L.E. Cognitive processes in social anxiety: The effects of self-focus, rumination and anticipatory processing. Behav. Res. Ther. 2000, 38, 243–257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- André, C.; Légeron, P. La peur des autres: Trac, timidité et phobie sociale; Odile Jacob: Paris, France, 2000. [Google Scholar]
- Falconer, C.J.; King, J.A.; Brewin, C.R. Demonstrating mood repair with a situation-based measure of self-compassion and self-criticism. Psychol. Psychother. Theory Res. Pract. 2015, 88, 351–365. [Google Scholar] [CrossRef] [Scilit]
- Neff, K.D. The Development and Validation of a Scale to Measure Self-Compassion. Self Identity 2003, 2, 223–250. [Google Scholar] [CrossRef] [Scilit]
- Raes, F.; Pommier, E.; Neff, K.D.; Van Gucht, D. Construction and factorial validation of a short form of the Self-Compassion Scale. Clin. Psychol. Psychother. 2010, 18, 250–255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirschner, H.; Kuyken, W.; Wright, K.; Roberts, H.; Brejcha, C.; Karl, A. Soothing Your Heart and Feeling Connected: A New Experimental Paradigm to Study the Benefits of Self-Compassion. Clin. Psychol. Sci. 2019, 7, 545–565. [Google Scholar] [CrossRef] [Scilit]
- Kennedy, R.S.; Stanney, K.M. Postural instability induced by virtual reality exposure: Development of a certification protocol. Int. J. Hum.-Comput. Interact. 1996, 8, 25–47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rector, N.A.; Bagby, R.M.; Segal, Z.V.; Joffe, R.T.; Levitt, A. Self-Criticism and Dependency in Depressed Patients Treated with Cognitive Therapy or Pharmacotherapy. Cogn. Ther. Res. 2000, 24, 571–584. [Google Scholar] [CrossRef] [Scilit]
- Field, A.; Miles, J.; Field, Z. Discovering Statistics Using R; Sage Publications: London, UK, 2012. [Google Scholar]
- Greenberg, L. Emotion-Focused Therapy: Theories of Psychotherapy Series; American Psychological Association: Washington, DC, USA, 2011. [Google Scholar]
- Whelton, W.J.; Greenberg, L.S. Emotion in self-criticism. Personal. Individ. Differ. 2005, 38, 1583–1595. [Google Scholar] [CrossRef] [Scilit]
- Liu, Q.; Wang, Y.; Tang, Q.; Liu, Z. Do You Feel the Same as I Do? Differences in Virtual Reality Technology Experience and Acceptance Between Elderly Adults and College Students. Front. Psychol. 2020, 11, 573673. [Google Scholar] [CrossRef] [Scilit]
- Felnhofer, A.; Kothgassner, O.D.; Beutl, L.; Hlavacs, H.; Kryspin-Exner, I. Is virtual reality made for men only? Exploring gender differences in the sense of presence. In Proceedings of the Conference of the International Society on Presence Research, Philadelphia, PA, USA, 24–26 October 2012; pp. 103–112. [Google Scholar]


Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).