


Abstract
The objective of this study was to investigate the therapeutic effect of Wuqinxi Qigong vs. stretching on single- and dual-task gait, motor symptoms, and quality of life in people with mild and moderate Parkinson’s disease (PD). This single-blind, randomized control trial included 40 participants with idiopathic PD who were randomized into the Wuqinxi Qigong (WQ) group or stretching group. Participants completed 12 weeks (two sessions/week) of intervention. The primary outcomes were gait parameters when performing single-task (comfortable pace) and dual-task (obstacle crossing, serial-3 subtraction and backward digit span) walking, including gait speed, stride length, and double support percentage. The secondary outcomes were ratings from the Movement Disorder Society Unified Parkinson’s Disease Rating Scale (MDS-UPDRS), results of the timed-up-and-go test (TUGT), results of the Mini-Balance Evaluation Systems Test (MiniBESTest), and responses from the 39-item Parkinson’s Disease Questionnaire (PDQ-39). All measures were assessed pre- and post-intervention. The WQ group demonstrated increased gait speed (p = 0.000) during the single task, and increased stride length (p = 0.001, p = 0.021) during the single-task and serial-3 subtraction task. Double support percentage significantly decreased (p = 0.004) in the WQ group during the obstacle crossing task, and also decreased (p = 0.045) in the stretching group during the single-task. TUGT (p = 0.005), MiniBESTest (p = 0.023) and PDQ-39 (p = 0.043) in the WQ group significantly improved, and both groups showed significant improvement in MDS-UPDRS after intervention. Wuqinxi Qigong is an effective method to improve single- and dual-task gait. While both exercises improve motor symptoms, Wuqinxi Qigong results in better mobility, balance and quality of life compared to stretching alone.
1. Introduction
Parkinson’s disease (PD) is a chronic neurodegenerative disorder that afflicts many patients globally. Gait impairment, characterized by short, asymmetric steps and slow speed, is a main motor symptom in patients with PD. As the disease progresses, gait function decrements increase the risk of falls [1]. Locomotor tasks often require acute attention and processing speed [2], and most daily activities depend on the simultaneous functioning of motor and cognitive tasks. Indeed, “normal” behaviors demand continuous integration of neuronal processing and the “dual-task” (DT) of cognitive and motor functioning [3]. However, gait deficits in patients with PD worsened under dual-task conditions and seriously affect walking ability [4,5]. When performing dual-tasks, people with Parkinson’s disease may concentrate on a secondary task (e.g., walking while speaking) and pay less attention to walking [6,7], resulting in reduced walking speed and stride length, increased gait variability, and subsequent increased risk of falling [8].
Although dual-task gait deficits cannot be treated with dopamine drugs [9], targeted motor or cognitive dual-task exercise can improve dual-task gait and balance [10]. Accumulating evidence suggests that the pattern of dual-task training improves gait and postural instability in people with Parkinson’s disease. The current research found that six consecutive weeks of integrated cognitive and gait task training in individuals with PD remarkably increased stride length and cadence [11]. Furthermore, adding cognitive training to a treadmill program alters the effects of training on the magnitude and lateralization of prefrontal lobe activation to reduce fall risk [12]. Preliminary data suggest 12 sessions of cognitive dual-task training (CDTT) reduces time of double support during cognitive dual-tasks; motor dual-task training (MDTT) further decreases gait variability during motor dual-tasks [11]. Notably, these studies combined two different tasks to improve the gait function; however, whether one type of exercise therapy is sufficient to obtain similar results remains unclear.
Traditional Chinese medicinal exercise is a method that integrates body movement with mental focus. Among the traditional Chinese medicinal exercise, Tai Chi and Qigong are the most practiced, and both aid in health and eliminate disease by incorporating body movement, mindful breathing, and cognitive training [13]. In contrast to Tai Chi, Qigong emphasizes standing posture and dynamic movement. Qigong combines position adjustment, breathing exercises and mindfulness practice to activate muscles and tendons [14], which promotes lower limb function and improves dual-task gait associated with cognition [15,16].
Huato, a physician in the Donghan Dynasty of ancient China, first developed the Wuqingxi method of Qigong exercise. It has since been edited by the Chinese Health Qigong Association and adopts the movement of five animals, including tiger, deer, bear, ape and bird [17]. Importantly, Wuqinxi improves health-related parameters in both healthy individuals and patients with chronic disease (i.e., chronic obstructive pulmonary disease and emphysema) [17,18]. Previous studies suggest that Wuqinxi is an effective at-home exercise that can alleviate chronic low back pain by improving the function of lumbosacral multifidus and reduce knee pain by enhancing knee muscle strength [19]; this has been particularly beneficial for elderly patients with knee osteoarthritis [20,21]. These studies demonstrate the effectiveness of Wuqinxi Qigong in helping respiratory, musculoskeletal and cognitive functions. However, the benefits of Wuqinxi Qigong on dual-task gait, balance and other functions remains unknown.
Therefore, we adopted a randomized control trial to compare the influence of Wuqinxi Qigong and stretching on gait, motor symptoms and quality of life in PD. The primary goal was to explore the differential effects of Wuqinxi Qigong versus stretching alone on single- and dual-task gait. The secondary objective was to examine their impact on balance function, mobility, and quality of life for patients with PD.
2. Materials and Methods
2.1. Study Design and Participants
This prospective, single-center, single-blind randomized controlled study compared the effects of Wuqinxi Qigong (WQ) versus stretching for individuals with PD. A total sample of 100 participants was approved by the ethics committee of Shanghai University of Sport and was registered online at the Chinese Clinical Trial Registry (ChiCTR1800016570). Participants were recruited from referrals by the neurology department of University School of Medicine and from the local community. A research assistant contacted participants interested in the study to lower potential expectation bias and confirm eligibility. Inclusion criteria were: (1) aged 60–80 years; (2) Idiopathic Parkinson’s disease according to British brain bank criteria [22]; (3) Hoehn and Yahr (H&Y) stage of 1–3; (4) Mini-Mental State Examination score ≥ 24; (5) ability to walk independently for at least 5 min (walking AIDS were allowed). Exclusion criteria: (1) experience practicing Wuqinxi Qigong; (2) severe cognitive, visual or auditory impairment, or unable to understand instructions and express demands; (3) other diseases such as cardiopulmonary diseases, liver and kidney diseases, tumors, musculoskeletal dysfunction, and any disease that may limit exercise; (4) irregular use of Parkinson’s disease medication. All participants were required to provide signed informed consent prior to baseline assessment. This study complies with the CONSORT guidelines (see Supplemental File).
2.2. Sample Size Calculation and Randomization
This RCT study aimed to determine whether Wuqinxi Qigong is superior to stretching for gait performance. In the absence of preliminary data on the effects of Wuqinxi Qigong and stretching on dual-task walking, we estimated the effect size in power calculations from previous studies that compared different patterns of dual-task gait training [23]. A sample size of 40 was determined after a power calculation utilizing G*Power software (version 3.1.9.3, Düsseldorf, Germany) was performed. This calculation was based on between group differences in primary outcomes (dual-tasking gait performance) between the Wuqinxi Qigong group and stretching group. Applying an effect size of 0.8, a type I error of 0.05, and 70% power, and accounting for a 15% attrition rate, at least 20 participants in one group needed to reach a statistically significant difference in the dual-task gait performance. Eligible participants were randomized to one of the interventions with an allocation of 1:1 through a permuted bloc randomization (STATA V.12.0, Stata Corp, Texas, USA). The random number table was generated by the program data analyst, and handled exclusively by a research staff member who gave it to an assistant in a sealed envelope. The assistant then notified participants of their intervention group. Assessors and investigators were blind to the expected study outcome.
2.3. Interventions
Both the WQ group and stretching group received group-based exercise at the University’s laboratory of sports science, and were asked to abstain from any extra at-home exercises throughout the twelve-week training period. Groups contained eight to ten participants in an effort to provide adequate instruction and attention to each. Two weekly 90-min sessions were conducted for 12 consecutive weeks. All exercise sessions were supervised at the study site. Each session included a 10-min warm-up on breathing and joint exercise, 60 min with Wuqinxi or stretching, 10 min of break intervals and a 10-min cool-down to relax muscle groups. Intensity was calculated by measuring heart rate (polar-team2; Polar Electro Finland) and having participants rate their perceived exertion (RPE). The heart rate at the start and end of the training session was set at 30–39% of the maximum heart rate (HRmax) for age, or at RPE of 6 on Borg scale. The training intensity was equivalent to 60~70% of HRmax, determined by the formula HRmax = 208 − (0.7 × age), or determined by whether participants reaches their limit of fatigue at an RPE of 12. During the first 6 weeks, participants were instructed to perform at a level of exertion that they felt “Light to Moderate” (equivalent to 6–9 on Brog scale) and developed to “Moderate to Strong” and “Strong” (equivalent to 10–12 on Brog scale) after 6 weeks of intervention [24]. All participants wrote their intervention-based activity in an exercise log throughout the trial.
2.3.1. Wuqinxi Qigong Exercise
Wuqinxi Qigong consists of 10 forms: (1) Raising the tiger’s paws, (2) Seizing the prey, (3) Colliding with the antlers, (4) Running like a deer, (5) Rotating the waist like a bear, (6) Swaying like a bear, (7) Lifting the monkey’s paws, (8) Picking fruit, (9) Stretching upward and (10) Flying like a bird (see Figure 1 and Supplemental File) [25]. During the first 2–3 weeks, exercise primarily emphasized learning and practicing two or three of these movements. Participants were instructed to repeat each movement six times and to incorporate natural breathing into the movement routine. Although exercise was progressive, movement pace, pattern and coordination, and joint range of motion were adjusted depending on whether each participant could keep up with the exercise. The instructor gave instructions and demonstrations, requiring participants to count or recite each form of Wuqinxi while practicing, as well as focus on maintaining balance, posture and action consistency.
Figure 1.
Ten forms of Wuqinxi Qigong. (A). Form 1: Raising the tiger’s paws; (B). Form 2: Seizing the prey; (C). Form 3: Colliding with the antlers; (D). Form 4: Running like a deer; (E). Form 5: Rotating the waist like a bear; (F). Form 6: Swaying like a bear; (G). Form 7: Lifting the monkey’s paws; (H). Form 8: Picking fruit; (I). Form 9: Stretching upward; (J). Form 10: Flying like a bird.
2.3.2. Stretching Exercise
Participants in the stretching group were instructed to practice stretching in both sitting and standing positions. Stretching is beneficial for relaxing stiff muscles and increasing joint flexibility. The stretching methods utilized by this group included self-stretching targeted toward upper limb muscles (deltoid, biceps, triceps), low limb muscles (iliopsoas, quadriceps, hamstring, tibialis anterior, gastrocnemius), and trunk muscles (pectoralis major, erector spinae) (see Supplemental File) [26]. Each muscle group was activated three to four times for 30 s each, with a 10 s resting period between each stretch. Participants were guided to breathe naturally and intensify the stretch to mild discomfort.
2.4. Outcome Assessments
All participants received assessments before and after the 12-week intervention. Baseline measurements included age, gender, cognition, body mass index (BMI), duration of disease, Hoehn and Yahr phase and freezing of gait. Participants performed each assessment at the “on” medication phase before and after the intervention. All experimental data were collected by the same trained assessor to ensure reproducibility.
The primary outcomes were gait parameters, measured using a 4.6 m long electronic walkway carpet with embedded pressure sensors (PKMAS walkway, ProtoKinetics, Havertown, PA, USA). Participants completed four types of tasks while walking on walkway: (1) single-task walking (comfortable pace); (2) obstacle crossing (15 cm height); (3) backward digital span; and (4) serial-3 subtraction. Gait parameters included gait speed, stride length and double support percentage during single and dual tasks. To avoid a learning effect, the order of each task changed randomly. Participants walked three consecutive loops on the walkway to minimize within-individual variability [27].
The secondary outcomes were motor symptoms, balance, mobility, and quality of life. Motor symptoms were rated by the Movement Disorder Society Unified Parkinson’s Rating Scale (MDS-UPDRS) [28]. Balance and mobility performance were assessed by Mini-Balance Evaluation Systems Test (MiniBESTest) [29] and Time-Up and Go Test (TUGT) [30]. Mini-Mental State Examination measured cognition [31]. Finally, quality of life was rated using the 39-item Parkinson’s Disease Questionnaire (PDQ-39) [32].
2.5. Statistical Analysis
Statistical analyses were conducted using SPSS V.22.0 software (IBM Corp, New York, NY, USA). The Shapiro-Wilk test determined data normality. Baseline demographics were examined using chi-square tests. Independent t-tests were utilized to analyze group differences. Significant between-group differences were determined using analysis of covariance. Variance homogeneity of data was assessed by Levene’s test. The outcome of the normally distributed data before (Pre) and after 12-week intervention (Post12wk) was analyzed using mixed-design repeated measures ANOVA for between/within-group differences. When an interaction effect was determined, one-way repeated-measures ANOVA was utilized to compare the within-group differences. Bonferroni’s post hoc test was then applied to compare results when main effects were significant. All descriptive statistics are presented as mean and standard deviation; significance level was set at p < 0.05. Intention-to-treat principles were used to address missing data, that is, all individuals initially enrolled in the study. Effect size was calculated using partial eta-squared (η2). The effect size thresholds were small = 0.01, medium = 0.06, large = 0.14 [33].
3. Results
3.1. Participants and Baseline Characteristics
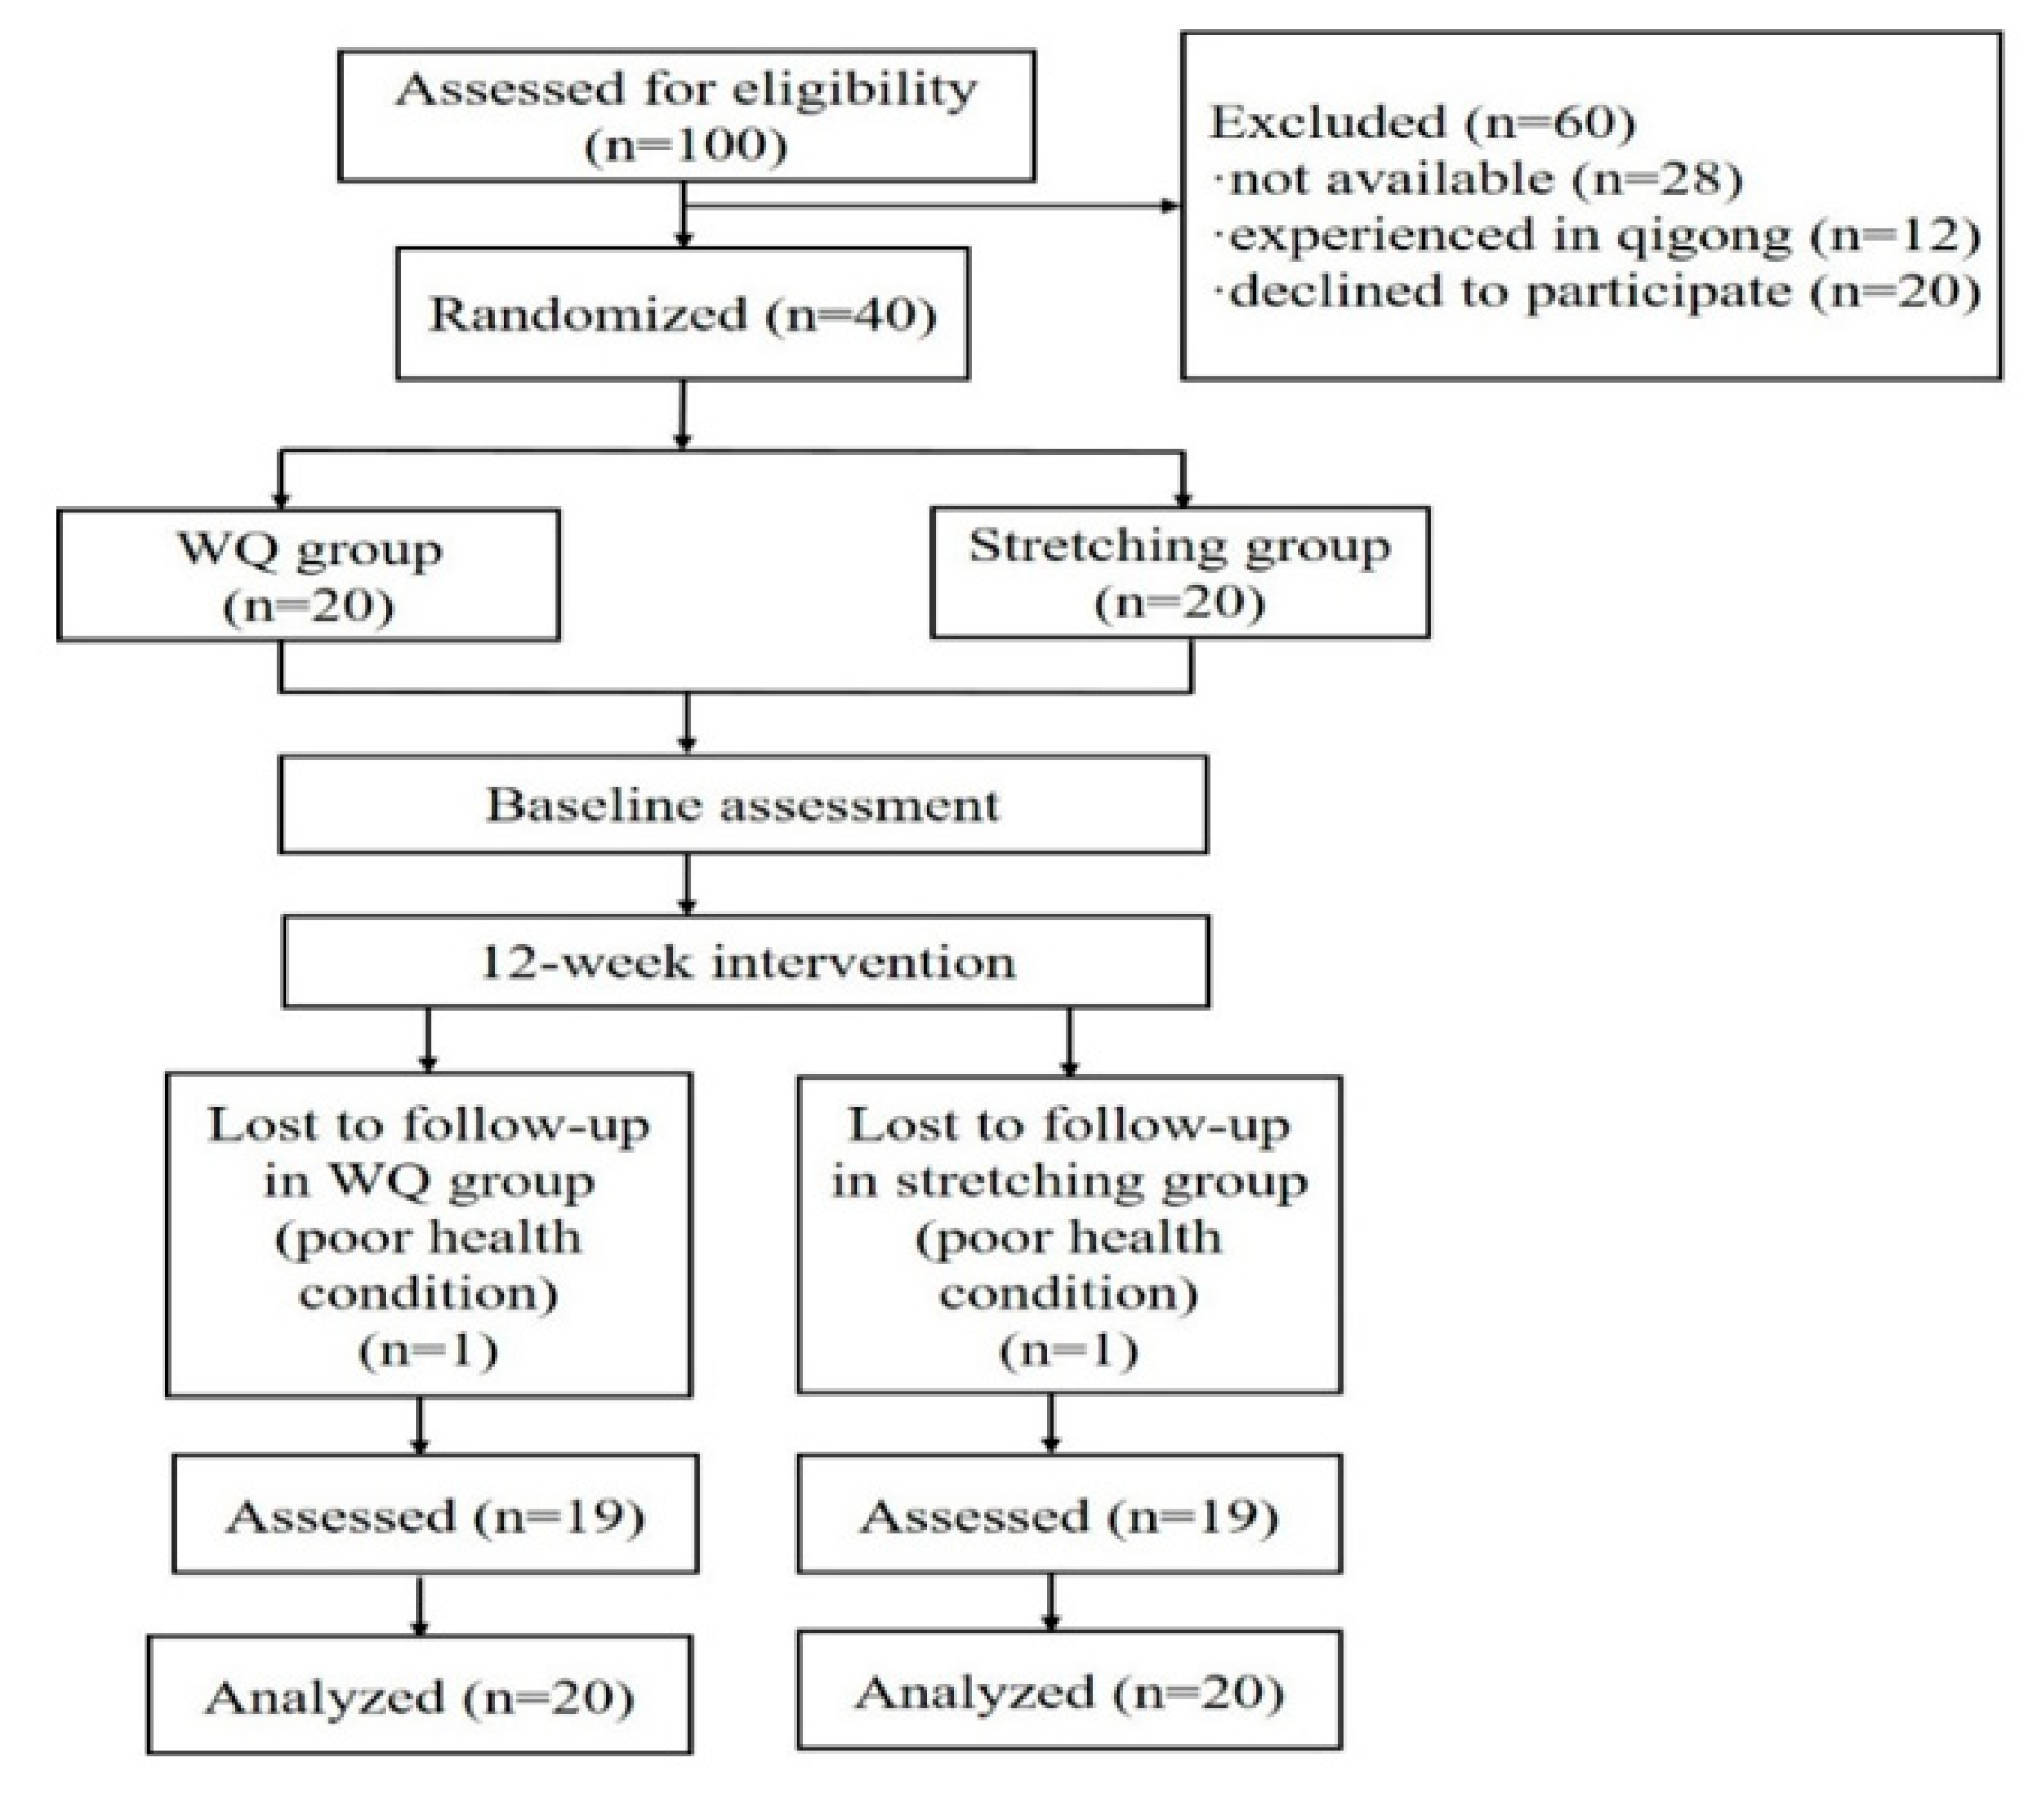
Forty participants were enrolled and randomly divided into the WQ group (n = 20) or stretching group (n = 20). One participant in each group withdrew due to medical issues unrelated to PD and did not complete the 12-week intervention, for an attrition rate of 5%. All the participants were analyzed at the end of the study (see Figure 2). No adverse events (such as fall, syncope or sports injury) occurred during intervention. Baseline characteristics showed no statistical differences between the two groups in age, gender, BMI, duration of disease, education, Hoehn and Yahr stage, motor function, or cognitive function (see Table 1).
Figure 2.
Flow diagram of the study.
Table 1.
Demographic characteristics and clinical outcomes.
3.2. Intervention Effects in Primary and Secondary Outcomes
Table 2 and Table 3 demonstrate the training effects on primary and secondary outcomes following the 12-week intervention. The WQ group demonstrated significantly increased performance from baseline in gait speed (p = 0.045) and stride length (p = 0.014) compared to the stretching group at post12wk. Between-group analysis demonstrated that the changes of gait speed in the stretching group from baseline is higher than the WQ group among the obstacle crossing task (p = 0.041). The changes of double support percentage in both groups during all dual-task measures showed a significant difference (p < 0.05), and the decrease of double support percentage in the WQ group was greater than that in stretching group. Furthermore, participants in the WQ group showed significantly increased gait speed (increase of 6.39 ± 5.98 cm/s; p = 0.000) and stride length (increase of 5.85 ± 6.45 cm; p = 0.001) following 12 weeks of intervention. Stride length also increased by 5.04 ± 8.98 cm (p = 0.021) in the serial-3 subtraction task. Double support percentage in the stretching group (from 33.27 ± 7.79 to 31.36 ± 8.19; p = 0.045) and WQ group (from 26.19 ± 4.59 to 24.15 ± 3.60; p = 0.04) was remarkably reduced as a single-task and obstacle-crossing task.
Table 2.
Within-group comparisons of clinical outcomes.
Table 3.
Between-group comparisons of changes from baseline for clinical outcomes.
The MDS-UPDRS Part III and total MDS-UPDRS scores in the WQ group significantly improved after 12 weeks of training (p = 0.021, p = 0.004), and decreased by 8.68 ± 14.96 points and 18.44 ± 23.34 points, respectively. The stretching group decreased on the MDS-UPDRS scores by 7.60 ± 13.34 points (p = 0.020). In the WQ group, TUGT time increased from 11.43 ± 3.48 to 10.05 ± 2.01 (p = 0.005), and MiniBESTest scores increased from 20.05 ± 7.18 points to 24.52 ± 4.20 points (p = 0.023). Finally, the PDQ-39 score significantly decreased from 30.00 ± 17.24 points to 22.37 ± 15.88 points (p = 0.043). These variables had no significant changes in the stretching group.
4. Discussion
We report that WQ improves walking speed and stride length of PD patients in the single and serial-3 subtraction tasks. Wuqinxi Qigong also reduces the double support percentage when participants cross obstacles, while stretching exercise reduces the double support percentage during single-task walking. Both exercise paradigms significantly alleviate motor symptoms, although WQ improves balance, mobility and quality of life better than stretching alone.
The gait characteristic of Parkinson’s disease is a bent posture; a decline in arm swing, gait speed, and stride length; and a prolonged double support phase which tends to cause falls [9,34]. The gait speed of participants in the WQ group increased by 0.0639 m/s, a value higher than the smallest meaningful change estimates (ranging from 0.04 to 0.06 m/s for gait speed) in older adults [35]. The 5.85 cm increase in stride length following 12-weeks of intervention demonstrates that WQ improves gait speed and stride length in single-task walking. Notably, several forms of Wuqinxi, such as swaying like a bear and picking fruit, require participants to move and change the center of gravity. This, accompanied with the movement of the upper limbs, slow movement, trunk control in space and shifting center of gravity, may account for the increase in gait stride. The movement patterns in WQ may benefit one’s ability to concentrate on supporting surface and postural stability, as well as ameliorate stride length and decline walking impairment [36,37].
This study showed that the double support percentage reduced when participants in the WQ group performed the obstacle-crossing task. Dual-task gait is related to motor and cognitive function, and the obstacle-crossing task is also related to muscle strength, executive function, attention and visual special abilities. Patients with Parkinson’s disease tend to increase their support base, reduce gait speed, and prolong double support time to prevent the risk of trips and falls when approaching obstacles [38,39]. Here, double support percentage is expressed as the percentage of total double support time to gait cycle time. The double support time is an indicator related to dynamic postural stability, which is associated with changes in stride length and stride time [40,41]. The current study shows that Wuqinxi Qigong intervention significantly reduced stride time variability (by 36.2%) and stride length variability (by 17.5%) for PD patients [34]. Importantly, Wuqinxi Qigong exercise requires participants to move and change the center of gravity following movements of the upper limbs. Slow movements, trunk control in space, and the transfer of the center of gravity in different directions was also emphasized. Moreover, most Qigong movements are closed-chain exercises of the lower limbs, and thus conducive to correction of inadequate heel stride and knee extension on gait cycle [42,43].
Previous studies have shown that increased attention demands, problem solving, recalling a memory, or engaging in visuospatial processing while walking in patients with Parkinson’s disease can lead to gait deterioration, cognitive decline, or both [44,45]. Dual-task training decreases time of double support during cognitive dual-task walking and reduces variability of gait during motor dual-task walking; it also improves the gait speed and stride length and reduces double support time in both motor dual-task and single-task walking [46]. Our study is consistent with these results and demonstrates that a 12-week WQ exercise regimen increases stride length in the serial-3 subtraction task, reduces double support percentage in the obstacle-crossing task, and improves gait speed and stride length in single-task walking. Wuqinxi Qigong includes cognitive components, and participants memorized the name of each form when performing the exercise. Each participant imitated and learned every movement and was able to practice all movements independently. This might increase cognitive functions such as memory, visuospatial, executive, and retelling. Moreover, we found that stretching exercise reduces double support percentage in a single-task. Several studies have demonstrated that static stretching combined with lower muscle strength improves balance and prevents falls in the elderly. It also improves motor symptoms and mobility and increases the speed of walking backwards for patients with PD [47,48].
Our study showed that TUGT increased from 11.43 ± 3.48 s to 10.05 ± 2.01 s, indicating an improvement in mobility after practicing WQ. Furthermore, the MiniBESTest score was 4.48 points higher than pre-intervention levels in the WQ group, which demonstrates a significant improvement in balance function. Notably, these levels reached the minimal clinically important difference of the MiniBESTest of 4 points [49]. The total score of the MDS-UPDRS test in the WQ and stretching exercise groups decreased by 18.44 ± 23.34 and 7.60 ± 13.43 points, respectively, which exceeded the threshold of 3.5 points for clinically important MDS-UPDRS score differences [50] These results suggest that both WQ and stretching improve motor symptoms of Parkinson’s patients and delay the progression of disease. Finally, the PDQ-39 scores in the WQ group decreased significantly, indicating that 12 weeks of WQ exercise effectively improves quality of life.
There are several limitations to this study. First, it was not feasible for participants and investigators to achieve a doubled-blind status for this study because intervention exercises were extensively open to the participants. Second, the results are only generalizable to patients with mild to moderate PD; whether these methods work similarly for advanced PD remains unknown. Third, intervention duration was relatively short and follow-up after intervention was not performed to evaluate long-term effects. Fourth, the study had an insufficient sample size; the addition of other centers to this trial as well as participants from other geographic areas would further strengthen these results. Future investigations should aim to increase the sample size and investigate the long-term therapeutic effects of WQ on patients with PD.
5. Conclusions
This study demonstrates that Wuqinxi Qigong improves single- and dual-task gait. While both Wuqinxi Qigong and stretching improve motor symptoms, Wuqinxi Qigong also improves mobility, balance, and quality of life to a greater extent than stretching alone. Additional investigation is required to explore the long-term sustained effects of Wuqinxi Qigong intervention in individuals with PD.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ijerph19138042/s1, CONSORT 2010 checklist of information to include when reporting a randomised trial. References [26,51] are cited in the supplementary materials.
Author Contributions
Z.L., J.Z. and Z.W. conceived and designed the study. Z.L. drafted the manuscript. T.W., T.S., J.H. and M.S. contributed to data collection and carried out statistical calculations. M.S. and W.G. monitored exercise and instructed participants. Z.L., J.Z., Z.W., T.W., T.S. and J.H. critically revised manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research was supported by major projects of the National Social Science Foundation of China (grant no. 19ZDA352), the Shanghai Key Lab of Human Performance (Shanghai University of Sport, grant no. 11DZ2261100).
Institutional Review Board Statement
The research was conducted according to the guidelines of the Declaration of Helsinki and approved by the Ethics Committee of Shanghai University of Sport (number: 2018031).
Informed Consent Statement
Informed consent was obtained from all participants involved in the study.
Data Availability Statement
The data presented in this study are available on request from the corresponding author.
Acknowledgments
We would like to thank all the participants who joined this study, and graduate students from the Shanghai University of Sport for their help with data collection and processing. We also thank Shanghai Frontiers Science Research Base of Exercise and Metabolic Health for its support and the doctors from the Neurology Department of Xinhua Hospital Affiliated to Shanghai Jiaotong University School of Medicine who provided health education and medication guidance for participants.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Myers, P.S.; McNeely, M.E.; Pickett, K.A.; Duncan, R.P.; Earhart, G.M. Effects of exercise on gait and motor imagery in people with Parkinson disease and freezing of gait. Parkinsonism Relat. Disord. 2018, 53, 89–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pelicioni, P.H.S.; Tijsma, M.; Lord, S.R.; Menant, J. Prefrontal cortical activation measured by fNIRS during walking: Effects of age, disease and secondary task. Peer. J. 2019, 7, e6833. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silva, A.Z.D.; Israel, V.L. Effects of dual-task aquatic exercises on functional mobility, balance and gait of individuals with Parkinson’s disease: A randomized clinical trial with a 3-month follow-up. Complementary Ther. Med. 2019, 42, 119–124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raffegeau, T.E.; Krehbiel, L.M.; Kang, N.; Thijs, F.J.; Altmann, L.J.P.; Cauraugh, J.H.; Hass, C.J. A meta-analysis Parkinson’s disease and dual-task walking. Parkinsonism Relat. Disord. 2019, 62, 28–35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kelly, V.E.; Eusterbrock, A.J.; Shumway-Cook, A. A Review of Dual-Task Walking Deficits in People with Parkinson’s Disease: Motor and Cognitive Contributions, Mechanisms, and Clinical Implications. Parkinson’s Dis. 2012, 2012, 918719. [Google Scholar] [CrossRef] [Scilit]
- Kleiner, A.F.R.; Pagnussat, A.S.; Prisco, G.D.; Vagnini, A.; Stocchi, F.; De Pandis, M.F.; Galli, M. Analyzing gait variability and dual task interference in patients with Parkinson’s disease and freezing by means of the wordcolor Stroop test. Aging Clin. Exp. Res. 2018, 30, 1137–1142. [Google Scholar] [CrossRef] [Scilit]
- Wild, L.B.; de Lima, D.B.; Balardin, J.B.; Rizzi, L.; Giacobbo, B.L.; Oliveira, H.B.; de Lima Argimon, I.I.; Peyré-Tartaruga, L.A.; Rieder, C.R.; Bromberg, E. Characterization of cognitive and motor performance during dual-tasking in healthy older adults and patients with Parkinson’s disease. J. Neurol. 2013, 260, 580–589. [Google Scholar] [CrossRef] [Scilit]
- Isaacson, S.; O’Brien, A.; Lazaro, J.D.; Ray, A.; Fluet, G. The JFK BIG study: The impact of LSVT BIG® on dual task walking and mobility in persons with Parkinson’s disease. J. Phys. Ther. Sci. 2018, 30, 636–641. [Google Scholar] [CrossRef] [Scilit]
- Dockx, K.; Bekkers, E.M.; Van den Bergh, V.; Ginis, P.; Rochester, L.; Hausdorff, J.M.; Mirelman, A.; Nieuwboer, A. Virtual reality for rehabilitation in Parkinson’s disease. Cochrane Database Syst. Rev. 2016, 12, CD010760. [Google Scholar] [CrossRef] [Scilit]
- Fritz, N.E.; Cheek, F.M.; Nichols-Larsen, D.S. Motor cognitive dual-task training in persons with neurologic disorders: A systematic review. J. Neurol. Phys. Ther. 2015, 39, 142–153. [Google Scholar] [CrossRef] [Scilit]
- Geroin, C.; Nonnekes, J.; de Vries, N.M.; Strouwen, C.; Smania, N.; Tinazzi, M.; Nieuwboer, A.; Bloem, B.R. Does dual-task training improve spatiotemporal gait parameters in Parkinson’s disease? Parkinsonism Relat. Disord. 2018, 55, 86–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maidan, I.; Nieuwhof, F.; Bernad-Elazari, H.; Bloem, B.R.; Giladi, N.; Hausdorff, J.M.; Claassen, J.A.H.R.; Mirelman, A. Evidence for Differential Effects of 2 Forms of Exercise on Prefrontal Plasticity During Walking in Parkinson’s Disease. Neurorehabilit. Neural Repair 2018, 2, 200–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.; Qiu, W.Q.; Hao, Y.L.; Lv, Z.Y.; Jiao, S.J.; Teng, J.F. The efficacy of traditional Chinese Medical Exercise for Parkinson’s disease: A systematic review and meta-analysis. PLoS ONE 2015, 10, e0122469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, R.; Grabowska, W.; Park, M.; Osypiuk, K.; Vergara-Diaz, G.P.; Bonato, P.; Hausdorff, J.M.; Fox, M.; Sudarsky, L.R.; Macklin, E.; et al. The impact of Tai Chi and Qigong mind-body exercises on motor and non-motor function and quality of life in Parkinson’s disease: A systematic review and meta-analysis. Parkinsonism Relat. Disord. 2017, 41, 3–13. [Google Scholar] [CrossRef] [Scilit]
- Ge, L.; Zheng, Q.X.; Liao, Y.T.; Tan, J.Y.; Xie, Q.L.; Rask, M. Effects of traditional Chinese exercises on the rehabilitation of limb function among stroke patients: A systematic review and meta-analysis. Complementary Ther. Clin. Pract. 2017, 29, 35–47. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Zhou, J. Analysis of the TCM theory of traditional Chinese health exercise. J. Sport Health Sci. 2013, 2, 204–208. [Google Scholar]
- Guo, Y.; Xu, M.; Wei, Z.; Hu, Q.; Chen, Y.; Yan, J.; Wei, Y. Beneficial Effects of Qigong Wuqinxi in the Improvement of Health Condition, Prevention, and Treatment of Chronic Diseases: Evidence from a Systematic Review. Evid. Based Complement Altern. Med. 2018, 2018, 3235950. [Google Scholar] [CrossRef] [Scilit]
- Wang, K.; Liu, S.; Kong, Z.; Zhang, Y.; Liu, J. Mind-Body Exercise (Wuqinxi) for Patients with Chronic Obstructive Pulmonary Disease: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Int. J. Environ. Res. Public Health 2018, 16, 72. [Google Scholar] [CrossRef] [Scilit]
- Zhang, F.B.Y.; Zhang, J. The Influence of “wuqinxi” exercises on the Lumbosacral Multifidus. J. Phys. Ther. Sci. 2014, 26, 881–884. [Google Scholar] [CrossRef] [Scilit]
- Yao, C.; Li, Z.; Zhang, S.; Wu, Z.; Zhu, Q.; Fang, L. Effects of Wuqinxi in the Patients with Chronic Low Back Pain: A Randomized Controlled Trial. Evid. Based Complement Alternat. Med. 2020, 2020, 1428246. [Google Scholar] [CrossRef] [Scilit]
- Xiao, C.M.; Li, J.J.; Kang, Y.; Zhuang, Y.C. Follow-up of a Wuqinxi exercise at home programme to reduce pain and improve function for knee osteoarthritis in older people: A randomised controlled trial. Age Ageing 2021, 50, 570–575. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tolos, E.; Wenning, G.; Poewe, W. The diagnosis of Parkinson’s disease. Neurol. Sci. 2006, 5, 75–86. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.C.; Yang, Y.R.; Tsai, Y.A.; Wang, R.Y. Cognitive and motor dual task gait training improve dual task gait performance after stroke—A randomized controlled pilot trial. Sci. Rep. 2017, 7, 4070. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borg, G. Borg’s Perceived Exertion and Pain Scales; Human Kinetics: Champaign, IL, USA, 1998; p. 104. [Google Scholar]
- Chinese Health Qigong Association. Theoretical Training Course in Health Qigong, 1st ed.; Foreign Languages Press Co., Ltd.: Beijing, China, 2015; pp. 202–203. [Google Scholar]
- Anderson, B. Stretching: 40th Anniversary Edition; Shelter Publication Inc.: Bolinas, CA, USA, 2020; pp. 108–113. [Google Scholar]
- Fernandes, Â.; Sousa, A.S.; Rocha, N.; Tavares, J.M. Parkinson’s Disease and Cognitive-Motor Dual-Task: Is Motor Prioritization Possible in the Early Stages of the Disease? J. Mot. Behav. 2016, 48, 377–383. [Google Scholar] [CrossRef] [Scilit]
- Liepelt-Scarfone, I.; Lerche, S.; Behnke, S.; Godau, J.; Gaenslen, A.; Pausch, C.; Fassbender, K.; Brockmann, K.; Srulijes, K.; Huber, H.; et al. Clinical characteristics related to worsening of motor function assessed by the Unified Parkinson’s Disease Rating Scale in the elderly population. J. Neurol. 2015, 262, 451–458. [Google Scholar] [CrossRef] [Scilit]
- Benka Wallén, M.; Sorjonen, K.; Löfgren, N.; Franzén, E. Structural Validity of the Mini-Balance Evaluation Systems Test (Mini-BESTest) in People with Mild to Moderate Parkinson Disease. Phys. Ther. 2016, 96, 1799–1806. [Google Scholar] [CrossRef] [Scilit]
- Benavent-Caballer, V.; Sendín-Magdalena, A.; Lisón, J.F.; Rosado-Calatayud, P.; Amer-Cuenca, J.J. Physical factors underlying the Timed “Up and Go” test in older adults. Geriatr. Nurs. 2016, 37, 122–127. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Jia, J.; Yang, Z. Mini-Mental State Examination in Elderly Chinese: A Population-Based Normative Study. J. Alzheimers Dis. 2016, 53, 487–496. [Google Scholar] [CrossRef] [Scilit]
- Jesus-Ribeiro, J.; Vieira, E.; Ferreira, P.; Januário, C.; Freire, A. Reliability and validity of 39-Item Parkinson’s disease questionnaire and Parkinson’s disease quality of life questionnaire. Acta Med. Port. 2017, 30, 395–401. [Google Scholar] [CrossRef] [Scilit]
- Cohen, J. Statistical Power Analysis for the Behavioral Sciences. Technometrics 1988, 31, 499–500. [Google Scholar]
- Wassom, D.J.; Lyons, K.E.; Pahwa, R.; Liu, W. Qigong exercise may improve sleep quality and gait performance in Parkinson’s disease: A pilot study. Int. J. Neurosci. 2015, 125, 578–584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perera, S.; Mody, S.H.; Woodman, R.C.; Studenski, S.A. Meaningful change and responsiveness in common physical performance measures in older adults. J. Am. Geriatr. Soc. 2006, 54, 743–749. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Gao, J.; Yin, B.; Yang, X.; Bai, D. Efficacy of Ba Duan Jin in Improving Balance: A Study in Chinese Community-Dwelling Older Adults. J. Gerontol. Nurs. 2016, 42, 38–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sawynok, J.; Lynch, M. Qigong and fibromyalgia: Randomized controlled trials and beyond. Evid. Based Complement Alternat. Med. 2014, 2014, 379715. [Google Scholar] [CrossRef] [Scilit]
- Maidan, I.; Eyal, S.; Kurz, I.; Geffen, N.; Gazit, E.; Ravid, L.; Giladi, N.; Mirelman, A.; Hausdorff, J.M. Age-associated changes in obstacle negotiation strategies: Does size and timing matter? Gait Posture 2017, 59, 242–247. [Google Scholar] [CrossRef] [Scilit]
- Alcock, L.; Galna, B.; Hausdorff, J.M.; Lord, S.; Rochester, L. Gait & Posture Special Issue: Gait adaptations in response to obstacle type in fallers with Parkinson’s disease. Gait Posture 2018, 61, 368–374. [Google Scholar]
- Roiz Rde, M.; Cacho, E.W.; Pazinatto, M.M.; Reis, J.G.; Cliquet, A.; Barasnevicius-Quagliato, E.M. Gait analysis comparing Parkinson’s disease with healthy elderly subjects. Arq. Neuro-Psiquiatr. 2010, 68, 81–86. [Google Scholar] [CrossRef] [Scilit]
- Schaafsma, J.D.; Giladi, N.; Balash, Y.; Bartels, A.L.; Gurevich, T.; Hausdorff, J.M. Gait dynamics in Parkinson’s disease: Relationship to Parkinsonian features, falls and response to levodopa. J. Neurol. Sci. 2003, 212, 47–53. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.L.; Chen, S.; Wang, Y. Effects of health Qigong exercises on relieving symptoms of Parkinson’s disease. Evid. Based Complement Alternat. Med. 2016, 2016, 5935782. [Google Scholar] [CrossRef] [Scilit]
- Klein, P.; Picard, G.; Baumgarden, J.; Schneider, R. Meditative movement, energetic, and physical analyses of three Qigong exercises: Unification of eastern and Western mechanistic exercise theory. Medicines 2017, 4, 69. [Google Scholar] [CrossRef] [Scilit]
- Rochester, L.; Galna, B.; Lord, S.; Burn, D. The nature of dual-task interference during gait in incident Parkinson’s disease. Neuroscience 2014, 265, 83–94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stegemöller, E.L.; Wilson, J.P.; Hazamy, A.; Shelley, M.C.; Okun, M.S.; Altmann, L.J.; Hass, C.J. Associations between cognitive and gait performance during single- and dual-task walking in people with Parkinson disease. Phys. Ther. 2014, 94, 757–766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.R.; Cheng, S.J.; Lee, Y.J.; Liu, Y.C.; Wang, R.Y. Cognitive and motor dual task gait training exerted specific training effects on dual task gait performance in individuals with Parkinson’s disease: A randomized controlled pilot study. PLoS ONE 2019, 14, e0218180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rawson, K.S.; McNeely, M.E.; Duncan, R.P.; Pickett, K.A.; Perlmutter, J.S.; Earhart, G.M. Exercise and Parkinson Disease: Comparing Tango, Treadmill, and Stretching. J. Neurol. Phys. Ther. 2019, 43, 26–32. [Google Scholar] [CrossRef] [Scilit]
- Mak, M.K.; Wong-Yu, I.S.; Shen, X.; Chung, C.L. Long-term effects of exercise and physical therapy in people with Parkinson disease. Nat. Rev. Neurol. 2017, 13, 689–703. [Google Scholar] [CrossRef] [Scilit]
- Godi, M.; Arcolin, I.; Giardini, M.; Corna, S.; Schieppati, M. Responsiveness and minimal clinically important difference of the Mini-BESTest in patients with Parkinson’s disease. Gait Posture 2020, 80, 14–19. [Google Scholar] [CrossRef] [Scilit]
- Horváth, K.; Aschermann, Z.; Ács, P.; Deli, G.; Janszky, J.; Komoly, S.; Balázs, É.; Takács, K.; Karádi, K.; Kovács, N. Minimal clinically important difference on the Motor Examination part of MDS-UPDRS. Parkinsonism Relat. Disord. 2015, 21, 1421–1426. [Google Scholar] [CrossRef] [Scilit]
- Ying, L. Health Qigong Wuqinxi, 1st ed.; Dalian Maritime University Press: Dalian, China, 2016; pp. 45–95. [Google Scholar]



Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).