


Abstract
Women face risks to their wellbeing during the perinatal period of pregnancy. However, there is a dearth of information on perinatal risk factors within the biopsychosocial paradigm. Emphasis is often placed on biological components associated with pregnancy and women’s health. However, psychological and social determinants of health are integral during the perinatal period, and mental wellness is often a determinant for positive maternal and neonatal health outcomes. This article reviews risk factors of perinatal wellness (e.g., physical and nutritional concerns, trauma, discrimination, adverse childhood events) and highlights protective factors for women in their perinatal period. Healthcare professionals can support perinatal health by focusing on culturally and contextually appropriate research and prevention, providing equal access to sexual and reproductive healthcare information and services, providing quality education and training for helping professionals, and supporting policies for positive sexual and reproductive women’s healthcare.
1. Introduction
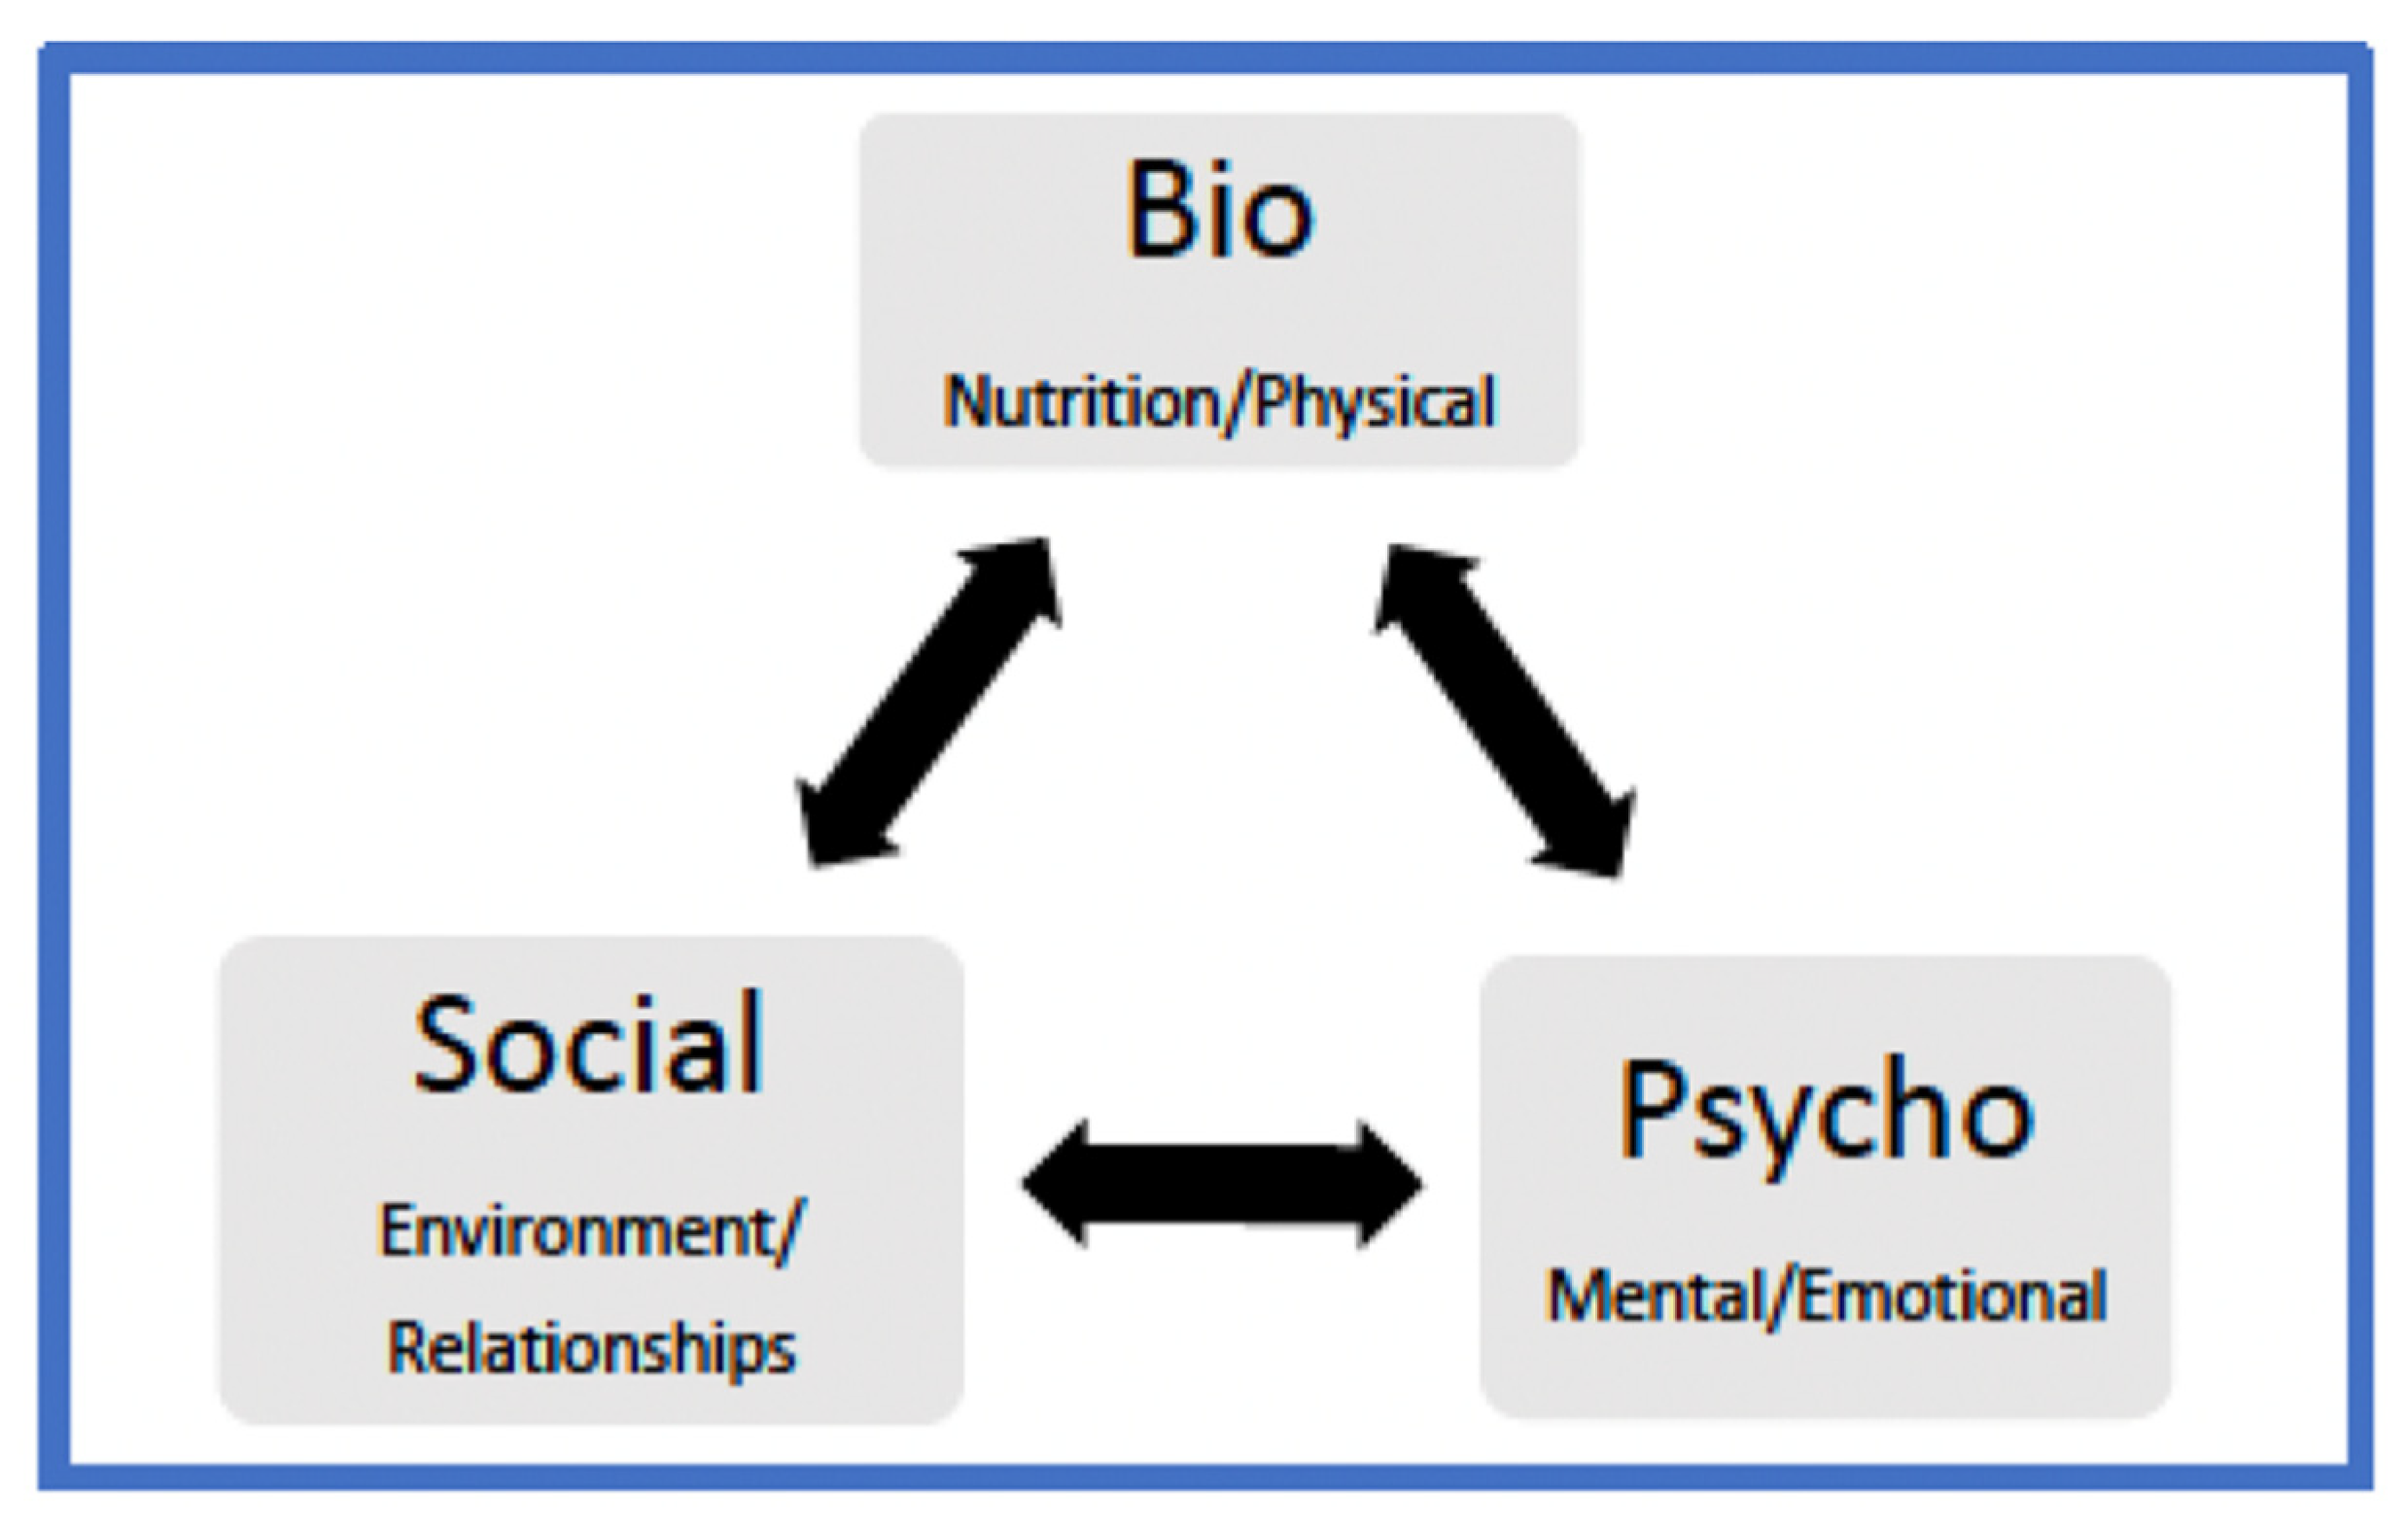
When focusing on the biopsychosocial risk factors related to perinatal health, it is important to consider a number of salient factors. Emphasis is placed on the biological components associated with pregnancy and women’s health, yet psychological and social determinants of health are integral during the perinatal period and are often determinants for positive maternal and neonatal health outcomes [1]. Thus, we attempt to bridge this gap by highlighting and emphasizing the importance of psychological and social determinants of perinatal health, along with biological factors. The World Health Organization (WHO) stated that “health is a state of complete physical, mental, and social well-being and not merely in the absence of disease or infirmity” [2] (p. 984). Additionally, viewing women’s health holistically allows healthcare professionals to account for a variety of factors influencing maternal wellbeing. As such, utilizing a biopsychosocial model to assess risk factors and protective factors during the perinatal period is fitting and can result in enhanced maternal and neonatal outcomes [3,4]. See Figure 1 for sample biopsychosocial pregnancy model.
Figure 1.
Example of Biopsychosocial Theoretical Pregnancy Model Incorporating Biological, Psychological, and Social Determinants of Health.
In the biopsychosocial realm, risks contributing the health and wellness of perinatal women exist. Examples such as epigenetic changes, transgenerational trauma, mental illness, stress experiences, racism, and microaggressions contribute directly to health disparities and poor maternal and neonatal outcomes [5]. Healthcare professionals need to account for impacts of these risks on perinatal health and wellbeing. The following sections highlight biological, psychological, and social risk factors of the perinatal period through a thematic review of the literature on perinatal wellbeing. Search terms included perinatal, wellbeing, wellness, preventative factors, biopsychosocial (biological, psychological, social), and risk factors across medical and alternative medicine-based journals (e.g., counseling, holistic practices). Limitations of the literature review and implications for healthcare professionals working with and supporting women in their pregnancy lifecycles are also provided. See Table 1 for risk factors.
Table 1.
Biopsychosocial model of wellness: risk factors for women in pregnancy lifecycles.
3. Discussion
Though a number of risks exist for women in perinatal periods, there are a number of protective factors. Protective factors for women in the perinatal period include: (a) increased access to health insurance, (b) access to quality health care, (c) access to providers that practice patient-centered and culturally sensitive care, and (d) access to reproductive healthcare (contraception, abortion, sexually transmitted infections screenings, reproductive cancer screenings) [56]. Prather and colleagues [40] suggested that healthcare professionals: focus on culturally and contextually appropriate research and prevention, provide equal access to sexual and reproductive healthcare information and services, provide quality education and training for helping professionals, and support policies for positive sexual and reproductive women’s healthcare. We echo these sentiments and suggest while working with women during their pregnancy lifecycle, healthcare professionals utilize a biopsychosocial clinical model, addressing the holistic needs of their patients. Using a biopsychosocial model involves collaboration with multiple stakeholders contributing to the patient’s health and may incorporate non-traditional medical services such as doula services and/or adding an in-home component which could be especially helpful for WOC [66]. Additionally, healthcare professionals can support perinatal wellness by providing culturally responsive services, advocating for their patients, and allowing patients to be assertive regarding their medical needs.
3.1. Implications for Healthcare Professionals
3.1.1. Culturally Responsive Services
Healthcare professionals are trained to provide multiculturally competent services, meeting patients where they are in empathic and genuine ways [67]. Since women’s healthcare is a biopsychosocial issue, a wellness philosophy is a fit for this population, as it allows for a holistic examination of factors influencing human functioning. Furthermore, recognizing gendered racism, depression, anxiety, and stress, could promote enhanced maternal health outcomes [5,68]. In addition, utilizing appropriate models based on women’s needs (e.g., operating from racial-cultural competency and utilizing race broaching skills when necessary) could be beneficial when working with diverse patients.
3.1.2. Advocacy Role
Factors such as medication/non-medication management and nutritional concerns in the biological realm, peri-and-post-partum issues in the psychological realm, and societal issues such as racism and socioeconomic influences in the social realm are paramount in providing sound clinical treatment for women in pregnancy lifecycles. As there are many variables at play, healthcare professionals might benefit women by taking a supportive role and aiding patients through advocacy work in medical settings. It may also behoove healthcare professionals to work in tandem with other helping professionals in an interdisciplinary nature [5]. When having conversations with women, it is especially important for counselors to consider and discuss social influences such as racism, microaggressions, race broaching, and cultural factors that could be influencing perinatal wellness [69]. Taking it a step further, health professionals can advocate and act against systemic power barriers affecting marginalized patients and take steps to advocate for equitable access to quality healthcare, reasonable insurance plans, and culturally-sound healthcare providers [69].
3.1.3. Patient Assertiveness
If women are empowered to “ask for” what they need/want and take an assertive stance in their healthcare, negative outcomes related to “not hearing women” and not trusting women as the experts over their own bodies, might be mitigated. Ultimately, doctors, health providers, and other helpers who are not meeting the individual patient’s needs can be replaced with individuals who listen and take into account the unique biopsychosocial variables influencing perinatal health.
4. Limitations of the Literature Review
As with any review, there are limitations. This thematic review focused on perinatal risk factors by reviewing literature associated with biological, psychological, and social determinants of health. Though many factors were discovered and discussed, the review is not exhaustive, as there may be additional risk to women in their perinatal period not included in this review. Furthermore, this paper includes a general review of the available literature, and the information and conclusions may not be applicable to all perinatal women and their neonatal offspring.
5. Conclusions
Women face risks to their perinatal wellbeing and it benefits healthcare professionals to have knowledge of the biopsychosocial determinants of health. Knowing the risks within a biopsychosocial paradigm allows for accountability and enhanced quality of care for expectant mothers. Incorporating and supporting protective factors for women in their perinatal period includes increasing access to health insurance and quality health care, providing patient-centered and culturally sensitive care, and enhancing access to reproductive healthcare. Further, healthcare professionals can support perinatal health by using this holistic model to assess for potential risks and discuss protective factors, while viewing each patient from their unique, diverse background. Ultimately, utilizing a biopsychosocial model can enhance discussions on the numerous facets influencing the perinatal period and increase patient/healthcare professional communication.
Author Contributions
Conceptualization, A.J.B., C.R.A. and K.S.; writing—original draft preparation, A.J.B., C.R.A., A.L.A.-B., C.H., G.P.; writing—review and editing, A.J.B., K.S. and G.P.; funding acquisition, G.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by CHRI to Guru Pendyala.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Srinivasan, K.; Satyanarayana, V.A.; Lukose, A. Maternal mental health in pregnancy and child behavior. Indian J. Psychiatry 2011, 53, 351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- International Health Conference. Constitution of the World Health Organization. 1946. Bull. World Health Organ. 2002, 80, 981–984. Available online: https://apps.who.int/iris/handle/10665/268688 (accessed on 12 July 2021).
- Buultjens, M.; Murphy, G.; Robinson, P.; Milgrom, J. The perinatal period: A literature review from the biopsychosocial perspective. Clin. Nurs. Stud. 2013, 1, 19–31. [Google Scholar] [CrossRef] [Scilit]
- Engel, G. The need for a new medical model: A challenge for biomedicine. Science 1977, 196, 129–136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yehudah, S.B.; Lorelle, S. Black birth outcomes and implications for counseling. J. Prof. Couns. 2020, 47, 46–60. [Google Scholar] [CrossRef] [Scilit]
- Moya, J.; Phillips, L.; Sanford, J.; Wooton, M.; Gregg, A.; Schuda, L. A review of physiological and behavioral changes during pregnancy and lactation: Potential exposure factors and data gaps. J. Expo Sci. Environ. Epidemiol. 2014, 24, 449–458. [Google Scholar] [CrossRef] [Scilit]
- Zhang, N.; Zhang, F.; Chen, S.; Han, F.; Lin, G.; Zhai, Y. Associations between hydration state and pregnancy complications, maternal-infant outcomes: Protocol of a prospective observational cohort study. BMC Pregnancy Childbirth 2020, 20, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Armstrong, C. ACOG practice bulletin no. 92: Use of psychiatric medications during pregnancy and lactation. Obstet. Gynecol. 2008, 111, 1001–1020. [Google Scholar] [CrossRef] [Scilit]
- Lockwood, L.E.; Youssef, N.A. Systematic review of epigenetic effects of pharmacological agents for bipolar disorders. Brain Sci. 2017, 7, 154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanson, C.; Schumacher, M.V.; Lyden, E.; Su, D.; Furtado, J.; Cammack, R. Fat-soluble vitamins A and E and health disparities in a cohort of pregnant women at delivery. J. Nutr. Sci. 2018, 7, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Radhika, M.S.; Bhaskaram, P.; Balakrishna, N.; Ramalakshmi, B.A.; Devi, S.; Kumar, B.S. Effects of vitamin A deficiency during pregnancy on maternal and child health. BJOG Obstet. Gynecol. Int. J. 2002, 109, 689–693. [Google Scholar] [CrossRef] [PubMed]
- McCauley, M.E.; Van Den Broek, N.; Dou, L.; Othman, M. Vitamin A supplementation during pregnancy for maternal and newborn outcomes. Cochrane Database Syst. Rev. 2015, 10, CD008666. [Google Scholar] [CrossRef] [Scilit]
- Hoekzema, E.; Tamnes, C.K.; Berns, P.; Barba-Müller, E.; Pozzobon, C.; Picado, M. Becoming a mother entails anatomical changes in the ventral striatum of the human brain that facilitate its responsiveness to offspring cues. Psychoneuroendocrinology 2020, 112, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anderson, M.V.; Rutherford, M.D. Cognitive reorganization during pregnancy and the postpartum period: An evolutionary perspective. Evol. Psychol. 2012, 10, 659–687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pearson, R.M.; Lightman, S.L.; Evans, J. Emotional sensitivity for motherhood: Late pregnancy is associated with enhanced accuracy to encode emotional faces. Horm. Beh. 2009, 56, 557–563. [Google Scholar] [CrossRef] [Scilit]
- Meins, E.; Fernyhough, C.; Fradley, E.; Tuckey, M. Rethinking maternal sensitivity: Mothers’ comments on infants’ mental processes predict security of attachment at 12 months. J. Child Psycol. Psychiatry 2001, 42, 637–648. [Google Scholar] [CrossRef]
- Szyf, M.; Tang, Y.-Y.; Hill, K.G.; Musci, R. The dynamic epigenome and its implications for behavioral interventions: A role for epigenetics to inform disorder prevention and health promotion. Transl. Behav. Med. 2016, 6, 55–62. [Google Scholar] [CrossRef] [Scilit]
- De Socio, J.E. Epigenetics, maternal prenatal psychosocial stress, and infant mental health. Arch. Psychiatry Nurs. 2018, 32, 901–906. [Google Scholar] [CrossRef] [Scilit]
- Bale, T.L. Lifetime stress experience: Transgenerational epigenetics and germ cell programming. Epigenetics 2014, 16, 297–305. [Google Scholar] [CrossRef] [Scilit]
- Buss, C.; Entringer, S.; Swanson, J.M.; Wadwa, P.D. The Role of Stress in Brain Development: The Gestational Environment’s Long-Term Effects on the Brain. Cerebrum 2012, 4, 1–16. Available online: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3574809/ (accessed on 15 July 2021).
- Lewis, A.J.; Galbally, M.; Gannon, T.; Symeonides, C. Early life programming as a target for prevention of child and adolescent mental disorders. BMC Med. 2014, 12, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Mersky, J.P.; Plummer Lee, C.T. Adverse childhood experiences and poor birth outcomes in a diverse, low-income sample. BMC Pregnancy Childbirth 2019, 19, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Racine, N.; Devereaux, C.; Cooke, J.E.; Eirich, R.; Zhu, J.; Madigan, S. Adverse childhood experiences and maternal anxiety and depression: A meta-analysis. BMC Psychiatry 2021, 21, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olsen, J.M. Integrative review of pregnancy health risks and outcomes associated with adverse childhood experiences. J. Obstet Gynecol. Neonatal. Nurs. 2018, 47, 783–794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bjelica, A.; Kapor-Stanulovic, P. Pregnancy as a psychological event. Med. Rev. 2004, 57, 144–148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jou, J.; Kozhimannil, K.B.; Johnson, P.J.; Sakala, C. Patient-perceived pressure from clinicians for labor induction and cesarean delivery: A population-based survey of U.S. women. Health Serv. Res. 2014, 50, 961–981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Renbarger, K.M.; Shieh, C.; Moorman, M.; Latham-Mintus, K.; Draucker, C. Health care encounters of pregnant and postpartum women with substance use disorders. West. J. Nurs. Res. 2019, 42, 612–628. [Google Scholar] [CrossRef] [Scilit]
- Nicholls, J.; David, A.L.; Iskaros, J.; Lanceley, A. Consent in pregnancy: A qualitative study of the views and experiences of women and their healthcare professionals. Eur. J. Obstet. Gynecol. Reprod. Biol. X 2019, 238, 132–137. [Google Scholar] [CrossRef] [Scilit]
- Bauman, B.L.; Ko, J.Y.; Cox, S.; D’Angelo, D.V.; Warner, L.; Folger, S. Vital signs: Postpartum depressive symptoms and provider discussions about perinatal depression—United States, 2018. MMWR 2020, 69, 575–581. [Google Scholar] [CrossRef] [Scilit]
- Beck, C.T. Predictors of postpartum depression. Nurs. Res. 2001, 50, 275–285. [Google Scholar] [CrossRef] [Scilit]
- Ely, D.M.; Driscoll, A.K. Infant Mortality in the United States: Data from the Period Linked Birth/Infant Death File. Natl. Vital. Stat. Rep. 2019, 68, 1–20. Available online: https://www.cdc.gov/nchs/data/nvsr/nvsr68/nvsr68_10-508.pdf (accessed on 12 July 2021).
- Lorch, S.A.; Enlow, E. The role of social determinants in explaining racial/ethnic disparities in perinatal outcomes. Res. Pediatr. 2015, 79, 141–147. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coussons-Read, M.E. Effects of prenatal stress on pregnancy and human development: Mechanisms and pathways. Obstet. Med. 2013, 6, 52–57. [Google Scholar] [CrossRef] [Scilit]
- Holzman, C.; Eyster, J.; Kleyn, M.; Messer, L.C.; Kaufman, J.S.; Laraia, B.A. Maternal weathering and risk of preterm delivery. Am. J. Public Health 2009, 99, 1864–1871. [Google Scholar] [CrossRef] [Scilit]
- Rubin, L.P. Maternal and pediatric health and disease: Integrating biopsychosocial models and epigenetics. Pediatr. Res. 2015, 79, 127–135. [Google Scholar] [CrossRef] [Scilit]
- Halfon, N. Racial and ethnic disparities in birth outcomes: A life-course perspective. J. Mother Child 2003, 7, 13–30. [Google Scholar] [CrossRef] [Scilit]
- Kramer, M.R.; Williamson, R. Multivariate bayesian spatial model of preterm birth and cardiovascular disease among Georgia women: Evidence for life course social determinants of health. Spat. Spatiotemporal. Epidemiol. 2013, 6, 25–35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Youssef, N.; Lockwood, L.; Su, S.; Hao, G.; Rutten, B. The effects of trauma, with or without PTSD, on the transgenerational DNA methylation alterations in human offsprings. Brain Sci. 2018, 8, 83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giurgescu, C.; Norr, K.F.; Dancy, B.L.; Twigg, N.; McFarlin, B.L.; Engeland, C.G. Stressors, resources, and stress responses in pregnant African American women. J. Perinat. Neonatal. Nurs. 2013, 27, 81–96. [Google Scholar] [CrossRef] [Scilit]
- Prather, C.; Fuller, T.R.; Jeffries, W.L.; Marshall, K.J.; Howell, A.V.; Belyue-Umole, A. Racism, African American Women, and Their Sexual and Reproductive Health: A Review of Historical and Contemporary Evidence and Implications for Health Equity. Health Equity 2018, 2, 249–259. Available online: https://soilorg/10/1089/heq.2017.0045 (accessed on 12 July 2021). [CrossRef] [Scilit]
- Ronsmans, C.; Graham, W.J. Maternal mortality: Who, when, where, and why. Lancet 2006, 368, 1189–1200. [Google Scholar] [CrossRef] [Scilit]
- Black, R.E.; Allen, L.H.; Bhutta, Z.A.; Caulfield, L.E.; de Onis, M.; Ezzati, M. Maternal and child undernutrition: Global and regional exposures and health consequences. Lancet 2008, 371, 243–260. [Google Scholar] [CrossRef] [Scilit]
- Agaku, I.T.; King, B.A.; Dube, S.R. Current Cigarette Smoking among Adults-United States, 2005–2012. MMWR 2014, 63, 29–34. Available online: https://www.cdc.gov/mmwr/preview/mmwrhtml/mm6302a2.htm (accessed on 15 July 2021).
- Cerdá, M.; Johnson-Lawrence, V.D.; Galea, S. Lifetime income patterns and alcohol consumption: Investigating the association between long- and short-term income trajectories and drinking. Soc. Sci. Med. 2011, 73, 1178–1185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strutz, K.L.; Hogan, V.K.; Siega-Riz, A.M.; Suchindran, C.M.; Halpern, C.T.; Hussey, J.M. Preconception stress, birth weight, and birth weight disparities among US women. Am. J. Public Health 2014, 104, 125–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Najman, J.M.; Hayatbakhsh, M.R.; Heron, M.A.; Bor, W.; O’Callaghan, M.J.; Williams, G.M. The impact of episodic and chronic poverty on child cognitive development. J. Pediatr. 2009, 154, 284–289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hamad, R.; Rehkopf, D.H. Poverty, pregnancy, and birth outcomes: A study of the earned income tax credit. Paediatr. Pernat. Epidemiol. 2015, 29, 444–452. [Google Scholar] [CrossRef] [Scilit]
- Kaufman, J.S.; Dole, N.; Savitz, D.A.; Herring, A.H. Modeling community-level effects on preterm birth. Ann. Epidemiol. 2003, 13, 377–384. [Google Scholar] [CrossRef] [Scilit]
- Cubbin, C.; Kim, Y.; Vohra-Gupta, S.; Margerison, C. Longitudinal measures of neighborhood poverty and income inequality are associated with adverse birth outcomes in Texas. Soc. Sci. Med. 2020, 245. [Google Scholar] [CrossRef] [Scilit]
- Bird, S.T.; Bogart, L.M. Perceived Race-Based and Socioeconomic Status (SES)-Based Discrimination in Interactions with Health Care Providers. Ethn. Dis. 2001, 11, 554–563. Available online: https://pubmed.ncbi.nlm.nih.gov/11572421/ (accessed on 12 July 2021).
- Lillie-Blanton, M.; Brodie, M.; Rowland, D.; Altman, D.; McIntosh, M. Race, ethnicity, and the health care system: Public perceptions and experiences. Med. Care Res. Rev. 2000, 57, 218–235. [Google Scholar] [CrossRef] [Scilit]
- De Marco, M.; Thorburn, S.; Zhao, W. Perceived discrimination during prenatal care, labor, and delivery: An examination of data from the Oregon pregnancy risk assessment monitoring system, 1998–1999, 2000, and 2001. Am. J. Public Health 2008, 98, 1818–1822. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pamuk, E.; Makjuc, D.; Heck, K.; Reuben, C.; Lochner, K. Socioeconomic Status and Health Chartbook (Report No. 76-641496); U.S. Department of Health and Human Services: Hyattsville, MD, USA, 1998. Available online: https://www.cdc.gov/nchs/data/hus/hus98cht.pdf (accessed on 15 July 2021).
- Dominguez, T.P. Adverse birth outcomes in African American women: The social context of persistent reproductive disadvantage. Soc. Work. Public Health 2011, 26, 3–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petersen, E.E.; Davis, N.L.; Goodman, D.; Cox, S.; Syverson, C.; Seed, K. Racial/ethnic disparities in pregnancy-related deaths—United States, 2007–2016. MMWR 2019, 68, 762–765. [Google Scholar] [CrossRef] [Scilit]
- Chalhoub, T.; Rimar, K. The Health Care System and Racial Disparities in Maternal Mortality. Cent. Am. Prog. 2018, 1–7. Available online: https://cdn.americanprogress.org/content/uploads/2018/05/09121820/HealthSystemDisparitiesInMaternalMortality-Brief.pdf?_ga=2.71795347.1206125014.1623721127-1221635400.1623721127 (accessed on 15 July 2021).
- Vedam, S.; Stoll, K.; Taiwo, T.K.; Rubashkin, N.; Cheyney, M.; Strauss, N. The giving voice to mothers study: Inequity and mistreatment during pregnancy and childbirth in the United States. Reprod. Health 2019, 16, 1–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McLemore, M.R.; Altman, M.R.; Cooper, N.; Williams, S.; Rand, L.; Franck, L. Health care experiences of pregnant, birthing and postnatal women of color at risk for preterm birth. Soc. Sci. Med. 2018, 201, 127–135. [Google Scholar] [CrossRef] [Scilit]
- Stapleton, L.R.; Schetter, C.D.; Westling, E.; Rini, C.; Glynn, L.M.; Hobel, C.J. Perceived partner support in pregnancy predicts lower maternal and infant distress. J. Fam. Pschol. 2012, 26, 453–463. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Whisman, M.A.; Davila, J.; Goodman, S.H. Relationship adjustment, depression, and anxiety during pregnancy and the postpartum period. J. Fam. Psychol. 2011, 25, 375–383. [Google Scholar] [CrossRef] [Scilit]
- Alhusen, J.L.; Ray, E.; Sharps, P.; Bullock, L. Intimate partner violence during pregnancy: Maternal and neonatal outcomes. J. Women’s Health 2015, 24, 100–106. [Google Scholar] [CrossRef] [Scilit]
- Tjaden, P.; Thoennes, N. Full Report of the Prevalence, Incidence, and Consequences of Violence against Women: Findings from the National Violence against Women Survey. Natl. Inst. Justice Cent. Dis. Control Prev. 2000, 1–59. Available online: https://www.ojp.gov/pdffiles1/nij/183781.pdf (accessed on 12 July 2021).
- Vest, J.R.; Caitlin, T.K.; Brownson, R.C. Multistate analysis of factors associated with intimate partner violence. Am. J. Prev. Med. 2002, 22, 156–164. [Google Scholar] [CrossRef] [Scilit]
- Bhatt, C.B.; Beck-Sagué, C.M. Medicaid expansion and infant mortality in the United States. Am. J. Public Health 2018, 108, 565–567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guttmacher Institute. Benefits of Contraceptive Use in the United States (Video Transcript). Available online: https://www.guttmacher.org/benefits-contraceptive-use-united-states-video-transcript (accessed on 12 July 2021).
- Thomas, M.P.; Ammann, G.; Brazier, E.; Noyes, P.; Maybank, A. Doula services within a healthy start program: Increasing access for an underserved population. J. Mother Child 2017, 21, 59–64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Granello, D.; Young, M.E. Counseling Today: Foundations of Professional Identity, 2nd ed.; Pearson: Upper Saddle River, NJ, USA, 2019. [Google Scholar]
- Myers, J.E.; Luecht, R.M.; Sweeney, T.J. The factor structure of wellness: Reexamining theoretical and empirical models underlying the wellness evaluation of lifestyle (WEL) and the five-factor wei. Meas. Eval. Couns. Dev. 2004, 36, 194–208. [Google Scholar] [CrossRef] [Scilit]
- Ratts, M.J.; Singh, A.A.; Nassar-McMillan, S.; Butler, S.K.; McCullough, J.R. Multicultural and social justice counseling competencies: Guidelines for the counseling profession. J. Multicult. Couns. Dev. 2016, 44, 28–48. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).