


Abstract
Lung cancer remains the leading cause of cancer-related mortality worldwide and is frequently diagnosed at advanced stages, when metastatic dissemination is already present. Tumour hybrid cells (THCs) are rare circulating cells formed through fusion between cancer stem cells with leukocytes, predominantly monocytes. These cells combine traits from both lineages, conferring enhanced migratory, invasive and immune-evasive capacities that could promote metastasis. In parallel, soluble immune checkpoints (sICs) have emerged as minimally invasive biomarkers and indicators of systemic immune dysregulation and tumour-driven immune escape. In this study, 31 patients with lung cancer were prospectively enrolled at La Paz University Hospital (Madrid, Spain). Circulating THCs were quantified by spectral flow cytometry, and plasma sICs concentrations were determined using multiplex immunoassays. Patients were stratified by metastatic status and survival. Variables showing the strongest discriminative capacity were integrated into multivariable logistic regression models. Number of THCs, and levels of sCTLA-4, s-41BB, sLAG-3, and sTIM-3 exhibited the strongest discrimination for metastasis, while THCs, sLAG-3, and sTIM-3 distinguished deceased from surviving patients. Integrating predictive models demonstrated high accuracy, and survival analyses supported their prognostic significance. These findings indicate circulating THCs and selected sICs represent promising liquid biomarkers for monitoring lung cancer progression and patient outcomes.
1. Introduction
Lung cancer (LC) is the second-most commonly diagnosed malignancy worldwide yet remains the leading cause of cancer-related mortality, responsible for nearly two million deaths each year [1]. Tobacco smoking is recognised as a predominant risk factor, contributing to approximately 85% of all lung cancer cases [2]. Despite notable advancements in diagnosis and therapy, most patients are diagnosed at advanced stages, when metastatic dissemination has already occurred [3]. This late detection profoundly limits therapeutic options and contributes to persistently poor overall survival associated with the disease. As with other solid tumours, metastatic spread accounts for more than 90% of LC-related deaths [4].
The biological mechanisms underlying metastasis remain poorly understood. Classical models emphasise the role of circulating tumour cells (CTCs), which detach from the primary lesion, intravasate into the bloodstream, survive immune attack, and colonise distant organs [4,5]. Several theories have been proposed to explain this process. The “seed and soil” hypothesis suggests that metastatic potential depends on the compatibility between tumour cells (the “seed”) and the target organ microenvironment (the “soil”) [6]. The epithelial-to-mesenchymal transition (EMT) model posits that tumour cells acquire migratory and invasive properties through a transient mesenchymal state, later reverting to an epithelial phenotype to colonise new sites [7,8].
An alternative and increasingly supported hypothesis is the cancer–cell fusion theory, first proposed by Otto Aichel in 1911 [5,9]. This model proposes that metastasis may be driven by tumour hybrid cells (THCs), which are heterogeneous cells formed through the fusion of tumour cells with leukocytes, particularly monocytes or macrophages [9,10]. It has been demonstrated that THCs retain essential leukocyte properties such as migration, chemotaxis, and immune evasion, while preserving the proliferative capacity of tumour cells [11]. Experimental evidence supports this hypothesis: THCs have been detected in both primary tumours and peripheral blood [12], and exhibit enhanced migratory and proliferative capacities compared with their parental cells [13]. Transcriptomic studies further suggest that these hybrids overexpress genes involved in motility, immune escape and metabolic adaptation [13]. Collectively, these findings position THCs as both a potential mechanistic driver of metastasis and a promising biomarker for early dissemination and prognosis [5].
In parallel, the immune system plays a decisive role in tumour evolution, and immune checkpoints (ICs) have emerged as key regulators of immune surveillance [14]. Among the sICs analysed in this study, several exert non-redundant roles in the regulation of T-cell activation and immune tolerance. One such element is CD25, which corresponds to the α-chain of the Interleukin (IL)-2 receptor (IL-2rα). This IC is expressed by activated T cells and regulatory T cells, where it governs IL-2-dependent proliferation and immune tolerance [15,16]. In contrast, PD-L1, LAG-3, TIM-3 and CTLA-4 function as co-inhibitory ICs that restrain T-cell activation through complementary mechanisms, including the inhibition of T-cell receptor and co-stimulatory signalling, the promotion of T-cell dysfunction and immune exhaustion, and the maintenance of peripheral tolerance [14,16]. Tumours frequently exploit co-inhibitory pathways, most notably the PD-L1/PD-1 and CTLA-4 axes, to evade immune detection [17]. Although immune checkpoint blockade (ICB) therapy has revolutionised cancer therapy, eliciting durable responses in certain patients, its efficacy remains limited by resistance mechanisms, heterogeneity in checkpoint expression, immune exhaustion, and the absence of robust predictive biomarkers [18].
Given these challenges, the combined parallel study of tumour hybrid cells and soluble immune checkpoints may offer complementary insights into the intertwined mechanisms of metastasis and immune escape. While THCs may facilitate metastatic spread, sICs can reflect systemic immune dysregulation that promotes tumour persistence [5,14]. The integration of these two biological dimensions could therefore enable the identification of circulating biomarkers with both prognostic and stratification values in lung cancer. Despite the modest sample size and lack of an independent validation cohort, this study underscores the potential of uniting cellular and soluble immune biomarkers to advance our understanding of lung cancer progression and inform precision clinical management.
2. Results
2.1. Description of the Lung Cancer Cohort
To access the prognostic value of soluble immune checkpoints (sICs) and circulating tumour hybrid cells (THCs) in lung cancer (LC), 31 patients were prospectively recruited at the Thoracic Surgery Department of La Paz University Hospital (Madrid, Spain) between 11 March 2020 and 14 April 2023. Circulating THCs and twelve sICs were quantified. Patients were categorised according to key clinical parameters, including tumour histology, anatomical site, TNM classification, disease stage, relapse or progression status, metastatic involvement, prior cancer history, lymphovascular invasion, surgical approach, smoking status, and the presence of comorbid respiratory disease. Most patients were diagnosed at stage I disease, while a minority presented with stage III–IV. The single-stage IV patient underwent surgical intervention for diagnostic purposes, as prior less-invasive procedures had not yielded a definitive histopathological diagnosis. During the 2.5-year follow-up period, five patients experienced relapse or disease progression. Of these, one case had initially been classified as stage I, one as stage II, two as stage III, and one as stage IV disease. Two of these patients (one stage III and one stage IV) died during the follow-up period. Demographic and clinical characteristics of the cohort are summarised in Table 1.
Table 1.
Clinical and demographic information of the patients included in the study. Statistical analysis was done by Mann–Whitney test and Chi-square test.
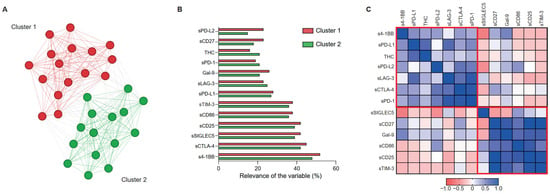
Unsupervised data analysis based exclusively on circulating THCs and sICs levels, with no demographic or clinicopathological variables included, identified two distinct clusters of LC patients (Figure 1A). To facilitate interpretation of cluster formation, the relative relevance of the individual variables contributing to each cluster, as determined by Graphext, is shown in Figure 1B. This analysis revealed differential contributions of soluble immune checkpoint markers between clusters. sPD-1 showed greater relevance in Cluster 2, while sPD-L2 exhibited markedly higher relevance in defining Cluster 1 (Figure 1B). To further support this clustering, correlation mapping across all variables further revealed two coherent groups of immunomodulatory factors (Figure 1C), suggesting shared regulatory or functional relationships. Notably, sCD25, sCD86, and sTIM-3 showed strong positive correlations, forming a tightly correlated immunomodulatory module, whereas sCTLA-4, sPD-L1, and sLAG-3 grouped within an opposing correlation module (Figure 1C).
Figure 1.
Correlation network and clustering of THCs and soluble ICs in patients with lung cancer. (A) Unsupervised clustering of lung cancer cohort (n = 31) based on all experimental variables analysed (sICs and circulating THCs). (B) Relative relevance of circulating THCs and sICs variables contributing to cluster definition. (C) Correlation matrix illustrating Pearson correlation coefficients between the levels of individual and the presence of circulating THCs. The colour scale represents the strength and direction of correlation (red: negative; blue: positive correlation), and clusters are delineated in red.
2.2. Immune Profiling Identifies a Four-Parameter Model Associated with Metastatic Progression in Lung Cancer
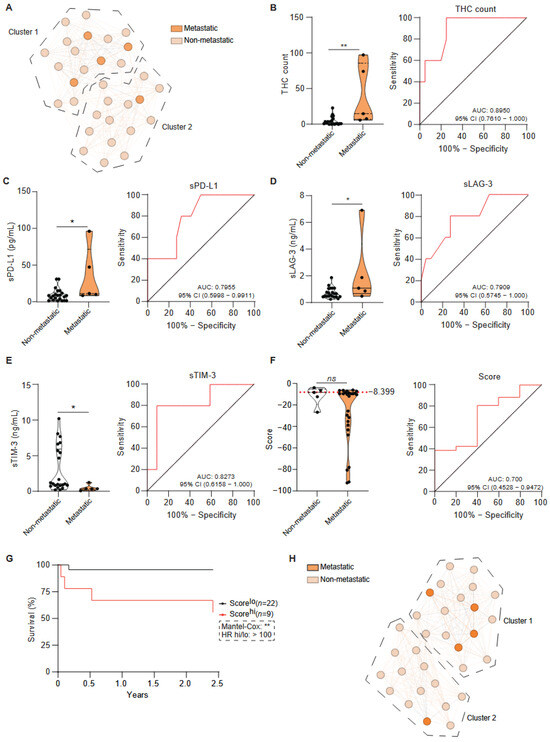
Using the same patient clustering obtained in Figure 1A, metastatic status was overlaid to evaluate their distribution across clusters; however, this unsupervised framework did not discriminate metastatic from non-metastatic patients (Figure 2A). Survival analyses were restricted to a 2.5-year follow-up period, as all observed deaths occurred within this interval. Among metastatic cases, the single individual located within Cluster 1 exhibited clinical and demographic features comparable to the remaining metastatic patients, except for a greater burden of pre-existing pulmonary disease, including COPD, obstructive sleep apnoea, and prior pulmonary thromboembolism. No additional distinguishing clinical variables were identified.
Figure 2.
Multivariate predictive modelling of metastasis in patients with lung cancer. (A) Unsupervised UMAP representation of the lung cancer cohort stratified by metastatic status (metastatic: dark orange, non-metastatic: light orange) using all experimental variables (sICs and THCs). Dashed lines correspond to clusters identified in Figure 1A. (B–E) Circulating THC counts (B) and plasma levels of sPD-L1 (C), sLAG-3 (D), sTIM-3 (E) in lung cancer patients categorised as non-metastatic and metastatic. The right panels of (B–E) show receiver operating characteristic (ROC) curves for each individual parameter with the corresponding area under the curves (AUC) and their 95% confidence intervals (CI). Parameters meeting both suggestive statistical significance (p ≤ 0.20) and acceptable discriminatory performance (AUC ≥ 0.70) were retained as potential predictors. (F) These variables were included in a binary logistic regression model (Backward Wald method) to generate a composite metastasis score. The optimal classification threshold, defined by the Youden index, is indicated by the dashed line. The right panel of (F) displays the ROC curve assessing the predictive accuracy of the model. (G) Kaplan–Meier survival analysis according to the metastasis score. (H) Clustering of lung cancer patients based on their metastasis score, coloured by metastasis status (metastatic: dark orange, non-metastatic: light orange). In the left panels of (B–F), each dot represents an individual patient. Data are presented as violin plots; statistical comparison between groups were performed using the Mann–Whitney t-test was used to compare the difference between groups. Abbreviations: AUC; area under the curve, CI; confidence interval. Statistical significance: ** p < 0.01 and * p < 0.05.
Direct comparison between metastatic and non-metastatic groups revealed significantly higher THC counts in metastatic patients (Figure 2B). Among soluble markers, levels of sPD-L1 and sLAG-3 were markedly increased in the metastatic subgroup (Figure 2C,D). Conversely, sTIM-3 concentrations were significantly lower in metastatic patients (Figure 2E). No significant differences were detected for s4-1BB, sCD25, sCTLA-4, Galectin-9, sCD27, sPD-1, sPD-L2, sSIGLEC5 or sCD86 (Supplementary Figure S1).
To further assess the prognostic value of these parameters for metastatic progression, variables with a receiver operating characteristic (ROC) area under the curve (AUC) above 0.7 were included in a binary logistic regression model with backward stepwise selection. This included statistically significant parameters (Figure 2B–E), as well as variables with an AUC value above 0.7 that did reach statistical significance (Supplementary Figure S1A–D). These variables were considered for their potential to improve the performance of the multivariate model (Supplementary Figure S1A–C).
After iterative removal of non-informative predictors, the final model retained five —THC count, CTLA-4, s4-1BB, sTIM-3, and sLAG-3— as the optimal predictors of metastasis. The resulting composite score demonstrated potential discriminatory power, with an optimal cut-off value of −8.399 (Youden index) and an AUC of 0.70 (95% CI: 0.4528–0.9427; p > 0.05; Figure 2F) with a sensitivity of 80.77% and a specificity of 60% at this threshold. Kaplan–Meier survival analysis confirmed that higher immune scores were significantly associated with reduced metastasis-free survival (Figure 2G). Furthermore, a UMAP projection that used only the variables that made up the composite score showed two distinct patient groups, with metastatic patients appearing more closely distributed than in the initial unsupervised model (Figure 2H). Notably, the outlier in this model did not correspond to that observed in Figure 2A, and no consistent clinical or demographic features distinguished the clusters generated.
2.3. Predictive Modelling of Survival Based on Circulating and Soluble Immune Markers
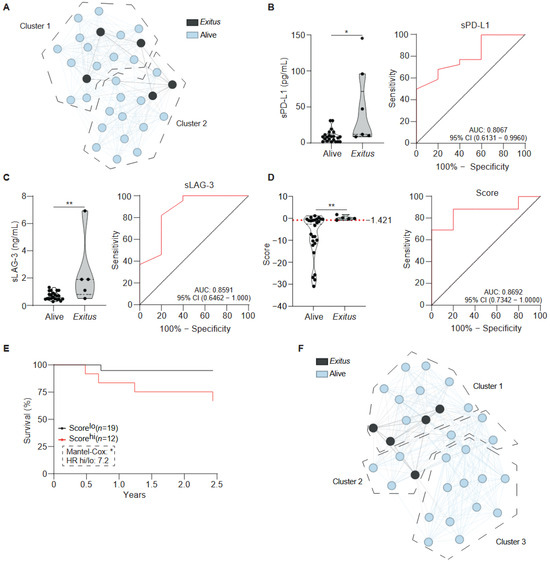
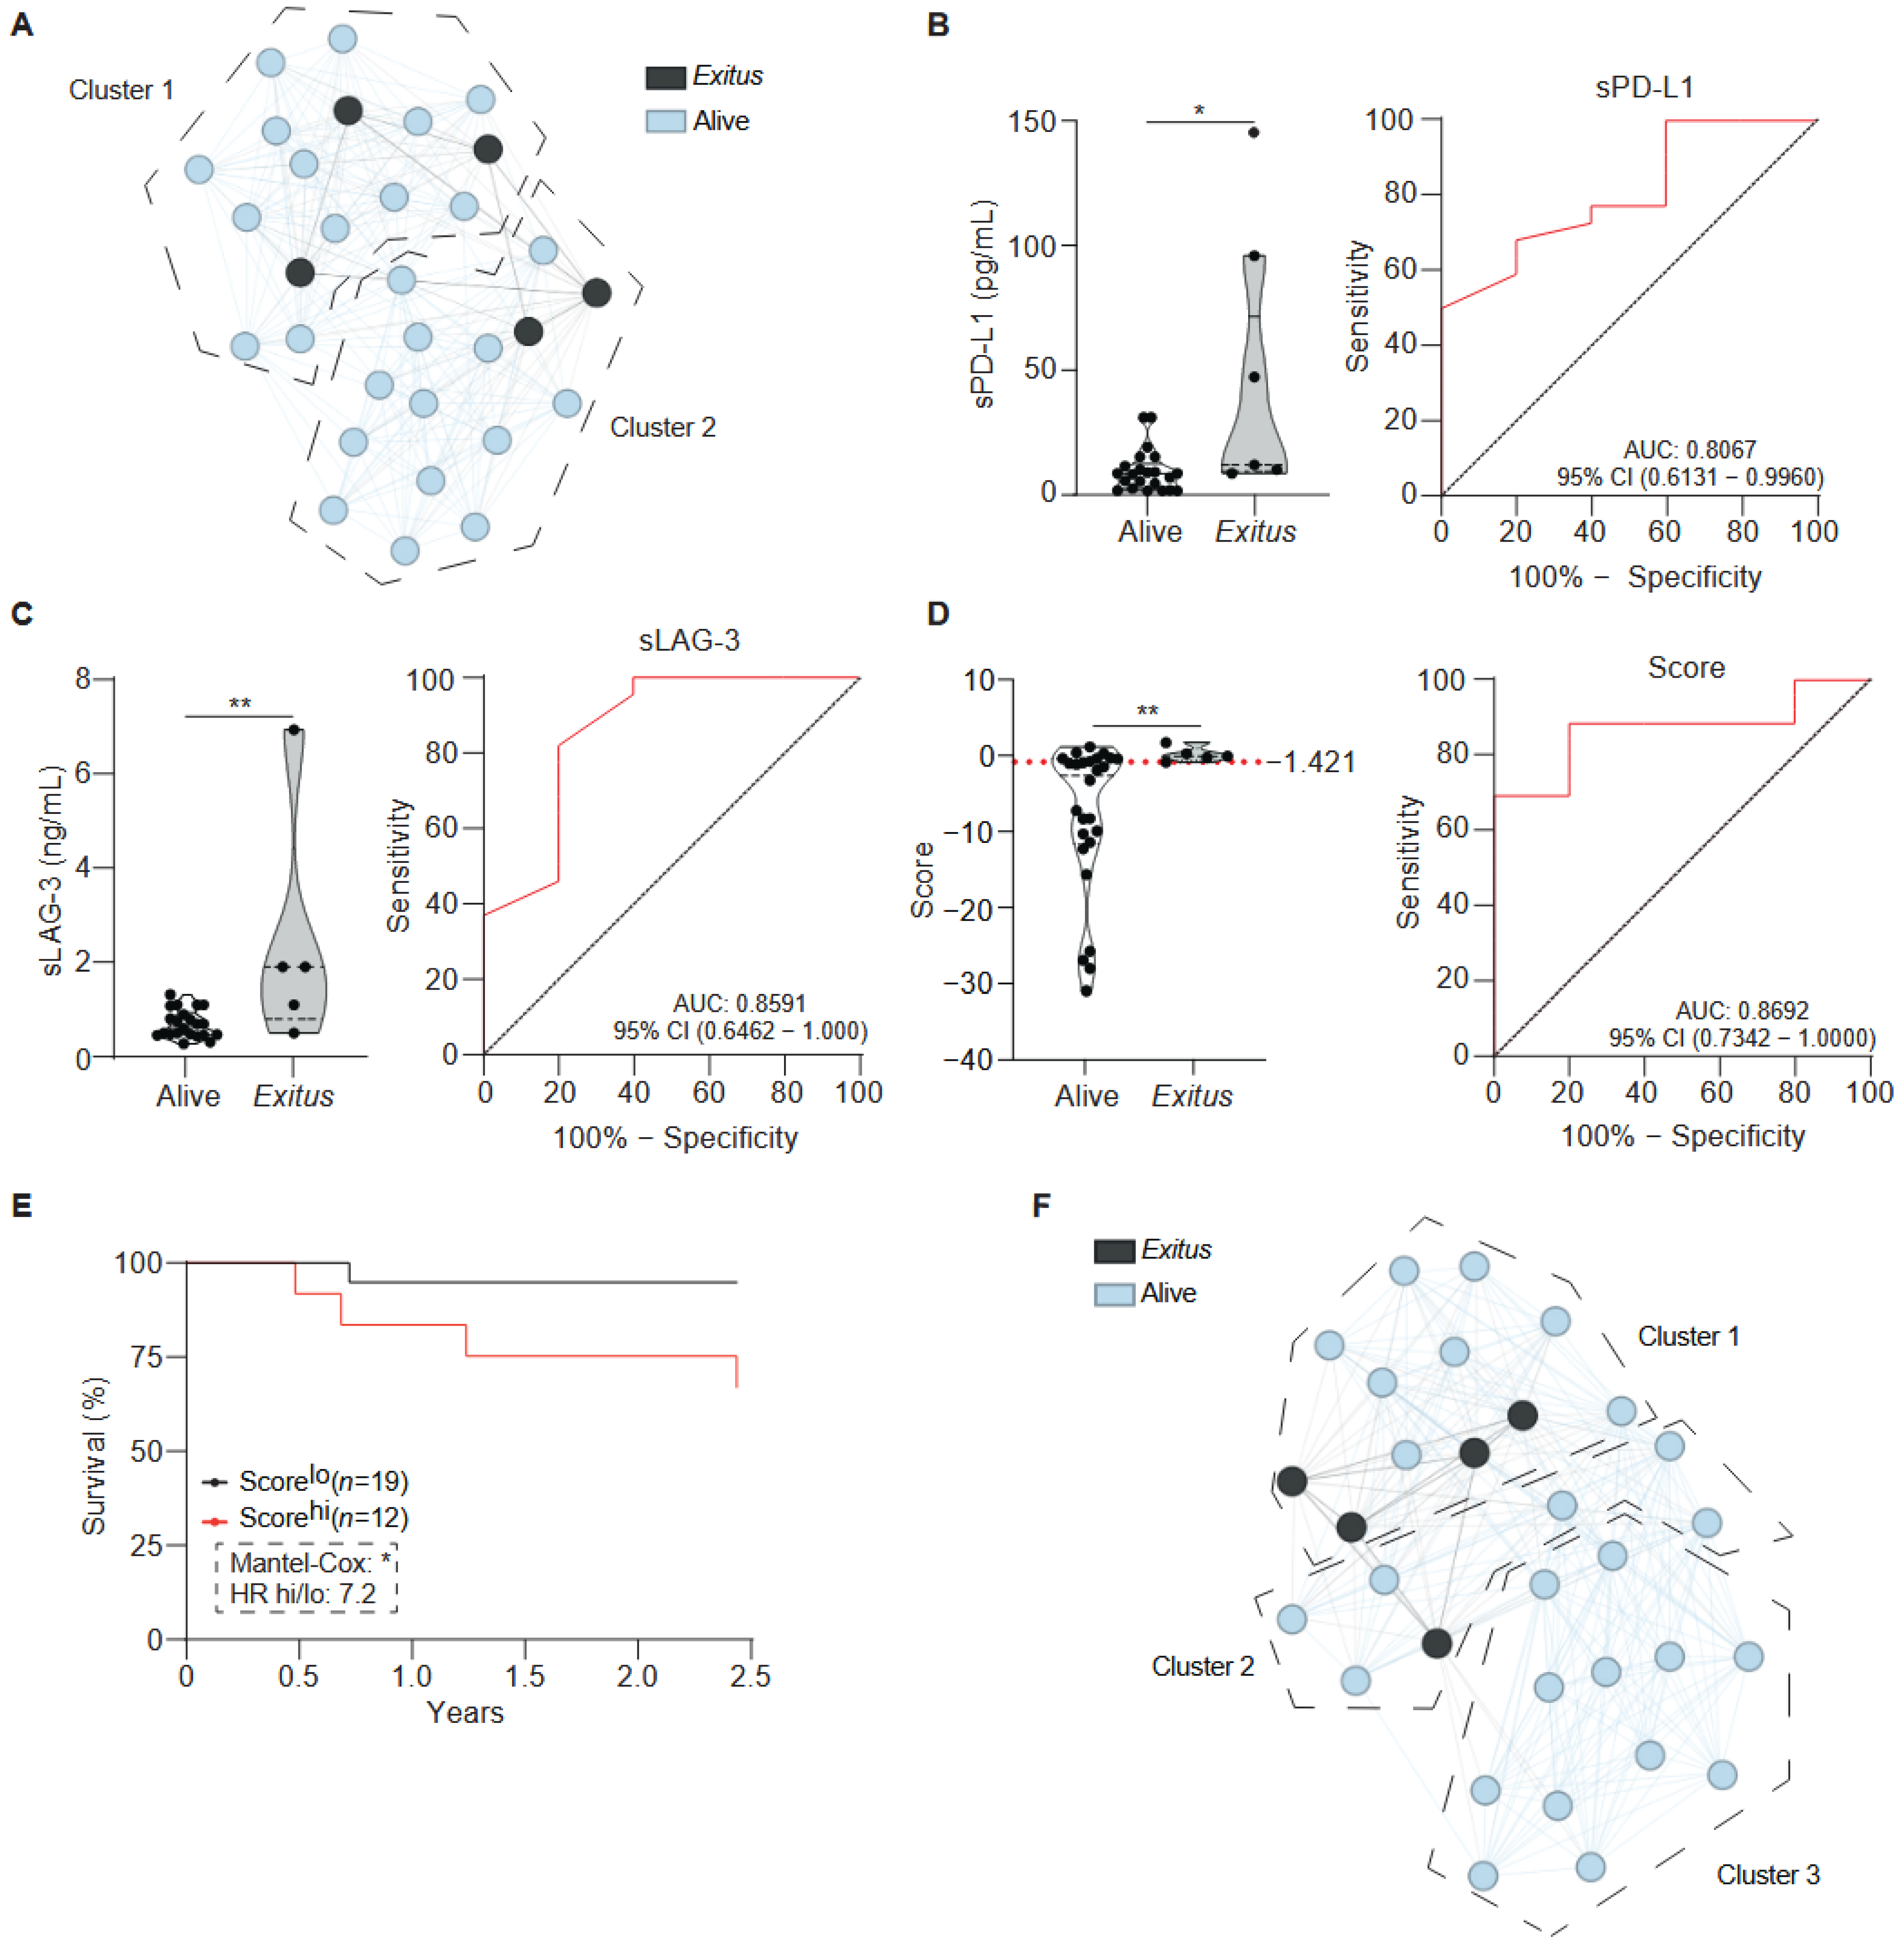
To explore the prognostic relationship between the circulating THCs, soluble markers, and overall survival, patients were monitored for up to 2.5 years of follow-up. The same analytical strategy was applied. As observed for the metastatic subgroups, unsupervised clustering did not differentiate alive (n = 28) from exitus (n = 5), and no clinical or demographic characteristics distinguished non-survivor individuals assigned to the different clusters (Figure 3A).
Figure 3.
Predictive modelling of survival outcomes in patients with lung cancer. (A) Unsupervised UMAP representation of the lung cancer cohort categorised by mortality (exitus: dark grey, alive: light blue) using all experimental variables (sICs and THCs). The dashed lines correspond to identified in Figure 1A. (B,C) Plasma levels of s-L1 (B) and sLAG-3 (C) in lung cancer patients. The right panels of (B,C) display ROC curves for each parameter with their respective AUC values and their 95% CI. Parameters showing both suggestive statistical significance (p = ≤0.05 to 0.2) and strong discriminatory ability (AUC ≥ 0.7) were selected as candidate predictors. (D) These variables were incorporated into a binary logistic regression model (Backward Wald method) to derive a composite mortality score. The optimal classification threshold determined by the Youden index is indicated by the dashed line. The right panel of (D) shows the ROC curve assessing model performance. (E) Kaplan–Meier survival analysis according to the mortality score. (F) Clustering of lung cancer patients based on the mortality score, coloured by survival status (exitus: dark grey; alive: light blue). In the left panels of (B–D), each dot represents an individual patient. Data are displayed as violin plots; statistical comparison between groups was performed using the Mann–Whitney t-test. Abbreviations: AUC; area under the curve, CI; confidence interval. Statistical significance: ** p < 0.01 and * p < 0.05.
Comparative analysis revealed that sPD-L1 and sLAG-3 levels were significantly elevated in the individuals who deceased (Figure 3B,C). THC counts, sTIM-3, and sCD25 approached statistical significance (Supplementary Figure S2A–C), with THC counts showing a trend towards higher values in exitus, whereas sTIM-3 and sCD25 tended to be higher in the alive. No significant differences were observed for sCTLA-4, sSIGLEC5, sCD86, sPD-L2, sCD27, sPD-1, Galectin-9 and s4-1BB (Supplementary Figure S2D–K).
Variables exhibiting an AUC above 0.7 were included in a binary logistic regression model with backward stepwise selection to identify predictors of survival. The final model incorporated three key parameters—THC count, sLAG-3 and sTIM-3— which collectively defined a survival-associated immune profile (Figure 3D). ROC analysis confirmed the robustness of this model, yielding an AUC of 0.8692 (95% CI: 0.7342–1.0000; p < 0.01 **; Figure 3D). The optimal cut-off value, determined by the Youden index, was −1.421, with a sensitivity of 69.23% and a specificity of 100% at this threshold.
3. Discussion
Despite considerable therapeutic advances, lung cancer (LC) remains associated with poor prognosis, largely due to delayed diagnosis, early metastatic dissemination, and therapeutic resistance [19,20]. The introduction of immunotherapy with immune checkpoint inhibitors (ICIs) has improved survival in selected patients; however, a substantial proportion derive limited or no clinical benefit, underscoring the urgent need for robust prognostic biomarkers capable of capturing tumour aggressiveness and immune escape beyond conventional staging and histopathology [21,22].
The primary objective of this study was to investigate whether circulating immune-related biomarkers, specifically soluble immune checkpoints (sICs) and tumour hybrid cells (THCs), could provide prognostic information in lung cancer. Patients were stratified according to metastatic progression and survival over a 2.5-year follow-up period, enabling the identification of biomarkers associated with both disease dissemination and clinical outcome.
The PD-1/PD-L1 axis represents a central mechanism of tumour-mediated immune evasion [23]. PD-1, also known as CD279, is an inhibitory receptor expressed on activated T cells, B cells, Natural Killer (NK) cells and antigen-presenting cells (APCs), where it limits immune activation [24]. Its ligand, PD-L1 (B7-H1), is induced under inflammatory conditions and is frequently upregulated on tumour cells, allowing them to suppress antitumour T-cell activity through PD-1 engagement [25]. This interaction has been shown to inhibit T-cell proliferation, cytokine release and cytotoxic function, thereby promoting an immunosuppressive microenvironment that favours tumour progression [26]. In lung cancer, PD-L1 expression has been correlated with advanced disease stages, smoking history, and a poor prognosis for patients [27]. In our cohort, soluble PD-L1 (sPD-L1) levels were significantly higher in patients with metastatic disease and in non-survivors. These findings support the notion that circulating PD-L1 reflects a systemic immunosuppressive state associated with aggressive tumour biology. Importantly, the heterogeneous clinical response to PD-1/PD-L1 blockade highlights the limitations of relying on a single immune checkpoint as a prognostic or predictive marker [28,29], reinforcing the value of multiplex immune profiling.
Similarly, soluble LAG-3 (sLAG-3) was markedly increased in metastatic patients and non-survivors. LAG-3 is a key inhibitory receptor expressed on activated T cells and plasmacytoid dendritic cells, where it promotes T-cell exhaustion and immune suppression through engagement with ligands such as FGL1 and Galectin-3 [30,31,32]. Previous studies have reported LAG-3–positive tumour-infiltrating lymphocytes in both NSCLC and SCLC, often correlating with aggressive tumour features and poor outcome [33,34]. Moreover, lung adenocarcinoma patients with higher numbers of LAG-3+ positive cells correlated with features of aggressive tumour characteristics [35]. Our findings extend these observations to the systemic level, suggesting that sLAG-3 may serve as a circulating marker of advanced immune dysfunction [31,36].
In contrast to sPD-L1 and sLAG-3, soluble TIM-3 (sTIM-3) was elevated in non-metastatic patients and alive individuals, indicating a distinct immunological role. TIM-3 is expressed across multiple immune compartments and participates in both immune activation and regulation depending on disease stage [37,38,39,40]. Notably, recent spatial and single-cell analyses have shown TIM-3 enrichment in early lung adenocarcinoma lesions, suggesting a role in initial immune modulation rather than terminal exhaustion [41]. This contrasts with the case of advanced tumours, where membrane-bound TIM-3 on TILs has been found to correlate with metastasis and poor survival [42,43]. This is consistent with our observation that higher sTIM-3 levels predominated in early-stage, non-metastatic survivors. Together, these findings highlight that the prognostic value of immune checkpoints is context-dependent and stage-specific.
Importantly, soluble immune checkpoints are not merely passive biomarkers: they retain biological activity and can actively modulate immune signalling by engaging cognate receptors and ligands [32,39]. Within this context, CTLA-4 represents a central regulator of early T-cell activation, acting upstream of PD-1–mediated inhibition by limiting CD28-dependent co-stimulatory signalling. Consistent with its role in the regulation of early T-cell activation, CTLA-4 has been established as a clinically relevant therapeutic target for immune checkpoint blockade, including in lung cancer [44,45].
Beyond immune checkpoints, a major strength of this study is the integration of tumour hybrid cells (THCs) into the prognostic framework. We demonstrate that circulating THCs are significantly increased in patients with metastatic disease and in non-survivors, strongly implicating these cells in aggressive clinical behaviour. THCs arise through tumour–leukocyte fusion, a process that confers both malignant traits (genomic instability, proliferative capacity) and leukocyte-derived properties such as enhanced motility, immune evasion, and tissue tropism [5,46,47]. This hybrid phenotype provides a compelling biological explanation for their heightened invasive and metastatic potential.
Consistent with our findings, fusion-derived hybrid cells have been reported in multiple malignancies, including melanoma, colorectal cancer, and breast cancer, where their presence correlates with metastatic spread and poor survival [48,49,50]. Importantly, THCs have been shown to upregulate immune checkpoints such as PD-L1, SIGLEC5 and CTLA-4, further facilitating immune escape [49,51,52,53]. The concurrent increase in THCs and immunosuppressive sICs observed in our cohort suggests a relationship between tumour dissemination capacity and systemic immune suppression.
Taken together, our data indicate that THCs and sICs capture two complementary dimensions of tumour progression. THCs reflect the tumour’s intrinsic ability to disseminate physically, while sICs could mirror a permissive immunological environment that enables metastatic outgrowth. Their co-detection may therefore define a “pro-metastatic state”, characterised by both enhanced migratory competence and impaired immune surveillance.
Although this study is limited by a relatively small cohort size, this limitation is mitigated by the depth of immune profiling and the longitudinal clinical follow-up. The consistency of associations across metastatic status and survival outcomes strengthens the robustness of our conclusions. Importantly, both THCs and sICs can be quantified from peripheral blood, highlighting their potential as minimally invasive biomarkers suitable for repeated monitoring.
From a translational perspective, the integration of THCs and sICs could support personalised medicine by identifying patients at higher risk of early metastasis or poor survival who may benefit from intensified surveillance, combination immunotherapies, or early systemic intervention. Future studies should focus on validating these findings in larger, independent cohorts, integrating THC and sIC profiling with tumour genomics, immune infiltration patterns, and treatment response. Phenotypic and functional characterisation of THCs, alongside longitudinal immune monitoring, will be essential to establish their clinical utility.
4. Materials and Methods
4.1. Participant Recruitment and Eligibility Criteria
Peripheral blood samples were obtained from patients with lung cancer (LC, n = 31) recruited at the Thoracic Surgery Service of La Paz University Hospital (Madrid, Spain) prior to surgery. All patients had a histologically confirmed diagnosis of LC prior to enrolment, were evaluated in the outpatient clinic, and subsequently reviewed by the hospital’s multidisciplinary Lung Tumour Committee.
The inclusion criteria were based on a histopathological diagnosis of primary non-small cell lung cancer (specifically adenocarcinoma and squamous cell carcinoma) in patients requiring diagnostic or therapeutic surgical intervention by the Thoracic Surgery Department at University Hospital La Paz. Furthermore, eligible participants were required to have provided written informed consent for both biobank storage and the collection of peripheral blood samples during routine follow-up prior to surgery.
Patients were excluded from the study if they presented with benign lesions, secondary lung metastases, or pulmonary neuroendocrine tumours. Furthermore, exclusion was applied to patients whose clinical status, such as those in palliative care or elderly patients with mobility issues, prevented sample collection without exceeding the standard of care. Finally, patients receiving postoperative follow-up at external healthcare facilities were excluded to prevent redundant clinical visits and unnecessary blood draws.
Blood samples were collected and processed within 24 h prior to surgical intervention. Detailed clinical and demographic information for this cohort is provided in Table 1.
4.2. Clinical Definitions
The following clinical definitions were applied to ensure consistent classification of disease status and outcomes throughout the study.
Metastasis was defined as the dissemination of neoplastic cells to organs different from the primary tumour site, as confirmed by clinical and radiological assessment, during follow-up (e.g., lymph nodes, bone, contralateral lung, or other distant organs). Relapse was defined as the reappearance of neoplastic disease after a documented period of clinical, radiological, and/or analytical remission following initial treatment (surgery, chemotherapy, radiotherapy and/or immunotherapy). The progression of the disease was defined as a deterioration in the patient’s condition during the follow-up period, as evidenced by the enlargement of existing tumours and/or the emergence of new metastatic lesions, in the absence of a prior interval without disease. The term “exitus” was defined as death from any cause during the follow-up period.
4.3. Plasma Collection
Plasma was isolated from EDTA-anticoagulated venous blood either by density gradient centrifugation using Ficoll-Plus solution (GE Healthcare BioSciences, Uppsala, Sweden) or by centrifugation at 3000 rpm for 15 min. The plasma fraction was aliquoted and stored at −80 °C until analysis. Prior to use, samples were thawed at 4 °C and clarified by centrifugation at 15,000× g for 10 min to remove residual cellular debris.
4.4. Detection of Soluble Immune Checkpoints
Plasma concentrations of soluble immune checkpoints (sICs) were quantified using the LegendPlex™ (BioLegend, San Diego, CA, USA, catalogue number 740867) following the manufacturer’s instructions. The panel 1 included: sCD25, s4-1BB, sCD27, sCD86, TGF-β1 (free active form), sCTLA-4, sPD-L1, sPD-L2, sPD-1, sTIM-3, sLAG-3, and Galectin-9. Prepared samples were acquired on a FACS Calibur flow cytometer (BD Biosciences, Franklin Lakes, NJ, USA), and data were analysed using LegendPlex software (v.8, BioLegend, San Diego, CA, USA).
4.5. Enzyme-Linked Immunosorbent Assay (ELISA)
Soluble SIGLEC5 levels in plasma were measured using a Human SIGLEC5 ELISA kit (Invitrogen, Carslbad, CA, USA, Cat No. EHSIGLEC5) in accordance with the manufacturer’s protocol. Absorbance was read at 450 nm using an Epoch™ microplate reader (BioTek, Instruments, Winooski, VT, USA).
4.6. Sample Processing and Full-Spectrum Flow Cytometry
Whole blood samples were collected in EDTA (ethylenediaminetetraacetic acid anticoag-ulated) tubes (Vacuette®, Greiner Bio One, Kremsmünster, Austria). Red blood cell lysis was performed using BD PharmLyse™ Lysing Buffer (BD Biosciences, Franklin Lakes, NJ, USA), yielding a leuko-cyte cell suspension, which was washed twice with phosphate-buffered saline (PBS). Cell viability was assessed using LIVE/DEAD™ Fixable Blue dye (Invitrogen, Carslbad, CA, USA). Subsequently, cells were incubated with an antibody panel detailed in Supplementary Table S1. The staining panel was designed to measure circulating tumour hybrid cells, gated as the CD14+ population expressing EpCAM+ and CD45+ and non-expressing CD3−, CD56−, CD16−, CD19- and CD1c−, as shown in Supplementary Figure S3.
4.7. Statistical Analysis and Bioinformatic Processing
All statistical analyses and graphical representation were performed using GraphPad Prism 10.3.1 (GraphPad Software, Inc., San Diego, CA, USA). Outliers were identified and excluded using the ROUT method (Q = 1%). Data normality was assessed by the Shapiro–Wilk test. Results are presented as violin plots displaying median values and interquartile ranges (IQRs). For two-group comparisons, the Mann–Whitney U test was used in non-parametric data, and the unpaired t-test was applied for parametric data.
Binary logistic regression models were constructed using the backward Wald method with IBM SPSS Statistics v.23 software (IBM Corp, Armonk, NY, USA). This stepwise approach begins with the full set of candidate independent variables and repeatedly removes them based on their statistical significance. For each variable included in the final model, a corresponding coefficient (B-factor) was calculated to reflect its impact on the differentiation between groups. The final scores were obtained using the following formula: Score = ([Parameter A] × B-factor A) + ([Parameter B] × B-factor B) + … + ([Parameter X] × B-factor X), as previously described [54,55]. Classifying scores were used to construct receiver operating characteristic (ROC) curves, where the area under the curve (AUC) and optimal cut-off values were obtained as the Youden index. The objective of selecting the most appropriate regression model was to identify a minimal number of variables while ensuring the retention of those exhibiting the greatest statistical significance.
Kaplan–Meier survival analyses were performed using Microsoft Office Excel and Kaplan–Meier Plotter web page (version 2025.06.16). For unsupervised data exploration, including Uniform Manifold Approximation and Projection (UMAP) visualisation and hierarchical clustering, Graphext (Madrid, Spain) was employed. Parameters were set as follows: Euclidean metrics, n_neighbours = 30, 127 n_components = 10 and min_dist = 0.01. The number of clusters was automatically determined by the algorithm based on variable strength.
Statistical significance was defined as follows: p > 0.05, not significant (ns); *, p < 0.05; **, p < 0.01; ***, p < 0.001; and ****, p < 0.0001.
5. Conclusions
This study provides evidence that the combined assessment of circulating tumour hybrid cells and soluble immune checkpoints offers a powerful, minimally invasive approach to prognostic stratification in lung cancer. By capturing both tumour plasticity and immune suppression, this dual biomarker strategy opens new avenues for understanding metastatic progression and tailoring precision oncology strategies.
6. Clinical Implications
The identification of circulating THCs and sICs as complementary prognostic biomarkers has direct clinical relevance for the management of lung cancer. As both parameters can be quantified from peripheral blood, they offer a minimally invasive approach to risk stratification that may complement conventional staging and tissue-based biomarkers. The co-detection of elevated THCs and immunosuppressive sICs could identify patients in a pro-metastatic state, characterised by enhanced tumour dissemination and impaired immune surveillance, who may benefit from closer clinical monitoring, early systemic intervention, or combination immunotherapeutic strategies. Moreover, integrating THC and sIC profiling into longitudinal patient follow-up may enable dynamic assessment of disease evolution and treatment response, supporting more personalised and adaptive therapeutic decision-making in lung cancer care.
7. Limitations of the Study
It is important to note that the present study is subject to certain limitations, which must be considered when interpreting the results. The cohort size was modest, with 31 patients included, which limits statistical power and may increase the risk of overfitting in the predictive models, particularly in complex models such as those applied in this study. Moreover, the single-centre design restricts the generalisability of the findings, as population characteristics, clinical management, and laboratory conditions may differ across institutions. Another important limitation is the absence of an independent validation cohort, meaning the logistic regression models should be regarded as exploratory and require external confirmation in larger, multicentre datasets. The heterogeneity of tumour histology, clinical stages, comorbidities and treatments within the cohort introduces biological variability that may influence both THC counts and sIC levels, although this reflects real-world clinical practice. Furthermore, all biomarkers were measured at a single pre-surgical time point, thereby preventing the analysis of temporal dynamics or treatment-related changes in THC or sIC profiles. In addition, the cellular sources of the analysed sIC were not characterised, which limits the interpretation of the mechanisms involved, since these circulating factors may originate from multiple tumour and immune cell compartments. Consequently, further mechanistic work is required to elucidate the biological pathways connecting tumour–immune fusion events with systemic immune dysregulation.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ijms27041994/s1.
Author Contributions
E.L.-C. and L.H.-N. designed, conceived and supervised the study. E.L.-C. provided fundings. S.L.P.-P. and M.E.C.-R. recruited the study populations. G.S.d.S.M.-D., D.A.-R., V.T.-A., K.M.-H., J.d.P.-M. and G.C.B.-P. performed the experimental work. G.S.d.S.M.-D., L.H.-N. and E.L.-C. analysed the data, interpreted results, conceived the experiments, and prepared the figures and paper writing. C.d.F., R.L.-R., J.F.-F., L.C., U.A.-L. and E.L.-C. contributed to data interpretation and critical review of the manuscript. All authors have reviewed and edited the output and take full responsibility for the content of this publication. All authors have read and agreed to the published version of the manuscript.
Funding
This work was funded by the PT20/00004 and PI21/00869 grants to E.L.-C. (ISCIII, Madrid, Spain). C.d.F. is funded by Instituto de Salud Carlos III (ISCIII) through the projects CP20/00106, PI21/01178, and PI24/01106 and co-funded by the European Union. L.H.-N. is funded by Instituto de Salud Carlos III (CD25/00102-Sara Borrell 2025).
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Committee for Human Subjects of La Paz University Hospital (HULP: PI-3521, 4 March 2019) and the Clinical Research Ethics Committees of the Hospitals of Madrid (17.10.1125-GHM, 4 February 2019) was provided for all participants.
Informed Consent Statement
Written and informed consent has been obtained from all participants to publish this paper, and all authors have given their approval for the publication of this final version of the manuscript.
Data Availability Statement
No datasets were generated or analysed during the current study. All data relevant to the study are included in the article or uploaded as Supplementary Information and are available from the corresponding author on reasonable request.
Acknowledgments
We would like to thank the entire research team of the Immune Response group and the Tumour Immunology laboratory at IdiPAZ for comments and suggestions throughout the development of this project.
Conflicts of Interest
L.H.-N. is co-founder and has shares in Viva in vitro diagnostics SL but declares that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest. The remaining authors declare no competing interests.
Abbreviations
| AUC | Area under the curve |
| CD | Cluster of differentiation |
| CTC | Circulating tumour cell |
| EMT | Epithelial-to-mesenchymal transition |
| IC | Immune checkpoint |
| ICI | Immune checkpoint inhibitor |
| IL | Interleukin |
| IFN | Interferon |
| LC | Lung cancer |
| THC | Tumour hybrid cell |
| TNF | Tumour necrosis factor |
References
- Zhou, J.; Xu, Y.; Liu, J.; Feng, L.; Yu, J.; Chen, D. Global Burden of Lung Cancer in 2022 and Projections to 2050: Incidence and Mortality Estimates from GLOBOCAN. Cancer Epidemiol. 2024, 93, 102693. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Cancer Research—Lung Cancer. Available online: https://www.wcrf.org/preventing-cancer/cancer-types/lung-cancer/#what-causes-lung-cancer (accessed on 24 November 2025).
- González, J.; de Castro, F.; Barrueco, M.; Cordovilla, R.; Fernández, J.; Gómez, F.; Moreno de Vega, B.; Ramos, J.; Serrano, A. Delays in the Diagnosis of Lung Cancer. Arch. Bronconeumol. 2003, 39, 437–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fares, J.; Fares, M.Y.; Khachfe, H.H.; Salhab, H.A.; Fares, Y. Molecular Principles of Metastasis: A Hallmark of Cancer Revisited. Signal Transduct. Target. Ther. 2020, 5, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Collazo, E.; Hurtado-Navarro, L. Cell Fusion as a Driver of Metastasis: Re-Evaluating an Old Hypothesis in the Age of Cancer Heterogeneity. Front. Immunol. 2025, 16, 1524781. [Google Scholar] [CrossRef] [Scilit]
- Akhtar, M.; Haider, A.; Rashid, S.; Al-Nabet, A.D.M.H. Paget’s “Seed and Soil” Theory of Cancer Metastasis: An Idea Whose Time Has Come. Adv. Anat. Pathol. 2019, 26, 69–74. [Google Scholar] [CrossRef] [Scilit]
- Pastushenko, I.; Brisebarre, A.; Sifrim, A.; Fioramonti, M.; Revenco, T.; Boumahdi, S.; Van Keymeulen, A.; Brown, D.; Moers, V.; Lemaire, S.; et al. Identification of the Tumour Transition States Occurring during EMT. Nature 2018, 556, 463–468. [Google Scholar] [CrossRef] [Scilit]
- Diepenbruck, M.; Christofori, G. Epithelial-Mesenchymal Transition (EMT) and Metastasis: Yes, No, Maybe? Curr. Opin. Cell Biol. 2016, 43, 7–13. [Google Scholar] [CrossRef] [Scilit]
- Aichel, O. Vorträge Und Aufsätze Über Entwickelungsmechanik Der Organismen. In Über Zellverschmelzung mit Qualitativ Abnormer Chromosomenverteilung als Ursache der Geschwulstbildung; Wilhelm Engelmann: Leipzig, Germany, 1911. [Google Scholar]
- Laberge, G.S.; Duvall, E.; Haedicke, K.; Pawelek, J. Leukocyte–Cancer Cell Fusion—Genesis of a Deadly Journey. Cells 2019, 8, 170. [Google Scholar] [CrossRef] [Scilit]
- Jiang, C.; Wu, J. Hypothesis: Hematogenous Metastatic Cancer Cells of Solid Tumors May Disguise Themselves as Memory Macrophages for Metastasis. Front. Oncol. 2024, 14, 1412296. [Google Scholar] [CrossRef] [Scilit]
- Whalen, R.M.; Anderson, A.N.; Jones, J.A.; Sims, Z.; Chang, Y.H.; Nederlof, M.A.; Wong, M.H.; Gibbs, S.L. Ultra High Content Analyses of Circulating and Tumor Associated Hybrid Cells Reveal Phenotypic Heterogeneity. Sci. Rep. 2024, 14, 7350. [Google Scholar] [CrossRef] [Scilit]
- Anderson, A.N.; Conley, P.; Klocke, C.D.; Sengupta, S.K.; Pang, A.; Farley, H.C.; Gillingham, A.R.; Dawson, A.D.; Fan, Y.; Jones, J.A.; et al. Detection of Neoplastic-Immune Hybrid Cells with Metastatic Properties in Uveal Melanoma. Biomark. Res. 2024, 12, 67. [Google Scholar] [CrossRef] [Scilit]
- He, X.; Xu, C. Immune Checkpoint Signaling and Cancer Immunotherapy. Cell Res. 2020, 30, 660–669. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shouse, A.N.; LaPorte, K.M.; Malek, T.R. Interleukin-2 Signaling in the Regulation of T Cell Biology in Autoimmunity and Cancer. Immunity 2024, 57, 414–428. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rezazadeh-Gavgani, E.; Majidazar, R.; Lotfinejad, P.; Kazemi, T.; Shamekh, A. Immune Checkpoint Molecules: A Review on Pathways and Immunotherapy Implications. Immun. Inflamm. Dis. 2025, 13, e70196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, P.; Tang, L.; Zhou, B.; Cheng, L.; Zhao, R.C.; Zhang, J. Analytical Methods for the Detection of PD-1/PD-L1 and Other Molecules Related to Immune Checkpoints. TrAC Trends Anal. Chem. 2022, 146, 116505. [Google Scholar] [CrossRef] [Scilit]
- Sharma, P.; Goswami, S.; Raychaudhuri, D.; Siddiqui, B.A.; Singh, P.; Nagarajan, A.; Liu, J.; Subudhi, S.K.; Poon, C.; Gant, K.L.; et al. Immune Checkpoint Therapy—Current Perspectives and Future Directions. Cell 2023, 186, 1652–1669. [Google Scholar] [CrossRef] [Scilit]
- Vicidomini, G. Current Challenges and Future Advances in Lung Cancer: Genetics, Instrumental Diagnosis and Treatment. Cancers 2023, 15, 3710. [Google Scholar] [CrossRef] [Scilit]
- Lahiri, A.; Maji, A.; Potdar, P.D.; Singh, N.; Parikh, P.; Bisht, B.; Mukherjee, A.; Paul, M.K. Lung Cancer Immunotherapy: Progress, Pitfalls, and Promises. Mol. Cancer 2023, 22, 40. [Google Scholar] [CrossRef] [Scilit]
- Wang, J.; Seebacher, N.; Shi, H.; Kan, Q.; Duan, Z. Novel Strategies to Prevent the Development of Multidrug Resistance (MDR) in Cancer. Oncotarget 2017, 8, 84559–84571. [Google Scholar] [CrossRef] [Scilit]
- Villadolid, J.; Amin, A. Immune Checkpoint Inhibitors in Clinical Practice: Update on Management of Immune-Related Toxicities. Transl. Lung Cancer Res. 2015, 4, 560–575. [Google Scholar] [CrossRef] [Scilit]
- Patsoukis, N.; Wang, Q.; Strauss, L.; Boussiotis, V.A. Revisiting the PD-1 Pathway. Sci. Adv. 2020, 6, eabd2712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, X.; Kang, K.; Chen, P.; Zeng, Z.; Li, G.; Xiong, W.; Yi, M.; Xiang, B. Regulatory Mechanisms of PD-1/PD-L1 in Cancers. Mol. Cancer 2024, 23, 108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jeong, H.; Koh, J.; Kim, S.; Yim, J.; Song, S.G.; Kim, H.; Li, Y.; Lee, S.H.; Chung, Y.K.; Kim, H.; et al. Cell-Intrinsic PD-L1 Signaling Drives Immunosuppression by Myeloid-Derived Suppressor Cells through IL-6/Jak/Stat3 in PD-L1-High Lung Cancer. J. Immunother. Cancer 2025, 13, e010612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, Y.; Liu, D.; Li, L. PD-1/PD-L1 Pathway: Current Researches in Cancer. Am. J. Cancer Res. 2020, 10, 727–742. [Google Scholar] [PubMed]
- Takada, K.; Toyokawa, G.; Okamoto, T.; Shimokawa, M.; Kozuma, Y.; Matsubara, T.; Haratake, N.; Akamine, T.; Takamori, S.; Katsura, M.; et al. A Comprehensive Analysis of Programmed Cell Death Ligand-1 Expression with the Clone SP142 Antibody in Non–Small-Cell Lung Cancer Patients. Clin. Lung Cancer 2017, 18, 572–582.e1. [Google Scholar] [CrossRef] [Scilit]
- Guégan, J.-P.; Peyraud, F.; Dadone-Montaudie, B.; Teyssonneau, D.; Palmieri, L.-J.; Clot, E.; Cousin, S.; Roubaud, G.; Cabart, M.; Leroy, L.; et al. Analysis of PD1, LAG3, TIGIT, and TIM3 Expression in Human Lung Adenocarcinoma Reveals a 25-Gene Signature Predicting Immunotherapy Response. Cell Rep. Med. 2024, 5, 101831. [Google Scholar] [CrossRef] [Scilit]
- Davis, A.A.; Patel, V.G. The Role of PD-L1 Expression as a Predictive Biomarker: An Analysis of All US Food and Drug Administration (FDA) Approvals of Immune Checkpoint Inhibitors. J. Immunother. Cancer 2019, 7, 278. [Google Scholar] [CrossRef] [Scilit]
- Huo, J.-L.; Wang, Y.-T.; Fu, W.-J.; Lu, N.; Liu, Z.-S. The Promising Immune Checkpoint LAG-3 in Cancer Immunotherapy: From Basic Research to Clinical Application. Front. Immunol. 2022, 13, 956090. [Google Scholar] [CrossRef] [Scilit]
- Sauer, N.; Szlasa, W.; Jonderko, L.; Oślizło, M.; Kunachowicz, D.; Kulbacka, J.; Karłowicz-Bodalska, K. LAG-3 as a Potent Target for Novel Anticancer Therapies of a Wide Range of Tumors. Int. J. Mol. Sci. 2022, 23, 9958. [Google Scholar] [CrossRef] [Scilit]
- Maruhashi, T.; Sugiura, D.; Okazaki, I.; Okazaki, T. LAG-3: From Molecular Functions to Clinical Applications. J. Immunother. Cancer 2020, 8, e001014. [Google Scholar] [CrossRef] [Scilit]
- Young, H.J.; Pharaon, R.; Bonjoc, K.-J.C.; Ally, F.; Yin, H.; Kang, R.; Gernon, T.; Maghami, E.; Chaudhry, A. Differential Immune Pathways in Classic and Mixed Variants of Anaplastic Thyroid Cancer. J. Clin. Oncol. 2020, 38, e18579. [Google Scholar] [CrossRef] [Scilit]
- Sun, H.; Dai, J.; Zhao, L.; Zhu, J.; Wang, H.; Chen, P.; Lu, H.; Chen, Q.; Zhang, Z. Lymphocyte Activation Gene-3 Is Associated with Programmed Death-Ligand 1 and Programmed Cell Death Protein 1 in Small Cell Lung Cancer. Ann. Transl. Med. 2021, 9, 18. [Google Scholar] [CrossRef] [Scilit]
- He, Y.; Yu, H.; Rozeboom, L.; Rivard, C.J.; Ellison, K.; Dziadziuszko, R.; Suda, K.; Ren, S.; Wu, C.; Hou, L.; et al. LAG-3 Protein Expression in Non–Small Cell Lung Cancer and Its Relationship with PD-1/PD-L1 and Tumor-Infiltrating Lymphocytes. J. Thorac. Oncol. 2017, 12, 814–823. [Google Scholar] [CrossRef] [Scilit]
- Workman, C.J.; Wang, Y.; El Kasmi, K.C.; Pardoll, D.M.; Murray, P.J.; Drake, C.G.; Vignali, D.A.A. LAG-3 Regulates Plasmacytoid Dendritic Cell Homeostasis. J. Immunol. 2009, 182, 1885–1891. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, M.; Zhu, C.; Kuchroo, V.K. Tim-3 and Its Role in Regulating Anti-tumor Immunity. Immunol. Rev. 2017, 276, 97–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sauer, N.; Janicka, N.; Szlasa, W.; Skinderowicz, B.; Kołodzińska, K.; Dwernicka, W.; Oślizło, M.; Kulbacka, J.; Novickij, V.; Karłowicz-Bodalska, K. TIM-3 as a Promising Target for Cancer Immunotherapy in a Wide Range of Tumors. Cancer Immunol. Immunother. 2023, 72, 3405–3425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, C.; Anderson, A.C.; Schubart, A.; Xiong, H.; Imitola, J.; Khoury, S.J.; Zheng, X.X.; Strom, T.B.; Kuchroo, V.K. The Tim-3 Ligand Galectin-9 Negatively Regulates T Helper Type 1 Immunity. Nat. Immunol. 2005, 6, 1245–1252. [Google Scholar] [CrossRef] [Scilit]
- Hastings, W.D.; Anderson, D.E.; Kassam, N.; Koguchi, K.; Greenfield, E.A.; Kent, S.C.; Zheng, X.X.; Strom, T.B.; Hafler, D.A.; Kuchroo, V.K. TIM-3 Is Expressed on Activated Human CD4+ T Cells and Regulates Th1 and Th17 Cytokines. Eur. J. Immunol. 2009, 39, 2492–2501. [Google Scholar] [CrossRef] [Scilit]
- Zhu, B.; Chen, P.; Aminu, M.; Li, J.-R.; Fujimoto, J.; Tian, Y.; Hong, L.; Chen, H.; Hu, X.; Li, C.; et al. Spatial and Multiomics Analysis of Human and Mouse Lung Adenocarcinoma Precursors Reveals TIM-3 as a Putative Target for Precancer Interception. Cancer Cell 2025, 43, 1125–1140.e10. [Google Scholar] [CrossRef] [Scilit]
- Gao, X.; Zhu, Y.; Li, G.; Huang, H.; Zhang, G.; Wang, F.; Sun, J.; Yang, Q.; Zhang, X.; Lu, B. TIM-3 Expression Characterizes Regulatory T Cells in Tumor Tissues and Is Associated with Lung Cancer Progression. PLoS ONE 2012, 7, e30676. [Google Scholar] [CrossRef] [Scilit]
- Zang, K.; Hui, L.; Wang, M.; Huang, Y.; Zhu, X.; Yao, B. TIM-3 as a Prognostic Marker and a Potential Immunotherapy Target in Human Malignant Tumors: A Meta-Analysis and Bioinformatics Validation. Front. Oncol. 2021, 11, 579351. [Google Scholar] [CrossRef] [Scilit]
- Tarhini, A. CTLA-4 Blockade: Therapeutic Potential in Cancer Treatments. OncoTargets Ther. 2010, 3, 15–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oresti, S.; Salomone, F.; Nuccio, A.; Ogliari, F.R.; Riva, S.T.; Mollica, L.; Bulotta, A.; Viganò, M.G.; Venanzi, F.M.; Passaretti, F.; et al. Impact of Platinum-Based Chemotherapy and CTLA-4 Inhibition on Acquired Resistance to First-Line Anti-PD-1/PD-L1 Agents in Non-Small Cell Lung Cancer: A Systematic Review and Reconstructed Individual Patient Data Analysis. eClinicalMedicine 2025, 88, 103482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiler, J.; Dittmar, T. Cell Fusion in Human Cancer: The Dark Matter Hypothesis. Cells 2019, 8, 132. [Google Scholar] [CrossRef] [Scilit]
- Shultes, P.V.; Weaver, D.T.; Tadele, D.S.; Barker-Clarke, R.J.; Scott, J.G. Cell-Cell Fusion in Cancer: The next Cancer Hallmark? Int. J. Biochem. Cell Biol. 2024, 175, 106649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gast, C.E.; Silk, A.D.; Zarour, L.; Riegler, L.; Burkhart, J.G.; Gustafson, K.T.; Parappilly, M.S.; Roh-Johnson, M.; Goodman, J.R.; Olson, B.; et al. Cell Fusion Potentiates Tumor Heterogeneity and Reveals Circulating Hybrid Cells That Correlate with Stage and Survival. Sci. Adv. 2018, 4, eaat7828. [Google Scholar] [CrossRef] [Scilit]
- Aguirre, L.A.; Montalbán-Hernández, K.; Avendaño-Ortiz, J.; Marín, E.; Lozano, R.; Toledano, V.; Sánchez-Maroto, L.; Terrón, V.; Valentín, J.; Pulido, E.; et al. Tumor Stem Cells Fuse with Monocytes to Form Highly Invasive Tumor-Hybrid Cells. OncoImmunology 2020, 9, 1773204. [Google Scholar] [CrossRef] [Scilit]
- Pawelek, J.M.; Chakraborty, A.K. Fusion of Tumour Cells with Bone Marrow-Derived Cells: A Unifying Explanation for Metastasis. Nat. Rev. Cancer 2008, 8, 377–386. [Google Scholar] [CrossRef] [Scilit]
- Montalbán-Hernández, K.; Cantero-Cid, R.; Casalvilla-Dueñas, J.C.; Avendaño-Ortiz, J.; Marín, E.; Lozano-Rodríguez, R.; Terrón-Arcos, V.; Vicario-Bravo, M.; Marcano, C.; Saavedra-Ambrosy, J.; et al. Colorectal Cancer Stem Cells Fuse with Monocytes to Form Tumour Hybrid Cells with the Ability to Migrate and Evade the Immune System. Cancers 2022, 14, 3445. [Google Scholar] [CrossRef] [Scilit]
- Tanjak, P.; Chaiboonchoe, A.; Suwatthanarak, T.; Thanormjit, K.; Acharayothin, O.; Chanthercrob, J.; Parakonthun, T.; Methasate, A.; Fischer, J.M.; Wong, M.H.; et al. Tumor-Immune Hybrid Cells Evade the Immune Response and Potentiate Colorectal Cancer Metastasis through CTLA4. Clin. Exp. Med. 2024, 25, 2. [Google Scholar] [CrossRef] [Scilit]
- Tajima, Y.; Shibasaki, F.; Masai, H. Cell Fusion Upregulates PD-L1 Expression for Evasion from Immunosurveillance. Cancer Gene Ther. 2024, 31, 158–173. [Google Scholar] [CrossRef] [Scilit]
- Mata-Martínez, P.; Celada, L.; Cueto, F.J.; Sáenz De Santa María, G.; Fernández, J.; Terrón-Arcos, V.; Valdés, N.; Moreira, V.G.; Del Toro, M.I.E.; López-Collazo, E.; et al. A Blood-Based Liquid Biopsy Analyzing Soluble Immune Checkpoints and Cytokines Identifies Distinct Neuroendocrine Tumors. J. Exp. Clin. Cancer Res. 2025, 44, 82. [Google Scholar] [CrossRef] [Scilit]
- Del Prado-Montero, J.; Guevara-Martínez, J.; Cantero-Cid, R.; Mata-Martínez, P.; Cueto, F.J.; Lozano-Rodríguez, R.; Terrón-Arcos, V.; Abad-Moret, R.; Díaz-Serrano, E.; De Diego, R.P.; et al. Age-Stratified Circulating Immune Signatures Reveal Non-Invasive Biomarkers for Colorectal Cancer Detection. Immun. Ageing 2025, 22, 40. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.