Skip to Content
  • 3.7
    Impact Factor
  • 4.2
    CiteScore
  • 22 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Diseases

Diseases is an international, peer-reviewed, open access, multidisciplinary journal with focus on research on human diseases and conditions, published monthly online by MDPI. 
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within Scopus, ESCI (Web of Science), PubMed, PMC, CAPlus / SciFinder, and other databases.
  • Journal Rank: JCR - Q2 (Medicine, Research and Experimental) / CiteScore - Q1 (General Medicine)
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 21.6 days after submission; acceptance to publication is undertaken in 2.6 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.
  • Sections: published in 8 topical sections.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (1,873)

  • Systematic Review
  • Open Access

Background: Artificial intelligence (AI) is increasingly being integrated into insulin management through decision-support systems, adaptive bolus calculators, conversational platforms, and automated insulin delivery (AID) technologies. However, the clinical effectiveness and safety of AI-assisted insulin management remain uncertain. Objective: To systematically evaluate evidence from randomized controlled trials (RCTs) investigating AI-assisted insulin management systems in individuals with type 1 or type 2 diabetes. Methods: A systematic literature review was conducted following PRISMA guidelines. PubMed/MEDLINE, Embase, and Cochrane CENTRAL were searched for RCTs evaluating AI-enabled insulin management interventions in insulin-treated individuals with diabetes. Eligible studies compared AI-based systems with standard care, clinician-guided insulin titration, conventional bolus calculators, or other AID algorithms. Outcomes included glycemic control, insulin titration, safety, and implementation-related measures. Owing to substantial heterogeneity, findings were synthesized narratively. Results: We included seven RCTs published between 2020 and 2025. Interventions comprised clinical decision-support systems, adaptive bolus calculators, conversational AI platforms, neural-network-based artificial pancreas algorithms, and exercise-aware AID systems. AI-assisted interventions consistently demonstrated favorable safety profiles, with no increase in severe hypoglycemia, diabetic ketoacidosis, or serious adverse events. Some systems, particularly fully automated closed-loop platforms and conversational AI-guided insulin titration, showed improvements in time in range, glucose control, adherence, and insulin optimization. User acceptance and adherence emerged as important determinants of effectiveness. Conclusions: Current randomized evidence suggests that AI-assisted insulin management systems are safe, feasible, and capable of achieving glycemic outcomes comparable to conventional care. Although certain technologies demonstrate promising clinical benefits, the evidence base remains limited by small sample sizes, short follow-up durations, and heterogeneity across interventions. Larger, long-term randomized trials are needed to establish comparative effectiveness, optimize human–AI interaction, and support broader clinical implementation.

Diseases

13 October 2026
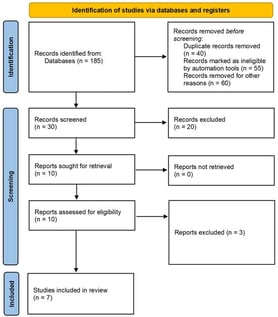
PRISMA flow diagram of study selection [14].
  • Article
  • Open Access

Objective: To develop and comparatively evaluate machine learning models for predicting 1-year survival in hepatocellular carcinoma (HCC) patients, focusing on the prognostic interplay between chronic liver diseases and diabetes aligned with the EASL Clinical Practice Guidelines (2018), and to assess the impact of class balancing via Synthetic Minority Oversampling Technique (SMOTE) on model performance. Methods: Retrospective analysis was performed on the UCI HCC Survival Dataset (N = 165). Following median/mode imputation of ~10% missing values, four classifiers were evaluated: Logistic Regression (LR), Multilayer Perceptron (MLP), Gradient Boosting (GB), and Random Forest (RF), each trained with and without SMOTE oversampling (eight variants total). Models were trained on 16 EASL-aligned clinical and biochemical features using a stratified 80/20 train/test split (training N = 132, held-out test N = 33). Performance was evaluated via accuracy, AUC-ROC (with 95% bootstrap confidence intervals across 1000 iterations), precision, recall, and macro F1-score. Stratified 5-fold cross-validation and multiple imputation sensitivity analyses (MissForest, KNN, MICE, complete-case) were conducted. SHAP (SHapley Additive exPlanations) was applied to the top-performing model to provide patient-level interpretability. Results: Diabetes was present in 33.9% of patients (56/165; 28/102 survivors [27.5%] vs. 28/63 non-survivors [44.4%]). Diabetes was significantly associated with 1-year mortality in univariate analysis (χ2 = 5.02, p = 0.025) but not after multivariable adjustment (aOR = 0.50, 95% CI: 0.21–1.22, p = 0.129). GB + SMOTE achieved the highest discriminative ability (AUC-ROC: 0.727, 95% CI: 0.552–0.886), while LR + SMOTE yielded the highest overall accuracy (72.7%) and macro F1-score (0.723). Without SMOTE, all models exhibited poor minority-class detection (non-survival F1 range: 0.300–0.615). SMOTE markedly improved non-survival recall across LR (0.231 to 0.769) and GB (61.5% to 69.2%). Stratified 5-fold CV AUC on the training set was highest for RF (0.779 ± 0.100), followed by GB (0.744 ± 0.065). TreeSHAP analysis identified ECOG performance status (mean |SHAP| = 1.284) and ALT (1.060) as the most influential predictors; diabetes ranked 15th (mean |SHAP| = 0.014), consistent with minimal independent predictive contribution. Conclusions: Gradient boosting and regularized linear regression combined with SMOTE class balancing provide competitive, well-calibrated, and transparent risk stratification on small, imbalanced tabular HCC datasets, offering an exploratory proof-of-concept for personalized prognostic modeling that requires external validation.

Diseases

13 October 2026

  • Review
  • Open Access

Hypertension is a major cardiovascular risk factor, but its epidemiology in people with multiple sclerosis (PwMS) remains unclear. Whether PwMS have a higher prevalence of hypertension than the general population, the potential pathways linking the two conditions, and the association between hypertension and MS-related outcomes remain incompletely understood. This narrative review summarizes current evidence on the prevalence of hypertension in PwMS, examines potential immunological, autonomic, vascular, behavioral, and treatment-related pathways that may link MS and hypertension, and explores how MS disease-modifying therapies may influence blood pressure regulation. It also reviews evidence on the association between hypertension and neurological disability, mobility, cognitive function, visual outcomes, and markers of neurodegeneration in PwMS, as well as hypertensive disorders of pregnancy in women with MS. Finally, it discusses the clinical implications of these findings and identifies priorities for future research.

Diseases

13 October 2026

  • Article
  • Open Access

Background: Accurate scoring is essential when patient-reported self-management instruments are related to biochemical outcomes. The principal contribution of this study was to reconstruct and audit Diabetes Self-Management Questionnaire (DSMQ) scores from item-level data before reassessing their cross-sectional association with glycemic control. Methods: We performed a cross-sectional secondary analysis of a clinical database of adults with type 2 diabetes. One non-patient header row was removed. Because 12 observation-sheet identifiers occurred twice and visit dates were unavailable, all 24 records carrying repeated identifiers were excluded from the prespecified primary analysis, leaving 238 records. Negatively keyed DSMQ items were reverse-scored, and total and subscale scores were transformed to a 0–10 scale according to the original algorithm. Associations with HbA1c were assessed using Spearman correlation, exploratory ROC analysis, and multivariable linear regression with HC3 robust standard errors. Results: HbA1c was available for 237 records; mean age was 64.18 years (SD 11.14), 56.1% of records with valid sex coding were female, and mean HbA1c was 7.81% (SD 1.94). The corrected DSMQ total score was 5.19 (SD 2.36). DSMQ total score correlated inversely with HbA1c (ρ = −0.467, bootstrap 95% CI −0.572 to −0.350; p < 0.001). In the adjusted model (n = 236), each one-point higher DSMQ total score was associated with a 0.254 percentage-point lower HbA1c (regression coefficient = −0.254, 95% CI −0.344 to −0.163; p < 0.001). Sensitivity analyses using all records or first/last repeated-record rules produced similar estimates. Conclusions: Correctly scored DSMQ results showed a moderate, independent cross-sectional association with HbA1c. The corrected analysis did not demonstrate excellent discrimination, and the cross-sectional data cannot support causal or predictive claims. Prospective studies with verified unique participants and clearly documented data provenance are needed.

Diseases

12 October 2026

Featured Articles of Last Quarter

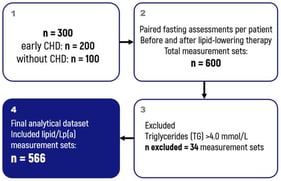
Study design.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

Inflammation
Reprint

Inflammation

The Cause of all Diseases 2.0
Editors: Vasso Apostolopoulos, Jack Feehan, Vivek P. Chavda
Inflammation: The Cause of All Diseases
Reprint

Inflammation: The Cause of All Diseases

Editors: Vasso Apostolopoulos, Jack Feehan, Vivek P. Chavda
XFacebookLinkedIn
Diseases - ISSN 2079-9721