


Abstract
This index meta-analysis estimated the pooled prevalence of human immunodeficiency virus (HIV) among individuals with monkeypox (mpox) globally. We searched seven databases: PubMed, Scopus, Web of Science, EMBASE, ProQuest, EBSCOHost, and Cochrane, for human studies published in English till 4 January 2023, as per International Prospective Register of Systematic Reviews (PROSPERO) registration protocol (CRD42022383275). A random effects regression model was used to estimate the pooled prevalence owing to high heterogeneity. The risk of bias in the included studies was assessed using the National Heart, Lung, and Blood Institute (NHLBI) quality assessment tool. The systematic search yielded 677 articles; finally, 32 studies were found eligible for systematic review and 29 studies for meta-analysis. The pooled prevalence of HIV infection was 41% (95% confidence interval [CI], 35–48). All studies were rated as fair or good quality. Studies from Europe and North America reported a high prevalence of HIV infection among individuals with mpox- 41% (95% CI 33–49) and 52% (95% CI 28–76), respectively, while studies from Nigeria, Africa reported a relatively low prevalence of HIV infection of 21% (95% CI 15–26). A history of sexual orientation and sexual partners in the last 21 days must be taken from individuals with mpox to identify the potential source and contacts for quarantining and testing them.
1. Introduction
Most mpox (previously known as monkeypox) cases were reported from central and west Africa in the past [1]. However, in May 2022, the disease began to emerge across the world in multiple countries. It was declared a “public health emergency of international concern’ by the World Health Organization (WHO) in 2022 [2]. Among all known transmission routes, a potential sexual route has been reported among 82.1% (16518/20126) of individuals with mpox [3]. Within mpox virus (MPXV), there are two distinct clades, namely clade I (formerly known as Central Africa strain) and clade II (formerly known as West African strain). Clade II encompasses two phylogenetically distinct subclades, IIa and IIb. The sub-clades are however distinct, with a differential evolution from an ancestor which dates back centuries [4]. The 2022 multicountry outbreak of mpox has been attributed to clade IIb. Pre-2022 outbreak of mpox was mostly associated with close contact through the skin lesions and respiratory route of transmission [5]. In contrast, sexual intercourse has been identified as a major risk factor for the 2022 multicountry outbreak. Close contact happening during sexual intercourse or as sexually transmitted infection due to the act are the potential routes of transmission implicated in the 2022 outbreak. This has led to the establishment and spread of MPXV among the communities with high-risk sexual practices, especially with the anal receptive sex. Semen samples have been reported to harbor a high load of MPXV [5]. Human immunodeficiency virus (HIV) is another viral infection that is transmitted majorly through a sexual route [6]. The burden of HIV is high, with prevalent cases of 39 million and 630,000 deaths in 2022 alone. Within these cases, Africa is the worst affected, with 2/3 of the people living with HIV (PLHIV) on the continent [7]. Mpox is also endemic in African countries [8].
Considering the overlap in the epidemiology of HIV and mpox in the context of the 2022 multicountry mpox outbreak, it would be relevant to explore the relationship between these viral infections at the global and regional levels. The clinical manifestation of mpox is self-limiting, but the disease can be severe in a specific population, such as individuals with immunosuppressed, including PLHIV[9]. Studies have reported poor outcomes among individuals with MPXV -HIV co-infection [10,11,12,13]. In a retrospective study from Nigeria among 40 individuals with mpox, it was reported that individuals with MPXV-HIV were susceptible to an increase in the duration of the disease, more prominent lesions, and increased secondary bacterial infection [13]. Uncontrolled HIV is associated with adverse outcomes, including deaths [12].
The epidemiological profile of mpox has shown considerable variation between continents, endemic/nonendemic countries, and the period of the cases (2022 multicountry outbreak vs. Pre-2022) in terms of mortality rates, clinical manifestations, and demographic characteristics of the affected population [14,15,16,17]. Studies in Africa before the current outbreak reported a prevalence of HIV among mpox in the range of 18.75% to 25%[18,19]. Studies in European countries showed varied HIV prevalence ranging from 15% in France to 64% in Spain [20,21]. Thus, multiple studies from current and past outbreaks have reported varying HIV prevalence among individuals with mpox. However, based on our systematic search in multiple databases, we did not find an analysis reporting the pooled prevalence of HIV among the individuals with mpox, and the regional and temporal variations.
Hence, we conducted a systematic review and meta-analysis to determine the pooled prevalence of HIV reported among individuals with mpox, and to synthesise the epidemiological characteristics of individuals with HIV-MPXV co-infections.
2. Materials and Methods
2.1. Research Question & Selection Criteria
The present systematic review and meta-analysis were carried out based on the research question, ‘What is the prevalence of HIV in individuals with mpox?’ The systematic search and identification of eligible studies were centered on the criteria elaborated in the Appendix A. (Table A1 and Table A2). The study population included laboratory-confirmed individuals with mpox, belonging to all age groups and sex. All suspected or probable individuals with mpox were excluded. The outcome of interest was the prevalence of HIV. All eligible human studies published in English that satisfied the above criteria were included in the analysis. The present meta-analysis was registered with the International Prospective Register of Systematic Reviews (PROSPERO), with reference ID CRD42022383275.
2.2. Databases included and Search Strategy
The search was carried out in seven databases: “PubMed, Scopus, Web of Science, EMBASE, ProQuest, EBSCOHost, and Cochrane”, until 4 January 2023 (Table A2). We also searched the pre-print servers such as “medRxiv, arXiv, bioRxiv, BioRN, ChiRxiv, ChiRN, and SSRN”. Furthermore, studies obtained by hand search in the references of eligible primary research papers and reviews, which met our eligibility criteria, were also included in the data extraction. The search keywords included “mpox” ‘MPXV’, ‘monkeypox’, ‘AIDS’, ‘HIV’ and ‘PLHA’. The database-wise search strategy applied and the results obtained have been enumerated in Table A2. The Mendeley Desktop V1.19.5 software was used to import articles, manage the citations, remove duplicates, and coordinate the overall review process between authors.
2.3. Selection of Studies
2.3.1. Title-Abstract Screening
Four senior authors independently reviewed the title abstracts of the studies obtained from the above systematic search applying the eligibility criteria and identified articles for full-text screening. If there was a disagreement about including a study for full-text review, the co-authors conversed among themselves to build consensus and decided on eligibility.
2.3.2. Full Text Screening & Data Extraction
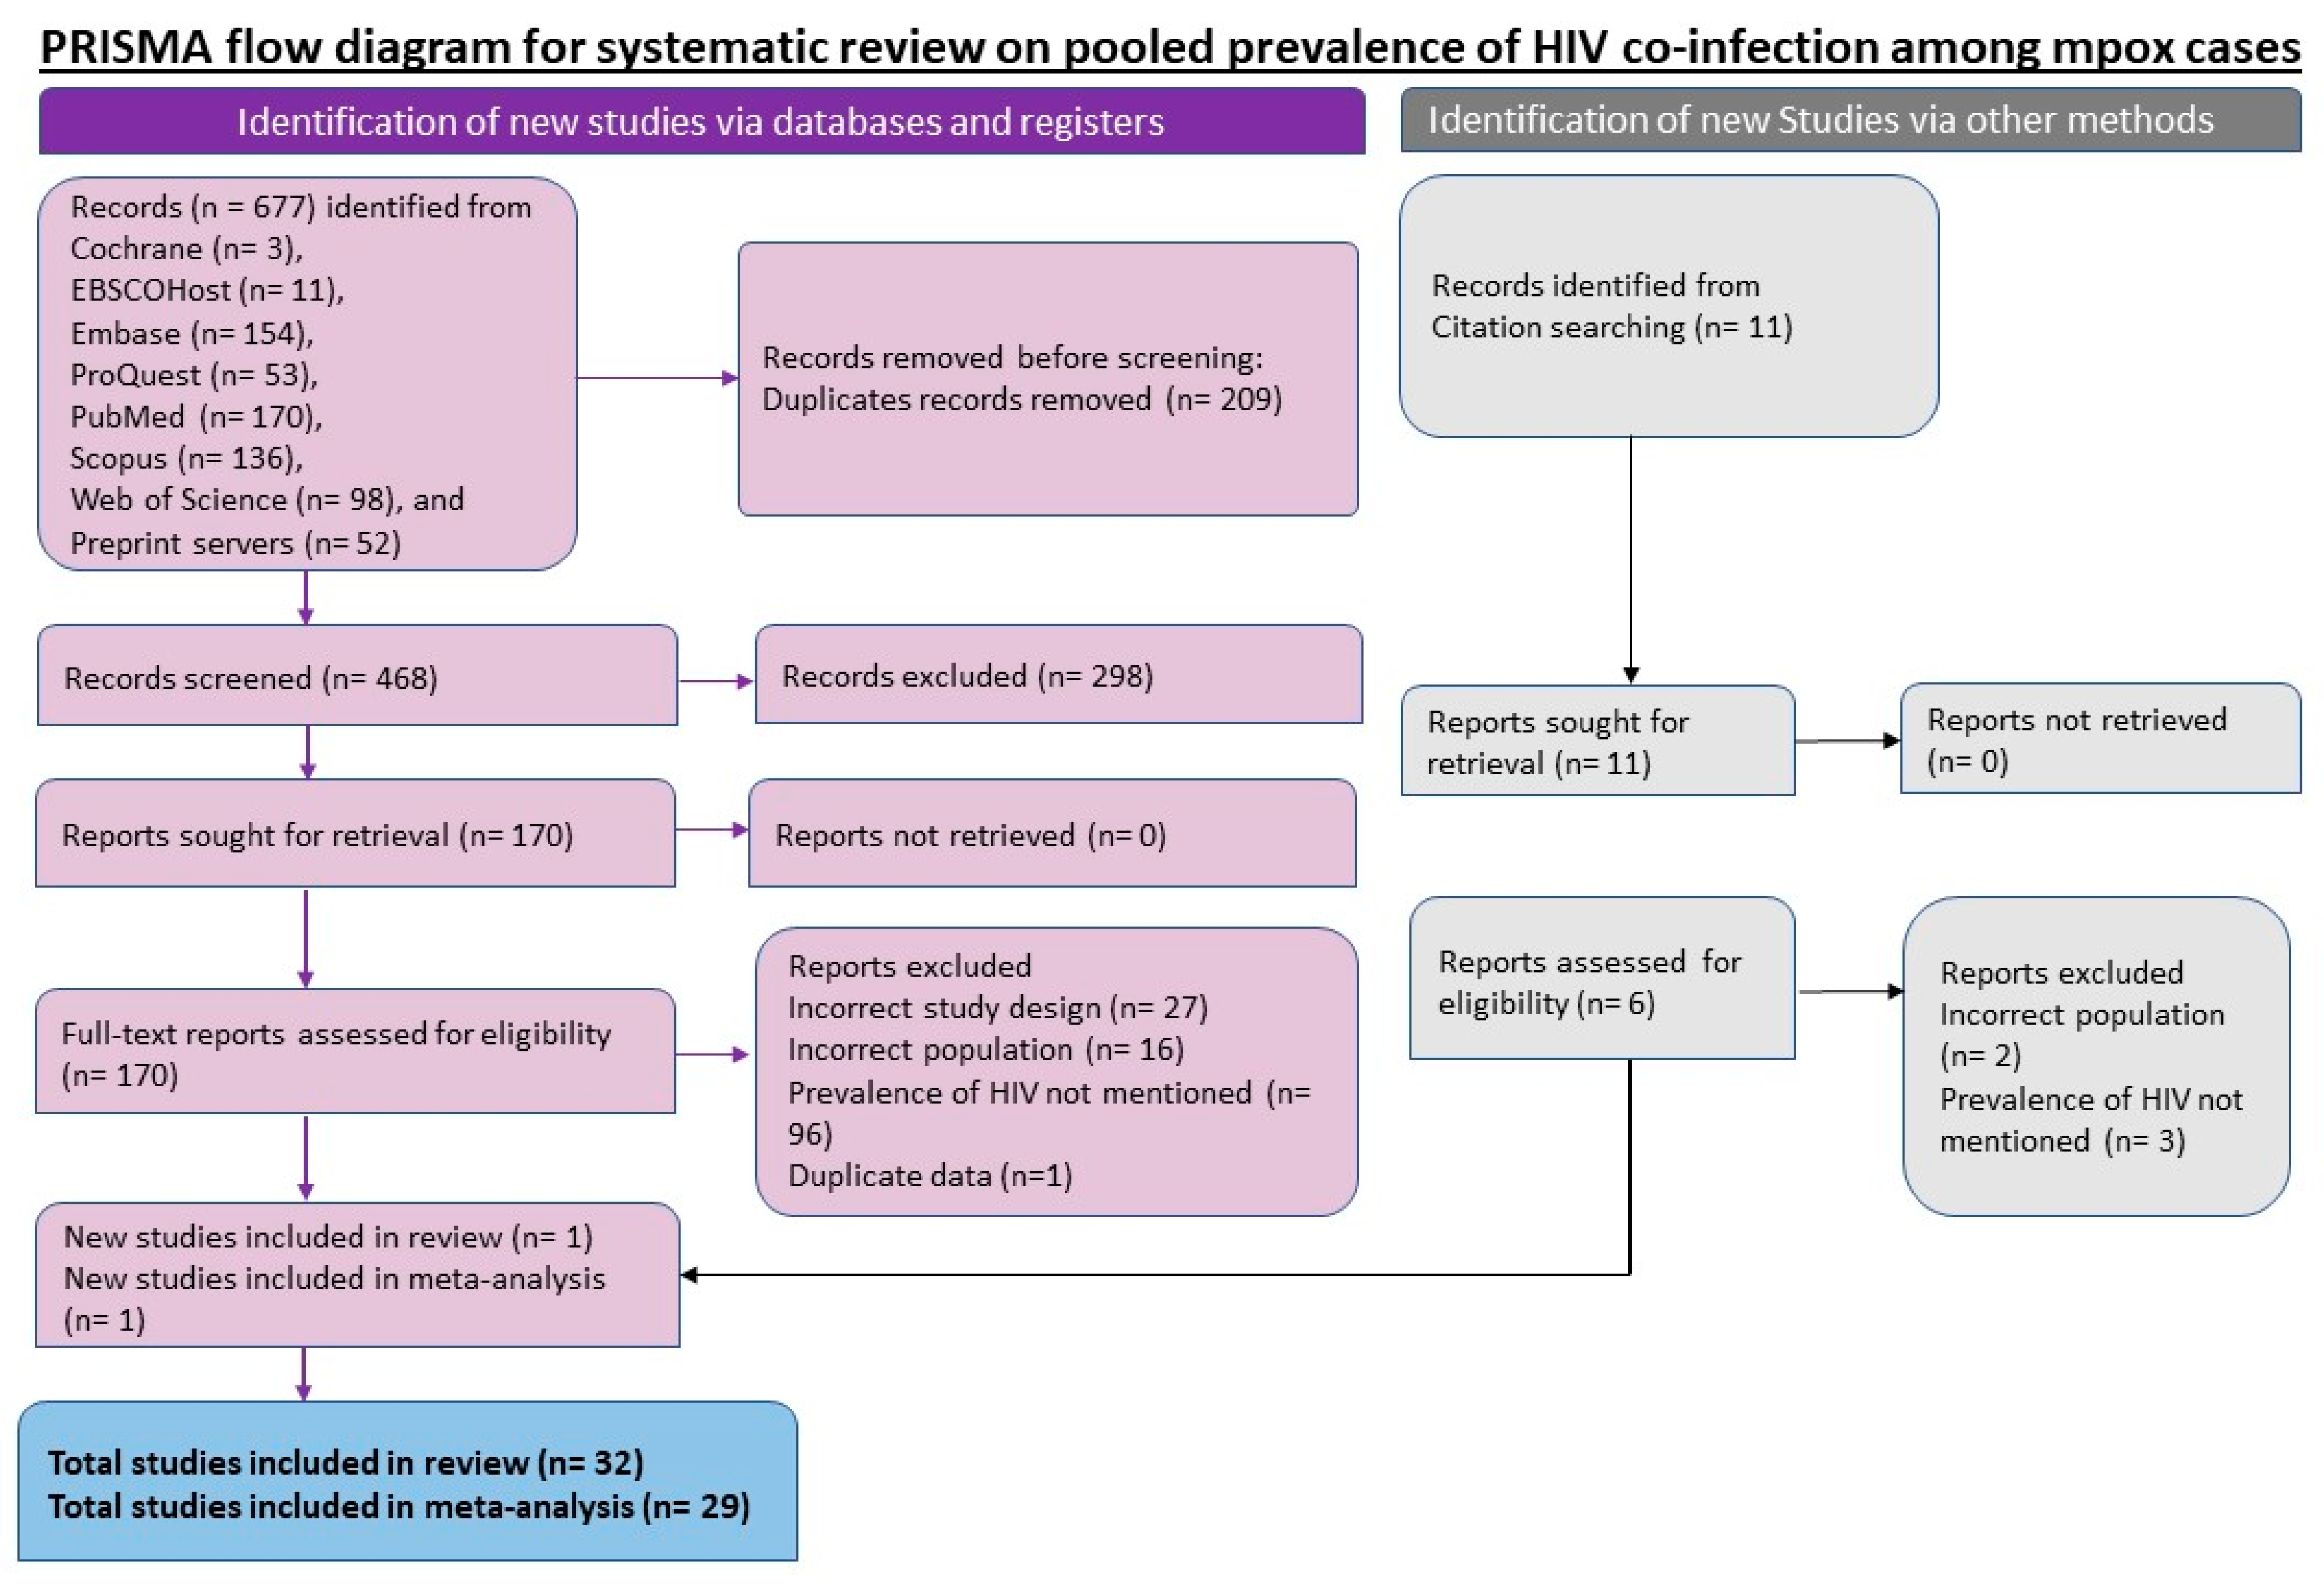
Eligible full-text articles were reviewed for suitability of data extraction by two authors, and data extraction was performed by them independently. Contradictions in the extraction of data between the authors were removed in a consensus meeting held at the end of the independent extraction. A final table was formulated that included information such as author’s name, publication year, sex distribution, age, study where it was conducted, study design, total mpox-positive individuals, and PLHIV. The preferred reporting standard of systematic reviews and Meta-analysis (PRISMA) flow chart and checklist were utilised to report general search, screening, data extraction, systematic review, and meta-analysis conducted to ensure scientific precision (Figure 1 & Table A3).
Figure 1.
PRISMA flowchart for included studies in systematic review and meta-analysis of prevalence of HIV among the individuals with mpox.
2.4. Quality Assessment
The risk of bias in the included studies was independently evaluated by two authors (MAS&SM) using the National Heart, Lung, and Blood Institute (NHLBI) quality assessment tool for case series and cross-sectional studies [22].
2.5. Data Analysis
The pooled prevalence of HIV infection was estimated as a proportion by collating the total number of individuals with mpox and PLHIV. To address the risk of bias, we planned a sensitivity analysis by excluding poor-quality studies. Baujat plot, Leave-one-out analysis, radial plot, and diagnostic test were applied to identify the outliers and undertake sensitivity analysis. The I2 test was applied to determine heterogeneity among the included studies. Depending on the I2 value, heterogeneity can be declared low (25%), moderate (25–50%), and high (>50%). A random effect regression model with the DerSimonian & Laird estimator was used to evaluate the overall effect, as heterogeneity was high. We performed a subgroup analysis to identify the source of heterogeneity: (i) geography (continent-wise), (ii) MPXV (endemic vs. non endemic countries), and (iii) 2022 vs. pre-2022 studies. Prediction interval (PI) for the outcome was calculated if the heterogeneity was high. Meta-regression was performed to assess the effect of age and sex on the outcomes using bubble plots. The funnel plot and doi plot were used to evaluate publication bias. If the funnel plot depicted possible publication bias, a trim-and-fill test was planned to address publication bias, and the Eggers test to evaluate the effects of the small study was planned. A p-value of less than 0.05 was interpreted as statistically significant. All analyses and graphs were performed using R-programming (v4.0).
3. Results
3.1. Eligible Studies
Figure 1 shows the article selection process as PRISMA flow chart. The systematic search yielded 468 articles after removing 209 duplicates. After the title abstract selection, 170 articles were eligible for full-text selection. In the full-text screening, 139 articles were excluded due to non-reporting of HIV status (96), incorrect study design (27), and incorrect patient population (16). Two new studies were included from the hand-search of the references from the included studies. Finally, 32 studies were found eligible for systematic review. Among them, two studies included individuals with MPXV-HIV co-infection as their study population, and one study had a data duplication. Hence 29 studies were included for data extraction in the meta-analysis.
3.2. Study Characteristics
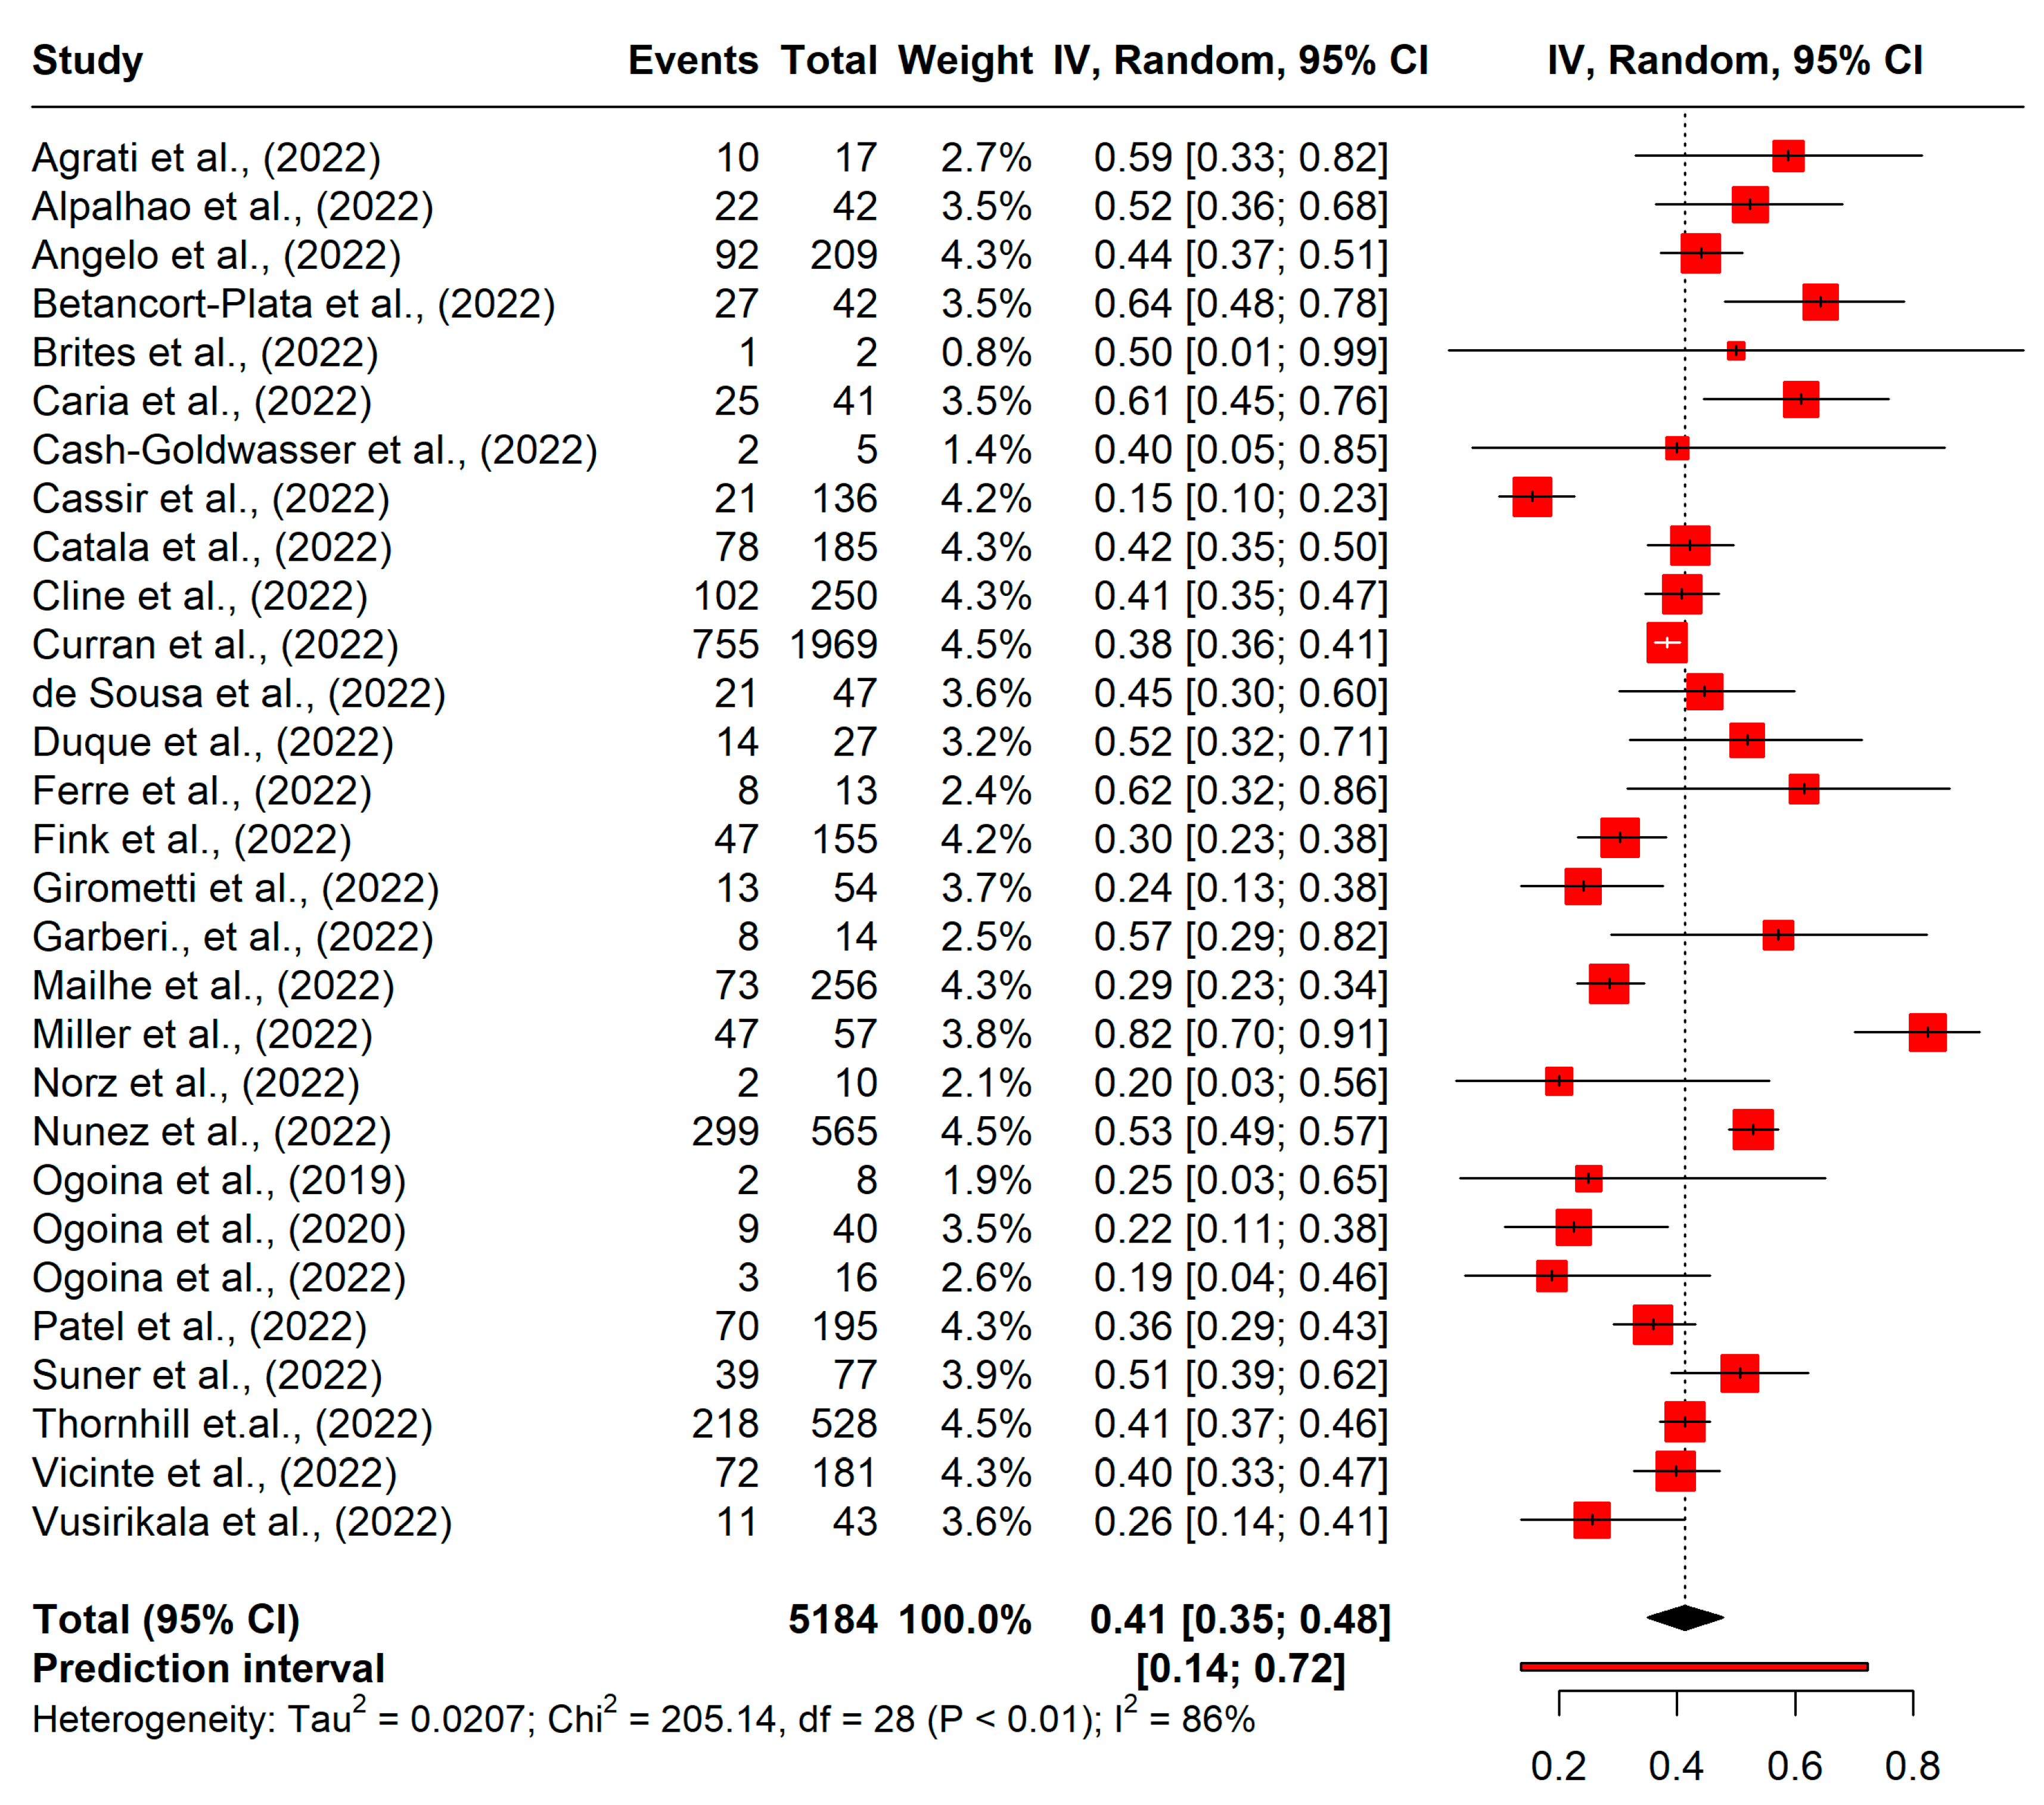
The included studies were conducted from 1987 to 2022. Among the 29 studies included, seven were cross-sectional studies [11,18,19,20,23,24,25] seven were retrospective studies[13,21,26,27,28,29,30], seven were prospective studies[31,32,33,34,35,36,37], and eight were case series[38,39,40,41,42,43,44,45]. The studies had sample sizes ranging from 2 to 1969. The median age of the participants ranged from 16 to 42 years in all studies. The proportion of men among the mpox cases was 75% in all studies, with 14 studies reporting 100% men cases. The studies from the United States of America (USA) and Spain were the most common, that is, six studies each of 32 studies (18.75%), followed by Nigeria (4/32), Portugal (4/32), and the United Kingdom (4/32) (Table 1). Sexual practices of the individuals with mpox were reported in 82.76% (24/29) of the studies and 75.86% (22/29) studies reported on high-risk sexual behaviours and/or high risk groups (HRGs) [mostly men who have sex with men (MSM)]. Penile-anal (81%), followed by oral-penile and oral-anal, were the common modalities of sexual behaviour reported by these HRGs [23]. The highest prevalence of HIV infection (82.46%) was reported by a study in the USA [44], while the lowest prevalence was reported in France (15.44%).[46] The heterogeneity between the studies was assessed to be high (I2 = 86%; p < 0.001) (Figure 2). Therefore, the random-effects model was applied to determine the pooled prevalence.
Table 1.
Baseline characteristics of studies reporting proportion of HIV infection in individuals with mpox.
Figure 2.
Forest plot of pooled prevalence of HIV prevalence in monkeypox virus.
3.3. Pooled Prevalence
The meta-analysis included a total of 5184 confirmed individuals with mpox, among whom 2091 reported HIV infection. The pooled prevalence of HIV infection in the target population was 41% (95% confidence interval [CI], 35–48) (Figure 2). The prediction interval was 14–71%.
3.4. Risk of Bias
The quality assessment of the findings of the included study is illustrated in the supplement file (Table A4), with all studies (30) rated as fair or good quality. The Doi plot was symmetrical with an LFK index of 0.91, indicating no publication bias (Figure S1). The layout of the funnel plot also showed a symmetric funnel, indicating no publication bias (Figure S2).
3.5. Sensitivity Analysis
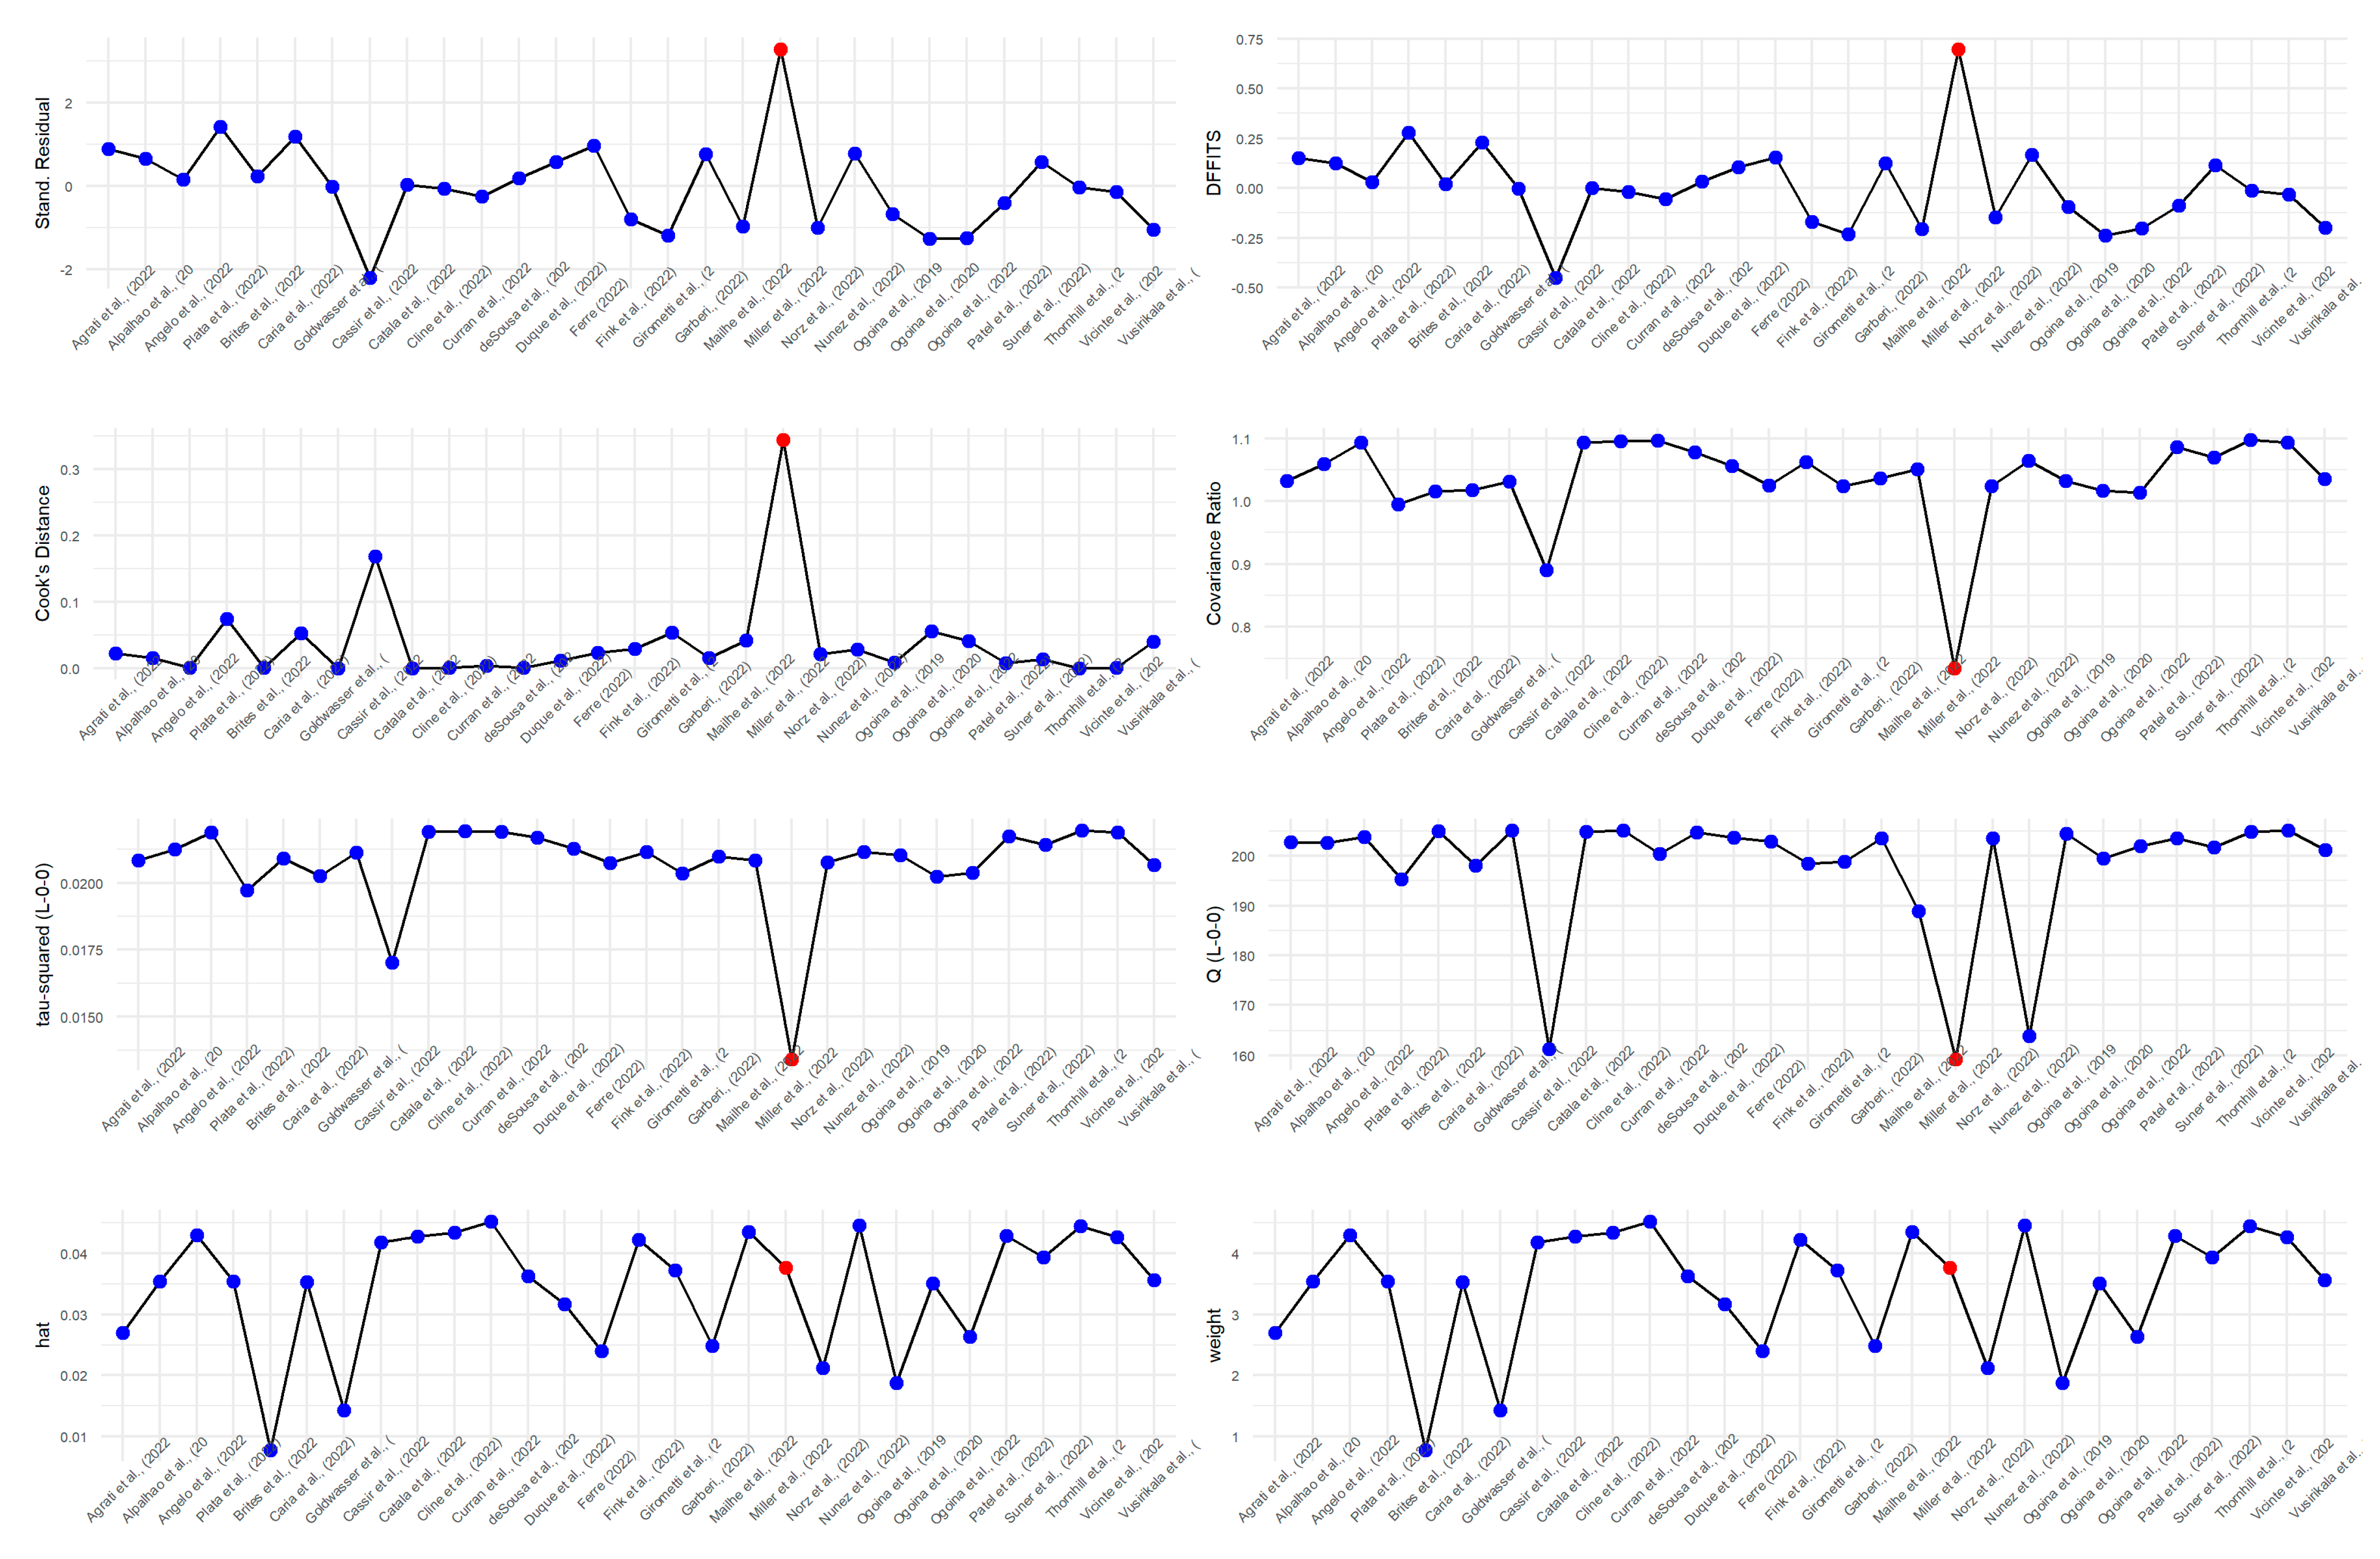
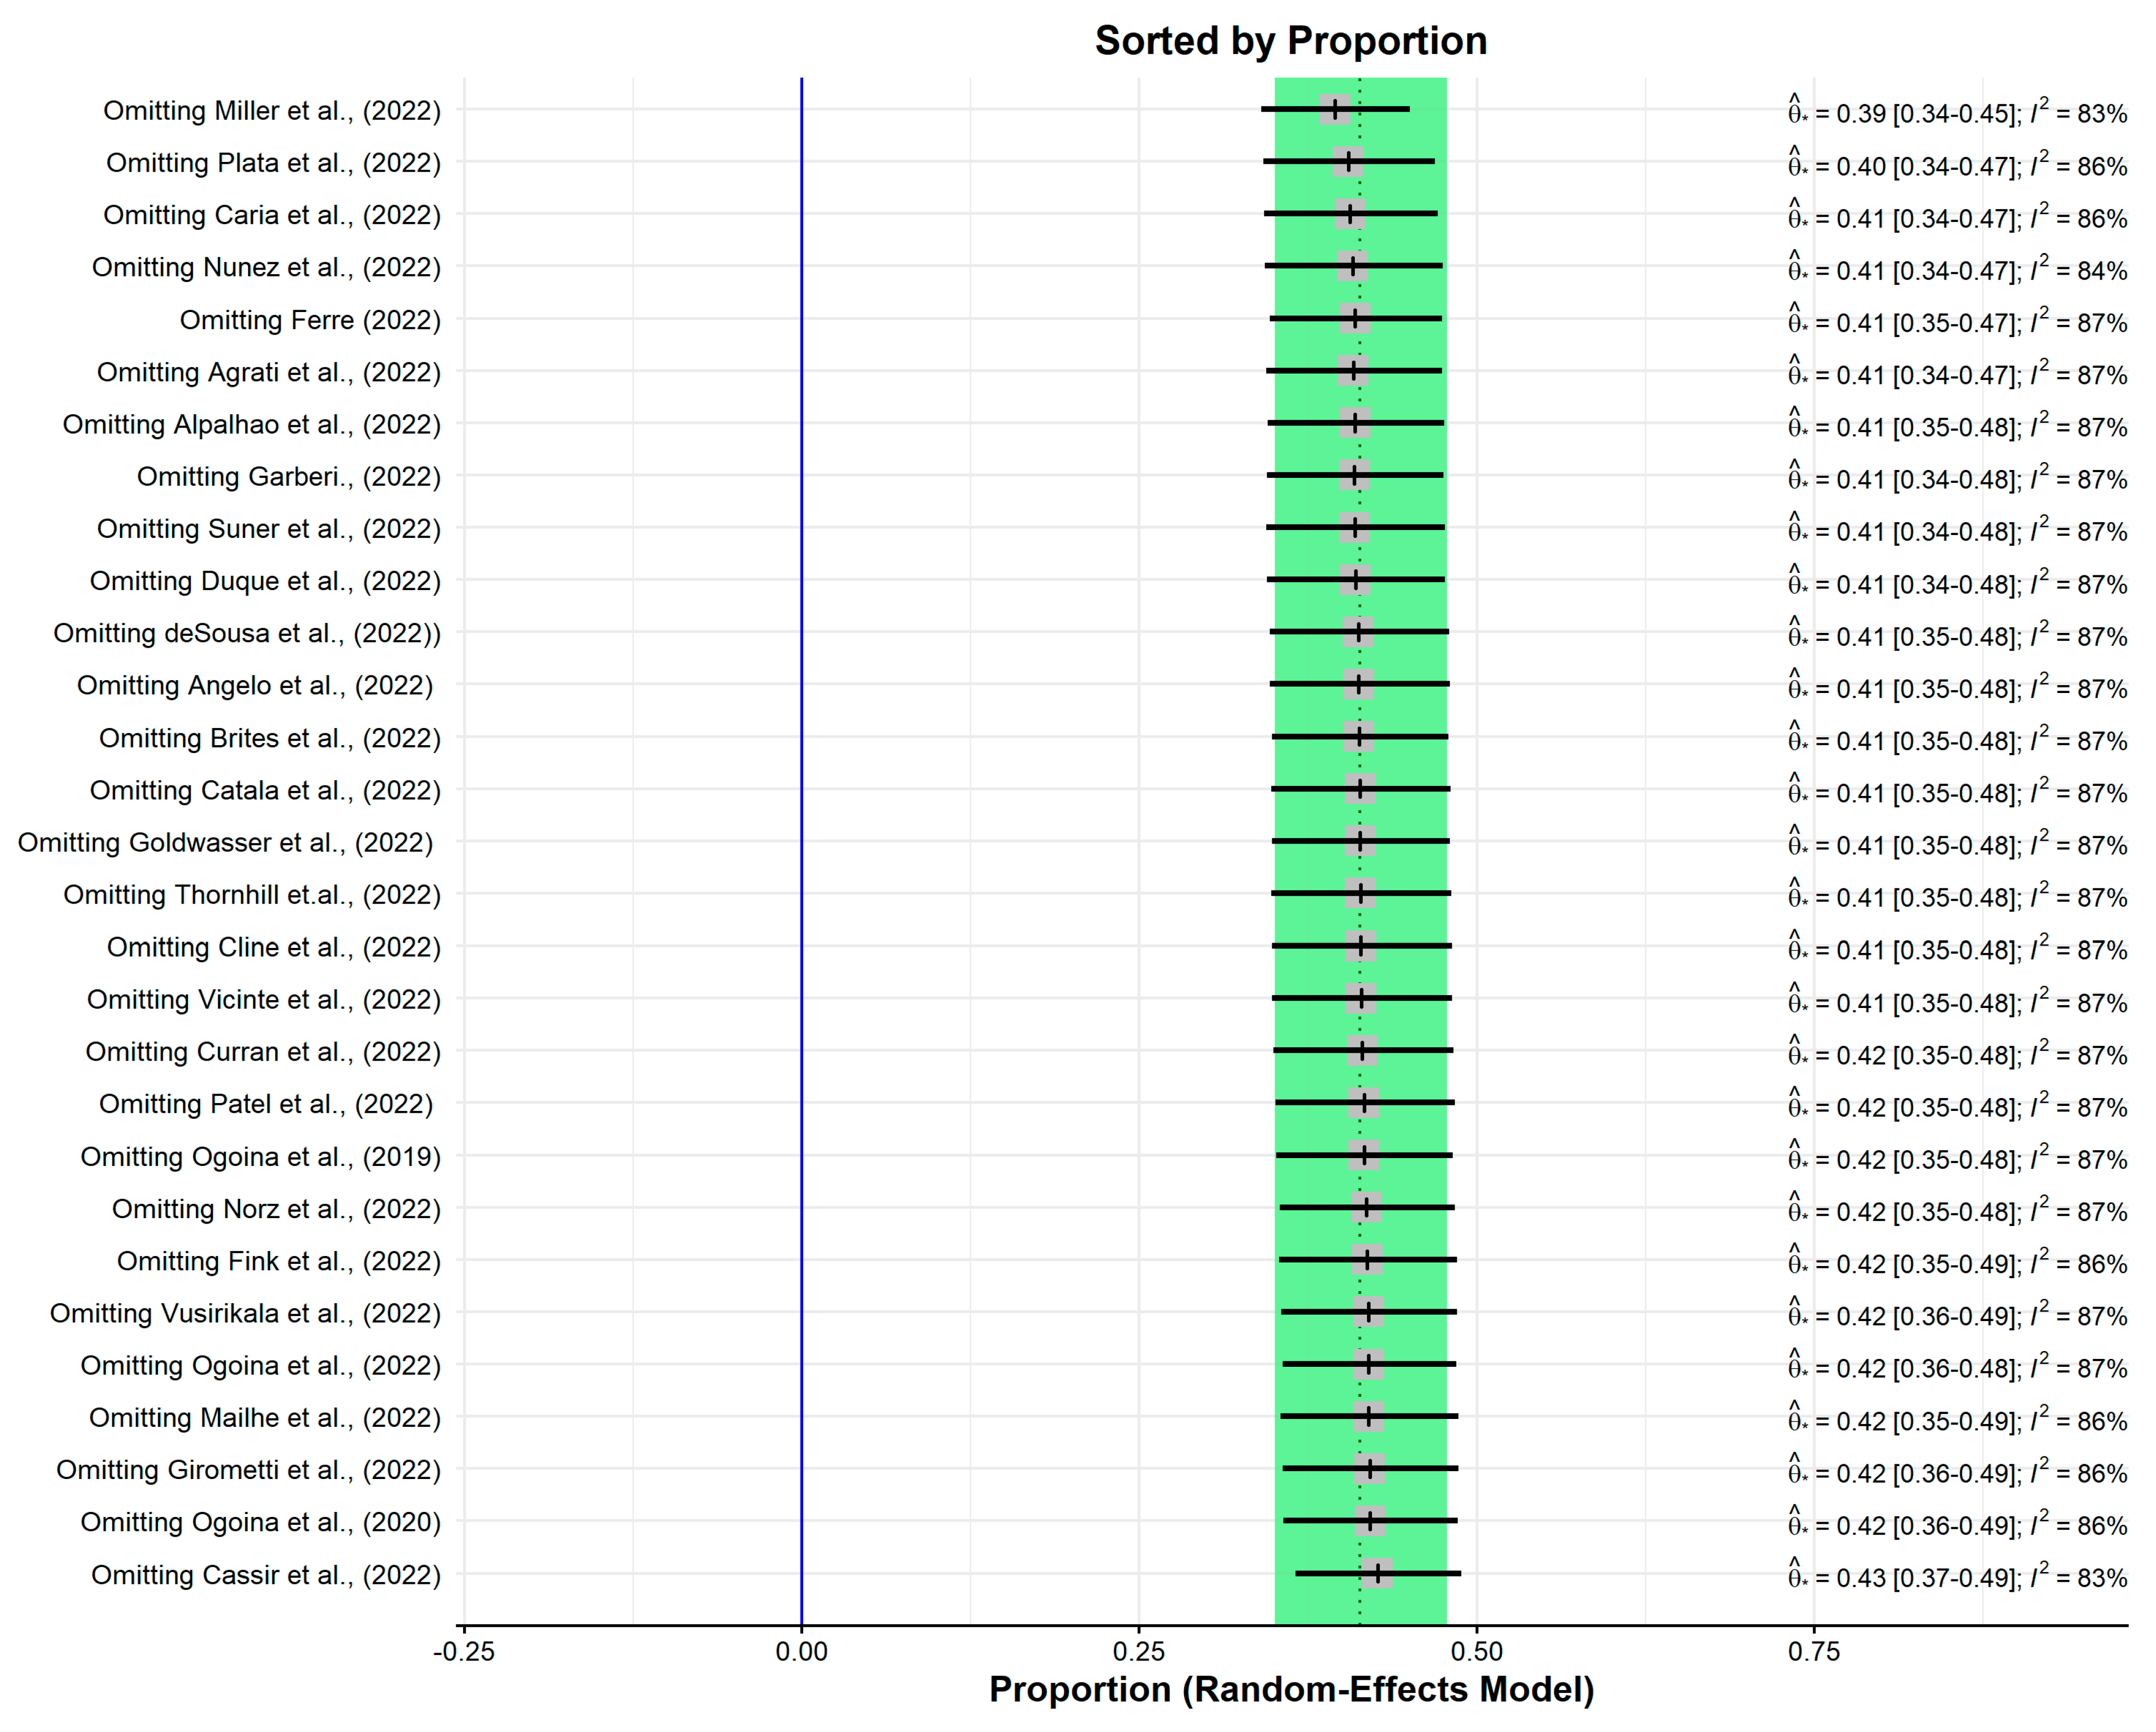
Sensitivity analysis enables the improvement of the robustness of the pooled estimates by eliminating or reducing the heterogeneity between the studies. In order to undertake sensitivity analysis, diagnostic tests were applied [46]. One of the studies (Miller et al. [44]) was identified as an outlier by the diagnostic test (Figure 3). However, leave-one-out analysis did not yield a significant change in the pooled estimate or heterogeneity (Figure 4).
Figure 3.
Sensitivity analysis: outlier detection by influence diagnostics.
Figure 4.
Sensitivity analysis by leave-one-out analysis.
3.6. Subgroup Analysis
Based on the geography in which the study was conducted, African studies reported a relatively low prevalence of HIV infection of 21% (95% CI 15–28) among individuals with mpox, while studies from Europe reported 41% (95% CI 33–49). Studies in North America reported a higher prevalence of 52% (95% CI 28–76) (Figure S3). The prevalence of HIV infection has been higher during the ongoing multicountry outbreak [42% (95% CI 36–49)] than from the cases reported before the 2022 outbreak [22% (95% CI 4–47)] (Figure S4). Similarly, the prevalence of HIV infection in individuals with mpox differed significantly according to mpox endemicity, with a higher pooled prevalence among nonendemic countries [43% (95% CI 36–50)] than in endemic countries [21% (95% CI 15–28)] (Figure S5). However, subgrouping based on the geography (continent), endemicity, and time of occurrence of the cases did not reduce the heterogeneity.
The bubble graph showed that age had an inverse relationship and that the proportion of males in the study had a directly proportional relationship with HIV prevalence among individuals with mpox. (Figures S6 and S7) However, the relationships were not significant. Similarly, metaregression did not show a significant effect of sample size on HIV prevalence. (Figure S8).
4. Discussion
Our review and meta-analysis revealed a pooled prevalence of HIV infection of 41.11% among individuals with mpox. However, the prevalence varied according to the cases’ geography, endemicity, and period. Studies in an African country (Nigeria) and before 2022 reported a lower HIV prevalence of 21.22% and 22.05%, respectively. The significant difference in the HIV prevalence might be due to the predominant transmission mode during the pre-2022 multicountry outbreak, which was mainly through close contact with the skin lesions [5,18]. The ongoing multicountry outbreak and nonendemic countries were found to have a higher prevalence of HIV infection among individuals with mpox (42.05% and 42.60%, respectively). The prevalence rate is very high compared to the prevalence of HIV among the general population in all included countries (African and non-African countries). However, the gap was more pronounced in nonendemic and non-African countries, with a study from Portugal reporting a difference of more than 100 times that of the general population [38]. The shift in human-human transmission routes might explain this. The current outbreak, which is more concentrated in nonendemic European and American countries, has a disproportionate share of the MSM, bisexuals, and gay population [30], who are HRGs for HIV. Although the burden and prevalence are high in African countries, the proportion of HIV infection among individuals with mpox is relatively lower than in Europe and the Americas, where HIV prevalence is low. In contrast, mpox lesions can also aid and abate the transmission of sexually transmitted diseases, including HIV [38].
Mpox lesions in the primary areas of the body of sexual contacts have been suspected to be the transmission gateway in patients with high-risk behavior [24]. Rectal and semen samples had shown 67–77% positivity for individuals with mpox. A series of cases with MPXV-HIV coinfection reported the presence of the MPXV in 90% of the rectal swabs [47]. Although the viral load was lower, the median clearance of the MPXV from semen samples has been reported to be 13 days, extending up to 39 days among the majority of the patients [36]. Asymptomatic individuals with MSM mpox from France had their samples tested positive for MPXV from anal swabs, indicating a possible shedding of the virus in the anal route [28]. These might be a potential explanation for MPXV transmission among people with high-risk sexual behaviors.
Clinical characteristics varied according to HIV infection status, with MPXV-HIV coinfected individuals having significantly higher composite rash scores. A significantly higher rate of oral and perioral lesions was found among the PLHIVs [23]. Acute coinfection with HIV and MPXV has been reported to lead to hospitalization [27]. In a global case series, the hospitalization rate among the MPXV-HIV coinfected individuals was reported to be 28% [48]. Severity varied according to the status of HIV control, with adverse outcomes reported in hospitalized individuals with poor HIV control [44]. A study from Spain reported the most severe mpox infection in the PLHIV with poor disease control (CD4 = 265), than in the other individuals with HIV-MPXV [32]. Studies from nonendemic countries reported good HIV control status among most individuals with HIV- MPXV coinfection [13,28,30,31,35,45,49]. A study from mpox endemic Nigeria reported a low CD4 count among the individuals with MPXV-HIV coinfection [18]. A study from the USA reported that poorly controlled HIV status had a longer duration of hospitalization than HIV-negative individuals with mpox [40]. A study in Nigeria reported poor clinical results among MPXV-HIV coinfected individuals but did not report the control status of HIV [11]. Individuals with asymptomatic mpox who were found to have HIV coinfection (61.54%) had it under good control [28]. It was also found that, irrespective of HIV infection, individuals with mpox were able to elicit a T cell response against the mpox virus [20,31].
We also found that, during the review, all African studies reporting HIV status in individuals with mpox were from Nigeria. However, none from the Democratic Republic of the Congo (DRC) reported a HIV status. This is of great importance because, while Nigeria had clade II MPXV, the mpox cases in the DRC were due to the more severe and fatal clade (Clade I). Additionally, the current multicountry outbreak in the endemic countries is primarily driven by clade IIb, thus limiting information on the interaction of HIV with the more severe clade of mpox virus (Clade I). A better understanding of the MPXV-HIV coinfection in the endemic African context, especially in the DRC, requires all future studies to report the HIV status of individuals with mpox.
Strengths and Limitations
This review included studies in multiple databases of published and unpublished literature to quantify and study the prevalence of HIV in mpox patients, globally and regionally. The risk of bias in the studies was assessed using standard tools. Subgroup analysis and metaregression (including multiple variables, such as sex, age, and sample size) were undertaken to explain the heterogeneity. A sensitivity analysis was performed methodologically, identifying and excluding outliers. However, the present analysis was not without limitations. There was significantly high heterogeneity among the included studies. The substantial heterogeneity observed in the study is hypothesized due to the global nature of the data in the review with varied patient characteristics in terms of geographic location, high-risk behavior, the types of HIV (HIV-1 and HIV-2), clades and lineages of the MPXV, and other comorbidities in the various studies.
5. Conclusions
Overall, the pooled prevalence of HIV infection among individuals with mpox was 41%. A relatively lower prevalence of HIV was observed in Africa, whereas a higher prevalence of HIV was found among nonendemic countries. Considering the high prevalence of HIV among individuals with mpox and the adverse outcomes reported among individuals with uncontrolled HIV, HIV testing for all persons with unknown HIV status may be conducted under routine investigation. A history of sexual orientation and of sexual partners in the last 21 days may be taken from individuals with mpox to identify the potential source and contacts for quarantining and testing them as part of the public health response. More epidemiological and analytical studies must be conducted to explore the relationship between HIV infection and mpox and the mediating role of high-risk sexual practices.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/epidemiologia4030033/s1, Figure S1: Doi plot of pooled prevalence of HIV among individuals with mpox. Figure S2: Funnel plot with a 95% confidence interval of pooled prevalence of HIV among individuals with mpox. Figure S3: Forest plot of the subgroup analysis according to the place of the study. Figure S4: Forest plot of the su-group analysis according to the period of study. Figure S5: Forest plot of the subgroup analysis according to endemicity of mpox. Figure S6: Bubble plot demonstrating metaregression based upon the participant’s age. Figure S7: Bubble plot demonstrating metaregression based upon the proportion of male cases. Figure S8: Bubble plot demonstrating metaregression based upon sample size.
Author Contributions
Conceptualization, A.P.G., B.K.P., P.S. and J.K.; methodology, M.S., M.A.S. and T.K.S.; formal analysis, A.P.G., B.K.P., M.S., M.A.S., T.K.S., P.S. and J.K.; data curation, A.S., R.S., S.R. and Z.H.A.-Q.; writing—original draft preparation, A.S., R.S., M.A.S., S.R., Z.H.A.-Q. and P.S.; writing—review and editing, A.P.G., B.K.P., M.A.S., M.S. and J.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study did not require ethical approval.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data are available in the studies used for this review.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Inclusion and exclusion criteria.
Table A2.
The adjusted search terms as per searched electronic databases [as of 04.01.2023].
Table A3.
PRISMA Checklist.
Table A4.
(a) Quality assessment of the included case series with the use of the NIH quality assessment tool. (b) Quality assessment of included cross-sectional and cohort studies with the use of the NIH quality assessment tool.
References
- Sah, R.; Mohanty, A.; Hada, V.; Singh, P.; Govindaswamy, A.; Siddiq, A.; Reda, A.; Dhama, K. The Emergence of Monkeypox: A Global Health Threat. Cureus 2022, 14, e29304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sah, R.; Padhi, B.K.; Siddiq, A.; Abdelaal, A.; Reda, A.; Lashin, I.; Mohanty, A.; Alshahrani, N.Z.; Rodriguez-Morales, A.J.; Rodriguez, A.J.; et al. Public Health Emergency of International Concern Declared by the World Health Organization for Monkeypox. Glob. Secur. Health Sci. Policy 2022, 7, 51–56. [Google Scholar] [CrossRef] [Scilit]
- 2022 Mpox (Monkeypox) Outbreak: Global Trends. Available online: https://worldhealthorg.shinyapps.io/mpx_global/#2_Global_situation_update (accessed on 31 December 2022).
- Likos, A.M.; Sammons, S.A.; Olson, V.A.; Frace, A.M.; Li, Y.; Olsen-Rasmussen, M.; Davidson, W.; Galloway, R.; Khristova, M.L.; Reynolds, M.G.; et al. A Tale of Two Clades: Monkeypox Viruses. J. Gen. Virol. 2005, 86, 2661–2672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pan, D.; Nazareth, J.; Sze, S.; Martin, C.A.; Decker, J.; Fletcher, E.; Déirdre Hollingsworth, T.; Barer, M.R.; Pareek, M.; Tang, J.W. Transmission of Monkeypox/Mpox Virus: A Narrative Review of Environmental, Viral, Host, and Population Factors in Relation to the 2022 International Outbreak. J. Med. Virol. 2023, 95, e28534. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Transmission of HIV/AIDS|Stanford Health Care. Available online: https://stanfordhealthcare.org/medical-conditions/sexual-and-reproductive-health/hiv-aids/causes.html (accessed on 16 July 2023).
- HIV. Available online: https://www.who.int/data/gho/data/themes/hiv-aids (accessed on 3 January 2023).
- Multi-Country Monkeypox Outbreak in Non-Endemic Countries. Available online: https://www.who.int/emergencies/disease-outbreak-news/item/2022-DON385 (accessed on 30 October 2022).
- Johri, N.; Kumar, D.; Nagar, P.; Maurya, A.; Vengat, M.; Jain, P. Clinical Manifestations of Human Monkeypox Infection and Implications for Outbreak Strategy. Health Sci. Rev. 2022, 5, 100055. [Google Scholar] [CrossRef] [Scilit]
- Satapathy, P.; Mohanty, P.; Manna, S.; Shamim, M.A.; Rao, P.P.; Aggarwal, A.K.; Khubchandani, J.; Mohanty, A.; Nowrouzi-Kia, B.; Chattu, V.K. Potentially asymptomatic infection of monkeypox virus: A systematic review and meta-analysis. Vaccines 2022, 10, 2083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Curran, K.G.; Eberly, K.; Russell, O.O.; Snyder, R.E.; Phillips, E.K.; Tang, E.C.; Peters, P.J.; Sanchez, M.A.; Hsu, L.; Cohen, S.E.; et al. HIV and Sexually Transmitted Infections Among Persons with Monkeypox—Eight U.S. Jurisdictions, May 17–July 22, 2022. Morb. Mortal. Wkly. Rep. 2022, 71, 1141–1147. [Google Scholar] [CrossRef] [Scilit]
- Yinka-Ogunleye, A.; Aruna, O.; Dalhat, M.; Ogoina, D.; McCollum, A.; Disu, Y.; Mamadu, I.; Akinpelu, A.; Ahmad, A.; Burga, J.; et al. Outbreak of Human Monkeypox in Nigeria in 2017–18: A Clinical and Epidemiological Report. Lancet. Infect. Dis. 2019, 19, 872. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ogoina, D.; Iroezindu, M.; James, H.I.; Oladokun, R.; Yinka-Ogunleye, A.; Wakama, P.; Otike-Odibi, B.; Usman, L.M.; Obazee, E.; Aruna, O.; et al. Clinical Course and Outcome of Human Monkeypox in Nigeria. Clin. Infect. Dis. 2020, 71, e210–e214. [Google Scholar] [CrossRef] [Scilit]
- Benites-Zapata, V.A.; Ulloque-Badaracco, J.R.; Alarcon-Braga, E.A.; Hernandez-Bustamante, E.A.; Mosquera-Rojas, M.D.; Bonilla-Aldana, D.K.; Rodriguez-Morales, A.J. Clinical Features, Hospitalisation and Deaths Associated with Monkeypox: A Systematic Review and Meta-Analysis. Ann. Clin. Microbiol. Antimicrob. 2022, 21, 36. [Google Scholar] [CrossRef] [Scilit]
- Gandhi, P.A.; Patro, S.K.; Sandeep, M.; Satapathy, P.; Shamim, M.A.; Kumar, V.; Aggarwal, A.K.; Padhi, B.K.; Sah, R.; Gandhi, A.; et al. Oral Manifestations of Monkeypox Virus: A Systematic Review and Meta-Analysis. eClinicalMedicine 2023, 56, 101817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gandhi, A.P.; Gupta, P.C.; Padhi, B.K.; Sandeep, M.; Suvvari, T.K.; Shamim, M.A.; Satapathy, P.; Sah, R.; León-Figueroa, D.A.; Rodriguez-Morales, A.J.; et al. Ophthalmic Manifestations of the Monkeypox Virus: A Systematic Review and Meta-Analysis. Pathogens 2023, 12, 452. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vogel, L. Making Sense of Monkeypox Death Rates. Can. Med. Assoc. J. 2022, 194, E1097. [Google Scholar] [CrossRef] [Scilit]
- Ogoina, D.; Izibewule, J.H.; Ogunleye, A.; Ederiane, E.; Anebonam, U.; Neni, A.; Oyeyemi, A.; Etebu, E.N.; Ihekweazu, C. The 2017 Human Monkeypox Outbreak in Nigeria-Report of Outbreak Experience and Response in the Niger Delta University Teaching Hospital, Bayelsa State, Nigeria. PLoS ONE 2019, 14, e0214229. [Google Scholar] [CrossRef] [Scilit]
- Ogoina, D.; Yinka-Ogunleye, A. Sexual History of Human Monkeypox Patients Seen at a Tertiary Hospital in Bayelsa, Nigeria. Int. J. STD AIDS 2022, 33, 928–932. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Betancort-Plata, C.; Lopez-Delgado, L.; Jaén-Sanchez, N.; Tosco-Nuñez, T.; Suarez-Hormiga, L.; Lavilla-Salgado, C.; Pisos-Álamo, E.; Hernández-Betancor, A.; Hernández-Cabrera, M.; Carranza-Rodríguez, C.; et al. Monkeypox and HIV in the Canary Islands: A Different Pattern in a Mobile Population. Trop. Med. Infect. Dis. 2022, 7, 318. [Google Scholar] [CrossRef] [Scilit]
- Cassir, N.; Cardona, F.; Tissot-Dupont, H.; Bruel, C.; Doudier, B.; Lahouel, S.; Bendamardji, K.; Boschi, C.; Aherfi, S.; Edouard, S.; et al. Observational Cohort Study of Evolving Epidemiologic, Clinical, and Virologic Features of Monkeypox in Southern France. Emerg. Infect. Dis. 2022, 28, 2409–2415. [Google Scholar] [CrossRef] [Scilit]
- Study Quality Assessment Tools|NHLBI, NIH. Available online: https://www.nhlbi.nih.gov/health-topics/study-quality-assessment-tools (accessed on 11 March 2023).
- Angelo, K.M.; Smith, T.; Camprubí-Ferrer, D.; Balerdi-Sarasola, L.; Díaz Menéndez, M.; Servera-Negre, G.; Barkati, S.; Duvignaud, A.; Huber, K.L.B.; Chakravarti, A.; et al. Epidemiological and Clinical Characteristics of Patients with Monkeypox in the GeoSentinel Network: A Cross-Sectional Study. Lancet. Infect. Dis. 2022, 23, 196–206. [Google Scholar] [CrossRef] [Scilit]
- Català, A.; Clavo-Escribano, P.; Riera-Monroig, J.; Martín-Ezquerra, G.; Fernandez-Gonzalez, P.; Revelles-Peñas, L.; Simon-Gozalbo, A.; Rodríguez-Cuadrado, F.J.; Castells, V.G.; de la Torre Gomar, F.J.; et al. Monkeypox Outbreak in Spain: Clinical and Epidemiological Findings in a Prospective Cross-Sectional Study of 185 Cases. Br. J. Dermatol. 2022, 187, 765–772. [Google Scholar] [CrossRef] [Scilit]
- Cline, A.; Marmon, S. Demographics and Disease Associations of Patients with Monkeypox and Recipients of Monkeypox Vaccine from Safety Net Hospitals in New York City: A Cross-Sectional Study. J. Am. Acad. Dermatol. 2023, 88, 1160–1163. [Google Scholar] [CrossRef] [Scilit]
- Caria, J.; Pinto, R.; Leal, E.; Almeida, V.; Cristóvão, G.; Gonçalves, A.C.; Torres, M.; Santos, M.B.; Pinheiro, H.; Póvoas, D.; et al. Clinical and Epidemiological Features of Hospitalized and Ambulatory Patients with Human Monkeypox Infection: A Retrospective Observational Study in Portugal. Infect. Dis. Rep. 2022, 14, 83. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Sousa, D.; Patrocínio, J.; Frade, J.; Brazão, C.; Mancha, D.; Correia, C.; Borges-Costa, J.; Filipe, P. Monkeypox Diagnosis by Cutaneous and Mucosal Findings. Infect. Dis. Rep. 2022, 14, 77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferré, V.M.; Bachelard, A.; Zaidi, M.; Armand-Lefevre, L.; Descamps, D.; Charpentier, C.; Ghosn, J. Detection of Monkeypox Virus in Anorectal Swabs from Asymptomatic Men Who Have Sex With Men in a Sexually Transmitted Infection Screening Program in Paris, France. Ann. Intern. Med. 2022, 175, 1491–1492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fink, D.L.; Callaby, H.; Luintel, A.; Beynon, W.; Bond, H.; Lim, E.Y.; Gkrania-Klotsas, E.; Heskin, J.; Bracchi, M.; Rathish, B.; et al. Clinical Features and Management of Individuals Admitted to Hospital with Monkeypox and Associated Complications across the UK: A Retrospective Cohort Study. Lancet. Infect. Dis. 2023, 23, 589–597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Girometti, N.; Byrne, R.; Bracchi, M.; Heskin, J.; McOwan, A.; Tittle, V.; Gedela, K.; Scott, C.; Patel, S.; Gohil, J.; et al. Demographic and Clinical Characteristics of Confirmed Human Monkeypox Virus Cases in Individuals Attending a Sexual Health Centre in London, UK: An Observational Analysis. Lancet. Infect. Dis. 2022, 22, 1321–1328. [Google Scholar] [CrossRef] [Scilit]
- Agrati, C.; Cossarizza, A.; Mazzotta, V.; Grassi, G.; Casetti, R.; De Biasi, S.; Pinnetti, C.; Gili, S.; Mondi, A.; Cristofanelli, F.; et al. Immunological Signature in Human Cases of Monkeypox Infection in 2022 Outbreak: An Observational Study. Lancet. Infect. Dis. 2023, 23, 320–330. [Google Scholar] [CrossRef] [Scilit]
- Gomez-Garberi, M.; Sarrio-Sanz, P.; Martinez-Cayuelas, L.; Delgado-Sanchez, E.; Bernabeu-Cabezas, S.; Peris-Garcia, J.; Sanchez-Caballero, L.; Nakdali-Kassab, B.; Egea-Sancho, C.; Olarte-Barragan, E.H.; et al. Genitourinary Lesions Due to Monkeypox. Eur. Urol. 2022, 82, 625–630. [Google Scholar] [CrossRef] [Scilit]
- Mailhe, M.; Beaumont, A.-L.; Thy, M.; Le Pluart, D.; Perrineau, S.; Houhou-Fidouh, N.; Deconinck, L.; Bertin, C.; Ferré, V.M.; Cortier, M.; et al. Clinical Characteristics of Ambulatory and Hospitalized Patients with Monkeypox Virus Infection: An Observational Cohort Study. Clin. Microbiol. Infect. 2023, 29, 233–239. [Google Scholar] [CrossRef] [Scilit]
- Nörz, D.; Brehm, T.T.; Tang, H.T.; Grewe, I.; Hermanussen, L.; Matthews, H.; Pestel, J.; Degen, O.; Günther, T.; Grundhoff, A.; et al. Clinical Characteristics and Comparison of Longitudinal QPCR Results from Different Specimen Types in a Cohort of Ambulatory and Hospitalized Patients Infected with Monkeypox Virus. J. Clin. Virol. 2022, 155, 105254. [Google Scholar] [CrossRef] [Scilit]
- Núñez, I.; García-Grimshaw, M.; Ceballos-Liceaga, S.E.; Toledo-Salinas, C.; Carbajal-Sandoval, G.; Sosa-Laso, L.; García-Rodríguez, G.; Cortés-Alcalá, R.; de la Torre, A.; Fragoso-Saavedra, S.; et al. Epidemiological and Clinical Characteristics of Patients with Human Monkeypox Infection in Mexico: A Nationwide Observational Study. Lancet Reg. Health Am. 2023, 17, 100392. [Google Scholar] [CrossRef] [Scilit]
- Suñer, C.; Ubals, M.; Tarín-Vicente, E.J.; Mendoza, A.; Alemany, A.; Hernández-Rodríguez, Á.; Casañ, C.; Descalzo, V.; Ouchi, D.; Marc, A.; et al. Viral Dynamics in Patients with Monkeypox Infection: A Prospective Cohort Study in Spain. Lancet Infect. Dis. 2022, 23, 445–453. [Google Scholar] [CrossRef] [Scilit]
- Tarín-Vicente, E.J.; Alemany, A.; Agud-Dios, M.; Ubals, M.; Suñer, C.; Antón, A.; Arando, M.; Arroyo-Andrés, J.; Calderón-Lozano, L.; Casañ, C.; et al. Clinical Presentation and Virological Assessment of Confirmed Human Monkeypox Virus Cases in Spain: A Prospective Observational Cohort Study. Lancet 2022, 400, 661–669. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alpalhão, M.; Sousa, D.; Frade, J.V.; Patrocínio, J.; Garrido, P.M.; Correia, C.; Brazão, C.; Mancha, D.; Núncio, M.S.; Carvalho, I.L.; et al. Human Immunodeficiency Virus Infection May Be a Contributing Factor to Monkeypox Infection: Analysis of a 42-Case Series. J. Am. Acad. Dermatol. 2023, 88, 720–722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brites, C.; Deminco, F.; Sá, M.S.; Brito, J.T.; Luz, E.; Stocker, A. The First Two Cases of Monkeypox Infection in MSM in Bahia, Brazil, and Viral Sequencing. Viruses 2022, 14, 1841. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cash-Goldwasser, S.; Labuda, S.M.; McCormick, D.W.; Rao, A.K.; McCollum, A.M.; Petersen, B.W.; Chodosh, J.; Brown, C.M.; Chan-Colenbrander, S.Y.; Dugdale, C.M.; et al. Ocular Monkeypox—United States, July-September 2022. Morb. Mortal. Wkly. Rep. 2022, 71, 1343–1347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perez Duque, M.; Ribeiro, S.; Martins, J.V.; Casaca, P.; Leite, P.P.; Tavares, M.; Mansinho, K.; Duque, L.M.; Fernandes, C.; Cordeiro, R.; et al. Ongoing Monkeypox Virus Outbreak, Portugal, 29 April to 23 May 2022. Eurosurveillance 2022, 27, 2200424. [Google Scholar] [CrossRef] [Scilit]
- Vusirikala, A.; Charles, H.; Balasegaram, S.; Macdonald, N.; Kumar, D.; Barker-Burnside, C.; Cumiskey, K.; Dickinson, M.; Watson, M.; Olufon, O.; et al. Epidemiology of Early Monkeypox Virus Transmission in Sexual Networks of Gay and Bisexual Men, England, 2022. Emerg. Infect. Dis. 2022, 28, 2082–2086. [Google Scholar] [CrossRef] [Scilit]
- Thornhill, J.P.; Barkati, S.; Walmsley, S.; Rockstroh, J.; Antinori, A.; Harrison, L.B.; Palich, R.; Nori, A.; Reeves, I.; Habibi, M.S.; et al. Monkeypox Virus Infection in Humans across 16 Countries—April–June 2022. N. Engl. J. Med. 2022, 387, 679–691. [Google Scholar] [CrossRef] [Scilit]
- Miller, M.J.; Cash-Goldwasser, S.; Marx, G.E.; Schrodt, C.A.; Kimball, A.; Padgett, K.; Noe, R.S.; McCormick, D.W.; Wong, J.M.; Labuda, S.M.; et al. Severe Monkeypox in Hospitalized Patients—United States, 10 August–10 October 2022. Morb. Mortal. Wkly. Rep. 2022, 71, 1412–1417. [Google Scholar] [CrossRef] [Scilit]
- Patel, A.; Bilinska, J.; Tam, J.C.; Fontoura DD, S.; Mason, C.Y.; Daunt, A.; Snell, L.B.; Murphy, J.; Potter, J.; Tuudah, C.; et al. Clinical Features and Novel Presentations of Human Monkeypox in a Central London Centre during the 2022 Outbreak: Descriptive Case Series. BMJ 2022, 378, 72410. [Google Scholar] [CrossRef] [Scilit]
- Viechtbauer, W.; Cheung, M.W.-L. Outlier and Influence Diagnostics for Meta-Analysis. Res. Synth. Methods 2010, 1, 112–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vivancos-Gallego, M.J.; Sánchez-Conde, M.; Rodríguez-Domínguez, M.; Fernandez-Gonzalez, P.; Martínez-García, L.; Garcia-Mouronte, E.; Martínez-Sanz, J.; Moreno-Zamora, A.M.; Casado, J.L.; Ron, R.; et al. Human Monkeypox in People With HIV: Transmission, Clinical Features, and Outcome. Open Forum Infect. Dis. 2022, 9, ofac557. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitjà, O.; Alemany, A.; Marks, M.; Lezama Mora, J.I.; Rodríguez-Aldama, J.C.; Torres Silva, M.S.; Corral Herrera, E.A.; Crabtree-Ramirez, B.; Blanco, J.L.; Girometti, N.; et al. Mpox in People with Advanced HIV Infection: A Global Case Series. Lancet 2023, 401, 939–949. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thornhill, J.P.; Palich, R.; Ghosn, J.; Walmsley, S.; Moschese, D.; Cortes, C.P.; Galliez, R.M.; Garlin, A.B.; Nozza, S.; Mitja, O.; et al. Human Monkeypox Virus Infection in Women and Non-Binary Individuals during the 2022 Outbreaks: A Global Case Series. Lancet 2022, 400, 1953–1965. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).